BY CHR. SIHLER, M. D., PH. D., CLEVELAND, OHIO.
Formerly Fellow of the Johns Hopkins University.
The submaxillary gland is of importance not only for its own
sake, but because its anatomical connections and situation are
such that it can be subjected to physiological experiment, and
a number of important results have been reached which I may
discuss at some future time.
The results of my work are not only contradictory to the
authorities in histology, but also do not harmonize with the requirements
of prevailing physiological theories. Bringing this
before you does not mean that I ask you to accept either facts
or conclusions. I am fully aware of the difficulty of such work,
the doubtfulness of the facts and the liability to error in the
conclusion. But it is just possible that some of the younger
194members may fare as I did—have not all their time occupied by
practice—and if I enlist the interest of any in this most important
region I shall feel happy.
A number of years have passed since I undertook this question,
and the work on the nerve-endings on muscle, which I had
the pleasure to communicate to this society a few months ago,
was undertaken more as a study, to make myself familiar with
analogous structures, than that I expected to find anything new.
In the investigations on the nerve-endings I used the submaxillary
of the half-grown cat, the calf, the ox and the puppy.
The method followed was in the main that of Beale. In the
case of the cat I injected the whole animal from the aorta with
Turnbull’s blue, dissected out the gland, duct, and the
nerves entering it. After breaking up the gland into pieces
by aid of a needle, from the size of a bean to a pea, I placed
it in a dish with a light cover, containing Beale’s carmine
(carmine dissolved in ammonia and glycerine). I am in the
habit of using a stronger solution than Beale’s. I suspect that
the carmine I used in some of these stainings was adulterated
with eosin, and that possibly this may have been of advantage.
In some of my stainings I used a fluid prepared from
cochineal; used ammonia in dissolving the coloring matter,
and then added carmine besides. It is of the utmost importance
to have no excess of ammonia present, otherwise the staining
will be slow and imperfect. I have been staining with this
method for years, yet I cannot say why the results differ so
much. Some time ago I stained a frog for the nerve-endings
in muscle and obtained the most beautiful results, but in the
number of stainings I have made since (trying to follow the
same method) I have not been by far as successful as then.
In breaking up the gland I do not always separate all the
pieces, but try to remove the connective tissue holding together
the small lobules with the dull end of a needle, and then throw
the coherent mass into the stain. In this way I procured a very
perfectly injected and beautifully stained submaxillary of a
half-grown cat, from which I made a number of valuable specimens.
195The material may remain in the staining fluid for
weeks, and may be examined every two or three days to note
how the staining is advancing. When the masses stained are
large, or the whole gland is subjected to staining, of course the
outer parts are more deeply stained than the inner ones, but it
is at times convenient to have material of different depths of
staining. After the process has continued long enough—the
nuclei at least should be very distinctly colored—the material
is transferred into a fluid containing glycerine five parts, water
and alcohol each two parts, acetic acid one part. Here it
may remain about twenty-four hours, and finally it is to be
preserved in a similar mixture containing but a trace of acetic
acid. I hold acetic acid of varying strength diluted with
glycerine in high esteem in such investigation. It does two
things, removes the superfluous stain and softens and clears up
the connective tissue. Thus treated, the material is ready for
examination.
The tissues thus prepared may be hardened in alcohol and
sections cut, but this will not aid much in the investigation of
the questions that interest us. For this purpose teasing and
compression with the cover glass are mainly to be relied upon.
It is to be commended to isolate one of the little lobules the
gland is composed of, because thus we certainly have ready
for examination all the elements making up the gland. The
little root which connects the lobule with the rest of the gland
will consist of the duct, vessel and nerves supplying the lobule.
Such a lobule is broken up with needles and by compression
between slides. All these manipulations are to be carried on in
glycerine. When the fragments are small enough they are
examined with lower powers. The ducts in well injected
specimens can be recognized by the rich supply of vessels, the
nerve-trunks by the arrangement of the nuclei.
After examining larger fragments with lower powers, smaller
ones are selected, subjected to pressure with cover glass, and
examined with higher powers. By compression with cover
glass, pushing from side to side, one can isolate almost any
structure. One can also then make sure whether a fine fibre is
196really in connection with any other structure, or only lying
above or beneath the same.
The staining with the carmine will generally not attack the
fine nerve fibres. To show these up I have used aniline
blue dissolved in water. By these means I have brought out
very plainly the nerve fibres, in nerve trunks, of considerable
size, as well as those along vessels. I took the material prepared
as described, broke up a little piece in fragments of the
size of mustard seeds, and left them twelve hours in the blue
fluid in a watch glass. Glycerine, if necessary, slightly acidulated,
will remove the superfluous stain. I was very much
pleased with the action of the aniline blue.
Notwithstanding its physiological importance there is among
the authorities as yet no uniformity of opinion on the histology
of this gland, save that it belongs to the racemose glands, and
is made up of epithelial cells.
The question whether there is present a special membrana
propria, enveloping the glandular epithelium, as Pflüger
teaches, or a network of partly coalesced connective tissue
cells, as Kölliker supposes, may not seem very important, but
certainly such points must be cleared up before such questions
as to how the nerves end can satisfactorily be answered.
This question, the importance of which will be admitted by
all, is also a disputed one. In Stricker’s handbook Pflüger has,
in the article on the submaxillary gland, given a detailed
account of the mode of nerve-ending in this gland. According
to his investigations it is of various kinds.
(1.) The medullary fibre approaches an alveolus penetrates
this membrane, the axis cylinder breaks up into innumerable
fine fibres, and these pass into the body of the gland cell.
(2) Or the nerve passes into a pale cell provided with numerous
processes, which in their turn form connections with the
secreting cells.
These results of Pflüger have, however, not been accepted
by all investigators. Thus Kölliker says on this question:
“The investigations on the nerve-endings in the salivary
glands are evidently far from being concluded, nevertheless so
much can be gathered from the work done that the nerve fibres
197are in more intimate relations with the glandular elements than
has been surmised heretofore. What these relations may be I
cannot say, for notwithstanding a very careful investigation of
this gland it has not been possible for me to reach views
definite and not open to doubt, although frequently enough I
have seen fibres and threads of various kinds apparently come
in contact with salivary cells. Further, regarding the drawings
and descriptions of Pflüger, I must confess, having at the
same time nothing but the highest esteem of this investigator,
as well as of the care and accuracy he employed in this question,
that these do not seem altogether convincing to me.”
I find that the gland cells are enclosed by a membrane (agreeing
altogether with Pflüger) which I look upon as decidedly
homogeneous (histologically speaking, of course), not showing
any structure; by no means being merely a reticulum of connective
tissue corpuscles, as Kölliker suggests.
Further: This membrane is provided with nuclei of an
oval form (generally), reminding me of the nuclei supplying
the nerve sheaths.
Finally: This membrana propria sends out from the alveolar
walls, processes, ensheathing—how complete I cannot say—the
gland cells. I cannot otherwise explain the glistening
lines, which we see in examining sections VI extending from the
alveolar wall between the cells, resembling altogether the sections
of the alveolar walls. To investigate this matter more
accurately, I have stained sections with carmine, also with log-wood,
and have found that the alveolar wall and these lines
stain the same way. Further breaking up such a section by
manipulation with cover-glass, one can obtain fragments of
these processes, thus demonstrating that these lines are not
merely optical illusions.
The nuclei of this membrana propria are situated on its inner
surface and could be distinguished in the gland of the cat, mentioned
above, not only by their more oval, oblong or elliptical
form, from the more roundish nuclei of the gland cells, but just
as plainly by the lighter red or pinkish staining which they
198take on the nuclei of the gland cells being stained a deeper
red.
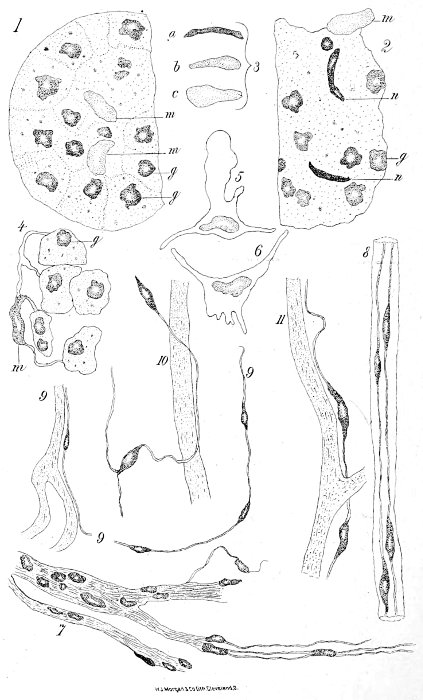
Compressing very small fragments of gland-substance (always
of course in glycerine), by means of the cover-glass, beating
and pushing it from side to side, thus bursting the alveolus and
tearing the membrane and isolating it from the contained gland
cells, one can prepare for examination greater or smaller pieces
of this membrane. There are by such means obtainable fragments
with all sorts of processes and fringes, short and long,
many and few, which undoubtedly may remind one of “connective
tissue cells.” (See fig. 4.) More convincing than these
are membraneous pieces, which may be obtained of various
sizes. (See figs. 5, 6.) I have a drawing of such a fragment,
which, if enlarged as figs. 1 and 2, would cover over one-quarter
of the page, and to which a number of nuclei, more than six,
are attached. As a rule, this membrane will, by the manipulations
with the cover-glass, not be spread out, but rather folded
up, huddled together inclosing some of the gland cells, forming
an indescribable nest.
I do not know if it will be necessary to mention in this connection
that I consider these nuclei identical with the half-moon
cells of Gianuzzi, and cannot help expressing my surprise
at the physiological importance assigned to them; for they
have been considered playing the role of mother cells, giving
origin to glandular epithelium formed to take the place of
cells used up in the process of secretion. The dark staining,
which in section they seem to assume as well as the
semilunar form, will be discussed later. Of course I look upon
these nuclei as belonging to flat epithelial cells, as we find them
lining nerve sheaths, and serous membranes, and consider them
of the same physiological importance as the nuclei of such
endothelial cells. A similar ensheathing membrane, or membrana
propria, I find in the ducts; but here I have not been
able to distinguish processes passing in between the cells. If
present they must be exceedingly delicate, for it is not difficult
to press out groups of cells from the ducts so that empty
pieces (short ones of course) of such can be examined.
While the membrana propria of the ducts can be separated
199rather easily from the inclosed cells, it is different from the surrounding
network of capillaries. It seems impossible to remove
the capillaries from the duct-walls; while, in the gland-structure
proper, among the alveoli, the separation of the capillary from
an alveolus, can with little difficulty often be accomplished,
so that a piece of capillary can be examined without any other
structures lying above or beneath it.
It was somewhat surprising to me, and not a little interesting,
to find that the ducts have a decidedly richer blood supply than
the gland substance proper, the meshes of the capillaries covering
the ducts very closely indeed.
I will also call attention to the fact that, along the terminal
portions of the ducts, no arteries or veins can be seen; and
what is still more important, no free nerve-fibres can be discovered.
Following the ducts outwards, as these attain larger
dimensions, and especially where they give off side branches,
we find arteries and veins accompanying them, and there
will also be found along-side of them fine nerve-branches.
So much is certain, that in that region, where arteries and veins
are not to be seen, there are also no separate nerve twigs, and
that here the union or coalescence of nerve and tissue which
the nerves are to influence must have taken place. If one considers
the fine meshes of the capillary network enveloping the
ducts, and keeps in mind the abundance of nuclei belonging to
the capillary, the membrana propria and the duct cells proper,
he can imagine how difficult it must be to follow the course
of the nerves through and among all these structures. That
it has been impossible for me to separate capillary and membrana
propria, has been mentioned.
If one were to ask the physiologist: What do you expect us
to find in our anatomical investigations on the nerve-endings in
the submaxillary gland, he would undoubtedly answer: “You
will find an arrangement analogous, if not similar, to that in
the striped muscle; the nerve-fibre will be seen to approach
the alveolus, penetrate its covering, and the protoplasm of
200the nerve and the gland-cell will be found to come in contact,
if not to coalesce.” And that is what has been found by Pflüger.
It has been my endeavor for some time to find something
similar to the descriptions of Pflüger, but so far in vain,
although many an alveolus has been carefully examined, flattened
out and slowly crushed, so that each nucleus could be
diagnosed, but never have I found anything which would remind
me of the drawings by Pflüger in Stricker’s ‘Histological Handbook.’
In this matter I reasoned thus: If there are any such structures
as specialized nerve-endings present in the glandular
elements, we might look for an analogy either to the striped
muscle fibres or to the capillaries, in both of which nerve-endings
are known to be present. In the former case we have
the so-called end-plate—the nerve fibre ends in a multi-nucleated
mass—but as the muscle fibre, standing for a number of cells,
is so different a structure from the gland-cells, we might, with
greater probability, expect some such arrangement as we see
on the capillaries. Here we see fine fibrils, provided with
nuclei, exceeding the fibres two to four times in thickness,
entwining the capillary, thus coming in contact with each of
the cells composing the capillary wall. In the (submaxillary)
gland there are similar structures to be influenced; at least in
the capillary as well as in the gland, we have cells lying side by
side to be influenced by nerves—hence we might expect similar
structures.
Although the books in general have very little to say about
the nerve supply of the capillaries, yet it is a fact, and can well
be demonstrated, e. g., in the frog’s muscle, that such is the
arrangement. As a rule, the fibril cannot so readily be detected,
but the nuclei belonging to it are not difficult to recognize.
A still more convenient and instructive locality is the
base of the frog’s mouth, where everything is one plane, and
where the nerve fibres can be followed to their ultimate ramifications.
Let us now see what evidence of nerve-endings we find in or
on the alveoli of the gland, examining one, or more accurately,
a part of one (the round eminence). We shall see what fig. 1
201presents. We see there two sets of nuclei; one kind oval,
longish, stained lighter than the rest, of a pink hue (fig. 1, m),
and these a further examination will demonstrate to be the
nuclei belonging to the membrana propria, which have also
been described before. Besides these nuclei, fewer in number,
there is another kind, making up the bulk of the nuclei, more
rounded in form (fig. 1, g), and of a deep-red color, which,
in their turn, will prove to be the nuclei of the gland-cells; and
these two are the only elements or structures that I have been
able to demonstrate in a glandular alveolus.
At one time I thought I had found in or on the alveoli the
evidence of a network of fine nerves. Quite frequently one
can observe longish, even spindle-shaped, often deeply stained,
nuclei, which resemble very much those belonging to the fine
nerve fibres. (Fig. 2, n, such nuclei are figured.) But so
far, whenever I examined such a spindle-shaped nucleus more
carefully, I found that it proved to be one of the nuclei
belonging to the membrana propria, already described, and
the form, as well as its dark color, was due to the fact
that it had been examined edgewise. If, by manipulation,
such a nucleus was turned over and compressed to present a
flat surface, it would have an oval outline and be of a light-red
color. Fig. 3 (a, b, c), shows the same nucleus as it
appeared when seen edgewise, when seen from the flat and
when seen in a position midway between these. Thus is also
to be explained the demilune: If the section would strike a
nucleus so that it would be seen only edgewise—especially if
the membrana propria has a chance to roll up slightly—we
should then have a deeply stained body, somewhat half-moon-shaped,
the demilunes of the books.
So far, nothing but the nuclei have been mentioned, and the
observation might very appropriately be made, that there might
exist some exceedingly fine and delicate nerve fibrils without
nuclei. Such a system of structures would, of course, be
almost impossible to demonstrate with any degree of certainty.
I have not, of course, sufficient reason to deny such an arrangement,
and would not consider it improbable if we had not, in
the capillaries of the frog’s muscle (and other structures) evidence
202certainly not in favor of such an assumption. The fine
nerve fibrils supplying the capillaries are richly supplied with
nuclei, although the cells which build up the walls of the
capillary are by far more insignificant elements than the secreting
cells of the gland. Certain it is that as yet there is no
evidence of the existence of such fine non-nucleated fibrils,
arranged either in the form of a network or a bundle of fine
branches.
The examination of the alveoli not leading to any results as
to nerve-endings—no structures being discovered there that
might be called nervous—I attacked the problem from the other
side. I took up the nerve trunks accompanying the ducts, and
tried how far I could follow their divisions and branches, and
can say that I have spent a great deal of time on this point.
In speakings of the bloodvessels, the fact was mentioned that,
where arteries and veins of any size run along-side of the duct,
these are accompanied by nerve branches, i. e., bundles of
nerve fibres, inclosed in a sheath, and these—at least in the cat,
the calf and the ox—are made up (excepting, possibly, the very
large trunks) of fine nerve fibres. Thicker or medullary nerves
I have not been able to discover, even in branches of considerable
size, consisting of, say six or eight fibres, and giving off
smaller twigs containing one to three fibres. Fig. 7 shows
such a nerve-trunk with side branches; neither in the main
stem nor in the offshoots are there any medullary nerves
discoverable.
If this observation is correct, we see that what has to be
traced further, is not the more easily recognized medullary
fibre, but exceedingly fine fibrils carrying in certain intervals
nuclei, the only distinguishing feature. It will be admitted
also (first) that it must be a matter of considerable difficulty to
follow such indifferent looking structures, as delicate fibres.
And (secondly), one cannot expect to find medullary nerves
approach the alveoli, penetrate the membrane, come in connection
with the secretory cells, etc., etc, as has been done
by Pflüger. If the question should be asked how far I have
been able to follow these nerves, I should say: Small twigs
consisting of one to three fine fibrils, enclosed in a sheath
203branch off from a trunk, not much larger, and apply themselves
to the membrana propria of the duct; their sheaths in all probability
coalescing with that membrane. Here they have been
seen to apply themselves to some bloodvessel and are now
lost out of sight, being hid by all the many structures mentioned
above, the nuclei of membrane, capillary, duct cells,
and the fibre cannot so readily be distinguished from the
membrana propria of the duct upon which it rests. But I
do not wish to be understood that because the nerves have
been lost out of sight, along-side of vessels, that they have
their “ending” there, inasmuch as the network of bloodvessels
is such a close one that the nerves cannot but help
coming in contact with them. Fig. 8 shows such a fine nerve-trunk.
By the aid of aniline blue the fine fibrils have been
made quite plain. Such fine fibrils can by the same means be
demonstrated in much larger trunks, as shown in fig. 7, and it
can be shown that even such large trunks consist of nothing
but these fine fibrils.
I have also seen, exceptionally however, fine nerve twigs
run into the alveoli directly, but the nerves here were of the
same nature as the ones described going to the duct. Fig. 9
shows a fine fibril passing on to an alveolus and running probably
on to a vessel; the nerve fibre resting upon gland cells,
also stained, could not with absolute certainty be traced to the
vessel. There is a small break shown in the drawing.
As intimated, especially if the cells of the duct are still in
situ, it is impossible to follow the fine nerve-fibres any further.
By pressing out the cells from the ducts, one can obtain portion
of the duct, with the capillaries belonging to them, but
they are short pieces, and the nerve fibril is not easily discoverable.
But there remains one fact to be mentioned, which may
throw light on the question, as to how the nerves end and
which in my opinion might and does clear up the difficulty.
Examining the capillaries supplying the gland alveoli,
one is able to find nuclei, not belonging to the capillaries
themselves. This statement can be made for two reasons. In
the first place, the majority of these nuclei have not the form
204of the nuclei of the capillary, and in the second place these
nuclei are situated on the outside of the capillary wall. Whoever
has examined the capillaries of the frog’s muscle knows
that just such or the same nuclei belong to nerve-fibres, supplying
the capillary wall. In the mammal of course these
nuclei are smaller and not so conspicuous, nor can we procure
pieces of capilliary of any length (the structures under examination
here, not being in one plane.) Thus we cannot expect to
have matters so plain here and easy of demonstration. After
finding these nuclei, it was of course my desire to find if they
were united by fibres. It must in this matter be kept in mind,
that if there are such fibres present to which these nuclei belong,
these may be expected to be in the most intimate relation
with the capilliary wall, if one is to influence the other—and
therefore not of ready and easy demonstration.
I have, however, succeeded in showing in a number of instances
that such fibres exist. Figs. 10 and 11 show such a fibre
uniting several nuclei. The shortness of these fragments makes
a more perfect demonstration almost impossible.
If this observation is correct, we find on the capillaries the
same (only finer) fibres provided with nuclei, which we have
lost out of sight following the branching out of the nerves.
There is also some evidence of fine fibres in the membrana
propria of the ducts, inasmuch as we find here nuclei along-side
of the capillaries, these not being the nuclei of the membrane,
but resembling altogether the nuclei of the nerve fibres.
Again, as stated above, I have not been able to find any
such evidence of nerves in connection with the gland cells
themselves. In case, however, such an arrangement or something
similar existed, why should it have been impossible for me
to find evidences of such as well here on the gland cells as on
the capillaries; and should they not be more readily found in
the gland than in the capillary, inasmuch as we have larger
structures to deal with here in the gland.
The conclusion then regarding the nerve-endings to which
my work has led me are these:
There were no special nerve-endings found in connection
with the gland cells themselves. We find, however, upon the
205capillaries evidence of the same kind of fine nucleated fibrils, which
we find to be present in the fine nerve twigs, as far as we can
follow them in their course towards their final distribution. To
explain the action of nerves on the process of secretion we
would have to assume either that the nerves accompanying
the capillaries also influence the gland cells, or that the glands
are stimulated to activity by some changes in the condition of
the capillary wall furnishing a greater amount of oxygen and
nutritive fluids.
The results are partly negative, partly positive. The latter
I wish to emphasize, believing it worthy of attention, as it may
throw light on the physiology of the capillary wall, which seems
to be altogether too much neglected. The negative I have
offered, knowing well enough that such negative results must
be accepted as final with much hesitation.
To any one feeling inclined to undertake investigation on
this gland, I would make a few suggestions:
(1) Make sections through gland hardened in bichromate of potash, or alcohol, and
stain with staining fluids.
(2) Compare in material prepared as above described, the vascular supply of duct
and gland substance proper.
(3) Compare gland and duct cells.
(4) Find the nuclei of the membrana propria and compare the same with the nuclei of
the gland cells.
(5) See if you can examine the same nucleus from different sides. Do you think that
the demilune of books and the nucleus of the membrana propria might be the same thing?
(6) Prepare pieces of the membrana propria covering the alveoli. What is your opinion—is
there a membrane or only a reticulum of connective tissue cells?
(7) Prepare pieces of membrana propria of duct.
(8) Can you find the nuclei of the duct, and other nuclei on the exterior of the capillaries?
(9) Can you find pieces of capillaries belonging to the alveoli, and do you find any
nuclei on them?
(10) Examine the wall of the duct in injected and uninjected material, both stained.
(11) Follow the bloodvessels—can you find nerves on the walls of arteries?
(12) Of what structure do you find the root of a little lobule to consist?
(13) How do the nerve trunks differ from the fibrous envelope holding together all
these structures?
(14) Differentiate between the nuclei of the nerve fibres and the nuclei of the nerve
sheath.
(15) Examine nerve branches of various thicknesses—what do you find the nature of
the nerve fibres to be? Do not forget the aniline blue and try other staining fluids.
(16) Can you find evidence in the alveoli of other structures besides capillary, membrana
propria and salivary cells?
(17) How far have you succeeded in following the fine nerve twigs?
206(18) By all means try different methods, different tissue, and compare the results. See
what you can discover by simply teasing material treated with Muller’s fluid, and other
stained and treated as I have described.
(19) Follow the course of the arteries, and note where the larger vessels pass into the
capillaries.
BY JOHN BENNITT, M. D.,
Professor of Principles and Practice of Medicine in the Medical Department of the Western Reserve University, Cleveland, Ohio.
[Continued from page 103.]
But the contributions to medicine of all his predecessors
dwarf into insignificance when compared to those of Galen—who
lived and wrote in the middle of the second century—and
whose writings were ultimate authority, until they were attacked
and publicly burned in the 16th century by the arch-quack
Paracelsus. Galen, although born in Pergamus, in Mysia and living
there, was called by the Emperors M. Aurelius, and L.
Verus to attend them in the northeastern frontier of Italy, and
was for a considerable period of time physician to the emperor,
spending a considerable portion of the last half of his life at
Rome. He died in Sicily in 201 aet 71 (?) There are ascribed
to him 83 treatises on medicine about which there is no question
as to their genuineness, 19 that are questionable, 45 undoubtedly
spurious, 19 fragments, 15 commentaries on Hippocrates’
works. Besides these, he wrote a great number of works (not
all on medicine) whose titles only are preserved, so that altogether
it is believed that the number of distinct treatises cannot
have been less than 500. These were, on (1) Anatomy and
Physiology, (2) Dietetics and Hygiene, (3) Pathology, (4) Semiology
and Diagnosis, (5) Materia Medica and Pharmacy, (6)
Therapeutics including Surgery, (7) Commentaries on Hippocrates,
(8) Philosophical and Miscellaneous. Most of these
works are still extant in Greek (in which they were originally
written). They have been translated into many modern languages.
His works on anatomy and physiology are most valuable.
207But it is not certain that he ever dissected human bodies.
His knowledge he derived from dissecting apes, bears, goats,
etc., and his knowledge of physiology from experiments on
these animals. His pathology was speculative.
In diagnosis and prognosis he laid great stress upon the
pulse, on which subject he may be considered as the first and
greatest authority, for subsequent writers adopted his system
without alteration. He placed great confidence in the doctrine
of “critical days,” which he believed to be influenced by the
moon.
In materia medica he was not considered as good authority
as Dioscorides. He was prone to making prescriptions containing
many ingredients, some of which were entirely inert.
He seems to have placed more faith in amulets than in
medicine, and is supposed to be the author of the anodyne
necklace, which was for a long time famous in England. He
was an allopathist in his notions, i. e., he believed that disease
is something contrary to nature, and is to be overcome by that
which is contrary to the disease itself. At the same time he
taught that nature is to be preserved by that which has relations
to nature, in accord. Hence his two indications, “Overcome
Disease,” “Sustain Nature.”
Before this time, as already intimated, the medical profession
was divided into several sects, who were always disputing with
one another. After him, all these sects seem to have merged
into his followers. The subsequent Greek and Roman medical
writers were compilers from his writings, and being translated
into Arabic, Galen’s works became authority in the East as well
as in Europe, and continued to be so for fourteen hundred years.
In 1559, Dr. Geynes was cited before the college of physicians
for impugning the infallibility of Galen. On his acknowledgment
of his error and humble recantation, signed with his own
hand, he was received into the college.
The great mass of Galen’s works, together with modern
improvements and researches, have now in great measure consigned
them to neglect, but his fame can only perish with the
science itself. As in the case of Hippocrates, his immeasurable
208superiority over his contemporaries seems to have acted as a
check to all attempts at further improvement.
The first names of any renown that occur subsequent to
Galen are those of Oribasius, Alexander of Tralles, Ætius and
Paulus Egineta, who flourished between the fourth and seventh
centuries. They were all jealous Galenists, and those of their
writings which are still extant are, for the most part, compilations
from the predecessors, especially from their great master,
Galen.
The writings of Paulus seem to be the last of any written in
the Greek language, which had been the language of medical
science for more than a thousand years. At about this time the
Arabian school was beginning to rise into notice. The earliest
Arabian writers on medicine of whom we have any notice or
certain account, is Ahrum, who was contemporary with Paulus.
The most celebrated physicians of this school were Rhazes,
(who flourished in the ninth century, and was the first to describe
small-pox) and Avicenna who flourished early in the
eleventh century, and whose ‘Canon Medicina’ may be regarded
as a cyclopaedia of all that was known of medicine at that time
(as well as collateral sciences). This was a compilation from
Greek writers, whose writings had been translated into Arabic,
(for Avicenna was not a Greek scholar himself). Avenzoar,
and Averrhoes flourished in the twelfth century. The last was
a celebrated philosopher as well as physician. The works of
Hippocrates and Galen, which, together with the works of Aristotle,
Plato and Euclid, were translated into Arabic in the ninth
century, formed the basis of their medical knowledge; but the
Arabian physicians did good service to medicine, introducing new
articles from the East into European materia medica, as for example,
rhubarb, cassia, senna, camphor, and in making known
what may be termed the first elements of pharmaceutical chemistry,
such as a knowledge of distillation, and of the means of
obtaining various metallic oxides and salts.
Upon the decline of the Saracenic universities in Spain, which
was about the time of the death of Averrhoes, the only medical
knowledge that remained was to be found in Italy, where the
School of Salerno acquired considerable celebrity, which it maintained
209for some time, till it was gradually eclipsed by the rising
fame of other medical schools at Bologna—where Mondino
or Mundinus de Leozza publicly dissected two human bodies
in 1315.
Contemporary with Mondini, lived Gilbert, the first English
writer on medicine who acquired any repute; and the next century
gave birth to Linacre, who after studying at Oxford spent
a considerable time at Bologna, Florence, Rome, Venice and
Padua, and subsequently became the founder of the London
College of Physicians. It was in this fifteenth century that the
sect of chemical physicians arose, who claimed that all the phenomena
of the living body could be explained by the same
chemical laws as those that rule inorganic matters. Although
the illustrations and proofs which they adduced were completely
unsatisfactory, yet the tendency at the present time is in the
same direction, since chemistry and physiology are better
known.
This seems to be a period prolific of new diseases. In the
thirteenth, fourteenth and fifteenth centuries we hear most
of leprosy, and of the visitation of the plague in Europe.
Whooping-cough and scurvy were never described by any
writer anterior to the fifteenth century. Syphilis was first recognized
in Italy in the fifteenth century, from which country it
spread rapidly over the whole of Europe.
In the sixteenth century the study of human anatomy may
be said to have been fairly established by the zeal and labors
of Vesalius, and in this and the succeeding centuries we meet
with the names of many physicians whose anatomical and physiological
investigations tended either directly or indirectly to
advance the science of medicine. This was the epoch of
Eustachius, Fallopius, Asellius, Harvey, Rudbeck, Bartholini,
Malpighi, Glisson, Sylvius, Willis, Bellini, etc., names preserved
in anatomy.
Chemistry was now being separated from alchemy, and advancing
to a science, and a combination formed between its
principles and those of physiology, which gave rise to a new
sect of chemical physicians, quite distinct from the sect represented
two centuries before by Paracelsus. The chemical
210school was succeeded by the mathematical school, of which
Borelli, Sauvages, Heill, Jurin, Mead and Freind were amongst
the most celebrated. While at the same time the old Galenists
were fast disappearing. To the rival sects of this period must
be added the Vitalists, which originated with Von Helmont,
and with some modifications was adopted by Stahl and Hoffman.
The greatest physician of the seventeenth century was,
however, Sydenham, who, though inclining to the chemical
school, did not allow his speculative opinions regarding the
nature of disease to interfere with a careful consideration of the
indications for treatment, as derived from the symptoms, and
from experience.
Boerhaave, a Dutch physician and philosopher, occupied
special prominence in last part of the seventeenth and the early
part of the eighteenth centuries. He engaged in the practice
of medicine at Leyden in 1693, and became professor of
theory and practice of medicine in the university of that city
in 1701. He was erudite, exact, simple and eloquent, and
hence as a lecturer very popular. He specially advocated simplicity
in practice of medicine. Professor of botany was added
to his duties in 1709. He wrote a treatise in 1703 (in Latin)
advocating mechanical and chemical hypotheses in medicine.
In 1708 his institutes of medicine extended his reputation; and
in 1709 appeared his famous ‘Aphorisms’ on the diagnosis and
cure of disease. In this was a well defined classification of
diseases, including their causes, nature and treatment, which
was adopted by his contemporaries. He was distinguished as
a botanist and chemist. He published a description of plants
at Leyden in 1710, and became professor of chemistry in 1718
in addition to his other duties. He made chemistry popular
by presenting it in a clear and attractive style, in his lectures
and in his ‘Elements of Chemistry’ (1724).
On account of his attack of gout he was constrained to give
up the teaching of botany and chemistry in 1727. He was
elected a Fellow of the Royal Society of London in 1730. His
fame extended over the world. A Chinese mandarin hearing
of his fame addressed a letter to Boerhaave, physician in
Europe, which reached him in due time. His practice was
211lucrative, and he spent money freely in the interest of science
and benevolence, yet such was his success that it is said that at
his death (in 1738) he left an estate of nearly a million dollars.
Cullen, who was born in 1710 and died in 1790, was undoubtedly
the greatest medical man of his age. It is especially
interesting to read the biographies of such men as Cullen and
of Hunter his contemporary, and of Jenner of the last half of
the eighteenth century, and of John Brown the quack—though
much quoted.
The present century may be considered as the epoch of physiological
experiment and clinical observation. The efficient
laborers of the last eighty years in the field of medicine have
been so numerous that it would be impossible to notice at this
time even those deemed most celebrated, while it would be invidious
to attempt such a selection.
In this time our materia medica has received a large number
of most important additions, amongst which may be noticed,
morphia, quinia, strychnia, iodine and the iodides, bromides,
cyanohydric acid, cod-liver oil, chloroform, chloral, nitrite, amyl
and a long list of preparations from the vegetable kingdom and
from the hydrocarbon series.
The physical diagnosis of disease has been facilitated to an
extent far beyond what the most sanguine physician of the last
century could have deemed possible, by the discovery and practical
application of the stethoscope, the pleximeter, the speculum
in various forms, the ophthalmoscope, the laryngoscope and the
thermometer; while chemistry and the microscopy have been
applied successfully to the investigation of the various excretions,
and especially of the urine, bile, and in the study of digestion
where the process could be observed in its various stages in the
person of Alexis St. Martin.
But the field for the medical historian broadens immensely and
can best be appreciated by study of a catalogue of medical
books and periodicals of the present century.
212
BY D. B. SMITH, M. D.
Professor of Diseases of the Eye and Ear in the Medical Department of Western
Reserve University.
On the fourth day of June I was called to see Miss C. R.,
aged nineteen years, a clerk, who told me that she had gone to
bed the night before perfectly well, and that when she awoke
in the morning she found herself totally blind, and had remained
so up to the time of my visit, about eleven o’clock. This
blindness she said had come on without the least pain or bad
feeling, and the eyes were not in the least degree uncomfortable,
nor had they been during the morning. No cause on the
part of the patient could be assigned for the attack, and nothing
of the kind had ever happened to any member of the family
before. The external examination gave not the slightest evidence
of any disease of the eyeballs or lids. The conjunctiva
was perfectly normal, as were also the cornea iris and
pupil. The ophthalmoscope revealed a perfectly healthy
retina and optic nerve and clear media. The tension of the
eyeball was normal. There was not the least constitutional
disturbance, if we except a marked nervousness caused by the
fear that she would be permanently blind. The patient declared
most positively that she could not see the lamp even when held
close to the eyes. From the fact that the pupils were perfectly
normal and moveable under the influence of light, and that the
patient put out her hand to shake hands with me in a way that
I felt she could not do if she did not see, I diagnosed a case of
hysterical blindness. It was more than a simulated blindness,
for all the anxiety and mental distress of actual blindness were
present; and I am satisfied the patient was honest in her belief
that she could not see. The ordinary remedies for hysteria
were given and were taken faithfully and regularly, and although
for several days she took large doses of the bromide, valerianate
of ammonia, hyoscyamus, assafœtida, and kindred drugs, there
was not the slightest improvement in her vision. These remedies
were continued from the fourth to the fourteenth without
any perceptible effect. After ten days I began to give her
213tonics instead, and although she took the elixir cinchona with
dilute hydrochloric acid, tincture of nux vomica, quinine, iron
oxid of zinc, and finally stimulants, there was no improvement
and the patient said she remained in total darkness. This tonic
course was continued up to the twenty-ninth, and had been
followed out thoroughly for two full weeks without effect.
During the nearly four weeks treatment the patient said that
when the eyes were shut she could discern the position of the
lighted lamp, but when the eyes were open she could not see
the lamp or the slightest object, or even tell daylight from darkness.
At various intervals during this time her pastor visited
her and offered her his most heartfelt sympathy. Her friends
were becoming exceedingly anxious least the sight would never
return, although I could assure them that there was not the
least danger of permanent blindness. I became satisfied at this
time that medication was not going to dispel this peculiar attack
of hysteria and that it would need something besides
medicine to produce such an impression upon her mind that she
could overcome it, so I told her that I was going to do something
the next day that would surely make her see before night,
and that she should be of good cheer for her sight would return
very soon. The next morning I went down about nine
o’clock armed with my ophthalmoscope, my case of trial glasses
and my Hearteloup’s artificial leech. The patient seemed to be
quite confident that she would soon see, and was very hopeful
as to the result of what was to be done. I looked into the eyes
with my ophthalmoscope, and then applied the cylinder of the
artificial leech to the temples without scarifying and used considerable
traction, first on one side and then on the other, having
previously told her not to open the eyes until I told her to
do so. In about half an hour I told her to open the eyes gradually
so as not to let the light in too suddenly and then tell me what
she could see. The instant she opened them she said I can see
the light and the position of the window. I then told her to
close the eyes again and I reapplied the cylinder and commenced
the suction as before. By this time the temples had
become red and so sensitive that she now complained of some
pain when the cylinder was reapplied. After twenty minutes
214she was told to open the eyes again and she said she could see
objects about the room distinctly. She was then tried with
large letters but she said she could not see to read them, but
could see the black objects. Told her glasses would help her
and placed a No. 72 convex spherical glass before the eyes
when she could see Jaeger No. 20, then told her she needed
other glasses and replaced the No. 72. She now saw to read
No. 16. I continued taking off and putting on this same No.
72, with good effect and whenever she came to a standstill in
reading reapplied the cylinder with uniform benefit until finally
after two hours constant work she could read Jaeger No. 1.
During all this day she was able to see distinctly. The next
day she was again unable to read but a short repetition of the
same course brought her vision back again. There was no return
of the blindness after that except occasionally for a short
time at intervals of two or three days.
In the course of ten days all trace of the difficulty had passed
by and since has never returned. This case was diagnosed as
one of genuine hysteria and not one of simulating blindness or
malingering, and is reported as the most marked case I have
ever had illustrating the effect of hokus pokusing (to call it by
a mild name) which produced such a strong mental impression
that the patient lost sight of her own peculiar mental condition,
and by which a perfect cure was effected.
To her the blindness was real, and her friends feel that a
remarkable cure has been performed. Such a blindness can
occur in any nervous hysterical patient, while simulated blindness
usually occurs in those who wish to avoid service in the
army or navy, or in the case of lazy young people who do not
wish to study at school or college, and in those who have
received a slight injury and wish to make it appear more serious
for the sake of obtaining large damages, either from private
individuals or corporations.
For its detection there are several methods which are usually
sufficient to give us positive proof that the blindness is not
real. Von Graefe placed a number eight or ten prism in front
of the eye, with the base upwards, downwards or sidewise, and
215if strabismus is present before the removal of the prism there
is binocular vision.
Juler places spectacles with an opaque glass in front of the
good eye, when, if the patient can read, he must see with both
eyes; or he places concave 20 before the good eye, when
if the patient can read fine print he must see it with the other
eye.
Juval places a ruler before the eye so as to cover part of the
page to be read, when, if one eye is blind, not all the page can
be read.
Mittendorf puts atropine in the good eye, when if the patient
can read fine print he is not blind with the other eye.
Wells places a prism in front of the supposed blind eye, and
notices whether the apis of vision of that eye changes when
the prism is removed.
Bull bandages the good eye and places a prism in front of
the other eye, and holds a lighted candle before the eye, and if
the eye turns as the prism is turned, the eye is not blind.
The test with Snellens or other colored letters is also a good
one. A word with alternate red and bluish green letters is
painted on glass and placed in the window, and the patient is
asked to read the letters. If a bluish green glass is held in
front of the good eye, he will see only the green letters unless
he can see with the other eye, for all but the red rays in the
red letters are cut off in the transparency in the window, and
the green glass cuts the red off, leaving those letters a perfect
blank to the well eye.
Kugel places various colored glasses before each eye and then
places an opaque glass in front of the sound eye, and a transparent
glass of the same color before the other one, and if the
patient sees the object, he is simulating blindness.
Herring has the patient look through a tube large enough to
cover both eyes, and then suspends a small ball in front of the
tube and drops small objects near this ball, and if the patient
can tell whether the balls are dropped in front of or behind the
suspended ball, he must see with both eyes.
Lawrence recommends the stereoscope for detecting binocular
vision, and places in a covered stereoscope a picture each
216side of which is different, and yet such as to make a single
picture when both sides are seen. A clock dial, for example,
with figures in one side only or figures with complemental
colors, such that with both eyes the object would appear differently
colored from what it would when seen with either eye
separately. The distance apart of two objects held up in front
of both eyes can be readily told by the patient if he sees with
both eyes, no matter how the objects are held with relation to
each other. But if there is vision with one eye only, the patient
can tell the distant apart with accuracy only when the objects
are both held at the same distance from the eye, but not when
one is held considerably in front of the other.
One who sees with one eye only always thinks he is nearer
to the object than he really is when reaching out for that
object. It is always more difficult for him to pour from a
pitcher into a cup or glass if held a little distance below it,
hence the blind in one eye usually place the nose of the pitcher
in contact with the glass before pouring. The old parlor trick
of placing two pins in the wall and putting a cent on them and
directing the patient to stand across the room and then walk
over to the cent and knock it off with the outstretched finger
without hitting the pins, may be made use of as a test in simulated
blindness, for with one eye the patient always falls short
of the mark the first time the experiment is tried. The most
simple method of detecting simulated blindness in one eye is
by noticing the movement of the pupil under the influence of
light. If an eye is blind, the light has little or no effect upon it
when the other eye is closed. The pupil is usually dilated. It
may be well to mention here that atropine dilatation is generally
wider than that due to amaurosis, and also that a cone of light
from a strong convex glass thrown upon the sound eye will
contract the pupil of the blind eye if the dilatation is not due to
atropine. Simulated blindness in both eyes is not likely to be
seen, and then the condition of the pupil is of great value in
detecting it, and is one of the best guides in connection with
the ophthalmoscopic observation.
217
BY S. W. KELLEY, M. D., CLEVELAND, O.
Miss H. E., aged 20, American of Irish parentage:
dark brunette, short in stature but apparently quite handsomely
formed, and ruddy with health. She has never
been sick in her life. Has menstruated normally since her
fifteenth year, though scantily during the past year. She
feared she had been injured a few days previously by the overturning
of a chair upon which she was standing, as she had
since felt pain and uneasiness in the lower pelvic and pubic
region, for which she sought advice.
Upon examination I found no injury worthy of record, but the
malformation here described. Cases of this anomaly have been
recorded from time to time, being always of interest to the
teratologist, occasionally requiring attention on account of interference
with the marital relation or parturition, and being
referred to in every discussion on superfœtation.
The external genitalia are well developed. No hymen, nor
any remains of one. I have no reason to doubt her virginity.
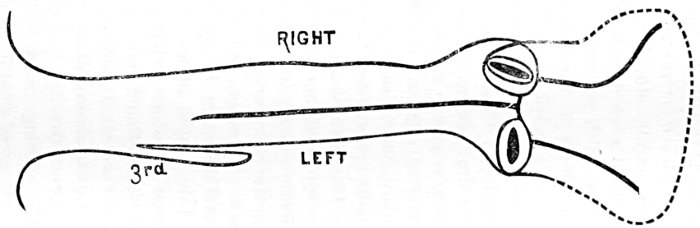
An inch within the introitus vaginæ the finger met a narrowing
into which only its tip would pass. Searching to the left another
smaller opening was discovered, the two being separated
by a strong membrane. Returning to the right or larger passage,
was able by careful dilatation for ten or fifteen minutes to
insert three-fourths of the length of the index finger and encounter
another narrowing, which being patiently overcome,
the first joint of the finger found more room and examined
uterine cervix and the external os, which is linear antero posteriorly.
The neck projects about half an inch into the vagina.
The lips are thin, of normal density. Withdrawing the finger
and finding the smaller opening, could succeed in penetrating
only about an inch. Observed a third, smallest opening in the
left vaginal wall, between the ostium vaginæ and the second
opening described.
218
The patient would consent to no interference that could possibly
cause even temporary disability for daily housework and
care of an invalid mother, but agreed to return daily for a few
days. After dilating without anæsthesia fifteen to twenty minutes
daily for four days, could pass two fingers or a Fergusson
speculum one and one-eighth inches into the right passage, and
could pass one finger readily, or speculum seven-eighths of an
inch in diameter into the left passage. The septum between the
two passages is placed antero posteriorly. It is about an eighth of
an inch thick, and has the appearance of any other portion of the
vaginal wall. It begins an inch within the introitus, and extends
219to the uterus, making a right and left vagina of normal
length. The third, smallest passage, admits a sound and
extends upward an inch in the left lateral vaginal wall and ends
in a blind extremity.
The right vagina discloses an uterine os three-eighths inch in
length antero posteriorly, the anterior end of the slit inclined
toward the median line. The sound passes readily a distance
of one and three-eighths inches, entering in a direction upward
and inward half that length, and then turning upward and outward.
The sound moves freely in the cavity, and the lining
membrane evidently contains folds. Secretion of the cervix
free.
On the left side the os uteri is smaller, the opening not exceeding
a quarter inch, the length being laterally. The lips
are in a pouting shape, the anterior, especially, having quite a
fold above it. The sound enters freely nearly an inch in a
direction upward, outward and slightly backward; lining membrane
apparently folded. Very little secretion. By introducing
two fingers of the left hand, palm upward, the index into
the right vagina and the second finger into the left, the two
uterine mouths can be examined simultaneously, and this gives
a very vivid impression of the condition. As to the shape of
the whole uterus very little can be determined by bimanual examination,
the vaginal walls being so tense and abdominal thick.
By the rectum the uterus can be felt flat and wide, but no
bi-lobing is apparent.
The young lady could not be persuaded to permit an examination
during menstruation to determine whether the flow
took place on both sides.
BY DR. WILLIAM FORSTER, RETIRING PRESIDENT VENANGO COUNTY MEDICAL SOCIETY, PENNSYLVANIA.
Though at best societies in their present form are not very
old, medical associations, differing somewhat in their organization
220and aim, are as old as the science of medicine itself. Even
in the fabulous ages it had its heroes, and some rose to the
height of deification. In earlier ages those who practiced
medicine were looked upon as inspired. They, in addition to
belonging to a profession, constituted a class or caste. In
some Asiatic nations, and among some of our Indian tribes, it
is very much the same at present.
One must belong to the caste, or be able to trace his descent
from it, as a necessary qualification to practice medicine.
This is the earliest form of a medical society, and though it
may not possess many progressive elements, it has elements of
strength.
What few investigations it did make, it kept. Its peculiar
organization and position fitted it for being a good conservator;
and when the star of empire took its western course, the tide of
medical knowledge stored up and held sacred and secret in
Asia, Egypt and Greece, flowed out and was diffused over five
continents.
Hippocrates, about twenty-five hundred years ago, took the
light from under a bushel. About three hundred years later the
great Alexandrian school or society—for it was a society as
well as a school—trimmed the light and set it higher, but it was
so obscured and encompassed with exclusiveness and secrecy
as to be a long time in reaching the masses.
The first societies in Germany, France and Great Britain
were in connection with their institutions of learning, as they
were at an earlier period in Egypt and Greece. In Rome we
have reason to believe that they were more independent, as the
physicians used a society seal as a label for their medicine.
Truly independent society organization and work is comparatively
of our own day. Even in the early part of the present
century, British authority was the London, Edinburgh and
Dublin colleges.
In our own country, previous to the organization of the
American Medical Association, about thirty-six years ago, there
was very little system in society work. That organization
marks a new era in society usefulness. From it sprung the
International Medical Congress, making a unit of medical
221investigation and progress of the world. We point with pride
to Philadelphia as the city in which the association was organized,
and to the able and determined stand our State has ever taken
in sustaining and strengthening it. It has been a power for
good to American medicine. It has elevated and is elevating
the standard of our American medical colleges.
The progress in society organization, work and usefulness in
the last thirty-six years is greater than in all American medical
history previous to that time. We had then a few isolated
independent medical societies without unity and without
influence. We have at present a society in almost every
county, a State society in every State, all united in an association
and wielding an influence national and world wide.
Great as the benefit has been to the profession at large, it has
been greater still to the individual practitioner. It has been
to him a post-graduate school.
In our societies A. meets B., B., C. and C., D. They compare
their investigations, experiences and theories, and each is
benefited.
Our society enables us to know one another better. It is a
true saying that, “no man is as good as his best deed nor as
bad as his worst.” Our meeting in society aids us in striking
the balance and makes us more united, by forming and cementing
friendships. They discourage quackery, empiricism and
everything that is professionally low and mean. They encourage
and stimulate purity, nobility and rectitude. They are a
strength to us medically and medico-legally. All that is necessary
on our part to secure us these benefits and many more
which might be enumerated, is to do our duty to our county,
State and national societies. I will now present to you what I
believe to constitute at least part of that duty.
First. Punctuality and regularity in attendance. This increases
our interest and gives the society strength.
Second. Support with our intellect. We may not all have
an equal number of talents, but he that has five should use
them, and he that has one should use it, and the use of that
one may be just what the society needs at the time.
222If we have anything we think good in theory or practice, or
any interesting case, let us report to our society.
I believe everything presented should be in writing, for very
few physicians are good extemporaneous speakers, and all
members should have such notice of the subject of all papers
to be read before the society as will give them time to prepare
for intelligent discussion; for unless a man has a clear idea of
his subject he is liable to wander off into a labyrinth of side
issues.
When appointed for a paper, we should have it ready and be
on hand to read it. We should have more papers published,
and to better prepare them for publication, each society should
have an editor and a publication committee, with ability and
power to revise, correct and publish papers and reports of the
society.
Third. We should support our society with our influence.
All have an influence, and there is no neutral ground. It
must be for or against.
Never was there a time when there was more need of the support
of the good men in the profession. The code of medical
ethics has been attacked. The American Medical
association has been attacked.
An attempt has been made to make the one obnoxious and
destroy the harmony and usefulness of the other.
Fourth. We should be prompt in paying our dues and all
other necessary demands that may be made on us by our society.
Negligence—for it is seldom or never inability—on our part may
not only embarrass the society, but tend to destroy our interest
in it.
I have a great regard for the Venango County Medical
Society. It was the first society I joined after graduating, over
twenty years ago, and I have always highly prized the friendships
herein formed.
Death has taken some from us, good men and true, but I am
pleased to see that we are also adding to our number so many
young men, and growing in strength. Let us each do our part
to keep up this growth, so that when we are weighed in the balance
we may not be found wanting.
I thank you for your kind aid and forbearance throughout the
year. May our society live long and prosper.
223
The Cleveland Medical Gazette.
A MONTHLY JOURNAL OF MEDICINE AND SURGERY.
One Dollar per Annum in Advance.
All letters and communications should be addressed to the Cleveland Medical Gazette, No. 5 Euclid Avenue, Cleveland, Ohio.
| A. R. BAKER, M. D., Editor. |
S. W. KELLEY, M. D., Associate Editor. |