INTRODUCTION — I. THE NATURE AND FORMS OF SYPHILIS OF THE NERVOUS SYSTEM (NEUROSYPHILIS) — II. THE SYSTEMATIC DIAGNOSIS OF THE MAIN FORMS OF NEUROSYPHILIS — III. PUZZLES AND ERRORS IN THE DIAGNOSIS OF NEUROSYPHILIS — IV. MEDICOLEGAL AND SOCIAL — V. SOME RESULTS OF TREATMENT — VI. NEUROSYPHILIS AND THE WAR — VII. SUMMARY AND KEY
13
It is a privilege to be allowed to write a word of introduction
to a textbook which so richly fulfils its function as does
this volume on the manifold disorders classified under Neurosyphilis,
a subject of which the importance for the welfare of
society is found to loom the larger the more deeply its mysteries
are probed.
The case histories with which its pages are so amply
stocked are carefully analyzed in accordance with a broadly
chosen plan, and the generalizations that precede and follow
them are obviously based on a wide and varied personal
experience such as alone could render a familiarity with the
literature of the subjects treated adequate to its best usefulness.
Both writers were indeed well adapted for this task.
Dr. Southard, as everyone is aware, has long been a highly
conscientious, ardent and productive worker in the department
of pathological anatomy, and of late years a careful
student of clinical diagnosis and methods, both at the Danvers
State Hospital and still more, at the Psychopathic Hospital
which he worked so hard to found; while Dr. Solomon’s
researches, in the special field of neurosyphilis, have been of
the highest order.
Undoubted as are the merits of the case-system of instruction
that has been so much in vogue in recent years,
and excellent as is the modern supplementation of this method
by the use of published records, the danger is still real that
the student will have presented to him a picture of nature in
disease that is too diagrammatic, too concise, with the result
that while the task of memory is lightened through simplified
formulation, the training of the doubting and inquiring
instincts is often given too little stimulus and scope. In
this book this danger is deliberately met through the casting
of emphasis rather on the pluralistic aspects of the processes
at stake than (primarily) on their unitary aspects.
14The student who utilizes this volume cannot but emerge
from his study a more thoughtful person than he was at the
period of his entry. He will have seen that clinical rules of
thumb cannot be followed to advantage, and that, on the
contrary, surprises are to be expected and prepared for.
Let the recognition of this fact, if it seems to increase the
difficulties in the way of diagnosis, not lead to pessimism in
that respect, or to hopelessness in therapeutics. On the
contrary the writers’ bias is towards the worth-whileness of
clinical efforts and an increased respect for accuracy and
thoroughness in the utilization of modern methods of research.
The chance is indeed held open that even the gaunt spectre
of “General Paresis” may prove to be less terrible than it
seems, and for this hope good grounds are given.
It is in this way made clear, on the strength of anatomical
evidence of much interest, that even if in the treatment of a
given patient, the time arrives when a fatal or unfavorable
result seems manifestly foreshadowed, it may be still worth
while to renew the treatment with fresh zeal, for the sake of
combatting some symptom or exacerbation, for which a
locally fresh process furnishes the cause.
Another noteworthy principle here emphasized and illustrated
is that the relationship between “functional” (hysterical,
neurasthenic, migrainoid) symptoms and the signs
(or symptoms) of organic processes is clinically important
and worthy of much further study. This is a matter which,
in a general sense, has interested me for many years. Above
and over the “organic” hovers always the “functional,” as
representing the first indication of the marvelous tendency
to repair, or substitution, for which the resources of nature
are so vast. Yet this functional tendency also has its laws,
of which, in their turn, the organic processes display the
action in quasi diagrammatic form. Hysteria, neurasthenia,
migraine, etc., do not arise de novo in each case, but conform
to typical, though not rigid, formulas, susceptible of description.
I have recently had the opportunity to study in detail
an analogous series of transitions between the movements
(and emotions) indicative of apparently purposeless myoclonic
movements (on an epileptoid basis) and the movements
15of surprise, engrossment, purposeful effort, the excitement
and joy by which the former were excited and into which
they shaded over.
Taken altogether, this book represents work and thought
in which, for amount and kind, the neurologists of Boston
may take just pride.
St. Hubert’s, Keene Valley, New York.
August, 1917.
16
Me miserable! which way shall I fly
Infinite wrath and infinite despair?
Which way I fly is Hell; myself am Hell;
And, in the lowest deep, a lower deep
Still threatening to devour me opens wide,
To which the Hell I suffer seems a Heaven.
Paradise Lost, Book IV, lines 73–78.
17
PARADIGM to show possible abundance and
variety of symptoms and lesions in DIFFUSE
NEUROSYPHILIS (“cerebrospinal syphilis”).
Autopsy.
Case 1. Mrs. Alice Morton[1] was in the hands of at least
five well-known specialists in different branches of medicine
and surgery during the nineteen years of her disease. It
appears that she acquired syphilis upon marriage at the age
of 23 to a man who later became tabetic and acknowledged
syphilitic infection previous to marriage. Mrs. Morton
remained without children and there were no miscarriages.
At the age of 27, she developed iritis, paresis of the left eye
muscles, and ulceration of the throat, with destruction of the
uvula. The syphilitic nature of her disease was at once
recognized and the classical treatment was given, although,
through numerous shifts in consultants, this treatment was
never pushed to the limit. At 28 Mrs. M. began to suffer
from severe headaches resembling migraine and accompanied
by attacks of paræsthesia; at 35, came severe pains in the
back and difficulty in walking.
At 36, the migraine attacks began to be accompanied by
blurring of vision and dizziness. The difficulty in walking
became extreme, affecting particularly the right foot. The
18legs became spastic, there were pains and hyperæsthesia of
the chest, and severe cramps of the legs. Antisyphilitic
treatment at this time yielded marked improvement.
During her thirty-sixth year, Mrs. M. sustained curious
transient losses of vision and of hearing. She was also irritable,
and at this time developed her first pronounced mental
symptoms, namely, delusions concerning her relatives.
There were also a few seizures of an epileptiform nature.
At 38 there was a spell of total deafness, followed by improvement.
The eye muscles were also subject to a variable
involvement with intervening spells of improvement.
The knee-jerks were lost, but after a time returned in less
pronounced form. Shortly, an absolute paralysis and extensive
decubitus developed, and death occurred at 39.
The autopsy is briefly summarized below, but it is important
in the understanding of Mrs. M.’s case (particularly some of
the sensory symptoms and the transiency of certain symptoms)
to consider the pre-infective history. Although there seems
to be no doubt that the patient acquired syphilis at about
23 years of age from a syphilitic husband, who himself later
became tabetic, yet it is of note that the patient was the
only child of parents, both of whom also suffered from mental
disease. Mrs. M.’s father died of what was called softening
of the brain (one should avoid terming all old cases of so-called
“softening of the brain” syphilitic, since the older diagnosticians
did not always distinguish between non-syphilitic
arteriosclerotic effects and syphilitic disease). Mrs. M.’s
mother also died insane (confusion and emotional depression).
It is clear, then, that we do not need to suppose that every
symptom shown by Mrs. M. is directly due to destructive or
irritative lesions immediately due to the spirocheta pallida.
The case is, in fact, an excellent lesson as to the association of
structural and functional effects in neuropathological cases.
Mrs. M. as a child had shown talent, but was somewhat
nervous and eccentric. At one time, she had an attack of
hysterical dysphasia; at another time, an attack of hysterical
dyspnea; during another period, an apparent obsession (kicking
the mopboard at regular intervals). Moreover, she had
for years suffered from migraines of a severe and unusual type.
19Both the hysterical tendency and the migrainous tendency
became mingled with the results of the neurosyphilis in later
stages of the disease in such wise that it was hard to tell
exactly where the structural phenomena left off and the
functional phenomena began.
For example, at the age of 32, nine years after infection
and four years after the earliest nerve symptoms traceable
to syphilis, and at about the time of the onset of spinal cord
symptoms, an attack was described as follows:
The patient had a very severe attack of migraine (?)
yesterday, preceded and accompanied by paraphasia,
so severe that for three hours she was unable to make
herself understood, and indeed felt “as if her ideas were
getting away from her.” This attack was ushered in
by a numbness of the forefinger and thumb of the right
hand, which lasted for about three hours, though the
earlier attacks had lasted for only about ten minutes.
During this period the hand felt as if it had been frozen
and the loss of muscular power was so great that she
was unable to hold objects in the hand. In some of
the attacks this paræsthesia has affected the entire left
half of the body, and occasionally the right half. Sometimes
the seizures come on with great suddenness, so that
once, when she was attacked while in the middle of
the street, she had considerable difficulty in reaching
the sidewalk. After the worst part of the attack is
over a certain amount of paraphasia may persist for
some days, together with awkwardness in the use of
the right hand and numbness. She has had a great
deal of nausea and vomiting, without reference to the
taking of food.[2]
Bearing in mind the mingling of structural with functional
symptoms in this case, let us consider the autopsy findings.
20
ANATOMICAL
FORMS OF NEUROSYPHILIS
AUTONOMIC (SYMPATHETIC) NEUROSYPHILIS?
CENTRAL NEUROSYPHILIS
MENINGEAL
VASCULAR
PARENCHYMATOUS
MENINGOVASCULAR
VASCULOPARENCHYMATOUS
DIFFUSE ( = MENINGOVASCULOPARENCHYMATOUS)
Chart 1
21
CLINICAL FORMS OF NEUROSYPHILIS
HEAD AND FEARNSIDES, 1914
SYPHILIS MENINGOVASCULARIS
CEREBRAL FORMS
HEMIPLEGIA
AFFECTION OF THE CRANIAL NERVES
MUSCULAR ATROPHY
LATERAL AND COMBINED DEGENERATIONS
EPILEPSY
SYPHILIS CENTRALIS
DEMENTIA PARALYTICA
TABES DORSALIS
MUSCULAR ATROPHY
OPTIC ATROPHY
GASTRIC CRISES
EPILEPTIC MANIFESTATIONS
22Peripheral neurosyphilis: The lesions of the cranial
nerves were characteristically asymmetrical. Whereas the
left third nerve looked entirely normal, the right third nerve
had its diameter reduced two-thirds. On the other hand,
the fourth nerves were equal and apparently normal. The
sensory portion of the left fifth nerve was normal; the right
fifth nerve was normal. The right sixth nerve agreed with the
right third nerve in being atrophic, and was in fact reduced
to a mere thread without contained nerve fibres at a point
2 mm. from its superficial origin. Although the right third
nerve was atrophic, it was the left seventh and eighth
nerves which had become atrophic; the process had spared
the right seventh and eighth nerves. The remainder of the
cranial nerves were grossly normal, except that the optic
nerves had an outer zone of a translucent nature. So far,
no spirochetes have been demonstrated in any portion of the
nervous system of this case, but such asymmetrical and focal
cranial nerve lesions are perhaps due to local spirochetal
infection, punctuating (as it were) the diffuse process.
How much of the transient blindness, deafness, and
ocular paralysis can be explained on the anatomical findings
in these nerves? Possibly a portion of the phenomena can be
so explained. Thus, the mechanical conditions of pressure
inside and outside these nerves, both in their peripheral course
and in their passage through the membranes, can be readily
understood to differ during the acute and subacute inflammation,
during the process of repair in the pial tissues, and
during the process of overgrowth of neuroglia tissue about
the superficial origins of the nerves. Of course, the majority
of lesions of these nerves were entirely extinct at the time of
the autopsy, and their history could be surmised only from
the appearances in the left eighth nerve. Here occurred a
sharply marked focal area of gliosis with apparently total
destruction of nerve fibres and related with a lymphocytosis
of the investing membrane (one of the few areas of lymphocytosis
found anywhere in this case).
If it were not for the pre-infective history, the hysterical
dysphasia and dypsnea, the youthful obsessions, the migrainous
tendency, and the psychopathic inheritance, we might be
tempted to try to explain the transient blindness, the deafness,
and ocular palsies on the basis of mechanical and toxic variations
in the conditions of the peripheral cranial nerves.
The existence of a trace of lymphocytosis in the left eighth
nerve leads to the hypothesis that treatment might still be
effective in this particular region (see below in discussion of
spinal symptoms).
23Spinal neurosyphilis: Not only the spinal cord but also
the posterior and anterior nerve roots exhibited severe lesions.
These lesions were both meningeal and parenchymatous.
The meningeal process differed in its intensity in different
parts of the spinal cord, being severest in the thoracic region.
At one point in this region, the dura mater was so firmly
attached to the pia mater that the line of demarcation between
the two membranes was hard to make out. In fact,
it seems clear that there could have been no free intercommunication
between the spinal fluid above these adhesions
of dura to pia mater and the spinal fluid below the adhesions.
Accordingly, it seems that lumbar puncture, had it been
practised in this case, would have failed to show features representative
of the whole cerebrospinal fluid system. Moreover,
since at no point in this region of adhesions or in the
pia mater of the spinal cord below this point, were found any
lymphocytes, it seems clear that the ordinary lumbar puncture
would have failed to reveal a pleocytosis. Whether this
fluid would have yielded a positive globulin and excess albumin
test, it is now impossible to say; but it appears that
the process in the lower part of the spinal cord was to all
intents and purposes extinct.
However, there was one region of more severe inflammatory
involvement. The spinal cord in the cervical region showed
a lymphocyte infiltration of its vessels amounting to a mild
myelitis (meaning, thereby, an inflammatory process of the
spinal cord remote from the pia mater). Moreover, in this
region, there was, besides the perivascular infiltration of the
substance, also an infiltration of the overlying membranes
themselves, especially in and near the posterior root zones.
The lessons of this finding are several: The inflammatory
process in this case does not appear to have been entirely
extinct! Can we not suppose that treatment might still
have benefited this local inflammation (perivascular infiltration
of the cervical spinal cord substance and overlying lymphocytic
meningitis)? Can we not also picture the gradual
ascent of the inflammatory lesions from lower segments to
higher segments and possibly conceive of the gradual elevation
of the zone of hyperæsthesia manifested in this case as
24following the gradual displacement upward of the lymphocytic
process? Are there spirochetes in this tissue? So far none
have been discovered, possibly through inaccuracies of
available technique. To the neuropathologist, however, the
lesion looks like a local reaction to organisms.
In addition to the spinal meningitis, chronic and acute,
as above described, there were extensive parenchymatous
spinal lesions.
In the first place, the meningitis had affected practically
all the posterior roots so that the explanation of the posterior
column sclerosis of this case is clear. The meningitis had
apparently been so marked, also, that all the fibres anywhere
near the periphery of the spinal cord had been likewise destroyed.
The posterior columns and the posterior root zones
were markedly sclerotic; or as we say (having reference to the
overgrowth of neuroglia tissue) gliotic. But there was as
much sclerosis (gliosis) of the lateral columns (particularly in
the posterior two-thirds) as there was in the posterior columns
and root zones. In fact, the entire posterior half or two-thirds
of the spinal cord markedly outstripped the anterior portions
of the cord in the severity of the gliosis (sclerosis) shown.
But although we can explain the posterior column sclerosis,
the sclerosis of the posterior root zones and the marginal
sclerosis (Randsklerose) round the entire periphery of the
cord, on the basis of long-standing effects of old meningitis,
we cannot thus explain another finding, namely, the destruction
of the fibres in the lateral columns. This, in fact,
is explained through lesions (mentioned below) that affected
the encephalon. The net result of all these lesions of the
spinal cord was to leave only the gray matter and a small
amount of surrounding fibres (belonging to short tracts uniting
nearby segments) intact. Briefly stated, every long tract in
the spinal cord appeared upon examination to be extensively
degenerated. The genesis of this parenchymatous loss was,
however, double, being in part due to a local meningeal process
(sometimes known as “perimeningitis”) and in part due
to a cutting off of the pyramidal tract fibres on both sides by
lesions higher up in the nervous system.
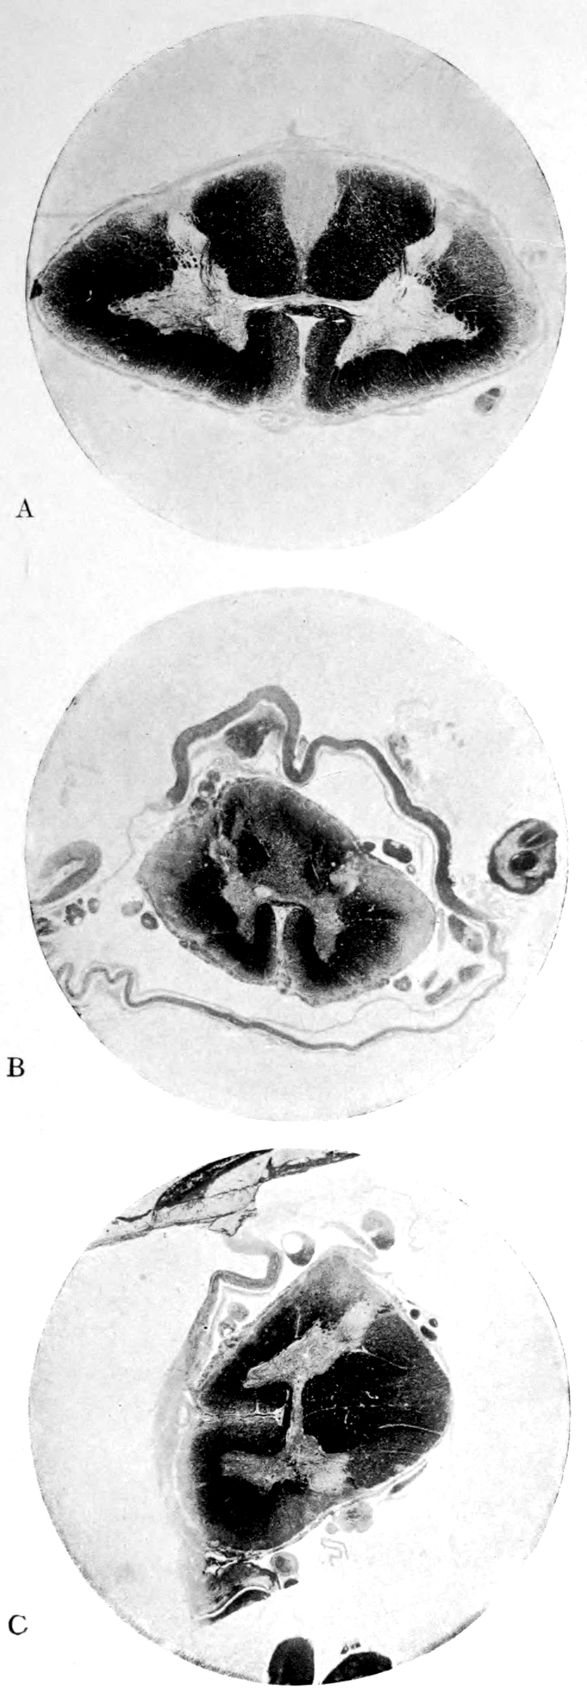
Case I. Spinal Cord (Three Levels) Showing:
A. Marginal sclerosis—effect of old meningitis now extinct.
B. Posterior column sclerosis—effect of meningitis about posterior roots also now extinct.
C. Bilateral pyramidal tract sclerosis—effect of cerebral thrombotic lesions.
Note distortion of tissues in B and C, partly artificial (tissues in places diffluent).
25
| ANATOMICAL FORMULAE |
| |
| MENINGOVASCULOPARENCHYMATOUS INVOLVEMENT |
| |
| M, V, P, or Combinations Applied to the Classification of Head and Fearnsides |
| |
| I. |
SYPHILIS MENINGOVASCULARIS |
|
| |
CEREBRAL FORMS |
M or V or MV[3] |
| |
HEMIPLEGIA |
V |
| |
AFFECTION OF THE CRANIAL NERVES |
M |
| |
MUSCULAR ATROPHY |
M |
| |
LATERAL AND COMBINED DEGENERATIONS |
M |
| |
EPILEPSY |
M or V |
| |
| II. |
SYPHILIS CENTRALIS |
|
| |
DEMENTIA PARALYTICA |
MVP or VP |
| |
TABES DORSALIS |
MP |
| |
MUSCULAR ATROPHY |
P |
| |
OPTIC ATROPHY |
P |
| |
GASTRIC CRISES |
(M? or) P? |
| |
| EPILEPTIC MANIFESTATIONS |
P? |
| |
| Chart 3 |
26Can we offer any explanation of the partial return of knee-jerks after their temporary total loss at a certain period of
the disease? We may assume that the knee-jerks were
functionally lost about a year before the death of the patient
through the partial or even almost complete destruction of
the entering posterior root fibres at that level of the spinal
cord which is directly related with the knee-jerk. The later
partial return of the knee-jerks apparently requires us to
suppose the maintenance of some fibres and collaterals by
which a functional connection can be effected between the
fibres of the posterior roots and the anterior horn cells which
innervate the quadriceps femoris. Let us now suppose
that pari passu with the actual return of the knee-jerks,
the destructive processes that are affecting both pyramidal
tracts high up in the nervous system are now advancing.
It is clear that, whatever inhibitory influence these pyramidal
tracts have been exerting up to this time upon the knee-jerk
reflex arc, that influence is now to be decidedly reduced in
amount and possibly absolutely lost. Upon the loss of
such inhibitory influences exerted from above, the few persisting
connections of the posterior roots and anterior horn
cells are now permitted to resume their functions.
Encephalic neurosyphilis: The lesions mentioned above
as causing destruction of the pyramidal tracts of the spinal
cord were symmetrically destructive and atrophic lesions of
the gray matter of both corpora striata with atrophy of the
anterior segments of the internal capsules. There was a
degenerative process of the corpus callosum especially affecting
the forceps minor of the tapetum. The ventricles
were largely dilated, indicating a considerable destruction and
atrophy of the white matter in general.
After the above discussion of the possible effects of pyramidal
tract lesion in this case, it is unnecessary further to
discuss the paraplegia produced by the cystic lesions of the
corpora striata. The theorist might inquire how these
cystic lesions are produced: whether by vascular blocking or
by toxic effects of the accumulations of spirochetes. Evidence
is lacking which would completely sustain either hypothesis.
Still, we do know that lesions almost identical in
appearance may be produced by the necrosis consequent to
27the plugging of nutritive vessels in an organ like the brain
supplied with end arteries. Therefore, it is probable that
most pathologists would believe these lesions of the corpora
striata to be produced by vascular plugging of the nature of
thrombosis.
It is worth while to note that there was a suggestion of
foci of encephalitis made out upon the gross examination.
The cortex in general showed strikingly few lesions. However,
the convolutions did show in places numerous ill-defined
areas of hyperemia and slight swelling. These areas were of
irregular distribution and only a few mm. or cm. in diameter.
No gross vascular lesions were demonstrable in connection
with these focal areas. Microscopically, however, venous
plugs of polymorphonuclear leucocytes were found, and the
local hyperemias were found to be largely due to venous congestion.
However, very few polymorphonuclear leucocytes
were found outside the blood vessels.
The white matter of numerous convolutions showed microscopically
certain pale spots suggestive of an early atrophic
process. Very possibly these represent a general tendency in
the cerebrum to the same process of parenchymatous loss which
had proceeded to such a marked degree in the spinal cord.
There was a single large so-called cyst of softening in the
cerebellum (1.5 mm. across by 0.5–7.5 cm. in depth).
How far can we explain the symptoms of this case on the
basis of these encephalic lesions? We can offer no correlation
with the cerebellar lesion; and possibly this lack of correlation
is to be expected on account of its failure to affect the vermis.
As to the cystic lesions of the corpora striata, their effect in
producing paraplegia at the close of life is obvious, and their
possible relation to the partial return of knee-jerks has been
discussed. Literally amazing was the comparative integrity
of the cortical gray matter of this case when the spinal cord
and the interior structures of the encephalon had been subjected
to such severe and numerous lesions. The only
mental symptoms noted in the case were sundry delusions
directed against the patient’s relatives and a certain optimism
which led the patient to cling as if with an obsession to the
belief that in the end she would get well.
28
| VARIOUS FORMS OF NEUROSYPHILIS COLLECTED FROM SEVERAL SOURCES |
| |
| MENINGEAL NEUROSYPHILIS (M) |
| |
| GUMMA OF DURA MATER |
M |
| GUMMATOUS MENINGITIS (Pial) |
M |
| SYPHILITIC MENINGITIS (Pial) |
M |
| SYPHILITIC CRANIAL NERVE PALSIES (Primarily Pial) |
M |
| SYPHILITIC BULBAR PALSY |
M |
| SYPHILITIC ROOT NEURITIS |
M |
| SYPHILITIC TRANSVERSE MYELITIS |
M |
| SYPHILITIC NEURITIS (Some Cases by Extension) |
M |
| SYPHILITIC EPILEPSY (Some Cases) |
M |
| SYPHILITIC MUSCULAR ATROPHY (Some Cases) |
M |
| |
| VASCULAR NEUROSYPHILIS (V) |
| |
| SYPHILITIC ARTERIOSCLEROSIS |
V |
| SYPHILITIC CEREBRAL THROMBOSIS |
V |
| SYPHILITIC APOPLEXY |
V |
| ANEURYSM |
V |
| SYPHILITIC EPILEPSY |
V |
| |
|
| PARENCHYMATOUS NEUROSYPHILIS (P) |
| |
| GUMMA |
P |
| CEREBROSPINAL SCLEROSIS |
P |
| SYPHILITIC PARANOIA |
P? |
| SYPHILITIC CHOREA |
P |
| SYPHILITIC EPILEPSY |
P |
| TABETIC PSYCHOSIS |
P? |
| SYPHILITIC MUSCULAR ATROPHY |
P |
| SYPHILITIC NEURITIS |
P |
| |
| Chart 4a |
29
| MENINGOVASCULAR NEUROSYPHILIS (MV) |
| |
| CEREBRAL SYPHILIS |
MV |
| CEREBROSPINAL SYPHILIS |
MV |
| SYPHILITIC EPILEPSY |
MV |
| |
| MENINGOPARENCHYMATOUS NEUROSYPHILIS (MP) |
| |
| CEREBRAL SYPHILIS |
MP |
| CEREBROSPINAL SYPHILIS |
MP |
| TABES DORSALIS |
MP |
| ERB’S SYPHILITIC SPASTIC SPINAL PALSY |
MP |
| |
| VASCULOPARENCHYMATOUS NEUROSYPHILIS (VP) |
| |
| CEREBRAL SYPHILIS |
VP |
| CEREBROSPINAL SYPHILIS |
VP |
| PARETIC NEUROSYPHILIS (GENERAL PARESIS) |
VP |
| LISSAUER’S GENERAL PARESIS |
VP |
| |
| MENINGOVASCULOPARENCHYMATOUS NEUROSYPHILIS (MVP) |
| |
| CEREBRAL SYPHILIS |
MVP |
| CEREBROSPINAL SYPHILIS |
MVP |
| PARETIC NEUROSYPHILIS |
MVP |
| TABOPARESIS |
MVP |
| |
| DOUBTFUL (TOXIC?, IRRITATIVE?) NEUROSYPHILIS (?) |
| |
| “PARESIS SINE PARESI” |
|
| SYPHILITIC NEURASTHENIA |
|
| TABETIC PSYCHOSIS |
|
| SYPHILITIC PARANOIA |
|
| SYPHILITIC POLYURIA, POLYDIPSIA |
|
| SYPHILITIC NEURALGIA |
|
| |
| Chart 4b |
30Summary: We have here dealt at length with a long-standing
Diffuse Neurosyphilis affecting to some extent
the entire meninges and producing a destruction of posterior
column fibres and numerous other fibres of the spinal cord
(tabetiform portion of the neurosyphilis picture). We have
also found central lesions of the corpora striata affecting the
destruction of both pyramidal tracts (paraplegic portion of
the neurosyphilis picture). We have found evidences of
acute inflammation (lymphocytosis) in the cervical region of
the spinal cord and in the left eighth nerve (progressive
inflammatory neurosyphilis picture). In short, we have
presented a case of diffuse (meningovasculoparenchymatous)
neurosyphilis characterized by an ascending character in
a course of at least 16 years; we have indicated a number
of possible clinical correlations, not only with the major portion
of the clinical course (symptoms of myelitis and pyramidal
tract destruction), but we have also mentioned, merely for
their suggestive value, a number of finer correlations between
histological findings and certain clinical features (notably
transient losses of vision and hearing, and a partial
return of the lost knee-jerks). Bearing in mind the clinical
and anatomical findings of this case, we shall be able to discuss
the cases that follow in a briefer and more condensed fashion.
31
TABETIC NEUROSYPHILIS (“tabes dorsalis,”
“locomotor ataxia”) complicated by vascular
neurosyphilis (hemiplegia). Autopsy.
Case 2. Francis Garfield had been a successful lumberman
and had enjoyed good health until his forty-fifth year.
Suddenly one day, while walking on the street, Garfield lost
the use of his legs and for a time was quite unable to walk.
However, he recovered locomotion and after a time there
was nothing wrong with his leg movements except a slight
ataxia.
At the age of 52 Garfield had to give up work. It appears
that he had been becoming cranky, sometimes, for example,
shouting, whistling and slamming doors, apparently to annoy
the family. His intellectual capacity seemed to be maintained,
although his memory was slightly impaired.
At 67 years there was an ill-defined seizure, followed a few
days later by another seizure with aphasia (wrong words
used and lack of understanding of things said).
For years Garfield had been totally deaf in the right ear
(following explosion of a gun?). Now, however, the left
ear also showed a sensory impairment. Slight slurring of
speech had been noticed first in the sixty-sixth year.
Physically there was a slightly enlarged heart with accentuated
second aortic sound and irregular rhythm. Neurologically,
inability to stand or walk; marked ataxia in his
leg movements; upper extremities quite well controlled;
the pupils were small and unequal, the left being larger than
the right; although the reactions were difficult to test, the
pupils seemed to react slightly to direct light stimuli; the
knee-jerks were absent; tests for sensibility so far as could
be determined did not show any abnormalities; there was
much complaint of sharp pains in the legs.
There is no doubt that we are here dealing with a case of
Tabes Dorsalis plus certain complications due to Vascular
Lesions. The case went on to death from rupture of aortic
aneurysm (also doubtless a syphilitic complication). The
death occurred at 71, four years after admission to Danvers
Hospital.
32
MAIN FORMS OF NEUROSYPHILIS
(CLASSIFICATION OF THIS BOOK)
DIFFUSE NEUROSYPHILIS
(non-vascular forms of “cerebral,” “spinal” and “cerebrospinal syphilis”)
VASCULAR NEUROSYPHILIS
(“cerebral arteriosclerosis,” “cerebral thrombosis”)
PARETIC NEUROSYPHILIS
(“general paresis”)
TABETIC NEUROSYPHILIS
(“tabes dorsalis”)
GUMMATOUS NEUROSYPHILIS
(“gumma of membranes, of brain”)
JUVENILE NEUROSYPHILIS
(paretic, tabetic, diffuse)
Chart 5
33
| POSSIBLE INVOLVEMENT |
| |
| BRAIN AND CORD SYPHILIS |
| |
| [M]embranes, [V]essels, [P]arenchyma |
| |
| [MVP] |
EARLY, LATENT?, SYMBIOSIS?, ATTENUATION?.... |
|
| MVP |
CEREBRAL, CEREBROSPINAL SYPHILIS, PARESIS |
MVP |
| [M]VP |
PARESIS; SYPHILITIC ARTERIOSCLEROSIS |
VP |
| M[V]P |
?SYPHILOTOXIN FROM MENINGITIS |
MP |
| MV[P] |
SYPHILITIC MENINGITIS; CEREBRAL OR CEREBROSPINAL SYPHILIS |
MV |
| [MV]P |
SYPHILOTOXIC ATROPHY OR SCLEROSIS |
P |
| M[VP] |
SYPHILITIC MENINGITIS |
M |
| [M]V[P] |
SYPHILITIC ARTERIOSCLEROSIS |
V |
| |
| M, V or P in brackets [] means not involved. |
| |
| Chart 6 |
34
BLOOD WASSERMANN
SPINAL FLUID WASSERMANN
SPINAL FLUID CYTOLOGY
SPINAL FLUID GLOBULIN
SPINAL FLUID ALBUMIN
SPINAL FLUID GOLD SOL
Chart 7
35This case has been especially worked up and published by
Dr. A. M. Barrett on account of the fact that the vascular
lesions of the brain had produced a condition of pure word-deafness.
Reference is made to the Journal of Nervous and
Mental Disease, Vol. 37, 1910, for a complete description of
the brain findings and an analysis of the word-deafness, a
summary of which is as follows:
“Reaction to Words and Sounds.—Total deafness to
words spoken, but gives attention to sounds; no ability
to recognize meaning of sounds heard; no ability to
repeat words heard. Spontaneous Speech.—Retained
ability to speak spontaneously, with rare paraphasic
utterances; occasional inability to speak readily the
word desired, but later always giving the correct reaction;
calculation fair; spelling good except for occasional
paraphasia; spelling good for words pronounced. Reaction
to Things Seen.—Objects correctly recognized
and named except for an occasional paraphasic reply;
mistakes in pronunciation not recognized; correct color
recognition. Reaction to Things Felt.—Good for
familiar objects; an occasional paraphasic reply. Reaction
to Words Seen.—Reads printing and writing
understandingly; unimpaired reading except for an
occasional paraphasic reply; meaning of familiar signs
recognized; slight difficulty in readily understanding
meaning of arithmetical signs. Writing.—Spontaneous
writing and drawing ability retained; ataxia
(tabetic) in writing movements; no ability to write
from dictation. Internal language.—No evidence of
impairment.”
The brain post mortem showed severe atheromatous degeneration
of the arteries at the base of the brain. Both
middle cerebral arteries showed scattered atheromatous
patches. The pia mater was transparent and delicate, except
in the regions of both Sylvian fissures. There were residuals
of old softening in both temporal lobes. In the fresh brain
the regions of the right and left first temporal convolutions
were sunken inward, and the pia intimately adherent to the
36softened areas. The limits and more exact localizing of these
softenings were worked out from serial sections.
Barrett found in his serial sections that, although the transverse
temporal convolutions of the left hemispheres were intact,
these convolutions were undermined throughout their
entire extent by degenerations in the fibres of the center of
the first temporal convolution. Barrett, accordingly, regarded
his case as essentially a case of subcortical tissue
destruction. He agrees with various authors that the pure
word-deafness of his case is the result of an isolation of the
receiving station in the transverse convolutions of the left
hemisphere. The tissue destruction produced by the vascular
lesion had cut off the transverse convolutions from
the internal geniculate body.
We are here, however, not considering the origin and relations
of pure word-deafness but present the case as one of
tabes dorsalis of 20 years standing, terminated by two characteristic
syphilitic complications, first, an extensive destruction
of brain tissue through cerebral thrombosis and secondly,
fatal aortic aneurysm.
Summary: We have here dealt briefly with a long-standing
case of Neurosyphilis of the Tabetic type: A characteristic
but not necessary complication of the case is the Late Cerebral
Vascular Involvement. The posterior column sclerosis
is virtually the only spinal change. Spinal meningeal changes
are absent (although it is to be assumed that chronic inflammatory
changes in the posterior roots were at one time present
in some quantity and although the spinal fluid characteristically
shows lymphocytosis in tabetic neurosyphilis).
Whether the spirochetes produce special toxic components
able to cause tabes or whether special kinds of spirochete are
the tabes-making kinds is hard to say. Special qualities of
individual tissue may be involved.
The cerebral lesions of a cystic nature are of vascular
origin, like the differently localized encephalic lesions of Case
1 (Alice Morton). Vascular syphilis is not a special property
of the vessels of the nervous system. In fact this very case
died of aortic aneurysm.
37
PARETIC NEUROSYPHILIS (“general paresis,”
“dementia paralytica,” “softening of the brain”).
Autopsy.
Case 3. James Dixon, 44, was first seen at the Danvers
Hospital, reciting verses in a dramatic and noisy way. He
remained good-natured and jolly; nor was there any change
in his euphoria until he had become physically weaker and
more generally demented. In fact, Dixon appeared to become
more and more expansive as he became physically
weaker. He was in the habit of describing himself as
“O. K., No. 1, Superfine.”
Physically the patient was gray and bald on vertex, had
a dusky complexion, was very thin (6 ft. in height, weight
155 lbs.); the mucous membranes were pallid; the teeth
rather poorly preserved; the heart was somewhat enlarged;
the pulse irregular in rhythm, of poor volume and tension.
Neurologically, the patient showed a characteristic Romberg
sign and ataxia in walking a straight line. The tremulous
tongue was protruded to the left, and there was a coarse
tremor of the extended fingers. The knee-jerks were absent,
and the Achilles jerks could not be obtained; the plantar
reactions were slight; the arm reflexes were present. The
pupils were stiff to light. There was a marked vocal tremor.
The sensations could not be tested on account of the patient’s
mental state.
It appears that Dixon had left school at about 16, at about
22 had gone into the provision business, and later had become
a hotel clerk. He had married at 28; there had been
two miscarriages, at three months and six weeks respectively;
one child was stillborn; four children were living.
The patient was not very alcoholic. The patient’s wife
thought the symptoms had been coming on since his forty-first
year when irritability set in, but he was not discharged
from work until about a year since. He was taken back again
after his wife’s pleas, and remained at work about three
38months; but for ten months before admission to the hospital,
Dixon had done practically nothing, had shown a marked
memory failure and speech defect, at the same time claiming
to be a person capable of doing and accomplishing everything.
He had become careless of his personal appearance, collected
a drawer-full of stumps of cigars, carried lumps of coal in his
pocket, laughed causelessly, and spat on the carpet.
We here deal with a case of unknown duration from the
initial infection, but with symptoms lasting about three
years and three months. Aside from the cause of death
(empyema of left pleural cavity associated with acute hemorrhagic
splenitis, acute ileitis, and bronchial lymphnoditis),
the body showed a number of other lesions outside the nervous
system. There was the usual sclerosis of the aorta, though
perhaps less marked than usual. There was a curious acute
arteritis with fusiform dilatation of the arteria profunda
femoris, with an edema of the thigh muscles and blebs of the
overlying skin. There were also multiple chronic caseating
lesions of the liver, without evidence of fibrosis. The explanation
of these liver lesions is not yet clear. There was a cloudy
swelling of the kidney.
The calvarium was dense and the dura mater thick and
adherent. There was a chronic leptomeningitis, which, however,
was rather unusual in being most marked in the posterior
cisterna and along the sulci of the cerebellar hemispheres.
There was a general cerebral sclerosis, with a question of
atrophy of the superior temporal gyri (suggesting the so-called
Lissauer’s paresis). There was a marked cerebellar sclerosis
with a consequent sclerosis (grossly palpable) of the commissural
fibres of the pons. There was a generalized slight spinal
sclerosis. As a fair sample of the variety of head findings in
paretic neurosyphilis, the details of the head examination are
presented.
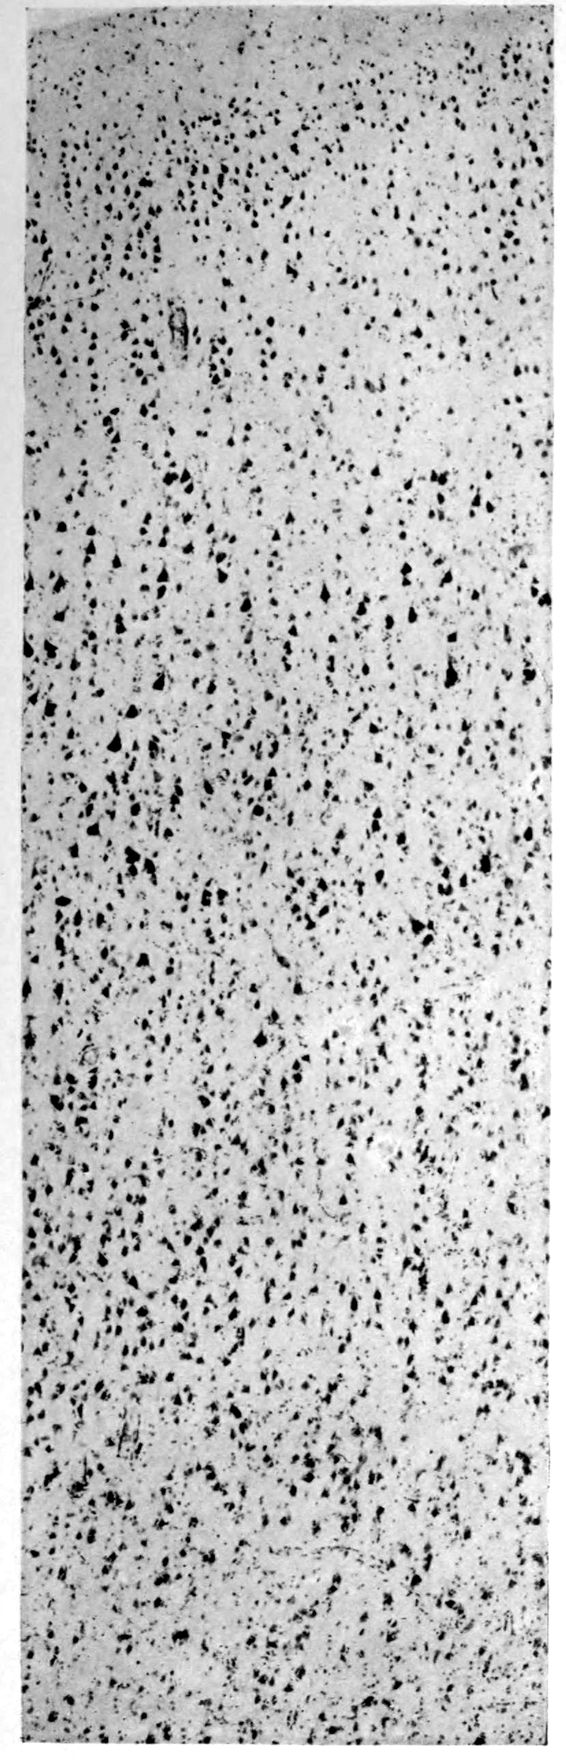
A. Normal postcentral cortex. (Compare B.)
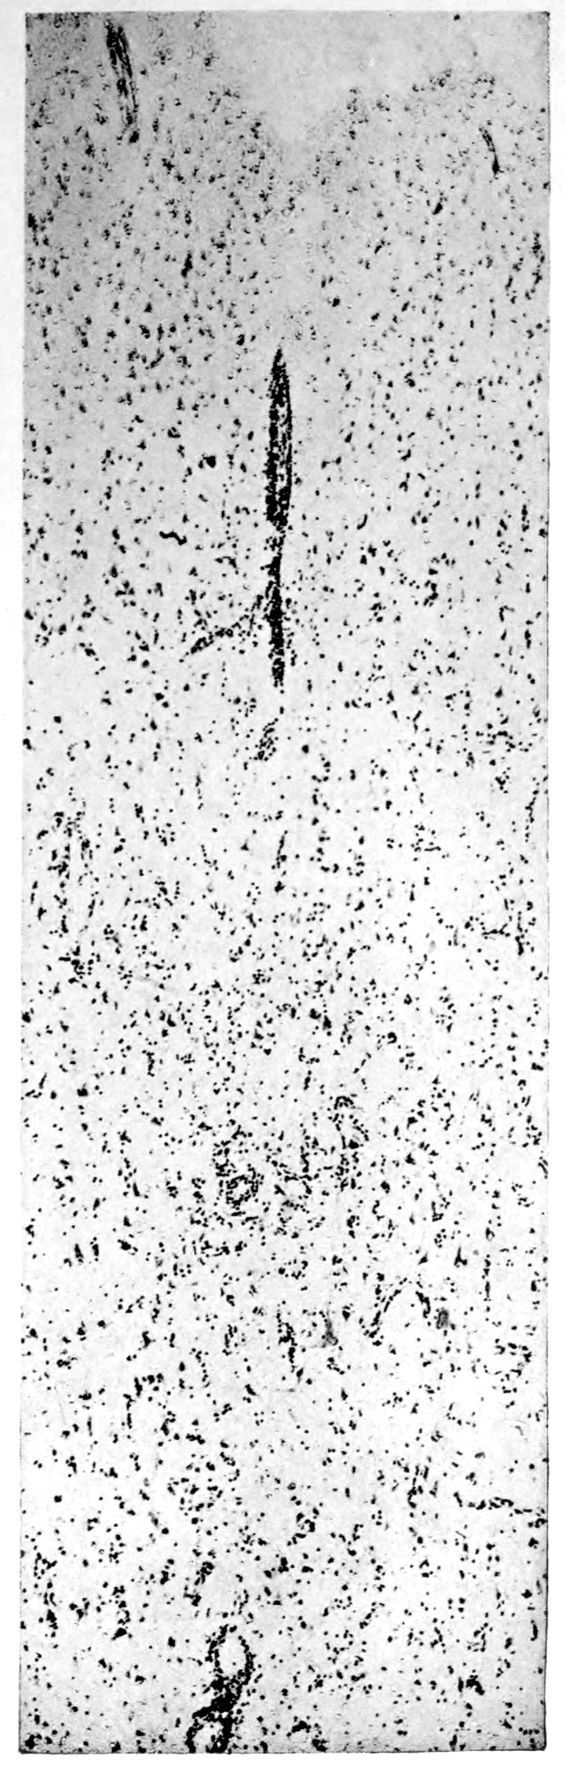
B. Nerve cell losses. Perivascular deposits of mononuclear cells, amongst which are numerous plasma cells. Note decrease in number of nerve cells. Note irregular disposition of nerve cells. From paretic neurosyphilis.
39Crown bald, with a slight fuzzy growth of short hairs.
Scalp slightly adherent to calvarium; latter of usual
thickness but denser than normal. Dura adherent
to calvarium in region of vertex; dura not remarkable.
Sinuses normal. Arachnoid villi moderately developed.
Pia mater a trifle thickened and rather evenly throughout the cerebral portion. Linear sulcal markings are
remarkable for their absence. The wall of the cerebellomedullary
cisterna is thick and opaque. The most
prominent pial thickenings are over the cerebellum.
These are linear or may show feathery out-growths and
are seated over the sulci, particularly in the neighborhood
of the fissure and about the great cerebellar
notch. They correspond fairly well with the focal
variation in consistence of underlying tissues noted
below.
Brain weight, 1265 grams. Consistence somewhat
increased throughout and somewhat evenly increased.
The prefrontal region shows the maximal increase of
consistence but the remainder of the frontal region and
corresponding occipital region are much firmer than
normal. The two superior temporal gyri appear to be
firmer than adjacent gyri and are possibly slightly
diminished in superficial diameter. The hippocampal
gyri are fairly firm. The substance on section is a
trifle more moist than normal. The gray and white
matter cut quite evenly. Diminution in depth of gray
matter, if existent, could not be demonstrated. The
ventricles show a moderate sanding throughout, best
marked in the fourth ventricle. The basal ganglia are
not remarkable except for the development of numerous
dilated perivascular spaces about the lenticulostriate
vessels. The pons is atrophic, but more so on the
right side. The pons, like the prefrontal cortex, shows
on section a distinct increase of consistence immediately
beneath the pia mater. The white bands of the
pons on section are distinctly firmer than the intervening
substance. The olives are of equal consistence.
Weight of cerebellum, pons, and medulla, 155 grams.
The cerebellum shows an obvious atrophic and gliotic
process of a symmetrical character. The superior
surface, including both vermis and hemispheres, shows
a consistence above normal and general reduction of
the depth measured from the white matter. The reduction
in depth gives rise to a visible depression as
compared with tissue posterior to the postclival sulci.
The lobus cacuminis, though slightly raised from the
surrounding lobes, is equally firm, if not firmer. The
superior and inferior surfaces show practically an equal
increase of consistence. The dentate nuclei are not
especially increased in consistence. The flocculi are
reduced in size about one-third.
40There was slight universal increase in consistence of
spinal cord, best marked in lumbar region.
Microscopic findings are here presented merely in
sufficient detail to establish the diagnosis. The left
superior frontal gyrus shows extensive and somewhat
irregular cellular and fibrillar gliosis of the plexiform
layer, together with an increase of thickened vessels
having lymphocytes and plasma cells in their sheaths.
The perivascular infiltrations are most extensive in
the lower layers of the cortex. The lamination is in
places thoroughly obscured, except that representatives
of the layer of large external pyramids are almost
always demonstrable.
The layer of medium-sized pyramids has undergone
more numerical loss of elements than have the other
layers.
Gliosis of white matter.
Specimens from the cerebellum show a destructive
process of great severity, but a little irregular in extent,
affecting chiefly the Purkinje cell belt. The Purkinje
cells are often absent throughout one side of a given
lamina, and there has ensued a dense accumulation of
neuroglia cells along a former Purkinje cell belt, together
with a considerable gliosis of the molecular layer.
Considerable gliosis of the white matter, both diffuse
and perivascular in distribution.
Perivascular plasma cell infiltrations as in cerebrum,
but largely meningeal or in the white matter.
Sections from the corpora striata demonstrate a mild
and early granular ependymitis, considerable subependymal
gliosis of cellular type, considerable perivascular
gliosis in the white portions of the tissue, and a moderate
infiltration of perivascular sheaths with pigmented
cells, lymphocytes, and plasma cells. There is little
evidence of alteration in the nerve cells. Some are
unevenly pigmented.
Summary: We here present a case with numerous and
widespread neurosyphilitic lesions. However, the gross cerebral
vascular complications of Case 1 (Alice Morton) and of
Case 2 (Francis Garfield) are notably absent in James Dixon.
Rather atypical (there seems to be always something atypical
in cases of neurosyphilis!) are the liver lesions and arteritis of
the leg, atypical, that is to say, for Paretic Neurosyphilis.
Highly typical of paretic neurosyphilis and almost constant
therein is the aortic sclerosis.

Apparent new formation of small blood vessel. Photographed by Dr. A. M. Barrett.
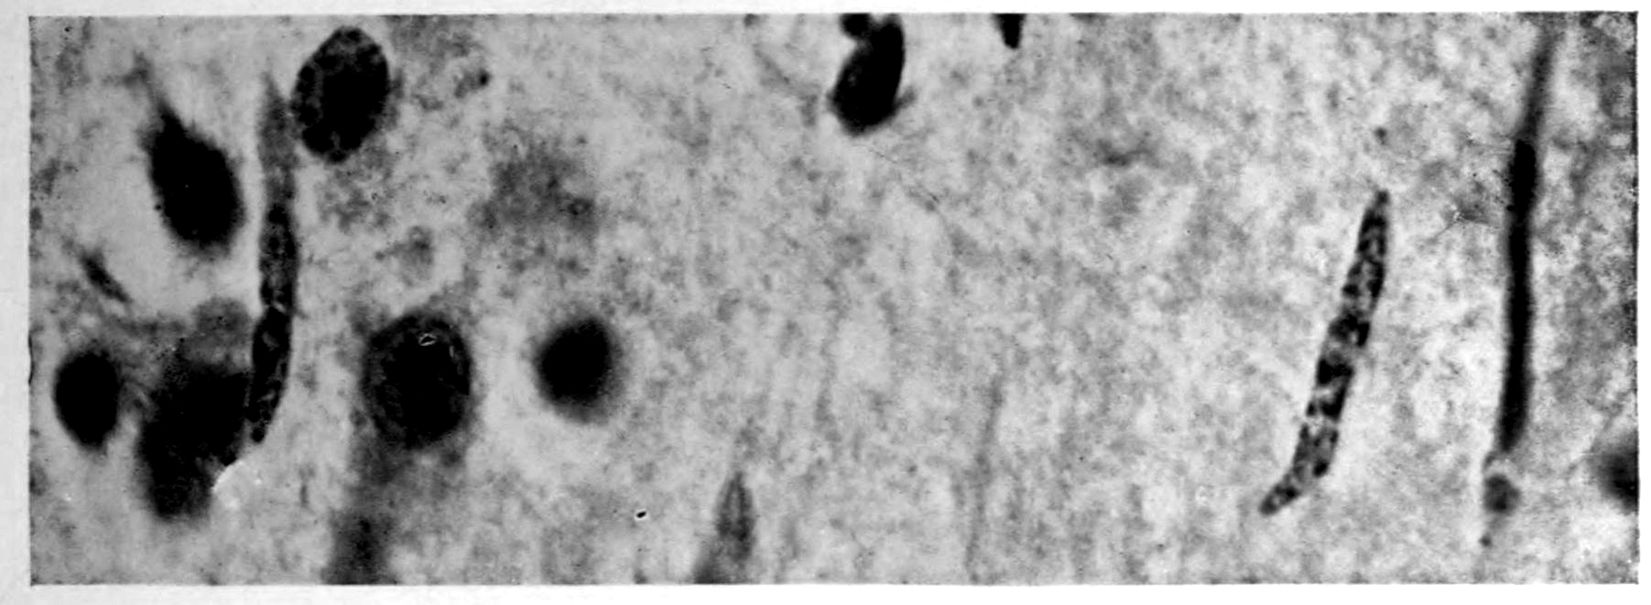
Rod cells (Stäbchenzellen) in paretic neurosyphilis. Photographed by Dr. A. M. Barrett.
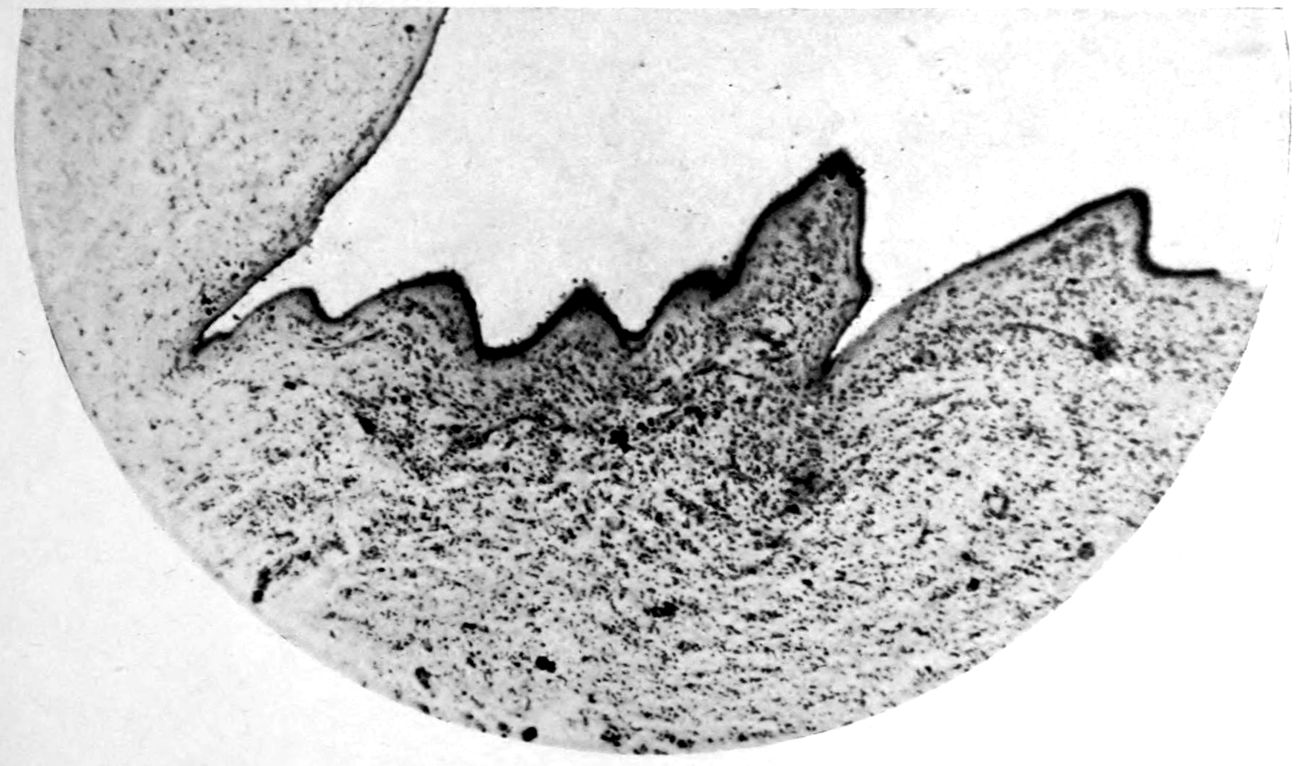
Granular ependymitis—microscopic appearance of a marked example of “sanding” of ventricle.
41Characteristic and constant in paretic neurosyphilis is the
Plasmocytosis and Lymphocytosis, Perivascular in distribution
about small cortical vessels. There is also a characteristic
(though characteristically less prominent) Plasmocytosis
and Lymphocytosis, Meningeal in distribution. The pleocytosis
of the spinal fluid, almost constant though variable in
amount in life, is an indicator of the meningeal picture and
less directly of the parenchymatous picture.
Granular Ependymitis (“sanding” of ventricle floors) is
characteristic and may be regarded as part of the parenchymatous
picture. This ependymitis is an indicator how
chemical changes could be readily produced at least in the
ventricular fluids, since the limiting membranes of the nerve
tissue are here subject to multiple breaks. The “sanding”
is a neuroglia reaction to these multiple small breaks (Weigert’s
explanation).
Parenchymatous losses have led to Atrophy and Sclerosis,
of very varying extent in different parts of the encephalon.
The atrophy is characteristic in paretic neurosyphilis, but by
no means constant. Numerous cases have come to autopsy
without clearly defined gross atrophy. Sclerosis is also characteristic
and even more frequent than atrophy, doubtless
because sclerosis represents an earlier phase of a process
eventuating in gross atrophy.
A Tabetiform Picture characterizes the spinal cord, but
in this case the tabetic clinical picture did not precede the
paretic clinical picture. We are consequently to regard the
tabetic spinal process as incidental and on all fours with
the Cerebellar and Pontine Atrophy.
42
VASCULAR NEUROSYPHILIS (“syphilitic cerebral
thrombosis”). Autopsy.
Case 4. James Pierce was an almshouse transfer to the
Danvers Hospital in his fiftieth year. He died three years
later. The accompanying brain pictures demonstrate so
extensive a lesion of the left hemisphere that it is of great
interest to determine if possible the genesis and course of his
disease. It appears that syphilis had been acquired somewhere
about the age of 38 or 40, so that the total duration of
the process was between 13 and 15 years. In Pierce’s forty-third
or forty-fourth year, he had a shock while walking in
the streets of his native city, whereupon he was subsequently
transferred to the Danvers Hospital, whose data have been
summed up as follows (we are obliged to Dr. Charles T.
Ryder for these data):
Neurological examination: Neuromuscular condition:
Barely able to walk or stand without assistance;
hemiplegia of right side; swings foot out and drags toe
out and around in attempting to walk. Right hand
held by side, flexed at right angle; fingers contracted
and thumb thrown across palm. Can lift arm from
side; practically no movements of forearms or fingers;
atrophy of deltoid, arm, forearm, and hand. Muscular
movements of left upper extremities fairly well
performed; good strength.
Cranial nerves: Refuses to respond to any tests to
determine hearing or vision, but evidently hears what is
said to him, and in his movements gives no evidence of
deafness. Right corner of mouth droops; tongue protrudes
straight.
Reflexes: Pupils dilated; margins irregular; left
pupil larger; they vary in size but it is impossible to
determine whether the variation is due to light or accommodation
reflex. Reflexes of right side extremely
exaggerated throughout; there is little ankle clonus;
Babinski is not obtained, patient holding his toes in
flexed position in resisting attempts to elicit reflexes.
43Sensations: Reaction to pain stimuli on either side.
Evidently some anesthesia on right side, but pressure
is apparently very painful. There is considerable
spasticity of limbs on right side on passive motion.
Too demented to make accurate tests.
The above examination was made on May 6, 1904.
On May 20th the record states:
There is almost complete sensory aphasia with word-deafness; some paraphasic circumlocution. Many of
his words are very well enunciated but have no meaning.
Is apparently unable to recognize objects or their uses.
Brother stated that he was always supposed not to be
over bright. Physician’s certificate states that he is
epileptic, averaging two attacks per week. On the
15th of May he had a general convulsion; was unconscious
for half an hour, and dull and drowsy for two
hours afterwards. On the 19th, he had a similar attack
in the afternoon, the convulsion lasting a minute, and
he was stuporous for an hour.
On November 8th he had a severe epileptic convulsion.
His body was curled up to the right. The
convulsive seizure lasted for two minutes and was
followed by complete unconsciousness for an hour,
when the patient roused and appeared as usual in a few
minutes. From that time to December 15th he had
five epileptic convulsions; he was much more feeble,
and unable to help himself as much as formerly.
Nov. 7, 1905: Patient has had occasional convulsions
since last note, but none during the last three
months. He is confined to bed, has become very much
demented, and shows very marked speech defect, so
that he is almost unintelligible. He understands only
the simplest directions. Legs are considerably contracted
and knees are flexed. Arm and hand on the right
are paralyzed and show some atrophic changes; partially
flexed. Left elbow jerk is very lively. On
May 23, 1906 he was reported as having Achilles on
right side only, and Babinski on right side. He died
January 5, 1907.
The autopsy findings were as follows:
Head: Calvarium of moderate thickness; diploë
present; dura slightly adherent over bregmatic region.
Longitudinal sinus contains cruor clot. Dura is somewhat
thickened and slightly more opaque than normal.
Pacchionian granulations, small but fairly numerous.
Pia contains throughout a considerable excess of clear
44serous fluid. The convolutions in general are of good
breadth and proportion. There is an atrophic area
roughly circular in outline and about 2 cm. in diameter
in the posterior part of the right third frontal convolution
corresponding to Broca’s area on the opposite
hemisphere. The space thus formed is filled with edema
held by the pia. On the left side is a similar subpial
collection which covers the site of the posterior portions
of all of the third frontal convolutions, parts of the
lower end of the precentral convolution, and the whole
of the first temporal convolution, which have disappeared
entirely. The basal vessels show slight changes.
Cerebellum and basal ganglia are grossly normal.
The spinal membranes are negative. The regions of
the pyramidal tracts in the cord are firm, project
slightly from surface of section, and are china white.
Summary: Here is a picture made up almost purely of
Vascular Neurosyphilis, with Secondary Spinal (Pyramidal
Tract) Changes. Doubtless the genesis of this
picture is allied to that of Case 1 (Alice Morton) and to that
of the terminal vascular complications in a tabetic, Case 2
(Francis Garfield).
The absence of meningeal and parenchymatous (i.e., outside
the region of necrosis produced by the vascular disease)
lesions is characteristic of an important group of neurosyphilitic
diseases. It is clear that the case, although one of
extensive lesions, is not one of diffuse lesions in the sense of
Case 1 (Alice Morton).
The spinal fluid picture in life may nevertheless show (as
other cases amply demonstrate) a certain amount of lymphocytosis
and possibly plasmocytosis, together with a variety
of other changes. Treatment might be expected to keep
down these associated changes, although obviously the effects
of the necrosis are final and definite. Franz in Washington
has succeeded in “reeducating” some of these hemiplegics,
employing lower mechanisms of the nervous system.
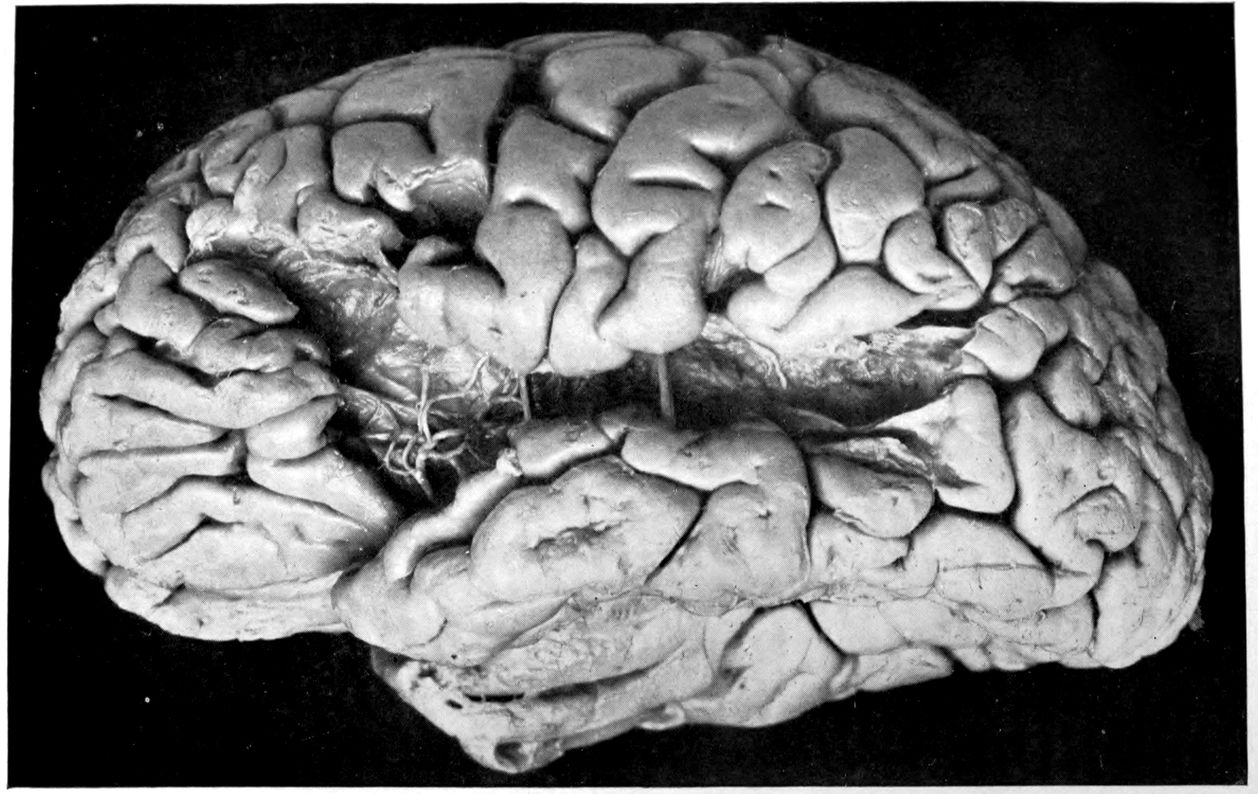
Vascular neurosyphilis—effects of syphilitic thrombosis of Sylvian artery 10 years before death. (Case 4.)
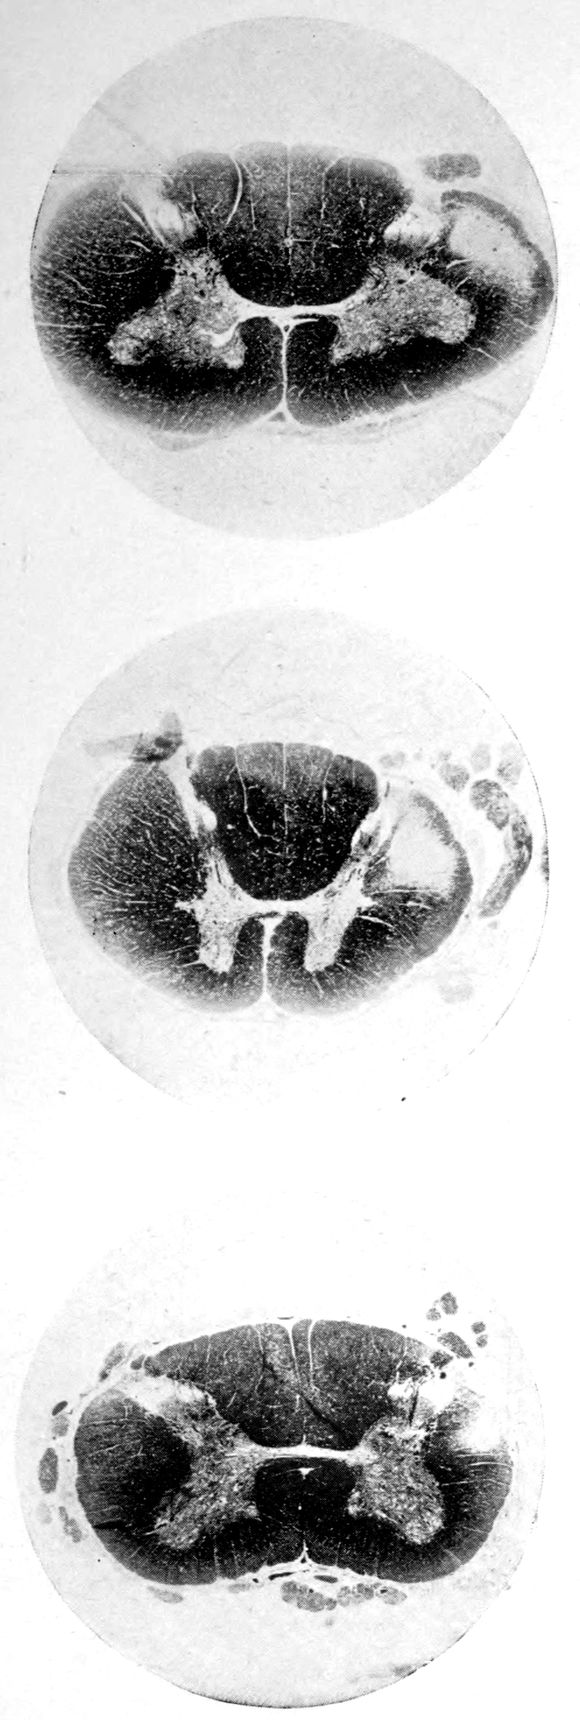
Case 4. (See previous figure for brain lesion.) Three levels of the spinal cord showing unilateral pyramidal tract sclerosis, 10 years after cerebral thrombosis.
45
JUVENILE PARETIC NEUROSYPHILIS (“juvenile
paresis”). Autopsy.
Case 5. John Lawrence was an under-sized negro, who
came under hospital observation when he was 23 years of
age. There was some evidence that the patient’s father was
a neurosyphilitic although accurate data were out of the
question. At all events, John had Hutchinsonian teeth, a forward
bowing of the tibiae, and Argyll-Robertson pupils.
These findings together with a history of backwardness at
school seem to stamp the diagnosis. It seems that there had
been a change for the worse from the age of 18, though the
boy had been able to sell newspapers and black shoes up to
within a year of his arrival at the hospital. During the last
months of his life, he showed a general incoördination, with
false movements suggesting those of a drunken person. There
were numerous tremors, the glance was shifting, and there
was a tendency to nystagmus. Some of these phenomena
(taking into account that the Hutchinsonian teeth were not
entirely typical and there was even at times some doubt as
to whether the pupils were actually stiff) led to a question of
the diagnosis multiple sclerosis.
There was, however, little doubt that the case was one of
juvenile paresis. Among the symptoms found at various
times in this case are the following: disorientation for time,
place and persons, confusion, with coarsely irrelevant replies to
questions, ill-defined and transitory delusions of persecution,
auditory, tactile, and visual hallucinations, and defective
memory.
Early in life, the patient had had a habit of falling asleep
in school hours, and had experienced a number of falls at
various times. During an attack of measles he had had a
number of spasms, each of which lasted ten minutes or more.
The autopsy showed death to be due to an early bronchial
pneumonia. The thymus was persistent, measuring 3 × 2 ×
.5 cm. The marrow of the femur was red.
46There was a moderate degree of sclerosis of the aorta confined
to a few plaques in the arch (not a characteristic syphilitic
scarring of the aorta). The spleen was small and had a
thickened capsule.
The majority of the lesions, however, were in the nervous
system, and the following description is taken from the routine
hospital records to exemplify the findings in a fairly characteristic
case of Juvenile Paresis.
Head: Scalp closely adherent to calvarium. Calvarium
heavy without diploë. Dura adherent to calvarium
in bregmatic region. Sinuses contain liquid
blood. Arachnoidal villi in considerable quantity. Pia
mater contains considerable clear fluid and shows diffuse
haziness and focal thickenings. The diffuse haziness
is almost universal and is best marked over the superior
surface of the cerebellum. The focal thickenings are
of general distribution over the veins of the sulci on the
superior surface of the brim and are heaped up to form
considerable linear mounds near the region of the arachnoidal
villi. The superior surface of the cerebellum is
traversed by similar linear mounds of fibrous tissue
running at an angle to the laminæ. There is no notable
increase of fibrous tissue at the base.
Brain: Weight 965 grams. The sulcation is roughly
symmetrical except in the occipital poles where there is
unusually rich and complex but shallow sulcation. The
cortical substance is everywhere firmer than normal,
but the sulci fail to flare notably. In a few places there
is a focal increase of consistence of still greater degree
with apparent local hypertrophy (or gliosis with increase
of substance). These foci are in the right second
temporal gyrus (3 cm. in diameter) and in the left first
temporal gyrus (of same size but somewhat less firm)
and are of a whitish, waxen appearance, being visible
several feet away by reason of their color and apparent
encroachment upon the adjacent sulci. The foci are
sharply limited by the sulci laterally, but pale out
gradually before and behind.
The convolutions of the vertex show another type of
lesion. The tissue of the greater part of the vertex
resembles that of the flanks and base in being firmer
than normal and of a grayish pink color. Behind the
fissure of Rolando on the right side and behind the anterior
limits of the ascending frontal region on the left
47side the brain tissue of the vertex becomes suddenly
still firmer and of a yellowish gray color. This lesion
disappears gradually into the occipital microgyria behind
and the gyri gradually lose their yellowish tint.
The lesion fades away gradually so that it fails to involve
the temporal convolutions.
The cerebral tissue cuts firmly and smoothly. The
tissue of the frontal region is a little edematous. The
white matter is of a normal appearance. The ependyma
of all the ventricles is somewhat sanded. The fourth
ventricle is most affected.
The cerebellum is not edematous and is as firm as
the normal olivary bodies. The cerebellar hemispheres
are symmetrical and of a normal appearance, save that
the laminæ are slightly narrower than usual and very
compactly set. The color, where not obscured by the
haziness of the pia mater, is of a grayish pink somewhat
suggestive of freshly tanned shoe leather. The substance
cuts smoothly and firmly. The dentate nuclei are
unusually firm. The pons is small, but of the usual
color. Lower structures normal except the cord which
is small and shows curious deviations from the normal
markings. The posterior horns and gray commissure
are at many levels the only structures to preserve the
normal gray appearance, so that the H or butterfly
appearance is replaced by a crescent. At these levels,
traces of gray matter often stand out in the loci of the
anterior horns.
The important anatomical diagnoses in the nervous system
are as follows:
Atrophy of cerebrum, 965 grams (there is of course a
question whether we are not dealing with a degree of cerebral
hypoplasia).
Focal scleroses of cerebrum, suggesting the tuberous
scleroses of Bourneville.
Occipital microgyria.
Cerebral and cerebellar gliosis.
Chronic ependymitis.
Gliosis of the gray matter of the spinal cord.
Chronic diffuse and focal leptomeningitis.
The microscopic examination confirmed the diagnosis of
paresis. The hypertrophic nodules were of special interest.
48They were found to be overlain by a characteristic though
thin exudate of lymphocytes and plasma cells, together with
pigmented cells. The nodules appeared to be supplied with
an unusual number of vessels of small calibre, about which
were a few lymphocytes. The large vessels and those with
well developed adventitiæ were surrounded by more numerous
lymphocytes and by more focal accumulations of pigmented
cells. The cortex in the middle of a nodule had almost lost
its characteristic cortical layering. The cortex was here
reduced (specimen from temporal lobe) to about one-quarter
of its normal thickness, and was found to be composed largely
of expanded neuroglia cells and vascular tissue, with a few
nerve elements, small, shrunken, and dark-staining. The
destructive process appeared to have borne hardest on the
layer of internal large pyramids and the fusiform layer.
There was, however, nowhere any evidence of focal necrosis
such as ought to characterize a true gumma. The sections
stained by the Marchi method failed to show evidence of
fatty degeneration within the focus, although there was a
marked diffuse accumulation of fatty granulations along the
nerve fibres in the underlying white matter. A special study
of the cerebellar material was made by one of the authors.[4]
Occasional Purkinje cells showed the characteristic binucleate
condition, which has frequently been noted in
recent literature.
The cerebellum of this case was perhaps the most markedly
diseased of all portions of the nervous system. As noted, the
cerebellar tissue was exceedingly firm. How far the notable
incoördination of the case (he was observed on staff rounds
characteristically curled up in a heap, showing quite an unusual
degree of general incoördination) was due to the cerebellar
lesions, it is perhaps not possible to say.
Summary: John Lawrence, Juvenile Paretic Neurosyphilis,
is a foil to Case 3 (James Dixon), paretic neurosyphilis
due to acquired syphilis.
Both showed Cerebral Atrophy, but Lawrence the more
49markedly because of hypoplasia incidental to the congenital
origin of his condition.
Whereas Dixon gave little or no sign of stigmata, Lawrence
(besides being under-sized, having suspicious teeth, and
showing at autopsy a persistent thymus) showed a Hydromyelia
and curious trefoil shape to the spinal cord. Dixon
on the other hand had liver lesions and arterial lesions of the
leg.
The suggestion of Tuberous Sclerosis in Lawrence is not
found in Dixon; but we have not found it elsewhere. Bourneville
did not describe tuberous sclerosis as syphilitic.
Binucleate Purkinje cells emphasize the congenital source
of the lesions in Lawrence.
Plasmocytosis and Lymphocytosis, Perivascular, and (less
marked) Meningeal, are found in both the congenital and
the acquired cases, as also parenchymatous changes, both
nerve cell losses and gliosis. Both also show granular
ependymitis.
It is clear that, over and above the factors of destruction
evident in both Lawrence and Dixon, the congenital case,
Lawrence exhibits also the effects of arrest (in brief not
merely atrophy but also hypoplasia). Early treatment is,
therefore, theoretically indicated in the juvenile group, which
means early diagnosis. Early diagnosis and treatment are
still more to be recommended because these juvenile cases
progress often very slowly at first.
50
FOCAL BASILAR MENINGEAL NEUROSYPHILIS
(“syphilitic extraocular palsy,” plus other
symptoms). Autopsy.
Case 6. Flora Black, a housewife of 43 years, had been
tired out for a year but had been apparently in fair health.
She awoke one day with double vision due to a left internal
strabismus. The visual difficulty gradually passed away so
that five months after the sudden seizure she was apparently
quite well again. There was one exception: about three or
four months after the attack of diplopia, Mrs. Black had begun
to feel a kind of weakness in various parts of the face and there
were also fairly definite paresthesiæ. In the sixth month
after the initial attack, the patient began to be unable to
chew and was fain to support the lower jaw with a bandage
to aid in mastication. Deglutition was, however, quite unaffected
and there was never any regurgitation of food.
There were pains in the face, the forehead and the back of
the neck.
Upon physical examination at entrance to a general hospital,
no changes in the body at large were discoverable.
There was a slight edema of the ankles, otherwise no sign
of bodily disease.
Conditions in the head were as follows: The facial lines
were (notes by courtesy of Dr. E. W. Taylor) smoothed out;
both upper and lower eyelids and the corners of the mouth
drooped slightly and more markedly on the left side. There
was slight photophobia and considerable lachrymation.
The patient was unable to pucker forehead, nose or mouth.
The unsupported lower jaw fell and the patient was unable
to open the mouth widely. The movements of the tongue
were normally performed. Speech was mumbling. Sensations
of touch, heat and cold were preserved all over the
face except that the left cheek below the level of the mouth
yielded a less accurate registration of tactile sensations.
A hot test tube did not feel as hot in the lower left cheek as
51elsewhere. Quinine and sugar could not be tasted over the
left half of the tongue in front. Smell and hearing were also
diminished on the left side. It appeared that there was a
complete paralysis of the 5th and 7th nerves and a partial
paralysis of the 8th, 11th and 12th, as well as a defect in
smell.
The patient died suddenly, three weeks after admission,
running a slight temperature during her stay. The autopsy
showed (rather surprisingly) a double ovarian carcinoma
with metastases into the retroperitoneal glands. Both
kidneys were found to be riddled with nodules of carcinoma.
The pelvic veins were thrombosed and there was a complete
occlusion of the pulmonary artery. There was a riding embolus
in the foramen ovale and there was coronary embolism.
The striking nature of these complications and the interest
of the case neurologically would warrant its publication in
complete detail. We here present the case with utmost
brevity as an example of a Syphilitic Cranial Neuritis
by extension from the meninges.
The brain was in general without change but there was
a considerable exudate over the entire pontine region which
had involved several cranial nerves. The 5th nerves, especially
the left, showed gross effects of the inflammatory
lesion. There seems to be little or no doubt that this neuritis
was of syphilitic origin despite the complication of the case
with carcinoma of the ovary and despite the fact that the
case was observed and came to autopsy before the modern
methods of systematic diagnosis could be applied. It is the
best case available to us for the demonstration of a focal
cranial nerve lesion of the type characteristic of neurosyphilis.
We may well suppose that similar conditions would have been
found at various stages in the development of Case 1 (Alice
Morton). The pontine region of Case 1 was entirely free
from lymphocytic exudate at the time of the autopsy. Possibly
the clearing up of the pontine pia mater in Case 1 was
a therapeutic effect of the thorough treatment therein used.
Whether a case like Mrs. Black’s could be cured (aside from
the ovarian carcinoma and its complications) by the institution
of vigorous systematic treatment is a matter of doubt.
52Still, in a general way, these cases of focal syphilitic neuritis
are among the most favorable cases for treatment.
Summary: We present the case of Flora Black to emphasize
how slight in extent and theoretically curable neurosyphilis
may be. We fear that Case 1 (Alice Morton) may
present too unrelieved and pessimistic a picture. The
extensive vascular lesions and complications of Alice Morton,
of Case 2 (Francis Garfield), of Case 4 (James Pierce) arrest
attention by the incurability of their residual effects (if we
omit modern attempts at reeducation of lower arcs). On the
other hand the unrelenting progress to destruction of important
parenchymatous structures, as shown in the paretic
James Dixon (Case 3) and his juvenile replica John Lawrence
(Case 5), as well as in Alice Morton (Case 1) and the tabetic
Francis Garfield (Case 2), lead to a certain justifiable pessimism.
For it is only the meningeal and fine vascular infiltrations
of these cases that we can theoretically hope to
combat, probably by destroying the spirochetes in these
meningeal and perivascular loci. We seem theoretically less
able to stop the progress of the often highly systemic and
symmetrical, parenchymatous lesions of the tabetic and
paretic group.
The condition in Flora Black is clearly much more hopeful,
both being more focal and being almost purely meningeal
and therefore accessible to therapy.
The two cases which conclude our general survey of neurosyphilis
are also focal cases, one of gumma (Lecompte) and
one of focal dural lesion (Wyman).
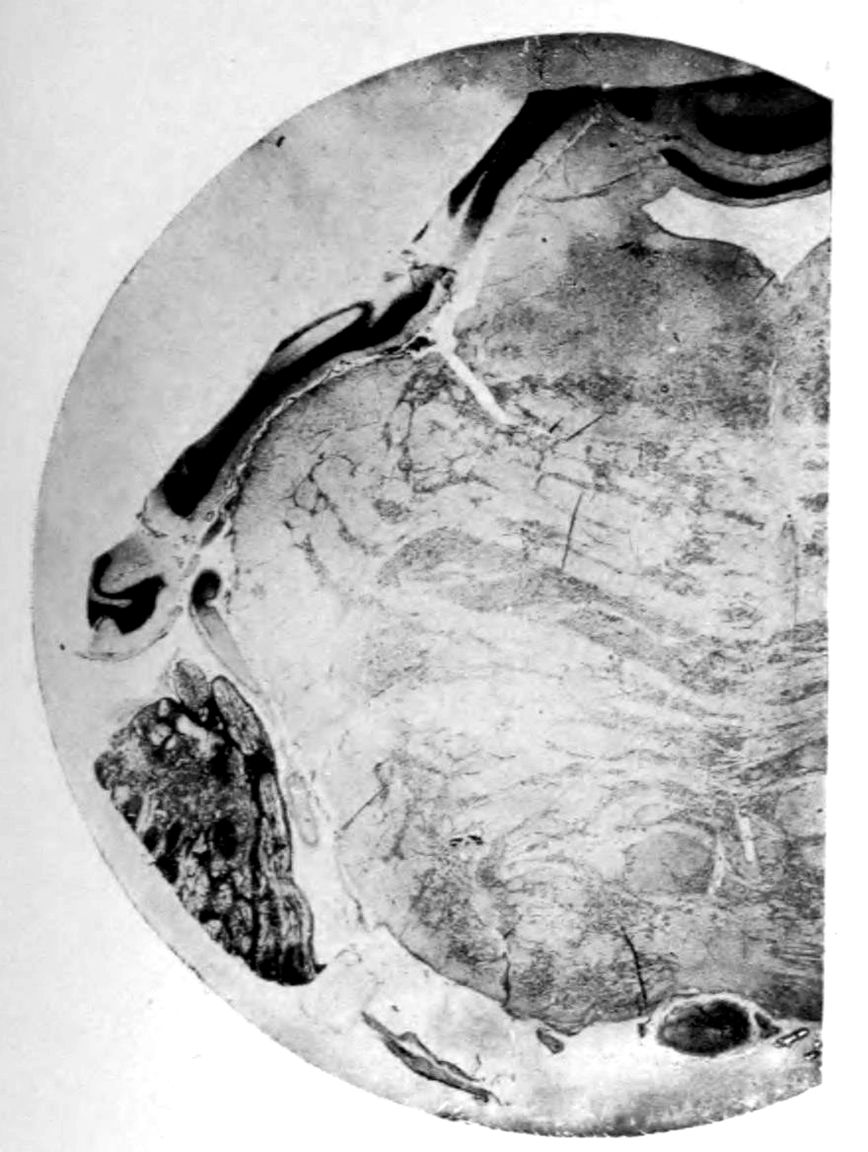
1. Pons, normal except for focal infiltration of left fifth nerve.
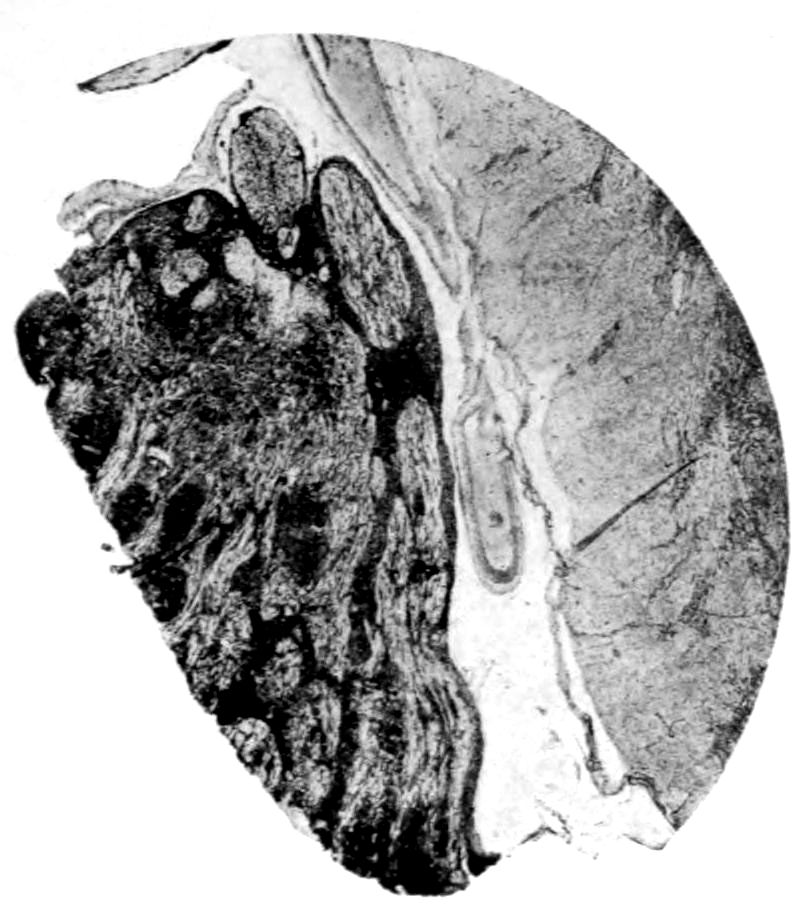
2. Higher power view of infiltrated left fifth nerve.
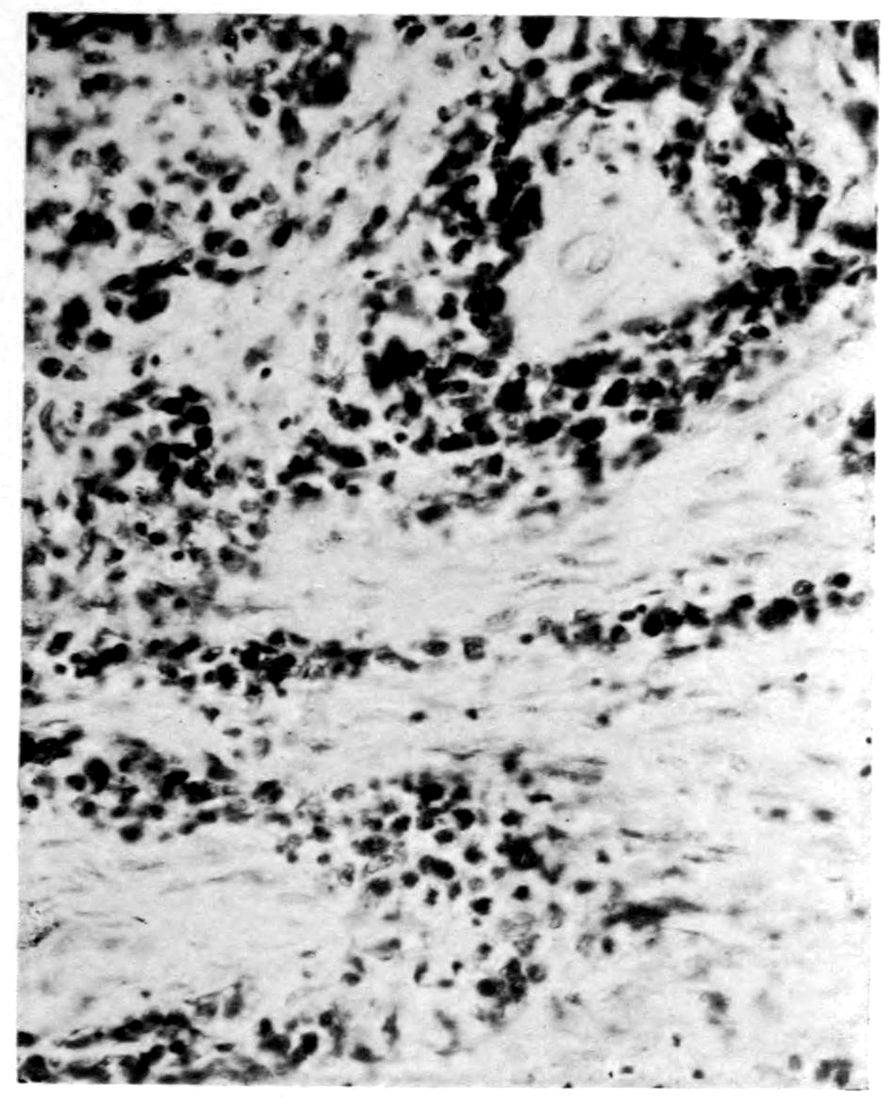
3. Detail of infiltrated left fifth nerve, showing: 1, diffuse infiltration with mononuclear cells; 2, perivascular infiltration; 3, strands of relatively unaffected nerve fibers.
Microscopic appearances in Case 6. Extraocular palsy (focal meningeal syphilis, especially
of left fifth nerve). Illustrates exquisite focality of the syphilitic process sometimes found,
as well as its unilaterality (giving rise to asymmetrical symptoms and signs). Process in
itself probably curable.
53
GUMMATOUS NEUROSYPHILIS (“gumma of
brain”). Autopsy.
Case 7. Mrs. Lecompte was a woman of middle age, who,
according to the history given by her son, had been entirely
well until her final illness, which began approximately two
years before admission to Danvers Hospital. The beginning
of her trouble seemed to be chiefly headaches, which would
last continuously for several days, or more than a week at a
time. These headaches lasted throughout the course of the
disease. In the morning, on arising, she would feel very dizzy,
but this would pass away during the day. She had had a
number of spells of unconsciousness, lasting about fifteen
minutes. In these attacks she would breathe heavily, there
was frothing at the mouth, twitching of the hands, and the
eyes would roll about. Her memory failed gradually, her disposition
changed and she became very irritable. Vomiting
occurred almost every day, and at times was of a projectile
character. She became hallucinated; the hallucinations were
chiefly of a visual nature.
About four months before admission to the hospital, after
one of her seizures, the entire right side was found to be completely
paralyzed, and she complained that it was numb.
At this time, she had difficulty with her speech. In a few
days, however, she was able to talk correctly again, and in a
week she was back at work, although the right side was weak
and awkward. She continued to grow worse, and then began
to have spells lasting several days, so that it became
necessary to have her placed in a hospital.
On admission to the hospital, aside from obesity, the general
viscera showed no points of special interest, and there was
no evidence of any new growth outside of the nervous system.
She was unsteady on her feet, standing with them wide apart.
The gait was quite ataxic; the whole right side was weaker
than the left and used more awkwardly. There was a paralysis
of the right side of the face; the right angle of the mouth
54drooped; the right eyelid could not be closed but remained
continuously open; nor could the right side of the forehead
be wrinkled. Vision and hearing were not affected. She
miscalled tastes and smells; whether this was due to aphasic
difficulties or to cranial nerve involvement could not be
divined. There seemed to be some difficulty in deglutition.
The knee-jerks were markedly exaggerated; slight clonus
was obtained but was not always present. Both pupils
reacted well to light and distance and consensually. Sensation
could not be readily tested. There was marked ataxia,
especially with the eyes closed. The speech was thick and
mumbling. The patient was unable to write or copy. Mentally
the patient was quite dull; at times, stuporous; when
aroused, was found to be entirely disoriented. Memory almost
entirely absent. In general she showed herself to be
very much confused.
She remained practically in this condition, even gaining in
weight, for the following two years, when suddenly one
morning, she had an epileptic seizure, vomited, coughed a
great deal, with bleeding from the mouth and ears, and died
in a few hours.
The symptoms in this case pointed to brain tumor. The
only inconsistent thing was the long-continued life,—four
years,—after the symptoms were observed. As she lived
before the W. R. and spinal fluid tests were known, no light
was gained in these ways. The post mortem examination
showed the patient had a Gumma of the Brain.
The summary of the anatomical diagnoses at autopsy was:
Decubitus.
Lymphadenitis of the mesenteric nodes.
Chronic fibrous peritonitis.
Chronic fibrous myocarditis.
Pulmonary hypostasis.
Thrombosis of vein in right adrenal, with hemorrhage.
Syphilitic leptomeningitis.
Gumma of left hemisphere.
Focal softenings in the pons.
The anatomical description of the head (Dr. A. M. Barrett)
is as follows:
55The sutures in the calvarium are well outlined;
diploë large in amount. The dura is diffusely but
lightly adherent to the calvarium; it is very dense,
especially over the left hemisphere. The meningeal
arteries are thickened but not atheromatous. The
sinuses contain a small amount of fluid blood and post mortem
clot. The inner surface shows nothing abnormal.
There is a great flattening of the convolutions of
the left hemisphere, which is not the case on the right
side. Over the convexity, the pia is thin and not abnormal
except for some slight adhesions between the
frontal lobes and the two lips of the Sylvian fissures.
The pia at the base over the cisterna, pons, and medulla
is thick, cloudy, and of a grayish gelatinous appearance.
It is so thick that it is easily removable in a large piece.
The surface of the left hemisphere is dry, and the
whole brain is flabby and bulges as if from internal
pressure. A section through the hemispheres at the
region of the optic chiasm shows a hard, firm area in the
left hemisphere deep down in the white substance. It
is about 2½ cm. in diameter, with a wavy border. The
central part is of a silver-gray gelatinous-like appearance,
with red spots and whitish streaks radiating from
the centre. In the pons on the right side, in a plane passing
through the posterior corpora quadrigemina, are two
pinhead size softenings among the pyramidal fibres.
The ependyma of the fourth ventricle is granular.
Microscopic examination of the tumor: The area
evidently contains several central necrotic foci surrounded
by zones of infiltration and proliferation, with
bordering areas of nervous tissue showing secondary
reactions. The necrotic area stains poorly. From
the edge there are projections of reddish homogeneous
bands, some intermixed with well-differentiated fibrillæ,
probably glia fibrils. The bordering zone is densely
infiltrated with lymphoid, plasma, and a few epithelial
cells. The nerve tissue outside of this zone is spongy
and infiltrated with lymphoid and plasma cells. There
are a few scattered, shrunken nerve cells. In this zone
and in the zone of infiltration near the necrotic area,
there are scattered cells resembling giant cells. There
are many obliterated vessels in the area, and other vessels
show many infiltrating lymphoid and plasma cells
in the walls. The examination of the specimen stained
by the methods for bacilli of tuberculosis are negative.
The growth is a classical gumma.
56
GUMMATOUS NEUROSYPHILIS (gumma of
spinal meninges, “meningitis hypertrophica cervicalis
of Charcot?”). Autopsy.
Case 8. John Wyman was first seen in his thirty-sixth
year by Dr. James J. Putnam. He denied syphilitic infection
and stated that the first symptoms had come four months
before. He had begun to notice a numbness of the fingers, at
first of the right hand and shortly thereafter of the left hand.
After a few weeks there had been difficulty in walking, and a
few weeks later headaches, especially on the right side, developed.
Two weeks before he was first seen medically, he
had begun to have a feeling of tightness or constriction in
his arms.
It appears that micturition had been impaired early,
that is to say, a few weeks after the initial sensory disorder
had begun. A catheter was used for a time and improvement
followed. Shortly before consultation retention of urine
developed again, this time associated with rectal incontinence.
The feet began to feel heavy and dead. Then
the legs began to be increasingly weak so that the patient
was almost bedridden. Vision appeared to be normal except
that reading was followed by fatigue. The speech
was also slow but the slowness could be attributed to fatigue.
Notes of Dr. Putnam’s physical examination are as follows:
The patient lay in bed on the left side, without motion, and
almost incapable of motion. The tongue was protruded,
and there was no paralysis of facial muscles, or of the eye
muscles (the right pupil had been reported to be slightly
larger than the left). There seemed to be a disinclination to
move the head, but with some effort it could be moved, and
without pain. The arms and hands were held rigidly in
median positions; many movements were possible, but all
were imperfect and of slight amplitude. The fingers were
flexed to a moderate degree, and could not easily be straightened,
and there was, in fact, a general rigidity of most of the
57muscles of the body below the neck, and even, in some degree,
of the neck. The immobility was so great that the general
impression made was almost that of a patient with fracture of
the spine in the cervical region. Even the breath, and especially
the inspiration, was imperfect. The legs were more
freely movable than the arms, but still the motions were very
stiff and awkward, and of slight amplitude; with effort the
whole leg could be lifted from the bed, and flexed or extended
with moderate force. The right leg was rather stronger than
the left, but the left hand and arm were stronger than the
right. The sensibility was almost absent over the hands
and lower part of the arms, and was impaired over the entire
head and neck, except the forehead, the middle part of the
face, and the nose. It is interesting to compare the conditions
of the sensibility here present with those seen in
cervical syringomyelia. The sensibility of the upper part
of the forehead was less good than of the lower part, and there
was slight impairment even over portions of the lower jaw.
The sensibility of the left (stronger) arm was rather more impaired
than that of the right arm, while on the contrary the
sensibility of the left leg was better than that of the right
leg, though the difference between them was not great. These
statements apply to sensory tests by contact, heat, cold, and
pricking. Knee-jerks were highly exaggerated, and likewise
the wrist-jerks. All forced attempts at movements were attended
by a high degree of muscular tremor, especially when
the patient was fatigued or under emotional strain. The
fingers especially were the seat of coarse tremor.
The remainder of this clinical description (courteously supplied
us by Dr. Putnam) may be quoted. A second examination
which included also a few facts not given in the
first examination was made on the following March 28, 1905.
This report says “the ends of the fingers became numb about
June 1, 1904. Work was given up on July 3, and at that
time the patient was walking very badly. No treatment was
used and no satisfactory diagnosis made. In the course of
July he improved somewhat, and during August he was able
to ride out a little (these spontaneous improvements are of
interest for the diagnosis). He went away from home for
58a short time, but from the time of his return, about the last
of September, he grew worse rapidly, and fell into the condition
above described, in which he was wholly unable to
help himself, even to turning in bed. At times he had a
great deal of pain in the neck and forehead. Antisyphilitic
treatment was recommended, and for a time potassium iodid
and other iodid preparations were given, but at first in
relatively small doses (grs. 75 daily). Under this treatment
the excretion of urine rose to four quarts daily as a maximum
though sometimes the quantity was not so great.”
Under this treatment the patient began soon to improve,
and continued doing somewhat better till about five months
later. He became able to walk downstairs and out of doors,
and regained considerable use of his hands. The quantity
of urine passed became greatly increased by the use of the
iodid.
About the middle of March he became worse again. A
careful examination of the sensibility showed that in general
the condition was much the same as that previously reported.
The iodid treatment, with perhaps some mercurial, was
resumed; the potassium iodid was given in doses which were
increased up to 850 grains daily, although this maximum dose
was taken only for about one week. This large quantity
gradually impaired the sense of taste for the time being, and
blurred his vision, but otherwise did him no harm. Under
this he improved, so that he became able to run more or
less, and went about freely, and attended to his business,
though still retaining some stiffness in his movements.
This improvement continued until about two years later,
when he again had a relapse, and was seen medically once
more. His condition at this time was still a pretty good one,
but the movements were stiff and awkward. The bin-iodid
of mercury was advised, which was taken in doses of 9
25 grain
daily. It will be remembered that this was long before the
days of salvarsan treatment.
This was toward the end of June, 1907. Contrary to expectation,
there was no material gain from this treatment,
and the patient died early in October, without being seen
again.
59The autopsy was limited to the nervous system and the
findings were as follows (Dr. A. R. Robertson):
Head: Hair abundant, fair, of fine texture and
rather curly. Scalp of medium thickness and strips
readily from calvarium. The latter appears normal
and upon removal is of about the normal thickness.
It lifts readily from the dura mater, except for the
numerous attachments of Pacchionian granulations.
Meninges: The dura is smooth, moderately injected
and shows no areas of thickening; it lifts readily from
the pia-arachnoid. The pia-arachnoid shows discrete
and in many places diffuse areas of opacity. There is a
moderate amount of subpial clear fluid and the vessels
are moderately injected. Over the anterior surface
of the medulla and lower portion of the pons and largely
confined to the right side there is a very marked thickening
of the pia-arachnoid to which the dura is densely
adherent. This thickening extends down anteriorly
and laterally on the right side over the upper part of the
cervical cord. The thickened meninges over the upper
part of the medulla completely surround the right
vertebral artery, shortly before it joins its fellow of the
opposite side to form the basilar. Dissection of the
arteries shows them to be patent and thin walled.
Over the cerebrum and cerebellum the pia-arachnoid
strips readily leaving a smooth surface. Section of
the cerebral cortex, basal nuclei, pons and cerebellum
show no gross lesions. The ventricles are moderately
distended with fluid. The ependyma contains numerous
small cysts. Section of the pons shows no
lesions of the nervous tissue, but very marked thickening
of the surrounding meninges as noted above.
Cord: Throughout the cervical and dorsal region
the dura is quite tensely distended with an abundance
of clear, light, straw-colored fluid. Upon snipping the
dura this fluid escapes with a small spurt, as if under
considerable pressure. The cord within, for the most
part, lies free, but over the upper three or four centimeters
of the cervical portion it is densely adherent to
the dura anteriorly and laterally on the right side.
Cross sections were made through the upper three or
four centimeters of the cord, and over this area the cord
is constricted by very marked thickening of all the
meninges. The meninges here average from one to
three millimeters in thickness. On the right side and
60somewhat anteriorly opposite the junction of the atlas
and axis there is a single nodular, firm mass which
on section shows a yellowish, firm center surrounded by
very dense, pearl-gray tissue. The demarcation between
the homogeneous yellowish centre and its surrounding
gray tissue is very sharp. This nodule
measures about 0.75 to 1 cm. in diameter. The adjacent
cord is deeply indented by it. Below this nodule there
is a translucent, grayish appearance of both posterior
sensory columns which extends downwards and diminishes
in intensity until it finally disappears in the
upper dorsal region. This same appearance is well
marked on the right outer margin of the upper cervical
cord corresponding to the crossed pyramidal tract, and
extends downwards diminishing in intensity until it
disappears about the mid-dorsal region. The left
pyramidal tract appears to be similarly but very
slightly involved; section of the lower dorsal cord entirely
negative. Microscopically, characteristic Gumma.
It is a question whether this case is one of the group described
in 1871 by Charcot under the name of pachymeningitis
cervicalis hypertrophica. Charcot did not regard his
new disease as syphilitic, and it is very probable that syphilis
is not responsible for all cases. Charcot, however, noted that
his new disease was not incurable: he noted that the resulting
paraplegia, although it might be very marked and
accompanied by flexion of the leg on the thigh and although
the paraplegia might have lasted a very long time, might
end in recovery. Charcot thought that surgical intervention
was necessary. He described three periods in the disease,
the first or neuralgic (pseudo-neuralgic) was characterized by
sharp pains in the neck and by the sensation of constriction
in the upper part of the thorax. The second phase of the
disease was, according to Charcot, the paralytic phase, in
which a cervical paraplegia accompanied by muscular atrophy
developed. Sometimes cases were found to remain in this
paralytic phase and even to end spontaneously in cure. If
the muscular atrophy was degenerative, then the atrophy
was never replaced; but, according to Charcot, some cases of
atrophy were simple and accordingly curable. If, however,
61the spinal cord itself became involved in the meningeal
inflammation, then phenomena of transverse myelitis set in
with a spastic paraplegia and involvement of the bladder and
rectum. Muscular atrophy never developed in the legs, at
least in typical cases.
Among the causes of this condition the following have
been mentioned: cold, overexertion, alcoholism, tuberculosis
and syphilis. Syphilis undoubtedly plays the major
part. Even before the days of the W. R., observers, among
whom may be mentioned Dejerine-Tinel and Pförringer,
discovered syphilis in nearly all sufferers from pachymeningitis
cervicalis hypertrophica.
It should be differentiated from caries of the spine and
cord and meningeal tumors. The spinal fluid examination
makes this somewhat easy.
Antisyphilitic remedies are indicated, and should be tried
even when the etiology is obscure, if only as a therapeutic
test.
62
But what have been thy answers? What but dark,
Ambiguous, and with double sense deluding,
Which they who asked have seldom understood,
And, not well understood, as well not known?
Paradise Regained, Book I, lines 434–437
63
PARETIC NEUROSYPHILIS (“general paresis”)
sometimes persistently receives the diagnosis
NEURASTHENIA simply through omission to
apply approved diagnostic methods.
Case 9. Greeley Harrison, a man of 46, certainly looked
like a neurasthenic. He wanted aid for nervous indigestion
of years’ standing, headache, insomnia, nervousness, failing
memory, and deafness. He volunteered, in fact, that he had
neurasthenia, and that he had been treated for this by hypophosphites.
During the practically negative physical examination, Harrison
complained of headache and throbbing in the head,
and during examination of the abdomen felt much nauseated
and proceeded to vomit rather persistently. There were
hemorrhoids.
Neurological examination showed that the left pupil was
smaller than the right, was irregular, failed to react consensually,
and reacted very slowly to direct light. For the
rest, however, the neurological examination was negative.
On account of the nausea and vomiting, special examination
of the gastric contents was made, but nothing abnormal
was found.
Mentally, it was rather striking that the patient’s memory
was quite inaccurate both for remote and for recent events.
His school knowledge was very meagre. As for delusions,
the only approximation thereto was the patient’s continually
dwelling upon his bodily symptoms. Emotionally, he varied
between depression and a sanguine attitude.
64Although there was no symptom directly suggesting syphilis
in the Harrison case, the slightly abnormal pupillary
reactions and the amnesia warranted the suspicion of syphilis.
The blood and spinal fluid both proved positive to the W. R.;
the gold sol reaction was of the “paretic” type; there were
18 cells per cmm.; there was considerable globulin, and an
excess of albumin. On the whole, therefore, we felt entitled
to make the diagnosis General Paresis. Why should
not a careful observer have considered syphilis seriously?
Yet in our experience such cases are frequently diagnosticated
neurasthenia, thus entailing dangerous delay in treatment
(in this case, five years’ delay).
Going over the history of the case with still greater detail,
we learned that for a number of years past, there had been
symptoms of a neurological nature. For instance, five years
before, at the age of 41, the patient had been apparently overcome
when working near a stove, and went upstairs talking
incoherently, but recovered shortly. Thereafter, such spells
occurred almost every month; later, more frequently; still
later, the attacks were associated with unconsciousness and
amnesia. Occasionally preceding the attack there would be
twitching of the mouth, jerking of the arms, and incoherent
talk. Throughout these last five years, in point of fact, the
patient had been unable to do regular work, had been given
to much complaining, and had been far less efficient than
formerly. In short, it would seem that, with the improved
technique now in the possession of medical science for the
diagnosis of general paresis, cases like that of Harrison will be
diagnosticated earlier and earlier.
1. How typical is the insidious onset of symptoms in the
case of Harrison? The onset of symptoms in neurosyphilis
is ordinarily considered to be sudden, and this
statement is generally true despite the fact that after
the diagnosis is established a number of mild prodromal
symptoms can be remembered by the relatives.
However, some cases, of which Harrison is an example,
have an exceedingly insidious onset without sudden access
of striking symptoms. Joffroy and Mignot remark
that with the improvement of clinical methods,
the course of paretic neurosyphilis must now be stated
65to take some six or seven years for completion. In
point of fact, there were early episodic symptoms
(seizures almost monthly) which should not have escaped
medical attention. They did escape medical
attention, however, and Harrison was wont to say
“Why wasn’t I told that my disease was syphilis five
years ago?”
2. Is there such a disease as syphilitic neurasthenia? According
to Kraepelin, syphilitic neurasthenia has been
described as occurring shortly after infection and in
the first stages of syphilis. There are milder and
severer forms; the milder forms show discomfort, difficulty
in thinking, irritability, insomnia, cephalic pressure,
indefinite variable, uncomfortable sensations, and
pains. The severer cases acquire anxiety, more pronounced
emotional disorder, dizziness, disorder of
consciousness, difficulty in finding the right word,
transient palsies, pronounced sensory disorders, nausea,
and increase of temperature. Kraepelin is in doubt
whether there is any definite clinical picture of this sort,
and whether there is any causal relation between the
syphilitic infection and such symptoms as those described.
If the effect of knowledge concerning infection
is a merely psychic effect, then it is improper to term
the neurasthenia in question a syphilitic neurasthenia.
For the relation of hysteria to the acquisition of syphilis,
see below the case of Alice Caperson (46). In point of
fact, modern work has shown even in the primary and
secondary stages of general syphilis more or less pronounced
neurosyphilitic phenomena in the shape of
the so-called meningitic irritation of French authors.
(Besides the case of Caperson (46), see the case of
Fitzgerald and the discussions under these cases.)
3. What is the relation of the early symptoms of this case
to the so-called preparesis of Dana? The case might
well have been an example of Dana’s preparesis. For
a discussion of this, see Case of William Twist (13).
4. What is the classical differential diagnosis between
paretic neurosyphilis and neurasthenia? The testing
of the blood by the W. R. is unconditionally necessary.
If the W. R. is negative, the diagnosis of paretic neurosyphilis
is extremely improbable. (It must be borne in
mind that a number of cases of paretic neurosyphilis
have been shown to have a negative W. R. in the serum,
and receive a proper diagnosis only after spinal fluid
examination.) Next to the serum W. R. stand the
66pupillary and aphasic symptoms. In the presence of
Argyll-Robertson pupil or even a slight speech defect,
the diagnosis of neurasthenia must certainly be made
with caution if at all. Kraepelin remarks: The sudden
occurrence of neurasthenic disorders in a male of
middle age without any evident cause therefor is always
suspicious. Yet it must be emphasized that a
complaint of occasional dizziness, slight speech defect,
tremor of tongue, and a moderate increase of tendon
reflexes do not possess any marked diagnostic significance.
Clear insight and understanding of the
nature of the disease phenomena, a persistent search
for recovery, reasonableness in conversation, progressive
improvement under appropriate treatment, speak for
neurasthenia.
Joffroy and Mignot differentiate what they call
preparetic neurasthenia from other neurasthenic states,
not only on the basis of its etiology but on the basis of
its symptoms. They also call attention to the fact that
neurasthenia, being a pure neurosis, develops either on
a manifestly hereditary basis or upon some physical
injury, weakening disease, or moral shock. The pure
neurotic suffers a great deal more than the patient who
is destined to become a victim of paresis. The character
change in neurasthenia does not amount to that
entire transformation of personality (even to the performance
of criminal acts) that we find in paretic
neurosyphilis; at the most, the neurasthenic shows
minor emotional disturbances and a certain pathological
egoism. The psychotherapeutic test also rather
readily dissipates many of the neurotic, hypochondriacal
fears and feelings. Although both pure neurasthenia
and the paretic pseudoneurasthenia are characterized
by sexual weakness, the sexual anæsthesia of the
preparetic is practically always preceded by a stage
of sexual over-excitement. These finer clinical indications,
however, fade into insignificance beside the
data that can and should be obtained from laboratory
tests.
5. How exceptional is such a case as that of Harrison? We
have in our experience seen many patients with a
similar course and configuration of symptoms, although
the majority of these cases in a community advanced
enough to provide easy access to a Wassermann laboratory
are now diagnosticated far earlier than was the
case of Harrison.
676. What attitude shall we take toward so-called syphilophobia?
It seems to us that resort to a serum W. R.
is indicated, both from the standpoint of the community
and still more importantly from the standpoint of the
patient. We are even inclined to suggest for a case of
persistent syphilophobia, when the serum W. R. has
proved negative, a lumbar puncture. Syphilophobia
must be considered, not as a syphilitic psychosis, but
as a phobia to be classified among the psychoneuroses.
It becomes a difficult question to decide at times
whether a patient who has had syphilis, has had a
considerable course of treatment and shows the symptoms
of a syphilophobiac should be further treated for
syphilis or merely for his phobia. We have seen recently
such a patient who gave a certain history of
syphilis and who was greatly disturbed lest he should
be developing paresis. This fear bothered him greatly.
Examination showed irregular pupils, but no other
signs of syphilis. The W. R. in blood and spinal fluid
was negative as were the other spinal fluid tests. It
was considered wise to treat him only for his phobia
and under this treatment he was given some relief.
68
PARETIC NEUROSYPHILIS (“general paresis”)
may look precisely like MANIC-DEPRESSIVE
PSYCHOSIS.
Case 10. The mental picture in Lyman Agnew, an architect,
58 years of age, was wholly characteristic of manic-depressive
psychosis. In the first place, there had been (at
55) a previous attack of depression, lasting a few months,
from which Agnew had completely recovered. He had
remained entirely well up to four months before consultation.
(Manic-depressive psychosis is, at least in a majority of
cases, hereditary. There had been mental disorder in one
maternal cousin, and mental impairment in the patient’s
mother some time before her death from cerebral hemorrhage.
There was no other report of mental disease in the family.)
It appears that in the interval between attacks, Agnew
had been working very hard and had been fairly successful
in paying off a mortgage on his house. A marked elation,
somewhat natural, followed this success and continued to an
abnormal degree. Agnew labored under considerable excitement,
was over-fussy, and at times showed a flight of
ideas. His mania or hypomania gradually diminished and
depression set in, in which depression he arrived for consultation.
He had marked ideas of self-accusation, was emotionally
unstable, wept much, and showed a characteristic
retardation of activities and unrest.
Physically, there was no neurological disorder. The patient
appeared rather under-nourished. The heart borders lay
2 cm. to the right and at 11½ cm. to the left of the mid-sternal
line. The aortic second sound was very loud. There
was a moderate radial arteriosclerosis. Systolic blood pressure
was 210, diastolic 155.
The high blood pressure suggested nephritis, possibly of
arteriosclerotic origin, but urine examination and blood-nitrogen
tests yielded no evidence of kidney disease. Moreover,
it is our experience that a manic-depressive psychosis
69in persons past middle life is not infrequently complicated
by high blood pressure. In point of fact, some authors insist
upon a relation between manic-depressive psychosis and
the arteriosclerosis which rather frequently sets in in this
disease.
Routine examination of the blood serum, however, yielded
a positive W. R. Following the approved rule of making an
examination of the spinal fluid in all mental cases having a
positive serum W. R., we proceeded to lumbar puncture. The
fluid was clear and contained 35 cells per cmm., the albumin
was in excess, and there was a positive globulin reaction.
The gold sol reaction was of the “paretic” type; the W. R.
was strongly positive.
On this basis, it seems worth while to consider the diagnosis
of General Paresis or that of some form of non-paretic
neurosyphilis. The former is the diagnosis which we
prefer.
1. What is the classical differential diagnosis between
manic-depressive psychosis and neurosyphilis? The laboratory
tests have naturally supplanted the older purely
clinical methods of differential diagnosis. The difficulties
lodge, in the first instance, in depressive states.
It would appear to be impossible on purely clinical
grounds in certain cases to tell the depression of neurosyphilis
from the depression of manic-depressive psychosis,
since the slightly greater interest in the outer
world taken by manic-depressive patients and their
greater responsiveness to diagnostic threats (suggestion
that patient is to be pinched or cut) are of no special
value in the individual case. Identical considerations
hold for the maniacal phases of manic-depressive psychosis,
for these maniacal phases may even develop delusions
(Kraepelin) of precisely the same nature as the
characteristic expansive delusions of the excited paretic.
2. If the clinical symptoms are insufficient in differential
diagnosis, are not the pupillary signs and the speech
defect of greater value? They are of value if present,
but as in the case of Agnew, the victim of neurosyphilis
may show no pupillary or speech disorder. Instances
are familiar, also, in which the pupillary and speech
signs are absent in very advanced cases of non-paretic
or even of paretic neurosyphilis.
703. Would not a circular course or recurrence of attacks
be decisive for manic-depressive psychosis? Paretic
neurosyphilis sometimes exhibits the same circular
or recurrent course. We conclude that neither the
clinical symptoms, the classical pupillary and speech
signs, nor the ups and downs of a particular disease, are
at all decisive as between manic-depressive psychosis
and paretic neurosyphilis. Resort must be had to
laboratory tests.
4. What is the significance of the high blood pressure in
paretic neurosyphilis? Work from our laboratory
(Southard and Canavan) has shown plasma cells in
the kidneys in 17 out of 30 paretics (56%), and in
16 of these 17 paretics with renal plasmocytosis, the
plasma cells were found in the periglomerular region.
What the relation of these findings may be to heightened
blood pressure is as yet unknown. The severe syphilitic
involvement of the aorta so characteristic in paretic
neurosyphilis, as in other forms, may possibly have a
bearing on blood pressure.
71
A POSITIVE SERUM WASSERMANN REACTION
associated with mental symptoms (even
with grandiosity) does NOT prove the EXISTENCE
OF PARETIC NEUROSYPHILIS (“general
paresis”).
Case 11. Juliette Lachine came to a general hospital
with pain in the right upper quadrant of the abdomen, wherein
was found an enlarged liver. This liver was regarded as
syphilitic on the ground that the patient had a positive serum
W. R. and that her two elder children were clearly suffering
from congenital syphilis. The liver mass was promptly reduced
by antisyphilitic treatment of the classical sort.
When, however, the patient was given an injection of salvarsan,
she shortly began to develop marked mental symptoms,
whereupon she was removed to the Psychopathic Hospital.
The mental picture at the Psychopathic Hospital was as
follows: Lack of orientation for time, marked distractibility
of attention, with a certain jumping from one subject to
another, delusions of a religious nature, claims of wonderful
powers possessed by the patient, moods variable, though as a
rule of a euphoric and elated nature, with laughing and singing.
The activity seemed to be of a mental rather than a
peripheral nature. The patient did not regard herself as
mentally abnormal. The liver was still 4 cm. below the costal
margin in the nipple line. We found the W. R. to be positive
in the serum but negative in the spinal fluid. In fact, the
spinal fluid was entirely negative.
So far as we are aware the picture presented by this case
is one of Manic-Depressive Psychosis. We regard the disease
as merely complicating the syphilis, although it is entirely
possible that some visceral condition incidental to the
syphilis might be proved (in a higher stage of psychiatric
science) to have produced the mania.
In any event, the patient quite recovered from her mental
symptoms in a month. She was then able to tell us of a
72previous attack of depression some 12 years previously,
namely, at the age of 26. It appears that she had at that time
been committed to a hospital for the insane.
1. In this case, in which the diagnosis of manic-depressive
psychosis and not paretic neurosyphilis was made,
are we sure that the symptoms that we term manic-depressive
psychosis were not actually produced by
syphilotoxins? In other words, in the absence of
spinal fluid signs of inflammation or chemical change,
might it not be possible for generalized syphilis outside
the nervous system to produce manic-depressive
symptoms? There is so far in the literature no experimental
or other evidence of syphilotoxins. The existence
of products and substances permitting the W. R.
and the gold sol reaction is not of course evidence of
syphilotoxins. Although there is no evidence of soluble
syphilotoxins, it is thought that in the so-called Järisch-Herxheimer
reaction (the intensification of clinical
symptoms after salvarsan injection) effects may be
due to the liberation of products from the killed bodies
of spirochetes. Such endotoxins are not here in
question.
2. Is visceral syphilis, such as gumma of the liver, able to
produce characteristic syphilitic reactions in the spinal
fluid? We have had an autopsied case in which there
was a “paretic” gold sol reaction of the fluid (though
without other signs). The autopsy showed gummata
of the liver. However, the finer anatomy of the nervous
system showed a mild but definite meningo-encephalitic
process, which was doubtless responsible
for the gold sol reaction.
3. What is the value of grandiose ideas? Ballet distinguishes
two groups of grandiose ideas: (a) ideas of self-satisfaction,
including ideas concerning extraordinary
capacity, strength, power, and wealth on the part
of the patient; and (b) ideas of ambition; the latter
being of a more exact, constant, uniform and systematizing
nature. The more vague and less systematized
ideas of self-satisfaction rest in a phase of contentedness
and optimism; the more definite ideas of pride and
ambition are responsible for striking transformations
of personality. General paresis shows, according to
Ballet, these ideas of self-satisfaction in their most
developed form. A certain variability, absurdity, incoherence,
73and contradictoriness characterize these
ideas and the patient has little or no insight into their
nature. When such ideas occur at the outset of the
disease, they naturally may be of medicolegal interest.
Cotard explains these ideas of megalomania on the part
of paretics on the ground that they are essentially motor
or will disorders and rest upon a sort of hyperbulia,
exhibiting itself in exuberant activity. Régis has
thought that the delusional generosity and liberality
of the paretic, and his willingness to lend his wealth
and talents to social progress, is helpful for diagnosis
when contrasted with the more personal egoism of the
victim of manic-depressive psychosis. The self-satisfaction
of the manic-depressive patient often does not
reach a delusional stage, but remains a mere feeling of
pathological well-being or euphoria. The maniacal
patient may compare himself with some great man but
he does not identify himself with him. It must be
remembered that these ideas of self-satisfaction occur
also in alcoholism, but according to Ballet they occur
only in the dementing phase of chronic alcoholism,
and have no special diagnostic value. They may be
a clinical stumbling-block for a time in the cases of
alcoholic pseudoparesis. As for the ideas of ambition
in which the patients believe themselves to be
princes, emperors, divine messengers, and the like, these
are less characteristic of paretic neurosyphilis than of
delusional psychoses of a non-syphilitic nature. At
all events, such ideas if definite, of long-standing,
and systematized by the patient to form a thorough-going
portion of his life, are not characteristic of neurosyphilis.
The victim of paretic neurosyphilis can as a
rule be persuaded out of his delusions, at least for
the time being. These distinctions, it must be added,
are hardly of value in the early cases of any of the
psychoses in question, and cannot be made as a rule in
either private or psychopathic hospital practice. Typical
examples of grandiosity, although not so frequent
as might be thought from textbooks, are always on display
in institutions for the chronic insane.
74
PARETIC NEUROSYPHILIS (“general paresis”)
may look precisely like DEMENTIA
PRAECOX. Autopsy.
Case 12. Henry Phillips remains a striking case in the
memory of those who knew him and his medical findings.
Phillips came to the hospital voluntarily at 42 years of age
from the bank where he worked as a clerk; he came at the
suggestion of his employer. It seems that he had been
annoying his associates because he had fallen into a habit of
continually scratching himself. Phillips was entirely sure
that he was the victim of what he called the “Scotch itch,”
and explained off-hand that this itch had been put upon him
by the Free Masons as a matter of revenge because he would
not join their order. He said once, for example: “At
times I feel like raising Hell; then I get a psychic intimation;
and then I get to using a foot-rule on my back and to slapping
my face.” He explained this psychic intimation as coming
from the order of Scottish Rites. Another example of talk is
as follows: “My father is a fighting man; that is part of it.
They mean to throw me down. I am through now trying
for membership in the Free Masons. They have good cause,
they must fight. They do not want me for some personal
matters. I can go just so far in agreeing and seconding their
advances, but in the end it fails. I have no strength nor
endurance.”
Aside from these delusions, there was little abnormality
to be found, though his recollection for minor events of the
immediate present was inaccurate. He was rather abnormally
impulsive, gesticulating a good deal while talking,
and was of the appearance that the laity call “nervous.”
It appears that he had always been peculiar, subject to
violent fits of temper, in which fits he might throw things at
other members of the family. He always had pronounced
likes and dislikes which he never concealed. He had never
had friends, had always been secretive; and he was often
75termed a great student. For some five years he had been
studying Japanese from time to time, associating himself
with a Japanese.
It never does to jump at the diagnosis dementia praecox.
However, the picture seemed characteristic enough for the
paranoid form of this disease. Physically, Phillips had
no particular abnormality; the knee-jerks were a little lively,
and the pupils reacted a little sluggishly. However, the
routine W. R. of the serum proved to be positive. Examination
of the spinal fluid was resorted to,—as in all cases
with a positive serum W. R.—and it also proved to be
positive and strongly so; the globulin and albumin were increased,
and there was a pleocytosis. A diagnosis of neurosyphilis
was hardly avoidable. Phillips later admitted a
chancre, which he claimed was located on the mucous membrane
of the cheek and acquired by using the same utensils
as his Japanese friend, which friend, he stated, had active
syphilis.
Antisyphilitic treatment of considerable intensiveness
was begun, with intravenous injections of salvarsan and
intraspinous injections of salvarsanized serum, but the
patient grew steadily worse. His mental symptoms became
more marked, although not especially characteristic of general
paresis. Neurologically, he did develop signs more suggestive
of general paresis, and 18 months later died.
The autopsy showed features of General Paresis. It is
not necessary to enter into the question of the details of histological
correlation at this time.
1. What conclusion can be drawn from lively knee-jerks?
Lively knee-jerks are of very little significance. Not
only certain neurosyphilitics but also a variety of neurotic
persons, victims of dementia praecox and hysteria,
are very prone to have active tendon reflexes. Of
course, extreme degrees of exaggeration are of importance,
and especially an association of the hyperreflexia
with the Babinski reaction, the Gordon, or Oppenheim
reflexes, ankle clonus, and the like.
2. Is there any special or differentiating factor in an extragenital
chancre as against a genital chancre? Probably
76this question should be answered in the negative.
Some have claimed that chancres draining by lymphatic
channels of the head are more likely to lead to
cerebral syphilis. This idea cannot be said to be
established.
3. Is there any significance in the story, if true, that
Phillips acquired his syphilis from a Mongolian? It
seems to be fairly well established that syphilis of the
nervous system is extremely rare in China and Japan,
whereas bone syphilis is very frequent there. It has
been held that this has to do (a) with strains of
spirochetes, (b) with the state of civilization, or (c)
with the degree of “syphilization.” Apparently when
a race is first infected with syphilis the lesions are
chiefly of the cutaneous and osseous systems; only in
later generations the vascular and nervous systems
suffer. However, involvement of the nervous systems
of Mongolians resident in this country is no rarity, a
point possibly in favor of the theory of special strains
affecting the nervous system as prevalent in western
countries. Little or nothing is known as to the effect
of transmission from one race to another, as from
Mongolian to Caucasian in Phillips’ story.
77
NEUROSYPHILIS is NOT to be entirely ruled out
by a negative serum Wassermann Reaction; for
the fluid Wassermann Reaction may be positive.
Case 13. William Twist is a case of note in the matter
of the so-called preparetic period (the idea of Charles L.
Dana which was scoffed at when first proposed by him in 1910).
The patient, a very successful traveling salesman, 35 years
of age, was admitted to the Psychopathic Hospital showing
a typical picture of general paresis.
Thus, mentally, the patient showed elation, grandiosity
(millions of dollars to give away), intellectual weakness,
disorder of memory, lack of judgment, rambling talk, speech
defect, omission of letters in writing and spelling.
Neurologically, there was tremor of the lips, slight irregularity
of the pupils, which however reacted well, and lively
knee-jerks.
Mr. Twist had sought advice at our out-patient department
in his thirty-third year. The records show that at that
time he was somewhat depressed, and his speech was even
then, according to his own statement, stammering. However,
we found the W. R. at that time to be negative in the blood
serum. It appeared that his mother had died of consumption;
his father was said to have committed suicide. A
brother had once recovered from an attack of depression,
presumably an attack of manic-depressive psychosis. Accordingly,
we thought at the time that the case was probably
one of manic-depressive psychosis. Moreover, our routine
serum W. R. failed to indicate any syphilitic process. As for
the so-called stammering of speech, this appeared to be a
matter of the patient’s own recollection rather than of our
observation. In any event, the patient had gone into the
country and appears to have entirely recovered; falling, again,
however, into mental difficulties after a short period, and
finally arriving at the hospital in the above-mentioned classical
condition.
78The W. R. in the blood serum proved again negative.
The test was repeated a number of times; also, after salvarsan
had been given. The salvarsan did not act provocatively,
and the blood serum has remained consistently negative.
In cases of syphilis the W. R. is at times negative. Swift
claims that in such cases an injection of salvarsan will often
produce a positive W. R. if the blood is tested on several days
following the injection.
The spinal fluid, however, did show a positive W. R. as
well as a gold sol reaction of a “paretic” type. There were
at the first examination 194 cells per cmm., there was a moderate
excess of albumin, and a positive globulin test. In
short, there was no question of any other diagnosis than
General Paresis.
1. How can the negative W. R. of the blood serum be explained?
It is difficult or impossible to explain this.
Figures differ as to the percentage of cases of general
paresis with negative blood serum; perhaps 3 to 5% of
these cases yield a negative serum W. R.
It is important to note the long preparetic period: at
least a year and a half. Could our diagnostic methods
be sharpened a trifle, such cases as these could be obtained
early in this preparetic period and it might
then be safe to promise good therapeutic results.
2. What is the nature of the preparesis of Dana? When
Dana’s brief paper on preparesis was written, there
was of course hardly any idea that cases of paretic
neurosyphilis could be cured or would recover, except
possibly vanishingly few curiosa about which there
would always rage a diagnostic question. Accordingly,
Dana, having found certain cases that seemed to him
to have early signs of paresis but had apparently been
cured by treatment, proposed to call them cases of
preparesis. His idea was that he would thereby not
offend those who held that general paresis was theoretically
a fatal disease. With modern work and the display
of more and more atypical cases of neurosyphilis,
and the observation of relatively numerous
cures or remissions under treatment, the designation
of preparesis for a separate entity, or even for a sub-form
of neurosyphilis, becomes superfluous.
793. What is the percentage of cases of paretic neurosyphilis
that show a negative serum W. R.? Among the best
figures are those of Müller, who found that of 386 examples
of paretic neurosyphilis, 379 showed all reactions
positive, or 98.5%.
4. What is the meaning and value of the so-called provocative
salvarsan injection? In practice, there may
be a series of negative W. R.’s in the blood serum
before a positive reaction is finally obtained, owing to
technical difficulties or biological peculiarities. Where
intensive work is being done upon the neurosyphilis
problem, it is beyond question desirable to make the
W. R. test upon at least three separate samples of blood
drawn at intervals, for the second or third test may
prove positive. This situation makes the interpretation
of the so-called provocative salvarsan injection exceedingly
doubtful; that is, the reaction might have been
positive on repetition without the injection of salvarsan.
The present case, as above stated, failed to yield a serum
W. R. even after repeated tests and the “provocative.”
5. What is the significance of the irregular pupils in this
group? Paretic neurosyphilis shows inequality of the
pupils in a high per cent of cases. Irregularity of outline
of the pupils is commonly thought to be an important
sign and to suggest neurosyphilis. It is true
that many cases of pupillary irregularity are syphilitic,
but the sign is of little or no differential value since
congenital malformations and relics of old injuries and
adhesions may produce effects identical with those of
neurosyphilis.
80
DIFFUSE (that is, meningovasculoparenchymatous[5])
NEUROSYPHILIS is typically associated
with six positive tests (serum Wassermann reaction,
fluid Wassermann reaction, spinal fluid gold sol
reaction, pleocytosis, positive globulin, excessive
albumin); but one or more, and frequently several,
of these tests are likely to run mild as
compared with the tests in PARETIC NEUROSYPHILIS
(“general paresis”). The clinical course
of the diffuse (and especially the meningovascular)
cases is likely to be protracted, with a good prognosis
as to life (barring fatal vascular insults).
Case 14. We shall present the case of John Jackson, a
surveyor, 31 years of age, suffering from a left hemiplegia,
with this in mind: To exhibit difficulties in diagnosis in the
presence of an embarrassment of symptomatic riches.
The patient arrived at the hospital, in the first place, because
he had been threatening a woman who lived next door
to him. He believed that this neighbor had been talking
about him and circulating reports against him. Excited by
these ideas, he had threatened to cut her throat.
Now the occurrence of hemiplegia in adult life before the
approach of senium is always suspicious of syphilis, and this
suspicion we naturally entertained from the beginning.
However, there was upon the scalp a crooked linear furrow
about six inches long, running from the vertex to the right
parietal eminence. Another furrow about an inch long
was present upon the forehead. These furrows appeared to
be of a bony nature and were not tender. There was evidence
of an old decompression operation on the right side of
the head; there were also large scars on both sides of the
neck, evidently the result of old operations; and there were
numerous palpable glands—the largest about the size of
a lima bean—all firm and not tender.
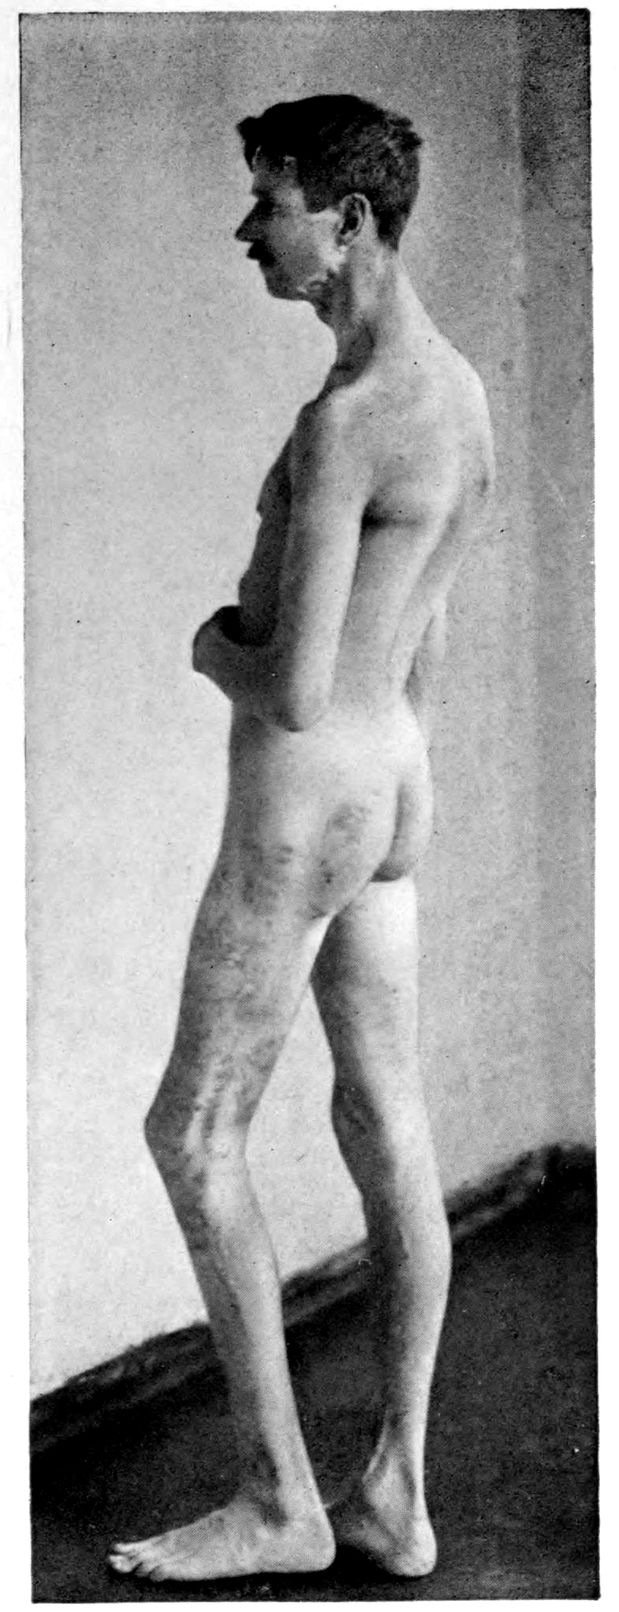
Station in syphilitic hemiplegia. Syphilitic pigmentation of skin.
81It seems that at the age of eight, according to the patient’s
mother, Jackson had received a head injury and had remained
unconscious for three weeks. Upon recovery, he
had to relearn both to walk and to talk; however, he was
able to begin school where he left off. He became more nervous
and irritable after the accident than previously. Nothing
further had developed until, at about 25 years of age, a
tubercle was discovered in his eye (the right pupil was
smaller than the left, reacting more slowly; right iris bound
down by adhesions, with white opacity of anterior chamber).
For two years, 25 to 27, the patient was under medical
treatment for tuberculosis, and at the conclusion of this
period numerous glands were removed from the neck and
diagnosticated tuberculous. However, the neck did not
heal and he carried bandages upon it for two years.
At 28, the patient’s mother described the occurrence of
a slight shock, with head retraction, for a minute or two,
and inability to speak. Thereafter there had been five or six
similar attacks, less severe, and without loss of speech. The
attacks were never accompanied by convulsive movements.
Then occurred a paralytic stroke, leaving the patient with a
left hemiplegia, which had somewhat improved. Mentally,
the patient had gone down hill, becoming less alert and more
apathetic, and to some extent amnestic. One had to consider,
accordingly, the somewhat doubtful possibility of
post-traumatic and post-operative conditions, and the question
of tuberculosis (possibly errors in diagnosis; the lungs
showed no evidence of tuberculosis).
Physically, the signs of a left hemiplegia were appropriate.
Spasticity on the left side was found; there were Babinski,
Gordon, Oppenheim reflexes and ankle clonus on the left
side (all absent on the right). Speech defect was present.
Mentally, aside from the delusions noted at the beginning of
our analysis, a striking feature was the patient’s childishness.
While reciting delusions, the patient was overactive and
evinced a somewhat childish interest. Arithmetically, Jackson had preserved a fair ability but his apathy and lack of
interest interfered with tests, and possibly also with the
exercise of memory. As above noted, we were compelled
to maintain the suspicion of syphilis throughout despite
the attractive hypotheses of traumatic and post-decompressive
effects and cerebral tuberculosis. A history of the
acquisition of syphilis an unknown number of years before
admission entered to strengthen the suspicion of the syphilitic
nature of the mental symptoms.
82
| TYPICAL LABORATORY FINDINGS IN NEUROSYPHILIS (Nonne, 1915) |
| Diagnosis |
W. R., Blood Serum |
W. R. 0.22 cc. Blood Serum |
Spinal Fluid, 1.0 cc. |
Phase I, Globulin |
Pleocytosis |
| PARESIS OR TABOPARESIS |
POSITIVE IN ALMOST 100% |
POSITIVE, 85–90% |
POSITIVE, 100% |
POSITIVE, 95–100% |
POSITIVE, ABOUT 95% |
| |
|
|
|
|
|
| TABES (not combined with paresis) |
POSITIVE, 60–70% |
POSITIVE, 20% |
POSITIVE, 100% |
POSITIVE, 90–95% |
POSITIVE, 90% |
| |
|
|
|
|
|
| CEREBROSPINAL SYPHILIS |
POSITIVE, 70–80% |
POSITIVE, 20–30% |
POSITIVE ALMOST ALWAYS |
POSITIVE almost always; NEGATIVE only EXCEPTIONALLY |
POSITIVE ALMOST ALWAYS |
| Chart 8 |
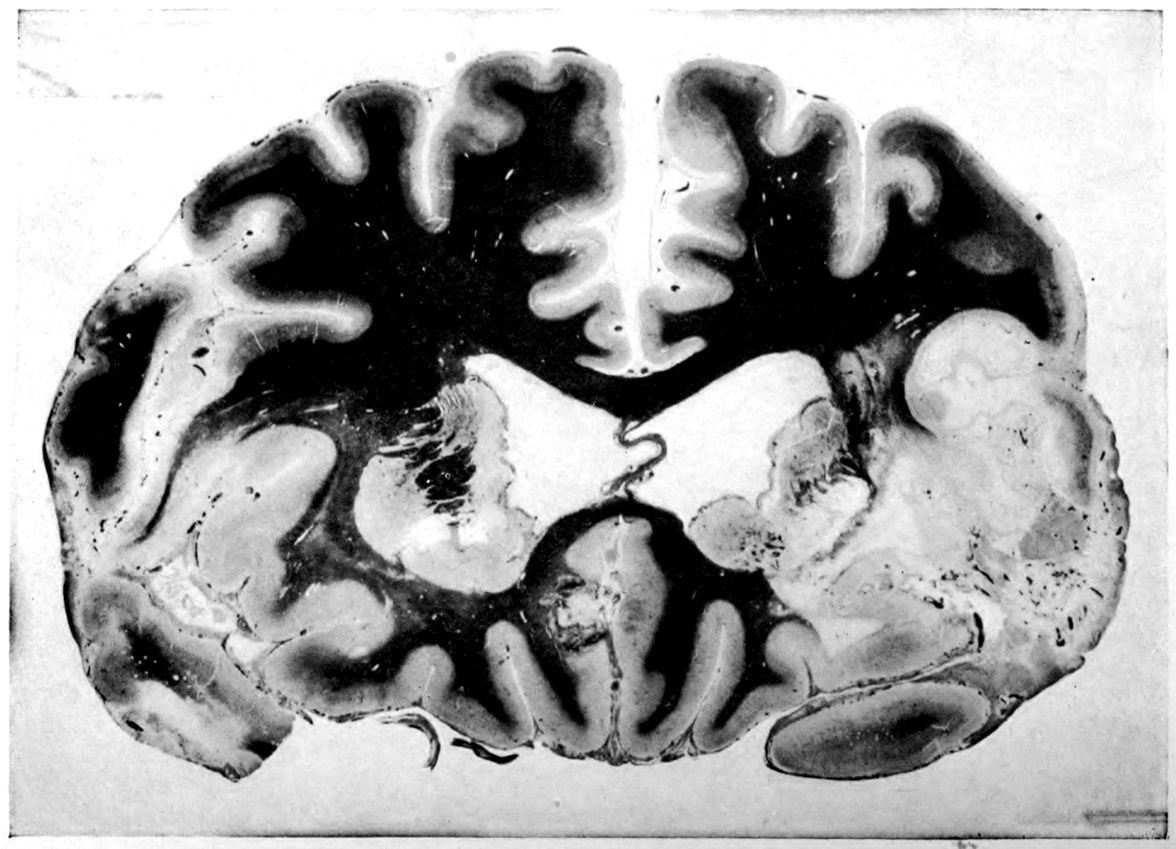
Syphilitic thrombosis. Contours of brain preserved.
83The W. R. proved positive in blood and spinal fluid. The
gold sol reaction was of the syphilitic type; 37 cells were
found per cmm.; there was a slight amount of globulin and a
slight excess of albumin.
We made a diagnosis of Cerebrospinal Syphilis rather
than general paresis on account of, first, the slow course of
the disease; second, the vascular type of the cerebral insult,
hardly typical of paresis; and third, the mild spinal fluid
reaction. Treatment will hardly cure the hemiplegia, at
least so far as restoration of cerebral tissues lost in the insult
is concerned. We were perhaps entitled to consider that, as
in the cases of Petrofski (17), O’Neil (19), Robinson (45),
the meningitic process could be arrested. Unfortunately,
our treatment of 20 injections of salvarsan over a period
of 10 weeks, followed by a number of months of bi-weekly
injections of mercury salicylate, proved incapable of making
any change in the mental and physical picture or in the
laboratory findings.
1. Can we explain the apparently poor reaction to treatment of
the cerebrospinal syphilis in the case of Jackson by
supposing a more deep-seated involvement than the
meningovascular involvement indicated by the hemiplegia
and the signs in the fluid? Autopsied cases in
our experience show focal parenchymatous involvements
that have not caused obvious clinical symptoms
at any time during the course of the disease. These
symptomatically silent lesions may have been present.
2. What is the comparative prognostic value of seizures
in paretic neurosyphilis and in such a meningovascular
case as that of Jackson? Paretic seizures are often
and indeed characteristically recovered from. Moreover,
84autopsies in paretic neurosyphilis characteristically
show no gross focal destructive lesions to correspond
with the seizures. The paretic seizures are
apparently more irritative than paralytic. However,
the seizures of the meningovascular group of neurosyphilis
are also, though less commonly, recovered from,
so that the differential diagnosis on the basis of the
outcome of seizures is not safe. Rarely paretic neurosyphilis
itself also develops seizures from which no
recovery is made.
3. What is the relation of neuropathic heredity to neurosyphilis?
The family history of John Jackson is undoubtedly
poor, since his father died of diabetes and
a paternal uncle was insane; and on the mother’s side,
the grandmother died of tuberculosis and an aunt died
insane. This general question was more interesting in
the days before the syphilitic nature of general paresis
and of allied diseases was known. However, we may
still hold perhaps that not only syphilis but also various
intoxications, especially alcoholism, do flourish upon
a neuropathic soil. This question, like that of Krafft-Ebing’s
celebrated claim of the relation between syphilization
and civilization, needs revision in the light of
more extensive applications of the W. R. in larger
and larger groups of persons under various community
conditions.
85
The SIX TESTS (serum Wassermann reaction,
fluid Wassermann reaction, pleocytosis, gold sol
reaction, globulin, excess albumin) are likely to
run STRONGER in PARETIC NEUROSYPHILIS
(“general paresis”) than in DIFFUSE (especially
meningovascular) NEUROSYPHILIS; in particular,
the gold sol reaction is likely to prove
“paretic” rather than “syphilitic.” The clinical
course of paretic neurosyphilis (“general paresis”)
is likely to terminate in death within a few
years.
Case 15. Pietro Martiro was a well developed and nourished
man, 30 years of age, who had been doing erratic things
and acting peculiarly for a few weeks before entering the hospital.
In the hospital, Martiro proved to be very excitable
and given to violence. He had marked delusions of grandeur,
saying he was worth many millions of dollars, was the greatest
singer in the world, the greatest athlete in the world, and
the like.
Physically, there was no disorder except overactivity
of some reflexes. The diagnosis of General Paresis offered
no difficulties, and it was confirmed by the laboratory tests
(positive serum and fluid W. R., “paretic” gold sol reaction,
42 cells per cmm., an excess of albumin, and a positive
globulin test).
Treatment: The perfect physique of this case and the
extremely brief clinical duration (a few weeks) would naturally
suggest a probably favorable outcome. However, cases
with marked delusions of grandeur have very frequently
proved to be cases with extensive brain tissue loss as shown
in certain studies with Danvers material.
In any event, the treatment in this case proved unavailing.
Enormous doses of salvarsan, twice a week, aided by mercury
and potassium iodid, were given. Although other cases had
been helped by such intensive treatment, Martiro went
steadily downhill, nor was there the slightest diminution in
the intensity of any of the spinal fluid reactions. After 50
injections of salvarsan over a period of 30 weeks without improvement,
treatment was discontinued. A few months
later, the patient died.
86
PARETIC NEUROSYPHILIS (GENERAL PARESIS)
PHYSICAL SYMPTOMS
EARLY HEADACHE
VISUAL DISORDER
HYPALGESIA
ADIADOCHOKINESIS
ATAXIA
NASOLABIAL FLATTENING
VOCAL CHANGE
SPEECH DISORDER
WRITING DISORDER
LOSS OF MANUAL DEXTERITY
PUPILLARY CHANGES
REFLEX CHANGES
SEIZURES
LATE: PARALYSIS, CONTRACTURE
Chart 9
87
PARETIC NEUROSYPHILIS (GENERAL PARESIS)
MENTAL SYMPTOMS
INTAKE IMPAIRED
CONSCIOUSNESS CLOUDED
FATIGUABILITY INCREASED
HALLUCINOSIS RARE
AMNESIA—RECENT! CHRONOLOGY AND STORAGE IMPAIRED. FABULATION
OVER-SUGGESTIBILITY
JUDGMENT IMPAIRED
FANTASTIC DELUSIONS
INSIGHT INTO ILLNESS NIL
EARLY IRRITABILITY OR HEBETUDE
QUICK SHIFTING EMOTION
CHARACTER CHANGE
CONDUCT SLUMP
Chart 10
881. What is the duration of paretic neurosyphilis (“general
paresis”)? If we omit the doubtful, early, and prodromal
stages and count the beginning of the disease
with the occurrence of definite symptoms, we find
(Kraepelin) that almost half the patients with pronounced
paretic signs die within the first two years of
their disease. Kraepelin’s observations upon 244 cases
are as follows:
| Year: |
1 |
2 |
3 |
4 |
5 |
6 |
7 |
8 |
9 |
10 |
14 |
| Cases: |
51 |
63 |
52 |
41 |
22 |
4 |
5 |
2 |
2 |
1 |
1 |
The average duration of the disease in months has
been calculated as varying from 24 to 32 months.
Juvenile paresis runs a slower and more insidious
course. The duration of paresis, according to many
observers, diminishes with the increasing age of the
patient. It is now held that a combination of tabes
with paresis does not prolong the duration of the
paresis. As noted above in the discussion of Case
Harrison (9), our conceptions of the characteristic
duration of paretic neurosyphilis must alter with the
increase of our knowledge due to the early application
of laboratory tests.
2. What is the significance of the term general paresis?
The case of Martiro is, of course, a good instance to
show that the term is sometimes a misnomer. The
characteristic generalized motor incapacity denoted
by the term general paresis is shown in patients in the
institutions for the chronic insane in their last few
months of life. The term paresis is perhaps to be
preferred to the term paralysis because the paralysis is
not complete but partial; but perhaps the best reason
is that the word paresis is a shorter word. When the
mental side is to be emphasized, the term paralytic
dementia is employed. In this book we have used the
term paretic neurosyphilis to mean a more precise
statement of the etiology of general paresis (general
paralysis, paralytic dementia). The lay term, softening of the brain, like the terms metasyphilis and parasyphilis
is in the present phase of our knowledge to be eschewed.

Euphoria in paretic neurosyphilis (“general paresis”). The head, arms and trunk were shaking with mirth; hence, the indistinct outlines of the photograph.
893. If this fatal case be typical of general paresis (for more
favorable results, see Part V), what is the toll of deaths
from this disease in the community at large? A striking
statement may be quoted from Dr. Thomas W. Salmon’s
“Analysis of General Paralysis as a Public Health
Problem:”
“With the information in our possession at the
present time, we are able to state that not fewer than
1000 persons in whom general paralysis is recognized
die in New York State every year. Let us compare
this with the lives lost from some other important
preventable diseases. It means that one in nine of
the 6909 men who died between the ages of 40 and 60
in New York last year died from recognized general
paralysis and that one in thirty of the 5299 women
who died in the same age-period died from this disease.
“The number of deaths from general paralysis in
New York last year about equalled the number of
deaths from typhoid fever. The following table gives
the number of deaths due to the ten most important
specific infectious diseases. Of course, deaths in
measles, typhoid fever and scarlet fever will be found
also under the names of some of the complications of
these diseases, but it should be remembered that
these primary diseases are not invariably fatal as general
paralysis is. Many of the patients with measles who
died from bronchopneumonia would have recovered
but for this complication, while the paretics with
bronchopneumonia would have died even if this complication
had not arisen. No attempt is being made to
compare the prevalence of general paralysis with that
of other diseases—we are trying only to estimate its
share in the mortality.
| “1. |
Tuberculosis (all forms) |
16,133 |
| 2. |
Pneumonia |
9,302 |
| 3. |
Bronchopneumonia |
7,217 |
| 4. |
Diphtheria and croup |
1,854 |
| 5. |
Influenza |
1,381 |
| 6. |
Measles |
1,071 |
| 7. |
Typhoid Fever |
1,018 |
| |
General paralysis (recognized) |
1,000 |
| 8. |
Scarlet fever |
837 |
| 9. |
Whooping cough |
818 |
| 10. |
Syphilis |
782” |
90
PARETIC NEUROSYPHILIS (GENERAL PARESIS)
CHARACTERISTICS
AMNESIA
QUICK SHIFTING EMOTIONS
CHARACTER CHANGE
CONDUCT SLUMP
NERVOUS DISORDERS
SPEECH DISORDERS
PUPILLARY CHANGES
REFLEX CHANGES
SEIZURES
CEREBROSPINAL FLUID PICTURE
Chart 11
91
SYPHILITIC NEURASTHENIA
GUMMA
SYPHILITIC PSEUDOPARESIS
APOPLECTIC CEREBRAL SYPHILIS
SYPHILITIC EPILEPSY
SYPHILITIC PARANOIA
TABETIC PSYCHOSIS
HEREDITARY
PARESIS
92
TABOPARETIC NEUROSYPHILIS (“taboparesis”)
is CLINICALLY a combination of the
symptoms of TABES DORSALIS and those of
GENERAL PARESIS. The COURSE of TABOPARESIS
is likely to be from a characteristic
tabes dorsalis (often of years’ standing) to a characteristic
general paresis; the ultimate paretic
picture is likely to retain various characteristics
of tabes. The LABORATORY TESTS in the
paretic phase are characteristic of ordinary (non-tabetic)
general paresis. The PROGNOSIS,
after the paretic phase has arrived, is apt to be
that of general paresis.
Case 16. Joseph Sullivan, a waiter, 50 years of age, sought
assistance at the Psychopathic Hospital voluntarily. His
complaint of severe and lancinating pains in the legs, difficulty
with his gait, and a feeling of constriction about the waist,
was forthwith suggestive of tabes dorsalis. He was a rather
poorly nourished, white-haired man, with a drooping of the
left side of the face. The pupils reacted sluggishly to light,
the right somewhat better than the left. A marked Romberg
reaction could be demonstrated. Ataxia in walking was
marked. There was some incoördination of the hands, considerable
tremor, and writing was poorly performed. The
ankle-jerks and knee-jerks were absent. On the whole,
the diagnosis of Tabes Dorsalis was clear enough.
The most appealing situation was mental. Sullivan was
exceedingly apprehensive about his condition on the ground
that it was growing progressively worse; if it was to get
worse, Sullivan feared he would commit suicide. From his
own account, he had become irritable, quick-tempered, and
often unreasonable. As usual in these cases, the question
arose whether the depression was psychopathic or natural.
93
| TABETIC SYMPTOMS AND SIGNS IN ORDER OF THEIR FREQUENCY |
| |
| ANALYSIS OF 250 CASES |
| |
| |
|
PER CENT |
| |
| 1. |
ROMBERG SIGN |
96.4 |
| 2. |
ABSENT KNEE-JERKS |
90.0 |
| 3. |
LANCINATING PAINS |
88.4 |
| 4. |
STAGGERING GAIT |
87.2 |
| 5. |
ARGYLL-ROBERTSON PUPIL |
80.0 |
| 6. |
ATAXIA IN UPPER EXTREMITIES |
68.2 |
| 7. |
SPHINCTER DISTURBANCES |
67.6 |
| 8. |
SENSORY DISTURBANCES |
58.2 |
| 9. |
VISUAL DISTURBANCES |
43.6 |
| 10. |
PARESTHESIA AND NUMBNESS OF FEET AND LOWER EXTREMITIES |
42.8 |
| 11. |
GIRDLE SENSE |
31.2 |
| 12. |
PTOSIS OF EYE-LIDS |
23.2 |
| 13. |
PARESTHESIA OR NUMBNESS IN HANDS OR UPPER EXTREMITIES |
13.6 |
| 14. |
STRABISMUS |
12.0 |
| 15. |
VISCERAL CRISES |
12.0 |
| 16. |
LOSS OF SEXUAL DESIRE |
11.5 |
| 17. |
CHARCOT JOINTS |
9.2 |
| 18. |
VERTIGO |
4.0 |
| 19. |
MAL PERFORANS |
3.2 |
| 20. |
PAIN IN JOINTS |
2.8 |
| 21. |
RECTAL TENESMUS |
2.8 |
| 22. |
MENTAL DEGENERATION (other than paresis) |
2.4 |
| 23. |
HEMIPLEGIA |
2.4 |
| 24. |
VESICAL TENESMUS |
2.0 |
| 25. |
DIFFICULTY IN ARTICULATION |
2.0 |
| 26. |
DEAFNESS |
1.2 |
| 27. |
ANOSMIA |
0.8 |
| |
| Baldwin Lucke. |
| |
| Chart 13 |
94While in the hospital things shortly came to a crisis. In
the midst of a fit of depression, Sullivan attempted suicide
by beating his head against the wall. Whether this attempt
could be regarded psychopathic, however, remained in question.
Sullivan had been drinking very heavily although he
had stopped about six weeks before admission, fearing that
the alcohol was causing a development of symptoms. The
remedy was almost worse than the disease because he then
became more nervous, lost his appetite, and had a marked
insomnia.
According to the patient’s own history, he had had several
attacks of gonorrhœa and a syphilitic infection at the age of
19; that is, some 31 years before admission to the hospital.
However, the first neurological symptoms of which the patient
was aware came about 27 or 28 years after infection, namely,
3 or 4 years before admission, when facial paralysis developed.
At that time, he had suddenly felt a peculiar sensation in the
throat and became unable to swallow for a time. His voice
remained hoarse and low for some time, and his face began to
droop. The lancinating pains and the ataxia also dated
back several years.
1. How shall we evaluate the mental symptoms? The prognosis
of tabes dorsalis is relatively good so far as life is
concerned, and it might even be possible for Sullivan by
training to remain capable of being a waiter. The
manual incoördination was not marked, and possibly
the manual tremor was in part due to alcohol. Accordingly,
the mental symptoms, such as emotional lability
and memory defect, were in the foreground of attention.
In point of fact, the laboratory examinations showed
positive W. R. in the serum and the spinal fluid, which
latter also contained 60 cells per cmm., positive globulin,
and an excess of albumin. The Diagnosis made
was that of Taboparesis, meaning thereby a tabes
associated with appropriate symptoms of a mental
nature.
2. How shall the term taboparesis be used? Some use the
term, as we feel erroneously, for instances of general
paresis which happen to show crural areflexia (absence
of knee-jerks). We feel that the best usage of the
term is for instances in which well-defined symptoms of
tabes (as well as of paresis) are present, namely, characteristic
ataxia, lightning pains, and the like. If the
95term is used more loosely, as above mentioned, then
practically every case of general paresis might perhaps
be termed taboparesis, since almost every case of paresis
does show involvement of the cord as well as of the
cerebrum. Such involvement may lead to hyperreflexia,
hyporeflexia, or areflexia according to the localization
of the process. In true taboparesis, in which there
is a commingling of the features of tabes with those of
paresis, we should find the posterior roots of the spinal
cord affected. The spinal lesions of paresis itself are
more apt to be intraspinal; that is, confined to the
nervous system within the pial investment.
3. Bearing in mind that Sullivan was a waiter, what shall
be said about the infectivity of these cases? It is
counted as a rule as negative, since there are no open
spirochete-bearing lesions. The longer the period since
infection the less, as a rule, is the chance of contagion
in syphilis; and as tabes and paresis occur fairly late in
the disease, the infectiousness at this stage is practically
negligible.
4. Of what differential value is the insight shown by Sullivan
into the nature of his symptoms? Kraepelin
remarks that a genuine insight into the nature of the
disease does not as a rule occur in paresis. At the
beginning of the disease, there may sometimes be a
correct understanding of the nature of the disease and
of its probable outcome; but the presence or absence of
insight into the fact of mental disease is by no means a
differential sign of practical value.
5. What is to be said of the occurrence of depression and
excited states in paretic neurosyphilis? A variety of
classifications of sub-forms of paretic neurosyphilis
have been propounded. Kraepelin, for example, deals
with four: the demented, depressive, expansive, and
agitated forms, but remarks that the division is merely
convenient for exposition. The institutional intake
does not accurately represent the distribution of cases.
Under psychopathic hospital conditions with the relatively
easy resort to such institutions, the number of
quiet cases increases; under the less advanced conditions
in Heidelberg, Kraepelin took in 53% demented
paretics as against 56% at Munich (73% women) under
the easier conditions of admission. The admissions of
demented paretics varied from 37 to 56%. The variations
depend much upon the facility with which the
cases can be brought to institutions. Where admission
96is beset with various legal restrictions, the quiet and
demented cases are more apt to be treated for long
periods at home. The depressive type of paretic
neurosyphilis forms a much smaller group, according
to Kraepelin, as only about 12% of his Heidelberg admissions
were of this type, and still fewer of his Munich
admissions. Other authors give percentages as high as
16 and 19. The so-called expansive group is larger,
Kraepelin finding 30% of his Heidelberg cases to be of
this group, and 21 to 22% of his Munich cases. The
rarest sub-form of paretic neurosyphilis is the agitated
form: 6% of Kraepelin’s Heidelberg admissions; 14%
among males and 5% among females in his Munich
admissions, where the diagnosis of agitated paresis was
entered on somewhat broader lines. French authors
(Sérieux and Ducaste) have enlarged the number of
sub-forms of paretic neurosyphilis as follows: Expansive
27%; sensory 24%; demented 24%; persecutory 3%;
depressive 2%; circular 7%; hypochondriacal 7%; and
maniacal 6%.
97
DIFFUSE (meningovasculoparenchymatous) NEUROSYPHILIS
may look precisely like PARETIC
NEUROSYPHILIS (“general paresis”) at certain
periods of clinical and laboratory examination.
Case 17. The police found Gregorian Petrofski crouching
on his knees on a Boston sidewalk, attempting to take
pickets off a fence. Petrofski knew little English; he said
that he had slept in Poland the night before. He did not
appear to be alcoholic.
When he was examined, through an interpreter, he told
how he had been in America two days, and in Boston two
years; that he was at the present time in Poland, and that
his brother had brought him to the hospital and left him
there.
The physical examination showed Petrofski to be well
developed and nourished. His pupils were somewhat dilated
and reacted somewhat slowly to light and accommodation.
Neurologically, there was nothing else abnormal found upon
systematic examination although, through lack of coöperation,
sensory and coördination tests proved difficult if not impossible.
There was a large ulcer on the under surface of the
glans penis, with several small smooth scars on the upper
surface. There was a purulent discharge from the external
meatus. There were exostoses of both tibiae.
The initial diagnosis had to consider uremia and diabetes,
which could be easily excluded on examination. Alcoholism
was excluded through absence of alcohol on the breath.
There remained such diagnoses as epilepsy, some post-traumatic
condition, or meningitis, to say nothing of the hypothesis
of syphilis raised by the tibial exostoses and the lesions
of the penis. The hypothesis of trauma was given up, as
well as epilepsy and meningitis upon the data of the lumbar
puncture. The spinal fluid proved to be clear but with
enormous amounts of globulin and albumin, 80 cells per cmm.,
a “paretic” gold sol reaction, and a positive spinal fluid
98W. R. (the serum W. R. was also positive). Accordingly, it
was clear that the case was one of neurosyphilis.
Treatment was instituted with injections of mercury salicylate,
a grain and a half twice a week, and potassium iodid.
After some weeks, diarrhoea and salivation with marked
symptoms of mercury poisoning set in; the treatment was
suspended, but later re-instituted. In a few weeks Petrofski
was apparently quite well, the spinal fluid tests had all become
negative, as had the serum W. R.
Petrofski now began to pick up a good deal of English, and
gave a consistent narrative of his past life, although the
period just prior to and during his early stay in the hospital
has remained blank. Without further treatment Petrofski
has remained well for over a year.
1. Does the “paretic” gold sol reaction mean general paresis?
In connection with this general question, a brief summary
of the significance of the gold sol reaction in this
group may be made. (1) Fluids from cases of general
paresis in the vast majority of cases will give a strong
and fairly characteristic reaction, especially if more
than one sample is tested. (2) Very rarely general
paresis fluid will give a reaction weaker than the characteristic
one. (3) Fluids from cases of syphilitic
involvement of the central nervous system other than
general paresis often give a weaker reaction than the
paretic, but in a fairly high percentage of cases give
the same reaction as the paretics. (4) Non-syphilitic
cases may give the same reaction as the paretics; these
cases are usually chronic inflammatory conditions of
the central nervous system. (5) When a syphilitic
fluid does not give the strong “paretic reaction” it is
presumptive evidence that the case is not general paresis,
and this test offers a very valuable differential diagnostic
aid between general paresis, tabes, and cerebrospinal
syphilis. (6) The term “syphilitic zone” is a misnomer,
as non-syphilitic as well as syphilitic cases give
reactions in this zone, but no fluid of a case with syphilitic
central nervous system disease has given a reaction
out of this zone, so that the finding may be used negatively;
and any fluid giving a reaction outside of this
zone may be considered non-syphilitic. (7) Mild reactions
may occur without any evident significance,
while a reaction of no greater strength may mean marked
inflammatory reaction. (8) Tuberculous meningitis,
brain tumor, and purulent meningitis fluids characteristically,
though not invariably, give reactions in higher
dilutions than syphilitic fluids. (9) The unsupplemented
gold sol test is insufficient evidence on which to
make any diagnosis, but used in conjunction with the
W. R., chemical and cytological examinations, it offers
much information, aiding in the differential diagnosis
of general paresis, cerebrospinal syphilis, tabes dorsalis,
brain tumor, tuberculous meningitis, and purulent meningitis.
(10) We believe that no cerebrospinal fluid
examination is complete for clinical purposes without
the gold sol test.
99
FREQUENT SYMPTOMS IN DIFFUSE AND VASCULAR NEUROSYPHILIS
(“CEREBRAL” AND “CEREBROSPINAL SYPHILIS”)
PUPILLARY DISORDER
HEADACHE
VERTIGO
INSOMNIA
DROWSINESS
CHANGE IN DISPOSITION
Irritability Slow thinking
SEIZURES
PARALYSES
Permanent Transient
APHASIA
HEMIANOPSIA
SENSORY DISTURBANCES
GASTRIC CRISES
SPHINCTER DISTURBANCES
INTRACRANIAL PRESSURE SYMPTOMS
POLYURIA, POLYDIPSIA, GLYCOSURIA
MÉNIÈRE’S SYNDROME
NYSTAGMUS
Chart 14
100See Appendix B for technical details.
2. What is the relation of the tibial exostosis to neurosyphilis?
The syphilographers have always stressed
the tibial lesions in the diagnosis of syphilis. Although
not so much attention has been paid to these and
kindred osseous lesions in neurosyphilis, yet we have
frequently found such lesions and they afford an important
auxiliary means of diagnosis.
101
A POSITIVE SERUM Wassermann reaction with
a NEGATIVE FLUID Wassermann Reaction may
be found in NEUROSYPHILIS, particularly in
VASCULAR NEUROSYPHILIS: the remaining
signs in the fluid, although frequently positive, may
even be negative.
Case 18. Frederick Wescott was a promoter, an elderly
looking man of 60 years. His health had been failing for 18
months. There had been shortness of breath, dizziness, a
tired feeling, inability to “get the words he wanted,” and
forgetfulness of names. About eight weeks before examination,
Wescott had had a convulsion, following which he had
been unable to express himself at all well. This convulsion
was not accompanied by loss of consciousness. Besides a
marked motor aphasia, there was agraphia.
Physically, Wescott showed arteriosclerosis and a blood
pressure of 135 systolic, but, except very lively knee-jerks,
no other reflex disorders or anomalies were discovered. In
particular, the pupils reacted fairly well.
There was, perhaps, no special reason to implicate syphilis
in the case, yet Wescott gave a history of syphilis at 35 years.
The W. R. of the blood serum proved positive; that of the
spinal fluid was negative, and the albumin was but slightly
increased; there was a very slight amount of globulin, and
there were 16 cells per cmm. in the fluid. The gold sol reaction
suggested syphilis.
We felt entitled to make a diagnosis of Syphilitic Cerebral
Arteriosclerosis, regarding the convulsion or seizure
eight weeks before as due to a vascular insult. The laboratory
picture in the spinal fluid in Wescott’s case seems to be
rather characteristic of this group of syphilitic arteriosclerotics.
1. What is the reason for the negative spinal fluid W. R.?
The theory would be that the syphilitic lesion is localized
in the vascular system and that the parenchyma
102is only secondarily, if at all, involved. The W. R.
producing bodies are accordingly not found in the fluid.
2. How frequently are several of the spinal fluid tests negative,
while others are positive? Whereas, clinically
speaking, the five tests in the spinal fluid (W. R., globulin
reaction, excess albumin, pleocytosis, and gold sol
reaction) are each indicative of a pathological condition
in the central nervous system, yet a specially
intensive study of the distribution of these tests has
shown that they are prone to occur independently.
Consequently, we must concede that they do not all
represent the same inflammatory products and chemical
conditions. The W. R. producing bodies, the gold sol
reaction producing bodies, as well as the globulins and
albumins, have been proved to be separate. Special
work has also shown that these tests disappear under
treatment at different rates. There is, unfortunately, no
doubt that the rate and intensity, presence or absence,
and the order of disappearance of these tests in either
treated or untreated cases, do not at all parallel the
clinical conditions of the patients.
3. What is the prognosis in vascular neurosyphilis, such as
in the case of Wescott? The prognosis is identical
with that of cerebral arteriosclerosis in general, that
is to say, bad, but with frequent periods of improvement.
In the neurosyphilitic type of arterial disease
thromboid formation is frequent. Where the lesion is
chiefly perivascular infiltration, rather than disintegration
of the vessel wall, improvement may very well
occur as a result of treatment. Wescott showed slight
improvement under treatment. He has already lived
two years since his first convulsion, and three and a
half years since the onset of symptoms.
103
DIFFUSE NEUROSYPHILIS (so-called “cerebrospinal
syphilis”) is often marked by SEIZURES.
Case 19. Agnes O’Neil, an unmarried woman of 28 years,
was first examined five weeks after the initial symptoms. It
appears that she had had certain seizures, with unconsciousness
and twitching of the limbs (otherwise not well described),
followed by confusion of mind and sometimes by a weakness
of the left side and a difficulty in speaking. Headache had
been almost constant, as well as pains in the arms and legs.
Physically, both in general and neurologically, there were
no signs or symptoms; mentally, we could discover no symptoms.
Syphilis was denied, although possible exposure to
syphilis was admitted.
The diagnosis of some form of organic brain disease was
clear with the picture of convulsions followed by slight aphasia
with headaches and limb pains. With onset at 28, the most
frequent cause for such epileptiform seizures is certainly
syphilis. Examination of the blood and spinal fluid showed
a positive W. R., in both. The albumin was also somewhat
increased. The clinical picture suggested a fairly generalized
meningitic involvement.
The prognosis in such cases of generalized meningitic
involvement is in general good, and this principle was illustrated
in the O’Neil case, in which the symptoms soon disappeared
under intensive antisyphilitic treatment. In fact
the spinal fluid W. R. became negative in the course of four
weeks. The blood serum W. R., however, has remained
positive despite eight months of active treatment.
104
CONDITIONS IN WHICH CONVULSIONS OCCUR
NEUROSYPHILIS
HYSTERIA
EPILEPSY MAJOR (Grand Mal)
EPILEPSY MINOR (Petit Mal)
DEMENTIA PRAECOX
TOXIC CONDITIONS:
Asphyxia, Uremia, Alcohol, Absinthe, Lead, Mercury, etc.
ORGANIC BRAIN LESIONS
Apoplexy, Meningitis, Intracranial Growths
STOKES-ADAMS DISEASE
MALINGERING
DISSEMINATED SCLEROSIS
Chart 15
1051. Are certain cases of syphilitic epilepsy really cases of
Jacksonian epilepsy? As a matter of nomenclature,
Jacksonian cortical epilepsy is usually the result of a
focal and circumscribed irritative lesion in the cortex.
Gumma, local syphilitic meningitis, and syphilitic
vascular lesions, as well as scars consequent upon the
latter, are among the causes of Jacksonian epilepsy,
along with such other focal lesions as trauma, tumor
abscess, tubercle, and the like. Even non-syphilitic
Jacksonian epilepsy has been observed from time to
time in cases of diffuse intracranial pressure. Jacksonian
attacks also have been found in so-called genuine
epilepsy. Accordingly, we must not conclude from the
occurrence of Jacksonian convulsions, even though in a
proved syphilitic case, that the convulsions in question
are surely due to a focal lesion, for they may be
due to diffuse syphilitic lesions.
2. What is the significance of aphasia in Agnes O’Neil?
Aphasia is not a characteristic symptom in ordinary
Jacksonian epilepsy, but the aphasia is another sign of
focal lesion and forms an added argument against the
diagnosis of genuine or idiopathic epilepsy. See also
discussion of aphasia in paretic neurosyphilis under
Case Levenson (22).
3. What is the behavior of the serum W. R. and the spinal
fluid W. R. under systematic treatment? Sometimes,
as in this case, the serum W. R. remains positive and the
fluid W. R. becomes negative; but in other equally
well-defined cases, the reverse holds true, and the serum
W. R. reaction becomes negative whereas the spinal
fluid reaction remains positive. The obvious conclusion
is that we cannot always be sure even by faithful
tests of either the serum or the fluid alone, whether the
treatment has succeeded in abolishing the laboratory
signs.
4. Can this case be regarded as one of cure? Not by the
definition adopted in this book or by the syphilographers
who take into account not only the nervous system but
the body which contains it. To be sure, the spinal
fluid of Agnes O’Neil is now entirely negative and she is
clinically free from symptoms; yet from the broad
standpoint of syphilis therapy in general, this patient is
not cured, as is evidenced by the positive serum W. R.
106
PARETIC NEUROSYPHILIS (“general
paresis”) is often marked by SEIZURES.
Case 20. Lester Crane, a plumber, 37 years of age, came
to the hospital with a slow and defective speech. Moreover,
there seemed to be some mental disorder since his answers to
questions were not always relevant. It appeared that he
was seeing bugs on the wall.
Physically, Crane was a well developed and nourished man,
with overactive knee-jerks and a Babinski reaction on the
left side.
It developed that there was an impairment in hearing.
The pupils reacted well both to light and to distance. The
patient was very restless and smiled in a silly fashion. His
memory was decidedly defective in all spheres, and he was
very slow in the intake of ideas.
The plumber’s wife said that, at about the age of 23 or 24,
he had a spell of confusion lasting two or three days, with
peculiar conduct, unintelligible talk, and a good deal of
weeping. The medical diagnosis at that time took into
account the fact that Crane was a plumber and was “lead
encephalopathy.”
However, according to his wife, Crane had acquired
chancre at about 26 years, was treated mercurially for about
three years and declared well. He had remained well up to
about 18 months before entrance, when, without previous
warning, the patient had a convulsion with the continuous
movements for about half an hour. He was semi-conscious
for about 18 hours and vomited continuously. There was
amnesia for the whole affair on regaining consciousness. In
a week’s time, Crane was entirely well. But six weeks later
there was another convulsion. Upon removal to a hospital,
the diagnosis of general paresis was made, and the patient
was given the Swift-Ellis intraspinous treatment. This
seemed to be very successful, and the patient discontinued
treatment after 14 weeks (during which time there had
107been seven treatments) on the ground that he was entirely
well.
However, after discontinuing treatment, there was another
convulsion in about a month, and further convulsions occurred
once a month. For six months, however, the patient took
no treatment, but finally returned to the hospital and was
given mercury. This treatment appeared to suspend convulsions
again for three months, but at the expiration of
six months, the patient had three convulsions in one day,
and several more during the following days. After the last
of these convulsions, there had been numbness on the right
side of the body and considerable headache.
The diagnosis of Paretic Neurosyphilis (“general paresis”)
is borne out by the laboratory tests. The W. R. of
the blood serum was, to be sure, negative, but the W. R. of
the spinal fluid was positive, and there was a “paretic” type
of gold reaction, together with other laboratory signs.
The case well demonstrates that group of paretic cases in
which convulsions periodically occur, leaving the patient worse
after each convulsion. Treatment with salvarsan was instituted,
and mercury and iodid was given by mouth. During
the period of eight months which have now elapsed since the
beginning of this treatment, there have been no convulsions;
there has been a great improvement in the memory, the hearing
has improved, the W. R. in the spinal fluid is much less
intense, the gold sol test has become negative, and the other
tests are all less intense.
The patient, however, has not been entirely well, for in
place of the generalized convulsions, he has had minor seizures,
beginning as a rule with a tingling sensation in the
right hand, extending up the arm, down the trunk and leg, and
through the right side of the face, with a bitter sensation on
the right half of the tongue. The patient maintains that
this sensation is absolutely confined to the right half of the
body (in this connection we may recall case Morton (1), in
which there was also a hemiplegia together with other apparently
hysterical symptoms at several times during the
long course of a disease with abundant structural correlations).
During these minor seizures, the patient is unable
to talk, although he does not lose consciousness and is entirely
aware of everything going on about him. These
attacks have of late been growing somewhat less frequent.
108
NEUROSYPHILIS
NEURITIS
(alcohol, diabetes, diphtheria, lead, arsenic, tubercle, cachexia, etc.)
Peripheral nerves sensory or motor
PERIPHERAL NERVE PALSIES
TEMPORARILY FROM COMPRESSION BY TOURNIQUET
FRIEDREICH’S ATAXIA
SUBACUTE COMBINED DEGENERATION OF POSTERIOR AND LATERAL COLUMNS
Posterior column disease
FOCAL LESION IN GRAY MATTER OF CORD
INFANTILE PARALYSIS (ACUTE ANTERIOR POLIOMYELITIS)
PROGRESSIVE MUSCULAR ATROPHY
(chronic anterior poliomyelitis)
Anterior cornua of cord
AMYOTROPHIC LATERAL SCLEROSIS
SYRINGOMYELIA
THROMBOSIS OF ANTERIOR SPINAL ARTERY
LANDRY’S PARALYSIS
Anterior cornua and peripheral motor nerves
MYOPATHIES
(pseudohypertrophic and atrophic types)
MuscLe itself
AMYOTONIA CONGENITA
FAMILY PERIODIC PARALYSIS
(during attacks)
INCREASED INTRACRANIAL PRESSURE
(especially hydrocephalus and tumors of posterior fossa)
PNEUMONIA
IMMEDIATELY AFTER ATTACK OF MAJOR EPILEPSY
(post-epileptic coma)
TOXIC COMA
(uremia, morphine, etc.)
DURING SPINAL ANESTHESIA
COMPLETE TRANSVERSE LESION OF CORD
1091. What is the cause of the negative serum W. R.? It is
claimed that 3 to 5% of all cases of general paresis
yield a negative blood serum. In this particular case,
there had been considerable treatment, including some
Swift-Ellis treatment, so that it may be that this
treatment had reduced a formerly positive blood serum
W. R. to a negative one.
2. What is the nature of the typical seizures of general
paresis? The most frequent seizures are epileptiform
and bear a general resemblance to cortical epilepsy;
but more rarely these seizures resemble the ordinary
epileptic attack or consist of a violent general shaking
of the whole body. A variety of initial minor disorders
usher in the attacks: the temperature is often increased.
The attacks are over after one or at most after a few
hours. Kraepelin speaks of one that lasted 14 days.
Sometimes a status paralyticus develops, suggestive of
the status epilepticus. Another rarer form of characteristic
seizure is the apoplectiform, which can hardly
be told from an ordinary stroke, and may be followed
by the usual post-apoplectic phenomena. A good
many of the strokes leading to sudden death in middle
life are probably cases of neurosyphilis although often
set down as early arteriosclerosis of a non-syphilitic
nature. Besides the epileptiform and apoplectiform
seizures, there are certain seizures of a less definite and
complete nature, ranging from simple fainting spells,
dizzy spells and petit mal attacks, to various special
forms of irritative muscular contractions and temporary
speech disorders. Sometimes these attacks occur with
complete preservation of consciousness. Transient paresthesias,
visual field defects, and especially attacks of
vomiting, which, according to Kraepelin, may precede
paresis by years (of course in this connection gastric
crises of tabes must be thought of), may be counted as
sensory seizures.
3. What is the proportion of paretic cases developing
seizures? Figures vary from 30 to 90%. According to
Kraepelin, seizures occurred in 30 to 40% of his cases
at Heidelberg; he was of the impression that treatment
in bed had reduced the number of seizures. 65% of
110paretics admitted to Munich (under very free conditions
of admission) were determined to have shown seizures
before their admission to the hospital. Seizures are
said to be somewhat more frequent in men than in
women. These paretic seizures are not due to either
hemorrhages or vascular plugging—at least in the
vast majority of cases—and must be ascribed to the
effects of microscopic injuries.
4. What is the effect of seizures upon the future course of
paretic neurosyphilis? The current idea as expressed,
for example, by Mercier, is that “immediately after
each crisis the patient is much worse than he was before
it, and thereafter there is some improvement, but he
never improves up to the point at which he was before
the occurrence of the crisis.” That is, “The course of
the disease is one of sudden plunges, each deeper than
the last, each followed by a gradual recovery that is less
complete than the recovery from the previous plunge.”
5. During what period of the disease are seizures most
common? Late in the disease many cases have convulsions,
even though there were none for the first year
or two. In other cases the convulsion is the first
indication of paresis.
111
DIFFUSE (non-paretic) NEUROSYPHILIS (“cerebrospinal
syphilis”) is often marked by APHASIA.
Case 21. Martha Bartlett, a woman of 40 years, was
brought to the Psychopathic Hospital aphasic, or at least
unable to talk distinctly enough to be understood, or even
to give name and address. The police had found her wandering
aimlessly about the streets. Although she was well-dressed,
she was mud-bespattered and apparently had not
changed her garments for several days. It shortly developed
that the patient, although unable to express herself either in
words or by writing, could understand everything that was
said to her and could indicate by the monosyllables yes or no
whether she agreed or disagreed with statements made.
It was thus determined that she was pretty well oriented.
She was able to understand both speech and printed words.
Although she approximated more than is at all common a
pure type of motor aphasia, it appeared that there was a slight
involvement on the sensory side, especially in the sphere of
visual imagery.
Neurologically, the patient showed moderate strabismus,
slight deviation of the tongue to the right, and considerable
tremor on protrusion of the tongue. The right side of the
palate hung lower than the left. The ankle and arm reflexes
were possibly more active on the left side, and the left grasp
was somewhat better than the right. Both knee-jerks were
active, but again the reflex on the left side was more active
than the right. No other abnormalities of reflex were determined.
There was no Rombergism but the gait was somewhat
ataxic. For the rest, the physical examination was
normal. The blood pressure was 120 systolic, 85 diastolic.
112
CONDITIONS IN WHICH SPEECH DEFECT IS FOUND
NEUROSYPHILIS
HYPOGLOSSAL PARALYSIS
FACIAL PALSY
PARALYSIS OF PALATE (Post-Diptheritic)
BULBAR PALSY
PSEUDOBULBAR PALSY
MYOPATHY—FACIO-SCAPULO-HUMERAL TYPE OF LANDOUZY AND DEJERINE
MYASTHENIA GRAVIS
FRIEDREICH’S ATAXIA
LARYNGEAL TABES
ALCOHOLIC INTOXICATION
POST HEMIPLEGIC
LENTICULAR DISEASE
BILATERAL ATHETOSIS
MULTIPLE SCLEROSIS
DEAF MUTISM
PARALYSIS AGITANS
CHOREA
STAMMERING
TICS
HYSTERICAL APHONIA
113The ready suspicion was that the case was one of apoplexy
of slight degree with post-apoplectic phenomena. Upon
investigation, this suspicion was confirmed since it appeared
that Mrs. B. had been apparently quite well until about six
months before admission, when without particular warning
she began to act strangely and promptly fell into a series of
convulsions. These convulsions would begin with twitchings
of the face, and then spread throughout the body. There
would be a period of unconsciousness for two or three hours.
It is not certain how many of these convulsive seizures the
patient had. At all events she is reported to have recovered
therefrom completely, remaining well for three months; whereupon,
suddenly, while visiting a friend, she suffered a paralysis
of the left side of the body. She remained dazed and
had hospital treatment for about a week. Ever since this
left-sided paralysis, the aphasic condition above described
has persisted.
Such a phenomenon has often been dismissed in the past
as due to an early arteriosclerosis, but most neurologists and
internists of today would look beyond the diagnosis of mere
arteriosclerosis and consider syphilis. The only suggestive
feature in the case, aside from the post-apoplectic reflex
disorder and spastic phenomena, is the irregularity and diminished
light reaction of the pupils. Our suspicions were
confirmed by the positive serum W. R. The W. R. of the
spinal fluid proved, however, to be negative. There was a
moderately strong gold sol reaction of the syphilitic type.
There was a slight excess of albumin, and there was an exceedingly
slight amount of globulin. There was but one cell
per cmm.
On the whole, it would seem best to consider the case of
Mrs. Bartlett to be one of Cerebral Arteriosclerosis of
Syphilitic Origin, and a case in which there is no evidence
of meningitis or meningoencephalitis.
1. What is the explanation of the negative spinal fluid
W. R.? It may be that none of the W. R. producing
bodies have gone over into the spinal fluid. It has been
shown by the work of Weston that the W. R. producing
body is not identical with the bodies responsible for
the other tests in cerebrospinal syphilis. Moreover, it
has been clearly shown that these several tests of the
spinal fluid do not run at all parallel with one another.
Especially is it true that the chemical tests do not correspond
at all with the degree or nature of the pleocytosis.
On the whole, when involvement of the nervous
114system is entirely vascular, it is not only theoretically
proper but also practically common, to find a spinal
fluid negative to several tests.
2. Omitting consideration of the syphilitic gold sol of this
case, what conclusion could be drawn from the albumin
and globulin findings? It would not be warrantable to
assume syphilis since it is a common finding after
cerebral hemorrhage due to non-syphilitic arteriosclerosis
to find excess albumin and also globulin in the
spinal fluid. Occasionally, also, pleocytosis occurs in
cases of cerebral hemorrhage even when the hypothesis
of an active meningitis can be excluded. We may recall
in this connection the pleocytosis in so-called meningitis
sympathica of certain brain tumors. (See also
the case of Milton Safsky (48), a case of brain tumor in
which there was an excess of albumin, a large quantity
of globulin, and a pleocytosis of 146 cells per cmm.)
3. What can be expected from treatment in these cases of
vascular cerebral syphilis? The condition offers very
little opportunity for therapeutic results. However,
antisyphilitic therapy is indicated to prevent if possible
further progress of the lesions. Since the lesions are,
however, vascular, and since it must remain a question
how far these vascular lesions are due directly to spirochetal
action, and since in any event it may be difficult
to reach the spirochetes thus active, perhaps it is
best to place most reliance on potassium iodid. In any
event, potassium iodid should be given. Salvarsan
and mercury are also indicated. It is common to warn
against administration of large doses of salvarsan in
this type of case on the ground that further vascular
ruptures may be produced. (See Friedberg, 108.)
4. If we conclude that the aphasia of the Bartlett case is
due to vascular disease, can we conclude a relation
between this vascular disease and vascular tension? It
is not safe to draw such a conclusion. The Bartlett case
itself showed low blood pressure. To be sure, some
cases of neurosyphilis show high blood pressure from
which one draws the à la mode clinical conclusion to the
effect that the kidneys are probably involved in the
arteriosclerosis; but other cases do not show a high
blood pressure but may in fact show a low blood pressure.
The vascular disease doubtless responsible for
the aphasia in the Bartlett case is probably not at all
an effect of blood pressure conditions, but is, on the
contrary, an effect of local syphilitic vascular lesions.
115
PARETIC NEUROSYPHILIS (“general paresis”)
is often marked by APHASIA.
Case 22. Meyer Levenson, a traveling salesman of 36
years, had for the last two or three years been undergoing a
change of disposition, quite interfering with his work. He
had begun to take unreasonable aversions to people, had
become irritable and emotionally depressed, and often fell to
weeping without cause.
About nine months before hospital observation, it seems
that a trunk-cover had fallen on Levenson’s head, and there
is some question as to whether he did not have a convulsion
at that time. However, a month later he had a definite
seizure, followed by speech disorder, a slight paralysis, and a
staggering gait. Four weeks later, however, he had gotten
over these post-convulsive difficulties and had gone back to
work.
At his work, he became tired easily, his gait and speech
did not seem entirely normal, and there was a considerable
memory disorder. After five more months, another attack
of a convulsive nature, with twitching of hands and face and
tongue-biting occurred, and the attending unconsciousness remained
for two days. Again improvement followed, though
without ability to return to work. Four (?) months later
there were several severe convulsions and Levenson would
remain unconscious for a day or two at a time. Restlessness,
irritability, and irrational talking followed.
Physically, the patient was fairly well developed and nourished;
blood pressure 168 systolic, 68 diastolic; pupils reacted
very sluggishly to light. There was a marked motor
aphasia, which the patient recognized as a speech difficulty.
On the whole, however, Levenson was very euphoric and was
entirely sure that he was improving and would surely get well.
Shortly after entrance, Levenson had a severe convulsion,
with unconsciousness. The movements were mainly on the
right side of the body, and there was a post-convulsive weakness
116of the right side for several days, followed by a slow
recovery of strength.
The course of the disease—convulsions followed by improvement—is
very characteristic of a paretic onset. The
laboratory findings were in all respects confirmatory. It was
rather striking that a permanent motor aphasia followed the
convulsions in this case, since the seizures of paresis do not
in the vast majority of cases leave permanent paralyses.
The course of the disease continued to show convulsions,
which would in each instance leave him at a lower terrace of
capacity than had been before shown. The patient died
four years after the onset of symptoms of a general asthenia.
With the exception of the permanent motor aphasia, this
case might be regarded as a fairly typical one of general
paresis.
1. What is the general nature of speech disorder in paretic
neurosyphilis? Speech disorder is, along with the
pupillary changes, one of the most important clinical
symptoms in paretic neurosyphilis. There are aphasic
and articulatory disturbances. The aphasia that accompanies
paretic seizures is of a transient nature as a
rule. A case with such long-standing motor aphasia
as shown by Levenson is not common. Paraphasia, with
incorrect naming of objects, may last longer. The so-called
“sticking” phenomenon is often observed.
Word-deafness is said to be rarer but is difficult to test
on account of the patient’s dementia. Agrammatism
(incapacity to form correct sentences) is sometimes
observed. But the most characteristic disorder is
in the syllabic composition of words. Syllables are
left out (“medaltricity” for medical electricity), or
fused (“exity”), or doubled (“electricicity”). Besides
the central speech disorders of which the above
are examples, there are disorders in articulation, which
at first occur as a consequence of paretic seizures or in
states of excitement, but later become permanent. These
are divided into paretic and ataxic disturbances.
2. What is the structural basis of these forms of aphasia?
It is believed that they are due to microscopic changes,
not to coarse destructive lesions.

BROOKLINE, MASS.
Mss. of Levenson, case 22. Paretic neurosyphilis. Tremor, misspelling. Metathesis of letters (Bk, not Br) omission of letters (Book).
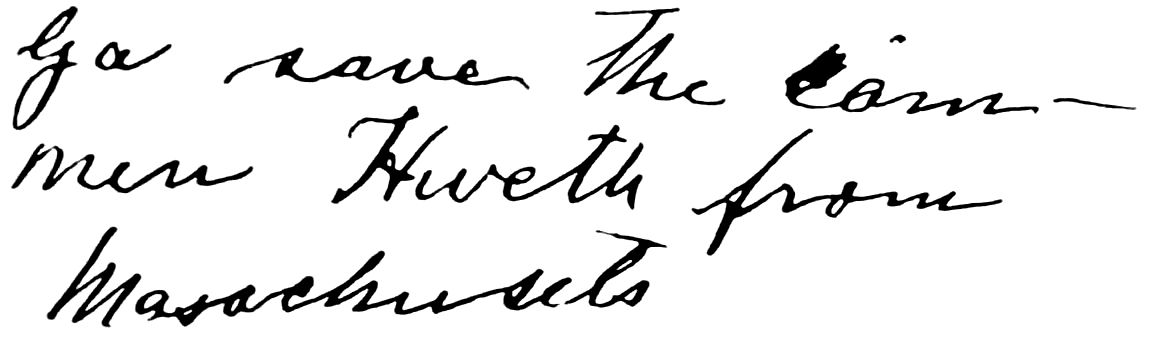
God save the Commonwealth of Massachusetts
Mss. of Safsky, case 48, brain tumor. Tremor not marked. Misspelling, omission of letters. Wrong letters (h in hweth).
Mss. of Halleck, case 31, cervical tabes. No brain disorder. Pen-holding and bearing on difficulties. Crowding of phrases result of ataxia.
Mss. of Collins, case 61, paretic neurosyphilis. One misspelling (-chussetts); not psychopathic? Characteristic tremor.
117
REMISSIONS of identical appearance occur in
PARETIC and in DIFFUSE (non-paretic meningovascular)
NEUROSYPHILIS.
Case 23. Thomas Donovan, a merchant 44 years of age,
acquired syphilis according to his own story at the age of 31,
and he was at that time treated at a well-known watering-place
with mercurial injections. Later he continued treatment
under his family physician, and at 34 was pronounced
cured. However, four years later—that is seven years
after his initial infection and in his 38th year—he had his
blood examined and it proved positive. He was accordingly
treated by salvarsan and his W. R. became negative. The
story did not end there, however, for at 43, mental symptoms
appeared of the nature of depression and a diagnosis of paresis
was made. He was released from the institution against
advice at that time, and without treatment, made a partial
recovery.
A sudden outburst of violence brought Mr. Donovan to
the Psychopathic Hospital; he was very surly, combative,
and difficult to manage, standing 6′ 2″, and weighing 210
pounds. He was oriented only fairly well and his surliness
was streaked with humor. He facetiously said that the
Psychopathic Hospital was the largest hospital in the country,
and that it was, in fact, a horse hospital; that he had come
because he liked the surroundings, not to make money; that
he was the healthiest man in the world, never having been
sick; that the Psychopathic Hospital was a club, for which
you have to get somebody to propose your name. There
was amnesia and no knowledge of current events. He
regarded the food as poisoned, refused to eat, and was very
irritable and untidy.
Physically, there were few abnormalities, but the pupils
failed to react either to light or accommodation, and the
knee-jerks and ankle-jerks were absent. There was a slight
Rombergism. There was a marked speech defect to test
phrases. Both serum and spinal fluid W. R.’s were positive;
the fluid showed 41 cells per cmm., there were large amounts
of globulin and albumin, and the gold sol reaction was of
the “paretic” type.
118
NEUROSYPHILIS
LESION OF PERIPHERAL SENSORY NERVES
DIVISION OF POSTERIOR ROOTS
TUMORS OR CHRONIC SCLEROSIS OF POSTERIOR COLUMNS
SUBACUTE COMBINED DEGENERATION
VESTIBULAR ATAXIA
FRIEDREICH’S ATAXIA
FAMILY PROGRESSIVE HYPERTROPHIC NEURITIS
THROMBOSIS POSTERIOR INFERIOR CEREBELLAR ARTERY
MARIE’S HEREDITARY CEREBELLAR ATAXIA
LESIONS OF CEREBELLUM, TUMORS, ETC.
WRITERS’ CRAMP
PREHEMIPLEGIA
MULTIPLE SCLEROSIS
PSEUDO-SCLEROSIS
HYSTERIA
119
CONDITIONS IN WHICH VERTIGO IS FOUND
NEUROSYPHILIS
HEAD TRAUMA
CEREBRAL ANEMIA AND HYPEREMIA
MENOPAUSE
ARTERIOSCLEROSIS
RENAL DISEASE
CEREBRAL HEMORRHAGE AND THROMBOSIS
INTRACRANIAL TUMORS
MULTIPLE SCLEROSIS
EPILEPSY (Aura)
TOXIC CONDITIONS:
alcohol, tobacco, constipation
PSYCHONEUROSIS
OCULAR DISTURBANCES
EAR DISEASE
MÉNIÈRE’S DISEASE
MIGRAINE
Chart 19
120Salvarsanized serum was injected intraventricularly through
a trephine opening in the right frontal region. Injections
were made through the corpus callosum into the third ventricle.
There was progressive symptomatic improvement
after each of four injections. In fact, after the fourth injection
the patient was allowed to leave the hospital despite
the fact that there was only a slight improvement in the
spinal fluid findings. The speech defect had entirely disappeared.
(Speech defect, according to many authorities,
including Kraepelin, is of very grave diagnostic significance.)
His memory returned. Mr. Donovan is now able to handle
figures rather extraordinarily well. He now has a good insight
into his delusions and tells stories about them with
great humor.
1. What is the definition of a remission in general paresis?
Remissions form a foil to seizures; just as seizures
mark a sudden advance in the severity of the disease
or may even lead to death; so remissions may cause
a sudden cessation of both mental and nervous phenomena
in the disease. Whereas the seizures occur
most often, according to Kraepelin, in the demented
types of paresis, the remissions occur in all cases except
in the terminal phase. Kraepelin quotes Hoppe as observing
pronounced remissions of long duration in
17% of male and 15% of female paretics. Gaupp
observed marked improvement in less than 10%, and
very marked improvement indeed in only 1% of his
cases. Kraepelin states that such improvements are
most frequent in agitated and especially in expansive
forms of paresis, and that they are rarer and less complete
in the depressive and demented forms. Sometimes
the improvement occurs over night, although the full
extent of the remission becomes complete only gradually,
perhaps in the course of months. The sensorium clears,
the disorientation disappears, the delusions retreat,
and the former delusions are treated as dreams and
imaginations. There is often a good deal of persistent
uncertainty as to events during the height of the disease.
121The nervous disorders are far more obstinate than the
mental. Still, both speech and writing may often
greatly improve.
Cotton in New Jersey found, among 127 cases of
paresis diagnosticated by modern methods during
seven years, that remissions occurred in but five, or
about 4%, lasting from a half to three years.
2. Does a remission ever amount to a cure? The classical
case quoted in this connection is one observed by
Tuczek. This case developed a picture of paresis in
1876, at the age of 36; and a remission, or cessation,
of symptoms, occurred in 1878; but in 1883, at 43 years,
the patient developed a tabes without any trace of
mental disorder, which tabes gradually advanced. By
the middle of 1898, when the patient was 58, certain
symptoms of excitement and confusion occurred, which
led to death with dementia, 22 years after the beginning
of the disease. Nissl pronounced the cortex to
be undoubtedly the characteristic cortex of a paretic.
This observation seems to indicate that a clinical
remission tantamount to a clinical recovery may occur
without the death of the spirochetes engaged. This
observation is to be held in mind in connection with all
therapeutic work with neurosyphilis.
Nonne states that during his clinical experience of
19 years he had followed 10 cases of paresis with apparent
recovery; but of these ten cases, four had to
be thrown out by Nonne because the apparent recoveries
turned out to be only long and almost complete
remissions, finally issuing in characteristic dementia.
Of the remaining six cases, perhaps two should hardly
be counted as paretic and Nonne rather preferred to
term them cases of syphilitic dementia in the sense of
a non-paretic cerebral syphilis. At the end, therefore,
of his review of observations, Nonne found himself
with four cases of true recovery from paresis.
Spielmeyer holds that there is no theoretical reason
why paresis might not be cured, since all the different
changes that have been described in the disease can
be halted, and many of them can be repaired. In
particular, he reminds us that the acute infiltrative process,
the neuroglia reaction, and the phagocytic action
of the large mononuclear cells are distinctly removable
processes. (See discussion below under Section V,
for apparent cures and remissions occasionally secured
under treatment.)
122
REMISSIONS of identical appearance occur in
PARETIC (“general paresis”) and in DIFFUSE
(non-paretic) NEUROSYPHILIS.
Case 24. Michael O’Donnell, a laborer of 48 years, came
home, one day, at 5:30, complaining of severe headache. His
wife told him he should lie down and, taking him by the arm,
tried to help him to the bed. At this moment, O’Donnell
lost control of both left arm and left leg, and fell, unable to
move but with consciousness preserved. The wife noted
that the left side of his face was drawn up and that he drooled.
He was at once carried to a general hospital, remaining there
for about three weeks, talking at random in a delirious manner
and tied in bed. Two intraspinous injections of salvarsan
were given, and O’Donnell showed considerable improvement
and went home.
However, upon his return from the hospital, he became
very wilful, would not remain in bed, and on one occasion
actually took the mattress from the bed, carried it to another
room, and then returned to his own room and slept upon the
springs. He became irritable and emotional, insisted upon
going to the hospital, did not go there but upon returning
home insisted that he had been there. That night, O’Donnell
left the house only partly dressed.
It appears that O’Donnell had been excessively alcoholic,
but that before August 15, when he sustained the left-sided
hemiplegia above mentioned, there had been no symptoms
except that in February he had once been very dizzy. It
appears that there had been another dizzy spell, three nights
before the paralysis, accompanied by a fall and unconsciousness
for about 15 minutes.
123
TRANSIENT OR FLEETING PARALYSES
NEUROSYPHILIS
MYASTHENIA GRAVIS
MYOTONIA CONGENITA (THOMSEN’S DISEASE)
PARAMYOTONIA CONGENITA
MYOTONIA ATROPHICA
INTERMITTENT CLAUDICATION
OCCUPATION NEUROSES
FAMILY PERIODIC PARALYSES
ETANY
EPILEPSY MINOR
HYSTERIA
MULTIPLE SCLEROSIS
APOPLEXY
CEREBRAL THROMBOSIS
Chart 20
124O’Donnell was brought to the Psychopathic Hospital some
six weeks after the paralysis, complaining merely of a slight
headache and desirous of treatment. There were no mental
symptoms of any sort. Physically, O’Donnell was in general
not abnormal (there was a slight pre-systolic murmur and
a blood pressure of 190 mm. systolic). The pupils were slightly
irregular, the left larger than the right; both reacted
sluggishly. Both ears were moderately deaf; the tendon
reflexes of the left arm and leg were somewhat more lively
than those on the right. The systematic neurological examination
otherwise revealed no abnormalities. The urine
was negative. The serum W. R. was positive but the spinal
fluid reaction was negative. There were but 2 cells per cmm.,
and there was a very slight trace of albumin.
1. How shall we account for O’Donnell’s transient paralysis?
We might invoke brain tumor, alcoholic pseudoparesis,
or some form of neurosyphilis. The diagnosis of brain
tumor seems quite untenable in view of the absence
of premonitory symptoms and in the absence of intracranial
pressure. As for alcoholic pseudoparesis it
is true that the patient was excessively alcoholic.
However, against these two diagnoses and in favor
of the diagnosis of Neurosyphilis, are the positive serum
W. R. and the pupillary reactions (although these are
short of the true Argyll-Robertson phenomenon).
Dizziness with retention of consciousness and associated
with the paralyses mentioned suggests rather a subcortical
than a cortical lesion. We are inclined to
regard this lesion as probably Thrombotic, and to place
it possibly in the region of the internal capsule. We
are inclined to regard the phenomenon as purely vascular
and as not in this case associated with an encephalitis.
We are, however, not entirely satisfied with the
diagnosis.
2. What shall be said as to treatment? A full-blown left-sided
hemiplegia may be produced even when the
thrombotic lesion is itself exceedingly small. It is
common to explain this on the basis that there is an
area of collateral edema about the small necrotic,
thrombotic, or hemorrhagic area responsible for the
lesion. In short, numerous neurones are functionally
rather than structurally affected, or at all events capable
of early restitution of function.
3. What is the prognosis in such cases? It appears that
now and again patients run for several years without
further trouble, both with and without treatment.
We are inclined, however, to advocate treatment rather
than absence of treatment for a variety of reasons.
125In the first place, vascular lesions may at any time
become associated with meningitic lesions, and treatment
by salvarsan may perhaps be counted on to head
off this process; secondly, the treatment with iodids
may possibly aid in the resolution of a local thrombotic
process.
4. What are the prodromal symptoms of cerebrospinal syphilis?
According to Nonne, headache, dizziness, sleeplessness,
mental symptoms of the irritability group, loss
of capacity as to mental work, whether severe or not,
and loss of capacity for difficult thinking; also impairment
of memory. Nonne does not regard these phenomena
as characteristic of syphilitic vascular disease,
and calls attention to the fact that in every organic
disease the same subjective symptoms occur. The
triad—headache, dizziness, and impairment of memory—is
for example now counted as a prodromal symptom
complex for arteriosclerotic apoplexy (Cramer).
Of course, apoplectic attacks occur without such preliminary
symptoms: particularly, according to Nonne,
the nocturnal attacks.
5. Can the fleeting paralysis be of service in differentiating
the diffuse from the paretic form of neurosyphilis?
Probably not. In both forms transient paralyses occur
as well as the permanent ones. In general, however,
the transient paralyses are more frequent in paretic
neurosyphilis, whereas the permanent ones occur more
often in diffuse neurosyphilis.
126
There are cases of NEUROSYPHILIS in which
the laboratory signs are positive but in which there
are no clinical signs or symptoms (PARESIS SINE
PARESI?).
Case 25. Richard Lawlor[6] was admitted to the Psychopathic
Hospital, October 29, 1914, being sent there from a
general hospital where he had gone on account of a self-inflicted
wound of the wrist, apparently made in a period of
depression with suicidal intent. Routine notes follow.
Family History. Paternal grandparents both died of
heart disease. Maternal grandfather died at seventy-two of
dropsy. Moderately alcoholic. Maternal grandmother died
of shock at fifty-six. Father died at age of forty, after an
illness of eight years, from heart disease. Father all his life
was subject to fainting spells and headaches. The only paternal
cousin died at thirteen months of brain fever. Mother,
aged forty-seven, is, to say the least, eccentric. Says “she
has several times been given up from tuberculosis.” Two
maternal uncles died of tuberculosis, one from rupture, one
from heart disease. One uncle who “doesn’t know anything
after he has a teaspoonful of liquor.” Several other uncles
and aunts whose history is not obtained. Patient is mother’s
only child. Mother was twice married. There were several
miscarriages by both husbands; patient child by first
marriage.
Past History. Patient born thirty-two years ago, full
term, normal delivery and development. Measles, mumps,
and chickenpox in childhood. Subject to headaches since
seven or eight years old. Kicked in the face by horse at
seventeen or eighteen, not considered serious. Hit by a
baseball three or four years ago, leaving him hard of hearing
127on left side. Married ten years ago; no children because
he says his wife needed an operation. He denies venereal
disease by name and symptoms. For past ten years has
had attacks of depression lasting but a short time, but quite
severe. Never caused him to quit work as a barber and he
felt better when working. His married life he says was
fairly happy except for his wife’s extravagances, and on this
account he left her a little over a year ago, and she has
applied for a divorce, which he is willing that she should
have, but does not wish to give her alimony. He admits
moderate alcoholism.
Present Trouble. Patient states that since he left his wife
a year ago he has felt sorry a number of times. He has
wished he had her back. He has felt lonely. He has had
six or eight periods of depression in that time similar to those
he has had for many years, lasting two or three days, and
sometimes a week. These were always precipitated by some
cause for worry. In these attacks he feels nervous, sleeps
poorly, has little or no appetite, sweats during his work and
everything looks black. Several times in these attacks he
has had suicidal ideas. Ten months ago he considered taking
corrosive sublimate. For a little over a week before entrance
to hospital he had been out of work and had been “sporting.”
The day before entrance he had a telephone message from
his lawyer which upset him somewhat and he walked the
floor all night. He had just been shaving when the idea of
suicide came to him. He sat down a minute when suddenly
the thought “to hell with the world” came to him; he took
the razor and slashed his wrist. He does not remember drawing
the razor across his wrist. As soon as he saw the blood
he felt sorry, called his mother, and was taken to an emergency
hospital and then sent to the Psychopathic Hospital.
Physical Examination. Patient is a well developed and
nourished man thirty-two years of age. Head is normal as
to size and shape; there are no scars or marks of injury.
Hair and skin not remarkable in any way. Ears negative
to external examination. Teeth well kept; two missing, several
gold fillings. Tongue very slightly coated. Throat
negative. Tonsils easily visible without evidence of inflammation
128or exudation. Neck, no thyroid enlargement, no
abnormal pulsations, no adenopathy. Chest, symmetrical,
expansion good, resonant throughout. Breath sounds transmitted
normally. No râles or rubs heard. Heart, no enlargement
or cardiac dulness. Sounds of good quality, no
murmurs heard. Rate regular. Pulses equal, regular and
synchronous, and of good volume and tension. Systolic
blood pressure 130, diastolic 65. Abdomen, flat, soft and
tympanitic throughout; no masses; no tenderness. Liver
edge not felt, below costal margin. Spleen not palpable.
Extremities negative, except for incised wound on left wrist.
Neuromuscular Examination. Pupils are large, round, regular,
equal and react readily to light and accommodation.
No nystagmus, strabismus or ptosis. No weaknesses or
paresis of facial muscles. The tongue projects medially and
shows no tremor. The triceps and biceps reflexes are readily
elicited, and are quite active, as are the knee-jerks and ankle-jerks.
On one occasion it was thought that the tendon
reflexes were slightly more active on the left than on the right.
This was never confirmed; always afterwards found equal.
There was no tremor of extended hands. Abdominal reflexes
not elicited. Cremasteric present on both sides. The
plantar response is flexor. There is no Babinski, Gordon
or Oppenheim. No Romberg. Coördination tests well performed.
No speech defect. No sensory disturbances. Urine
examination negative.
Wassermann reaction in the serum: Positive, with cholesterinized
antigen; negative, with syphilitic fetal liver antigen.
Wassermann reaction in fluid positive on two occasions.
Examination of spinal fluid, November 4: globulin +++, albumin
++, 100 cells per cubic millimeter; large lymphocytes,
8 per cent; small lymphocytes, 90 per cent; plasma cells,
0.7 per cent; endothelial cells, 1.3 per cent. November 11,
globulin +++, albumin +++, cells 18 per cubic millimeter.
November 26, globulin ++, albumin ++, cells 92 per cubic
millimeter; large lymphocytes, 13.1 per cent; small lymphocytes,
82.1 per cent; plasma, 1.2 per cent; endothelial,
3.6 per cent.
Gold sol, November 4, 5555432100.
Gold sol, November 26, 3332100000.
129Mental Examination. On entrance to hospital patient
seemed slightly depressed and a bit irritable. This condition
lasted two days, after which he was agreeable and apparently
entirely over his depression. Even during his mild depression,
however, he talked freely. There was no evidence of
retardation. He told his story readily. Orientation was
intact. Memory excellent. Educational knowledge well retained.
There was no evidence of any hallucinations or
delusions.
1. Was Richard Lawlor insane?
There was, then, on the mental and physical examination
nothing to make a definite suggestion of a
psychosis, and the most one could think of was a
psychoneurosis or a cyclothymia of at least ten years’
duration. The findings in the cerebrospinal fluid and
the Wassermann reactions, however, give us material
for thought. Certainly one cannot call the man
insane; all who saw him agreed on this point.
2. If Richard Lawlor should some day develop mental
symptoms, what would be the genesis of the new psychosis?
Though writers such as Fildes and McIntosh, and
Swift, have suggested an anaphylactic or hyperallergic
explanation for the development of symptoms after a
normal interval; such a hypothesis could hardly obtain
in the present case. The hyperallergic hypothesis for
the development of tertiary neurosyphilis would run
to the effect that in the secondary stages there had been
a definite disease of the nervous system, which, however,
absolutely cleared up, leaving no inflammatory vascular
or parenchymatous relics of its existence. Nothing
would on this hypothesis remain except a hypersensitisation
of the tissues. In some later period of the
now clinically normal person, one or more spirochetes
from a lesion outside the nervous system are carried
into the nerve tissues and there set up an anaphylactic
or hyperallergic reaction. It is obviously difficult
to prove the correctness or incorrectness of the
hyperallergic theory without numerous examinations
of the spinal fluid, in clinically normal persons after the
secondaries have passed. The present case, so far from
demonstrating a normal fluid, demonstrates a highly
pathological fluid, even though there are absolutely
no clinical symptoms which could be regarded as of
130nervous origin. The burden of proof at the present
time would seem to lie with those who claim hyperallergy
in neurosyphilis. We prefer on present evidence
to think that at the conclusion of the secondaries
a disease process often remains in the nerve tissues
despite clinical quiescence.
3. What is the prognosis in the case of Richard Lawlor?
The prognosis re neurosyphilis is doubtful. We have,
however, boldly termed the condition PARESIS SINE
PARESI, meaning thereby to suggest that the patient
is in considerable danger of the efflorescence of a true
diffuse or paretic neurosyphilis. We have no means of
telling, however, whether the positive symptoms would
be those of a paretic or a non-paretic neurosyphilis.
As data accumulate regarding these cases of paresis
sine paresi, we may be able finally to come upon some
case in which trauma shall bring out the clinical symptoms
of neurosyphilis. For discussion of this matter,
see the case of Bessie Vogel (52) in Part III of this book.
4. Should Lawlor have been brought to a psychopathic
hospital? It is a safe working rule to have any person
who attempts suicide observed. A large percentage of
suicides occur in psychotic individuals and a suicidal
attempt is not infrequently the first recognized abnormality.
Immediate observation is a necessary safeguard
against another more successful attempt.
131
Demonstrates SYMPTOMS and LESIONS of
PARETIC NEUROSYPHILIS (“general paresis”).
Autopsy.
Case 26. John Morrill, 49, an operative in a mill town in
Essex County, Mass., was described as a “Saturday night
and Sunday drinker,” with a history of very serious long
sprees at the age of 43. It seems that he had had what was
called “sciatica” at 35, and was treated in hospital for
seven weeks at that time. The nature of this sciatica is in
doubt, but there was a history of syphilitic infection at 36
years (scar of glans).
Morrill had been married twice, and two of the children
were dead; one daughter was described as “very nervous,”
but there were four children under ten years of age, all regarded
as perfectly healthy.
Morrill had been a mill operative of average capacity, was
industrious, and had supported his family despite alcoholism.
The syphilis had been treated with reasonable thoroughness.
Aside from alcoholism, there had been no symptoms up to
two months before admission to Danvers Hospital. Then
there had been insomnia, fatigue, agitation, eruption on foot,
loss of ten pounds in weight, hypochondriacal fears, apprehensiveness
for the future of the children, incoherent talk;
and just before admission, his talk was described as foolish.
He had taken to running away and hiding in bushes by a
pond and in the cellars of other people’s houses.
The patient was of medium height and weight, with thin
grayish hair and grayish irides; musculature was slender.
The face was blank in expression, the teeth poorly preserved
with atrophy of gums, the tongue coated, and the breath
foul. There was a gummy secretion of the eyelids, an area
of brownish branny eruption over both clavicles, a number of
depressed scars over the limbs and back, and another area
of scaly eruption on the right heel and the sole of the foot.
The heart area was increased, and the sounds were faint at
132the base, with the first sound accentuated at the apex. The
urine showed a trace of albumin.
Neurologically, the Romberg position was maintained with
a general tremor and fluttering of the eyelids. In complicated
movements, the patient was slightly ataxic. The
pupils were irregular, the left being much larger than the
right. There were no light reactions to be obtained in window
light. The reaction to accommodation was present, though
slight. Vision was poor, ¼-inch capitals could not be read by
left eye at reading distance. The knee-jerks were diminished
equally; the Achilles jerks were absent; the other reflexes were
normal. Upon the sensory side, the patient gave a history
of pains in the legs at irregular intervals for several years.
These pains he described as of a darting character. There
was little or no sensory disorder, although the outer surface
of the right leg required a deeper pressure to elicit sensation.
There were no disorders of muscle sense.
If Morrill was to be trusted, he had been born in Ireland,
and had come to the United States at the age of 17. He married
at 18; there had been seven pregnancies by the first wife,
with one stillborn child; one child had died at five weeks.
The four children by the second wife were healthy. The
first signs of neuritis had occurred at 45 and had received the
diagnosis neuritis, although no connection between the
neuritis and the syphilis had been noted.
The patient entered the hospital July 26, 1904, and was
discharged, improved, January 5, 1905. He returned a little
more than a year later, January 15, 1906, and died March 21,
1906. The total duration of the disease from the onset of
mental symptoms may therefore be stated as somewhat under
two years. When the patient appeared at the hospital the
second time, he showed a positive Romberg sign, an unsteady
gait, an ataxia that still was moderate, and somewhat more
marked tremors, involving fingers, tongue, and face. He
was now unable to read ½-inch type with the left eye. The
knee-jerks, formerly diminished, were both exaggerated, the
left slightly more so. The Achilles reaction, not obtained
formerly, now appeared on the right side. The pupils reacted
as before. The sensory loss had become more marked, since
133sharp and dull points could hardly be distinguished. Deep
pinpricks were not felt in the leg, and heat could not be told
from cold.
The speech in 1904 had been somewhat defective (“truly
rural” rendered as “tooly lualal,” “sifted soft thistles” as
“thoft thsistles”), and there had been little further development
of the speech defect. The handwriting had lost appreciably
in legibility and had become much more tremulous.
During the first period of hospital observation Morrill had
what might possibly have been visual hallucinations, but it
was impossible to tell whether his story of seeing his wife and
children trying to get in through the window was hallucinatory
or a matter of fabrication. Memory was decidedly
imperfect and few details of recent events could be produced.
The association of ideas was almost a so-called “flight”
of apprehensive, fearful ideas, loosely connected, incoherently
expressed, and dealing chiefly with his work and his children.
Judgment was imperfect; the height of the room was estimated
as 24 feet, but the height and weight of persons were
estimated with fair accuracy, and also the length of small
objects, whose lengths were doubtless remembered rather
than estimated. The estimate of time elapsing during a
medical examination was accurate, but the estimate of longer
durations involving over-night memories was hopelessly
imperfect. Emotionally, there was a dulling of sensibility,
an appearance of suspicion and apprehensiveness; the patient
fancied himself to be in a hopeless condition as a result of
syphilis, but at the same time accompanied his statement
of his hopelessness with laughter. A sample of his hypochondriacal
ideas: “I am all gone; I am good for nothing;
I am all gone now; I can’t drink now; can’t write or talk at
all; worse than when you saw me first; nothing in my inside;
all wrong through me again; I aint got no swallow now;
I can’t die even; my heart aint much good; I can’t hear
it beat; I don’t think it flutters; no life in these hands;
they are all cold and dead” (pointing to his arms and moving
them about). During such a portrayal the patient laughed
in a silly way.
During the second hospital stay, Morrill was at first restless,
134sleepless, profane, imperfectly oriented for time, possibly
for place, and also for the attendants. A few weeks later he
became stuporous and confused, and his feebleness and physical
exhaustion were finally ended by death, March 21, 1906.
Death was preceded by a semi-comatose condition; a left
otitis media had developed.
At the autopsy, it appeared that death was due to an early
bronchopneumonia associated with acute splenitis and doubtless
related to the otitis media of the left side. The body at
large showed, aside from these acute lesions, a few chronic
lesions, including slight scars of the left apex, and chronic
adhesive pleuritis, chronic diffuse nephritis, and aortic and
coronary syphilis. The aorta showed slight linear and nodular
markings, with a single small dark ulcer in the upper thoracic
region, but the aorta did not show the characteristic scarring
which syphilitic aortas often show. The femoral marrow
was of a dark red chocolate color. The thyroid appeared
to be smaller than normal. A slight sacral decubitus had
developed.
The description of the head (E.E.S.) is given in full on
account of the encephalitic lesions shown. These encephalitic
lesions may be summed up as follows:
Local cerebral atrophy and sclerosis of the frontal,
orbital, and central regions, especially of the left operculum
and left supramarginal gyrus.
Extension of sclerosis to hippocampal gyri with
effacement of substantia reticularis alba.
Slight chronic internal hydrocephalus.
Granular ependymitis (especially of floor of 4th
ventricle).
Compensatory edema of frontal and central pia mater.
Cerebellar sclerosis (culmen monticuli, lobus culminis,
lobus cacuminis).
Spinal sclerosis (grossly evident in the posterior
columns of the upper thoracic region and of the lumbar
enlargement).
The details are as follows:
Head:—Bald on top. Hair gray. Scalp normal.
Calvarium thin, deeply excavated by arachnoidal villi
to right of vertex. Diploë absent. Dura closely adherent
in bregmatic region. Dura of usual thickness.
135Sinuses contain cruor clot. Arachnoidal villi slight.
Pia mater hazy and over sulcal veins porcelain white
over all of vertex except occipital poles and over flanks
(notably left). Thickened also around circle of Willis,
over culmen monticuli and in posterior cerebellar notch.
Edema of pia corresponding to atrophy of frontal and
central regions. Cerebral atrophy most marked in
orbital surfaces of both frontal lobes, in left area of
Broca, and in left supramarginal region. The ascending
branch and the ascending ramus of the posterior
limb of the left Sylvian fossæ both readily admit the
thumb by reason of atrophy of adjacent substance.
Induration corresponds closely with atrophy, but is
not more marked about the left Sylvian fossa. There
is sclerosis of both hippocampal gyri, with loss of the
substantia reticularis alba. The culmen monticuli and
lobus culminis are firmer than the clival regions, and
the lobus cacuminis is again slightly firmer than the
clival region. Cerebellum a little softer than usual.
Pia strips with usual readiness from all regions. The
subpial region of the frontal lobes is a trifle grayer
than that of the rest of cerebrum. Ventricles slightly
dilated. Surfaces evenly sanded. Floor of fourth
ventricle shows numerous coarse, closely set granules.
Brain wt. 1200 grms. Cord shows a slight increase of
consistence over one or two upper thoracic segments
and in lumbar enlargement corresponding with a slight
graying out of posterior columns. In places there is
a suggestion of graying out also in lateral columns.
A few calcified plaques in posterior lumbar pia.
Analysis of these details shows a number of lesions that
characterize paretic neurosyphilis (among others, granular
ependymitis, frontal atrophy, chronic leptomeningitis), but
the lesions are more than merely frontal, extending as they
do back as far as the postcentral regions on both sides, and
even as far as the left supramarginal gyrus. The cerebellar
involvement although frequent, can hardly be said to be
characteristic in paretic neurosyphilis. The spinal involvement
is characteristic of a case which is probably to be regarded
as one of taboparesis; that is, of paretic neurosyphilis
following a number of years after the establishment of tabetic
neurosyphilis. The aorta is almost constantly affected by
sclerosis in paretic neurosyphilis. The absence of diploë in
136the skull is not infrequent and the adherent dura mater is
often found.
Microscopically, the tissues showed the characteristic
lesions of Paretic Neurosyphilis; nerve cell destruction,
fibrillar and cellular gliosis, lymphocytic and plasma cell
deposits about the small vessels.
1. What are the clinical evidences of syphilis outside the
nervous system? The brownish branny eruptions of
the skin, the depressed scars and the scaly eruption
on right heel and sole are very suggestive of syphilis.
Such clinical evidences of syphilis are very important
in systematic examination. Although the laboratory
tests are of the utmost assistance in the diagnosis of
syphilis, the clinical signs should not be neglected, and
no physician should rest satisfied with laboratory signs
alone. X-ray diagnosis of bone conditions sometimes
succeeds when all other methods have failed.
137
GUMMA of cerebral cortex verified by operation;
death.
Case 27. The presenting picture in the case of David
Tannenbaum was that of deep dementia, in which condition
the patient was brought to the hospital. There was a meagre
history to the effect that about four months before admission,
he had lost his job in a hotel through lack of further work.
We heard that at this time he had begun to suffer with excruciating
pains in the head; at first, worse at night, later,
worse by day. It appeared that this pain, though it came
and went, was chiefly localized on the left side of the head.
For a fortnight, Tannenbaum had been dragging his legs,
until finally he had become unable to walk at all.
Pari passu with these developments, Tannenbaum had
become mentally confused and irritable, and his memory had
become untrustworthy. For several days before admission,
an appearance of marked dementia was presented, with slow
incoherent, or at all events, irrelevant words, and a complete
disorientation for person. However, his vision had become
so poor that it would have been hard for him to have recognized
any one.
It appeared that the family history was entirely negative;
that the patient was without education but had been physically
very strong, and had been fairly successful at first in the
junk business, and later in the clothing business; but latterly
he had been less fortunate in the clothing business, and
finally had to resort to work as a laborer around a hotel.
His wife had had eleven pregnancies with but one miscarriage.
Nevertheless, out of the eleven pregnancies, there
were now but four living children.
Physically, Tannenbaum was a rather small man; he was
flabby and looked as if he had recently lost weight. The skin
showed areas of pigmentation on the face and sides of the
neck, and some dark copper-colored circular areas, marble-size,
in the neck (syphilitic?). There was a slight radial
138arteriosclerosis. The heart was slightly enlarged with distant
and indistinct sounds. There was a small pedunculated
growth on the right side of the abdomen.
The pupils failed to react to flash-light but they reacted to
sunlight. They both were slightly irregular but were equal in
size, and reacted in accommodation. There was apparently
almost complete blindness and extreme deafness. Arm-jerks
and knee-jerks were absent; there was an occasional slight
response of the left ankle-jerk, but the right ankle-jerk was
absent; the left abdominal reflex was very feeble; the right
absent; the cremasteric reflexes were absent, but there were
no other abnormalities in the systematic examination. Hand
grips weak; gait awkward, with right leg held somewhat flaccidly.
It was significant that percussion over the left frontal and
parietal regions was able to elicit great pain. Either through
the patient’s deafness or through sensory aphasia, spoken
language was not understood. The serum W. R. was positive,
the fluid W. R. negative.
Diagnosis: The clinical symptoms seem clearly to indicate
syphilis. The local skull tenderness and impairment of
vision might well suggest intracranial pressure. Uniting
these suggestions, we might automatically arrive at a diagnosis
of cerebral gumma. We have learned to be rather cautious
of making a diagnosis of gumma of the brain through its
mere rarity.
Decompression was suggested and executed. A deep
growth resembling a Gumma, in the view of the surgeon, was
discovered. No attempt could be made to remove it. The
patient died without recovering consciousness.
1. What is the significance of the negative fluid W. R. in
this case of cerebral gumma? The W. R. producing
substances not infrequently fail to appear in the spinal
fluid from a gumma of the brain. The serum W. R.
was positive in this case, but even the serum W. R. may
be negative in cases of gumma, both of the brain and of
the body at large. It must be remembered that the
serum W. R. may be negative in paretic neurosyphilis
(general paresis); the serum W. R. is even more apt
to be negative in cases of gumma.
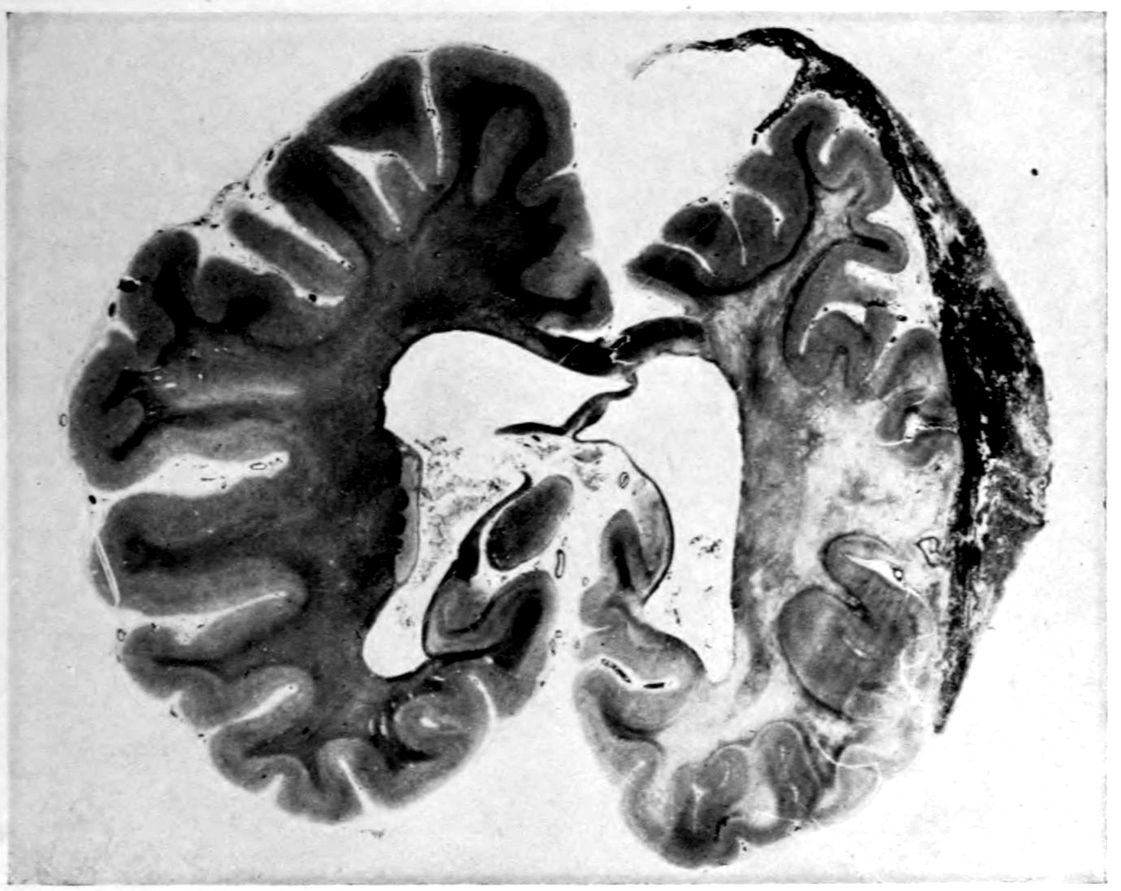
Gummatous meningitis. Compression of hemisphere. Tissue destruction of underlying cortex.
1392. Is operative procedure to be advised in cerebral gumma?
There are cases in which the acute and threatening
symptoms of heightened intracranial pressure require
operative treatment simply because the therapeutist
cannot wait for the effect of antisyphilitic treatment.
Moreover, antisyphilitic treatment of cerebral gumma
is not always as successful as that of most syphilitic
lesions.
3. Could the intracranial pressure be caused by other syphilitic
lesions than gumma? A heavy meningitis may
cause symptoms such as produced by an intracranial
tumor. In such a case one will usually find evidences
of inflammation in the spinal fluid. Cysts caused by
syphilitic lesions may also produce identical symptoms.
4. What is the significance of cranial tenderness? Where
sensitiveness to cranial percussion is not due to a scalp
lesion it is very suggestive of a tumor underlying this
point. A gummatous lesion of the cranium itself, may
occur without causing pain or increased sensitiveness.
140
CRANIAL NEUROSYPHILIS (focal syphilitic
extraocular palsy) without mental symptoms.
Case 28. A chef, Paolo Marini, 28 years of age, reported
that on awaking one morning, everything appeared double to
him and that his right eyelid had begun to drop. In the following
month Marini had begun to feel weak and to have
difficulty in swallowing, as well as at times difficulty in breathing.
The diplopia was found to develop when Marini looked
to the right. Mentally, the patient was in all respects normal,
and no other physical signs were found except the diplopia
and ptosis above mentioned. The W. serum test was positive,
but the tests of the spinal fluid were negative.
Diagnosis: “Cerebral syphilis.”
1. What is the anatomical cause of this condition? It is
thought to be due in a number of cases to a small diffuse
gummatous lesion at the basis cerebri. In the case
of Marini this lesion appears to have been a little more
extensive and to have interfered with the tenth and
twelfth nerves also.
2. Why is the spinal fluid negative in such a case as that of
Marini? Head and Fearnsides believe that intracerebral
lues is characterized by a negative spinal fluid,
under which circumstance one has always to consider
the possibility of brain tumor or migraine in addition to
the suspicion of syphilis.
3. What other causes besides syphilis should one consider
for the sudden diplopia? Brain tumor, multiple sclerosis,
cerebral arteriosclerosis, tuberculous meningitis,
trauma and migrainous ophthalmoplegia, are not
infrequently at the bottom of this condition. Cases
also occur in which the etiology remains obscure, even
at autopsy.
Under antisyphilitic treatment, Marini slowly improved.
141
The SIX TESTS in TABETIC NEUROSYPHILIS
(“tabes dorsalis”) may run milder than in paretic
neurosyphilis (“general paresis”) and characteristically
run somewhat like those of diffuse (meningovascular)
neurosyphilis; in particular, the fluid
Wassermann Reaction and the gold sol reaction
are apt to run milder. The clinical course of tabes
dorsalis is protracted and the prognosis as to life
is good.
Case 29. Mario Sanzi, 55 years of age, had been having
what he called rheumatism since his 43d year. This rheumatism
affected only the hips and legs, had at times been very
severe, and for two years past had been almost constant.
Before that time, pains had come at intervals, lasted a variable
period, and suddenly disappeared. They were of
knife-thrust character, and could probably be called “lancinating.”
In a given attack, these pains would come at
intervals of seconds or more. There was also a certain
unsteadiness in locomotion and inability to control the
vesical sphincter.
Physically, the patient was entirely normal so far as could
be made out except neurologically. Argyll-Robertson pupils,
absence of knee-jerks, and ankle-jerks, Romberg sign, and
characteristic gait, left no cause for doubting the diagnosis
of Tabes Dorsalis. The blood and spinal fluid both proved
positive to the W. R., though the W. R. in the fluid gave a
negative reaction with 0.1 cm. and became positive with
0.3 cm. or more. The globulin was somewhat increased though
less markedly so than in paresis. The gold sol reaction was
“syphilitic” but weak. It is to be noted that the disease had
run a 12–years’ course before a doctor had been consulted.
The primary infection occurred at 32 years, namely, 11
years before the symptoms began. At the time of his primary
infection, Sanzi had received several years of treatment,
chiefly in the form of mercury by mouth.
1421. What is the value of mercurial treatment of syphilis
in the prevention of tabetic or other forms of neurosyphilis?
“Fournier strove for many years to convince
the medical profession that a syphilitic patient
should be treated for at least two years after his infection,
whether the syphilis seemed latent or patent.
The method of treating only the symptoms he characterized
as the opportunist method; treatment in the
absence of definite symptoms the preventive method, as
preventing the later manifestations. That prolonged
treatment does prevent is shown by Fournier’s figures
analyzing 2396 cases presenting tertiary signs. These
he divides into three groups: Group I, comprising 1878
cases, or 78 per cent of the whole number, having no
treatment or inadequate treatment—that is mercury
for less than one year; Group 2, comprising 455
cases, or 19 per cent, having moderate treatment—that
is, mercury for one to three years; and Group 3,
comprising the remaining 19 cases which represent
only 3 per cent of the whole number, having treatment
for more than three years.”[7]
In the light of what we now know concerning latent
neurosyphilis, it would seem well for patients to be
followed from time to time with the W. R. on blood
and spinal fluid after the supposed completion of the
treatment of primary and secondary syphilis. The
examination of the spinal fluid is not superfluous, as
our experience with the so-called paresis sine paresi
abundantly shows. At the present day it is not good
practice to assure a patient that he is cured after two
years of ordinary mercurial treatment without resort
to frequent spinal fluid tests, even though the serum
W. R. be negative.
143
TABETIC NEUROSYPHILIS (“tabes dorsalis”)
is often quite ATYPICAL clinically and may even
show no single symptom warranting the old clinical
name “locomotor ataxia.”
Case 30. Stephen Green is a case of Tabes Dorsalis with
active knee-jerks and without locomotor or muscle-sense
disorder. When observed at the age of 45, it appeared that
there were but two complaints: lack of control of the vesical
sphincter and shooting pains in the legs. It appeared that
the urinary disorder dated back ten years, when there had
been difficulty in passing the urine. Sounds had been
passed at the time; occasionally there had been incontinence
during after years, ascribed by Mr. Green to the passing of
the sound. However, the physician at that time stated that
the incontinence was a symptom of tabes dorsalis. The
incontinence had recently become worse, especially marked
at night, though also occurring in the day; much worse during
excitement, and very much worse after taking alcoholic
drinks. Besides incontinence, there is also difficulty at
times in passing the urine, as well as dysuria.
As for the pains in the legs, they had been first noticed
some three or four years ago and considered to be mild
rheumatic effects. Now, however, they have grown progressively
worse and have been the effective cause of giving
up business. The pains are sharp, darting, pinching, and
burning, and last, say, about a second with an interval of
about the same length. The attack will continue sometimes
for many hours.
There is a strabismus of the left eye, ascribed by the
patient to an accident with an umbrella (there had been
operation without relief). The pupils showed the Argyll-Robertson
effect and were markedly irregular. Despite the
divergent strabismus with diplopia, the eye movements were
well performed although not in parallel axes. Ankle-jerks
could not be obtained even on reinforcement, but the knee-jerks
144were lively, and the other deep and skin reflexes proved
normal. The blood and spinal fluid tests were characteristic
of tabes dorsalis.
It appears that the syphilis was acquired by this patient
15 years before; that is, 5 years before neurological symptoms
began. Three courses of treatment had been taken at a
well-known watering-place, and mercury pills had been taken
for two years by mouth. The patient is married; has no
children; there have been no pregnancies.
1. What causes may be assigned for the absence of children
in the family of a tabetic? There may be lesions of the
genital apparatus (orchitis, or more specialized toxic
lesions). But impotence such as characterized the
present case must also be taken into account.
2. What is the therapy for tabetic pains? Pyramidon is
nowadays much in favor; morphine may be used;
some authors recommend that the patients be instructed
to chloroform or etherize themselves slightly
for relief of the pain. Surgery of the nerve roots
may be resorted to in extreme cases. Intraspinous
therapy, suggested by various authors, seems to exert
beneficial effect in many cases.
3. Is the lack of control of the vesical sphincter an unusual
initial symptom? On the contrary, the more careful
the clinical observation, according to some observers,
the more likely is the examiner to find that vesical
symptoms were the earliest or among the earliest complaints
of the patient. Baldwin Lucke found sphincter
disturbances to be initial in 8¼% of his long Blockley
series. He found sphincter disturbance to occur in
some stage of the disease in 67.6%, being exceeded in
frequency only by staggering gait (87.2%) and lancinating
pain (71.6%). According to Lucke, the most
frequent initial symptom is lancinating pain in the
lower extremity, which, it will be noticed, occurred
also in our case of Stephen Green as an initial symptom
along with vesical disturbance. Lucke’s figures show
that paresthesia of the lower extremities (17.6%) and
weakness of the extremities (16.4%) are the next initial
symptoms in frequency.
4. Could the early treatment in the case of Stephen Green
be considered as adequate? No better answer can be
given to this question than by quoting from Dr. Joseph
145Collins,[8] who probably has done more than any other
one man in this country in insisting on the need of
proper treatment of syphilis. As to the adequate treatment
of syphilis he says:
“It consists in the proper use of salvarsan and mercury
begun at the earliest possible moment after infection
and kept up till all biochemical evidence of the disease
has ceased, while the metabolism of the individual is
maintained as nearly normal as possible. But the physician
does not do his whole duty when he has accomplished
this. He must solicitously watch the individual
to see that no evidence reappears for months and even
years after the apparent cure. As an index of such reappearance
the Wassermann test of the blood serum and
of the cerebrospinal fluid is the safest guide.
“Until there is a definite unanimity of belief among physicians
as to when the treatment of syphilis shall be
begun, and some concert of action as to what constitutes
the adequate treatment of syphilis, we cannot
hope to make any considerable progress in the prevention
of syphilis of the nervous system, save by educating
the individual toward infection.”
146
TABETIC NEUROSYPHILIS may produce symptoms
chiefly if not entirely in the region supplied
by the CERVICAL plexus (“cervical tabes”).
Case 31. Paul Halleck, 35, was a salesman who had begun
to find it hard to carry his sample case, since he was unable
to tell whether or not he had it in his hand. There was not
only an anesthesia of the hands, but they felt numb and
there was often a tingling sensation. Of late it had become
hard for Halleck to dress himself or to write, and these symptoms
had been slowly growing worse. There was no other
complaint. There was, however, a history of a chancre about
7½ years before, which had been followed by a rash and a
sore throat. There had been treatment with mercury and
potassium iodid alternating for a period of two years.
Physically, there was no evidence of disease except neurologically.
The pupils were unequal (the right larger than the
left) and reacted slowly to accommodation and not at all
to light. A marked ataxia of the hands was shown in coat-buttoning.
The finger-to-nose test showed a marked dysmetria.
Arm-jerks as well as knee- and ankle-jerks were
absent. There was a slight swaying in the Romberg position
but no true Romberg sign. There was no difficulty in
locomotion. Both blood and spinal fluid proved positive
to the W. R.; globulin and albumin were increased. The
gold sol reaction was syphilitic, and there were 85 cells per
cmm.
This case is probably not a pure example of Cervical
Tabes, since the knee-jerks are also absent, and we may
suppose a degree of lumbar spinal cord changes in addition to
the cervical changes. It well illustrates, however, that the
tabetic involvement of the cord may be quite generalized and
that it may strike high as well as low.
147
ERB’S SYPHILITIC SPASTIC PARAPLEGIA.
Case 32. Margaret Neal, a maid-of-all-work, 36 years
of age, was committed to a home for inebriates on account
of her excessive alcoholism, but she was shortly transferred
to the Psychopathic Hospital on account of difficulty with
locomotion. We found a very marked spasticity in walking,
with a characteristic scissors gait. The pupils were somewhat
irregular, and although both reacted to light, the
left reacted far more slowly than the right and the reaction
failed to hold well. The arm reflexes were very active, and
the knee-jerks and the ankle-jerks were particularly exaggerated.
There was a double Babinski reaction, as well as
Oppenheim and Gordon reflexes and a bilateral ankle clonus.
There seemed to be tenderness over the nerve trunks in the
back of the leg, below the knee. There was no evidence of
incoördination, no Rombergism, no disturbance of sensation,
no disorder of the special senses, and not even a tremor of
the tongue or hands.
Mentally, the patient was entirely negative.
Diagnosis: Symptomatically, it is entirely clear that
the patient was suffering from Spastic Paraplegia. One
would have to consider besides spinal syphilis, also amyotrophic
lateral sclerosis, syringomyelia, and spinal cord
tumor. However, there appeared to be no definite wasting
of muscles, and the fact that the sensations were intact seems
to rule out also syringomyelia. There was none of the
characteristic pain associated with a cord tumor. There was,
in fact, a strong clinical premonition that the case was one of
spinal syphilis, simply because syphilis is the most common
cause of spastic paraplegia in the adult. The pupillary
anomalies were also highly suggestive.
The serum W. R. proved to be weakly positive, as was also
the gold sol reaction in the zones characteristic of syphilis.
The spinal fluid examination yielded 14 cells per cmm. There
148was a positive globulin test and a moderate increase in albumin.
The W. R. of the spinal fluid was negative.
1. Why was the spinal fluid W. R. negative in this case of
spinal syphilis? The explanation of negative W. R.’s
in spinal syphilis is not easy. Possibly, however, in
the course of years the intensity of the process has been
reduced and possibly the W. R. has been one of the
first tests to disappear.
2. How shall we explain the nerve trunk tenderness? We
might consider this to be due possibly to an inflammation
about the posterior roots. On the whole, partly
on account of the situation of the pains below the knee,
it seems probable that the nerve trunk tenderness of
this case is the residuum of an alcoholic neuritis.
Treatment: Under injections of mercury salicylate, there
was a rapid improvement. In fact, in the course of several
months, the patient regained an ability to walk long distances.
There still remains a certain spasticity, but the abnormal
spinal reflexes above mentioned are no longer present.
149
SYPHILITIC MUSCULAR ATROPHY, probably
due either to spinal parenchymal lesions, or to root
neuritis, or to both.
Case 33. Joseph Graham, now 50 years of age, seemed
no longer to be able to do good work as a teamster. His
arms had become weak and the muscles had become tremulous
and apparently wasted. There was also pain in the left leg
and hip. It appears that this latter symptom had been
thought to be rheumatism, having begun about 8 years before
with a sudden sharp shooting pain in the left hip, about the
region of the sciatic notch. Graham had rubbed the hip
with liniment, but without reducing the so-called rheumatism.
The trembling of the hands had begun some years later,
but no wasting had been noticed except during the past year.
The pain in the leg had suddenly become so severe that a
month before medical observation he had quit work. The
question immediately arose whether Graham was not
suffering from some familial form of muscular atrophy;
but according to his representations, there was nothing of
the sort in the family.
Physically, there was little to note. Neurologically, there
was more. The pupils were somewhat irregular in outline,
and the right was larger than the left. The left pupil failed
to react to light, and the right pupil reacted very slowly
and with but a slight excursion. There was no tremor of the
tongue and no evidence of facial palsy nor was there smoothing
of the nasolabial folds. It was somewhat remarkable,
that in the absence of these signs, there was a marked speech
defect. The atrophy of arms, forearms, and hands was
well marked, especially the atrophy of the thenar and hypothenar
eminences of the right hand. The extended hands,
especially the right, showed a marked coarse tremor. Fibrillation
was found in the muscles of the hands, forearms, arms,
and pectoral muscles. There was no dysmetria, and the
diadochokinesia was normal. Strength was diminished (dynamometer
150right hand, 32 kg., left 31 kg.). There was little or
no atrophy of the legs, although the left thigh was perhaps
slightly atrophic and the gluteal muscles of the left side
were somewhat flabby. The patellar and Achilles reflexes
were absent on both sides. There was a slight swaying in
Romberg position. Gait was normal. There was a marked
tenderness on the left side of the sciatic notch, as well as
over the entire distribution of both external and internal
popliteal nerves. This area of skin was also hyperesthetic.
There were no other neurological signs on systematic examination.
Diagnosis: The sensory disorder, the speech defect, and
the pupillary abnormalities seem to render the diagnosis
of progressive muscular atrophy doubtful. Nor was there
any dissociation of sensations to suggest a syringomyelia.
Under such circumstances, one must fall back upon the question
of syphilis. Both blood and spinal fluid proved to be
positive to the W. R.; the globulin was increased and the
albumin markedly so; there were 61 cells per cmm., and the
gold sol reaction read 4 4 4 4 3 2 1 0 0 0.
1. Is there a relation of Syphilitic Muscular Atrophy to
amyotrophic lateral sclerosis? Spiller, some years since,
claimed such a relation, and it would seem with some
justice.
2. How shall the present case be classified? There is
evidence of root pains (left hip). We may naturally
suppose that these root pains are reasonably good
clinical evidence of a meningitic lesion, of which the
spinal fluid clinically gave a confirmation. The fibrillation
in this case somewhat suggests, however, a
central origin for the muscular atrophy. Accordingly,
it would be difficult to definitely classify the present case
as either one of meningovascular syphilis or one of
central syphilis. It will be remembered that Head
and Fearnsides classify muscular atrophy under both
these headings.
151
The period of SECONDARY SYPHILIS is frequently
(over a third of all cases?) MARKED BY
approved signs of NEUROSYPHILIS precisely like
those of full-blown paretic or diffuse (meningovascular
non-paretic) neurosyphilis. These signs
occur sometimes in association with severe clinical
symptoms, sometimes without clinical symptoms.
Case 34. John Bennett, 28, was brought to the Psychopathic
Hospital much confused. His brother, who came
with him, said that he had been a very heavy drinker but had
given up drinking about four months before. He had
recently had a cold but was otherwise in good health up to
the night before admission. On this night, Bennett had
become suddenly excited and went into his mother’s room,
at the common home, and began to curse her. However, he
was put to bed safely, but on the next morning began to
moan continuously. After some hours of moaning, he was
brought to the hospital. Here he remained difficult to manage,
being irritable, noisy, and resistive. Questions he either would
not or could not answer, and there was even no evidence
that he understood questions. However, within a few hours,
it was clear that he was slowly coming out of the confused
state. On the following day, it was possible even to rouse
him and get his name. The confusion gradually cleared
still further and, by the end of three days, he had become
mentally absolutely well so far as could be determined.
He then informed us that he had had a chancre about five
or six months before, followed by a secondary skin eruption;
that he had received four injections of salvarsan (the last,
a month before admission) and three injections of mercury.
At about the time of the last injection of salvarsan, he had
developed headache with pain and slight stiffness in the back
of his neck; and a fortnight later, he began to have dizzy
spells, followed during the last week by difficulty in hearing.
There was amnesia for everything that happened after his
152spell of sudden excitement on the evening before admission,
and this amnesia was never lifted for the four days that
followed.
Physically, Bennett was very well built and muscular.
Nor were there any evidences of disease outside the nervous
system. There was some slight stiffness of the neck and slight
pain on movement of the head, which probably ought to be
attributed to meningitis. The neurological examination
showed tendon reflexes all normal, and normal sensations.
There were, in fact, no neurological signs except that both
pupils were dilated; the left was larger than the right. Both
pupils reacted to light but reacted very poorly. They reacted
much better to accommodation.
The W. R. proved to be positive, as might well be expected
in a man whose infection had taken place less than
six months before. The globulin and albumin of the cerebrospinal
fluid were in great excess, of a degree which we
clinically express by ++++. The W. R. of the fluid also
was strongly positive down to 0.1 of a cmm. The gold sol
reaction was the “paretic” type, and there were 228 cells
per cmm.
1. How early may clinical evidence of neurosyphilis set in
after infection? Craig found one case of “brain
syphilis” occurring one month after infection. Frye
claims a case of tabes dorsalis developing six weeks
after infection. Craig states that he has had three
cases of brain syphilis occurring within six months,
and six within a year of infection.
2. What effect did the salvarsan injections have in causing
or preventing the symptoms in this case? Nonne sums
up the neurorecidive question as follows: Since the
introduction of salvarsan therapy for neurosyphilis,
paralyses of various cranial nerves are seen more frequently.
This higher frequency is in part only apparent
since more attention has been paid of late to
auditory and labyrinthine disorders. On the whole,
however, it must be considered that salvarsan does mobilize
spirochete foci which without salvarsan therapy
would perhaps have remained latent. Probably we are
here dealing in some instances with fresh infections of
neurosyphilis, in other cases with a Herxheimer reaction.
153Ehrlich believed that these latent foci occur particularly
in places with stagnant blood current; as, for
instance, in the narrow bony canals. This hypothesis,
sufficient in some instances, is less satisfactory for cases
of peripheral neuritis, for example.
3. What treatment is indicated? Intensive antisyphilitic
treatment is strongly indicated. Whatever may be the
truth concerning the production of neuro-recurrences
(“neurorecidives”) it is certain that the symptoms
usually vanish with a continuance of salvarsan therapy.
The important point is to give efficient treatment, and
in a case like Bennett’s improvement is fairly certain
unless some serious insult occurs before the remedial
efforts have been given time. It is still an open question
whether intraspinous treatment is more efficient
in such cases than intensive intravenous injections of
salvarsan. In Bennett’s case diarsenol was injected
intravenously twice a week in 0.6 gm. doses, reënforced
with intramuscular injections of mercury salicylate and
potassium iodid by mouth. Under this treatment improvement
began slowly and in a few months he was
symptomatically well and after three months his tests
were practically negative.
154
JUVENILE PARETIC NEUROSYPHILIS (“juvenile
paresis”) with OPTIC ATROPHY.
Case 35. Mary Coughlin, a blind girl of 16 years, was
brought to the hospital in a state of great excitement, laughing
and crying alternately. The neurologist is entitled to
think of blindness, and particularly of the optic atrophy
which Mary showed, as probably due to syphilis. However,
there was no history of syphilis in the father, who died in an
accident at the age of 40, or the mother, who died at 45, of
heart trouble. An elder sister was married and well; two
younger sisters were living and well. The fifth sibling, a
boy, had died in infancy. There had been no miscarriages.
In fact, the only point in favor of syphilis was the somewhat
far-fetched point that the younger brother of the patient
had died in infancy.
The patient’s history was rather suggestive of some other
diagnosis. Her birth had been normal, she walked and
talked at 13 months, was at school from six to twelve, reaching
the seventh grade, and was considered bright. At three
years of age, she had been run down by a car and dragged
under the fender for a considerable distance. Her head was
hurt but the patient did not lose consciousness in the accident.
Fainting spells began at 11, in which spells the patient would
lose consciousness for a minute or two. About this time, the
patient’s eyesight had begun to fail, and for some four years
she had been entirely blind. Headaches had come on of late.
The Coughlin case, except for the above-mentioned suspicion
of syphilitic optic atrophy, might be regarded as an
unusual example of a post-traumatic disease.
We found her to be fairly well developed and nourished;
there was a deformity of the lower half of the sternum and of
the third and fourth ribs on the right side. There were no
other physical phenomena found upon systematic examination.
The left pupil still reacted to light; the right failed to
react, but this lack of reaction could not be regarded as of
155Argyll-Robertson nature on account of the finding of optic
atrophy with the ophthalmoscope.
Mentally, it appeared that the patient’s retention of
school knowledge was poor, though her blindness for four years
had doubtless given her little opportunity to keep such information
fresh. Rather strangely, Mary gave utterance to
many delusions: first, expecting to receive her sight by an
operation on the head; second, to write a book of her doings;
third, to buy a house for the children; fourth, would pay
$3000 for the house, earning the money by working at a
tailor’s or as a trained nurse; fifth, to go on the stage to earn
money by dancing; sixth, will have lots of money.
One of Mary’s characteristic statements is as follows:
“Won’t it be lovely when I can see Dr. H.’s face in heaven or
some other lovely place? Dr. H. was a grand doctor to me,
and when we get together again we are going to Tremont
Temple and keep us together. I am going to do some dancing
and play the piano. I am going to graduate at the high
school and go to Trinity College in Washington, and I hope
I shall be a faithful keeper of mother’s tomb.”
The patient was at times euphoric and expansive.
At this stage, what with optic atrophy, euphoria, and
expansive delusions, we should perhaps be entitled, had Mary
been an adult, to offer the diagnosis General Paresis. In
fact, on the whole, any other than a syphilitic cause for the
optic atrophy was exceedingly doubtful. Brain tumor of a
nature to produce optic atrophy might very improbably last
so long as five years. There was no evidence of any intoxication
at the time when the blindness occurred.
The W. R. was positive in the blood and spinal fluid;
there was a positive globulin test, and an excess albumin
as well as 15 cells per cmm.
1. What is the significance of Mary’s trauma at three years?
So far as we are aware, none.
2. What light could be thrown by a W. R. study of the
family? In some instances, much light is thrown; in
the present case all three living sisters of the patient
have been examined and their serum W. R.’s have been
found negative.
1563. What is the prognosis of juvenile general paresis? Death
within a few years, as in general paresis in adults.
The patients live rarely more than four or five years after
the onset of symptoms. Mary Coughlin died a year
and a half after the above examination, namely, in her
eighteenth year, some seven years after the onset of
symptoms.
4. What can be said of treatment? A few favorable results
have been reported after intraspinous therapy (Swift-Ellis).
Too little work has been done with systematic
treatment of juvenile neurosyphilis, both paretic and
non-paretic, to permit important conclusions at this
time.
5. How can we explain the infection of this sibling whereas
the others, both younger and older, escaped? It would
seem that we would have to discard the hypothesis of
a congenital infection and consider that it was acquired
accidentally during the lifetime of the patient. Considering
the prevalence of syphilis it is rather to be
wondered that more such cases of “innocent” infection
do not occur in children. We may recall how many
instances of juvenile gonorrhea occur. In a case as
this where the symptoms calling attention to syphilis
necessarily occur so long after the original infection it
is practically impossible to trace the origin of the
infection.
157
The diagnosis of JUVENILE PARESIS is often
easy.
Case 36. Theresa Mullen, an under-sized girl of 12 years,
presented a remarkable appearance due to congenital amputations
of the fingers and toes. She lay in bed, drivelling
and making unintelligible cries. It appeared that the patient
weighed about 12 pounds at birth and was very fat; that
she had been fed on condensed milk, had survived cholera
infantum, whooping cough, and, as the parents said, “two
kinds of measles.”
Theresa had gone to school at 5 years, reaching the third
grade at the age of 9; but at this time, she began to lose
ground and was put in a class for backward children. Moreover,
at about this time, the teachers noticed spells of causeless
laughter and meaningless twisting back and forth.
Theresa would also scream at night, looking about the room;
once, rising and crying, “Take him away, that black thing,”
though no appropriate object was present. There had been
little or no complaint of headache. Theresa had been deteriorating
for some time, and for a year past had been
having increased difficulty in walking. For two months the
child had not spoken intelligible words; for the last week,
she had been incontinent.
The diagnosis was almost obvious from the manual and
pedal deformities taken in connection with the saddle-back
deformity of the nose. It was interesting in connection with
the contentions of W. W. Graves, that the scapulae were
scaphoid in type.
Accordingly, the history given by the parents seemed
consistent enough. The parents were both 36 years of age,
having married at 23. The first pregnancy was a miscarriage
at two months, of unknown cause. Theresa came next;
thirdly, came a miscarriage at three months; fourthly, a
girl, who is not strong or well physically, has suffered much
from headaches and sore throat, but is fairly bright. The
158fifth pregnancy resulted in a boy, who is bright but of under-size.
Three more pregnancies resulted in miscarriage.
Taking into account the above-mentioned physical characteristics,
the personal history, and the family history of
Theresa, the diagnosis could hardly be in doubt even in the
absence of a lack of pupillary reaction to light on the right
side, infantilism of genitalia, positive W. R.’s of serum and
spinal fluid, positive globulin, and excess albumin, 34 cells
per cmm. and the paretic type of gold sol reaction which
were found.
The prognosis of this case appears to be rapid deterioration,
terminating in death within a few months. Now and again,
however, some such cases spontaneously improve. Such a
case as that of Theresa Mullen is always disheartening in
itself but suggests the social value of Wassermann tests in the
other members of the family. The other children of the Mullen
family proved to be suffering also from syphilis, since
their blood sera all showed a positive W. R.
1. What is the characteristic age of onset in Juvenile
Paresis? An impression has prevailed in some quarters
that the typical onset of juvenile paresis is in the adolescent
years, and Clouston’s first case (1877) developed
in a boy of 16. Thierry’s 58 cases, developing from the
8th to the 20th year, averaged 14 years of age at onset.
Mott’s 22 cases from the 8th to the 23d year, averaged
17 years at onset. According to Clouston, juvenile
paresis develops most often at puberty (15 to 17 years).
It is sometimes claimed that cases developing symptoms
early live longer, and that juvenile cases developing
symptoms after the 20th year run a short course. For
a case developing in the 5th year, see John Friedreich,
Case No. 77.
2. What may be concluded from the physical signs (congenital
amputations) present in this case before the
development of mental symptoms? Some cases of
juvenile paresis appear to show no physical signs whatever
in childhood. While these amputations might be
the accidental result of a difficult delivery, it is more
probable that they are due to a syphilitic process.
Juvenile paresis—congenital amputation of digits. This case reached fourth grade in school before deterioration.
159
CONGENITAL SYPHILIS is apparently capable
of producing simple FEEBLEMINDEDNESS (that
is, a form of disease non-paretic, non-tabetic, without
special tendency to progression, and without
tendency to vascular insults).
Case 37. Isaac Goldstein was a small boy of six years and
seven months, with a father known to be suffering from general
paresis. The child was very irritable and nervous and
very difficult to manage, but would hardly have been the
subject of medical attention except in a family study suggested
by the paresis of the father.
The child had been born at term and had apparently
undergone a normal development. Physically, he showed no
definite signs of congenital syphilis. In fact, the physical
examination was to all intents and purposes negative. The
W. R. of the serum, however, proved to be positive. Mental
tests showed that his mental age was that of a child of a
little over five years. Taking all things into account, it is
probable that he should be regarded, therefore, as somewhat
retarded mentally.
1. Is syphilis answerable for the mental retardation in this
case? Provided that the family is free from feeblemindedness
and mental disease, it would seem that
the retardation of a congenital syphilitic should perhaps
be regarded as syphilitic in origin. Of course, the
institutions for the feebleminded have not shown exceedingly
high percentages of syphilitic children in
various W. R. surveys; still, the percentage of positive
reactions in institutions for the feebleminded is clearly
higher than the incidence of congenital syphilis shown
in the population at large. Hence, we may conclude
that syphilis is one of the etiological factors in the
production of feeblemindedness. Dr. W. E. Fernald,
of the Waverley School for the Feebleminded, has recently
pointed out that the syphilitic cases belong
rather in the lower grades (idiots and imbeciles) of
feeblemindedness than in the higher (morons).
1602. Can we guess what the pathological anatomy and histology
of the brain may be in such cases? The Waverley
studies now in process seem to indicate that some
cases have little or no gross alterations, but show a few
slight traces of lymphocytic accumulations discovered
upon extended search, and a certain tendency to the
appearance of rod cells in various foci. But the whole
matter is still sub judice. It is a question whether
these traces of chronic inflammation are the residuals of
a more active process or the beginnings of a process that
is about to be more active.
3. How characteristic is a positive W. R. in the serum of a
child without physical stigmata of congenital syphilis?
If we limit the term stigmata to the major and more
important signs, we must reply that it is not unusual
to find positive W. R.’s in sera of physically normal-looking children. Except in family studies, such
cases will often escape notice, either because there
are no stigmata whatever, or because such stigmata
as exist are of a minor nature and regarded as unimportant
anomalies. Some of these cases occur in the
clinics later in life as so-called syphilis hereditaria tarda.
If one wishes to discover these cases with late development
of symptoms before their full bloom, the
most obvious method is to examine carefully the children
of known syphilitics.
161
JUVENILE TABETIC NEUROSYPHILIS (“juvenile
tabes”); TREATMENT.
Case 38. The point in presenting Archibald Sherry, a
Juvenile Tabetic of 12 years on admission, is perhaps
to exhibit pride in therapeutic results.
There was little or no doubt of the diagnosis; in an adult,
the phenomenon would be called tabes dorsalis with a question
of general paresis. The right pupil was larger than the
left and reacted neither to light nor to distance. There was
a slight tremor of the tongue and of the outstretched hands.
The knee-jerks and ankle-jerks could not be obtained, nor
could the periosteal reflexes in the legs. There was a slight
unsteadiness in the gait and in various finer movements, and
a slight ataxia of the legs. There was not a classical Romberg
sign but there was slight swaying in Romberg position. The
teeth were Hutchinsonian. For the rest, the physical examination
was practically negative.
The family history was of interest. On the paternal side
there was nervousness as well as alcoholism and degeneracy.
The maternal grandmother had cancer. Archibald’s father
was immoral and alcoholic. There was a girl four years
older than Archibald, who, though nervous and unstable, has
shown no signs or symptoms of syphilis and does not yield a
W. R. in blood or spinal fluid.
Archibald himself was born at term, a large child, who,
however, lost weight rapidly, developing a marked skin
eruption on head and back three weeks after birth. This
skin disease lasted for a month and a half and then spontaneously
disappeared. Archibald remained weak and sickly,
not walking until three years of age. However, he did well
in school up to the end of his 11th year, when he failed to
keep up with the children. He had been an amiable child
and had gotten on well with his playmates. Some time in
his 10th year physical disability had begun; there was numbness
in the legs with weakness; at times, actual inability to
162walk. The right pupil was noticed by the mother to have
increased in size; the eyelashes had turned white. There
was pain over the left eye and a feeling of weight on top of
the head. Speech became difficult or even confused.
Consistently enough, the W. R. both in blood and spinal
fluid was positive. Globulin and albumin were present in
large amounts; there were 150 cells per cmm.
Granting that this be in some sense a case of juvenile
tabes we may raise a doubt whether the case is one of congenital
syphilis. The W. R.’s of the blood of both father and
mother are negative. Syphilis is denied by them. The
nervous and unstable older sister failed to show definite
symptoms of syphilis or a positive W. R. There had been no
miscarriages or stillbirths. The question arises whether the
Hutchinsonian teeth do not indicate congenital syphilis. It
appears, however, that it is possible to develop Hutchinsonian
teeth if syphilis is acquired before the teeth are formed. We
have no data as to how or why this particular baby should
have acquired syphilis, if he did so acquire it, at the age of
three weeks. On the whole, sceptics may doubt our suggestion
that the case is one of acquired juvenile tabes. Possibly
the question is academic so far as treatment is concerned.
Prognosis: The rarity of juvenile tabes is such that little
can be said as to prognosis. Three and a half years have
passed since a few injections of salvarsan were made. The
pains above mentioned rapidly disappeared, the gait became
steadier, the attacks of confusion ceased, and the speech improved.
Unfortunately, on account of a lack of coöperation
on the part of Archibald’s mother, we have been unable to
continue treatment. However, we have from time to time
followed the patient in his home and he seems to have shown
no falling back after the initial improvement. It would be of
great value could we know the situation in the spinal fluid at
the present time.
1. Is there any explanation why paresis should occur in
some juveniles and tabes in others? There is no
available explanation for this difference nor any for
the characteristic early optic atrophy of juvenile
tabetics.
164
Be frustrate, all ye stratagems of Hell,
And, devilish machinations, come to nought!
Paradise Regained, lines 180–181
165
This part of the case collection, dealing with puzzles and
errors, is ushered in by six cases (39–44) drawn from a group
of errors in diagnosis made some years since at the Danvers
Hospital. These six are autopsied cases. Attention is called
to the fact that modern methods of diagnosis might have
prevented the errors.
DIFFUSE NEUROSYPHILIS (“cerebrospinal
syphilis”) versus PARETIC NEUROSYPHILIS
(“general paresis”). Autopsy.
Case 39. Caroline Davis, dead at 49 years, was a case
of error in the diagnosis of general paresis. Like Cases
40 to 44, Case 39 was diagnosticated by the full Danvers
staff as a case of general paresis; however, it must be added,
before the days of the W. R. and the modern methods of
systematic diagnosis. As will transpire in the sequel, there
is a large question whether Case 39 is not after all really a
case of neurosyphilis, possibly not of the paretic group.
The details are as follows:
Caroline Davis was a normal school girl till 15, apt in
studies, mill worker till marriage at 18; one child, dead
(cause unknown). Habits good. Moderate deafness set in
in the forties and in 1901 patient became completely deaf
in three months’ time. In 1905 she became unable to take
care of her house and had a shock in which the right leg was
affected.
On commitment patient showed good development and
nutrition with slight enlargement of capillaries of cheeks,
redness and roughening of skin of right ankle. Teeth
166absent. Slight radial and brachial arteriosclerosis. Urine
negative. Sluggish pupil reactions to light both directly and
consensually. Deafness absolute, bone conduction defective.
Arm reflexes brisk, knee-jerks equal, brisk. Bilateral Babinski
reaction more marked on the right side, tremor of
tongue, Romberg’s sign, gait defective. Speech stumbling,
writing clear, without tremor.
Communicated by writing only. Consciousness normal,
disorientation for day of month, for place (misnames hospital)
and for persons (recognizing nurses, not patients).
Patient wrote many letters complaining of pain, headaches
and especially of pain in the abdomen and side. The patient
was thought to show a slight defect of memory, but her
deafness rendered diagnosis difficult. The patient died
suddenly on May 23, 1908, shortly after supper, falling backwards,
and dying in five minutes with marked respiratory
distress.
Post Mortem Findings. The cause of death was not clear.
The heart’s blood and cerebrospinal fluid were sterile. There
was a small hemorrhage in the anterior part of the right
ventricle derived from a small artery of the caudate nucleus.
There was about 400 cc. of blood between the dura mater and
the pia mater. There was a slight sclerosis of the basal and
Sylvian arteries. The brain substance was uniformly softer
than normal.
It is possible that the hemorrhage had taken place some
time before the patient’s fall and that the brain substance
had swollen in consequence. Just before the fall she had a
weeping spell.
The anatomical diagnoses were as follows:
Obesity, unequal pupils, fresh wound near left ear, edema
of legs, slight focal adhesive pleuritis, hypostatic congestion
of lungs, chronic endocarditis, chronic myocarditis, congestion
of kidneys, congestion of pancreas, subacute splenitis, chronic
adhesive pelvic peritonitis, hematoma and cystic condition of
Fallopian tubes, calvarium dense and thick, subdural hemorrhage,
slight chronic leptomeningitis, general cerebral atrophy,
marked in tips of frontal lobes, old cyst of softening
between left corpora albicantia and optic chiasm, small
167punctures of left ear drum, drums opaque, chronic spinal
leptomeningitis; brain weight, 1190 grams.
There were marked firm interadhesions between dura and
pia throughout. A lumbar puncture soon after admission
in 1907 had shown:
|
Per cent |
| Endothelial cells |
10 |
| Lymphocytes |
30 |
| Plasma cells |
0 |
| Phagocytes |
0 |
| Polymorphonuclear cells |
51 |
| Unclassified |
9 |
| Fibroblasts |
0 |
| Cells in 100 fields |
125 |
It will be noted that the lumbar puncture yielded no
plasma cells and yet showed 30% of lymphocytes. Alzheimer,
in 1904, attempted to distinguish the histology of the
cerebral syphilitic from that of the general paretic, maintaining
that lymphocytosis was the characteristic feature of the
ordinary neurosyphilitic, whereas plasma cells were associated
with the lymphocytes in the paretic. This case showed lymphocytic
deposits. To be sure, they were decidedly subordinate
in the cerebral cortex, cerebellum, and basal ganglia,
to the marked evidences of nerve cell destruction, although
there were perivascular infiltrations about a few of the larger
vessels in the white matter of the cerebral cortex.
The spinal cord, however, showed a most severe infiltration,
especially in the gray matter, where the infiltration
accompanied severe nerve cell changes and arterial changes.
The pia mater of the spinal cord was also packed with mononuclear
elements, among which, however, no plasma cells
could be found.
But although the inflammatory changes in the shape of
lymphocytosis were relatively more prominent in the spinal
cord than in the cortex, yet the cortex yielded evidence of an
exceedingly marked destructive process. Perhaps no layer
of any of the areas of the cortex examined failed to show some
atrophic alteration. The upper layers of the cortex were
everywhere more severely diseased than the lower layers.
Here we are dealing with an instance of an active meningomyelitis
168and subcortical encephalitis. It is, of course, probable
that the W. R., had it been performed, would have been
positive in this case. On the basis of the histology, we are
inclined to regard the clinical picture in this case as belonging
among cases of Non-paretic Diffuse Neurosyphilis.
This case, as also the next several, is especially instructive
in teaching the difficulty in differentiating paretic and non-paretic
neurosyphilis. Not only is this difficulty met in
clinical diagnosis, but in pathological diagnosis as well.
The histological diagnosis depends in large part on the
work of the Nissl-Alzheimer school, which has received great
recognition. At the present time, however, there is beginning
to be considerable doubt as to the entire validity of this
teaching. At any rate there are many borderline cases in
which the differentiation is well nigh impossible. In this
case note chronic meningoencephalitis, with cortical degeneration,
in the absence of plasmocytosis.
From the clinical standpoint the intensity of the W. R.,
the character of the gold sol reaction, and the result of
therapy have added new points in differentiation. Much
more work controlled by autopsies is still needed, however,
to put us on sure ground in borderline cases.
169
VASCULAR NEUROSYPHILIS(?) versus PARETIC
NEUROSYPHILIS (“general paresis”). Autopsy.
Case 40. Case 40 like Case 41 was an error in the diagnosis
of general paresis which might be regarded as academic
rather than practical. Both were cases of arteriosclerotic
brain disease with severe cerebellar involvement. Case 40
had a spinal cord that was not quite normal. There was a
tabetiform lesion in the cervical spinal cord (not elsewhere),
together with a unilateral degeneration suggesting in some
respects a radicular origin. The most striking feature, however,
of Case 40 as in Case 41, was a lesion of the cerebellum.
In Case 40 the dentate nuclei were in large part destroyed
by cysts of softening, although the cerebellar cortex was
fairly well preserved on both sides. The details of Case
40 are as follows:
H. F., male, gear maker, born 1850.
Heredity. Maternal grandmother insane. Mother insane
at 52, became demented and lost use of limbs, died at 71.
Aunt insane.
Personal History. Common school education. Capable
workman till within a few months. Early in life alcoholic.
Drunk almost every week until 1899 or 1900. Irritable,
nervous, selfish, loose in relations with women. Venereal
disease denied by wife. Married in 1883. Three frail
children. No miscarriages. Neuralgia in 1901 or 1902.
January, 1904, patient left carriage shop on account of
mistakes in work, became more pleasant, childish, fearful,
talkative, did funny things, later became vagrant, stole from
fruit stores, smoked cigarettes picked up in the street, and
became restless and irritable.
Committed to Danvers, June 24, 1904, with slightly
enlarged heart, somewhat heightened blood pressure, and a
slight sediment of epithelial cells in urine.
Romberg’s sign was present, but there was little or no
demonstrable incoördination otherwise. Very slight tremor
170of fingers. Left knee-jerk absent, right obtained on reinforcement.
Achilles jerk absent. Triceps, wrist and
normal plantar reflexes present. Pupils react to accommodation,
but very slightly, if at all, to light. Sensations normal
except in legs. The legs show preservation of tactile and
temperature senses, but abolition of pain sense except over
dorsum of foot.
Speech showed slurring of syllables and “brigrade” for
“brigade.” Disorientation for time, place and in part for
persons. Admitted that his work had been deficient but
regarded himself as well. Emotionally variable, crying at
times and suddenly becoming jocular. Eloped July 3 and
somehow reached his wife’s house in a neighboring city.
Euphoria persisted. The pupils continued Argyll-Robertson,
and the knee-jerks remained absent. Became oriented
for place and partially as to time (month and day of week
correct).
During 1905 failure became rapid, with ataxia of legs,
persistent euphoria, and loss of weight.
Convulsions, regarded as general paretic, developed in
1906. Death sudden, December 7, 1906.
Post Mortem Findings. The cause of death was streptococcus
septicemia, probably derived from a gangrenous
bronchopneumonia or related with a small thrombus of the
right auricular appendix. There was also an acute purulent
otitis media, mastoiditis and sphenoidal sinusitis, as well as
extensive decubitus. From this decubitus or from the
intestinal tract may have been derived the numerous colonies
of bacillus coli communis which developed on plates from the
cerebrospinal fluid.
Arteriosclerosis was little in evidence, being confined to
the coronary, right vertebral and carotid arteries (slight in
all). Cysts of softening existed in the posterior part of each
dentate nucleus and may probably be interpreted as indicating
vascular disease.
Chronic disease outside the nervous system was prominent
and in part suggestive of senile findings; milky patches of
pericardium, adhesions about liver and gall-bladder, adhesions
about spleen, adhesions and fibrous thickening of parietal
171peritoneum, adhesions in both pleural cavities, chronic diffuse
nephritis, hypertrophy of bladder wall, dense calvarium, dural
adhesions.
The nervous system showed several unexpected features.
The absence of chronic leptomeningitis was striking: the pia
mater was everywhere delicate and transparent except that
the walls of the cerebellar and chiasmal cisternæ were thickened
and that there were slight opacities along the sulcal
veins of the convexity. Brain weight 1090 grams. There
was a generalized sclerosis and pigmentation of the cerebral
cortex. The sclerosis varied in degree and was most marked
in the prefrontal regions, the anterior halves of the superior
frontal gyri, the middle third of the right precentral gyrus,
the region of the splenium on the left side, and the sagittal
rami. If the bacillus coli communis found in the cerebrospinal
fluid had any effect upon the consistence of the brain,
obviously hard to prove in a brain of leathery consistence at
the outset, it was shown only in the right Rolandic area in the
vicinity of the sclerotic part of the precentral gyrus. Granular
ependymitis of all ventricles. Weight of cerebellum, pons
and bulb, 135 grams.
Perhaps the most remarkable feature of all in the case was
the occurrence of cysts of softening in the posterior part of
each dentate nucleus. For discussion, see Case 41.
172
VASCULAR NEUROSYPHILIS (?) versus
PARETIC NEUROSYPHILIS (“general paresis”).
Autopsy.
Case 41, like Case 40, was one of arteriosclerotic brain
disease with severe cerebellar involvement. Here is another
case in which the Danvers staff made a diagnosis of general
paresis without dissenting voice. There were some tabetic
symptoms, and the spinal cord at autopsy did show a moderate
lymphocytic infiltration of the meninges, entirely consistent
with the picture in the spinal fluid. In this case, the dentate
nuclei of the cerebellum were not destroyed as in Case 40,
but were affected by cell atrophies of variable degree in different
parts of the nuclei. There was also a severe gliosis of
the cerebellar cortex. The left hemisphere of the cerebellum
was more severely diseased than the right. The cortex
showed far more marked and generalized cell atrophies
throughout the layers than did Case 40. The details of this
case, which was that of a colored coachman, Samuel North,
are as follows:
He was born in 1871. Learned to read and write at school.
Stableman and coachman. Alcoholic till 1902. Took much
quinine, possibly impairing hearing thereby. Memory impaired
and growing worse since 1902. Gait unsteady for a
longer but unknown period. August 13, 1907, wandered
about, instead of attending boot-black stand, muttered,
talked incoherently. In the next few days talked about
religion and apparently had hallucinations of hearing. Committed
August 16, 1907.
On commitment stoop-shouldered, flat-chested. Gait staggering.
Unsteadiness in Romberg’s position. Incoördination
of arms and fingers. Coarse tremor of tongue. Tremor
of lower jaw. Exaggeration of left knee-jerk and diminution
of right. Exaggerated Achilles jerks. Spurious left ankle
clonus. Questionable Babinski reaction of left side. Abdominal
and epigastric reflexes present but cremasteric
173absent. Left pupil smaller than right and fails to react to
light. Reaction of right pupil sluggish. Moderate defect of
hearing of both sides.
During the first week the patient developed hallucinations
of sight and hearing, but of no other senses. Disorientation
for time, place, and persons. Answers to arithmetical
problems given with assurance but as a rule incorrectly (as
17 and 32 are 90; 18 divided by 3 is 88). Handwriting
scarcely legible. Memory poor, especially for recent events
(recalled a lumbar puncture as an exercise in baptism).
Impressibility and attention poor. Euphoria.
Death after gradual failure July 29, 1908.
| Lumbar puncture showed: |
Per Cent. |
| Endothelial cells |
9 |
| Lymphocytes |
81 |
| Plasma cells |
6 |
| Phagocytes |
0 |
| Polymorphonuclear cells |
4 |
| Unclassified |
0 |
| Fibroblasts |
0 |
| Cells in 100 fields |
700 |
Post Mortem Findings. The cerebrospinal fluid showed
a pure culture of Bacillus coli communis, and the heart’s blood
showed many colonies of an unidentified bacillus. Culture
from mesenteric lymph nodes sterile.
The cause of death is somewhat in doubt. There was an
early pneumonic process with fibrinous pleurisy, and there
was an early acute hemorrhagic ileitis with a very slight
overlying peritonitis and slight corresponding enlargement of
mesenteric lymph nodes. There was an infection of the
meninges with Bacillus coli communis.
Evidences of chronic disease outside the nervous system
were: coronary and pulmonary arteriosclerosis, chronic
fibrous endocarditis, mitral sclerosis, aortic sclerosis with
calcification, chronic splenitis, chronic interstitial nephritis,
hepatic atrophy (wt., 900 grams), thickening of cartilaginous
portion of right auricle (old trauma), scars of apices of lungs.
The calvarium was dense and the dura mater everywhere
adherent. The arachnoidal villi were but slightly developed,
174but there was one small focus of cortical herniation through
the dura mater of the left middle cranial fossa. The pia
mater was delicate except for slight opacities along sulci.
There was some pial thickening over the region of the interparietal
sulci on both sides. There was pial pigmentation
anteriorly and superiorly.
There is no gross evidence of intracranial arteriosclerosis,
except (1) that afforded by the lesions of the dentate nuclei
of the cerebellum mentioned below and (2) the swerving to
the right of the basilar artery, possibly due not to arteriosclerotic
lengthening of the artery but to an unusual shape of
the pons (see below).
The brain weighed 1245 grams (cerebellum and pons 165
grams). The anatomical diagnoses of central nervous system
were:
Slight general encephalomalacia (post mortem imbibition
of fluid, 31 hours). Slight gliosis of right prefrontal and
frontal gyri. Slight gliosis of right optic thalamus. Generalized
granular ependymitis, especially near fornix and about
foramina of Monro. Anomaly of pons (not gliotic, but
possessing far more white matter on the left side than the
right). Severe arteriosclerosis confined to the dentate nuclei
of the cerebellum.
As we now look over the data in Cases 40 and 41 we are
inclined to ask the question, whether modern systematic
diagnosis would not have shown these cases to be Neurosyphilitic?
One is inclined to answer this question in the affirmative,
on the basis that Case 40 showed somewhat questionable
Argyll-Robertson pupils, and Case 41 showed unilateral
Argyll-Robertson effect. Both cases showed Romberg sign,
but the dentate nucleus and other cerebellar disease in each
case may in some way have contributed to or imitated this
phenomenon. Whether Case 40 was a tabetic must remain
a question, but Case 41 must be regarded as a case with spinal
and meningeal changes highly characteristic of syphilis.
175
VASCULAR NEUROSYPHILIS plus TABETIC
NEUROSYPHILIS (“tabes dorsalis”) simulating
paretic neurosyphilis (“general paresis”). Autopsy.
Case 42. The case of Elizabeth Brown was at one time
carefully studied by Dr. A. M. Barrett in his work on mental
diseases associated with cerebral arteriosclerosis and, like
Case 43, was one in which tabes dorsalis was a factor. Elizabeth
Brown’s maternal grandfather and mother were insane;
there had also been insanity in a sister. Mrs. Brown was
struck on the head at 44, and was unconscious for an
hour, but there were no sequelae to this accident. At 48,
there was a shock, or apoplectiform attack, followed by
unconsciousness for two hours and by left hemiplegia, right
ptosis, and thick speech. Mrs. Brown began to walk again
after two weeks, but was found to be forgetful and fabulatory.
She seemed at times to be hearing music, and somewhat
repeatedly became helpless and unable to walk. She could
not remember from day to day, showed incontinence of urine
and feces, and was brought to the Danvers Hospital. The
physical and mental deterioration was progressive. There
were some signs of organic brain disease. The musculature
was especially flabby on the left side. The left angle of the
mouth drooped, and the left nasolabial fold was smoothed
out. The arm movements were ataxic, the tongue protruded
to the left, the right pupil reacted but slightly to light (eye
blind from cataract), the knee-jerks, Achilles, wrist, and
elbow reflexes, were absent. The patient was unable to
stand, and there was a marked tremor of the hand, tongue,
and lips. There was a zone of anesthesia for pain and
tactile stimulation extending round the body, from the 3d
to the 6th rib, and there were symmetrical areas of anesthesia
on the inner surface of the forearms and the legs.
The autopsy showed a general arteriosclerosis with chronic
and acute meningitis. The brain weighed 1110 grams;
176the pia mater was moderately thickened; the basal vessels
were highly arteriosclerotic. The brain itself, however,
normal externally, upon dissection, showed a number of
small cysts irregularly scattered in the white substance.
The basal ganglia were porous, and there were several small
cysts in the pons. Microscopically, there was evidence of
severe vascular disease, involving not only the arteries but
also the veins. It was the superficial rather than the deep
arteries that were more often attacked. There was a marked
perivascular gliosis. Extensive search yielded no evidence
of lymphocyte infiltrations, either in the brain or in the spinal
cord.
The spinal cord showed degenerations in both the lateral
and posterior columns, of which the explanation may possibly
be like that in our paradigm, Case 1.
Is the case of Elizabeth Brown one of neurosyphilis? We
cannot definitely say on account of the non-availability of
the modern systematic tests, but it may well be that the case,
although certainly not one of paretic neurosyphilis, was one
of Tabes with Vascular Complications.
177
TABETIC NEUROSYPHILIS (“tabes dorsalis”)
with symptoms of cerebral origin producing a picture
resembling taboparetic neurosyphilis (“taboparesis”).
Autopsy.
Case 43. Robert Allen was the fifth case of error in the
diagnosis of general paresis analyzed some years since from
the staff meeting records of the Danvers Hospital. The
Allen case resembles the case of Elizabeth Brown in that
there was a combination of tabetic phenomena with cerebral
lesions of a non-paretic character at autopsy. But although
there seemed to be an utter absence of inflammatory
cells (lymphocytosis) in the case of Elizabeth Brown (42),
there were some slight perivascular cell accumulations in
the Allen case, with a few mononuclear cells suggestive of
lymphocytes. The cerebrum, however, failed to show plasmocytosis.
It was seriously diseased, showing a marked
neuroglia proliferation about the atrophic nerve cells.
Robert Allen was a printer coming from a long-lived race.
The following are the main facts:
Married in 1875 (two children, healthy); again married in
1893 (one child, healthy). Compositor from 1890. In 1898
and 1899 girdle and lancinating pains. Thereafter for
several years gait was unsteady. During 1904 and 1905
freedom from pains and improvement in gait but gradually
increasing irritability and nervousness. Stopped work on
last of March, 1905, owing to sudden increase of irritability,
emotionality, boastfulness, expansive schemes, and ataxia.
Habits: no tobacco, very little alcohol at long intervals.
No drug habits, no sexual irregularity known.
Committed to Danvers April 3, 1905, with slight muscular
development, poor nutrition, acne, irregular, poorly preserved
teeth, gingivitis, flat-foot, slight radial arteriosclerosis, slight
arcus senilis, a few hyaline casts, leucocytes, epithelial cells,
and trace of albumin in the urine, scar in sulcus, and enlarged
inguinal lymph nodes.
178Ataxic gait, Romberg’s sign, fibrillary twitching of chest,
abdominal and facial muscles when standing; right pupil
slightly larger than left, pupillary margins irregular, light
reactions (electric bulb test) both consensual and direct
absent, slight pupillary reaction in accommodation; biceps,
triceps and wrist reflexes lively and equal; abdominal, cremasteric
and plantar reflexes normal, knee-jerks, Achilles
and front taps negative even on reinforcement.
The patient himself stated that his ataxia began in 1904,
that he had been under treatment for swelling of legs and
feet and pain in limbs since 1903, and that there had been
some trouble with limbs since 1895. He had been told that
his disease was lead-poisoning. About three weeks before
commitment patient said he had had an attack of unconsciousness.
The patient’s speech showed considerable defect. Words
were pronounced slowly with slurring and tripping especially
of the labials. Orientation perfect. School knowledge well
retained. The easier arithmetical problems were accurately
performed. Memory imperfect for minor recent events.
Estimations of space and time often very imperfect. Variability
of mood, sometimes euphoric, sometimes tearful and
irritable. Occasional expansive estimates of personal powers
(“Can lift three five-hundred pound weights with one finger”).
Indistinct expansive financial ideas.
The patient continued oriented, euphoric, expansive,
untidy, till October, 1905, but on October 12 developed an
infection at the site of a callus on the sole of the foot and died
with pyemic symptoms, October 17.
Post Mortem Findings. The cause of death was streptococcus
septicemia with acute ulcerative colitis, acute splenitis,
bilateral purulent pleuritis, multiple infarctions of lungs.
There were no signs of chronic disease outside the nervous
system except a moderate thickening of the mitral valves,
and slight dural adhesions.
The brain weighed 1450 grams. The vessels at the base
showed a slight degree of sclerosis. There was a slight
opacity of the frontal, parietal, and temporal pia overlying
slightly atrophied convolutions, whose surfaces showed in a
179few places slight cuppings. The ependyma over the thalami
and the floor of the fourth ventricle was finely roughened.
The spinal cord showed a typical Tabes Dorsalis.
Although we probably cannot regard either Case 42 or
Case 43 as a case of paretic neurosyphilis, and although it
must remain doubtful whether they are cases of any form
whatever of neurosyphilis (in the absence of the modern tests),
yet it seems clear that both these cases may very well have
been cases of neurosyphilis on account of the existence of a
definite tabetic process in each. The symptoms of these
cases, like those of Cases 38 to 41, suggest how difficult it
must be to make a clinical diagnosis of general paresis safely
without employing available laboratory tests. Yet how frequently
in the past have neurologists brought data concerning
various phenomena in long series of so-called paretics
in which the error of diagnosis was certainly between
5 and 15% and frequently still greater. The entire question
of the symptomatology of paretic and non-paretic neurosyphilis,
therefore, needs re-opening and revision.
180
CEREBRAL GLIOSIS (probably non-syphilitic)
producing the clinical picture of paretic neurosyphilis
(“general paresis”). Autopsy.
Case 44. John Hughes was a hostler, and later assistant
with a wholesale drug company, with which he remained
for 32 years. He had been moderately but constantly alcoholic
all his adult life up to 50 years of age, and at 45 had
had an attack of so-called nervous prostration, in which his
head had troubled him and he had been seclusive. At 49,
he had a serious attack of otitis media, associated with
delirium, swelling of the feet, and what was called rheumatism.
After this attack of otitis media, Hughes appears to
have been not altogether right.
At 53, after a quarrel with his employer, Hughes quit
work, began to trade a little in hens and pigs, became forgetful,
especially of recent events, and did “a variety of
peculiar things.” He was a married man but he had no
children. There had been miscarriages but of unknown
origin; venereal disease was denied. At 55, a week before
admission, Hughes had a spell of unconsciousness for several
hours, after which his speech was thick, and restlessness, insomnia,
and a wandering tendency set in. Visual hallucinations,
fabulation, tremors, “excited-looking” eyes, are
described. He would sweep things from the dining-room
table, pulled a hot stove into the middle of the floor, attempted
to sweep paint off the floor, and cut up a carpet
with a knife.
The patient on commitment November 5, 1904, was well
developed and nourished. The mucous membranes were
rather pale. Bruises and excoriations of limbs. Harsh
breathing at the base of each lung. Enlargement of heart;
sounds irregular. Accentuation of aortic second sound;
tension fair, rate 80. Slight brachial arteriosclerosis. Abdomen
slightly distended. The urine contained a faint trace
of albumin and many hyaline casts.
181Moderate tremor of extended hands. Slight tongue
tremor. Romberg’s sign absent (slight swaying). Considerable
ataxia of extremities (inability to stand with foot
on opposite knee). Vision poor. Hearing could not be
tested accurately. Prompt pupil reactions with direct light.
Slight consensual reaction in left pupil, absent in right. Deep
reflexes equal and lively.
Quiet and orderly at first. Later restless and noisy.
Questions were answered at times relevantly, more often
irrelevantly. Patient irritable, intractable. Required repeated
urging to take nourishment. Consciousness clouded.
Orientation imperfect. Attendants are possibly “officers.”
Date September, 1995. Slight errors in repeating alphabet.
Mistakes in Lord’s Prayer with rhyming tendency. Simple
arithmetical tests answered automatically with many mistakes.
More complex combinations incorrect. Handwriting
tremulous (noted as “typical of general paresis”). Auditory
hallucinations (answering invisible persons), “All right, I’m
coming.” Amnesia and confabulation. Q. “Have you
had breakfast?” A. “No,” (later) “Yes, I had a very light
breakfast.” Q. “What did you have?” A. “Anything
that came along. A few green peas and beans that were left,
bread and butter and pie. I had a good breakfast. Guess
feed is very high.” Q. “Give names of your sisters and
brothers.” A. “There are three or four I never see. I will
have to think them up.” (Later)—“Lillie, Abbie, Julia,
George.” On repetition of question, “Elizabeth, Julia,
Annie and Lizzie.”
Delusions somewhat doubtful. At no time euphoria.
The patient remained only nine days in the hospital,
developing diarrhea a week after admission.
Post Mortem Findings. The cause of death was bilateral
bronchopneumonia of hypostatic distribution, accompanied
by bronchitis and acute splenitis. The intestinal tract was
normal (despite the diarrhea). No cultures. The heart
showed acute myocarditis.
The vessels in general showed no sclerosis, except that the
aorta showed a few patches with calcification near bifurcation.
There was a moderate degree of mitral sclerosis. The kidneys
182showed a moderate degree of chronic interstitial nephritis.
The heart weighed 530 grams and there was moderate dilatation
of all the valves.
There were some evidences of chronic disease outside the
nervous system, namely, an obliterative pleuritis on the right
side, chronic perisplenitis, and chronic external adhesive
pachymeningitis.
The nervous system showed a pia mater thin and transparent,
with a moderate congestion of larger and smaller
vessels. No noteworthy change of the brain substance or of
the ventricles was found, except that the cerebral substance
was of unusual firmness (autopsy twelve hours after death).
It is clear that the brain was not wholly normal, exhibiting
a general induration due in part to subpial gliosis and in part
doubtless to perivascular gliosis. Microscopically the tissues
showed features of great interest, especially multiple focal
neuroglia cell proliferations of a perivascular distribution,
considerable subpial fibrillar gliosis of an unusually focal
type, and a rather general subpial cellular gliosis. Histologically,
it seemed that this chronic progressive process had
started, not so much in relation with dying nerve cells, as in
relation with blood vessels. The perivascular deposits of
neuroglia cells were confined almost exclusively to the infragranular
cortex layers. It seems plain that the diagnosis of
general paresis was not justified. It is probable that the diagnosis of
neurosyphilis is not justified. The explanation may
be that now and then cases of cerebral sclerosis may clinically
imitate the neurosyphilitic process. It must be borne
in mind that the diagnosis in this case was made, like the other
cases at head of Part III, without the advantage of modern
systematic methods. Clinically speaking, of course,
there was no definite Argyll-Robertson pupil, although the
consensual reaction, slight on the left side, was absent in the
right pupil. The general picture appeared to be one of
the so-called demented form of paretic neurosyphilis.
183
Differential diagnosis between NEUROSYPHILIS
and NEURASTHENIA.
Case 45. Albert Robinson, a man of 28 years, was shipwrecked
on one of the Great Lakes. The ship was on the
rocks for eight days, and Robinson was under a great strain.
Ever after the wreck, Robinson had felt severe pain in the
head, neck, and back, and a feeling of great weakness whenever
he exerted himself physically or mentally, and seven
months after the wreck, he had several attacks of fainting.
For a number of weeks he had worried a good deal about
his inability to make money, especially as money was badly
needed on account of his wife’s approaching confinement.
A few days before entrance, Robinson had become very
forgetful, and was unable to recall, the night before entrance,
where he had been during the day. On the whole, however,
on mental examination no actual evidence of memory defect
could be shown to exist.
Physically, Robinson was entirely negative, except for
some hard glands in each groin. Mentally, there was little
to show except depression, worry over his financial condition,
and his inability to work. The serum W. R. proved
negative.
Diagnosis: On the whole, the diagnosis of psychoneurosis
(see case Harrison (9)) due to the shock at the time of
the shipwreck seemed to be proper. To be sure, the patient
gave a history of a chancre at 25, treated for two years, after
which he was declared cured.
However, following up the clue of admitted syphilis,
rigorous questioning elicited the fact that a few months
before there had been diplopia, lasting part of a day.
Lumbar puncture seemed desirable. The fluid was clear
but contained 125 cells per cmm. with appropriately increased
amounts of albumin and globulin. The spinal fluid
W. R. was positive. The diagnosis of Cerebrospinal
Syphilis seemed established.
184The lesson of this case appears to be that perhaps we should
never exclude syphilis until we have made an examination
of the cerebrospinal fluid. The W. R. of the blood in meningovascular
(non-paretic syphilis) is negative in many cases
(the figure is sometimes set as high as 40%).
Treatment: After a half dozen injections of salvarsan,
all symptoms disappeared and Robinson went back to work,
claiming to be in a better condition than for some time past.
1. How shall we explain such a symptom as the transient
diplopia? This diplopia is probably an example of
a neurorecidive, but it will be observed that it occurred
without salvarsan therapy. See discussion above under
the case of Bennett (34), where the general result of
the neurorecidive inquiry launched by Ehrlich early
in the history of salvarsan therapy showed that precisely
similar phenomena had always occurred in
neurosyphilis, whether under treatment or not. The
anatomical and histopathological explanation of such
phenomena is, of course, doubtful, but a review of the
findings in the case of Alice Morton (1) will show how
many apparently serious symptoms in neurosyphilitics
are actually irritative or at least due to lesions which
are entirely recoverable. We may suppose, first, a
local proliferation of spirochetes; second, a local over-formation
of toxic substances, directly or indirectly the
product of spirochetosis; thirdly, a local exudation;
fourthly, a local proliferation; fifthly, a combination
of these phenomena, any or all of which may be regarded
as but transient. We have sometimes found at autopsy
very little exudate except in small areas; sometimes
not more than a few mm. or cm. in superficial extent.
Note, for example, the small areas of lymphocytosis
demonstrable in but two foci in the case of Alice
Morton, the paradigm placed at the beginning of this
book.
185
NEUROSYPHILIS(?) in the SECONDARY STAGE
of syphilis. HYSTERICAL symptoms. Diagnosis?
Case 46. Alice Caperson was a colored girl of 18 years.
She had acquired syphilis five months before admission to
the hospital, and the secondary symptoms of this syphilis
had just disappeared before admission.
Very shortly after acquiring syphilis, the young negress
began to act peculiarly. She describes herself as having
a sort of nightmare, both when asleep and also when awake.
For instance, she saw her dead grandmother. It appeared
at first like a seraph; then it came nearer to her and seemed
to fill out; and then was dressed precisely as her grandmother
had been. This seraph appeared as though trying to tell her
something, but she could not make out what the something
was. The vision had appeared on two or three occasions.
Our examination detected little beyond instability and
irritability of mood with some depression. The patient
readily fell to weeping. She soon made friends in the wards,
however, and got on well. Physical examination was entirely
negative but the W. R. of the blood serum was positive.
The W. R. of the spinal fluid was negative, as was the gold
sol reaction; there was an excess of albumin and a positive
globulin test; there were seven cells per cmm.
The psychiatric diagnosis of a case like that of Alice Caperson
would waver between hysteria and dementia praecox.
However, as for dementia praecox there are hardly any
typical symptoms. There is insight into the hallucinations,
which are hypnagogic. There are, however, no hysterical
stigmata.
The spinal fluid reaction is typical of the secondary stage
of syphilis. It is commonly said that in every case of syphilis
the nervous system is involved at some period, if only
to the degree shown in the present case. However, such
involvement tends to disappear both with and without antisyphilitic
treatment, just as do the secondary skin symptoms.
186So far as syphilis is concerned, the prognosis under radical
treatment is as good as usual. We are inclined to regard
the case as one of the Hysterical or Psychopathic group
and inasmuch as cases occurring in the developmental stage
of a patient’s life are of fairly good general prognosis, we
are inclined to regard the prognosis in this particular case as
good under proper therapy and hygiene.
1. What is the relation of neuroses to syphilis? Neurasthenia,
chorea, hysteria, and epilepsy are often grouped
(for example, by Nonne) as neuroses bearing at times
important relations to neurosyphilis. (For the relations
of neurasthenia, chorea, and epilepsy, see cases of
Greeley Harrison (9), Margaret Green (72), and David
Borofski (49), respectively.) As for the hysteria shown
in Caperson, Charcot enumerated syphilis among agents
provocateurs of hysteria along with alcohol, lead, arsenic,
and the like. Fournier has also considered the
problem. It is clearly necessary to show that before
infection there were no hysterical symptoms, and that
the hysteria developed during the operation of the syphilitic
process, and it is probably necessary to show that
the symptoms will clear up under antisyphilitic treatment,
if we are to concede the existence of a syphilitic
hysteria.
2. What are the evidences of neurosyphilis in the secondary
and primary stages of syphilis? As above stated, the
findings in Caperson are typical enough. Wile and
Stokes at first stated that 60 to 70% of the secondary
syphilitics show changes in the spinal fluid; in a further
article they maintain that probably every case
shows such changes and that clinical symptoms of
neurosyphilis of the secondary period can probably be
determined. They claim that it is probable also that
the same holds for primary syphilis itself. The importance
of these claims lodges partly in the relation
of these early signs of neurosyphilis to the whole question
of latency and to the question of paresis sine paresi.
For a discussion of paresis sine paresi see cases Lawlor
(25), Vogel (52).
187
Differential diagnosis between NEUROSYPHILIS
and MANIC-DEPRESSIVE PSYCHOSIS.[9]
Case 47. As in other instances (compare Martha Bartlett
(21) and Annie Monks (85)) so also in the case of Ethel Hunter,
a woman 61 years of age, there was no initial suspicion of
neurosyphilis. Mrs. Hunter was brought to the hospital
stuporous as a result of an overdose of paraldehyd. The
paraldehyd had been administered by a physician to combat
insomnia and agitation. As soon as Mrs. H. had recovered
from the drug stupor, this agitation appeared once more, and
it was clear that she was suffering from marked depression.
There was tremendous worry over the sickness of a woman
with whom the patient lived. The patient was very self-accusatory,
blaming herself for many things that had happened
in the household. Besides her agitation, depression,
self-accusations, and insomnia, the patient showed a good
deal of the symptom frequently termed “retardation”—a
kind of lagging of all mental processes found, according to
Kraepelin, in manic-depressive psychosis.
Accordingly, the diagnosis of manic-depressive psychosis
might well have been rendered. The fact that the psychosis
so far as known began in the involution period was not against
the diagnosis since the so-called involution-melancholia of
this period is at least in a certain fraction of cases nothing
more or less than a form of manic-depressive psychosis.
However, the physical examination made the diagnosis of
manic-depressive psychosis a little doubtful. There was a
superficial thickening of the arteries (blood pressure: systolic,
170; diastolic, 104), which thickening would not in itself be
against the diagnosis of manic-depressive psychosis. (In
point of fact, arteriosclerosis is rather common late in this
188disease and previous attacks could not be excluded on the
basis of available history.) The contracted pupils were
irregular and both reacted sluggishly to light, although better
to accommodation; the right pupil was larger than the left.
The arm reflexes were pretty active. The left knee-jerk
could not be obtained, nor was the right knee-jerk more than
very sluggish. The Achilles reflexes could not be obtained.
Although there was not a positive Romberg sign, there was
a considerable swaying in Romberg position. There was
no speech defect. The other reflexes showed nothing abnormal.
On the whole, we had to conclude that, although
Mrs. Hunter might be an instance of manic-depressive psychosis,
still there was much of neurological interest in the
case.
This conclusion was emphasized when the W. R. of the
blood serum was found to be positive. The spinal fluid W. R.
was also positive, and the gold sol index was of the “paretic”
type. There were 74 cells to the cmm. Globulin stood at
++++, and albumin at ++++.
This case, therefore, again illustrates, as well the protean
nature of General Paresis (the diagnosis rendered), as the
doubtful value of making a psychiatric diagnosis without
due consideration of the physical examination and laboratory
findings. How easy might it have been, at least some years
ago, to consider that this patient of 61 years had suffered a
slight shock at some previous time (left knee-jerk absent),
but was as a matter of fact a case of manic-depressive
psychosis with a vascular complication!
Note: We must again duly insist that the merely sluggish
light reactions of the pupils in such a case as this do not
especially point to general paresis. The literature seems to
establish that sluggishness of light reaction precedes the
classical Argyll-Robertson pupil. Yet it does not do to say
that, if the Argyll-Robertson pupil pretty conclusively points
to neurosyphilis (for exceptions see cases Falvey (55), Murphy
(60)), then a sluggish pupillary reaction to light looks in the
same direction. Sluggishness may precede stiffness in many,
or perhaps all, cases, but sluggishness of pupils is a frequent
phenomenon outside the syphilitic group of cases.
1891. What part is played by emotional shock and psychic
causes in the starting up of general paresis? The
answer to this question cannot be definite. That a
paretic process can be started up after trauma is admitted
on all sides; but we here suppose actual physical
or chemical brain disturbance permitting increased
spirochetosis or inflammatory reaction. In the case of
psychic shock, or what might be called psychogenic
general paresis, our best resort will be to the indirect
effects of hormone action, or of vasomotor and other
autonomic disturbances produced directly or indirectly
by emotion. We are clearly here dealing with material
too speculative to be of practical service at this time.
2. Was the depressive drug therapy in the case of Hunter
justifiable? The paraldehyd had been administered by
a physician apparently on purely symptomatic grounds
to combat the insomnia and agitation of this woman of
61 years. With all due acknowledgment of the difficulties
of private practice, we must insist that when
ordinary measures in the relief of insomnia and agitation
are insufficient to curb these conditions, then a positive
danger ensues with the larger doses. As a rule, with
these larger doses and with the withdrawal of sensory
stimulation, the patients relapse into a stupor of
grave moment. We need only recall the situation in
delirium tremens where adequately depressive drugs
often tend to kill the patient.
190
Case for diagnosis. Errors in the diagnosis of
NEUROSYPHILIS are possible even when abundant
clinical and laboratory data are available.
Case 48. The first error chosen for demonstration is that
in the case of the machinist, Milton Safsky.
Safsky, about 8 months before his entrance to the hospital
in the 42d year of his life, had begun to lose strength, to grow
thin and pale, and to suffer from an extreme and continuous
thirst. He was said to have drunk as much as 6½ gal. in a day,
and passed appropriately large quantities of urine. After a
time, his management at a general hospital became difficult,
as Safsky became confused, cried “hysterically,” and was at
times very noisy. He sustained a marked memory loss,
seemed to show visual hallucinations, and complained of
headache, both frontal and occipital, and of pain about the
eyes. Sometimes the patient was very euphoric and expressed
what seemed to be delusions of grandeur, saying he
was wealthy and owned many machine shops.
Some symptoms, e.g., polydipsia and polyuria amounting
to a diabetes insipidus, associated with headache and arrested
attention, suggested possibly a new growth in the pituitary
region. The mental symptoms might naturally be supposed
to be due to some infiltration or pressure effect of intracranial
growth. After admission to the Psychopathic Hospital, the
patient was found difficult to arouse, although he could
eventually be aroused. His orientation proved to be as poor
as his memory. From time to time, the patient became a
bit more intelligent and able to execute requests.
The physical examination was in general almost entirely
negative. Neurologically, the pupils were markedly contracted
and reacted slowly to light, though they were otherwise
normal. The deep reflexes were all somewhat lively,
though equal. The umbilical and cremasteric reflexes in
particular were present. Systematic examination revealed
no other reflex disorder, nor any disturbance of sensation.
191There was a coarse tremor of the extended hands. There
were no phenomena of importance in the visual fields.
As against the diagnosis of growth, pituitary or extrapituitary
(diabetes insipidus and headache), a hypothesis of
neurosyphilis had to be considered. Not only were the contracted,
slowly-reacting pupils and the active deep reflexes
suggestive, but the euphoria with grandiose ideas looked
entirely consistent. As for the polyuria, one had to think of
the so-called syphilitic polyuria of the textbooks, which is
regarded as a more or less characteristic result of syphilitic
involvement of the basis cerebri. Moreover, the W. R. in
the spinal fluid proved to be slightly positive; 146 cells per
cmm. were found therein; there was a large quantity of
globulin, and a very marked increase in albumin. These
observations seemed to be exceedingly suggestive of a cerebral
syphilis.
However, as the case progressed, the diagnostic situation
changed. The W. R. upon a second puncture fluid proved
negative. After some weeks, characteristic symptoms of intracranial
pressure developed; the diagnosis of Brain Tumor
had to be taken as established, and there is no doubt of its
correctness.
1. What is the explanation of the weakly positive W. R. in
Safsky’s spinal fluid? An explanation is not easy to
find. Possibly we may regard the reaction as an example
of error in technique. It is even possible that it
may have been produced by exudative products in the
spinal fluid.
2. What precautions may be taken against an error in
diagnosis such as was first made through the positive
spinal fluid Wassermann in the case of Safsky? First,
repetition of the W. R.; secondly, it is very unusual
to find a weakly positive W. R. in a case with such
marked excess of albumin and such very marked increase
of globulin as was shown by this case.
3. How can we explain the inflammatory products in the
puncture fluid? Superficial brain tumors are frequently
associated with a so-called meningitis sympathica.
The products of such meningitis are exhibited:
viz., globulin, albumin, and pleocytosis, exactly
as shown in Safsky.
192
Can PARETIC NEUROSYPHILIS (“general
paresis”) appear clinically EARLY (e.g., two years)
after the initial syphilitic infection?
Case 49. David Borofski, a street car conductor, 27 years
of age, suddenly had a convulsion while at work in his car.
For four months Borofski continued to have rather numerous
convulsions, was finally compelled to discontinue work, and
resorted to the Psychopathic Hospital. It appears from his
own story that, about two years before, he had had a chancre,
for which he had been treated at a general hospital syphilis
clinic, and of which he was told he was cured. With a progressive
loss of memory and with convulsions, Borofski became
much concerned about himself, and was finally persuaded
by his fellow-workers to come to the Psychopathic
Hospital.
The convulsions were described as follows: The patient
gives a short cry, has convulsive movements for about ten
minutes, remains unconscious for perhaps half an hour, and
wakes with headache, dizziness, and a feverish appearance.
Sometimes the attacks were more severe, with frothing at
the mouth, biting of lips, and loss of sphincter control. There
were also slight attacks, occurring almost every day, without
loss of consciousness; these latter attacks consisted of dizziness,
inability to speak for a few seconds, and some arm
twitching.
Physically, Borofski was well developed and nourished, with
a blood pressure of 160. The only abnormal phenomena
neurologically were absent knee-jerks and ankle-jerks, sluggish
pupillary reactions, and slight tremor of the hands.
Mentally, despite suggestive complaint of amnesia, the
memory was found to be fairly good but knowledge of current
events and school knowledge was poor. The simplest
problems in arithmetic Borofski gave up.
The first diagnosis in such a case would naturally be
epilepsy. However, when an epileptic or epileptiform attack
193occurs for the first time in adult life, the chances are
probably against an idiopathic epilepsy. (This is not a
universal rule but will serve.) Borofski himself, moreover,
gave a history of syphilis. And the very nature of the attacks,
with arm twitching and without loss of consciousness, would
not readily fit into the frame of the idiopathic group. The
absence of certain reflexes and the sluggish pupils are naturally
also suggestive of syphilis, although not convincing.
The W. R. of the serum proved positive, as did that of
the spinal fluid. The gold sol reaction was characteristically
“paretic”; there was an excess of albumin and a positive
globulin, and there were 15 cells per cmm. There could be
little or no doubt of the diagnosis of some form of neurosyphilis.
The laboratory picture was consistent either with
general paresis or with cerebrospinal syphilis. So far as we
are aware in the present stage of knowledge, the two conditions
can hardly be differentiated unless we choose to rely on
therapeutics. However, it is exceedingly rare for general
paresis to occur only two years after the original infection.
If we can trust this statistical fact, we shall perhaps be wiser
to term the case of Borofski one of Diffuse Cerebrospinal
Syphilis, and not one of paresis.
Treatment: Borofski was put on antisyphilitic treatment
consisting of 0.6 gram of salvarsan twice a week and
potassium iodid, together with intramuscular injections of
mercury salicylate. The convulsions then ceased. After
four months Borofski returned to work, and he has remained
at work for a year. He has never regained his former health.
Fifteen months after beginning of treatment the laboratory
tests were again made (there had been more than 60 injections
of salvarsan), and the cell count and gold sol reactions
were found to be negative. Globulin and albumin were
also in smaller amounts than in the original examination.
However, the W. R. of the serum and the spinal fluid remained
positive.
Head and Fearnsides state that cases of cerebrospinal
syphilis should return negative spinal fluid tests after six
months of treatment. Upon this criterion of Head and
Fearnsides, Borofski would not be a case of cerebrospinal
194syphilis; but it is probably impossible to separate various
forms of neurosyphilis into categories on any such grounds.
1. Shall case David Borofski be regarded as one of paretic
neurosyphilis (“general paresis”)? He has returned to
work and has remained at work, though without regaining
his former health. In any event, however, he does
not offer the typical picture of inevitable decline and
death presented by the typical case of Pietro Martiro
(15) presented in our discussion of systematic diagnosis.
However, we could not upon laboratory grounds,
or even upon the ground of clinical observation, distinguish
Borofski from Martiro; Borofski has greatly
improved; Martiro is dead. Borofski developed his
obvious neurosyphilis only two years after the original
infection. The conservative syphilographer might, accordingly,
reply that David Borofski is not a typical
case of paretic neurosyphilis (“general paresis”) either
in the length of the incubation period for his neurosyphilitic
symptoms, or in his outcome.
2. What is the cause of such convulsions as those developed
by David Borofski? Evidence from clear cases of
general paresis with convulsions leads to the hypothesis
that such convulsions as those developed by Borofski
are not necessarily based upon frank destructive
lesions such as would be produced by the plugging of
terminal arteries. They may well be produced through
the activities of minor lesions, only demonstrable by
microscopic methods, either through properly disposed
cell losses or by the pressure of exudate, or even by
endotoxins or other substances derived from the bodies
of dead or living spirochetes.
3. Aside from the well-known syphilitic epilepsy due to
meningitis, is there a non-meningitic epilepsy (such
a disease as Fournier formerly described under the term
parasyphilitic epilepsy)? We dismiss from discussion
the so-called symptomatic epilepsies which are the
result of a gross organic disease of the brain substance
or its membranes, and which do not differ so far as we
are aware from organic epilepsy produced by other
gross lesions of an identical size and structure. These
symptomatic epilepsies may be partial, or even may
present the appearance of generalized epilepsy. We
may also leave out of account those epileptic pictures
which are produced in general paresis itself, and which
195may be viewed as nothing but partial phenomena of
general paresis. The kind of so-called “parasyphilitic”
epilepsy that Fournier described is a kind of epilepsy
that cannot be distinguished from genuine epilepsy, in
which the sole disease-phenomenon throughout a long
period of time consists of epileptic convulsions. It appears
that these “parasyphilitic” imitations of genuine
epilepsy occur in individuals with a very long post-infective
“incubation period,” but that there are some
cases in which the epilepsy appears, on the contrary,
in the very earliest stages of syphilis. The attacks
are a little less common than those of idiopathic epilepsy;
they have the same apparently causeless beginning;
are associated with complete amnesia; and
are followed by characteristic dazed states. The
patient’s intelligence, however, suffers little. Now and
then a case reacts well to antisyphilitic treatment energetically
pushed. (Spontaneous long remissions in
non-syphilitic epilepsy must be remembered.) Petit
mal attacks occur sometimes between the more severe
attacks. In short, it would appear that there is a
group of syphilitic epilepsies in which the brain shows
no gross structural lesions, which accordingly do not
exhibit any Jacksonian appearances, and which last
a comparatively long time without changing their
character, and often without being especially altered
for the better by any form of antisyphilitic treatment.
This condition is sometimes known as a post-syphilitic
epileptic neurosis. Nonne had been able to collect up
to 1902 some 12 cases from his own service.
4. Would it be proper to call Borofski a case of taboparesis?
Absent knee-jerks in a victim of paretic neurosyphilis
should not be used to suggest a diagnosis of taboparesis.
This question of terminology has been discussed above,
under Sullivan (16).
5. What is the mechanism by which the amnesia of a case
like Borofski is produced? The answer runs in the
same terms as the answer to the questions concerning
the cause of convulsions. The amnesia in general
paresis has surprising functionality. A study of autopsied
cases of general paresis has shown that amnesia
is practically as common in cases without marked
destruction of brain tissue as in cases with atrophy of
classical extent and depth. The clinical recovery in
this case was practically complete in respect to memory.
We must regard the amnesia as not due to the destruction
196of storage cells bearing the so-called neurograms
(Morton Prince).
6. What is the explanation of the persistently positive W.
R.’s of the serum and spinal fluid associated with
diminished globulin and albumin tests, a negative gold
sol reaction, and normal cell count? See discussion
under Case Martha Bartlett (21).
7. How atypical is the early development of paretic symptoms
in David Borofski? C. B. Craig has collected,
in 100 cases of brain syphilis (a list including both
paretic and non-paretic cases), some data on this
point. The shortest period reported by Craig was in
a case in which the neurosyphilitic symptoms appeared
one month after infection. Craig found three cases
where symptoms appeared in six months, and six cases
within a year. The longest post-infective period of
Craig’s list was thirty years. Our case of Chatterton
(73) developed symptoms 33 years after infection and
Washington (66), forty years after infection. Nonne
casts some doubt on statements to the effect that
tabetic symptoms may occur three to four months
after infection. It seems to be admitted that pupillary
anomalies and reflex changes may occur in the early
secondaries and may recover under antisyphilitic treatment.
Nonne’s case of longest post-infective interval,
like that of Craig, was one of 30 years.
Myerson has reported a 20–year old patient who
acquired chancre April 1, 1911 (spirochetes demonstrated);
salvarsan was administered April 20th. There
were no secondary symptoms, but in May, headache,
visual disturbance, vertigo, and other symptoms developed
(neurorecidive). Upon June 20th, that is,
11 weeks after development of the chancre, aphasia
and astasia developed, with numbness of the left side.
At this time, the pupils were slightly irregular and unequal
but reacted normally. The signs in the fluid
were positive. Upon this question see our cases of
Bright (121) and Bennett (34).
197
Hemitremor following hemiplegia in PARETIC
NEUROSYPHILIS (“general paresis”). Autopsy.
Case 50. Achilles Akropovlos, 39 years, had symptoms
six months before commitment to Danvers Hospital. There
were attacks of confusion, difficulty in walking, and speech
defect, resulting in an entire incapacity to work and
eventual commitment. Rather unusual and striking was a
very marked tremor, apparently limited to the right side of
the body. Physically, Akropovlos was normal, but neurologically
he showed, in addition to the marked right-sided
tremor, a marked speech defect, and a degree of ataxia.
The tendon reflexes were very active, but there were no abnormal
reflexes, and the pupils reacted normally. According
to the history, the difficulty had followed a slight attack of
apoplexy. Mentally, there was a marked confusion. The
blood serum and the spinal fluid were both positive to the W.
R.; globulin was present, and albumin was increased; there
were 43 cells per cmm. There was hardly any diagnosis to
make except general paresis.
Death followed 18 months later, or two years after onset
of symptoms. Increasing weakness, emaciation, and dementia
preceded death. Autopsy confirmed the diagnosis of
Paretic Neurosyphilis.
1. What is the usual cause of death in general paresis?
Intercurrent disease very frequently occurs in general
paresis, and such intercurrent disease is then given as
the cause of death. As a matter of fact, however, one
feels that in many of these cases the intercurrent
pneumonia or infection—frequently of the bladder,—bedsores,
sepsis, and the like, are merely accidental
incidents in a condition that is leading to death, and
which has caused a lowered resistance to infection.
In certain instances where nursing is exceptionally good
and where no such infection occurs, the patient continues
to grow weaker and weaker, paralyses of all the
muscles follow and finally paralysis of deglutition or
198respiration may lead to death. The emaciation and
paralyses may be of such a grade that the patient is
entirely devoid of fat and unable to move at all. Not
infrequently vascular crises occur, and one of these may
be responsible for death.
2. What was the cause of the hemitremor? The hemitremor
suggested an irritative or destructive lesion in
the motor path. Delving into the history it was
learned that the patient had had a shock followed by
a right hemiparesis. This had cleared up leaving the
tremor as a residuum. The autopsy disclosed a reddish-brown
pigmentation and fibrous thickening of the pia
over the left motor area, confirming the idea of a
previous hemorrhage. As a rule the shock phenomena
occurring in paresis clear up more completely and no
gross lesion is visible post mortem. However, cerebral
hemorrhage must be expected in any person suffering
from syphilis, and is no rarity in paretic neurosyphilis.
199
PARETIC NEUROSYPHILIS (“general paresis”)
with NORMALLY REACTING PUPILS. History
of trauma. Autopsy.
Case 51. Daniel Wheelwright, a barber of English extraction,
57 years of age, had had a sunstroke at 15. At 42,
there had been pneumonia, after which an attack of rheumatism
was said to have kept the patient from work for a year.
There was trauma of head (falling wrench) at 44. This blow
on the head was the assigned cause of the mental disease,
symptoms of which, however, did not develop until about the
first of September, 1905, about three months before entrance,
January 9, 1906, and about six months before death, March
20, 1906.
It seems that the patient had begun to change in manner;
he had become despondent and apathetic, silent, and somnolent.
Two weeks later, he stopped working, began to
read the papers once more, and became somewhat more
cheerful.
About Thanksgiving, Wheelwright got up at midnight, and
remained up, lighting all the fires and talking continuously.
During the next two weeks, he talked much to himself,
laughing out at times. About two weeks before Christmas
he went out and started to make a sidewalk of old boards,
working in his shirtsleeves, without a hat. He would work
until midnight making screens for windows. During the
day, he would go out and give money to passing children;
would offer to pay the grocer twice as much as articles were
worth.
On the day before Christmas, he put out all the fires and
lights in the house, sent all the family to bed, and opened all the
doors. Christmas morning, he rose early and got the washtubs
ready. He helped his compliant wife to do the washing, then
put out all the fires and opened the windows. After Christmas,
he began to tell how rich he was going to be through starting
a garden and by making butter. He bought six or seven
200quarts of milk daily, and procured carrots and oranges,
grinding them up to color the milk. January 9th he was
committed to Danvers Hospital.
Physically, there were few symptoms. Neurologically, there
was a tremor of tongue, fingers, and face. The knee-jerks
were lively. The pupils reacted normally; the patient was
restless, pacing up and down. There was a speech defect
demonstrable with test phrases. Orientation was imperfect
for time and for place. Handwriting was poor, memory
impairment was marked, but the patient was given to fabrication
as to past events. A characteristic sample of statements:
“Do you know that this is an insane hospital?” “Yes;
there are two or three men here out of their heads. I could
cure them with my hands but they won’t let me. I could get
all the sick men on their feet just by rubbing them. I can
do anything with my hands. I can build a house by just
sitting down and thinking about it. I can whip all the men
in this place. I have better sense now than I ever had in
my life.”
Again, “How long have you been here?” “Over three
months; they have put me in heaven three times since I have
been here. They killed me, crushed my heart, and turned
my blood to water. I am all right now. I let the sun shine
on my heart and it brought it together. I can whip every
man in here as fast as they come up.”
Again, “I will make a million dollars on my garden when
I get it. I can make a million dollars on half an acre.
I can do anything. I can move this house by just thinking
of it.”
During a special examination, the patient told how he had
fastened wings on his hands and feet, and how he had gone to
heaven; he told how he had soared high above the earth, and
how differently the stars look when up near heaven than they
do from the earth. He spoke of seeing angels and of the
beauties of heaven.
The diagnosis of Paretic Neurosyphilis was confirmed
at autopsy.
2011. What is the significance of the normally reacting pupils?
While it is usual to find pupillary anomalies in
neurosyphilis, these changes are not an essential part
and it is not rare to find normal pupils in all forms of
neurosyphilis. It is less frequent to find a normal
pupil in tabetic than in diffuse or paretic neurosyphilis.
In paretic neurosyphilis it is the rule to find pupillary
changes during some stage of the disease, but not necessarily
early. At times the pupillary sign may be one of
the earliest signs of neurosyphilis—again it may occur
only as a late symptom, if at all. One of the most important
of the pupillary signs is irregularity of contour.
While this does not always mean neurosyphilis it is
highly suggestive and certainly indicates careful examination
even though the W. R. in the blood be negative.
2. What was the relation of trauma to the development
of the neurosyphilitic symptoms? It is, of course, the
rule in all forms of mental disease to have some factor
offered by the patient or relatives as the cause of the
psychosis. Often these assigned causes are minor
events thought of only after the later appearance of
symptoms. In this case it was not thought that the
trauma had any causal effect. For a discussion of
trauma and neurosyphilis see cases Joseph O’Hearn
(90), Levi Sussman (91), and Joseph Larkin (92).
202
NEUROSYPHILIS, probably PARETIC, with
symptoms highly suggestive of MANIC-DEPRESSIVE
PSYCHOSIS.
Case 52. Bessie Vogel[10] was admitted to the Psychopathic
hospital New Year’s day, 1915, in a very much excited
condition. The family history is very meagre, and all
that is of significance is that mother has always been very
“nervous.” The records in part:
Past History. Very healthy as a child, and except for occasional
throat trouble and headache had no physical ailments
until eight years ago, when she had an operation for appendicitis,
and two and one-half years ago was operated upon for
hernia and adhesions. Following this she began to show a
lack of energy, neglected her housework, was much depressed,
wept frequently, complained constantly of pain in various
places, and was ill-tempered. In about five months she
improved, and then after a couple of weeks at the shore
seemed entirely well.
Present Illness. In November, 1914, that is, about
seventeen months after the recovery from the previous depression,
she again began to show practically the same
symptoms. She was depressed, could not sleep, and would
get up in the night and sew; was self-centered and hypersensitive,
then became restless and nervous; wanted to go
shopping and out for dinner; went to New York and then to
New Bedford. Symptoms became more marked; she became
very ill-tempered, threatened her husband when angry
over trifles, threatened suicide, then began to get active and
spent money extravagantly. At the end of two months, that
is, Jan. 1, 1915, she was admitted to the hospital.
Physical Examination. A small, thin woman, appearing
to be about 45 years old (actual age 37). Aside from the
203absence of teeth and the operation scars, the general examination
is negative. Neuromuscular system: The pupils
are round, regular, equal, and react to light and accommodation,
but do not hold very well. Extraocular movements
well performed, no palsies of facial muscles, tongue
protruded medially without tremor. Uvula is raised symmetrically.
Biceps and triceps and supinator reflexes are
present and brisk. Patellar and Achilles reflexes are equal
on the two sides and brisk. Abdominal skin reflexes not
obtained. Plantar reflex active and flexor in type. No
Babinski, Gordon, or Oppenheim. No tremors.
Wassermann reaction serum positive. Examination of
spinal fluid: clear, globulin ++++, albumin ++++;
cells, 130 per cmm.; small lymphocytes, 79.9%; large lymphocytes,
14.1%; polymorphonuclear leucocytes, 4.6%;
plasma cells, 0.7%; endothelial cell, 0.7%. W. R. positive.
Gold sol reaction, 55555522 +-.
Mental Examination. On admission patient showed great
psychomotor activity, was very playful, marked flight of
ideas, was expansive, very emotional, very erotic. She
slept very little, appetite was poor, and she lost weight
rapidly. Orientation and memory intact. No hallucinations
elicited. In about three weeks improvement began, and at
the end of eight weeks she appeared practically recovered.
On April 9, 1915,—that is, 13 weeks after admission,—she
was allowed home on visit. On leaving, she appeared
normal in every way. There was no evidence of psychotic
symptoms, she had good insight, and physically there was
absolutely nothing of a neurological nature that was abnormal.
This case, with the history of a previous depression and its
clinical picture during the acute stage, and its recovery,
is certainly in every respect typical of manic-depressive insanity,
and only the positive result of the six tests causes us
to put it in the group of General Paresis. Only the further
course will shed any light as to the correct significance of
these findings, and even then we shall not be too sure that we
had not been dealing with a manic-depressive psychosis in a
latent neurosyphilitic. We would strongly emphasize the
point that at the present time this patient presents no mental
204or physical signs of cerebrospinal syphilis or general paresis;
but the six tests are still positive. This case differs from the
ordinary general paresis remission in that there is not a single
physical sign of paresis present.
There are many transitional cases between this case which
shows no symptoms or signs of neurosyphilis except the laboratory
tests, and the typical case of general paresis. Thus
we have cases with slight character change and no physical
signs except rare “seizures.” On the other hand, in many
cases the presence of abnormal neurological phenomena without
definite mental signs is first noted. Certain remitted
cases show only some slight pupillary or reflex abnormality.
We believe we have here added the last link in the chain
between the primary and quaternary symptoms.
This case is illustrative of several which we have published
elsewhere under the name of paresis sine paresi or
latent neurosyphilis to illustrate how all the laboratory signs
of neurosyphilis may be present in a patient without any
physical or mental symptoms that may be correlated with
these findings.
We summarize our discussion of this as follows:
1. There is a group of cases showing the laboratory signs
characteristic of central nervous system syphilis: (a) positive
W. R. in the serum, (b) positive W. R. in the spinal fluid,
(c) pleocytosis, (d) excess of albumin, and (e) of globulin in
the spinal fluid, (f) gold sol reaction of central nervous
system syphilis, and which show no sign or symptom of
neurosyphilis.
2. We believe these cases represent a form of chronic
cerebrospinal syphilis, probably paretic in type.
3. They have the greatest theoretical and practical
significance in the consideration of the life history of neural
syphilis, in the concept of Allergie, in regard to results of
treatment, and finally as to the evaluation of the laboratory
tests.
4. Here is perhaps offered the last link to form a complete
chain between the symptoms of the primary stage of syphilis
and its final termination of life as the result of the diseases
cerebrospinal syphilis or general paresis.
205
SYPHILIS (?); EXOPHTHALMIC GOITRE; neurosyphilitic
old lesion of optic thalamus; unilateral
induration and atrophy of left cerebral cortex.
Autopsy.
Case 53. Carrie Pearson, a housewife 25 years of age, died
at Danvers Hospital less than a week after admission, and it
was at first stated that her symptoms had lasted but two
weeks before admission. In point of fact, a further investigation
showed an important succession of symptoms, lasting
some four years.
Carrie had been considered a healthy child, going to school
at the usual age, and progressing well with her studies. She
however, left school in the ninth grammar grade, at the age
of 15, and went to work in a milltown. She married a worthless
person at the age of 18, and lived with her husband
for three years. There was one child born a year after
marriage. Two years later, however, a tremendous goitre
had developed such that her neck was described as “out
square with the face,” and at the same time the patient’s
eyes had become prominent.
About two weeks before admission, she had gone to a
neighboring town to take care of a sick woman, but during
her endeavor to be a nurse, she had broken out into a mania,
tearing up furniture and bedding, and talking irrelevantly
for a period of four days. She also showed insomnia and
continually tore off her clothing from her body.
Upon examination, the marked enlargement of the thyroid
gland together with the prominent eyeballs, husky voice, and
pulse rate of 150 per minute, were entirely consistent with
the diagnosis of exophthalmic goitre. The patient described
herself as “Carrie Nation.” Asked to write her name,
she took the pen and tried to spatter ink, wrote hurriedly and
carelessly her maiden name and several words without apparent
meaning. Asked to write, “God save the Commonwealth
of Massachusetts,” she wrote: “God save the
206common pal U S Spe Manor Gen, or til pat. Since Lord, or
no prime in Hear to the God Tel. Ho. n and or Mabel, or gal.”
After this, she took paper and wrote meaningless scrawls,
saying that it was Japanese writing. There was much
motor restlessness with distractibility, pointing and grimacing,
mimicking the actions of those about her.
Death occurred from exhaustion, and the case might not
have been regarded as unusual except for the autopsy, which
showed a peculiar brain lesion, described below. The point
of greatest interest in the case was the fact that syphilis is,
although not proved to exist by laboratory tests, beyond
question a factor in the case. Although the woman had
given birth to a normal child, who is still alive, yet in the
period of a few years her breasts had atrophied, her hair had
disappeared from the axilla and from the pubes; varicose
veins had developed in both legs. Whereas there was little
or no fat over the chest or back, the omentum and mesentery
were very plentifully supplied with fat. It is probable, then,
that we are dealing with a case of exophthalmic goitre somehow
of syphilitic origin. The brain lesion is consistent with
this hypothesis.
Autopsy, March 3, 1907. Four hours post mortem.
Body length, 165 cm. Body of a well developed and
well nourished young woman. Lividity in dependent
parts. Purplish discoloration of left thigh to knees.
Skin rough and scaly. Petechial eruption over chest.
Neck thick, protrudes anteriorly. Varicose veins over
upper parts of calves on both legs. Eyes protruding,
not covered entirely by lids. Pupils equal, dilated.
Subcutaneous fat very deep over lower part of body.
Very little fat over chest and back. Breasts are very
small, apparently atrophied. Normal amount of hair
on head, slight amount over pubes. Axillary hair absent.
Fat on section of a light yellow color. Omentum
extends to pubes, plentifully supplied with fat. Large
amount of mesenteric fat. Appendix normal. Intestines
smooth and glistening. Slightly injected. No
fluid in peritoneum. Uterus small, retroverted.
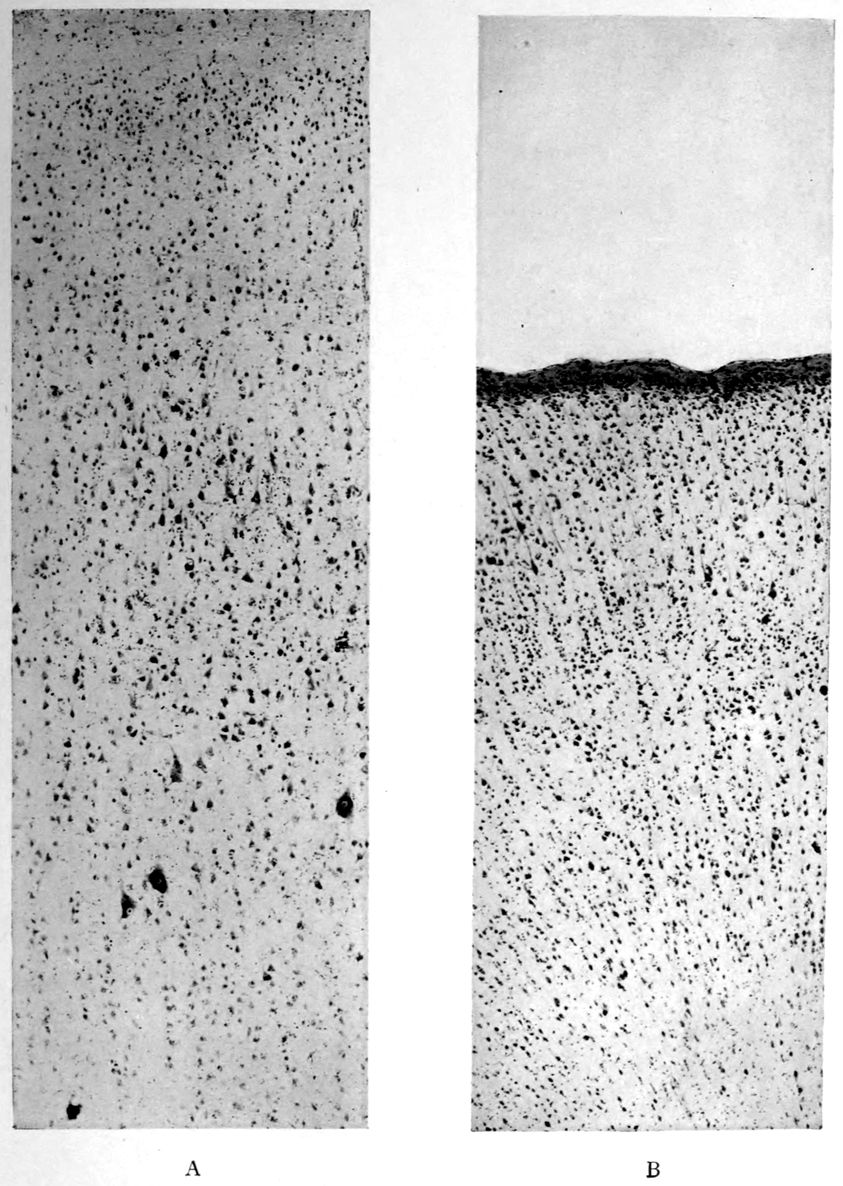
Cortical hemiatrophy—A, relatively normal right precentral (“motor”) cortex; B, atrophic left precentral.
Note in B:
1. Absence of giant pyramids of Betz (corticospinal, upper motor neurones).
2. Superficial (subpial) condensation of tissues with sclerosis (gliosis). The tissues in all areas examined on the left side yielded this effect.
207Head: Hair in good quantity. Scalp normal.
Calvarium shows diploë. Dura Mater over left
cerebral hemisphere inseparably adherent to calvarium,
over right hemisphere normal. Arachnoidal Villi
moderately developed. Pia Mater shows injected
veins, notably in the sulci of the right hemisphere.
Pia mater everywhere thin and clear. Vessels at base
of normal appearance.
Brain weight 1180 grams. Spread on a board, the
right hemisphere tends to flatten so that it measures
1.5 cm. more from side to side than its fellow. Besides
more marked venous injection, the right hemisphere
shows also flatter and slightly more plastic
convolutions. The posterior poles of the hemispheres
are a little firmer than the parts anterior. The orbital
and hippocampal gyri on the right side are a little
firmer than the surrounding parts. On section the
gray and white matter shows no lesions, excepting the
slight plasticity of the tissues at large on the right side
and a well marked induration, with retraction under
the knife, of the occipital and hippocampal white
matter. The basal ganglia of the left side are
normal. On the right side a sagittal section demonstrates
a rounded area of induration, with ill-defined
borders, measuring perhaps 1.5 cm. from above downwards
by 2 × 2 cm., situated largely in the lenticular
nucleus and involving the greater portion of the globus
pallidus, a small segment of the putamen below and
behind and the regionary part of the anterior commissure
with surrounding tissues. The most striking
feature of this lesion is the occurrence in the middle
of a cluster of vacuoles or cystic clefts, with smooth
pale interiors, ranging from pinhead to 0.25 cm. or even
0.5 cm. in greatest diameters. There are six to eight
clefts to a surface of section. The color of the lesion
differs little from that of the globus pallidus itself, but
the tissue is a trifle translucent. It is impossible to
demarcate the lesion with the eye. Induration is demonstrable
several mm. beyond the visible part of the
lesion. The consistence of the lesion slightly surpasses
the usual consistence of the olivary bodies.
Cerebellum, Pons and Bulb weight 165 grams.
Cerebellar tissue a trifle more plastic than usual.
The right olive is not so prominent as usual.
Note. Thyroid: Weight 125 grams. Both lobes
and isthmus enlarged. One lobe more than the other;
lobe on one side measuring 6 × 4 cm.
Enlargement of thyroid gland.
Exophthalmos with dilated pupils.
Fatty degeneration of thoracic muscles.
Slight aortic sclerosis.
Dilatation of right heart.
Hypertrophy of left ventricle.
Slight tricuspid endocarditis.
Bicuspid aortic valve.
Hypostatic pneumonia.
Acute and chronic splenitis.
Fatty liver (central necroses?).
Acute nephritis.
Chronic gastritis.
Small breasts.
Axillary hair absent.
Petechial eruption of chest.
Varicose veins.
Chronic external adhesive pachymeningitis of left side.
Moderate swelling of right hemisphere with venous
injection.
Slight occipital gliosis of both sides.
Slight gliosis of orbital and hippocampal gyri of
right side.
Sclerosis with atrophy of occipital and hippocampal
white matter of right side.
Gliotic lesion (1.5 × 2 × 2 cm. of right lenticular
nucleus involving anterior commissure).
1. Was the exophthalmic goitre in Carrie Pearson due to
syphilis? Unfortunately we have no clear proof that
Carrie Pearson was syphilitic. She was stated to have
been syphilitic by the physician who treated her before
her commitment to Danvers Hospital. There is, however,
no proof of syphilis, inasmuch as the patient died
in the pre-Wassermann period.
2. Is the thalamic lesion probably syphilitic? No lymphocytosis
or plasmocytosis characterizes the lesion, which
is the only lesion of the sort in the Danvers collection.
It would not do to call a lesion syphilitic just because
it is sui generis. In any event, the clinical analysis of
the case faced the claim of syphilis as an actual factor
in the patient’s life and as a possible factor in the goitre.
209
It is well known that the ARGYLL-ROBERTSON
PUPIL is characteristic of the so-called “PARA-SYPHILITIC
DISEASES” (“general paresis”
and “tabes”); does this sign occur in other neurosyphilitic
conditions?
Case 54. Julius Kantor was a shoemaker of 35 years,
who came to the hospital for treatment because his family
physician had found a positive W. R. in Kantor’s blood
serum. He had had a cough for a number of years, and
during the last year a little blood had been found in the
sputum; whereupon Kantor had been placed under active
anti-tuberculosis treatment. The enterprising family physician
had found the positive W. R. in the first days of his
treatment for tuberculosis. There was, in fact, a history
of a chancre nine years before, which had not been followed
by any secondary or tertiary symptoms, and which had
been but scantily treated.
There were no mental symptoms.
Kantor was physically fairly well developed and nourished.
There were a few piping râles in the left upper chest, both
in front and back, and also a slight dulness with increased
vocal and tactile fremitus. No tubercle bacilli, however,
could be found on repeated sputum examination.
Neurologically, the pupils were myotic and both showed
the Argyll-Robertson reaction. There were no abnormal
reflexes whatever, and there was neither ataxia nor speech
defect. Not only the blood but also the spinal fluid W. R.
proved to be positive; there was a marked increase in the
albumin and globulin; there was a gold sol reaction of the
syphilitic type, and there were but three cells per cmm.
1. In view of the headache in case Kantor, what other
causes of headache are to be considered? It is certain
that irritations of the dura mater can produce
headache, and the physiological observation of the
sensitiveness of the membranes and the non-sensitiveness
210of the brain substance is an ancient and classical
observation. Internal hemorrhagic pachymeningitis
produces severe headache. The relations of this disease
to trauma, to arteriosclerosis, and possibly to
syphilis (alcohol perhaps should also be considered) in
certain instances have not been entirely cleared up.
Syphilitic headaches are, according to Lewandowski,
dependent also upon a dural affection or upon a periosteal
affection. The headaches of brain tumor are also
commonly related to dural conditions, either directly
due to the pressure of the tumor itself, or indirectly to
the heightened intracranial pressure consequent upon
the tumor. It is clear that the tension under which the
dura mater lies is not always localized in the region
of a brain tumor or a syphilitic lesion. Head has
claimed that brain tumor produces headaches of two
kinds, according to whether the disease affects the dura
mater or is dependent upon an increase of pressure in
the brain. It does not appear that the pia mater has
any relation to headaches, but meningitis, in which
the inflammation is confined to the pia mater, is nevertheless
associated with headache; the headache is here
supposed to be due to the increase in brain pressure,
and thus actually to an effect wrought upon the dura
mater. Vasomotor disorders and various types of
cephalic hyperemia are thought to produce a kind of
headache, but Lewandowski calls this kind of headache
somewhat in question. Reflex headaches are
stated to be produced indirectly by a process of radiation
from interior lesions in the brain. There are
certain headaches called nodal headaches (Schwielen-Kopfschmerz).
Hypermetropia, caries of the teeth,
adenoids, and diseases of the nose and axillary cavities,
to say nothing of thoracic and abdominal diseases,
are also counted among conditions that may produce
headaches. In this connection, Head has claimed
differential zones of headache corresponding to certain
diseases.
The brain itself may produce headache through intoxications,
through conditions produced by a variety
of diseases; may follow neuroses. Alcohol may produce
headaches in some persons even when it is taken
in very small doses. Certain uremic cases yield headaches,
as do also gouty and chlorotic conditions.
According to Lewandowski, the headaches of arteriosclerotics
are due possibly to vasomotor disturbances
211in the membranes, or one may think of nutritive cerebral
disorders. A peculiar form of headache is that of
fatigue after mental work, allied to which is the neurasthenic
headache; constitutional headaches have been
assumed to occur, to say nothing of hysterical headaches.
There remains also the important question of
migraine, for which a vasomotor explanation has been
proposed.
2. Was Kantor suffering from tuberculosis of the lungs?
The hypothesis of lung syphilis ought certainly to be
very seriously considered. Upon repeated sputum
examination, no tubercle bacilli have yet been found.
3. Is Kantor a case of general paresis? In the absence of
mental symptoms, and in consideration of the mildness
of the reactions, it is certainly not easy to make
the diagnosis of general paresis. However, the diagnosis
of tabes dorsalis is not justified either. Accordingly,
we may answer our question: whether the
Argyll-Robertson pupil occurs in other neurosyphilitic
diseases, by pointing out that in the case of Julius
Kantor, as in the case of Henri Lepère (105) and
Frederick Stone (106), the Argyll-Robertson pupil has
been found in syphilitic conditions that are neither
typically paretic nor typically tabetic.
212
Does the Argyll-Robertson pupil necessarily indicate
neurosyphilis?
Case 55. Daniel Falvey, 44 years of age, was an almshouse
transfer to the Danvers State Hospital in the year 1904,
when the principle of state care was adopted in Massachusetts.
As in most of the almshouse transfers of that day,
little could be discovered as to antecedents. He had been a
mill-worker from the time of his immigration in 1890, at 30
years of age. He had been somewhat alcoholic. There was
a shock some 17 months before his death, which occurred
about seven weeks from the date of transfer.
Not only was he unable to walk unsupported, but when
supported there was a slight dragging of the left leg and the
gait was noted to be somewhat propulsive. The tongue and
hands were tremulous, and the left grasp was somewhat
weaker than the right. Both knee-jerks were increased
although neither more than the other. There was no sensory
disorder.
Although but 44 years of age, Falvey presented the appearance
of a much older man. His heart was somewhat enlarged
and there was a degree of peripheral arteriosclerosis. On the
whole, no special attention was attracted to this case clinically
and he was regarded as an example of arteriosclerotic
dementia, like many another among the transfers. However,
we owe to Dr. H. M. Swift the important observation of the
Argyll-Robertson pupils. The case was studied long before
the Wassermann method was available, and is here reported
merely to call attention to the fact that the stiff pupils may
have other neural origin than neurosyphilis.
The autopsy material in the case was worked up by one of
the authors.[11] The autopsy had been performed by Dr. A. M.
Barrett, who found on section through the brain stem at the
213anterior border of the pons a mass springing from and continuous
with the pineal gland, lying in the third ventricle and the
aqueduct of Sylvius. Upon further study, this mass was
found to begin posteriorly in the pineal body itself, from
which the mass could hardly be told in the gross except by an
injected border.
This mass proved upon microscopic examination to be a
psammoma, which histologically resembled a glioma rather
than a sarcoma. Throughout the mass there was a variable
content of fibrillary intercellular substance having the histological
reactions of neuroglia fibrillæ. The histological
details (mitosis, large giant cells with multiple nuclei, etc.) do
not here concern us. We deal with a neoplasm springing from
the pineal gland growing on the posterior half of the third
ventricle, the anterior orifice of the aqueduct of Sylvius, and
the space between the velum interpositum as far back as the
posterior corpora quadrigemina. There is no evidence in the
body of old syphilis; although it is possible that the stiff
pupils were neurosyphilitic, it seems probable that they were
related to the pineal tumor. At all events, there are in the
literature evidences that the pineal-quadrigeminal group of
tumors and other lesions may bring about pupillary disturbances.
On this account, we here include the case. The
tumor hardly led to an error in diagnosis since neither neurosyphilis
nor brain tumor was at all expected clinically.
1. Can alcoholism produce identical results? See Case
Murphy, (60), one of alcoholic pseudoparesis.
2. What is the nature of stiff pupils? A pupil is called
stiff in the sense of the Argyll-Robertson pupil if it
fails to react to illumination either of itself or of the
other eye and at the same time if it reacts properly in
convergence and accommodation. Of course the stiffness
of a blind eye must not be regarded as an Argyll-Robertson
pupil. In a case of right-sided Argyll-Robertson
pupil, therefore, the left pupil reacts properly
both to direct illumination of itself and to illumination
of the right eye, but the right eye fails to react to illumination
of either eye. Such an Argyll-Robertson right
pupil will remain of the same width both in darkness
and in light. Clinicians agree that the Argyll-Robertson
214is diagnosticated rather too frequently than too
seldom, and this by reason of the fact that a sluggishness
of light reaction is interpreted as stiffness. The
sign, as is well known, has come to be regarded as almost
pathognomonic of tabetic or paretic neurosyphilis.
Nonne, however, has found among 510 cases of alcoholism,
nine instances of Argyll-Robertson pupil and
19 cases of sluggish light reactions. The pathological
anatomy of this sign is still doubtful although a number
of schematic accounts are available; among hypotheses,
one may think of an elective effect of the tabetic or
paretic degeneration upon reflex collaterals. The explanation
would then resemble that for absent knee-jerks
and kindred reflex disorders. We should then
hypothesize a loss of the finer processes of the terminal
arborizations about the cells of the nucleus of sphincter
nucleus iridis. However, the situation of the sphincter
iridis has not yet been absolutely determined.
When a pupil is said to be entirely stiff it means that
it reacts neither to light nor accommodation. This
condition not infrequently follows the partial stiffness
or Argyll-Robertson reaction.
3. Is the Argyll-Robertson pupil more tabetic than paretic?
This has been claimed at times, but in point of fact, the
Argyll-Robertson pupil is very frequent in paresis, and
so also are posterior column changes. According to
statistics of Bumke, 36% of tabetics fail to show the
Argyll-Robertson pupil, and 38% of paretics. When,
however, finer methods, such as those standardized by
Weiler, with photographic records, are employed, the
number of cases without at least a tendency to the
Argyll-Robertson pupil becomes much smaller.
In connection with the important question as to the
classical Argyll-Robertson pupil and pupillary sluggishness
to light, it may be inquired what are the ocular
signs in neurosyphilis? Joffroy has tabulated the signs
in 300 general paretics as follows:
| Sign. |
No. of cases. |
Per cent. |
| Alterations of light reflex |
235 |
78 |
| Inequality |
205 |
68 |
| Abolition of light reflex (bilateral or unilateral) |
156 |
52 |
| Abolition of light reflex (bilateral) |
133 |
44 |
| Irregularity of pupil |
117 |
39 |
| 215Irregularity of both pupils |
109 |
36 |
| Diminution of light reflex |
108 |
36 |
| ditto (bilateral) |
79 |
26 |
| Alteration in accommodation reflex |
79 |
26 |
| Diminution of accommodation reflex |
52 |
17 |
| Mydriasis |
41 |
13 |
| Myosis |
40 |
13 |
| Diminution of light reflex (unilateral) |
35 |
11 |
| Abolition of accommodation reflex |
35 |
11 |
| Diminution of accommodation reflex (bilateral) |
29 |
9 |
| Abolition of accommodation reflex (bilateral) |
26 |
8 |
| Diminution of accommodation reflex (unilateral) |
23 |
7 |
| Fundus changes |
21 |
7 |
| Vascular changes |
16 |
5 |
| Abolition of accommodation reflex (unilateral) |
12 |
4 |
| Paresis of the third nerves |
10 |
3 |
| Ptosis |
9 |
3 |
| Irregularity of one pupil |
8 |
3 |
| Nystagmus |
7 |
2 |
| Visual acuity lost |
7 |
2 |
| Atrophy of disc |
6 |
2 |
| Total blindness |
5 |
2 |
| Paralysis of the fourth nerves |
1 |
1 |
216
Can neurosyphilis exist in the absence of positive
findings in the spinal fluid?
Case 56. There was no great difficulty in setting up a
diagnosis of general paresis in the case of James Burns, a
mechanic of 31 years of age, who came voluntarily to the
Psychopathic Hospital for treatment. The point in Burns’
case was that the spinal fluid proved entirely negative in all
respects despite the fact that the serum W. R. was positive,
and despite the following facts of history and mental examination.
The patient claimed syphilitic infection seven years before,
namely, at 24 years of age, and also claimed that he had
infected his wife, who was in fact at the time undergoing antisyphilitic
treatment. He complained of insomnia, worry,
depression, hypersensitivity to noises (such as those made
by his own children), thoughts of suicide, and amnesia. The
amnesia, however, might be regarded as subjective since our
tests failed to show amnesia. Nor was there any diminution
in arithmetical ability. Despite the patient’s claim that
he had been “way off in his way of thinking,” there appeared
to be no delusions. Beyond a certain flightiness in conversation,
we could hardly get any evidence of psychosis unless of
the neurasthenic order.
Physically, however, the left pupil failed to react to light
though it was found to react to distance, and the right pupil
exhibited a diminution of its reaction to light. There was
no ataxia of gait, yet there was a complete Romberg reaction.
There was a moderate tremor of the hands and of the tongue.
Otherwise there were no reflex disorders upon systematic
examination, nor was there any demonstrable disorder in the
rest of the physical examination.
1. What is the diagnosis in the case of James Burns? On
the whole we agree with Nonne, that negative spinal
fluid findings (of course, in the absence of treatment)
preclude the diagnosis of general paresis. The symptoms
217might possibly be explained, however, by means
of a localized syphilitic involvement of the cerebrum,
no cells or products of inflammation having penetrated
to the spinal fluid. According to Head and Fearnsides,
this condition may be found especially in the anterior
or middle fossa. Accordingly, going upon these views
of Nonne and of Head and Fearnsides, we should be
entitled to make, perhaps, a diagnosis of cerebral
syphilis.
2. What is the significance of the Argyll-Robertson pupil in
James Burns? Nonne states that if one follows cases
with Argyll-Robertson pupil over a sufficient period
of years, they one and all eventuate in active symptoms
of cerebrospinal syphilis (not necessarily of the cortical
type), and this despite the fact that the pupillary change
may have been present a number of years before any
other symptom had developed.
218
Neurosyphilis (“DISSEMINATED ENCEPHALITIS”)
within seven months of initial infection.
Autopsy.
Case 57. We borrow the main features of a remarkable
case examined at the Danvers State Hospital clinically by
Dr. H. W. Mitchell and reported elaborately by Dr. A. M.
Barrett. This case, whom we shall call John Summers,
acquired syphilis at about the end of the third week in May,
1902, and consulted a physician on June 12, at which time
a characteristic initial lesion of syphilis was plain. Summers
was excessively alcoholic at times and was not seen by a
physician again until July 2, just after an alcoholic debauch.
At this time there was ulceration of the primary lesion, and a
papillary eruption had developed over the arms, chest,
abdomen, and legs. Mercurial treatment and mixed treatment
were given. Arthritis occurred but disappeared with
increased dosage.
About six months after infection, the patient developed
severe headaches, hardly controllable by treatment. Amnesia
and a certain stupidity, with neglect of personal habits, and
even of eating, developed, whereupon Summers was admitted
to the Danvers Hospital, December 11, 1902. He weighed
124 pounds, was extremely feeble, with dull and expressionless
face, coarse purposeless movements of arms; left pupil
larger than right; right external strabismus and ocular ptosis;
increased knee-jerks, crossed adductor reflex, coarse tremors
of arms and hands; and extreme clouding of consciousness.
It was doubtful whether the pupils were stiff to light or not.
The patient died on the ninth day, December 18, in a
state of coma. After admission, his stupor had become more
marked; there had been incontinence of urine and fæces,
and the patient could be aroused only by loud tones.
Difficulty in swallowing had developed; the right-sided
ptosis had become more marked, and muscular twitchings
had developed on the right side. When the left leg was
pinched, there was twitching of the left leg and arm. There
was slight spasticity of the right arm and leg. An examination
upon the day of death definitely showed a lack of reaction of
the pupils to light.

1. Exudate in pia mater—mononucleosis.
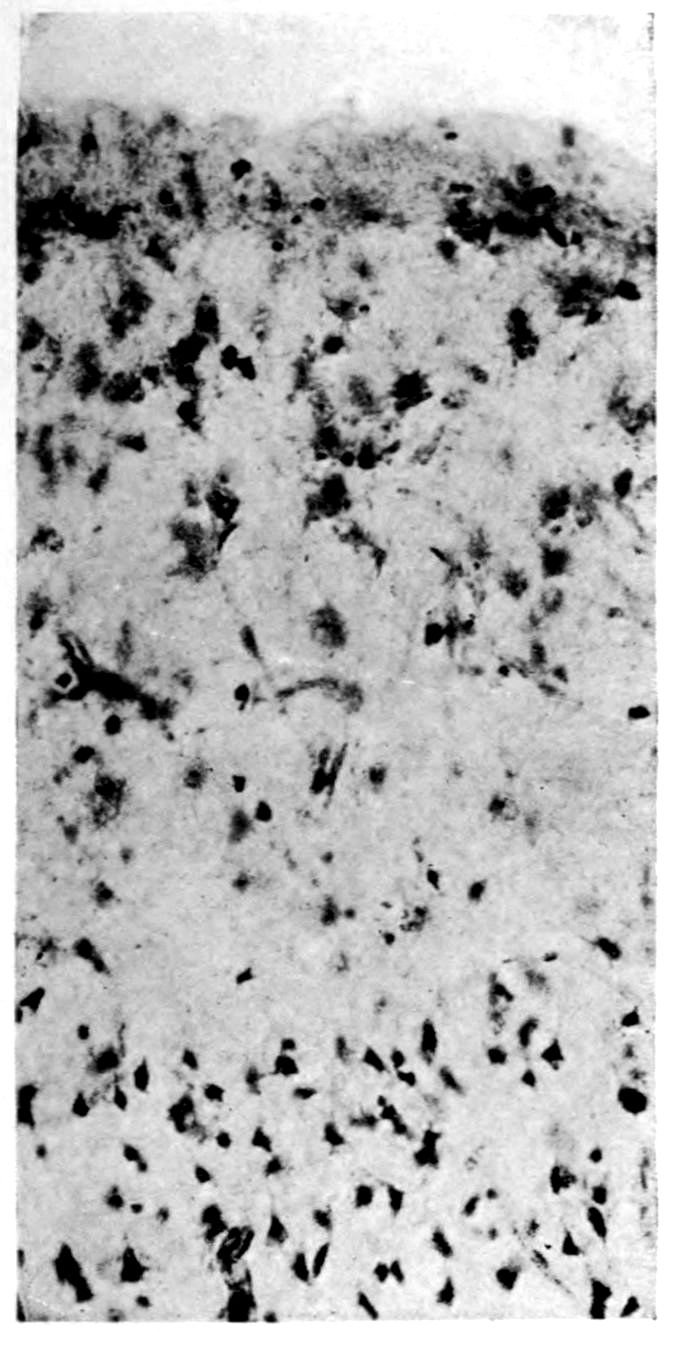
2. Superficial (subpial) cellular reaction of neuroglia tissue (expanded cell bodies).

3. Cellular gliosis of deeper layers of cortex. Apparent increase in capillary supply, possibly relative to loss of neural elements.
Case 57. Neurosyphilis (“disseminated syphilitic encephalitis” of A. M. Barrett), fatal seven months from initial infection. (Photographs by A. M. Barrett.)
219Dr. Barrett was able to find in the literature a case of
Bechterew which histologically resembled his own case, but
though in the instance reported by Bechterew the first symptoms
developed within the year following infection, death did
not occur until two years later.
In view of a total duration of symptoms clearly not over
seven months, it is interesting to inquire how far microscopic
brain changes could have proceeded. Neither calvarium
nor dura mater showed changes. There was a slight
haziness of the pia mater over the convexity, but the pia
mater over the base (especially below the cisterna and from
thence spreading out over the pons and into the fissure of
Sylvius) was not only hazy but definitely thickened and
hyperæmic. The thickening was most marked about the
root of the right third nerve (corresponding with the eye
findings in life). There was also a macroscopic thickening of
the left Sylvian artery. Section of the brain showed nothing
abnormal except a small area among the pyramidal fibres
of the right side of the pons, where there was a single hemorrhagic
area about 7 mm. in diameter around which there
were small punctiform hemorrhages. (Compare twitchings
of left leg and arm upon stimulation of left leg, and note
also the muscular twitchings and slight spasticity of right
leg and arm noted just before death.) This case was examined
and reported upon in 1905. We learn from Dr. Barrett
that a re-study of the case with modern methods has failed
to demonstrate a spirochetosis.
The meninges show infiltration and destructive and proliferative
changes of the blood vessels. Condensed extracts
from Dr. Barrett’s full report follow:
There were local variations in the severity of the
meningitis. The sulci showed the most marked infiltration.
The slighter degrees of exudation were
made up largely of lymphocytes with a few plasma
cells, occasionally large mononuclear cells, and rarely
220a polymorphonuclear leukocyte. Where the exudation
was more extensive, the large mononuclear cells became
more common and the polymorphonuclear leukocytes
increased in number. The large mononuclear cells were
often phagocytic, containing from one to six leukocytes.
The exudate was always most abundant about the
blood vessels. The plasma cells were always most
numerous in the adventitia of the veins, here greatly
outnumbering the leukocytes. The polymorphonuclear
leukocytes were relatively infrequent except where there
were necrotic areas, which areas were usually continuous
with an infiltration of a vessel wall.
As to vascular changes, the media was not often
involved, nor was the adventitia so often affected as the
intima. Such lesions as appeared in the intima and
adventitia were infiltrative rather than proliferative.
The elastica of the blood vessels proved to show but
slight changes.
A characteristic change was the endarteritis,—of a
focal nature with a few large mononuclear and lymphocytic
cells pushing the intima inward at the edge of a
lesion. In the more marked portion of the focal process,
the thickness of the intima was greatly increased by
proliferation. Great numbers of large mononuclear
cells could be seen between the intima and the elastica.
About these cells and interlacing among the other
elements of the proliferating tissue was an excess of
connective tissue fibres.
The meningeal veins were more often diseased than
the arteries; there was adventitial infiltration with
lymphoid and plasma cells; sometimes the vein walls
had become necrotic and infiltrated with polymorphonuclear
leukocytes.
It will be remembered that the left Sylvian artery
was grossly thickened, and microscopic section of this
vessel showed a partial thrombosis.
The brain showed diffuse and focal changes. The
diffuse process was one of nerve cell degeneration and
proliferative changes in the neuroglia and blood vessels,
and no section of the many examined proved to be free
from such changes, although in the majority of instances,
these diffuse changes were slight. The cortical layers
showed more of these diffuse changes than did the
white substance. Barrett considered that the glial cell
changes were more delicate indicators of the cortical
changes than the nerve cell changes. He found rod
cells, satellitosis, superficial gliosis, and a large gamut
of changes in the neuroglia. There were two rather
characteristic nerve cell changes: a shrinkage change
going on to almost complete destruction, and a type of
cell swelling, also apparently proceeding to complete
destruction.
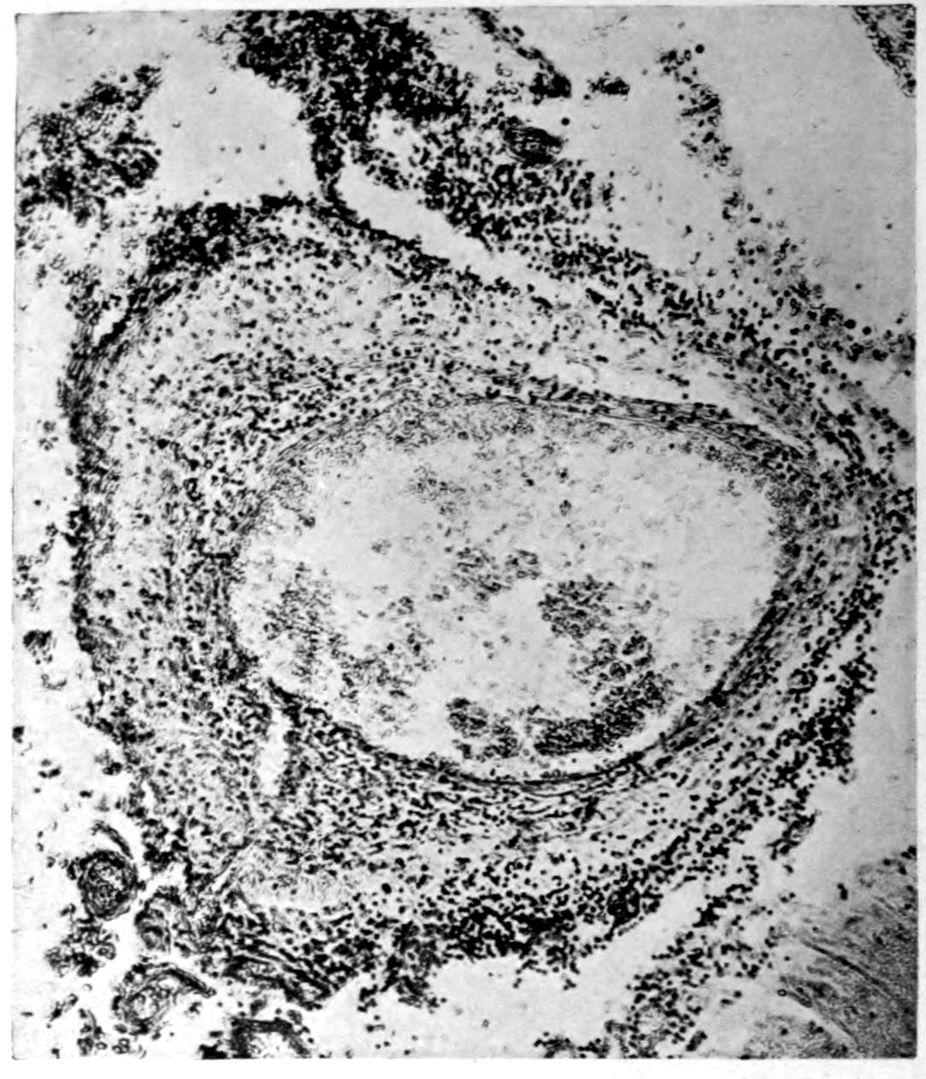
4. Arteritis of pia mater.
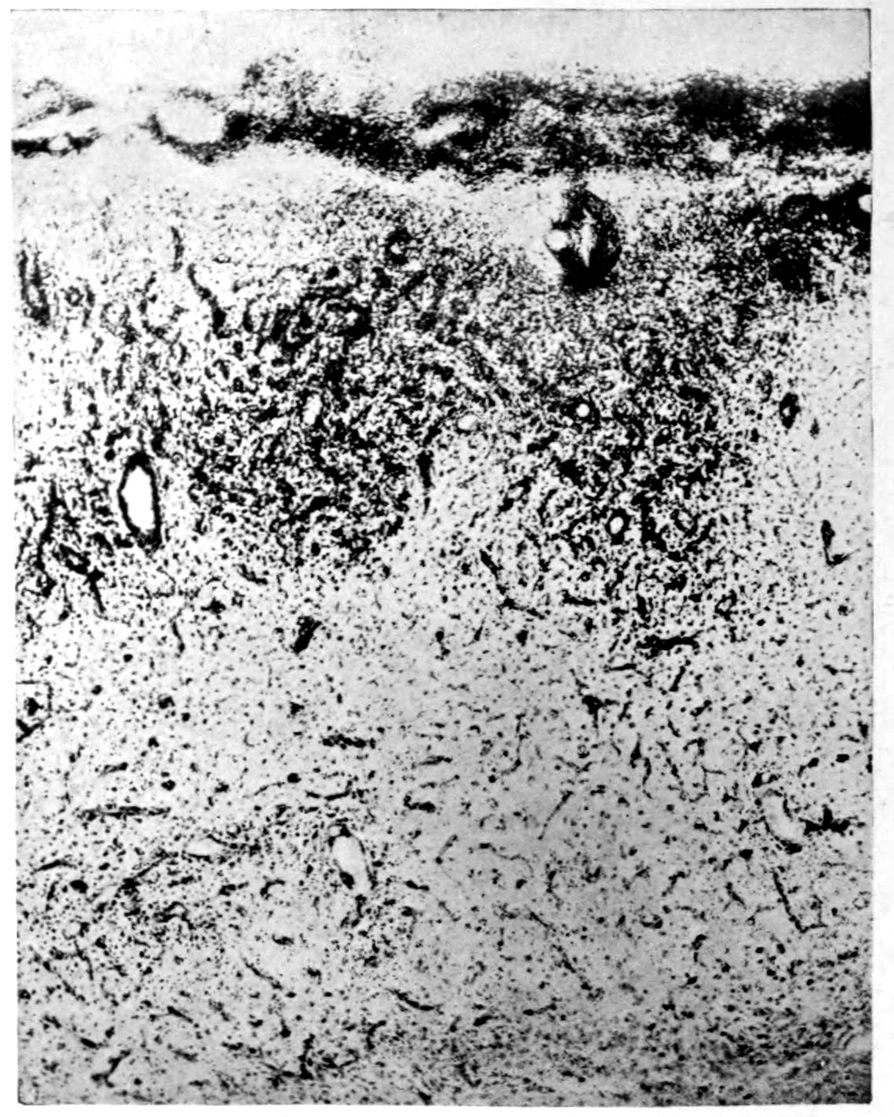
5. Focal vascular lesions.
Case 57. Seven months from infection. “Disseminated syphilitic encephalitis,” Barrett. (Photographs by Barrett.)
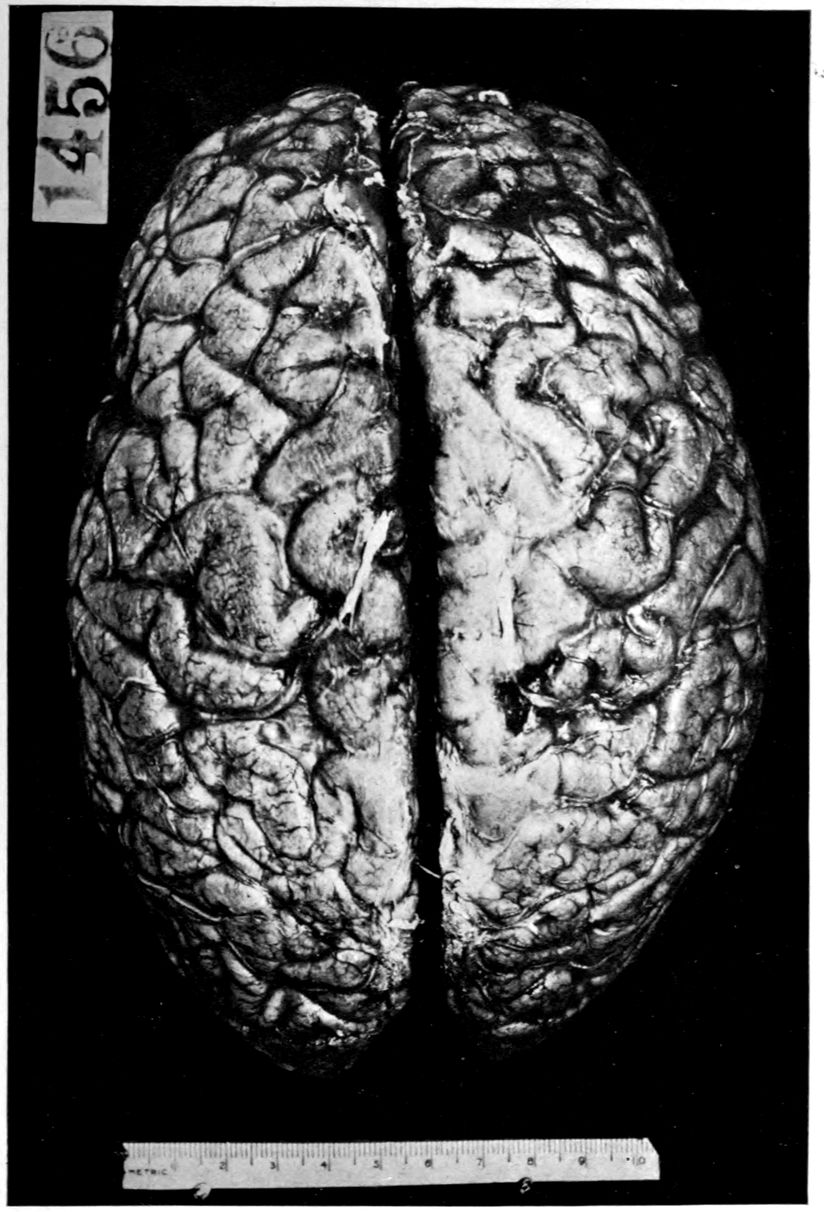
Paretic neurosyphilis (“general paresis”)—cerebral atrophy, without meningitis. Therapeutics cannot hope to restore lost tissue.
Duration. 3 years from beginning of well marked symptoms; 6 years from beginning of obvious symptoms; 12 years from a so-called “nervous prostration.”
221Among focal changes, there were four main types:
Areas of encephalitis, having the general appearance
of granulation tissue, areas of simple necrosis or softening,
apparently directly related to vascular changes
near by, hemorrhages, and certain foci regarded as
gummatous.
Save for pial infiltration and a few vascular changes,
there was very little change in the medulla and spinal
cord. There was a hypertrophic gliosis of the margin
of the medulla and cord throughout, and a focal lesion
of well marked gliosis at one point in the bulb. There
were no fibre degenerations in the medulla or cord, nor
were there any coarse fibre degenerations in the cortex
itself except in one locus, the left gyrus rectus. This
case is of peculiar value in showing to what extent
lesions may proceed in a period of six to eight months
after primary infection.
Of course the case is in one sense entirely atypical. The
lesions were not confined to the nervous system. Aside from
the maculo-papular eruption and ecchymosis of the skin,
there was a diffuse hemorrhage of the inner half of the conjunctiva
of the left eyeball, a small hemorrhagic focus in the
mitral valve, a caseous nodule, one cm. in diameter, in the
apex of the left lung whose tuberculous or syphilitic nature is
left in doubt; a broad milk-colored patch of thickening of
the capsule of the liver. It is to be noted that there were no
gross lesions of the aorta.
222
On the classical assumption that PARETIC NEUROSYPHILIS
(“general paresis”) is a fatal
disease, is there a disease PSEUDOPARETIC
NEUROSYPHILIS (“pseudoparesis”) which may
recover or pursue a long course like that of a case
of diffuse neurosyphilis (“cerebrospinal syphilis”)?
Case 58. Peter Burkhardt had been an efficient highway
inspector, but in his forty-fifth year he had begun to be unable
to do his work satisfactorily. His wife had become somewhat
afraid of him. He had had somnolent spells in his chair and
had squandered money. The mental symptoms had lasted
for some six months, but had become more marked during
the month preceding admission. Burkhardt would at times
fail to recognize his friends.
The general physical condition of Burkhardt was very good.
The pupils were irregular and reacted sluggishly both to light
and to accommodation. The knee-jerks and ankle-jerks were
absent. There were no other neurological disorders upon
systematic examination. There was a speech defect. Mentally,
little could be determined except a certain sluggishness.
History and physical examination at once suggested general
paresis. The serum W. R. was doubtful, but the spinal
fluid reaction was positive, as was the gold sol reaction (which
was “paretic”); the globulin and albumin were greatly
increased; there were 48 cells per cmm. Antisyphilitic
treatment, consisting of salvarsan twice a week and potassium
iodid by mouth, was followed by a rapid mental improvement.
After two months, Burkhardt was discharged apparently
normal, with all the blood and spinal fluid tests negative.
He has been taken back into the highway service.
1. What is the proper definition of pseudoparesis? Fournier
termed pseudoparesis certain cases that looked like
paresis but were not syphilitic in origin. Of these
cases the most characteristic group is that of alcoholic
pseudoparesis. It is clear that there will be no difficulty
223in the definition of a disease pseudoparesis whose
entity is presented in the adjective that precedes the
term (e.g., alcoholic pseudoparesis). According to this
usage, a case of pseudoparesis would be one in which the
symptoms and possibly some of the signs somewhat
resemble the symptoms of paresis itself but for which
another etiology could be fairly established.
2. Are there any cases of syphilitic pseudoparesis? We are
of the opinion that the term should be dropped. It is
true that there are cases which clinically look like general
paresis and exhibit the appropriate laboratory signs
of general paresis but seem to differ from paresis in their
course even when they receive no treatment whatever.
In the present phase of doubt as to the classification of
paretic and non-paretic forms of neurosyphilis, it seems
to us of doubtful utility to characterize a case as pseudo
simply because it differs in its course, particularly as
the literature has always duly recognized that a number
of cases of general paresis have had long courses and
sometimes very long remissions.
There is also another group of cases that have been
termed cases of pseudoparesis, namely: certain cases of
neurosyphilis which clinically look like general paresis
and seem to be following its classical course but are
interrupted by treatment. Here again it seems to us
doubtful whether the designation pseudo should be
attached to this group of cases, particularly while the
whole therapeutic question in the paretic group of neurosyphilis
cases remains sub judice. Accordingly we are
tempted to include in the group of paretic neurosyphilis
cases that either get well of themselves, or get well under
treatment, or pursue a very long course, or are subject
to very long remissions. But we make this decision in
terminology without prejudice to the therapeutic question
and it is open to any critic to throw these cases into
an atypical non-paretic group of neurosyphilis cases.
3. How shall we explain the absence of ataxia of case Burkhardt
when knee-jerks are absent and when, therefore,
we are entitled to conclude a certain degree of spinal
disease? As stated in connection with case Sullivan
(16), the absence of knee-jerks is not a warrant for
terming a case—paresis of the tabetic form. The fact
is that the lesion in paresis tends to be intraspinal,
just as the higher brain lesions tend to occur within the
brain substance. The meninges are relatively spared
both within the cranium and within the spinal canal.
224The characteristic degeneration of posterior nerve
roots which we find in tabes dorsalis is not necessarily
found in general paresis even when there are somewhat
extensive spinal lesions. Accordingly the absence of
sensory returns by way of the posterior nerve roots
which characterizes tabes dorsalis is not necessarily a
phenomenon of general paresis. The mechanism by
which the knee-jerks are lost depends upon histological
detail. They may be lost when under tabetic
conditions the posterior roots are severely diseased
and when under paretic conditions only intraspinal
collaterals or a small portion of fibres are affected.
The whole question hinges upon where and to what
degree the various reflex arcs are cut in the disease.
The tabetic phenomena are, as so commonly stated,
intradural; that is, the sensory or gangliospinal neurones
at certain levels are affected all the way in from the
points at which they pierce the dura mater. The affection
of these and other neurones in general paresis is
an intraspinal and parenchymatous affection.
225
Neurosyphilis; auditory hallucinations; ideas of
persecution; attacks of excitement. SYPHILITIC
PARANOIA (Kraepelin)?
Case 59. Bridget Curley was a case that was discharged
from the Psychopathic Hospital, recovered, after 26 days in
hospital. The symptoms so resembled those of alcoholic
hallucinosis that the diagnosis was made despite the fact that
the patient consistently denied the use of intoxicants. There
was, in fact, no proof that she drank alcohol. The case was,
however, not clearly one of alcoholic hallucinosis or of any
other well-defined form of mental disease. A provisional
diagnosis of manic-depressive psychosis, manic phase, had, in
fact, also been made.
The illness had begun with depression and inactivity,
Bridget’s friends accounted for these conditions on the ground
that a lover had departed for Ireland. A few days after the
depression began, Bridget became dizzy and refused to give a
boarder his breakfast, stating that she had lost her memory
and had begun to hear bells ringing and people talking. She
then became greatly excited and was brought to hospital,
where the prolonged baths quieted her.
It seems that Bridget had had stomach trouble and headaches
at the top of her head or sometimes in her temples.
Physical examination showed the left pupil to be larger than
the right, a slight tremor of the lips, a slight systolic murmur
at the apex, slightly irregular pulse, and moderate edema of
ankles. The blood serum was negative to the W. R., but
lumbar puncture was executed and the fluid showed a positive
W. R.
The patient was tested by the Binet and other methods,
and although 35 years of age, seemed to be by the mental
tests hardly over 11 years old. She was inclined to be feverish,
somewhat restive, and pugnacious; rather slow of
speech, sometimes refusing to answer and grimacing. Her
pugnacity was, however, easily controllable, and the excitement
226was largely at night. This excitement subsided rapidly
in the course of a few days.
1. What is the diagnosis in this case? The following diagnoses
and suggestions for diagnosis were made at the
staff meetings:
- Unclassified mania.
- Manic-depressive psychosis, manic phase.
- Toxic delirium.
- Dementia praecox.
- Bacterial infection of the brain.
- Unclassified delirium.
- Acute delirium.
- Infectious psychosis.
- Acute confusional psychosis.
- Psychopathic personality by use of alcohol.
- Mental deficiency with atypical mental state.
- Syphilitic paranoia.
2. Is this a case of syphilitic paranoia? The so-called syphilitic
paranoia of Kraepelin is a rare and uncertain type
of syphilitic mental disease. Delusions and hallucinations
are prominent. As a rule, the onset is stated
to be slow and insidious, or at any rate there are a
variety of indefinite prodromata. Jealousy is a prominent
feature, sometimes attended with marked sexual
excitement. Auditory hallucinations and ideas of
persecution are particularly in evidence. The most
striking feature in Kraepelin’s group was a sudden occurrence
and equally sudden disappearance of violent
excitement, with or without external cause. Thus,
an excitement would be produced by a few words
spoken, and immediately after, the phase of excitement
would pass and the patient would become entirely
friendly and accessible once more, as if nothing had
happened. About half of Kraepelin’s cases showed a
positive serum W. R. He does not report lumbar
puncture findings, and grounds the existence of disease
upon certain autopsied cases. The speech and writing
disorder of paresis as well as the characteristic disorientation
for time and muscular weakness of general
paresis were absent in the group. It appears that
most cases of the group have hitherto been placed in
dementia praecox.
227
The clinical symptoms of CHRONIC ALCOHOLISM
are sometimes largely identical with those of
PARETIC NEUROSYPHILIS (“general paresis”):
differentiation by means of the laboratory findings.
To demonstrate this proposition, the cases of Francis
Murphy (60) and David Collins (61) are in point, being
sharp foils to one another.
Case 60. A laboring man about 44 years of age was brought
to the Psychopathic Hospital one summer day, in a stupor.
This patient, Francis Murphy, had been at his regular work
as axeman in the Park Service, when he suddenly fell in a
heavy convulsion. He was carried to a general hospital,
still in convulsions, and ether was administered to quiet
the movements. The convulsions shortly ceased, but the
patient’s consciousness failed to clear; hence his transfer to
the Psychopathic Hospital.
Here he remained much disturbed and was placed in a room
with a mattress on the floor. On this mattress he would
crouch on all fours for a considerable time, looking fixedly
downward as if at an object on the floor, unresponsive to
questions but compliant with efforts to place him on his back.
He gave the impression of daze and either disorientation or
confusion.
Within twenty-four hours the patient became more tranquil
and consciousness became clearer, but the patient was at
a loss to bring to memory either recent or remote events.
However, he replied to questions, giving some different story
each time he was approached. Curiously enough, the patient
seemed very contented and good-natured and would even
laugh foolishly at times, saying that he felt fine and all
ready to go out to work.
The general impression conveyed by Francis Murphy at
once suggested the possibility of neurosyphilis. Convulsions,
perhaps initial in middle age, with a post-convulsive
228stupor, followed by a partial clearing up, with persistent
amnesia and a suggestion of fabrications with euphoria, bore
out the suggestion.
The physical examination strengthened the impression
of neurosyphilis. Well developed and nourished, florid, with
a manual tremor and sweating of the palms, the patient
was in general without physical symptoms. Neurologically,
however, whereas the left pupil was larger than the right and
reacted properly to light, the right pupil was a bit contracted,
somewhat irregular, and either reacted not at all to light or
very slightly so (reacting perfectly to accommodation). The
knee-jerks could be obtained only with reinforcement, and
several other reflexes could not be elicited (triceps, radial,
ulnar, periosteal, Achilles, umbilical). Moreover, the heel-to-knee
test was poorly performed; some of the common tests
phrases were very poorly repeated; there was marked tremor
in writing; and the paragraphia seemed to be not merely
peripheral, for syllables were left out in words and ordinary
words spelled incorrectly (psychographic disturbance).
We do not care here to insist that the right pupil was really
an example of the Argyll-Robertson phenomenon since the
slightest tinge of doubt is important if a positive diagnosis
is practically equivalent to asserting syphilis. Practically,
however, the right pupil was regarded as an Argyll-Robertson
pupil under hospital conditions (flash-light reaction). Argyll-Robertson
pupil, areflexia, speech disorder, writing disorder,
memory disorder, conduct disorder, and euphoria, all with a
history of convulsions, certainly warranted the tentative diagnosis
of neurosyphilis.
As usual, resort was made to the W. R. in the serum and in
the spinal fluid. One of the first results to come through
from the laboratory was the absence of globulin, normal
albumin, negative gold sol reaction, and a cell count of two
cells per cmm. in the spinal fluid. Later the W. R.’s were
returned negative for blood and spinal fluid.
In the meantime, an illuminating change had occurred in
the patient, for two days later,—three days after the first
convulsion in the park,—the patient had apparently quite
recovered; his consciousness became nearly clear; he could
229remember every event up to the time of the convulsion, and
his memory came back in appropriate degree for both remote
and recent events.
The patient, it appeared, had for some time been drinking
more and more heavily. In recent days, he had been taking
five or six whiskeys and a half dozen beers daily on the
average, and often much more. About ten years before, the
patient narrated, there had been a convulsion at a ballgame,
and this convulsion the patient himself called a “rum fit.”
Here, then, is a case of Alcoholic Pseudoparesis. Without
the W. serum test and without the spinal fluid examination,
it is probable that the diagnosis of general paresis might
have clung to the patient for some time on account of the
apparent Argyll-Robertson pupil, which had to be accepted
as such on the flash-light data. In point of fact, in this case
the pupil later reacted more normally to light, and the speech
and writing disorders measurably cleared up.
1. Can alcohol produce the Argyll-Robertson pupil? The
majority of neurologists would today answer, Yes.
2. If in the case of Francis Murphy, the W. R. in the blood
had happened to be positive on account of a non-neural
syphilitic infection (spinal fluid negative), would the
diagnosis general paresis be warranted? Probably the
diagnosis general paresis would have been made. If
the patient had been lost to observation, he might
well have been regarded as an atypical paretic with
prodromal convulsions.
3. Would positive globulin and excess albumin in the spinal
fluid alone or in association with a positive serum W. R.
warrant the diagnosis general paresis or neurosyphilis?
The chances are that most neurologists would advocate
proceeding to treatment in any case of positive serum
reaction, whether or not there was globulin or excess
albumin; but the positive globulin and excess albumin
would probably not warrant the diagnosis general
paresis or neurosyphilis in the absence of excess cells
and the characteristic gold sol reaction and W. R. in
the fluid.
4. Is the case of Francis Murphy one of alcoholic epilepsy
(as suggested by Murphy’s own phrase, “rum fits”)?
It must be remembered that epileptics become alcoholic
and that epileptic convulsions increase or become
230more severe with alcoholism. On the other hand, the
literature indicates that alcoholism can produce convulsions,
as can many other factors. The literature
also indicates that there is a condition of epilepsy in
which the convulsive tendency sets in as a result of
alcoholism in a patient not previously disposed to epilepsy;
it appears also that sometimes, though very
rarely, the epilepsy continues after withdrawal of alcohol,
and even after giving up the habit. Francis Murphy
appears to have had but two spells of convulsions, both
of them following heavy bouts with alcohol. There is
so far, then, no warrant for calling Francis Murphy’s
case one of alcoholic epilepsy.
5. Does the use of alcohol by a subject destroy the value
of the W.R.? It has been held by some that alcoholism
interferes with the accuracy of the W. R. This
has not been our experience and for the present we
are of opinion that the results have the same value
in alcoholics as in non-alcoholics. The next case
(Collins, 61) is one in which a positive W. R. occurred
in an alcoholic. When dealing with paretic neurosyphilis
it is especially true that the W. R. is disturbed
very rarely, if at all, by toxins or drugs, except antisyphilitic
drugs.
231
Alcoholism may cloud the diagnosis of NEUROSYPHILIS.
Differentiation by laboratory tests.
Case 61. David Collins was a steamfitter of about 43
years of age, picked up at 6.45 a.m. in the midst of convulsions
and talking incoherently, in a state apparently of fairly clear
consciousness. On arrival at the hospital, the patient was
able to tell how he had always been a hard drinker, and how
during the past week of unemployment he had taken large
quantities of poor whiskey,—perhaps an average of a pint a
day. Collins also told how he had had delirium tremens several
times, but he said the present spell was quite unlike delirium
tremens. There was no disorientation or impairment of
memory, and the patient did not in any wise suggest a mental
case a few hours after admission.
It appears, according to Collins, that he had obtained some
work the night before, and had quit work about 6.30, whereupon
he stepped into a barroom, took one drink of whiskey,
left the barroom, walked down the street, and suddenly lost
track of the world, coming to consciousness in a carriage with
two policemen, but remaining, as he said, “dopy,” inattentive,
and confused. After a meal, however, the patient began
to feel better and soon felt quite all right.
The physical examination was quite negative except that
neurologically there was lingual and manual tremor, a speech
defect, apparent only with test phrases, unsteadiness of handwriting,
left knee-jerk greater than right, a left-sided Babinski
reflex, and a difficulty in executing rapid successive movements
(dysdiadochokinesis). This degree of neurological disorder
in our experience warrants lumbar puncture as well as a
serum test. The lumbar puncture shortly disclosed a positive
globulin and excess albumin, and the returns from the W. R.’s
were positive for both spinal fluid and blood serum. The
data of the gold sol reaction were not available on account of
technical difficulties. However, it appears that the diagnosis
of neurosyphilis could hardly be avoided in this case.
232David Collins differs from Francis Murphy, then, in showing
a positive blood and spinal fluid reaction for syphilis as
well as a positive globulin and excess albumin. As above
remarked, it is probable that the positive globulin and excess
albumin would not warrant more than a suspicion of neurosyphilis
taken by themselves.
Unfortunately, we were unable to persuade the patient to
submit to treatment, and from the patient’s point of view
possibly his decision, not to submit to treatment, was a good
one since he has had no symptoms of any sort for a period of 18
months since his episode. However, as abundantly elsewhere
demonstrated, we feel that the patient is wrong, and
that the physicians are right in urging treatment.
1. Is not the convulsive episode an alcoholic phenomenon
in David Collins entirely separate from the patient’s
general and neurosyphilis? Possibly; however, an
outbreak of neurological symptoms with spontaneous
recovery is not only consistent with the diagnosis of
syphilis, but somewhat characteristic of neurosyphilis.
We suspect that another attack will occur in David
Collins.[12] We shall from time to time make use of the
social service to suggest his going under treatment, and
shall employ his record of contact with a public institution
to drive in our suggestion. Still it is clear that
there are numerous cases in the community that are
not accessible to social service initiated from a public
institution. Accordingly, educational propaganda is
necessary for salvage of the middle- and upper-class
victims of syphilis. It is a little unfortunate that the
ethics of the private practitioner make such salvage of
middle- and upper-class persons not very likely. Might
it not be that an extension of state medicine to this
field would incidentally increase the amount of successful
private practice?
2. What may be the cause of such a convulsive episode as
that of David Collins? It would appear that the convulsions
of general paresis and of neurosyphilis in general
often occur without gross structural lesions of the
brain. It may be suggested that vascular irritation or
233parenchymal irritation by spirochetes, acting in appropriate
parts of the central nervous system, can produce
such convulsions.
3. What is the significance of the unilateral phenomenon in
David Collins (left knee-jerk greater than right; left-sided
Babinski)? The current explanation of hyperreflexia
is that somehow inhibitory impulses from upper
portions of the nervous system have ceased to influence
the local arcs that mechanize reactions like the knee-jerk
and the normal plantar reflex. The phenomena are
commonly found in cases with pyramidal tract disorder,
and in the case of David Collins one may suspect, therefore,
that there was a central disorder affecting the right
pyramidal tract above its decussation. One might
suspect that the convulsions were initiated by a lesion
(whether gross or microscopic in range) in the right
side of the cerebrum; but whether in the white matter
or in the gray matter must be left doubtful. The
clearing up of all symptoms suggests either that the
lesion was microscopic in range or that the phenomena
were transient and functional.
4. Can the dysdiadochokinesis be used to indicate cerebellar
lesion in David Collins? Possibly; but it does not
appear that the difficulty in executing successive movements
was unilateral. It seems impossible to bring
into close topographical relation the basis for the
Babinski and left-sided hyperreflexia, and the basis for
the dysdiadochokinesis. Alcohol is sometimes asserted
to exert an especial effect upon the cerebellum.
5. Must we suppose structural lesions, either (a) of the
nature of cell losses demonstrable microscopically, or
(b) of the nature of secondary degenerations demonstrable
by Weigert myelin sheath methods, in the case
of David Collins? It appears that we do not need to
assert the existence of such lesions.
6. Could the hyperreflexia and the Babinski reaction be due
to local spinal cord disease? Possibly; but the existence
of other neurological symptoms (lingual and manual
tremor, speech defect to test phrases, ataxic handwriting,
and dysdiadochokinesis) makes it probable
that there were lesions, or at any rate disordered functions,
within the cranium; and there appears to be no
basis for asserting local spinal cord disease.
234
Differential diagnosis between NEUROSYPHILIS
and ACUTE ALCOHOLIC PSYCHOSIS.
Case 62. Joseph Buck was a chef of 60 years who came in,
seeking advice because his memory was getting poor; he
was unable to remember names and what he was about to do.
He was tremulous and had much pain in his limbs. He had
been drinking heavily for weeks,—probably ten weeks;
in fact, he described himself as having had “the shakes”
and as having lately seen animals and people that were unreal.
He had had the shakes before and the condition had lasted
for two to three days after alcohol was discontinued.
Physically, Buck was tall, well developed, although poorly
nourished, with a skin suggesting alcoholism. There was
a slight acne over the back and chest; there was a slight
enlargement of the heart, with blood pressure, systolic, 180,
diastolic, 120. There was a corneal opacity of the left eye,
which the patient said was the result of syphilis following a
chancre, which he had acquired at the age of 27. There
was also a ptosis of the upper lid of the left eye. The right
pupil was irregular and reacted to light sluggishly, and with
a very small excursion. The patient was slightly deaf in
both ears. The deep reflexes were all lively and equal. The
tremor was most marked in finely coördinated movements.
There was a slight swaying in the Romberg position but the
sign could not be said to be present. The gait was unsteady.
There was a marked tenderness over the nerve trunks.
So far as mental examination went, it seemed that the
patient’s claim of amnesia was subjective. There was certainly
no more amnesia than a slight difficulty in recalling
details. The diagnosis of alcoholism with convalescence
from delirium tremens would certainly seem to have been
sufficient for the phenomena, and the suggestion of alcoholic
neuritis only confirmed the picture. To be sure, one might
expect a diminution or absence of deep reflexes; still, these reflexes
may be overactive in an irritative stage of the disease.
235Naturally, however, the history of syphilis and the pupillary
phenomena and ptosis, made the consideration of neurosyphilis
necessary. Both serum and fluid W. R.’s proved
positive; there was an excessive amount of albumin and
globulin, the gold sol reaction was typically “paretic,” and
there were 377 cells per cmm.
The patient improved upon a rest treatment and was
given injections of mercury for his syphilis. After a few
months he felt well enough to return to work, and continued
at work throughout a season, receiving mercurial treatment
throughout this time. A spinal fluid examination fifteen
months later showed a weaker gold sol reaction, reduction
in the amount of globulin and albumin, and but 26 cells to
the cmm. The W. R.’s had remained positive.
1. What are the forms of syphilitic neuritis? According to
Nonne, syphilitic neuritis and polyneuritis have at
last acquired standing in neuropathology. The older
claims depended upon findings on palpation and recovery
after antisyphilitic treatment. Since the introduction
of salvarsan, cases of ophthalmoplegia,
facial, acoustic, and optic nerve disease, as well as
neuritis of the extremities, have been reported in large
numbers. These phenomena are to be regarded as
neurorecidives in the modern sense of that term. The
neurorecidive is not a salvarsan effect, but is an effect
of the syphilitic process itself, settling in the peripheral
nerves. Paresthesias are especially prominent in peripheral
mono- or polyneuritis, and this point is of some
value in differentiating the syphilitic peripheral neuritis
from root neuritis. Root neuritis is more often characterized
by neuralgic attacks. Objective hyperæsthesia
of neuromuscular origin is also found in these cases,
demonstrated by pressure on the nerves. The motor
phenomena consist in a flaccid paresis or paralysis,
especially affecting the radial, ulnar, and peroneal
nerves. Nonne states that it is rare for syphilis to
affect a single nerve region, and he regards cases in
which a single region alone is affected as usually due to
a local gummatous process.
2. What is the significance of 377 cells per cmm.? See
discussion of Washington (Case 66).
236
Differential diagnosis between NEUROSYPHILIS
and CHRONIC ALCOHOLISM.
Case 63. Albert Fielding, 46, was an insurance broker,
who was brought to the hospital for excessive alcoholism.
Indeed, he showed all the signs, both of chronic and acute
intoxication, except that there was no nerve trunk tenderness.
Fielding was very loquacious though his speech was rather
thick. He showed tremor of hands and an alcoholic skin.
Physical and neurological examination proved entirely negative.
Fielding claimed that he had had a nervous breakdown at
about 36 years of age, after disappointment in love. He had
the drinking habit and began to drink more and more. He
had now become nervous and tremulous and had to drink in
order to brace himself. After a few days, the patient began
to be much better, having recovered from acute alcoholism.
Mental examination now showed good memory with orientation
intact. There was a certain tendency to reminiscence
and to somewhat childish actions. He had attempted to stop
drinking but had been unable to quit. As a matter of fact,
his mother and father had been excessive drinkers and he had
inherited the tendency, etc.
The diagnosis seemed to be plain. The routine W. R.
upon the blood serum was negative. However, the patient
had remarked during the history taking, that he had had a
chancre and secondary symptoms of syphilis. Accordingly,
lumbar puncture was resorted to. The fluid showed a slightly
positive W. R.; the gold sol reaction was of the syphilitic
type; there was a considerable increase in albumin and
globulin, and there were 20 cells per cmm. The diagnosis
of neurosyphilis seemed clear.
Course: The patient received six months’ treatment in a
sanatorium but the symptoms remained almost as before,
and the patient showed the same childishness and inability
to take care of himself. Since the symptoms continued six
237months after the withdrawal of alcohol, it might well be
suspected that the condition was more than a merely alcoholic
one. However, in a number of purely alcoholic cases,
such long-standing effects are found: even as long as six
months or longer after the withdrawal of the alcohol, and one
might conclude therefore that Fielding was actually a victim
of alcoholic dementia. The spinal fluid after these six months
(during which period antisyphilitic treatment was given)
showed no change, and the prognosis was offered that the
case would probably develop into one of paresis.
A year later, after six months sanatorial care and six
months life in the community, the patient returned to the
Psychopathic Hospital in an alcoholic condition. The lumbar
puncture showed all signs negative except the W. R. which
was slightly positive. The W. R. of the blood was negative.
In connection with this case, see the case of paresis sine
paresi (25).
1. What is the relation of the syphilitic and alcoholic process
in Robert Fielding? One does not like to break the
so-called rule of parsimony in diagnosis, but it would
seem that the effects in Fielding are the combined
effects of syphilis and alcoholism.
238
Differential diagnosis between NEUROSYPHILIS,
DIABETIC PSEUDOPARESIS and BRAIN
TUMOR.
Case 64. A large and imposing person, Calvin Hall, 55,
had been employed as a doorkeeper and guard, in which
position he was on duty for 12 to 14 hours daily. Eventually,
however, he had begun to have a good deal of pain in the legs
and a few months before observation, one day, his legs gave
way and he fell to the floor. There was, however, no loss of
consciousness, and he was carried to a general hospital. The
result of an examination there was that his family was informed
that he had some nervous trouble.
Hall now began to be melancholy and wept a good deal.
His appetite and sleep remained intact. He felt too weak to
walk. At the end of about a year, he began to improve and
again became able to do a little light work. About a month
before coming to the Psychopathic Hospital, about two years
after the onset of symptoms, Hall suddenly began to talk
excessively, in a rambling and rather senseless way. A fortnight
later, he began to suffer from insomnia and restlessness.
Some medical facts were available: It seems that at 25
years this patient had become infected with syphilis though
there had never been any secondary signs. He was married
four years later but there had not been any children. Moreover,
for four years past, the patient had been treated for
glycosuria.
Upon admission, the patient’s sensorium was clear, but
his orientation was only partial. He could give a fair account
of his life, but it appeared that his memory was somewhat
impaired. There were auditory hallucinations (voices of
relatives). He often mistook the identity of persons about
him. He talked in a grandiose fashion of his great strength
and especially of a God-given power to read minds. His
flow of thought was rapid, rambling, circumstantial, and with
traces of irrelevance. He was rather continuously busy and
239at times restive. There was a good deal of emotional agitation
and apprehensiveness, and again the patient would
become suspicious and tearful.
Physically, there was a discharging sinus connected with
the right humerus, close to the elbow. The pupils, though
equal and regular, were sluggish in reaction to light. The
knee-jerks and ankle-jerks were absent. There was no Romberg
sign but there was some swaying in the Romberg position.
There was a moderate ataxia in walking. Glycosuria to a
moderate degree was determined. There were no casts or
albumin in the urine. The W. R. of the blood and of the
spinal fluid was negative. The albumin of the fluid, however,
was considerably increased. X-ray examination of the skull
yielded a suggestion of absorption of the posterior clinoid
processes of the sella turcica. The X-ray examination of
the arm in the region of the sinus showed a chronic osteomyelitis,
possibly syphilitic (or diabetic?).
The diagnostic problems in the case of Calvin Hall are
extremely intricate. There are clinical suggestions of general
paresis, not confirmed by the laboratory findings.
1. Are we dealing with a case of diabetic pseudoparesis?
Is the pain in the legs of like origin, and has a neuritic
process led to the absence of the knee-jerks? The
Allen treatment appears to have had no beneficial
result in this case.
2. Is there a tumor of the sella region, which could account
for the mental symptoms and the glycosuria? The
spinal fluid albumin might be regarded as consistent
with a variety of psychoses, including that of brain
tumor. We have to remember the definite history of
infection, the sterile marriage and the possibly syphilitic
osteomyelitis.
240
DIABETES AND NEUROSYPHILIS, relations?
Case 65. Donald Barrie, a man of 61, diabetic for several
years, had begun to worry about the diabetes, feeling that
he was about to die, and had gone so far as to make several
threats of suicide. Hence he was brought to the Psychopathic
Hospital for observation.
Barrie was rather well developed and nourished, although
he looked far older than he was. There was a marked arcus
senilis; the skin was dry and rough; the radial and other
accessible vessels were markedly sclerosed; abdomen obese;
right testicle very low with thickened and hard epididymis.
Neurologically there was little abnormal to discover. The
pupils were irregular; both reacted fairly well to light.
There was a slight tremor of the extended hands, and still
less of the tongue. The voice was slightly thick and the
patient stumbled somewhat on test phrases. Urine: specific
gravity, 1029; sugar; no acetone; no diacetic acid. Sugar 2
to 11 grams for 24 hours on ordinary diet. It proved impossible
to get the patient sugar-free, either by cutting down
the carbohydrates or by using the Allen method.
Mentally, the depression with reiteration of wrong-doing
and self-accusation because of the contraction of syphilis,
were the striking features. There was, to be sure, a slight
imperfection of memory for remote events; memory for recent
events and knowledge of current events was very poor.
Barrie claimed that his condition was entirely hopeless, that
his memory was exceedingly bad, and that he was no longer
capable of supporting his family.
1. What shall be said as to diagnosis in a man of 61 with
glycosuria, depression, amnesia, sluggish pupil, slight
tremor, slight speech defect, and a history of syphilis?
The W. R. of the serum proved positive, and also the
W. R. of the spinal fluid. The gold sol reaction of the
fluid was of the syphilitic type. There were 112 cells
241per cmm., there was an excess of albumin, and a large
amount of globulin. Accordingly, the diagnosis of
PARETIC NEUROSYPHILIS (“general paresis”), especially
in view of the laboratory findings, seems necessary.
2. What is the cause of the glycosuria? First: possibly
it has no relation with the syphilis; secondly: it may
possibly be due to a syphilitic involvement of the pancreas;
thirdly: it is barely possible that it is due to
syphilitic disease of the fourth ventricle or of the base
of the brain, involving the pituitary region. Perhaps
our case is too complex for analysis. At all events, the
case brings up the possibility of a syphilitic glycosuria.
3. Can the diabetes in the case of Barrie be explained as
syphilitic? Warthin of Ann Arbor has recently described
somewhat remarkable spirochete findings in
his autopsy material. The order of organic infection
according to frequency is: aorta, heart, testis, adrenal,
pancreas, nervous system, liver, and spleen. Warthin
has called attention to the relation of pancreatitis and
spirochetosis to diabetes in a recent review[13] of findings
in 41 autopsied cases from the University Hospital in
Michigan. Warthin found active luetic lesions in the
pancreas in 6 cases.
242
Hemianopsia in a case of neurosyphilis.
Case 66. Lawrence Washington, a colored cabman, 58
years of age, began to forget addresses given him by his fares.
Moreover, he could no longer see as well as before, especially
on looking toward the right side. He himself states that the
visual trouble dated back as long ago as his 39th year, at
which time he had a terrific pain in both temples, leading
back from the eyes. Washington thought that his vision
had been getting slowly but steadily worse ever since.
We got the impression that the amnesia claimed by Washington
was more or less subjective and he was found to be
well informed. This association of amnesia and impairment
of vision naturally suggests syphilis. The patient himself
stated that he had had a chancre at the age of 18.
We found the W. R. of the serum to be appropriately positive.
The W. R. of the spinal fluid was also positive though
weakly so. There was an excess of albumin; globulin appeared
in large amount; the gold sol reaction was of the syphilitic
type; there were 186 cells in the spinal fluid.
Is this case one of paresis or of some other form of cerebrospinal
syphilis? Let us consider the data of the physical
examination. On the whole, the patient was well preserved.
There was a slight radial arteriosclerosis, but on the whole
the cardiovascular system was almost negative. The blood
pressure was 100 systolic, 65 diastolic. Neurologically the
visual field of the left eye was somewhat limited, and there
was a temporal hemianopsia of the right eye. The ophthalmoscopic
examination showed a disseminated choroiditis on
both sides. The right pupil failed to react to light. The left
pupil reacted slowly. Both pupils reacted properly to accommodation.
The knee-jerks could be obtained only on reinforcement,
and when obtained, the right was apparently more active
than the left. The left Achilles was absent; the right present.
There were no other abnormal reflexes.
243The motility of the facial muscles was somewhat impaired.
Finger-to-finger and finger-to-nose tests were rather poorly
done. The muscle sense was good; there was no swaying
in Romberg position; and there was no speech defect.
We are unable to decide whether the case is one of the
parenchymatous type (paretic) or of the meningovascular
type of neurosyphilis. It is certainly rather unusual to find
hemianopsia in a paretic.
We have been unable to get definite results from the treatment
of this case, since the patient would not return for
months after getting an injection or two of salvarsan, on the
ground that he was improved enough and did not require
further treatment.
1. What conclusion can be drawn from the 186 cells per cmm.
in the spinal fluid? Ordinarily this finding would
indicate an active process. Some writers have claimed
that a cell count running above 100 per cmm. was an
indicator of diffuse non-paretic neurosyphilis. It does
not appear that this claim has been substantiated.
It is remarkable that this case shows an interval of 40
years between infection and the occurrence of definite
clinical symptoms. With respect to the cell count,
both in untreated and in treated cases, the following
conclusions from a recent article (Solomon and Koefod)[14]
are in point:
1. The number of cells found in the fluid of untreated
cases offers no definite information of prognostic
value.
2. One is not justified in drawing any conclusions
as to whether the case is cerebrospinal syphilis
or general paresis, nor the time the process has been
active, nor the severity of it, from the cell count.
3. The cell count may vary greatly from month to
month, or when the interval is but several days, while
at other times it may remain very nearly the same
after an interval of months.
4. Cases showing natural remissions may show no
reduction in the cell count, or other spinal fluid findings.
2445. Cases treated with salvarsan, either intraspinously
or intravenously, tend to show a more or less
rapid fall in the cell count. This count will, as a rule,
remain low during treatment, but is likely to rise when
treatment has been discontinued, but may rise during
treatment after having first fallen.
6. Cases may show remissions during treatment
and still have a pleocytosis.
7. Treated cases having the cell count fall to normal
may at the same time become very much worse and
develop more marked paralytic symptoms.
8. In general paresis the cell count in no way parallels
the other spinal fluid findings.
9. In cases in which the other tests show an improvement,
for instance cerebrospinal syphilis, the cell
count also readily and early drops to normal. At times
it may drop to normal before other spinal fluid tests
become negative; again it may be last to reach normal.
10. The change in cell count seen in syphilitic
disease untreated is also found in non-syphilitic diseases,
as brain tumor.
11. The cell count offers nothing of prognostic
importance in syphilis of the nervous system unless accompanied
by improvement of the other laboratory
signs.
12. The cell count is not an index to the predominance
of irritative or degenerative changes.
245
Case of CEREBRAL MALARIA and SYPHILIS:
simulation of PARETIC NEUROSYPHILIS (“general
paresis”).
Case 67. Joseph Temple, 45, who had been a sea-going
steamboat steward, was brought to the hospital in a semi-stupor.
He was entirely uncoöperative, often resistive, attempting
to bite the physician’s fingers, and for the most
part lying curled up. He was incontinent and tube-fed.
This phase, it seems, had begun the night before entrance to
the hospital. Twenty-four hours later, an extraordinary
change was noted. Temple became alert and attended to his
wants, began to eat well, and began to behave as normally
as probably he ever behaved.
He was now able to give a coherent history. It was now
January. In the previous September, he had left for Mexico;
he was returning when he suddenly fell to the deck, unconscious.
After this fall, he had not been well, having had
chills and fever. At the Marine Hospital, he had been
diagnosed as suffering from malaria, and was given quinine.
He had been delirious a short time in the hospital, not being
able to recognize his wife, who called. He shortly improved
so that his wife was able to take him home. Nevertheless,
headache, gastric distress, and intermittent vomiting continued.
A spell of confusion took place, two days before
admission. The patient tossed about, moaned, and failed
to recognize anyone. Malaria of the æstivo-autumnal type
was demonstrated in the hospital. The temperature always
remained at normal. He was somewhat emaciated and pale.
The pupils were small, somewhat unequal, and reacted though
poorly to light and distance. The tendon reflexes were
lively.
The W. R. of the serum was positive, and information from
the patient’s physician runs to the effect that there was a
syphilitic infection some seven or eight years ago, followed
by secondary symptoms, but the patient had refused to take
246any protracted treatment. The spinal fluid examination
was practically negative.
Mentally, the patient was euphoric, expansive, boastful,
and showed a marked emotional instability and considerable
memory defect.
1. Can the diagnosis of general paresis be made in Joseph
Temple? Certainly the acute confusion and the syncope
are consistent enough with the diagnosis, yet the severe
malaria makes it seem likely that the phenomena were
due to a cerebral attack of malaria, and such occurrences
are found in the æstivo-autumnal form of malaria.
Yet malaria would hardly explain the euphoria,
memory defect, and the pupillary findings, to say nothing
of the irritability and the active tendon reflexes.
Even if we regard the active tendon reflexes and the
irritability as malarial, the other phenomena remain
outstanding as exceedingly suspicious of paresis.
On the other hand, if we try to support forcibly the
diagnosis of general paresis, we are hardly able to explain
the negative findings in the spinal fluid.
In point of fact, a study of the patient’s past life
revealed a story that the mental traits of euphoria,
irritability, and memory defect had been characteristic
of the patient for many years. In fact, there is some
question whether the patient is not really to be regarded
as a moron of high grade.
Upon this basis, if we regard the confusional phenomena
as malarial and the persistent mental phenomena
as characteristic of a moron and somewhat exaggerated
by the disease, we have merely to explain the suggestive
pupils. As to these, it must be remembered that though
they reacted poorly to light, still they reacted somewhat,
so it is not a question of explaining an Argyll-Robertson
pupil, but only an impaired pupillary reaction. Of
course, some workers are of the opinion that pupillary
changes, perhaps even the Argyll-Robertson pupils,
may occur in syphilitic cases that are not neurosyphilitic,
or at all events are not victims of central neurosyphilis.
Finally, we must remember that there are cases of
neurosyphilis of a vascular type which yield negative
spinal fluids. The case leaves many questions unanswered.
247
Can paretic and non-paretic neurosyphilis be differentiated
by means of the gold sol reaction?
The gold sol reaction in this case was an extremely
mild one and would not at all have warranted the
diagnosis GENERAL PARESIS, yet the discovery
of a heavy meningeal exudate including an unusually
heavy deposit of plasma cells even in the
spinal pia mater will perhaps warrant us in making
a final retrospective diagnosis of paretic neurosyphilis.
Autopsy.
Case 68. We would like to give the full effect of our surprise
at the outcome of the case of Margaret O’Brien, a
school-teacher, 26 years of age. To be sure, Miss O’Brien
developed symptoms at 22 or 23 which we can now explain
consistently with the outcome of the case; for at that time,
she began to complain of severe pain in the head, especially
in the forehead and temples, and also became nervous, unable
to remain quiet, and given to insomnia. She was markedly
depressed at the time and would refuse to talk at times.
However, only the headache in this prodromal period could
be regarded as particularly suggestive of syphilis, and headache
in an over-worked school-teacher is not uncommon.
In fact, the picture presented by the patient was one of
catatonic dementia praecox. The patient was admitted to
the hospital after a sudden onset of excitement. At first she
was very restless, continually looking about and getting up
and walking away from the examiner, giving the impression of
understanding all questions but preserving an air of indifference.
A few days later, the patient was gotten to answer
more coöperatively. She remarked that the hospital was
heaven although in Boston; that it was summer time (correct)
and that her memory was greatly impaired. The physician
was a messenger of God (delusion later corrected). The
patient had not done God’s will; her breath was leaving her;
God’s voice was heard from time to time, and Miss O’Brien
248had heard it for a long time. God tells her to do His will.
However, as Miss O’Brien remarked, “I must think all this
nonsense, turning against God.”
The patient frequently attitudinized and would remain
in an apparently catatonic condition for many minutes.
For the most part, she was resistive and mute and non-coöperative
as to examination. From time to time, she
made impulsive suicidal attempts. So far as a somewhat
inadequate physical examination was concerned, nothing abnormal
could be made out; in particular, the pupils reacted
normally to light and were otherwise normal. The routine
W. R. of the blood serum, however, returned positive, and
in accordance with the policy of the Psychopathic Hospital,
the patient was subjected to a lumbar puncture. The lumbar
puncture yielded a positive W. R., 109 cells per cmm., a
positive globulin and a considerable excess of albumin, and
an exceedingly mild gold reaction—syphilitic type.
Ten days after admission, the patient had a convulsion.
She never regained consciousness, continued to have convulsions
for a few hours, and died, apparently from paralysis
of respiration. The heart continued to beat for a short
period after respiration ceased. The autopsy was consistent
with the diagnosis which had been rendered after the
surprising results of the W. R. in the blood and the laboratory
findings in the spinal fluid had been learned. There was a
generalized encephalitis with congestion of all the smaller
cerebral vessels and petechial areas in the meninges and
upon the cortical surfaces. We regard the case as one of
syphilitic encephalitis.
The brain weighed 1265 grams, indicating a loss of 79
grams by Tigges’ formula (8 times the body length in centimetres).
The pia mater was, in the gross, quite normal
within the cranium; nor were any cells found in a smear
from this pia mater; but the pia mater over the spinal cord
was visibly edematous, and a smear from the spinal pia
mater showed great numbers of lymphocytes and especially
of plasma cells—a finding which was confirmed in stained
section, by which a remarkable display of plasma cells was
found plastered somewhat generally over the entire pia
249mater of certain segments. The brain substance was softer
than normal, but displayed no differences of consistence.
The stripping of the pia mater of the temporal lobes on both
sides yielded the so-called “decortication” (that is, the adhesion
of small bits of brain substance to the pia mater). The
optic nerves were somewhat thinner than normal. No other
gross lesions of the brain were found.
The dura mater, although dense and injected, was not
otherwise abnormal. There was an early visible sclerosis
of the middle meningeal arteries, more marked on the left
side.
The cause of death, so far as the autopsy revealed it,
was bronchial pneumonia. There was a diffuse nephritis.
1. Are the hallucinations in the case of O’Brien characteristic?
Hallucinations are regarded as playing a minor
rôle in general paresis. In fact, earlier workers sometimes
denied that hallucinations occurred at all, and
this denial has been made once more of late by Plaut,[15]
but Kraepelin quotes Obersteiner as observing hallucinations
in 10%, and regards that figure as approximately
corresponding with his own experience. Junius
and Arndt are cited as finding 17% of their cases hallucinated.
Auditory hallucinations are somewhat more
frequent than those of vision (alcoholic psychosis must
be considered). The visual hallucinations of paresis are
thought by Kraepelin to be related with atrophy of the
optic nerves, and he states that they occur by preference
in patients having such atrophy. Hallucinations
though not common are more frequent in non-paretic
neurosyphilis than in paretic neurosyphilis.
2. What was the cause of death in Margaret O’Brien?
The autopsy, as above stated, indicated pneumonia.
In point of fact, this patient developed convulsions and
ceased respiration, the heart continuing to beat for
some time after respiration had ceased. It may be
that the death should be counted as one of neurosyphilitic
seizure.
250
Tonsillar abscess associated with neurosyphilis
(Lues Maligna?).
Case 69. Frank Mason, 49 years, a rectifier of spirits,
was admitted to the Psychopathic Hospital in a tremulous,
mentally confused, depressed, and unhappy state. He was
particularly concerned because he could not give an accurate
account of his past life and because he found that he was
continually contradicting himself.
Superficial examination shortly discovered the pupils to be
much contracted, irregular, and non-reactive either to light
or distance. Although these pupils showed more than the
Argyll-Robertson phenomenon, yet the suspicion of syphilis
was important.
Throat examination showed a large area of ulceration
involving the whole of the right tonsil and extending even
to the left side of the median line so that the whole of the
faucial pillar was involved. In the midst of this ulcerative
area was a mass of purulent necrotic tissue, about which the
edges of the ulcer stood out sharply. There was, however,
very little acute reaction about the margin of the area.
The association of pupillary changes (especially stiffness
to light), what looked like tonsillar gumma, and mental disorder
(including memory disturbance) heightened the impression
of syphilis.
However, the remainder of the examination was not especially
confirmatory of the diagnosis. The man was well
developed and obese, with a slightly enlarged heart, with
sounds of poor quality and the aortic second sound accentuated.
The systolic blood pressure was 130; the diastolic,
90. There was no disorder of reflexes except that the arm
reflexes were very lively.
After a time, a few facts concerning the patient’s life
became available. Although a rectifier of spirits, Mason
could not be found to have over-indulged in alcohol. It
appears that some five months before his admission to the
251hospital, a wisdom tooth had been extracted. About four
months before admission, the ulceration of the faucial pillar
had begun, and this ulceration was immediately laid to infection
from the wisdom tooth cavity. Mason then had to
discontinue work and a depression followed. But the account
of this depression led us to think that he was a victim more
of natural sadness than psychopathic depression. There
was much worry and insomnia. To meet the insomnia,
large amounts of hypnotics were administered. The sequence
of these hypnotics was a tremendous disturbance and continual
crying out by the patient. In fact, Mason became so
excited that he was removed to the Psychopathic Hospital
for temporary care in the condition above mentioned.
We naturally awaited the outcome of the serum W. R.
The return was negative. However, the typical position of
the ulcerative lesion and the non-reacting pupils,—to say
nothing of the mental symptoms and the associated tremors,
with incoördination (this incoördination was non-characteristic
and apparently due largely to the tremor),—led to lumbar
puncture.
The spinal fluid yielded a weakly positive W. R. There
was a slight positive albumin, the globulin test was slightly
positive, there were 14 cells per cmm., and the gold sol reaction
was of the syphilitic type. We were, then, probably
entitled to conclude that syphilis was active not only in the
body at large but also in the nervous system. Looking back
upon the case, we considered that large doses of morphine and
hyoscyamus might well have produced the marked mental
confusion and possibly the tremors that characterized Mason
on his arrival at the hospital.
Improvement followed after a few days of rest; the confusion
disappeared and the tremors diminished; the pupils
returned to their normal size and reaction; depression persisted,
and the patient was very properly much concerned
about the tonsillar lesion. However, further improvement
did not take place under antisyphilitic treatment and patient
died after several weeks from what was believed to be an
embolus from the tonsil.
2521. What was the true interpretation of Frank Mason’s
pupillary changes? They were probably due to the
opiates, despite the fact that, taken in association with
the gummatous lesion of the faucial pillar, we had regarded
them as possibly syphilitic.
2. How shall the negative serum W. R. be explained?
Such a reaction is consistent with the diagnosis gumma.
It is, however, a little surprising that with active neurosyphilis
and a relatively active non-nervous syphilitic
lesion like that in this case, the serum W. R. should
have been negative. Possibly a repetition of the test
at various times would have shown a positive serum
W. R. In any event, the fluid reaction was positive.
3. Could the tonsillar ulceration be due to dental infection?
The chances are against this on account of the interval
(2 months) between extraction of the wisdom tooth
and the ulceration, which itself seems to be of a tertiary
syphilitic nature. In point of fact, the patient
admitted a syphilitic infection 21 years previously
namely, at 28 years of age. At that time he took
large quantities of mercury and potassium iodid by
mouth.
4. Relation of the case of Frank Mason to the so-called
lues maligna? The case closely resembled the cases
reported by Bly. Frank Mason showed great destruction
of tissue, toxemia, failure to react to antisyphilitic
treatment. In both of Bly’s cases, the tonsil was the
starting point of the illness; and in both cases there was
a trauma of the tonsil or peri-tonsillar structures (tonsillectomy
and application of caustic). In our case
there not only had been extraction of a wisdom tooth,
but the tonsil had been cauterized.
253
Neurosyphilis versus multiple sclerosis.
Case 70. Annie Kelly is a young Irish woman, 21 years of
age, who was perfectly well until three months before her
admission to the Psychopathic Hospital, when suddenly
one evening she became very dizzy. This was followed by a
chill and vomiting. The next day she had a sore throat but
was able to be about and do her work. The dizziness,
however, continued and she began to feel rather queer.
Gradually it became difficult for her to walk on account of
staggering.
A little later she noticed a weakness of the left side, involving
face, arm, and leg; then she began to find it difficult
to talk. Finally the right leg became weak, making
walking practically impossible. All these symptoms grew
worse and the dizziness increased. At times her vision would
be blurred; there were somewhat frequent attacks of diplopia.
Finally she had to take to her bed, and at last she lost control
of her sphincters.
At no time did she suffer any pain. She was taken to a
hospital, and after a time improved somewhat; but she was
told she had a brain tumor and had better be in a large city,
where she could have surgical aid if this became necessary;
consequently, she was brought from Montana to Boston.
On admission to the hospital, the examination disclosed no
important symptoms outside of the nervous and locomotor
systems. She was unable to walk unless assisted. The
pupils were large but reacted well to both light and accommodation,
were equal in size, and regular. Slight nystagmus
was present; there was no ptosis or strabismus; vision in
the left eye was poor. The other cranial nerves showed
no involvement. The tendon reflexes were all present and
very lively; Babinski, Gordon, and Oppenheim signs were
present on either side. The ataxia was marked, especially
of the lower arms, and she had some difficulty in the alignment
of the fingers. The sense of position of the limbs was
254very poor. There was some tremor, which was not of the
intention type. The writing showed some incoördination.
The speech showed nothing abnormal. Mental examination
disclosed nothing of note objectively, but patient stated she
could not think so clearly as she could formerly.
The diagnosis would seem to lie between brain tumor,—which
had been suggested to the patient by her physician,—multiple
sclerosis, and neurosyphilis. The numerous neurological
symptoms without any definite evidence of intracranial
pressure were sufficient to rule out for the moment
the consideration of brain tumor. The syndrome of multiple
sclerosis is not complete, but the race, age, and onset, with
the increasing and decreasing intensity of symptoms are
very suggestive of this diagnosis. The symptoms, of course,
are all consistent with neurosyphilis also, and while the patient
denied any knowledge of syphilitic involvement, the
examination of the blood and spinal fluid was made. The
W. R. was negative in both the blood serum and spinal fluid.
Further examination of the spinal fluid showed presence of
globulin and an increase in the albumin content, 43 cells
per cmm. and a “paretic” type of gold sol reaction. With
the negative W. R. of both blood serum and spinal fluid,
and with so much in favor of Multiple Sclerosis, this
diagnosis was made.
1. What is the relation of multiple sclerosis to syphilis?
There is no definite relationship between multiple
sclerosis and syphilis,—that is, multiple sclerosis is
not a syphilitic disease; but the complete syndrome
of multiple sclerosis is often given by a syphilitic involvement
of the central nervous system (see case
Lauder, 71).
2. Is the spinal fluid finding in this case consistent with
multiple sclerosis? According to Nonne, about 19%
of the cases of multiple sclerosis show globulin and
pleocytosis in the spinal fluid. As a rule, the number of
cells ranges between 10 and 20 per cmm. and the globulin
is not present in large amounts. In this case, the
amount of globulin, which was given as 2+, is only a
moderate amount,—less than is usually found in
cases of general paresis. There are not very many
255cases of multiple sclerosis in the literature in which
a gold sol reaction has been performed, but in the
majority of those tested, the reaction is reported as
mild. However, cases of multiple sclerosis giving a
typical paretic curve have been described by a number
of observers, among whom may be mentioned Kaplan
and Solomon.
3. How frequently is it necessary to make a differential
diagnosis between multiple sclerosis and neurosyphilis?
Before the days of the W. R. this differentiation was
much more difficult than at present. But we, however,
still have to face a not very rare difficulty in separating
the two conditions. Syphilis is prone to cause small
localized lesions in the nervous system. The changes
in the patient’s condition, with improvements and
regressions are equally characteristic of both diseases.
How closely the symptomatology of neurosyphilis may
simulate that of typical multiple sclerosis is shown in
the next case (Lauder, 71). When the sclerotic area
of multiple sclerosis occurs in appropriate parts of
the cerebrum, symptoms of mental disturbances will
occur. In its histological picture multiple sclerosis is
at times highly suggestive of syphilis, even showing
mononucleosis and meningitis.
256
Optic atrophy; nystagmus; spasticity; intention
tremor. Diagnosis: ?
Case 71. James Lauder began to lose his eyesight at 32
years, and was shortly determined to be suffering from
primary optic atrophy. In the course of a year, he had
become completely blind. No mental symptoms had developed.
Physically, Lauder was in very good condition. Neurologically,
there was a complete optic atrophy with paralysis
of the internal rectus muscle, marked nystagmus, and absent
pupillary reactions. All the tendon reflexes were exceedingly
lively, though the right arm reflexes were more
lively than the left, and the left leg reflexes more lively than
the right. There was an ankle clonus on both sides. The
abdominal and cremasteric reflexes were lively. There was
a slight intention tremor. There was, however, no ataxia
and no speech defect.
Diagnosis: The nystagmus, optic atrophy, and the reflex
disorder suggested multiple sclerosis, although the
liveliness of the superficial reflexes, especially the abdominal
reflexes, was a point somewhat against any advanced degree
of multiple sclerosis. It would appear that the absence of
pupillary reaction to accommodation is also rather unusual
in multiple sclerosis.
The serum and spinal fluid W. R.’s proved positive. There
were 25 cells per cmm., albumin was in excess, and there was
a positive globulin reaction.
1. What is the significance of optic atrophy and other
optic changes with respect to neurosyphilis? Canavan,
from our laboratory, has reported that she found that
40 of 58 unselected cases of mental disease exhibited
obvious and undeniably important changes in the
optic nerve. She found that optic nerve changes were
even more frequent than chronic spinal cord changes
as detectable by the same method (Weigert myelin
257sheath method); there were only 34 of the 58 cases
which showed chronic spinal cord changes. Eighteen
cases very probably syphilitic (although the clinical
evidence was not in all cases supported by the W. R.)
failed to show optic nerve changes in but three instances.
The 15 syphilitic cases that did show optic
nerve changes showed them in but one eye in three cases,
in both eyes in 12 cases. Canavan incidentally demonstrated
a spirochetosis in the pial sheath of the optic
nerve in a case of neurosyphilis, possibly paretic.
2. What is the frequency of eye changes in neurosyphilis?
Posey and Spiller (“The Eye and the Nervous System,”
1906) quote Kéraval as finding 42 instances of fundus
change in 51 cases of paresis. Clifford Allbutt found
41 cases of atrophy in 53 of paresis; other authors have
found far fewer. Optic atrophy sufficiently marked to
cause blindness is relatively rare in paresis. Compare
table of eye changes from Joffroy under Case
Falvey (55).
As for optic atrophy in tabes, Posey and Spiller
record statistics as so various as to be on the whole
unsatisfactory. The highest percentages found appear
to be those of Mott, 80%, and Gross, 88%. It is evident
that the standards for measuring optic atrophy
must differ very much.
258
Atypical case of neurosyphilis. Picture of Huntington’s
chorea.
Case 72. Margaret Green, 28, was received at Danvers
State Hospital in an excited and frightened state. She was
very talkative and said that she was being bitten by snakes
and serpents. She thought every one approaching her was
the devil, and sprinkled what she called “holy water” about
her for protection. It was clear that she was hallucinated.
She heard her child crying, and she saw a woman carrying it
away.
After a few weeks, Mrs. Green grew quiet and more rational
except for a few spells of violence and noise; she gave the
impression of a rather pleasant and agreeable, though somewhat
demented, patient. Physically, beyond a tremor of
fingers and tongue and lively knee-jerks and some evidence
of enlargement of the heart, there was nothing to be found.
Margaret Green is still in the Danvers Hospital, being now
48 years of age. During the twenty years, she has presented,—besides
the mental picture of impairment of memory—occasional
spells of confusion, a variety of delusions based,
at least in part, upon auditory and vivid visual hallucinations,
a certain irritability and psychomotor excitement, and a
picture of Huntington’s chorea. The diagnosis of Huntington’s
chorea has always been in doubt by reason of the lack
of any evidences of hereditary taint; it has, however, not
been possible to secure a properly intensive account of her
relatives.
It appears that the choreic movements were first observed—in
the hospital at least—about 16 years ago. The
patient has always been decidedly mixed upon dates. From
internal evidence derived from her obviously in part erroneous
statements, it may be that the chorea began at the age of
23. It appears that she had been often termed a victim
of St. Vitus’ dance, and had had to leave her work in the mill
on account of the disease. From one source of information,
259it would appear that the patient began to have what was
called St. Vitus’ dance when she was 14 or 15 years of age;
so far as this informant knew, no other member of the family
had had the affliction.
The first movements observed in the hospital were irregular,
jerking movements, more marked in the left arm but also
occurring in the other extremities, as well as in the face,
wherein were produced peculiar grimaces. The twitching
movements would become decidedly worse during spells of
irritability. Observation in the patient’s early thirties left
the question in doubt whether the left pupil reacted to
light or not. In 1904, when the patient was 36, both pupils
failed to react to light either directly or consensually. At
this time, the jerky movements continued, especially in the
left hand and forearm, the tongue was tremulous, test
phrases were poorly pronounced, the knee-jerks were exaggerated
(especially the left), and both wrist-jerks were exaggerated.
The systematic examination, however, revealed
no other neurological disorder. Within a year, slight spurious
ankle clonus developed on both sides; the eyes, especially
the left, gave the appearance of developing cataracts.
A slight consensual light reaction was demonstrable
on the right side, but all light reactions were absent in the
left eye.
At the age of 42, the patient was still disoriented for time,
place, and persons and subject to a deep amnesia; was
tidy, tranquil, and of a pleasant demeanor, but many of her
muscles were in continual motion. There were chewing
movements and both hands and feet were rarely still. There
were no longer any spells of irritability or violence; and
once when found crying on the piazza, Mrs. Green, on being
asked the reason, replied that a gray cat had come and looked
at her so hard it made her cry. There were other crying
spells at times for equally good reasons, or for no reason.
More recently, the patient has become fairly well oriented
for time and place, and has acquired a fairly good insight
into her condition and a good memory for past events.
She has had occasionally auditory hallucinations, as of water
running. In 1914, it was reported that the pupils reacted
260to light, and the rest of the systematic neurological examination
was negative except that the knee-jerks were exaggerated;
and a re-examination in 1916 showed the pupils still reacted to
light. At present, the patient is disoriented for time, stating
that her age is about 25; she is no longer subject to auditory
hallucinations; she has a marked difficulty in enunciation,
emphasized by the lack of teeth and in part due to continual
movements of the tongue; the movements appear to be part
of a generalized chorea.
In a systematic review of the Wassermann findings in the
hospital population, the blood of Margaret Green was examined
and found to be positive. Lumbar puncture forthwith
performed showed a positive W. R. in the fluid; there
was a positive globulin and an excess of albumin; the gold
sol was characteristic of paresis; there were, however, but
three cells per cmm.
1. Are the choreiform movements related to the demonstrable
syphilis of the nervous system? Neither the
fluid W. R. nor the gold sol reaction should be regarded
as necessarily an indicator of tissue loss. The fluid
W. R. is commonly thought to signify merely that the
fluid contains substances which are somehow due to the
presence of spirochetes in some region pretty closely
related with the fluid. The gold sol reaction, although
well established to be characteristic of neurosyphilis,
is perhaps not so strong an evidence of the existence of
spirochetes in the region from which fluid constituents
are derived. There is no pleocytosis. However, the
positive globulin test and the excess of albumin do
indicate a certain amount of destructive process somewhere
in the neural tissues. Are we to suppose that
these substances have been continually found during
the course of this disease? This question cannot be
answered with the data in hand, and we can only suspect
that these positive tests for albumin and globulin
are an effect of tissue destruction caused by neurosyphilis.
It must be admitted that the argument
here is a little tenuous. The lesson is plain: that
in the present stage of our knowledge the W. R.
should not be omitted even in cases which present a
fairly convincing picture of some well-known entity.
Thus, a disease, which looks like Huntington’s chorea,
261as well as a disease suggestive of multiple sclerosis,
requires investigation by the methods of the syphilographer.
2. How shall we explain the changes in pupillary reaction
in this case? They cannot yet be explained. A few
observers have reported changes in pupillary reflexes
in the direction of normality. In our experience such
changes have not been noted. It cannot be too strongly
emphasized that it is very easy to make errors in
judging pupillary reaction if care is not used. For
instance, if the patient is accommodating for near
vision, light will probably not cause contraction. A
frequent cause of error in testing the light reflex arises
from using a weak electric light. An electric flash-light
is much less efficient than daylight. Probably
the most satisfactory method is to take the patient to
a window, ask him to look at a distant object, shade
the eye with the hand, remove hand, and observe.
3. What is the chief triad of symptoms in Huntington’s
chorea? (1) Choreiform movements associated with
(2) progressive mental enfeeblement, (3) occurring in
a patient whose family history shows a similar condition
in a preceding generation.
262
Differential diagnosis between NEUROSYPHILIS
and SENILE ARTERIOSCLEROTIC PSYCHOSIS.
Case 73. Marcus Chatterton was a retired sea captain,
75 years of age. At the age of 71, he had had a seizure with
a slight right hemiplegia and inability to talk. He had been
slightly confused for a short time but had rapidly recovered.
During the intervening four years, there had been three
similar attacks, and the last one had caused him to come to
the hospital. He was, in fact, confused upon admission
but had become perfectly clear by the next day. There was
a considerable memory defect, which the patient himself
did not entirely appreciate. Possibly his judgment had been
deteriorating slightly. He had been irritable of late and
sometimes sleepless.
Physical examination showed a rather well preserved
man with but slight senile changes. The pupils were equal
and reacted readily to light and accommodation. There
was no sensory disorder and no disturbance of coördination.
There were no tremors. The systolic blood pressure was 205,
the diastolic 135. The arteries were sclerotic upon palpation.
A sufficient diagnosis would have seemed to be arteriosclerosis,
and the hypothesis of syphilis would hardly have been raised
off-hand by most practitioners. The W. R. of the serum was
negative. What led to lumbar puncture in this case was the
fact that the sea captain’s wife had died 15 years before of
general paresis. The lumbar puncture was rewarding since
the W. R. was positive. There was an increase of albumin
and globulin, a “paretic” type of gold sol reaction, and 56
cells per cmm.
Accordingly, we must regard the condition as one of
neurosyphilis. Perhaps the arteriosclerosis was of syphilitic
origin. If this is a case of general paresis as we suppose,
it is one of very long-standing syphilis.
2631. Do delusions of grandeur in the senile period suggest
syphilis? Not necessarily; it appears that there is a
small group of senile cases which might be called cases
of senile pseudoparesis in which extravagant delusions
of grandeur are entertained, and in which frontal
atrophy is found although entirely without evidence of
chronic inflammation. It has not been proved that
these cases are of syphilitic origin. It is suggestive
that the site of the most extensive lesion is precisely
the site of the most extensive lesion classically found in
paretic neurosyphilis, viz., in the frontal regions.
2. Is neurosyphilis frequently found in both mates? It
can hardly be said that this is a usual finding. However,
it is far from rare, and it occurs frequently enough
to be used in support of the theory that there is a
special strain of spirochete that has a predilection for
nervous tissue. It must be remembered, however,
that the wives of syphilitics are frequently infected
without being aware of it. In such cases they receive
no treatment and consequently have a larger
chance of developing neurosyphilis. It is a good rule
to consider the mate of every syphilitic a candidate for
neurosyphilis.
264
An atypical case of recurrent dazed states resembling
HYSTERICAL FUGUES. Probably an instance
of NEUROSYPHILIS.
Case 74. Abel Bachmann, a man of 40 years, remains
doubtful and perhaps belongs to the still unresolved group
of mental cases due to syphilis that cannot be placed in any
of the well-known categories. Bachmann had been found by
the police, working in front of a cowbarn without the consent
or even the knowledge of the owner. Bachmann had, in
fact, spent the night in the cowbarn and was working with
the idea of paying for his night’s lodgings. The situation
struck the police as so peculiar, and Bachmann was so confused
and irresponsive, that he was brought to the Psychopathic
Hospital. The afternoon of his admission, however,
he entirely cleared up and was able to give a good account of
himself.
His story was that he had been worrying a good deal about
a divorce suit, and the morning of his episode he had awakened
with peculiar feelings. He walked from Boston to Cambridge,
feeling that he was in a strange city. He recognized the
places he passed, yet they all seemed to be changed. Upon
reaching Harvard Square, he determined to return to Boston
and walked and walked, failing to reach Boston. All day he
had eaten nothing; when night fell he stole into a field and dug
out radishes. A postman stopped and said, “Hello, Bill,”
which awakened him as by an electric shock. A barn presented
itself, in which he spent the night. In the morning,
the barn looked different. In fact, his entire surroundings
appeared mysterious. As he felt like working, he went to
work in front of the barn.
It seems that in his life there had been two other episodes
of a similar nature; in fact, Bachmann had been in a state
hospital for six weeks after the first episode. The first
episode had lasted a few days only, and followed worry when
he learned that the girl with whom he was in love was married.
265The second attack followed the death of his mother, whereupon
he was taken to a state hospital although the total
duration of symptoms was only three days. Bachmann
had had a chancre or some other form of genital disease at
26, and had at that time been treated with mercury.
Except for irregular and absolutely rigid pupils, reacting
neither to light nor to accommodation, Bachmann showed
no physical and especially no neurological disease whatever.
Moreover, the W. R. in the blood serum was negative.
As to diagnosis, one might consider hysteria, of which,
however, there are no visible stigmata. It would not appear
that brain tumor would be likely to have lasted so long as
eight or nine years, even if we should attempt to make the
hypothesis of tumor cover both the non-reacting pupils and
the episodes. Bachmann was non-alcoholic, and there was
no sign of any other form of intoxication. The spinal fluid
showed a negative gold sol reaction, there were no cells in the
fluid, there was no globulin; albumin was normal. However,
the W. R. was strongly positive.
The situation, then, in this case is that we have somewhat
peculiar psychopathic episodes, pupils rigid to light and
accommodation, a positive W. R. in the spinal fluid, and extremely
little else to permit a diagnosis. We are ignorant
as to the course and pathology of such cases. However, we
cannot resist the temptation of the diagnosis of neurosyphilis,
although further classification is not ventured.
1. What is the significance of stiff pupil as an isolated
symptom? Nonne finds that in the end, after years of
observation, the Argyll-Robertson pupil turns out to
be an advance courier of other more functionally
serious signs and symptoms of neurosyphilis. We can
confirm this experience and regard it as an established
clinical proposition that the Argyll-Robertson pupil
cannot be neglected. In this connection, refer to the
case of alcoholic pseudoparesis (Murphy, 60), and also
to the case of pineal tumor (Donald Falvey, 35). Enthusiastic
reports have occasionally been made upon
apparent restoration of the true syphilitic Argyll-Robertson
pupil to normal light reaction. The difficulties
in rendering the symptomatic diagnosis of
266Argyll-Robertson pupil in a given case are so great, and
the chances of complication so numerous, that we are
inclined to attach little significance at present to these
claims.
It may not be amiss to mention a somewhat humorous
incident familiar to some local neurologists. A case was
reported by the interne for a number of months as a
victim of a pupil stiff to light and accommodation, and
the entirely adequate cause of this phenomenon was
actually only discovered at autopsy by the triumphant
medical examiner, who demonstrated that the patient
in question was possessed of a glass eye.
267
TABETIC NEUROSYPHILIS (“tabes dorsalis”)
versus PERNICIOUS ANEMIA with spinal
symptoms.
Case 75. Mrs. Brown was a woman of 56, who for the
past eight or ten years had been complaining of trouble in
her legs. As she described it, at times her legs were so weak
she could hardly stand; at other times there was considerable
pain and numbness. She has always been considered
“high strung”; that is, she had a very bad temper and
lost control of herself almost entirely when she became
excited. Her legs had been growing progressively worse,
and for about a month prior to admission she had been unable
to stand or walk. She had also lost control of her
bladder. On account of her temper, it had been almost
impossible to nurse her; no nurse would stay with her because
of her scolding and fault-finding. Recently, she had
been having fits of the blues.
Her husband, who was seen before Mrs. Brown, was an
old gentleman, over 70, who was chiefly remarkable from the
fact that he had unequal, irregular pupils, which reacted
neither to light nor accommodation; there was also a speech
defect.
The patient herself proved to be extremely irritable, as
had been stated,—so much so that at times it seemed
almost impossible to do anything for her. She was very
querulous, constantly complaining, and not satisfied with
anything that was done. Aside from this, her mental examination
proved to be entirely negative; that is, there were
no psychotic symptoms.
The systematic physical examination gave the following
significant findings: blood pressure, 160 systolic, 90 diastolic;
no evidences, however, of peripheral arteriosclerosis. Patient
was unable to walk or stand, and had no control over her
bladder. The knee-jerks and ankle-jerks absent on both
sides; ataxia in the leg movements; loss of sense of localization,
268with no tenderness over the nerve trunks; no atrophy,
paralyses, or muscular asymmetry of the parts. The vibratory
sense was maintained. Subjectively, the patient thought
that the vibratory sense differed in the legs from that in the
arms. Localization, touch, pain, heat, and cold responded
to correctly. The arms showed nothing abnormal; there
was no incoördination, dysmetria, or dysdiadochokinesis.
Her pupils were equal, regular, and both reacted normally
to light and accommodation.
Diagnosis: The first consideration in the case is naturally
tabes dorsalis, especially when one considers that the husband
had signs which suggested syphilis of the nervous
system. The rapid onset of the acute symptoms in this
case, and the absence of the characteristic signs of pain were
at least atypical for this diagnosis, as was the absence of
any pupillary signs. Further, the W. R. was negative in
the blood and spinal fluid; there were no definite signs of
inflammatory reaction as shown by the other spinal fluid
tests. These findings made a diagnosis of tabes entirely improbable.
After tabes, the most frequent cause of the symptoms
above enumerated is perhaps to be found in pernicious
anemia. Examination of the blood showed that the patient
had 2,500,000 erythrocytes per cmm. The hemoglobin by
Tallquist scale was 80%. The smear was practically negative;
no blasts could be seen. Although this picture is not
a typical one for pernicious anemia, at least it is significant
in the low number of red cells to be found, and as no causes
for anemia were to be found, it seemed probable that we
were dealing with a primary anemia. The diagnosis in the
case, therefore, is spinal sclerosis of primary anemia. The
mental picture was not uncharacteristic of Pernicious
Anemia.
1. Could the diagnosis be rendered in this case without
a lumbar puncture? In the first place, the emaciation
is not entirely characteristic. The pupils react normally
to light. Probably such a case might well
have been regarded as one of tabes dorsalis in former
days, or even at the present time, if a lumbar puncture
had not been resorted to.
2692. Could this case possibly have been one of tabes dorsalis
with negative spinal findings? Such cases have been
reported frequently, but, unlike the present case, are
apt to be of long-standing and non-progressive, in
which the active inflammation is no longer present.
The negative findings would not be consistent with
tabes, in which the symptoms are of short duration
and of sudden onset.
3. If the serum W. R. had been positive would the diagnosis
have been neurosyphilis? We are loath to make
the diagnosis of spinal syphilis when the spinal fluid is
normal. Syphilis may produce a marked anemia,
however, and thus produce symptoms such as shown
by Mrs. Brown. It is even possible that such is the
explanation of this case, taking into consideration the
suggestive findings in the husband. However, there
is insufficient evidence to make such an hypothesis
rock firm, and we do not more than suggest it.
270
Atypical case of CONGENITAL NEUROSYPHILIS—peculiar
mental state.
Case 76. James Seabrook, 20 years of age, obviously
showed a number of signs of congenital syphilis. The
physical examination disclosed an old scar and indentation in
the right mastoid region, another on the right side of the
neck, another on the posterior surface of the right forearm,
and two on the outer surface of the right upper arm. The
lesions were about the size of half a dollar. There was a
saddle-shaped nose and a perforation of the palate and
uvula; there were palpable cervical and axillary glands, small
but numerous. There was a dulness in the region of the right
scapula, and slight dulness on both sides behind. There were
loud whispering and piping râles and bronchial breathing
throughout the chest, more marked on the left; there was
much coughing, and the sputum was at times blood-stained.
The pupils were irregular but reacted perfectly. The left
knee-jerk was slightly more active than the right. The W.
R. in blood and fluid was negative; the gold sol, globulin and
albumin tests were negative. There were, however, 56
cells per cmm. in the fluid.
We learned that the patient had had several spells of great
excitement, with pounding on the door and a desire to fight
bystanders. There were spells of headache and vertigo.
Mentally the tests showed him to be subnormal.
The diagnosis Of Congenital Syphilis seems established;
possibly the pulmonary condition is syphilitic. The mental
subnormality as well as the abnormal traits and episodes
are probably to be accounted for on the basis of syphilitic
involvement of the brain.
1. Are the headache and vertigo connected with syphilis?
This is perhaps suggested by the pleocytosis in the
spinal fluid.
2. How shall we explain the negative W. R.? This patient
had received, shortly before his entrance to the hospital,
271salvarsan and mercury. Possibly the drug treatment
has little or nothing to do with the negative W. R.’s
since they not infrequently grow weaker as congenital
syphilitics grow older.
3. What is the explanation of the spells of excitement?
Compare the spells of excitement in a form of neurosyphilis
described by Kraepelin, namely: syphilitic
paranoia, discussed in the case of Bridget Collins (59).
4. Is treatment indicated considering the W. R.’s to be
negative in blood and fluid? Despite the negative
W. R.’s in this case treatment is strongly indicated
on account of the pleocytosis. This would seem to
indicate that there is an active inflammatory process
in the cerebrospinal axis, and it is more than probable
that this process is syphilitic. How much real improvement
of the symptoms would result from antisyphilitic
treatment it is impossible to prophesy.
Every case is a special problem, and this case is very
unusual in showing a pleocytosis in the absence of
other indications of syphilitic nervous disease, viz.,
globulin, albumin and W. R.’s.
272
CONGENITAL NEUROSYPHILIS resembling
an undifferentiated case of FEEBLEMINDEDNESS—actually
PARETIC.
Case 77. John Friedreich, a 7–year old boy, was brought
to the Psychopathic Hospital by agents of a charitable society,
who found him a neglected child and quite evidently a subnormal
one.
The dominance of syphilis in the situation was clear. The
boy’s father had died but a few months before of syphilitic
heart disease, from which he is said to have suffered for five
years. The boy’s mother (the parents were first cousins)
had also been treated for syphilis and was excessively alcoholic.
The first child of this union—a girl—had died
at 6 years, of a disease diagnosticated spinal meningitis.
The history indicates that syphilis was acquired after the
birth of this first child; but in any event it is possible that
the meningitic condition of which the first child had died was
syphilitic. The second pregnancy terminated in a stillbirth;
the third issued in a girl, who died two weeks after
birth of what was termed “inward convulsions.” The
fourth pregnancy resulted in a miscarriage; the fifth in our
patient, John Friedreich. The sixth pregnancy resulted in
a girl, now 5 years of age, who is apparently normal. (Her
W. R. was negative and she shows no stigmata of syphilis.)
The patient, John Friedreich, at some very early age had
a rash on his body diagnosticated as syphilis. He also had
many seizures called fainting spells. Ever since birth he had
been taking mercury pills. He had not learned to talk
until his third year, and was able then to say only a few disconnected
words. In fact, John has never been able to talk
in complete sentences, mumbling much that is quite unintelligible.
However, he walked at 15 months in a normal
fashion and nothing peculiar in his gait was noted until he
was 5 years old, when he began walking on his toes, particularly
those of his left foot. Shortly thereafter, the seemingly inevitable trauma appeared; John fell out of a window
and severely injured his left leg, whereupon the peculiarity
of toe-walking became more pronounced and associated
with a limp.
Juvenile paresis. 7 years.
273The patient strikes one physically as having the development
of a child of about five years (actual age, 7). There
are a few lymph nodes palpable in the anterior triangles of the
neck. The dilated and slightly unequal pupils react neither
to light nor accommodation. There is practically complete
deafness; loud sounds are not at all noticed.
Withal, the child in a general way presents a somewhat
attractive appearance, being very playful and mischievous,
lying about on the floor and playing with whatever comes to
hand, talking to himself or making a few indistinct remarks
to the bystanders. He walks awkwardly, on the toes of the
left foot. He pays little or no attention to his toilet and
needs to be dressed and cared for in all ways. He is quick-tempered
and at times very difficult to manage.
There was, of course, little doubt of the diagnosis of Congenital
Syphilis and of Feeblemindedness. The W. R.
was positive both in the blood and in the spinal fluid. The
gold sol reaction of the fluid was of the “paretic” type;
there were 44 cells per cmm. and there was a large excess of
albumin and much globulin.
As to prognosis, there is doubt.
1. Is, or is not, this a case of juvenile paresis?
2. Is it, perhaps, a relatively permanent case of feeblemindedness
due to congenital syphilis? On the whole,
on account of the spinal fluid symptoms, we should be
inclined to give the case a relatively poor prognosis,
namely, of death in a few years. However, we may
perchance be later surprised to learn that the patient
has lived on, at least into early adult age.
Note: Mercury tablets in some cases of congenital
syphilis do not seem effective. John Friedreich was
treated most intensively by syphilographers from birth.
Dr. W. E. Fernald in a personal communication stated
that syphilitic cases of feeblemindedness are rather those
of the imbecile and idiot groups than of the higher levels.
This statement emphasizes again that the true hereditary
274cases of feeblemindedness are rather those of the higher
group, whereas the cases in which special causes have
operated in the uterus or in early life eventuate in idiocy
and imbecility. However, such a case as that of Friedreich
shows that now and then a case of feeblemindedness
without evidence of neurological disorder and looking
in almost all respects like an hereditary case may be
at times produced by syphilis.
3. How often is the central nervous system involved in
hereditary syphilis? An interesting table bearing on
this point is presented by Veeder.[16] The table concerns
the lesions in various parts and systems of the body in
100 cases of late syphilis. It appears that in 47, or
approximately one-half of Veeder’s series of 100 late
cases, the infection developed some form of lesion of
the nervous system. As Veeder remarks, this result
runs counter to the common statements of pediatricians,
notably of Holt.
| Bones: |
|
| Periostitis tibia |
4 |
| Periostitis skull |
1 |
| Osteomyelitis |
1 |
| |
|
| Joints: |
|
| Acute arthritis knee |
8 |
| Acute arthritis ankle |
1 |
| |
|
| Skin: |
|
| Macular eruption |
1 |
| Condyloma anus |
3 |
| Gummata |
3 |
| Alopecia |
3 |
| |
|
| Eye: |
|
| Interstitial keratitis |
24 |
| Choroiditis |
1 |
| |
|
| Ulcerations: |
|
| Nasal |
2 |
| Laryngeal |
1 |
| Pharyngeal |
1 |
| |
|
| Central Nervous System: |
|
| Mental deficiency |
23 |
| Cerebrospinal syphilis |
14 |
| Hemiplegia |
6 |
| Epilepsy |
5 |
| Spastic paraplegia |
4 |
| Chorea |
2 |
| Hydrocephalus |
2 |
| |
|
| Miscellaneous Conditions: |
|
| Ozena |
1 |
| Enlarged spleen (only symptom) |
1 |
| Torticollis |
1 |
| Aortitis |
1 |
| Obscure abdominal pain |
1 |
| Obscure pain in legs |
2 |
| Endarteritis obliterans |
1 |
| Paroxysmal hemoglobinuria |
1 |
| Raynaud’s disease |
1 |
| Hutchinson’s teeth |
4 |
275
Juvenile paretic neurosyphilis. Quadriplegia.
Case 78. Gridley Ringer, 15 years of age, had the facies of
a congenital syphilitic, including Hutchinsonian teeth, rhagades
of the face, and the so-called Olympic brow. No
secondary sexual characteristics had developed. There was
a marked speech defect. Mentally, Ringer was a low-grade
imbecile. He had been born at full term, and delivery had
been normal. There had never been other pregnancies.
He had never developed normally.
The father admitted syphilis 23 years before, namely,
8 years before the birth of his son, but the father had been
treated for several years and had been declared cured.
1. What would be expected in the spinal fluid of this case?
Without the history, it would perhaps be impossible to
say whether the case was one of a quiescent imbecility
or one of juvenile paresis. The spinal fluid of the juvenile
paretic gives a picture identical with that in the
adult. The spinal fluid in this case showed a positive
W. R. (as did also the serum), a marked increase of
albumin and globulin, 115 cells per cmm., and a “paretic”
gold sol reaction. Accordingly, the diagnosis of
General Paresis was made.
2. What is the prognosis? The prognosis of juvenile paresis
is currently regarded as entirely grave. There is
probably less hope for improvement in juvenile paresis
than in the acquired paresis of adult life, since it seems
to be a general principle that congenital syphilis is
always more difficult to cure than acquired syphilis.
This case had seizures a few months after initial
observation, and the seizures were followed by a transient
right hemiplegia. This right hemiplegia was
shortly followed by a left hemiplegia, which remained
permanently. Moreover, a few weeks later, a right
hemiplegia again developed, leaving the patient with
complete paralysis and aphasia. Death followed in
six weeks.
3. What effects were shown in the parents? Following up
the parents was rewarded by the discovery that the
276mother was suffering from nerve deafness, probably
of syphilitic origin, and that the father had recently
begun to suffer from what he considered rheumatism,
but which on examination was shown to be tabetic
neurosyphilis (“tabes dorsalis”). This family again
supports the hypothesis that there is a strain of spirochetes
especially prone to attack the nervous system.
Here it would seem that the syphilis acquired by the
father had infected the mother and been transmitted
to the son. In all three infected by the same strain
or strains of organisms the nervous system was involved.
It is difficult, nevertheless, to explain on this
hypothesis why in one case the disease took the form
of tabes dorsalis, in the second, eighth nerve involvement
and in the third, paresis. This question of strains
is really more than academic because it enters deeply
into the question of treatment, as well as that of the
suggested increased viability of the neural strain.
277
Is there a relation between epilepsy and juvenile
neurosyphilis?
Case 79. John Doran fell off the rear of an ice-wagon, at
six years of age, and shortly afterward developed fits. It
appears that John was not unconscious at the time of his fall,
but that he complained of headache. Although the convulsions
were fairly frequent at first, it appears that they later
became rare and occurred only when the patient got into a
temper. At the stage of exhaustion after violent excitement,
John would fall.
Physically, at 9 years a fair development and nutrition
were evident. There was a great exaggeration of the frontal
bosses; the nose could not be said to be typically saddlebacked,
yet there was a suggestion of a sinking of the
bridge. The teeth slightly suggested the Hutchinsonian
type, but only slightly. There was a slight roughening of the
tibia, and there was a slight scar over either knee. The
patient graded according to the Binet scale at 9 years, and
he was regarded as definitely feebleminded.
The family physician states that, according to his information,
the father contracted syphilis when the child was between
three and four months of age, and that the mother also was
infected at this time. However, the child had not been
suckled except immediately after birth, and there had been
no evidences, according to the family physician, that John
had acquired syphilis.
Ordinarily, one might content himself regarding the case
of John Doran as one of idiopathic epilepsy with mental
defect or deterioration. However, the frontal bosses, suggestive
teeth, the flattened bridge of the nose, the roughened
tibiae, and the old scars, though singly not of great significance,
collectively make one suspicious. Despite the family physician’s
belief that John could not have acquired syphilis from
the parents, the infection seems entirely possible despite the
fact that no symptoms developed early thereafter.
278The W. R. in this case proved positive in both blood
serum and spinal fluid.
1. What is the relation of trauma to this case of Juvenile
Neurosyphilis? Probably none.
2. What would be the effect of treatment? For a number of
years John Doran was lost sight of. He was, however,
treated, according to our information, with intraspinous
injections of salvarsanized serum, whereupon
his convulsions shortly ceased. He has been recently
examined mentally once more, and still grades as feebleminded.
He still has violent outbreaks of temper.
3. Is such a case as Doran typical? Shanahan has investigated
conditions at Craig Colony. There were 22
out of 886 epileptics (at Craig Colony) or 2½%, who
showed a positive W. R. Nine of these cases were
regarded by Shanahan as cases of epilepsy actually
caused by syphilis. Viet had found 7%, and Bratz and
Lüth 5% of constitutional epileptics to be syphilitic,
but the data of these German authors were obtained
before the era of Wassermann tests.
279
Adrenal tuberculosis complicating juvenile paretic
neurosyphilis (“juvenile paresis”). Autopsy.
Case 80. When James Arnold appeared at the Danvers
Hospital in his 22d year, he looked as if he were but 12 or 14
years of age. He was excessively fat but of fair muscular
development. The left eye diverged outward, and the left
pupil was smaller than the right. An odd feature was a high
degree of pigmentation of the skin of the genitalia and the
groins (the axilla, the mammillary areas, and the oral mucosæ
were free from pigmentation). Physically speaking, the
patient was practically normal. Neurologically, however,
there was much of interest, in the light of which the clinical
history was of value.
It seems that after an apparently normal early childhood,
the boy had begun, at the age of 11, to experience difficulty
in carrying out every-day school tasks; and after this his
mental capacity had slowly but progressively deteriorated.
The deterioration was not merely intellectual, but the boy
became dishonest and untrustworthy and developed a number
of untidy and uncleanly habits, behaving at the age of 16, as
the parents stated, like a child of six.
In his seventeenth year, the boy had been taken with a severe
attack of what was regarded as an “attack of indigestion.”
This attack ushered in a gradually developing muscular
weakness, especially involving the limbs. By the age of 21
he had become irritable and the paresis was so extreme that
the patient was unable to get in or out of a carriage.
This generalized muscular weakness was plain upon admission
to the hospital though there seemed to be no actual
paralysis. The patient was unable to walk in a straight line
and Romberg’s position could not be maintained. Marked
tremor was present in the hands and lips. There was bilateral
impairment of vision and nystagmus. Reflexes and
sensations normal. Speech was markedly affected, all syllables
being very much slurred. School knowledge and memory
280for both recent and remote events very poor. The patient’s
habits were very untidy. He was very emotional, easily
made to laugh or cry; and in behavior, extremely childish.
Two months after his admission to the hospital, the weakness
suddenly became extreme. He was constantly nauseated,
refusing food. The face and hands were cyanosed and
the heart’s action rapid, weak, and irregular. This attack
lasted for a week and was followed by a period of improvement,
during which, however, he still remained very weak and
apathetic.
One month later he again became so feeble that he was
unable to raise himself in bed. He complained persistently of
feeling very “sick.” His temperature was elevated and there
occurred the same train of circulatory symptoms observed
previously, viz., rapid and tumultuous action of the heart,
with cyanosis of face and extremities. He soon became
unconscious, remaining so until his death, which occurred
on the seventh day of the acute attack.
This case was under observation before the days of the
W. R., yet clinically the case had been diagnosticated Juvenile
Paresis. There was no history of the acquisition of
syphilis or any likelihood of its acquisition. Considered clinically,
many of the classical features described by Addison
were present, viz., marked asthenia and apathy; severe and
frequent gastro-intestinal symptoms (the disease probably
commencing with the attack of so-called “acute indigestion”
six years prior to patient’s death); attacks of extreme cardiac
weakness with the characteristic small, low-pressure pulse.
On the other hand, pigmentation of the skin (usually the
most striking clinical feature) was limited to the external
genitalia, these being colored a deep brown.
The most striking feature found at autopsy was a bilateral
adrenal tuberculosis (caseation, giant cells, lymphocytosis, tubercle
bacilli). The thymus gland was persistent (7×5×.5
cm.), whereas the thyroid gland was smaller than usual.
The brain showed macroscopic and microscopic features
entirely consistent with the diagnosis of general paresis,
including lymphocytosis, plasmocytosis, irregular degrees of
281nerve cell destruction, and gliosis, with an especially characteristic
microscopic picture in the frontal regions.
It may be of note to consider the degree of change undergone
by a brain in 11 years or more of deterioration, and the
following description of the head findings is therefore
included:
Head: Hair abundant, dark. Scalp normal. Calvarium,
weight 435 gm., transparent in bregmatic region
only, elsewhere thick and dense. The average thickness
of the vertical plate of the frontal bone is 7 mm.
The frontal bone shows a moderate thickening and
hardening of the inner table with obliteration of diploë.
Dura mater moderately adherent to the bregmatic
region of calvarium. Arachnoidal villi moderately
developed. Sinuses not remarkable. Pia mater shows
a moderate focal thickening with opacity, especially
along sulci. Vessels well injected. Brain: Weight,
1200 gm. The brain shows marked focal variations
in sulcation and consistence. Spread on a board, the
right hemisphere is obviously somewhat bigger than
the left. There is a difference of only 0.5 to 0.75 cm.
on measurement of the greatest circumference of the
cerebrum, taken from the median line superiorly to the
median line inferiorly, but the right hemisphere is
throughout slightly more convex than the left. Both
postcentral gyri are much narrowed in their superior
portions, and the sulci posterior thereto are deeper
than the other sulci of the hemispheres. The sulci
of the orbital surfaces are asymmetrical and, on the
left side, show a tendency to microgyria. The cerebral
hemispheres as a whole show a remarkable tendency to
slight protrusion of the border gyri; especially those of
the two poles, of the free edges along the great fissure,
and most strikingly the gyri at the boundary line between
the inferior and lateral surfaces. This marginal prominence
is slight but obvious and is emphasized by a
slightly paler color in some regions. The cerebrum
shows a general induration which is greatest in the frontal
tips and along the inferior borders of the lateral surfaces
of the hemispheres, especially right. The orbital surfaces
are firm, especially anteriorly and externally (prefrontal);
the tips of the temporal lobes are firm, and
the superior temporal gyri are firmer than adjacent
gyri. The postcentral gyri are indurated more than
282the other gyri of the superior surface. The hippocampal
gyri are likewise firmer than adjacent gyri.
Cerebellum and pons: Weight, 145 gm. The inequality
of the two hemispheres is more marked than in
the case of the cerebrum.
Greatest lateral diameter; left, 4.5 cm., right, 5.5 cm.
Anteroposterior diameter adjacent to notch: Left,
5.8 cm., right, 5.5 cm.
There is no appreciable difference in depth. The
diminution in volume appears to be chiefly at the expense
of the right clivus. The inferior surface is firmer than
the superior. The laminæ adjacent to the horizontal
fissure are firmer than the remainder of the cerebellum.
The pons is small.
There was also a lateral curvature of the spinal column,
as well as characteristic adhesions between spinal dura and
pia mater which are always suggestive of syphilis. For the
rest, there were few findings of note: some adhesions of the
left pleura, hypostatic congestion of the lungs, tracheitis, and
chronic gastritis. There were four lobes of the right lung
but it is doubtful whether this should be regarded as a stigma.
1. Can we separate the symptoms of Addison’s disease from
those of paresis in this case? The extreme cardiac
weakness with a characteristic, small low-pressure
pulse is in point. The asthenia and apathy are consistent
enough with Addison’s disease as well as with paresis
itself. It would also be possible to ascribe the gastro-intestinal
symptoms to either disease.
2. Of what significance is the persistent thymus? Persistent
thymus has been observed in a few cases of Addison’s
disease, but that it plays any part in the symptomatology
thereof is a matter of doubt.
3. How can the obesity be explained? It is of course of
note that the thyroid gland was small, but microscopically
there were no peculiar features in this gland.
4. Was the adrenal tuberculosis actually primary? Minute
search failed to reveal evidences of tuberculosis elsewhere
unless we regard the few adhesions binding the
lower half of the lung to the chest wall as indicative
of an old tuberculosis. In particular, the mesenteric
lymph nodes were normal.
283
Neurosyphilis? Secondary stage of syphilis.
Case 81. Florence Fitzgerald, a woman 25 years of age,
applied at the police station to be taken care of. She said
she had been a prostitute for the last few months, was now ill,
and wanted to reform. She appeared physically ill and was
sent to the Psychopathic Hospital, where she remained at
first almost mute, making answers chiefly by nodding the
head. She gave the impression of daze or stupor, and in
fact her condition was at first regarded as catatonic. This
reaction, after a few days, changed and Florence became
quite normal, giving a full account of her condition.
It seems that four months before going to the police station,
she developed a chancre, which was locally treated. A
careful physical examination showed a fine red macular
eruption which was without much question a syphilitic
roseola. The spinal fluid yielded a positive W. R. although
other tests of the fluid were negative. Curiously enough, no
physical sign of involvement of the nervous system could be
discovered. We were inclined to regard the mental symptoms
as partly due to the syphilitic intoxication, and partly due to
a psychic reaction of the nature of defense. As for the positive
W. R. in the spinal fluid, in early secondaries various
observers differ as to the frequency both of the W. R. and
of other changes, percentages being given that range from
25 to 90%. See case Caperson (45). It is of note that
clinically there were symptoms referable to a syphilitic involvement
of the nervous system; namely, marked headache
and malaise. The headaches of the secondary period are frequently
the result of meningeal involvement.
284
TABOPARETIC NEUROSYPHILIS (“taboparesis”);
death from TYPHOID MENINGITIS.
Autopsy.
Case 82. Frederick Estabrook was a salesman, who, be it
noted, had never had typhoid fever or any disease remotely
resembling typhoid fever. He had acquired syphilis at 19;
had married at 22; was the father of two healthy children
(no miscarriages); had had a certain disturbance of bladder
and rectum, but remained a successful salesman to the age of
28, when advancing tabes confined him to bed for a time.
At 30, mental signs of Paretic Neurosyphilis developed,
and death followed at 32, after an acute illness of a week.
The details of the history after the first symptoms at 28
are as follows:
At twenty-eight patient lost control of limbs and was confined
to the house about two months, under medical care.
Three months later he had regained partial control of his
limbs but had lost all control of his sphincters. After another
month he had returned to work, but did not work steadily
and seemed to have lost ambition. In the summer of 1905,
his mind became obviously altered. He grew indolent and
extravagant and given to buying expensive and useless articles.
Loss of interest in things followed, together with loss
of memory for recent events, lack of insight into illness, delusions
of persecution by wife, irascibility followed quickly by
crying. Before admission to hospital, he was euphoric, drawling
and tremulous in speech, sprawling in penmanship, alternately
depressed and exalted in manner. Knee-jerks were
absent, gait ataxic, pupils stiff to light.
The family history was negative with respect to insanity.
All the family were reported as nervous. A brother died of
peritonitis at twenty-eight, a sister of pneumonia under twenty.
Another brother and sister are living. Father and mother died
of heart trouble at about sixty-seven and sixty respectively.
The patient was at high school one year and was a fair
285student. Considerable tobacco was used, and some alcohol.
Intoxication denied. There was no history of typhoid fever
or other acute disease.
The patient on admission was sallow, poorly nourished, and
flat-chested, with a slight lateral curvature. There was
slight dulness over right apex in front and in right upper
back. Voice sounds were increased over right apex in front
and over whole right back. The right chest showed bronchial
respiration throughout. The respiration in front of right chest
was of an interrupted character. The liver seemed moderately
enlarged. The urine showed a very faint trace of
albumin. There were a few small nodes in right groin and a
scar on dorsum of penis.
Neurological Examination. Slight swaying in Romberg
position. Slight tremor of protruded tongue and extended
fingers. Pupils irregular, left slightly larger than right. Left
pupil reacted to light consensually, but not directly. Right
pupil reacted very slightly to direct light, not consensually.
Knee-jerks and Achilles jerks absent. Ankle clonus absent,
abdominal and cremasteric reflexes brisk. Sharp and dull
points were recognized in the legs with numerous mistakes.
Vocal and facial tremor. Speech slow and drawling. Test
phrases repeated well if care was taken. Consciousness clear.
Orientation perfect. Calculating ability preserved. Many
words omitted in writing. Penmanship clear but shaky.
Hallucinations absent. Memory of recent events poor.
Associations of a logical or defining type. Patient denied
various statements in commitment papers and had little or no
insight into the mental side of his disease—slight euphoria.
After a month’s observation the patient was removed to a
quiet ward and set to work a few days in the scullery. One
night he began to yell as if assaulted and said later that he
had an idea that he was going to die. Before three months
had passed he had become untidy, disorderly, and imperfectly
oriented.
The general degeneration continued rapidly. One week
before death the temperature rose to 103 degrees F., and the
patient succumbed to what seemed clinically like a bronchopneumonia.
Unconsciousness two days before death.
286Note with respect to history of typhoid.—Inquiries of
his physicians, wife, employer, and brother tend to show
conclusively that the patient never had a disease even remotely
resembling typhoid fever.
The autopsy findings were as follows:
Acute conditions:
Hypostatic pneumonia, with early serofibrinous pleuritis
and without lymph node swelling; enlargement of mesenteric
lymph nodes; acute cerebrospinal leptomeningitis; multiple
small hemorrhages of spleen.
Other findings:
Scar of penis; sclerosis of aortic arch (Heller’s type?) and
slight coronary arteriosclerosis; calvarium thin and dense;
dura mater thickened and adherent to calvarium; calcified
arachnoidal villi; chronic cerebral and cerebellar leptomeningitis;
atrophy of frontal lobes; granular ependymitis; sclerosis
of posterior columns of spinal cord; emaciation; unequal
pupils; slight parietal fibrous endocarditis, slight mitral sclerosis;
gastro-intestinal atrophy; chronic cystitis; chronic abscess
of prostate.
The description of the head findings is as follows:
Skin exceedingly loose, and the whole skull cap
thinned. The diploë are absent. Adhesion with dura
easily separated. The dura somewhat thickened, but
not distended. Along the longitudinal sinus extensive
calcareous granulations adhere to it. The longitudinal
sinus does not contain blood, and the inner surface
is normal in color. The pia is extensively thickened
and opaque and a general subpial exudate exists which
is more marked over the vertex where it lifts the pia
from the brain surface to the extent of three centimeters
in Rolandic, superior frontal, intraparietal,
and mesial precentral sulci on each side. The arteries
at base are free from atheroma. The temporal lobes
are much bound down by adhesions, as is the cerebellum.
Post mortem softening is evident. The hemispheres
show no asymmetry, but the frontal convolutions are
markedly atrophic. The corpus callosum is united to
the cortex by old adhesions and has to be dissected
away from it. Lateral ventricles contain some slight
amount of cloudy fluid, and the pia along the vessels
287is opaque. Some granulations in ependyma. Brain
weight, 1305 grams. Pons and cerebellum, 195 grams.
Cord.—Dura much thickened, and the pia corresponds
to its appearance in brain with a like exudate.
Cross sections of cord show sclerosis of posterior
columns.
Bacteriologically the typhoid bacillus was cultivated
from the meninges and from the swollen mesenteric lymph
nodes. The blood was negative; the intestines were
negative so far as lesions were concerned.
The microscopic examination confirmed the clinical diagnosis
of General Paresis and of Tabes, since there was
not only an extensive chronic encephalitis, with the usual
lymphocytic and plasma cell deposit and irregular gliosis,
but also a well marked posterior column sclerosis, not unusual
save in its extreme degree.
It might be surmised that some difficulty would arise in
distinguishing the effects of paretic meningoencephalitis from
those of the more recent typhoidal process. The well-known
tendency of typhoidal processes to escape polynuclear exudation,
at least until frank necrosis has set in, gave rise to
the idea that the two mononuclear pictures—that of general
paresis and that of typhoidal processes—might be confusing.
The picture presented by the meninges was scarcely what
might be expected. Although numerous mononuclear phagocytic
cells are everywhere found, yet the predominant
picture is that of a polynuclear exudation.
The polynuclear leucocytes occur in greatest numbers in
the tissue spaces, especially in the meshes of the lumbar arachnoid
and in the spaces of the frontal and paracentral pia
mater. In the lumbar region of the spinal arachnoid wide
fields occur in which the cells are almost one hundred per
cent polynuclear leucocytes. In places phagocytic cells occur,
and in a few fields, even in the open tissue spaces, the
number of phagocytic cells may arise to fifty per cent.
Edema is a considerable feature in the meninges. Fibrin is
found chiefly in the cerebral meninges and appears in numerous
delicate strands in the tissue spaces.
288
Moloch, horrid king, besmeared with blood
Of human sacrifice, and parents’ tears;
Though, for the noise of drums and timbrels loud,
Their children’s cries unheard that passed through fire
To his grim idol.
Paradise Lost, Book I, lines 392–396
289
Neurosyphilis in a public character: eloquence,
reformatory efforts, notoriety.
Case 83. Major Isaac Thompson, M.D., was a character.
He had been regarded as eccentric for many years prior to
his death at 63. In fact, it seems that there had been more
or less definite symptoms and signs about his fortieth year.
The doctor himself had a ready explanation for his Argyll-Robertson
pupils; he explained that he had had a peculiarly
heavy smallpox at about the age of 27 (which would be
about 1872).
The doctor had a good secondary education, he had gone
through the Civil War as a hospital steward, went into business
after the war, married, and then went to the medical
school, graduating at the age of 34. He continued in practice
for a dozen years, and then gave it up. For years he
had been especially interested in certain literary lines and
he had published any number of pamphlets, all of a somewhat
striking description, often with a political color and
intended to stir up reform measures. The doctor never bore
a very good reputation, and years later it was recalled that
certain books disappeared from libraries and their loss was
almost certainly traced to Dr. Thompson. In general, however,
he was considered to be a rather worthy local figure.
It is possible that a fall on the ice in his 61st year actually
started the fatal process, since after that time the patient
had difficulty in walking, and a few months later developed
periods of excitement with peremptory insistence on obedience
to his wishes. Whereas formerly the doctor had
finished up one literary piece of work after another, he now
began to do very scattering work. He appeared in public
290to denounce certain financial schemes with great force and
unusual eloquence. His eloquence was greatly complimented,
and these compliments induced the doctor to a
remarkable crusade against a certain corporation; there was
so much truth mixed with the fiction of his eloquence that
he obtained a considerable following in his campaign. He
wanted to start a bureau of information for the instruction
of the public on these matters, and he planned to put up a
building adjoining his own home for the accommodation of
the various clerks and writers in this bureau. However,
before the building had been actually started, an outbreak
occurred.
One morning the doctor was very excitable and noisy over
the telephone, ordering typewriters and giving directions to
mechanics. He repaired to Boston in connection with certain
resources that he supposed (and gave others reason to
believe) had been supplied by the Government and by a
large newspaper. One evening he returned very late. It
appeared that he had had a fracas at a hotel and had knocked
down one or two colored porters, acting as though drunk.
Upon being put to bed, the doctor talked incessantly of
religious matters, proposing to undertake a Sunday School
class. His interlocutor did not exhibit a particular interest
in this scheme, whereupon Dr. Thompson threatened him
with violence. Police and doctors were called in and a constant
stream of conversation lasted for hours. The patient
was finally brought to Danvers Hospital upon representation
by physicians, to whom he told that his luck had
turned, that he was about to be made senator from the
district, and that he and Roosevelt were going to break up
the trusts, and that, as a matter of fact, he was a relative
of Mr. Roosevelt.
Upon admission, the patient was a well preserved and
well groomed man with gray hair and beard. He was somewhat
pallid but his teeth were well preserved and well cared
for, and there was little or no physical change except a slight
hypertension. He claimed that he had suffered from kidney
disease for some years, and there was in fact a trace of
albumin in the urine.
291Neurologically, the plantar and Achilles reactions could
not be obtained, but there were no other reflex disorders
except the bilateral Argyll-Robertson pupil. The doctor’s
explanation for these stiff pupils, which he described as
existing for many years, was frank and circumstantial, so
that the unlikelihood of Argyll-Robertson pupils due to smallpox
was rather frowned upon by him. Without entering upon
a detailed description of the clinical symptoms and course
of the disease which led to death a little over a year after
admission, it may be said that the differential diagnosis lay
between the expansive form of general paresis and a maniacal
condition, presumably the maniacal phase of manic-depressive
psychosis. From the data of a special staff meeting
held upon the case, we learn that the diagnosis of manic-depressive
psychosis was entertained more strongly than that
of general paresis. Thus, for general paresis alone was the
somewhat gradual onset with increasing excitement, accompanied
by expansive delusions concerning unlimited finance,
personal over-importance, and Argyll-Robertson pupils.
Dismissing the Argyll-Robertson pupils from consideration,
the diagnosticians were led to see in the constant motor
activity displayed in conveying an enormous number of
thoughts on paper, inconsistent talking with digressions, a
manic-depressive psychosis. There was no amnesia and no
other sign of mental deterioration. There was a certain
improvement early in the hospital stay of the patient.
Consciousness was clear and orientation perfect. The delusions
themselves, though extravagant, were not inconsistent
or fantastic. The hallucinatory disorder was hardly
characteristic either of manic-depressive psychosis or of
paresis.
The patient might be described as “interesting.” A
good preliminary training with years of travel and variety
of occupation, furnished him with a fund of knowledge.
An excellent memory, prompt replies and repartee, endless
digressions with voluntary return to the original topic,
caused him to be an amusing and even instructive interlocutor.
However, his commitment and confinement in the
institution seemed always entirely wrong, and he expressed
292mixed feelings about the family, now being bitter against
them, and again condoning their mistakes. The patient’s
conduct was good and he was tidy in habits, and tried as
far as possible to conform to the requirements of the hospital.
The doctor showed a marked antipathy toward a
certain male attendant, who had removed articles from his
clothing upon admission and had reclaimed a book on rules
and regulations. The doctor prepared a list of 327 different
acts of abuse, lack of care, and insubordination which
he said he had observed in the hospital.
In the last weeks of the patient’s illness, his ideas became
more expansive and extravagant, dealing with a grapevine
system of wireless communication and delusions of unlimited
wealth. He would at times keep his room flooded
with urine and water for the purpose of keeping down the
plague which he said was infecting the hospital. Later he
mixed food with urine and other ingredients, claiming that
he was constructing an elixir of life.
The autopsy showed few changes of the calvarium or of
the dura mater, nor was the pia mater more than slightly
thickened and milky over the frontal poles, along the longitudinal
fissure and over the sulci. There were fairly firm
adhesions of the pia mater to the dura mater along the
longitudinal fissure and over the frontal poles and at the
temporal tips. The hemispheres were firmly interadherent,
and the cerebello-pontine tissues were covered with a firm
leptomeningitis. The floors of the ventricles were smooth
and the basal vessels showed little beyond a few spots of
sclerosis. There was a generalized increase of consistence.
The frontal gyri were rather prominent with wide sulci, but
upon section no very marked atrophy of the gray matter
could be shown. The rest of the brain failed to show any
flaring of sulci or any special evidence of cortical atrophy.
The brain weighed 1250 grams; a possible diminution of 100
grams, considering the patient’s body length. However, it
must be remembered that he was at this time 63 years
of age.
Microscopically, the diagnosis of General Paresis was
confirmed on the basis of plasmocytosis, lymphocytosis, gliotic
293changes and nerve cell destruction. There was an unusual
variation in the degree of the destructive process, which
picked out, for example, certain regions of the right side
for maximal lesion (cornu ammonis, gyrus rectus, and superior
frontal gyrus).
If the patient’s own estimate of 35 years’ duration for
his Argyll-Robertson pupils can be trusted (and in general
his memory was extremely good), we may well conceive an
unusual duration for the process in his case. There was,
however, in the body at large no very marked degree of
changes. There was a slight old tuberculosis. There was
a slight interstitial nephritis, with cardiac hypertrophy and
fibrous myocarditis. There was also a sclerosis of the mitral
and aortic valves; there were chronic changes in the spleen,
liver, and bladder; there was generalized arteriosclerosis of
mild degree; there were two round gastric ulcers near the
pylorus. The liver weighed but 800 grams, and its left
lobe was somewhat rough.
This case is placed among the medicolegal and social
cases because the phenomena that ushered in his last illness
were mistaken by the local public for meritorious social
reform measures. They were regarded as not markedly
different from the variety of steps taken by the very active
doctor in previous years; indeed the public eloquence that
he displayed a year before his death was quite in line with
previous habits, despite the suspicious over-brilliance of
language. It is an important question, how far the eccentricity
and literary overactivity of the latter half of the
doctor’s total life can be explained on the basis of a mild
syphilitic irritation of the nervous system. In this connection
we are tempted to recall the suggestions of Mœbius
concerning a portion of the literary products of Nietzsche.
Our doctor was by no means so brilliant an exemplar of
syphilitic literature as was Nietzsche, if we grant the hypothesis
of Mœbius to cover our doctor’s case as well as
that of Nietzsche. In the future, important studies of
character change under the influence of syphilis will doubtless
be made. With modern diagnostic methods, of course,
the diagnosis would have been rendered almost at once in
294the case of Major Isaac Thompson, M.D., and much of his
past life would have been brought under special review in
connection with the syphilis which doubtless the blood
serum or at any rate the cerebrospinal fluid would have
shown.
This case illustrates but one of the many social complications
arising as the result of paresis. When one recalls
that the onset is often insidious and not correctly understood
for a period of time, it is readily seen that many unfortunate
acts may be committed by a patient. As hypersexual
desire is not an infrequent early symptom and as judgment is
early disturbed, loose morals may ruin the patient’s reputation.
The poor judgment and expansive delusions often lead to
foolish business deals wherein the patient’s family is left
destitute. At other times the onset is sudden and then the
danger of false commands or acts by a person in a responsible
position, as a steamship captain, an engineer or chauffeur,
may lead to loss of life and property.
295
Sudden grandiosity: debts. PARETIC NEUROSYPHILIS
(“general paresis”): Question of liability.
Case 84. Lester Smith was a salesman, 31 years of age,
who, while on a business trip, accompanied by his wife,
suddenly developed grandiose ideas. He originated a scheme
of cornering the phonograph market. His prospects seemed
so certain to him, that he hired an expensive suite of rooms
in a hotel at something over $35 a day. As at the first
presentation of his bill it was found that he had no money
to meet these charges, he was taken into custody and at
once transferred to a hospital for the insane, where it was
discovered that he was suffering from General Paresis.
1. What is the patient’s responsibility for these debts?
Legally the patient or his estate is responsible for
debts accruing from services rendered or goods received.
As he is adjudged non compos mentis contracts
entered into would not hold, and he would not
be considered liable for criminal acts.
Note: This case shows how dangerous paresis may be
not only to the life and usefulness of a patient, but further
how it may ruin a family financially. Mr. Smith’s little
escapade used up all the money that he had been able to
save in his life and when he was taken to a hospital his wife
was left destitute.
296
Suicidal attempt (?) by a neurosyphilitic.
Case 85. At first Mrs. Annie Monks, a widowed seamstress,
50 years of age, did not particularly suggest syphilis.
Mrs. Monks was sent to us from a general hospital. She
had been found unconscious in her room, with gas turned
on, and a diagnosis of gas poisoning was made. Mrs. Monks
remained unconscious for 24 hours, and her apparent suicidal
attempt seemed to warrant her being sent to the
Psychopathic Hospital. Mrs. M., however, scoffed at the
idea of any attempt at suicide, and claimed to have had no
recollection of any such affair. On the contrary, she had
gone to mass the morning of the day on which she was
taken to the hospital, remembered well enough returning
to her room but nothing of what followed until she woke up.
Mrs. Monks was not coöperative and would reveal few
facts about her history. For years, she had had edema of
the feet and palpitation of the heart (the heart was somewhat
enlarged, with a double murmur in the aortic area,
systolic louder, and a blood pressure of 160 systolic and
85 diastolic; clubbed fingers; palpable liver). She had
been treated in the out-patient department of a general
hospital for a number of months. We could obtain no
evidence of mental impairment, particularly none of memory.
Aside from the heart lesions above indicated, the patient
was fairly well nourished, with a slight enlargement of
superficial glands, and was otherwise normal.
Neurologically, the slightly irregular pupils reacted poorly
to light; the right knee-jerk could not be obtained, whereas
the left knee-jerk was very active. Systematic examination
revealed no other disorder except that the abdominal reflexes
could not be obtained.
Here we have, in a cardiac patient, a possibly or probably
accidental gas poisoning, and little to go upon for a profounder
diagnosis than the sluggish irregular pupils and
unilateral absence of knee-jerk.
297The routine serum W. R. came through as positive. Following
custom, we examined the spinal fluid, finding the
W. R. here again to be moderately positive (strongly positive
to 1 cc., moderately to 0.7 cc., and negative to 0.5, 0.3,
and 0.1 cc.). The gold sol index was 1 2 2 1 0 0 0 0 0 0,
which must be interpreted as syphilitic. There were 16
cells to the cmm., the albumin was 1+, and the globulin stood
at 2+.
Here, then, we seem to have evidence of an inflammatory
process of the central nervous system, and it is natural
forthwith to be sceptical as to the accidental nature of the
gas poisoning. Perhaps there was an attempt at suicide
based upon a passing impulse, or perhaps there was a period
of confusion in which the cock was not turned off.
In any event, we feel justified in making the diagnosis of
cerebrospinal syphilis on the basis of the neurological and
laboratory findings. On the whole, we are inclined to
make a diagnosis of Vascular Neurosyphilis with a moderate
involvement of the Meninges.
1. What is the outcome in such cases as that of Annie
Monks? The case somewhat resembled that of Martha
Bartlett, who still survives. The case of Annie Monks
illustrates another outcome. A few days after her
admission, she became unconscious once more, and
upon recovery remained very much confused and
aphasic, moaning, and unable to handle herself well,
although without definite paralysis. Three weeks
later the patient died, although in the meantime
strenuous antisyphilitic therapy was practised. Death
was sudden. We thought death due to cerebral
embolism.
298
Early delinquency and neurosyphilis in a juvenile.
Case 86. Frank Johnson was 21 years of age when he
was taken up by the police for threatening his sister with
a revolver. The police thought he deserved an examination
at the Psychopathic Hospital. The patient protested
that he had threatened his sister only to frighten her because,
he said, she nagged him and made him nervous. In
fact, they had always had trouble as she had always nagged
him and they had always fought together. Moreover, their
mother always took the sister’s part. They had been troubling
him for days, and at last Frank could stand it no longer.
His sister had complained of the way he treated her dog.
Moreover, Frank said he had not been feeling well; there
had been some trouble with his stomach; and after one of
the nagging attacks, he had taken out an old empty pistol
to scare his mother and sister.
In these cases, it is good practice to consult the sister also.
She said that Frank had always been very difficult to manage,
unwilling to work, preferring to loaf about, spending
every obtainable cent; he was once in a reformatory for
several years, but not reformed thereby; recently given to
drinking; at times acting somewhat peculiarly (sitting at
the window with his hat on, refusing to move).
Further mental examination of Frank showed that he was
properly oriented and in possession of a good memory, although
he was quite obviously a liar. He lay about in bed at
the hospital, saying that he was too weak to be up. He was
a bit dull, at times not readily grasping ordinary questions.
Physically, Johnson was rather thin; the teeth were somewhat
peg-shaped although far from typically Hutchinsonian.
The pupils were unequal and irregular, and failed to react
to light or even to accommodation when tested. The deep
reflexes of arms and legs could not be obtained, though the
superficial reflexes were present. For the rest systematic
examination proved negative. Serum W. R. negative.
299The first thought in such a case would be that the criminological
diagnosis of delinquency would be sufficient. However,
the pupillary disorder and the areflexia are suggestive
despite the negative serum W. R. Resort was naturally had
to lumbar puncture, whereupon a positive W. R. was found,
a characteristically “paretic” gold sol reaction, globulin, excess
albumin, and 134 cells per cmm. In short, it would appear
that we must consider a diagnosis of Juvenile Paresis,
and, in point of fact, the patient deteriorated rapidly from
this time, becoming demented at the end of a few months.
1. How far are the early difficulties of management (leading
to a reformatory) due to syphilis? We should not
dogmatically say that there is a relation between the
early delinquency and syphilis. Still, it is not unusual
to find emotional disorder and instability as well as
delinquency in congenital syphilitics.
2. What suggestion, if any, should be made to the patient’s
intelligent and seemingly normal sister, two years
older? We prevailed upon Miss Johnson to submit
to the W. R. of the serum, which was found, as in the
case of Frank, to be negative. Frank’s sister should
undoubtedly submit to a lumbar puncture; but in
the present phase of mental hygiene, she would be
difficult to persuade.
3. How is it possible to find such a marked evidence of
congenital syphilis in a younger sibling with no evidence
of syphilis in the elder? In the first place, there
may be a history of entrance of syphilis into the lives
of the parents between the pregnancies. However, in
other instances, there is no evidence of such intercurrent
syphilis, and contrary to the prevailing opinion
it is not so infrequent to find congenital syphilis in
the younger brother or sister of a normal person.
4. What can be said of treatment in such cases? In the
first place it is clear that delinquent cases should be
tested far earlier for the possibility of syphilis. Had
this case been examined by a neurologist or alienist
many years earlier, it is probable that the same pupillary
signs and the peg-shaped teeth would have been
found, and that the hypothesis of syphilis might have
been raised. There is no good evidence as yet that
these cases can be markedly benefited by treatment.
300
Neurosyphilis in a “defective delinquent.”
Case 87. Vivian Walker, 22 years of age, was arrested
on the streets of Boston for drunkenness. Upon arrival at
the jail, she developed a series of convulsions, each lasting
a very brief time, with loss of consciousness, frothing at the
mouth, and jerky movements of the arms and legs.
The Walker family was known to the police, since there
were police records in two generations on the maternal side.
The father was regarded as of rather low-grade mentality;
a sister had committed suicide. Vivian herself had been
irregular at school, was regarded as vicious, and had been
hysterical. She had been committed to a reformatory at
the age of 15 years. In the reformatory she had a number
of excited outbreaks, with resentment of discipline, and these
outbreaks presented hysterical traits. After each outbreak
Vivian was depressed. It was during her stay at the reformatory
that her sister committed suicide. Vivian attended
the funeral, and the idea of suicide appears to have
taken hold of her mind, as she constantly spoke of suicide,
threatened suicide, and made several attempts. She claimed
at this time to see visions and to hear her sister’s voice.
On that ground she had been committed to a hospital for
the insane at 16.
At the hospital there were many fluctuations in mental
condition. Vivian professed discouragement on account of
poor home influences, telling how her mother had often been
in prison, allowing Vivian to come under the influence of
bad girls. Now and then Vivian had outbreaks of profanity
and glass-breaking, and she also made at the hospital
for the insane several half-hearted attempts at suicide. At
the age of 19 she was returned to the reformatory, whence
she was placed out on probation and allowed to return home.
However, she was shortly re-committed to the insane
hospital in a phase of excitement, talking continuously of
men and sex relations, and also of imaginary illicit sex relations
301with any man whom she happened to see. Again
from time to time she made attempts at suicide. However,
she was allowed to go out on visit, returned to her habits,
and at the time of her arrest was living as a prostitute.
After her convulsions in jail, she was admitted to the
Psychopathic Hospital. At first obstinate and stubborn,
later she became tractable. Special mental tests left her
in the subnormal class, but we could hardly class her as
feebleminded. We were able to observe her in a number
of seizures, during which she would drop to the floor, apparently
lose consciousness, writhe about, and assume the
position of opisthotonos, the whole attack lasting but a
minute or two.
There was pelvic tenderness, with gonococci in the urethral
smear. Salpingectomy had to be performed, but after the
operation Vivian insisted upon getting up and running about
on the second day, tearing the bandages from her abdomen,
and infecting the wound. Outbreaks of excitement also
followed the operation.
In the diagnosis of this case, we must probably separate
the convulsive phase from the remainder of the phenomena.
The conduct disturbance, emotional outbreaks, and suicidal
attempts date from early youth, and no doubt the diagnosis
defective delinquent would fit Vivian from the beginning.
The hereditary taint is characteristic enough. The sundry
phenomena in the insane hospital, and particularly the hallucinations,
lead one to wonder whether Vivian is not possibly
even suffering from dementia praecox.
As to the convulsions, it would hardly appear that they
are typically epileptic, although certainly epileptoid. Their
onset at 22 is somewhat unusual. Several features of the
seizures together with the opisthotonos and the previous
history of hysteria, lead one to think of making the diagnosis
hysteria.
1. Can cerebrospinal syphilis cause the symptoms? We
found the serum W. R. to be positive though Vivian
denied syphilitic infection. (She also denied gonorrhœal
infection despite the clinical and laboratory
findings.) We found that the spinal fluid yielded a
302gold reaction of a typical syphilitic nature, showed an
excess of albumin, a slight amount of globulin, and
130 cells per cmm. Even these findings, however,
would perhaps not justify stating that the convulsive
seizures are of syphilitic nature. The seizures disappeared
under the administration of antisyphilitic
remedies. It would seem, therefore, that the seizures
should be regarded as of syphilitic nature. In any
event, the diagnosis of cerebrospinal syphilis is justifiable.
This syphilis, however, is of an active nature
and probably of recent production. We should be at
a loss to explain the earlier mental features in Vivian
as syphilitic and are therefore fain to associate the two
psychoses, Psychopathic Personality and Diffuse
Cerebrospinal Syphilis.
303
NEUROSYPHILIS (“paresis sine paresi”) in an
habitual criminal, a forger.
Case 88.[17] —— was brought to the hospital by the
police. He was charged with having forged a check, and on
account of the crudeness of the work his mental condition
was suspected.
Family History. The paternal grandfather was considered
fast, drank a great deal and was said to be a thief. The
father is said to have been forced to leave the State when a
young man in order to avoid the reformatory. Paternal
cousin murdered a man; the sisters of this cousin said to have
been wild and one brother married a prostitute. Nothing
known of maternal relatives.
Past History. Medical history is unimportant. He denies
syphilis. His early childhood is of little significance. He
was somewhat dull in school. At about the age of twelve he
began to lie and steal, and has continued this ever since.
His attempts have all been very crude, it is said, and when
confronted he would strenuously deny his deeds, even when
the evidence was overwhelming. He forged checks, borrowed
money from all his friends, and charged things at stores to
the family. The family paid the bills for a time, and then
later had him sent to a reform school. He was married at
nineteen, but wife has left him and obtained a divorce. He
has been excessively alcoholic for years, and is suspected also
of taking drugs. He was discharged from the navy dishonorably.
He later joined the army and was discharged therefrom
on account of “rheumatism,” according to his account,
but in reality deserted. He had finished a jail sentence of
thirteen months for forgery a little over a year before entrance.
Physical examination shows a well developed and nourished
man. The general physical examination is negative.
304The lungs show nothing abnormal. The heart is not enlarged,
there are no murmurs or irregularities; blood pressure, 145
systolic. The alimentary system is negative. No palpable
lymph glands. Neurological examination: pupils equal and
react to light and accommodation. Extraocular movements
well performed. Tongue projects in the median line, with no
tremor. There is no evidence of facial paresis or weakness
of the muscles. The biceps, triceps, knee-jerks and ankle-jerks
are present and equal on the two sides. There is no
Gordon, Babinski or Oppenheim; no ankle clonus. There is
no tremor of the extended hands. No Romberg sign. There
is a little difficulty in the finger-to-finger test. There is no
sensory disturbance either subjective or objective. No tenderness
over nerve trunks.
Mental examination shows nothing of a psychotic nature.
Patient is well oriented; memory for remote and recent
events is well preserved, school knowledge well retained, grasp
on current events good; no delusions or hallucinations elicited.
Patient is not feebleminded, according to the intelligence
tests of Binet and Simon and Yerkes-Bridges, but shows poor
attention and gives evidence of weakness in volitional spheres;
is very suggestible.
To summarize the case, then, we have a man of thirty years
of age who has shown criminalistic and anti-social tendencies
since childhood, whose general physical and neurological examination
is negative (excepting the laboratory tests), whose
mental examination shows no psychotic symptoms, and who
seems not feebleminded. In other words, with the exception
of the serological and chemical findings in the blood
and cerebrospinal fluid, there is nothing to suggest that he is
more than a “criminal type.”
Wassermann reaction in blood serum positive.
Wassermann reaction in cerebrospinal fluid positive. Examination
of cerebrospinal fluid: globulin ++, albumin ++,
cells 55 per cubic millimeter; large lymphocytes, 9.1 per
cent; small lymphocytes, 90 per cent; plasma, 90 per cent.
Gold sol reaction, 3321000000.
3051. Can the criminalistic tendencies be condoned in this
case on the ground of neurosyphilis? As a matter of
fact the delinquencies in this patient reach back to
early childhood and as there is no evidence of congenital
syphilis it cannot be held that syphilis had any
bearing in the causation of symptoms. Even were the
delinquencies only of recent date it is doubtful if the
court would take cognizance of the laboratory findings
in the absence of definite mental symptoms. In this
connection it may be stated that the court takes cognizance
only of the acts of a patient at time of examination,
and not of the history or laboratory findings,
in committing a person. We have had several patients
who from history, physical signs and laboratory tests
made the diagnosis of paretic neurosyphilis easy and
yet who could not be committed because they were
mentally clear at the time. Such patients may be of
grave potential danger to themselves and families, and
present numerous social problems. See case of Joseph
Wilson (95).
306
JUVENILE PARETIC NEUROSYPHILIS (“juvenile
paresis”) with initial trauma.
Case 89. Margaret Tennyson was a small girl of six
years, described as having been normal until run down by a
double-runner sled about 13 months before her arrival at the
hospital. The change was stated to be remarkable. “She
was as unlike her own self as darkness and daylight.” Once
fat and sunny, talkative and demonstrative with her toys, now
Margaret had become silent, sullen, worried, and of a violent
temper, stubborn and unmanageable. It does not appear
that the patient was seriously injured by the double-runner,
as she was able to walk a short distance home. Shortly,
however, she began to have trouble with her feet (diagnosed
at the time as flat-foot), and thereafter her whole character
and disposition changed. Upon arrival at the hospital, the
patient walked with a typical scissors gait of spastic paraplegia.
Physical examination was very difficult through lack of
coöperation and a screaming and kicking resistance upon
every attempt. There was a suggestion of hydrocephalus
in the protrusion of the forehead. The pupils reacted readily
to light and accommodation. The knee-jerks were active,
but there was otherwise no disorder of reflexes. The patient
had great difficulty in getting up from the floor, and for the
most part insisted upon lying in ventral decubitus on the floor,
crying when attempt was made to raise her. An attempt
was made to test her by the Binet scale, by which she was
found to rate at 2⅘ years although a portion of this low-rating
was thought to be due to a failure of coöperation.
The family history threw little or no light upon the case.
The parents were living and well; a brother of 16 years was
at work in the market district; two of the other siblings are
in the first and second grades at school and regarded as exceptionally
bright by their teachers. The fourth was the
patient, Margaret; a fifth had died at 9 weeks of heart trouble;
the sixth, seventh, and eighth, of 3, 1½ years and 3 months
respectively, appeared entirely well. There were no miscarriages
or stillbirths.
Juvenile paresis—spastic paraplegia. 5 years.
307The scissors gait and spasticity seem to point undoubtedly
to organic disease of the nervous system, along with which
the mental deterioration seemed to suggest an active progressive
involvement of the cerebrum. The history seemed
to be convincing that the child was not an instance of congenital
feeblemindedness.
A neurologist’s clinical diagnosis would naturally be syphilis.
In point of fact, this diagnosis was borne out by the laboratory
tests, which showed a positive W. R. in the serum and spinal
fluid, positive globulin, a slight excess of albumin, and a
syphilitic gold sol reaction.
1. What is the significance of the trauma in the case of
Margaret Tennyson? The trauma seemed to the
family the precipitating cause. We find cases of general
paresis in adults very definitely following trauma,
yet neurosyphilis, both in adults and in younger patients,
mainly occurs without trauma. On the whole, in this
case, it is perhaps safer to regard the trauma as mere
coincidence. A sister older than Margaret was found
upon examination to have a positive W. R. The other
children could not be examined.
308
Traumatic form of PARETIC NEUROSYPHILIS
(“general paresis”).
Case 90. The point about Joseph O’Hearn was his entire
mental soundness up to the time of an injury at work, when
he was blown through a double window in an explosion,
badly bruising his head. Shortly after the accident, although
not immediately, the patient began to show signs of mental
disorder, doing very foolish things, losing his memory, and
becoming unable to work.
It was eight months after the explosion when O’Hearn, at
the age of 36, was admitted to the hospital with general mental
impairment. O’Hearn was confused and disoriented for
time and place, although he seemed to understand that he
was in a hospital. He was given to foolish laughter and a
silly manner. There was considerable emotional disorder;
judgment was clearly impaired, and memory was poor.
Physically, there was little to be found except upon neurological
examination. The right knee-jerk was greater than
the left; the tongue and fingers showed marked tremor, there
was a speech defect and writing disorder.
On the whole, it seemed impossible not to make the diagnosis
General Paresis, especially in view of the laboratory
tests, with positive W. R. in both serum and fluid, a “paretic”
type of gold reaction, 59 cells per cmm., excess albumin,
and a large amount of globulin.
1. What is the relation of the trauma to the paresis?
Trauma is regarded as a precipitating cause, and Industrial
Accident Commissions have been known to
allow damages in such cases. Mott believes that the
symptoms of a post-traumatic paresis must not develop
until after a week’s interval of freedom from symptoms,
since he believes that time is required to destroy or
irritate the brain to the point of producing the paretic
picture. Our data are in agreement with those of
Mott. Mott also points out that gumma sometimes
occurs at the site of the trauma.
309
False claim for compensation in neurosyphilis.
Case 91. The facts in the case of Levi Sussman can be
brought out by the following extracts from a report to the
Industrial Board: A claim was made to the Board that the
symptoms had developed after a fall from a building, some
nine months before hospital observation. No connection could
be found between this accident and the Paretic Neurosyphilis
found. We introduce the case to emphasize the
possibility that irrelevant accidents may be regarded by
ignorant or unscrupulous persons as setting up a mental
disorder for which damages are claimed. If symptoms are
already in existence before the accident and are not especially
increased thereafter, naturally no damages should be recovered.
Unscrupulous persons may falsify about the pre-traumatic
history and claim the development of symptoms
immediately after the accident. Such claims are beyond
question to be viewed with the greatest suspicion. Some
days or weeks should elapse before definite symptoms in
post-traumatic paresis appear. Just how long an interval
may elapse between trauma and paretic symptoms and shall
entitle the case to be regarded as one of traumatic paresis,
is perhaps a matter of doubt. It would seem, however, on
general grounds that three months is the longest period in
which the post-traumatic effects are likely to be delayed.
The question of traumatic paresis is of great interest on
account of the war. The great strain under which the men
at the front live and the physical injury due to being
“buried” is probably responsible for an increasing number
of cases of neurosyphilis. Such at least is the impression
of Canadian medical officers with whom we have spoken.
See Section VI, Neurosyphilis and the War.
310
Traumatic exacerbation(?) in PARETIC NEUROSYPHILIS
(“general paresis”).
Case 92. The case of Joseph Larkin was of note from the
point of view of the Industrial Accident Board. This Irish
teamster was said to have been injured in his head two or
three months before coming up for examination at the age of
45. For a week Larkin had had frontal headaches, had been
sleeping poorly, and had been somewhat worried. In fact,
he had stopped work. The W. R. of the serum was positive
and a diagnosis of Paresis could be made. The case did not
come up for consideration by the Industrial Board until two
years after his initial appearance.
The physical examination showed irregular pupils, sluggish
pupillary reactions, Achilles absent, swaying in the Romberg
position, enlargement of the heart to the left, positive W. R.
of the blood and of the spinal fluid.
Mentally, the patient’s orientation for place was poor
and his memory defective. Emotionally he was depressed or
apathetic and was apprehensive. His flow of thought was
slow, and his insight into his condition poor.
It is interesting that a variety of causes have been assigned
in this case for the condition: such as, his work, anemia,
unhygienic surroundings, and arteriosclerosis.
This case is not a sharply-defined case of post-traumatic
general paresis, since there had undoubtedly been a variety
of mental changes before the accident. Accordingly, recovery
of damages to a full amount could hardly be expected
as in certain cases in which the phenomena of paresis appear
only after the trauma.
Post-traumatic cranial gumma—developing 13 months after local injury of skull.
311
Trauma: syphilitic lesion of skull at site of injury.
Case 93. The medicolegal interest of Richard Marshall
is extreme, as may be seen from the following brief report by
the Psychopathic Hospital to the Industrial Board.
“As to the case of Richard Marshall, a patient under
the provisions of the temporary care act from December
1 to December 10, inclusive, this case has proved unusually
interesting in that the patient has proved to be
syphilitic by the Wassermann reaction of the blood.
There is no evidence of syphilis in the examination of
the cerebrospinal fluid. The X-ray examination of the
skull, taken in connection with the Wassermann reaction
of the blood, warrants the diagnosis of syphilitic
osteitis of the skull at the site of the old injury. We
regard his present condition as shown by the X-ray
as a syphilitic bone condition predisposed to by the
injury. We do not find that the patient has any features
of traumatic neurosis.
“Mentally, having an actual age of 30, patient grades
at 11.2 years. It may be that patient has always been
a moron. He has earned about $8.30 a week.
“We regard the patient as deserving treatment and
feel that responsible parties in the case would do well to
have such treatment instituted.”
The principal symptom of which Marshall complained
was headache chiefly felt in the region of the osteitis.
There was marked sensitiveness to percussion in this area.
It is of course difficult to decide whether the headache
was entirely due to the gummatous lesions or whether the
trauma had caused contusions of the brain as well. It is
also possible that the dura underlying this area was involved.
312
OCCUPATION-NEUROSIS in a granite-cutter:
SYPHILITIC NEURITIS?
Case 94. David Fitzpatrick was a case referred to the
Psychopathic Hospital by the Industrial Accident Board.
He was a granite-cutter of 52 years of age, and had begun to
complain of pain in the forearm, extending back from the
elbow, about six months before admission. It seems that
the patient had been growing progressively worse and had
thought he would have to quit work because of difficulty in
grasping the hammer. A physician had told him that he
must stop his work at granite-cutting or else he would entirely
lose the use of his arm. He was in point of fact laid
off because of slackness of work and had been unable to get
work again. The pain in the arm, however, had continued
and at times was very severe. Sometimes the pain and the
worry led to insomnia. Fitzpatrick wanted the insurance
company to pay certain accumulated bills, and maintained
that he would be able to do work at $15 a week if work could
be found for him. The general situation in this case can be
gathered from the following abstract from the report to the
Industrial Accident Board.
“Secretary Industrial Accident Board,
“Dear Sir:
“In re David Fitzpatrick
referred to us with a copy of an impartial report filed
by the Massachusetts General Hospital,—we concur
with said impartial report that there is now no evidence
of paralysis of the arm. We do not find that the
positive Wassermann reaction, although it indicates a
history of syphilis, has affected the patient other than
possibly to have reduced his general mental capacity.
Our special tests yielded a percentage of 62% of what
a patient of his age and station should possess. There
seems, however, to be no connection between this reduction
of mental capacity and the difficulty with the arm.
We cannot connect the history of alcoholism with the
arm trouble.
313“There is some evidence that other stone workers
have at times shown such effects.
“The patient’s fairly circumstantial account of his
difficulty seems to point to a degree of myalgia or muscular
pain in the region of the forearm when held in a
certain position and a feeling of numbness in the third
and fourth fingers. Whether these phenomena are due
to local pressure upon nerves in the upper part of the
forearm due to neuritis, or whether we are dealing with
a functional neuralgic phenomenon is a question.
“We have applied some special tests for faradic
sensibility to all the fingers of both hands and have
found that the fingers of the right hand are still less
sensitive than those of the left, particularly the thumb
and the little finger. This test has not yet been applied
in a sufficiently large number of cases to prove
any difficult point, nevertheless the findings are in line
with the patient’s own circumstantial account of former
feelings of numbness in the third and fourth fingers of
the right hand.
“Obviously, then, our opinion is that there is still to
be found some effect of the disease, whatever it was,
which caused the patient to knock off work. If we had
more experience with such cases and more data with the
new test which we have applied, we should perhaps be
inclined to admit the diagnosis of occupation neuritis
and to suppose structural alterations in the nerve trunks
corresponding with the location of the muscular pain
and the anesthesia of fingers and the dulling of electric
sense, but in the present stage of our experience, it
is probably wiser to call the case one of occupation
neurosis.”
It is clear that the W. R. in this case was of peculiar value
in at least partially clearing up the findings, yet it must be
remembered that it is a principle of the modern administration
of industrial accident boards and similar organizations
that it is the employer’s lookout whether the employee has
syphilis. Recovery can be made as if the injury were due
wholly to an accident. It was not possible however definitely
to prove or disprove a relation of syphilis in the form
of a syphilitic neuritis to the condition in this case.
The special tests above referred to are the electric sensory
threshold tests of E. G. Martin.
314
Character change: neurosyphilis.
Case 95. Joseph Wilson offered a very serious social
problem. He was the father of two children, and his wife
was pregnant at the time of his admission to the Psychopathic
Hospital. He was a husky-looking man of 33 years of
age, but for the past four years he had been deteriorating in
his work; he had been drinking heavily, and finally had stolen
to obtain money for liquor. It was on account of his alcoholism
and delinquency, which were taken as an indication of
change of character, that he was sent to the hospital.
Examination on his arrival disclosed at once that there was
more to the case than alcoholism, for the neurological examination
showed that the pupils were irregular, the right
being larger than the left, both reacting sluggishly to light,
and there was an inequality in the reaction of the two eyes,
the left being better than the right. The tendon reflexes
were exaggerated, with ankle clonus on both sides, more
marked on the right. There was also a marked speech defect.
Otherwise the physical examination showed nothing
of importance.
The W. R. of the blood and spinal fluid was strongly
positive. The globulin test was strongly positive, the albumin
was markedly increased, there were 74 cells per cmm.,
and a gold sol reaction of the “paretic” type.
A formal mental examination did not show very much of
consequence; his memory showed no marked impairment,
he was not deluded or hallucinated, and he had a pretty
good insight into his failings. However, he was somewhat
childish, and his irritability was quite marked. Were one
to rely upon the mental signs alone, it is probable that a diagnosis
of chronic alcoholism with deterioration would be made;
but in the presence of the physical findings and the laboratory
tests, the diagnosis of neurosyphilis had to be given. It is
obvious that, while the patient was suffering from a progressive
brain disease, and while he did show mental symptoms,
315there was not sufficient ground on which to commit
him, and therefore he had to be turned out into the community.
As a matter of fact, he was not prosecuted on account
of his theft, because, although legally responsible, it
was felt that his disease was at the basis of the character
change which had led him into difficulties. Further developments
of his relations with society had to be considered,
however. It was possible to get him to discontinue the use
of alcohol altogether, and for nearly a year he has taken no
alcoholic liquor and has been self-supporting. However, his
irritability has been very great, making it very difficult for
his wife to live with him, and causing his sister to break off
all relations with him.
Here, then, is a man with a marked Character Change
as the result of neurosyphilis, so that it is difficult for him
to maintain the usual social relations. It does not seem
possible to remove him from the community.
1. May one speak of general paresis without mental symptoms?
If one considers general paresis a mental disease,
of course it cannot exist without mental symptoms.
However, if one considers the disease as a chronic
syphilitic meningoencephalitis characterized by its
pathological anatomy, then one may readily speak of
general paresis although no real evidence of mental
symptoms can be discovered. It would seem that we
must take this attitude with our present conception
of brain localization, for it is easy to conceive of a
general paretic process affecting areas which do not
definitely relate to psychic function. And further, such
a process may exist but not be of such a grade as to
cause mental symptoms.
316
The neurosyphilitic’s family should not be forgotten
in diagnosis and treatment.
Case 96. The Bornstein family is remarkable. Let us
hang the story on Becky, the mother, an Austrian woman of
43 years, who appears to have been perfectly well up to within
a year. About a year ago, Mrs. Bornstein began to suffer
from severe headaches, which were treated with apparent
success by an osteopath: at all events, Mrs. Bornstein recovered
therefrom in about six months. However, two
months later, she had a convulsion, with foaming at the
mouth, blueness of face, and general muscular stiffening.
The convulsion lasted for several minutes. Again, a fortnight
before admission, the patient had five convulsions of
an identical nature in a single night.
Moreover, since the first convulsion, Mrs. Bornstein’s
mental condition has altered and become variable, so that at
times she is excited, at times depressed. She would assert
inaccurately that there was some one in the house, and that
she had at different times committed crimes of a heinous
nature. Now and then she would seem to see moving pictures.
Her memory was poor and she seemed to believe
that events of five or six years ago had just happened.
The pupils were sluggish, the knee-jerks and ankle-jerks
were absent, there was slight ataxia, and there was speech
defect. The suspicion of neurosyphilis was so strong that it
seemed surprising that the W. R. of the blood serum, even
after repeated tests and after the provocative injection of
salvarsan, proved negative. However, the spinal fluid yielded
a positive W. R., and a gold sol reaction of the “paretic”
type, together with 12 cells per cmm., and a marked increase
of albumin, with positive globulin. It would seem warrantable
to make a diagnosis at least of syphilis of the nervous
system in this case, but it is a question whether we should be
warranted in making the diagnosis general paresis.
That the diagnosis is doubtful may perhaps be seen from
317the variety of diagnoses in the rest of the family. In the
first place, Mrs. Bornstein’s husband admits syphilitic infection
many years before. He states also that his wife after
marriage showed signs of syphilis and received some treatment,
although limited. It is stated also that the husband
himself at this time has a positive W. R. and has stiff pupils
and petit mal attacks. The oldest son, 22 years of age, is
confined in an institution with juvenile paresis. The second
son has recently died at the age of 20 years, receiving a diagnosis
of rupture of the aorta. A third son, 19 years of age,
has the appearance of having achondroplasia, although the
proportions of his limbs do not quite correspond with those
of an achondroplast. The fourth son, 17 years of age, is
suffering from caries of the spine. A fifth son, 14 years old,
is neurotic and has the so-called Olympic forehead. The
sixth and last son died shortly after birth of unknown cause.
318
Neurosyphilitic’s normal-looking family proved
syphilitic.
Case 97. Walter Heinmas was a draughtsman 33 years of
age when he was brought to the Psychopathic Hospital suffering
from mental disease. This was diagnosed as general
paresis, both on account of the clinical symptomatology and
on account of the laboratory findings. In fact, it was a case
of the classical type with marked euphoria and grandiosity.
As is the routine procedure at the Psychopathic Hospital,
in the case of all syphilitic patients, the family was sent for.
This consisted of the wife and two daughters, aged 9 and 7
respectively. The patient denied any knowledge of a syphilitic
infection. The wife, also, gave no history of any primary,
secondary, or tertiary symptoms; there had been no abortions,
miscarriages, or stillbirths; both children had been
born at term and had been entirely healthy. Examination
showed that the mother had no signs referable to syphilis, and
that both the children were mentally well endowed, with
good physique and showing no stigmata of congenital syphilis.
Still the W. R. of all three (the mother and the two children)
was positive in the blood serum. These tests were repeated
several times on the children, with and without injections
of salvarsan, and they remained consistently positive.
1. Are these children to be considered congenital syphilitics
despite the absence of stigmata or symptoms? We
must consider these children as congenital syphilitics
and candidates for the group frequently spoken of as
syphilitis hereditaria tarda.
2. What is the frequency of syphilitic involvement in the
mate and children of paretics? In our series, we have
found that about 15% of the marriages where one
member develops paresis, result in sterility; that in
18% abortions, miscarriages and stillbirths occur;
and that in 15% positive W. R. is obtained. We have
adopted the motto: “The families of paretics are the
families of syphilitics.”
319
Neurosyphilis: question of marriage.
Case 98. Mr. Jacobs’ wife was admitted to the hospital
with a diagnosis of general paresis. A few weeks after her
admission, she died as a result of her disease. According to
our routine, her husband and the children were examined for
evidences of syphilis.
Mr. Jacobs’ blood serum was found on repeated tests
to be positive. He resolutely denied any knowledge of a
syphilitic involvement, but it was later learned from his
brother that about two years before his marriage—that is,
more than 25 years before we saw him—he had acquired
syphilis and had had a very small amount of treatment.
Mr. Jacobs was put upon antisyphilitic treatment in the
form of injections of .3 gram of salvarsan every two weeks
with occasional intramuscular injections of mercury salicylate.
After seven months of treatment, the blood serum still remained
positive. At about this time, the patient came to us
to ask about getting married again. He said that he was
living with his sister, who kept telling him that he was the
cause of his wife’s death, and this was so unpleasant that he
desired to start a home for himself again!
1. What advice should be given? It is a general opinion
that the longer the period after the initial infection, the
less the chances of infecting a partner. This chance
is further reduced under antisyphilitic treatment, of
which a considerable amount had been given in the
case of Mr. Jacobs. However, when one considers
the trickiness of syphilis and the fact that there is some
chance of infection, which we would apparently overlook
if we gave him permission to marry at this time,
the only possible course was to tell the patient that he
should not consider marriage until his Wassermann
had become negative and remained so for some time.
The children in this case were negative.
2. What is the physician’s duty to the family of a syphilitic
patient? It is our firm conviction that it is the duty of
320every physician to his syphilitic patient, to the patient’s
family, and to the community, to examine the mate
and the children for evidence of syphilis acquired or
congenital and to offer treatment if it is found to be
needed. This is one of the chief means at our disposal
today to prevent the late disasters of syphilis, acquired
or congenital, for by such examinations the syphilitic
condition is discovered before lesions have occurred
which are irreparable. We know that the mate and
children of a syphilitic patient have been exposed to
syphilitic involvement, and it is our duty as physicians
in possession of such knowledge, and as guardians of the
public health, to investigate such cases, so that if they
be found to have syphilis, steps may be taken to treat
them early.
3. How much danger is there of causing unhappiness and
breaking up families by this procedure? This question
offers a chance for many theoretical answers. The
facts are, however, that in doing this as a routine
for nearly three years and examining several hundred
families, there has been no instance to our knowledge
in which a family has been broken up or grave difficulties
have been encountered by this procedure.
4. In what percentage are the mates or children of neurosyphilitics
found to show definite symptoms of syphilis?
It is our opinion that the situation in regard to neurosyphilitics
is the same as for syphilitics in general:
That the same laws of attenuation of virus, and of
chance occur here as elsewhere.
Just as this book is going to press, we have learned that the
distraught Mr. Jacobs, still desirous of starting a home for
himself and feeling entirely well, consulted a physician.
This physician took a sample of blood and had it tested at a
competent laboratory, which reported the blood negative.
On the strength of this test, the physician felt himself
warranted in recommending, or at least not advising against,
Mr. Jacobs’ marriage, which has probably now taken place.
Although there is some doubt what ethical relation a state
institution shall maintain with physicians in private practice,
we took occasion to call the attention of our patient’s new
counsellor to the fact of the patient’s neurosyphilis. We
noted that the man’s serum had been constantly positive
321(Massachusetts State Board of Health findings) in a score or
more of observations. We called attention to the fact that
lumbar puncture had shown positive signs of neurosyphilis,
including a positive W. R., globulin, excess albumin, pleocytosis,
and positive gold sol. These facts, according to a letter
received from the private practitioner in question, have
not altered his opinion in the slightest to the effect that our
patient is completely normal and entirely suitable for marriage.
It is clear that he regards the patient as not a victim
of General Paresis.
5. What is the significance o the negative observation
eventually obtained in Jacobs’ serum? One’s first
thought is to impugn the accuracy of the laboratory
work, but against this suspicion is the excellent reputation
of the laboratory in question, and the agreement
in the majority of its findings with those of the
State Board of Health. It is more likely, as we assured
the private practitioner at whose request the observation
was made, that this negative test was an exceptional
and isolated observation such as is not infrequent in
long series of observations, particularly those made
under therapeutic conditions. In so important a matter,
we are inclined to feel that the physician in question
should have resorted to two more observations at intervals
before running counter to the position taken
by the hospital.
322
——many a hard assay
Of dangers, and adversities, and pains.
Paradise Regained, Book IV, lines 478–479.
323
Cases 99–103 show the Variety of Structural Lesions that
Treatment has to face.
SPASTIC HEMIPLEGIA in PARETIC NEUROSYPHILIS
(“general paresis”), showing marked
degenerative changes, a condition in which therapy
could be theoretically of very little avail. Autopsy.
Case 99. James McDevitt arrived at the Danvers Hospital,
July 20, 1906 (saying that he came to be “thawed
out”), and died less than six months later: January 12, 1907.
He was 34 years of age. He had been a shoe-worker after
leaving school, had worked eight years with the General
Electric Co., and had then become a bartender. He had,
however, stopped work in September, 1905, and we may
safely say that mental symptoms had begun insidiously at
about that time. His symptoms, if there were any, had been
masked by a heavy alcoholism, but an obvious change had
appeared in November, 1905. The patient lost ambition,
smoked and loafed about his room, and developed speech
disorder. He denied venereal disease, nor was there any
superficial evidence of such.
Physically, the patient showed little or no disorder except
acne of the trunk, patches of eczema on the left lower chest,
and numerous brownish scars along both tibiae.
Neurologically, the Romberg position was maintained, but
the gait was very unsteady on attempts to walk a straight
line; fingers, tongue, and face were tremulous, and finer
movements were performed with marked incoördination.
No direct or consensual light reactions could be obtained in
the pupils, which were dilated and irregular.
The condition of the reflexes is important on account of
the autopsy findings. The abdominal and cremasteric reflexes
were prompt, and the knee-jerks equal and very lively.
Achilles and normal plantar reactions were present; there
was no clonus; the arm reflexes were very brisk.
324
COMMON THERAPEUTIC CONCEPTION
- [M]VP =
- TYPICAL PARESIS
- MV[P] =
- TYPICAL CEREBROSPINAL SYPHILIS
- [M]V[P] =
- TYPICAL SYPHILITIC ARTERIOSCLEROSIS
(M = Membranes, V = Vessels,
P = Parenchyma, [] = not involved)
Chart 21
325The mental symptoms need not detain us. Consciousness
was clear; orientation for time, place, and to some extent for
persons, was imperfect. Arithmetic had been largely forgotten.
Handwriting was irregular and scrawling, and in
places unintelligible. Although the patient claimed that
his memory was intact, it was decidedly imperfect. He
remarked that John D. Rockefeller, a Chicago king, was President;
the General Electric Works had almost 50,000 people
at work; and in fact Lynn was one of the largest cities in the
state, having over 12,000 people. The height of patient’s
room was estimated at 25 feet. There was a slight euphoria.
There was never any doubt of the diagnosis of Paretic
Neurosyphilis (“general paresis”).
Five months after admission, slight convulsions developed,
after which the patient was more dull and demented; he
became bedridden. More convulsions followed, leaving the
right arm and hand useless. There were clonic spasms of the
muscles of both lower legs. Decubitus developed and death
occurred.
We may set the total duration of symptoms in the case of
James McDevitt at a little over a year; nor is there any
evidence of previous or prodromal symptoms beyond a total
period of about 15 months, unless we may regard his leaving
the General Electric Works to become a bartender some nine
years before death, as a symptomatic change of character.
In any event, it is of note that the autopsy showed singularly
few lesions. Death was due doubtless to complications
following decubitus, and there was a slight acute splenitis.
The kidneys showed some parenchymal change. The aorta
showed many patches of sclerosis, with calcification or ulceration
throughout its length. These changes were not characteristic
of syphilitic disease. There was considerable coronary
arteriosclerosis and a slight mitral valvular sclerosis. There
was a brown atrophy of the heart muscle, somewhat surprising
in a man of 34 years. The brain was practically normal,
weighed 1200 grams, and showed convolutions normal in
size, relation, and arrangement. There was no sclerosis
326grossly evident in the blood vessels. The pia mater appeared
to contain a considerable excess of clear fluid. The calvarium
was of normal thickness and showed diploë and the dura
mater failed to show adhesions. There were no macroscopic
signs of lesion in the spinal cord.
Microscopically, the lymphocytosis, plasmocytosis, and
phagocytosis of the perivascular spaces, (relative?) increase
in blood vessels, the gliosis, and evidence of nerve cell destruction,
taken together warranted the diagnosis of Paretic
Neurosyphilis. It was plain that the nerve cell destruction
was best marked in the inner layers of the cortex. The
microscopic study of the spinal cord showed that there was
very possibly a slight sclerosis of the posterior columns in the
lumbar region, but this was so slight that it could hardly be
noted in the myelin sheath stains (Weigert). Very sharply
marked, on the other hand, were the bilateral pyramidal
tract lesions in the lumbar and thoracic regions, less marked
at the cervical levels.
Without attempting to analyze carefully all these findings,
it is interesting to note in this case a foil to the usual spinal
cord picture of paretic neurosyphilis. The spinal cord, ordinarily
normal, or perhaps more usually affected by a degree
of posterior column sclerosis, in this case showed such well marked
pyramidal tract sclerosis that we may perhaps place
the case in a subordinate group of Spastic Paretic cases
of Neurosyphilis. The source of the pyramidal tract disease
lodges, however, in the cortex cerebri itself, being part
and parcel of the lesions mentioned above as affecting more
directly the inner layers of the cortex. Many of the so-called
giant, or Betz, cells had undergone a complete destruction.
It will be remembered that clonic spasms of the muscles of
the legs appeared in the fortnight preceding death, and that
there had been convulsions for about six weeks before death.
There was no evidence at the autopsy why the right arm and
hand should have become useless, whereas the left upper
extremity remained normal. This case, then, forms an exception
to the ordinary paretic neurosyphilis group in that
the brunt of the microscopic process was borne by the inner
layers of the cortex. The cells of origin of the pyramidal
tract fibres had been cut in this lesion, and had become subject
to partial or complete destruction. Note, however,
that the lesion remained a microscopic one and that the
marked convulsions were not related to gross lesions, thereby
following the rule for paretic seizures.
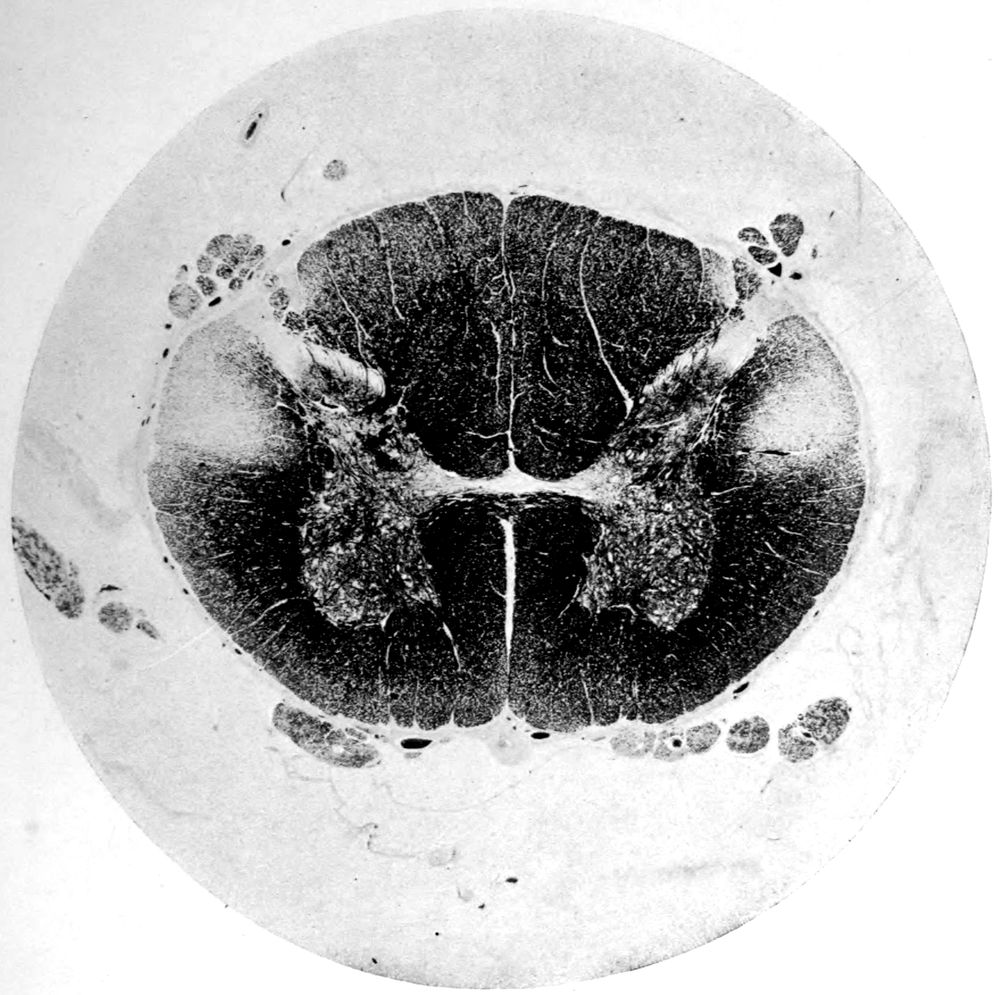
Bilateral pyramidal tract sclerosis, secondary to destruction of large motor (Betz) cells of motor (precentral) cerebral cortex—paretic neurosyphilis.
327From the standpoint of possible treatment, it is of course
true that few organs of the body showed grave lesions save in
the calcified and ulcerated aorta, which conceivably might
have become quiescent under appropriate treatment. But,
although the brain was almost if not quite normal in the gross,
and although its membranes showed practically no lesion,
treatment would not have been very promising. To be sure,
the exudate might have been cleared away if the spirochetes
responsible therefor had been destroyed by treatment. Yet
the destruction of the giant cells of origin of the pyramidal
tract fibres to such an extent as in this case could hardly
have been compensated for by any known process. So far
as we are aware, the destruction of considerable numbers of
the smaller association elements of the brain is subject to the
compensation of other elements of the nervous system, which
conceivably might be re-educated or newly educated to perform
certain processes. The histological picture in a case
like that of McDevitt accordingly leads to the hypothesis
that so well marked a spastic paresis, even in the presence
of otherwise favorable signs, would be of especially baneful
portent therapeutically.
328
NEUROSYPHILIS with total duration of symptoms
twenty-two days. The comparatively MILD
BRAIN LESIONS, INFLAMMATORY AND NOT DEGENERATIVE
in type, suggest the possibility that
therapy might have been successful. Autopsy.
Case 100. Jacob Methuen, 35, was a carpenter from
Newfoundland. He was working upon a certain Thursday
with his brother, who noticed that Jacob was lifting the tools
about in an unusual manner and talking strangely to his
fellow workmen. He fell asleep, going home in the street car,
and said afterward that he felt dazed and peculiar. He talked
all kinds of nonsense to his wife upon arrival. Methuen
remained in bed next day, fancying he was going to die,
calling his family together, and saying good-bye to them.
He remained in bed all through the next day, but on Sunday
appeared better,—more active, and in fact quite natural.
He slept only an hour Sunday night, calling to his wife that it
was time to get up. On Monday he began to be irritable
to his wife, and accused her of flirting with his brother and
intending to elope with him. He struck his wife several
times, and when two brothers came to watch him, accused
them both of trying to steal his wife, and struck them. Tuesday
he remained in bed until late at night, when he arose
and tried to assault the family.
It seems that another brother of the patient had died but
eleven days before his admission to the hospital and five days
before the onset of Jacob’s symptoms. Since his brother’s
death he had been dwelling upon religious matters, and in
fact the day after his brother’s death, he waked up during
the night, saying that he was too happy to sleep, that he
heard the Master’s voice, and at times the devil’s voice;
that there was to be a modern miracle and his spiritual life
from now on would be different.
Eleven days after admission to the hospital, Methuen
died, making a total duration of symptoms, beginning at his
brother’s death, of 22 days.
329
NEUROSYPHILITIC LESIONS
LESIONS OF THE SECONDARY PERIOD
(1) INTERSTITIAL ENCEPHALITIS OR MYELITIS
(“meningitis”)
(2) PARENCHYMATOUS ENCEPHALITIS OR MYELITIS
(“encephalitis,” “myelitis”)
LESIONS OF THE TERTIARY PERIOD
(1) CHRONIC INTERSTITIAL ENCEPHALITIS OR MYELITIS
(“gummatous meningitis”)
(2) CHRONIC PARENCHYMATOUS ENCEPHALITIS
(“dementia paralytica”)
(3) CHRONIC PARENCHYMATOUS MYELITIS
(“tabes dorsalis”)
“We have shown that the central nervous system is affected by syphilis
at the same periods and in the same manner as are other internal organs.
In addition the ‘parasyphilitic’ lesions are also of a typically syphilitic
nature, being directly comparable to the parenchymatous affections
found elsewhere in the body. They are ‘tertiary’ lesions differing
only from the so-called ‘gummatous’ processes in the central nervous
system in that their localization is in the parenchyma while that of the
latter is in the interstitial tissues.”
McIntosh and Fildes, 1914
330Physical examination showed a man 5′ 9″ tall, weighing
149 pounds, rather pale and poorly nourished, with a somewhat
enlarged heart and no evidence of venereal disease.
Neurologically there was a slight facial and digital tremor,
but otherwise no symptom or reflex disorder except that the
tendon reflexes were generally increased; the knee-jerks
especially were very vigorous. There was no speech defect.
His handwriting was fairly legible.
The patient was very noisy and uncontrollable, tearing
clothing and biting, striking the attendants, refusing food,
talking rapidly, loudly, and incoherently. His manner suggested
auditory hallucinations but no positive evidence of
these was obtained. His clothes could not be kept on him.
The following is a sample of his reactions: As the examiner
entered, the patient stood stark naked and glaring. He
started to talk as follows: “Methuen,—I, Saviour, come
to life and ought to die—— Now I lay me—— Now I
die—— The heart beats—— No, I ain’t going to die—— I
am going out soon. I want my clothes—— You
can’t hold me; I am strong.” (Struggles violently with the
attendants.) “I am God. God. I know you, you can’t
fool me.——I am here——I can do you all. How
many doctors are there here?” (Struggles violently. Looks
at examiner.) “He is writing something. Sir, you can’t fool
me in a million years. Do you understand that, doctor?
You can’t fool me. Write all the prescriptions you want to.
Ten thousand years; you hear that, doctor? Ten thousand
years. You can’t fool me; ten thousand years. Ten thousand
years are but a day for the spirit of the Lord,” etc., etc.
The excitement continued unabated. The patient became
entirely disoriented, and finally almost unable to move.
He lay in bed trying to talk and muttering broken gibberish,
still attempting to struggle to the extent of his limited
strength.
The autopsy showed no sign of lesion (brain weight 1380
grams), unless, perhaps, the occipital regions were slightly
firmer than the rest of the brain. Death was apparently
due to a bilateral pneumonia, bronchial type. There was
an acute splenitis. The only chronic lesions of the body
were a bilateral chronic adhesive pleuritis and a slight sclerosis
of the arch of the aorta.
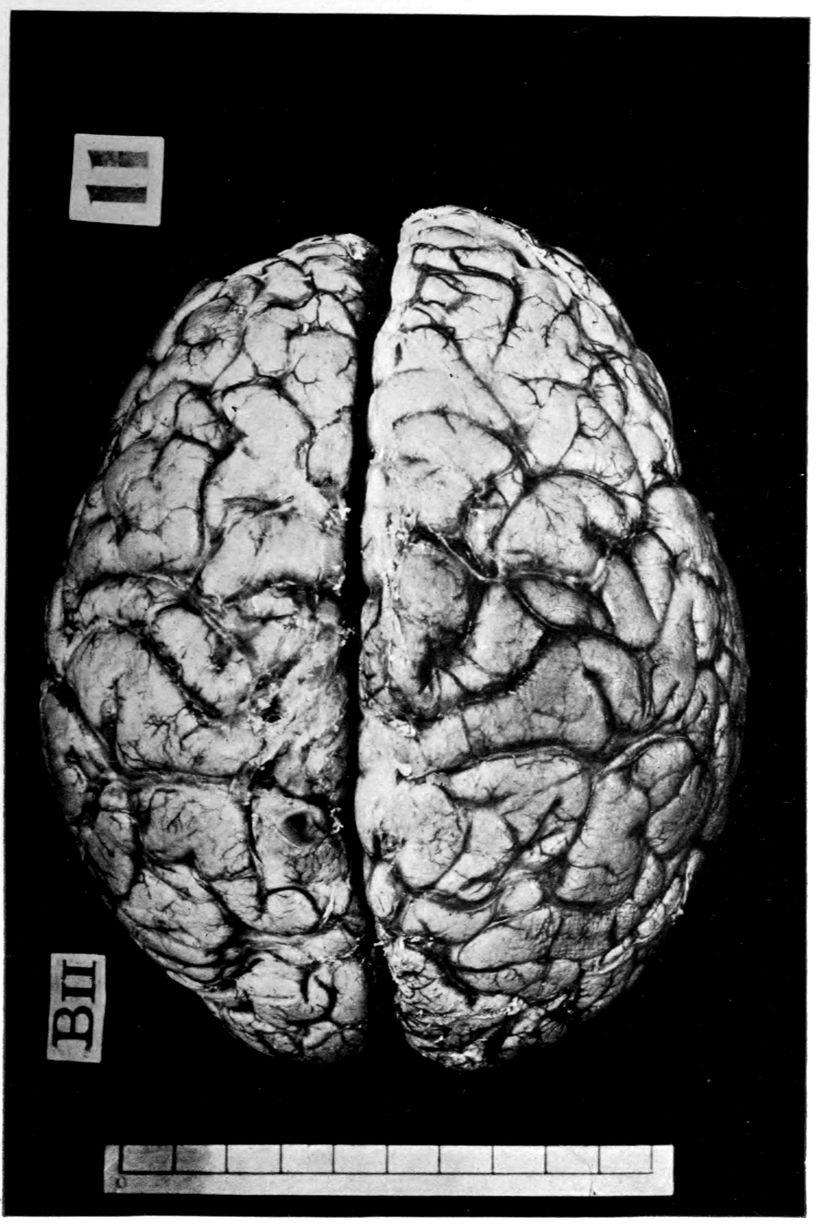
Paretic neurosyphilis (“general paresis”) macroscopically normal, microscopically characteristic. Treatment does not have to face massive destructive processes already complete.
331Microscopically there was a distinct though mild degree
of lymphocytosis of the perivascular spaces in many regions.
Somewhat extended search failed to reveal plasma cells, and
it is certain that if plasma cells existed, they must have
occurred in very small numbers.
Here, then, was a case of Diffuse Neurosyphilis (with
brain picture consistent) with symptoms lasting but 22 days
and with an appearance of acute mania. It is to be noted
that this case arrived at the hospital on the eleventh day of
his symptoms. The case occurred long before the development
of the temporary care system in Massachusetts. It is
probable, or at any rate possible, that he would have been
brought to the hospital far earlier, say, upon the sixth day,
had the modern temporary care system been installed at
that time. The routine W. R. examination would then
have been made. With more effective hydrotherapy, it is
possible that the patient’s life might have been prolonged
and that treatment might have been effective. So far as
we can see, the case would have been a singularly good one
for treatment despite the practical unmanageability of the
case under ordinary home treatment, and even under hospital
conditions where modern hydrotherapeutic appliances
are not available.
332
PARETIC NEUROSYPHILIS showing very
MARKED MENINGITIS, suggesting that therapy
might have produced improvement. Autopsy.
Case 101. We report the case of John Baxter, a boat
tender of 48 years, because this particular victim of Paretic
Neurosyphilis seems to have had the most markedly thickened
and altered meninges in our whole series. Of course, the
therapeutic theory upon which we now proceed in the treatment
of non-paretic and possibly even of paretic neurosyphilis
is that, other things being equal, the meningitis
can be removed by treatment, or in the course of treatment,
so that the degree of ultimate recovery rather depends upon
the condition of the brain substance itself than upon the
condition of the meninges. Here, at all events, is an example
of the most highly meningitic neurosyphilis that we have
seen.
Curiously enough, two of Baxter’s brothers were also
patients at the hospital at which Baxter died, and a number
of the other members of the family are reported as “nervous.”
It seems that at 35 Baxter began to drink heavily and had
never given over the habit of alcoholism.
Upon admission to the hospital, in fact, he showed a sufficiently
typical picture of delirium tremens. His consciousness
was clouded, he had vivid visual hallucinations and was
very apprehensive.
His heart was enlarged to the left; the pulse, 120, was of
increased tension and irregular; there was peripheral arteriosclerosis;
the teeth were poor; the tongue coated; and
the mouth foul. The urine showed a trace of albumin and
rare hyalin casts.
Neurologically, the gait was somewhat unsteady, there
was an extreme tremor of the whole body, including the
tongue and fingers. The Romberg sign was negative although
there was marked swaying. The pupils were equal and reacted
normally; the knee-jerks were markedly exaggerated, the
arm reflexes somewhat exaggerated. The remainder of the
reflexes upon systematic examination were negative.
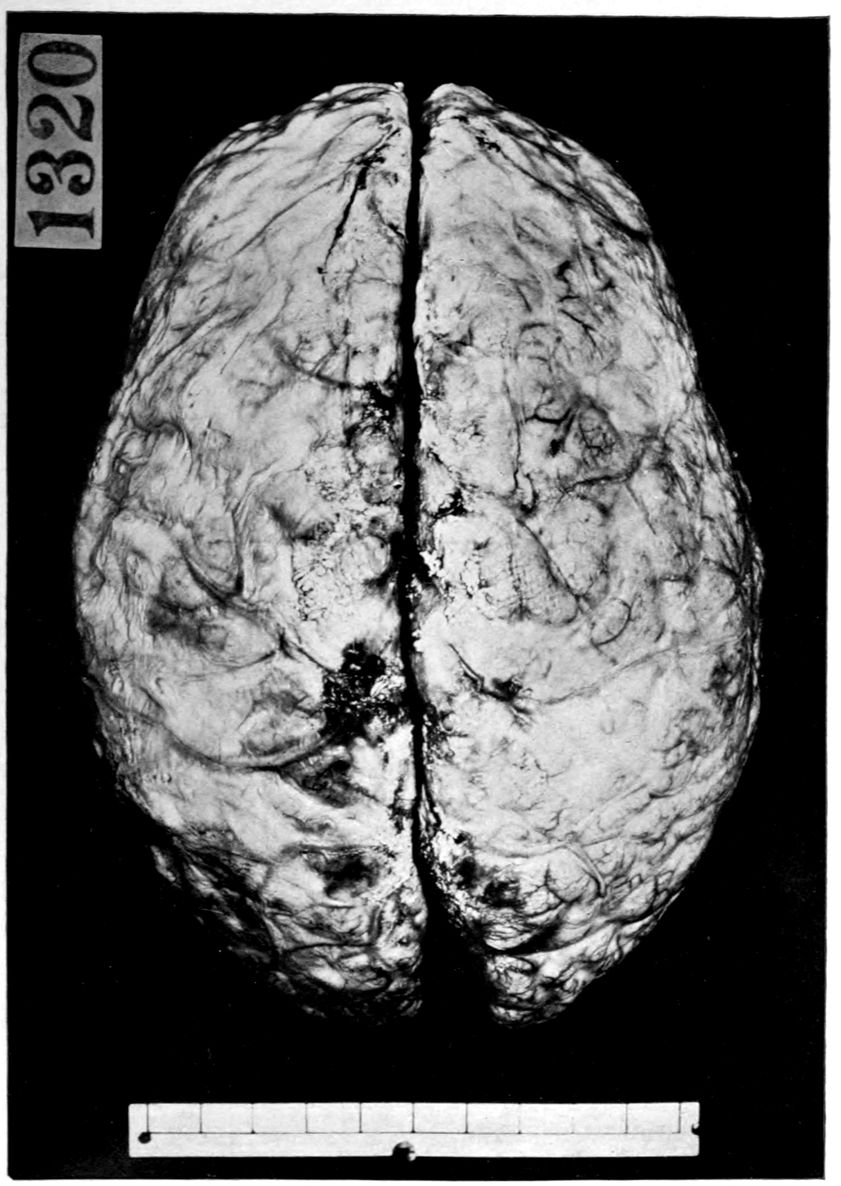
A high degree of chronic leptomeningitis. Pia mater thick, opaque, concealing brain. In paretic neurosyphilis (“general paresis”).
333Upon arrival, Baxter was put to bed, but he barricaded
his door and fought with the attendants. The tremor increased,
the hallucinations were both visual and auditory.
After a few days, Baxter became so weak that he could not
move. He refused to eat for a period of two days, explaining
in whispers that he did not wish to be poisoned; a voice
had told him the food was to be poisoned. The voice was of
agreeable tones, probably belonging to a lady; it did not
speak, but sang to him. The clouding of consciousness
failed to clear up, as in delirium tremens, so that, though
patient was admitted March 3d, it was hardly possible to
speak freely with him until more than a month later, April 9th.
A good-natured conversation would run as follows:
| “What is your name?” |
“Baxter.” |
| “First name?” |
After long pause, “Don’t know.” |
| “John?” |
Pause of 7 seconds, “Yes, I think it is.” |
| “How old are you?” |
“There are legs——there is a body——up to here——” |
| “Say the alphabet.” |
Term not understood. |
| “Say the a, b, c.” |
“Oh yes; a, b, c, d (long pause), e, f; I cannot say it, I did not have much education; I am not intelligent.” (In point of fact, the patient had a good grammar-school education, and had long worked as a clerk in a grocery store, with good wages.) |
| There was some speech defect. |
|
Soon the hallucinatory phase passed, and the patient
remained in a cloudy and disoriented state, inaccessible,
rarely speaking, and gradually failing physically. Death
occurred about three months after admission (pulmonary
symptoms).
In estimating the duration of the process in John Baxter,
we must take into account that he left the grocery business
and became a hard-working but poorly-paid boat tender at
334about 35 years, at the same time that the alcoholic habit
began.
The autopsy showed that death was due to bronchopneumonia
with pleurisy. There were in the body a variety
of chronic lesions, such as gastritis, colitis, epididymitis,
splenitis, parietal and valvular endocarditis, prostatitis, chronic
appendicitis, and some mesenteric lymphnoditis. The heart
was somewhat hypertrophied. There was a slight diffuse
nephritis with cysts, emaciation, and decubitus. The calvarium
was thick and somewhat dense. The dura was
thickened and adherent, and the pia mater,—as above
stated, the most thickened and altered pia mater in our
series,—is described as everywhere thickened, of a brownish
gray and white color, especially over the vascular lines, and
as showing small white areas of deeper thickening scattered
over the surface, but most markedly over the sulci, and not
as a rule over the crowns of the gyri. There were also yellowish
brown spots with a suggestion of fibrin over the lateral
aspects of both hemispheres. The vessels at the base were
not remarkable in the gross. The brain weighed 1220 grams,
and appeared to be of darker color than usual.
335
Some cases of PARETIC NEUROSYPHILIS
(“general paresis”) have so much BRAIN
ATROPHY that it is not possible to expect much
improvement through antisyphilitic therapy.
Case 102. Theodosia Jewett, dead at 58 years, showed the
most remarkably wasted brain in a long series of victims of
paretic neurosyphilis. We present her case to emphasize
what therapy must face in certain instances, but would
recall the fact that exceedingly few such wasted brains have
come to our attention in cases dying in the institutions of
Massachusetts.
Mrs. Jewett, a housewife, whose parents died of shock, and
one of whose two brothers also died of shock, was a normal
child and schoolgirl, and worked as dressmaker until she
was married, at 24, to a grocer, by whom she had two children.
At the age of 46, Mrs. Jewett began to suffer from so-called
“nervous prostration.” The attack lasted some two years,
but there were no psychotic symptoms beyond worry and
insomnia. The menopause occurred at 52, at which time
the first signs of psychosis appeared, namely, a forgetfulness
concerning familiar matters, such as sewing, cooking, and
the like. At 55, this amnesia had become so marked that
Mrs. Jewett could neither write nor tell time. She, however,
was a perfectly quiet and easily manageable patient, often
subject to drowsiness in the day.
Six months before her admission to the hospital, she began
to suffer from insomnia, failed to recognize her surroundings,
and had a number of crying spells. Restlessness had begun
a month before admission; auditory hallucinations developed
in the form of imaginary conversations with dead persons.
A certain loquacity set in, and for a week before admission,
Mrs. Jewett became somewhat resistive.
Physically, the patient was sallow, poorly nourished, with
pale mucous membranes, peripheral arteriosclerosis, no teeth,
muscular feebleness, tremor of hands and tongue, and active
336knee-jerks. Mentally, the patient was depressed, talked to
herself, assumed a supplicating position, suddenly altered
her attitude, and was very tremulous. Her talk was low,
mumbling, and incoherent, for the most part composed of
answers to her own questions. Sometimes there was a
curious difficulty in speaking, such that the lips moved but no
sound emerged; but for the most part there was no difficulty
in uttering words. The patient either could or would not
write. Only when the attention was secured by speaking to
her sharply was she apparently able to understand questions,
and the answers to these sharp questions came spasmodically
and as if interrupting her own thoughts. Nor was it ever
possible to obtain a repetition of the same answer.
The patient died in exhaustion, with pulmonary symptoms
three weeks after admission.
The autopsy which was performed 3½ hours after death
showed the following points of interest:
The heart weighed 210 grams. There was marked thickening
of the aortic valve. The coronaries were slightly
thickened.
The lungs were slightly adherent to the chest wall at the
apices and posteriorly. The right lung was consolidated
in the lower two lobes posteriorly and the bronchi exuded
pus; the left lung was not remarkable. There was a chronic
splenitis.
The liver showed fibrous changes, was a brownish-red in
color, mottled with yellow.
Combined weight of the kidneys 195 grams. The capsules
were adherent, tearing the cortex when stripped.
The diploë were well marked. The dura was not adherent.
The pia was slightly thickened and raised from the cortex by
a large amount of subpial fluid (showing atrophy of the cortex).
The pial vessels were injected, more markedly so on the left
side. The arachnoid villi were reported as moderately developed,
especially along the longitudinal fissure.
The brain was rather soft in all regions. The weight
was 1045 grams. According to Tigges’ formula the weight
of the brain should be approximately 8 times the body length
in centimeters. The length in this case was 158 cm., therefore,
according to this formula the weight of the brain should have
been 1464 grams. The difference of more than 400 grams
is evidently a loss to be accounted for by atrophy, a very
heavy loss.
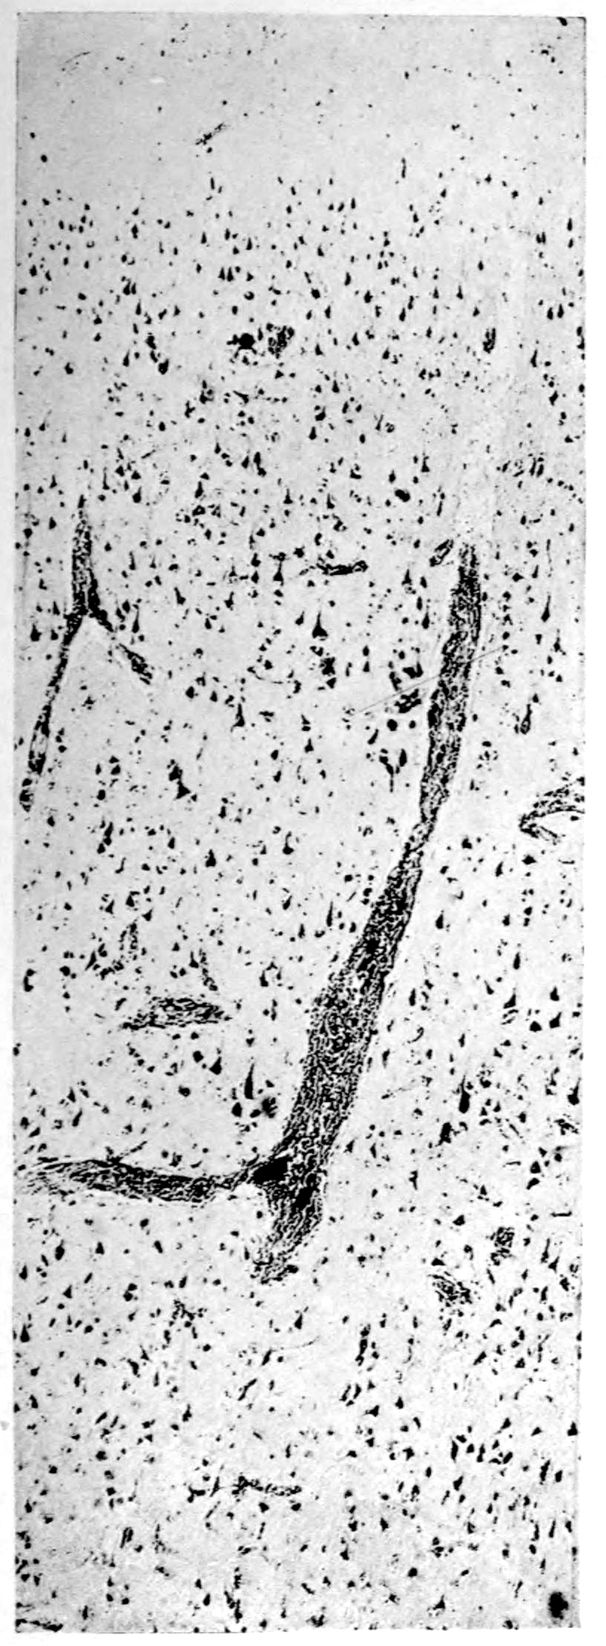
Perivascular exudate (low power) in atrophic cortex from case of general paresis.
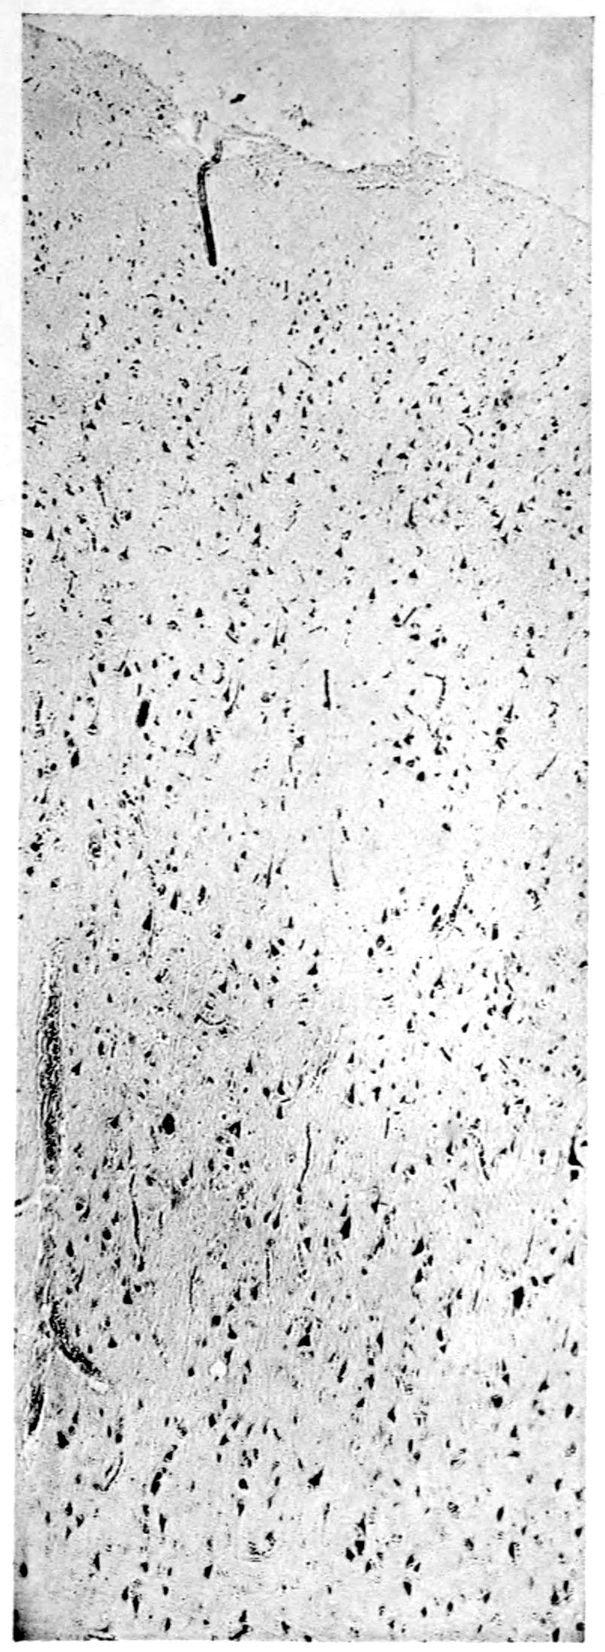
Markedly atrophic cortex, but without local perivascular exudate.
3371. Was the “nervous prostration” at 46 of syphilitic
origin? One cannot give a categorical answer to this
question. The high incidence of shock in the family
suggests poor stock in which a psychoneurosis is not
an unusual phenomenon. The presence of syphilis
might act as a debilitating factor or agent provocateur,
if it were not to cause any demonstrable brain lesion.
As pointed out in the case of Harrison (9), however,
it is not unusual in neurosyphilis to find a history of
symptoms occurring years before the final breakdown
and symptoms frequently not recognized as of neurosyphilitic
nature.
2. Does the fairly long duration of the psychosis (at least
3 years) explain the marked atrophy? Cases having
symptoms even much longer than three years at times
show relatively very little atrophy, so that this factor
in itself cannot be said to explain the tremendous
destruction of tissue.
338
The THERAPY OF NEUROSYPHILIS has to face
not merely variations in the degree of brain
wasting and in the degree of meningitis, but also
variations in the topographical distribution of
lesions. Autopsy.
Case 103. To bring out this point we may instance the
case of Alfred Weed, a victim of Paretic Neurosyphilis,
dying at the age of 48 years after a course of about seven
years. The following is an abstract of the clinical history:
A. W. suffered from lues some 24 years before his death at
Danvers Insane Hospital in 1907. There is no account of
insanity in his family. The patient had been undergoing
mental changes for six years before death. At the age of 42
began to take interest in socialism and spiritualism. Would
become excited at times and was observed to talk to himself.
At times it seemed that he was reacting to visual hallucinations.
After eight months he became depressed and apprehensive
and developed delusions of poisoning.
On admission to the Danvers Insane Hospital in June,
1902, the subject was found to be ataxic, falling in the Romberg
position. Pupils were equal but of pin-point size.
There was tremor of the facial muscles. The knee-jerks were
absent. Speech was ataxic. Memory defective. Depressed.
Thought he was to be punished. Refused to eat.
Later in the year of admission, patient became more
negativistic. He refused to have his clothes brushed. His
answers were slow. Mental arithmetic was correctly but
slowly done. During January, 1903, the patient was apt to
be active and talkative for a time, and then his attitude
would suddenly change to one of silence, resistivement and
untidiness. From time to time he would be querulous
and sulky. In August, 1903, the patient became weaker
and could walk with assistance only. Paralysis developed
in the left facialis region and in the left external rectus.
Pupils were still small, but the left had become smaller than
339the right. Light reaction tests unsatisfactory. Knee-jerks
could not be obtained.
In December, 1903, the patient was untidy and helpless,
lying with his thighs and legs flexed. The limbs were spastic
on passive motion. In 1905, the pain sense of the legs was
found lost and the pupils were small and stiff. The protruded
tongue was deflected to the right. The right labial
fold was more prominent than the left. Knee-jerks remained
absent. Ataxia was extreme.
The Neurological Findings may be summed up as follows:
- 1.
- Ataxia of the legs.
- 2.
- (Probable) Diminished sensibility in the legs.
- 3.
- Pupils small and stiff. Left smaller than the right.
- 4.
- Paralysis of left facialis.
- 5.
- Paralysis of left external rectus.
- 6.
- Tongue protruded to right.
- 7.
- Right elbow jerk greater than left.
- 8.
- Knee-jerks absent.
The cause of death was bronchopneumonia. The walls
and valves of the heart showed a few chronic changes. There
was a marked splenitis and an atrophy of the liver. The
kidneys showed numerous depressed scars. The arch of the
aorta was somewhat sclerotic. The following is a full description
of the head findings which we present by way of
comparison with other cases. Note especially the cerebellar,
dentate, and olivary changes. Note also the fact that palpable
sclerosis is demonstrable over a far larger area than
atrophy, so that we may almost safely conclude that the process
of induration sometimes precedes that of atrophy. One
gets the impression from the extent of visible atrophy and
tangible induration in this case, that a possible therapy would
have not merely to clear the perivascular spaces of cells and
spirochetes, but would also need to arrest the indurating and
wasting process. Nor could any therapy deal effectively with
the superior frontal and upper central atrophy of the cerebrum
of this case, or with the olivary and cerebellar lesions.
Head: Hair thin at vertex. Scalp normal. Calvarium
340thin and dense. Dura mater slightly adherent to calvarium
at vertex. Sinuses normal. Arachnoidal villi well developed.
Pia mater of anterior and central regions contains an
excess of fluid. The pial veins well injected.
The pia mater exhibits one unusual lesion: Faintly yellowish
brown spots of miliary and slightly larger size are scattered
irregularly in clusters over the vertex. These miliary
pial macules are observed especially over the posterior third
of the left superior frontal gyrus (a group of twelve or more).
Two are seen in the pia mater of the right superior frontal
gyrus. One is seen in the upper part of the left post central
gyrus. The upper end of the right postcentral gyrus contains
three macules.
Besides these brownish macules, the pia mater also shows
focal white thickenings which resemble the more frequent
appearances of chronic fibrous leptomeningitis. The white
thickenings are of irregular size but are, as a rule, larger than
the macules above mentioned. They occur, as a rule, over
the sulcal veins and are most frequent in the anterior region.
The vessels at the base are normal. There is no evidence
of pial thickening at the base of the brain. Brain weight,
1265 grams. There is visible atrophy of both superior frontal
gyri and of the upper two-thirds of both central gyri. The
extent of palpable sclerosis surpasses that of visible atrophy.
Palpable increase of consistence is shown by the prefrontal,
orbital (more marked on left side), frontal, central, hippocampal
and occipital regions. The temporal cortex is of
normal or slightly reduced consistence.
Section of the cerebral cortex shows everywhere preservation
of the cortical markings. The sclerosed areas show a
diminution in depth of the cortex, which is more marked in
the left prefrontal region. The white matter of the centrum
semiovale of the prefrontal and occipital regions on both
sides shows an increase of consistence. The cerebellar cortex
also shows variations in consistence. The clivus and lobus
cacuminis and the posterior half of the inferior surfaces of
both cerebellar hemispheres are firmer than normal. The
laminæ of the left clivus are a trifle narrower than those of
the right. There is visible extensive atrophy of the laminæ
341on both sides of a fissure in the middle of the left lobus cacuminis.
In the coördinate portion of the right cacumen there
is a similar process which is less marked. The dentate nuclei
are firm. The olives show an increase of consistence, equal
on both sides. The left olive shows on section a crowding
together of its folds in the middle part of the upper limb.
Spinal cord was not remarkable.
Summary:
- Adhesive pachymeningitis
- Chronic fibrous leptomeningitis
- Miliary pial macules
- Cerebral atrophy
- Cerebral sclerosis
- Cerebellar atrophy and sclerosis
- Bronchopneumonia
- Chronic splenitis
- Nephritis
- Aortitis
342
It is generally recognized that DIFFUSE NEUROSYPHILIS
(“cerebrospinal syphilis”) frequently
is cured through antisyphilitic therapy. Example.
Mental improvement, in one month; recovery from
paralysis, ten months.
Case 104. John Edwards, a man of 28 years, well developed
and nourished, with general enlargement of glands
and skin lesions, came to the hospital in a stuporous condition,
with evidences of a complete hemiplegia.
According to the wife, Edwards had had a chancre of
the lip about a year before, for which he had been treated
with an intravenous injection, presumably of salvarsan, and
also presumably with mercury. The lip lesion had then
disappeared. For a month before admission, Edwards had
had headache and dizziness, for which he was given pills
and drugs. There had also been difficulty with speech and
numbness of the left arm as far up as the elbow, but this
paresthesia had quickly disappeared. The hemiplegia was
of only a few days’ duration. After a feeling of nausea and
vomiting, the patient had fallen with left-sided paralysis.
Afterwards, he had shown mental peculiarities, eventually
becoming noisy, hard to manage, and appropriate for hospital
care.
The physical examination showed a variety of increased
reflexes, including ankle clonus on the left side.
The question might arise whether this case was one of
hemorrhage or thrombosis, and the facts about the onset
of the hemiplegia are inadequate for a decision. However,
at so early an age, the probability of syphilis is large and the
history of labial chancre was quite suggestive. If we may
conclude neurosyphilis, the diagnosis of thrombosis rather
than rupture of blood vessel is likely. The laboratory tests
bore out the diagnosis since the W. R. of serum and fluid
both proved positive; the gold sol reaction was syphilitic;
there were 176 cells per cmm.; there was excess albumin,
and a positive globulin reaction.
343
| NON-PARETIC NEUROSYPHILIS |
| |
| DIFFUSE NEUROSYPHILIS, MENINGOVASCULAR PARENCHYMATOUS, CEREBROSPINAL SYPHILIS |
| |
| CASES SYSTEMATICALLY TREATED |
13 |
| CLINICAL RECOVERY, C.S.F. NEGATIVE |
11 |
| UNIMPROVED |
1 |
| UNIMPROVED, BUT C.S.F. NEGATIVE |
1 |
| |
| Massachusetts Commission on Mental Diseases, |
| November, 1916 |
| |
| Chart 23 |
344The outcome in such a case is dubious. If death does
not occur soon, recovery is not impossible under treatment.
At all events, a considerable improvement is likely.
Edwards was given bi-weekly injections of salvarsan,
intramuscular injections of mercury salicylate, and doses of
potassium iodid, averaging 100 grains, three times a day.
Under this treatment, he slowly recovered and became
mentally clear after a few weeks. The paralysis seemed
complete and permanent. Even after three or four months,
there was absolutely no change in the condition, and Edwards
was quite unable to move either arm or leg. Meanwhile,
the spinal fluid had become practically negative to all tests.
Treatment was somewhat optimistically continued and
was rewarded at the end of ten months with marked improvement
such that the patient was able to stand on the
paralyzed leg and move the arm to a certain degree. This
improvement is still continuing. The spinal fluid and the
serum have remained negative to laboratory tests.
Note: A period of six months is commonly regarded as
that period in which improvement in paralysis is to occur
if there is to be any improvement. There was certainly
not the slightest improvement in the paralysis of this case
before eight or nine months of treatment had elapsed, and
it took ten months to secure the marked improvement
mentioned.
1. What is the significance of the prodromal symptoms?
The headache and dizziness should have been viewed
with great gravity. They are characteristic in Meningovascular
Neurosyphilis.
Moreover in this case there had also been difficulties
with speech and other transient symptoms which
should have called attention far earlier to the possibility
of neurosyphilis.
2. What is the significance of the high cell count: 176 per
cubic millimeter? Such high cell counts are frequent
enough in diffuse neurosyphilis, but low cell counts are
frequent also. But although the high cell count taken
alone is of lesser significance, the fact that the high
345cell count in this case is associated with a “syphilitic”
gold sol reaction is of far greater significance for diagnosis.
These associated findings are characteristic of
meningovascular neurosyphilis.
3. What kind of recovery may be expected in successful
examples of treatment in meningovascular cases?
Recovery with defect. It will be noted that ten
months elapsed before any marked improvement occurred
on the paralyzed side. We could not expect a
complete recovery from this paralysis.
4. Was inadequacy of treatment following the chancre
responsible for the early cerebrospinal involvement?
In this connection one must remember that such neural
involvements occur occasionally even during active
treatment (neurorecidives). The discontinuance of
treatment after a short period, in this case less than
a year, is always a risk to say the least. And this is
true even though the W. R. becomes negative, for
trouble of a neurosyphilitic nature may occur later;
this when both blood and spinal fluid have previously
been found negative. The old rule of following and
treating a syphilitic for several years despite the disappearance
of symptoms is still a good rule.
346
The results of systematic, intensive, intravenous
salvarsan therapy in atypical neurosyphilis (cases
not certainly paretic, tabetic or the common types
of meningovascular neurosyphilis) may be in our
experience as good as the results of treatment in
common meningovascular cases: example.
Case 105. Henri Lepère, a machinist, 48 years of age,
came voluntarily to the Psychopathic Hospital for a gradually
failing memory and inability to work. He had had
indigestion for four years (epigastric distress, nausea, no
vomiting). He was still suffering from epigastric distress
and from headaches. At times he had had difficulty in
walking.
Physically, Lepère looked older than he was; he was very
poorly developed and nourished, and seemed very weak.
There was a slight visceroptosis.
Neurologically, there was considerable speech defect, particularly
well marked in test phrases. The pupils were
contracted and gave the Argyll-Robertson reaction. Neurologically
there were no other signs.
Mentally, there was a depression with worry; but it was
a question whether these phenomena were not entirely
natural. The special complaint was of failing memory.
The Argyll-Robertson pupil also prima facie signifies
neurosyphilis. Lepère, in fact, admitted syphilitic infection
at 23. The gastric symptoms at once suggested tabes. The
knee-jerks and ankle-jerks were, to be sure, preserved; however,
this is not very unusual in tabes. The amnesia and
aphasia naturally suggested paresis. Without resort to
laboratory findings, accordingly, the diagnosis of taboparetic
neurosyphilis (“taboparesis”) was suggested.
347
| EFFECT OF EARLY TREATMENT ON THE DEVELOPMENT OF NEUROSYPHILIS |
| |
| TOTAL CASES |
|
|
4134 |
| DEVELOPED GENERAL PARESIS |
|
|
198 = 4.8% |
| DEVELOPED TABES DORSALIS |
|
|
113 = 2.7% |
| DEVELOPED CEREBROSPINAL SYPHILIS |
|
|
132 = 3.2% |
| |
|
|
|
| |
|
|
443 = 10.5% |
| |
| EFFECT OF TREATMENT |
|
None |
1 course |
Repeated energetic |
| NUMBER OF CASES |
100 |
134 |
924 |
| DEVELOPED G.P. |
25 = 25% |
31 = 23.1% |
30 = 3.2% |
| DEVELOPED TABES |
11 = 11% |
16 = 11.9% |
25 = 2.7% |
| DEVELOPED C.S.S. |
3 = 3% |
21 = 15.6% |
71 = 7.6% |
| |
|
|
|
|
Poorly treated
1880–84 |
|
Better treated
1895–99 |
| NUMBER OF CASES |
617 |
|
1139 |
| DEVELOPED G.P. |
60 = 9.7% |
|
37 = 3.2% |
| DEVELOPED TABES |
22 = 3.5% |
|
16 = 1.4% |
| DEVELOPED C.S.S. |
15 = 2.4% |
|
28 = 2.4% |
| |
| MATTAUSCHEK AND PILCZ |
| |
| Chart 24 |
348The serum W. R. proved positive, but the spinal fluid W. R.
very slightly so (yielding only moderate reaction with 1 cc.,
0.7 and 0.5 cc., and a negative reaction with 0.3 and 0.1 cc.).
Globulin was moderate, and albumin was found in only
moderate excess. There were 21 cells per cmm. in the spinal
fluid. The gold sol reaction was that which we regard as
typical of syphilis or tabes. If we were to rely upon the
weakness of the fluid W. R. and the nature of the gold sol
reaction, we should be inclined to favor the diagnosis of
Diffuse Neurosyphilis (“cerebrospinal syphilis”) rather
than resort to the diagnosis of paretic neurosyphilis.
Salvarsan treatment was attended by the rapid disappearance
of headaches and gastric symptoms and by a rapid
gain in weight and feeling of well-being. Salvarsan was
continued twice a week for two months, whereupon Lepère
returned to work. He has been successfully at work now for
seven months without return of symptoms. Four months
after beginning of treatment, the spinal fluid was examined
and found entirely negative. Nevertheless, the serum W. R.
has remained positive despite eight months of salvarsan treatment.
1. What is the meaning of the titrations in the spinal fluid
Wassermann reaction? When Plaut originally applied
the Wassermann reaction to spinal fluids, he used 0.2 of
a cc. of spinal fluid. With this amount of fluid he found
that cases of general paresis gave a positive reaction
in about 100% of the cases while this positive reaction
was only given by 40 to 60% of the cases of cerebrospinal
syphilis and tabes dorsalis, hence he promulgated
a differential point that a negative reaction in
spinal fluid indicated that the case was not general
paresis. Hauptmann later showed that if 1 cc. of spinal
fluid were used, a positive reaction would occur in
practically 100% of the cases of general paresis, cerebrospinal
syphilis and tabes. Therefore, at present,
we use the different titers of spinal fluid from which we
draw the following conclusions: If the reaction in the
untreated case is negative with 0.1 and 0.3 of a cc. and
positive with the 0.5, 0.7 and 1 cc. dilutions as in the
case of Lepère, we are probably dealing with non-paretic
neurosyphilis. With this method of titration
we are also better able to watch the progress of treatment
as the dilutions of 0.1 and 0.3 cc. become negative
first.
3492. How soon can one expect improvement after commencement
of salvarsan therapy in cases of diffuse neurosyphilis?
The time relation of results in treatment varies
with each individual case. In the case of Lepère
gastric symptoms that had been present for a number
of months disappeared as if by magic after the first
injection of salvarsan. As a rule, it is true that the
more acute the symptoms the quicker their disappearance
but this does not hold for all cases, as in this
particular instance the long-standing symptoms disappeared
very rapidly. The symptoms often disappear
very much more rapidly than the laboratory, tests
change.
3. How can the mental symptoms (depression and failing
memory) of which patient complained be explained?
In the first place, as has been stated, it is doubtful if
these are more than subjective and the result of the
patient’s feeling of discomfort and pain. However, it
is also possible that there may be intracranial involvement
of the meninges or of the brain itself. And, if
such were the case, the improvement might be the
result of the treatment.
350
The Argyll-Robertson pupil should not be used as
a basis for a necessarily bad prognosis if treatment
can be given.
Case 106. Frederick Stone was a business man of large
interests. He had been in the hands of physicians for several
years for a variety of disorders such as renal, respiratory,
cardiovascular, and so on. No suspicion of syphilis had
apparently been uttered by the physicians despite the fact
that Mr. Stone readily stated that he had had a chancre
thirty years before, and that he had received several years’
treatment of mercury and potassium iodid by mouth.
It appeared that a few years ago he had begun to have
trouble with his nose, which was cauterized and operatively
interfered with without satisfactory results. This nasal
condition had later been diagnosticated as gummatous, and
had improved considerably under a mild antisyphilitic
treatment. However, this nasal condition had been considered
and treated quite separately from the remainder of
Mr. Stone’s troubles.
What brought him to attention was a sudden diplopia with
ptosis. There was a paralysis of the external rectus of the
left eye, as well as a drooping of the lid on this side. The
left eye was much inflamed. The diplopia greatly bothered
the patient, and there was also considerable pain in the left
frontal region, confined chiefly to the distribution of the first
division of the trigeminal nerve. According to the patient
this headache was periodic. There was considerable tenderness
to pinprick over the area and a diminution of sensory
discrimination of fine touch. Both the pupils failed to react
to light.
The remainder of the neurological symptomatic examination
was surprisingly clear of disorder, nor was there anything
in the history suggestive of tabes. There was ozena as
well as evidence of the operative work upon nares and throat.
Possibly the arteries were slightly hardened; blood pressure
was 165 systolic. There was a large trace of albumin, and
there were numerous hyalin casts in the urine.
351
| PARETIC NEUROSYPHILIS |
| |
| (GENERAL PARESIS) |
| |
| Cases systematically treated |
|
50 |
|
|
| |
| CLINICAL REMISSIONS |
|
34 |
|
68% |
| |
C.S.F. ALTERED TO NEGATIVE |
4 |
|
8% |
|
| |
C.S.F. ALTERED TO WEAKER |
16 |
|
32% |
|
| |
C.S.F. UNALTERED |
14 |
|
28% |
|
| |
| CLINICALLY UNIMPROVED |
|
16 |
|
32% |
| |
C.S.F. WEAKER |
7 |
|
14% |
|
| |
C.S.F. UNALTERED |
9 |
|
18% |
|
| |
| Massachusetts Commission on Mental Diseases |
| November, 1916 |
| |
| Chart 25 |
352Mentally, there was a degree of depression and worry
hardly out of keeping with the general situation. Despite
the preservation of memory, Mr. Stone failed to do rather
simple arithmetical calculations; this was the more remarkable
as in his business he had to handle figures a great
deal and had been doing so until recently. There was a
slight tremor in his writing, as well as a certain difficulty in
enunciating test phrases. Insomnia, irritability, and a feeling
of nervousness and of being tired out, completed the
picture.
A suggestion for diagnosis would be classically offered
by the Argyll-Robertson pupils. Should not a patient with
the Argyll-Robertson pupils have either tabes or paresis?
However, in favor of tabes, besides the pupil, are to be counted
merely the troubles with the eyes. In the direction of paresis
we have to consider speech defect, to say nothing of less definite
symptoms such as insomnia and increased irritability.
We are inclined to think, however, that the disease in this
case is meningovascular. This diagnosis is suggested by the
cranial nerve palsies and by the headache. Headache is
much more rarely a phenomenon in the paretic type of neurosyphilis
than in the meningovascular type.
In point of fact, the spinal fluid phenomena bore out the
diagnosis of Meningovascular Neurosyphilis inasmuch as
the globulin, albumin, cellular content, gold sol, and W. R.’s
were all weakly positive.
1. How far can we regard the cardiorenal defects as syphilitic?
Perhaps we may do so on the general principle
of parsimony in scientific interpretation.
The diagnostic lumbar puncture led to an extremely
severe exacerbation of the pains on the left side of the head.
In fact, these pains could not be held in check by the exhibition
of pyramidon. Mr. Stone regarded the pain as due
to the lumbar puncture. However, there was no improvement
in the pain in the prone position,—a feature characteristic
of lumbar puncture pains. Upon administration of
353salvarsan, this local pain rapidly disappeared. In fact, there
was a startling improvement; the ocular palsies disappeared
in a few weeks, although these palsies had been present
for several months before the administration of salvarsan.
The blood pressure was reduced; the urine became negative.
Perhaps the most startling feature of all (although of this we
are not sure) was that the patient states he was accepted by
a life insurance company although he had been twice refused
previously.
Note in this case the 30–year interval between infection
and generalized neurosyphilitic involvement. Note also
the amenability of the process despite this duration. We
are perhaps entitled also to note that a neurological examination
careful enough to detect an Argyll-Robertson pupil
should have been made by a number of examiners long
before the particular crisis which we have sketched. It is
also permissible to note that the rhinological work should not
have been carried out independently of all other medical
work.
2. What are the untoward results of lumbar puncture?
It is true that there is always a possibility of setting up
a septic meningitis by lumbar puncture, but this is a
very remote possibility and with any reasonable care
it is not to be considered. Lumbar puncture also has
a considerable danger in cases of increased intracranial
pressure. In cases of brain tumor where the tumor is
located in the posterior fossa, sudden death may occur
from withdrawal of spinal fluid. This is supposed to
be due to the medulla being pressed down into the
foramen magnum and causing paralysis of respiration.
Therefore lumbar puncture should never be performed
except with the greatest caution in a case in which
brain tumor is suspected.
However, aside from these remote serious consequences
which play very little rôle in the ordinary procedure
of lumbar puncture, certain unpleasant symptoms
do frequently arise. These symptoms are chiefly
headache and nausea, but, however, may go as far as
vomiting. These symptoms occur almost entirely in
the cases in which there is no abnormal condition producing
increased spinal fluid pressure. Such unpleasant
354symptoms may last as long as four or five days; as a
rule, however, last only for a period of a day or two.
3. What is the treatment of discomfort following lumbar
puncture? It is a rule well worth observing that the
patient after lumbar puncture should remain flat on his
back without a pillow for 24 hours in order to avoid any
unpleasant symptoms. If any symptoms do occur,
it will be almost certainly when the patient arises, and
in nearly every instance they will be overcome if the
patient again assumes the prone position. Raising
the foot of the bed so as to lower the head also helps.
Veronal or bromides may be given but as a rule are not
very satisfactory.
4. How permanent is the improvement obtained in the
case of Mr. Stone likely to be? As a matter of fact,
the patient discontinued treatment as soon as he felt
well again, but after two months the pain returned to
be again quickly dispelled by salvarsan. This improvement
must be considered as only temporary.
Under continued treatment there may be no further
relapse. There is, however, evidence that much damage
has been done to the body by the spirochetes,
much of which is irreparable. It is even possible that
further disintegration might occur even while undergoing
treatment. Still treatment offers much in such
a case and is to be highly recommended.
355
In DIFFUSE NEUROSYPHILIS, rendering the
spinal fluid negative by treatment may mean
neither cure nor disappearance of symptoms.
Case 107. Greta Meyer, a widow, 51 years of age, came
voluntarily to the hospital, seeking medical aid for a marked
depression. She was also suffering from a right hemiplegia.
It appeared, according to Mrs. Meyer, that she was married
at 16, and lived with her husband until 29, whereupon she
left him on account of his alcoholism, his abuse of her, and
the discovery through his physician that he was suffering from
venereal disease. She had had two healthy children and
there never had been miscarriages or stillbirths. Six years
after the separation, namely at 35 years of age, and 16 years
before resort to the Psychopathic Hospital, Mrs. Meyer
developed certain red areas on her hand, and learned at a
hospital that these were due to syphilis. She kept up
treatment for these lesions for a year, until she seemed perfectly
well.
She had, in fact, remained perfectly well for some 14 years,
until at 49, a small tumor had appeared on the right side of
the forehead, near the hair line. This tumor was firm and
not sore. Medical treatment reduced it, leaving, however,
a depression in the bone. One day, about a month after the
appearance of the tumor, the patient lay down for a nap,
and upon awaking found she could only with difficulty move
her right arm and leg. Her face was not affected; she was
not in pain; and there was no disorder of speech. In a few
days she got much better and she had been improving
for some time past through the administration of further
medicine.
However, since the onset of the hemiplegia Mrs. Meyer
had been very despondent. There had been ups and downs
but she had rarely felt well. The depression was a mild one
and in point of fact may perhaps be regarded as non-psychopathic,
since at her age with her disability, there might well be
a degree of sadness and unhappiness concerning the future.
Mentally, there was no other disorder of note, and in particular
no disorder of memory.
356
I. BY MOUTH.
1. MERCURY
2. IODIDES
3. ARSENIC
II. INTRAMUSCULAR INJECTIONS
1. MERCURY
2. SALVARSAN, NEOSALVARSAN, OTHER ARSENIC PREPARATIONS
3. SODIUM NUCLEINATE
4. ANTIMONY
III. INTRAVENOUS
1. MERCURY
2. MERCURIALIZED SERUM
3. SALVARSAN, NEOSALVARSAN, ARSENIC
4. IODIDES
IV. SPINAL INTRADURAL
1. SALVARSANIZED SERUM (In Vivo—Swift-Ellis)
2. SALVARSANIZED SERUM (In Vitro—Marinesco-Ogilvie)
3. MERCURIALIZED SERUM (Byrnes)
V. CEREBRAL SUBDURAL AND INTRAVENTRICULAR
1. SALVARSANIZED SERUM (In Vivo)
2. SALVARSANIZED SERUM (In Vitro)
3. MERCURIALIZED SERUM
Chart 26
357Physically, the patient showed a right-sided hemiplegia
with excessive right knee-jerk, but without Babinski or other
abnormal reflex phenomena. The extraocular movements
were somewhat restricted in range but there was neither
strabismus nor nystagmus.
The question arose whether the hemiplegia was of hemorrhagic
or thrombotic origin. After all, at 51 years, hemiplegia
is rather unlikely to be of a non-syphilitic arteriosclerotic
origin; moreover, we had a clear history of syphilis. The
serum W. R. proved positive as well as the spinal fluid W. R.
The finding of 77 cells per cmm., excess albumin, and positive
globulin test, taken in connection with the entire picture
seems to warrant a diagnosis of Cerebrospinal Syphilis.
If we proceed on statistical grounds, it might be regarded as
more probable that the hemiplegia is Thrombotic in origin
rather than hemorrhagic. It appears that syphilitic cerebral
thrombosis rather characteristically occurs without preliminary
symptoms, despite the fact that many cases do show
headache, dizziness, and restlessness as prodromal symptoms.
1. What is the treatment indicated in the case of Mrs.
Meyer?
It would appear that little or nothing can be done
for the hemiplegia unless the claims of Franz with
respect to reëstablishment of a degree of function in
certain hemiplegics are substantiated. However, the
indication of meningitic process as shown by the spinal
fluid, suggests that the case is not a purely vascular one
but may be regarded as meningovascular. (Possibly,
also, we should regard the left frontal depression and
scar as indicative of a non-parenchymatous and non-vascular
process.) Accordingly, antisyphilitic treatment
should be theoretically of some value.
In point of fact, the patient was given injections of
mercury salicylate, mercury by mouth, and potassium
iodid. Her psychopathic depression under this treatment,
supported by proper hygiene and rest, diminished.
However, six months later, the patient slipped
on a wet floor and fell. Though the impact seemed
358hardly sufficient to cause a fracture, the pelvis was
somewhat severely fractured. Very probably there
was a syphilitic rarefaction of the bone. Six months
later the patient’s depression was still in evidence,
though somewhat less than upon admission. The
blood serum remained positive but the spinal fluid had
become entirely negative, both in respect to the W. R.
and in respect to the other findings.
2. How may one explain the continuance of the depression
after the spinal fluid had become entirely negative under
treatment? It may be that while the active process
had been stopped, as seems probable from the negative
spinal fluid, that a permanent destruction of brain
tissue may account for the depression. We recognize
this readily in instances of vascular disturbance where
(as also in this case) the active process being stopped, a
residual defect remains.
3. Should treatment have been discontinued on reduction of
the gumma? It cannot be too often emphasized that
the disappearance of symptoms in cases of syphilis can
not be considered as evidence of cure. The neurologist
and psychiatrist see only too often cases of neurosyphilis
occurring in patients who have been declared
cured at some time previous because the symptoms then
present had cleared up and remain in abeyance for
years.
359
Contrary to various warnings, arteriosclerosis by
no means absolutely contraindicates intensive
salvarsan therapy.
Case 108. Victor Friedberg, 42 years of age, gave the following
history. He acquired syphilis at 22 years. He had
“adequate” medical treatment for two years with inunctions
of mercury and mercury by mouth and potassium iodid.
The only secondary symptoms were skin lesions of the legs;
these disappeared upon treatment. Married, Friedberg has
one child, apparently normal. There had been no miscarriages
or stillbirths.
At about 34 years, there began to be shooting pains in the
legs, occurring at first about once in three months, but later
much more frequently. These pains were severe, lightning
in character, lasting several days at a time, at which period
his head would feel heavy; but there were no disturbances,
crises, or difficulty in locomotion.
At 36 years of age, Friedberg waked up with pain one night,
and found he was unable to move his left leg or hand, and he
felt his mouth drawn to the left. Upon trying to get out of
bed, he fell to the floor. In five hours, however, he was
entirely recovered, able to get up and walk about, and to use
his left arm quite normally. He went to sleep, but upon
waking up after an hour, discovered that his left side was
again paralyzed. After two weeks in a hospital, he was able
to walk with a crutch. The arm remained helpless for about
a year. Both arm and leg improved slowly for two years,
after which time his condition had remained stationary.
For four years past, there had been no more pain, but at 42—about
two years before admission—the pains returned in his
legs, back, and side. At that time he received four injections
of salvarsan, mercury tablets, and potassium iodid. Three
weeks before admission to the hospital, Friedberg again
began having headaches, very much worse than formerly.
At first these headaches were frontal, then occipital, and there
360was a feeling as if something were growling inside of the head.
There was a feeling of pressure in front on the head and at the
base of the nose.
Physically, Friedberg appeared somewhat older than his
assigned age. There was a degree of general peripheral
arteriosclerosis, but in general the physical examination was
negative. Neurologically, there was a left hemiplegia with
appropriate increase of the reflexes on that side, spasticity,
Babinski reflex, and an Oppenheim; the pupils reacted properly;
there was no Romberg reaction.
Mentally, Friedberg was entirely negative.
The W. R. of the blood serum was doubtful, as was that of
the spinal fluid. There were but two cells per cmm. and there
was neither globulin nor excess albumin in the spinal fluid.
The differential diagnosis might lie between cerebral
hemorrhage and syphilitic thrombosis. Thrombosis is much
more common as a result of syphilis than is hemorrhage.
The occurrence of the thrombosis during sleep without premonitory
symptoms is also characteristic in syphilis. Possibly
there was a low-grade spinal meningitis at the bottom of
the lancinating pains. Whether the headache is an arteriosclerotic
effect or due to a meningitis not shown in the
cerebrospinal fluid is doubtful. However, the absence of inflammatory
products in the cerebrospinal fluid rather indicates
that the headache is of arteriosclerotic origin. Autopsies,
however, warn us that we may have a localized meningitis
in various parts of the cranial cavity without the determination
of any inflammatory products in the spinal fluid.
1. How shall we explain the doubtful (slightly positive)
W. R. in the spinal fluid if the case is one of Vascular
Brain Syphilis? The finding is not unusual in these
cases. The W. R. producing body is recognized to be
of a separate nature from the globulin and albumin
bodies, and is probably also separate from the gold sol
reaction producing bodies.
Treatment: The theory of treatment is that any spirochetes
that may be still active in the body should be destroyed.
Accordingly, although salvarsan can certainly have
361no effect in reproducing nerve tissue, it nevertheless seems
indicated. It is frequently stated, however, that salvarsan
is dangerous in cases of this group. We have not found this
statement correct. In this case, there was a symptomatic
improvement, as far as pain and discomfort went, under
salvarsan and iodids.
2. What precautions should be taken in intensive salvarsan
treatment of syphilitic arteriosclerosis? Treatment
should be begun with very small doses of salvarsan,
that is, about 0.1 of a gram and then the amount slowly
increased. The injection should be given slowly so as
not to put too great a load upon the cardiovascular
system.
3. What rôle does the mental attitude of the patient play in
a case like that of Friedberg? It was quite evident
that Friedberg was neurotic and that he had a syphilophobia.
Consequently some of the symptomatic improvement
may have been more results of assurances
offered by the physician and knowledge that he was
being treated, than results of salvarsan. In some cases
mental anguish suffered by the patient is of more
importance than the actual symptoms of the disease
and this point must be always borne in mind in handling
syphilitic patients.
362
Symptoms of intracranial pressure cured by antisyphilitic
treatment.
Case 109. Mrs. Annie Rivers, a housewife 36 years of age,
sought advice and treatment for severe convulsions which
she had had during a period of several weeks. She left the
hospital before being properly examined, and had several
more convulsions, after which she was brought back in a state
of marked confusion. The confusion shortly disappeared
almost completely, and a good history was obtained.
It appears that the patient led a normal life and had had
six children, the last of whom was born about four months
before her coming to the hospital. The first symptoms
appeared about a month after the birth of the child, when,
one afternoon, Mrs. Rivers suddenly fell unconscious while
ironing. She remained unconscious for nearly three hours.
During this attack there were no convulsive movements or
tongue-biting; and after the spell, she felt neither lame nor
sore, but merely tired. This was Mrs. Rivers’ statement;
but her daughter stated that the patient really did have convulsive
movements. A week later came a second convulsion,
followed by daze and stupor. This second attack
lasted two hours.
About a week before entrance, the patient had remained
in bed on account of dull grinding pain in the left side of the
head, below the ear, and upon this day the patient vomited
twice. In addition to the dull grinding pain, there were
pains referred to the ear itself and to the left side of the head,
especially over the left eye; there were no pains on the right
side of the head. The next day the patient was better, but
the day thereafter again remained in bed. The only other
symptoms were cold feelings at times and bright spots in the
field of vision.
No mental symptoms were observed in Mrs. Rivers except
a bit of depression after her hasty retreat from the hospital
the first time. Upon her second admission, however, after
a week or ten days’ residence, apathy developed together
with considerable amnesia for the same facts she had quite
readily remembered a few days previously. Along with the
apathy and amnesia developed considerable headache; and
there were attacks of vomiting.
363
UNTOWARD SYMPTOMS OF THERAPEUTIC AGENTS
A. SALVARSAN
CYANOSIS MALAISE
RAPID PULSE
PERSPIRATION
RESPIRATORY DIFFICULTIES
FEVER
NAUSEA, VOMITING, DIARRHOEA
DERMATOSES
EDEMA
KIDNEY IRRITATION
LIVER IRRITATION
INTENSIFICATION OF SYMPTOMS
COLLAPSE
SALIVATION
FETID BREATH
EXCESS FLOW OF SALIVA
TENDERNESS OF TEETH—LOOSENING AND FALLING OUT
SPONGY GUMS—EROSION
METALLIC TASTE
NECROSIS OF BONES OF JAW
SORENESS OF PARETIC AND MAXILLARY GLANDS
SWELLING AND EROSION OF TONGUE AND MUCOUS MEMBRANES
GASTRO-INTESTINAL SYMPTOMS
ANEMIA
PAIN IN JOINTS
NEPHRITIS
SKIN LESIONS
METALLIC TASTE
SALIVATION
CORYZA
URTICARIA (EVEN TO GRADE OF ANGIONEUROTIC EDEMA)
PAINS
CONSTIPATION
INVOLVEMENT OF JOINTS
FEVER
SOFTENING AND BLEEDING OF GUMS
EROSION OF MUCOUS MEMBRANES
GASTRO-INTESTINAL SYMPTOMS
ANOREXIA
WEAKNESS
Chart 27
364On the physical side, it is interesting to note that the ophthalmoscopic
examination upon Mrs. Rivers’ first admission
to the hospital was entirely negative, whereas a week later,
pronounced difficulty with vision appeared so that in a few
days she was able to make out only very large type. The
fundi now showed hazy and indistinct disc outlines, with
small yellowish areas of fatty degeneration above the disc,
reduction of arterial calibre, and dilated and somewhat tortuous
veins (no projection of papillæ), so that the ophthalmological
diagnosis was chronic neuritis.
The physical examination otherwise was mostly negative.
The skin presented irregular areas covered with silvery scales
over the arms and chest, back, abdomen, and legs (the patient
had had psoriasis several years before). Both pupils reacted
to light and distance, though the right was slightly larger
than the left and somewhat irregular. There was a slight
tremor of the tongue and extended fingers. The reflexes
were active, especially the knee-jerks; no abdominal reflexes
could be obtained. The serum W. R. was positive, but the
spinal fluid W. R. was negative. The spinal fluid showed
but 3 cells per cmm., but there was a positive globulin test
and an excess of albumin.
Diagnosis: After the symptoms had fully developed, it
became clear from the optic neuritis, headaches, and vomiting
that a condition of intracranial pressure existed. In view
of the positive serum W. R., it is natural to conceive that the
agent producing the intracranial pressure was a gumma.
It is, of course, possible that a marked degree of meningitis
might be so localized as to produce the same symptoms. The
diagnostician would crave a pleocytosis of the spinal fluid
if a diagnosis of meningitis is to be made; and there was no
such pleocytosis. On the whole, we do not feel that it is
possible to make a diagnosis either of Meningitis or of
Gumma.
365Treatment: Treatment, however, caused a disappearance
of all symptoms. The treatment consisted of but one injection
of 0.3 gram of salvarsan, followed by a few injections of
mercury; whereupon Mrs. Rivers became much brighter,
recovered her vision, lost her headaches, ceased to have convulsions
or vomiting spells.
1. Is salvarsan contraindicated in cases with involvement of
the optic or auditory nerves? Such a contraindication
exists according to prevailing opinion. In this particular
case, a hemorrhagic retinitis occurred after the
injection of salvarsan, but this retinitis disappeared
along with the other symptoms. On the whole we
believe that in many cases of optic or auditory nerve
involvement salvarsan should be used. However, one
should never lose sight of the possibility of untoward
results and should advise such treatment only when
other treatment seems inefficient.
366
TABETIC NEUROSYPHILIS (“tabes dorsalis”)
may show very marked improvement as a result
of intraspinous therapy.
Case 110. Mr. McKenzie[18] was a retired merchant of 42
years whose complaint was that he tired very easily, could not
make his legs go where he wished, was unsteady and felt a
numbness in his legs. These symptoms had been in progress
for a few months only when the examination was made.
This disclosed Argyll-Robertson pupils, absent knee-jerks
and ankle-jerks, Romberg sign, unsteady gait, moderate
ataxia and dysmetria. The W. R. was negative in the
blood serum but positive in the spinal fluid with 0.2 cc., and
there were 107 cells per cmm. With the symptoms and signs
it was therefore easy to make the diagnosis of Tabetic
Neurosyphilis (“tabes dorsalis”).
The patient was given five intraspinous injections of mercuric
chloride in blood serum (mercurialized serum) according
to the method of Byrnes. The dose was 0.001 gm. of mercury.
Two weeks after the first injection the cell count was 58 cells
per cmm., the Wassermann was positive only with 0.4 cc.
After the fourth injection there were but 18 cells and the
Wassermann reaction was negative even with 1½ cc. of spinal
fluids. The symptoms had improved to such a degree that the
patient had no complaint whatsoever and considered himself
cured.
1. What are the unpleasant results of intraspinous therapy?
Frequently there is an exacerbation of symptoms and
pain may be quite severe after intraspinous injections.
This, however, lasts only a short period, that is, as a
rule less than 24 hours. There may be other symptoms
of cord irritation as retention of urine or lack of
sphincter control. A rise of temperature is not unusual.
367
Treatment may alter the W. R. to negative in
blood and spinal fluid in TABES DORSALIS.
Case 111. Ivan Rokicki was a baker, 43 years of age, who
came complaining of exceedingly severe attacks of abdominal
pain with vomiting. He described these attacks as having
occurred periodically for a number of years, lasting sometimes
as long as a week, during which time Rokicki could not eat or
get relief short of large doses of morphine.
Upon his arrival, Rokicki was seen in one of his attacks;
he was curled up with excruciating pain, and the abdomen
was rigid, though it was impossible to produce additional
pain by external pressure. There was spasmodic vomiting,
frequently followed by slight relief from the pain, which
however shortly recurred and caused the patient to cry out in
his suffering. The condition was controlled by opiates but
lasted a full week. The leucocytes remained normal and
there was no rise of temperature. The attack ceased spontaneously.
Save for the pain, Rokicki’s mental examination proved
entirely negative. Physically, Rokicki was fairly well developed
and nourished. His pupils were slightly irregular: the
left markedly larger than the right; both pupils failed to
react to light, and the left pupil also failed to react in accommodation.
There were no other reflex disorders evident
to systematic examination, nor was there sensory disturbance
or speech defect. The heart seemed somewhat enlarged
but there were no murmurs; blood pressure: systolic
150; diastolic 110.
The correct symptomatic diagnosis in Rokicki’s case proved
to be gastric crises, and this diagnosis must perforce be the
first to entertain in view of the chronicity, the periodicity,
the non-relation to diet, and the spontaneous cessation of
the seizures. The observation of Argyll-Robertson pupils
was naturally held to substantiate the diagnosis of Tabes
Dorsalis.
368The possibility of abdominal inflammation could be shortly
dismissed on account of the absence of tenderness (the rigidity
in this case was not accompanied by tenderness), fever,
and other characteristic signs. There was no diarrhoea, such
as is found in lead colic, and there was no other sign of
plumbism. Jaundice was absent and there was no special
radiation of pain from the abdomen. One had to think of
gastric ulcer and hyperchlorhydria, and possibly malaria or
gastroenteritis.
The pupillary reactions pointed to a syphilitic condition
despite the fact that the lack of reaction to accommodation
(over and above the Argyll-Robertson phenomenon) in the
right pupil is not entirely typical. Accordingly, although
there was no areflexia, Romberg sign, or ataxia, resort was
had to the W. R. This however proved negative, in blood
and spinal fluid; nor was there any globulin or excess albumin;
there were 5 cells to the cmm., in the spinal fluid.
We are left, accordingly, with characteristic gastric crises;
Argyll-Robertson pupils, slightly irregular; and a somewhat
enlarged heart.
Upon investigation, it appeared, however, that a year
before the attack above described, the patient had been
examined and both blood and spinal fluid found positive to
the W. R. At that time, treatment, consisting of intravenous
injections of salvarsan and intraspinous injections of salvarsanized
serum (Swift-Ellis), had been instituted. Whereupon
the laboratory tests had become negative, as above stated,
and there had been no alleviation of the symptoms.
1. How can Rokicki’s normal deep leg reflexes be explained?
The abolition of the deep reflexes is of course due to
lesions properly localized. It is probable that this
particular case of tabes dorsalis is more truly “dorsal”
than most cases; for most cases exhibit lesions involving
regions lower than the dorsal. Both in these dorsal
cases and in certain rare cases of cervical tabes, the
deep leg reflexes are preserved. (See cases Green (30)
and Halleck (31).)
2. What is the mechanism by which a characteristic gastric
crisis is produced? The mechanism is unknown. Some
endeavors have been made to meet gastric crises by
369surgery of the posterior roots, on the assumption that
the irritation causing the pain was located either in
the posterior ganglion or in the passage of the nerve
through the meninges. In only a few instances, however,
has the result been what was desired. In many
instances the gastric crises and pain continued uninterrupted
and in addition came discomfort due to the lack
of sensation in the part supplied by the severed nerve.
At present this treatment is seldom carried out.
3. Should antisyphilitic treatment be continued in such a
case? As far as our present knowledge of syphilis goes
one would hesitate to suggest further antisyphilitic
treatment, feeling that the active process had been entirely
stopped as suggested by the absence of any positive
findings either in the blood serum or in the spinal
fluid. We should perhaps conclude that there was no
more activity in this case and that the crises were due to
the changes that had already taken place in the nerve
tissue and which could no longer be changed.
370
The literature is in doubt concerning (in fact is
preponderantly against) the success of treatment
in PARETIC NEUROSYPHILIS (“general paresis”).
Our experience has yielded a number of
apparently successful results through systematic
intensive intravenous salvarsan therapy. Example.
Case 112. Albert Forest had always been a successful
salesman, but in the middle of March, in his 46th year, he
was arrested for grabbing a purse from a woman in front of
a theatre and running down the street with it. In court,
Forest acted strangely and he was sent to the Psychopathic
Hospital for observation. Upon investigation, it appeared
that his wife thought he had been showing mental changes
for about a year. For example, he would embrace his wife
on a street car, or refuse to pay her fare. He once attempted
to hit his son on the head with a red-hot poker. Now and
then he would become sleepy and stupid. He looked rather
older than his age and had a coarse tremor of the hands.
Otherwise, no change could be detected in the physical
examination, either neurologically or otherwise. As for the
manual tremor, Forest’s wife gave a history of considerable
alcoholic indulgence on his part.
For several days, nothing abnormal could be detected in
the man; and in particular, his memory for both remote and
recent events was very good and his knowledge of current
events was good. Simple arithmetic was easy to him.
One evening his temperature was found to be 104° F. and
no cause could be discerned for this. The next morning,
Forest was discovered in a stupor, with a complete right
hemiplegia. The Babinski reflex, the Oppenheim reflex, and
ankle clonus had appeared on the right side, and the right
arm was spastic.
However, all symptoms of this paralysis had disappeared
by four o’clock in the afternoon, and the paralytic phenomena
were replaced with violence. The patient fought with the
371attendants and for some time remained extremely difficult to
manage, being confused and subject to outbreaks of violence
with destruction of furniture and other property about the
ward.
Diagnosis. At first we were naturally inclined to dismiss
the case with a diagnosis of alcoholism. The transient
hemiplegia at once raised a considerable question of brain
syphilis or of brain tumor.
The W. R. of the serum was doubtful. The spinal fluid
yielded, besides marked excess of albumin and much globulin,
also a “paretic” gold sol reaction and 75 cells per cmm.
The W. R. was positive.
Treatment. The patient was given injections of salvarsan,
0.6 gram, twice a week, with potassium iodid. After
a few weeks improvement followed, and after several months
all the laboratory tests became negative, the patient was
apparently perfectly normal mentally and was discharged
from the hospital, and has remained well for 18 months
without further treatment. The serum W. R. has continued
to be negative.
1. What is the significance of the so-called “doubtful”
W. R.? Where there is not a complete uniformity the
results of the strong and weak antigens (see appendix
on technique of Wassermann reaction) the result is
reported as doubtful. In the majority of instances
repetitions will give a strong positive reaction.
2. Is the case of Forest to be regarded as one of general
paresis? Sometimes such cases are termed in the
literature syphilitic pseudoparesis (see case Burkhardt
(58)). The differential diagnosis of this group is
entirely therapeutic. There are, unhappily, no laboratory
tests which will suffice in the present stage of
knowledge to differentiate a case of so-called pseudoparesis
from general paresis. We are inclined to term
the case one of General Paresis, with recovery, or,
at all events, with remission.
372
The literature is in doubt concerning (in fact is
preponderantly against) the success of treatment
in PARETIC NEUROSYPHILIS (“general paresis”).
Our experience has yielded a number of
apparently successful results through systematic
intensive intravenous salvarsan therapy. Example.
Case 113. We present the case of Gussie Silverman, a
housewife, 35 years of age, among other reasons, for its social
interest. The case is, on the whole, sufficiently typical of
General Paresis. Physically, for example, the pupils failed
to react to light and accommodation and were unequal, the
right being larger than the left. The knee-jerks were sluggish
though equal. The ankle-jerks could not be obtained. The
abdominal reflexes were not obtained. Otherwise, there was
no reflex disorder.
From the laboratory point of view, the W. R. was positive
in the blood and in the spinal fluid. There were 80 cells per
cmm. and there were an appropriate globulin and albumin
reactions. Mrs. Silverman was rather poorly nourished and
had a slight edema of the ankles.
Mentally, she was found on admission to be markedly
depressed. It appeared that during a recent pregnancy,
terminated by the birth of a 7–months child, she had fainted
several times a day, that since the confinement she had been
very nervous, that she had been asking her husband not to
send her away, that she had refused to leave the house, that
she had become excited even to the point of injuring herself,
especially at night, and that she would go so far as to scratch
her husband, shortly afterward being very sorry for her performances.
Before this last pregnancy there had been four
others and the resulting children were all apparently in good
health. Except for the fainting spells during the pregnancy,
it would not appear that the story just told is at all characteristic
of paresis.
373However, in the hospital Mrs. Silverman could hardly be
got to answer questions, continually saying, “You know what
it is; I don’t have to tell you.” She claimed so marked a
degree of confusion as not to know where she was and what
she was doing. She would beg despondently that something
be done for her, and iterate and re-iterate these claims.
There appeared to be a marked degree of amnesia. Some
one, she felt, had controlled her thoughts and made her do
things she did not want to do and say things she did not want
to say, things she did not know she was about to say. She
said, “I feel like jumping around. I couldn’t believe myself
as if I am me. Some one is making me jump around. I used
to hear him talking. I don’t know who it is. I used to keep
my eyes open and I couldn’t move. I feel only I would like
to talk, and talk, and talk, and talk all the time. It seems to
me that some one talks in me. I couldn’t sleep for five minutes.
My God, I wish I could sleep! I used to feel something
in my heart. I used to faint. It seems to me I used to see
a funny thing. What it was I can’t tell. It used to talk to
me, make me get out of bed, throw me about, make me do
things. O, I don’t know what it was.”
These not entirely characteristic mental symptoms, together
with the suggestive physical signs and the laboratory
examination, caused treatment to be instituted; under which
treatment (intravenous injections of salvarsan) she improved
rapidly. Mental symptoms disappeared under the administration
of 12 injections of salvarsan within two months.
Moreover, the spinal fluid became entirely negative. Two
and a half years have now elapsed since her discharge and she
has shown no return of symptoms. The serum W. R. has
always remained negative although there has been no treatment
since leaving the hospital. There has, however, been
no change in the reflexes, which remain as on admission. The
7–months baby has continued to be perfectly healthy. Its
W. R. is negative, as are the W. R.’s of the husband and the
other three children. It must seem surprising that a healthy
child could have been born from a mother with generalized
syphilis as in this case. However, perhaps there are more
instances than we imagine like the case of baby Silverman.
3741. May a patient be considered permanently cured although
there has been no recurrence of symptoms for 2½ years
and although the Wassermann has remained negative?
One would hesitate to give a definite statement that the
patient was cured until more time had elapsed. It is
quite possible that spirochetes may be lurking in some
portion of the body without causing the production of
symptoms or Wassermann bodies and yet ready to
break out at any time. This hypothesis has added
weight from the recent work of Warthin already quoted.
We advise examination of this patient at intervals of
not longer than six months for a good many years.
2. Should the course under treatment cause us to change
the diagnosis? It has often been stated that a differential
point between cerebrospinal syphilis and general
paresis is the reaction to treatment, that is, that a case
which recovers could not be general paresis. Head
and Fearnsides state that if six months after beginning
of treatment the spinal fluid has become negative, the
case should be considered as one of cerebrospinal
syphilis and not general paresis. We do not feel ready
to concur in this view as we know of no similar logic in
medicine. We have many cases in which a spinal
fluid has remained positive for six months and later
become negative, so that where the symptoms shown
are those of paretic neurosyphilis, we are inclined to consider
the case such until such time as more definite
evidence checked by post mortem examination causes
us to change this point of view.
3. Do the reflexes change under treatment? The signs of
spasticity often do disappear under treatment and also
when there is no treatment. A few instances have
been reported in the literature where Argyll-Robertson
pupils are said to have altered to normal. It has never
been our good fortune to see such a change nor have
we seen an absent knee-jerk become normal, as has
also been reported, except where it is the result of
pyramidal tract disease superimposed upon the posterior
column sclerosis causing a return of reflex. This,
of course, is not to be considered as a return of the
normal. (See Case 1.)
375
Some RESULTS of systematic intravenous salvarsan
therapy are PARTIAL (e.g., clinical recovery
and persistence of positive laboratory tests).
Case 114. Walter Henry was an undertaker in a small
town. He was married and the father of two healthy children.
In May, 1914, he began to lose his appetite. He felt restless
and seemed to be losing his grip, and in August he repaired
to a sanatorium, where he remained for two months. Shortly
after leaving the sanatorium, he fainted one day, while digging
a grave, during a spell of great heat. Since that time
there had been numerous “weak spells,” with headaches and
general debility, insomnia, and loss of weight.
In February, 1916, Mr. Henry came to the hospital for
advice, but the trip from a distant part of the state was apparently
such a strain for him that shortly after admission
he collapsed. There were no convulsive movements in this
collapse, but the patient was confused and his breathing was
rapid and stertorous. The semi-stupor lasted for about 48
hours. Upon recovery from the stupor, Henry was found
entirely disoriented, much confused, and laboring under the
belief that he was digging a grave. After a time he again
fell into a stupor and his temperature rose to 103° F.
The emaciation of this man was striking and unusual,
but systematic physical examination showed no special disease.
Neurologically, there were marked tremors, and there
were purposeless movements of the arms. There was a
marked speech defect. The pupils were dilated, regular, and
equal, and reacted, though slightly, to light. Nothing abnormal
was noted upon systematic examination of the reflexes.
The W. R. was strongly positive in the blood and in the
spinal fluid; the gold sol reaction was typically “paretic”;
there were 16 cells per cmm., globulin was present, and albumin
was greatly increased.
The diagnosis General Paresis was accordingly made, and
treatment instituted. Intravenous injections of arsenobenzol,
376at first, and later of diarsenol, were given, as a rule twice a
week (usual dose, 0.6 of a gram). Mercurial injections and
potassium iodid were also given. This treatment was continued
as the patient began to improve. The improvement
was of such a degree that at the end of four months, Mr.
Henry returned to his home and his work. He had had 30
intravenous injections of salvarsan substitutes. Despite the
treatment and the clinical improvement, the laboratory tests
remained essentially unchanged. The W. R.’s of the blood
and spinal fluid remained strongly positive, as well as also the
globulin and albumin; the gold sol reaction was still “paretic”;
the cells stood at one per cmm. The patient has continued
antisyphilitic treatment since leaving the hospital, and has
remained apparently well, with good insight into his condition.
1. What is the significance of a temperature of 103° in a
paretic without signs of infection and a normal leucocyte
count? Temperatures of this type are not infrequent
in the course of general paresis. They are usually
spoken of as “paretic temperatures.” Their meaning
is not understood, but they are often stated to be due to
a disturbance of the heat-regulating mechanism. Such
temperatures may remain elevated for a considerable
period of time, but the elevation may be very transitory.
At times they vary, like septic temperatures.
2. What can be argued from the fact that the cell count
became normal? If thorough antisyphilitic treatment
is vigorously given, it will be found that in the vast
majority of cases of neurosyphilis the cell count will
return to normal. It matters not whether the treatment
be intravenous or subdural. It is very difficult,
however, to obtain this result in general paresis by the
use of mercury alone. It cannot, however, be urged
that this finding has any great prognostic significance
as it occurs in the cases which do poorly as well as in
those which recover symptomatically.
3. Is it safe to give large doses of salvarsan to a patient in
a stupor? It is not a good plan to give a large dose to
such a patient on account of the danger of sudden
death. This is probably due as much to the strain
put on the heart as it is to any effect on the nervous
system, or specific arsenic effect. In this particular
instance, a dose of 0.15 gm. was the initial injection
and this was increased five centigrams per injection.
377
IMPROVEMENT IN PARETIC NEUROSYPHILIS
(“general paresis”) may become evident
only after several months of intensive treatment.
Case 115. Henry Ryan was a shipping clerk, 54 years of
age, who was brought to the hospital following a convulsion.
For a few months preceding this period, Mr. Ryan
had been failing in his abilities. He had been very forgetful,
showed no energy, and had become very irritable. He also
complained of insomnia and of feeling nervous.
On admission to the hospital, the most striking feature in
the mental situation was that he claimed that he had not
slept a wink for three months, and each day he would solemnly
affirm that he had not slept at all the preceding night, although
the records might show that he had slept eight hours. Argument
was of no avail against this conviction. In addition,
his memory was very poor; he showed little knowledge of
current events, and had no ability with arithmetical problems.
Neurologically viewed, the points of chief significance were
contracted immobile pupils and a speech defect, especially
noticeable on the repetition of test phrases. The whole
picture was suggestive of general paresis, and this diagnosis
was confirmed by the laboratory findings. It was found that
the W. R. was positive in the blood and spinal fluid, that
there was a pleocytosis, positive globulin reaction, excess of
albumin, and a “paretic” gold sol reaction. Consequently,
the diagnosis of General Paresis seemed justified, although
the patient denied any knowledge of a syphilitic infection.
Treatment in this case consisted of intravenous injections
of salvarsan, diarsenol, or arsenobenzol, whichever drug was
most easily obtainable, given twice a week in doses of 0.6
gram each. In addition, he was given occasional injections
of mercury salicylate as well as potassium iodid by mouth.
Once or twice a week, 40 to 60 cc. of spinal fluid were withdrawn.
Under this treatment for a period of three months,
the patient showed no improvement whatsoever, either in
378his mental condition or in the laboratory findings. However,
treatment was faithfully persevered in, and shortly after the
three months, improvement began to be noticed. At first,
the patient began to admit that possibly he may have slept
a few winks some time during the previous six months, for
he said he realized it was not possible for a man to live without
sleep for that period. Then he began to admit that he might
have slept a few hours during the night, and later that he
was sleeping pretty fairly. His memory also showed improvement.
His general attitude showed alertness, and he
began to interest himself in his surroundings and in the events
of the world, and finally he gained complete insight into his
condition.
In the meantime, that is after three months of treatment,
the laboratory findings began to grow weaker. The gold sol
reaction was the first to decrease in strength, and after four
months of treatment, it vacillated between negative and a
mildly positive “syphilitic” reaction. Then the globulin
and albumin became less in amount, and the W. R. began
dropping off in the 0.1 and 0.3 cc. dilutions. As is usually
true in those cases of neurosyphilis that receive adequate
treatment, the cell count early dropped to normal. The
W. R. in the blood serum, however, remained positive.
As the patient’s condition seemed so much better, he was
allowed to leave the hospital at the end of five months. He
took things easily for the following seven months, and then,
after being out of employment for the period of a year, as his
health continued good, he decided to return to work. Before
doing so, he entered the hospital again for a lumbar puncture.
At this time, it was found that the cell count was normal,
there was a very faint trace of globulin, possibly a slight increase
above normal albumin content, and a very mild gold
reaction. The W. R. in the spinal fluid was negative including
the 1.0 cc. dilution; the blood serum remained positive.
The patient then returned to his old position and has done
satisfactorily for the past six months. During this entire
time, he has been coming to the hospital for treatment:
during the major portion of the time, about once in two weeks;
of late, once in four weeks.
379The significant point in this case is that improvement did
not show itself until after more than three months of intensive
treatment, and then the improvement was synchronous with
a weakening of the spinal fluid tests.
It is further significant that his mental and physical condition
was good before the tests had reached anything like
normal; and that under treatment, these tests continued
to grow weaker and weaker, until at the end of a year, they
were practically negative.
The case further illustrates the enormous number of injections
of salvarsan preparations that may be given to a
patient without causing any appreciable damage to the general
health or to the kidney function. Mr. Ryan has had
more than 60 injections.
1. How soon after treatment is instituted does improvement
usually occur in paretic neurosyphilis? In our experience
improvement usually shows itself in from two
or three months of treatment. Occasionally the improvement
may be very marked shortly after treatment
is commenced, that is, after three or four injections of
salvarsan. This is not, however, the rule and as in
the case of Ryan, it may be only after more than three
months that improvement is seen. This means that
in the treatment of these cases patience must be exercised
and much work done.
2. What is the point of withdrawing large amounts of spinal
fluid as in the case of Henry Ryan? It has been stated
that the withdrawal of 40 or more cc., of spinal fluid
while the patient is under treatment has the effect of
reducing the intraspinous and intracranial pressure and
thereby allowing the drug to diffuse into the nervous
tissue better than it would do under ordinary conditions.
How much truth there is in this contention it is
difficult to say and there is as yet no experimental evidence
to confirm this contention. As a matter of fact,
the spinal fluid in cases of paresis is usually under
increased pressure and it is at least plausible to conceive
that a reduction of this pressure may give some symptomatic
relief.
380
Evidence of the activity of syphilis outside the
central nervous system may be seen in cases of
neurosyphilis despite intensive treatment.
Case 116. William Rosetti was a speculator, 43 years of
age, when he was brought to the Psychopathic Hospital on
account of an outbreak in which he smashed a showcase at
the store where his sweetheart was employed; he caused so
much commotion that he was arrested.
On admission, he was very excited, talking loudly and at
length. For some days it was very difficult to manage him,
he was so active. At any moment, he would insist upon
undressing and taking physical culture exercises. He was
very euphoric and expansive, and had no insight into his
condition.
Physically, he was a powerfully-built man and in very good
physical condition except for an iritis and moderate thickening
of the peripheral arteries. The neurological signs of importance
were Argyll-Robertson pupils, and absent knee-jerks
and ankle-jerks. With these findings in mind, a tentative
diagnosis of General Paresis was made, and this was substantiated
by the laboratory tests, which gave positive W.
R.’s in blood and spinal fluid, globulin, excessive albumin,
slight pleocytosis, and a “paretic” gold sol reaction.
When the patient’s mental condition was somewhat better,
he gave a history of syphilitic infection 15 years before, for
which he had had almost continuous treatment. As a matter
of fact, treatment had been pretty strenuous because he had
recurring skin lesions and iritis. It was practically impossible
to get the skin lesions to heal with mercury, and it was
not until salvarsan was introduced that a good result was
obtained in this respect. After one or two injections of this
drug, the skin lesion disappeared and has never returned.
However, at least once a year, he has had attacks of iritis,
and for this reason was still being treated for syphilis at the
outbreak of his psychosis.
381He was at once placed on more strenuous antisyphilitic
treatment in the form of diarsenol, semi-weekly, aided by
mercury injections. After a few months of this treatment,
his mental condition improved so much that he seemed to be
entirely normal. Treatment was continued, however, without
any abatement, and it was of great interest to note at the
end of five months of such treatment that, although mentally
he seemed entirely well, he had an attack of iritis, which was
considered as a sign of active syphilis. This would appear
to indicate the great difficulty of getting results in certain
cases of syphilis with any drugs at our command at present,
as in the iritis we are dealing with a condition which as a
rule reacts fairly readily to antisyphilitic remedies.
1. Are there different strains of spirochetes showing various
degrees of malignancy? This question has been discussed
at length in the literature but there is no satisfactory
answer at the present time. We must always
consider the reaction of the organism and the host; and
it is true in syphilis, as in every other disease, that in
some individuals it is more difficult to get any therapeutic
results than in others.
2. Was the failure to obtain results by long years of treatment
due to “drug fastness” of the spirochetes? It has
been held that the organism of syphilis will develop an
immunity after a time to mercury and arsenic preparations.
This led Fournier to recommend intermittent
treatment as more efficient than continuous treatment.
Noguchi has shown that in test tube experiments, the
spirochetes develop a tolerance to increasing doses of
arsenic. It must be emphasized, however, that this finding
has not been established for the conditions in vivo.
Another explanation of the failure of treatment in certain
instances has been offered by McDonagh, who describes
a life cycle of the organism of syphilis under the name of
cytorrhyctes luis, of which he believes the spirochete to be
merely one form, the other forms not being affected by
arsenic or mercury.
382
Some results of systematic intravenous salvarsan
therapy in PARETIC NEUROSYPHILIS (“general
paresis”) are partial in the sense that with
clinical recovery the laboratory tests remain partially
or less strongly positive.
Case 117. Annie Martin was a charwoman, 37 years of
age. She had applied for relief at a general hospital, to which
she was admitted on the suspicion of nephritis; but upon
admission she became markedly excited and noisy, and spoke
of seeing angels and hearing God speak to her. As the attendants
were unable to quiet her, she was promptly transferred
to the Psychopathic Hospital. She maintained that
she had been sent to the Psychopathic Hospital through the
spite of the general hospital doctors, and she claimed that
other people were also attempting to work her harm for the
purpose of taking her children from her. Visual and auditory
hallucinations were marked, as was the patient’s loquacity,
irritability, and flight of ideas. However, she seemed entirely
oriented and her memory appeared to be intact. She was
able to explain somewhat clearly her supposed condition.
The voices told her that somebody was after her and that
her soul belonged to the devil; that she was to be married
but that her soul was to be damned. These voices probably
belonged to priests. She was under the impression that she
was going to be sent to an electric chair and said, “I think I
am coming to the end and I want a pair of rosary beads
before the end comes.”
This patient’s pupils were markedly unequal and entirely
stiff to light and accommodation. Neurologically, however,
there were no other symptoms. There was a slight trace of
albumin in the urine and there were no casts.
The psychiatric diagnosis in this case would off-hand
undoubtedly be dementia praecox. Yet the stiff pupils are
almost proof positive of neurosyphilis. If further proof
were necessary, it is found in the laboratory tests, which
383showed a positive W. R. of the serum and fluid, with a
“paretic” gold sol reaction; there were 22 cells per cmm.,
there was excess albumin, and a positive globulin reaction.
Under intensive antisyphilitic treatment, there was a slow
improvement. After several months, the patient was entirely
free from mental symptoms; the spinal fluid tests
became entirely negative except that the gold sol reaction
has remained strongly positive.
1. Should treatment be continued in the case of Annie
Martin in spite of the clinical recovery and the negative
tests except the gold sol? We would again emphasize
that it is unreasonable to suppose that a long-standing
case of syphilis can be cured in a period of a few months
of treatment and while the tests may become negative,
it would seem foolhardy to stop treatment on this
account. We do know that in many cases a Wassermann
reaction remaining negative for many months
may again become positive, indicating that the negative
reaction did not mean cure but rather the absence
of the Wassermann bodies in the circulation at the time
the test was made.
2. What is the significance of the paretic gold sol reaction
when the other tests have become negative? As
previously stated, the gold reducing substance in the
spinal fluid seems to be different from the substances
which give the other pathological reactions. We
should feel in this case that the process which was
producing these gold reducing bodies had not been
stopped, in other words, cure was not complete.
3. Should one make a diagnosis on the “paretic” gold sol
reaction alone? The so-called paretic gold sol curve
is not always indicative of general paresis or even of
syphilis but may occur in non-syphilitic conditions as
brain tumor, multiple sclerosis, etc. In our experience
we have seen no case of untreated neurosyphilis in
which the gold sol alone was positive, that is, in cases
in which therapy has not changed the findings in the
spinal fluid. In our experience the gold sol reaction
has been fortified by one or several of the other tests
as the W. R., globulin test, pleocytosis.
384
Some effects of systematic intravenous salvarsan
therapy in PARETIC NEUROSYPHILIS (“general
paresis”) are limited to the laboratory findings
without clinical improvement.
Two examples of such limitation are offered: William
Roberts (118) and John Silver (119).
Case 118. A bank teller, William Roberts, 39, was sent
to the Psychopathic Hospital for a depression so marked that
he had become entirely unable to work or care for himself.
The story was that some money had been left him by his
uncle, that Roberts could not prove his right to the money,
and that depression, insomnia, and occasional periods of
confusion had followed during a period of about five months.
On admission, Roberts appeared wholly disoriented and
unable even to give his correct age. Attention could not
be held, and the patient would slide off into statements like:
“Oh, I made a mistake, I fooled a lot of people, I have a
terrible disease, they are going to get it, they are going to get
me,” etc., etc. There was great difficulty in thinking, and a
marked reaction of fear. This cluster of phenomena certainly
suggested very strongly the diagnosis of manic-depressive
psychosis.
Neurologically, Roberts proved quite negative except that
the tendon reflexes were very active and the pupils reacted
somewhat sluggishly to light. The blood serum W. R. was
negative. No history of syphilis could be obtained; nevertheless,
Roberts kept dropping remarks about the terrible
disease from which he was suffering. It seemed best to proceed
to lumbar puncture, and the spinal fluid disclosed a
positive W. R., globulin, increased albumin, pleocytosis, and
“paretic” gold sol reaction.
The diagnosis of General Paresis was accordingly made.
During the next year and a half, no improvement was made;
a slight speech defect was developed, and tremors of the hand
and tongue appeared.
385The effect of treatment is particularly instructive. Only
after 18 months in the hospital was intensive antisyphilitic
treatment instituted; but after a few months of this treatment
the W. R. of the spinal fluid had become negative, the
cells normal in number, globulin absent, albumin present
only in normal amount. Only the gold sol reaction remained
positive. It is still of a paretic type. Treatment,
however, did not succeed in altering the patient’s mental
condition in the slightest. At the end of many months of
treatment, we still confront a man showing marked psychic
symptoms and a “paretic” gold sol reaction without other
laboratory signs.
1. What is the significance of the practically negative tests
in this case without clinical improvement? One must
believe that the tests became negative as the result of
treatment, and that this change in the tests was due to
the clearing up of some inflammatory reactions which
were present. This may mean that the syphilis had
been reduced to inactivity or latency if not cured, or
at least that there was no activity sufficient to cause
a positive W. R. in the blood serum, whereas whatever
activity was present in the brain was in such a region
that it did not cause any reacting substances to be cast
into the spinal fluid. This would not mean that there
would necessarily be any return of function already lost,
because this may be considered as a permanent loss which
cannot be compensated for. As to these tests, we now
feel that the case should remain stationary; that is,
that no new symptoms will be added. However, we
believe that it is somewhat premature with our present
knowledge to make this claim very forcibly, and would
rather suggest that this case be considered as demonstrating
an interesting fact, the meaning of which can
be learned only after a period of years.
2. Why does the gold sol reaction remain strongly positive
when all the other tests become negative? As already
pointed out, above (Case Martin (117)) there is no known
rule about the disappearance of one or other of the abnormal
findings in spinal fluid under treatment, and we
can at present offer no explanation of this phenomenon.
It does, however, illustrate how careful we must be in
drawing any conclusions from tests in cases that are
being treated.
386
Diminution in the spinal fluid tests may occur
in treated cases of neurosyphilis without clinical
improvement.
Case 119. John Silver, a man 29 years of age, presented
classical symptoms of General Paresis: He had a convulsion
shortly before his admission to the Psychopathic Hospital,
his memory was poor, he was only partially oriented, he was
very euphoric and expansive—thought he had millions,
that he was the Czar of Russia, and so on. His tendon reflexes
were very much increased and there was a marked
speech defect. The W. R. of both blood and spinal fluid
were strongly positive; the spinal fluid showed globulin,
increased albumin, pleocytosis, and a “paretic” gold sol
reaction. There was, therefore, no question about the
diagnosis, and the patient was at once put under antisyphilitic
treatment. This was continued for five months; slowly
the intensity of the reactions in the spinal fluid diminished.
At the end of the five months, there was the very slightest
possible trace of globulin, with a doubtful increase in albumin,
one cell per cmm., and a mild syphilitic gold sol reaction.
The W. R.’s in the blood and spinal fluid, however, remained
strongly positive. There was no mental improvement coincident
with the weakening of the spinal fluid tests, and at
the end of the five months, the patient had a series of convulsions
in which he died.
This case is given as a contrast to Case Henry (114) in which
clinical improvement occurred without diminution in laboratory
tests; in the case of John Silver, marked diminution
in the intensity of these tests had no prognostic significance.
This was in keeping with the condition as shown in
Case Roberts (118) where, while the gold sol was the only test
to remain positive, the patient did not improve mentally.
1. What is the explanation of the lessening of the pathological
elements in the spinal fluid under treatment?
We have seen that the various findings may occur independently
387of one another, and we must admit that
we do not know definitely what it signifies, or why one
may be present or absent. It has been held by Head
and Fearnsides that the findings in the spinal fluid
represent conditions in the spinal cord and spinal
meninges, or at the base of the brain only, and not
conditions elsewhere. This is in keeping with our
finding that the gold sol reaction in the spinal fluid
post mortem very often differs from that in the ventricular
fluids or cerebral, subdural, and subpial fluids.
And further, we have found that during life the findings
in paresis in the spinal fluid may differ markedly from
those in the third ventricle, and that the change in the
fluid in these two areas under treatment may not occur
simultaneously.
388
Systematic intensive treatment of PARETIC
NEUROSYPHILIS (“general paresis”), including
intraventricular injections of salvarsan, may entirely
fail.
Case 120. James McGinnis, aged 39, came to the hospital
on a stretcher, semi-conscious, moaning, unable to reply to
questions; there were signs of a right hemiplegia.
The next day, McGinnis cleared a little and became able
to utter a few words. His wife said that he had been entirely
well up to four years ago. At that time he was struck
in the eye by the head of a hammer that flew off the handle.
Diplopia had developed, but disappeared.
Only two years later did a marked change appear. McGinnis
became careless as to personal appearance. Seemed
absent-minded, apathetic and drowsy; he would fall asleep
in his chair or while at work. He lost his position and became
apprehensive, making not very strenuous efforts to
find work, and finally consulted a physician. The physician
told him that he had a sluggish liver and gave him calomel.
Six months later, McGinnis was restored to his position
as foreman, and his work remained satisfactory for some six
months. Then (about six months before coming to hospital),
his speech became slow and somewhat unintelligible. He
quit work, saying that his speech was going from him and
that he might be considered to be drunk. His memory
grew rapidly worse. There was improvement after a vacation
and he returned to work, but continued to be ataxic, complained
of vertigo, and fell down several times, though
without loss of consciousness. On the very day of his admission
to the hospital, in attempting to get out of bed, he
fell, and psychotic symptoms at once appeared. There
was slight improvement again with entire disappearance of
all paralysis after a few days, a slow clearing up of the speech
disturbance, and a certain return of memory.
Physically, there was little to note. Neurologically, the left
389pupil failed to react to light. The tendon reflexes were all
very active, and more active on the left side. Other abnormal
reflexes were absent. Improvement continued for a number
of weeks, but the patient never recovered from his speech
defect, and his memory remained impaired. Irritable at
times, McGinnis was for the most part very happy and sure
he would get well. The W. R. of the blood serum was
negative, but the spinal fluid reaction was strongly positive,
even down to 0.1 cc. The globulin and albumin amounts
were excessive. There was a “paretic” gold sol reaction.
There were 7 cells per cmm. The diagnosis of General
Paresis was made.
Intravenous injections of salvarsan, arsenobenzol or diarsenol
were made, and intramuscular injections of mercury,
and potassium iodid by mouth were given. No real improvement
occurred after a certain initial betterment; the
spinal fluid yielded no changes. Diarsenolized serum according
to the Swift-Ellis technique was then injected into
the third ventricle. Under this treatment also there was no
change for the better over a period of several months. The
patient died suddenly after a series of convulsions, apparently
from paralysis of respiration.
1. What are the causes of hemiplegia and confusion or
unconsciousness? We must consider epilepsy, brain
tumor, cerebral thrombosis, cerebral hemorrhage, multiple
sclerosis, cerebral spinal syphilis, and general
paresis.
390
MILD TREATMENT, often thought “adequate,”
MAY FAIL, WHEN INTENSIVE TREATMENT
PROVES SUCCESSFUL.
Case 121. Arthur Bright, a printer, had acquired syphilis
in his 49th year, some six months before examination. He
had been treated during these six months by three injections
of salvarsan, injections of mercury, and mercury by mouth.
He had been apparently cured until about a month before
admission. He had fallen without warning from his chair
in a convulsion accompanied by unconsciousness, which lasted
about two hours. The patient had since been feeling rather
peculiar. For instance, time seemed to flow too rapidly.
Sometimes the patient had had difficulty in talking.
Physically, nothing abnormal could be found either in
general condition or neurologically. The patient was, however,
incontinent. Mentally, he was apathetic and unalert,
even paying no attention to his outside physician when he
came to visit him.
The diagnosis of cerebrospinal syphilis already suggested
by his history was confirmed by the laboratory tests, which
showed a positive serum and spinal fluid W. R., paretic
gold sol reaction, 41 cells per cmm., an excess of albumin,
and a positive globulin test.
1. What is the prognosis in cerebrospinal syphilis in the
early secondary stage? The prognosis appears very
good provided that intensive treatment be given and
provided that no vascular insult or other focal destructive
lesion occurs before treatment has had time to do
its work.
2. Why did not the “effective” (?) treatment for the syphilis,
dating from the primary lesion, succeed in staving off
the cerebrospinal syphilis? It remains a question
whether the treatment by three injections of salvarsan
was efficient in this particular case. Of course, it may
prove true that no treatment whatever in the present
stage of knowledge will stave off cerebrospinal symptoms
in certain cases.
391Treatment: Bright was given intravenous injections of
diarsenol twice a week, with occasional injections of mercury
salicylate. After two weeks, the patient seemed markedly
improved, and continued to improve rapidly. He was symptomatically
well at six weeks. The spinal fluid had then
become negative, although the serum W. R. had remained
positive.
After discharge from the hospital, Bright returned to his
work, but continued to take the diarsenol treatment weekly,
and two months later the serum W. R. became negative.
Small injections of diarsenol at intervals of a month were
continued, and Bright remained perfectly well for four
months, when a peculiar seizure developed and lasted for
several hours. This seizure consisted in a sort of somnambulism
in which Bright stood up at a table, making marks
on paper, and could not be persuaded to desist. After this
seizure, Bright re-entered the hospital, again showed no
mental or physical symptoms and no abnormalities of blood
or spinal fluid.
3. What is the explanation of this seizure? It is possibly
due to a small vascular insult, for which potassium
iodid may be suggested with precautions as to hygiene
and continued observation. He has since remained
entirely well.
392
Another example where MILD MEASURES
(though conceived to be “adequate”) SEEMED
TO BE LEADING TO FAILURE; INTENSIVE
THERAPY SUCCESSFUL.
Case 122. Levi Morovitz, a waiter, 39 years of age, came
to the hospital with evidences of an old left hemiplegia, including
the left side of the face (there was a left-sided Babinski,
Gordon, and Oppenheim, and all the reflexes were
fairly active; sluggish pupil reactions, Rombergism, and
speech defect). Morovitz was much depressed, very slow
in thinking processes, had a marked memory disturbance in
general and apparently much deterioration mentally.
A history was obtained to the effect that Morovitz had
acquired syphilis at about 33, but that he had received
practically continuous treatment ever since at a dispensary.
He had, in fact, received four injections of salvarsan a year
before coming to the hospital. Of late, Morovitz had become
much more cheerful and talkative, imagining he could do
great things if he had money. He had begun to eat very
rapidly and to be very nervous. His feet had begun to drag;
a distinct speech defect developed, but from this he had recovered.
About six weeks before entrance, Morovitz had a
shock, which left him with the left hemiplegia above mentioned
and with considerable headache.
Even while the preliminary examination was being performed,
Morovitz developed a minor seizure without loss of
consciousness. First came severe pain over the frontal
region, which grew in severity so that the patient held his
head in his hands. A bit later, twitching movements began
in the thumb and in the fingers of the left hand, and the
small muscles of the extensor group of the thumb and third
finger showed contractions. These contractions grew more
general and the excursions of the fingers greater, until finally
every finger of the left hand became involved, whereupon
movements of the same sort, though of smaller amplitude,
393began in the other hand. Finally the left arm began to jerk
with alternate contractions of the biceps and triceps. The
whole seizure lasted more than five minutes. During the
seizure there was dizziness and pain in the head, chiefly on
the right side.
Diagnosis: The attention is at once arrested by the data
of the seizures described. It appeared that we had to assume
an irritation of the right side of the brain, possibly due
to vascular disease, or to brain tumor, or perhaps to syphilis.
The shock with residual hemiplegia would be consistent
enough with any of these diagnoses. However, the history
seemed somewhat long for brain tumor. Nor were there
any definite symptoms of intracranial pressure. “Adequate”
treatment unfortunately does not rule out syphilis. The
comparatively early age (39) of the patient makes it difficult
to explain the vascular disease except on the basis of syphilis.
Add to the hemiplegia the euphoria and grandiose ideas of a
year’s duration, and we arrive at a diagnosis of neurosyphilis,
probably Paretic Neurosyphilis.
The laboratory tests showed the W. R. of the serum and
spinal fluid positive, 80 cells per cmm. in the fluid, large
amounts of globulin and albumin, and a “paretic” type of
gold sol reaction.
To be sure the Jacksonian seizure is not especially characteristic
of paretic neurosyphilis, and even suggests a local
irritation in the motor area, such as a localized meningitis,
possibly of a diffuse gummatous nature.
This patient was put on intensive antisyphilitic treatment,
namely, salvarsan twice a week and injections of
mercury. He recovered rapidly. After a few months he
left the hospital, and after treatment had continued for a
year, he resumed his work by which time both blood and
spinal fluid had become negative.
It must be recalled that this patient had from the time of
his infection what has been considered good antisyphilitic
therapy, in spite of which he developed after a period of
years, the symptoms and signs of neurosyphilis in its most
dangerous form. The conclusion must be drawn that
however good such treatment is for the majority of cases, it
394was insufficient for Morovitz. That the early failure to cure
was not due to any “drug fastness” of the spirochete or to any
peculiarity of strain is proved by the result of more vigorous
antisyphilitic treatment which caused an apparent if not a real
cure. With our modern methods of treatment checked by
Wassermann reactions and spinal fluid examinations, treatment
is given according to the needs of the individual patient
rather than according to general preconceptions. We have
reason to believe that under these conditions there will be
fewer cases developing late symptoms on account of insufficient
treatment given even to patients who are willing
to co-operate to the last degree.
The fact that Morovitz had no apparent symptoms for
several years led to rather desultory treatment chiefly in the
form of mercury by mouth. Previous to the time when the
W. R. and lumbar puncture were available, the physician had
no exact means of determining cure except the non-appearance
of symptoms. But a period of years of quiescence before
the outbreak of symptoms referable to the involvement of
the nervous system is characteristic of syphilis. With this
knowledge in mind it is evident that today the care of a
syphilitic patient must be guided, in part at least, by examinations
of the spinal fluid and W. R.
395
Salvarsan treatment may even occasionally be of
value in simple FEEBLEMINDEDNESS due to
congenital syphilis.
Case 123. The somewhat unattractive Robert Matthews
was brought, at 5 years of age, to the hospital for backwardness
of mind. It appears that the patient was born at term,
with instruments, that he began to talk at a year, and to
walk at 13 months, but that in point of fact, he had not
talked intelligibly to date. Robert had never played with
other children and is regarded by his parents as backward.
In fact, Robert’s sister—a year his junior—is much
brighter. Robert had had scarlet fever but without sequelae.
Examination by the Binet scale showed that, although he
is actually 5½ years, he graded by the Binet scale at 4 and
was regarded as feebleminded.
The physical examination showed a general adenopathy
and prominent frontal bosses. In the study of the family
history in the search for an etiology for the evident feeblemindedness,
little or none could be found. There were no
miscarriages or stillbirths; the parents were living and well.
There was only the one sister above-mentioned, who is
brighter than Robert.
The advantage of a routine W. R. is here well shown, for
the W. R. in the serum was positive.
1. What is the prognosis of cases of syphilitic feeblemindedness?
It would appear that every case is an individual
problem.
2. What is the effect of treatment? Robert Matthews was
given mercury protoiodid ⅛ gr., three times a day, by
mouth, for three months. The protoiodid was followed
by ten injections of salvarsan, average: 0.15 gram,
during six months. At the end of this period, the W. R.
in the blood had become negative. A re-examination by
the Binet scale, when Robert was 65
12 years of age,
showed him to grade at 5⅖, so that one might conclude
that Robert had shown more mental progress in a year
than he had previously.
396Note: The patient’s sister, 4 years of age, is attractive
and bright, measuring beyond her actual age according to
the intelligence tests. However, the girl was found to have
a positive W. R. It may be that Robert and his sister
illustrate the hypothesis of Mott: that the syphilitic virus
becomes less potent as the years go on, and that the younger
children in the family are less affected than the older. However,
in our series, there are a number of instances in which
this hypothesis is not substantiated.
3. What is the share of syphilis in the production of feeblemindedness?
The percentage of syphilitic cases found
in institutions is not high. A variety of cases have
been proved to be congenitally syphilitic in the absence
of a positive serum W. R.
Fernald[19] has charted a comparison of cases diagnosticated
“moron” (that is, feeblemindedness proper, in the
narrower English sense) and “imbecile.” Fernald says that
the morons have, as a group, many more bad family histories
than have the imbeciles, to quote—“Only 70% of the
[imbecile] group have bad family histories. This at first
seems surprising, but when we consider that more of our
syphilitic, traumatic, and sporadic cases tend toward the
lower end of the feebleminded group, and when we remember
that with such cases there is often a seemingly normal family
tree, the drop in the curve appears logical.”
The situation with the idiots, of whom only 38 came into
Fernald’s study, was similar; 12 out of 38, or 32%, of idiots,
had good family histories. On these figures, how unfortunate
it would be to dub feeblemindedness hereditary! It is
true, however, that 68–70% of the idiots and imbeciles,
judging by W. E. Fernald’s intensive study, do have bad
family histories.
Goddard[20] states that of all the causes of feeblemindedness,
397there is perhaps none for which there is less evidence than
syphilis. Goddard found syphilis in 27 of his intensively
charted cases of feeblemindedness, that is, in 9% of all his
charts. He finds the majority of the syphilis cases occurring
in relatives of the feebleminded to be in the hereditary group;
for example, of 164 charts in the hereditary group, 17, or 10%,
showed syphilis. In 34 charts in a group termed “probably
hereditary” 3, or 9%, showed syphilis. Of 37 charts in the
group termed “neuropathic” 4, or 11%, showed syphilis,
whereas in 57 “accident” and 8 “no cause” groups, there
were but 2 (4%), and one, or 13%, showing syphilis. However,
Goddard concedes that much more careful studies are
necessary if we are to give an exact evaluation of syphilogenic
feeblemindedness.
The first ten of the Waverley Anatomical Series are shortly
to be described in a forthcoming publication.[21] Of these ten
cases, four showed some slight evidence of chronic inflammatory
changes, indicating the possibility of a syphilitic or
similar infectious condition. These cases, be it remembered,
were not cases of juvenile paresis, but cases of what, for the
lack of a better name, may be called “ordinary” feeblemindedness.
If all or any of these processes are syphilitic, the syphilis is
virtually extinct. The cases had not been treated for syphilis
and were not regarded as syphilitic, though several of them
showed a few stigmata somewhat suggestive of syphilis. The
anatomical conclusion at this time is still doubtful.
As in the text case, the hypothesis of syphilis as a direct
cause for simple feeblemindedness must be entertained for a
few cases. In any event, it would not seem logical to let
any institution for the feebleminded run without a Wassermann
analysis of the population. In addition to the Wassermann
data from the blood serum, osteological data from the
X-ray have proved of occasional value for syphilis diagnosis
in this as in other groups.
398
“Within the gates of Hell sat Sin and Death.”
Paradise Lost, Book X, Line 230.
399
Although the American toll of war syphilis has not yet
begun and although the crop of neurosyphilis due to war
infections may not arrive until the mid or late twenties of
the century (witness German experience in the eighties of
the last century), it seems proper here to give a number of
abstracts re neurosyphilis as it has developed in the war.
Available reports from English, French, and German sources
have been levied upon for the years 1914–16.
It is clear that all the armies have had their share of
neurosyphilitics, some clearly diseased before enlistment,
some developing symptoms as a result of training, stress,
or shock, others hastened or made worse by war conditions.
There are important questions of pension, retirement, and
compensation for neurosyphilitics. No previous war has
had the benefit of the Wassermann reaction and other exact
tests bearing upon the nature, progress, and curability of
neurosyphilis.
That we shall have our fill of pension and other problems
can already be seen from continental reports. Thibierge,[22]
for example, states that syphilis has become a real epidemic
among the French soldiers and mobilized munition workers.
Hecht[23] of Austria claims that no less than an equivalent
of 60 army divisions have been temporarily withdrawn from
fighting on the Teutonic side for venereal diseases. He
commends Neisser’s idea that salvarsan and mercury should
be given in the trenches. While hundreds or thousands of
Austrians are sick with syphilis, sound and healthy men are
being shot down in their stead. The diagnosis of syphilis,
according to Hecht, ought to be a signal for sending the men
to the front. He makes even the somewhat bizarre suggestion
400that special companies of syphilitics should be formed,
for convenience of treatment, on the firing line.
Not only is the syphilis problem in the army of importance
to the military authorities, but also to the civil population,
and perhaps to them a greater problem. With the great
increase of venereal disease that is the result of the conditions
of army life in war time, there will be a considerable percentage
of cases developing neurosyphilis a number of years after
discharge from the army, but caused by the infection acquired
during service. In addition many men will bring the disease
back to America in an infectious stage and spread it. We
would advocate that the names of all soldiers who had
acquired syphilis and were not considered cured at time of
discharge should be given to health organizations in their
home states that they may be given further care.
These practical and several theoretical questions are
raised by the following fourteen cases which we have condensed
from their sources.
401
A tabetic lieutenant “shell-shocked” into paresis?
Case from Donath of Vienna.
Case A.[24] An apparently competent German professor in
an intermediate school, a lieutenant of infantry reserves, 33
years old, on the 17th August, 1914, was stunned for a while
by the shock of a cannon-firing 25 feet away. Urination
became difficult. Headaches and limb pains ensued, with
paralysis of fingers, gastric troubles, forgetfulness especially
for names, insomnia, and general scattering of mental faculties.
Neurologically, the pupils were irregular, left larger than
right; Argyll-Robertson reaction. Right knee-jerk livelier
than left. Achilles reactions absent. Slow and dissociated
pain reactions in feet, lower thighs and lower quarter of upper
thighs, with hypalgesia or analgesia. Station good; gait
steady. Mentally depressed, slow of thought. Speech poor
and of indistinct construction (mild dementia). Calculation
ability poor. No pleasure in work.
Wassermann reaction of serum weakly positive.
It seems that for a year the patient had been subject to
spells of anger. He was irritated by his wife who had been
nervous since an earthquake.
On the occasion of the earthquake, 1911, the patient himself
had had a spell of difficulty with urination. The spell had
lasted two or three months. The patient had had a chancre
in 1902, “cured” in four or five weeks with xeroform. In
1908, when about to marry, he had had six mercurial inunctions.
1. Is this a case of traumatic paresis? From the somewhat
meagre account it would appear that Donath’s
lieutenant should rather be termed “shell-shock paresis,”
in the sense of a paretic neurosyphilis liberated by
402shell-shock (using shell-shock in the sense of a shock
without direct brain injury).
2. What compensation is due such a man as Donath’s
lieutenant? The ordinary principles applicable to
traumatic paresis are not here in point, since no
symptoms pointing to trauma of brain ever supervened.
See discussion under Case G.
3. How frequent is paresis in armies? R. L. Richards in
White and Jelliffe’s Treatment of Nervous and Mental
Diseases writes as follows (of course concerning peace
times):
“The French estimate that paresis cases are 7 per
cent of all their military cases. The German estimate
is 6.6 per cent. In our own army at the Government
Hospital for the Insane, of 490 cases of mental diseases
among officers and enlisted men, 37, or 7 per cent, were
paresis. During the Russo-Japanese War, in the
Russian Psychiatric Hospital at Harbin, the percentage
of paresis was 5.6 per cent among the cases developing
at the front.”
403
A French soldier “shell-shocked” (also burial)
into incipient tabes dorsalis? Case from Duco and
Blum of Paris.
Case B.[25] A French soldier was buried by effects of shell
explosion September 8th, 1914. He sustained no wound or
fracture.
Incontinence of urine developed. Anesthesia of penis and
scrotum. Reflexes absent; pupils sluggish. Wassermann
reactions suspicious.
The diagnosis tabes dorsalis incipiens was made (hematomyelia
of conus terminalis eliminated).
The patient was estimated to be “40% incapacitated,”
according to the French “échelle de gravité” of conditions. A
full pension would not be justified in the opinion of the
French authors.
1. Is there evidence of an increase or exacerbation of
tabes dorsalis in the war? Birnbaum,[26] reviewing
German war neurology, quotes Weygandt as believing
that the war has probably had to do with the production
of both tabes and paresis in many instances.
Other cases, however, have merely been made worse
by the war stress. Thirdly, there are cases in which
the war stress has done no harm whatever. Westphal
has seen both tabes and paresis develop in men who
had never before shown any mental or physical symptoms
whatever, and accordingly, Westphal must be
counted among those who regard war stress as a liberating
factor for these diseases. Redlich and Donath are
cited in the same connection. (The case of Donath is
the case presented above as Case A.)
A very interesting claim was made by Cimbal to the
effect that he found many examples of paresis developing
in the early period of the war, particularly in November
and December, 1914. Later, according to Cimbal,
cerebrospinal syphilis and tabes became more prevalent.
404
Neurosyphilis in a German recruit, possibly AGGRAVATED
ON military SERVICE. Pension not
allowable. Case from Weygandt.
Case C.[27] A German, long alcoholic and thought to be
weakminded, volunteered, but shortly had to be released from
service. He began to be forgetful and obstinate, cried, and
even appeared to be subject to hallucinations. The pupils
were unequal and sluggish. The uvula hung to the right.
The left knee-jerk was lively, right weak. Fine tremors of
hands. Hypalgesia of backs of hands. Stumbling speech.
Attention poor.
It appeared that he had been infected with syphilis in 1881
and in 1903 had had an ulcer of the left leg.
The military commission denied that his service had
brought about the disease. In the phrase of the Canadian
Pension Board the German commission would probably have
rendered a report “aggravated on service,” not “by service.”
(See Canadian cases D, E, and F.)
1. Has paresis increased in the war? Both French and
German figures controvert the claim. Marie, for
example, found not a single paretic amongst the skull
injury cases at the Salpétrière. Most authors are
found demonstrating cases which they clearly regard as
in some way produced or unfavorably influenced by
the war. There seems, therefore, to be a little inconsistency
between the general statement that paresis has
not increased in the war and the somewhat frequent cases
described as occurring in and modified by the war.
However, Bonhoeffer, on the basis of nine months’ war
experience, also holds it to be probable that paresis is
no more frequent in the field than in the home population.
2. Is the old syphilitic especially liable to break down under
war conditions? According to Richards, Shaikewicz
says that in the Russo-Japanese war paresis was noted
405especially among the officers and non-commissioned
officers, and that it was undoubtedly hastened in its development
by war conditions. Steida says that while
ordinarily we find paresis developing twelve to twenty
years after the primary sore of syphilis, in these cases it
developed in five to ten years after the primary sore.
Some of the cases progressed with unusual rapidity. It
was also noticed that among soldiers from the front,
under treatment, evidences of syphilis were present in
20%, while among the other soldiers under treatment,
evidences of syphilis were present in 1.6%. Undoubtedly
the old syphilitic is especially liable to break
down under war conditions.
But, on the whole, the German authors in this war
find no evidence favoring Steida’s claim of the hastened
post-infective outbreak.
3. How did it come about that the efficient German system
permitted this alcoholic and weakminded syphilitic to
enter the army? As will be seen, he was a volunteer.
In general, the German system has been supplied with
army surgeons who have been trained, not by brief and
“brush-up” courses, but by longer periods, sometimes
two years in duration.
406
Syphilis contracted before enlistment, “AGGRAVATED
BY SERVICE.” Canadian case, courtesy
of Dr. J. L. Todd, Canadian Board of Pension
Commissioners.
Case D. A laboring man, 42, who always strenuously
denied syphilitic infection, proceeded to France eight months
after enlistment. He had not been in France three weeks
when he dropped unconscious. He regained consciousness,
but remained stupid, dull in expression, and with memory
impaired. His speech was also impaired. There was dizziness
and a right-sided hemiplegia.
He was confined to bed four months and was then
“boarded” for discharge.
Physically, his heart was slightly enlarged both right and
left; sounds irregular; extra systoles; aortic systolic murmur
transmitted to neck; blood pressure 140:40. Precordial
pain, dyspnea.
Neurologically, there was a partial spastic paralysis of the
right thigh which could be abducted, could be flexed to 120°,
and showed some power in the quadriceps. There was also
a spastic paralysis of the right arm, but the shoulder girdle
movements were not impaired. There was a slight weakness
on the right side of the face. There was no anesthesia
anywhere.
The deep reflexes were increased on the right side, Babinski
on right, flexor contractures of right hand, extensor contractures
of right leg, abdominal and epigastric reflexes absent,
pupils active, tongue protruded in straight line.
Fluid: slight increase in protein. W. R.+++
The Board of Pension Commissioners ruled that the condition
had been aggravated by service. (See Case E, “aggravated
on service.”)
1. In view of the fact that the majority of the cases here
abstracted happen to be in common soldiers, is there
any evidence bearing on relative incidence in officers
and men? Quoting R. L. Richards:
407“The percentage of paresis cases among officers alone
is variously estimated from 50 per cent in the German
army (Stier) to 58.9 per cent in the Austrian army
(Drastich). Since paresis is a disease of more advanced
life, it is but natural that the percentage of paresis
among officers, non-commissioned officers, and older
soldiers should be higher than among the whole military
body, where the average age is, as we have seen, well
below thirty years. Hence the above figures do not
mean a greater prevalence of syphilis among those
classes, but that we have no means of knowing how
many of the others develop paresis. If anything it
shows that these ‘soldiers by calling,’ have a more
stable mental make-up, since they succumb chiefly to
an exogenous toxin.”
Rayneau at the 19th Congress of French Alienists
and Neurologists at Nantes in 1909, discussing the
insane of the army from a medicolegal point of view,
states that the most frequent mental disease amongst
officers and soldiers is general paresis. At least, this
disease is the most frequent basis of invaliding, retirement,
or placing in the inactive list. He states that
French and foreign statistics are at one upon this
matter, quoting Christian as finding 32% among the
soldiers interned at Charenton; Gamier at Dijon,
59%; Meilhon at Quimper, 42% and Talon at Marseilles,
33.8%. Grilli found 31 of 40 officers interned
in Florence, Sienna and Milan victims of general
paresis. Stier’s German statistics indicate about 50%.
Rayneau himself found 16 of 20 officers paretic and 17
out of 27 subalterns and gendarmes.
The Neurological Society of Paris held a conference
December 15, 1916, with the chiefs of the neurological
and psychiatric military centres of France, and discussed
a variety of questions concerning invaliding,
incapacity, and compensation in neuroses and psychoses
of war. Dupré dealt especially with the psychoses
of war as caused by trauma, strain, infection,
and intoxication. General paresis is regarded by
Dupré as the most important of the dementias found in
the army. The medicolegal point of view is, of course,
that general paresis is necessarily related to an old
syphilis, but its late development leads to misinterpretations
as to its probable cause, both by the family and
friends and even by magistrates. The war acts in
the French nomenclature as an agent revélateur or as an
408agent accélérateur. Although its cause is prior and
exterior to the war, general paresis in a majority of
cases is brought out (revélé) by the lack of adaptability
of the general paretic to the novelty and difficulties of
his surroundings and duties in war. Trauma, strain,
and alcohol in a certain number of cases accelerate the
progress of a general paresis. The aggravation of
paresis is produced by these same factors, but especially
by violent cerebral trauma. According to Dupré, the
Val-de-Grace statistics show that the number of paretics
has not been increased by the war. Medicolegally,
the victim of general paresis, like the victim of
traumatic or infectious chronic mental disorder, may
be assigned an incapacity of from 50 to 100%, and
these patients are invalided under Réforme No. 1,—a
permanent invaliding.
Lépine of Lyons also discusses the compensation
question in general paresis. Lépine thinks that, although
syphilis is indispensable in paresis, yet the truth
is that syphilis plus something else unknown to us is
responsible for general paresis. This something else is
neither a special kind of virus nor is it a particular kind
of prepared soil alone. Trauma, physical, intellectual,
and moral strain, and insomnia are the factors to which
he calls special attention as adjuncts in the production
of general paresis. As to the responsibility of the State
for the production of general paresis, according to
Lépine, the maximal responsibility should be 40% on
account of the very considerable predisposition to paresis
created by pre-existent syphilis.
Marie remarked that, although there had been
thousands of head cases at the Salpétrière, there had
not been a single case of general paresis. Dupré agreed
with Marie that trauma was not a frequent etiological
factor; strain and alcohol were more important. The
Society agreed that in exceptional cases, where an
encephalic trauma could be regarded as accelerating
or aggravating the disease, the degree of incapacity
might be set at from 10 to 30 per cent.
409
Syphilis contracted before enlistment, “AGGRAVATED
ON SERVICE.” Canadian case, courtesy
of Dr. J. L. Todd, Canadian Board of Pension
Commissioners.
Case E. A laboring man, 44, acquired syphilis at a time
unknown. Ten months after enlistment this man developed
symptoms on the firing line. He was inattentive, irrational,
incoherent. The diagnosis was then “mania.”
There were, however, scars at angle of mouth and on lower
lip. Occipital glands were palpable, fine tremor of hands.
The W. R. was +++.
Later the patient became violent, destructive, untidy,
disoriented. Auditory hallucinations are recorded.
He was “boarded” for discharge five months after the first
symptoms. The board agreed that these symptoms would
have appeared in civil life. In view of a difference of opinion
as to the part played by stress of service, his condition was
set down as “aggravated on service” (not, it will be noted, by
service, see Case D).
1. Under what conditions should pensions be awarded for
disability resulting from venereal diseases? According
to a personal communication from Dr. J. L. Todd,
Chairman of the Board of Pension Commissioners for
Canada, pensions are awarded for all disabilities appearing
during service, unless they can be shown certainly
to be due to the men’s own fault and negligence. It
would appear that during service covers both aggravations
by and on service. There remains some doubt
as to whether contraction of venereal disease constitutes
negligence.
2. What have been conditions in the small inactive American
army of the past? Richards has made a study of
statistics at the Government Hospital for the Insane,
Washington.
“The leading features of this mental disease were
well exemplified in our cases the past year. They
formed 7.5 per cent of the total number. They averaged
forty years of age, and Ziehen says 80 per cent of
410all cases are in the fourth or fifth decade of life. They
averaged ten and a half years’ service, which would
indicate that the military life was their calling. Only
one had any serious hereditary defect. Stigmata of
degeneration were infrequent, averaging only two for
each case. 66 per cent had good schooling, considering
their opportunities. Physical signs were frequent in
each case. Only one showed normal light reaction.
Ziehen says the light reaction is retained in only 20
per cent of the cases. Patellar reflex was absent in one
case and normal or exaggerated in five. The speech
defect was slight in four cases. Other physical signs
were present in the usual proportions. Memory defects
existed in all the cases. In four the onset was
with excitement. One began with a character change
as the most marked feature. In only two were the
transfer diagnoses correct. One, beginning as a quiet
dementia, was diagnosticated paralysis agitans, because
of a marked tremor. One was excited and
euphoric and was called a manic-depressive psychosis.
One with an obscure onset was diagnosticated as a
neurasthenic. The other one was first observed in this
hospital. The physical signs should have led to a
correct diagnosis in each of these cases.”
411
Duration of neurosyphilitic process important re
compensation. Canadian case, courtesy of Dr.
C. B. Farrar, Psychiatrist, Military Hospitals
Commission.
Case F. A Canadian of 36 enlisted in 1915, served in
England, and was returned to Canada in February, 1917,
clearly suffering from some form of neurosyphilis (W. R.
positive in serum and fluid, globulin, pleocytosis 108).
There is no record of any disability or symptom of nervous
or mental disease at enlistment. The first symptoms were
noted by the patient in May, 1916, six months or more after
enlistment. The case was reviewed at a Canadian Special
Hospital, October 11, 1916, by a board of examiners. This
board reported that:
“The condition could only come from syphilitic infection
of three years’ standing” (a decision bearing on compensation);
but the general diagnosis remained:
“Cerebrospinal lues, aggravated by service.”
The picture which the medical board regarded as of at least
three years’ standing was as follows:
History of incontinence, shooting pains, attacks of syncope,
general weakness, facial tremor, exaggerated knee-jerks,
pupils react with small excursion. Speech and writing disorder,
perception dull, lapses of attention, memory defect,
defective insight into nature of disorder, emotional apathy.
1. Was the conclusion “aggravated by service” sound?
On humanitarian grounds the victim is naturally conceded
the benefit of the doubt. But it is questionable
how scientifically sound the conclusion really was.
2. Could the condition come only from syphilitic infection
of at least three years’ standing? Hardly any single
symptom in this case need be of so long a standing; yet
the combination of symptoms seems by very weight of
numbers to justify the conclusion of the medical board.
412
Can PARETIC NEUROSYPHILIS (“general
paresis”) be lighted up by the stress of military
service without injury or disease? A possible
example from P. Marie, Chatelin and Patrikios
of Paris.
Case G. In apparently good health a French soldier
repaired to the colors, in August, 1914, being then 23 years
old.
Two years later, August, 1916, symptoms appeared:
speech disorder with stammering, change of character (had
become easily excitable), stumbling gait. He became more
and more preoccupied with his own affairs, grew worse, and
was sent to hospital in October, 1916.
He was then foolish and overhappy, especially when interviewed.
There was marked rapid tremor of face and tongue.
Speech hesitant, monotonous, and stammering to the point
of unintelligibility. His memory, at first preserved, became
impaired so that half of a test phrase was forgotten. Simple
addition was impossible and fantastic sums would be given
instead of right answers; handwriting tremulous, letters often
missed, others irregular, unequal, and misshapen.
Excitable from onset, the patient now became at times
suddenly violent, striking his wife without provocation.
After visit at home, he would forget to return to hospital.
Often he would leave hospital without permission (of course
the more surprising in a disciplined soldier).
No delusions were found.
The serum and fluid W. R. were positive, albumin in fluid,
lymphocytosis.
Neurological examination. Unequal pupils, slight right-side
mydriasis, pupils stiff to light, weakly responsive in
accommodation, reflexes lively, fingers tremulous on extension
of arms.
The patient had, December 5, 1916, an epileptiform attack
with head rotation, limb-contractions and clonic movements.
4131. Should this soldier recover for disability obtained in
service? Marie was inclined to think military service
in part responsible for the development of the paresis.
Laignel-Lavastine thought so also, but that the
amount assigned should be 5%–10% of the maximum
assignable.
2. What is the duty of the military authorities relative to
so called traumatic paresis? Medicolegally speaking,
Froissart, quoted by Rayneau, states that a victim of
traumatic paresis may or may not have presented mental
disorders before the accident, that is, that the paretic
symptoms may develop out of a clear sky as a result
of the accident. The accident itself must be of a
serious nature. The accident must be followed by
phenomena pointing to brain injury of traumatic
nature. These phenomena need not be characteristic
symptoms of general paresis at the outset. The period
elapsing between the trauma and the supervening condition
of paresis must be occupied without notable
interruption, at first by phenomena of a purely traumatic
nature, later by signs indicating the onset and
evolution of general paresis.
The French invaliding process called Réforme No. 1
with pension is granted according to the governmental
instructions only to officers, subalterns, and soldiers
whose disease is due to trauma. In view of this
governmental regulation, the military surgeon must
write out certificates describing every cranial trauma,
however slight, which might have a bearing on the
development of paresis. However, he should not too
readily admit trauma as a cause of paresis. If a long
period of quietude, a period in which the trauma itself
seems to have undergone a complete recovery, supervenes,
then general paresis should not be reported by
the surgeon.
Lépine has recently noted the following features as
desirable in board reports concerning paretics: nature
of trauma, length of service, fatigue endured, insomnia,
date of infection, treatment, W. R.
414
Can “gassing” light up a paresis? Example from
de Massary of Issy-les-Moulineaux.
Case H. A soldier, 35, was sent to the Centre Neurologique
with a hospital ticket reading:
“Neurasthenia, general weakness following intoxication
by gas.”
The soldier was thought at first to be a neurasthenic. But
he soon showed signs of more pronounced mental trouble.
The voice was suspicious. There was a slight irregularity of
pupils.
An epileptiform attack occurred, followed by aggravation
of symptoms.
Lumbar puncture showed pleocytosis. The W. R. of the
serum proved positive.
Yet the evident neurosyphilis, possibly paretic (de Massary’s
diagnosis), was preceded by a neurasthenia and the
neurasthenia was preceded by “gassing.”
De Massary believes the patient and his family would
perhaps be justified in believing the condition produced by the
injury. De Massary is not clear as to the financial deserts of
the patient. It is not a manifest case of aggravation of antebellum
symptoms, even if it be neuropathologically an instance
of acquired loss of resistance to pre-existent spirochetes
in body or brain.
1. What adjuvant factors have been recognized in military
paresis? Aside from syphilis, Rayneau finds that alcoholism,
malaria, sunstroke and various intoxications
serve as causes for paresis. Rayneau points out that the
apparent integrity of the mind in general paresis may
be such that they last in the army some time and have
their oddities ascribed to misconduct or breaches of
discipline. In fact the Legrande du Saulle called this
early period in general paresis the medicolegal period,
showing, as it so often does, thefts, outrages against
decency, frauds, assaults, exhibitionism and the like.
To be sure these acts are absurd and infantile and not
difficult to recognize as of psychotic origin.
415
Syphilis may bring out epilepsy in a subject having
taint. Case from Bonhoeffer, 1915.
Case I.[28] A man of 35 in the Landwehr acquired syphilis
some time in the summer of 1914. He was a good soldier,
passed through several clashes, and was promoted to Unteroffizier.
To understand what followed it must be stated that he had
been a bed-wetter to 11, had been practically a teetotaler
(Bonhoeffer’s point is perhaps that otherwise epilepsy might
have developed sooner?), and, when he did drink, vomited
almost at once, and had amnesia for the period of drunkenness.
His father had been somewhat of a drinker. His
sister had suffered from convulsions as a child.
February, 1915, the Unteroffizier lost appetite, got headaches,
and went to hospital for a time. Upon getting better,
he was sent on service to Berlin. In a Berlin hotel he had
his first convulsions and unconsciousness, biting his tongue.
He was confused for several days, and, when he had become
clear, had a pronounced retrograde amnesia together with a
tendency to fabricate a filling for the lost period.
This retrograde amnesia is uncommon in epilepsy and
suggests organic disease. No sign of organic disease was
found on neurological examination. The patient had no
signs of the epileptic make-up. The serum W. R. was
negative. On the whole, Bonhoeffer regards the epilepsy as
“reactive” to the syphilis, as a syphilogenic epilepsy.
As to the amnesia, it is of interest that alcohol should long
before have been able to cause amnesia in this man in the
same way as does now the syphilitic epilepsy.
1. In view of the fact that this Landwehr man appears to
have acquired syphilis while on campaign, what is the
responsibility of the government for treatment? The
416Canadian authorities, as stated under Case E, are in
doubt whether contraction of venereal disease constitutes
negligence on the part of the soldier. It would
appear to us that where a government does not take
suitable steps to prevent the acquisition of syphilis by
the soldiers, the government must assume a measure
of responsibility for the syphilis incurred. The government’s
responsibility would be still greater in equity,
it would appear, if commercial opportunities for the
acquisition of syphilis are maintained under more or
less close government supervision or (even as has been
claimed for certain encampments on our own Mexican
border) if shelter for illicit sex relations is afforded
within the limits of a military camp. In a certain community,
“E,” for example, it is claimed by Exner,[29] the
district for prostitutes was “situated within the lines of
military camps and protected and ‘regulated’ by the
military authorities.”
But even if the government has no legal responsibility
in this regard, it would be well to consider the
ultimate results of the syphilis that will probably be
acquired by great numbers of soldiers under campaign
conditions. Aside from the ravages of syphilis outside
the nervous system, it is well known, as Weygandt
intimates for German conditions, that the aftermath
of war will be a high proportion of cases of neurosyphilis.
Weygandt remarks in his review of the influence of
the war upon psychiatry, that the opportunity for
syphilitic infection in the campaign is considerable.
In the war of 1870, the conditions in this regard were
extremely unfavorable, and writing in 1915, Weygandt
remarks that at present there should be a prophylaxis
against syphilitic infection by the soldiers, which
prophylaxis should be the most energetic possible.
Continence on the part of the soldiers and the isolation
of infected women, with examination by specialists,
have been advocated by Neisser and by Mendel. In
the ’80’s a great number of cases of locomotor ataxia
developed in Germany, which were due to syphilis
acquired by the soldiers and officers in the war of 1870.
417
Syphilis in a psychopathic subject. Convulsions
5 days after Dixmude. Case from Bonhoeffer, 1915.
Case J.[30] A soldier in the reserves, 23, was, subsequently
to his being brought to hospital, described by his wife as a
rather over-sensitive fellow, who could hardly look at blood
and was meticulous about the household. He had always
been subject to headaches, especially after hard work.
However, he had passed through his military training well in
1910, not even having been bestraft.
He began service in October and fought at Dixmude on
the 19th. On the 24th in the trench and while being carried
back, he had several spells of pallor, falling stiff, and then
having convulsions. Brought finally to the Charité in Berlin,
he had more spells of sudden pallor, collapse with brief convulsions,
tossings in bed, and absences, post-convulsive headaches,
and mild bad humor.
There were numerous attacks several days apart in the
first seven weeks. The patient was not of an “epileptic”
disposition, though he was rather readily dissatisfied. Headaches
also occurred without relation to convulsions.
The serum W. R. was positive. Treatment by mercurial
inunctions. No further convulsions. Prognosis as to the
possibility of a constitutional epilepsy unknown.
418
SYPHILITIC ROOT-SCIATICA (lumbosacral
radiculitis) in a fireworks man with a French artillery
regiment. Case presented from Dejerine’s
clinic by Long.
Case K. No direct relation of this example of root-sciatica
to the war is claimed nor was there a question of
financial reparation.
There was no prior injury. At the end of March, 1915,
the workman was taken with acute pains in lumbar region
and thighs, and with urgent but retarded micturition.
Unfit for work, he remained, however, five months with the
regiment, and was then retired for two months to a hospital
behind the lines. He reached the Salpétrière October 12,
1915, with “double sciatica, intractable.”
There was no demonstrable paralysis but the legs seemed
to have “melted away,” fondu, as the patient said. Pains
were spontaneously felt in the lumbar plexus and sciatic
nerve regions, not passing, however, beyond the thighs.
These pains were more intense with movements of legs; but
coughing did not intensify the pains. Neuralgic points could
be demonstrated by the finger in lumbar and gluteal regions
and above and below the iliac crests (corresponding with
rami of first lumbar nerves). The inguinal region was
involved and the painful zone reached the sciatic notch and
the upper part of the posterior surface of the thigh.
The sensory disorder had another distribution objectively
tested. The sacral and perineal regions were free. Anesthesia
of inner surfaces of thighs, hypesthesia of the anterior
surfaces of thighs and lower legs. The anesthesia grew more
and more marked lower down and was maximal in the feet,
which were practically insensible to all tests, including those
for bone sensation. There was a longitudinal strip of skin
of lower leg which retained sensation.
Position sense of toes, except great toes, was poor. There
was a slight ataxia attributable to the sensory disorder—reflexes
419of upper extremities, abdominal, and cremasteric
preserved, knee-jerks, Achilles and plantar reactions absent.
The vesical sphincter shortly regained its function, though
its disorder had been an initial symptom.
Pupils normal.
The “sciatica” here affects the lumbosacral plexus.
Signs of disorder at one time or other affected the first lumbar
distribution of the third lumbar and first and second sacral
nerves.
As to the syphilitic nature of this affection, there had been
at eighteen (22 years before) a colorless small induration of
the penis, lasting about three weeks. There was now evident
a small oval pigmented scar. The patient had married at
20 and has had three healthy children.
The lumbar puncture fluid yielded pleocytosis (120 per
cmm.). Mercurial treatment was instituted.
The treatment has not reduced the pains. Long thinks it
was undertaken too long (six months) after onset. The
warning for early diagnosis is manifest. There was somehow
a delay under the medical conditions of the army.
420
Can the “lighting up” of NEUROSYPHILIS IN
CIVIL LIFE be induced by the domestic stress of
war? A possible example from Dr. R. Percy Smith,
London.
Case L. A German Jew in London passed into the
Paretic form of Neurosyphilis shortly after the outbreak
of war under conditions suggesting that the stress of emotions
directly or indirectly lighted up the neural process.
The man was a bank-officer, 52 years old, and married.
He had lived many years in England and was in fact a
naturalized citizen. He had been under treatment for
syphilis by Sir Jonathan Hutchinson, 29 years before, namely,
at the age of 23. Subsequently, Sir John had given him permission
to marry.
It proved that for years the man had had fixed pupils,
absent knee-jerks, and a perforated ulcer of the foot. However,
there had been no other mental or nervous symptoms
preventing bank-officer’s work.
At the outbreak of war the man was discharged from the
bank. He grew worried and sleepless. He began to charge
himself with sex irregularity. He went down to the city and
burned trust documents belonging to others.
From worry and self-accusation he passed into depression
and agitation. He developed a belief that not only he but
also his German wife were to be executed. He thought he
was a criminal and was to be hanged.
The depression then altered to a condition of hilarity and
loquacity.
In addition to the fixed pupils and absent knee-jerks, a
speech disorder shortly developed.
The patient was placed under care, but quickly (a few
months?) passed into an advanced stage of paretic neurosyphilis
and died.
421
SHELL-SHOCK PSEUDOPARESIS (non-syphilitic).
Recovery. Case from Pitres and Marchand
of Bordeaux.
Case M. June 19, 1915, a shell exploded some distance
from Lieutenant R. He remembers the gaseous smell, the
bursting of several shells nearby and a sensation of being
lifted into the air. When he recovered consciousness, he was
in hospital at Paris-Plage, covered with bruises and scratches.
They told him he had been delirious and had vomited and
spat blood.
June 24, his wife came to see him, but this visit he could
not remember. Nor could his wife at first recognize him, he
was so thin. He roused a few moments and recognized his
wife, but relapsed into torpor again. Speech was difficult
and ideas confused.
A few days later he was able to rise; but his mental status
grew worse, especially as to speech and writing; the latter quite
illegible. There was insomnia, or, if he slept, war dreams.
August 7, he began a period of five months’ convalescence
passed with his family, depressed, given to spells of weeping,
confined to bed or couch, unable to “find words,” conscious
of his state and troubled about it, speaking of nothing but
the war, and afraid to go out for fear of ambuscade. There
was at first a slight lameness of the right leg. Although he
could walk, he felt pain in the knee on flexing the right leg
on the thigh. He walked holding this leg in extension.
On going back to the colors, he was immediately evacuated
to the Centre Neurologique at Bordeaux, January 20, 1916.
Examination found a bored, impatient, irritated man, vexed
that a man who was not sick should be sent up “comme fou.”
Omitting negative details, neurological examination showed
slight lameness as above, body stiff and movements jerky;
difficult, unsteady gait. The lieutenant could stand for some
time on either leg, tongue and face tremulous during speech.
Limbs moderately tremulous, especially in the performance
of test movements.
422Knee-jerks and Achilles jerks absent. Other reflexes, including
pupillary, normal. Segmentary hypalgesia of right
leg, especially about knee. Tremulous speech and writing.
Patient would stop short in speaking for lack of words.
Malnutrition. Appetite good, but a bursting feeling after
meals.
Skin dry, scaly on legs, fissured on fingers.
Serum W. R. negative. Fluid not examined.
Mental examination. Conscious and complaining of his
troubles, Lieutenant R. claimed persistently that he was not
sick. Memory for recent events was in general poor. Errands
easily forgotten. Lost in the street. Complaint of
corpse odors round him. Everybody is looking at him and
making fun of him. He was apt to insult bystanders. He
was afraid of German spies. Things in shops angered him
as they seemed to him to be of German manufacture.
There were frequent periods of depression, with pallor and
no spontaneous speech for some hours to a half-day. Headaches
coming on and stopping suddenly.
As to diagnosis, the first impression, say Pitres and Marchand,
was that of general paresis. The progress of symptoms
after the shock was consistent with this diagnosis. The
mental state and the physical findings seemed consistent,
although the pupils were normal. His partial insight into
his symptoms was not inconsistent with the diagnosis. He
had a characteristic self-confidence. There had been four
stillbirths (two twins) two children are alive, 11 and 13.
Typhoid fever at 30. Syphilis denied. No mental disease
in the family.
The patient had never done military duty, having been
invalided for “right apex.” But he had volunteered and been
accepted in September, 1914.
1. Was this diagnosis, general paresis, at any time justified?
The spinal fluid should of course have been examined.
The peculiar lameness of the right leg was certainly
not characteristic of general paresis, and was perhaps
hysterical. (There was no limitation of visual fields or
any other definite sign of hysteria.) Presumably some
quality of speech defect, the amnesia, and the euphoria,
423together with absent knee-jerks, led to the diagnosis
general paresis. By the 20th of March, 1916, the knee-jerks
had become lively; the Achilles jerks normal. At
this time the patient had gained in weight, could walk
though stiffly, had headache (especially right frontal)
and a feeling of lead in head, less tremor, lack of desire
to undertake anything. He still wanted to go back
into service. He still saw spies about. Dreams terrible;
devoured by spiders, leggins instruments of
torture. Skin still atrophic. June 4 there was no more
tremor of speech or face. Symptoms largely disappeared
except a few ideas of persecution. Recovery
October, 1916.
2. How was Lieutenant R. cured? Apparently by rest in
the Centre Neurologique. Pitres and Marchand do not
speak of the subtle relation between mental state and
the idea of non-return to military service. This motive
might still work even if Lieutenant R. kept protesting
quite sincerely that he wanted to go back into military
service.
424
SHELL-SHOCK PSEUDOTABES (non-syphilitic,
serum W. R. positive). Improvement. Case from
Pitres and Marchand of Bordeaux.
Case N. Innkeeper B., 36, a shell-shock and burial victim
June 20, 1915, was looked on by a number of physicians as
a case of genuine tabes.
Even eight months after the episode, he still showed (when
observed by Pitres and Marchand, February 3, 1916)
absence of knee-jerks and Achilles jerks, a slight swaying in
the Romberg position, pupils sluggish to light, incoordination,
delayed sensations. There was also a history of pains in the
legs, compared by the patient to those of sciatica. These
pains came in crises, the longest of which had lasted 30 hours.
It seems that this soldier’s troubles began the day after his
shock with a feeling of swollen feet and of cotton wool under
them. He stayed on service, however, walking with increasing
difficulty.
At the time of his evacuation, July 10, he could walk with
great difficulty. “Strips of lead were between his legs.” He
could hardly control movements in the dark, or descend
stairs. Often his legs would bend under him. Vesical function
sluggish.
After a few months the patient could walk better. On
February, 1916, he walked thrusting his legs forward trembling,
and dragging toes a little. He could not support himself
on either leg. Jerkiness and incoordination in extension
or flexion of leg on thigh.
The muscular weakness was decidedly against tabes or at
all events a pure tabes. The incoordination proved to be due,
not to loss of position sense (which was intact) but to unsteady
muscular contractions. Deep sensibility was intact.
There were no mental symptoms. There was a slight
hesitation in speech and doubling of syllables, but nothing
demonstrable with test phrases.
The serum W. R. was positive. Syphilis denied.
4251. What is the cause of these phenomena? Pitres and
Marchand lean to the hypothesis of slight internal
traumatism. They believe that there is either (a) slight
internal hemorrhage in the nervous system, or possibly
(b) what they call “nerve cell contusion,” or perhaps
(c) caisson-disease-like phenomena from aerial decompression.
Some authors incriminate (d) the gases. It
has been reported by certain French authors that
shortly after shell-shock injury or burial there is a
pleocytosis in the spinal fluid as well as evidence of
hemorrhage. The pleocytosis is said to last only a short
time; hence when patient arrives at a base hospital
lumbar puncture usually discloses nothing.
426
Paradise Lost, Book I, line 422.
427
No more important human problem now exists than
syphilis. Syphilis of the nervous system or, briefly, neurosyphilis
is a highly important fraction of the total problem.
The few outstanding dates and items which we present on the
following page give but a faint idea of the amount of observation
and thinking which the medical aspects of neurosyphilis
alone have required. The present work deals with but a small
fraction of the results of this work, nor can we more than
glance at the scientific history of syphilis and neurosyphilis—a
history that would form an epoch in itself.
It is only in the most recent years that syphilology and
the narrower science of neurosyphilology have threatened to
become separate disciplines boasting full time specialized
workers. Up to recent years the contributions to the theory
of syphilis have been largely by-products of work in larger
sciences and arts. Thus, the cellular pathology of syphilis
as worked out by Virchow and the more special vascular
features as worked out by Heubner were incidental in the
progress of pathological anatomy and histology. The bold
procedure of Quincke in proposing lumbar puncture also had
its more general ground in the extension of clinical medicine,—an
interpretation likewise true of the French achievements
in the cyto-diagnosis and chemical diagnosis of the lumbar
puncture fluids. The careful histological definitions of the
Nissl-Alzheimer group were incidental to the application of
approved and classical pathological methods to neurological
and psychiatric material.
Again, the work of Schaudinn, as well as that of Metchnikoff
and Roux, was ingenious work with the methods of parasitology
and experimental pathology. The great work of
Schaudinn in establishing the constancy of the spirocheta
pallida in syphilis may be said to have started syphilology
as something approaching a special discipline. The ideas
of one of the greatest of immunologists, Bordet, were almost
immediately applied to the serum diagnosis of syphilis by
Wassermann and the further application of this method to
the problems of neurosyphilis was almost immediate, with the
spirocheta pallida as an object of attack. The commanding
intelligence of Ehrlich could at once seek application of long
incubated ideas of chemotherapy with the startling outcome,
salvarsan.
428
| DATES, NEUROSYPHILIS |
| |
| VIRCHOW |
PATHOLOGY |
1858 |
| HEUBNER |
ENDARTERITIS |
1874 |
| QUINCKE |
LUMBAR PUNCTURE |
1891 |
| RAVAUT, SICARD, NAGEOTTI, WIDAL |
CYTODIAGNOSIS, C.S.F. |
1901 |
| WIDAL, SICARD, RAVAUT |
ALBUMIN, C.S.F. |
1903 |
| METCHNIKOFF AND ROUX |
TRANSMISSION TO APES |
1903 |
| ALZHEIMER |
HISTOPATHOLOGY, BRAIN SYPHILIS |
1904 |
| SCHAUDINN AND HOFFMANN |
SPIROCHETA PALLIDA |
1905 |
| WASSERMANN, NEISSER AND BRUCK |
SERUM DIAGNOSIS |
1906 |
| PLAUT |
WASSERMANN REACTION, C.S.F. |
1908 |
| EHRLICH |
SALVARSAN |
1909 |
| SWIFT AND ELLIS |
SALVARSANIZED SERUM |
1912 |
| NOGUCHI AND MOORE |
SPIROCHETES, BRAIN TISSUE, PARESIS |
1913 |
| LANGE |
GOLD SOL TEST |
1913 |
| |
| Chart 28 |
429The history of syphilis and neurosyphilis was now to be
thickly sown with ideas and results growing from the achievements
of Schaudinn and Ehrlich. The positive reactions
in the blood and spinal fluid in the most striking of mental
diseases, general paresis, led to the impression that general
paresis itself might at last be proved to be what Mœbius had
suspected, namely, 100% syphilitic. We know how difficult
is the technical proof of spirochetosis in the brains of general
paretics both post mortem and ante mortem, but no one
doubts the certainty of the syphilitic hypothesis concerning
the origin of general paresis.
The data of the gold sol reaction ultimately obtained from
the ideas of Thomas Graham concerning colloids, as developed
by Szigmondi and effectively applied by Lange, have broadened
and solidified the whole plane of attack.
The ingenious suggestions of Swift and Ellis (salvarsanized
serum) and the notable work of Noguchi and Moore (spirochetosis
in paretic brains) indicate to us as Americans what
the establishment of scientific institutes may do to permit the
rapid application of new ideas to branches of inquiry that are
opened out. Scientific institutes do not manufacture a
Virchow, a Metchnikoff, a Schaudinn, a Bordet or an Ehrlich
but they directly permit such men to work and indirectly
stimulate the development of more.
The series of 137 cases here at least presented does not
touch systematically the problems of the neuropathology of
syphilis, which would themselves require a textbook of respectable
size. We have, however, presented in Part I, cases 1 to 8,
some indication of the protean nature of the material and
from time to time in the remainder of the book somewhat
fuller accounts of the pathological anatomy and histology
have been presented than are strictly necessary in the demonstration
430of the principles of modern systematic diagnosis
and treatment.
Our work may be said to represent psychopathic hospital
practice as available to us in our official capacities at the
Psychopathic Department of the Boston State Hospital.
A word is necessary concerning the nature of this practice.
The dispensary and ward practice of a modern state psychopathic
hospital, such as the Boston institution (founded in
1912) and the Ann Arbor institution (founded in 1906), is
to be sharply distinguished from asylum practice. Those
who have not followed the evolution of the modern psychopathic
hospital with the lowering of bars to the admission of
patients and the extension of its benefits to a group of sick
persons far removed from the medicolegal concept “insanity”
may not soon grasp the general nature of psychopathic
hospital material. Psychopathic hospital practice stands,
in fact, almost midway between asylum practice in the classical
sense and private practice. This has come about through
the great extension of the so-called voluntary relation under
which hundreds of patients now resort to the beds and out-patient
rooms of a psychopathic hospital, who would formerly
have remained untreated or inadequately treated. Moreover,
the broadening of the concept of mental diseases as a
whole has permitted in some parts of the world the establishment
of laws under which psychopathic and psychotic patients
may be brought to psychopathic hospitals and even to asylums
under the easiest possible conditions and restrictions, omitting
court procedure altogether. The operation of the voluntary
and temporary care provisions of law has accordingly yielded
us, in the Boston institution, a great group of cases formerly
not at all accessible to hospital diagnosis and treatment.
Needless to say, as always under such conditions, we have
been able to show not merely that hospital diagnosis or treatment
is of importance to a new group of cases, but also that
home treatment, especially home treatment under supervision,
is possible and even ideal for a large group of cases
about which utter darkness or profound misgivings ruled in
the not very distant past.
Accordingly, we are fain to insist that our material is of
431importance in new programs of community organization for
the stamping out of disease. The work in psychopathic
hospitals upon neurosyphilis in particular is essentially a
part of the public health program, although our special work
will not soon be taken over by the public health officers,
so complicated are the ramifications of medical and social
diagnosis and treatment in the neurosyphilis group.
We have tried in Part IV (medicolegal and social cases)
to give a few examples to illustrate the part played by neurosyphilis
in society; but we regard this part of our work as the
least satisfactory and the least representative in the total
work. Our colleagues in social service, in mental hygiene,
in psychopathology and in criminology will easily in the next
few years provide a far more adequate basis for a full account
of the public and social aspects of neurosyphilis. One point
we should emphasize here. The psychopathic hospital worker,
whether physician or social worker, must shortly decide
upon and consolidate a program with relation to the families
of neurosyphilitics.
The syphilographers of the dermatological and special
syphilis clinics have their identical problems with the families
of syphilitics; but the dispensaries for mental cases and in
particular the psychopathic hospital and asylum out-patient
departments tap another reservoir of syphilitic families at a
stage when the memory of the initial horrors of syphilitic
infection is dimmed or erased. Any program for the diagnosis
and treatment of syphilis of the innocent must take into
account not only the skin, syphilis, and internal medicine
clinics but also the clinics for mental and nervous diseases
wherein neurosyphilitics are not infrequent. Whether the
ultimate percentage will stand at 10, 15 or 20% for the neurosyphilitics
in mental clinics, is of no importance to the principle.
There are enough neurosyphilitics having economical
importance and humanly precious families to warrant definite
steps.
The Massachusetts Commission for Mental Diseases has
in the last few years employed the services of two medical
workers whose time has been largely devoted to the applications
of our recent knowledge in neurosyphilis and has gone
432so far as to establish a neurosyphilis ward in one of the district
state institutions (Summer Street, Worcester, under the
Grafton Hospital Board). Special social workers in the
field of neurosyphilis have also been available from time to
time. These social workers are enabled with the support
of the medical profession to do a great deal of good, for example,
with the slogan The Child of a Paretic is the
Child of a Syphilitic.
The nature of the intake of patients into psychopathic
hospital wards and out-patient clinics is such that great
numbers of non-mental syphilitics arrive for diagnosis and
possible treatment. Moreover, the existence of syphilis in
non-suspects is a fact picked up by the way in routine Wassermann
serum diagnosis.
The mental clinic in the modern sense with the medicolegal
bars lowered or well nigh removed, turns rapidly into
a clinic for neurological cases as well. The German models
for mental and nerve clinics are rapidly being imitated.
The result of this administrative novelty in our hospital
procedure has incidentally yielded us many representative
cases of entirely non-psychotic and even non-psychopathic
neurosyphilis. Our impression grows and deepens that the
neurosyphilitic is seldom merely a spinal syphilitic. The
neurosyphilitic is nearly always the victim not merely of
spinal disease but also of intracranial disease. Per contra,
the victim of intracranial neurosyphilis is almost always
more or less importantly affected by spinal neurosyphilis.
The net result of the modern work on neurosyphilis has
been to bring the neurologist and the psychiatrist together
upon one platform in diagnosis and more and more upon one
platform in treatment. But aside from the clinical evidence
that the neurosyphilitic is apt to be a victim of both brain
syphilis and cord syphilis, the autopsy evidence is stronger
still. Even the victim of tabetic neurosyphilis (“tabes
dorsalis”) himself is rarely found at autopsy without more
or less evidence of significant encephalic disease of a chronic
inflammatory or degenerative nature. Aside from tabes
dorsalis and Erb’s paraplegia, the rule is almost universal
that neurosyphilis is a matter of the entire nervous system.
433In view of the generalization of neurosyphilitic process,
one might question the advantage of any topical grouping of
neurosyphilitic disease. Practically speaking, however, as we
have shown in Chart 5, it seems advisable to separate the
neurosyphilitic diseases into six roughly distinguishable groups.
First, there is the great group that we have chosen to term
diffuse neurosyphilis, including many of the cases of so-called
cerebral or cerebrospinal syphilis of the neurological clinics
and the group of cases that have been treated in private
practice by internists and neurologists without recourse to
institutions. These cases have lived at home and have not
been socially hard to manage until the late phases of their
disease when the victims, if poor, are sent to almshouses and
infirmaries under municipal or state care. These are the cases
which have been in the past regarded as most amenable to
the classical iodid and mercurial treatment. Indeed there
is record of numerous therapeutic successes in the group.
Whereas the lesions in diffuse neurosyphilis are chiefly
chronic inflammatory and degenerative changes of a diffuse
nature (with vascular changes incidental or subordinate to
the inflammation and the degeneration), there is an important
and large group of cases that we have termed vascular neurosyphilis
in which the factors of inflammation and degeneration
are subordinate to vascular insults. These are cases of syphilitic
arteriosclerosis and the best examples are victims of
cerebral thrombosis. The clinical symptoms of the immediate
attacks (of apoplectiform, epileptiform or other acute nature)
are not in themselves distinguishable from the immediate
effects of non-syphilitic vascular disease; nevertheless the
establishment of their syphilitic etiology is of the utmost
importance on account of the possibilities of treatment of
the underlying syphilis. For, as the neuropathologist must
always insist, the immediate effects of vascular insults whether
syphilitic or non-syphilitic are much more extensive than the
ultimate paralytic or residual irritative effects; and by consequence
a greater optimism is justifiable in the confronting of
these cases than the nihilistic observer is likely to entertain.
Physicians dealing with chronic disease in general are apt
to be somewhat nihilistic, but this nihilism is increased a
434hundred fold in disease of the nervous system. How important
then is any work which shall demonstrate partial
or even complete recovery from serious looking apoplectic
and other seizures, besides all of which the point of syphilitic
treatment naturally lies in the prevention of future insults
of the same sort. Therapeutic experience in this vascular
group has almost as good a toll of successes as in the diffuse
neurosyphilis group above mentioned, that is to say, the
modern systematic treatment and even the old pre-salvarsan
treatments have succeeded fairly well in removing the products
of inflammation from the membranes of the nervous system
and in abolishing vascular disease.
The old principle that the dead neurone in the central
nervous system cannot be regenerated remains a perfectly
firm principle; but there are any number of neurones and even
neurone systems that are not essential to life or to the pursuit
of happiness. We accordingly have just as good a theoretical
therapeutic outlook in many instances of chronic neurosyphilis
as we have in chronic diseases of many other organs.
Add to this the fact that a great number of the most sharply-defined and grave symptoms are probably not due to destruction
of neurones but to irritation and functional disability
of neurones, and the conclusion is compelled that, as
hinted above, an entirely unjustifiable pessimism and nihilism
have prevailed in some quarters. Of course, the recoil from
such pessimism with the onset of salvarsan treatment led
various enthusiasts to an undue optimism.
Another great group distinguished by the existence of
spinal cord disease is the group we have termed tabetic
neurosyphilis, which group contains the classical tabes dorsalis
or locomotor ataxia and its congeners.
The question of therapeutic optimism comes up most
forcibly in the field of tabes. It is hard, however, at this
time to give a proper and scientifically founded estimate of the
therapeutic outcome in tabetic neurosyphilis with modern
methods. So much can be said: namely, that the alleviation
of pain and the palliation of other symptoms can be successfully
claimed as a result of the renewed interest in the treatment
of this affection. What was said above concerning the
435finality of the death process in a dead neurone is very strikingly
true, of course, of some of the neurones of the posterior
columns in tabes dorsalis. Still only portions of these neurones
(namely, those which run an intradural course) are
strikingly altered in a great many cases. Now and again
one is greatly astonished to observe the restoration of the
lost knee-jerk in cases of neurosyphilis (see for instance the
case of Alice Morton (1), with discussion). In short, the relation
of several tabetic symptoms to irritative conditions
and functional disability of neurones may be considered
established. Naturally, moreover, if therapy can stop the
upward course of the affection as it passes from lower to
higher nerve roots (according to reasonably well-established
ideas of the genesis and progress of this affection), we are
entitled to a further degree of optimism.
The question of therapeutic optimism versus pessimism is
forced upon attention in the fourth great group of neurosyphilitic
diseases which we have chosen to distinguish, namely, the
group of paretic neurosyphilis including the disease formerly
known as general paresis, paralytic dementia, softening of
the brain and the like.
Of course, no one can gainsay there is a group of cases
having in the natural course of events a prognosis of fatality
within a term of years, say three to five years, and we have
cases in our series which go to show that even with the modern
intensive treatment the characteristic down-grade symptomatic
progress and ultimate fatality occur. Still, we have
other cases diagnostically on all fours with the fatal cases
that have seemed to get either entirely well with the laboratory
tests returning to normal and without further mental
symptoms, or else lose mental symptoms on the one hand or
laboratory signs on the other. We should strongly object
to any account of paretic neurosyphilis which should insist
that its necessary outcome is fatality within a term of years.
Of course, viewing our knowledge of the affection in the past,
we should be compelled to object to the generalization “paresis
fatal” on the evidences of the universally recognized remissions.
If nature can stop a paretic process, why cannot
man do as much? Can it be alleged that our own apparent
436therapeutic successes and those of others are merely curious
examples of coincidences, namely, that remissions have chosen
to occur precisely when therapy was systematically applied?
The percentage of therapeutic successes with modern intensive
treatment, wherever it may ultimately stand, is already too
high for this hypothesis of fortuitous remissions.[31]
Moreover, we believe that the details of the clinical progress
of some of the reported cases are convincing on this point.
What, however, is the distinguishing feature of paretic neurosyphilis?
It is in one sense a particular kind of diffuse neurosyphilis.
The tissues are apt to show not only encephalic but
also spinal changes. There is apt to be a more or less well-defined
meningitis, but the characteristic feature, without
which the diagnosis of paretic neurosyphilis would hardly
be rendered, is the existence of disease of the cerebral cortex.
This disease is parenchymatous in the sense of showing nerve
cell destruction. There is also an interstitial reaction in the
shape of a neuroglia overgrowth, but the striking and pathognomonic
feature is the infiltration of the sheaths of the
small vessels in the cortex, giving evidence of an inflammation
very intimately affecting the cellular mechanisms of the
nervous system. It is striking how often a smaller or larger
share of the cells found in the vessel sheaths are plasma cells.
It does not appear, however, that the diagnosis of paretic
neurosyphilis as against diffuse non-paretic neurosyphilis can
be made in the stained sections with complete safety on the
basis of plasmocytosis in the former and lymphocytosis in
the latter. Whatever the results of careful histological differentiation
by future neuropathologists may yield, it is at all
events true that we cannot yet make an important differentiation
clinically on the basis of the differential count of
plasma cells and lymphocytes in the puncture fluids. However
437this may be, there is an important distinction between
diffuse neurosyphilis of the non-paretic type and paretic neurosyphilis
in that paretic neurosyphilis rarely if ever fails to
show important degrees of intracortical perivascular inflammation
with larger or smaller numbers of plasma cells.
What has the therapeutist to face in this matter? The
answer, as elsewhere, depends somewhat upon what the future
may decide as to the habitat and toxic or antitoxic activities
of the spirocheta pallida. The early claims that the spirocheta
pallida was extravascular and lay for the most part
in the parenchyma and not in the vessel sheaths were perhaps
overbold, since other workers have found the spirochete in
the vessel sheaths also (Mott).
Aside from the spirochete and its accessibility to spirochetocidal
drugs, there seems to be no reason for supposing
that the perivascular sheaths cannot be cleansed of their
inflammatory contents. There is, again, no reason why the
phagocytic cells should not continue to perform their scavenger
function until such time as the degenerative process in the
parenchyma (a process not necessarily progressive in the absence
of the spirochete or its products) ceases. There is every
reason to suppose that a great many of the clinical phenomena
are not necessarily due to permanent destruction of neurones
and neuronic organs (dendrites, axis-cylinders, nets and the
like) but are due to various microphysical conditions of
pressure, intoxication and the like.
The inflammatory conditions in the spinal cord of poliomyelitis,
which conditions are precisely as striking as those of the
paretic cortex, are beyond a question cleared away in the
progress of the affection. Reference to the paradigm case (1)
will show the type of our argument. There is no manner of
doubt that in this paradigm case almost every portion of the
nervous system had been sometime swept by spirochetosis
and many of its small vessel sheaths stuffed with chronic
inflammatory products. As for paretic neurosyphilis itself,
a great many of its most striking clinical phenomena, such as
loss of memory and disorientation, as well as great degrees of
apparent dementia, are found virtually as often in cases with
very slight anatomical changes as in cases with marked cortical
438devastation. The inference is plain, that these phenomena
are to a degree functional rather than structural.
In brief, we conclude not only from therapeutic experience
but also on a priori grounds that the histological conditions in
paretic neurosyphilis are not entirely hopeless, and certainly
not more hopeless than conditions in many chronic diseases
outside the nervous system. Accordingly, we plead for a temperate
optimism as to therapeutic results in general paresis.
A fifth group of neurosyphilitic cases bulking rather largely
in textbooks of pathology is the group of the gummata.
For a variety of reasons (therapeutic and otherwise) the
actual number of gummata of the nervous system available
for clinical or even for anatomical study is much smaller than
the books might lead one to infer.
The sixth and last of the main groups of neurosyphilitic
diseases is that of the juvenile forms, among which we find not
only diffuse forms without a special and well-defined course,
but also characteristic examples of paretic and tabetic neurosyphilis.
The distinction of a juvenile or congenital group
of neurosyphilitics is, on theoretical grounds, perhaps hardly
defensible. On practical grounds, however, the juvenile
neurosyphilitics do form a group having special relations to
feeblemindedness, epilepsy and the like.
We must be clearly understood as to the rough, six-unit
classification just given. It is practical merely. For comparison
we have given in other charts more expanded lists
of the diagnostic entities in neurosyphilis among which that
of Head and Fearnsides is of special interest, see Chart 2,
page 21.
We shall now proceed to a brief analysis of the findings in
our chosen series of 137 cases. We shall not reproduce the case
headings of these cases, but expand their statements where
necessary and tie them together so far as possible into a
reasonable and systematic statement of the situation in neurosyphilis.
The footnotes will contain references to other cases
in which identical points are illustrated as in the leading
cases. The leading cases will in all instances be placed first
in the footnotes.
439The paradigm[32] shows meningeal, vascular and parenchymatous
lesions and thus illustrates our definition of the
term Diffuse which means precisely meningeal, vascular and
parenchymatous. The meningeal lesions gave rise to two
prominent sets of lesions, first, the marked tabetic lesions of
the spinal cord (due to the spinal root neuritis incidental to
the spinal meningeal inflammation), secondly, the characteristic
asymmetrical and focal atrophy of cranial nerves incidental
to a now largely extinct meningeal process at the base
of the brain. The vascular lesions are responsible for another
important and characteristic factor in the case, namely, the
bilateral pyramidal tract sclerosis; the bilateral cysts of softening
of the corpora striata are characteristic effects of old
syphilitic cerebral thromboses. The parenchymatous disease
in our paradigm is everywhere obvious, less so perhaps in
the cortex itself than elsewhere, although here also evident
in the shape of lesions suggesting an early phase of tissue
atrophy.
The paradigm is of interest in demonstrating what in broad
lines must be taken as an ascending disease proceeding not
only from spinal cord to encephalon but also traceable as
proceeding from lower parts of the spinal cord to upper parts
thereof and from the lower encephalon to the higher structures
of the cerebral cortex itself.
The paradigm insistently calls attention to the advantage
of persistent therapy not only in its display of remarkable
successive recoveries from permanent looking symptoms but
also histologically from the remnants of inflammatory process
to be found in an otherwise almost wholly dismantled nervous
system with extinct lesions.
Tabetic Neurosyphilis[33] (“tabes dorsalis”), of course,
often proceeds to death without special complications of syphilitic
nature. We have chosen a case, however, to demonstrate
a terminal complication with vascular insult. Incidentally the
case shows another complication inasmuch as the cause of
death was rupture of aortic aneurysm. It is important to
bear in mind these complications in tabes dorsalis which go
440to prove that the spirochetosis of tabetic neurosyphilis is not
limited to the region of the spinal roots or to the spinal region
in general. Tabetic neurosyphilis is apt to be only a part of a
total picture of neurosyphilis just as neurosyphilis itself is
only a part of the general syphilitic process.
Our case of Paretic Neurosyphilis[34] (“general paresis”)
is a characteristic one in duration (three years and three
months). The aortic sclerosis almost constantly found in
neurosyphilis and especially in paretic neurosyphilis is here
also shown. The spinal cord showed lesions which are also
almost always found in paretic neurosyphilis. The characteristic
frontal emphasis of the atrophic and indurative lesions is
shown. There is also a display of gross changes in the pia
mater. The characteristic so-called granular ependymitis or
sanding of the ventricular surface is shown. The case is distinguishable
from the paradigm in not showing the effects of
vascular insults in the shape of cysts of softening. The cerebellar
sclerosis of the case is fairly characteristic of paretic
cases. There is even a suggestion of atrophy in the temporal
region suggesting the so-called Lissauer’s paresis. Clinically
the case belongs in the classical grandiose group of paretics
(“O. K. No. 1 superfine”).
Vascular Neurosyphilis[35] is illustrated in a fourth autopsied
case. It may be noted that the pia mater in this case is
practically normal. The tissues outside the area of softening
due to the syphilitic thrombosis of nutrient vessels are practically
normal. The case was one of almost complete sensory
aphasia with word-deafness. The clinical picture is accordingly
quite distinct from those of the paradigm (1) and of the
case of general paresis (3) just discussed.
Juvenile Paresis[36] is illustrated by a case with exceedingly
extensive lesions, largely meningeal and parenchymatous.
The cerebral lesions are atypical since in places they suggest
the tuberous sclerosis of Bourneville. The brain atrophy is
extreme (965 grams) and it is possible that this apparent
brain atrophy was in part hypoplasia, since the spirochetosis
441of this case was doubtless congenital. However, clinically
the patient was fairly normal up to the age of 18.
A case of so-called Syphilitic Extraocular Palsy[37] demonstrates
a characteristic meningeal process more extensive
than the clinical symptoms would have indicated. In fact,
focal clinical nerve palsies are as a rule, if not constantly,
partial phenomena of a far more extensive process of neurosyphilis.
They are far more limited clinically than anatomically
and histologically. It seems at first sight improper
to term them cases of diffuse neurosyphilis in view of their
clinical focality, yet they are best described as partial cases of
diffuse neurosyphilis.
A case of Gumma[38] of the left Hemisphere is presented
which appears to have led to death in about four years from onset.
This case, like many others, is not an example of purely
focalized syphilitic process inasmuch as cysts of softening
indicating slight vascular insults are present elsewhere (pons).
There is also a degree of leptomeningitis, particularly basal.
Our discussion of the nature and forms of neurosyphilis
is completed by a rare case probably belonging in the so-called
cervical hypertrophic meningitis of Charcot but actually
due to a Gumma of the Spinal Meninges.[39] The importance
of therapeutic optimism is emphasized in this case as in
the paradigm. Theoretically the meningeal inflammation of
neurosyphilis ought to be almost entirely if not entirely
removed by therapy, and these two cases, like several others
in the series, seem to illustrate this possibility.
Neurosyphilis sometimes receives the clinical diagnosis neurasthenia
simply through omission to apply proved diagnostic
methods. An instance is given in which the Paretic form
of Neurosyphilis (“general paresis”) received the diagnosis
neurasthenia[40] for a period of five years, at any time during
which period it would doubtless have been possible to render
the correct diagnosis and apply treatment.
442Neurosyphilis may imitate not only the psychoneuroses
but also the psychoses themselves. We present a case of an
architect, which looked almost precisely like manic-depressive
psychosis[41] and had a history of attacks, but in which the
positive serum W. R. led (in accordance with hospital rules)
to an examination of the spinal fluid. The spinal fluid tests
proved the case to be one of Paretic Neurosyphilis.
However, a positive serum W. R., even when associated
with mental symptoms, and when those mental symptoms
include grandiosity, does not prove the existence of neurosyphilis
either in its paretic or non-paretic form. Our instance
seems to be one of Manic-Depressive Psychosis.[42]
The spinal fluid tests were entirely negative. The course of
the disease was also that of manic-depressive psychosis. In
the absence of positive spinal fluid tests, the diagnosis neurosyphilis
was excluded.
Neurosyphilis and even Paretic Neurosyphilis may
result in symptoms that would ordinarily lead to the diagnosis
dementia praecox.[43]
It is important not to rule out neurosyphilis on the ground
of a negative serum W. R. The fluid W. R. may turn out
positive. We present a case (of a salesman)[44] in which the
serum W. R. was repeatedly negative (even salvarsan did
not act provocatively) yet the spinal fluid W. R. proved
positive. The case was clinically one of classical Paretic
Neurosyphilis (“general paresis”). It is a good rule to proceed
to lumbar puncture, even when the serum W. R. is negative,
if there are suspicious symptoms (e.g., speech defect and
443memory impairment, grandiosity) or signs (e.g., marked reflex
disorder, especially pupillary disorder).
Diffuse Neurosyphilis was above defined as “meningovasculoparenchymatous.”
This disease is typically associated
with six positive tests (positive serum W. R., positive fluid
W. R., pleocytosis, gold sol reaction, positive globulin reaction
and excess albumin). One or more and frequently
several of these six tests are likely to run mild in diffuse
neurosyphilis; that is to say, these tests are apt to run milder
than the identical tests in paretic neurosyphilis (“general
paresis”). The clinical course of the diffuse, and especially
the meningovascular cases, is likely to be protracted. The
prognosis as to life is good, barring fatal vascular insults.
The illustrative case[45] was a case with slow course. There
was a series of attacks followed by a paralytic stroke, a finding
highly typical of the diffuse form of neurosyphilis. The
spinal fluid reactions were mild, suitable to the general principle
above stated.
These tests are likely to run stronger, as above stated,
in paretic neurosyphilis (“general paresis”), than in the
diffuse form. In particular, the gold sol reaction is likely
to be shown in what is termed “paretic” form rather than
in what is termed “syphilitic” form. The clinical course of
Paretic Neurosyphilis is likely to be brief. A characteristic
case[46] with very heavy globulin and albumin tests is
presented.
Taboparetic Neurosyphilis[47] (“taboparesis”) is clinically
a combination of the symptoms of tabetic (“tabes
dorsalis”) and those of paretic neurosyphilis (“general
paresis”). First comes the tabes dorsalis lasting often
for many years. Afterward follows a characteristic general
paresis. The ultimate paretic picture is likely to retain,
however, various characteristics of tabes. The laboratory
tests in the paretic phase of taboparesis are characteristic
444of general paresis and not of tabes dorsalis. The prognosis
after the paretic phase has arrived is that of general paresis.
The diagnosis of the neurosyphilitic forms would be easy
if these principles were always carried out to the letter.
The important fact is as follows: diffuse (that is, meningovasculoparenchymatous
neurosyphilis) may look like paretic
neurosyphilis (“general paresis”)[48] at certain periods of the
clinical and laboratory examination. This fact is of obvious
importance. The general prognosis of diffuse neurosyphilis
is regarded as good quoad vitam. The general prognosis of
paresis is bad. If, however, the differential diagnosis cannot
be rendered at particular phases of a given case, then no safe
prognosis can be offered in the individual case. In particular
no prognosis affecting the administration or non-administration
of modern systematic treatment can or should be
offered in these doubtful phases.
It is not always safe to exclude neurosyphilis even when the
fluid W. R. is negative.[49] Particularly in vascular neurosyphilis
the fluid W. R. and even all the other laboratory signs
in the spinal fluid may sometimes be negative. A positive
serum W. R. yields the correct pointer to diagnosis. Of
course, also in many cases of vascular neurosyphilis one or
more of the laboratory signs may be suggestive even when
the fluid W. R. is negative. Theoretically there may be
cases in which all the six tests are negative and yet the diagnosis
neurosyphilis be the correct one.
A clinically important sign in neurosyphilis is the so-called
seizures. These occur both in Diffuse Non-paretic Neurosyphilis[50]
and in Paretic Neurosyphilis.[51]
445Aphasia is likewise a symptom in both these forms of
neurosyphilis, namely, in the Diffuse non-paretic[52] and in
the Paretic form.[53]
The literature contains reference not only to seizures and
aphasia as characteristically paretic but also to remissions.
Remissions like seizures and aphasia are found in both the
Paretic[54] and Non-Paretic forms of neurosyphilis.[55] They
have important bearings on prognosis in all forms of neurosyphilis
and are of especial significance in the evaluation of
treatment. (Remissions coincident with apparent cure.)
So far we have been dealing with cases of neurosyphilis
in which there was no doubt of the existence of mental
symptoms. There are cases, however, in which although the
laboratory signs of neurosyphilis exist, proving beyond doubt
the existence of a chronic inflammatory reaction and allied
pathological conditions in the cerebrospinal axis, there are no
mental symptoms of neurosyphilis. We have called some of
these cases Paresis Sine Paresi[56] and present examples.
To illustrate complications we give a case of Paretic Neurosyphilis
with autopsy in which there were ante mortem
signs of Herpes Zoster[57] or, at all events, of a skin eruption
limited to the area of a thoracic nerve.
A case of Gumma of the brain[58] in which decompression
was warranted and performed is presented. The fluid W. R.,
as in many such cases, was negative; serum positive.
A case of Cranial Neurosyphilis (extraocular palsy[59]
without mental symptoms) showed a positive Wassermann
serum test and a negative spinal fluid.
446The laboratory reactions in Tabetic Neurosyphilis[60]
(“tabes dorsalis”) run somewhat like those of diffuse non-paretic
neurosyphilis and are accordingly milder than those
of paretic neurosyphilis. The fluid W. R. and the gold sol
reaction in particular are apt to run mild. The clinical course
of tabes dorsalis is well known to be protracted and the prognosis
quoad vitam is good except that we must always bear in
mind the possibility of vascular insults and complications
of a syphilitic origin in the rest of the body.
It is important to remember that Tabetic Neurosyphilis
is often quite atypical[61] clinically and may even show no
single symptom warranting the old clinical name locomotor
ataxia.
There are even cases in which the name tabes dorsalis is
not warranted in view of the fact that the lesions are not
low in the cord but are higher up (Tabes Cervicalis[62]).
A rare form of neurosyphilis is Erb’s Syphilitic Spastic
Paraplegia[63] against which one needs to consider a number
of non-syphilitic spinal cord diseases. Our case showed a
weakly positive serum W. R., a negative fluid W. R., and the
other tests of the spinal fluid were moderately positive.
Syphilitic Muscular Atrophy[64] is classified by Head and
Fearnsides both in their meningovascular group and in their
group of the so-called syphilis centralis. Our case affecting
in large part the small muscles of the hands in a teamster,
may be due either to spinal parenchymal lesions or to root
neuritis or to both.
It is a little extraordinary and very important that the
laboratory signs are apt to be positive even in the Secondary
period of Syphilis. Perhaps a third of all cases of syphilis in
the secondaries would, if tested, yield positives precisely
like those of full-blown paretic or diffuse neurosyphilis.
447Strangely enough, these signs may occur without clinical
symptoms. The illustrative case,[65] a mechanic, yielded various
mental symptoms. The cases of secondary syphilis with
laboratory signs of neurosyphilis but without clinical symptoms
are of the greatest theoretical importance in relation
to the problem above mentioned of paresis sine paresi. It
may well be inquired whether in some instances the neurosyphilis
of the secondaries does not persist until the exhibition
of mental or physical symptoms of neurosyphilis
years later. It must be remembered that this conception is
hardly more than a hypothesis at the present time. That
such signs of chronic inflammation could exist without
symptoms is not so surprising when one thinks of the startling
immediate improvement seen after treatment or even in
remissions without treatment. One is reminded of the crisis
in pneumonia wherein clinical improvement takes place entirely
independent of the mechanical conditions in the lung
which just after the crisis remain as suppurative as before.
The diagnosis of Juvenile Neurosyphilis is made upon
the same lines as that of neurosyphilis in the adult. We present
two cases, one with optic atrophy[66] and the other with signs
of congenital syphilis antedating the symptoms of paresis.[67]
Congenital syphilis is also apparently capable of producing
a simple form of Feeblemindedness,[68] that is to say, a form
of disease non-paretic, non-tabetic, and without special tendency
to vascular insults.
We present a case of Juvenile Tabetic Neurosyphilis
(“juvenile tabes”).[69] The tests were all positive.
The line of separation between typical and atypical cases
of neurosyphilis is vague and indistinct and some of the
448cases classified by us amongst puzzles perhaps belong under
systematic diagnosis and vice versa. The section on PUZZLES
AND ERRORS in the diagnosis of neurosyphilis is
introduced by six cases of error in the diagnosis of the paretic
form of neurosyphilis.[70] These errors were made known by
autopsy. Aside from the sixth case, whose etiology must remain
in doubt and which was a unique case of Perivascular
Gliosis, there is ground for the belief that the other five cases
in this Danvers Hospital study of diagnostic errors were perhaps
actually syphilitic though not of the paretic form of
neurosyphilis. At all events, the brain tissues in these cases
failed to show the plasma cell deposits which are characteristic
in the sheaths of the intracortical vessels in paretic neurosyphilis.
A case illustrates the complication of Tabes by arteriosclerotic
symptoms, in which case the arteriosclerosis may
naturally have been of syphilitic origin. Two cases especially
illustrate the possibility of confusing the ataxia of general
paresis with Cerebellar Ataxia. These cases showed
lesions of the cerebellar structures, notably of the dentate
nucleus. No one can read these cases or any of the autopsied
cases in our series, without perceiving how fundamental
and even critical is the demand for autopsies in fatal cases
of neurosyphilis. The practitioner who can secure an autopsy
in a fatal case of neurosyphilis and have the tissues worked
up by approved neuropathological methods is almost bound
to add his bit to neurological theory. Even cases of classical
tabes dorsalis are often signally important to the theorist on
account of the relations of the neural to the non-neural complications.
We then proceed to a group of cases without special order
in which a variety of diagnostic questions arose.
A case of questionable neurosyphilis in the secondary stage
of syphilis brings up the problems of syphilitic neurasthenia.[71]
449Syphilis may act as agent provocateur of Hysteria as
Charcot insisted.[72]
A case illustrative of difficulties in diagnosis between neurosyphilis
and manic-depressive psychosis follows.[73]
A case for diagnosis is given which shows that errors in
the diagnosis of neurosyphilis are entirely possible even when
abundant clinical and laboratory data are available. A case
with a weakly positive Wassermann reaction in the spinal
fluid finally turned out to be one of Brain Tumor.[74]
Some questions as to the diagnosis of Neurosyphilis versus
Idiopathic Epilepsy are brought up by a case in which phenomena
of paresis seemed to have occurred very early, about
two years after the initial syphilitic infection.[75]
A case of Paretic Neurosyphilis is offered in which
hemiplegia and hemitremor strongly suggested vascular lesions;
but the autopsy showed no coarse lesions and merely confirmed
the diagnosis paresis microscopically.[76]
An autopsied case of Paretic Neurosyphilis is given, in
which the pupils persisted in reacting normally. Herpes
zoster-like lesions in life yielded no special signs at autopsy
(all root-ganglia looked alike above and below zone of
“shingles.”)[77]
An example of Neurosyphilis, probably Paretic, yielded
symptoms highly suggestive of manic-depressive psychosis.[78]
An interesting feature in this case was the birth of a healthy
child nine months after the onset of the psychotic attack.
An example of exophthalmic goitre[79] following the acquisition
of Syphilis showed at autopsy a heavy scarring of
the optic thalamus and unilaterally atrophic process in the
cerebral cortex.
450We come to some questions concerning the Argyll-Robertson
pupil. It is agreed on all hands that the Argyll-Robertson
pupil is characteristic of the paretic and tabetic forms,
but the sign occurs also in other neurosyphilitic conditions;[80]
in fact the sign does not necessarily indicate neurosyphilis
as an instance of Pineal Tumor demonstrates.[81]
The question raised above as to the possibility that neurosyphilis
may exist in the absence of positive findings in the
spinal fluid is illustrated in a man, a mechanic, who claimed
syphilitic infection and showed an Argyll-Robertson pupil
on one side.[82] The serum W. R. was positive; the fluid tests
were negative.
An extraordinary case is given in some detail in which
Neurosyphilis in the form termed Disseminated Encephalitis[83]
proved fatal within seven months of the initial infection.
We have frequently mentioned the classical assumption
that paretic neurosyphilis (“general paresis”) is a fatal disease.
Some have suggested that there is another form clinically
almost identical with general paresis except that it pursues
a long course and the suggestion has been made that these
cases be termed pseudoparesis.[84] We are of the opinion that
this term should be dropped and advocate the use of the
word pseudoparesis only for non-syphilitic disease looking
like paresis, such as alcoholic pseudoparesis and the like.
The question whether there is a form of mental disease
Syphilitic Paranoia[85] is raised by a case with auditory hallucinations,
ideas of persecution and attacks of excitement.
The diagnosis of alcoholic hallucinosis was actually made although
there is no proof that the patient ever drank alcohol.
Alcohol may cause symptoms identical with those of
451paretic neurosyphilis, including seizures, Argyll-Robertson
pupils, speech defect and mental symptoms. The differentiation
is readily made by the negative laboratory findings.
An illustration is given in our case of the alcoholic teamster.
Cases such as this bear the name Alcoholic Pseudoparesis.[86]
However, when the clinical picture is the same as in the
case of our teamster, the alcohol may only be a complicating
factor in neurosyphilis, as shown by our next case of the
alcoholic steamfitter who in fact was shown to have Neurosyphilis.[87]
Sometimes cases of apparently frank alcoholism, even with
apparently characteristic delirium tremens and neuritis, prove
to be essentially neurosyphilitic.[88] On the other hand, true
combinations of Alcoholism and Neurosyphilis occur which
it would be proper to classify under either heading and in which
therapy must take serious account of both conditions.[89]
As above stated, we elect to use the term pseudoparesis only
for non-syphilitic cases. There are other forms of pseudoparesis
than alcoholic pseudoparesis. The question of Diabetic
Pseudoparesis is raised by an exceedingly complicated
case of which our best interpretation is that the patient, a
proved syphilitic (with syphilitic osteomyelitis (?)), a huge
doorkeeper, was perhaps suffering from an old Syphilitic
scarring of the Pituitary body.[90] Neither this case nor a
second case, one of Paretic Neurosyphilis with glycosuria
is actually entitled to the diagnosis diabetic pseudoparesis.
The second case of paretic neurosyphilis with glycosuria
brings up some unanswerable questions as to the pancreatic
or basal meningitic or other origin for the glycosuria.[91]
Isolated symptoms are often presented by neurosyphilitics
(e.g., hemianopsia);[92] but we tend to regard these cases as due
to focal lesions that are merely part and parcel of Diffuse
Lesions.
452A neurosyphilitic case (a steward) with the rather unusual
complication (for our northern region) of severe Malaria
producing cerebral thrombosis is reported.[93]
The diagnosis Dementia Praecox[94] was actually made in
the case of a young school-teacher in whom the laboratory
findings proved conclusively that the condition was one of
Neurosyphilis. The gold sol reaction in this case was mild.
The chief lesion at autopsy was a fresh looking, gelatinous
pial exudate over the spinal cord which turned out to contain
an almost pure display of very numerous plasma cells.
The question of Lues Maligna[95] is brought up in a rectifier
of spirits in whom the characteristic tremendous destruction
of tissue, toxemia and failure to react to antisyphilitic treatment
were illustrated. Moreover, this case had a trauma
(cautery) to the tonsil, as in other cases of lues maligna.
A case somewhat suggestive of brain tumor, of neurosyphilis
and of multiple sclerosis[96] turned out to be Multiple
Sclerosis (the fluid showed a pleocytosis and a moderate
amount of globulin with a paretic type of gold sol reaction).
As a foil to this case that we regard as multiple sclerosis,
we present a second case with nystagmus, optic atrophy and
spasticity in which the suspicion of multiple sclerosis might
well be raised but which the tests demonstrated to be
Neurosyphilitic.[97]
An even stranger imitation of well-defined non-syphilitic
entities was presented by a case apparently of Huntington’s
chorea[98] (except for absence of the hereditary taint) which
case, however, proved to the surprise of all diagnosticians to
be one of Neurosyphilis.
Frequent errors of diagnosis must occur in the field of the
senile psychoses. We present a case that would at first
blush warrant the diagnosis of senile arteriosclerotic psychosis[99]
453in a sea captain of 75 years (wife dead 15 years before of
general paresis) who turned out to be a characteristic case
from the laboratory standpoint of Neurosyphilis.
The Protean nature of the symptomatology of neurosyphilis
is sufficiently established. Still, a case that might fit into textbooks
concerning Dissociation of Personality[100] is certainly
a clinical oddity, as illustrated by a fugacious musician.
A case with strong suspicions of neurosyphilis of tabetic
type turned out to be more probably one of neural complications
in Pernicious Anemia.[101]
Neurosyphilis in Juveniles presents puzzling conditions.
One case was marked clinically by attacks of excitement.[102]
It is impossible to place this case among the main groups of
juvenile neurosyphilis.
Another case of Feeblemindedness,[103] also Neurosyphilitic
in origin, presented physical symptoms and laboratory
signs of paretic neurosyphilis; yet this case had been
considered one of simple feeblemindedness.
A case apparently of Juvenile Paretic Neurosyphilis in
a 15 year old boy presented the rather unusual complication
of shocks with quadriplegia,[104] a vascular complication not
usually expected in the paretic type of neurosyphilis in adults.
Epileptic phenomena[105] are rare as the effect of Juvenile
Neurosyphilis, but occur as demonstrated in a case which
slipshod methods of diagnosis might well have regarded as
one of idiopathic epilepsy.
A case of Juvenile Paretic Neurosyphilis with the
complication of Addison’s Disease[106] is given (autopsy
confirmation).
The puzzle in diagnosis offered by syphilis in the secondary
stage[107] is illustrated by a case which showed the characteristic
Neurosyphilitic complications of the Secondary Stage of
454syphilis. This patient may well have been a moron at the outset
and exhibited some reactions (refusal to talk) explicable on
the basis of feeblemindedness. She was a neurosyphilitic only
in the sense of the neural complication that we find in the
secondary stage of syphilis. As stated above, we do not yet
know what the fate of these neural complications of secondary
syphilis is to be. The frequency of this finding in secondary
syphilis is probably too great to warrant the hypothesis that
it must always go on to a chronic neurosyphilis; but we
certainly are warranted in regarding these cases as potential
chronic neurosyphilitics.
A case of Taboparetic Neurosyphilis in which the heavy
exudate characteristic of paresis became a soil for a growth
of the typhoid bacillus is presented with autopsy.[108] This
fatality with Typhoid Meningitis is merely a concrete example
of the many complications which syphilitics and especially
neurosyphilitics have to sustain.
The case series then goes on to illustrate, though quite
inadequately, a variety of MEDICOLEGAL AND SOCIAL
complications of neurosyphilis. It is well known that many
social complications with grave moral, economic and even
political difficulties occur.
Our series starts with a “public character”[109] whose eloquence
and reformatory efforts led to a considerable notoriety.
The autopsy in this case showed singularly few lesions
despite the fact that the case was microscopically one of
wholly characteristic Paretic Neurosyphilis. The question
might arise how far we are entitled to correlate the reformatory
efforts of this always eccentric character with syphilis.
The man himself a physician, was aware of the doubt which his
Argyll-Robertson pupils threw upon his medical situation.
He explained them on the basis of an old smallpox! We are
inclined to think that the whole of this man’s life, from his
giving up of medical practice to live as a kind of literary and
political hack, was due to subtle changes of neurosyphilitic
455origin. The fact that there was a certain delinquent streak
in the man is not inconsistent with this idea. Interestingly
enough, a fall on the ice in the man’s 61st year actually
started up the fatal process, a condition of affairs amply
illustrated in cases of neurosyphilis, brought out by trauma
that come to the attention of the Industrial Accident Board
in connection with claims for compensation.
A case of sudden grandiosity[110] illustrates an episode of
Neurosyphilitic origin. Such a person might well be regarded
by the lay newspaper reader as a crank or a grafter but
the neurosyphilitic possibility should always be entertained
in cases of this order.
As against the social difficulties that look in the direction
of the classical paretic grandeur, we present a case of apparent
suicidal attempt by gas, which attempt was followed by a
period of amnesia that, taking into account the laboratory
findings, was probably Neurosyphilitic.[111]
Vistas of extraordinary interest are opened out by studies
of the relation of neurosyphilis to delinquency. The case
of the psychopathic reformer (Case 83) above mentioned was
one in which the delinquency may possibly have been related to
acquired syphilis. We present also a case of juvenile neurosyphilis,
a young man of reform school type[112] in which Juvenile
Paretic Neurosyphilis was established. This patient,
in fact, deteriorated very rapidly to a condition of considerable
dementia a few months after the diagnosis was established.
A striking case of so-called Defective Delinquency is
presented, an alcoholic prostitute of the reformatory group.[113]
The Neurosyphilis in this case was a complication rather
than an original factor in the delinquency.
One case of Paresis Sine Paresi was that of an habitual
criminal[114] and forger who, without showing mental or physical
symptoms of neurosyphilis, yielded the laboratory signs of
paretic neurosyphilis. Again, as in the case of the prostitute
456just mentioned, the Criminality[115] seems to have antedated
the neurosyphilis and even to have been hereditary.
By way of introducing the next group of Industrial Accident
Board cases, we present a case of Juvenile Paresis
with initial Traum.
The Industrial Board group is of note in that the signs of
the traumatic form[116] of paretic neurosyphilis do not occur
immediately upon the accident. Some time elapses in which
the physical, chemical or parasitological changes have time
to work themselves out in the injured tissues. Many hypotheses
may be raised as to the reason why a trauma lights
up a syphilitic process. Of course, false claims[117] may be
made for compensation by neurosyphilitics in whom the
symptoms were already in existence before the accident and
in whom they may not even be markedly exacerbated by the
accident. The false claimants can probably not readily
frame a story which the expert psychiatrist cannot discredit
if he is allowed to perform laboratory tests and give the patient
the benefit of thorough examination. However, some cases
of established Paretic Neurosyphilis are perhaps truly
subject to exacerbations[118] of the clinical process and it may
well be held that such exacerbations warrant partial compensation.
The fact that a trauma may light up a syphilitic process
is illustrated in a case that came to the Psychopathic Hospital,
in which a Syphilitic Lesion developed in the skull at the
Site of Skull Injury.[119]
A case of Occupation-neurosis[120] that might be interpreted
as a syphilitic neuritis is presented. The case is still in doubt
as to its scientific evaluation.
The workmen’s compensation group of syphilitic cases is
of extraordinary general interest since it indicates that
457employers may well be on the lookout not to employ known
syphilitics unless fortified by special insurance arrangements.
Whether in future employers may desire to employ only W. R.
negative workmen is one of the highly complicated questions
re workmen’s compensation and health insurance.
But the problems of neurosyphilis are not merely medicolegal
and broadly public or social. The most appealing difficulties
lodge within the bosom of the family. Now and
then a case of Incompatibility of Temperament, perhaps
complicated by alcoholism, occurs which tests prove to be
Neurosyphilitic.[121]
Special attention should be drawn to a certain Neurosyphilitic
Family[122] in which both parents and five children
showed a variety of syphilitic diseases, including syphilis
without apparent neural complications, paretic neurosyphilis,
juvenile paresis, aortic aneurysm, achondroplasia and caries
of the spine, and an as yet indefinite neurosis. There was a
sixth child that died shortly after birth, as well as three stillborn.
One cannot conclude from the normal[123] look of a neurosyphilitic’s
family that the normal-looking members are not
syphilitic, as illustrated by the family of our draughtsman.
The most intricate social complications may arise. We
present a case of a syphilitic man (a well-to-do merchant)
who was apparently being goaded into a second marriage[124]
because he was continually being charged with having caused
his first wife’s death. This he had actually done in a certain
sense because his wife had died of general paresis, having
contracted syphilis from him.
In the fifth section on THERAPY, we have attempted to
outline some of the principles and problems that arise in the
treatment of neurosyphilis. Enough has probably been said
458concerning the attitude of optimism or pessimistic nihilism
that may be adopted toward the whole subject. It must be
borne in mind, however, that a great deal of the work on
treatment of neurosyphilis is still in the experimental stage.
As a rule, each case must be considered separately and individually
and the prognosis can be made satisfactorily only
after treatment has been given. This section contains a
group of cases that have been treated rather intensively and
the results of this treatment are indicated. The section is
introduced by five untreated cases, the brains and cords of
which have been studied post mortem. These illustrate the
pathological conditions which we have to meet, and from
these examples we can draw the theoretical conclusion that
some cases are beyond the aid of therapy on account of the
brain destruction. Others, in which the symptomatology
bespeaks just as grave a situation, turn out on autopsy to have
very little actual damage to the brain tissues and therefore
should theoretically at any rate be amenable to antisyphilitic
therapy.
In order to get any adequate conception of the possibilities
of therapeutic results in cases of neurosyphilis, one must
consider the pathological changes that occur and how far
these changes are reparable. In cases in which the destruction
of tissue is marked, it is, of course, out of the question to
expect to get any marked clinical improvement. A case of
spastic hemiplegia[125] in paretic neurosyphilis is given with the
autopsy findings as an illustration of irreparable damage
that may occur to the parenchymatous structure, thus precluding
any chance of functional recovery.
On the other hand, there is a group of cases in which the
symptoms may be exceedingly severe and yet the actual destruction
of tissue be almost nil. This point is illustrated by
a case[126] in which total duration of symptoms terminating in
death was only 22 days. At autopsy there was very little in
the way of macroscopical lesions, and microscopically there
was no marked evidence of destruction in the parenchymatous
459tissue. The lesions were represented chiefly by perivascular
infiltration. According to all our modern ideas, this type of
reaction is resolvable under antisyphilitic treatment. Though
this case was one of very short duration, similar pathological
pictures may be obtained in cases of considerably longer
standing. It is also of great importance to remember that
symptomatically such a case may be in no way distinguished
from a case with marked atrophy.
Another autopsied case is given which shows an exceedingly
marked meningitis.[127] The meningitic processes according to
the literature and experience react very readily to antisyphilitic
treatment in the form either of mercury and iodid or in
combination with salvarsan. The lesion here present would
probably have improved had intensive treatment been given.
Clinically the diagnosis of general paresis was made and, as
has been the rule in the past, treatment was not given on
the ground that it had no value in paresis. While this is an
extreme case of meningitis, it is to be remembered that the
vast majority of cases of paretic neurosyphilis show some degree
of meningitis. Just as in the marked meningitis of the
diffuse neurosyphilis, so with the meningitis of the paretic
form, improvement is expected under treatment. As a part
or even the whole of the symptomatology in a given case may
be due to this meningitic process, we have reason occasionally
to expect marked improvement as the result of antisyphilitic
treatment.
As a contrast to this case with marked meningitis, another
case of marked atrophy[128] is given. Here the atrophy was very
perceptible on macroscopical examination and the mere view
of the brain at once indicated that in such a case important
results from treatment were not to be expected.
The topographical variation of the lesions in neurosyphilis
must be remembered when treatment is to be instituted.
Thus very marked lesions may exist in portions of the brain
which do not give any very definite localizing symptoms. As
a result, one may be led to believe from clinical evidence
that the case is a very mild one though the lesions may
460really be very extensive. The topographical distribution
must, therefore, be taken into consideration in trying to
estimate the damage done. This point of topographical distribution
of the lesions is illustrated by a case.[129]
It has been generally recognized that clinical improvement,
if not cure, may be readily obtained in the group of diffuse
neurosyphilis, i.e., so-called cerebral and cerebrospinal forms
of syphilis. These are cases in which the parenchyma is very
slightly, if at all, affected and in which the lesion is chiefly
in the meninges and blood vessels, irritative rather than
degenerative. A case[130] is given to illustrate this point. In
our experience systematic intravenous salvarsan therapy
associated with mercury and iodid gives remarkably good
results in the vast majority of this group of cases.
It is generally conceded that antisyphilitic treatment,
particularly salvarsan, has a very satisfactory result applied
to diffuse neurosyphilis. But the same good results may be
obtained in cases which are not so typically of the diffuse
type. An illustration is given in the case of a machinist in
which the diagnosis was in doubt between paretic, tabetic or
diffuse neurosyphilis.[131] The result of treatment was as satisfactory
as could be expected in any type of neurosyphilis
and this in a case of several years’ duration with Argyll-Robertson
pupils.
As a rule, the Argyll-Robertson pupil is taken as a grave
omen for treatment, an idea based upon a conception that
the Argyll-Robertson pupil so frequently represents the old
so-called “parasyphilitic” cases, which, in the past were
taught as being incapable of improvement by the ordinary
antisyphilitic methods.
A second case[132] with Argyll-Robertson pupil shows again
that the prognosis may be very good despite the Argyll-Robertson
sign.
461But even in the diffuse neurosyphilis, the symptomatic results
of treatment may not be entirely happy. Under treatment
it may be possible to reduce the spinal fluid tests to
negative without, however, as in the case of our hemiplegic
lady,[133] making the physical or mental symptoms disappear.
In other words, it may be possible to stop the active progress
of the disease without removing the symptoms.
One is always warned of the danger of intravenous salvarsan
therapy in hemiplegic cases due to arteriosclerotic conditions.
While this warning is well justified, it does not mean that the
most intensive treatment is contraindicated, as shown in the
case of our hemiplegic machinist.[134] Such may be given over
long periods of time with the most satisfactory results.
A case[135] is given which illustrates the value of antisyphilitic
treatment in cases showing symptoms of intracranial pressure
due to syphilitic disease. In the case of the woman which
we cite, we believe that the symptoms of intracranial pressure
were probably due to a gummatous new growth, although it is
possible that they were due to a marked meningitic process.
However, the results of a limited amount of antisyphilitic
treatment in this case were very brilliant. Similar results
may often be obtained in gumma of the brain. This is not
always true, however, and it may become necessary to use
surgical procedure in order rapidly to overcome the effects of
intracranial pressure.
While it has always been conceded that treatment would
greatly help cases of diffuse and vascular neurosyphilis, the
utmost pessimism has existed concerning the results to be
obtained by treatment in cases of tabetic and paretic neurosyphilis.
Only in the last five or six years, due to the stimulus
of Ehrlich’s discovery of salvarsan and the introduction of the
intraspinous methods of therapy, have intensive work and
study been given to the treatment of these cases. And though
it has been by no means settled in the minds of the various
workers in this field, as to what the ultimate results of such
462treatment will be and though some do not believe that there is
any good to be expected from our present methods, still the
majority of men who are treating these cases systematically
feel very much encouraged.
At times very brilliant results are to be obtained by intraspinous
treatment in tabetic neurosyphilis (“tabes dorsalis”).
A very striking illustration is given of a case of
this sort in which the symptoms dated only a few months but
which had all the classical symptoms, signs and laboratory
tests. Five intraspinous injections of mercurialized serum
were sufficient to cause the disappearance of the subjective
symptoms and to reduce the spinal fluid test to negative.[136]
It must be emphasized that the best results in cases of
tabetic neurosyphilis are usually to be expected in cases in
which the symptoms are of short standing. Where the process
is of long duration and much destruction of spinal cord
tissue has occurred, the best one can expect is that the activity
and progress may be halted. This is illustrated by our
case of a baker, 43 years of age, who had been suffering from
the symptoms of tabes for some years. Under treatment it
was possible to get an entirely negative serology of the blood
and spinal fluid.[137] Despite this evidence that the activity
of syphilis had ceased, the symptoms continued unabated.
We are ready to believe, however, that much good was accomplished.
For the patient should not have any further
untoward developments or the appearance of any new
symptoms. These, without such treatment, might well be
expected. At times excellent clinical results are obtained in
long-standing cases.
The results of treatment in paretic neurosyphilis (“general
paresis”) have been considered even less hopeful than in
tabetic neurosyphilis (“tabes dorsalis”); indeed, it has
often been stated that the patients are made worse by
treatment. Recent work, however, supports a much more
optimistic viewpoint. We feel that intensive treatment has
been of the greatest value in a number of cases of paretic
463neurosyphilis. Two cases are given which show the most satisfactory
and brilliant results of intensive intravenous salvarsan
therapy in cases diagnosed as general paresis. The first case,
an excellent salesman, 46 years of age, with most aggravated
mental symptoms, recovered symptomatically and all his
tests were rendered negative.[138] He has now remained entirely
well and economically efficient for about two years without
further treatment. The other case,[139] a housewife, also with
very marked symptoms suggestive in all ways of general
paresis, also recovered rapidly under treatment and her
tests became negative. Her remission has now lasted for
nearly three years without further treatment.
At times it is not possible to get the spinal fluid tests to
become negative in cases of paretic neurosyphilis under the
most intensive salvarsan therapy. In spite of this, the
clinical condition of the patient may improve so greatly that
the patient can be considered clinically recovered. An illustration
is given of an undertaker[140] who was brought from a
condition of the greatest cachexia and mental confusion to a
condition of robust appearance and mental efficiency under
intravenous salvarsan therapy, in spite of the fact that his
tests were very slightly if at all reduced in intensity. He
has been able to resume his former occupation and his former
life with great satisfaction to himself and his family.
Improvement in paretic neurosyphilis under treatment is
not to be expected very early. Two or three months of
active treatment may elapse before one sees signs of improvement.
Indeed, as illustrated by our case of the shipping clerk,
this improvement may begin to make its appearance only
after more than four months of intensive treatment consisting
of two injections of salvarsan per week.[141] In spite of the long
delay in this case, complete clinical recovery occurred and the
tests became almost negative at the end of a year of treatment.
464It is not only in the central nervous system that the
syphilitic process may resist the most intensive treatment.
In the case of the speculator, a victim of paretic neurosyphilis,
which we cite, a perennially recurrent iritis appeared after
several months of the most intensive salvarsan treatment
which was apparently sufficient to reduce the symptoms of
the paretic neurosyphilis,[142] but not of non-neural syphilis.
We give the case of a charwoman having the diagnosis of
paretic neurosyphilis, who, under intensive treatment, made a
symptomatic recovery. The interesting point in her findings
is that all the tests in the spinal fluid became negative except
the gold sol reaction which remained of the “paretic” type.[143]
There is no general rule as to the reaction of the spinal fluid
tests under treatment. At times one test is the first to disappear
under treatment; again it is another. We have seen
many cases in which the gold sol was the first test to become
negative and others, as the case given, in which it is the last to
show any change. As in our undertaker, symptomatic clinical
improvement may be practically complete without any
change in the spinal fluid tests.
One must remember that it is the condition of the patient
that is of first importance; not so much the laboratory tests.
Having shown the clinical recoveries with the tests remaining
positive, we now have to report two cases in which there
was improvement as shown by the tests but no clinical improvement.
The first patient, a bank teller[144] of 39 years, with
a diagnosis of paretic neurosyphilis, received intensive intravenous
salvarsan for several months. Under this treatment
all the tests became negative except the gold sol which remained
of the paretic type. In spite of this, there was not
the slightest improvement in his mental condition.
The second case, a young man of 29 years in whom the symptoms
of neurosyphilis had recently appeared, under treatment
showed a marked diminution in the intensity of the spinal
465fluid tests, notwithstanding which the patient became more
and more demented and died after a series of convulsions.[145]
Of course, good results indicated above in some of our cases
of paretic neurosyphilis are not to be expected in every case
no matter how intensive the treatment. We give a case of
paretic neurosyphilis in which the most intensive intravenous
salvarsan therapy gave no satisfactory results. This was
followed by several intraventricular injections of salvarsanized
serum. The results of this combined treatment, however,
were still not satisfactory, and the patient died.[146]
In order to emphasize as strongly as possible what we believe
is a great advantage of systematic intensive treatment
for neurosyphilis, we offer two cases in different time periods
of neurosyphilis. The first is a printer with the symptoms of
diffuse neurosyphilis six months after the appearance of his
chancre.[147] These symptoms appeared despite three injections
of salvarsan, injections of mercury and mercury by mouth.
Under intensive treatment (meaning injections of salvarsan
twice a week and continued injections of mercury), complete
recovery occurred in a few weeks.
The second case is that of a waiter with signs and symptoms
of neurosyphilis in whom the diagnosis lay between the diffuse
and paretic forms.[148] This patient developed his symptoms
in spite of continuous antisyphilitic treatment during the six
years since his infection. This treatment had been comparatively
mild, consisting in great part of mercury by mouth.
However, he had had courses of injections of mercury and
several injections of salvarsan. Under a systematic course of
intravenous injections of salvarsan twice a week for a number
of months, all symptoms disappeared and the spinal fluid tests
became negative as well as the W. R. in the blood serum.
A final case is offered which indicates that antisyphilitic
treatment may occasionally be of service in improving the
mentality of a Feebleminded Congenital Syphilitic.[149]
466No attempt has been made in this section to give a per
cent evaluation of the results of treatment in any one group of
neurosyphilis. Two charts (charts 25 and 26), however, are
appended which give an indication of some of our results. It
seems to us, however, that it is too early to make any definite
statements as to how far treatment will take us in the groups
of neurosyphilis. We do feel decidedly, however, that many
patients, in whatever group of neurosyphilis the diagnosis
may place them, will respond to intensive systematic antisyphilitic
treatment. It is unfair to give an entirely grave
prognosis in any case of neurosyphilis until the effect of
treatment has been tried.
In a separate section, entitled NEUROSYPHILIS AND
THE WAR, we have presented fourteen cases selected from
British, French and German writers in the war literature of
1914–16. Most of these cases were naturally somewhat inadequately
reported under the critical conditions of literature
made in the war. We present the cases for what they are
worth: at all events they draw attention to the extraordinary
interest of the neurosyphilis problem in relation to the war.
Such cases as A, one of tabes dorsalis apparently developing
paresis by a process akin to shell-shock, is of value in the
interpretation of the development of paresis in civil life.
By “shell-shock” we commonly refer to a condition in which
there is no actual traumatic injury of the brain. The hypothesis
must be then that the explosion in some way indirectly
caused an alteration of living conditions of the spirochetes,
permitting the development of paresis.
Case B similarly seems to be a case in which a latent syphilis
has turned shell-shock into tabes dorsalis.
Cases C, D, E bring up the question of aggravation of
neurosyphilis by service and on service, respectively.
Case F likewise shows how, in the determination of amount
of pension, the probable duration of the neurosyphilitic process
is important.
Case G seems to show that war stress alone, without the
emotional or physical effects of shell-shock, may kindle a
latent syphilis into paretic neurosyphilis.
467Case H similarly suggests that the “gassing” process may
effect the same result.
Case I seems to show that the neuropathically tainted
person may have latent epilepsy brought out through syphilis,
the syphilis in this case having been acquired during the first
summer of the war.
Case J was an interesting case of a syphilitic who, after
the stress of the Battle of Dixmude, became an epileptic.
Syphilitic root-sciatica was developed in Case K at work
in the war zone.
Case L is one of a civilian who apparently would not have
developed paresis at precisely the moment when he did, if
he had not been discharged as a German Jew from his long-held
bank position in London.
Two cases, M and N, are cases of shell-shock, non-syphilitic;
yet the picture of paresis in the one case and of tabes
in the other was for a long time almost convincing to the
examiners. They are better termed cases of pseudoparesis
and pseudotabes, using the prefix “pseudo”, as usual, to
signify a non-syphilitic imitation of the disease in question.
To sum up in the most general way the lessons of this
book, we may emphasize again (1) the unity-in-variety of the
phenomena of neurosyphilis, (2) the value of a hopeful approach
to the therapy of all cases of neurosyphilis, even the paretic form,
and (3) the value of applying syphilis tests to every case of neurosis
or psychosis.
(1) Re unity-in-variety of neurosyphilitic phenomena.
The unity of these phenomena is confirmed, theoretically,
by the common factor of spirochetosis: practically, by the
Wassermann reaction, positive in serum or spinal fluid! Almost
at this point the unity of phenomena ceases. Neither
chronicity, nor evidence of mononuclear cell deposits, nor
evidence of serious structural damage to the nervous system,
nor presence of other positive tests than the W. R.,[150] nor
468existence of mental or nervous symptoms or signs, is a common
feature of neurosyphilis. Sometimes the nervous system
appears to harbor spirochetes in the most cordial manner as
guest-friends (paresis sine paresi.) Again, perhaps as an
expression of elaborate processes of immunity, the spirochetes
take effect in relatively huge gummata. Sometimes
the neurosyphilitic process rises as if by a regular process of
siege from spinal nerve-root to spinal nerve-root (tabes
dorsalis and diffuse neurosyphilis). Again, the nervous
system is taken by storm, as it were (disseminated encephalitis).
Very frequently the neurosyphilis is simply an indirect
effect of blood-vessel disease, and huge masses of
tissue are scooped out in necrosis with dependent secondary
degenerations; and later the extinct lesions of vascular origin
may or may not betray evidence of their syphilitic origin.
Sometimes diffuse processes run on, apparently, with perfect
fatalism to a mortal issue in a few years both with and without
treatment. Again treatment appears to accomplish much
(see fuller discussion under 2). The laws governing the preference
of processes to lodge in membranes, vessels, and
parenchyma, and in all combinations of these, have not been
worked out. Hardly a case of neurosyphilis, properly studied
ante mortem and post mortem, but would throw important
light on our medical approach to one of the great problems
of civilization, the problem of syphilis as a whole.
(2) Re value of a hopeful approach to the therapy of neurosyphilis.
The prognosis of neurosyphilis is not worse than that of
the chronic diseases in general. In fact, the prognosis of
neurosyphilis quoad vitam is either good or dubious, certainly
not bad. The surprising reversals of form which the spirochete
shows in certain remissions are always to be awaited.
Treatment of neurosyphilis has certainly effected amazing
results, not so much by way of Ehrlich’s therapia sterilisans
magna as by means of systematic intensive treatment.
Even paretic neurosyphilis (general paresis) seems to have
been cured. Preparetic phases are theoretically hopeful.
Nor is it so certain that paretic neurosyphilis will ultimately
prove a perfectly distinct species of neurosyphilis. General
469paresis seems to us at least to be more closely related to diffuse
neurosyphilis than is tabes dorsalis to diffuse neurosyphilis.
In any particular case, moreover, during a good part of the
early months or years, it is difficult or impossible to tell the
paretic from the non-paretic forms of diffuse neurosyphilis
by any combination of clinical observations and tests. In
the instance of more protracted neurosyphilis, e.g., tabetic,
the outlook for vascular complications is such that antisyphilitic
treatment directed at prevention of these complications
is scientifically warrantable, even if the tabetic process itself
proves unassailable. The old distinction of syphilis and
parasyphilis, so striking and apparently satisfactory when
introduced by Fournier, seems to be a false distinction which
should be dropped. Therapeutically, we should approach
all cases of neurosyphilis without bias or nihilistic prejudgments.
(3) Re universal applicability of syphilis tests in nervous
and mental cases.
The importance of putting every neurosis or psychosis
through syphilis tests is not based alone on the frequency of
neurosyphilis, though neurosyphilis is surely frequent enough.
The importance of universally applying these tests is established
by the experience of lingering doubts both in the physician’s
mind and (nowadays increasingly) in the patient’s
and friends’ minds, so long as these tests are not applied.
Nor should the positive serum Wassermann reaction fail to
be followed by lumbar puncture and appropriate tests. The
general practitioner confronting neuroses or psychoses—and
what practitioner does not?—must not expect valuable
results from consultation with neurologists and psychiatrists
when he does not carry to these specialists the results of at
least the serum W. R. in his patient. Not only are practitioners,
specialists, and patients subject to discomfiture on
the eventual and delayed proof of syphilis or neurosyphilis,
but valuable time has been lost to treatment. How often
the physician of yore (and really not so long since) had to be
regarded as an eccentric virtuoso if he tested urine as routine!
Well, for routine use in nervous and mental diseases, the
Wassermann serum reaction is at least as important as urinalysis.
470Nor would we cease our homily with the general
practitioner. We know neurologists and psychiatrists who
use the Wassermann test only when it is likely to be positive!
But they are dying out.