Under the caption of sexual anaesthesia will be treated here
not only the deficiency of sexual emotion or the absence of the
sexual feeling, i. e., the impotence of voluptas or the lack of
erotic desire, but all other deficiencies, declines or abatements
in the realm of sex, such as absence of experiencing satisfaction,
impotency of copulation and of propagation.
Etiology of male impotence.—In the etiology of impotence
three main causes must be taken into consideration. Impotence
is almost always met with in congenital or acquired malformation.
Such anomalies lie more in the province of surgery
and need not be considered here any further. Impotence is
also found as a symptom in certain constitutional diseases. The
patients suffering from these troubles, are seeking medical advice
more for their causative anomaly than for the symptom of
impotence, which in these cases is of secondary importance.
Hence the consideration of these cases may also be omitted.
The anomaly of impotence par excellence and for which medical
advice is mostly sought is nervous impotence. This impotence
from nervous collapse is the commonest and complicates all
other kinds.
The patients of this class have always been normal in their
sex-life. Suddenly, one day, they find themselves impotent.
The cause of this kind of impotence is, in the majority of
cases, sexual excesses, and four different kinds of excesses may
be taken into consideration, excesses in copulation, in masturbation,
in mental erethism, or commonly called day-dreaming,
and finally excesses in tactile eroticism, or the common sexual
dalliance or caresses of young lovers.
Copulation excesses.—During coition all the parts of the
genital apparatus are in a state of extreme congestion. If
such congestions are too often provoked they have a more or
less deleterious effect upon the organs. Especially the colliculus
and the prostatic portion of the urethra are affected by such
repeated congestions. While the other parts assume their normal
state soon after ejaculation and the cessation of erection,
the colliculus remains still in a state of turgescence for some
time. Now, the prostatic urethra is very rich in sensible
nerves, and by its congestion all the generative organs are kept
in a state of erethism. The irritation of this area is also
capable of deranging the spinal genital centres. It either increases
excitability and causes ejaculatio praecox, or it decreases
excitability, and erections are no longer evoked.
Besides affecting the special nerves, the repeated orgasm,
through the mental vertigo, the muscular convulsion, the cardiac
and respiratory excitement, must lead to nervous disorders. As
a matter of fact, venereal excesses are followed by malaise,
nervousness, mental depression, lassitude, fatigue, satiety, heaviness
in the head, disposition to sleep, dulness of intellect, indisposition
to exercise, want of decision, regrets and ill humor,
and the other symptoms of general neurasthenia.
Masturbatic excesses.—Still excesses in copulation are not
so harmful as excesses in masturbation. In the first place excesses
in copulation are self-limited. Indulgence in intercourse
requires the consent of the partner, and where a second person
is needed, there is always a limit put to the will of the first
party. Furthermore, excesses in coition require each time a
complete erection, and abused nature will finally deny erections.
If the young and vigorous individual should in the beginning
be able to command quite a number of erections in one night,
after a certain time, he will be glad if he could have one complete
erection during a night, or even once a week. In this
way Nature herself regulates such excesses and takes care that
“the trees should not sweep the stars down.”
The case is different with masturbation. No limit is set
here to the excesses. Self-abuse does not require cooperation
of a second person, and what is of more importance, erection
is not requisite. Thus even Nature is here powerless. Hence
when there is a propensity to masturbatory excesses, there is
nothing to prevent the individual from abusing its favorite
pastime.
Besides the harm to the greater frequency, excesses in masturbation
offers additional injury through the youth of the
individual. Copulation excesses are indulged in by individuals
after puberty, i. e., by persons with fully developed generative
organs and in full virility. The practice of masturbation, on
the other hand, is often begun by mere children, before the
genital organs have had time to fully develop, and it is easily
seen that excesses will cause greater damage to these undeveloped
organs. Hence when young individuals are given to
inordinate masturbation, they harm the organs in a higher
degree than excesses in copulation.
Furthermore, ejaculation in masturbation is forced through
purely local manipulation. There is only a local excitation of the
nerves. The help of the psyche and phantasy is missing, and
the lumbar centres are tasked to the utmost. When the masturbator
tries to supply the psychic means, he relies on the
fertility and the extravagance of the lewd images which he
presents to his mind to increase the libido. Hence masturbation
is more injurious because it is generally effected through
the influence of an exalted imagination.
Very soon the masturbator discovers that visions, once sufficient
to produce the requisite excitement, have lost their power,
and that the images need to be of a more extravagant salacity.
In this way, the masturbator accustoms himself to extraordinary
means of sexual gratification, so that attempts of normal copulation
are no longer successful. When he attempts coition, he
finds that reality is so much less than his imagination has led
him to believe and that it is incapable of rousing his appetite.
Another injury done to the character of the masturbator
is the guilty conscience. Almost every masturbator seems to
feel that his acts degrade his manhood.AR He seems to know
by intuition that his practice is injurious to his health and is
morally wrong, because it is not in accord with the general
plan of the creative power in the universe. Still in spite of
himself, he continues to indulge in it. The will seems to have
entirely lost its control. The masturbator is thus engaged in a
conflict between moral conviction and sensual indulgence. Herein
lies one of the most harmful effects of masturbation. It is
undermining the individual’s will-power and destroying his
character. Every masturbator resolves again and again, after
each exercise, to resist henceforth the inclination and to overcome
the temptation,AS each time with the same futile result.
A paralyzing sensation arises in him, a feeling of shame and
self-contempt overtakes him, because he has again failed to
show enough energy, has again been too weak to resist the
impulse. Finally these disturbing and paralyzing sensations
give rise to the conviction of his being lacking in will-power
and to the feeling of being generally deficient in everything
else in life. In this way, excesses in masturbation harm the
generative organs not only directly but also indirectly by first
injuring the individual’s entire nervous system, and the different
kinds of impotencies are only symptoms of the general
neurasthenia.
Mental erethism.—The other kind of sexual excesses, those
of mental erethism and frustrate eroticism, are even more harmful
than excesses in copulation and masturbation.
By mental erethism or, as it is generally called, or rather
misnamed, mental masturbation, is understood the filling of
the phantasy with lascivious pictures. The dreamers give themselves
up to sensual thoughts, allowing the mind to dwell constantly
on sexual ideas, or erotic subjects of connubial enjoyments,
conjuring before the unruly imagination extravagant and
voluptuous visions and bawdry portrayals. The mind is fixed
on images of individuals of the other sex, all in lustful positions,
on pictures of the nude and of their genitals and of
couples in actione coeundi.
The voluptuous day-dreamers, not needing material manipulation,
may busy themselves with their favorite thoughts while
seemingly conversing with their friends or on the most solemn
occasions, as when listening to a sermon, etc. These erogenous
thoughts, these libidinous images, these constant broodings on
sex-matters create a habit which secures such a hold upon the
individual that he cannot overcome it. The habit becomes so
rooted in some instances that it is impossible for the patients
to free their thoughts from fancies and pictures of lustful situations,
while alone. Not even with the greatest efforts are they
able to rid themselves from imagining erotic scenes of various
kinds. Their minds are constantly preoccupied with a single
engrossing subject to the exclusion of all other topics and are
perpetually turned on sexual subjects, so that they are unable
to concentrate their attention upon any other matters.
These perennial broodings on sex subjects keep the genital
organs in a permanent state of sexual excitation and erethism.
While in masturbation the material congestion of the generative
organs is removed with each ejaculation, in mental erethism
relief by ejaculation is missing. In the first stage of the vicious
habit, the morbid mental lubricity and the lascivious unlicensed
thoughts may occasionally provoke an ejaculation. But later
on, when the genitals have undergone a certain weakness, ejaculation
is not brought on any longer by these images, and the
genital organs remain in a continual state of material congestion
and nervous tension. In this way not only the colliculus
and prostratic urethra, as in excesses of copulation and masturbation,
but all the genital organs are in a state of chronic
inflammation, which in time becomes the cause of impotence.
Tactile eroticism.—Worse than mental erethism is tactile
eroticism. By tactile eroticism is understood, keeping the
genital organs constantly irritated by dalliance with individuals
of the other sex, stopping short of the act of copulation. On
a walk through the city parks, any summer evening, or on a
trip on the Sunday excursion boats, young men and women
may be observed lying in each other’s arms in a continual
caress, kissing, hugging, and fondling each other for hours,
scarcely confining themselves within the limit of decency. These
couples are actually exercising the sexual act, although they do
not obtain sexual congress. These tremors and ecstasies, these
amorous ardors and intoxications, these sensual joys which
stimulate with rapture the higher centres and infuse the mind
with sexual gratification, are all a part of the chain of the
sexual act. The interruption of this chain of impulses short
of copulation may satisfy the moral conscience of the young
people, but it does not make such excesses less injurious. On
the contrary, the generative organs are deprived of the relief
which ejaculation lends to these organs. The genital tube remains
surcharged with blood, and the hyperaemia subsides but
slowly. The normal outlet of the sex-activity has been cut off
by a special process of repression. If these frustrate stimulations
are frequently repeated, they perpetuate the genital congestion,
and through the retention of the secretions, a catarrh
of the genital organs ensues, just as inflammations often originate
in the mammary glands through the accumulation of the milk
after weaning the child.
These perennial congestions are the cause of prostatic inflammations
not seldom met with in young men who never
were infected by gonorrhoea. The ulcerations of the cervix
so often found in young girls and young mothers of one child
may often be attributed to no other cause than to frustrate
eroticism in the young girls and to onanismAT in the young
mothers. The cervix is damaged in the same way as the soil,
burned by the sun, in the absence of a beneficent rain, cracks
and slits.
The frequently repeated engorgements of the blood vessels
which do not receive the normal physiological relief by ejaculation
provoke in both parties an exaggerated sex-sense and
produce the emotions, known as satyriasis in men and as
nymphomania in women. The exaggeration is followed later
on by exhaustion of the libidinous impulses, and the men become
hypochondriacs and impotent and women neurotic and
shallow.
The continual congestion in the genitals causes also a continued
feeling of heaviness and discomfort in the lower abdomen.
Urination becomes frequent in both sexes, and in women menstruation
is irregular. The patients complain of profuse pains
in the back, legs, sides, and of weakness, nervousness and sleeplessness.
These troubles cause general debility and a complete
breakdown of the nervous system.
The generative centres are particularly damaged by the
constant congestion of the genitals. The frequent stimuli keep
the lumbar centres in a condition of constant irritation. The
nervous system, presiding over the function of erection, thus
becomes worn out and exhausted, and the nerves do not respond
even to the strongest stimulations, which would otherwise set
them in action. In this way, the centres get accustomed, so to
say, of not responding any longer with erection to the proper
stimuli, or in other words, the consensualism between the genital
nerves and their centres is broken.
Hence, besides the harm done to the nerves by the general
debility, there is great damage done to the genital nerves and
centres by the break in the chain of the reflex mechanism. In
no other sex-activity, except in actual copulation, are the generative
organs in such a constant and intense excitement as in
dalliance with individuals of the other sex, no other erotic
stimuli create such libidinous turgescence of the organs and
such a high degree of sex-tension, exciting with rapture the
higher centres, no other excitations cause such a consumption
of nerve power as this gratification of the impulse of contrectation
by tactile manoevres. The erections of penis and clitoris
are vigorous and violent. The organs are set in a state of
expectancy for the final act. If the act is not terminated within
a certain limited time, the state of expectancy cannot last for
ever. The mode of action is limited in length of time. Except
in the abnormal state, known as priapism, the duration of erection
is relatively short in the normal individual. Its beginning
is synchronous with the onset of the material congestion and
nervous tension of the genital parts, and its subsidence should
normally be synchronous with ejaculation. If the latter be prevented,
erection has to cease sooner or later, even when congestion
and tension remain unabated. Hence after long and
lasting amorous caresses the erections fail.
If these manœuvres are often repeated, the excitations finally
do not effect the proper response, and erection fails from the
outset. The strong and continuous stimulations render the
nerves and their centres inert in reaction and weak in power.
The centres of erection and ejaculation become blunted, the
inhibitory centres get very sensitive, and erection cannot be
provoked. When the nerve centres presiding over the function
of erection get into the habit of not responding to the highest
excitations of the tactile stimuli, they do not respond even to
the stimulations concarnationis. The cooperating nerve-apparatus
has been affected, and a perverted innervation is created.
The close interdependence of the mechanism of erection and the
centres is removed, and an abnormal reflex-excitability is produced.
The consensualism between the corpora cavernosa and
the centre of erection is interrupted.
Before the indulgence in frustrate caresses has become a
habit, i. e., in the beginning of the practice, erections are
vigorous and of considerable duration. But the duration diminishes
with each repetition. After a few months or years of
these nerve-destroying practices, according to the patient’s
nervous constitution, there is no response by erection even to
the strongest stimuli. The consentaneous action, which, otherwise,
connects the excitement of the organs with erection and
completion of the act, does not take place. This lack of consensualism
on the part of the several factors which go to make
up the orgasm leads finally to complete impotence.
Continence, if long continued, has been claimed to be the
cause of impotence. But there is no valid reason for this
belief. To prove the harmfulness of continence, an analogue
is brought forward between the atrophy of a muscle in enforced
idleness and the injury to the sex organs in enforced abstinence.
But the proof is somewhat feeble. The essential organs of
generation are not muscles but glands, and who has ever heard
of a tear gland atrophying for lack of crying. Furthermore,
abstinence does not condemn the generative organs to absolute
rest. Every individual, especially when abstinent, has frequently
nocturnal erections through the entire period of his
sexual activity, and there is no reason why such erections should
not keep the genitals in the required exercise and should not
prevent the alleged atrophy. As far as the exercise to prevent
atrophy is concerned, nocturnal erections ought to be of the
same service as erections followed by intromissions. The nocturnal
erections seem to be even more harmless. The engorgement
of the colliculus is less pronounced in these erections.
Micturition, on awakening with an erection, is immediately
possible, while there is a pronounced inability of micturition
after an erection and ejaculation either through initu aut stupro
manu.
The histories of patients are cited to prove the deleterious
effects of total abstinence. Cases are known of alleged abstinent
neurasthenics, on the point of a complete breakdown, who
recovered perfect health after marriage. But even this proof
cannot stand a closer scrutiny. Who can prove the total abstinence
of these patients? The layman is prone to regard the
actual intromission only as sexual activity. If he has abstained
from this final phase, he considers himself abstinent. But
chastity is not continence by any means. Absolute continence
is abstinence not only from the gratification of the impulse of
detumescence concarnatione, but also from that of contrectation,
i. e., from mental and tactile caresses and from all other
abnormal practices. We must distinguish between chastity and
abstinence. Those who are chaste out of fear of venereal infection
or for lack of opportunity are not always abstinent.
They are just the individuals who are indulging immoderately
in mental erethism or even masturbation.
The mere assertion of the patient that he never indulged
in unnatural practices does not count. The patient’s veracity
is very questionable. All venereal troubles seem to exert an
inhibitory influence upon the truth-centres. The propensity of
the masturbator to conceal the truth is notorious. If such a
patient claims that he has never masturbated, it is likely that
he is still practising it. A special psychical element, associated
with this habit, prompts the majority of patients to gross and
intemperate prevarication.
But even if such a “rara avis,” who has abstained from
actual manusturpation, should exist, still mental erethism cannot
entirely be excluded. The elicitation of a history of mental
erethism is connected with great difficulty. Masturbation with
these patients means only the indulgence in manual practices;
the voluptuous day-dreams are considered of no account, and
the peculiar type of mendacity prevents them from revealing
the truth even to him, upon whom they called to consult.
Hence the loss of sexual power in these patients may not
have been effected by continence but, on the contrary, by continual
erethism. The examination of such patients really shows,
as a rule, the prostatic urethra in a state, which is usually caused
by prolonged erethism. After marriage, with its regulated
sexual activity and the removal of the inclination to the wild
erotic fancies, the neurasthenia is soon cured, not because the
patient has given up abstinence, as interpreted by the anti-abstinence
advocates, but, on the contrary, because he has now
become real abstemious from the excesses of mental erethism.
Hence the cure of neurasthenia by marriage is no proof against
sexual abstinence. The patients who seek medical advice for
their neurasthenic troubles may be those who have only abstained
from coition but have freely and immoderately indulged in the
unnatural modes of sensualism, whence their troubles originated.
The real continent individuals who avoid any kind of erotic
practices remain sound and healthy and do not require medical
help. Their cases remain hence unknown to the profession.
If total abstainers from every kind of sexual erethism
should sometimes become neurasthenic, this fact would not
prove yet that the nervous trouble was caused by total abstinence
from the gross sexual gratification. Even the man about town
may become neurasthenic for lack of the gratification of the
impulse of permanent mating. The apologists of promiscuous
intercourse forget or are ignorant of the fact that the impulse
of permanent mating in normal men and women cannot be
satisfied by promiscuity. The craving for a permanent mate,
home and family unconsciously demands gratification even from
him who leads a promiscuous sexual life. If this impulse is
not gratified, as in cranky old bachelors or hysterical old maids,
it may lead to severe attacks of neurasthenia. Such cases will
not be cured by the association with venal women or by promiscuous
sensuality, but they may be cured by a permanent
mate, home, and family life. Hence the cure of the total abstainer
from his nervousness by marriage is again no proof
against total abstinence. The cause of the trouble may have
been the unsatisfied impulse of permanent mating which has
been now satisfied by marriage. Promiscuous relations would
not have cured the neurasthenia, but marriage with its accompanying
emotional tones.
There is, therefore, no valid proof of the harmfulness of
total abstinence in a healthy individual without a hereditary
taint. If total abstinence ever harmed anybody, the patient
was either a congenial weakling or has acquired his lack of
resistance through indulgence in early eroticism. A perfectly
healthy man is never injured by abstinence. At least there is
no sufficient proof that it ever did. But there are unmistakable
proofs that total abstinence does not harm the individual. The
best proof is furnished by many chaste and healthy women.
Few women seem to suffer from total abstinence. The rejoinder
that woman’s sexual desires are very feeble, that the
female sex has no sexual needs, that it is more or less frigid,
are mere masculine assertions without objective proofs. Women
writers, who ought to know best the feelings of their own sex,
claim just the opposite. Johanna Elberskirchen (in Sexualempfindung
bei Weib und Mann) has well satirized the masculine
impertinence which tries to teach woman what her emotions are
or are not. The fact that many a young woman runs the risk,
in the present state of sex-morality, of ruining her entire future
by the indulgence in extra-marital sexuality, under conditions
where pecuniary or other considerations are entirely out of the
question, would tend to show that the sexual impulse is by
no means so weak in women, as many would lead us to believe.
It is simply incomprehensible that the female sexual needs
should be less urgent than those of the male sex. Woman has
by far the greater part of labor in the sex-performance. With
the ejaculation the man’s biological part is at an end. He
may leave now the scene of his activity, while the woman’s
part just begins and is continued through nine months of pregnancy
and about a year of nursing of the new being. Dr. M.
Glasgow, as a woman perfectly competent to judge, says (Review
of Reviews, 1912, p. 319): “The strong sexuality displayed
by a sex whose contribution to the germ of the race is discharged
in a brief moment of enjoyment must be greatly less
than exhibited by the other party, whose contribution is made
through long months of patient endurance.” The prominent
part woman takes in the propagation of the race forces to the
logical conclusion that her erotic needs are of necessity stronger,
although, as Ellen Key puts it, they may be calmer than that
of man’s. Woman is able in a quite extraordinary way to
produce the impression that she herself is really non-sexual
and that her sexuality is only a concession to man. But the
seeming reluctance of the female is intended to increase the
sexual activity in both mates. The passivity of the female
throughout nature is only apparent, it is the passivity of the
magnet. As a matter of fact, women experience during the
orgasm an ecstasy of feeling greater than in men, involving
the whole system in an ecstatic nervous erethism.
Still the normal woman can stand absolute continued continence
without any injury to her body and mind (e. g. nuns).
Hence there is no reason why the human male, if left to himself,
and nothing comes to disturb the natural course of his
sexual development, should be harmed by abstinence. Until
the impulse of permanent mating enters into play, and this
comes relatively late in life, abstinence will harm neither men
nor women, if they live in an atmosphere free from the influence
of artificial stimulation.
If the animal kingdom could be taken as proof for or
against total abstinence in man, we find that pet animals, as
canary birds or dogs, who rarely have the opportunity to exercise
their sexual powers, are generally as healthy and live as
long as those living in freedom.
Hence the claim that abstinence is the cause of impotence
has absolutely no ground to stand upon. If the young man
kept his thoughts pure and avoided exciting amusements which
create emotional disturbances, impotence would be an unusual
occurrence. If the young woman would avoid puttering over
her genitalia, pelvic obsession with its accompanied hysterical
conditions of hyperesthetic or paresthetic erethism would be
rarely met with.
The only cause for impotence remains sexual excesses.
They are very seldom the immediate cause of the impotence.
But they leave such weakness in the genital organs and in the
nervous system that it requires only the least disturbance to
provoke total impotence. Such disturbances, as remorse over
the formerly committed irregularities, or distrust in one’s
powers, or the mental attitude of the woman to whom sexual
approaches are a matter of real or assumed indifference, are
sufficient to render the weakened neurotic man total impotent.
Next to excesses, gonorrhoea, in a great many cases, leaves
the genitals in a similar weakened condition. Gonorrhoea often
causes acute inflammation of the prostatic urethra, and the
mucous membrane not seldom undergoes the changes characteristic
of chronic catarrh. The sensory nerves reflexly keep
the centres for erection and ejaculation in a condition of hyperesthesia.
This condition finally leads to the paralysis of
the centres and nerves, and reflex-erection cannot be produced.
Psychic causes of impotence are mental fatigue, overwork,
preoccupation with mathematical or financial problems, fear,AU
anger, grief, and disgusting sights or odors. Prolonged excitement
before attempting coition may also lead to temporary
impotence.
The other causes of impotence are the symptomatic ones.
Impotence is met with in tabes dorsalis, diabetes, nephritis,
obesitas, oxalic diathesis, haemorrhoids, fissures of the anus,
seat worms, etc. Excesses in the consumption of certain drugs
may also lead to impotence. Such drugs are alcohol,AV morphine,
cocaine, tobacco and the bromides.
Etiology of impotence in women.—The same causes, at work
in producing impotence in men, are also affecting impotence in
women. The only modification lies in the fact that impotence of
copulation, which is the impotence par excellence in men, is of a
negligible quantity in women. The main mode of impotence
found in women is that of experiencing libido. This impotence
may be either idiopathic or also caused by excesses as the impotence
of copulation in men. Idiopathic impotence of libido
is oftener met with in women than in men. Still even in
women this insensibility is much rarer than is generally believed.
The explanation for the greater frequency of impotence
of libido in women than in men has first been given by
Freud (Sig. Drei Abhandlungen über Sexualtheorie).
The autoerotic activity of the erogenous zones in children
is the same in both sexes. It may be asserted, says Freud,
that the sexuality of the little girl has entirely a male character.
The chief erogenous zone in the female child is the
clitoris which is homologous to the male penis. The frequent
spontaneous discharges of sexual excitement in little girls
manifest themselves in twitching and erections of the clitoris.
But while in the male the erogenous zone remains the same
after puberty as before, namely in the penis, puberty is distinguished
in the girl by a wave of repression of the clitoris-sexuality
and in the change of the erogenous zones. The rôle of
the clitoris is henceforth to conduct the excitation to the adjacent
parts. It often takes some time to affect this transference.
During this time the young woman remains anaesthetic
to stimulations of the internal organs as vagina or cervix.
This anaesthesia may become permanent if the clitoris zone
refuses to transfer its excitability. This anaesthesia in women
is often only apparent and local. They are anaesthetic at the
vagina and cervix, but not at all unexcitable through the clitoris
or even through other erogenous zones, such as the lips or the
nipples. The women are impotent of experiencing libido in
coition but potent when the clitoris is excited by any other
stimuli.
The refusal to transfer the clitoris sexuality is, as a rule,
caused by an excessive irritation of the clitoris by manusturpation
during childhood. The excesses which cause impotence of
libido in women are the same which cause impotence of copulation
in men, namely excesses in copulation, masturbation, mental
erethism, and tactile eroticism. In women the excesses in
copulation are more harmful than in men. While in men
these excesses are self-limited by the impossibility of provoking
any erections, after a certain time of continuous indulgence;
in women there is no limitation to the practice. Playing the
passive rôle, she can stand congressum continuum for a considerable
length of time and tire out a number of men in
succession. The vaginal pavement-epithelial lining is very
strong.
“Conteritur ferrum, silices teneantur ab usu.
“Sufficit et damni pars caret illa metu.”
sings Ovid in his “Ars Amandi.” Hence when a woman has
any proclivity for excesses in initu, there is no natural limit
to her indulgence. Through the influence of the frequent
irritation in copulative excesses, the vaginal mucous membrane
undergoes considerable changes. It becomes a veritable skin, a
stiff parchment, and thus loses sensitiveness.
The other cause for impotence of libido are excesses in
masturbation. The evil results of these practices in women
are fully as great as in men, although with women it is the
orgasm alone that does the damage, since there is no seminal
discharge or loss of vital fluids. Through the frequent application
of friction to the parts, they become first hypersensitive
and later hyposensitive and non-responsive to normal excitations.
Accustomed to excite the genitals by manual stimuli,
which may be kept up for a considerable length of time, the
masturbator is, later on, impotent to reach the acme through
the normal, relatively short excitations, as they take place
through the internal organic events in the genitals in normal
sex-activity.
In women, the same as in men, the greater damage through
excesses in masturbation is done by the greater frequency, because
it requires no help, from an outsider, because it is not
bound by time and locality, and may be practised by the undeveloped
child, and last but not least, because of the constant
conflict and struggle of the masturbator between the sensual
impulse and the inability to desist and the feeling of womanly
unworthiness, dissatisfaction and shame.
Excesses in mental erethism and excessive dalliance with
members of the other sex have no less injurious effects in
women than in men. In the long run these excesses cause in
the woman a number of nervous troubles which take the form
of hysteria or assume the character of neurasthenia. These
excessive practices of erethism or tactile eroticism are, also in
women, worse than excesses in copulation and masturbation,
because the former do not lead to the orgasm and to the relief
of the nervous tension and material congestion.
Another cause of impotence of libido in women is onanism
or the practice of withdrawal. This coitus interruptus which
rarely leads to orgasm in the woman, has the same effect upon
her as excessive mental erethism or tactile eroticism, because
it does not lead to relief from the nervous tension and the
congestion. Excesses in onanism are, therefore, very harmful
in women, while they are of lesser consequence in men. The
repeated congestions of the parts in all these practices lead
first to chronic hyperaemia and stasis, and in its further progress
to chronic inflammations of the tissues, known under the respective
names of metritis, perimetritis, parametritis, endometritis,
salpingitis, and ovaritis. The inflammations constantly
irritate the nerves and their centres and in this way blunt
their normal sensibility. Besides the dulling of the nervous
elements, these conditions give rise to great pain in commixtione,
and pain and fear are the greatest enemies of libido.
Other causes of impotence of libido in women are excesses
in alcohol, bromides, cocaine, morphine and other narcotics and
stimulants. Sometimes impotence of libido is the result of a
hard confinement. During such confinements extensive lesions
in the erectile tissues of the bulbs and in the sphincter cunni
muscles are apt to occur. Now, the integrity of the vaginal bulbs,
of the sphincter cunni, of the intermediary net of vessels, and
of the clitoris is necessary for the normal experiencing of libido.
If a serious lesion occurs, the blood current is interrupted, and
the blood is prevented from leaving the bulbs and from entering
the corpora cavernosa of the clitoris. The following case
will serve as an illustration:
The patient, twenty years of age, married twenty months, has a
baby ten months old. She states that since her confinement she has no
libido during coition. Before this event she always found perfect gratification.
The examination shows a first-degree laceration of the
perineum.
Absence or smallness of the clitoris and an adherent prepuce
may also often diminish the feeling of libido.
Pathology of male impotence.—The minute penetration
into the different causes of sexual anaesthesia in the preceding
pages was of particular importance, in order to fully understand
the pathology of the different kinds of impotence.
The accomplishment of the physiological act of copulation
and impregnation requires from the man the possession,
first of the desire to associate with the other sex, or of the
instinct of voluptas,AW secondly the power of effecting intromission
or the potency of erection, thirdly the potency of ejaculating
a healthy sperma for impregnation, and finally it requires
that libido or pleasure accompanies the emission to assure the
repetition of the act.
From these requirements it follows that the individual
must command over four potencies, the potency of voluptas,
which compels the individual to seek the society of the other
sex, the potentia coeundi, which depends upon strong normal
erections, the potentia generandi, depending upon normal secreting
testicles, and upon the perviousness of the entire seminal
canal, from the testicle to the meatus of the urethra, and finally
over the potency of libido, which depends upon the intact centripetal
nerves and normal centres of generation in the brain.
If any of these potencies are missing, the individual will be
impotent. Hence four kinds of impotencies may be distinguished
in both sexes:
(1) The impotence of voluptas, or the absence of sexual
desire.
(2) The impotence of immission, or absence of the power
of erection in men and the anomalies at the entrance into the
vagina in women.
(3) The impotence of impregnation, or the absence of
spermatozoa in men and of ova in women.
(4) The impotence of libido, or absence of the ability to
experience pleasure at the moment of emission.
Impotence of voluptas.—The impotence of voluptas, or
male frigidity, unassociated with the two other impotencies of
copulation and impregnation, is very rare in men.
Physiological impotence of voluptas exists in childhood and
in old age. In the latter period the desires disappear pari
passu with the power. Although the feeling of desire is of
purely mental origin, the generative organs playing only a
secondary part, still when these organs are powerless or absent,
the desire is generally also absent.
Impotence of voluptas is found in eunuchs and in castrates,AX
who have been operated upon before puberty. Such
castrates, even if the penis has not been removed, show not only
impotentia coeundi, but also complete frigidity. Their habitus
and feelings differ entirely from those of normal men. Castrates,
who have been operated upon later in life, retain the
habitus of normal men and also the impulse of contrectation.
The potency of immission is even greatly enhanced, at least
for the first few years after the operation. In normal men
erection subsides immediately after the ejaculation. In eunuchs
ejaculation does not take place. Hence the erections may last
for hours or even days. In the course of time the potentia
coeundi even of these castrates begins also to decrease and later
on becomes entirely extinct.
Impotence of voluptas is also found in severe cases of
neurasthenia, where the entire nervous system is in a low state
of efficiency. The history of the following case may serve to
illustrate the symptoms of the neurasthenic impotence of
voluptas.
Mr. B., 35 years of age, unmarried, had gonorrhoea several times,
never lues. Since puberty until about two years ago he was a typical
rounder and had an abundance of femininity at his disposal. He is now
suffering from general debility and shows all the symptoms of severe
neurasthenia, as headaches, pains in the back and abdomen, dyspepsia,
constipation, anorexia, insomnia, etc. In addition he has lost all desire
for sexual gratification. While in the days of unimpaired vigor his
sensual activities were of great frequency, several initus almost every
day, at present the necessity for concarnatio is entirely lacking. When
he does associate cum muliere, erection and ejaculation are perfectly
normal, but the sense of libido is greatly diminished. Sese injungit
nowadays only once every three to four months, out of curiosity to
try his potency, but not because he feels any necessity for the same.
The case is thus one of pure male frigidity combined with
a certain diminution of libido.
Male frigidity or impotence of voluptas is also found among
psychopathics, as low idiots and cretins. These patients lack
the understanding of the opposite sex. No mental excitations
will, therefore, have any effect upon them.
Sexual perversion is another psychosis connected with impotency
of voluptas to the opposite sex.
Impotence of voluptas is also often found in dementia.
Sometimes impotence of voluptas is congenital with an individual
otherwise normal. The impotence is then analogous to colorblindness.
Such cases are exceedingly rare.
Impotence of libido.—Similar to impotence of voluptas is
the impotence of libido. Here the desire is powerful, the erections
are vigorous, yet ejaculation takes place without the usual
accompanied libido. It is analogous to the loss or impairment
of the sense of taste. Idiopathic impotence of libido in
men is very rare. It is mostly found as a symptom of some
other anomaly.
Impotence of libido exists in cases of loss of testicles, as
in castrates and eunuchs.
As a rule, impotence of libido is met with in men who
have severely over-taxed their brains and hence are less impressionable
than when in a normal state of health. The impotency
is an indication of an exhausted brain where the
centres for experiencing libido reside.
Sometimes the centripetal nerves which serve for transmission
of the pleasurable sensations to the centres have their
impressionability obtunded by excesses in venere. When the
nerves are deranged, the desire is strong, the erectile power is
sufficient, the mind is in concurrence, emission occurs at the
right moment, yet scarcely a vestige of pleasurable sensation is
experienced during emission. The following case may serve as
a proper illustration of the nature of this anomaly.
Mr. X., fifty years of age, was seduced to the practice of manusturpation
when about thirteen years old. The exercises were carried out
daily. After puberty, from about sixteen to nineteen years of age, he
was given less to these practices, still once a week he could not resist
of indulging in his favorite pastime. At this time he began to associate
with meretricious women. This activity alternated with manusturpation
until he was forty years old. There were periods of months or
even years, while living in localities where the opportunity for normal
sex activity was entirely lacking, when he took refuge to weekly practices
of manusturpation. At the same time he indulged in excesses of
mental erethism. His day-dreams on his long walks and in sleepless
nights were filled with images, all taken from the realm of sex. Sometimes
he also indulged in excesses of tactile eroticism (manibus ludere
cum genitalibus mulierum). At the age of forty he married a very
attractive young woman, and although he is greatly in love with his
wife and two children, who arrived in the course of time, and is leading
a regular sex-life, still the pleasure experienced at the ejaculation is
practically nil. What induces him to still keep up his sexual activity
is to please his young wife.
Here is a case where the three potencies of voluptas, copulation
and procreation are perfectly intact, and where the patient
is only suffering from the impotency of experiencing pleasure
or libido during his sex-activity. In another case the impotency
of libido is complete every time the patient practises coition,
but is less pronounced when the act is repeated within an hour
after the first exercise.
Mr. N., thirty-five years of age, a prominent lawyer, is suffering
from a severe attack of neurasthenia for the last three years, the
greater part of which he spent in sanitaria. As a boy he practised
masturbation to some extent, but quite moderately. The symptoms are
greatly pronounced in the morning, and are manifested by a general
malaise, pressure in the head, bulging of the eyes, tremor of the hands,
pressure in the rectum, in the prostatic region, and burning at the tip
of the penis after urinating. The pressure in the rectum is relieved
the day following coition, but returns in aggravated form on the second
day. At the same time a mucus-like sediment appears in the urine
which, on repeated examinations, showed to consist of oxalate of lime.
For the last few years, ejaculation, in concarnatione, takes
place without any trace of libido. But if the act is repeated within an
hour, the patient experiences some pleasure. For this reason the patient
always exercebat concubitum bis in hora which served to aggravate his
neurosis.
In some patients the libido is only diminished. In extreme
narrowness of the prepuce the pleasure incident to sexual
relation is slight. The author had only recently performed on
a man, thirty-two years old, circumcision to cure this anomaly,
although, it is said, that in persons who have been circumcized
for ritual considerations, the libido is much slighter than in those
not circumcized. In the latter, the covering of the glans is
almost a mucous membrane and is very sensitive, while in
circumcized people the covering of the glans is almost a veritable
skin and has lost its finer sensibilities.
Impotence of procreation.—The type of impotence, most
frequently met with but rarely complained of by men, is the
impotence of propagation. Almost fifty per cent. of all cases
of absolute sterility in married couples are caused by this
anomaly in men.
Congenital and acquired deformities of the genitals may
often cause impotence of procreation. All castrates, even those
operated later in life, as the Skoptzies in Russia, are, of course,
impotent for procreation, although if the penis has been left intact,
they are very vigorous sexually, for a certain time, and are
very salacious. Anorchismus, cryptorchismus, atrophy of the testicles,
tumors of the testicles, compression by hydrocele, inflammation,
ossification, tuberculosis, and cancer of the prostate may
cause impotence of procreation without impairing the power of
copulation.
Some epispadias and hypospadias may cause impotence of
procreation. When the opening is very far back, the emission
will take place outside of the vagina.
Aspermia, whether idiopathic or acquired, will always cause
impotence of procreation. In the congenital form of aspermia
all the genital organs seem to functionate normally, still no
ejaculation takes place.
In the acquired form of aspermia both ejaculatory ducts
are obliterated, as a rule, through suppurative prostatitis or
tuberculosis of the prostatic gland. In both diseases the glandular
tissue is frequently destroyed.
Aspermia may also be due to neurasthenia as the following
case may show:
Mr. S., twenty-four years of age, has been treated about two years
previously for nocturnal pollutions. They happened every night once or
twice and weakened the patient in such a degree that he was unable to
perform any kind of work. Electric treatment, hydrotherapeutics, and
some medicinal tonics restored him to health. The pollutions happened
once in three to four weeks only. A year later the patient called again,
this time complaining of weakness in sexual power. After a few weeks’
treatment the improvement was such that the patient was lost sight of.
Six months later the patient returned with the complaint of suffering
from aspermia and lack of orgasm. He is erotic, and he has
strong vigorous erections, but no matter how long he remains in
initu, ejaculation does not take place. The patient falls back from sheer
exhaustion, sometimes mentulato membro, without being able to bring
it to an ejaculation and orgasm.
In this case the aspermia is due to a certain nervous weakness
of a neurasthenic nature. The patient has no strictures,
and his testicles are intact.
Aspermia is sometimes found in strictures of the urethra.
In such cases the semen flows backward into the bladder.
In comparison with azoospermia, as a cause of impotence
of procreation, all the other described anomalies are of a great
rarity.
In azoospermia ejaculation and orgasm are perfectly normal,
but the semen shows, under the microscope, the absence of spermatozoa.
Azoospermia is sometimes temporarily found after
excesses in initu aut stupro manu.
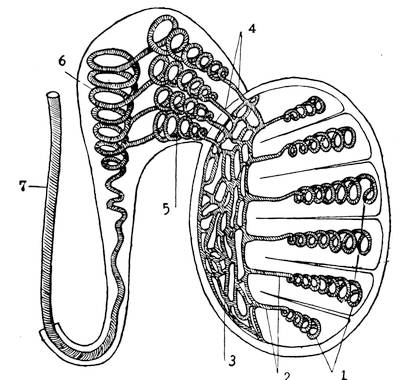
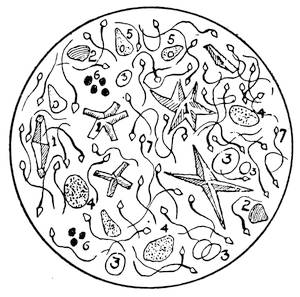
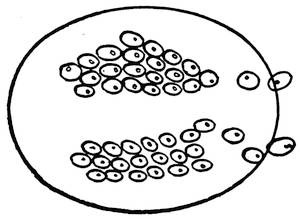
CUT XLII.
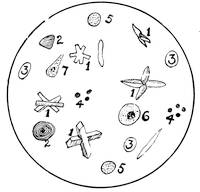
Azoospermia.
1, Boettcher’s crystals; 2, amyloid bodies; 3, hyaline bodies; 4, lecithin;
5, testicular cells; 6, prostatic epithelium; 7, urethral epithelium.
Permanent azoospermia is, as a rule, caused by inflammations
of the testicles or of the epididymis. These bilateral inflammations
of the testicles or of the vasa epididymis are almost
always the result of gonorrhoea. The vasa deferentia are obliterated
and impervious. The ejaculated semen consists only
of the secretions of the seminal vesicles, of the prostatic glands
and of the urethral glands.
The spermatozoa being absent, the sperma is much thinner
than in the normal state. The absence of the spermatozoa and
their movements is also the cause why the Boettcher’s crystals
usually form much earlier; they appear within half an hour
after ejaculation and in a considerable amount. They often
cover almost the entire microscopical field. In the normal semen
the movement of the spermatozoa prevents the early formation
of the crystals; they appear after several hours’ standing and
are fewer in number. The thin azoospermatic semen is more
transparent and watery and contains more epithelia and fat than
normal semen.
The patient is, as a rule, unaware of his anomaly. It is
often discovered after his wife has undergone innumerable treatments
for her supposed sterility. If the anomaly has been caused
by gonorrhoea with the accompanying inflammation of the
testicles, epididymitis, or spermatic funiculitis, the loss is almost
irremediable. The revelation to the couple of their doom
to childlessness is one of the many tragedies played in the
doctor’s office.
Impotence of copulation.—The anomaly, most complained
of, which drives the patient to seek medical help is the impotence
of copulation. It is the anomaly which strikes the hardest
blow to masculine vanity. It is a psychological fact that most
men are proud of their potency of copulation and feel greatly
humiliated when the same is impeded. A woman will not seldom
discuss with her friends the double ovariotomy performed upon
her, but the man deprived of his testicles will never mention
the fact of his castration to his closest friends.
The impotence of copulation is best divided into four types:
1) Organic impotence.
2) Symptomatic, or paralytic impotence.
3) Psychic, a) transitory, b) relative, c) temporary impotence.
4) Atonic impotence.
Organic impotence may be congenital or acquired. Among
the congenital forms are total absence of the penis. Smallness
of the penis may also be the cause of impotence, although this
cause has been somewhat exaggerated by most writers. The male
generative organs on the Greek statues are in comparison with
the size of the other parts quite small. Still, if the smallness
goes beyond a certain degree it will cause impotence. In the
same way enlargement of the penis beyond a certain degree will
also result in impotence. Adhesions of the penis to the neighboring
parts or torsion of the penis will render intromission impossible.
Congenital absence of the testicles is always accompanied
by loss of power.
Among the acquired deformities are counted neoplasms of
the penis, elephantiasis, and the destruction of the penis through
ulceration. Syphilis and tuberculosis of the testicles are generally
destructive to virility. Removal of the testicles, even if
operated later in life, is, after a certain time, followed by atrophy
of the penis and impotence. Indurations and ossifications of
the cavernous bodies lead, as a rule, to impotence.
Symptomatic impotence.—The organic type of impotence is
relatively very rare. The other type, symptomatic impotence,
is oftener met with. It is found in cerebral diseases, diabetes,
tabes dorsalis, chronic nephritis, extreme obesitas, chronic rheumatism,
chronic alcoholism and in the cachexies of anaemia,
cholaemia and uraemia. But since the desire fails with the
failure of power, such patients rarely seek medical aid for this
anomaly. They consult the physician for their original ailment
which is of far greater importance to them than the loss of
power. They mention this anomaly only in the course of the
anamnesis.
Symptomatic impotence is, as a rule, paralytic in form.
Libido is more or less absent, and if emissions ever occur they
take place without erection or pleasure. In the paralytic form
of impotence nocturnal erections are absent, nor do erections
occur at any other time. This sign is almost pathognomonic of
this type. If the vagina is very wide, and intromission with
semi-erection should be effected, ejaculation does not come in
jets but slowly. The function of the bulbo-cavernosus muscle is
impaired, hence no ejaculation with force in a jet is possible, but
a slow dribbling from the meatus takes place.
In paralytic impotence the genitals are more or less withered.
The skin of penis and scrotum is almost anaesthetic.
The entire urethra is insensible, the sound passes into the bladder
with the greatest ease. The skin of the thigh in the vicinity
of the genitals is more sensitive to electric currents than that
of penis and scrotum. The following history well illustrates a
typical case of paralytic symptomatic impotence:
Mr. H., 45 years of age, a widower with one child, contracted lues
fifteen years previously and was apparently cured after two years’ treatment.
For the last two to three years he began to suffer from shooting
pains around the abdomen (Gürtelschmerz) and in his legs. Micturition
is frequently urging, and the stream is slow. The knee-jerks are greatly
exaggerated. The patient’s gait is still normal, and he does not show
any other sign of tabes dorsalis. About the time when the pains first
appeared, he also noticed a certain weakness in erection and premature
ejaculation. He began then to associate with meretricious women who
practised on him fellatricia, or insertio fascini in os. From this
time the impotence increased and is now complete. For the last two
years he never had even nocturnal erections. The penis is in a state
of atrophy, and is now of the size of a boy’s, fourteen to fifteen years
of age. The skin of the penis is shriveled and cold. The glans is pale.
The entire skin of the penis and scrotum is quite anaesthetic to the
galvanic current. An application of about fifteen milliamperes in
strength, which produced an ulceration by burning, was scarcely felt by
the patient. The faradic reaction is normal.
Psychic impotence.—The mode of impotence known as
psychic is a very frequent anomaly. It is the disease of the
cultured classes. The action of the nervi erigentes is incomplete
in psychic impotence, and the complete relaxation of the
corpora cavernosa does not take place. Hence a sufficient quantity
of blood can not enter the erectile tissue to exert pressure
on the outgoing veins. The corpora cavernosa become smaller
and harder at the critical moment and do not admit the entrance
of the blood. The diameter of the penis becomes less than that
of the glans. The penis feels cartilaginous, and the skin is
found in transverse folds through the contraction of the corpora
cavernosa. Hence erections are feeble or entirely wanting
at the critical moment. When the patient is lying in bed alone
he has, in distinction from atonic impotence, quite vigorous
erections.
Psychic impotence is transitorily found also in healthy individuals
when they are in a state of agitation. The more
agitated the patient is, the more the penis shrinks. In psychic
impotence, if the wife is of an exceedingly passionate disposition,
she will make advances and may often evoke powerful
erections, whereas the wife’s indifference would cause impotence.
In this way this form of impotence is often only relative.
With one woman the inability injungendi is complete, while the
virile power is exuberant in concarnatione with another. As a
rule, the patient who has reached the critical age of fifty to
sixty, does not succeed in his conjugal duties but is able commisceri
meretricis auxilio. The indifference of the wife who,
as a rule, is about forty to fifty years of age and has
either passed or is very near the climacterium, accounts for
the husband’s impotence in her company. Such men are able to
perform the act only when the woman actively or at least cheerfully
and willingly yields herself. The sullen, supine position
of the frigid wife is not enough to hold a man’s love forever.
Temporary psychic impotence of short duration is sometimes
met with in newly married men through lack of confidence.
When about to be married, the broodings over things to come
overstimulate the inhibitory centres in the brain. As a result,
at the critical moment, the penis gradually shrinks, grows smaller
and moves in a worm-like manner in the course of its
diminution.
The following case may serve as an illustration for such
cases:
Mr. S., 23 years of age, had suffered from gonorrhoea a few years
previously. He has practised stuprum manu moderately at the time of
puberty. Later on he associated cum meretricibus. He always considered
himself healthy. The seminal discharge was somewhat precipitated,
but the patient attributed this phenomenon to his extraordinary
strength and was rather proud of it. When he became engaged to
his present wife he abstained henceforth from illicit relations. Two
days before the consultation the patient married and, upon approaching
his young bride, found that the erection was too weak to transgress the
virginal portals. After his first failure, every repeated attempt caused
the penis to shrink almost half the normal size of the flaccid condition.
The wife’s genitals were perfectly normal. She did not suffer from
vaginism. Therapeutic suggestion and a medicinal tonic (ut aliquid
fiat) removed the anomaly in a few days.
In this case the anaphrodisiac of fear after the first failure
was the cause of the impotence.
Psychic impotence is sometimes present for a short time
after long continued abstinence in men who for some reason have
interrupted their regular sexual relations. Young men who have
never had yet any sex relations are never affected by mere abstinence.
Psychic impotence is not seldom found in men with a
certain vocation requiring great mental strain, as literary men,
bookworms, mathematicians, engineers, etc.
Extreme excitement and desire may cause temporary impotence.
The number of stimuli arriving from the brain is too
vast and paralyzes the centre of erection. A violent lover, who
has for a long time repressed his desires, plunges his entire
organism, in the moment of their realization, into a kind of
ecstasy. His soul, i. e., the immaterial part of his being, concentrates
in the object of his desires all his force and vitality.
He appears entirely to forget his organs which ordinarily serve
to transmit his desires. It is hence first necessary for him that
everything be restored to the ordinary channel, that the moral
over-excitation ceases or that it returns at least to the normal
type of simple excitation, before the centre of erection will have
power to exercise its function.
Want of responsiveness from the mate has sometimes a disadvantageous
effect upon the man. Hence obstacles, on the side
of the woman, will not seldom cause psychic impotence. The
history of the following case is characteristic of this kind of
disturbances:
A young medical student made the acquaintance of a young girl
who had previously given birth to a child. The girl did not want to
reveal her secret to her lover, and fearing that, as a medical student,
he might discover her secret in initu, she refused to grant him
her favor. One evening while alone with her in his room, he tried
hard to accomplish his desire by persuasion, caresses, and other means.
When just at the point to break her resistance, the erection suddenly
ceased, and the penis shrunk to half its normal size. From this moment
he suffered from complete impotence. Even nocturnal erections did
not take place any longer. The impotence resisted every kind of treatment,
until, one day, the girl wrote the patient that she was now willing
to yield to his desires. At the first meeting following the letter, puella
tentavit actively to arouse his passion, and he succeeded in having a
powerful erection actionis peragendo. From this moment he was cured
from his ailment and enjoyed his full virile power of former days.
This case shows the vast influence the psyche is wielding
even upon the unconscious state of the brain during sleep. The
stimulation of the inhibitory centre was so strong as to prevent
even the occurrence of nocturnal erections.
In illicit relations, the fear of surprise or of infection, shame
or loathing may have inhibitory effects upon the centre of erection
and cause psychic impotence.
Violent shocks to the nervous system, as great fright, pain,
or grief, etc., and all other strong emotions which often affect
the urinary system by causing temporary frequent micturition,
polyuria, or glycosuria, may also give rise to disturbances of the
sexual functions and cause psychic impotence of a transitory
nature.
Over-estimation of the difficulties of defloration sometimes
causes temporary impotence in nervous newly married men.
The timidity of inexperience may in the same way have the
effect of an anaphrodisiac.
Sometimes the exaggerated veneration of his young wife
may cause temporary loss of vigor in the young husband. The
thought that such an exalted personality, as his young innocent
wife, should have to submit to such an indignity (not a few
have this strange opinion of the conjugal act), works as an
inhibition of the proper performance of the act.
The most frequent cause of psychic impotence is the thought
of failure. An accidental single failure through the temporary
abuse of alcohol, tobacco, coffee, or tea or through intense desire
may occur, some day, which in the healthy man would pass
unnoticed. But the nervous man will begin to brood over this
failure, and this brooding will prevent the formation of associative
paths in the brain at every subsequent attempt of coition.
In nervous men, the imagination, having once become impressed
with groundless fears, may retain them with extreme tenacity
and busy itself with constant brooding in solitude over the fancied
ills. Thus a disorder of adjustment is established, and a
psychic trauma is created, through the subconscious effects of
cryptogrammic nerve-currents. This psychic trauma is translated
into fear again. The subconscious cerebral processes lead
to the formation of ideas, later recallable in memory. These
morbid ideas become the substratum of future anxiety-attacks.
A pathological state is thus induced where the natural course of
erection fails to follow the sexual excitement. In this way a
veritable disease is produced, where there is a strong desire without
full power. Every additional failure provokes more intense
broodings which are naturally again the cause of failure. Thus
a vicious circle is created which may render an occasional innocent
failure a permanent impotency.
Atonic impotence.—The most frequent form of impotence
of copulation, in fact, the impotence “par excellence,” is the
atonic impotence. This is the impotency which is generally
caused by venereal excesses, either in copulation, masturbation,
mental erethism, frustrate eroticism, or last but not least, conjugal
onanism or coitus interruptus. These excesses cause the
exhaustion of the centre of erection, irritation of the centre of
ejaculation and a debilitation and enervation of the genital
nerves. For when the lumbar centre of erection fails to respond,
there is a deficiency in activity, excitability, mobility, and tonicity
of the entire genital apparatus.
In the atonic form of impotence conditions of absolute
impotency are quite rare. Absolute impotence is mostly found
in the paralytic form which is caused by cerebrospinal and nervous
diseases. In the atonic anomaly the vast majority of cases
are of partial impotence.
The impotence due to weakness is distinguished by premature
ejaculation and the subsequent immediate subsidence of
erection. Sometimes a vigorous erection ceases suddenly before
emission has occurred, and the penis becomes completely flaccid
and shrivels to half its normal size before the entrance into the
vagina. When ejaculation does later occur it takes place without
erection or pleasurable sensations. Not seldom the entrance
into the vagina is effected with good erection, but when about
to begin the act, the penis suddenly wilts, the wilting either followed
by ejaculation or not. The following case illustrates the
ordinary symptoms:
Mr. L., 45 years of age, happily married, and father of several
children, was always healthy and strong and had never had gonorrhoea
or syphilis, but had freely masturbated when he was young. He always
considered himself a powerful man. He is given to athletics, horseback
riding, ball playing, swimming, rowing, etc. For the last year
the patient noticed a certain weakness in his potency. As soon as he
enters the vagina, ejaculation takes place at once and is followed by
immediate flaccidity of the penis. Sometimes, while trying intromission,
the erection ceases like a shot ante portas. When he does not
try congressus the erection lasts much longer. The patient’s wife has
been of a rather frigid nature, never asking or caring for concarnatio.
But recently she seems at times to have rather a certain longing for the
embrace. This fact makes the patient feel doubly miserable, not to
succeed, when the partner seems to desire and enjoy the initus.
This case is one of those where objectively there is very little
to discover. In some cases of atonic impotence the patients
show neurasthenic or cerebrasthenic symptoms. The underlying
cause of the impotence, as a rule, determines the symptom-complex
of the case. If the cause of the impotence is excess in
masturbation, the case will show all the symptoms of the typical
masturbator. The latter is generally small, emaciated, hollow-chested,
thin-necked and weak-kneed. He shows deep-set eyes
and pale hollow cheeks. The penis and testicles are small. The
penis is cold and shriveled. The patient has a bad taste in his
mouth, and suffers from winds in his stomach. He also suffers
from obstinate constipation and colicky pains in the bowels. He
complains of palpitation of the heart, shortness of breath and
of a burning sensation in his arms. He suffers from loss of
memory and from tinnitus aurium. The patient also shows a
certain moral abasement, incontrollable restlessness, carelessness
in dress and person and shambling in gait. The history of the
following case is that of a typical masturbator:
Mr. C. is 31 years of age and unmarried. At the time of puberty,
when he was 14 years old, he began to practise stuprum manu. Se
stuprabat manu three to four times daily. When twenty years of
age he began to associate cum meretricibus. But the natural initus
did not seem to satisfy him. Post omnem initum manu se stuprabat,
in addition, as soon as he reached his residence. Three years ago
he contracted gonorrhoea, from which he suffered a whole year. Since
a year he noticed a certain weakness in his potency. He is able to effect
intromission, but before he can begin the act, ejaculation without the
least trace of libido takes place, followed by immediate flaccidity of the
penis. He has some erections in the morning but they are not complete
as in former times.
When the cause of the atonic impotence was venereal excesses
or gonorrhoeal prostatitis, the long-kept-up congestion of
the prostatic urethra and of the colliculus leads to general reflex
excitability, to a high degree of nervousness, cerebrasthenia, and
neurasthenia. The colliculus being an organ which finds its
analogue in the female uterus, its constant irritation will show
phenomena in men, usually found in intensely hysterical women
only.
The impotent men generally change their entire psychic
nature. They become timid, morose, solitary, melancholic, hypochondrical
and despondent. They are discontented, peevish, ill-humored,
and evince either blunted or inordinate sexual desires.
They show profound agitation at the slightest excitement. The
patients are troubled with insomnia or unrefreshed sleep and
with a feeling of heaviness on rising. The mind is enfeebled
and the memory impaired. The mental debility and dulness
cause inability to collect their thoughts and thus enfeebles the
mind in its power of concentration. The patients suffer from
vertigo, singing in the ears, from a feeling of fulness in the
head, from asthenopia, depression, anxiety and irritability. They
often suffer from palpitation of the heart, sick headaches, coldness
of the hands and feet, dull heavy feelings, a sense of
fatigue and a loss of flesh. They also complain of creeping sensations
in the loins, of pricking in the back, of twitching and
jerking of the muscles, of muscular weakness, of lumbar pain
and asthma. The intestinal canal shows a general derangement,
as coated tongue, poor appetite, sense of weight in the epigastrium
after eating, flatulence, sluggishness of the bowels and
constipation. The general health of the patient is broken, the
countenance is vacant and the gait feeble.
Besides the general symptoms, the genito-urinary organs
are especially affected in atonic impotence. The external genitals
show a certain flaccidity, shrinkage, paleness of the mucous
membranes and a diminution of the sensibility and electrical
irritability. The skin of the penis is cold, shriveled and somewhat
insensible to electrical stimulation. The electrical irritability
of the skin of the two halves of the scrotum is of a different
degree, the right half being sometimes more sensitive than
the left.
The testicles are often very painful and tightly drawn up
against the external abdominal rings. The spermatic cord often
shows an enlargement of the veins (varicocele). The vas deferens
and the ampulla are in a state of inflammation.
The seminal vesicles are plainly felt indurated, nodular and
distended with fluid. In a large proportion of cases the repeated
congestion causes a veritable seminal vesiculitis. This inflammation
is not seldom extended to the ejaculatory ducts and occludes
the same. Through this occlusion spermatic colic, i. e.,
a severe pain in the region of the vesicles, often seizes the patient,
especially after some sexual excitement, as dancing, caressing,
and even flirting. After such excitement a dull pain in
the region of the prostate and in the perineum as well as in
the testicles, spermatic cords and in the rectum is very annoying
to the patient. Ejaculation often removes these pains. For
that reason the patient tries to relieve himself from the painful
sensations by masturbation. Ejaculation also removes the irritations
of the thighs, hips, anus, hypogastric region and in the
smalls of the back.
The entire urethra is often in a state of hyperaesthesia and
paraesthesia, and the prostatic portion shows congestion and not
seldom an inflammation of the mucous membrane. Especially
the colliculus is often in a severe inflammatory condition. There
is thickening sponginess or puffiness of the parts immediately
involving the ejaculatory ducts. The urethra manifests great
sensibility. The introduction of a bougie produces unbearable
pains. The withdrawal of the sound is often followed by several
drops of blood. This hypertrophy and inflammation of the
colliculus seminalis is the cause of the ejaculatio praecox in the
beginning of the disease. Later on the condition provokes weak
erections and finally ejaculation with flaccid member before
entrance into the vagina.
The irritation of the urethra causes hypersecretion of the
glands of Littré and Cowper which is manifested by the so-called
urethrorrhoea. In urethrorrhoea the secretion is thin, transparent,
perfectly clear and sticky. The secretion has no spermatic
odor and does not stain the linen, but stiffens it. It is
seen as a drop in the morning at awakening with an erection.
The drop is sticky and tenacious. The meatus urethrae sticks
together. The drop is not rarely found in healthy men after
violent and continuous erections. The secretions show under
the microscope nothing beyond free mucous and columnar and
pavement epithelia.
Besides the hypersecretion of the urethral glands, there is
also a hypersecretion of the prostate, especially in patients who
have indulged in excesses in masturbation and in onanism (coitus
interruptus). Masturbation as well as onanism do not give the
same satisfaction as normal coition, hence constant hankering
for more and overindulgence. Prostatorrhoea is often found
after gonorrhoea, when the yellowish drop gradually becomes
whitish, flocculent, and finally a colorless watery drop of clear,
slightly viscid fluid. It is best seen when the lips of the meatus
are held apart.
In prostatorrhoea the discharge is never milky, white or
purulent as in pure prostatitis. Microscopically the slowly dried
slide shows the characteristic crystals of sodium chloride, but
no spermatozoa. In prostatorrhoea the orifice of the urethra
shows constant moisture. The copious evacuations occur while
straining in the water-closet. The patients are, as a rule, constipated.
The discharge is attended with peculiar sensations,
sometimes of a pleasurable nature, sometimes of a dropping
sensation, weight in the region of the prostate, anus and rectum.
Examination per rectum often shows hard points and nodules
in the prostatic gland.
The most frequent anomaly caused by venereal excesses is
spermatorrhoea and nocturnal pollutions. The excesses provoke
a chronic hypertrophy of the prostatic gland, and this hypertrophy
renders the ejaculatory ducts insufficient.
In spermatorrhoea there is an oozing of semen from the
urethra without erection or pleasurable sensations. The rhythmic
muscular contractions, found in normal ejaculations, are missing
here. The failure of the normal contractions is due to a paresis
of the muscular fibres of the ejaculatory ducts.
Spermatorrhoea usually takes place after micturition or
during defecation. Sometimes spermatorrhoea is caused by the
slightest excitement. The sight of a woman’s bust or of her
leg, the touch of her hand, the smell of her perfume, the glance
at a lascivious painting, or a voluptuous thought may cause a
precipitate discharge, without an erection or with an imperfect
erection. The discharge taking place at a complete relaxation of
the ejaculatory ducts, the voluptuous sensations are, as a rule,
entirely absent.
Spermatic discharges sometimes occur in affections of the
central nervous system, where the usual inhibitions through consciousness
are ineffectual.
Microscopically the discharge in spermatorrhoea shows amyloid
bodies, lecithin and prostatic epithelia. The fluid has the
seminal odor which is peculiar to the spermin reaction; the
amount of spermatozoa is somewhat diminished.
The testicles and the skin of patients, suffering from spermatorrhoea,
are less sensitive to electrical stimulation, while the
urethra is hypersensitive.
Nocturnal emissions constitute the other anomaly of ejaculation.
Physiologically all healthy continent men between the
ages of fifteen to fifty, with very few exceptions, have nocturnal
emissions at intervals of about four weeks (male menstruation).
The pollutions arise during sleep and are accompanied by erotic
dreams and erections. They usually awaken the sleeper. Normal
pollutions occur only in sleep and are accompanied by vigorous
erections, erotic dreams and orgasm. They also cause a sensation
of relief. When pollutions are frequent, two or three times
a week, they become pathological. They are then followed by
lassitude, dizziness, faintness, dragging pains in the occipital
region, mental depression, disinclination for mental effort, sense
of fatigue, lessening of physical strength, pain in the back and
reflex irritability. The patients are startled at the least noise.
They change color every moment. The eyeballs run unsteadily.
There is often found a disturbance of speech, difficulty in breathing,
and palpitation of the heart.
The following case will best illustrate the symptoms in nocturnal
pollutions:
Mr. A., 25 years of age, was always well and never had gonorrhoea
or syphilis. When a boy he practised stuprum manu in a moderate
degree, as he says. A few years ago he noticed a certain weakness
in erection. The emission took place soon after the entrance into
the vagina and was followed by the immediate flaccidity of the penis.
Sometimes the ejaculation occurred ante portas. The patient, therefore,
gave up trying intercourse. Since then he is suffering from nocturnal
pollutions, which occur every night or at least three to four times a
week. The following day the patient feels very weak, as to prevent him
from performing his usual work in his trade. He suffers from headaches
and pains in the lumbar region and in the legs. He is engaged
to be married and is looking forward with great apprehension to the
approaching time of this momentous event.
Pathological pollutions are caused by a paralysis of the
circular muscular fibres of the ejaculatory ducts. This paralysis
may be either of a purely nervous nature or caused through inflammatory
processes. Atony of the mouths of the ejaculatory
ducts not seldom produces nocturnal pollutions. Sometimes pollutions
are also due to a spasm of the detrusors of the seminal
vesicles.
When the seminal vesicles and the ejaculatory ducts are
thus affected, very little is needed to cause a nocturnal emission.
Any diurnal excitement will be followed by nocturnal erotic
images and pollutions. Sleeping on the back, by causing a fluction
of blood to the spinal cord, will also produce pollutions.
Besides the genitals, the urinary system is also greatly affected
in atonic impotence. The hyperaesthesia and hyperaemia
of the prostatic urethra and of the colliculus, usually found in
atonic impotence, are the cause of a continual irritation of the
bladder.
The irritation of the neck of the bladder provokes a spasm
of the detrusor vesicae. To this spasm is due the frequent painless
impulse to urinate, by day when under mental activity, and
in sleepless nights.
Sometimes the detrusor is in a paretic condition. In paresis
of the bladder the patient has to wait for the urine to come
and has to use abdominal pressure to effect urination. The
urine falls without force perpendicularly from the urethra.
There is often desire to urinate, but never a feeling of satisfaction
after urinating. When catheterization is attempted, there
is a powerful resistance at the neck of the bladder, through a
certain spasm of the sphincter.
In spasm of the sphincter of the bladder there is also frequent
impulse to urinate. Not seldom such patients are unable
to urinate in the presence of others. Sometimes the urine cannot
be passed at all. The spasm of the sphincter creates a certain
difficulty in starting the act of micturition. The stream is
often interrupted and, at the end, a dribbling of urine takes
place. Through the spasmodic contraction of the muscular
fibres of the sphincter the urethra represents a rigid open tube
in which one end is closed; it thus resembles a pipette which
retains the fluid as long as one end is closed. When the relaxation
takes place, the fluid contained in the urethral tube dribbles
out of the meatus.
In paralysis or paresis of the sphincter the patient urinates
often but in small quantities. In paresis of the sphincter there
is no resistance to catheterization at the neck of the bladder.
In the beginning of the paresis there is incontinence of urine
during the night. Later on when the disease has progressed,
and a perfect paralysis has ensued, the incontinence of the urine
is constant even in daytime.
In enuresis nocturna, often found in masturbating children,
there is an imperfect innervation of the sphincter, while the
innervation of the detrusor of the bladder is perfect.
In all these anomalies the urethra is very sensitive. The
passage of an instrument causes unbearable anguish. The patient
acts as mad when the sound is introduced. There is often
found a troublesome burning in the urethra, especially in the
fossa navicularis, during or after micturition.
Besides the frequent urgency to urination, in all these
troubles, there is not seldom an actual polyuria present. The
urine is pale, clear, watery, with low specific gravity, often as
low as 1002. The urine is not seldom loaded with phosphates.
Sometimes oxaluria, with high specific gravities up to 1050, is
discovered. Transient glycosuria as high as two to three per
cent. is also found. At times vesical tenesmus is met with.
Sometimes anuria is observed, although the kidneys are in perfect
order.
The pathology of female impotence.—The same four kinds
of impotencies found in men are also met with in women, with
the only difference that the frequency of one or the other of
the impotencies is different in the different sexes. They are:
1) impotence of voluptas, 2) impotence of copulation, 3) impotence
of reproduction, and 4) impotence of libido.
Impotence of voluptas.—The entire absence of the sense of
sex, or impotence of voluptas, where the individual has absolutely
no sexual inclination to any individual of the other sex, is more
frequently met with in women than in men. Still even in
women this idiopathic frigidity, this insensibility where the
woman is completely frigid by temperament, is much rarer than
is generally believed. In fact, it is extremely difficult to find a
woman who is without aptitude of sexual emotion.
Physiological frigidity exists in infants and in very old age.
After a regular and satisfactory orgasm the woman is physiologically
more or less anaesthetic for some time. The ablation of
both ovaries before puberty causes total anaesthesia, while the
operation after puberty produces, for a certain time, at least,
only an impairment of libido, or orgasmus retardatus. Congenital
degeneration of the ovarian glands will be accompanied
by total absence of the sense of sex. As in men, the total absence
of sexual desire is found in severe cases of neurasthenia,
where the entire nervous system is in a low state of efficiency.
Idiopathic impotence of voluptas is further found in low idiots
and in dementia, where there is lack of understanding of the
opposite sex. The sexual perversity of homosexuality, as a
rule, causes total impotence of sexual desire for the opposite
sex. Sometimes the cause for the anaesthesia lies in the centre,
otherwise the patient is perfectly normal, as in the following
case:
The patient, forty years of age, twenty years married, is a highly
cultured lady. She never had a child or was pregnant while living
with her two first husbands. A prominent gynaecologist, who had
examined her several years previously, attributed the cause of her
sterility to an infantile uterus. She has never, in her life, experienced
any sexual desire and seems to be proud of it. She attributes this lack
of passion to her great mental activity. An examination revealed a
pregnancy of about four months.
Impotence of copulation, except in the anomaly known as
vaginism, is very rarely found in women. Conjugation is, of
course, impossible in the rare cases of total absence of the vagina.
In hypospadia, where the vaginal orifice is situated within the
rectum, vaginal conjugation is well-nigh impossible. Adhesions
of the labia majora or minora, a rigid imperforated hymen, an
extreme vaginal atresia near the orifice and elephantiasis of the
vulva will cause impotence of conjugation. All acute inflammations
of the vulva, vagina, rectum, uterus tubes, or ovaries may
render approach painful and impossible. Urethral caruncles,
urethritis, fissures at the neck of the bladder, rectal fissures or
hemorrhoids may also render conjugation difficult. The tetanic
contraction of the sphincter cunni and the tetanic spasm of
the perineal muscles, constrictor cunni, transversus perinei,
sphincter and levator ani which close tightly the orifices of
the vagina and the entire vaginal canal will also be the cause
of impotentia coeundi. The solitary tetanic contraction of the
sphincter cunni, known under the name of vaginism, will make
conjugation impossible until the hymen is removed. The following
case operated by the author illustrates this anomaly:
Mrs. X., twenty-two years of age, for three months married to a
physician, was unable to be approached by her husband. As soon as
the penis touched the labia, the sphincter cunni contracted so tightly
that there was an utter impossibility to transverse the virginal portals.
During the examination, at the least touch of the nymphae, the
sphincter could be observed contracting, just as seen in animals after
defecation when the sphincter ani contracts. The ablation of the hymen
cured the anomaly. This fact shows that it was only a reflex-irritation,
started at the highly sensitive hymen. The sphincter itself was perfectly
normal.
Impotence of reproduction.—More frequent than impotence
of copulation is female impotence of reproduction. This anomaly
is naturally found in all those cases where there is impotence
of copulation. It is sometimes met with in excessive acid reaction
of the vaginal contents, where the spermatozoa are killed
before they reach the uterus.
When one lip of the cervix is considerably elongated, covering
apron-like the external os, the spermatozoa will not be able
to enter the cervix, and sterility will result. Sterility is also
found in the obliteration of the cervical canal, produced by
caustics or scars after tears during confinements and after curettings.
Ectropion, stenosis of the external or internal os of the
cervical canal, endocervicitis, causing an increased cervical secretion,
and the swelling of the plicae palmatae may prevent the
entrance of semen into the uterus and thus cause impotence of
propagation.
The anomalies of the uterus are also sometimes responsible
for sterility. Uterus foetalis and obliterations of the lumen of
the uterus will result in absolute sterility. Uterus infantilis,
hypoplasia of the uterus, atresia of the uterus or polypi, hypertrophic
chronic metritis, degeneration of the uterus or uterine
deviations may often be the cause of sterility.
The anomalies of the tubes which cause sterility are absence
of the tubes, rudimentary tubes, total or even partial obliteration
of their lumen, as in salpingitis nodosa, closing of the ends of
the tubes in bilateral salpingitis, and adherences of the tubes
to the neighboring parts, as found in pelviperitonitis, perimetritis,
perisalpingitis, and perioöphoritis.
The anomalies of the ovaries, causing impotence of procreation,
are absence of the ovaries, hypoplasia of the parenchymatous
tissue of the ovaries, fibrous degeneration of the ovaries, alteration
of their position, as extreme prolapsus and hernia of the
ovaries.
All these anomalies may produce either absolute or relative
sterility. In regard to frequency they are of slight significance
in comparison with endometritis and pelviperitonitis after gonorrhoea.
The gonorrheic infection is, therefore, the cause par
excellence of the impotence of procreation in women as in men.
Impotence of libido.—While in men the common form of
impotence is inability of conjugation, the common form of impotence
in women is failure to experience the orgasm, or the
impotence of libido. In this anomaly two grades may be distinguished,
total anaesthesia and partial anaesthesia or orgasmus
retardatus.
In absolute anaesthesia there is not even a vestige of a
libidinous sensation during intercourse. The woman likes caressing,
hugging, kissing, etc., because the potency of voluptas is
intact. But there is no vestige even of the fore-pleasure, or the
ant-orgastic libido. The woman is devoid of sexual sensation,
her genitals have no more excitability for pleasurable sensations
than her fingers. Hence no desire for coition exists. On the
contrary, there is, as a rule, a pronounced disinclination to the
act. Where there is complete absence of pleasurable feelings,
the act becomes naturally loathsome to the individual. If coition
is granted it is done either from a sense of duty or for gain.
Physiological anaesthesia exists in children until puberty,
and in adults in old age. Even after menstruation has set in,
the girl is, as a rule, anaesthetic in regard to libido, although
she may be erotic. “The girl has to be kissed into a woman.”
After the climacterium the woman generally becomes again
more or less anaesthetic. Some women may continue to experience
libido years after this period, and may manifest symptoms
of great sexual excitement as seen in the following case:
Mrs. X., married to an elderly man, looked upon the marital
relations more as a duty than as a pleasure during her entire married
life. But since the climacterium has set in, the rare approaches of her
husband are impatiently awaited and they cause her great sexual excitement
and satisfaction, never experienced before during the entire
period of her active sexual life.
Such cases are extremely rare. Generally there is a close
connection between the activity of the generative glands and
the degree of libido.
After a regular and satisfactory coition the woman is,
physiologically, more or less anaesthetic for some time. The
length of the neutral period varies in different individuals. Intense
mental activity, emotional depression and long sexual continence
also diminish the sensual pleasure.
Apart from this temporary anaesthesia, there are many
women who are impotent to experience libido throughout their
lives. There is a total absence of pleasurable feelings during
coition or any other kind of sexual stimulation.
A young lady, twenty-two years of age, complains that while
during the time of her engagement she greatly enjoyed her fiancé’s
caresses and became sexually excited when fondled by him, since her
marriage she is unable to experience any libido in coition, although
her husband is possessed of great potency. The patient is a beautiful
brunette, with fiery eyes, and is a picture of health. Examination
shows a uterus infantilis.
The potency of voluptas in this case is wholly intact. The
patient enjoys being fondled and caressed. The cause of the
impotency of libido lies in the periphery, although uterus infantilis
is seldom accompanied by impotence of libido.
In some cases the woman is normally developed in every
respect, menstruates regularly and is frequently quite prolific.
The power of procreation is sometimes even very great. The
woman is generally quite erotic and falls in love easily. Yet she
never experiences the least libido.
A young lady, twenty-eight years of age, mother of two healthy
children, was sent by her family physician from Chicago to consult the
author for her impotence of libido. The husband stated that he is
sure of his wife’s attachment to him. She enjoys his company and likes
to be caressed by him. Still during the eight years of their married
life she never showed the least sign of libido at coition. She remains
cold and indifferent, and only submits conjugationi to please
her husband. The examination showed the genitals to be in perfect
order.
In the following case, too, no cause whatsoever could be
found for the anaesthesia in regard to libido.
Mrs. L., twenty-nine years of age, is seven months married. Her
menstruation set in when she was fifteen years of age and was always
regular of about six days’ duration. At that time she began to satisfy
herself by manusturpation and found some libido in the manipulation.
But soon she read in a book about the ill effects of this practice
and stopped it.
In the beginning of her married life coitus caused her great pain,
which diminished by degrees after a few weeks. At present, coition
causes her only disgust. The day after she feels tired and weak.
The examination shows a feminine habitus, breasts well developed,
clitoris normal. The hymenal rests are very sensitive to the touch.
The painful sensation and the feeling of disgust increase when the
anterior vaginal wall is touched. The uterus is enlarged to the size of
a goose-egg, the cervix is soft, and the external os narrowly closed.
Diagnosis, two months’ pregnancy.
In this case some traces of libido were present at the time
of puberty, which later on entirely disappeared. In some cases
the patient is very prolific, as the following history shows:
The author recently performed a perineorrhaphy on an otherwise
healthy woman, mother of five children, who confided in him that she
has never experienced the slightest libido in intercourse. Yet, she
added, if her husband would not take precautions, she would give birth
to a child every year, as was the case in the beginning of their married
life.
Anaesthesia in women is, as a rule, due to inexcitability of
the genital nerves and to lack of excitation at the centre of
libido. Sometimes anatomical anomalies of the genitals may
cause impotence of libido. The integrity and the free exercise
of the generative organs are necessary for the integrity of the
libidinous feeling, although sexual pleasure is experienced at
the nervous centres, and the generative organs play only a
secondary part. The vaginal bulbi and their muscle, the constrictor
cunni, the intermediary net of veins between the bulbs
and the clitoris, and the free part of the latter, the glans of the
clitoris, must functionate normally in order to give full satisfaction
in intercourse.
Hence diminution or extinction of the sense of libido will
be caused by castration, degeneration of the ovarian glands,
marasmus, sexual excesses and overindulgence in alcoholic beverages
or cocaine.
In the following case the erotic feeling increased in such
a degree after the castration, probably through the extinction of
the libido, as to deceive the family physician and lead him to
make the diagnosis nymphomania.
Miss X., a school teacher, over thirty years of age, was always
chaste and indifferent not only to any carnal pleasure, but also to male
company. On account of a uterine fibroid, a total extirpation of uterus
and ovaries was performed. Since the operation the patient complains
of great sexual excitability she had never experienced before the operation.
She is so excited sexually that she is possessed of the almost
imperative impulse to kiss every male person she meets on the street, and
but for her position, she would have long ago yielded to this impulsive
desire.
In another case of diminution of the potency of libido, only
uterine inflammation and pregnancy could be discovered.
Mrs. M., thirty-five years of age, four months married, had always
suffered pain in the back during menstruation. The patient complains
that she only experienced libido twice since she has been married.
Since the last experience in the first weeks of her married life, she
has no pleasure at all. Coition, though not painful, causes her a disagreeable
feeling. An examination revealed anteflexio uteri, enlargement
and catarrh of the cervix, erosions and a three months’ pregnancy.
In the following case castration caused inability to experience
libido.
Mrs. M., thirty-five years of age, for the last fifteen years married
but sterile. When she was only two years married she began to suffer
from attacks of headaches and vomiting, which repeated almost every
other day. Her menstruation was regular. After having tried all the
stomach specialists in the city without finding any relief from the
vomiting spells, she consulted a gynaecologist, and he promptly found
an ovary to be the cause of all her troubles. She had been previously
operated upon for gall stones, which were not found and for appendicitis,
when the presumably diseased appendix was removed. She now
submitted to ovariectomy on the left side. Three months after the
operation the vomiting spells returned, and she submitted again to a
removal of the right ovary. But even this double castration did not
relieve her. When she first consulted the author she was still suffering
from these spells, especially before menstruation, which is still present
although irregular. The patient declares that previous to the ovariotomies
she experienced full libido and was able to induce orgasm.
After the second ovariotomy this potency was lost. She gets excited
during coition, but the orgasm cannot be produced. The following day
she feels nervous and weak.
In another case of impotence of libido nothing else but
anteflexio could be discovered.
Mrs. H., twenty-four years of age, four years married, was confined
by the author a year ago of a healthy girl. The patient complains
of never having experienced any libido. Before her confinement coition
caused her great pain and misery. Since her confinement she suffers
no more pain during the act, but libido is still absent. She complains
of great dryness of the parts, so that vaseline has to be used to facilitate
walking. At the examination there was found redness of the vulva,
catarrh and erosion of the cervix and anteflexio.
In the following case of anaesthesia the author could discover
no other cause but general weakness.
Mrs. W., twenty-six years of age, was always pale and weak.
Menstruation set in at twelve years of age. At nineteen she was
married, and ten months later gave birth to her first child. Four years
later gave birth to another child. For the last year she complains
of stomach trouble and weakness, pain in the back and abdomen.
Menstruation is now four to six days ahead of time and lasts five
days. She never experienced orgasm but twice. Both times the intercourse
was followed by pregnancy. Other times coition only excites
her but never brings full satisfaction. The following day she suffers
from severe headaches. An examination only revealed a catarrh of the
cervix. The patient received a tonic, and the husband was given some
hygienic rules to observe in initu. Five weeks later the husband
informed the author that the anaesthesia had disappeared.
Sometimes sexual anaesthesia is the result of a hard confinement
producing lesion of the muscle bulbo-cavernosus or of
the erectile tissue of the bulbs themselves. The blood is then
prevented from leaving the bulbs and from entering the corpora
cavernosa of the clitoris. In this way the erection of the clitoris,
which is more or less necessary for the full and normal inducement
of the orgasm, is rendered impossible.
The author recently treated a young lady, twenty years of age.
She had her first menstruation when she was sixteen years old and was
always regular. She had been married eighteen months, and her baby
was eight months old. The patient called to be treated for leucorrhoea,
but her husband called the following day and stated that his wife
has no pleasurable feeling during initus since her confinement. Before
this event, she found perfect gratification. An examination revealed
nothing but a catarrh of the cervix and a slight enlargement of the
left ovary.
Roubaud also relates the confidences of a patient who wished se
stuprare manu a few days after her confinement, but could not, with
all her manipulations, induce the desired orgasm. The normal potency
returned only after a long rest.
The number of women afflicted with the anomaly of impotence
of libido is considerable. It is claimed by many authorities
that ten to twenty per cent. of all women are afflicted with
this anomaly.
The symptoms of total anaesthesia are subjective and objective.
There is first the statement of the husband about his
wife’s indifference and coldness during the conjugal embrace.
The woman complains of lack of orgasm and ejaculation and
of the immediate flowing off of the sperma after coition. The
peristaltic contractions of the vaginal walls, beginning at the
vaginal orifice, and the aspirating movements of the uterus, as
they take place in the normal woman, during the orgasm, are
missing here. Hence the sperma is immediately discharged
from the vagina.
One of the most conspicuous objective symptoms is a relaxation
of the entire genital tract. The glans of the clitoris is often
undeveloped or wholly adherent to the prepuce. In some women
old lacerations of the perineum are present. The genital muscles,
the levator ani and constrictor cunni as well as the perineum,
are languid and withered. The mucous membrane of the entire
genital tract is in a state of hypersecretion, as in true chronic
inflammations. The vagina is wide and flabby, the walls are
lacking elasticity. The portio vaginalis uteri is flabby and
pointed. The uterine walls are weak and soft, and the cavity is
wide. The uterus is extremely movable and generally lies in retropositio,
the relaxation of the uterine ligaments allowing it to
fall downward and backward. The patient’s general health is
often poor, she is anemic, nervous and weak. Sometimes there
is only hypoplasia of some of the genital organs, otherwise the
woman enjoys good health.
Women suffering from anaesthesia may without sacrifice
refuse their favors to their husbands and render them submissive
to their will and henpecked. Single women, having no pleasure
in and hence no desire for conjugation, if they are not induced
to give themselves for pecuniary considerations, easily remain
virtuous and seem to be very proud of this enforced purity.
Even among married women there are wives who pride themselves
on repugnance or distaste for their conjugal obligations.
They speak of their coldness and the calmness of their senses
as though they were not defects but great virtues. Yet the sour,
shallow, sexless shrew is surely an imposture as a wife. Her
marriage is nothing else but a fraud.
In congenital anaesthesia the therapy is valueless, although
electricity by Apostoli’s method and massage may be tried in
uterus infantilis and in undeveloped ovaries. In prolific women
the only advice the physician may give is that, in harmony with
Ovid’s recommendation,
“Tu quoque cui Veneris sensum natura negavit,
“Dulcia mendaci gaudia finge sono.”
for the sake of matrimonial peace, simulation of libido and
orgasm is a justifiable fraud. Even to resort to some lubricant
to simulate the secretion from the Bartholinian and cervical
glands is permissible. The man is easily deceived in this respect.
He does not in any way feel the ejaculation of the woman. He
only surmises her orgasm by her bearing during the culmination
of the libido.AY The woman also does not feel immediately the
male ejaculation, but she perceives it soon by the increase of
moisture. Then the effect naturally increases the excitement,
as the following case shows:
A young woman of twenty-two, who has practised stuprum manu
from her early childhood, confided to the author that she derived more
libidinem de stupro manu quam de initu. Yet, she added, after some
abstinence from regular initus, although she is fully indulging in her
favorite pastime, she has a veritable sitim seminis.
Patients afflicted with congenital impotence of libido are
very seldom seen by the physician. They are not aware of their
anomaly, and being otherwise normal and in full possession of
the power of procreation, they never ask for treatment. The
physician learns of such cases only by chance. It is different
in acquired impotence of libido. Here the patient knows what
she has lost, and the physician is often asked for advice and
for a remedy. Hence the study of this anomaly is very important
for the physician, although this impotence has not the same importance
in women as it has in men, where it causes impotence
of copulation and destroys the marriage relations of the couple.
Orgasmus retardatus.—The other grade in the impotence
of libido is partial anaesthesia, in which the patient is able to
experience the ant-orgastic pleasure, but cannot induce real
orgasm. The intensity of the pleasurable feeling does not reach
the sudden climax and does not diminish abruptly. The climax
is never reached, and the ant-orgastic libido decreases gradually
and slowly, it dies away. In idiopathic partial anaesthesia,
where the anomaly is congenital, the patient has never experienced
an orgasm, and hence is not aware of her anomaly.
It is different in the acquired form of partial anaesthesia
or in the so-called orgasmus retardatus. The sexual excitement
of the woman suffering from orgasmus retardatus is never abated,
her libido is unimpeded, but the potency of experiencing orgasm
is diminished or entirely absent. The following extracts of a
letter from a patient suffering from a certain degree of orgasmus
retardatus well illustrates the complaints of this class of patients:
I have been married over a year now, and have never experienced
any satisfaction in initu. The glands seem to secrete the
fluids, and the cupido congressus is there, but no satisfaction. I
am always sleepless and nervous afterwards and sometimes suffer from
headaches the following morning. I am at times bothered with leukorrhoea.
When a child faciebam stuprum manu, but not since my sixteenth
year of age, and I am at present twenty-five years old. I have
never been pregnant.
The following case is extremely interesting, because the patient
is able to induce orgasm only in one certain position. In
all other positions she is impotent of experiencing libido. In
March, 1908, the patient consulted the author about her anomaly.
Being a highly educated woman (she was a school teacher before
she married) she was asked to write in a letter the history of
her case, and the following are the contents of her letter:
I am forty-one years of age, eleven years married, have two
children, one ten, the other eight years old. I began to menstruate at
the age of thirteen and was always regular, the menstruation lasting
three to four days. The flow was always scanty.
As a child I was sad and dreamy. I can recall times when I
would weep, I scarcely knew for what. When I was nearing puberty
coepi me stuprare manu. No one taught me. I could not help it;
I did not know what I did it for (I was reared on a farm).
The method was sitting on a chair and moving to and fro. I must
have continued till I was eighteen or nineteen years old. I stopped it
long before I knew it was wrong, long before I have ever read it in
books. No one told me it was wrong. I was a good girl in the eyes
of every one.
At the age of twenty I went to college. I think the reason I
stopped stuprum manu was that my mind was greatly engrossed in my
studies. True, I often had the desire, but the association with the opposite
sex would lessen it. I was fond of men in a silent way. I
never, even though in their company, was familiar with them.
When twenty-three years of age I met one towards whom I was
changed. I could not keep away from his presence. I remained a virgin
till we married, when I was thirty years of age. I had known him
seven years, but only saw him often, say three or four times a week,
for the last two years. We spent only one or two evenings each week
together. I allowed and deeply enjoyed all caresses, but they were not
of the lewd fashion. I must have been excited sexually, for I would
experience excessive humorem ut in initu.
At the age of forty-one, libidinem capio ex initu, yet experience
no orgasm save in the position “vir infra,” and in this
position very, very little sensation till the orgasm comes. I am fond
of the concarnatio, but aside from the position just mentioned, I have
not the least libido inter initum. It is a pleasure, you know, to give,
but my own libido is wanting in any of these positions. My husband
prefers alios positus to the one in which I have orgasm; præbente
majorem libidinem.
Multum humesco in initu. Quamquam comisceor quot noctibus
præferrem longum quam parvum temporis spatium concarnationi.
I am never ill, no aches or pains. The only premonition I have
of the approach of the menses is a fulness and tenderness of the breasts.
I menstruate very regularly.
Believe me when I say that once only in the seven years I knew
the one I eventually married—I must have been twenty-three and a
half years old, when I had spent hours in his company, with no more
familiarity than a kiss at parting—I was so excited ut pulvillum
premerem usque ad orgasmum. I could not have helped it, no matter
what had occurred. Often I have been excited thus, but I never
before or since did the same.
I never yielded to desire, though gently pressed to do so. Had
I been urged beyond my power of endurance I cannot tell what I would
have done. Yet I trust my virtue was due to a predominance of will-power
and not a lack of passion.
I cannot say the lapse of years has changed my desires or lessened
what I call my passions. I am affectionate by nature, but I trust
my emotions are more than affection.
The patient makes these last remarks because she is unable
to bring in accord her own feelings with the diagnosis frigidity,AZ
received from several physicians whom she had consulted. She
herself knows well that she is passionate enough to exclude any
possibility of frigidity. Hers is a typical case of orgasmus retardatus
of a slight degree (for, in the position “vir infra” orgasm
is possible, for in this position coition lasts considerable
longer), due probably to masturbation but mostly to the tactile
eroticism, practised during the seven years of her engagement.
In pronounced orgasmus retardatus the sexual impulse is
very vivid, but the patient can never find the acme of gratification
in coition. It may often require hours concarnationis continuæ
before the orgasm is induced, and sometimes it may never
be experienced. While there is a strong desire and a theoretical
ability to induce the orgasm,—the patients are able to experience
the orgasm in all its intensity by masturbation—in practice it is
seldom or never attained, because the male will always reach the
acme of coition before the woman has arrived at this point. Her
nervous system remains, therefore, excited to the highest pitch
and brought to a state of expectancy which is not realized.
This lack of orgasm may also happen in normal women.
The woman is generally slower to reach the height of the venereal
paroxysm than the man. Ab initio commixtionis, she experiences
a certain degree of libido that is of greater intensity
than that of the man, i. e., the ant-orgastic libido is of
higher value in women than in men. But this libido is not
developed to its utmost extent, the orgasm, as rapidly as it is
with the man. Still in the normal woman normal conditions will
finally ensue after some experience—it is known that in women
lustful feelings are not always brought about by the first contact,—while
the conditions are entirely different in the partially
impotent woman. No one man, except he be a eunuch, is ever
able to satisfy her in a natural way. Her nervous system remains
in a constant state of excitement to the highest degree,
analogous to satyriasis in men. Her active potency appears to
the superficial observer to be increased, it is almost inexhaustible.
The following case will illustrate this point:
A young lady, twenty-one years of age, for six months pregnant
with her first child, showed at the examination normal internal genital
organs, but small nymphae and an undeveloped clitoris. The patient
coepit stuprum manu facere, tres annos nata, femora commissa fricando
ultro citroque aut pulvillum aut aliam rem inter ea. As far as she can
remember she always felt humorem in genitalibus suis after such manipulations.
She practised stuprum manu several times daily until her marriage.
Her husband left her in the first months of her pregnancy and she
began to indulge in her favorite practices. “In coitione usitata frictiones
continuas poscit”, and can endure them for hours. She claims to have
the feeling of becoming wet several times during the “copulatione longa
et continua,” but the libido does not materially increase cum humorem
sentiat. The intensity of the libido remains always the same.
She is continually uttering endearing words to her mate and is begging
him, ne patiatur ejaculationem cito venire. She remains excited “postquam
frictiones cessaverunt” and is always showing her disappointment
when the penis “retractus est.” After a little while, her excitement
gradually subsides, and the patient falls asleep. When she awakes she
immediately “coitionem iterum poscit.”
Here we have a case of a partially impotent woman whose
anaesthesia and slight development of the clitoris was in all
probability the result of her early practice of masturbation. The
orgasm cannot be induced, but the ant-orgastic state is accompanied
by libido of a considerable degree. The glands furnish
enough secretion to give the feeling of moisture; there is no
real ejaculation as in normal congressus.
While the totally anaesthetic woman has no natural desire
for coition, and in this respect resembles the woman who is
suffering from idiopathic frigidity or impotence of voluptas, the
woman with the power of experiencing libido, but afflicted with
the anomaly of orgasmus retardatus, has an intense desire for
conjugation. She seeks it oftener than the normal woman, for
the reason that her desire is seldom satisfied. She demands,
therefore, commixtionem continuam per horas et pæne quot noctibus.
Such a Messalina is able commisceri centies in una nocte
and yet be unsatisfied. Even if she had it in her power,
like Katherine of Russia, to order cubili suo a whole regiment
of soldiers quot noctibus, she would still remain unsatisfied.
This anomaly, for these reasons, may often be confounded
with the perversion of nymphomania, where a normal orgasm is
induced with every copulation, but where an immediate reawakening
of desires, after normal satisfaction, takes place.
Through the similarity of the symptoms of orgasmus retardatus
and nymphomania great mistakes in treatment have often been
committed. The wisdom of amputating the clitoris in a case of
nymphomania is very questionable, but the advice to amputate
it in a case of impossible or retarded orgasm and permanently
damage the already weakened nerves is a mistake that borders
almost to malpractice. For the amputation of the clitoris will
impede the inducement of the orgasm even to a greater extent
than before. The genital apparatus, which was weakened by
excesses in venere or in narcotics, is now irreparably destroyed
for all time.
The case of Barrus shows what clitoridectomy may sometimes do.
The patient, a young woman, stuprum faciebat manu more or less, all her
life, and finally after suffering from several attacks of nymphomania
decided to have the clitoris amputated. The result was not only failure
to relieve the alleged nymphomania, but even an increase in its severity,
causing a shameless and, almost literally, continuous indulgence in the
habit.
The cause of orgasmus retardatus is almost always self-abuse,
either in form of masturbation, mental erethism, or tactile
eroticism. The excitability of the clitoris is so increased through
these practices that it refuses to transfer its excitability upon
the internal genital organs for the inducement of orgasm by
coition. The ant-orgastic pleasure is hence intact or even increased,
but the orgasm is seldom or never provoked.
The unsatisfied intercourse will in the long run cause a
number of nervous troubles which take the form of hysteria or
assume the character of neurasthenia. The unsatisfied initus
repeatedly practised, in not leading to the acme of libido and
to the relief from the congestion by the ejaculation, is the cause
of chronic hyperaemia and stasis. This leads, in its farther
progress, to chronic inflammations of the tissues, which are
known under the respective names of metritis, perimetritis, parametritis,
endometritis, salpingitis and ovaritis. The labia are
tumefied and dry, the meatus urinarius inflamed and the urethra
pouted out. The clitoris is elongated, inflamed and often
abraded. The external genitals are in a state of burning heat.
The vaginal mucous membrane is hard and excoriated, the cervix
is congested and the external orifice inflamed.
Apart from these pathological changes caused by the failure
or the retarding of the orgasm, the anomaly is of grave social
importance. The woman with whom orgasm is impossible generally
repels her husband. Her nerves never being exhausted,
as in the normal woman (it is little known that a woman is more
affected and fatigued by a real orgasm than a man), spatium
congressus may last as long as the vaginal epithelia can
endure it, which means a considerable length of time. This is
mistaken by the husband for increased potency. He believes her
to be more potent than he is, and, in the long run, a man dislikes
a lascivious woman. What he wishes is a modest woman
who never asks for conjugal embrace when he is not disposed
to it, and at times even knows gently and tactfully to refuse her
favors when they are asked. Orgasmus retardatus is hence not
simply a question for the physician; it is a matter of serious
social importance.
The correct treatment for this anomaly is, in the first
place, total abstinence from sexual excitement in any form, and
then strengthening of the nerves by tonics, hydrotherapeutics
and electricity by Apostoli’s method.
Orgasmus praecox.—The exact opposite to orgasmus retardatus
is the anomaly of orgasmus praecox. In men, suffering from
this anomaly where ejaculation occurs before the penis has time
to enter the vagina, the precipitated orgasm has the same effect
as the real impotence of concubitus. In women suffering from
orgasmus praecox, the orgasmus is induced as soon as the mentula
reaches the vestibule.
In some women the excitability of the genital nerves reaches
such a degree that the mere touch of the gynaecologist’s finger
during an examination will immediately induce orgasm. Since
erection ceases in both sexes after the orgasm, this anomaly is
of great importance in men, because the conjugal embrace cannot
be consummated. In women, on the other hand, with their
passive rôle during concarnatio, and with whom erection of the
clitoris is not requisite for sexual congress, the act may be continued
as in the normal woman. The anomaly is hence of less
importance in women. Still it has some bearing upon the
woman’s fecundity. In the ideal commixtione the female orgasm
ought to take place immediately after that of the male, so that
aspiration of some amounts of sperma could be effected. In the
anomaly of orgasmus praecox the spermatozoa have to rely upon
their own power of motion to reach the interior of the uterus.
The anomaly may, therefore, sometimes lead to sterility. Otherwise
medical aid is never sought for. The pathological condition
is extremely rare, anyway.
In the same way the anomaly of a diminished frequency is
of no importance to the physician when occurring in women.
He may be asked for advice when it is met in men, for it may
lead to some incongruities in the matrimonial life of the couple,
especially when the wife is of a sensual nature. But a woman
who is able even very rarely to experience orgasm will never
seek the advice of her physician.