The laryngoscope is a combination of instruments designed for the
examination of the interior of the larynx and upper part of the
trachea, while the rhinoscope is a similar combination of instruments
designed to explore the posterior nasal cavity; and both are
comparatively recent inventions.
HISTORY OF THE LARYNGOSCOPE.—In medical literature before the middle
of the eighteenth century no mention is made of an instrument or
apparatus resembling the laryngoscope, but recent excavations at
Pompeii have brought to light small polished metal mirrors attached to
slender handles which are supposed to have been used to inspect the
cavities of the human body. The first authenticated attempt at
laryngoscopy and rhinoscopy was made by the distinguished French
accoucheur M. Levret in the year 1743, who invented, among other
surgical instruments, an apparatus by means of which polypoid growths
in the cavities of the nose, throat, ear, etc. could be seen, and a
ligature be passed around them for their removal.1 This apparatus
consisted mainly of a polished metal mirror which "reflected the
luminous rays in the direction of the tumor," and on whose surface the
image of the growth was seen to be reflected. The great value of this
apparatus for the diagnosis and treatment of nasal and laryngeal
diseases was, however, not recognized, and it shared the fate of many
other valuable discoveries which were made before the world was ready
to receive them: it was forgotten.
1 Mercure de France, 1743, p. 2434.
In 1807 a certain Dr. Bozzini, living in Frankfort-on-the-Main,
published a work describing an apparatus which he had invented for the
illumination and examination of the cavities of the human body.2 This
apparatus consisted of a peculiarly-shaped lamp and of a number of
metal tubes, polished on their inner surface, of various shapes and
sizes adapted for the different cavities of the body. The one intended
for the examination of the larynx was bent near its end at a right
angle, and had a mirror placed at the bend, which served to throw the
light downward toward the opening of the larynx when the tube was
inserted into the mouth. When reflected light was to be used, the
interior of the tube or speculum was divided into two portions by a
longitudinal septum, and two mirrors were inserted at the bend—one for
the reflection of the light downward, and the other for receiving the
reflected image. This invention of Bozzini was treated, however, with
derision by the medical profession, probably on account of the
extravagant descriptions given of it in the papers, which were not
verified by its performances.
2 "Der Lichtleiter," Philipp Bozzini, Med. und Chir. Dr.,
Weimar, 1807.
In 1825, Cagniard de Latour, an investigator of the physiology of the
voice, made some unsuccessful attempts to examine the living larynx.3
3 Physiologie de la Voix, par Ed. Tournié, Paris, 1865.
Senn of Geneva in 1827 endeavored to examine the larynx of a
little girl suffering from an affection of the throat by means of a
small mirror which he had made and which he inserted into the pharynx,
but he failed to see the glottis, because, as he says, the mirror was
too small, and because he used neither direct nor reflected light to
illuminate the cavity below the mirror.4
4 Journal de Progrès des Sciences, etc., 1829.
In the year 1829, Benjamin Guy Babington published5 an account of
what he called the glottiscope, an apparatus which consisted mainly of
two mirrors. One of these was small and attached to a slender stem, and
was used to receive the image, while the other, an ordinary hand-glass,
was used to reflect the rays of the sun or ordinary daylight upon the
smaller mirror in the fauces. This combination was essentially the same
as is used at the present day in the laryngoscope, with the difference
that we now use artificial light in most instances, and a concave
mirror instead of a plane one for reflecting the light.
5 Lond. Med. Gazette, 1829, vol. iii.
While Babington was still engaged in perfecting his instruments, a
mechanic named Selligue, who suffered from an affection of the throat,
in 1832 invented a speculum for his physician, Bennati of Paris, with
which the latter was able, as he asserted,6 to see the vocal cords.
This instrument was similar to the one invented by Bozzini, and
consisted of a double speculum bent at right angles and carrying two
mirrors—one for illuminating the cavity, and the other for reflecting
the image. Selligue was rewarded for his efforts by a complete cure of
his affection.
6 Recherches sur le Mécanisme de la Voix humane.
A number of others worked in the same direction, and endeavored to see
the interior of the larynx in the living subject by employing different
apparatus and methods of illumination. Thus, in 1838, Baumès of Lyons
described a mirror the size of a two-franc piece (11/8 inches in
diameter) as useful in examining the larynx and posterior nares.7
Then Liston in 1840 used a dentist's mirror,8 and Warden of Edinburgh
employed a prism of flint glass attached to a long stem as a laryngeal
mirror.9 In the latter part of the same year Avery of London employed
a speculum with a mirror in its end for examining the larynx, using as
an illuminator a concave reflector with a central opening, which was
supported by a frame to be worn on the head of the operator.10
7 Compte Rendu des Travaux de la Société de Médecine de
Lyons, 1836–38.
8 Practical Surgery, 1840.
9 Lond. Med. Gazette, vol. xxiv. p. 256.
10 Med. Circ., June, 1862.
Up to this time all efforts at laryngoscopy had been made with a view
to diagnose diseases of the larynx, with the exception of those made by
Latour. In the year 1854, however, Signor Manuel Garcia of London,
without any knowledge of previous efforts, conceived the idea of
studying the changes in the larynx during phonation in his own throat.
For this purpose he placed a small dentist's mirror against the uvula
and reflected the rays of the sun into his mouth and upon the small
mirror by means of a hand-glass held in the other hand. By arranging
his position in relation to the sun in such a manner that he could see
the reflected image of the small mirror in his throat in the
hand-glass, and in it the illuminated image of his larynx, after a few
ineffectual attempts his efforts at auto-laryngoscopy were crowned with
such success that he was enabled to study the movements of the vocal
cords during phonation, and accurately describe the registers of the
voice in a paper read before the Royal Society of London in 1855.11
Although Garcia was the first who practised laryngoscopy successfully,
his communication to the Royal Society attracted little attention, and
would have been forgotten if it had not been that, in 1857, Tuerk of
Vienna, having heard of Garcia's paper, began to use the laryngeal
mirror on the patients in the K. K. Algem. Krankenhaus for
diagnostic purposes.12 At first he was not very successful in his
attempts, and began to experiment with laryngeal mirrors of different
sizes and shapes. While thus engaged Czermak borrowed Tuerk's mirrors,
and modified them until he succeeded in the greater number of cases in
seeing the vocal cords,13 using artificial light for illuminating the
larynx. Meanwhile, Tuerk continued his experiments, and also succeeded
in almost all cases of throat disease which came to his department of
the hospital in seeing the interior of the larynx and in treating the
lesions. Both Tuerk and Czermak improved their apparatus, and
especially the latter, who by substituting artificial light for
sunlight, and by inventing a number of different illuminating
apparatuses, has given us the laryngoscope in the form in which it is
used at the present day. It is but natural that Tuerk should have
claimed priority in the successful use of this instrument, and in
consequence of this claim a controversy was carried on for a number of
years in the medical press between him and Czermak, which at times
became quite spirited, but which left Czermak master of the field. In
the winter of 1858–59, Madam E. Seiler, having heard of Czermak's
experiments, had a laryngeal mirror constructed from his description,
practised laryngoscopy successfully on herself and others, among them
the writer, with a view to study the physiology of the voice. Her
efforts being crowned with success, she was able not only to verify
Garcia's observations in regard to the registers, but also discovered
the so-called head register of the female voice, as well as two small
cartilages in the vocal cords.14
11 Proc. Royal Society of London, vol. vii. No. 13, 1855.
12 Zeitschrift der Ges. der Aerzte zu Wien, April, 1858.
13 Wien. Medicin. Wochenschrift, March, 1858.
14 Altes und Neues, Leipzig, 1861.
HISTORY OF THE RHINOSCOPE.—Rhinoscopy, or the art of viewing the
naso-pharyngeal space by placing a small mirror behind the velum
palati, naturally suggested itself almost as soon as any attempts at
laryngoscopy were made, but in the literature we find that Bozzini was
the first to clearly express the idea.15
15 Loc. cit.
A number of years later Wilde endeavored to see the opening of the
Eustachian tubes by means of a small mirror: an account of these
experiments he published in his famous work on the diseases of the ear.
In 1836, Baumès used the rhinoscope, and claimed to have seen
ulcerations in the naso-pharyngeal cavity.16 It remained, however,
for modern times to develop this field of research, and it is again
Czermak whom we have to thank for the perfection of this valuable means
of diagnosis.
16 Loc. cit.
THE LARYNGOSCOPE.—The laryngoscope as it is used at the present day,
both by the specialist and the general practitioner of medicine,
consists of a so-called laryngeal mirror and of an illuminating
apparatus more or less complicated. The laryngeal mirror is a small
circular glass mirror mounted in a metal frame varying in size from ¾
inch to 1½ inches in diameter, and attached to a wire stem at an angle
of 120°. This stem, about 4 inches in length and about
1/10 inch in
thickness, should be soldered to the back of the mirror in such a
manner that the rim of the frame forms the angle with the stem, and
should not be below it, as this would increase the diameter of the
instrument without increasing its reflecting surface. The stem is made
to slide into a hollow handle of wood, ivory, or ebonite, and is
clamped at any desired length by a set-screw. This arrangement is
preferable to having the stem permanently fixed in the handle, inasmuch
as the stem can be pushed entirely into it, thus economizing space and
rendering the instrument more portable, and also allowing an adjustment
of the length of the stem when in use. The handle should be 4 inches in
length, and of the thickness of an ordinary lead-pencil (Fig. 1).
|
FIG. 1.
|

|
|
Laryngeal Mirror.
|
Mirrors of various shapes have been used, but it has been found that
the circular form is the one most easily borne by the patient, and can
be used in a greater number of cases than any other shape, at the
same time giving the largest reflecting surface for its size. However,
in cases where an hypertrophy of the tonsils is present an oval mirror
can be introduced between the protruding glands more easily than a
round one.
This laryngeal mirror, however, would be of little or no value as an
instrument of diagnosis if used by itself, for in order to see the
cavity of the larynx it must be illuminated, lying as it does far below
the level of the back of the tongue; and this cannot be done
satisfactorily by merely allowing ordinary daylight to fall into the
oral cavity. It becomes, therefore, necessary to use a stronger light
to illuminate the larynx, and for this purpose either direct or
reflected artificial or sunlight may be used.
Direct illumination, by allowing a strong artificial light or sunlight
to fall into the patient's mouth, although it is used by several of the
eminent laryngologists of Europe, is both inconvenient and
unsatisfactory, because the observer must either place his head in the
path of the light in order to be able to see the surface of the
laryngeal mirror, as in the case when sunlight is used, or he must
place the lamp, candle, or other source of light between himself and
the patient, which materially interferes with the freedom of his
motions. For these reasons reflected light is now almost universally
employed in laryngoscopy.
Reflected light may be obtained by throwing the light of a lamp,
candle, gas-jet, or light from any other source into the mouth of the
patient by means of a round concave reflector. This concave
mirror—which, when made of glass, should be silvered and not backed
with amalgam—is from 3 to 4 inches in diameter, and should have a
focus of from 12 to 14 inches. The metal frame in which it is mounted
is attached by means of a ball-and-socket joint to some contrivance by
which it can be supported on the observer's head or be attached to the
source of illumination if a stationary artificial light, such as a
gas-lamp, is used at the physician's office.
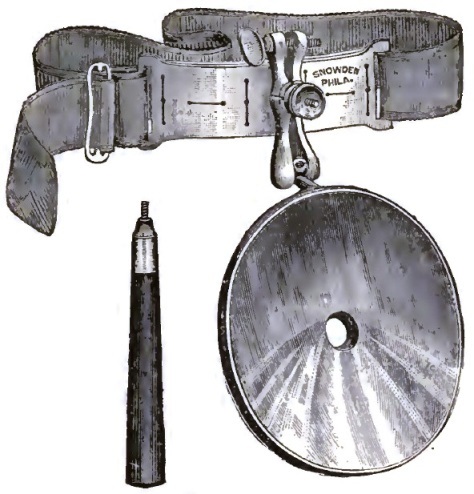
A variety of devices for fastening the reflector on the head of the
observer is in use, among which the head band, introduced by Cramer,
will be found the most serviceable. It consists of a broad strap of
some strong material which passes around the head and is fastened at
the back by a buckle. To the part of the band or strap resting on the
forehead is attached a padded plate, to which the reflector is fastened
with its ball-and-socket joint (Fig. 2). The reflector usually either
has a small hole in the centre or a small space in the centre is left
unsilvered. This opening is intended to be brought before the pupil of
one or the other eye of the observer in such a manner that the line of
vision and that of light have exactly the same direction. Using the
reflector in this way like the reflector of the ophthalmoscope, it is
easier to obtain the image of the larynx well illuminated, but with the
great disadvantage of monocular vision, which makes all objects
appear on the same plane and prevents a correct interpretation of
distances—a very important point in laryngoscopy. It will therefore be
found more advantageous to place the reflector on the forehead, and
from thence reflect the light into the patient's larynx. Both eyes may
thus be employed in viewing the laryngeal image, and a correct idea of
the relations of parts in regard to distance may be formed.
|
FIG. 2.
|
|
|
Head Reflector.
|
The line of vision and the path of the beam of light in order to obtain
the best results should be in the same plane as though the light
emanated from the pupil of the observer; but practically the position
of the reflector upon the forehead is nearly as good as when the hole
in it is brought before the eye, because a line drawn from the pupil of
the eye to the laryngeal mirror, and a line from the reflector upon the
forehead to the mirror, do not form an angle sufficient to make any
very great difference in the reflection of the light downward, and very
little difficulty will be experienced in obtaining the desired image.
The head reflector should be concave when artificial light or ordinary
daylight is used, but be plane when direct sunlight is employed, for
the concentration of the sun's rays by a concave reflector produces so
much heat as to become painful to the patient.
THE SOURCE OF LIGHT.—As an artificial source of light a candle, coal
oil lamp, gas-flame, or incandescent electric lamp suffices for
ordinary purposes. But frequently it is desirable to have a much
stronger light than can be obtained without concentration, and several
forms of apparatus for concentrating artificial light have been
constructed and are in use. Among these, Tobold's lamp and Mackenzie's
light concentrator are the most convenient and most universally used.
Tobold's lamp consists of a brass tube containing several lenses, which
are placed, one before the other, at such distances as to give the
greatest possible amount of concentration of light. The back part of
the tube is closed, while near the end two large holes are cut in its
sides opposite to each other, through which the chimney of the lamp
projects. The whole is fastened by means of clamps to a stand, to which
is also attached a jointed arm bearing the reflector. This apparatus is
used either in connection with a student's lamp or with an argand
gas-lamp, and it will be found very convenient to have it mounted upon
a gas-bracket which can be raised and lowered and swung from side to side.
Mackenzie's light concentrator consists of a cylinder of sheet iron
about 6 inches long by 2½ in diameter. Near one end a hole is cut in
the side of the cylinder, and a short piece of tube holding a
condensing lens is attached to the edge of the hole. This lens, which
is plano-convex with a spherical curve, and of 2½ inches diameter, is
placed with the plane side toward the light. This concentrator is
intended to be slipped over the chimney of an argand burner, and should
be so adjusted that the centre of the flame corresponds with the centre
of the lens. It may, however, be used in connection with a student's
lamp, incandescent electric lamp, or even a candle, giving in all cases
a very satisfactory light, which, however, must be reflected from the
head mirror into the patient's mouth.
The best light, however, when the examinations are conducted in the
office of the physician, is the electric incandescent light, which
presents numerous advantages over the gas or oil lamp. It is more
brilliant and whiter than any other suitable artificial light, giving
off neither gases nor heat, nor does it consume the oxygen in the room;
and since the introduction and perfection of storage batteries it has
become available and convenient for use in private houses. Numerous
experiments which the author has carried on for some time have resulted
in the application of this form of light for laryngoscopy in two ways
which are both very satisfactory. The incandescent lamp is mounted upon
the universal gas-bracket in place of the argand burner, and either the
Tobold lamp or Mackenzie's light concentrator is slipped over it, so
that it comes opposite the centre of the lens. In fact, the electric
lamp is substituted for the gas-burner, and the whole apparatus is used
as described above. The arc light may also be used in the same manner,
but does not give as satisfactory results on account of its unsteadiness.
|
FIG. 3.
|
|
|
The Author's Electric Illuminator for the Laryngoscope.
|
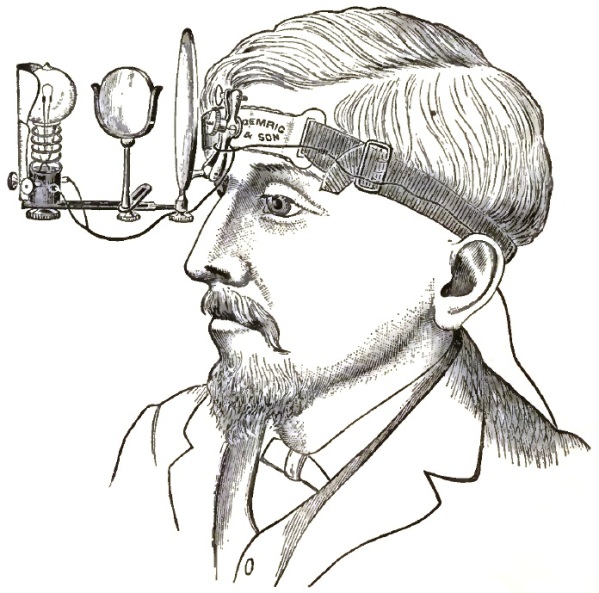
The second method is to mount the electric lamp on the head mirror in
such a way that it projects a little from the surface and is a little
to one side of the centre of the reflector (Fig. 3). The light is then
thrown forward in a cone, and can be directed with great ease into the
mouth of the patient. Since thus the source of the light moves with the
mirror, the observer can follow the motions of the patient more easily;
and if, in the first place, an easy position of the head has been
assumed when adjusting the light, much less fatigue is experienced
by the examiner with this apparatus than when the light is reflected
from a stationary source. Still another mode of using the incandescent
lamp, which was suggested by Trouvé, is to mount the lamp within a tube
one end of which is closed by a plano-convex lense, while the other end
is covered by a metal cap carrying in its centre a ball-and-socket
joint, by means of which it is fastened to the frontal plate of the
head band. In this way the light with its condensing apparatus is
carried on the forehead like the head mirror.
Sunlight is certainly the best source of light for the illumination of
the interior of the larynx and nasal cavities, but, unfortunately, it
is not available at all times and in all localities. When it can be
obtained, however, the student should not neglect the opportunity, and
should not be deterred from using it for examination by the little
extra apparatus and trouble necessary.
The most convenient plan is to place a small plane mirror mounted upon
a stand in such a manner that it can be turned in any direction, such
as a small toilet-glass, in the direct rays of the sun coming through a
southern window. Then turn the mirror until the reflection falls upon a
second plane mirror supported by a jointed arm and placed in a distant
corner of the room, and in front of the chair upon which the patient is
seated, with his back to the first mirror. The light from the second
mirror is then thrown into the patient's mouth in the same manner as
when a light concentrator is used. The second mirror may also be
mounted on the head band and used as a head reflector, but this latter
plan is not as satisfactory, because the reflected light from the first
mirror is apt to strike the observer's eye and temporarily blind him.
Sunlight, as well as the light from the oxyhydrogen and electric-arc
lamps, is white, and therefore shows us the parts in their natural
coloring, which is claimed as a great advantage over all other sources
of light. It is true that the yellow rays which are predominant in all
other artificial lights make the mucous membrane appear redder than it
really is, and the observer may be led to believe that a congestion
exists if the patient be examined by white light first, and then by
yellow light on different occasions. But as all our knowledge and
appreciation of shades of color depend upon a comparison with a
standard, it makes no difference whether this standard, as in the case
before us, is a little redder when viewed by yellow light or not so red
when seen by white light. This advantage of the white light is,
therefore, not of much practical value, and the expense and
difficulties connected with the use of the oxyhydrogen or electric
arc-light for laryngoscopy fully outweigh any advantage which can be
claimed for it.
THE ART OF LARYNGOSCOPY.—Before entering upon a description of the
details of the art it will be necessary to clearly understand the
optical principle upon which the use of the laryngoscope is based, and,
further, to remember that the object to be viewed is situated below the
straight path of light and vision. The optical law referred to is, that
"The angle of incidence is equal to the angle of reflection," and
consequently, in order to illuminate the cavity of the larynx and to
see its details, the laryngeal mirror must be placed in such a position
in the fauces that the light is reflected downward. The light rays
forming the laryngeal image will then be reflected from the surface of
the laryngeal mirror into the eye of the observer. It should always be
borne in mind that the image seen in the mirror is a reflected one,
like the image of one's self seen in a looking-glass, so that what
appears to be right is left, and vice versâ. On account of the
difference in height of the parts forming the image, and because the
mirror must be placed above and slightly behind the opening of the
larynx, the picture appears reversed in an antero-posterior direction.
The same holds good when viewing a drawing of a laryngeal image.
POSITION
OF PATIENT AND OBSERVER.—The relative positions of the
patient, observer, and the source of light are of very great
importance, especially to the beginner, and a want of proper adjustment
will often make it extremely difficult, if not impossible, to obtain
the desired view of the larynx. The patient having been seated upon a
chair, or better still upon a piano-stool, the source of light is
placed upon a table at his right, at such a height that the centre of
the flame is on a level with his eyes and a few inches behind. The
observer then takes a seat directly in front of the patient, and,
separating his knees, places his feet on either side of those of the
patient, thus being able to grasp the patient's knees with his own
should occasion require him to do so. This position is preferable to
the one in which the knees of the observer are either on one side or
the other of the patient's knees, because then the observer, in order
to throw the light from the head mirror into the mouth of the patient,
has to assume a constrained position which very soon becomes fatiguing.
Under no circumstances should the patient be allowed to grasp the
observer's knees, for then the latter is powerless to restrain the
struggles of his patient, and cannot quickly leave his seat should
vomiting occur. When the examination is made at the physician's office
or wherever it is practicable, it is of advantage to have a head-rest,
such as photographers use, for the patient's head.
The positions having been taken, the observer places the head reflector
upon his forehead a little above the left eye, and by rotating it upon
its ball-and-socket joint reflects the light from the lamp- or
gas-flame upon the patient's face so that the circle of light is
bounded above by the tip of the nose and below by the tip of the chin.
It is of great importance that the adjustment of the reflector should
be made by means of its joint, and not by rotating or inclining the
head, for it is necessary that the head should have an easy position
which can quickly be resumed should it become necessary to move the
head. It requires considerable practice to quickly reflect the light
from the head mirror in any desired direction, and it is therefore well
for the beginner to practise this by throwing the light upon a spot on
the wall before he attempts to examine a patient, as he will thus save
himself, as well as the patient, unnecessary annoyance. If a light
concentrator be used which supports the reflector on the jointed arm,
this of course is not necessary, but the practice with the head mirror
will even then be found advantageous, because when a patient is to be
examined in the sick room a light concentrator cannot usually be
employed, and the physician has to fall back upon the head mirror for
illuminating the laryngeal cavity.
When the reflector has thus been properly adjusted the patient is
required to incline his head backward and open his mouth as wide as
possible, when it will be found that the centre of the circle of light
falls upon the root of the uvula. A careful examination of the oral
cavity, the anterior and posterior pillars, the tonsils, and the wall
of the pharynx should be made before the laryngeal mirror is
introduced, not only because the condition of these parts often imparts
valuable information, but also in order to be sure that no infectious
sores be present which might contaminate the instruments to be
introduced. The laryngologist cannot be too careful to prevent the
carrying of infectious material from one patient to another; and if he
should by this preliminary examination discover a specific sore, he
should use only such instruments as are reserved for this class of
cases, and which are kept in a separate box or drawer of the
instrument-case.
Everything being in readiness, the laryngeal mirror is held over the
lamp, with the glass side down, for a few seconds until it is warm, so
as to prevent the condensation of moisture on its reflecting surface,
and is then introduced in the following manner: The handle is held
between the thumb and fore finger of the right hand like a pen-holder
(Fig. 4); the hand is bent backward upon the wrist and held below
the chin of the patient. Meanwhile, the protruded tongue is grasped
between the folds of a napkin or towel held in the left hand, and
gently but firmly pulled out of the mouth. Great care should be
exercised to prevent the frænum of the tongue from coming in contact
with the sharp edge of the front teeth, for this soon becomes very
painful and may prevent a successful examination. Many laryngologists
are in the habit of letting the patient hold his tongue, which becomes
necessary when operations or applications are to be made to the larynx;
but for the purpose of examining only it is better for the observer to
hold the tongue, as he thus gains more control over the movements of
the head of the patient.
|
FIG. 4.
|
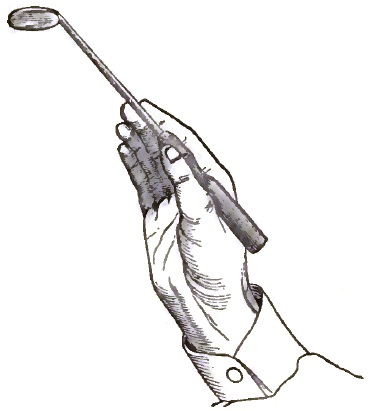
|
|
Position of Hand in holding the Laryngeal Mirror.
|
The mirror is now rapidly introduced into the mouth of the patient,
without touching the tongue or the palate, and carried backward until
its rim touches the wall of the pharynx, when it is lifted upward,
carrying on its back the uvula, and the stem is brought into the angle
of the mouth, so as to be out of the line of vision (Fig. 5). In this
position the light of the reflector will fall upon the reflecting
surface of the laryngeal mirror, and will be reflected downward so as
to illuminate the laryngeal cavity and reflect the laryngeal image into
the eye of the observer.
|
FIG. 5.
|
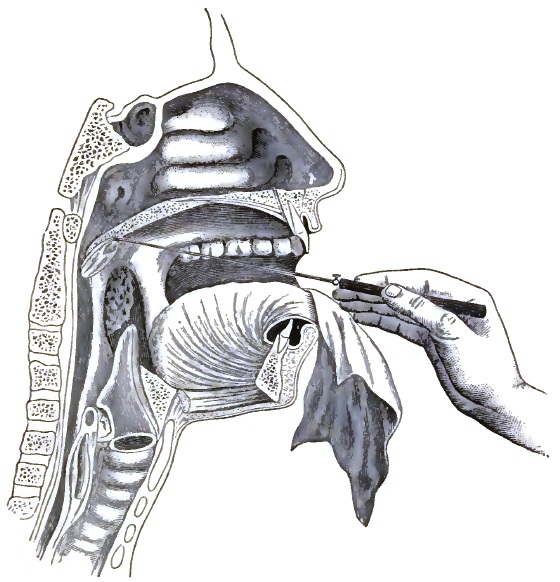
|
|
Diagram of Section of Head, showing the Position of
Laryngeal Mirror in the Pharynx.
|
There are, however, numerous obstacles and difficulties which must
be overcome to successfully practise laryngoscopy—obstacles which are
partly due to the want of skill on the part of the operator, and partly
to over-sensitiveness and want of control of the patient, or, finally,
to abnormal positions of the parts. Taking them up one by one, in the
order named above, the reader will soon learn to overcome these
obstacles by practice and careful attention to details.
As has already been pointed out, a satisfactory view of the laryngeal
image cannot be obtained if the position of the light, of the patient's
head, and of the observer is not properly arranged; further, if the
laryngeal mirror is either too cold or too hot. In the former case the
moisture of the breath will condense on its reflecting surface and
render it non-reflecting, and in the latter case the patient will feel
the heat and will object to the presence of the mirror in the fauces.
The examiner should therefore carefully test the temperature of the
mirror on the back of his hand before introducing it. Many
laryngologists are in the habit of testing the temperature by placing
the mirror against the cheek, but this is a dangerous practice, for a
slight scratch or abrasion of the skin from shaving may be inoculated
with infectious material from a specific sore, and the writer knows of
more than one instance in which such infection has occurred; while a
scratch on the hand is not so likely to be overlooked, and therefore
the danger is much less. Pulling too hard upon the tongue, so that the
frænum becomes injured by the edge of the teeth, is another obstacle,
for the patient will not bear the pain thus occasioned. Touching the
tongue or palate in the act of introducing the mirror, besides coating
the reflecting surface with the secretions of the mouth, causes in most
patients gagging, and should therefore be avoided. When the mirror has
been introduced it should be held very still, and if it becomes
necessary to rotate it, this should be done slowly and steadily,
because the slightest trembling motion of the rim of the mirror resting
against the wall of the pharynx produces gagging and cuts the
examination short at once. It is therefore advisable to steady the hand
holding the mirror by placing the third finger against the cheek of the
patient, or, better still, against the thumb of the hand holding the tongue.
Undue irritability of the fauces is of very rare occurrence, and is
almost invariably produced by one or the other of the above-mentioned
mistakes of the examiner. When it does exist independently, it can in a
measure be overcome by letting the patient drink a large draught of
ice-water immediately before introducing the mirror, and by holding the
mirror so that it does not touch either the pharyngeal wall or the
palate. In this manner but a very unsatisfactory view of the larynx can
be obtained, and it is better to overcome the irritability by practice
on the part of the patient—i.e. by introducing the mirror frequently
and removing it before gagging sets in, and by directing the patient to
introduce a teaspoon into the fauces before a looking-glass several
times a day. Even the most obstinate cases can thus be educated to
allow of a lengthy examination. No matter how tolerant a patient may
be, however, the mirror should never be left in the fauces after the
first symptoms of gagging show themselves, but should at once be
removed. It is better in all cases to leave the mirror in the mouth but
a short time and to introduce it frequently, thus studying the
different parts of the image one after the other, than to attempt to
see everything at once. In laryngoscopy, as in many other arts, not
only the hand, but also the eye, must be educated to appreciate all the
details and the variations from the normal.
Among the malformations of the parts which present obstacles to
laryngoscopy are, in the first place, hypertrophied tonsils, which by
narrowing the space in the fauces make it impossible to introduce the
ordinary-sized mirror. A smaller mirror or one of oval shape can,
however, usually be slipped past the enlarged glands and the
desired image obtained. An elongated uvula does not exactly prevent a
view of the larynx, but it materially interferes with a good image,
because its end by hanging below the rim of the mirror is seen in the
reflecting surface and obscures part of the image. Removal of the uvula
by surgical means is of course the best remedy.
The third and most serious obstacle presented by malformation or
malposition of parts is a pendent epiglottis—i.e. an epiglottis
which by being bent too far over covers the laryngeal opening and
prevents a view. This obstacle exists to a certain extent in most cases
that come under observation, but is easily overcome by letting the
patient sound the vowel sound of eh, which causes a rising of the
epiglottis and opens the laryngeal cavity to view. There are some
cases, however, in which this expedient does not sufficiently raise the
epiglottis to obtain a glimpse of the vocal cords, and only the
arytenoid cartilages are seen, from the motion and color of which we
can often obtain valuable information in regard to pathological
processes. In these cases, when it becomes absolutely necessary to see
the whole extent of the vocal cords, we may succeed by causing the
patient to laugh in a high key, but when this fails the only resource
left is to lift the epiglottis by grasping its upper margin with a pair
of curved forceps especially designed for this purpose and called
epiglottis forceps (Fig. 6). If this instrument is not at hand, the
same object may be attained by clasping the edge of the epiglottis with
a bull-nose forceps, to which is fastened a string weighted at the
other end by a small weight, such as a rifle-bullet. The string with
its weight hanging out of the mouth of the patient makes traction upon
the forceps, and thus the epiglottis is raised. In cases of operation
within the laryngeal cavity this method of raising the epiglottis is
even preferable to the epiglottis forceps, because it leaves the hands
of the operator free to use the mirror and the instrument to be used in operating.
|
FIG. 6.
|

|
|
Elsberg's Sponge-holder and Epiglottis Forceps.
|
AUTO-LARYNGOSCOPY.—There is perhaps no better method for the beginner
to overcome the difficulties besetting laryngoscopy than to practise
the art on himself, for then only will he be able to appreciate to its
full extent the necessity of observing all the minute details described
above, as the pain and inconvenience which he inflicts upon himself by
his false movements will teach him better, and enable him to attain
proficiency in the use of his instruments quicker than any other method
of practice. Nothing need, for auto-laryngoscopy, be added to the stock
of instruments necessary for the examination of others, except a stand
to which the reflector is fastened and a small toilet-mirror. The
observer seats himself beside a table upon which, at his left, is
placed the lamp a little behind his head and the centre of the flame on
a level with his eyes. The stand, an ordinary retort-stand, is placed
in front of him, and to it is fastened at the proper height the
reflector. On the same stand, and immediately above the reflector, is
attached the plane mirror in such a manner that it can be inclined at
an angle. Inclining the head slightly backward, the observer then by
watching his face in the plane mirror directs the light upon his mouth
by moving the reflector upon its ball-and-socket joint until the circle
falls upon his mouth. He then opens his mouth as wide as possible,
grasps his protruded tongue between the folds of a towel or
napkin
held between the thumb and fore finger of the left hand, and introduces
the laryngeal mirror with the right hand in the manner described above.
The laryngeal image as it appears on the surface of the laryngeal
mirror is reflected by the toilet-glass above the reflector, and can be
seen in all its details by the person practising auto-laryngoscopy. By
substituting a perforated mirror for the toilet-glass the student can
demonstrate the image to others in his own person if the observers look
through the perforation in the mirror.
Before giving a description of the laryngeal image it will be well, for
the sake of completeness, to mention the fact that of late photography
has been employed to reproduce this image, both in this country by T.
R. French of Brooklyn17 and by Lennox Browne of London, England, with
very gratifying results. The writer himself several years ago made
experiments in this direction, which, however, were not very
satisfactory in their results. The method employed by French is a very
simple one, and it will be best to give his own description of the
process:
"The camera consists of a box 4½ inches long,
17/8 inches
wide, and ¾ of an inch in thickness. The back opens upon hinges, and
admits of the introduction of either the ground glass or the
plate-holder. On the anterior face a tube
11/8 inches long is
attached, in the outer end of which the lens is placed. This lens has a
focus of 1¼ inches. At the side of the tube a part of the handle of a
throat mirror is fixed, and into that the shank of the throat mirror is
passed and fastened by a thumb-screw. The shank of the mirror is
somewhat curved, and is attached to the side of the frame holding the
mirror. The object of this is to allow the lens being held opposite any
part of the opening of the mouth, and also to prevent the possibility
of a shadow being cast upon the mirror. In the front part of the box is
a shutter made of lead and perforated with a hole just the size of the
lens. The shutter is held in position by a lever acting as a key on the
anterior face of the camera.
"The apparatus is used in the following manner: A reflector, either
plane or concave, attached to a head band, is arranged over the left
eye so that the pencil of sunlight from the solar condenser is received
upon it and thrown into the mouth. The patient, with the head inclined
slightly backward, now protrudes the tongue and holds it well out
between the fore finger and thumb of the right hand. The throat mirror
with the camera attached, held in the right hand of the observer, is
placed in position in the fauces, and the light adjusted so that the
larynx can be seen with the observer's left eye to be well illuminated.
If, now, the tongue does not mount above the level of the lower edge of
the lens and the lower edge of the mirror, it may be taken for granted
that when the plate is exposed the picture received upon it will be
nearly the same as that seen with the left eye in the throat mirror.
The photograph is taken by pressing upon the key with the index finger;
this releases the shutter, which in falling makes an instantaneous
exposure amounting to perhaps one-seventh of a second.
"In using condensed sunlight with a small camera it is important to
throw the circle of light from the inner side of the reflector, that
nearest the nose; for in this way a part of the larynx exposed to the
lens of the camera may be illuminated which cannot be seen with the
eye. To ensure this it is best to cover the outer half of the reflector
with black silk. On account of the parallax or displacement of the
image due to the difference in point of view between the eye and the
camera, some skill is necessary in managing the illumination so that
the part which it is desired to bring out will be exposed to the lens
if not to the eye."
17 Archives of Laryngology, vol. iv. No. 4.
THE LARYNGEAL IMAGE.—When the mirror is introduced and is held in the
proper place, and the light is reflected downward, the laryngeal image
will appear on the surface of the mirror. As it is, however, so
different from what might be expected after having examined a larynx
removed from the body, it requires a detailed description, and the
student will do well to refer to the diagrams frequently while
examining patients, to make himself familiar with the details he sees,
and to recognize them when they are altered by disease or when they are
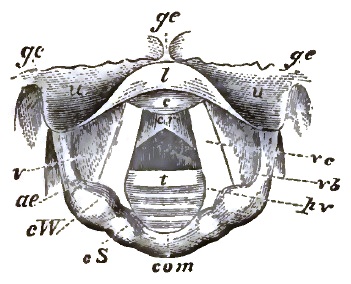
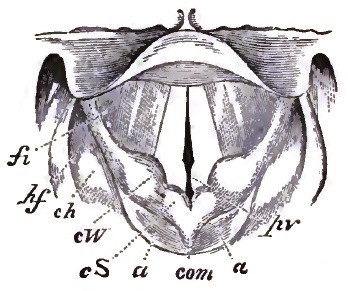
slightly different in shape in different individuals. Figs. 7 and 8
represent the image of the larynx in the act of respiration and of
phonation as it appears on the surface of the mirror, while Figs. 9 and
10 are diagrammatic, and are intended to represent the same.
|
FIG. 7.
|
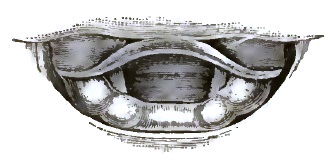
|
|
Laryngeal Image during Respiration.
|
|
FIG. 8.
|
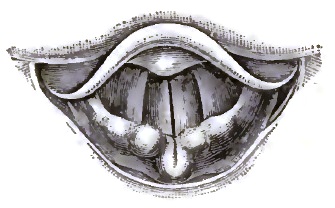
|
|
Laryngeal Image during Phonation.
|
|
FIG. 9.
|
|
|
Laryngoscopic Diagram showing the vocal cords
widely drawn apart, and the position of the various parts above and
below the glottis during quiet breathing. g. e. Glosso-epiglottic
fold. s. u. Upper surface of epiglottis. l. Lip or arch of
epiglottis. c. Protuberance of epiglottis. v. Ventricle of the
larynx. a. e. Ary-epiglottic fold. c. W. Cartilage of Wrisberg.
c. S. Cartilage of Santorini. com. Arytenoid commissure. v. c.
Vocal cord. v. b. Ventricular band. p. v. Processus vocalis.
c. r. Cricoid cartilage. t. Rings of trachea. (From Mackenzie.)
|
|
FIG. 10.
|
|
|
Laryngoscopic Diagram showing the approximation
of the vocal cords and arytenoid cartilages, and the position of the
various parts during vocalization. f. i. Fossa innominata. h. f.
Hyoid fossa. c. h. Cornu of hyoid bone. c. W. Cartilage of
Wrisberg. c. S. Cartilage of Santorini. a. Arytenoid cartilages.
com. Arytenoid commissure. p. v. Processus vocalis and cartilages
of Seiler. (From Mackenzie.)
|
The first detail to attract the eye is the epiglottis, which appears as
a yellowish-red arch reaching from side to side across the image. It is
thicker in the middle than at either end, and a protuberance is usually
seen in the centre pointing forward. This arch is the upper margin of
the epiglottis, and the protuberance is the tubercle, situated near the
insertion of the epiglottis into the thyroid cartilage. The shape as
well as the color of the epiglottis is very variable in different
individuals, being sometimes rounded as in the drawings, sometimes
rolled up like a dried leaf, sometimes notched in the centre, and
sometimes presenting a point at this place. However, all these
variations in shape have nothing to do with any pathological process,
and may therefore be termed normal. The color of the organ also varies
from a bluish-yellow to a pink-red, and these variations are also
normal, being due to a greater or less thickness of the tissue covering
the cartilage, which by shining through imparts its bluish color to the
tissue. The superficial blood-vessels also are more prominent in some
individuals than in others, and may not be noticeable in some cases.
Immediately behind the epiglottis we see two pit-like depressions,
separated from each other in the middle by a fold of mucous membrane
and bounded on either side by similar folds less prominent. These folds
are the glosso-epiglottic ligaments, and serve to connect the tongue
with the epiglottis, while the depressions are the glosso-epiglottic
grooves, in which we usually find the foreign bodies which have
accidentally been swallowed.
The ends of the epiglottic arch are lost in folds of mucous membrane,
which run forward and inward to meet in the median line some distance
in front of the epiglottis. Along their course several nodules of
different size are noticed, which are symmetrically situated on either
side. The one nearest to the epiglottis is the cartilage of Wrisberg, a
small cartilaginous nodule imbedded in the tissue. The larger one,
situated at the end of the fold of mucous membrane, is the arytenoid
cartilage, and a third small nodule is noticed close to the arytenoid
cartilage between it and the cartilage of Wrisberg, which is called the
capitulum Santorini. The folds of mucous membrane are termed the
aryteno-epiglottidean or ary-epiglottic folds. Their color is normally
of a pinkish-red, and does not vary much in different individuals.
The arytenoid cartilages forming the ends of the ary-epiglottic folds
are movable, approaching and separating alternately during the act of
respiration, while during phonation they are pressed against each
other, thus obliterating the space between them which is seen when they
are separated. This space is the inter-arytenoid space or commissure,
and is formed by the lateral walls of the arytenoid cartilages and the
upper margin of the posterior portion of the cricoid cartilage. The
mucous membrane in this commissure is very loosely attached to the
deeper structures, and is thrown into folds by the approximation of the
arytenoid cartilages. Its color is much lighter than that of the
ary-epiglottic folds, due to the shining through of the cricoid
cartilage. Outside of the ary-epiglottic folds and the inter-arytenoid
commissure is the tissue forming the posterior and lateral walls of the
oesophagus (not shown in the diagrams), and near the epiglottis a space
called the pyriform sinus is noticed between the ary-epiglottic folds
and the wall of the oesophagus.
Running from the epiglottis to the ary-epiglottic folds are two broad
bands, one on either side, covered with mucous membrane and of a
pinkish-red color, which are lost on either side in the tissue forming
the walls of the laryngeal cavity, while toward the middle of the image
they present concave and tolerably sharp edges. These are the
ventricular bands, which were formerly termed the false vocal cords,
and which form the lip to the opening of the ventricle of the larynx.
Between the ventricular bands filling up the central portion of the
image are seen the vocal cords, two bands of a pearl-white color which
are attached to a cartilaginous process of the arytenoid cartilages,
and run from these parallel with each other to the angle of the thyroid
cartilage immediately below the tubercle of the epiglottis. These
present sharp edges toward each other, and follow the motions of the
arytenoid cartilages to which they are attached, so that when in
inspiration the cartilages are separated the edges of the vocal cords
are also some distance apart, forming, together with the
inter-arytenoid commissure, a triangular opening called the glottis.
That portion of the opening which is bounded on either side by the
edges of the vocal cords alone is called the membranous portion, while
the base of the triangle is termed the cartilaginous portion, being
bounded on either side by the vocal processes of the arytenoid
cartilages. This portion is readily distinguished from the membranous
portion by its slightly yellow color, and by the fact that a very
obtuse angle is formed at the junction of the two portions when the
glottis is wide open during respiration. Through the open glottis the
lower edge of the cricoid cartilage and several of the rings of the
trachea can usually be seen, and there are a few cases in which even
the bifurcation of the trachea can be dimly illuminated, showing in the
laryngeal image the openings of the bronchi. The distance is,
however, too great for bright illumination, and nothing can be seen
distinctly, so that it is of little value in a diagnostic point of
view. During phonation the glottis is narrowed to a slit by the
approximation of the arytenoid cartilages and inner edges of the vocal
cords, and, as has already been stated, the inter-arytenoid space
becomes obliterated. In the higher notes of the female voice, the
so-called head tones, the cartilaginous portion of the glottis remains
closed entirely, while the membranous portion appears as an elliptical
opening which is diminished in its longitudinal diameter with each rise
in pitch. This becomes possible because of the presence in the vocal
cords of a slender rod-like cartilage attached to the end of the vocal
process, which can readily be seen in the female larynx, but which is
only rudimentary in the male.
This description, intentionally, has been made without reference to the
anatomical relation of the parts, but to give a clear idea of what is
seen in the laryngeal mirror. The reader should therefore always bear
in mind that the laryngeal image, being a reflected one, is reversed,
and that, on account of giving a bird's-eye view of the larynx from a
point above and behind the organ, distances are materially diminished;
and the image is also reversed in an antero-posterior direction, so
that the epiglottis appears to be posterior when in reality it is anterior.
RHINOSCOPY.—Rhinoscopy, or the art of inspecting the nasal cavities
and the naso-pharyngeal space, is divided into two portions—viz.
anterior and posterior rhinoscopy; and it will be convenient to observe
this division in the following description of the methods employed. But
before proceeding with the description it will be well to briefly
review the topographic anatomy of the parts, because in most works on
general anatomy the nasal and naso-pharyngeal cavities are discussed in
a few sentences, and they are rarely if ever examined in the
dissecting-room, so that the student has but a very imperfect knowledge
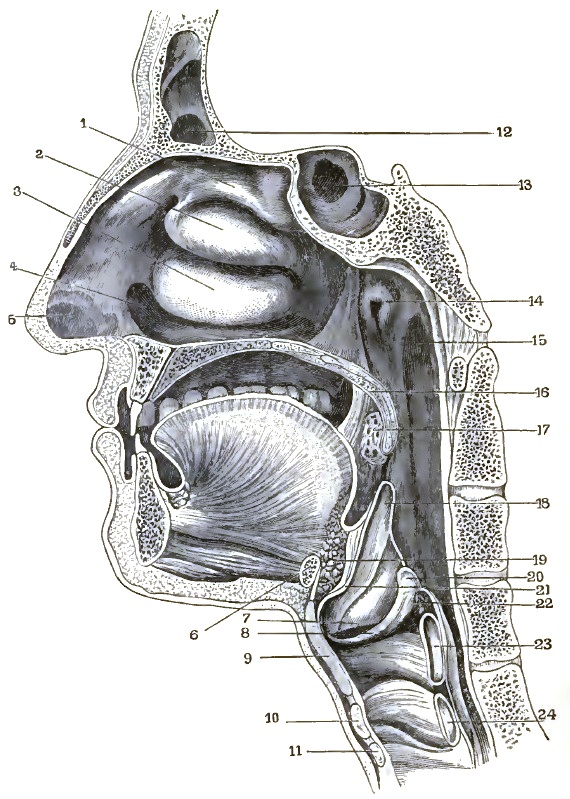
of the relation of the parts belonging to these cavities. (See Fig.
11.) The nasal cavities, which are wedge-shaped, with a narrow arched
roof, extend from the nostrils to the upper portion of the vault of the
pharynx. Their outer walls are formed by the nasal process of the
superior maxillary and lachrymal bones in front; in the middle, by the
ethmoid and inner surface of the superior maxillary bones; behind, by
the vertical plate of the palate bone and the internal pterygoid
process of the sphenoid and the turbinated bones. These latter run
before backward, three on each side, and are designated as the
inferior, middle, and superior, the latter being the smallest of the
three. The sinuses or spaces between these turbinated bones are called
meatuses; so that the space between the floor of the nose and the lower
turbinated bone is called the inferior meatus, the one between the
lower and middle turbinated bones is the middle meatus, and the one
between the middle and superior turbinated bones is the superior meatus.
|
FIG. 11.
|
|
|
VERTICAL SECTION OF HEAD,
SLIGHTLY DIAGRAMMATIC.
|
|
1. Superior turbinated bone. 2. Middle turbinated bone.
3. Lower turbinated bone. 4. Floor of nasal cavity. 5. Vestibule. 6.
Section of hyoid bone. 7. Ventricular band. 8. Vocal cord. 9 and 23.
Section of thyroid cartilage. 10 and 24. Section of cricoid cartilage.
11. Section of first tracheal ring. 12. Frontal sinus. 13. Sphenoidal
cells. 14. Pharyngeal opening of Eustachian tube. 15. Rosenmüller's
groove. 16. Velum palati. 17. Tonsil. 18. Epiglottis. 19. Adipose
tissue behind tongue. 20. Arytenoid cartilage. 21. Tubercle of
epiglottis. 22. Section of arytenoid muscle.
|
The nasal cavities are separated from each other by a septum or
division wall composed of the perpendicular plate of the ethmoid bone
and the vomer posteriorly and the cartilaginous septum anteriorly, thus
presenting a smooth surface as the inner wall of each cavity. The floor
is formed by the palatine process of the superior maxillary bone and by
the palate bone, and runs in a slanting, downward direction from before
backward. The roof is formed by the nasal bones and nasal spine of the
frontal in front, in the middle by the cribriform plate of the ethmoid,
and posteriorly by the under surface of the body of the sphenoid bone.
Directly communicating with the nasal cavities are other cavities
situated in the bones of the skull, the lining mucous membrane of which
no doubt is largely affected by the pathological processes in nasal
diseases: these are the antra of Highmore, large triangular cavities
situated in the body of the superior maxillary bone and communicating
with the nasal cavities by an irregularly-shaped opening in the middle
meatus;
then the frontal sinuses, two irregular cavities situated
between the two tables of the frontal bone. The communication between
them and the nasal cavities is established by the infundibulum, a round
opening in the middle meatus, and finally the sphenoidal cells or
sinuses, found in the body of the sphenoid bone, communicating with the
nasal cavities by small openings in the superior meatus. That portion
of the nasal cavities which projects beyond the end of the nasal bone
is surrounded by cartilages forming the alæ of the nose.
In the cartilaginous septum of the lower animals we find a small cavity
lined with mucous membrane, called after its discoverer Jacobson's
organ, the minute anatomy of which has lately been described by
Klein.18 This
organ in man is, however, only rudimentary. The
nasal cavities are lined with mucous membrane, which varies greatly in
thickness in different localities, and which materially decreases the
size of the cavities in the living subject from that seen in the
denuded skull. This mucous membrane is covered by ciliated epithelium
in man, with the exception of that portion which lines the
vestibule—i.e. that portion of the cavity of the nose surrounded by
cartilage only—which is covered by pavement epithelium.
18 Quarterly Journal of Mic. Science, January, 1881.
In the lower animals we find that in the olfactory region the ciliated
epithelium is either absent, or that ciliated and non-ciliated
epithelium alternates in patches.19 The author has not been able to
find a statement in the literature on the subject as to the kind of
epithelium found in the accessory cavities in man, but it is very
probable that the mucous membrane of the frontal sinuses and the antra
of Highmore is covered with ciliated epithelium; otherwise it would be
difficult, if not impossible, for the secretions of that mucous
membrane to pass through the narrow channels into the nasal cavities.
The color of the normal nasal mucous membrane is of a light pink shade
in what is termed the respiratory portion, while it is of a yellowish
hue in the olfactory region, that portion of the mucous membrane which
covers the roof and the outer walls of the nasal cavities down to the
upper margin of the middle turbinated bone and the septum down to about
the same level. It is in this region that the nerve-ends of the
olfactory nerve are distributed. Immediately beneath the mucous
membrane, and between it and the periosteum of the bony walls and the
perichondrium of the cartilaginous portion of the septum, we find a
tissue which bears a striking resemblance to the erectile tissue of the
genital organs.20 It is composed of a network of fibrous tissue, the
trabeculæ of which contain a few organic muscular fibres. Its meshes of
various sizes and shapes are occupied by venous sinuses lined with
endothelium. These are supplied with blood by small arterioles and
capillaries, which are quite numerous in the fibrous tissue and can
readily be demonstrated under the microscope. In this arrangement of
elements of the nasal mucous membrane we find a ready explanation of
the fact that liquids of greater or less density than the serum of the
blood when introduced into the nasal cavities produce pain, for we have
here the most favorable conditions for osmosis, which will cause either
a contraction or a distension of the sinuses. In the larger masses of
fibrous tissue between the sinuses or caverns we find imbedded the
glands, with their ducts opening out between the epithelial cells of
the mucous membrane. There are two kinds of glands in this region,
which have been described by Klein21—viz. serous and mucous glands.
19 Haenle, Anatomy des Menschen, vol. ii.
20 Haenle, loc. cit.
21 Loc. cit.
This cavernous erectile tissue is most abundant at the lower portion of
the septum and of the lower turbinated bones; and, although it has been
recognized and described as true erectile tissue by Haenle, Virchow,
and others, yet to Bigelow of Boston belongs the honor of having first
called attention to the part which this tissue plays in nasal diseases.
He gave to it the name turbinated corpora cavernosa.22 The expansion
of the nasal cavities formed by the alæ of the nose is termed the
vestibule, which is lined with pavement epithelium and forms the
entrance to the cavities proper. The naso-pharyngeal cavity extends
from the posterior ends of the turbinated bones and the edge of the
vomer to the line where the velum palati touches the pharyngeal wall
during the act of deglutition or phonation. In this cavity we find the
openings of the Eustachian tubes, two crater-like elevations, with a
pit-like depression of variable size and shape, one on either side; and
a collection of glands with a central duct-like opening disposed on the
roof and posterior wall of the cavity. This gland was named by
Luschka23 the pharyngeal tonsil. The openings between the edge
of the vomer and the lateral walls of the naso-pharyngeal cavity are
termed the posterior nares.
22 Boston Med. and Surg. Journal, April, 1875.
23 Der Schlundkopf des Menschen.
ANTERIOR RHINOSCOPY.—Anterior rhinoscopy is a very easy and simple
procedure, and is practised as follows: The patient is placed in
position as for laryngoscopy, and the light directed upon his face so
that the centre of the circle of reflection from the head mirror falls
upon the tip of the nose. The examiner then elevates the tip of the
nose with his left hand, resting the fingers on the forehead of the
patient, and lifts the ala away from the septum with a slightly bent
probe, when he will be enabled to see a considerable distance into the
nasal cavity. It is, however, better to employ a speculum instead of
the bent probe, because the parts then are seen in their usual relation
to each other, and are not distorted by the forcible traction necessary
when the probe or a dilator is employed. The nasal speculum (Fig. 12)
is best made of hard rubber and shaped like the ordinary ear speculum,
except that the narrow end is oval instead of round. This instrument is
to be introduced by a sort of rotatory motion until the end has passed
the edge of the vestibule, when it will remain in position, displaying
the interior of the nose. Great care should be exercised, when
introducing the speculum, not to scratch the mucous membrane of the
septum, for this will give rise to pain and start hemorrhage, both of
which are to be avoided as much as possible. When applications are to
be made to the mucous membrane of the septum or turbinated bones, or
when operations are to be performed within the cavity, it is best to
employ an instrument called a nasal dilator, of which there are a large
number of different forms, the most satisfactory of which is shown in
Fig. 13. The dilator is introduced by compressing the blades between
the thumb and fore finger, and pushing them into the nostril until
their ends have passed the edge of the vestibule. The pressure is then
removed, and the spring separating the blades holds the nostril open;
the handle or stem of the instrument, hanging down, need not be held or
supported, as the blades press sufficiently upon the tissues to retain
the instrument in position. If the pressure is too great, however, it
will soon produce pain, and the patient will object to the use of the instrument.
|
FIG. 12.
|

|
|
Nasal Speculum.
|
|
FIG. 13.
|

|
|
Bosworth's Nasal Dilator.
|
The view obtained both by the speculum and the dilator is rather
limited, and usually comprises only the anterior portions of the lower
and middle turbinated bones, together with the cartilaginous portion of
the septum. In order to get a good view of the lower and middle meatus
and of the floor of the nose the patient's head should be inclined
forward or backward as occasion requires. The student should, however,
not be satisfied by simply inspecting the parts, but should aid the eye
by the sense of touch, for pathological changes are of common
occurrence, and their nature, whether soft and fleshy or hard and bony,
erosions of the mucous membrane, or deep ulcerations, can often only be
determined by the aid of the probe. In the same manner can the
permeability of the meatuses be determined better than by inspection
only. In cases where it becomes necessary to determine whether the
anterior portion of the septum is of normal thickness, or whether a
projection seen through the speculum is due to localized deflection, an
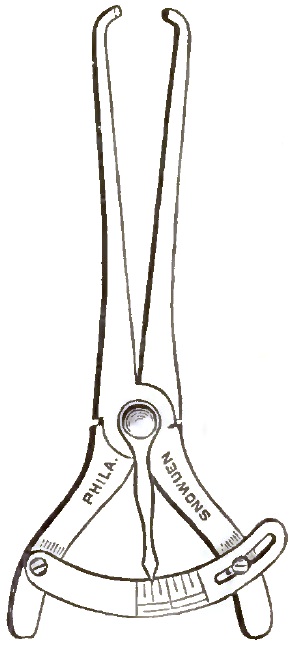
instrument called the septometer is of great assistance (Fig. 14). This
instrument is similar to the one used by mechanics to determine the
diameter of a piece of wood or iron being turned on the lathe. In using
it the long straight shanks are introduced one in each nostril, and,
being closed upon the septum, the rounded points are gently moved up
and down and backward and forward over the bulging portion of the
septum. The motion of the index attached to the curved shanks of the
instrument accurately indicates the relative thickness of tissue
grasped between the points in the nose. By means of this instrument we
can thus ascertain whether we have to deal with a deviation or a
localized thickening of the septum; for if it is a deviation the index
will move but slightly, while it will travel a considerable distance
when the points pass over a thickened portion.
|
FIG. 14.
|
|
Septometer for Measuring
Thickness of Nasal Septum.
|
Although simple in its details, anterior rhinoscopy is often made
difficult or altogether prevented by obstacles which are mostly due to
malformation of the parts, such as deviation of the cartilaginous
portion of the septum, exostoses from the superior maxillary bones
reaching into the nasal cavity, adhesion between the anterior portion
of the lower turbinated bone and the septum, nasal polypi, anterior
hypertrophies of the mucous membrane, and so forth; or they may be due
to faulty instruments, as too much pressure in the spring of the
dilator; or, finally, they may be caused by want of care in the
handling of the instruments, as when the septum is scratched by the
edge of the speculum and hemorrhage ensues.
POSTERIOR RHINOSCOPY.—Posterior rhinoscopy is much more difficult than
laryngoscopy or anterior rhinoscopy, and requires more patience and
dexterity on the part of the examiner than either of the former,
because but very few persons have control over the movements of the
velum palati, and in most of these the upper portion of the pharyngeal
wall is so sensitive that the slightest touch with an instrument gives
rise to reflex cough and to gagging. In many cases, however, with
patience and skill the naso-pharyngeal cavity and the posterior portion
of the nasal cavities can be illuminated and inspected. To do this the
patient is placed in the same position as for laryngoscopy, except that
the head is not inclined backward, and after the mouth is opened as
wide as possible the light from the reflector is thrown into the oral
cavity. The tongue is then depressed with a tongue depressor. This
instrument in its simplest form in which it is daily used by the
practitioner for examining the fauces is the handle of a spoon. For
laryngoscopic or rhinoscopic purposes, however, the spoon is not to be
recommended, because the hand holding it must be on a level with the
mouth, thus obstructing the view and light. An instrument has therefore
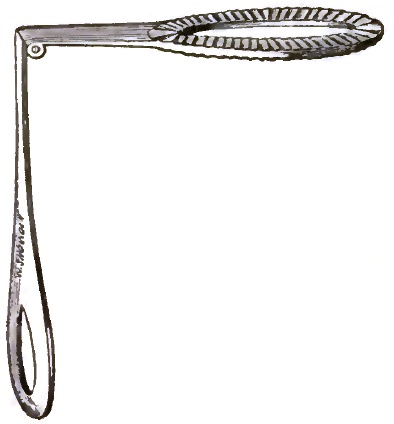
been constructed which obviates this difficulty. It consists of a
leaf-shaped blade of silver or German silver bent at right angles and
inserted into a flat wooden handle. The lower surface of the blade is
slightly concave, and ribbed so as to take a better hold of the
slippery back of the tongue, and from the bend is about 3 inches in
length. It is introduced into the mouth as far back as possible, and
pressed upon the back of the tongue while the hand of the examiner is
below the chin of the patient. For the sake of convenience in carrying
the instrument the blade has been so hinged to the handle that it will
fold up against the latter and will open at a right angle with it
(Fig. 15). A more elegant and lighter instrument of the same
description has lately been introduced in which the handle is also made
of metal, and, like the blade, is heavily nickel-plated, and which when
folded can be carried in a pocket-case. Soon, however, the metal tongue
depressor becomes tarnished by the secretions of the mouth or by the
substances used for applications to the throat, and then presents an
appearance disgusting to many patients, who will not on that account
submit to its use. For the sake of greater cleanliness, J. Solis Cohen
devised a tongue depressor made of hard rubber, which is known as
Cohen's tongue depressor (Fig. 16). It consists of a piece of ebonite
bent upon itself, either end being a little over 3 inches long. The
bend being more than at right angles, the hand holding the instrument
rests underneath the chin of the patient; but if a different curve be
desired for any particular case it can easily be obtained by placing
the instrument for a little while in hot water. When soft it can be
bent into any shape, which it will retain when cooled by immersion in
cold water. Great care should be exercised not to carry the blade of
the instrument too far back, as then gagging will at once set in. In
cases where the tongue resists the pressure of the tongue depressor, it
is better to exert but a gentle pressure upon the back of the organ,
under which it will slowly recede, than to try to subdue it by force,
for in the latter case it will unavoidably slip from under the blade of
the instrument, and the desired space in the fauces is not obtained.
With children the writer has found the fore finger of the left hand to
be the best means of depressing the tongue, for the little patients as
a rule have a horror of the formidable-looking instrument.
|
FIG. 15.
|
|
|
Folding Tongue Depressor.
|
|
FIG. 16.
|

|
|
Cohen's Tongue Depressor.
|
After the tongue has subsided into the floor of the mouth a small
laryngoscopic mirror is introduced into the pharyngeal space behind the
velum palati, with the reflecting surface upward, and is held there
without touching the wall of the pharynx. The handle of the mirror, as
in laryngoscopy, is brought into the angle of the mouth, so as to be
out of the line of vision. As is usually the case, the velum palati at
the approach of the mirror will rise and apply itself to the posterior
wall of the pharynx, when of course the naso-pharyngeal space, being
shut off, cannot be illuminated. Under these circumstances the velum
must be made to hang down as in the act of nasal respiration, which is
most easily accomplished by telling the patient to breathe through his
nose. It is of course impossible to do so when the mouth is open, but
the patient, not being cognizant of the fact, will make the attempt,
and the palate will come down, permitting illumination and inspection
of the naso-pharyngeal space and the posterior nares. In those cases in
which this expedient fails it becomes necessary to forcibly pull
down the velum by means of a blunt hook made by bending a silver
laryngeal probe, or to tie it down by passing small elastic bands
through the anterior nares and bringing the ends through the mouth and
tying them over the upper lip. The smallest black rubber tubing is
admirably suited for this purpose, as it can be introduced without an
instrument. When the palate is pulled down with the palate hook, or
when operations in the naso-pharyngeal space are to be performed, the
patient must hold the tongue depressor himself, so as to leave the
other hand of the operator free. Few persons can do this, however,
satisfactorily, and it will be found more convenient to use Jarvis's
tongue depressor and rhinoscope, as modified by the writer (Fig. 17).
The instrument consists of a stout wire, which, after having been
forked or divided at some distance from its insertion into the handle,
forms the loop for the tongue depressor. The two branches then cross
each other, and are bent to form another loop at an angle to the larger
one. The ends of the wire are somewhat flattened and press against each
other, thus closing the smaller loop and forming a sort of pincette,
which can be opened by pressing the sides of the larger loop toward
each other. The ends of the pincette are perforated by a small hole,
which receives a pin attached at right angles to the short shaft of a
small mirror, thus forming a hinge, so that the mirror can be placed at
any desired angle with the handle or stem. The spring of the pincette
cannot be made strong enough to prevent a change of the angle of the
mirror by coming in contact with the pharyngeal wall, and therefore a
ratchet was placed at the shaft of the mirror where it hinged to the
end of the pincette, and a small steel spring, coming from one of the
branches of the wire where they cross each other to form the small
loop, by engaging in the teeth of the ratchet holds the mirror at the
angle given to it before introducing. The large loop acts as a tongue
depressor, so that with this admirable instrument the examination of
the post-nasal cavity can be made with one hand, leaving the other free
for the manipulation of other instruments. In order to be able to exert
more pressure upon the tongue and to bring the hand out of the line of
vision, the handle may be attached to the stem at an angle like the one
in the folding tongue depressor. Except in cases of cleft palate the
naso-pharyngeal cavity cannot be illuminated in its whole extent, and
must be studied in parts, which when placed together in the mind of the
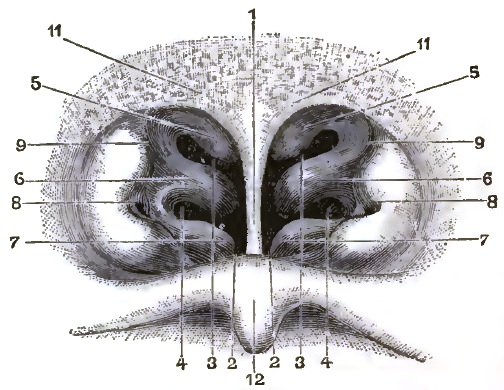
examiner form the rhinoscopic image, a slightly diagrammatic drawing of
which is seen in Fig. 18.
|
FIG. 17.
|

|
|
Jarvis's Rhinoscopic Mirror and Tongue Depressor.
|
|
FIG. 18.
|
|
|
RHINOSCOPIC IMAGE.
|
|
1. Vomer or nasal septum. 2.
Floor of nose. 3. Superior meatus. 4. Middle meatus. 5. Superior
turbinated bone. 6. Middle turbinated bone. 7. Inferior turbinated
bone. 8. Pharyngeal orifice of Eustachian tube. 9. Upper portion of
Rosenmüller's groove. 11. Glandular tissue at the anterior portion of
vault of pharynx. 12. Posterior surface of velum.
|
THE RHINOSCOPIC IMAGE.—In the middle of the drawing we see a
triangular plate with its apex downward; this is the posterior margin
of the vomer or nasal septum. On either side we notice curtain-like
folds projecting against the septum; these are the posterior aspects of
the turbinated bones. On either side of these and on the margin of the
drawing we notice pointed elevations projecting toward the interior of
the cavity, with a crater-like depression on their apices; these
are the lateral pharyngeal walls with the orifices of the Eustachian
tubes. Above we see the vault of the pharynx, and below the posterior
surface of the velum palati with the uvula.
Another method of examining the laryngeal and naso-pharyngeal cavities,
which is especially valuable in cases where neoplasms or impacted
foreign bodies hide the parts forming the laryngoscopic and rhinoscopic
images, is by means of digital palpation. Even where no obstruction is
present the beginner will do well to resort to this method in all
cases, for he will thus become better acquainted with the topography of
the parts than by inspection only. The procedure is not as difficult
nor as disagreeable to the patient as might be imagined, and needs but
little description.
When the laryngeal cavity is to be examined by palpation, the head of
the patient is thrown back, and steadied in that position by the left
hand of the examiner while he introduces the index finger of the right
hand into the mouth and slides it along the back of the tongue until
the tip comes in contact with the upper margin of the epiglottis.
Passing downward along its lateral margin on either side, the
ary-epiglottic folds and the tips of the arytenoid cartilages can be
felt, and likewise the upper surfaces of the ventricular bands. The
vocal cords are, as a rule, too low down to be reached by the tip of
the finger. An examination of this kind should of course be made
quickly while the patient is holding his breath, so as not to obstruct
respiration too long, which in cases of narrowed glottis by neoplasms
might give rise to serious results. When the naso-pharyngeal space is
to be explored by the finger, the patient's head is bent forward, and
the index finger is gently pushed upward between the velum and the
pharyngeal wall. When this is accomplished, the velum is drawn forward
and the finger pushed along its posterior aspect until the different
portions forming the rhinoscopic image are reached and explored by the
sense of touch.
Coryza is an acute inflammation of the mucous membrane of the nasal
chambers. The disease is ordinarily idiopathic, but may be produced by
irritative vapors, pollen, or dust. In the idiopathic form the symptoms
of coryza are often preceded by malaise, with chilly sensations, and in
severe attacks with headache. The attack itself is divided into two
stages: that of determination or congestion, and that of exudation. In
the first stage the excessive quantity of blood flowing into the
arterio-venous network and the capillaries of the nasal mucous membrane
distend them and obstruct the nasal chambers.
The symptoms are referable either to such obstruction of nasal
respiration—in which group are included oral respiration, sensations
of distension, and throbbing in the nose—or to reflexes, such as
frontal headache, attacks of sneezing, and dull aching pain in the teeth.
The first stage lasts for a period varying from a few hours to several
days, and is followed by the stage of exudation. This is characterized
by a free watery or mucoid discharge from the nasal chambers, and by
the cessation of the symptoms due directly or indirectly to pressure of
the layers of swollen mucous membrane against each other. The discharge
at first is watery, and is doubtless composed of transuded liquor
sanguinis. It is followed by a mucoid fluid, which in severe or
neglected cases may assume a purulent character. In many instances,
even in mild cases, the discharge becomes muco-purulent toward
recovery. The second stage is associated in children and adults of
delicate constitution with excoriations of the nostrils.
Suppuration may take place in nurslings and in old people. It would
appear that in coryza, as it exists in the northern countries of
Europe, the beginning of the second stage is apt to be marked by free suppuration.
Acute coryza may involve the sinuses of the face, particularly the
maxillary sinus. The involvement of the frontal and sphenoidal sinuses,
while possible, is infrequent. Pharyngitis, laryngitis, and
occasionally acute aural catarrh, often coexist with the disease.
The symptoms of coryza are so distinctive that the diagnosis is easily
made. But since any obstructive or catarrhal state of the nose is
described by patients as a cold in the head, it is necessary for the
medical attendant to distinguish the various diseases so denominated.
Acute coryza may be confounded with angiose hypertrophy; with the
obstruction to nasal respiration due to deflection of the nasal septum
or to an inflamed soft polypus; with catarrhal irritation affecting
surfaces which are already enlarged by hyperplasia or which are
undergoing atrophy; or with the effects of operative interference in the nose.
In angiose hypertrophy the swollen membranes will contract under a mild
current of electricity or by change in the position of the body.
Both chambers are rarely involved at the same time. Reflexes are of
infrequent occurrence. Obstruction to nasal respiration due to a
deflected septum arises from causes which are insignificant and do not
affect the constitution. The genuine influenzal or catarrhal element is
absent. In an inflamed soft nasal polypus an attempt at inspiration
will, as a rule, detect the presence of the growth. In diffuse multiple
polypi the case is different. Many persons who are reputed to take cold
readily, or who may be said never to be free from cold, are really
sufferers from neglected polypi. Persons suffering from atrophic
catarrh always speak of an exacerbation of their symptoms as a fresh
cold, and describe the disease itself as a cold. The sense of fulness,
the throbbing, the heat, and the characteristic discharge of coryza are
absent. A fresh cold in atrophic catarrh is an attack of inflammation
(often catarrhal in character, it is true) which affects the involved
surfaces, but is attended with an increase of plastic exudation and
accompanying fetor.
It is a common occurrence for patients who have had a cautery
application made or a polypus removed to return after a few days'
absence with the report that they have contracted a cold. While the
condition may be an attack of acute coryza, the chances are in favor of
the symptoms being excited by the manipulation or the reaction from the
operation. The symptoms are mild in character.
TREATMENT.—The treatment of coryza is both local and constitutional.
The local treatment consists in applications of agents which tend to
constrict the vessels of the nasal mucous membrane. In the first rank
of such agents may be named cocaine, which in a 2 per cent. or a 4 per
cent. solution will often give notable relief by overcoming the sense
of obstruction. Individuals will be found in whom the effect is of
short duration, and in some persons I found the medicine to have no
effect whatever. In more favorable subjects the relief will be
acknowledged for a period varying from four to six hours. Next in rank
may be named a current of constant electricity (say from six to ten
cells) passed through the cheeks. Should neither of the above-named
agents be available, inhalations of iodine vapor, a few drops of
chloroform rubbed upon the palms and inhaled, or the inhalation of the
spirits of ammonia may be recommended. Toward the later stages of the
disease detergents and mild astringents are well borne. The
constitutional treatment includes the administration of diaphoretics
and minute doses of opium, especially in the early stages of the
disease. Coryza is commonly self-limited, and by far the larger number
of cases do not come under the care of the physician.
Chronic nasal catarrh embraces those more or less persistent affections
of the nasal chambers whose symptoms resemble those of acute coryza.
The term catarrh is inexact. It is used to include several diseases
associated by a single characteristic—namely, the existence of an
increased amount of mucous secretion upon the affected membranes.
In order to understand the varieties of nasal catarrh, it is necessary
to have clear conceptions of the uses of the nasal chambers. The normal
performance of the function of respiration demands that when the mouth
is closed the currents of air should pass through the nose. These
currents, however, do not sweep over the entire nasal surfaces, but are
confined to those portions which answer to the inferior meatus and the
space bounded within by the septum, without by the median surface of
the inferior turbinated bone, and above by the under surface of the
middle turbinated bone. In the lower mammals this space is separated
posteriorly by a transverse bony lamina which effectively excludes
the upper portion of the nasal chambers from the tract just named.
Anteriorly, at the termination of the inferior meatus and the middle
turbinated bone, the tract is in freer communication with the upper
spaces. The passage thus briefly defined may be called the respiratory
tract, and when it remains patulous no serious interference with nasal
respiration can occur.
The transverse diameters of the tract are subject to frequent changes,
owing to the erectile character of the mucous membrane in its walls.
But as long as the surfaces do not touch one another obstruction cannot
exist. The passage, even when narrowed to a chink or line intervening
between the median and lateral walls of the tract or between the floor
and the roof of the inferior meatus, is sufficient evidence that there
is room for the transit of the currents of air. The membranes
themselves are subject to changes in form which are dependent upon the
degree of development of their erectile tissue.
There is doubtless a disposition on the part of the erectile tissue to
grow in the direction of the least resistance, and thus to occupy, by a
process of compensative hypertrophy, the spaces left as the result of
variations or defects in development in the bones composing the
framework of the nasal chambers. The greater development of the
erectile tissue may in this way be found on the side answering to the
larger respiratory tract, which may therefore be more apt to suffer
from changes in the conditions of nasal breathing than the chamber
having the smaller tract. The erectile tissue acts as a monitor to the
throat and lungs by presenting warm surfaces over which the air passes,
thereby having the temperature raised before it enters the throat and
lungs. It also acts by occluding the chamber, and thus aids in shutting
out irritant vapors and dust. The lower animals possess a higher degree
of development of the tissue at the point where the adducted ala
presses against the septum. This point answers to the position of the
organ of Jacobson. With man, the locality of the adduction corresponds
to the junction of the premaxillary with the maxillary portion of the
nasal chambers, and is often the seat of a delicate band of mucus
extending across from the inferior turbinated bone to the septum.
That portion of the nasal chamber above the respiratory tract may be
called the olfactory tract. It does not appear to be involved in the
diseases under consideration, or, if it is, no clinical signs or
symptoms are presented with which the author is acquainted. It will
therefore receive no attention in this article.
For convenience the varieties of chronic catarrh may be classified as
follows:
FIRST VARIETY—that dependent on defective nasal respiration.
This variety is caused by—
(a) Osseous obstruction in the nasal chamber.
(b) Membranous obstruction in the nasal chambers from compensatory
hypertrophy of the erectile tissue, alone or with hyperplasia.
(c) Obstruction arising from hypertrophy of the adenoid tissue in
the pharyngeal vault.
(d) Contracture of the levator palati muscles.
SECOND VARIETY—that dependent on structural changes in the component
parts of the nasal chamber.
This variety is associated with—
(a) Chronic inflammation of the nasal mucous membrane without
hypertrophy of the erectile tissue.
(b) Atrophy of the turbinals and their associated mucous membrane.
(c) Necrosis of the bones which enter into the framework of the
nasal chambers.
FIRST VARIETY.—Defects in nasal respiration induce hyperæmia,
distension of the erectile tissue, hyperplasia of the mucous membrane,
and
inevitable distress in the nose. A sense of fulness across the
bridge of the nose and at its sides is complained of. Frontal headache
may be present.
(a, b) When the septum is deflected and the left nasal chamber is
narrowed, the labor of sustaining nasal respiration is thrown on the
right side. This arrangement invites a flow of blood to the already
large turbinals, and creates obstruction which is frequently referred
to the right side, although both are alike affected. Thus, subjects in
which the initial obstacle is osseous complain of distress caused by
cavernous-tissue hypertrophy of the lining membrane of the opposite
side. This represents a very common class of cases.
When the septum is not deflected, but projections from it impede the
current of air, there may be either unilateral or bilateral
obstruction, dependent upon the shape of the septum itself. Hypertrophy
of the cavernous layer of the mucous membrane usually coexists. These
cases are numerous, but less common than those last described.
Infrequently, cases are seen where the distress is occasioned by
defects of the osseous structures not accompanied by cavernous hypertrophy.
Treatment of the above disorders consists in restoring nasal
respiration by removing obstructions, whether they be osseous or
membranous. The septal projections may be drilled or filed away, or, if
marked deflection of the anterior portion be present dependent upon a
malposition of the triangular cartilage, an operation simple in
character may be performed for its correction. This consists in
severing the connection of the lower margin of the cartilage with the
maxilla and slipping the partially free cartilage to a new position.
The details attendant upon the operation need not be here given. The
reduction of the hypertrophied membranes can be best accomplished by
cauterization. The most efficient method is by means of the electric
cautery. The electrode used should be flexible and of small size. The
points which most frequently require cauterization are the premaxillary
portion of the inferior turbinated bone, the under surface of the same,
and the septum at the maxillary spur. Rarely the inferior surface of
the inferior turbinated bone at the palatal region requires attention.
The applications are best made over small surfaces at a time, and
should be repeated at intervals of from two to three days until all
suspected points have been at least once cauterized. Not infrequently,
the effect of the cauterization at one spot will cause constriction to
take place in the vessels of the entire mucous surface, so that while
this condition lasts it is impossible to tell what additional points of
the membranous obstruction demand removal. At the following visit,
however, the vessels have become relaxed, the membranes are again
turgescent, and if obstruction now occurs it can easily be detected.
The galvano-cautery can only be used in the nasal chamber in patients
who are earnestly seeking relief and are willing to assist the
physician in all his efforts. With the tractable, intelligent subject
it can with proper care be limited exactly to the spot intended. It is
scarcely necessary to observe that any erratic or unexpected motion of
the head will sear unaffected and sensitive surfaces. The interior of
the vestibule is perhaps the most sensitive of these, and should always
be protected by the use of the nasal speculum. No additional protection
is needed, though in the judgment of others, among whom may be
mentioned E. Shurly of Detroit, Michigan, an ivory shield passed in the
nose parallel to the electrode is a necessary safeguard.
The pain of the application is generally slight, and can be in part
annulled by a previous application of a 4 per cent. solution of
cocaine. Some annoyance is acknowledged on the following day from the
pressure of the eschar. Traumatic congestion of the entire mucous
surface of the corresponding chamber is at the same time detected, and
is usually sufficiently decided to produce some of the effects of acute
coryza. This condition will spontaneously terminate in from thirty-six
to forty-eight hours. The most annoying features
following an
application of the galvano-cautery which has been too freely made do
not belong to the group just indicated, but rather to reflex
disturbances. Pains are occasionally excited in the teeth, in the
temple, eye, nape of the neck, and the middle ear. On one occasion in
the writer's experience a unilateral reflex excitation of the entire
opposite side of the body occurred, and a prickling sensation, followed
by numbness, ensued, which lasted for twenty-four hours. Very rarely a
congestion of the pharynx, of the larynx, and the larger bronchial
tubes ensues, which can scarcely be directly attributable to the
application, yet it has followed in a sufficient number of cases to
lead me to believe that the two are in some remote way associated.
Perhaps such a condition is analogous to the slight irritation of the
respiratory tract following excision of the tonsil. Careful use of the
galvano-cautery will obviate the conditions above described. They are
important to remember as serving as limitations to the use of this
valuable agent.
(c) It will be seen that osseous obstruction in the nasal chamber and
hypertrophy of the cavernous nasal tissue often coexist. More rarely, a
third element occurs as a complication, or it may be found
independently of all other morbid processes. I allude to the presence
of hypertrophy of the adenoid tissue in the pharyngeal vault. When this
tissue is only moderately developed, it need not, and does not,
interfere with nasal respiration; but when it projects downward to such
a degree as to lie within the axis of the lower portion of the
posterior nares, it produces the same effect upon nasal breathing as
though obstruction existed within the chamber. The growths can be
easily detected, as a rule, from behind by the aid of the rhinal
mirror, but it should not be forgotten that they also can be seen from
in front, provided the chamber is free from obstruction along the
respiratory tract. In some individuals the ribbed or lobate structure
of the mass can be discerned, but more often its presence is revealed
by the minute points of light reflected from the lobules. If it be a
matter of doubt whether these points of reflection are within the nasal
chamber or beyond it in the pharyngeal vault, the patient may be
requested to swallow, or to pronounce the letter e; when, if the
point of reflection is within the nasal chamber, it will not change its
position, but if it be within the naso-pharynx, it will be moved
slightly from side to side, or it may for a moment disappear.
The symptoms of nasal catarrh which are provoked by the presence of
such a growth can be alone successfully treated by the removal of the
offending mass. In young individuals—say, from twelve to eighteen or
twenty years of age—the finger inserted into the naso-pharynx from
behind can often break down the growth. Slight hemorrhage follows this
procedure, and the tags of imperfectly-destroyed tissue can be
subsequently treated by caustics and powerful astringents. In the event
of the patient proving intractable, the growth may be reached from in
front through the nasal chamber, and the galvano-cautery can be used by
passing the electrode backward through the nostril until it meets with
resistance, which is invariably at the pharyngeal vault. Should this
method of treatment not be permitted by an undisciplined or nervous
person, the prolonged use of a glycerole of iodine may gradually reduce
them in size; but no definite result can be promised from such treatment.
(d) Very rarely, through inordinate elevation of the soft palate
owing to over-action of the levator palati muscles, the passage of
communication between the naso-pharynx and the oro-pharynx is
inadequate. Consequently, the nasal chamber is imperfectly ventilated,
and its secretions, not flowing backward or being displaced to the
normal extent, become semi-inspissated, and create obstruction by
lodging in the respiratory tract, either in the premaxillary or palatal
portions. To successfully combat this condition it is evident that no
local treatment is demanded, either in the nose or the naso-pharynx,
other than to increase the tonicity of the pharyngeal and palatal
muscles. Very frequently in such cases there is a symmetrical atony in
the muscles last named, which demands the internal use of strychnia and
iron and the application of galvanism.
PROGNOSIS.—When nasal catarrh has proved to be dependent on defective
respiration, the removal of the causes entering into this condition may
with reason be expected to effect recovery. The prognosis, therefore,
is favorable. In young persons, in whom reparative power is present in
the highest degree, and in whom a secondary hypertrophy of the
cavernous tissues is least developed, a prompt cure may be obtained by
removal of the osseous or other forms of obstruction. In adults,
however, the prognosis is less favorable, especially with those who
have approached or passed middle life, and who have contracted vicious
habits of breathing, which are likely to persist even after the removal
of their causes. It is also tenable that in such subjects the mucous
lining of the cranio-facial sinuses has become involved. Should anosmia
persist after the capacity of the chambers has been augmented—in a
word, should this condition not be dependent upon obstruction, but upon
changes in the olfactory surfaces—the prognosis is less favorable than
in any of the cases of the above-named group.
Treatment will, however, always secure amelioration of the symptoms,
and few cases occur which cannot be greatly improved. The general
health is invariably benefited. Should a tendency to asthma exist, it
is apt to disappear, the complexion clears, and in adolescence the rate
of general development is accelerated.
SECOND VARIETY.—The group of nasal diseases included under this head
is not a natural one, since it embraces disorders characterized by a
negative feature—viz. absence of obstruction to nasal respiration.
Nevertheless, it is convenient to consider under a single head a number
of relatively infrequent disorders in which there is invariably an
underlying constitutional cause. Subjects of disorders herein embraced
are not merely sufferers from insufficient oxygenation of the tissues,
but have impaired general vitality or possess a decided constitutional
taint, whether specific or otherwise. The nasal condition is simply the
most prominent of the local manifestations.
Three distinct disorders are herein named: first, chronic inflammation
of the nasal mucous membrane; second, atrophy of the turbinals and
their associated mucous membrane; third, necrosis of the bones entering
into the framework of the nasal chambers.
(a) Inflammatory thickening is a rare affection. It is more frequent
in males than in females, and in persons of a sedentary occupation than
in those who are actively employed. Those subject to it are apt to have
light-blue or gray eyes and auburn or sandy hair. On examination, the
chambers may be found free from peculiarities of bony structure,
capacious, and without hypertrophy of the cavernous tissues, yet the
membranes be of a deep-red color and of cushiony consistence, yield
bright reflexes, and the shank of the instrument introduced into the
nose is mirrored upon them. The most conspicuous alteration is not seen
on the turbinals, but on the septum. The parts are very vascular, and
the most moderate manipulation will often end in free capillary oozing.
The discharge, though moderate in quantity, is inclined to be purulent,
and resembles semi-coagulated albumen. Quite frequently, in the
examination of a neglected case, minute flecks of this modified
secretion are seen scattered over the septum and the inferior
turbinated bone. Rarely, the discharge is maintained by the presence of
a morbid growth or inflammatory products, either in the nasal chamber
or a chamber accessory to it. The discharge then appears to consist of
pure pus mixed with the normal secretion of the nose, and, thus
rendered viscid and tenacious, it excites by its presence a condition
of the lining mucous surface quite similar to that above described.
Under excitement, as after an attack of coryza, the discharge
becomes more serous in character, and is occasionally of a chocolate
color from its admixture with blood. It is without odor. There is no
obstruction to respiration except during sleep, when, in aggravated
cases, mouth-breathing may be established. Thus, the patient will often
complain of an obstruction which is never present at the time of the
examination. He further complains of a sense of dryness in the nose,
with some pharyngeal irritation. The palato-pharyngeal and
palato-glossal muscles are weak and often asymmetrical; the tonsils are
small, but the adenoid tissues are generally unaffected. In a dry
atmosphere, especially if it be loaded with irritating particles, the
pharyngeal irritation is increased—a complication which is probably
due to the inspired air passing too rapidly through the capacious and
imperfectly-guarded nasal chambers and throat. Although I have
carefully searched for all indications of aural complications,
especially for the symptoms of progressive dry catarrh, I have never
detected them but in a single instance.
The prognosis is to be guarded, although a careful course of treatment
and proper care of the general health will greatly improve, if not
entirely cure, the disease.
TREATMENT.—This consists in the application of nitrate of silver,
either in strong solution or in the solid stick, to the under surface
of the inferior and middle turbinated bones, of washing the parts with
a dilute solution of carbolic acid, and of passing through the cheek
tissues a constant electrical current of a strength of from five to ten
cells. Tonics and alteratives should not be neglected, and an outdoor
life, as far as is practicable, should be enjoined. The galvano-cautery
may be used to destroy any nodules of tissue which resist other
treatment. All applications are well borne, if indeed we may not look
upon the condition of the surfaces as partially analgesic, and thus far
of unfavorable significance. It is certain that indurated tags of
oedematous and chronically inflamed mucous membrane overlying a bone,
such as the middle turbinated or the alveolar line about the necks of
the teeth, will never yield to anything but the most powerful
astringents. Upon such tissues the most concentrated solutions of
nitrate of silver are never caustic. The premaxillary portion of the
inferior turbinated bone is frequently seen hopelessly infiltrated, and
it must then be destroyed by the electro-cautery. When a discharge of a
pus-like character exists, careful search should be made for the cause.
If a tumor or foreign body be found, it should be removed, but if the
cause lie in one of the outlying spaces of the nasal chamber, it is
evident that the above treatment is palliative only.
(b) In atrophy of the nasal mucous surfaces and turbinals we have, as
in the last-named group, spacious chambers, a purulent discharge,
pharyngeal irritation (in many cases), and always associated a thin and
relaxed, if not a paretic, condition of the velal muscles. These cases
might be looked upon as an advanced stage of the preceding affection,
since it may be surmised that the stage of infiltration has been
succeeded by one of atrophy. The mucous membranes are everywhere pale,
and closely bound to the underlying bony framework. The discharge is
purulent and confluent; where in contact with the air it is desiccated,
but where protected, as by crust-like surface-layers, it is semi-fluid
and tenacious. There is, consequently, no disposition for the discharge
to escape from the nose, and it accumulates until the sense of
obstruction induces the patient to remove it by artificial means. When
first seen, the nasal chambers are frequently so fully occupied with
discharge as to conceal the characteristic appearances of the mucous
surface. This prolonged retention induces incipient decomposition of
the mass, which gives rise to the odor so characteristic of this group
of cases.
The subjects of atrophic catarrh (ozæna) are never in robust health.
They are, as a rule, of spare habit, anæmic, and with family histories
which, while not distinctive, indicate that the affection is, to
some degree at least, hereditary. A few cases have come under my notice
in which all the general features of atrophic catarrh were present, but
with very slight although confluent discharge, unaccompanied by fetor.
Such cases are, strictly speaking, examples of atrophic catarrh, while
they could not, under the old nomenclature, be included under the head
of ozæna.
The prognosis is unfavorable for entire recovery, but treatment
systematically pursued will make the patient entirely comfortable to
himself and others—will arrest the progress of the disease and vastly
improve the general health. As in other forms of nasal disease, should
anosmia be present the prognosis is less favorable.
|
FIG. 19.
|
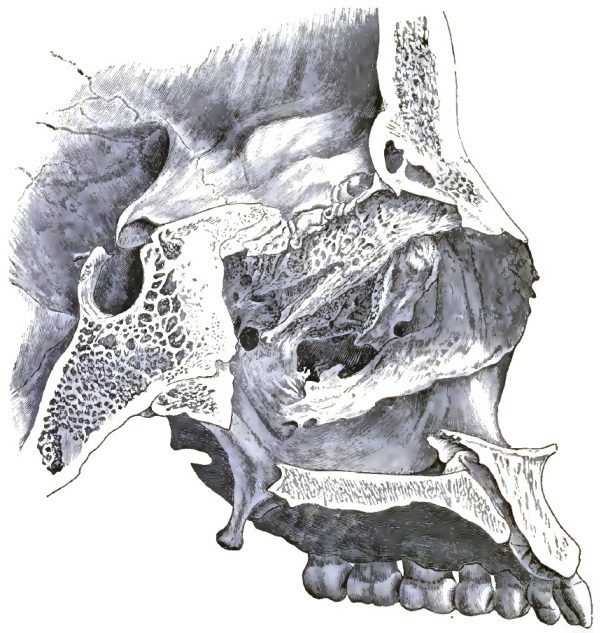
|
|
Antero-posterior section of the bones of the
face in position, showing the premaxillary portion of the floor of the
nose greatly elevated above the plane of the remaining portions. In
ozæna, as mentioned in the text, a disposition of parts may exist
similar to that delineated, and cause discharge to collect and undergo
offensive decomposition.
|
TREATMENT.—The parts should be carefully cleansed—an act which, while
imperfectly accomplished by either the syringe or the douche, is, in my
judgment, best performed by the galvano-cautery. This instrument, the
one relied upon for the subsequent treatment of the case, is to be
selected for its initiation. The largest speculum which the nose will
admit being placed in position, a spiral-looped electrode is introduced
cold into the nose and held against one of the crusts. When heated it
will effect so firm an attachment to it as to enable the mass to be
withdrawn with great ease. In patients with whom the palatal
portion of the floor of the nose is depressed below the level of the
maxillary a considerable quantity of discharge may lie concealed from
observation. When, after the removal of all visible crusts, the fetor
persists, it is reasonable to suppose that the palatal depression is
filled with decomposed pus and mucus. To test such a condition, the
electrode should be appropriately curved and introduced. I have been
surprised at the quantities of discharge which can in this way be
withdrawn from a locality which, as far as I know, cannot be cleansed
in any other way.
With the removal of the crust relief is at once experienced, and if the
discharge could be removed as fast as it forms the disease would not
really be a source of offence. The general health would also improve,
from the fact that an atmosphere tainted with a burden of decomposition
would no longer be breathed. But in practice this cannot be attained,
and it is imperative, after the chambers have been entirely cleansed,
to cauterize the lining membrane throughout. I have been in the habit
of beginning such cautery treatments with the middle turbinated bone,
passing thence to the inferior turbinated bone, then to the roof of the
nose in front of the sphenoidal sinus, and lastly to the septum. Small
surfaces only should be covered at a single treatment, so that it may
take a month or six weeks to finish a single series of applications.
This treatment is almost always well borne, nothing ever ensuing beyond
a slight headache or a temporary establishment of a serous discharge.
Notwithstanding that the condition in question is one of atrophy, the
reparative power of the mucous membrane remains apparently unaffected.
At all events, no danger from sloughing is to be dreaded after such
extensive destruction of tissue. The thin eschars separate within from
three days to a week, leaving a healthy mucous membrane beneath. In one
instance the cauterization had extended to a sufficient depth to expose
the bone, and yet from this denuded surface no exfoliation took place,
the parts healing rapidly and satisfactorily. No other local treatment
is relied upon for fetid atrophic catarrh than the one mentioned. No
disinfectant washes are required if the discharge is removed as
described. Should the patient be so situated as to be unable to report
regularly for its removal or treatment, a wash composed of one part of
Labarraque's solution to sixteen parts of water may be ordered with
advantage, or a solution of carbolic acid, gtt. j to fluidounce j, with
a little glycerin, may be snuffed up the nose twice a day, or
listerine, diluted one-half with water, may be used with advantage. The
general health, of course, should be cared for, and any complications
met. I have found that during the winter months arsenic and cod-liver
oil are well borne, associated with minute doses of Lugol's solution.
For adolescents earthy and the calcareous phosphates are indicated, and
for all abundant exercise and careful dieting. When the symptoms have
been relieved, the patient should be requested to report once a month,
for it is not to be expected that all symptoms will disappear, and some
point of advice can be advantageously offered at this interval.
(c) Necrosis in the nasal chamber is a cause of catarrh, inasmuch as
the fragments of bone lying within the nose excite irritation and
induce discharge. I have never seen a case of this form of disease
which was not due to syphilis. The remains of syphilitic angina are apt
to be present, and the general manifestations of constitutional
syphilis are well developed. The septum is more frequently affected
than the turbinals.
Discharge due to necrosis can be readily distinguished from that
arising from any other cause by the presence of detached fragments of
denuded bone, by the characteristic fetor, and by the history of the case.
The prognosis is favorable, for all symptoms will cease upon the
extraction of the fragments, or at least those which remain are of an
entirely different character, and are due to the resultant
imperfections of the septum, and consequent irritation arising from the
too free entrance of air into the nose. I have seen in one case an
extensive tumefaction and infiltration of the tissues covering the
middle turbinated bone at the same time that the septum was breaking
down. These masses require treatment with the galvano-cautery and
astringents after the dead fragments have been removed.
A TABLE OF NASAL DISEASES
GROUPED BY SYMPTOMS.
| Cases in which interference with nasal respiration
is a conspicuous symptom: |
| |
Due to deflection of nasal septum (common).
Due to angiose hypertrophy of the mucous membrane (common).
Due to tumors lodged in the nasal chamber.
Due to adenoid hypertrophy in the naso-pharynx.
Due to over-activity of the levator palati muscles (rare). |
| Cases in which discharge is a conspicuous symptom: |
| |
Due to hyperplasia of the mucous membrane over the turbinated bones
(common). The discharge when flowing backward is described as a
dropping; when forward, as a running at the nose. The discharge is
either mucoid or muco-purulent.
Due to tumors lodged in the nasal chambers or appendages. The
discharge is usually excessive. When due to myxomata (polypi) the
discharge is mucoid (common). In inflammatory complications of the
same the discharge is muco-purulent (common). When due to neoplasms
other than myxomata the discharge is purulent, and rarely
muco-hæmic (rare). |
| Cases in which retention of mucus in the nose or upper part of the
throat is a conspicuous symptom: |
| |
Due to retention of inspissated mucus at
the roof of the naso-pharynx (common).
Due to the mucous secretion of the nose and throat being excessively
tenacious (rare). |
| Cases in which fetor is a conspicuous symptom: |
| |
Odor putrid. |
Due to retention and decomposition of plasmic exudation from
atrophied bone and mucous membrane (common).
Due to necrosis of the bones within or bordering upon the nose (rare).
Due to decomposition of muco-pus in the maxillary sinus (rare). |
| |
Odor musty. |
Due to partial decomposition in small patches of desiccated mucous crusts (common).
Due to morbid secretion unaccompanied by profound alteration in the
structure of the nose (rare).
Due to ulcerations of the mucous membrane (rare). |
| Cases in which a sense of dryness is a conspicuous symptom: |
| |
Due to ineffective erectile tissue permitting air imperfectly warmed
to enter the nose and the pharynx (often met with in neurosis). It
is caused by temporary constriction of the erectile tissue or by
the atrophy of the tissue.
Due to neurosis. Neurotic patients will often complain of a sense of
dryness in the nose and the naso-pharynx when all the conditions of
excessive mucoid discharge are present. |
| Cases in which hyperæsthesia exists, so that slight lesions that in any
way interfere with the nasal functions form the basis of persistent complaint (not infrequent). |
Epistaxis, or nose-bleed, is a form of local hemorrhage perhaps of more
frequent occurrence than hemorrhage from any other mucous surface of
the body. This is doubtless owing to the extreme vascularity of the
lining membrane of the nose and the special arterio-venous (cavernous)
spaces of the turbinated bones; and the bleeding may be said to be of
grave character in proportion as these spaces are involved. In some
individuals a special disposition to nasal hemorrhage exists. From the
fact that the affection is transmitted from parent to offspring, and is
frequently found in all members of a given family, this form of
hæmophilia is probably dependent upon some structural peculiarities in
the cavernous spaces.
The causes of epistaxis are both local and general. Among the local
causes may be included traumatism, either from blows or other injuries,
attempts on the part of the patient to relieve irritation by picking
the nose, or from the use of cutting or other instruments in the
hands of the surgeon. Septal ulcerations in this way are often
accompanied by moderate bleeding. In a case reported by R. G. Curtin
the nasal branch of the ophthalmic artery was thought to have been
ruptured. Among the general causes the most frequent is undoubtedly the
depressed state of the system preceding or accompanying typhoid and
other anæmic states. Thus, among the prodromes of typhoid fever
epistaxis holds a conspicuous position. It is also seen in chlorotic
females, especially in those suffering from that phase of anæmia known
as Grave's disease. It also occurs in vicarious menstruation and in
local facial or encranial congestions. In those disorders of nutrition
accompanied by a tendency to capillary extravasation, such as purpura
and scurvy, the nasal mucous surface participates in the general
disorder. In a case of the former disorder coming under the notice of
the writer the blood had forced its way out in large quantities by
every capillary avenue.
TREATMENT.—Epistaxis when a symptom of a dyscrasia is of course to be
treated as a local expression of a general condition. In typhoid fever,
scurvy, and purpura or anæmia the bleeding is a sign of the general
distress, and requires no special local method of treatment. Epistaxis
when of local character should be treated, first, by removing the
cause; second, by diminishing the flow of blood to the part; third, by
cold and astringent washes to the affected surface; and, fourth, by
compression.
First. Should the bleeding be kept up by fragments of bone impinging
upon or lacerating the mucous membrane, they should be restored as far
as possible to their natural position and retained there by appropriate
apparatus. If they are entirely denuded of their periosteum and mucous
membrane, they should be removed. Foreign bodies should be extracted,
and if septal ulceration be present it should be carefully treated, the
crusts removed, the ulcerated surfaces touched with nitrate of silver
in stick, and the nasal chamber plugged from in front to exclude the
outside air.—Second. The position of the body is of great importance
in treating epistaxis. The recumbent position is no doubt to be
preferred. The patient often holds one arm elevated or ties a cord
about the proximal end of a limb. These innocent accessories to
treatment may be permitted, since they are based upon well-known
physiological principles, although it must be said that the bleeding
can in all instances be checked without their aid. Cold applications to
the nape and sides of the neck are often of service. Various internal
remedies, such as ergot, gallic or sulphuric acid, and erigeron, may be
administered with good effect in addition to the local
measures.—Third. Astringent washes, such as a solution of alum—about
drachm j to the pint—will often check a moderate degree of capillary
bleeding without other aid. Tannic or gallic acid may also be used.
Should these measures fail, the Monsel solution may be used on pledgets
of cotton carried up to the bleeding spots. In Curtin's case, already
quoted, a pledget saturated with the solution of the perchloride of
iron placed over the nasal branch of the ophthalmic artery promptly
arrested the bleeding. In lieu of these styptics the platinum wire loop
of the galvano-cautery battery may be used. The writer has often
succeeded in checking bleeding after a removal of a polypus or the use
of the galvano-cautery when the exact position of the hemorrhage is
known by laying upon the affected spot a little square of patent lint.
It acts much as in checking the bleeding from a leech-bite.—Fourth.
Compression of the mucous lining of the nose and exclusion of these
surfaces from the air—a method familiarly known as plugging the
nose—is the dernier ressort in the treatment of epistaxis, and is to
be relied upon in the event of failure of other methods. This failure
is, however, relatively infrequent. Observers agree in describing the
procedure tedious and rather disagreeable, as much to the operator as
to the
patient, who has already been exhausted by loss of blood
and the previous measures resorted to for his relief.
|
FIG. 20.
|

|
|
Bellocq's Canula.
|
The instrument usually relied upon for this purpose is known as
Bellocq's canula (Fig. 20). This little instrument consists of a hollow
curved tube of metal fashioned somewhat like a Eustachian catheter, and
bearing within it a flexible and adjustable metallic band which carries
at its extremity an eyelet. Any one who has used the Eustachian
catheter will recall the number of instances in which it could not be
passed, or if passed the frequency in which great distress followed. If
this be true of the Eustachian catheter, it is also true of the Bellocq
canula, the difficulty in the case of the catheter, indeed, being the
lesser of the two, inasmuch as the physician has a number of sizes to
select from. Conceding, however, that the instrument (with a long stout
thread passed through the eyelet of the stylet) has been placed in
position in the nasal chamber, one end of the thread is seized within
the mouth and brought out between the lips, while the other, carried by
the instrument, is withdrawn through the nose and is allowed to hang
from the nostril. The two ends of the thread are now tied firmly
together, and a pledget of lint or cotton, fashioned somewhat after the
shape of the posterior naris, is tied to the thread. Traction is now
made upon the nasal portion of the thread until the plug is firmly
lodged against and within the posterior naris. The remaining portion of
the oral thread is now cut off close to the velum, and the free end of
the nasal thread secured by adhesive plaster to the integument. The
nostril should next be stopped from in front by pledgets of lint or
absorbent cotton. The size of the nasal chamber and naso-pharyngeal
varies so markedly that a rhinoscopic examination is of use in fixing
upon the size of the plug. If it be too small, it will be drawn
entirely within the nose, and possibly beyond the bleeding spot. If it
be too large, it will partially or entirely occlude the posterior naris
of the opposite side, and thus by interfering with nasal respiration
greatly increase the distress, or by pressure against the Eustachian
fossa and velum interfere with the hearing and with deglutition. The
plug should be retained in position until a purulent mucus appears
within the nose: this is usually about the third day. The plug now
usually becomes a little loose, and can readily be withdrawn by pushing
it back into the pharynx, where it is seized with forceps. Too long
retention of the plug in position is followed by great fetor and the
free formation of muco-pus—conditions which tend to debilitate the
patient.
D. Hayes Agnew informs me that he for a long time practised stopping
nasal hemorrhage by plugging the chamber from in front. Strips of
patent lint four inches long by half an inch wide are employed for this
purpose. They are gradually pushed into the chamber until the entire
space is filled as far as is practicable. An essentially similar method
is described by F. H. Bosworth in his Manual of Diseases of the Throat
and Nose.
These may be said to include the myxoma, sarcoma, fibroma, carcinoma,
also the true hypertrophies and submucous inflammatory thickening.
The myxoma, more commonly known by the name of soft or gelatinous
polyp, is the most prominent of the morbid nasal growths. It occurs
ordinarily in small pedunculated seed-like masses, ranging in size from
that of a grain of wheat to a grape. The most common seat is on the
anterior portion of the middle turbinated bone and on the median
surface of the inferior turbinated bone at the palatal portion. Instead
of being pedunculated, they may be sessile; that is, each tumor may
have a base equal to, if not exceeding, any diameter of the tumor.
The symptoms of nasal polypus are of three kinds: (1) those arising
from obstruction of the nasal respiration; (2) those arising from the
irritation excited by their presence; (3) the symptoms, reflex in
character, manifested at points beyond the limit of the nasal chambers.
(1) The polypi necessarily tend to obstruct the respiratory tract of
the nasal chamber. The first symptoms are of this character, and as a
rule furnish the first intimation to the patient that trouble exists.
Difficulty of nasal respiration is acknowledged, accompanied with a
sense of tension and fulness, which is found to be worse during damp
weather than when the air is dry and bracing. If the growths are freely
pendulous, the act of blowing the nose may change the position of the
mass and secure temporary freedom from distress. Incidental to
obstruction, an intonation of the voice is often present. Loss of
smelling and of taste is a frequent result of the mass interfering with
the movement of the odoriferous particles. The loss of the sense of
taste is dependent upon the loss of the sense of smelling.
(2) Polypi when large enough to press against the membranes of the nose
excite an increased flow of mucus. As a rule, this flows forward, and
is removed by the handkerchief. The quantity of fluid thus escaping is
often very great. Patients often report the necessity of carrying about
with them for a single day's use from eight to ten handkerchiefs. In
the turgesence excited by an attack of coryza the mucus becomes thicker
and of a yellowish color. Occasionally a sensation of dropping of mucus
from the nose into the throat is a source of complaint.
(3) The reflex symptoms belonging to the presence of nasal polypi are,
as a rule, referred to the forehead. This is especially the case if the
growths involve the middle turbinated bone. When the tumors are so
located, and have not impinged upon the respiratory tract, the symptoms
of obstruction may be absent, and those of mucus excitement so moderate
as not to excite attention, while the tension in the forehead,
especially over the frontal bos, is pronounced. This sensation is
intensified by prolonged inclination of the head forward, being
especially aggravated in the acts of writing at a desk, working at a
sewing-machine, kneeling at prayer, etc. Occasionally tinnitus aurium
and suffusion of the conjunctivæ are present.
Neglected polypus ends in deformity of the nasal chambers and bones of
the face. The face assumes a peculiar expression called by the older
observers frog face. This is rarely if ever seen in this country, owing
doubtless to the fact that the sufferers from nasal polypus seek
medical advice in the early stages of the affection. Moderate degrees,
however, of deformation of the turbinated bones are often seen.
Since the symptoms of soft nasal polypus are produced entirely by
mechanical means, they can be closely imitated if not replaced by other
morbid states of the mucous membrane. A hyperplastic state of the
membrane over the middle turbinated bone will give rise to all the
symptoms of a sessile polypus in the same situation. It is well to
remember that this condition of the membrane often coexists with
polypus, and of course will persist after the polypus has been removed.
It follows that a guarded prognosis should always be made in case of
sessile polypus. A tedious course of treatment of the indurated and
chronically inflamed membranes may be required after the
tumors
have been removed before a cure is effected. The prognosis of soft
polypus is more favorable as to the immediate results of treatment than
in sessile polypus. The liability to recurrence can be materially
lessened by carefully conducted after-treatment.
The diagnosis of soft pedunculated polypus is readily accomplished if
the examination is made by aid of an appropriate speculum, the rhinal
mirror, and a powerful light. Even without these aids the tumors can be
seen by direct sunlight within the nostril if they are entirely
occluding the chambers, and even in the event of nothing being visible
by such inspection the movement of the masses by the act of blowing the
nose will be noticed. The fact that the nasal obstruction is aggravated
by damp weather seems to assist the physician in framing a diagnosis.
The diagnosis of sessile polypus requires a careful use of all the aids
of rhinoscopy. They can be distinguished from hyperplasia of the mucous
membrane by their lobulated form, and from the fact that the probe can
move them slightly from their base. They can be distinguished from
adenoid growths at the root of the pharynx by the fact that they remain
unmoved during the act of swallowing.
The disease is not apt to recur if the treatment is thoroughly carried out.
The treatment of soft polypus consists in their removal. All observers
are now agreed on this point. Injection by astringents and acetic
acid—a process that at one time held out much promise—has been
generally abandoned. In removal of the polypus one of two methods may
be resorted to: that by avulsion, and that by the use of the snare.
Avulsion is effected by forceps adapted for this special use. With such
an instrument the polyps can readily be seized and removed. The rule
that nothing should be seized which is not seen is subject to no
exception. In no other way can the operator be secure against
accidents. Incautious operators have frequently torn away strips of
mucous membrane or portions of the turbinated bones in their crude
attempts to remove these growths. Severe hemorrhage and death through
violent lacerations of the ethmoid bone near the cribriform plate, and
subsequent extension of the inflammation thereby excited to the
membranes of the brain, have been known to follow these crude surgical procedures.
|
FIG. 21.
|
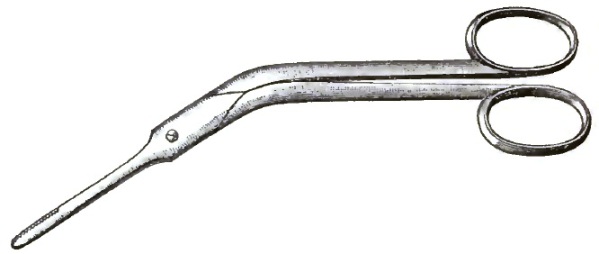
|
|
The Author's Nasal Forceps.
|
W. C. Jarvis of New York has modified the wire snare for application to
the nose for the removal of polypi and hypertrophied tissues, and
reports that it is a safer, more expeditious, and less painful method
of operation than the forceps, which he unqualifiedly condemns. His
instrument, while undoubtedly an ingenious adaptation of the principle
of the snare, and a valuable addition to our means of treating nasal
affections, cannot, in my judgment, take the place of the forceps in
removing nasal polypi. As the aurist finds both the forceps and the
snare useful in removing growths from the external meatus of the ear,
so I am sure the physician will need both in the treatment of nasal
polypi. In many cases the malformations of the nasal septum are such
that
I have been unable to use the snare where the forceps could
be used with relative ease. I find when the loop is quickly drawn the
same amount of bleeding follows as when the forceps are used. When it
is slowly drawn, the sitting is tedious, and both the patient and
attendant find the process wearying. The amount of blood lost when the
forceps are properly used is not considerable, and is always under
control. F. H. Bosworth1 describes the operation as extremely
painful. So far from this being the case in my experience, I find the
patients complain greatly of the constriction of the wire loop on the
pedicle of the polypus, and invariably prefer the forceps. I must add
that this preference was in no way influenced by myself, for I was
disposed at one time to agree with the writers who have of late
criticised the method of removal of the polyps by avulsion.
1 A Manual of Diseases of the Throat and Nose, 1881, p.
241.
No matter which of the methods be accepted, the treatment of polypus
resolves itself into two simple propositions. When one or two large
polypi are present in a capacious nasal chamber, the removal of the
growths either by avulsion or snaring is a simple matter, and can often
be accomplished in a single sitting. When numbers of small polypi are
scattered over a large surface, particularly if they grow from the
sides of the middle turbinated bone, the treatment is tedious, and even
after the growths are removed a series of applications are required to
cure the thickened and infiltrated mucous membrane.
Sarcoma, fibroma, and carcinoma are infrequent causes of nasal disease.
When located in the nasal chambers they do not present any characters
with which I am familiar which distinguish them from the expressions
they assume in other parts of the body. When involving the respiratory
tract they alike create symptoms by obstruction, by excitement of the
secretions, and by the reflexes due to the involvement of the branches
of the fifth pair of nerves. When situated in the olfactory track the
obstruction to nasal respiration is absent, but the reflex symptoms are
pronounced: the patient is liable to depression of spirits and to
frontal headache. Encroachment upon the orbital, pharyngeal, and
encranial spaces is common in the last stages.
Perhaps the most common way in which these morbid growths induce
symptoms referable to the nose is by obstruction of the respiratory
tract by the incursions of a mass originating at a point beyond the
limits of the nasal chambers. In this way a growth in the pharynx may
close one or both choanæ, or protrude into the nose from the
spheni-palatine space by breaking down the ascending plate of the
palatal bone as it forms the median wall of this space; or the growth
may project inward from the superior maxilla.
In one case under my care, of obscure growth high up within the nose,
which ended fatally by involvement of the membranes of the brain, a
tenacious mucus of a dark chocolate color was withdrawn from the nose
into the throat. The peculiar color of the mucus was found to be caused
by a mixture of blood. In my judgment, this peculiar mixture of blood
and pus was significant. The blood and mucus had not been mixed in the
nasal chamber to cause the chocolate or rusty hue, for then we would
have had the appearance customary in epistaxis of bright blood and
frothy mucus mechanically held together. The even dissemination of the
blood through the mucus would point to the conclusion that the blood
had escaped in small quantity at the time of the formation of the
mucus. Why such mucus does not constantly form in inflammatory states
of the mucous membrane of the nose, as it does from the pulmonary
mucous membrane in pneumonia, I am not prepared to say. But existing as
it did in a case where a deep-seated disease was present may be
accepted as a fact in some way connected with the invasion of a morbid
growth in and upon the nasal mucous surface.
The pharynx is always in a state of hyperæmia when morbid growths of
the above groups are present in the nose. The front of the velum
is apt to be covered with a great number of minute papillæ, which,
however, are often seen in anæmic individuals, and are not therefore
pathognomonic.
The treatment of the growths enumerated and the general conduct of the
cases are subjects for the general surgeon, and a consideration of them
here would be out of place.
It may, however, be well to describe a few instruments which have been
found useful in the large group of cases where cauterization is the
principal treatment indicated. Foremost among these is the instrument
shown in Fig. 22, which combines advantageously the essential features
of the galvano-cautery and the wire snare.
|
FIG. 22.
|
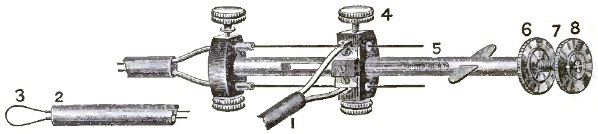
|
|
The Galvano-cautery Snare described in the
text: 1, the cable of the battery; 2, the canula (which is not shown in
full length); 3, the platinum wire; 4, the vulcanite carriage, with
screws holding the ends of the platinum wire in metallic contact with
the hinge-connections, by which the current is transmitted from the
battery; 5, a slotted barrel of aluminium; 6, a movable nut on the
screw; 7, a small portion of the screw disengaged from the slotted
barrel; 8, milled stationary screw-head.
|
|
FIG. 23.
|
|
|
The Double Battery employed by the Author: The
two sets of plates are seen united by a flat band of metal. The case
which encloses the two separate batteries opens in front, displaying
the cells, the plates (which are seen pendent over the cells), and the
treadle. Above the figure of the battery lies a figure of the Flemming
electrode handle and the electrode in position.
|
It is well known that a loop of wire which is steadily narrowed has
great power in severing the attachment of tumors and other outgrowths.
When of a large size, it may be sufficiently powerful to pass through
bony structures, as well as the softer parts of the body. The principle
of the snare has been employed both in the throat, the ear, and the
nose; but when my attention was first directed to this subject the
forms available were too large and heavy for the delicacy of
manipulation demanded in removing small tumors lodged in the narrower
recesses of the nose. Moreover, no snare that I could then find would
permit the galvanic current to pass through the loop at the time it was
being narrowed. I was led, therefore, to inquire into the
practicability of an instrument which would at once be light, be of
small size, and yet be sufficiently powerful to remove that class of
hypertrophied tissues and polypoid growths which are of such frequent
occurrence in the nasal chambers. The instrument shown in Fig. 22
combines these qualifications, and satisfactorily performs the service
for which it was designed. The only feature of an essential character
which may be said to be novel is the fact that the platinum wire (3,
Fig. 22) forming the snare is covered with a uniform coat of copper,
excepting alone the portion forming the loop, which is bare. As a
consequence of this arrangement the current of electricity from the
battery is conducted through a double canula (2, Fig. 22) by means of
the copper. The length of the instrument being about 9½ inches, and its
weight less than ½ ounce, delicacy of manipulation is not interfered
with. Besides possessing all the features of the cold wire snare, it
has the additional advantage of securing a more rapid and painless
operation, without any hemorrhage. Sessile (pyramidal) or resilient
growths may be removed by first burning a groove of any depth into
them, after which the loop is drawn while the current is passing
through it. For this task the cold wire snare is obviously incompetent.
Growths of unusual size or hardness may be destroyed by the same
procedure, and nodules no larger than a grain of wheat may also be
excised with great nicety. It will be seen that failure to remove
at least a portion of the growth attacked is an event exceedingly
unlikely to occur. I have been particularly struck with the facility
with which hypertrophies of the inferior turbinated bone can in this
way be treated; and if cocaine be freely applied before the operation,
it constitutes, in my judgment, the most speedy and the least painful
of any means by which such conditions can be reduced. By using a canula
with a curved end it is easy to snare growths situated on the posterior
portion of the inferior turbinated bone. The current passing through
the battery (Fig. 23, B) to the instrument can be interrupted by any of
the numerous devices with which the practical electrician is familiar;
or the treadle of the battery can be depressed and locked by the
lever-catch, and the interruption of the current be determined by the
pressure of the finger on the knob in the handle (Fig. 23, A).
This is under all circumstances desirable, since the weight of the
cells is sufficient to demand considerable force to be exerted by the
foot—always enough to destroy the delicacy of the manipulation of the instrument.
|
FIG. 24.
|

|
|
Two Electrodes of peculiar shape in use by the Author.
|
An electrode which is wrapped nearly to its distal end (Fig. 24), and
used either in a straight or a curved form, is of great advantage in
reaching growths within the naso-pharynx. The straight form can be
thrust directly back through the nasal chamber, and the curved form can
be passed from the oro-pharynx to the naso-pharynx without danger of
burning the posterior border of the soft palate.
BY HOSMER A. JOHNSON, M.D., LL.D.
DEFINITION.—Disorders of sensation or motion, or of both sensation and
motion, due to disease, first, of the centres from which the nerves of
the organ are derived; second, to disease along the track of the
nerves; third, to disease in the terminal distribution of the nerves;
fourth, to reflected irritation from neighboring or distant parts; and
fifth, to myopathic change. This last condition is not necessarily a
neurosis; it is nevertheless a cause of modification of the function of
the parts to which the nerves are distributed, often a result of
paresis or paralysis, and therefore inseparably associated with the
neuroses of the organ. Disorders of innervation, depending upon
structural disease of the larynx, such as ulceration or tumor, are not
included in this definition.
ANATOMICO-PHYSIOLOGICAL CONSIDERATIONS.—The framework of the larynx
consists of cartilages securely but rather loosely articulated with
each other. The movements of these cartilages produce changes in the
position and tension of the soft parts. The thyro-cricoid articulation
allows ginglymoid and sliding motion; the aryteno-cricoid, rotatory and
sliding motion; the hyo-thyroid, ginglymoid motion. The physiology of
the muscles of the larynx is quite complex, since nearly all have
fibres taking a number of different directions, and the changes in the
form and positions of the parts depend upon the combined action of
different muscles and parts of muscles which may be individually
brought into action to produce the required results. The muscles may,
however, be roughly divided into groups: 1. Constrictors of the
superior strait; 2. Dilators of the superior strait; 3. Adductors of
the vocal cords; 4. Tensors of the vocal cords, external, internal; 5.
Relaxers of the vocal cords; 6. Abductors of the vocal cords.
The superior strait of the larynx is closed by the action of the
oblique portions of the arytenoideus, acting in conjunction with the
ary-epiglottici, into which some of its fibres are continued, thus
drawing the cartilages of Santorini downward and inward and
approximating the ary-epiglottic folds and depressing the epiglottis;
while the thyro-epiglottici complete the closure by further depressing
the epiglottis. Fibres of the latter muscle, acting alone, may dilate
the superior strait by drawing apart the ary-epiglottic folds.
The transverse portion of the arytenoideus and the superior fibres of
the crico-arytenoidei postici approximate the arytenoid cartilages. The
crico-arytenoidei laterales, and also in a slight degree the external
fibres of the thyro-arytenoidei, rotate these cartilages, turning their
vocal processes inward: the action of the latter two muscles as
adductors is imperfect unless the arytenoids are drawn backward and
fixed by the arytenoidei postici.
The tensor group comprises a number both of the extrinsic and intrinsic
muscles of the larynx. The crico-arytenoidei postici draw the
arytenoids back, external rotation, and consequent abduction, being
prevented by other muscles. The anterior fibres of the crico-thyroid
and those fibres of the sterno-thyroid inserted anterior to the
crico-thyroid articulation approximate the cricoid and thyroid
cartilages, and thus tighten the vocal bands. The posterior fibres of
the crico-thyroid slide the thyroid upon the cricoid, lengthening the
antero-posterior diameter of the larynx. This muscle, acting as a
whole, also compresses the alæ of the thyroid with the same effect. The
constrictors of the pharynx have a similar function. The hyo-thyroidei,
acting in conjunction with the elevators of the hyoid bone, draw the
thyroid forward and tilt it downward upon the cricoid. The form and
internal tension of the vocal bands are greatly influenced by the
thyro-arytenoidei, especially their inner fibres, while the ascending
fibres of the muscle draw the inferior portions of the vocal bands
upward and prevent the sagging of their edges. This muscle, acting
alone, has been thought to cause extreme relaxation of the vocal bands.
Modern research renders this statement of relaxation doubtful. The
contraction of those fibres of the sterno-thyroidei inserted
posteriorly to the crico-thyroid articulation tilts the thyroid upward,
and thus relaxes the tension of the bands.
The crico-arytenoidei postici rotate the arytenoid cartilages outward,
separating the vocal processes, and, acting in conjunction with the
posterior fibres of the crico-arytenoidei laterales, draw the
cartilages outward and downward.
In the cadaveric condition, which is one of relaxation of all the
laryngeal muscles, the glottis is neither closed nor widely open; the
epiglottis is erect against the dorsum of the tongue; the arytenoid
cartilages are slightly separated, so that the glottic opening is a
triangle with the base posteriorly, as in the act of inspiration, but
the separation is much less than in the act of breathing. This
condition is met with in paralysis affecting all the muscles of the organ.
The nerves of the larynx are derived from the pneumogastrics. The
superior laryngeal is mainly a nerve of sensation for the parts above
the edges of the vocal bands. There are some notable exceptions to this
statement: a branch, external, descends to the crico-thyroid muscles
and is motor in its function. Filaments from the superior laryngeal
endowed with motor functions are also distributed to the folds
extending from the arytenoids to the epiglottis; these are the
ary-epiglottidean bands, and are concerned in the movements of the
epiglottis. It is probable that the arytenoids are also in part
supplied by the superior laryngeal; in other words, that both the
superior and inferior laryngeal nerves are mixed, branches from the
spinal accessory, as well as from the pneumogastric proper, entering to
each of these nerves. Beclard1 states that the one, the spinal
accessory, is a nerve of phonation; the other, the pneumogastric, is a
nerve of respiration. The sensations of the mucous surfaces below the
glottis depend upon filaments from the pneumogastrics returned along
with the motor fibres from the spinal accessory. The two orders of
fibres go to make up the recurrents. The relations of the recurrents
themselves to the large vessels, as well as to the bronchial glands,
are of importance. At the point of their origin they are in close
relation with the aorta and right subclavian; they are also in close
relation with the top of the lungs. Disease of these organs and
structures, especially of the large blood-vessels, such as aneurism of
the aorta or subclavian, disease of the glands, tumors, abscess,
traumatism, etc., may modify or completely destroy the functions of the
laryngeal nerves. In short, anything or any condition by which pressure
may be made upon the pneumogastrics or recurrents may become a cause of
nervous disturbance in the larynx. In addition to this general source
of innervation, Elsberg2 describes a special centre of sensation for
the throat in the medulla oblongata. He also describes three kinds of
sensibility in the larynx—tactile, dolorous, and reflex. Rossbach3
details experiments from which he concludes that there are nerve-cells
in
the mucous membrane of the larynx which preside over the
function of secretion. The larynx is endowed with at least two kinds of
sensibility: the one tactile—when exalted it becomes painful; the
other, reflex sensibility, is double. First, there is as a result of
excitement a contraction of the subjacent muscle, and there follows
closure of the glottis. This is seen in the application of irritants to
the parts, such as solutions of nitrate of silver or other escharotics.
There is no cough, but great difficulty of inspiration. Expiration is
free and easy. There may follow some degree of pain for several hours.
It will be seen that the phenomena are the same as those observed in
the irritation of other mucous surfaces. The irritation is immediately
translated into motion; this motion is probably reflex, but not
necessarily through the centres, such as the brain or cord. The motion
is of the subjacent muscles. Second, the mechanical irritation produced
by the presence of a drop of water or a morsel of food in the larynx
results in violent and explosive cough. The cough persists until the
offending drop or body has been removed. This kind of sensibility calls
into action distant muscles. There is no spasm of the adductors of the
glottis, as in the case of the application of caustics. It is probable
that the filaments of the nerves, the irritation of which gives rise to
spasm, are distributed more generally than those which preside over
reflex action at a distance and produce cough. The one set of functions
are designed probably to protect the organ from the intrusion of
foreign bodies; the other for their expulsion, as well as for the
removal of the secretions of the parts or of matter brought up from
below. The hypothesis of a third form of sensibility, as described by
Elsberg—namely, the dolorous—seems hardly to be demanded for the
larynx more than for all other mucous surfaces subject to pain. The
nerve-cells of Rossbach in the mucous membrane may be peculiar to the
larynx and trachea, as he claims, but further observations are required
for the demonstration of this as a special histological fact
distinguishing laryngeal from other mucous surfaces.
1 Dic. Eng. des Sci. med.
2 Int. Med. Cong., 1881.
3 Ibid.
PERVERSION OF SENSATION OF THE LARYNX.
There is some difficulty in grouping the derangements of the
sensibility of the larynx, for the reason that in many cases the
perversion of this function is only a symptom of some other disease of
the organ. Probably in all cases the trouble is, in fact, an expression
either of disturbance in the structures of the larynx, involving more
than the sensory nerves, or it is the result of change in structure or
function of neighboring or distant parts. Various attempts have been
made to classify these disorders according to the kind of perversion
and also according to the cause of the trouble. Elsberg, in a paper
presented to the International Congress, London, 1881, p. 224. vol.
iii., makes an attempt at a scientific classification based upon
anatomico-physiological facts. That there is yet much to learn in
regard to these facts, especially the physiological facts, will be
admitted by every one at all familiar with the literature of the
subject. Elsberg, under the term of dysæsthesia, makes two principal
divisions—namely, first, disorders having reference to the quantity or
intensity of the sensation; this embraces simple hyperæsthesia and
simple anæsthesia. The second grand division relates to the quality of
the sensation, and includes only paræsthesia or sensory delusions.
These grand divisions are still further subdivided.
In fact, we have to do with exaltation of sensibility simply, with
sometimes pain; second, with delusion of sensation; and, third, with
lost or diminished sensation. For all practical purposes,
therefore, we may adopt this arrangement, but should consider it as
only provisional, as has been well observed by Schnitzler. These
conditions are described under the terms hyperæsthesia, with or without
pain; paræsthesia; anæsthesia.
DEFINITION.—Exalted sensibility of the larynx, not necessarily
associated with pain or other disorders of function. This condition is
rare, but it is nevertheless met with. We sometimes find that the
larynx is abnormally sensitive to touch or to an irritant, even though
there is no marked inflammation. The symptoms and history justify the
consideration of the condition apart.
ETIOLOGY.—Predisposing causes are probably to be found in the general
condition of the nervous system. Persons of a highly susceptible
nervous organization are, other things being equal, more prone to this
affection. Certain habits of life, such as confinement to the house or
want of exercise in the open air, excessive use of the voice in
singing, especially in unnatural keys or after unnatural methods, have
seemed to me to predispose to the exaltation of the sensibility of the
organ. It must be confessed, however, that so little is accurately
known of the history of the disease that we are left in much doubt as
to the rôle of these conditions in the production of the abnormal
state. The exciting causes of hyperæsthesia of the larynx are the
long-continued action of the predisposing causes—acute and chronic
inflammation, mechanical and chemical irritants, etc. So far as my own
experience goes, the use of the voice in an unnatural key, or perhaps
rather the strain upon the parts by efforts to force the organ to
perform the function of phonation in an abnormal manner, has more
frequently been assigned by the patient as the cause than any other one
thing. I have seen quite a number of singers who have by an effort of
the muscles, apparently, produced an intensified irritability of the
mucous surfaces. It is possible that in rare instances there may be an
exalted activity of the receptive centres, and that the local trouble
in the larynx is only a manifestation, in the distribution of the
nerves, of the central disease. In such cases, however, the disorder
should reach all the parts supplied by the pneumogastrics. Inflammation
of the pharynx, soft palate, posterior nares, and perhaps of the
structures of the ear, have an influence over the sensibility of the
parts below, probably through the relations of the glosso-pharyngeal
and other nerves to the laryngeal branches of the pneumogastrics. E. F.
Ingals of Chicago has seen a case of laryngeal hyperæsthesia produced
apparently by a varicose condition of the vessels about the base of the
tongue. Frankel, Tornwaldt, Bayer, Schnitzler, A. H. Smith, Glasgow,
and others have reported cases in which there were symptoms of
hyperæsthesia or of reflex motor disturbances due to trouble in the
nose or pharynx. The general health has much to do with the development
of the local trouble. Asthenia is associated so frequently with
hyperæsthesia of other parts that we should expect to find this
relation also in the larynx.
SYMPTOMS.—The symptoms of hyperæsthesia of the larynx are in part
involved in the definition of the affection—exalted susceptibility to
the touch, intolerance to the presence of mechanical irritants, a
sensation of discomfort in the presence of chemical agents, such as
gases or impure air, and, when the exaltation is excessive, positive
pain. This pain may be only a soreness or tenderness or it may amount
to neuralgia. This last form of exaltation is rare. When present it has
been considered a special disease and treated as a separate affection.
Von Ziemssen and Mackenzie regard it as a variety of hyperæsthesia.
Schnitzler, Jones, Wagner, and Mackenzie report cases. The
pain is
said to be not confined to the larynx, but to extend up toward the ear
and along the course of the superior laryngeal nerve. In two cases
observed by the writer the pain not only extended along the course of
this nerve, but into the pharynx and posterior nares as well. In these
cases the patients were both singers, and both had adopted with great
enthusiasm a new method by which the abdominal muscles were brought
into action at the expense of the muscles of the thorax. The pain was
always aggravated by any effort to sing, but more especially by any
return to the method noted. The pain not unfrequently extended to the
face as well as to the ear.
Neuralgia of hysterical origin, according to Thaon,4 is more
frequently met with on the left side than on the right. Instead of
being general, it is not unfrequently limited to points or
circumscribed patches.
4 Proceedings Laryng. Cong., Milan.
COURSE AND TERMINATION.—The course of the affection is very uncertain.
In the neuralgic variety the pain may be transient, passing away in a
few days or hours even, but generally there are frequent recurrences
extending through weeks or months. Simple exaltation of the common
sensibility is much more persistent and more uniform in its character.
Hyperæsthesia of the larynx is so largely dependent upon the general
health that not only is it very irregular in its course and duration,
but its termination is equally uncertain. It can hardly be said to be a
cause of death, as it does not involve structures necessary to life. It
disappears occasionally without treatment. When complicated with other
affections, such as acute or chronic inflammation, alterations of the
function of the pneumogastrics, with disease of the thoracic viscera or
with general derangements of the nervous system, its course and
termination must depend largely upon the persistence of these
complications.
PATHOLOGY.—So far as the pathology and morbid anatomy have been
studied, there is no appreciable change of structure. This is true, of
course, only of those cases which are not complicated. Whether the
primary lesion is in the mucous membrane, denuding, pinching, or
otherwise modifying the terminal portions of the nervous filaments, or
whether there is an alteration of the conducting portion of the sensory
nerves, or, in fine, whether there is some lesion of the receptive
centres, it is impossible in most instances to say. It is probable,
however, that in some cases the first morbid fact has been an
alteration in the nerves themselves. The cases induced by unnatural
methods of using the vocal organs are apparently of this character.
The diagnosis, prognosis, and treatment will be considered in
connection with Paræsthesia.
Closely connected with hyperæsthesia of the larynx is a form of sensory
delusion consisting of the impression that some foreign substance is
lodged in the organ or that there is some alteration an the structure
of the parts. This is known as paræsthesia.
ETIOLOGY.—The first variety of sensory delusion depends on a primary
injury to the parts. A bone or pin or some other foreign body, perhaps
having lodged in the parts for a short time, has left a persistent
impression upon the mucous surfaces. It is possible that in some
instances there may have been no foreign body in the parts, as we have
in many cases only the statement of the patient. Local inflammations,
small in extent, may possibly have left the parts in a morbidly
sensitive condition justifying on the part of the subject the
hypothesis of a foreign body.
The second variety of paræsthesia is the expression of some disturbance
in
a distant part. It is usually hysterical in its character or a
variety of hysteria associated with neurasthenia. It belongs to the
same class of phenomena as the sensory delusions in other parts of the
body. The globus hystericus is one of its forms. Thaon5 says that
hysteria may give rise to neuralgia as well as to other forms of
hyperæsthesia of the larynx. It also, according to this author,
produces that form of paræsthesia in which there is a sense of a bone
or pin or some foreign substance in the larynx. The general condition
of asthenia, and especially of neurasthenia, may be assigned as a
predisposing cause. The local injury in the one case and the general
hyperæsthetic condition in the other, with some determining fact, such
as the mental impression or an apprehension of trouble in the larynx,
constitute the exciting causes.
5 Proceedings of the International Congress of
Laryngology.
SYMPTOMS.—It usually comes on after an injury or as a result of the
presence of a mechanical obstruction or irritation, the presence of a
bone or pin being frequently invoked as an explanation of the feeling.
In a few cases the sensation is suggestive of an alteration of the
structure of the parts. Patients are inclined to think that they have a
tumor or that there is some deformity. In the first class of cases
there is a sense of pricking or of scratching in the larynx. This is
not constant in locality or in intensity. There will be times,
occasionally days, in which the sensation may be entirely absent, after
which it returns with great severity, the patient insisting that the
cause of the trouble has simply changed its location—in other words,
that there is a migratory body in the throat. That form of paræsthesia
in which the sensation is that of a tumor or malformation is also
irregular in the mode of its manifestation or kind of disturbance. Like
the other forms, it comes and goes, changes its location, and undergoes
modification in its character. It may be associated with neuralgia.
DIAGNOSIS.—Hyperæsthesia and paræsthesia are recognized by the
symptoms already described and by the aid of the laryngoscope. The
mirror reveals the fact that the parts are normal in structure and that
there is no foreign body present. The mucous membrane may be hyperæmic
or anæmic, but is not the seat of any active inflammation. The
excessive sensibility and pain of the larynx in ulceration of the parts
will be excluded from this group of troubles by the revelation of the
laryngeal mirror. Cases of pain or perverted sensation dependent upon
the disorders of the nerve-centres usually involve the whole range of
functions supplied by the pneumogastrics, and will generally be
recognized by this fact. Such cases can hardly be called local, and do
not belong to the group of affections embraced in this article.
PROGNOSIS.—The prognosis of simple paræsthesia of the larynx is not
grave. Though it may exist for a long time, it, so far as we know, does
not terminate in death. While it sometimes results in recovery without
treatment, it in a large proportion of cases yields only to both local
and general treatment. Its duration is uncertain. Paræsthesia coming on
after the presence of a foreign body in the organ may last many months
and then gradually disappear. This result will be largely aided by the
moral support which is gained if we can convince the patient that the
sensation is entirely a delusion.
TREATMENT.—For the purpose of meeting local indications in
hyperæsthesia we may apply with a brush or by the means of the atomizer
a solution of morphine and alum of the strength of 15 centigrammes of
morphine and 2 grammes of alum to 50 grammes of water, or to this may
be added 20 centigrammes of carbolic acid and 10 grammes of glycerin.
Of this solution an application may be made each day with the
hand-atomizer. The hand-atomizer is preferable to the steam-atomizer,
for the reason that we know in the use of the former the strength of
the solution. In the use of the steam-atomizer the medicated solution
is diluted with the water of the steam, and we are
ignorant as to
the strength of the application. The method of application by the use
of the atomizer is to be preferred to the brush or sponge probang, for
the reason that we produce by it no mechanical irritation of the parts.
The brush or sponge can hardly be used without giving pain or
discomfort. In addition to the solution above indicated, solutions of
borax, of sulphate of zinc, of tannin and glycerin with chloroform, of
nitrate of silver not too concentrated—2 to 10 centigrammes to 30
grammes of distilled water—tincture of aconite, solutions of the
bromides, cocaine and other anæsthetics, may be used with benefit. In
many cases the administration of general tonics along with the local
treatment will be of the greatest value. The application of electricity
to the parts through the surfaces—that is, from one side of the larynx
to the other—will add to the efficacy of other local treatment. The
strength of the current should not be so great as to give rise to any
discomfort. The current should be continuous, and should be repeated
every day for several weeks if the disorder does not yield sooner. In
cases which have been induced by vicious habits of living or of
exercise of the organ there should of course be an entire change of the
habits. The producing cause should, if possible, be removed. The
exposure of the parts to anything which gives rise to pain is to be
avoided. If hyperæsthesia has been induced by unnatural methods of
singing or of speaking, these should be remedied.
In neuralgia the general treatment for that affection is indicated.
Quinine and iron have especially been found useful. In the hysterical
variety of both hyperæsthesia and paræsthesia general treatment is of
more value than local measures. General tonics, moral support, such as
will be secured if we can convince the patient that there is really no
serious trouble with the organ, but that it is only a morbid sensation,
will be of the greatest value. In these cases change of climate, change
of occupation, diversion by new associations, with expectation of
recovery on the part of the patient, often bring about the most
satisfactory results. The diagnosis should be certain and the physician
should be able to speak with confidence in the matter. This will go far
toward effecting a cure. For the purpose of diminishing the general
irritability of the system bromine in some of its combinations,
potassium, sodium, iron, quinine, etc., may be useful.
DEFINITION.—Diminished sensibility of the mucous surfaces dependent
upon lesion of the nerve-centres, alteration of the conductivity of the
nerve-trunks, or upon disease in their terminal distributions. It is
usually bilateral, but may be limited to one side. This alteration of
the sensitive condition of the mucous membranes is usually observed
after diphtheria. It is also met with in bulbar paralysis. In this last
condition it is only one of the phenomena of paresis or paralysis
involving several different organs. It is not, therefore, properly a
disease of the larynx, and the consideration of it will not be embraced
in this article. It has been stated that hysteria is frequently
accompanied with anæsthesia of the larynx. Von Ziemssen, Chairou, and
Schnitzler have published cases. It seems very improbable that this
condition of the organ is so generally present in hysteria as is
claimed by Chairou. It is, however, certain that anæsthesia as well as
hyperæsthesia of the larynx exists as a complication of hysteria. In
the later stages of all exhaustive diseases, as cholera, etc., the
sensibility of this organ is either diminished or abolished. This is
not, however, a true paralysis in the sense in which we generally use
the term. It is only one of the manifestations of the general failure
of the life-forces. The special senses, the reflex functions, all share
in this paresis, this severing of the relationships of life. Anæsthesia
of the larynx is usually confined to the parts supplied by the
superior laryngeal nerves, and is sharply limited by the edges of the
vocal bands. If there is anæsthesia of the parts below these bands, it
is of much less significance and hardly requires our consideration.
ETIOLOGY.—So far as we know, there are no predisposing causes. The
chief exciting cause of this affection is unquestionably diphtheria. It
is, in fact, a sequel of diphtheria. It will hardly be necessary to
repeat here what the reader will find fully discussed in the sections
devoted to diphtheritic inflammation of the fauces and adjacent parts:
we are mainly concerned with the phenomena. Just how this morbid
process produces paralysis is not known. It is believed by some
observers that the disease is produced by the alteration of the
nutrition of the parts during the progress of the diphtheria. It is
stated that the parts most nearly related to the seat of the exudation
are most likely to become involved. This is thought to sustain the
theory of the direct propagation of the morbid changes from the mucous
surfaces to the nerves and muscles. That the paralysis following
diphtheria is not, however, produced alone in this manner seems to be
made evident by the fact that distant parts, parts which have not been
at all involved in the disease, do nevertheless become affected with
paralysis. This paralysis develops when the general health and the
nutritive changes are all improving. It is quite evident, therefore,
that the loss of power in the laryngeal muscles, as well as the altered
sensibility, in part at least, must be due to some lesion of the
nerve-centres. In addition to the causes above noted, anything which
impairs or destroys the function of the superior laryngeal nerve may
produce this affection. In the anæsthesia from hysteria we know only
the fact, but do not know just how the derangements of the nerves in a
distant part, or in the nerve-centres perhaps, are so reflected as to
change the function of this organ. The hyperæsthesias, the
paræsthesias, and the anæsthesias of hysterical character are all
probably produced in the same manner. Anæsthesia in bulbar paralysis is
easily understood, but need not, for the reasons already given, engage
our attention.
SYMPTOMS.—This condition is usually associated with paresis or
paralysis of the muscles of the part. One of the first symptoms of loss
of sensibility is, therefore, a failure of the constrictors of the
larynx to protect the organ from the intrusion of foreign substances in
the form of food and drink. Particles swallowed find entrance into the
respiratory tube, and this with no sense of discomfort. If the
paralysis is complete both above and below the glottis, the intrusion
of these substances is not recognized. There may be no cough or spasm
to indicate the fact. In the mean time, the particles of food descend
into the bronchi, and may become the exciting causes of
broncho-pneumonia. It is often noticed after tracheotomy for diphtheria
that food and drinks gaining access to the respiratory tract are
discovered at the tracheal opening. In several cases within the
knowledge of the writer this fact has led the operator to fear that the
posterior wall of the trachea had been opened. In all cases in which
the pharynx is in a state of paresis a careful examination should be
made by means of the laryngeal mirror.
There are no subjective symptoms, and this fact makes it probable that
the affection is more common than has been supposed. The patient
complains neither of pain nor of any other discomfort. This statement
is only true, however, when there is simple loss of sensation. There
may be paræsthesia associated with partial anæsthesia. In such cases
there will be noted the usual symptoms of paræsthesia. In hysterical
forms of anæsthesia the appearance of the parts is often variable from
day to day. The location of the disordered function is well defined at
the time of one examination, while at the next the condition may be
quite different. It is stated by Thaon6 that in one-sixth of the
cases of hysteria the larynx is in some way affected. The epiglottis is
more usually the seat of the affection in the hysterical variety.
Several authors have noted that with the laryngeal disorder there is
often a zone of modified sensation beneath the chin and on each side of
the larynx. This sometimes amounts to absolute loss of cutaneous sensibility.
6 Loc. cit.
COURSE AND TERMINATION.—According to Mackenzie, Von Ziemssen, and
others, the anæsthesias following diphtheria usually terminate in
recovery. It is quite possible, however, that the literature of the
subject does not give us elements on which to base an opinion. I am
inclined to think that cases die from this disorder in which the nature
of the affection is never recognized. It is quite certain that
paralysis of the fauces is not unattended with danger. It is also
probable that in many of these cases the real danger is not so much
from the loss of muscular power in the pharynx, and consequent
inability to swallow, as from the fact that the larynx is not protected
from the introduction of foreign substances, that the intrusion of
these substances is not recognized, and the consequent disorders of the
lungs become the cause of death more frequently than has been supposed.
DURATION.—Paralysis of the sensory nerves of the larynx usually lasts
only a few weeks. When a result of diphtheria it disappears with the
motor trouble with which it is associated. As a complication of
hysteria, or rather when hysterical in character, it may last
indefinitely. When dependent upon changes in the centres from which the
pneumogastrics are derived it has a history commensurate with that affection.
The PATHOLOGY AND MORBID ANATOMY have been suggested in the discussion
of the cause and symptomatology of the disorder. The question of the
local or general changes in the diphtheritic variety is noted in the
history of the disease.
The DIAGNOSIS is made mainly by the examination with the laryngoscope.
The probe will at once determine the presence or absence of the
sensibility of the mucous membrane of the parts. In addition to touch,
electricity may be employed. In these cases the alteration involves
both the tactile and reflex sensory functions. There will therefore be
neither cough nor spasm resulting from a mechanical irritation. The
surfaces are usually quite normal in color and form. The epiglottis is
erect, abnormally so, and there will often be more or less paresis, or
even complete paralysis, of the other muscles of the organ. In some
cases the difficulty in deglutition due to derangement of the reflex
functions may be also suggestive of alterations of sensation in the
parts within the larynx, but it is only a suggestion.
The PROGNOSIS is usually favorable, but for the reasons given above
this should be accepted with some degree of reservation. The
diphtheritic varieties share in the uncertainty of other forms of
paralysis in that disorder. The hysterical forms are not dangerous, but
may continue so long as the primary affection persists.
TREATMENT.—This should be both local and general. The local treatment
consists almost entirely in the application of electricity. Both the
galvanic and faradic currents are recommended. In my own practice I
have been accustomed to resort to the galvanic, but modified by the
introduction of a shunt or switch, so as to produce a wave of
electricity. The manner in which this is accomplished is to connect in
the circuit a coil such as that used for the faradic current. This
takes out of the direct current, with each closure of the circuit in
the coil, a portion of the quantity of the current, and without
entirely interrupting the working circuit gives a wave of electricity,
producing, so far as I can judge, the results of both the primary and
secondary currents. There is not the shock of complete interruption,
while there is the stimulus of the irregular quantity. The electrode
which will be found most convenient is that devised by Mackenzie or
some modification of it. It should be applied through the parts
from one side of the larynx to the other by placing the tip or point of
the instrument in one of the pyriform sinuses over the superior
laryngeal nerve. A double electrode will often answer better, placing
one point in one sulcus, while the other is in contact with the mucous
membrane of some other part of the organ or in the opposite sinus; that
is, on the other side of the larynx. The current then passes through
the parts and stimulates all the tissues between the two poles. The
application should be made every day, and for several minutes at each
sitting, interrupted, of course, as required by the variable condition
of the parts. The current should not be so strong as to produce
positive pain. This is not easily reached, however, for the reason that
the response is slow and uncertain. The strength of the current should
be tested upon the normal surfaces of the patient, or, better, upon the
mucous membranes of the operator, before applying it to the morbid parts.
In case a reliable tangent galvanometer is used, much more certainty
can be reached than when the strength is determined solely by the sense
of touch. With this exhibition of electricity there should also be
administered such remedies as are best calculated to restore the
general strength of the patient—quinia and iron, with the bitter
tonics, and especially strychnia in what would be considered large
doses (.003–.005 grammes), two or three times a day, with interruptions
every few days. In the hysterical cases, as well as those following
diphtheria, electricity is often of great value.
Attention should also be given to the proper treatment of any local
trouble in the viscera of the abdomen or pelvis. Uterine disease, if
present, as it frequently is, demands attention. It is believed by some
authorities that the unilateral disorders of the larynx dependent upon
ovarian irritation generally manifest themselves upon the side
corresponding to the diseased ovary. It is, however, rare to meet with
complete unilateral anæsthesia. In addition to the use of these
measures, change of surroundings, especially in the hysterical variety,
diversion by new associations, new occupations, etc., are to be secured
whenever practicable.
Disorders of motion are perhaps more complex than those of sensation.
They may be divided into two general groups—1st, exalted action; 2d,
diminished or arrested action. The first group is susceptible of a
subdivision: first, those in which the sensory functions are exalted as
well as the motor. In some of these cases the real disturbance is very
probably hyperæsthesia rather than increased irritability of the nerves
going to the muscles. Generally, however, the morbid phenomena are
mixed; the two sets of nerves are both in a state of over-action.
Spasm, for instance, may be the result of excessive activity of the
sensory function coupled with the exaltation of the motor impulses, or
exaggerated irritability. Second, the spasm or exalted activity of the
muscles may be entirely independent of sensory impressions, possibly,
in some instances, dependent upon muscular conditions, but generally
only the local expression of some central nervous trouble. Chorea may
be cited as an example. The diminished action of the motor system may
also be due to either a want of the sensory common or special
impressions; or it may be due to failure of the motor centres or some
interruption of the continuity of the conducting media; or, lastly, it
may be for the reason that the muscles themselves are so changed that
they do not respond to the normal stimuli, such as the
commands of
the will or reflex impressions. It will be seen from this brief
statement that the subject of motor derangements is one of much
complexity. From the very nature of the complications it is often
impossible to satisfactorily analyze the symptoms and to determine with
certainty, in a given case, whether we have to deal with a simple or a
compound result. We may, it is true, in some instances arrive at
approximately correct conclusions by resorting to the physiological
methods of testing the muscle by galvanism and faradism. In other
instances we may by a careful study of the history of the disease reach
at least a provisional opinion. We must, after all, admit that much
will in many of these derangements remain to be conjectured.
There is quite a difference among authorities as to the place in the
classification of disease of the larynx which should be assigned to
spasm as met with in childhood, and which is also occasionally
encountered in adult life. It is not possible, perhaps, in the present
state of knowledge, to separate in every instance those cases in which
there is disorder of the circulation and nutrition of the larynx from
those in which the spasm is the result of disturbance simply of
innervation, or in other cases the reflex manifestations of nervous
irritation elsewhere. Generally, however, this can be done. I have for
a long time been accustomed to consider the affection known as
spasmodic croup to be a mild inflammation of the larynx, and that it
differs from the same affection in the adult for the reason that the
lumen of the tube is smaller, the cartilages are more yielding, and the
susceptibility of the parts is greater, and further for the reason that
the nervous system in childhood is always more prone to spasm than in
the adult. Stridulous laryngitis, however, is a real disease, and is
for the reasons above given a neurosis, even though it is an
inflammation. It is entitled to a separate description for the reason
that the symptoms are so well marked and differ in so many particulars
from those of ordinary inflammations. That there is, besides, a true
spasm of the muscles of the larynx, independent of inflammation, by
which the vocal cords and the constrictors are brought into action and
possibly kept in a state of tonic contraction, is possible.
In a majority of instances of laryngeal spasm there is a degree of
inflammation, as above stated, or at least a degree of congestion of
the mucous membranes. It is certainly true, however, that in
exceptional cases there are no indications of such a condition of the
parts, so far as we can determine by ante- or post-mortem study. It
seems to be evident, then, that under this name of spasm of the larynx
or of some synonym of it many careful observers have recorded facts and
have grouped them with the thought that the functional derangement was
the main trouble. The real difficulty appears to be that the spasm is
in fact a symptom—a symptom of perhaps several different disorders,
but so prominent and creating so much alarm that it has seemed for the
time being to be the disease itself; and yet in most cases there is a
mild form of inflammation, local in its extent, and producing, so long
as there is no interference with the function of respiration, no
general disturbance. It is perhaps appropriate to include in the
discussion not only the purely nervous cases, but also those conditions
in which, while there is hyperæmia, and probably always some
derangement of secretion, nevertheless the symptoms and dangers concern
mainly the motility of the muscles of the organ.
The disease occurs both in children and in adults. There is, however,
in its etiology, course, and terminations quite a marked difference, as
observed before and after puberty. We shall therefore consider, first,
spasm of the glottis in children; second, in adults.
SYNONYMS.—Laryngismus stridulus, False croup, etc.
ETIOLOGY.—Predisposing Causes.—The disease occurs most frequently in
children from a few months to two or three years old. It is
occasionally met with in those still older and up to puberty. It seems
to be more often encountered in patients of a strumous habit than in
those of a healthy constitution. Rickety children are especially liable
to the affection: the German pathologists especially insist upon this
factor. Patients of a nervous temperament predisposed to general spasms
are especially predisposed to this affection in the larynx. It is a
general law that muscles weakened either by disease or by fatigue or by
deficient nutrition are especially irritable. In them mechanical as
well as other forms of stimuli produce local contraction with great
readiness. These contractions are, it is true, rather the expression of
the condition of the muscles than of the nerves. The muscular condition
must, however, be regarded as a predisposing cause of the spasm. In the
same way, perhaps—namely, by the inherited tendency to lower forms of
vitality, weakened muscular power—we may account for the fact that
family history of similar conditions, such as false croup in other
members or in the parents, should be considered as among the evidences
of predisposing tendencies to spasm of the glottis.
Sex has in this affection, as well as in most laryngeal diseases of
children, a predisposing influence. Mackenzie has collected in all,
from different sources, 8248 cases. Of these, 5378 were boys and 2870
girls—a proportion of nearly 2 boys to 1 girl. In adults the reverse
holds good, females being much more frequently seized than males. It is
certain that season has something to do with the development of the
disease, but this influence should be regarded rather as a producing
than a predisposing cause.
Dentition, worms, weaning, or anything which produces an irritation of
the alimentary canal may also, by exciting the reflex irritability of
the nervous system, become predisposing causes of laryngismus. The
influence of dentition has, however, been probably over-estimated.
The exciting causes of spasm of the glottis are not well defined. In a
few cases we are able to definitely fix upon something as the occasion
of the attack. It is possible that there may be some central lesion,
and this may be well defined. This is rare, however. It is nevertheless
true that the onset is generally preceded by some derangement of the
general health. There has been for a day, or perhaps only for an hour
or two, a slight cold, a little hyperæmia of the respiratory mucous
surfaces, or disturbances of the digestive tract, or the child has been
unusually fatigued or excited from play or study. The secretions have
in other cases been deranged. No one of these causes has perhaps been
of sufficient gravity to attract the attention of the mother or nurse.
The indisposition, if it has been noticed at all, has been regarded as
only one of the many ephemeral troubles that so often occur in infancy,
and no anxiety has been felt. Of all these possible causes, the one
most frequently invoked after the attack is a cold, slight, it is true,
but nevertheless, in the light of the subsequent history, evidently a
mild form of inflammation of the laryngeal mucous membranes.
SYMPTOMS.—Spasm of the glottis usually takes place at night. It is
true that some authorities deny that this is the case. Stefen says
"that it is quite as likely to occur during the day as night." In a
great majority of instances, however, it will be found that the attack
occurs after the child has been asleep. During the day there has been
perhaps a slight disturbance of the general health, a little
inclination to cough, or there has been a catarrh of the fauces or
bronchial mucous surfaces; nothing, however, of a serious character has
been observed. At midnight or later the little one awakes with a
crowing or
whistling inspiration. It starts up in bed, and
evidently experiences great difficulty in breathing; this difficulty is
manifestly in inspiration; expiration is easy and free. The eyes are
prominent, the lips blue, the surface often bathed in perspiration;
pulse frequent, small, at times irregular; there is, if the child be
old enough to reason in the matter, great alarm; there is often cough,
and this cough is characteristic: it is a hoarse, metallic, barking,
peculiar cough, described as croupy. If the spasm is limited to the
larynx, the other muscles not being affected, the patient clutches at
whatever it can reach, and often seizes the throat as though there was
something there to tear away. The general surface becomes cyanotic and
all the symptoms of asphyxia are present. The voice, though not
generally extinct, is altered; it becomes hoarse, or husky, as it is
called; in a few minutes the severity of the attack is passed, and the
little sufferer sinks exhausted into a sleep more or less disturbed. A
second attack may occur the same night, or there may be nothing more to
alarm the attendants till the next night. The second attack, if it
occurs, as it generally does, on the succeeding night, is less severe
than the first; the third still more mild; and this generally ends the
case for the time being. During the intervals—that is, during the
day—the patient in a majority of cases is up, and seems to be but
slightly affected by the seizure of the night before. There will
perhaps be a slight cough, with some loss of appetite and indisposition
to engage in play. This is the most usual type of the disease. In a few
cases there is more marked derangement of the general health. The
spasms are more severe; the cramp is not confined to the laryngeal
muscles, but involves other parts, such as the muscles of the chest and
the extremities. During the intervals of the attack there is perhaps a
little fever, the digestive tract is disordered, the cough may be
marked during the day, there may be an increase in the secretions of
the respiratory surfaces. Attacks may recur during the day and for
several days; the cough may retain its croupy character, and the voice
may continue to be hoarse.
COURSE AND DURATION.—Spasm of the larynx is usually a transient
phenomenon, lasting only from a few seconds in the milder cases to
several minutes in the more severe forms of the disease. The attacks
are intermittent. The seizures are relieved by intervals of comparative
relaxation of the muscles of the parts. Even in the intervals there is,
however, a degree of contraction of the constrictors, so that the
relief is not absolute. Two or three days elapse before the attack may
be said to have entirely ceased. In the severer forms the consequences
of the spasm may continue even for a still longer time. There are
usually no sequelæ. When the patient has recovered there is nothing
left of the disease, though there is often a predisposition to a
recurrence; the same causes that produced the first attack, or even
slighter causes, may produce a second. These causes are generally
persistent; the seizures are therefore usually repeated.
PATHOLOGY.—In cases dependent on central disease the pathological
changes are to be sought for outside of the larynx. In rickets and
other morbid conditions which by reflection produce spasm of the
glottis the pathology proper is distant and not in the organ; there is
only an excess of motility in the nerves and muscular apparatus.
Efforts have been made to differentiate spasm and false croup, but the
confusion is only equalled by the disagreement as to the relation of
diphtheria to true croup. It is probably true that the cramp is
generally due to some excess of motility in the system at large, and
that the larynx is the seat of pathological changes that determine the
spasm in that organ. This is especially true in those cases associated
with rickets, derangement of the alimentary canal, etc. It seems to be
a fact, nevertheless, that in a majority of cases the mucous membranes
are, as already stated, the seat of a very mild inflammation. Or
perhaps we should say they are slightly hyperæmic. So far as we can
judge from
examination in cases which have terminated fatally, as
well as from ante-mortem observation, there is no structural change of
tissue to be recognized by the naked eye, unless it be, during life, a
slight fulness of the vessels. There is a change, however, in the form
of the organ, at least at the entrance to the larynx. The constrictors
are in a state of action, so as to partly close the superior opening to
the larynx, and the epiglottis is rolled so as, in some instances, to
become almost a tube. I have repeatedly recognized this in the image
seen in the laryngeal mirror. Cohn reports a case of impaction even of
the epiglottis in the vestibule of the larynx (p. 627). This fact is
also suggested by the difficult inspiration and the altered voice and
cough. In young children the yielding character of the cartilages
probably adds largely to the obstruction produced by spasm of the
muscles about the vestibule.
DIAGNOSIS.—The diseases with which spasm of the larynx is most likely
to be confounded are true croup, simple inflammation of the larynx,
foreign bodies in the larynx, and possibly, in the absence of the
history of the case, tumor situated in the glottis or along the vocal cords.
It will readily be distinguished from true croup by the fact that in
the one case, true croup, the attack is insidious: the patient has been
sick some time, usually several days before spasm occurs; there is also
fever, with usually more cough; the voice is altered before the
appearance of spasm; the first seizure is slight, almost imperceptible,
and the subsequent attacks become more and more severe; dyspnoea is
continuous. All these facts are in marked contrast with the picture of
an attack of spasm of the glottis as we have attempted to describe it.
In the one case the most alarming symptoms are at the beginning. There
is an explosion of morbid phenomena, each recurrence less alarming till
complete convalescence is established. In the other disease the
symptoms and dangers are constantly increasing in severity, till at
last the spasms become as fearful as the initial seizure in
laryngismus. The morbid anatomy of the two diseases is also widely
different; and this difference can be recognized during life. Simple
ordinary inflammation of the larynx may give rise to hoarseness and
cough; the hoarseness is, however, different from that in laryngismus.
There is fever, and the hyperæmia of the organ can be readily
recognized. The disease is progressive, does not present its most
alarming symptoms at the beginning, and spasm, if it occurs, is a late event.
It is possible that spasm of the larynx might be mistaken for a foreign
body in the organ. It will be remembered that the attacks of spasm
usually occur at night after the child has been asleep. The history of
foreign bodies in the larynx reveals what we should expect—namely,
that the accident almost always occurs during the day. In a great
majority of cases this history also furnishes reliable information of
some substance or object which was in possession of the child, and
which has disappeared. The dyspnoea is more continuous and the course
and symptoms more variable. There will therefore be no great difficulty
in any case, and in most cases no difficulty at all, in making a
certain diagnosis as between these two conditions. In a few cases of
laryngeal tumor the symptoms are very similar to those of the disease
under consideration. The attacks in the case of a pedunculated tumor on
the vocal cords may take place at night and may be intermittent. The
rarity of this affection in children in comparison with spasm of the
larynx, and the further fact that in the case of tumor there is a more
continuous disturbance of respiration, make the differentiation easy.
Paralysis of the adductors gives rise to more dyspnoea during sleep,
but the history and laryngeal mirror make the diagnosis easy and certain.
PROGNOSIS.—The large majority of cases of spasm of the larynx recover.
Statistics show that there are deaths from this disease, but in
proportion to the number attacked I think the mortality is small;
how small we do not know. The confusion in classification is so great
that we cannot place much dependence upon published statistics. In our
climate I think most observers will admit that a patient seldom dies
from this affection unless there be associated with it some morbid
condition of a serious nature.
TREATMENT.—The immediate and pressing indication in spasm of the
larynx is for something to relax the constrictors and allow the act of
inspiration to be accomplished without embarrassment. For the
accomplishment of this purpose three methods of treatment may be
resorted to: First, heat; second, emetics if there be time; third,
anæsthetics and antispasmodics. Of all these measures, the first is the
most easily applied, and will probably in a great majority of cases
prove efficient. It is usually within the reach of the attendant or
nurse. It can in any event do no harm. This fact is not to be
overlooked, as the symptoms are so alarming that friends and physicians
are often tempted to do too much. Heat may be applied by means of
cloths dipped in hot water (110° F., or even more) applied to the neck
and chest of the patient, or the child may be placed in a bath of 105°
F., while the head is kept cool by cloths wet with cold water. This
treatment may be continued till the spasms yield. The second of the
measures suggested is usually safe, and may be resorted to along with
the first. Those agents should be selected which act with most
promptness, and the doses should be adapted to the age and condition of
the patient. Alum, sulphate of zinc, sulphate of copper, are perhaps
the best, but by no means the only ones. Ipecacuanha, by the relaxing
effect which it has upon the muscular and nervous system, may be useful
not only in overcoming the spasm, but in preventing the recurrence of
the attack. Antimony is unsafe, and the other emetics are quite as
useful in relaxing the muscles. The third of the measures suggested
should be used with great caution. It may be doubtful whether, in fact,
anæsthesia is ever indicated in simple spasm of the muscles of the
larynx. The dyspnoea renders it very difficult to produce full
anæsthesia, and without this the relaxing effect is not reached. In
cases in which there is serious disease outside of the larynx there
should be appropriate treatment directed to the extrinsic trouble.
During the intermission—that is, during the day following the
spasm—attention should be directed to the condition of the digestive
and excreting organs as well as to the respiratory tract. In malarial
districts I have thought that quinia given in antiperiodic doses the
morning after the seizure has been of benefit in preventing or
diminishing the severity of the next spasm. In addition to these
measures, for the prevention of the subsequent attacks bromide of
potassium or bromide of sodium in 3 to 5 grain doses may be given once
in three to six hours after the spasm has ceased. Five grains of
chloral, as advised by Mackenzie, given at bedtime the night after the
attack, will also diminish in a certain number of cases the severity of
subsequent seizures, or possibly entirely prevent them. Musk, myrrh,
camphor, castor, and other similar antispasmodics are theoretically
indicated, but, in fact, are of but little if any value. If the disease
is central, involving the floor of the fourth ventricle, the local and
general spasms are only symptoms, and the treatment must be directed
entirely to the preservation of life. It should be remembered in this
connection that in the floor of the fourth ventricle the pneumogastric
and the glosso-pharyngeal, as well as filaments of the spinal
accessory, have their origin. The range of distribution of these nerves
marks to some extent the range of the morbid phenomena in disease of
central origin. It may of course be true in any given case that only a
small portion of the central gray matter is involved, but as a rule the
organic change in one of the nerves at the point of origin does give
rise to disorder of function of one or both of the others.
General tonics and attention to hygienic conditions are of great
importance for the purpose of giving vigor and regularity to all forms
of nervous and muscular activity.
Spasm of the Glottis in the Adult.
The affection is usually bilateral; that is, all the muscles guarding
the vestibule of the larynx, and probably in most cases the adductors
of the vocal cords, are involved. That this is not always true,
however, I am convinced by a case now under observation in my own
practice. The patient is an adult, and I have been able to determine by
laryngoscopic examination that the muscles on the left side are the
seat of the spasm. The epiglottis is drawn downward and backward on
that side. The top of the left arytenoid cartilage is drawn forward,
while the similar parts of the right side remain in their normal
position except the change necessarily produced in the epiglottis. This
condition is not constant, and is not a paralysis of the opposite side.
This is the only case that I have seen, and I do not know of any
similar case on record. Nothnägel7 reports a case of spasm of the
adductors upon making an effort to phonate. The cords were normally
separated in inspiration, but at the first effort to speak they closed
firmly, leaving no line of opening between them. The attack seemed to
have been produced by a powerful impression made upon the nervous
centres. It seems probable that it was hysteria. Krishaber describes a
form of what he calls spasm of the larynx in adults, which seems to be
rather a local manifestation of a central disease than a neurosis of
the larynx. It is in many respects similar to epilepsy. The danger,
even in cases in which life is threatened, is not from asphyxia, but
from the arrest of the functions of circulation and respiration—an
arrest of the effort even to breathe. It hardly seems proper to include
this among the troubles of which we are treating. He calls it ictus laryngé.
7 Deutsch. Arch. für klin. Med.
ETIOLOGY.—It is certain that the same causes that produce spasm in
childhood are efficient in the adult, though there is an absence of
some of the conditions that render the disease so frequent in infancy.
The cartilages have become more firm, and consequently are not so
easily moved by the action of the constrictor of the vestibule of the
glottis; the size of the cavity in proportion to the necessities of the
body for air is larger; the control of the voluntary over the automatic
actions of the muscles of mixed function is greater; the reflex
irritability of the nervous apparatus is less. These facts all render
the probability of spasm in the adult much less than in the child. On
the other hand, the development of the generative organs, and the
widespread influence which they have upon the respiratory and
circulatory as well as upon the central nervous system, introduces a
new factor as a cause of motor disturbances of the larynx. This new
element is a reason for the fact that in adults the predisposing
influence of sex is reversed: after puberty the disease occurs more
frequently among females than among males. The hysterical character of
many of these cases may be inferred from this preponderance of one sex
over the other among the subjects attacked.
This fact has been seen and described by Charcot, Lefferts, and others.
Irritation along the track of the nerves, morbid conditions of the
mucous surfaces, or muscular irritability, may be each a cause of spasm.
SYMPTOMS.—The symptomatology of spasm in the adult does not differ in
any material respect from the phenomena observed in children. It is in
the rarity and the comparatively milder character of these symptoms
that the difference is to be found. The attacks occur at night, as in
children, but, so far as I have observed them, they may also take place
during the day. When very severe they occasion great alarm to the
patient, and for this reason produce a profound impression, not
only upon the physical, but also upon the mental and emotional, state.
The duration and termination of the affection are about the same as in
children. In the mortality-tables we find every year a certain number
of deaths from spasm of the larynx in adults. It is probable that among
these there are quite a number which should be placed elsewhere. A
patient may die from spasm of the larynx, which spasm is produced by an
ulceration, by a tumor, by the presence of a foreign body in the organ.
As in children it is quite certain that the deaths reported as from
spasm of the larynx include many that should be referred to central or
other diseases, so here the immediate cause of death is not
unfrequently given instead of the real and essential cause. This fact
makes it difficult to reach anything like a definite conclusion as to
the termination of the disease; only this can be said: the great
majority of cases recover.
PATHOLOGY.—With the exception of those cases in which there is disease
of the central nervous system or along the course of the nerves, we
know nothing of the morbid anatomy of this affection. In fact, there is
no appreciable alteration of the tissues or of the relations of parts;
the spasm is to be considered as a symptom of disease, and not as the
disease itself, or necessarily even as a sign of morbid structure in
the organ.
DIAGNOSIS.—In adults we can make the diagnosis certain by the aid of
the laryngoscope. This can be done in a certain number of cases in
childhood, it is true, but not with the same ease as in those who have
reached more mature years. Ulcerations, benign and malignant growths,
and foreign bodies may each or all produce spasm, but the existence of
such causes is revealed by the mirror, and excludes such cases from the
group under consideration.
TREATMENT.—This does not differ in any essential respect from that
suggested in spasm of the larynx in children. Attention to the
condition which has been instrumental in the production of the
affection, the use of antispasmodics, such as bromides, chloral, myrrh,
musk, camphor, ether, chloroform, etc., will meet the urgent symptoms,
while the use of tonics, such as vegetable bitters, quinine, iron,
cod-liver oil, with attention to a proper hygiene, constitutes the
general treatment.
The question of tracheotomy in spasm of the larynx should be
considered. It is sometimes stated that there is never in simple spasm
a justification for this operation, and that the other means at our
control are always adequate to meet the indication. Krishaber, Thaon,
and others are of this opinion. Gougenheim and Schnitzler think it is
sometimes required. While in a very large majority of cases of
uncomplicated spasm of the larynx the spasm will yield to the measures
recommended, it is nevertheless true that there are cases in which this
result is not realized. The slowness of the action of some of the
drugs, the difficulty in securing their introduction into the system,
their absence at the time of the attack, and the delay in their
administration,—all these facts may render it absolutely necessary to
resort to an operation for the purpose of saving the life of the
patient. It is, however, rare that this necessity will occur. In one
case recently in my own practice I think a life was lost for want of
the operation. The trouble was, as I thought, of hysterical origin, and
at the time of the consultation did not threaten life. There was free
movement of the vocal cords, and the vestibule of the larynx was not
obstructed. Spasm of the constrictors occurred at night, and did not
continue for a great length of time. There was certainly not paralysis
of the abductors of the glottis. I directed an antispasmodic, and
advised that if the spasm returned the next night a physician in the
neighborhood should be sent for. The spasm did recur, and the physician
was called, but before he reached the house the patient was dead. No
post-mortem was held, and the question of the morbid anatomy could
not be determined with any degree of certainty. From the fact that
there had not been spasm till the night previous to the consultation,
that she was an adult female previously in good health, with no organic
disease, no tumor, no ulceration, no paralysis, and with a perfectly
healthy condition of all the parts of the organ as revealed by the
mirror, I am led to believe that the cause of death was simple spasm of
the larynx. It is possible that this was one of those cases described
by Krishaber and Charcot under the name of ictus laryngé or laryngeal
vertigo, and that the death was due to some central disease; but the
description given by the attendants was that of true spasm of the
muscles of the larynx, and it is more probable that, as in Cohen's
case, there was impaction of the epiglottis in the vestibule. The
question of the operation should be considered in severe spasm which
does not readily yield to the ordinary means. It is certain, I think,
that life may sometimes be saved by a timely opening of the trachea.
E. F. Ingals suggests tubage of the larynx in cases of spasm
threatening death. If the physician is present at the time of the
dangerous symptoms, this may be attempted. A large-sized catheter or
one of Schrötter's dilators may be used with no danger to the patient,
and possibly with the result of saving life.
There is a kind of disturbance of the motor function of the larynx
which has been described as chorea. The derangements of phonation and
of respiration are such as we should naturally expect from want of
co-ordination of the muscles concerned in speaking and breathing. There
may be a true chorea of the laryngeal muscles when there is no other
indication of the disease. Lefferts, in the first volume of the
Transactions of the American Laryngological Association, reports
three cases which he designates chorea of the larynx. They were all
characterized by spasm of the muscles concerned in phonation. It is to
be observed, however, that all three were women in early life, and that
there were no other choreic troubles mentioned. There were, so far as
the histories indicate, no hysterical phenomena present, if we assume
that the laryngeal trouble was not of that character. In the recital of
these cases the author seems to think that the evidence that the
patients were not simulating is a sufficient proof that the troubles
were not hysterical. This will not, I think, be accepted as adequate
proof of the absence of hysteria. It is certainly possible that the
patients were all three really choreic, but there is at least in the
fact of the sex, the absence of other manifestations of this disease,
and, so far as the author informs us, no antecedent history of
rheumatism or other morbid conditions so frequently preceding chorea, a
doubt as to the nature of the affection. Chorea affecting the muscles
of the throat and of respiration is, I think, not unfrequently met
with, but there is in these cases, so far as I know, such well-marked
symptoms of the origin and nature of the trouble as to leave no
reasonable room for doubt.
Cases of unmistakable chorea limited to the laryngeal muscles have been
seen by Knight, Roe, and others. Chorea or spasm of the expiratory
muscles alone may occur. I have the records of one such case, an adult
male. I was unable to say certainly that the larynx was the only part
involved. After a full inspiration there followed a series of short,
jerky, expiratory acts till the movable air in the thorax was all
expelled. For a few breaths the respiration was regular and full, when
the same phenomena were repeated. There was no organic disease. There
was forcible closing of the glottis during the
spasmodic
expiratory efforts. The patient recovered under treatment by
arsenic.8
8 It may not be easy in all cases to distinguish between the
true choreic cases and the hysterical affections. Knight of Boston has
given special study to choreic troubles of the larynx. He recognizes
three varieties: The first includes those cases in which the adductor
and expiratory muscles each side of the larynx are involved; second, in
which the laryngeal muscles alone are involved; third, in which the
expiratory muscles alone are involved.
TREATMENT.—This should be the same as for other forms of chorea.
Besides this ataxic condition we have hysterical disturbances of the
motor functions, which are of various kinds according to the muscles
involved. A constant effort to clear the throat, as it is called, is
sometimes met with—a scraping of the throat, by which there is
produced a rough, harsh sound similar to that which is heard in some of
the inflammations of the organ. At other times the form is that of
cough—a cough which is almost constant, and which is not associated
with disease of the mucous surfaces of the thoracic viscera. This cough
is sometimes almost continuous for days, and months even. It occurs at
intervals of a minute or more, with the same character of hoarseness
and roughness, without any interruption, except during sleep, when the
breathing is free and easy. I saw a few years ago a little patient who
had a cough of this nature which lasted several weeks, when it was
replaced by the peculiar rasping, scraping effort mentioned above. The
patient was a girl of fourteen years and had not developed. The moral
effect of a severe case of typhoid fever in a younger sister, followed
by the confinement of the mother, effected a cure. It is not at all
uncommon to find that certain patients suffering from uterine troubles
are also affected with laryngeal derangement of this character. A lady
was seen by the writer a few months ago who had a rough, harsh cough,
with attacks of asthma. There was no evidence of thoracic disease, and
I learned that she had had this cough from the time of her last
confinement. I advised her to consult a gynæcologist, who found that
she had a laceration of the cervix uteri. For this she was operated
upon, and from the time that she recovered from the immediate effects
of the operation she had no more asthma or cough. It had been purely hysterical.
Cohen reports in his work On Disease of the Throat (p. 627) an
epidemic of hysterical cough in a school for girls near Philadelphia.
The cough was peculiar in character. The neighbors called them the
barking girls. Cough of this character may be dependent upon other
conditions than hysteria. Irritations reflected from other parts, as
the ear and naso-pharynx, have been noticed.9
9 Cohen, p. 636.
E. F. Ingals reports a case of an adult female whose voice had been
abnormal for several years. It had been preceded by measles. Upon
laryngoscopic examination the ventricular bands were seen to be
approximated during the effort of phonation, while the true or vocal
bands were, when last seen, moderately separated. The voice was not
extinct, but hoarse, low in pitch. The true cords could not be seen
during phonation on account of the closure of the false cords. This
could hardly be considered as chorea, but there must have been an
irregularity of muscular action, something between chorea and
hysterical ataxia. There were no other abnormal movements of the larynx.
TREATMENT.—For these hysterical forms of trouble the treatment should
be such as to correct, if possible, the morbid conditions upon which
they
depend. Under the subjects of Anæsthesia, Hyperæsthesia, and
Paralysis this has been sufficiently discussed.
PARALYSIS AND PARESIS OF THE MUSCLES OF THE LARYNX.
The function of the muscular apparatus concerned in respiration and
phonation depends mainly upon the action of the recurrent nerves, as
stated in the paragraph devoted to the Anatomico-physiological Facts.
Disease of the centres in or near the floor of the fourth ventricle,
where, in close proximity, the pneumogastric fibres of the accessory
and the glosso-pharyngeal nerves take their origin, may be the sole
cause of a paralysis of these muscles. Disease along the course of the
nerves anywhere between this centre and the termination of the nerves
may give rise to the same result. Change in the structure or function
of the nerves at the point of their contact with the muscles in some
instances may possibly be the sole cause of the paralysis. Alteration
of the muscles themselves, such as atrophy or degeneration, produces a
like effect. In certain cases both the nerves and muscles are involved
in the morbid processes, but in some instances, even where there are
undoubted changes in the muscles, these changes are secondary, the
result of the long inactivity of the muscles. It is possible to group
these morbid conditions with reference to the nerves involved; but it
frequently happens that several different conditions are present at the
same time, and groups of muscles supplied by different nerves are
simultaneously involved. It is therefore difficult to classify these
troubles with reference to the nerves by which the parts are supplied.
The further fact that of individual muscles or parts of muscles
supplied by the same nerve-trunk some are affected, while others are
intact, renders this effort to make a physiological classification
still more unsatisfactory. As a rule, however, we may state in general
terms that diseases of the superior laryngeal nerves produce paralysis
or paresis of the external tensors of the vocal cords, the
crico-thyroids, and, to a certain extent, of the constrictors of the
larynx. Diseases of the recurrent nerves produce paralysis or paresis
of the other muscles of the organ. If the disease of the nerve is of
one side only, we have, as a rule admitting of only a very few
exceptions, a unilateral impairment of the motor functions of the
parts. In the case of the loss of power of individual muscles or parts
of muscles it is by no means easy to find a satisfactory explanation.
It seems probable that in some instances the reason is to be sought in
the centres, but in a great majority of cases the muscles are
degenerated or the nervous filaments of the particular parts are in a
morbid condition.
Notwithstanding this difficulty of classification, the troubles of
respiration and phonation due to the complete or partial paralysis of
the muscular apparatus are, for the convenience of study, divided into
groups. These groups are based either upon the seat of the primary
lesion or upon the kind of disturbance or the symptoms of the case.
Neither method of grouping is satisfactory. We must content ourselves
with a provisional arrangement. With the single exception of the
arytenoideus, the muscles are double and symmetrical; paralysis may
therefore be general or partial, unilateral or bilateral.
The causes, symptoms, or terminations vary with this general or
partial, double or single, character of the affection. We propose,
therefore, to consider these motor derangements under the following
heads, which in the main follow the classification of Mackenzie and
most other writers upon the subject:
1. Paralysis of the whole larynx—of one-half of the larynx;
2. Paralysis of the constrictors of the larynx;
3. Paralysis of the adductors of the vocal cords: (a) unilateral,
(b) bilateral, (c) central;
4. Paralysis of the tensors of the vocal cords: (a) internal, (b)
external, (c) unilateral, (d) bilateral;
5. Paralysis of the abductors of the vocal cords, openers of the
glottis: (a) unilateral, (b) bilateral.
Paralysis of the Whole Larynx.
Paralysis of all of the muscles of the larynx gives rise to a position
of the parts which has, as before stated, been called the cadaveric
condition. The vocal cords are neither abducted nor adducted. The
opening of the glottis is sufficiently wide to admit of easy
respiration, but the cords are so far apart as to make phonation
impossible. The effort to articulate is not attended with any change in
the position of the vocal bands. In respiration there is no additional
widening of the glottic chink. The superior portion of the larynx is
also in a peculiar condition. The epiglottis is erect, standing against
the dorsum of the tongue; the vestibule of the larynx is widely open;
deglutition is difficult.
ETIOLOGY.—So far as we know, the causes are to be found either in
central disease or hysteria. When the cause is in the centres, there is
almost of necessity functional lesion of other parts of the muscular
apparatus, especially of the parts supplied by the glosso-pharyngeal
nerve. There will, therefore, be dysphagia. It is possible that the
central lesion may be very circumscribed; in such cases we may have
paralysis of individual laryngeal muscles or parts of muscles. These
cases are probably very rare, and the indication of more general
paralysis is, in fact, the point upon which the diagnosis of central
disease depends. Tumor or other disease along the track of the spinal
accessory before it unites with the pneumogastric may produce the same
effect. When the affection is upon one side only the paralysis is also
unilateral. There are, as before noted, exceptions to this statement.
In these instances it is probable that the innervation of the affected
part or side is supplied by branches from the opposite trunk. Such
cases have been reported by George Johnson, Lefferts, and others. It
has also been found that injury or paralysis of one recurrent nerve is
sometimes followed by bilateral paralysis. Schnitzler reports a case in
the Wiener Med. Report for 1882. The left recurrent was compressed by
aneurism of the arch of the aorta; the right was normal. There was,
however, bilateral paralysis. Experiment by Tourgues10 demonstrated
the fact that powerful excitation and consequent exhaustion of one of
the pneumogastrics may result in paralysis of the other. This result is
in accordance with facts seen occasionally in traumatism of one of the pneumogastrics.
10 Reported in the Gazette de Montpellier, Nos. 35 and 36,
1882.
A pure, uncomplicated paralysis, in which all of the muscles of the
larynx are implicated, and in which no other muscles are concerned,
will almost always be found to depend upon some lesion of the
pneumogastrics or the spinal accessories after they leave their point
of origin. Whether the paralysis is dependent upon the lesion at one
point or another, the symptoms are the same so far as the larynx is
concerned. The vocal cords are in a state of absolute rest between
abduction and adduction; the effort at phonation gives rise to no
contraction of the tensors; the arytenoids leave the cartilages
slightly separated; and the state of the organ is that of muscular death.
When the lesion upon which a paralysis of the muscles of the larynx
depends is below the point at which the superior laryngeal nerves leave
the
pneumogastrics, the paralysis is limited to the phonators and
respirators. The muscular bands and fibres by which the glottis is
constricted are, in part at least, still capable of being thrown into
contraction. This condition of recurrent paralysis may be due to a
disease of the nerve-trunks, tumor pressing upon the nerves,
cicatricial tissue by which the nerves are compressed, aneurism of the
arch of the aorta or right subclavian artery, disease of the apex of
the lung, especially of the right side, pleuritic adhesions, or, in
fact, any injury or lesion along the trunks of the recurrents or
pneumogastrics. The paralysis may of course be partial or complete.
The SYMPTOMS vary according to the extent of the muscular disability.
In case of complete paralysis of one side there may be aphonia, but not
dyspnoea. The glottis admits a sufficiency of air, but does not close
so as to allow of the vibration of the cords. Where there is complete
paralysis on one side only, the voice is not necessarily entirely
suppressed, but it is changed in its quality; it becomes rough, weak,
and in its use gives rise to great fatigue. In long-continued cases
there is in part a compensation for the want of motion of one of the
vocal bands. The muscles of the sound side act with increased vigor, so
as to carry the sound cord at its posterior extremity beyond the median
line. The result is, that the two cords are brought so near each other
that phonation is possible. The arytenoid of the non-paralyzed side is
drawn forward beyond its fellow. The cord upon the affected side is
less tense than that on the healthy side. The vibrations are therefore
not equal; the pitch is different; the voice is therefore unnatural,
rattling, uncertain.
As we proceed to discuss the lesions in individual muscles or sets of
muscles we shall have occasion to refer to these etiological
considerations, as well as to some of the symptoms noted with partial
or complete loss of power of the whole group of muscles of the organ.
Paralysis of the Constrictors.
Complete paralysis of the muscles, by which the vestibule of the larynx
is closed, is rare. The partial paralysis of these muscles is, however,
by no means uncommon. As we have already endeavored to show, it is
probable that the motor functions of the muscular fibres in the
ary-epiglottic folds—the superior constrictors—are mixed. Probably
both the superior and inferior laryngeal nerves are concerned in their
movements. It is not, therefore, easy to group these disorders
according to the nerves involved, as has been done by Von Ziemssen,
Mackenzie, and others.
Partial paralysis of the constrictors may be due to deficient power of
one or both of the laryngeal nerves, superior or inferior. The parts
involved are the arytenoids, transverse and oblique, and the muscular
fibres in the folds going from the arytenoid and from the thyroid
cartilages to the epiglottis.
The ETIOLOGY of this form of paralysis associates itself with that of
anæsthesia of the parts—namely, the arrest of motor impression in the
centre, obstruction along the course of the nerve, disease in the nerve
itself, in its trunk or termination, or, lastly, myopathic changes
rendering the muscle incapable of responding to the nervous influences.
Disease in the centres may possibly affect only these muscles; the
disorders of motion may be well defined and local in extent, but
usually, in case of central disease, there is a complication of
external manifestations and we have a wider range of disturbances. The
most common cause of this loss of power is diphtheria.
SYMPTOMS.—The symptoms of paralysis of the constrictors of the larynx
are for the most part mechanical. The failure to close the vestibule of
the organ in the act of swallowing allows food or drink to pass into
the larynx,
and, as there is usually anæsthesia of the parts also,
the invasion of the larynx is not perceived; no reflex irritation is
produced, no cough for the extrusion of the offending matter, which may
descend into the trachea, and, reaching the bronchi, may become the
agent in the development of a bronchitis or a broncho-pneumonia. The
secretions of the mouth overflow the borders of the laryngeal opening
and fall into the tube below. Fluids are swallowed with greater
difficulty than solids. The voice is not altered except in cases where
the crico-thyroids, one or both, are involved, as in complete paralysis
of the superior laryngeal nerve. The effort to close the glottis, as in
the preliminary act of coughing, is accomplished with difficulty. The
sound of the cough is somewhat altered. This is for want of the
reinforcement to the adductors furnished by the closure of the
vestibule of the larynx. Upon laryngoscopic examination the epiglottis
is seen to stand erect against the dorsum of the tongue. The
ary-epiglottic folds are lax or wide apart. With this is loss or
diminished sensibility of the surfaces. There is little or no change in
the color of the membranes. The secretions are normal in quality, and
only slightly in excess in quantity.
The course of the disease is in cases of diphtheritic origin like that
of anæsthesia from the same cause. The termination, except in rare
instances, is recovery. In cases of central origin the local symptoms
in the larynx are almost necessarily associated with disorders of other
parts. The progress and termination will depend upon the nature and
extent of the central lesion.
The PATHOLOGY of this form of paralysis is probably multiple. When of
diphtheritic origin it has been believed to consist in a change of the
nerves along the trunk or in their distribution, or an alternation of
nutrition due to the local changes in the larynx or pharynx during the
progress of diphtheria, or to both of them. It is also probable that it
is in many cases as much a myopathic as a neuropathic trouble. In other
words, during the progress of the diphtheria the muscles, as well as
the nerves, have undergone a change in their nutrition; and this local
change in the peripheral portions of the nerves, along with this
degeneration of the muscles, goes to make up the pathological anatomy
and constitutes the essential local morbid condition.
There is, however, abundant reason to think that in some cases at least
the influence of the diphtheria in the production of paralysis reaches
far beyond the parts which are the seat of the local manifestations of
the trouble, or even the centres from which these nerves are derived.
It is well known that the extremities may be affected, and that other
muscles become involved which can have no direct and immediate relation
to the tissues which have been attacked with the diphtheria. It seems
therefore evident that there must, at least in certain cases, be a
general derangement of the centres, or that there must be some other
explanation for the impairment of the muscular power than that which
ascribes its loss solely to the local and poisonous action of the
morbid deposit or to the defective nutrition of the parts. It is
probable that there is in these cases a widespread influence, a
constitutional trouble, which, like the disease itself, is general and
not local except as to its manifestations.
Paralysis of the Adductors.
A pure, uncomplicated paralysis of the adductors of the vocal cords is
extremely rare. When present it is marked by symptoms and signs which
are easily recognized. A partial paralysis of an hysterical nature is,
however, not unfrequently encountered. The etiology of paralysis of the
lateral crico-arytenoid muscles is in most instances the same as that
of the other muscles of the larynx. There may be a morbid condition of
the centres in the fourth ventricle, from which the spinal
accessory takes its origin. It is certainly possible in theory that
certain fibres ultimately distributed to these muscles may alone become
diseased in their course along the trunk of the nerve. There may be
change in the final distributions by which the function of the nerve is
arrested. There may be myopathic change in the muscle itself, rendering
it non-responsive even to normal nerve-impressions. All of these causes
are theoretically possible. In fact, however, we know but little of the
real causes which operate in any given case. Mackenzie, Von Ziemssen,
and others ascribe it in some instances to catarrh from exposure to
cold. There is developed a hyperæmia of the mucous surfaces of the
supraglottic space. The structures beneath are involved in the
tumefaction as a result. The voice is impaired or lost; the aphonia,
which was at first due to the mechanical difficulties in the way,
persists after the local inflammation has subsided. The vocal cords
remain permanently apart, even though there is no swelling to prevent
the arytenoids from approaching each other. Gerhardt attributes this
form of paralysis in certain cases to a rheumatic inflammation
affecting either the articulations or the muscles themselves. Trichina
have been found in one or both muscles, producing a paresis. Syphilis,
central or laryngeal, may account for a number of cases. When the loss
of power is due to local syphilitic trouble, there is, however, usually
a recognizable change in structure, something more than a simple paralysis.
It would seem strange to find a rheumatism so localized as this
hypothesis implies. Mackenzie has met with a case in which the
paralysis was unilateral and toxic, due to lead-poisoning. He thinks
there may be other cases of similar origin, and suggests arsenic also
as a possible cause. In his case he compares this paralysis of the
lateral crico-arytenoids to the loss of power in the extensors of the
forearm in well-marked cases of lead-poisoning. The affection was
limited to the adductor muscles. Seifert and Lublinsk in Berlin. klin.
Woch. also report cases. The adductors only were affected. The very
few cases in which this form of paralysis has been carefully noted do
not supply us with the material for a more exact opinion as to the
causes of the trouble.
SYMPTOMS.—The symptoms of this form of paralysis are for the most part
such as depend upon the mechanical relation of the parts. There is no
pain; there is no dyspnoea, except in cases in which there is a catarrh
of the larynx; there is no cough. There is however, complete aphonia.
There may be an exception to this statement when the paralysis is
unilateral. It is possible that where one cord comes to the median
line, and the other is affected only with paresis, in the course of
time the cord on the sound side may pass beyond the median line and
render phonation possible. In such cases, however, the voice is not
normal in quality.
Upon inspection with the laryngoscope the glottis is seen to be widely
open. The cords approximate the lateral walls of the supraglottic
space. Upon an effort to phonate the cords remain immobile. If the
constrictors are unaffected, the act of laughing is still possible,
from the fact that a partial occlusion of the lumen of the tube is
accomplished by the action of the borders of the laryngeal opening and
by the approximation of the false cords. In case of unilateral
paralysis of course there is motion of the cord upon the sound side,
leaving one-half of the glottis open. It has been stated by Von
Ziemssen that there is sometimes an anæmic condition of the mucous
surfaces. When present, this is probably only a contingent phenomenon,
the evidence of a slight alteration of the circulation in the tissues.
It is true that the permanent immobility of the parts ought to diminish
the activity of the circulation in the muscles, and perhaps also in the
neighboring structures. On the other hand, the surfaces have been found
hyperæmic. Probably no importance should be attached to the surface
condition as a means of diagnosis.
The course, duration, and termination of this form of paralysis
must depend largely upon the cause. When the disorder depends upon a
catarrh, we may expect that the trouble will disappear, or at least be
mitigated, as the local affection is relieved. If of syphilitic or
rheumatic origin, it should disappear pari passu with the primary
disease. So far as we know, there is no danger to life, the loss of
voice being the only important result.
The DIAGNOSIS is easy. The laryngoscope will enable the observer to
differentiate it from all other affections by which the voice is
destroyed. It is possible that disease affecting the articulation of
the arytenoids, and thus preventing their movement, might give rise to
a doubt. A careful examination in such cases will, however, generally
reveal the fact of tumefaction or other evidence of structural change.
Closely allied to the paralyses which we have just been considering are
the affections of the glottis of hysterical origin.
If the cases of true paralysis of the lateral crico-arytenoid muscles
are rare, it is equally true that a partial arrest of the action of
these muscles, and temporary for the most part in duration, is not
unfrequently met with. The etiology of these cases seems to be much
more within our knowledge than that of those of which we have just been
speaking; at least the conditions under which they occur are much
better known. For the most part they occur in females. They are met
with in patients of nervous temperament, generally adults, though I
have seen one case in which the subject was still undeveloped. There
are very generally the evidences of hysteria in some of its various
manifestations. We may therefore assume that the disease is functional
in its nature and that it is reflex in origin. It has been said that,
as it is not dependent upon any disease of the muscles or nerves of the
larynx, so far as we know, it should not be classed among the
paralyses. For the same reason it should not be considered as a
neurosis of the organ, but of the system in general. But it is a
neurosis of the larynx, and therefore ought to be placed here. In
addition to this, it is in its symptoms identical with or very similar
to the true paralyses dependent upon alteration of the nerves or of the
muscles of the part.
The etiology of the affection has already been suggested in the
definition. A disturbance of the functions of the uterus, or possibly
of other portions of the nervous system, may be so reflected as to
materially interfere with the action of the muscles of the larynx. It
is possible that the affection may occur in males, as other troubles
called hysterical sometimes do. That the uterus is not always the
source of the reflex disturbance is certain. I have very recently seen
a case in which there was unquestionably an intermittent partial
paralysis of the adductors of the muscles in an adult man. It seemed to
be dependent upon the condition of the stomach. Whenever there was
flatulence or an accumulation of gases in the stomach, the voice became
husky, requiring great effort and expenditure of air in phonation, and
then extinct. Examination with the laryngoscope showed the cords in the
condition of adduction. In the effort to speak there was a very slight
approximation of the vocal bands, but not enough to admit of their
vibration. With the recovery from the disorder of the stomach this
condition disappeared. I have seen one other case similar in character.
I think we may therefore assume that the trouble can be produced by any
affection which creates a disturbance of the pneumogastrics, and which
by reflex action interferes with the proper functions of the spinal accessory.
The disease is always bilateral. Its advent is generally sudden. The
symptoms are first and almost solely loss of voice. The aphonia may
from the beginning be persistent, or there may be intervals when the
patient speaks with ease. In some cases the patient is able to whisper;
in others this power is also lost: in the effort to phonate there is
absolutely no sound. There is no pain, but there is often cough:
this cough is hoarse, like that which has been described under a
previous heading. The general health is in some cases apparently
perfect, but in a majority of instances there will be found some
disturbance of the viscera of the abdomen. Perhaps in all cases this is
true, but so slight that we are obliged to look carefully in order to
find it. Upon inspection with the laryngoscope the cords are seen to be
separated, but not so widely as in complete paralysis of the adductors
from other causes. There is no marked morbid condition of the mucous
surfaces. The secretions are not affected. It is possible that there
may be at the same time a partial paralysis of the pharyngeal muscles,
so that there is also dysphagia. In a few instances there is a
paræsthesia of the parts above. The dysphonia or aphonia is then
associated with a feeling as though there was a foreign body in the
throat. In efforts at phonation the cords usually move slightly toward
the median line, but not enough to enter into vibration. When this
condition of things is observed, and there is no other cause for the
explanation of the loss of voice, we may with safety assume that we
have to do with an hysterical paralysis of the adductors.
The duration of this form of motor disturbance is uncertain. It may
terminate suddenly after a short duration or it may continue
indefinitely. It is a cause neither of dyspnoea nor asphyxia. It always
ends finally in recovery. This statement is possibly subject to an
exception in cases in which there are other diseases present and when
these diseases are of themselves dangerous to life.
The pathology and morbid anatomy are dependent upon the length of time
during which the muscles have been in a state of inaction. It is
possible that the muscles may degenerate or lose their power to act
with the normal vigor, or there may be a simple atrophy of the muscles,
as in a case reported by Mackenzie. So far as I know, this alteration
of the muscles is very seldom found in hysterical paralysis. When
degeneration or atrophy does exist, it is probably a result, and not a
cause, of the paralysis. So far as we know, there is no antecedent
change in the larynx. This must of necessity be the case, since the
disease is reflex, and not primarily in the organ of speech. Why the
morbid influences are manifested in this organ to the exclusion of
others we do not know. In fact, we do not know that this is the case.
So far as we can judge from the records of similar cases found in the
literature of the subject, we may safely believe that there is in
nearly all of the patients some other disorders of motility, but the
derangements of speech are so striking that these have masked all minor troubles.
The intimate relation between the organs of expression, of which speech
is one of the most important, finds in these cases a striking
illustration. The quality of the voice is modified by emotion. The
evident relation of the generative functions to this psychical state is
well known. This fact explains the association of these troubles so
frequently encountered in the study of the morbid conditions of the
larynx. It is true that the disturbance is not always limited to the
phonators, but it is nevertheless more frequently met with in these
muscles than in the muscles of respiration. Emotion and the expression
of emotion go together. Their morbid conditions are therefore associated.
Paralysis of the Arytenoideus—Central Adductor.
The function of this muscle is to approximate the arytenoid cartilages.
Its paralysis leaves the posterior borders of the cartilages separated,
even though the vocal processes are by the action of the lateral
crico-arytenoids made to approach the median line. There is left a
triangular opening at the base of the cartilages, through which the air
escapes in the act of speaking. This, the
cartilaginous portion of
the glottis, remains patent even though the anterior three-fourths of
the space be closed. The result is generally, but not always, a loss of
speech. The air whistles through this opening, but phonation is
difficult or absent. The causes are to be sought in the derangements
resulting in the loss of power of the other muscles. Upon examination
with the laryngoscope the triangular opening is readily seen. The
ligamentous portion of the glottis is seen to close in the effort to
speak, while the cartilaginous portion is widely open. There is no
other morbid condition necessarily present. The trouble is frequently
associated with paralysis of the adductors of the two sides—that is,
the lateral crico-arytenoids. In these cases there is complete
separation of the cords throughout the whole length.
The DIAGNOSIS is easy except in instances where there is ankylosis of
the articulation of the cartilages. Even in these cases a careful study
of the parts, as revealed by the mirror, will enable the observer in
most instances to recognize evidence of structural disease on the walls
of the larynx. There will also be a history of some antecedent
affection, such as syphilis or tuberculosis, or possibly arthritis. The
course and termination of this form of paralysis depend largely upon
the etiology in any given case.
Paralysis of the Tensors of the Vocal Cords.
It will be remembered that these are in two groups, the internal and external.
The internal are the thyro-arytenoids. While their function is in part
still a matter of discussion, it is very generally conceded that they
have to do with the form and tension of the cords. Their paralysis
produces a very marked derangement of the functions of the larynx as
the organ of speech. They act ordinarily along with the crico-thyroids,
but from the fact of their separate innervation it would seem very
probable that they should be the seat of special functional
derangements. In fact, it is true that their paralysis in a limited
number of cases is found to be quite independent of any disturbances of
the external tensors.
ETIOLOGY.—In addition to the general causes of laryngeal paralysis,
the use of the voice in an unnatural or too high a key or the too
long-continued use of the organ may result in a temporary or even
permanent impairment of the power of these muscles. Their exposure to
the causes of inflammation, lying as they do so near the surface of the
mucous membranes, subjects them to the morbid influences of the
catarrhal troubles to which the glottis is liable. They are probably
more frequently affected than the literature of the subject would lead
us to suppose, as in many cases the disease is temporary.
SYMPTOMS.—These consist mainly in the alteration of the voice. It is
hoarse, the register is lower, the quality is uneven. Occasionally a
note is, if not lost, uttered with difficulty; some letters, such as
the aspirates, requiring the careful adjustment of the glottis, are
articulated with great uncertainty. There is what has been called a
rattling of the voice. It is quite impossible to sing or to speak long
in a high key; even prolonged ordinary conversation gives rise to
fatigue, for the reason that there is so great a waste of air in the
effort. The pressure upon the under surface of the cords in their
relaxed condition forces its way upward and through the glottis without
throwing them into normal vibration.
DIAGNOSIS.—The laryngeal mirror reveals the glottis only partly
closed. There is an oblong opening extending from the thyroids to the
base of the arytenoid cartilages. The vocal processes even are not
brought to the median line, but are so far apart as to leave a
noticeable slit between them. It seems from this fact that these
muscles are therefore the aids of the lateral
crico-arytenoids in
the rotation of the cartilages on their bases. In the effort at
phonation the cords are seen to move with difficulty. The disease may
be unilateral or bilateral.
This form of paralysis in course and termination does not in any
essential respect differ from other paralyses of the larynx. The
duration is therefore very uncertain, and will depend largely upon the
cause of the affection.
Paralysis of the External Tensors of the Cords.
This is a rare disease, but is present in complete paralysis of the
superior laryngeal nerve. It is then associated with anæsthesia of the
superior portion of the glottis, as well as paresis of the depressors
of the epiglottis, and generally of the constrictors of the vestibule
of the larynx.
ETIOLOGY.—It may be the result of injury to the external branch of the
superior laryngeal in its distribution to the muscles. It may be caused
by diphtheria. It is possible that the motor fibres of the superior
laryngeal nerve may be alone involved, while the sensitive portion is
still normal. Cases of partial paralysis are recorded by Von Ziemssen,
Gerhardt, and others.
The SYMPTOMS are such as we should expect in diminished tension of the
vocal bands: lowering of the pitch of the voice, with inability to
reach the higher notes. There ought to be, therefore, hoarseness. Acute
paralysis of this muscle has been known to produce aphonia (Ramon).
DIAGNOSIS.—It is said that this form of paralysis gives rise to a
well-recognized condition which may be seen in the laryngeal mirror.
The cords are described as wavy, irregular in their relation to each
other, like the position of two pieces of ribbon, which, having an
attachment at their extremities near to each other, are allowed to fall
into folds. This condition, if ever present, is, I am convinced, very
rare. It is probable that the descriptions have been given to
correspond with what ought to be seen, rather than what is actually
seen, in the mirror. There is said to be a slight depression of the
vocal processes in the act of inspiration, and a corresponding
elevation of them in the act of expiration and phonation. The
diminished tension should produce this change in position. The disease
may also be recognized by placing the finger upon the edge of the
crico-thyroid muscle during the effort to speak. The muscle acts so
strongly in the healthy condition that it may be easily felt; in
paralysis this contraction is wanting.
The course and duration of the disease must depend upon the cause and
complications. When the muscles suffer in common with the sensory
apparatus supplied by the superior laryngeal nerve, as in the case of
diphtheria, there is reason to expect that it will disappear with the
other morbid phenomena.
Paralysis of the Posterior Crico-Arytenoids.
The functions of these muscles render any loss of their power as
glottis-openers a matter of importance. It will be remembered that they
are so situated that they not only rotate the arytenoids, turning the
vocal processes away from each other, but they also serve to fix the
cartilages, giving them a firm support as points of attachment for the
vocal cords. The outer fibres tend also to draw the body of the
arytenoids away from each other, as well as to fix them in a
postero-lateral position. They are, more than any other of the muscles
of the larynx, organs of respiration. They are also in constant action:
with each inspiration they contract, and during expiration they
fall into rest. In this respect they resemble the other muscles of
respiration and the central organ of the circulation. In some respects
they also resemble the muscles of the heart in the degenerative changes
to which they are subject. Their antagonists are the lateral
crico-arytenoids. When both sets of muscles are paralyzed, the glottis
is in what is known as the cadaveric condition; that is, the vocal
cords are neither widely separated nor parallel to each other. There is
an opening of a triangular shape as in the act of easy inspiration, not
sufficiently approximated to admit of speech, but sufficiently open to
admit of free inspiration. With this understanding of the physiology of
the parts, we can readily appreciate the results of the loss of power
of these muscles. As stated by Bosworth, the especial danger is in the
integrity of the adductors, tending for the want of antagonism to keep
the glottis closed. Of all the muscles of the larynx, these are
therefore the most important so far as life is concerned.
The disease is progressive (Lefferts, Semon, Bosworth).
The first symptom which attracts attention is generally inspiratory
dyspnoea while taking active exercise. The difficulty continues to
increase till there is constant difficulty in the act of inspiration,
usually with spasm. The dyspnoea is more marked during sleep than when
awake. Death may occur at this period of the disease before the gravity
of the trouble has been recognized. As a rule, tracheotomy will be
required to prolong life, after which the dangers to the patient are passed.
The ETIOLOGY of this form of paralysis presents some peculiar problems.
In all paralyses of the individual muscles we are obliged to invoke
nerve-changes in special nerve-cells in the centres from which the
individual nerves have their origin—changes along the course of the
nerves; or, on the other hand, some myopathic change in the muscles
themselves. In the muscles now under consideration we have a special
function—namely, respiration—involved. The disorder is usually
limited to these muscles alone. If it becomes general, it commences
here. The phonators not being involved, it is probable that in a part
of the cases reported the essential cause of the paralysis must be
ascribed to disease in a centre in the brain, or at least along the
course of the nerve near its origin. Other cases are evidently due to
pressure on the pneumogastrics or recurrents. This view has been
proposed by Bosworth. Von Ziemssen and others have thought that
syphilis enters very largely into the pathology of this group of cases.
There has been noted, as confirmatory of this proposition, that other
symptoms of central disease have been in a few instances observed.
Diseases affecting the recurrents have been known to affect these
muscles alone: Ingals reports cases. On the other hand, it is quite
certain that in a large majority of the cases recorded there has been
no satisfactory cause assigned. In nearly all of the post-mortems there
has been found a degeneration of the muscles. This is as we should
expect to find it where the structures have been for a considerable
time in a state of inaction. The histological change may possibly be in
any case only the result of the paralysis, and not the cause of it. In
a few instances there has been discovered a degeneration of the
nerve-trunks by which the parts are supplied. As to the causes by which
the muscles may become affected, we can imagine that the exposed
position suggested by Mackenzie renders them peculiarly liable to
mechanical injuries from hard substances forced down the oesophagus.
They are subjected to changes of temperature produced by hot and cold
drinks and food. Their relation to the seat of local inflammation of a
specific as well as of a non-specific character renders them liable to
become involved in morbid processes. The fact that the disease
occasionally occurs after diphtheria, as I have in two instances
demonstrated, gives additional weight to this hypothesis. The fact
probably is that there are several varieties of the affection. The want
of more accurate information as to the previous history, as well
as to the immediate antecedents of the attack, renders it impossible as
yet to differentiate the cases due to one or other of these causes. For
the present, then, we may conclude that paralysis of these muscles may
depend upon either disease of the centres, disease along the track of
the nerves, pneumogastric or recurrent, or to disease of the peripheral
branches or fibrils, or to disease of the muscles themselves.
SYMPTOMS.—These are at first so slight that the trouble is usually not
recognized till it has reached such a stage that the act of inspiration
is either attended with fatigue or there is stridor which annoys the
patient or alarms his friends. Soon afterward there begins to be a
dyspnoea, a difficulty in breathing, especially during any active
exertion and during sleep. The voice in the mean time remains normal.
Expiration is free. The general health is usually undisturbed. There
may be a catarrhal affection of the mucous surfaces, but if so it is
quite accidental. Spasm supervenes. There is at times great difficulty
of breathing, and, finally, the effort becomes so great that the
patient becomes alarmed. Upon examination with the laryngoscope the
vocal cords are seen in close proximity to each other even during the
inspiratory effort. In fact, they are, by the pressure of the air upon
their upper surfaces, brought closer together during inspiration than
during expiration. They seem to act as valves which are closed by the
weight of the atmosphere upon their wide, flat upper surfaces, pressing
them against each other. Hence the inspiratory stridor and dyspnoea.
The act of expiration is a passive one in health, and in this condition
the air is easily forced out by pressing the cords away. The order of
the movements of the cords is therefore changed—in the normal
condition wide in inspiration, narrow in expiration; in this disease
narrow in inspiration, and while not wide, at least wider, in
expiration than in inspiration. In other respects the parts are normal.
There is nothing to suggest the trouble except the closure of the
glottis during inspiration.
The course and duration of the disease are in a large majority of cases
chronic. Once established, it tends to persist. The cases of
diphtheritic origin should be excepted from this statement. In those
forms in which the trouble is entirely in the muscles of the part life
may, so far as we know, be continued indefinitely. Where the trouble is
central it is probable that the cause has a tendency to involve other
parts of the brain, and in this way to lead to other, and possibly
dangerous, complications. Of this, however, we know but little. The
paralysis is not directly the cause of death, except as it closes the
glottis. The dangers are therefore mechanical. When the patient has
once been placed in a condition of safety by the operation of
tracheotomy the local paralysis no longer endangers life.
Mackenzie, Von Ziemssen, Cohen, and in fact almost all writers upon the
diseases of the larynx cite and publish cases by the way of
illustration of the symptoms, course, and termination of this class of
troubles. They are now so numerous that it would seem to be hardly
necessary to do more than to give the conclusions which the recorded
instances suggest. Fortunately, this form of laryngeal disease is rare,
and when present it is easily recognized. The treatment is clearly
indicated. In all cases in which the inspiratory difficulty is marked
tracheotomy should be performed, even though suffocation does not seem
to be imminent. The treatment for the radical cure of the disease must
be in the main the same as that required in other forms of laryngeal paralysis.
TREATMENT OF PARALYSIS OF THE LARYNX.—The grouping of these disorders
for the purpose of description has, for the reasons already given, been
based largely upon symptoms. For the purpose of treatment we may
properly divide them with reference to their causes. With these in
view, we have, first, those cases in which the cause of the affection
is within the cranium—central disease; second, those in which the
loss of power is the result of disease or pressure along the course of
the nerves outside the cranium and before reaching the larynx; third,
those in which there is disease of the structure of the larynx itself,
nerves or muscles; fourth, those in which the cause is to be found in
some distant part—reflex paralysis; fifth, those of toxic origin. This
last includes paralysis after typhoid fever, diphtheria, etc., as well
as those produced by lead, arsenic, mercury, and possibly copper and
other toxic agents.
Diseases of the base of the brain or medulla are for the most part not
amenable to treatment. They are generally organic and progressive. The
exception to this statement, or at least the most notable exception, is
syphilis. The influence of this disorder in the production of paralysis
of central origin must be admitted, but it seems to have been by many
authorities overstated. The coincidence of paralysis with an earlier
infection does not by any means justify the inference that the one
disease has been produced by the other. When, however, there is reason
to think that this relation may exist, antisyphilitics should be
administered. In a few cases this treatment has been followed by marked
improvement of the laryngeal disease.
Cases dependent upon malignant growths within the cranium are
absolutely beyond the reach of treatment. Paralysis dependent upon bony
tumors, even though they are benign in character, are also for the most
part beyond the reach of surgical interference. If the paralysis is
complete—that is, if all the muscles are involved—there are no
indications for any operative procedure. If, however, only the nerves
that supply the posterior crico-arytenoids are involved, as
occasionally happens, tracheotomy should be resorted to even though the
dyspnoea is not urgent. This operation places the patient in a
condition of temporary safety, and gives time to resort to other means
if the indications for their use can be found.
The second group of cases includes all those in which the cause of the
paralysis is due to the presence of disease of the nerve-trunks, or to
pressure upon the nerves between their emergence from the cranium and
their terminations in the muscles of the larynx. Malignant growths and
benign tumors situated along the tract of the nerves, and pinching
them, are readily recognized, and when not contraindicated by other
facts they should be removed. Enlargement of the thyroid gland may in
some cases press upon the nerve and cause paralysis. This is
occasionally relieved by appropriate treatment directed to it. Among
those means which have occasionally been found efficacious for this
purpose iodine or some of its compounds, and especially electricity in
the form of galvanism, seem to be entitled to the most confidence. For
paralysis dependent upon cicatricial pinching of the recurrent
nerve-trunks relief may possibly be obtained by dissecting out the
bands by which the nerves are compressed. This is hardly indicated for
the partial derangements which do not endanger life, as in unilateral
paralysis of the recurrent. Where the trunk of the nerve is entirely
obliterated nothing can be done, and in many cases of injuries along
the trunk of the recurrent it will be impossible to know that the nerve
has not been destroyed in the mechanical lesion.
Paralysis caused by pressure upon the intra-thoracic portion of nerve
is beyond the reach of surgical interference. When this is aneurism,
disease of the apex of the lung, or pleuritis, as may possibly happen,
the paralysis or paresis must of course have a history coeval with the
thoracic disease. The causes themselves are unfortunately persistent
and tend to terminate in death; the paralyses are therefore persistent
and beyond the reach of medical or surgical relief. In cases where the
posterior crico-arytenoids are especially involved, tracheotomy, as in
the same condition from intra-cranial disease, should be performed. It
is certainly true that there may be a morbid condition of one or
both of the pneumogastrics or recurrent nerves without macroscopic
changes in their structure; in such cases the use of the faradic
current together with general tonics is indicated.
The third group is made up of those cases in which there is disease of
the nerves or muscles of the larynx itself. It seems to be true that in
most of these patients there is a derangement of the general nutrition;
but this is not all: there is also a special morbid condition of these
special structures. For degeneration of the muscles of the larynx there
is probably no remedy; for atrophy there may be something done by
different methods of exercising the muscles. The use of electricity
when the muscles are still responsive to the current should be
attempted. Regular applications by which they are thrown into action
may result in the improvement of their nutrition. The use of them so
far as they are phonators, without carrying it to the extent of
producing fatigue, is also indicated. In addition to these local
measures, tonics for the purpose of improving the general condition may
be administered. Strychnia, with the purpose of stimulating the
centres, will also be found in some cases useful. When the disease is
partial, as in the case of the posterior crico-arytenoids, such
operative measures as have been already indicated must be resorted to.
The purpose is to prolong life, even though we cannot cure the disease.
The fourth group, the paralyses of reflex origin, are generally within
the reach of treatment; at least, they usually recover. They depend for
the most part, as will be remembered, upon some disorder of distant
organs. There is primarily no disease of the larynx, and not
necessarily even a secondary disorder of its structures. It is true
that long inaction may result in atrophy of the muscular structure, but
this is, I am convinced, a rare exception to the rule that in
hysterical paralysis there is maintained a complete integrity of the
muscles of the organ, even though the parts have been for years in a
state of inaction. For some reason, the nutrition is maintained much
better than in paralysis from other cases. The trophic nerves are
evidently not involved. The treatment should be both local and general.
It should be directed to the larynx and to the distant part upon which
the motor disorder of the larynx depends. So far as the larynx is
concerned, we know of nothing better than electricity. The faradic
current, by which the muscles are stimulated and the nervous energies
awakened, seems to be most useful. The method of applying electricity
to the larynx may be varied according to the nature of the case and the
age of the patient. In young children the current should be directed
through the walls of the larynx from side to side or from before
backward. It should be repeated every day if possible. In adults the
current may with advantage be passed through the larynx from within
outward or from one side to the other. This may be accomplished by the
use of Mackenzie's laryngeal electrode. The instrument is either single
or double. Armed with a sponge and bent to the proper curve, one pole
is introduced into the larynx, the other placed upon the neck, and then
by pressing a spring the circuit is closed, permitting the current to
pass through the parts from one pole to the other. In using the
instrument with two electrodes, as in paralysis of the arytenoids and
constrictors, the instrument with two branches, each armed with a
sponge, and to which the two poles are attached, is introduced with one
branch in one of the depressions in one side of the larynx, and the
other on the opposite side in the corresponding depression. The circuit
is now closed as before, with the muscles between the two poles as part
of the circuit. The electrodes may be carried down into the organ and
the stimulus applied directly to the vocal bands. In some cases the
first shock is followed by distinct phonation; in others repeated
applications are necessary; while in still others all efforts of this
kind fail entirely. Both the galvanic and the faradic current may be
used. When the object is to stimulate the dormant energies of the
nerves or muscles, the faradic is probably the more useful; if it is
desired to modify the nutrition of the parts, the galvanic is
preferable. The strength of the current should be carefully tried upon
the surface of the hand of the operator before introducing it into the
larynx. The shock to the nervous system from the dread of the operation
has sometimes resulted in the recovery of the voice before anything has
been done. The morbid spell is broken and the patient speaks. This is
true in spasm even, as shown in a case reported by Lefferts, where it
was thought that tracheotomy was necessary for the purpose of saving
life. The patient, frightened at the thought of the operation,
recovered, and respiration became easy. There was no reason to think
that the case was one of simulation.
For the general condition, which is usually one of asthenia,
nerve-stimulants are indicated, and the bitter tonics, with iron and
strychnia, good generous diet, outdoor exercise, change of
surroundings, travel, moral impressions, in short everything that tends
to promote general good health,—these are among the most important
requirements. If there is local uterine trouble, this of course
requires attention, or if there is any other derangement which serves
as the point of departure for the morbid phenomena, this will also
demand consideration. In fact, no organ suffers alone. There is a
community of function and there is a community of suffering. This
subject has been perhaps sufficiently discussed in the consideration of
the treatment of hysterical disorders of sensation and of spasm, to
which the reader is referred.
The fifth group comprises paralyses toxic in their origin. When the
cause is typhoid fever or diphtheria, we may confidently expect the
paralysis to disappear with the other manifestations of adynamia. Time
and tonics, with attention to diet, and in the more protracted cases
electricity, will generally be all that is required. Cases depending
upon the toxic effects of lead or arsenic demand the treatment
appropriate for the other manifestations of these forms of paralyses.
The iodide of potassium internally, with attention to the general
health, and especially to the functions of the excreting organs,
constitute the most important measures. In addition, strychnia may be
administered, and the faradic current applied through the larynx. It is
certainly possible that laryngeal paralysis may be produced by arsenic,
as shown in the case reported by Mackenzie, and probably also by copper
or mercury. Such cases, however, must be exceedingly rare. The
potassium iodide, as suggested for lead-paralysis, may be resorted to
in case mercury is supposed to be the cause. For arsenic- and
copper-poisoning the reader is referred to articles upon these subjects
elsewhere. Cases in which there is evidence of a local lesion due to
syphilitic intoxication should receive both local and general treatment.
PATHOLOGY.—Catarrhal inflammations of the mucous membrane and the
submucous tissue of the larynx are of frequent occurrence. They are
either general or local; that is, confined to the epiglottis or the
vocal cords, etc. The affected parts are red (only less so where the
elastic fibres are developed to an unusual degree and capable of
compressing the dilating capillaries) and more or less tumefied.
Sometimes small hemorrhages occur. The secretion is either changed in
character or in quantity. It is either mucous or purulent, or (mainly
in passive congestions produced by interrupted venous circulation)
serous. The epithelium is either thrown off or accumulated in some
spots, particularly on the vocal cords, so as to form whitish
conglomerates which may become the abode of schizomycetæ. The
muciparous follicles are enlarged and dilated; to this condition is due
the granular form of laryngitis, with the nodulated condition of the
epiglottis or the fossæ Morgagni or the inferior vocal cords.1
1 Ziegler, Pathol. Anat.
When the catarrhal process is of longer duration, the capillaries and
small veins become permanently enlarged; round cells are deposited
between the epithelium and cellular tissue; the cellular tissue becomes
hypertrophied; papillary elevations are formed on the vocal cords. The
disintegration of the epithelium and the bursting of the tumefied
muciparous glands lead to the formation of erosions and ulcerations;
the chronic swelling and hypernutrition of the muciparous follicles to
their destruction by cicatrization or simple induration; and to atrophy
of the mucous membrane.
Many of the specific causes of inflammation of the larynx exhibit no
peculiar alterations of their own. Scarlatina, measles, and
exanthematic typhus are complicated with either a catarrhal (in most
cases) or a diphtheritic laryngitis. Variola, however, has a peculiar
form of its own, with red, pointed, whitish stains or nodules,
consisting of a cellular infiltration or of a deposit upon or into the
upper layers of the mucous membrane, composed of necrotic epithelia and
pus-corpuscles or of coherent membrane. Hemorrhages or abscesses are
but rare, and chondritis seldom results from it. Even syphilis has not
always changes which are characteristic. The laryngitis accompanying it
is often but catarrhal, without anything pathognomonic about it. But
whitish papules consisting of granulation-tissue (plaques muqueuses),
gummata often changing into sinuous ulcerations, particularly on the
epiglottis and posterior wall of the larynx, also perichondritis with
loss of cartilage and deep cicatrization, such as are not found in
either carcinosis or tuberculosis of the larynx, are frequently met
with. Typhoid fever shows different forms of laryngitis, from the
catarrhal to the ulcerous. Epithelium is thrown off at an early period
of the disease; erosions and ecchymoses follow; rhagades on
the margins of the epiglottis, and a deposit on the anterior wall of
the larynx and the vocal cords, consisting of epithelium and round
cells, are frequent. That they should be mixed with micrococci and
bacteria is self-understood. Not so that these bacteria are to be
considered as the cause of the disintegration which is taking place,
the less so as no specific typhoid bacterium has been demonstrated, and
several varieties of them are found both in the mouth and in these
ulcerations. These changes are apt to terminate in ulceration of the
epiglottis and false vocal cords; these will extend in different
directions, and to the deeper tissue down to the cartilage.
In tuberculosis, laryngitis is a frequent occurrence. In most cases it
is secondary to the pulmonary affection, and due to the direct
influence of the contagious sputum—according to Heinze, however, not
to contagion, but to the influence of the infected blood. In other
cases it appears to develop spontaneously, before any pulmonary
affection is diagnosticated, and may then be due to some poison
circulating in either blood or lymph. Tubercular laryngitis, according
to Rindfleisch, commences in the excretory ducts of the muciparous
glands. That this is so in a great many cases is undoubted. The first
changes visible are small cellular subepithelial infiltrations or real
subepithelial tubercles, which, while growing, undergo gaseous
degenerations and ulcerate. These ulcerations are either flat and small
or deeper with an infiltrated edge, and are apt to terminate in
secondary nodulated infiltrations and abscesses. Large tumors are not
met with, but oedema and phlegmonous inflammations are by no means rare.
ETIOLOGY.—The predisposition varies according to individuals, ages,
and seasons. Some mucous membranes appear to be more sensitive than
others. The hereditary transmission of peculiarities of structure of
all or some tissues or organs is apparent, in the case of laryngitis,
in the fact that many children in the same family or the children of
parents who were sufferers themselves are affected. Children are more
liable than adults, infants more than children: 20 per cent. of all the
cases are met with under a year, 25 from the first to the second, 15
from the second to the third. Not many occur after the twelfth year.
The narrowness of the infant larynx and the looseness of its mucous
membrane afford full play to injurious influences, such as dust, cold
and moist air, changing temperatures, hot vapors and beverages. Colds,
though their nature and effects can hardly be said to be understood,
are certainly amongst the main causes. Perspiring surfaces afford
frequent opportunities. One of the principal causes is insufficient
clothing—more amongst the well-to-do than amongst the poor. The latter
have this blessing in their misfortune, that they are protected
uniformly if at all, and have their skins hardened by exposure. The
bare necks and chests, the exposed knees, the low stockings and thin
shoes of the children of the rich, old and young, are just as many
inlets of laryngeal catarrh, inflammatory disease, and phthisis.
Persons suffering from nasal catarrh or pharyngeal catarrh are liable
to have laryngitis. Thus, not only rachitis, with its influence on
lymphatic glands and the neighboring mucous membranes, but also acute
infectious diseases, such as whooping cough, measles, influenza,
erysipelas, hay fever, tuberculosis, syphilis, typhoid fever, and
variola, are as many causes of laryngitis. That over-exertion of the
voice should produce laryngitis seems probable, but experience does not
teach that those babies who cry most are most subject to laryngeal catarrh.
SYMPTOMS.—Acute laryngitis is a frequent disease, and has always been.
Still, in 1769, Millar mistook it for a sensitive neurosis, considering
it as identical with spasm of the glottis, and recommended
antispasmodic treatment. Guersant understood its nature better. He
first (1829) used the names false croup and stridulous laryngitis.
Acute laryngitis is attended with but little fever in the adult, but
with a high elevation of temperature in the young. In all, it
yields a number of symptoms, part of which are uncomfortable only;
others are liable to become dangerous.
Seldom without any catarrhal premonitory symptoms of other parts of the
respiratory tract, sometimes, however, without any, there is a burning,
tickling, irritating sensation in the larynx—a sense of soreness in it
and the lower portion of the pharynx. Sometimes these sensations amount
to actual pain, to difficulty of deglutition, and to the sensation of
the presence of a foreign body. Speaking, coughing, cold air, increase
the discomfort and pain. Hoarseness, sometimes increasing into aphonia,
follows soon after, is seldom simultaneous with, the first appearance
of cough, but lasts longer than the latter, which is, according to the
severity of the case or the stage of the disease, changing between
loose and dry, hoarse and barking. Inspiration is apt to become
impeded, mainly in infants and children. In these it is often sibilant.
It is followed by a reflex paroxysm of cough, with interrupted and
brief expirations, during which the forcible compression of the thorax
may result in cyanosis. The principal attacks are met with at night
amongst children. Quite suddenly they wake up with a dry, barking
cough, interrupted by considerable dyspnoea, which is great enough
sometimes to give rise to much anxiety. They toss about or cling to a
solid body, raise themselves on their knees, breathe with great
difficulty, exhibit cyanosis in its different hues, perspire very
freely, and yield all the symptoms of the strangulating attacks of
membranous croup, its over-exertion of the sterno-cleido-mastoid
muscles and supraclavicular and diaphragmatic recessions not excepted.
These attacks occur but rarely during the day; on the contrary,
well-marked remissions are quite common in the morning. Their
occurrence during the night is best explained by the facility with
which mucus will enter the larynx from above during the reclining
posture, the increasing dryness of the pharynx during sleep, perhaps
also the nervous influence depending upon the relative diminution of
oxygen and increase of carbonic acid in the respiratory centre, leading
to spasmodic contractions.
Some of these grave attacks of sudden dyspnoea are explained by the
participation of the submucous tissue in the morbid process. When that
occurs, adults also, who as a rule do not suffer from dyspnoea in
laryngeal catarrh, are badly affected. The symptoms are rigor, high
temperature, pain, hoarseness or aphonia, a barking cough, labored
expectoration—which is sometimes bloody—dyspnoea, orthopnoea,
cyanosis. In some cases, to which the name of laryngitis gravis or
acutissima has been given, the symptoms grow urgent to such a degree
that tracheotomy alone is capable of saving life.
Otherwise, the severity of the symptoms does not go parallel with the
local lesions. Particularly in children, hoarseness, cough, and
dyspnoea are liable to be grave, while the local hyperæmia is not
intense at all. A pharyngeal catarrh is very apt to increase the
suffering. Complications with tracheitis or bronchitis are liable to
prolong the course of the disease and to render respiration—which is
not accelerated in laryngeal catarrh—more frequent. Otherwise, the
disease runs a favorable course. Remissions of the severe attacks which
may occur in several successive nights take place in the morning.
Expectoration, which in the beginning was either absent or scanty,
becomes soon more copious and mucous; the hard, barking, loud cough
grows looser with increasing secretion. In most cases the violence of
the affection is broken in from three to five days, and the disease
runs its full course in a week or two. But hoarseness may remain behind
for some time; in rare cases aphonia has become permanent and relapses
are frequent. Not infrequently children are presented who are reported
to have had croup five or ten or more times. In some families all the
children are subject to laryngeal catarrh, and hereditary influence
cannot be doubted.
The very worst complication of laryngitis is oedema of the glottis. It
affects both the mucous membrane and the submucous tissue of the
larynx. It is met with on the inferior (posterior) surface of the
epiglottis, in the ary-epiglottic folds, and on the false (inferior)
vocal cords, the submucous tissue of which is of a very loose structure
normally. Amongst its causes—which may be various (foreign bodies in
the larynx, injuries, mechanical and chemical irritants of any kinds;
typhoid, tubercular, variolous, syphilitic ulcerations; erysipelas of
the neighborhood, inflammations of the parotids or tonsils, suppuration
in the pharynx, thyroid body, and cellular tissue of the neck)—both
catarrhal and croupous laryngitis are not at all uncommon. This is
particularly so when they are complicated with cardiac and renal
anomalies, pulmonary emphysema, and compression of the veins of the
neck by glandular swellings; also with changes in the structure of the
walls of the blood-vessels. The last-named pathological conditions are
alone capable of giving rise to chronic oedema of the larynx, which is
by no means so fatal, but still dangerous.
In glottic oedema the dyspnoea is both very great and very sudden.
First, it is inspiratory only, but soon becomes both inspiratory and
expiratory. The swelling is felt distinctly by the examining finger;
the laryngoscope is neither required nor advisable.
DIAGNOSIS.—It is by no means easy in all cases. When laryngeal
diphtheria (membranous croup) happens to be frequent, the most
experienced diagnostician will meet with occasional difficulties. The
sound of the barking, explosive, tickling cough locates its origin in
the larynx, but the affection may be very mild or very severe.
Expectoration in small children is not pathognomonic; even when it is
copious it is not brought up, but swallowed. Fibrinous expectoration
would settle the diagnosis of a croupous process. Depressing the tongue
with a spoon or spatula and producing the movements of vomiturition
often reveals the presence of a tough, viscid mucus rising from the
larynx. It renders the catarrhal nature of the laryngitis positively
clear. The frequency or volume of the pulse is of no account in
diagnosis; it is too variable. Of more importance is the temperature,
at least in children. Uncomplicated sporadic croup has no increase, or
very little; catarrhal laryngitis is mostly attended with high fever.
In very many cases this symptom has guided me safely, in spite of the
statements of the books. The stenosis of catarrhal laryngitis comes on
very suddenly, in diphtheritic laryngitis mostly slowly. In the former
it is not of long duration; remission sets in soon, and is more
complete than in membranous croup. An attack of stenosis occurs mostly
in the night, and is apt to return with the same vehemence after a fair
remission after twenty-four hours. The frequency of relapses in
catarrhal laryngitis in children who have been affected before must,
however, not prejudice in favor of the catarrhal nature of an
individual case, for not infrequently will those who have had many
attacks be taken with membranous croup some other time. In the latter
the main symptoms—viz. stenosis, hoarseness (or aphonia), and
cough—will mostly develop simultaneously and in equal proportion; the
unproportionality of these symptoms—for instance, much stenosis and
cough, but little hoarseness, or barking cough and hoarseness with
little stenosis—would speak for catarrh. The laryngoscope, when it can
be used—viz. in the adult and very docile children—reveals redness of
the mucous membrane of the pharynx and all or part of the larynx; also
tumefaction of the epiglottis or fossæ Morgagni or ary-epiglottic
folds. Sometimes the inferior part of the larynx only is affected;
Ziemssen has described a severe form under the name of hypoglottic
laryngitis. The vocal cords can be watched easily. Their proportionate
and parallel contraction is often interfered with.
Tubercular laryngitis, particularly when there is no pulmonary
tuberculosis, is not easily diagnosticated by the local changes only.
The long duration of hoarseness and fever, increasing emaciation,
and the knowledge of the presence of tuberculosis in the family are
more conclusive than local examinations can be.
PROGNOSIS.—The termination of catarrhal laryngitis in the adult is
almost always favorable. Still, relapses are frequent, and it may
become chronic, with permanent tickling of the mucous membrane and
submucous tissue. In children it is mostly favorable; still, it is
doubtful, because of the frequency of complication with, or
transmutation into, bronchitis, pneumonia, or glottic oedema, and
because of the facility with which in a prevailing epidemic the
catarrhal laryngitis becomes diphtheritic. The elevation of temperature
is not a very significant symptom in regard to prognosis. The danger
does not increase with the temperature at all. On the contrary, those
cases which set in with a high temperature will, as a rule, terminate
soon and favorably. When, however, the temperature rises again after
having gone down to the normal or nearly normal standard, complications
or extension of the catarrhal or inflammatory process must be expected.
Catarrhal secretion from the nasal mucous membrane, which was dry in
the beginning, is a favorable symptom; so is the looser and moister
character of the cough.
TREATMENT.—Whatever plays an important part in the etiology of the
disease ought to be carefully avoided. The feet must be kept warm under
all circumstances, nothing being more injurious to health in general,
and to that of the respiratory organs in particular, than cold and
moist feet. Shoes and stockings must be kept dry, the latter changed
when wet, and of slowly-conducting material. No part of the body must
be kept uncovered, and the dresses of children made the particular
object of care on the part of the family physician. Linen must not be
in immediate contact with the skin, cotton—or, still better in all
seasons, wool—being required for the undergarment. At the same time,
the hygiene of the skin requires attention. Regular washing or bathing
need not be mentioned as a requisite, as it is self-understood. What,
however, cannot be insisted upon too much is this, that the skin must
get accustomed to cold water. The whole body must be exposed once a day
to cold water—washing or bathing—and well rubbed off afterward with a
thick towel. Young infants and those who are very susceptible to colds
begin with tepid water, the temperature being lowered from day to day.
Even children of three or four years enjoy, finally, a morning bath at
sixty or sixty-five degrees F. in winter. Such as do not get easily
warmed up under the succeeding friction may mix alcohol with the water
they use for washing and sponging purposes, in the proportion of 1:5–8.
Sea-bathing also makes the skin more enduring, to such an extent that
exposure to cold air has no longer any damaging influence. In fact,
cold air without wind is easily tolerated even by those who have a
tendency to respiratory disorders, while wind and draught must be
avoided. From this point of view the change of climate sometimes
required for such as suffer from catarrhal laryngitis must be
instituted. It is not always necessary to select a very warm climate;
undoubtedly, many of the winter resorts are badly selected, for the
very reason that they are too warm. On the other hand, great elevations
are not advisable. The sudden atmospheric changes and fogs of high
mountains are injurious.
Patients suffering from catarrhal laryngitis or a tendency in that
direction must avoid all irritation of the pharynx and larynx. They
must not smoke, or talk too much or too loud. Those few clergymen who
suffer from clergymen's sore throat in consequence of speaking only
will remember that they can speak just as forcibly when speaking less
vehemently. The use of alcoholic beverages, unless greatly diluted, is
prohibited. Catarrh of the nares and pharynx must get cured. The former
will get well in most cases under the use of salt water. A tepid
solution of 1 or ½ per cent. of table-salt in water, snuffed up
copiously (a tumblerful) from the hand of an adult patient, or a
similar solution in a small quantity injected through each nostril of a
child, twice or three times a day for weeks and months in succession,
will often remove a laryngeal as well as a pharyngeal catarrh. Care
must be taken that the fluid passes the whole length of the nasal
canal. It must be applied in the fauces, and will then be ejected
through the mouth or a small portion of it swallowed. Many a severe
nasal catarrh requires no other treatment. Some chronic ones require
the use of a spray of nitrate of silver in a solution of ½–1 per cent.
every other day, or of a 2 per cent. solution of alum daily. Where both
the pharyngeal and nasal catarrh are complicated with, or kept up by,
enlarged or ulcerated tonsils, these organs must be resected. The
combination of these two measures, exsection of the tonsils and nasal
injections, has proved very beneficial in a great many cases.
The treatment of an acute case requires great care. Avoid injurious
influences. The patient must keep silent and quiet in bed. The
temperature of the room is to be about 70° F., the air moistened by
vapor, which must not be allowed to get cold before it reaches the patient.
When swelling and dyspnoea are considerable, particularly in those
grave cases attended with swelling of the submucous tissue, the
application of an ice-bladder or ice-cloths will be found beneficial
and agreeable. But the cases in which these applications are
indispensable are but few. In most of them the necessity of subduing
intense inflammation is less urgent than the advisability of increasing
the secretion of the congested larynx. For that purpose warm poultices,
but of light weight, act very favorably. Inhalation of warm vapors
either constantly or at short intervals, or of muriate of ammonium or
spirits of turpentine, will prove beneficial. The latter is evaporated
from the surface of boiling water, on which a small quantity, from a
teaspoonful to a tablespoonful, may be poured every one or two hours.
The hydrochlorate of ammonium is evaporated, 10 or 20 grains (1.0
gramme), every one or two hours by heating it on a hot stove or
otherwise. The white cloud penetrates the air of the whole room, and,
while not uncomfortable to the well, serves a good purpose in
liquefying the viscid and tough secretion of the mucous membrane. The
internal administration of liquefying and resolvent remedies may
properly accompany the external applications and inhalations. Amongst
them I count the alkalies, mainly bicarbonate and chlorate of potassium
or sodium and the hydrochlorate of ammonium. A child of two years will
take daily a scruple (gramme 1.0–1.5). The iodide of potassium will
also have a good effect and counteract many a predisposition to
chronicity. A child may take from 8 to 15 grains a day (gramme
0.5–1.0). Hydrochlorate of apomorphine, gr.
1/50–1/30 (0.001–0.002),
dissolved in water, a dose to be given every two hours or every hour,
is quite sufficient to act as a fair expectorant without being enough
to produce emesis. Antimonii et potassii tartras has been used more
extensively in former times than at present. An adult would take gr.
1/20–1/15
every two hours. Children ought to be spared the drug, as it
is depressing, produces unnecessary vomiting now and then, even in
small doses, and, what is still worse, diarrhoea. The other antimonial
preparations, such as kermes mineral and the oxysulphuret of antimony,
are less depressing and less purging, but also less effective; and
there are but few cases where a good substitute could not be found. For
the purpose of increasing secretion the hydrochlorate of pilocarpine
has been recommended. It certainly has that effect, but its indications
become doubtful in many cases where the saving of strength is of
paramount importance. I shall return to this subject in my remarks on
the therapeutics of membranous laryngitis.
Derivation is of great service when well directed. Local depletion must
be avoided. A purgative in the beginning is beneficial—a dose of
calomel
as good as, or mostly better than, anything else.
Diaphoretics and diuretics act quite well; the best of them all are
warm beverages of any kind. They need not come from the apothecary's
nor be very unpleasant to take—water not too cold, Apollinaris,
Selters, or Vichy, hot milk, tepid lemonade in large quantities and
very often. Sinapisms have a good effect. When not kept on longer than
a few minutes—long enough to give the surface a pink hue—they may be
applied every hour or two.
Some urgent symptoms may require symptomatic treatment. When secretion
is copious, but too tough, and expectoration insufficient because of
both the character of the mucus and the incompetency of the respiratory
muscles, ipecac in small doses or camphor is indicated. A child's dose
of the latter would be gr. ¼–½(gramme 0.015–0.03) every one or two
hours. In these cases the hydrochlorate of ammonium may be combined
with the carbonate (ammon. chlorid. drachm ss. (2.0); ammon. carbonat.
scruple j (1.25); extr. glycyrrh. pur. scruple ij (2.5); aq. pur.
fluidounce iij (grammes 100.0)—teaspoonful every hour). When the
difficulty of expectoration is excessive an emetic may be resorted to.
It is true that infants and children vomit with less straining and
difficulty than adults, but, still, the practice of flinging emetics
around is too common. The unpleasantness of getting up in the night
because of a pseudo-croup in a distant patient's baby is not a correct
indication for encouraging the indiscriminate use of emetics. When they
are required, antimonials ought to be excluded from the list. Ipecac,
sulphate of zinc, sulphate of copper, turpeth mineral are preferable.
In urgent cases the hydrochlorate of apomorphia may be used
hypodermically (six or ten drops of a 1 per cent. solution in water).
Cases of such urgency, and so excessive dyspnoea coupled with cyanosis,
as to necessitate tracheotomy are but very rare. But once in thirty
years and in many more than four hundred tracheotomies have I been
compelled to operate for a case of catarrhal laryngitis. Still, a few
such cases are on record. The best-known amongst them is that of
Scoutetten, who operated successfully on his own daughter six weeks old.
Narcotics prove quite beneficial, particularly in complications with
pharyngeal catarrh. A dose of gr. j–jss of Dover's powder (gramme
0.05–0.1) at night will secure rest for several or many hours to a
child of two or three years; an adult is welcome to a dose of 10 or 12
grains (0.6–0.75). When the irritation is great during the day, it is
advisable to add a narcotic (acid. hydrocyan. dil., min. j; vin opii,
min. viij–xij; codeine gr.
1/3–½, or extr. hyoscyam. gr.
ij–iij—daily) to whatever medicine was given. I am partial to the
latter, giving it up to gr. viij–x (0.5–0.6) to adults daily in their
mixture, retaining the single dose of opium or morphine to be taken for
the night. At that time a single larger dose is rather better than
several small ones. Narcotics cannot be dispensed with in all those
cases in which—as, for instance, in tubercular laryngitis—deglutition
is very painful because of the catarrhal and ulcerous pharyngitis.
Bromide of potassium has a fair effect, but frequently fails, and the
administration of morphia before each meal is sometimes an absolute necessity.
That complications, such as bronchitis, have their own indications is
self-understood. The general rules controlling the treatment of
laryngitis are not interfered with by them. Oedema of the glottis,
however, when occurring during an attack of laryngitis, has its own
indications, and very urgent ones indeed in all acute cases. In chronic
cases a causal treatment is required according to the etiology of the
affection as specified above. In acute cases it is not permitted
because of want of time. The danger of immediate strangulation is often
averted only by a deep scarification or the performance of tracheotomy.
Chronic cases require all the preventive measures enumerated above and
the internal use of iodide of potassium or sodium (scruple
j–scruple iiss = gramme 1.25–3.0 daily, for adults), and tincture of
pimpinella saxifraga three or four teaspoonfuls daily. When it is given
it ought to have an opportunity to develop its local effect on the
pharynx also by giving it but little diluted, and not washing it down
afterward (tinct. pimpinella saxif., glycerin. aa, teaspoonful every
two hours). In these cases, while the local salt-water treatment
recommended above is indispensable, the nitrate-of-silver spray
mentioned in that connection is here again referred to as very
beneficial indeed. But the solution of 1 per cent. is the highest
degree of concentration allowable. Conducted through the nose, it will
reach the larynx better than through the mouth. When both accesses are
rather difficult the application must be made directly to the larynx.
PATHOLOGY.—Pseudo-membranous laryngitis is characterized by the
presence, on and in the mucous membrane, of a pseudo-membrane of a
whitish-gray color, various consistency, and different degrees of
attachment. It has been called croupous when it was lying on the mucous
membrane without changing much or at all the subjacent epithelium and
could be removed without any difficulty. It has been called
diphtheritic when it was imbedded into the mucous membrane and was
difficult to remove. This difference exists, but it does not justify a
difference of names except for the purpose of clinical discrimination;
for the histological elements of the two varieties are the same, and
the difference in their removability is explained by the anatomical
conditions of the territory in which they make their appearance. The
membrane consists of a net of fibrin studded with and covering
conglomerates of round cells, mixed with mucus-corpuscles, epithelial
cells more or less changed, and a few blood-cells. The fibrinous
deposit is either quite superficial or lies just over the basal
membrane or on layers of round cells originating from the basal
membrane. It is continued into the open ducts of the muciparous
follicles, filling them entirely in the worst cases, or meeting the
normal secretion of mucus in the interior of the duct. The principal
seat of the pseudo-membrane is that mucous membrane which is covered
with pavement epithelium; thus it is that the tonsils are the first,
usually, to exhibit symptoms of diphtheria. But cylindrical epithelium
is by no means excluded. However, while pavement epithelium is
generally destroyed by the diphtheritic process, the cylindrical
epithelium is frequently found unchanged, or but little changed, on top
of the mucous membrane under the pseudo-membrane.
The nature and consistency of the pseudo-membrane in the larynx is best
studied by the light of the study of its anatomy. There is a great deal
of elastic tissue in both epiglottis and larynx; the mucous membrane of
the latter is thin, and sometimes folded on the vocal cords. The
epithelium of the epiglottis is pavement; only at its insertion it is
cylindrical. In the larynx it is also pavement on the true vocal cords
and in the ary-epiglottic folds, and fimbriated toward the fossæ
Morgagni and trachea. Lymph-vessels are but scanty on the epiglottis,
still more so in the larynx. Of acinous muciparous glands there are
none on the epiglottis, none on the true vocal cords; they are more
frequent in and round the fossæ Morgagni, with cylindrical epithelium
in the glandular ducts. The trachea and bronchi contain a good many
elastic fibres, less connective tissue, fimbriated epithelium, some
lymph-vessels, but no lymph-glands, and acinous muciparous glands in
large numbers. Wherever the pavement epithelium membrane is abundant
the membrane is firmly adherent and imbedded into the mucous membrane.
Where it is cylindrical and plenty of acinous glands secrete their
mucus, they are loosely spread over the mucous membrane, from which
they can be easily removed; while the histological condition of
both the imbedded and the loose membrane is exactly the same.
Before the membranous deposit takes place the surface is in a condition
of catarrh. Round the membrane the mucous membrane is red and slightly
swollen. Not always, however, is that so. Particularly, the epiglottis
may be covered on its inferior surface with a solid membrane or be
studded with tufts of membrane, without much or any hyperæmia. The same
can be said of the larynx, which is supplied with but a scanty
distribution of blood-vessels and a sufficient network of elastic
fibres to counteract the dilatation of blood-vessels peculiar to the
catarrhal and inflammatory processes.
In uncomplicated cases of membranous laryngitis the membrane is
confined to the larynx. Dozens of years ago—viz. before 1858, when
diphtheria began to settle amongst us, never, it appears, to give up
its conquest again—that took place in most cases. But since that
period we meet with few such simple cases. As a rule, the membrane
makes its appearance in the pharynx first, from there to descend into
the larynx, and not infrequently into the trachea and bronchi. In
other—fortunately, but few—cases the membrane is formed in the
bronchi and trachea first, and invades the larynx from below.
Other organs suffer but consecutively and from the results of impeded
circulation only. Thus, in post-mortem examination hyperæmia of the
brain, liver, and kidneys, and bronchitis, broncho-pneumonia, or
pulmonary oedema, are met with. Only those cases of membranous
laryngitis which are complicated with general diphtheria yield the
additional changes of the latter.
ETIOLOGY.—Intense irritants will produce an irritation on mucous
membranes. In the larynx the product is, according to the severity of
the irritation, either a catarrhal or a phlegmonous or a croupous
laryngitis. The irritating substances may be mechanical, chemical, or
thermical. Heubner produced diphtheria of the bladder by cutting off,
temporarily, the supply of circulation. Traumatic injury of the throat
and larynx will soon show a croupous deposit. Caustic potassium,
sulphuric acid, caustic ammonium, corrosive sublimate, arsenic,
chlorine, or oxygen, applied to the trachea or larynx, produce croupous
deposits.1 Inhalations of heat, smoke, and chlorine have the same
effect. These, however, are not the usual causes of croup. Cold and
moist air is a more common cause, mainly during a prevailing epidemic
of diphtheria. In former times, which are unknown to the younger
generation of physicians, when no such epidemics existed, the only form
of diphtheria occurring now and then was the local laryngeal diphtheria
called pseudo-membranous croup. It was then a rare disease, while at
the present time it is of but too frequent occurrence. In my Treatise
I have explained at some length the relations of the two (p. 128).
1 A. Jacobi, Treatise on Diphtheria, p. 111.
Age has some influence in its development. The disease is not frequent
in the first year of life; between the second and seventh years almost
all the cases are met with. There are families with what appears to be
a general tendency to croupous laryngitis. It may return. Even
tracheotomy has been performed twice on the same individual.2 It is
contagious. In the same family, from a case of croup, either another
case of laryngeal croup may originate or another form of diphtheria
will develop in other members of the household. It is not so
contagious, it is true, as generalized diphtheria must be, for the
infecting surface is but small in uncomplicated membranous croup, and
the membrane not so apt to macerate and be communicated. Boys appear to
be affected more frequently than girls. But the previous constitution
makes no difference.
2 Treatise, p. 27.
SYMPTOMS.—Membranous laryngitis begins sometimes with but slight
symptoms of catarrh, sometimes without them. Nasal, pharyngeal, and
laryngeal catarrh may precede it a few hours or a week, with or without
fever and with
a certain sensation of pain or uneasiness in the
throat and a moderate amount of cough and hoarseness. This condition
has been called the prodromal stage of membranous laryngitis, though it
is just as natural to presume that the changes in the mucous membrane
merely facilitated the deposit of false membrane. The latter is more
apt to develop on a morbid than on a healthy mucous membrane. The
membranous laryngitis proper dates from the time at which, with or
without an elevation of temperature, a paroxysmal cough makes its
appearance—first in long, afterward in shorter intervals—which is
increased by a reclining posture, mental emotions, or deglutition. At
an early period this cough, which is very labored and gives rise to
dilatation of the veins about the neck and head, is complicated with
hoarseness, which gradually increases into more or less complete
aphonia. Respiration becomes audible, sibilant, with the character of
increasing stenosis. Inspiration becomes long and drawn; expiration is
loud; head thrown back; the scaleni, sterno-cleido-mastoid, and serrati
muscles are over-exerted; above and below the clavicles and about the
ensiform process deep recessions take place in the direction of the
lungs, which are expanded with air, but incompletely; dyspnoea becomes
the prominent symptom, and occasional attacks of suffocation render the
situation very dangerous and exciting indeed. These sudden attacks of
suffocation are due—besides the permanent narrowing of the larynx by
the membranes, which gradually increase in thickness—to occasional
deposits of mucus upon the abnormal surface of the larynx and vocal
cords, by partly-loosened false membrane, which now and then become
audible, yielding a flapping sound, by oedema in the neighborhood, and
by secondary spasmodic contractions. They are mostly met with in the
evening and night; there is often a slight remission in the morning,
which rouses new hopes, which soon, however, prove unfounded.
Meanwhile, the pulse becomes more frequent in proportion with the
increase of dyspnoea, and finally irregular; the temperature rises but
little, and usually only when the throat or other organs, which are in
more intimate connection with the lymph circulation than the larynx,
are participating in the exudative process; and the laryngeal sounds
become so loud as to render the auscultation of the lungs impossible.
The glands of the neck are not swollen when the process is confined to
the larynx. Now and then small or larger, rarely cylindrical, pieces of
false membranes are expectorated, with or without any amelioration of
the condition. In this condition the patient may remain a few hours or
a few days.
Then the dyspnoea will rise into orthopnoea; the anxious expression and
bearing of the little patient—for the vast majority of the sufferers
are children—becomes appalling to behold; cyanosis increases; the head
is thrown back; the larynx makes violent excursions upward and
downward; the abdominal muscles work in rivalry with those of the
thorax and neck; the surface is bathed in perspiration; still,
consciousness is retained by the unhappy little creature tossing about
and fighting for breath, and in complete consciousness he is strangled
to death. Now and then the carbonic-acid poisoning renders the pitiful
sight a little less appalling to the powerless looker-on by giving rise
to convulsions or anæsthesia and sopor, which finally terminate the
most fearful sight, the like of which the most hardened man, the most
experienced medical attendant, prays never to behold again.
Besides the brain symptoms just mentioned, but few other organs give
rise to abnormal function. In the kidneys the stagnant circulation
results in albuminuria—in the bronchi and lungs, in hyperæmia,
inflammation, and oedema.
The symptoms described above are the same both in those cases which are
strictly localized and those which descend from the pharynx. In the
latter there is fever only when the pharyngeal diphtheria was attended
with it. The process descending into the trachea and bronchi changes
the symptoms
but little, as far as the laryngeal stenosis is
concerned, for it is the latter which destroys by suffocation. Only
when tracheotomy has been performed, and the immediate danger of
suffocation has been removed, the further progress in a downward
direction gives rise to a new series of symptoms. After the temporary
relief procured by the operation dyspnoea will set in anew, not always,
however, of that intense degree of the laryngeal stenosis; respiration
will become dry and loud again, and a little more frequent than in the
uncomplicated laryngeal cases. Death will finally also result, either
from suffocation or from the symptoms I enumerated above.
Lastly, when membranous laryngitis is but the terminating development
of extensive membranous bronchitis, the symptoms differ from those
described above in this, that the laryngeal symptoms last but a short
time. For days or weeks no symptoms but those of an ordinary bronchial
and tracheal catarrh were observed: all at once the process reaches the
larynx; in a few hours the very last stage of croupous stenosis is
reached; even tracheotomy does not relieve the symptoms. Or the
fibrinous bronchitis was extensive enough to give rise to a sufficient
number of symptoms before the larynx was reached. Amongst them is,
foremost, frequency of respiration, because of its insufficiency;
diminution of respiratory murmur over the area supplied with the
affected bronchi; sometimes localized absence of respiratory murmur,
while the percussion sound is sonorous. Another complication is
emphysema, either subpleural or pulmonary. It is not frequent, except
in combination with fibrinous bronchitis. The increase of respiratory
movements is quite sudden, percussion sound tympanitic, and
auscultation negative. Pulmonary oedema is quite frequent; it is the
result of the rarefaction of air in the bronchi, the consecutive
dilatation of the blood-vessels, and the effusion of serum by
intravascular pressure. Every severe case is accompanied with it; in
every tracheotomy it is met with coming up into the incision. Oedema of
the glottis is less common, but it is met with in the same manner and
with the same symptoms which characterize the glottic oedema of
catarrhal laryngitis.
PROGNOSIS.—It is not favorable even in the simple and uncomplicated
cases. Infants and children under two years almost invariably die. The
percentage of average mortality rates very high—from 80 to 90 and
more. It is probable that some recent therapeutical advances have
reduced it, will reduce it, considerably. Tracheotomy is known to do so
certainly, as from 20 to 45 out of 100 operations prove successful. The
previous condition of the patient is of very little account in regard
to the course and termination of the disease; no constitution protects
or saves. The more the disease is local the better the prognosis. When
fever makes its appearance, it means a complication, such as extending
diphtheria or bronchitis or bronchi-pneumonia, and impairs the chances
of recovery. The expectoration of membranous shreds or whole membranes
does not improve the prognosis much, as the new formation of membranes
may be very rapid indeed. I have seen new membranes rising to a
formidable extent in from two to seven hours. The prognosis is improved
when the cough becomes looser, expectoration more purulent, pulmonary
respiration become audible again after having been covered by the
laryngeal noises, rhonchi become moist, and portions of lungs which
before were inaccessible to air by clogging membranes are reopened.
Increasing debility, frequent and irregular pulse, are ominous
symptoms. Even more so is the failure on the part of emetics to take effect.
DIAGNOSIS.—It may be quite difficult to diagnosticate croupous from
catarrhal laryngitis, particularly in those cases where the former is
not complicated with any visible exudative process in the fauces. In
membranous laryngitis stenosis begins gently (except in those cases
which ascend from the bronchi) and increases gradually; there are, it
is true, remissions in the morning (mostly), but they are but
slight, and the subsequent evenings are worse than the previous ones.
It increases from day to day until a slight cyanotic hue of the lips is
followed with more general cyanosis. There is no fever or very little,
except in the cases of generalized diphtheria. The character of the
cough does not change; perhaps it becomes more dry and suppressed after
a while. Hoarseness does not improve, but increases steadily into
aphonia. Expectoration is but scanty; now and then a small portion of
mucus from the lower portion of the respiratory tract, now and then
shreds of membrane, are expelled.
In catarrhal laryngitis stenosis begins abruptly and suddenly, and is
often at its height a few minutes after the commencement of the attack.
Remission sets in soon, is more marked, sometimes complete, and a new
attack, just as sudden as the first, may occur in the next night. Real
cyanosis is but rarely developed; when it is, it changes soon into a
more normal condition. Catarrhal laryngitis in the child is a febrile
disease. In it the cough changes after a little time, some moisture
mixes with the expectoration and changes both cough and articulation;
also, the voice is not equally husky; now and then a clear note comes
in. Close inspection of the throat exhibits sometimes a thick, viscid
mucus floating up and down with the excursions of the larynx in
catarrh. It never has any membranous expectoration.
Local oedematous swelling of the ary-epiglottic folds, with or without
membranous deposits in some other parts of the larynx, yields all the
symptoms of membranous croup with its dangers and death-rate. The
effect of this oedema is partial paralysis of the vocal cords. Thus,
inspiration is impeded, as in membranous obstruction; expiration,
however, is free and the voice intact to a certain extent. This local
oedema may be detected by palpation.
General oedema of the larynx (glottis) is fortunately rare. The attack
is very sudden; there is no cold, no hoarseness, no choking cough, no
membrane; there is only dyspnoea, gasping, asphyxia, sopor, and death,
unless relief is given almost instantaneously.
The presence of a foreign body has been mistaken sometimes for
membranous laryngitis. The history is a different one; there was no
prodromal catarrh; the children were taken suddenly while playing or eating.
The laryngoscope would be a great aid in diagnosis if it could be used
during the distress of a membranous laryngitis. Still, it has been
employed by Ziemssen, Rauchfuss, and others. But the opportunities are rare.
TREATMENT.—The objects of treatment differ with the various stages of
the disease. The inflammatory symptoms of the commencement, the
completed exudation, the maceration and disintegration, and also the
expectoration of the pseudo-membranes, and, finally, the asphyctic
stage, have each their own indications. If there is anything which must
not be recommended, it is depletion. Fortunately, there are but few
practitioners left who still apply leeches or employ more general
depletion, but these few are still doing too much harm by their
practice and teaching. The application of ice, however, in bags over
and near the larynx, and of iced cloths frequently changed, combined
with the swallowing of small pieces of ice from time to time, is apt to
be beneficial in well-nourished, hearty children. Such as have been
anæmic, with thin muscles and pale mucous membranes, do not bear it so well.
The most powerful and reliable preventive and solvent, thus far, is
hydrargyrum. It is true that many voices have been raised against it,
but from Bard, Bretonneau, and Billard to Rauchfuss, Ch. West, Lynn,
Pepper, and others, the remedy has had its admirers. Large single doses
of calomel have been given by some, amounting to 15–30 grains (gramme
1.0–2.0), but that treatment has not found many friends. In small and
frequent doses it has been of good service to me both in fibrinous
laryngitis and bronchitis, particularly in the latter; gr. ¼–½
may be given every half hour or every hour. Tartar emetic is liable to
develop so many unfavorable effects that even doses—in combination
with calomel—of
1/100 of a grain require great caution. The most
reliable mercurial preparation, in my experience, and the least
hurtful, is the corrosive chloride. In the stomach it combines with the
chloride of sodium, is absorbed without being changed, and transmuted
into an albuminate during its circulation in the blood. Babies of
tender age bear one-half of a grain and more, daily, many days in
succession. Salivation and stomatitis are exceedingly rare after its
use. Gastro-intestinal disturbances are not at all frequent; diarrhoea,
if observed at all, is very moderate, and can be avoided or removed by
the administration of mucilaginous and farinaceous food or a mild dose
of an opiate. But the administration of the bichloride requires care in
regard to its solution. A fiftieth of a grain may be safely given to a
baby a year old every hour, but it must be dissolved in one-half of a
tablespoonful or a whole tablespoonful of water. The solution of a
grain in a pint of water is about correct. In those very rare cases in
which no preparation of mercury is borne internally the inunction of
sufficient and frequent doses of the oleate of mercury may take the
place of the internal administration or alternate or be combined with
it. The blue ointment is not so effective as the oleate. The
subcutaneous injection of the corrosive chloride may be added to the
modes of administration if no time must be lost in introducing as much
as possible of the drug into the system. Now and then, however, the
subcutaneous tissue of the child does not tolerate it well in that
form, though the solution may be not larger than 2 per cent.3 The
cyanide of mercury, in doses of a hundredth of a grain every hour, has
been warmly praised by A. Erichsen and C. G. Rothe.
3 The Medical Record, May 24, 1884.
The large mortality in croup and the inefficiency of remedial treatment
have been the reasons why the recommendations of remedies have been
very numerous. Alkalies were held in great favor during different
periods of our literature, mainly the carbonate and bicarbonate of
potassium (and sodium), in daily doses, to a child, of ½ drachm or 1
drachm or more; also the chlorate of potassium or sodium. As an
adjuvant it may be useful; as an antidiphtheritic or antimembranous
remedy it must not be regarded. What it can do is to heal or prevent a
catarrhal stomatitis and pharyngitis. The best and most reliable is
probably the iodide, in larger doses than are usually given. One or two
drachms daily (grammes 4.0–8.0) are well tolerated when sufficiently
diluted. Benzoate of sodium was recently recommended for its supposed
antifermentative and antibacteric effect; its practical utility is but
very limited; not even its antifebrile effect is anything but reliable.
Lime-water has not fulfilled in my hands the promises made by
others—neither its internal use nor spray nor inhalation. The most
certain mode of introducing lime particles into the larynx is, after
all, the inhalation of slaked lime, which allows a quantity sufficient
to be somewhat effective to enter the respiratory organs. Its
comparative inefficiency has been acknowledged by those who add 1 per
cent. of the liquor of caustic potassium or sodium to the lime-water.
Quinia, in doses of 15 or 30 grains (grammes 1.0–2.0) daily, has been
recommended by Monti for the same indications, mainly in the
commencement of febrile cases. It has been claimed that cold
applications, to be changed every hour or two according to the
Priessnitz or hydropathic plan, had a great power in macerating and
disintegrating mucous membrane. Many of the successful cases of these,
as of all other specialists, are undoubtedly the result of the
convenient substitution of a grave diagnosis for a milder one. The
effect of such applications in laryngeal catarrh, like that of warm
applications, is undoubted. Vesicatories applied to the neck over the
larynx are never
useful—frequently injurious by the sore surface
becoming the seat of a pseudo-membrane.
Inhalations of warm vapor are decidedly beneficial, but atomized water
is not of equal value. Thus, Richardson's atomizer is not so useful as
Siegle's inhaler or other apparatuses working on the same plan.
Lactic acid, in solutions of 1:10 or 25 (Monti's solution of 1:200 is
certainly too weak), has been applied by means of a sponge, inhaled, or
thrown in from an atomizer for the same purpose. Good results have been
reported, failures also; and still, recoveries are rushed into print
much more readily than failures. The same may be said of the local
applications of glycerin, boric acid, carbolic acid in solutions of 1
or 2 per cent., salicylic acid, iodoform, and hypermanganate of
potassium; also of bromine (bromine and potas. bromid. aa) 1:water
500, or a stronger solution.
Tannin, dry or with glycerin, is rather more injurious than it can be
useful. It is apt to coagulate the mucus contained in the pharynx and
the upper part of the larynx, and to render the dyspnoea graver than
before. Such an aggravation of symptoms must be carefully avoided,
though it be but temporary. The same must be said of alum, which has
been used solid, in finely-powdered condition, down to a 3 per cent.
solution in water.
Spirits of turpentine are inhaled either from an inhaling apparatus or
by saturating the air of the room. Water is kept boiling constantly on
a stove, oven, or alcohol lamp (not on gas, which consumes a larger
quantity of oxygen), and a tablespoonful of the spirits of turpentine
is poured hourly or in shorter intervals upon the boiling surface.
Hydrochlorate of ammonia can be used in the same manner as described in
the article on Catarrhal Laryngitis.
Hydrochlorate of pilocarpine was introduced into the treatment of
diphtheria and pseudo-membranous croup some years ago, and recommended
as no less than a specific. It increases, physiologically, the
secretion of the skin, the mucous membranes, the lachrymal and
muciparous glands, the kidneys. It also depresses the heart's action.
In all cases in which the latter effect is to be feared the drug is
contraindicated; thus in septic diphtheria, in pseudo-membranous croup
with great asthenia, in general debility and anæmia. By increasing the
secretion of the mucous membranes it is expected to macerate the
pseudo-membrane and raise it from its bed. This can be accomplished
wherever the membrane is deposited upon the mucous membrane—that is,
whenever the number of muciparous follicles is large and the epithelium
is cylindrical. This is not so on the vocal cords, and thus the
floating effect of pilocarpine cannot be obtained exactly where it is
most needed—that is, on the vocal cords, where the pseudo-membrane is
more intimately imbedded into the tissue than, for instance, on the
posterior wall of the fauces or the trachea and bronchi. Still,
pilocarpine may be tried, in combination with other modes of treatment,
as long as the heart's action is competent and the general condition
satisfactory. It is dissolved in water; its dose, for a child a year
old, 1/30 grain (2 milligrammes = 0.002) every hour. A subcutaneous
injection every four or six hours of
1/60 grain (three drops of a 2 per
cent. solution) will prove very effective for good and evil. I believe
it has rendered me good service in some well-marked but mild cases of
pseudo-membranous laryngitis, which it either aided in healing or
prevented from getting worse.
Emetics have their distinct indication. It is irrational to expect any
relief from them when the larynx is narrowed by firmly-adhering
pseudo-membranes. Their indication depends on the possibility of
removing something which acts as a foreign body. This something can be
either mucus or loose or partially loose membrane. The peculiar
flapping sound produced by the latter admits of or requires the
administration of an emetic. Above I have stated which
of them
ought to be selected. Turpeth mineral in a dose of from 3 to 5 grains,
repeated in six or eight minutes, acts quite well. Hypodermic
injections of apomorphine may be required in urgent cases.
The introduction of catheters into the larynx, according to the methods
of Horace Green, is a dangerous proceeding and ought not to be indulged
in. It gave the idea to Loiseau and Bouchut to force a tube into and
through the larynx, full of pseudo-membrane, for permanent use until
the pseudo-membrane would have disappeared. This tubage was rendered
ridiculous at once by the assertion of Bouchut (1858) that children
suffering from croup who were supplied with this laryngeal tube were
not only relieved at once, but expressed their gratitude in audible
oratory. Still, there are some cases on record of more recent date in
which tubage is reported to have been attended with success. It is not
very probable, however, that a larynx which admits of no air, because
of its being clogged with firm pseudo-membrane, should be willing to
admit and endure the presence of a tube.
Massage of the larynx has been recommended by Bela Weiss. It consists
in systematical gentle pressing and kneading of the larynx by the
physician while sitting behind the patient. He asserts its satisfactory
influence not only in catarrhal but also in diphtheritic (croupous) laryngitis.
The inhalation of oxygen has proved rather advantageous in my hands in
a few instances. The most memorable case of the kind I have mentioned
elsewhere. It was that of a child on whom tracheotomy had been
performed. The pseudo-membranous process, however, invaded the bronchi,
with the result of producing dyspnoea, cyanosis, and convulsions.
Whenever a current of oxygen was introduced into the lungs through the
canula both cyanosis and convulsions would cease, and returned when its
supply was stopped.
But if no medication will have proved successful, the symptoms of
stenosis, dyspnoea, cyanosis, and the supra- and intraclavicular and
epigastric recension increase steadily to an alarming extent. When the
pulse becomes frequent and intermitting, even without the presence of
asphyxia and anæsthesia, air ought to be introduced into the lungs by
tracheotomy. No positive rules can be laid down as to the length of
time one ought to wait before performing it. No subdivision of the
disease into several stages is of any benefit in selecting the exact
period in which the trachea must or may be opened. No alleged
contraindication to the performance of tracheotomy, whether the tender
age of the patient or a complication with either an inflammatory or an
infectious disease, must be considered valid. The one strict indication
for the performance of tracheotomy is when the diagnosis of
pseudo-membranous laryngitis is undoubted, the increasing dyspnoea,
cyanosis, and approaching asphyxia, with the certainty that a
well-directed and sufficient medicinal treatment has been, and in all
probability will be, useless. Even under these circumstances there is
no mathematical certainty. The matured experience of a well-informed
and thoughtful physician will commit but few errors. If there be the
slightest doubt, the operation ought to be preferred to suffocation.
The operative procedure and the surgical treatment after the
performance of tracheotomy will form the subject of a special article
in this work. In this place a few remarks upon the medicinal and
dietetic treatment in that period of the disease must suffice.4
4 Cf. The Med. Rec., May 24, 1884.
The nutrition of the patient has generally suffered much. Before the
operation but little food was taken, still less was digested, and the
operation itself and the anæsthetic have added to the previous weakness
or exhaustion. Moderate feeding and stimulation are therefore to be
commenced soon. Vomiting after chloroform I have seldom seen to last
long or to be embarrassing under these circumstances. Feeding and
stimulation are the more necessary the more the hungry
lymph-vessels are liable to absorb injurious material when not supplied
with healthy food.
Is internal treatment required? The general treatment must be
continued. If it consisted in the administration of hydrargyrum, either
internally or externally, it must be continued. If its effect was not
sufficient to clear the larynx and to render the operation unnecessary,
it will or may be sufficient to complete its effect in the next day or
two, to prevent the process from descending or the membranes becoming
too many or too thick. No changes ought to be made in the treatment
unless there be changes in the symptoms. Not infrequently the first
symptoms of broncho-pneumonia come on within a few hours after the
operation, recognizable by frequent pulse, respiration frequent beyond
proportion, and physical symptoms. The stomach is not very reliable.
Quinine answers best hypodermically. From 6 to 10 grains may be
injected at once. The preparation which has served me best in the last
few years is a solution of the carbamid in five parts of water. If an
additional remedy is required, from 20 to 30 grains of sodium
salicylate may be given in the course of three or four hours, in hourly
doses, to reduce the temperature. Tincture of digitalis will prove
advisable at the same time when the heart appears to require it.
Strychniæ sulphas will act as a powerful nervine;
1/25 grain may be
given to a child two years of age every two hours, until four or five
doses shall have been taken. The rest of the treatment of the
complications depends on their nature and character. It is not the name
of the disease which has to be treated, here as in every case, but the
individual patient.
In regard to stimulants I have but little to say. I use alcohol in the
most pleasant shape, preferring brandy or whiskey. I use a great deal
of camphor, 10 to 40 grains daily, or in cases of urgency Siberian
musk, from 2 to 5 grains, every half hour or hour, until from 15 to 20
grains have been taken in cases of collapse or great prostration.
BY LOUIS ELSBERG, A.M., M.D.
Inflammation, Erosion, and Ulceration of the Epiglottis.
Of the diseases of particular portions of the larynx, those of the
epiglottis deserve especial attention in a work designed for general
practitioners, on account of the comparative ease of recognizing and
treating them if understood, and the promptness their management
requires. They occur more frequently than is generally supposed, their
symptoms are often erroneously ascribed to other affections, and they
may lead to extensive disease in the respiratory apparatus, sometimes
of a very serious character. Adjacent portions of the root of the
tongue and pharynx or of the larynx are apt to be coaffected. In
diseases which commence in the pharynx, usually the lingual surface,
and in such as spread upward from the larynx only the laryngeal
surface, of the epiglottis is involved mainly or exclusively.
Before describing the affections of the epiglottis a few words must be
said of the manner of using the tongue-spatula. Physicians almost
without an exception press the tongue from above downward and from
before backward; but in order to bring the epiglottis into view in the
majority of instances the proper method is just the opposite of
this—viz. from below upward and from behind forward. Place the spatula
far back, lift up the base of the tongue, and draw it forward. The
usual manner of depressing the tongue—no matter how good or bad an
instrument may be used, and an ordinary spoon-handle serves the purpose
better than most of the so-called tongue-depressors—pulls upon and
irritates the pharyngo-glossal fold, and often hides the epiglottis
instead of bringing it into view, besides producing intolerance and
intractability. The blade of the tongue-spatula should be long (at
least four, still better five, inches), slightly curved downward, not
more than from half an inch to one inch wide, and joined to the handle
at an obtuse angle.
1. Acute inflammation of the epiglottis is usually caused by taking
cold, exposure to draughts, wet, sudden changes of temperature, etc.
The symptoms are local pain and difficulty of swallowing; in severe
cases also some dyspnoea and dysphonia. Only occasionally there is a
hemming cough, and that a peculiar one, induced (usually voluntarily)
by a feeling of a foreign body at the root of the tongue. The diagnosis
is made by means of the tongue-spatula and laryngeal mirror, the
epiglottis being seen to be inflamed and swollen. When the lower
portion, the so-called cushion of the epiglottis, is affected, the
mirror is required for diagnosis. In this case suppuration is apt to
occur. The prognosis is good with attention; neglected epiglottitis may
cause great discomfort, and even death. Treatment must be
antiphlogistic and supporting. For mild cases systemic and dietetic
regulation suffices, with externally either hot fomentations or cold
applications as the patient can best bear. Severer cases require in
addition leeches and ice to the part; and cases of threatened
suppuration, medicated and unmedicated steam inhalation, and, when
necessary, lancing of the abscess through the
mouth under
guidance of the mirror. After the acute inflammation has subsided,
local treatment may become necessary to hasten or produce complete
restoration, as will be noticed in Chronic Epiglottitis.
Inflammatory oedema of the epiglottis will be considered under the head
of Laryngeal Oedema.
Chronic inflammation of the epiglottis is usually the result of uncured
acute epiglottitis or of laryngitis. The main symptom is dysphagia. The
epiglottis is found swollen and more or less discolored. Not only
tongue-spatula and laryngeal mirror, but also the finger carefully
introduced into the mouth, may ensure the diagnosis, especially if the
upper portion be affected: then the thickened epiglottis is seen and
felt as a peculiar rounded tumor at the base of the tongue. Oedema is
distinguishable from chronic inflammation by both sight and touch. As
to prognosis, it must be observed that the process of restoration is
slow and that there is always danger of acute exacerbation. The
treatment consists in attention to the general health and habits and in
local applications. The latter are indispensable, and should be made by
means of an instrument (Elsberg's applicator or the like) carrying a
little wad of cotton or sponge. Some prefer a brush: to such individual
preference no objection need be made, but powders and sprays are not
advisable. The remedies to be applied should be in liquid form, and
belong pharmacologically to the class of alteratives. Iodine, iodoform,
and silver nitrate in solution are most useful. In subacute
inflammation (see above) potassium bromide and chlorate, respectively,
in saturated aqueous solution, may be applied once a day, or a
saturated solution of iodoform in sulphuric ether, or ten grains of
crystallized silver nitrate dissolved in an ounce of water, every other
day. In chronic epiglottitis the tincture or compound solution of
iodine, the ethereal solution of iodoform, and the watery solution of
silver nitrate, in degrees of concentration varying according to the
severity of the case and the individuality of the patient (the choice
of either of the three agents, the repetition of the same, or the
change from one to the other depending upon the effect produced),
should be accurately applied to the part affected by means of the
laryngeal mirror or the tongue-spatula.
2. The most frequent, and at the same time the most neglected, morbid
condition of the larynx is erosion of the free edge of the epiglottis.
Louis has called attention to the epiglottic erosions in connection
with tubercular phthisis: he found them present in about one-sixth of
the patients who died of that disease, and they are caused, in his
opinion, by the constant passage of pus over the part. Horace Green was
the first who pointed out that they are also frequently met with
independently of tubercular disease. According to him, "These
instances, for the most part, have been found occurring in those cases
in which a persistent, teasing cough, following chronic follicular
disease or common catarrhal inflammation, has obstinately resisted all
the ordinary measures for its arrestment. On depressing the tongue in
such cases by means of the ordinary bent spatula or tongue-depressor,
so as to bring the epiglottis into view, this cartilage has been found
frequently inflamed, vascular, and its superior border marked at one or
more points by distinct erosions. In much the largest proportion of
cases these erosions make their first appearance on the left superior
edge of the epiglottis. Next in frequency they will be found occupying
its centre, and occasionally, but very rarely in comparison with the
two preceding locations, they have been observed upon its right border.
These erosions are not readily detected, at first, by the inattentive
observer, as they are quite small, are only slightly depressed, with a
pallid base, sometimes a little reddened, and with whitish, linear
edges. The surrounding mucous membrane is generally inflamed, its
delicate network of superficial vessels is red and injected, and the
epiglottis itself more or less thickened." Sometimes epiglottic
erosions exist without much cough, and certainly a cough can
exist without erosions; but the two seem frequently to act
interchangeably as cause and effect; and certain it is that a cough,
from whatever cause, once firmly established, when such erosions have
supervened rarely if ever yields so long as the erosions continue, and
often stops when they are cured. According to my experience, the left
and right sides of the upper border are affected with about the same
frequency, and oftener than the centre. The erosions are catarrhal in
their nature, even in tubercular subjects; in non-specific cases they
degenerate exceedingly rarely into ulcers—i.e. they may exist for
years without involving any tissue below the epithelium unless the
patient is or becomes syphilitic or phthisical. They often produce
symptomatically, especially in the beginning, more hemming than cough.
The diagnosis is easy on thorough inspection of the epiglottis.
Prognosis is generally favorable, except in phthisical cases; in
others, although they sometimes prove exceedingly obstinate, they
usually yield with surprising promptness to topical treatment. In
specific cases, and even in chronic naso-laryngeal catarrh, they are
apt to recur, however. A cotton wad dipped in a strong solution (gr.
xxx–drachm j ad ounce j water) of either silver nitrate or gold
chloride must be brought accurately into contact with the eroded spots
once in twenty-four or forty-eight hours; ordinarily only a fortnight's
treatment is necessary, except for the frequently accompanying (or
underlying) catarrhal condition of a more or less large extent of the
upper respiratory mucous membrane. In very severe cases a few
applications at longer intervals of a still stronger solution (drachm
j–drachm ij), or even of the solid silver or gold preparation, may be required.
3. Epiglottic ulcerations differ from erosions in the fact that the
latter are confined to the epithelium, while the former involve also
deeper structures. It has been asserted by some observers that an
erosion is always the first stage of an ulceration, and by others that
the one never passes into the other. I believe that both of these
extreme assertions are incorrect; but if it were possible to
distinguish, clinically or pathologically, every case of superficial
ulceration from erosion, I might incline to agree with the latter.
Histologically, epiglottic ulceration affects the mucous membrane,
glands, or cartilage. Most frequently it seems to originate in the
follicles. As Horace Green has long ago pointed out, "At first an
enlarged or pimple-like follicle appears on the border of the
epiglottis, surrounded by an inflamed and highly-injected portion of
mucous membrane. Soon the follicle softens, and degenerates into an
ulcer with irregular edges and an inflamed and reddened circumference.
In many instances these ulcers remain for some time superficial,
destroying only the mucous membrane; in others they penetrate deep into
the fibro-cartilage, and occasionally they result in the total
destruction of the epiglottis." Sometimes the ulcer seems to originate
in the superficial layer of the mucous membrane, the molecular death
proceeding from the surface downward; these are the cases which in the
beginning cannot be distinguished from erosions. Both these kinds of
ulceration of the epiglottis occur without, and with, grave
constitutional affections, but the cartilaginous tissue usually, though
not invariably, remains intact except in phthisis, syphilis, and
cancer. Lupus, lepra, and glanders also give rise to ulceration, and
sometimes to much accompanying thickening of the epiglottis. The seat
of the ulcers is, as a rule, on the upper border and laryngeal surface
of the epiglottis, only exceptionally on the lingual. Together with
ulcers on the laryngeal face those on the lingual face are found, but
not vice versâ. Ulcers of the epiglottis are usually small, but
numerous, worm-eaten in appearance, and frequently pass to other
laryngeal structures. Though occasionally resulting from tuberculosis,
syphilis, and other constitutional affections, they also occur as
primary disease due to catarrh and local injury, but may become the
antecedents, and in many instances the exciting cause, of other grave
maladies. Indeed, I quite agree with Horace Green that they are
often "not only among the earliest manifestations of thoracic diseases,
but are themselves in many instances the true exciting cause of these
affections; and furthermore, this postulate once established, that we
have it in our power, by timely topical medication, to arrest,
positively, cases of disease which otherwise would, and in many
instances which do, terminate fatally."
The symptoms vary with the seat and extent of ulceration. Cough and the
sense of irritation in the throat are usually present. "In several
instances all the prominent rational signs, with some of the earlier
physical manifestations, of pulmonary disease have been observed to
follow long-continued ulceration of the epiglottis; all of which
symptoms have been seen to disappear after these lesions have been
healed." When the upper border is extensively affected, and still more
when either surface, especially the lower portion of the laryngeal
surface, be involved, there is difficulty of swallowing; the pain is
due often as much to surrounding inflammation as to the epiglottic
lesion. In some cases the voice also is affected.
The diagnosis of the existence of an ulcer is easily made when the
epiglottis can be seen not only with the spatula, but also with the
laryngeal mirror. Its origin and nature are, however, not always easily
recognized, and the patient's general condition and history, as well as
the appearance of the ulcer, must be taken into account. The diagnosis
of catarrhal epiglottic ulceration must be made only after other
underlying conditions, as phthisis, syphilis, malignant disease, lupus,
lepra, and glanders (see the articles on those subjects), have been
excluded. The prognosis is good, except in cases of phthisis, syphilis,
etc., or in which already a great deal of the cartilage has been
destroyed; and even in these cases appropriate treatment will often
give the patient much comfort. Appropriate constitutional treatment
must be instituted in all cases in which the constitution is affected.
Topical treatment consists in the application of alteratives,
astringents, stimulants, or sedatives, as the case may call for. Some
cases may require once or more times touching with solid silver
nitrate; watery solution of this remedy, varying in strength from gr. x
to drachm ij to the ounce; solution of gold chloride of similar
strength; of iron pernitrate and perchloride drachm ss–drachm j to the
ounce; of zinc chloride (gr. x–drachm ss to the ounce); a solution of
iodine in olive oil (gr. x–xxv ad ounce j with a few grains of
potassium iodide), or of iodoform in sulphuric ether (drachm i–drachm
ij ad ounce j); carbolic acid in glycerin (gr. v ad ounce j) or
Magendie's solution of morphine, or a mixture of morphine and syrup of
tolu (gr. 1/8–½ to a few drops),—have most frequently been
beneficial in my hands. In many cases in which the pain on swallowing
has been so great as to make deglutition almost impossible, I have
succeeded in temporarily anæsthetizing the parts before a meal by
applying, after cleansing them, a watery solution of cocaine
hydrochloride (gr. xx ad ounce j). If, in spite of all, the difficulty
of swallowing threatens the patient with starvation, feeding with the
oesophageal tube must be resorted to.
DEFINITION.—Infiltration of a fluid or semi-fluid into the submucous
connective tissue of the larynx.
SYNONYMS.—Oedema of the glottis (often incorrectly so called, as will
presently be seen), Oedematous laryngitis, Phlegmonous laryngitis,
Submucous laryngitis, Dropsy of the larynx, Angina laryngis infiltrata,
Angina laryngea oedematosa, Angine infiltro-laryngée, etc.
CLASSIFICATION.—Cases of laryngeal oedema are classified as to their
occurrence into acute and chronic, corresponding generally to
inflammatory
and non-inflammatory; as to the nature of the
infiltration, into serous, purulent, sanguineous, sero-purulent,
sero-sanguineous, etc.; as to the extent of the infiltration, into
diffuse and circumscribed (the latter often leading to
abscess-formation, and then called laryngeal abscess rather than
laryngeal oedema, differing, however, from perichondric abscess); and
as to the seat, into epiglottic, supraglottic, infraglottic, and
glottic. When epiglottic, it implicates, besides the upper border,
often the glossal, hardly ever the laryngeal, surface; in supraglottic,
the ary-epiglottic folds, arytenoid region, ventricular folds, or
ventricles are involved; in glottic, the interfibrillar connective
tissue of the thyro-arytenoid muscle is infiltrated, very
exceptionally, if ever, the submucous tissue of the vocal bands
themselves;1 and in infraglottic, the submucous connective tissue
down to the first ring of the trachea. Glottic oedema occurs extremely
seldom, but the designation oedema glottidis is often used, no matter
what portion of the larynx is affected. Laryngeal oedema usually
affects both sides; occasionally one side more than the other, still
more rarely one side exclusively.
1 Such a case has been positively reported, or I would deny
the possibility of its occurrence.
ETIOLOGY.—Laryngeal oedema is seldom, if ever, idiopathic. Usually it
accompanies or follows either some disease or injury of the larynx2
or neighboring structures or a constitutional affection. Acute oedema
may be caused by catarrhal or diphtherial pharyngo-laryngitis;
irritation from scalds, burns, caustics, foreign bodies (especially
sharp ones), or other trauma; laryngeal ulcers, especially syphilitic
and tuberculous; laryngeal perichondritis, tonsillitis, parotitis, or
inflammation of cervical tissues on the one hand, and pyæmia and
septicæmia, endocarditis, erysipelas, small-pox, scarlatina, measles,
typhoid fever, typhus, or acute Bright's disease of the kidneys on the
other. "It has ensued upon deglutition of very cold water and upon
prolonged vocal efforts" (Cohen). Perichondritis and chondritis,
tuberculous, syphilitic, carcinomatous, or typhoid ulcerations of the
larynx, especially when deep-seated or extensive, are sometimes
attended with acute, but more often with chronic, oedema.
Non-inflammatory or chronic laryngeal oedema is sometimes part and
parcel of general dropsy in consequence of heart, kidney, or lung
disease: Horace Green has reported a case occurring in a man who had
hydræmia from great losses of blood from hemorrhoidal tumors; and it is
sometimes due to some impediment to free venous circulation in the
laryngeal tissues, from paralysis of the walls of the vessels,
mechanical obstruction, tumors of the thyroid body or in the
mediastinum, etc. compressing the jugular veins, compression of the
superior vena cava, etc.
2 According to Sestier, who has written (in 1852) the most
elaborate treatise extant on the subject, four-fifths of all cases
occur in other laryngeal affections.
Cohen mentions cases to show that acute iodism and mercurialization may
cause laryngeal oedema. He also says that although occurring in
individuals in good general health, it is more apt to take place in
those of impaired constitution or recently convalescent from acute
diseases; and in some instances there would appear to be some peculiar
predisposition toward its occurrence the nature of which is not
understood, for examples are on record of more than one attack in the
same individual. Under all these circumstances the immediate exciting
cause, when apparent, seems to be exposure to cold and moisture.
Laryngeal oedema is not a disease of childhood; exceptional under five
years, it is very rare until after ten. Most cases occur between
eighteen and thirty-five. After the sixtieth year it is again rare; and
it occurs more rarely in women than in men.
SYMPTOMATOLOGY.—The symptoms of laryngeal oedema vary with the seat
and degree—that is, according to the class to which the case belongs.
Increasing interference with breathing is the most prominent
symptom. Interference with swallowing, though not always present, is
the next prominent. Sometimes the occurrence is so sudden, insidious,
or overwhelming that the patient dies before aid can be procured. Such
was Boerhaave's case of a man who during dinner suddenly spoke with a
changed voice, which his companions took as a joke, and in a few
minutes fell dead; Rühle's case of a servant-girl, who, a trifle
hoarse, went out lightly clad on a cold morning and suffocated while
going up stairs on her return; and the case of a patient of mine with
subacute catarrhal laryngitis, who rode out behind a fast horse on a
cold afternoon, and died, within ten minutes after entering his own
house, from serous infiltration of the upper aperture of the larynx. A
number of similar cases have been reported, but usually the disease
runs its course less rapidly. When the ary-epiglottic folds are the
seat of the oedema, the patient experiences either suddenly or
gradually a difficulty of inspiration, while the expiration may be at
first unimpaired, and with increasing sensation of constriction of the
throat or of the presence of a foreign body, hoarseness, and stridor,
but often without dysphagia, the most threatening paroxysms of
suffocation supervene. When the epiglottis is the main seat, while
respiration is also more or less impeded, swallowing is rendered
painful, difficult, and sometimes impossible without choking and
regurgitation through the nares, and the voice roughened and sometimes
extinguished. When the arytenoid region is also affected, respiration
and deglutition are still worse, aphonia is complete, the sense of
irritation at the upper aperture of the larynx often amounting to pain,
and the patient with great effort expectorates slightly. In oedema of
the ventricular folds there is early aphonia and gradually increasing
dyspnoea, which affects both expiration and inspiration, sometimes the
former even worse than the latter. This makes the sufferer's efforts to
breathe most frightful to witness, the feeble inspiration being
accompanied by a slow whistling sound, and the expiration, despite most
violent exertion, almost entirely shut off. Glottic oedema is, as
before said, exceptional; when it occurs to any great extent apnoea
ends the case unless operative relief is immediately afforded. In
infraglottic oedema, which is exceedingly rare and chronic in nature,
there is steadily increasing dyspnoea, wheezing, cough, and abundant expectoration.
In acute cases of supraglottic and epiglottic oedema the suffocative
paroxysms may last several minutes, and recur at irregular intervals of
a few hours with increased intensity. If not relieved, patients become
wildly excited or terror-stricken; they may throw the chest forward,
open the mouth, grasp the throat outside or thrust their hands into it,
and make convulsive movements in their struggles for breath; with
protruding eyes and flushed face they become cyanotic, the extremities
cold, the pulse small and frequent; coma supervenes, and death. In
chronic cases the symptoms are not so violent, though they may steadily
progress to impending strangulation, but for a long time the dysphagia
gives the patient much more distress than the dyspnoea.
In circumscribed acute cases leading to the formation of an abscess
there is usually pain in a particular spot, and often general
feverishness, in addition to all the symptoms before mentioned,
according to the seat of the oedema. Sometimes the suffering in
laryngeal abscess at its height is very intense. Perforation into the
pharynx, oesophagus, or even externally, may take place, but usually
the pus points into the larynx. When the pus is evacuated either
spontaneously or by incision, violent choking, coughing, and hawking
may occur, but after it is evacuated all dangerous symptoms usually
rapidly subside.
In sanguineous infiltration the symptoms do not differ from serous or
purulent oedema under the same circumstances. Hemorrhagic infusion is
usually
sudden, and the resulting stenosis often fatal. Muscular
spasm or paralysis sometimes coexists with laryngeal oedema, and
greatly adds to the interference with respiration.
PATHOLOGY AND MORBID ANATOMY.—The seat of the morbid process being the
connective tissue, those localities of the larynx in which this tissue
is most abundantly interposed between the mucous membrane and the
cartilage are most liable to infiltration. I must say from my own
experience that the epiglottis—particularly the glosso-epiglottic
region—is most frequently affected,3 next the ary-epiglottic folds,
then the arytenoid region, and then the ventricular folds. The
ventricles and the vocal bands are very rarely involved. Infraglottic
oedema is still more rare, and is never an extension of the
supraglottic. The disease is never a primary one, and, though seated in
the submucous connective tissue, it may have started with inflammation
of either the overlying mucous membrane or the underlying
perichondrium. Effusion of blood is generally limited to traumatic
cases, but has ensued from mercurialization, small-pox, and typhus;
purulent infiltration and abscess formation is the result of
phlegmonous inflammation and breaking down of the tissue, occurring
especially in the cushion of the epiglottis and in the ventricular and
ary-epiglottic folds; but as a rule the effusion in laryngeal oedema is
of a serous or sero-purulent character.4 In infraglottic oedema it is
said to be fibrinous.
3 According to Sestier, the ary-epiglottic folds are
affected in nearly every case, either alone or together with other
parts.
4 In 90 cases Sestier found the infiltration serous 60
times, sero-gelatinous 6, sero-purulent 9, sero-purulent with plastic
lymph 4, purulent 8 times, sero-sanguineous twice, and sanguineous
once.
The mucous membrane covering the oedematous structures is tense and
discolored; except in very inflammatory conditions it is yellowish,
shimmering, and pallid. On cutting into the diseased parts often but
little exudation takes place, and sometimes even squeezing between the
fingers does not suffice to cause disgorgement.5 After the fluid is
evacuated the parts collapse and the mucous membrane is left wrinkled
and folded.
5 In 23 autopsies Sestier found that incisions into the
oedematous structures made the liquid run out either without any or
with slight pressure 10 times; with repeated pressure, with difficulty
and only in small quantity, 6 times; and not at all, in spite of
repeated incisions and pressure, 7 times.
DIAGNOSIS.—With the laryngoscope, the spatula, and the finger the
seat, the degree, and often the nature of the infiltration can be
determined. A successful laryngoscopical examination may sometimes
require in such cases more than ordinary skill, and there is often so
much tumefaction that the parts are not easily recognizable. The
epiglottis may appear as a thick roundish tumor, or be of a more or
less indistinct horse-shoe shape, overhanging the laryngeal aperture;
the ary-epiglottic folds may be converted into large lateral cushions
pressing against the arytenoid bodies, or be merged with the latter
into huge, irregularly pear-shaped, oval, or globular masses; and the
ventricular folds may be immensely tumefied, or else, by means of the
swelling and the being pushed into a horizontal position of the whole
lateral lining of the upper laryngeal cavity, may be obliterated
altogether. Glottic oedema never occurs except with supraglottic, and
the upper surface of the vocal bands may look elevated, arched, and
bladder-like, even if only the thyro-arytenoid muscles are infiltrated.
In infraglottic oedema there is usually neither epiglottic nor
supraglottic oedema; pads are seen underneath the vocal bands, either
ring-shaped or projecting from side to side toward the middle line, and
fill up to a greater or less degree the rima glottidis. The oedematous
parts have sometimes a pinkish, but usually a yellowish, translucent or
semi-translucent aspect. Accumulation of pus lessens the translucency
and sometimes makes the yellow more marked. Sanguineous
infiltration shows a bluish-red or livid discoloration. In chronic
oedema the color is lighter, sometimes a dirty gray.
I have already explained the proper method of using the spatula. It
reveals in all cases, sometimes best during retching, the epiglottis,
and in many cases the ary-epiglottic folds. With the finger these parts
can be touched, and all the more easily when they are swollen; but
great care must be exercised to avoid provoking by digital examination
a suffocative paroxysm. When felt by the finger the peculiar elasticity
or fluctuation present is unmistakable.
PROGNOSIS.—Laryngeal oedema is always a very dangerous condition—in a
chronic case less so than in an acute one. The prognosis depends
largely upon the causative or accompanying disease. The more local the
oedema and the more promptly medical, and in most instances surgical,
aid can be had, the more favorable is the prognosis, though uncertain
even then. Sometimes a rapidly fatal attack supervenes in a mild,
chronic, or apparently convalescing case. In abscess formation it is
generally favorable unless the underlying disease makes it the reverse.
TREATMENT.—Antiphlogistic treatment of every sort has been recommended
against this dread disease. Its frequently rapid course usually
necessitates primarily topical measures. Even fifty years ago, when
bleeding and tartar emetic were in vogue, Ryland entirely
discountenanced these, and said: "Our chief reliance must be placed on
the local detraction of blood by means of a large number of leeches
applied in the vicinity of the larynx; on the use of blisters, which
should never be put on the front of the neck, as their operation will
interfere with the subsequent performance of tracheotomy should such a
step be necessary, but on the back of the neck or the upper part of the
chest; and on the internal administration of large doses of calomel,
which, either by their purgative effect or by their specific action on
the general system, tend to check the inflammation in the glottis and
to promote the absorption of the effused fluids. These remedies can
only be of use during the early stages of the disease, and experience
shows but too plainly that even then we have far more reason to
anticipate failure than success."
Many years ago it was proposed to catheterize the trachea for the
purpose of allowing air to reach the lungs in this and other diseases
in which the larynx is obstructed; and more recently Hack has shown the
great benefit of using, under sight by means of the laryngoscopic
mirror, Schrötter's dilating hard-rubber tubes in acute as well as
chronic laryngeal oedema. According to him, they do good not only
symptomatically, but also curatively.
Furthermore, we can employ, under the guidance of the mirror or of the
finger, scarifications of the infiltrated structures by means of the
laryngeal lancet, or in its absence of a long bent, sharp-pointed
bistoury covered, except for a quarter of an inch or so from its point,
with adhesive plaster. (For the epiglottis the ordinary gum lancet will
often do.) An abscess is opened in the same way. When the bleeding
following scarification is excessive we use ice internally or
externally, or both; when bleeding is insufficient, steam inhalation,
hot fomentations, etc. To promote absorption we make topical
applications, either before or certainly after the scarification, of a
saturated solution of iodoform in sulphuric ether (drachm ij ad ounce
j), or of a strong watery solution of silver nitrate (scruple ij–drachm
j ad ounce j). Astringents, especially tannin and alum, applied in the
form of spray to parts that cannot otherwise be reached, are advisable;
and antispasmodics and narcotics (potassium bromide and morphine)
should not be omitted in cases complicated with muscular spasm, etc.
The internal administration of fluid extract of jaborandi in drachm
doses or the hypodermic injection of pilocarpine is highly lauded as
promoting absorption; also diaphoretics, purgatives (salines and croton
oil),
etc. From the beginning the patient's general functions
must be regulated and his strength supported by tonics and nutritives,
and any underlying disease amenable to treatment must of course be
attended to. The slow swallowing of pieces of ice is often of great
benefit. In every case that does not visibly improve by the vigorous
carrying out of the treatment hitherto detailed, especially the
catheterization by means of Schrötter's tubular dilators, the ultima
ratio—viz. tracheotomy, particularly inter-crico-thyroid
laryngotomy—must be resorted to without waiting until the patient has
lost much ground by the impediment to respiration. One of the lessons
taught us by pathological investigation is that epiglottic,
supraglottic, and glottic oedema does not extend beyond the upper
surface of the vocal bands: therefore, while in infraglottic oedema,
and when the two conditions supraglottic oedema and infraglottic
coexist, tracheotomy should be performed, in the other cases the
air-passage should be opened by introducing a tube through the
inter-crico-thyroid membrane. This operation is, especially for the
general medical practitioner, much easier, safer, and quicker of
performance, and answers in those cases all purposes. This important
lesson is not heeded by any of the recent authors on the subject.
Indeed, Cohen expressly says: "The trachea is to be opened in
preference to the larynx, as being at a greater distance from the seat
of the disease and less liable to involvement, as well as for the
reason that the disease occasioning the oedema may be extending low
down in the larynx, and therefore exist at the very point usually
selected for laryngotomy." Supraglottic oedema does not extend to the
region of the inter-thyro-cricoid membrane, and the tube may therefore
safely be there introduced.
Perichondritis and Chondritis of the Larynx.
DEFINITION.—Inflammation of the laryngeal perichondrium and cartilage.
SYNONYMS.—Phthisis laryngea of the older authors, Laryngitis affecting
the cartilages, Deep-seated ulcerative laryngitis, Caries cartilaginum
laryngis, Vomica laryngis, Perichondric laryngeal abscess, Necrosis
laryngis. (Some of these names refer to the product or terminal stage
of the disease.)
ETIOLOGY.—Laryngeal perichondritis and chondritis occur either as
idiopathic or as symptomatic or secondary affections. Even the former,
caused by so-called catching cold or exposure to cold and wet while the
system is in a state of lowered vitality, may have a septicæmic basis;
it is much more rare than the secondary. Rühle has remarked that
arytenoid perichondritis may probably sometimes start in the
crico-arytenoid articulation, and in an instance which has come under
my observation this certainly seemed to have been the case. Authors
state that occasionally the inflammation commences in the cartilaginous
tissue itself, instead of in its investment; this is hardly
conceivable. Perichondritis must always precede chondritis, but it
always causes the cartilage to become involved in the morbid process.
Quite often perichondritis and chondritis constitute an extension of a
particular ulcerative disease of the mucous and elastic membranes. In
the great majority of cases the causes are tuberculosis, syphilis,
diphtheria, cancer, lupus, typhus and typhoid fever, small-pox, or else
traumatic occurrences, especially suicidal throat-cutting, decubitus or
other pressure upon the part—as, for instance, the frequent
introduction in an aged subject of the oesophageal sound observed by
Ziemssen, and overstrain of the voice alleged by Flormann. At least
three cases are reported (viz. by Porter, Lawrence, and Eppinger) in
which the disease has been ascribed to the administration of mercury,
and Graves and Stokes remark that in broken-down constitutions,
where large quantities of mercury have been used, chronic laryngitis is
very apt to terminate in ulceration of the cartilages.
The disease occurs oftener in men than in women, and oftener between
the twentieth and fortieth years than at any other age.
SYMPTOMATOLOGY.—I distinguish three stages of laryngeal perichondritis
and chondritis—viz. the inflammatory, suppurative, and necrotic. The
symptoms of the first stage are obscure: the main one is pain, usually
of a boring, burning character, localized according to the precise
cartilage affected, which is increased by functional or other movement
of the part and by pressure from the outside. To the pain there are
gradually added—also depending somewhat upon the precise seat of the
inflammation—cough, dysphonia, and dysphagia. In cricoid
perichondritis—especially when, as is generally the case, the
posterior surface of the plate of the cricoid cartilage is
affected—there is sometimes inflammatory reddening of the pharyngeal
mucous membrane which may extend upward to the palate. Inflammatory
swelling of some part of the cartilaginous framework may be
recognizable in the first stage of the disease by means of the laryngoscope.
The suppurative stage is attended with more swelling of the part
affected, due to accumulation of pus and to collateral oedema. Pain,
dysphagia, or dysphonia, and sometimes irritative, harsh cough may be
much augmented; but, above all, dyspnoea now appears, which sometimes
so rapidly increases that the patient dies asphyxiated unless
tracheotomy is performed.
During the necrotic stage the symptoms of laryngeal stenosis sometimes
persist, and sometimes cease with the expectoration of quantities of
pus containing possibly a part, and occasionally the altered whole, of
the affected cartilage: with continued purulent expectoration the
patient's strength fails, the breath becomes very fetid, and hectic
fever and death may supervene.
Swelling of cervical lymphatic glands, though by no means always
present, has been observed in the early and sometimes only in the later
stages of the disease.
The course of the disease, whether idiopathic or secondary, is either
acute or chronic. It tends either toward abscess-formation, which
predominates, or toward new growth of tissue; for a time sometimes the
one, sometimes the other occurs, and, as a rule, during the former the
process is more acute, and during the latter more chronic: the
proliferated tissue, after being produced, may break down and increase
the amount of pus. When acute, the three stages of the disease follow
each other rapidly, if, indeed, the third be not cut off by the death
of the patient. When chronic, the pus collected is very apt to burrow
and to make fistulous passages and openings internally and externally.
At various points also perichondric hypertrophies, ecchondroses, and
exostoses are apt to occur.
The inflammatory stage can terminate by more or less complete
resolution, though usually some enlargement of the cartilages
permanently remains; recovery can also take place in the later stages,
and leave deformities and produce cicatricial contractions.
PATHOLOGY AND MORBID ANATOMY.—The perichondrium of the larynx is
diseased comparatively oftener than that of any other region of the
body; which, aside from other causes, is partly due to the fact that
the laryngeal cartilages become with increasing age normally vascular
and ossified. The morbid process never affects at one time the whole of
the cartilaginous framework of the larynx, and usually only one
cartilage, or even only a limited portion of one cartilage, except in
the case of the cricoid and arytenoid, which are sometimes together
implicated. Perichondritis does not spread easily. The cricoid is most
frequently affected, next the arytenoid, far less often the thyroid,
and exceedingly rarely the epiglottis.
As already remarked, the inflammation of cartilage and perichondrium
has a great tendency to suppuration—occasionally, though rarely,
proliferation and hypertrophy; or, on the other hand, and more
frequently if the inflammation is a slowly progressing one, the
processes leading to ossification take place. The suppurative stage
follows the inflammatory quickly unless the latter has been
comparatively very slight. A great abundance of pus collects between
the cartilage and its investing membrane. As the former is thereby
denuded and separated from its nutritive vessels, it must become
necrotic. Exfoliated pieces of cartilage are generally found in the
abscess. Caries of adjacent tissues is apt to take place, and oedema of
the surrounding connective tissue, and sometimes far-reaching
destruction, before the perichondrium bursts or becomes destroyed over
a large extent. In cricoid perichondritis, the plate mainly being
affected, the abscess projects mostly toward the oesophagus and the
trachea, or it points outwardly when the narrow portion is involved;
the opening when the abscess has burst is frequently large, and shows a
portion of the necrosed cartilage; sometimes there are a number of
perforations. In arytenoid perichondritis the abscess bulges either
into the interior of the larynx or into the adjacent pyriform sinus;
bursting usually occurs at the posterior portions of the ventricular
folds or near the posterior vocal process, and the undermined edges may
disclose the dead cartilage. In thyroid perichondritis either the
interior of the larynx, the pyriform sinus, or the outside of the neck
is encroached upon.
In the course of the necrotic stage of the disease the laryngeal
framework may cave in, and a stenosis be produced which may quickly put
an end to the patient's life unless tubage—as explained under the head
Oedema—or tracheotomy be performed. A loose piece of dead cartilage
getting into the rima can produce the same fatal effect. Smaller or
larger pieces of necrosed cartilage, sometimes partially or wholly
ossified, have been expectorated, or, post-mortem, found lying in the
respiratory passage, looking dirty-yellowish or blackish. Fistulous
openings may take place in the larynx, pharynx, and in the skin
covering these parts. Gaucher has reported an extraordinary case in
which a perichondritic abscess of the thyroid cartilage had opened into
the vertebral canal, as well as externally by the side of the
sterno-cleido-mastoid muscle. If the perichondritis has followed
deep-going ulcerative destruction of the mucous membrane, the
perichondritic abscess bursts more easily, and less burrowing of the pus
usually takes place.
In the rare termination of healing of the necrotic stage of
perichondritis the loss of cartilage-substance is supplied by
connective-tissue granulation emanating from the perichondrium. Cohen
has reported a case in which there was apparently a reproduction of the
whole cricoid cartilage, the necrosed original one remaining in the
interior of the larynx as a foreign body.
Just as laryngeal stenosis is the grave danger during the continuance
of the disease before the perichondritic abscess has opened from its
protrusion into the laryngeal cavity, together with the accompanying
oedema, and from the undermining of soft parts by burrowing pus, and
after the abscess has opened from exfoliated pieces of cartilage
blocking the interior, or, when eliminated, from caving in of the
laryngeal framework, so laryngeal stenosis is the grave consequence of
the disease from remaining deformity, cicatricial contraction,
ankylosis of the crico-arytenoid articulation, etc. An open
perichondritic abscess may also lead to extensive gangrenous
destruction, and occasionally to subcutaneous emphysema.
Under the microscope the first stage of perichondritis is marked by the
appearance in the fibrous basis-substance of the perichondrium of more
or less coarsely granular corpuscles, the so-called inflammatory
corpuscles. As to their origin, it is well known that Virchow taught
that they are produced by the enlargement, division, and subdivision of
the connective-tissue corpuscles, while Cohnheim claimed that they are
nothing but emigrated colorless blood-corpuscles: in point of
fact, most of them arise from the liberation of the living matter
contained in the basis-substance, by the liquefaction or melting out of
the non-living ingredient, and the increase and division of this matter
into medullary or inflammatory corpuscles which constitute the
so-called inflammatory infiltration. So long as the corpuscles remain
connected by filaments of living matter, the inflammatory process may
terminate by a new formation of basis-substance in hyperplasia—i.e.
in the new formation of connective tissue. When, on the contrary, the
inflammatory corpuscles are torn apart and become suspended in a liquid
exudate, they constitute pus, and then the termination of the
inflammatory process is in suppuration; that is to say, usually in an abscess.
The perichondrium and cartilage are normally so closely connected that
the one tissue passes gradually into the other without definite
boundary-line, and the cartilage participates in the inflammatory
process by a liquefaction of its basis-substance, reappearance of the
living matter therein contained, and the formation of more inflammatory
corpuscles. So long as the inflamed perichondrium remains in living
connection with the cartilage, both tissues may participate in the new
formation of a dense connective tissue, and hyperplasia be the result
of the perichondritis and chondritis. Should, on account of suppuration
at the boundary of the cartilage, the vascularized portion of the
perichondrium become detached, the cartilage, being itself devoid of
blood-vessels, will become dead. Its corpuscles will shrivel, and
together with the lifeless basis-substance become disintegrated. Pieces
of necrotic cartilage may be found lying in the surrounding pus, and,
though usually chondritis has preceded the necrosis, the latter may
ensue without previous change of the cartilage tissue, especially if
the perichondritis runs its course to suppuration rapidly; but in every
case suppurative perichondritis precedes necrosis of the cartilage.
After the elimination of necrosed portions cartilage is as a rule
replaced by newly-formed dense fibrous connective tissue. Some
clinically-observed cases, aside from the remarkable case of Cohen
already mentioned, indicate, however, that, exceptionally, new
formation of cartilage may occur from hyperplastic perichondrium, in
the same manner as new bone is sometimes formed from hyperplastic
periosteum after osseous necrosis.
DIAGNOSIS.—The inflammatory stage may be suspected, rather than
positively recognized, from the peculiar pain if the laryngoscope (or,
in the rare case of thyroid perichondritis, palpation) reveals
enlargement of a part of the cartilaginous structure without much
injection of the mucous membrane. The presence of other symptoms
mentioned, and in the case of cricoid perichondritis the localized
pharyngeal reddening, make the diagnosis more probable. During the
suppurating and necrotic stages the diagnosis becomes certain from the
symptoms I have described, especially expectoration of fragments of
necrosed cartilage, together with direct examination. The laryngoscope
may show the abscess; sometimes the finger or a probe can detect
fluctuation, and frequently through an opening the probe detects the
necrosis. The movement of one or both vocal bands may be affected
either mechanically from purulent accumulation, or from articular
ankylosis, or from interference with muscular attachments or action, or
with innervation. In my hand, and in that of others, a probe introduced
through an external fistula has been seen in the larynx; others have
been able to inject colored fluid and find it in the interior.
PROGNOSIS.—Except in slight cases death is more apt to take place than
recovery. If tracheotomy has saved the patient from impending death,
ultimate prognosis is still unfavorable in severe cases. In idiopathic,
traumatic, and syphilitic cases the prognosis is of course better than
in others in which we have to face grave dangers of the underlying
disease as well. The remaining laryngeal stenosis after recovery
makes the prognosis bad as to the doing away with the tracheotomy-tube,
although it is far more favorable at the present day than it was
previous to Schrötter's success with dilating measures.
TREATMENT.—Throughout the disease the patient's general health and
strength must be carefully attended to, tonics and stimulants used
according to circumstances, and the underlying condition of secondary
perichondritis, such as syphilis, etc., treated secundum artem.
Locally, the treatment during the first stage must be antiphlogistic,
by leeches, ice, etc., and soothing, especially by inhalations.
Afterward, abscesses must, if accessible by means of the laryngoscope,
be opened. Artificial feeding, through either an oesophageal or a
rectal tube, may become necessary. Schrötter's hard-rubber tubes may be
inserted to conduct air to the lungs, but tracheotomy, not laryngotomy,
must be performed if, in spite of this tubage, suffocation threatens.
The methodical dilatation of post-perichondritic laryngeal stenosis
requires special bougies, catheters, hard-rubber tubes, pewter plugs,
and dilators which are not to be found in the ordinary armamentarium of
a medical practitioner; but the proper and frequently successful use of
these can be acquired with patience and perseverance when a case of the
kind presents itself for treatment.
DEFINITION, SYNONYMS, AND
CLASSIFICATION.—Under the name chronic
laryngitis are brought together a number of different diseases of the
larynx which have the character in common that they are more or less
inflammatory and chronic in their course. The various conditions of
chronic inflammation of the mucous membrane (chronic laryngeal catarrh)
prominently belong to this category, but the chronic inflammation of
every other constituent tissue of the larynx, except cartilage and
perichondrium, is included.
The synonyms refer mostly to individual etiological and other factors
not applicable to all cases, as clergymen's laryngitis, phthisical
laryngitis, and many of the designations of different classes.
Chronic laryngitis frequently involves more than one tissue, but
usually one prominently. Histologically, the following kinds of chronic
laryngitis have been distinguished: viz. catarrhal, when simply or
principally the mucous membrane is affected; granulous or glandular,
when the muciparous glands; submucous or parenchymatous, when the
connective tissues underneath the mucous membrane are prominently
implicated; and muscular, when there is chronic inflammation of the
muscular tissue. According to the seat, there will be supraglottic,
glottic, and infraglottic chronic laryngitis. There have also been
described atrophic, hypertrophic, and polypoid chronic laryngitis; dry
and blenorrhoeic or hypersecreting chronic laryngitis; simple, fetid or
ozænic, and ulcerative; phlebectasis laryngea, trachoma, etc.
ETIOLOGY.—Chronic laryngitis is caused in many ways. Frequently it
follows uncured or neglected acute laryngitis. It is apt to occur in
persons whose avocations or habits lead them to strain or otherwise
abuse their vocal organ, to work in an impure or irritating atmosphere,
or to use tobacco or alcohol excessively; and it may depend upon or be
an extension of chronic inflammation of either the naso-pharyngeal or
tracheo-bronchial mucous membrane. Secondarily, it accompanies all
long-continued laryngeal affections, such as phthisis, syphilis, lupus,
etc. Males suffer more often than females, and middle-aged persons more
often than either children or the very old. Boys at the time of puberty
are liable to become affected.
SYMPTOMATOLOGY.—The diseases comprised under the collective name of
chronic laryngitis give rise to various symptoms, of which the chief
are
morbid sensations in the region of the larynx and alteration
of the voice. Unless ulceration have occurred, the morbid sensations
hardly amount to pain, except on acute exacerbation from catching cold
or after long-continued use of the voice. They consist in a sense of
dryness or of pressure, in a tickling or in an unnatural feeling that
cannot be definitely described in words. Though not acute, they are
sufficient to make the patient constantly conscious of their existence
and to induce fruitless efforts at clearing the throat, etc. The
alteration of the voice varies from occasional unsteadiness or veiling,
or a loss of power or purity of tone, to different degrees of
hoarseness, dysphonia, and even aphonia. In singers and public speakers
the disease interferes sometimes with professional vocal efforts only,
ordinary conversation not being affected. The voice is best, sometimes
worst, after a night's rest, and in either instance changes after
moderate use for worse or better as the case may be; but long-continued
exercise is always harmful. The voice is comparatively easily fatigued,
and then the vocal organ becomes positively painful.
In addition to the two chief and constant symptoms there are others
that may or may not be present, and which sometimes assume even greater
prominence than the modification of the voice. Thus, secretion, which
in most cases is very slight, glassy grayish, and viscid, is
occasionally very abundant, yellowish, or darkish, or more rarely still
mixed with streaks of blood and in clumps, though not sticky or dried
into scabs, and is sometimes so fetid that the patient's breath is
exceedingly malodorous. Cough, which in most cases is either absent or
comparatively trifling, barking, or hacking, occasionally is the most
troublesome of all the symptoms. Dysphagia is sometimes present even in
simple or mild cases. In severer cases, in the later stages, especially
in syphilitic and phthisical chronic laryngitis, swallowing becomes
painful and difficult, or even impossible. Dyspnoea occurs only from
accumulations of phlegm in the larynx, and is then lessened after
expectoration, or it may depend upon the diminished lumen of the
laryngeal cavity on account of thickening of the walls, as it is
especially apt to do in subglottic chronic laryngitis, or on account of
so-called polypoid hypertrophies in simple cases, gummata or
cicatricial tissue in specific cases, etc. Dyspnoea may become so
urgent as to require tracheotomy.
PATHOLOGY AND MORBID ANATOMY.—In catarrhal chronic laryngitis there is
congestion of the mucous membrane, dilatation of the blood-vessels, and
altered secretion. The mucous membrane becomes, as a rule,
hypertrophied, tougher, and more firmly connected with the subjacent
tissues. Laryngeal venous congestion (so-called phlebectasis laryngea)
is occasionally, though rather rarely, met with; and still more rare is
a hemorrhage from the surcharged vessels in chronic cases. In granular
or glandular chronic laryngitis—i.e. when the muciparous glands are
prominently involved in the inflammatory process—they form elevations,
making the surface uneven, and the tissues become tenser and more
compact. When the submucous connective tissue takes much part in the
process the hypertrophy is still greater, and not only may the lumen of
the laryngeal cavity become greatly diminished, but projections of
various lengths (the so-called cellular polypi and papillary
excrescences) are apt to occur. The objective term tuberosa is
sometimes added to laryngitis or to the designation for inflammation of
a portion of the larynx; as, for example, that of the vocal bands—viz.
chorditis tuberosa, when small whitish, tumor-like elevations occur.
These, especially on the vocal bands, where they have been described by
Tuerck, Elsberg, Cohen, and others, are also called trachomata. In
cases to which the name muscular chronic laryngitis is given the
muscular tissue has been found prominently hypertrophied. Moura
Bourillou has recorded a case in which the striated fibres of the
posterior crico-arytenoid muscle were converted into fibrous tissue. In
many of
the common cases of catarrhal chronic laryngitis the
alteration of the voice depends upon paralysis of the
muscles—especially the thyroid arytenoid and the arytenoid—directly
caused by the transmitted inflammation and by thickening of the
overlying mucous membrane. In fetid chronic laryngitis there is usually
found excoriation of the mucous membrane, and atrophy. That
erosions—i.e. superficial ulcerations extending no deeper than the
epithelial layer—frequently occur in the course of catarrh is admitted
by everybody, but much unnecessary discussion has been indulged in
concerning the question whether deeper ulcerations of the mucous
membrane can ever take place under these circumstances. It has been
insisted upon that catarrhal ulcerations never occur. This is a
mistake, but it is true that catarrhal ulceration is rare unless the
patient is greatly debilitated or cachectic. Ulcerative chronic
laryngitis in the majority of cases depends upon some cachexia—i.e.
tuberculosis, syphilis, lupus, lepra, etc.
Tuberculous chronic laryngitis—laryngeal phthisis proper—frequently
accompanies pulmonary consumption. Usually it follows, but occasionally
precedes, the latter. Unquestionably, it also occurs, though rarely,
without any disease in the lungs. Anæmia of the laryngeal mucous
membrane is present from the first, and usually persists throughout.
There is a low form of inflammation, swelling of the tissue, and then
ulceration, the ulcers being at first small, and afterward coalescing
to form larger ones. Much destruction may take place, and more or less
oedema is always present. Paralysis of some of the interior laryngeal
muscles may also occur, depending alike upon anæmia and oedematous
infiltration of the muscular substance, or upon compression of the
nerve-tracts by enlarged lymphatic glands (most frequently on the right
side) or upon involvement of the nerves—pleuritic adhesions,
tuberculous deposits, etc.
Syphilitic chronic laryngitis is a local manifestation occasionally of
hereditary, but usually of acquired, syphilis. It may vary from a
slight erythematous condition of the mucous membrane to intense
inflammatory thickening or destructive ulceration, may be accompanied
by laryngeal oedema and pericarditis, and may lead to dangerous
adhesions, cicatrizations, and stenosis. The chronic laryngitis
occurring in lupus and lepra and in malignant diseases of the larynx
partakes of the character of these processes, and is accompanied by
their peculiar thickenings, tuberosities, granulations, and ulcerations.
DIAGNOSIS.—Chronic alteration of voice, local morbid sensation, and
other symptoms mentioned may lead us to suspect the presence of chronic
laryngitis, but are insufficient for diagnosis without mirror
examination. The diagnosis can be positively made only by means of the
laryngoscope, and even by this means requires care. It is of the utmost
importance that the physician make himself perfectly familiar with the
appearance of the healthy larynx by the particular illumination he uses
for examining patients.
A very able laryngoscopist, Carl Michel of Cologne, confesses6 that
he has many times diagnosed chronic laryngitis when none existed, and
explains that with inadequate illumination the contours of the small
vessels run into one another and make the whole surface which they
traverse appear red. In simple chronic laryngitis the redness has a
somewhat livid look; in syphilitic chronic laryngitis it is darker and
more angry-looking; in phthisical cases it is duller, even though the
mucous membrane be congested, while usually it is pale. In both the
latter diseases the swelling is greater, the natural contour of the
parts more changed, and destruction more imminent than in the simple
chronic laryngitis. When oedema is present there is a peculiar
transparent or translucent appearance. In subglottic chronic
laryngitis, especially when much hypertrophy has already taken
place, the color is often quite light grayish instead of red.
6 Practische Beiträge zur Behandlung der Krankheiten des
Mundrachenhöhle und des Kehlkoffes (Leipzig, 1880).
Phlegm found in the larynx may have come from the bronchial tubes or
the trachea; when it is cleared away by cough or otherwise, the larynx
may prove to be unaffected. In all cases of suspected secondary chronic
laryngitis, phthisical, syphilitic, etc., the state of the lungs and
whole respiratory tract, as well as the general health in every
respect, hereditary tendencies, and past diseases, must be carefully
inquired into.
PROGNOSIS.—The prognosis of chronic laryngitis is good as to life
except in broken-down constitutions, neglected exacerbations, and grave
underlying affections; but, even with these exceptions, it can be said
to be favorable as to cure only with expert local treatment and if no
severer tissue-alterations, usually hypertrophic, have as yet taken
place. If the latter have taken place—especially if the submucous
tissues are prominently involved—the organ can seldom be restored to
perfect integrity. For persons in ordinary vocations and situations in
life the recovery that can generally be secured may be entirely
satisfactory, but more exacting demands on the speaking and singing
voice require special measures, including hygienic precautions, to be
carried out carefully, and sometimes to be long continued.
TREATMENT.—Whatever the grade or stage of a chronic laryngitis, the
constitutional condition or proclivity of the patient always requires
suitable hygienic, dietetic, and therapeutic management. The repair of
regional or local morbid conditions may often be confidently entrusted
to such constitutional measures; and it is only when these morbid
conditions resist the influence of systemic treatment, or are of some
special character obviously insusceptible to such influence, that
topical medication or actual surgical procedure becomes requisite in
addition. The accessibility of the interior of the larynx to
instrumental manipulation under laryngoscopic guidance offers great
temptations for topical interference. The result is, that the diseased
larynx is sometimes submitted to unnecessary, and even injurious,
direct attack at the hands of a dexterous manipulator untrained in
general practice, and consequently ignorant of the beneficial influence
of purely constitutional measures upon many local morbid conditions.
While it is highly proper, therefore, to utter a few words of caution,
it is equally proper to assert that many local conditions are entirely
beyond the control of systemic measures, and require topical treatment.
Constitutional Treatment.—Simple or catarrhal chronic laryngitis,
unassociated with special diathesis, is often admirably influenced by
the prolonged administration of some preparation of cubeb; the
oleoresin being preferred by the writer in doses of from fifteen to
twenty-five minims for the adult, three times a day on crushed sugar.
This drug being eliminated in part by the bronchial tract, it seems
especially adapted to exert upon chronic inflammatory conditions of the
aërial mucous membrane that healing process which it is known to exert
on mucous membrane elsewhere. Among other useful constitutional
remedies from which similar service can be expected may be enumerated
compound tincture of benzoin in doses of from thirty to sixty minims
for the adult, three or more times daily; fermented infusion of tar or
tar beer, several ounces daily; and petroleum mass, one to two grains
for the adult, three or four times daily, with pulverized extract of
glycyrrhiza in pill or capsule. In cases with deficient secretion
ammonium chloride is indicated. In cases associated with impaired
digestion, with excess of acidity, the prolonged use of alkaline
mineral waters is advisable; preferably, if convenient, at their
sources. In cases associated with chronic diarrhoea the mineral acids
are indicated. Cod-liver oil, hydrated chloride of calcium, and
preparations of iodine and of arsenic are useful in patients of the
scrofulous diathesis. Iodoform, one grain for the adult, rubbed up with
glucose or some other excipient, in pill or capsule, three times a day,
is often useful in patients with the tuberculous diathesis. Specific
remedies are required for syphilis. In like manner, any constitutional
abnormality is to be systematically attacked.
The functions of skin, kidneys, and intestine are to be maintained as
nearly normal as may be, or even a little in excessive action from time
to time for derivative purposes. Abstinence is to be enjoined from all
exposures or indulgences deleterious to the parts diseased; with as
sparing a use of the voice as is compatible with ordinary domestic or
social demands, and absolute rest for prolonged periods of days at a
time whenever unusual demands have resulted in exacerbating the malady.
Under such treatment many cases of simple catarrhal or glandular
chronic laryngitis may get well, as has been intimated, without any
special local measures.
Topical Treatment.—The difficulty of impressing patients with the
necessity of submitting to these hygienic measures and to dietetic
restrictions, and for avoidance of occupations or habits which favor or
maintain the condition of chronic inflammation, renders topical
treatment necessary in many instances. Direct instrumental medication
requires the personal attention of the medical attendant. Medication by
inhalation or insufflation may be entrusted to the patient or the nurse
in most instances. In instituting a course of topical treatment several
things must be taken into consideration, such as the condition of
hyperæsthesia, hypersecretion, insufficient secretion, congestion,
hemorrhagic infiltration, hemorrhage, hypertrophy of tissue or
tissue-elements, erosion, fissure, ulceration, and excessive
granulation. The first three of these furnish the clue to the nature of
the home-treatment, the remainder to that required at the hands of the
physician. The home-treatment is to be directed to keeping the parts
clean and comfortable; the manipulation of the physician is to be
directed toward overcoming special pathological conditions.
Should secretion be defective, alkaline sprays inhaled at regular
intervals, for a few minutes at a time, tend to augment secretion and
to facilitate the detachment of adherent mucus. For the purpose choice
may be made of the following drugs in the proportion of about five
grains to the ounce for the adult, dissolved in distilled water or
tar-water, with the addition of a sedative when the parts are
hyperæsthetic, or an opiate when they are painful: ammonium chloride,
sodium borate, sodium bicarbonate, sodium chloride, sodium chlorate,
sodium iodide, potassium iodide, potassium chloride. The spray should
be propelled by means of compressed air, with what is known as the
hand-ball atomizer, in preference to steam, the effect of which is too
relaxing in most instances. A few drops of some aromatic or balsamic
product will render the spray more agreeable in many instances. Should
these agents fail, pyrethrum or jaborandi may be found more
serviceable, in the proportion of from one to five minims of the fluid
extract to the ounce of water.
Should secretion be excessive, astringents are indicated; and choice
may be made from alum, five grains to the ounce of rose-water; tannic
acid, two or three grains; zinc sulphate or zinc sulphocarbolate, two
grains; lead acetate, two grains; ferric chloride, one grain; and
silver nitrate, half a grain to the ounce. Personal supervision of the
initial inhalations is requisite to ensure proper use of the spray.
Whether the medicament is to be propelled directly into the larynx by
means of a tube with a vertical tip to be passed beyond the tongue, or
to be inhaled by efforts of inspiration from spray projected
horizontally, will depend upon the skill of the individual using it.
Hard-rubber
spray-producers are furnished with series of tips, so
that either method may be employed. When the horizontal tip is used,
the instrument should be held some distance from the mouth, so that the
spray may be deflected into the larynx by the act of inspiration. When
the tube is placed within the mouth most of the spray becomes condensed
upon the pharynx, and very little can be drawn down into the larynx. As
metallic tubes are liable to become reduced by certain
remedies—ammonium chloride, for instance—tubes of glass or of hard
rubber are to be preferred.
Should a steam apparatus be employed, the patient should remain housed
for half an hour after inhalation, except in very warm weather. In
cases of hyperæsthetic mucous membrane the home inhalation of volatile
remedies daily is often useful. Compound tincture of benzoin,
camphorated tincture of opium, oil of pine, oil of turpentine,
terebene, eucalyptol, creasote, carbolic acid, may be inhaled from a
bottle containing hot water or from a special inhaler, a few drops of
chloroform being advantageously added when there is a good deal of
irritative cough. A few drops of the more pungent volatile substances,
such as terebene, eucalyptol, and creasote, may be dropped on the
sponge supplied with the perforated zinc respirator of Yeo of London,
and the apparatus be worn for an hour or longer continuously. In cases
with excessive secretion and in syphilis, ethyl iodide is indicated as
a remedy appropriately administered by this method. When the parts are
very irritable, a respirator of this kind or some similar contrivance,
or a fold or two of woollen or silk gauze worn in front of the mouth
and nose while in the open air, will often protect the tissues from too
cool an atmosphere, and enable the patient to bear exposure with comfort.
Topical treatment of a more decided character being required, the
physician usually chooses between powder and solution. Powders are
usually propelled by a puff of air through a properly curved tube,
whether from a rubber ball, a reservoir of compressed air, or the
mouth. The mouth allows the most delicate and accurate application, but
the mouthpiece should be protected by a valve from receiving a return
current when the patient coughs. Solutions may be applied by means of
pipette, syringe, brush, cotton wad, or sponge, according to
indications. A fragment of sponge securely fastened to a properly-bent
rod or pair of forceps is the safest and most effectual material for
positive contact against a limited surface, and a brush the best for
painting larger surfaces. The use of the cotton wad involves a slight
risk of leaving a detached shred of fibre in the larynx, but renders
the manipulation less unpleasant to the patient than the use of the
sponge, and is less irritating to the mucous membrane. Spasm of the
larynx is usually excited the first time that a medicinal application
is made within it, and even death by suffocation has followed the
incautious use of powerful agents. Hence strong solutions should not be
used until the tolerance of the parts has been sufficiently tested by
weak or innocuous ones. The remedies which have been employed topically
for intra-laryngeal medication seem to include every available
medicinal agent that could be mentioned, from rose-water to the
incandescent cautery. The list of really useful ones is not very long.
Those upon which the most reliance is placed by the writer comprise
tannic acid (a saturated glycerite), zinc sulphate (thirty grains to
the ounce of rose-water), and silver nitrate (forty to sixty grains to
the ounce) in obstinate and protracted cases of simple chronic
laryngitis; iodine and carbolic acid, singly or in combination (one
grain or more to the ounce of glycerin), and chinoline tartrate or
salicylate (five or more grains to the ounce), in cases attended with
infiltration; iodoform (finely pulverized or in recent saturation in
sulphuric ether) in ulcerative or proliferative tuberculosis; and
iodoform and acid solution of mercuric nitrate (one part to ten or
twelve of water) in progressive ulcerative syphilis resisting
appropriate constitutional treatment. Other astringents in the
simple varieties; resorcin in the glandular, hypertrophic, polypoid,
and tuberculous varieties; chromic acid and incandescent metal in the
circumscribed hypertrophic and in the polypoid varieties; and zinc
chloride and copper sulphate in the syphilitic varieties,—proffer
additional resources. These applications are to be made at intervals of
one day or more, according to results. Hyperæsthesia and pain, whether
of the larynx or of parts adjacent, can usually be subdued by the local
anæsthetic effect of solutions of erythroxyline hydrochloride (2 per
cent. or stronger) applied at intervals of a few hours, or even by the
fluid extract or a strong aqueous infusion of the erythroxylon-leaves.
Before the anæsthetic effect of this drug was known, morphine powder
(one-eighth to one-fourth of a grain, alone or associated with tannin
or with iodoform) or aqueous solutions of morphine salts and of aconite
were employed to relieve pain and obtund sensitiveness. The oleate of
morphine (2 to 4 per cent. solution) and the oleate of aconitine (2 per
cent. solution) are similarly useful. Morphine, by its constitutional
influence, is preferable to erythroxyline in some instances, though
less prompt in its effects. Where ulcerative processes at the top of
the larynx or thereabouts entail odynphagia, these preparations should
be used before administering nourishment. The use of erythroxylon
products may be entrusted to the nurse or to the patient with
comparative safety. Morphine and aconite should be applied only by a
medical attendant or an exceptionally skilled nurse. Before any
medicinal curative or reparative agent is applied the parts should be
thoroughly cleansed of suppurative and secretory products. This may be
done with sprays of alkaline solutions—five or more grains of sodium
borate or bicarbonate, for example—dissolved in pure water, in
tar-water, or in an emulsion of coal tar. An excellent agent,
especially in the presence of pus, is hydrogen dioxide, usually
furnished in a 10-volume solution which should be diluted with two or
more parts of distilled water. It is likewise disinfectant and gently
stimulant to mucous membrane. The manipulations by the physician
preparatory and medicatory should be performed laryngoscopically,
otherwise the entire procedure must be haphazard.
Neoplasmata and fungous growths may require removal should they
interfere with respiration. In the presence of stricture, surgical
interference by tracheotomy may become requisite. Elsberg, according to
the testimony of his assistant, Schweig, seems to have been
particularly favorable to the performance of this operation in
obstinate cases of ulcerative laryngitis of whatever character, and
even in protracted non-ulcerative cases, for the purpose of securing
physiological rest to the parts, although the procedure might not be
indicated to relieve any embarrassment in respiration. The writer's
experience in tracheotomy as a factor in producing rest has not been
favorable, such a result being usually defeated by the cough so
frequently following a tracheotomy, no matter how well-adjusted a tube
may have been inserted. His recommendation, therefore, is limited to
cases of embarrassment to respiration due to stricture or constriction
unamenable to intra-laryngeal interference.
Morbid Growths of the Larynx.
DEFINITION.—Neoplastic formations, benign and malign, in the interior
of the larynx, in its cartilaginous framework, in its
investment-tissues, or upon the exterior of the organ.
ETIOLOGY.—Inflammation of the mucous membrane, local irritation or
injury, ulceration, cell-proliferation, and excessive granulation seem
to be the exciting causes of benign neoplasms. They follow on
laryngitis, whether catarrhal, syphilitic, tuberculous, exanthematic,
toxic, or traumatic. They are quite common, so to speak, several
thousands of cases being on record, and as many or more probably being
unrecorded. Heredity does not seem to play any special part in their
production. They are occasionally congenital, and may be developed at
any age; but they are encountered the most frequently in subjects
between the ages of thirty and sixty years, probably because of the
greater exposure to laryngitis attending the activity incidental to the
prime of life. Males are affected far more frequently than females,
probably on account of greater exposure to sources of laryngitis.
Benign growths are sometimes followed by malign growths in recurrence,
and are sometimes converted into malignity by irritation, whether
physiological, mechanical, or instrumental. Malign growths are
attributed to cold, chronic laryngitis, and traumatism as the initial
exciting causes. Butlin suggests a cryptogamic origin. They are far
more common in males than in females, and occur chiefly between the
ages of twenty-five and seventy, but they have been noted as occurring
exceptionally much later, and even as early as the first year.
PATHOLOGY AND MORBID ANATOMY.—By far the greater number of laryngeal
morbid growths belong histologically to the category of benign
neoplasms, but the important location they occupy often renders them
clinically malign. By far the greater number of benign growths are
papillomas, perhaps fully two-thirds, although Elsberg has reported
that but 163 instances were papillomas out of 310 seen in his own
practice.7 This has been an exceptional experience. Then we have
fibromas, myxomas, adenomas, lymphomas, angeiomas, cystomas,
ecchondromas, lipomas, and composite neoplasms. Laryngeal morbid
growths, too, occasionally undergo the fatty, colloid, or amyloid
degenerations. Papillomas are frequently multiple, and most frequently
sessile, but the other benign neoplasms are most frequently single and
are more often pedunculated. All this class of morbid growths affect
the anterior half of the larynx more than the posterior. They are most
frequent on the vocal bands or very near to them, although they may
occupy any portion of the larynx. They vary in size from the smallest
protuberance to a bulk sufficient to block up the cavity of the larynx
and even project above it. The dimensions of the greater number of
papillomas vary from the size of a pea to that of a small mulberry.
Other benign neoplasms rarely reach the bulk attained by papillomas.
7 Archives of Laryngology, p. 1, New York, 1880.
Malign growths are far less common than benign ones. They comprise both
sarcomas and carcinomas. Sarcomas occur in the varieties of
spindle-celled, round-celled, giant-celled, mixed-celled, fibrosarcoma,
lymphosarcoma, and myxosarcoma. Some attain only the size of small
beans, and few exceed the size of a pigeon's egg. The majority of them
are primary growths. Most of them originate in the interior of the
larynx, whence they may extend by contiguous infiltration, even
penetrating the laryngeal walls. The vocal band and the ventricular
band are the most frequent seat. The epiglottis is a common seat. These
growths appear either in irregular, smooth, spheroid masses, or
nodulated, mamillated, and dendritic. They are much the more common in
males, and occur chiefly in subjects between the ages of twenty-five
and fifty. Their growth is slow for a year or more, and then becomes
more rapid.
Carcinoma is much more common than sarcoma. It is most frequently
primary, and primarily limited to the larynx, but occurs likewise in
extension of carcinoma of the tongue, palate, pharynx, oesophagus, or
thyroid gland. It rarely extends to the oesophagus or penetrates the
laryngeal walls.
Squamous-celled carcinoma or epithelioma is the commonest variety,
large spheroidal-celled or encephaloid being much less frequent, and
small spheroidal-celled and cylindrical-celled occurring still more
rarely. Intrinsic
laryngeal carcinoma is usually unilateral at
first, and most frequently in the left side. Its most frequent seat is
at the vocal band. It rarely occurs below this point, and when it does,
as in the five cases analyzed by Butlin,8 it seems to be at some
point just beneath. Extrinsic laryngeal carcinoma usually begins in the
epiglottis, and sometimes occupies that structure only. It may begin in
a cicatrix in the skin.9 Carcinoma is the more common in males,
chiefly in subjects between the ages of fifty and seventy. It has
occurred within the first year, at three years, and as late as at
eighty-three years. Carcinoma is liable to extend by infiltration of
tissue and destroy all the contiguous and overlying tissues, so that it
may extend into the pharynx or even externally; the large
spheroidal-celled variety presenting the most frequently progressive
ulceration into contiguous tissue, and the squamous-celled, intrinsic
ulceration. Hemorrhage is frequent. Perichondritis, abscess, necrosis,
and fistula take place in old cases.
8 On Malignant Disease of the Larynx, p. 36, London,
1883.
9 Cohen, Transactions American Laryngological Association,
p. 113, 1883.
SYMPTOMATOLOGY.—Small growths in localities where they neither provoke
cough nor interfere with voice or respiration may run their course for
a long time without giving rise to any symptoms at all. Growths of
larger size, pedunculated growths, and growths located upon important
structures give rise to interference with voice, respiration, or
deglutition as may be—to cough, and even to pain. Dysphonia is due to
mechanical interference with vibrations of the edges of the vocal
bands; aphonia, to mechanical interference with their approximation;
diphthonia, to mechanical interference at an acoustic node. These
manifestations may be permanent or intermittent. Dysphonia is one of
the earliest symptoms of carcinoma, and is usually continuous for a
number of months before any other indication. Aphonia in carcinoma is
often due to nerve-lesion. Dyspnoea is due to some considerable
mechanical occlusion of the respiratory tract, whether by the growth
itself or in consequence of oedema or of intercurrent tumefaction. It
is inspiratory rather than expiratory, and subject to aggravation at
night. As with the dysphonia, it varies with the size, location, and
mobility of the growth and the position of the head and neck. It may be
intermittent or permanent; be slight or severe; or it may terminate in
apnoea by spasm, by mechanical occlusion of the calibre of the larynx,
or by impaction of the growth at the chink of the glottis. Marked
encroachment on the breathing-space is not accompanied with as marked
dyspnoea as in acute processes, the parts seeming to acquire tolerance
during the slow growth of neoplasms.
Dysphagia is due to a growth at the top of the larynx or on some
portion of its pharyngeal surface. It is quite frequent in carcinoma,
preceding dysphonia in the extrinsic varieties. It may be associated
with regurgitation of food, drink, or saliva into the larynx,
provocative of paroxysms of suffocation. Cough is due to growths which
project from the vocal bands or press upon them, or to hemorrhage or
accumulation of secretory or suppurative products. Hemorrhage, cough,
and expectoration of bloody and fetid masses are indicative of
carcinoma. Pain is usually due to intercurrent conditions. Aches in the
part and sensations of the presence of a foreign substance are more
frequent. Intense pain is exceptional in benign neoplasmata; it is
often an early symptom in carcinoma, in which it is apt to radiate
toward the ears and along the neck. Epileptic seizures and vertigo are
sometimes occasioned by reflex influence. Exceptionally, large growths
may produce change in the external configuration of the larynx. The
general health is not much involved in benign growths, unless they
interfere seriously with important physiological functions. Impaired
health is far less manifest in sarcoma than in carcinoma. Emaciation,
pyresis, and marasmus eventually occur as constitutional manifestations
of malign growths.
DIAGNOSIS.—Laryngoscopic inspection usually reveals the growth
and furnishes the best means of diagnosis. Intra-ventricular and
subglottic growths may elude detection. Palpation is sometimes
available, especially with children. Palpation with probes under
laryngoscopic inspection is sometimes requisite to determine the
mobility of a growth, its form and seat of attachment, and even its
size. It seems, too, to discriminate a neoplasm from an eversion of a
ventricle. While the histological character of a growth cannot be
definitively decided by laryngoscopic inspection, the varieties present
a series of characteristics sufficiently pronounced for approximative
discrimination. Papillomata are often multiple, usually sessile, and
usually racemose or dendritic. Some are white, but the majority are
red, and the tinge varies from one extreme of the tint to the other.
Some are as small as the smallest seeds; most of them have a bulk
varying from that of a pea to that of a berry; some of them are so
extensive as to appear to fill the larynx or even project above its
borders. They are far the most frequent in the anterior portion of the
larynx, and are often located upon a vocal band. Fibromata are most
frequently single, smooth and pedunculated, and red. Some are white or
gray. Some are vascular. When fully developed they vary in size from
small peas to large nuts. They are more frequent upon a vocal band.
Their development is slower than that of papillomata. Myxomata are
usually single, smooth, pyriform, and pedunculated. They are usually
red or reddish. Their ultimate size varies from that of grains of rice
to that of Lima beans. They are most frequent at the commissure of the
vocal bands. Angeiomata are usually single, reddish or bluish, vary in
size from that of small peas to that of berries, and are most frequent
on the vocal bands. Cystomata are usually globular, sessile,
translucent, and white or red. They are most frequent in a ventricle or
on the epiglottis. Their size varies from that of hempseed to that of
peas. Ecchondromata are usually developed in the posterior portion of
the larynx. Other benign growths are very rare, and do not seem to
present special features for recognition by laryngoscopic inspection.
Sarcomata are usually present as sessile, hard, well-circumscribed
growths, smooth or lobulated. Some are dendritic on the surface, but
not to the extent noticed in papillomata, and their location at the
posterior portion of the larynx would suggest their true character, for
papillomata rarely occupy this position except in tuberculosis.
Superficial ulceration occurs in some cases, but is not extensive.
There is no peculiarity in the color of the mucous membrane, which may
be paler or redder than is normal. The lymphatic glands are not
involved.10 Carcinomata present first as diffuse tumefactions in
circumscribed localities, gradually undergoing transformation into
well-formed growths, then nodulation, and then ulceration. Meanwhile,
especially in extrinsic varieties, the submaxillary and the cervical
lymphatic glands become successively involved and tumefied.
Squamous-celled carcinoma becomes pale, wrinkled, and nodulated, and
sometimes dendritic. Large spheroidal-celled carcinoma becomes
nodulated, dark, and irregularly vascular, and finally ulcerated,
perhaps at a number of points. In the ulcerative stage of carcinoma of
the epiglottis and of the interior of the larynx discrimination is
requisite from syphilis and from tuberculosis. In all cases of doubt as
to malignancy, laryngoscopic inspection should be supplemented by
microscopic examination of fragments detached for the purpose. The
early detection of sarcoma may lead to surgical measures competent to
save life—a remark applicable, perhaps, in a far more limited degree
to intrinsic carcinoma.
10 Butlin, op. cit., p. 14.
PROGNOSIS.—The prognosis is usually good in benign growths submitted
to proper surgical treatment. Left to themselves or treated
medicinally, the prognosis is bad both as to function and to life. Such
growths are occasionally expectorated after detachment during cough or
emesis. Some
occasionally undergo spontaneous absorption. Some
remain without change for years. Most of them enlarge and compromise
life as well as function. Recurrence occasionally follows thorough
removal, and this recurrence is occasionally malign in character.
Repullulation frequently follows incomplete removal. The prognosis is
favorable in sarcomata, provided thorough eradication can be
accomplished by surgical procedure. Incomplete removal is followed by
repullulation or recurrence. Unsubmitted to operation, sarcoma will
destroy life either mechanically by apnoea or physiologically by asthenia.
The prognosis is unfavorable in carcinoma. Recurrence takes place as
the rule despite the best devised resources of surgery. Intrinsic
carcinoma offers some hope of success to the surgeon; extrinsic
carcinoma, little if any. Life is shortest in the large
spheroidal-celled, and longest in the small spheroidal-celled variety,
other conditions being equal. Death may take place by apnoea or
asthenia, as in sarcoma, or by hemorrhage, collapse, or pyæmia.
Submitted to tracheotomy at the proper moment in cases in which death
is threatened by occlusive dyspnoea, life is prolonged and suffering
mitigated. The fresh lease of life is longest in the squamous-celled variety.
TREATMENT.—The essential treatment is surgical, and to surgical works
the reader must be referred for details. Suffice it to say that when a
benign growth is small and does not embarrass respiration, it need not
be attacked at all, unless its interference with the voice deprives the
patient of his means of livelihood. The majority of benign growths are
accessible to instruments passed through the mouth. Some require
external incision into the larynx, whether partial or complete. The
intra-laryngeal procedures in vogue include cauterization, both
chemical and by incandescence, incision, abscission, crushing,
brushing, scraping, and evulsion. According to the character and
location of the growth, direct access from the exterior is practised by
infra-hyoid pharyngotomy, by partial or complete thyroid laryngotomy,
mesochondric laryngotomy, cricoid laryngotomy, complete laryngotomy,
laryngo-tracheotomy, or tracheotomy, as may be indicated.
The thorough eradication of sarcomata usually requires a direct access
by section of the thyroid cartilage or even of the entire larynx. This
procedure failing or appearing insufficient, partial or even complete
laryngectomy may be necessary. Temporizing is of no avail.
The treatment of carcinoma is palliative, unless it be decided
advisable to attempt eradication, which may offer some chance of
success in intrinsic carcinoma still confined to the larynx.
Laryngectomy may be unilateral in some instances, and must be bilateral
in others. Unilateral laryngectomy is the more hopeful. Eradication
proffers no hope in cases of extrinsic carcinoma in which the growth
has passed the boundaries of the larynx. After recovery from the
laryngectomy an artificial appliance may be adjusted to the parts for
the purpose of supplying a mechanical method of producing sound in the
larynx for speaking purposes. Should no radical procedures be
instituted, treatment is relegated to general principles, with
prophylactic performance of tracheotomy in the presence of dangerous
occlusion of the larynx. The voice should be used but little. All
sources of laryngitis should be avoided. Ergot or hamamelis may be
given to restrain hemorrhage, and morphine to relieve pain and secure
sleep. Sprays can be used to keep the parts free from morbid products.
Erythroxyline may be applied to produce local anæsthesia as required.
Semi-detached portions of growth may be removed from time to time.
Nourishment may be given by the bowel when necessary, and so on as in
other diseases of the larynx in which the functions of respiration and
deglutition are seriously impaired. Medicinally, arsenic may be given
in the early stages, as that drug is conceded to possess some slight
retarding influence on the growth of carcinoma.
Lupus is rare in the larynx. It usually occupies the structures above
the vocal bands. It is most frequent in females, and usually associated
with cutaneous lupus.
ETIOLOGY.—Scrofulosis and syphilis seem to be the predisposing causes.
Climate may have some influence. The reason of the special proclivity
of the female is undetermined. Of 9 reported cases, records of which
are before the writer, 8 were in females.
PATHOLOGY AND MORBID ANATOMY.—Laryngeal lupus is usually an extension
of the disease from the upper lip or the nose, extending along the
nasal passages, pharynx, and palate. Destructive ulceration takes
place, with irregular cicatrization and the formation of hard nodules
of hyperplastic tissue of irregular conformation, varying from the size
of hempseeds to that of small peas, similar to the cutaneous buccal and
pharyngeal nodules.
SYMPTOMS.—These include dysphonia, dyspnoea, dysphagia, and cough.
Pain is exceptional.
DIAGNOSIS.—Laryngoscopic inspection reveals the characteristic
nodulation, the nature of which is inferred from the coexistence of
external lupus. The disease may be confounded with lepra, syphilis,
tuberculosis, or carcinoma. Discrimination from syphilis is the most
difficult, and is predicated chiefly on its slow progress and on the
absence of constitutional manifestations.
PROGNOSIS.—This is unfavorable. The reported cures seem to have
occurred only under the influence of antisyphilitic treatment.
TREATMENT.—The prolonged use of cod-liver oil and of potassium iodide
seems to be more beneficial than any other systemic treatment.
Destruction of the nodules and ulcerated tissues is indicated when the
diseased structures are sufficiently circumscribed and accessible. This
may be done with the sharp spoon or with the electric cautery. Silver
nitrate and iodine have been lauded as topical remedies.
Lepra is rare in the larynx.
ETIOLOGY.—Its cause seems to be climatic. In Europe it is most
frequent in Norway and Sweden, and in America in Cuba and the West Indies.
PATHOLOGY AND MORBID ANATOMY.—It is always associated with cutaneous
lepra, and usually with lepra of the nasal passages and the pharynx.
According to Schroetter's observations, laryngeal lepra occurs as small
connective-tissue nodules on the epiglottis or in the interior of the
larynx, or as uniform thickenings, general or circumscribed. These may
lead to stricture. Extensive ulceration may ensue.
SYMPTOMS.—Dysphonia, aphonia, dyspnoea, cough, and local anæsthesia
are the main symptoms. Pain is infrequent.
DIAGNOSIS.—This depends upon the external manifestations of lepra and
the laryngoscopic detection of the characteristic thickenings and
nodulations.
PROGNOSIS.—This is unfavorable.
TREATMENT.—This must be conducted on general principles. Elsberg
commended iodoform topically and gurgun oil internally.
BY LOUIS ELSBERG, A.M., M.D.
Disease originating in or confined to the trachea is rare. It hardly
ever follows tracheotomy unless the shape of the canula or its relation
to the windpipe be improper; the normal tracheal mucous membrane
probably resists cadaveric disintegration longer than any other mucous
membrane of the body. But morbid processes of the larynx often extend
downward, and those of the bronchial tubes still more frequently
upward, so that the trachea is found affected in connection with both.
Indeed, in what is ordinarily simply called bronchitis (see article on
BRONCHITIS) the windpipe is seldom free from the inflammatory condition.
We shall here consider Inflammation, Ulceration, Morbid Growths,
Stenosis, and Dilatation (hernia, fistula). Tracheotomy may have to be
performed in any of these diseases to prevent impending suffocation,
and in some to gain access to the part for further treatment. (See
article on TRACHEOTOMY.)
Tracheitis is either simple or complicated, and acute or chronic.
DEFINITION.—Inflammation of the windpipe limited to the mucous membrane.
SYNONYMS.—Catarrhal tracheitis, Tracheal catarrh.
Its ETIOLOGY may be gathered from the corresponding sections on
Catarrhal Laryngitis and Bronchitis.
SYMPTOMATOLOGY.—In acute catarrhal tracheitis local irritation is
complained of, varying according to the severity of the case from a
mere tickling sensation to soreness and pain. This morbid sensation is
increased by pressure on the part, and with it there is cough and
expectoration—the former either brassy and hacking, or paroxysmal and
violent; the latter at first scanty, but very soon more copious than
when the larynx alone is affected, although much less so than when the
inflammation involves the bronchial tubes at the same time. The
sero-mucous secretion gradually becomes muco-purulent or even purulent.
When inflammation is confined to the trachea there is no alteration of
the voice, and, except in children, in whom the calibre of the windpipe
is proportionately small, usually no or only very slight dyspnoea. In
mild cases there are no constitutional disturbances. Severe cases are
accompanied by
the febrile symptoms of a bad cold. The disease
runs its course in from a few days to a week or two.
Uncured or too frequently repeated attacks of acute catarrh of the
windpipe lead to chronic tracheitis, occasionally with considerable
hypertrophy of the mucous membrane. In mild cases the cough and
expectoration are less than in the acute disease, but persist, with
exacerbations in cold, damp weather; in other cases the cough is more
frequent, and the expectoration either thick, glutinous, and scanty, or
else thin, frothy, or glairy, semi-transparent, and abundant. The
separation by forcible paroxysmal coughing of accumulated adherent
tough secretion from the tracheal mucous membrane has been observed to
cause not only slight dyspnoea, but even the dangerous suffocating
attacks of foreign bodies in the larynx. In color the sputa vary from
gray to green and yellow; occasionally they are streaked with blood;
sometimes they are without taste or odor; sometimes they are nauseous
and fetid. Frequently patients with chronic tracheitis complain of "a
sort of tightness at the root of the neck." In some cases a sense of
dryness in the region of the trachea is the principal or the only
symptom complained of, and this may alternate with, or even actually
coexist with, occasional hypersecretion of tracheal or bronchial mucus.
In chronic bronchitis and senile pulmonary emphysema mucorrhrea and
cough usually depend to some extent upon the chronic tracheitis that is
present.
PATHOLOGY AND MORBID ANATOMY.—The pathological characteristics of
simple tracheitis are hyperæmia, active or passive, swelling, and
increased secretion of mucus. There is no fibrinous exudation.
Acute inflammation causes the mucous membrane to become softened,
swollen and red, either uniformly or in points or patches, frequently
with ecchymoses and catarrhal erosions, more perceptible in the lower
than in the upper portions of the trachea. Scanty secretion sometimes
lies upon the surface in pearl-like drops, which might be mistaken for
solid elevations only that they can be wiped off.
In chronic inflammation the redness is more dull, reddish-blue or
grayish; the secretion, sometimes more scanty and sometimes more
abundant, is puriform and usually spread out over larger portions of
the surface; and the glands are enlarged and prominent, with their
ducts so dilated that their mouths are readily visible, sometimes, to
the naked eye, and always with a low-power lens, and the rest of the
tissue is hypertrophied, especially at the back wall of the trachea.
Catarrhal tracheal ulcers are exceedingly rare, superficial, and of but
slight extent, but they do occur, and are usually situated on the
intercartilaginous membrane.
DIAGNOSIS.—Tracheoscopy, a modification of laryngoscopy, can alone
determine with certainty whether, and to what extent, the trachea is
inflamed. Unfortunately, very few practitioners have as yet mastered
this method of examination, which, though really not more difficult
than laryngoscopy, requires greater illumination (necessitating under
some circumstances a mirror of longer focal distance) and different
relative position of patient and operator. (See article by Seiler.)
Figs. 25 and 26 show the tracheoscopical images of a case in which
there was intense acute tracheitis. The anterior wall is seen in Fig.
25, and the posterior in Fig. 26; on both, but especially the latter,
clumps of phlegm and ramifying injected blood-vessels are distinctly
seen. In many cases, by means of the stethoscope, either dry sonorous
or mucous râles may be heard over the windpipe; at other times we may
be aided in coming to a conclusion by the presence of
dysphagia—increased when the chin is raised and diminished when the
chin is pressed on the chest, as pointed out by Hyde Salter—and by the
morbid sensations, increased by pressure, in the region of the windpipe
when there is cough and expectoration.
|
FIG. 25.
|
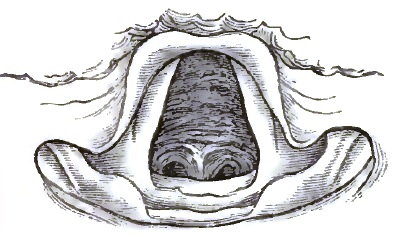
|
|
Acute Tracheitis: anterior wall.
|
|
FIG. 26.
|
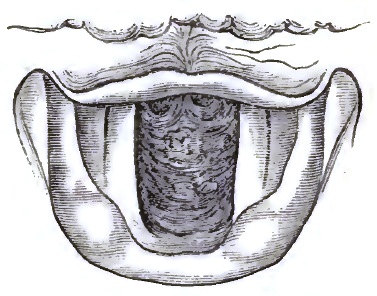
|
|
Same case as Fig. 25: posterior wall.
|
PROGNOSIS.—Simple tracheitis, though occasionally not without danger
in extremely young and very old patients, rarely if ever destroys life.
Under good hygienic circumstances it frequently gets well of itself,
and it does not usually produce sufficient swelling or hypertrophy to
cause stenosis. It is, however, when severe, an annoying disease, apt
to recur, and, unless properly managed, difficult to eradicate.
TREATMENT.—Tracheitis is treated very much like bronchitis confined to
the larger tubes, only that local measures are more prominently
applicable, especially in chronic cases. Frequently, when acute, the
disease may be arrested by a Dover's powder, a warm bath, and a
diaphoretic drink at night, with hygienic attention, regulation of
systemic functions, and soothing applications, such as inhaling simply
vapor of water or medicated water, or using warm-water poultices
externally. Expectorant mixtures, containing ipecacuanha, sanguinaria,
squills, or senega, may be given, according to the age and condition of
the patient, with matico and the like, when the secretion is abundant,
and with ammonium acetate or sodium bromide (potassium carbonate or
ammonium carbonate where there is depression) or tincture of aconite
(especially when fever is present), or a very minute quantity of
tincture of veratrum viride, when there is much dryness. Inhaling the
steam arising from a pint of hot water (160–170° F.) containing 10 grs.
of extract of conium, 1 drachm of compound tincture of benzoin, and
half a drachm of ammonium sesquicarbonate, or inhaling nebulized
solution of potassium bromide, 10 to 20 grains to the ounce, or fumes
of evolving ammonium chloride or of nitre-paper, is very serviceable,
as well as placing a mustard plaster or a hot poultice on the upper
part of the chest (not directly over the windpipe) and on the back of
the neck or between the shoulders. Some patients require for several
days to take daily from 8 to 10 grains of quinia sulphate, then a
smaller quantity, care being taken not to discontinue the remedy
suddenly. Smoking eucalyptus-leaves, with much inhalation of the smoke,
is useful in protracted cases. In chronic as well as acute tracheitis
not only balsamic, anodyne, and astringent inhalations either of
vapors, or of liquids nebulized by the various spray-producers are in
vogue, but also insufflations of powders, injections of liquids, and
touchings with the sponge or cotton-wad probang or tracheal applicator.
Powders should never or only rarely (as, e.g., morphia,
1/16–1/8 of a
grain, when the cough is troublesome, etc.) be blown into the trachea;
injections and touchings should be made use of only after the operator
has acquired the necessary skill to apply them by means of the mirror.
A few drops of a solution of silver nitrate, varying in strength
inversely as the chronicity of the case from 5 grains to 60 to the
ounce of water, thus accurately applied at proper intervals of time,
have proved successful in otherwise intractable cases. In chronic
tracheitis general tonic treatment must be combined with the local, and
attention be paid to possible coexistent cardiac and
broncho-pulmonary affections or other morbid conditions. In some cases
it is advisable to administer potassium iodide; in rheumatism, sodium
salicylate; in gout, colchicum. The utility of producing alkalinity of
the blood (as by giving alkaline mineral waters to drink, etc.) has
received a new and direct support by Rossbach's recent observations of
diminution of the blood-supply and of the secretion in the tracheal
mucous membrane of cats whose blood was made alkaline by injecting
sodium carbonate into the femoral vein.
Patients subject to tracheitis should observe all the precautionary
measures of so-called bronchitics as to sponging, bathing, and friction
of the body, wearing a respirator, clothing, exercise, habits, etc.
Under this heading are here classed together all inflammatory
conditions of the windpipe differing from simple or catarrhal
tracheitis. In these, other tissues may be affected as well as the
mucous membrane. In exanthematous, erysipelatous, and exudative
tracheitis the mucous membrane is prominently involved; in oedematous
and phlegmonous tracheitis, the submucous connective tissue; and in
perichondritic and chondritic tracheitis, the cartilages and their
investing membrane. The latter forms are connected with suppurative and
ulcerative processes, and, unless traumatic, almost never occur, except
in phthisical and syphilitic tracheitis. I shall speak of them under
the head of Ulceration.
The tracheitis of measles and scarlatina consists in an acute catarrh,
with sometimes considerable desquamation of epithelium, erosion, and
capillary hemorrhage. In cases of small-pox in which the larynx is
affected, the same disease may extend into the trachea, varying in
severity from a congestion of the mucous membrane to an intense
pustular process. Erysipelas of the larynx may also involve the
windpipe, and when it does is exceedingly dangerous. More than half a
century ago Gibson observed in an epidemic of erysipelas that when it
spread to the trachea it generally proved fatal.1 Tracheal oedema is
extremely rare even when the larynx is oedematous. Phlegmonous
inflammation and abscess have been observed in a few instances.
Tracheal diphtheria is usually an extension of diphtherial disease of
the larynx. Without entering into a discussion of the nature and cause
of diphtheria, as either a local or general disease, it is here
sufficient to refer to the fact that while in simple inflammation of
mucous membrane no fibrinous exudation takes place, certain poisonous
irritations lead to the exudation of lymph which infiltrates the tissue
and may form a pseudo-membranous deposit upon it: experiments have
proved that ammonia, chlorine, and, certainly, bacteria, are able to
produce this. In laryngo-tracheal diphtheria or croup the disease most
frequently commences in the pharynx, occasionally in the larynx, and
much more rarely in the trachea.
1 Transactions of the Edinburgh Medico-Chirurgical
Society, vol. iii., 1828.
The treatment of each of these forms of complicated tracheitis is the
same as the treatment of the corresponding form of laryngitis.
Tracheal ulcers are just as multiform as laryngeal ulcers, but far more
rare. Like inflammation, they may occur by extension from above or
below,
and only those following localized morbid conditions are
certain to have arisen in the trachea. Under the head of Inflammation
it has been stated that simple catarrhal ulceration does occasionally
occur; of this there is really no doubt, but some writers have denied
it and thrown the whole subject into great confusion. It is true,
however, that a tracheal ulcer has usually a so-called dyscratic base,
and either is diphtherial or phthisical (tuberculous) or syphilitic or
lupoid or leprous or carcinomatous, or else comes from extraneous
causes; as, for instance, from traumatic ulceration or extension or
perforation from neighboring abscess, etc. There are two kinds of
ulcers—viz. one in which the molecular death of tissue proceeds from
the surface inward, and another in which it proceeds from within to the
surface. Catarrhal ulcers, as well as ulcers from decubitus after
tracheotomy, from pressure of the canula, belong to the first kind;
when involving only the epithelium or the epithelium and the layer
immediately underneath it the name erosions is given them; and if it
were true that catarrhal erosions never penetrate to the deeper
structures, it would be justifiable to say that there are no catarrhal
ulcers, but only erosions: they do, however, penetrate, and sometimes
to great depths. In the second kind of ulcers the epithelium is at
first normal or intact, and the loss of substance of underlying tissue
in consequence of inflammatory processes in the mucosa, submucosa, or
perichondrium affects the epithelium secondarily. This occurs whenever,
from any cause, there is primarily caries of cartilage or suppuration
of submucous tissue, especially in typhoid conditions, in phthisis, and
in syphilis.
|
FIG. 27.
|
|
|
Tuberculous Ulceration of the Trachea, as seen during life.
|
|
FIG. 28.
|
|
|
Same case as Fig. 27: post-mortem appearance.
|
|
FIG. 29.
|
|
|
Syphilitic Ulceration of Trachea, as seen during life.
|
|
FIG. 30.
|
|
|
Same case as Fig. 29: post-mortem appearance.
|
The seat of tracheal ulcers is usually the posterior wall and the lower
portion, unless the upper portion is affected by extension from the
larynx or by pressure from a tracheotomy-tube. They are found also in
other portions, and sometimes are so numerous that they give to the
membrane a sieve-like appearance. Occasionally they denude some of the
tracheal rings. In shape they vary, being mostly irregularly circular
or oval, and excavated or scooped out; in size they vary from that of a
pin's head to that of a marble. In tuberculosis they are generally
small and numerous, have a pale background, and are occasionally
confluent, while in syphilis they are usually isolated and large, very
destructive, and apt to cause contractions or other deformities by
partial or extensive cicatrization. Such contracting ray-like
cicatrices have more than once produced fatal stenosis.
The SYMPTOMS are frequently obscure, but local pain and irritation are
usually, purulent or muco-purulent sputa are sometimes, present. The
diagnosis is difficult unless tracheoscopic examination reveals the
condition. Fig. 27 shows the tracheoscopical image, and Fig. 28 the
post-mortem appearance, of a case of tuberculous tracheal ulceration on
the upper portion of the front wall, while Figs. 29 and 30 show the
image during life and the appearance after death of a case of
syphilitic ulceration. In Fig. 30 the posterior wall is seen with the
ulcers, and below them a star-shaped cicatrix.
The PROGNOSIS generally depends upon the underlying disease, and is
grave because the latter is. Perforation may take place, as well as
cicatrization and hypertrophy, and either process may lead to a fatal
issue. In a number of instances post-mortem examination has shown that
tracheal ulceration may produce surprisingly great ravages before
destroying life.
TREATMENT, like the prognosis, depends somewhat upon the disease
underlying the ulceration. Pain is relieved by anodyne, and
cicatrization promoted by alterative inhalations, as of nebulized
glycerated solutions of morphine, ethereal solution of iodoform,
iodinic preparations, oil of solidago, citronella oil, etc. Catarrhal
ulcers heal without special treatment with the subsidence of the
catarrhal inflammation. In syphilitic ulceration, stenosis from
cicatrization is to be dreaded, and specific constitutional treatment
is the main reliance. The internal administration of cod-liver oil has
been found of service in nearly all cases of tracheal ulceration,
especially in phthisis, lupus, etc. Appropriate general treatment must
be combined with the local.
DEFINITION.—Tumors, benign or malignant, growing from the wall and
projecting into the interior of the windpipe. Inversion of the mucous
membrane forming a protrusion into the interior will be spoken of under
the head of Stenosis; and tumors of other organs extending into the
trachea, such as cancer of the oesophagus, lymphatic glands, thyroid
body, etc., are excluded from consideration under the present head.
FREQUENCY OF OCCURRENCE.—Aside from post-tracheotomic
granulation-tumors, which with careless tracheotomy or after-treatment
occur often, the disproportion in the frequency of laryngeal and
tracheal morbid growths is even greater than that of other laryngeal
and tracheal affections. I have met with only eight instances of
tracheal morbid growths, strictly so called, in a special practice
during more than twenty-five years. This is exclusive of
post-tracheotomic vegetations and tumors from contiguity.
ETIOLOGY.—Local irritations and chronic inflammatory conditions seem
often, if not always, to be the forerunners of tracheal tumors, but the
real cause of the latter is unknown. Recently it has been suggested
(see the article on LARYNGEAL TUMORS) that the ever-present bacilli
play a rôle in the production of morbid growths as well as in that of
other diseases. As it is known that some parasitical organisms on
plants use up their nidus very slowly, with the formation of peculiar
excrescences, while others very rapidly destroy the tissue of their
host, it would be easy to suppose that some such difference in the
micro-organism causing the tumor determines its benign or malignant character.
Post-tracheotomic vegetations may arise from the irritating pressure of
a
tracheotomy-tube, especially from the use of a fenestrated tube
or a tube ill fitted to the patient. Some observers are of opinion that
such tumors existed before the performance of the operation, and,
indeed, led to it, even though the supposed reason may have been
laryngeal or some other tracheal disease. While it cannot be denied
that such may have been the case sometimes, there is no doubt that in
other instances—and not only in those in which the vegetations "always
grow from the cicatrix" (Petel)—they are truly caused by the
operation, or by the wearing of the tube, especially if it be in any
way unsuitable as to size, form, etc.
SYMPTOMATOLOGY.—The symptoms of tracheal tumors are local irritation;
tickling or other morbid sensation, sometimes inducing and sometimes
not inducing cough; and encroachment upon the
breathing-space—dyspnoea—depending on their precise seat, size, and
rapidity of growth. It is usually difficult for the patient to specify
the beginning of his trouble, because, on account of the large size of
the windpipe, dyspnoea generally comes on very gradually. An accidental
catarrhal condition of the tracheal mucous membrane from a cold usually
first arrests the patient's attention. The very great diminution of the
calibre of the tube that the patient can bear when the tumor enlarges
slowly is sometimes astonishing. Unless the tumor is pedunculated (so
that expiratory efforts can throw it up into the larynx), which is
generally not the case, expiration and inspiration are equally
affected, both becoming gradually more and more labored and noisy.
Sometimes the act of swallowing large morsels brings on an increased
dyspnoea; sometimes respiration is accompanied by a sort of valvular
sound. Cough is frequently, but not always, present, and depends,
together with expectoration, upon either coincidental catarrhal
condition or irritation from the tumor: in the latter case it is
essential, dry, and persistent, and may vary with the position of the
patient. Sputum may be bloody and even contain shreds of the tumor, as
in similar cases of laryngeal growth. With increase of the tumor the
voice becomes weak and suffers in extent of range, as in other cases of
tracheal stenosis; the same is true of the diminished rising and
falling of the larynx. The course and duration of the disease vary
considerably with its nature. I have observed a tracheal fibroma to
remain stationary for eight years, when the patient died from other
causes and the diagnosis was confirmed post-mortem; and, on the other
hand, a cancer to grow so rapidly that the patient died from
suffocation within five months of its first causing the slightest
symptom. If not relieved, suffocatory paroxysms, with or without
consequent bronchitis and pneumonia, lead to a fatal termination.
PATHOLOGY.—As in the larynx, so in the trachea, the pathological
character of neoplasmata is generally that of papilloma. Of my eight
cases, all observed during life, four were papillomatous (two examined
microscopically after successful extirpation, one post-mortem, and one
in situ macroscopically only), one was a fibroma, microscopically
examined, one an osteo-chondroma, one a sarcoma, and one a carcinoma,
the three last having been examined post-mortem.
Of non-malignant tracheal tumors observed by others, the large majority
were papillomata; next in number come fibromata. Aside from these two
kinds of tracheal tumor, the cases recorded in literature are the
following: Rokitansky more than thirty years ago described tracheal
enchondromata found after death; and Cohen discovered in the corpse of
a phthisical patient a number of small enchondromata on the central
portions of the tracheal cartilages. Steudener, Demme, Wilks, Chiara,
and Eppinger have observed, post-mortem, tracheal osteomata. Gibbs has
described a tracheal cystic tumor2 seen with the laryngoscope;
Müller, under the guidance of Gerhardt, a myxo-adenoma observed
tracheoscopically and carefully studied during life and after
death; and Eppinger has recorded a case of post-mortem tracheal
adenomata and cysts, Simon having previously found three similar tumors
on dissecting a new-born tigress. Virchow speaks of the occurrence of
retro-tracheal retention-cysts, and Gruber has observed several; but
there can be no doubt that at least some of the tumors thus described
are nothing but circumscribed dilatations of the tracheal mucous
membrane—practically, dilated mucous glands. As to malignant tumors,
in addition to my two cases Schrötter has reported two cases of
sarcoma, and Labus one of fibro-sarcoma, while Rokitansky, Klebs, Koch,
Schrötter, Langhans, and Mackenzie have described cases of carcinoma.
2 Cohen questions whether this was a cyst or an abscess. It
burst spontaneously.
Cases of cancer of the oesophagus, which involve the trachea—excluded,
as before stated, from present consideration—are, comparatively
speaking, by no means rare, and are apt to establish a fistulous
communication between the two tubes.
DIAGNOSIS.—The symptoms mentioned are those common to nearly all cases
of tracheal stenosis, and will be referred to again under that head.
Tracheoscopy alone makes the diagnosis certain; unless when the seat of
the disease is ascertainable without, its nature is shown by the
expectoration of portions of the tumor. The first case of tracheal
tumor ever diagnosed during the patient's life was observed by means of
the mirror by Tuerck in 1861; but it is very difficult in the mirror to
estimate distances as to depth, and unless the number of tracheal rings
above a tumor can distinctly be counted, a growth in the lower cavity
of the larynx may readily be mistaken for one in the trachea, and vice
versâ. Catheterism of the trachea shows the distance at which the tumor
is situated, sometimes very accurately, but it is dangerous unless
performed under the guidance of the mirror, and even then requires
great care. The introduction without the mirror of a probe or sound for
the same purpose is still more dangerous and unjustifiable, while with
the mirror it is perfectly safe in proper hands. Localized protrusion
of the mucous membrane into the interior is the condition which most
simulates tracheal tumor. (Compare Fig. 32.)
|
FIG. 31.
|
|
|
Papilloma of Trachea.
|
The pathological nature of a tracheal tumor can sometimes be determined
in situ with more or less probability. Without microscopical
examination it is not always possible to say whether a growth is benign
or malignant unless the mass has advanced to ulceration, and then
specific disease must be excluded by the history and concomitant
symptoms. Papillomata have a peculiarly uneven surface; fibromata are
usually more smooth. With equally good illumination, tumors of the
trachea resemble tumors of the larynx, and may be similarly
differentiated. The former are almost always non-pedunculated, or at
least none of those hitherto observed have had a long pedicle. Their
seat is generally the posterior wall, or the cicatrix of the anterior
wall after tracheotomy. In Fig. 31 is seen the tracheoscopic appearance
of one of my cases of tracheal papilloma.
PROGNOSIS.—The prognosis is always unfavorable in malignant cases, and
also in non-malignant when the tumor grows rapidly or has already
attained a large size. The introduction of the laryngoscope has
bettered the prognosis, inasmuch as in many cases early recognition
enables us, by performing tracheotomy, to prevent sudden death from
suffocation, and also because by the aid of the mirror removal has been
accomplished through the natural passages.
TREATMENT.—Removal of a tracheal tumor through the natural passages
by means of either cutting or cautery instruments requires so
much special ability on the part of the operator that it need not be
described in detail in a work designed for general medical
practitioners. When the tumor is situated above a point at which
tracheotomy can be judiciously performed, no physician worthy of the
name should hesitate to lay open the trachea in any case in which
suffocation is impending. Removal of the tumor by surgical operation
after opening the windpipe may be attempted or not according to
circumstances, but in all cases palliative measures by sedative
inhalation and otherwise may be resorted to, and the patient's general
health, especially in malignant cases, must be kept up as much and as
long as possible.
DEFINITION AND PROXIMATE ETIOLOGY.—Stenosis is narrowing or more or
less occlusion of the windpipe. It is either stricture or constriction
from within, or compression from without, or both combined.
Constriction within the trachea is due to swelling or thickening or
cicatricial displacement of the mucous membrane or other tissue,
inversion of its walls, or morbid growth or foreign body in its
interior. Compression from without is due to goitre (which has in some
cases prevented viability) or other disease of the thyroid body;
aneurism; abscess; enlarged bronchial glands or cervical lymphatics;
disease of the sternum, clavicle, or vertebræ; mediastinal tumor;
cystic, emphysematous, or other tumor of neighboring tissue; or foreign
body. According to Rose's observations of goitre,3 compression of the
trachea leads to fatty degeneration of the cartilages and their
subsequent softening and absorption; after which, the windpipe having
become membranous throughout and no longer patulous, death can
easily—in some positions or flexion of the body, etc.—take place.
3 Der Kropftod und die Radicalcur der Kröpfe, Berlin,
1878.
In acute tracheitis, though there is swelling of the mucous membrane,
the large size of the tube usually obviates stenotic symptoms, while
chronic tracheitis does occasionally lead to sufficient contraction to
interfere with respiration; but generally stenosis is the result of
syphilis, and frequently follows ulceration and cicatrization. In a
case recorded in the Bullétin des Sciences médicales for January,
1829, the lumen of the trachea was reduced to two lines.
|
FIG. 32.
|
|
|
Involution of Trachea, due to aneurism.
|
SYMPTOMS AND DIAGNOSIS.—The main symptom is the peculiar, gradually
increasing dyspnoea; once observed, it is recognized without much
difficulty. There may also be mucous râles; cough rough and sibilant;
attempts at clearing the throat without expectoration, or occasionally
with some expectoration, which is at first light-colored, then streaked
with blood, and at last purulent, but never abundant (unless
accidentally complicated by catarrh), and always difficult to eject;
perhaps occasional pain, but constant disagreeable sensation
(tightness) in the trachea just above the sternum. Tracheoscopy
settles the diagnosis. The tracheal rings are seen either as diminished
circles or arcs—sometimes concentrically placed, sometimes in two
different directions, as shown in a case of tracheal stenosis from
compression causing protrusion of the mucous membrane into the
interior, represented in Fig. 32, or else constricting bands are visible.
As to the dyspnoea, both inspiration and expiration are
affected—frequently, however, the former more than the latter, as is
shown by pneumatometry. The head is thrown forward and the chin up; the
larynx moves up and down less energetically than in health (while the
respiratory movements of the larynx are abnormally increased in
laryngeal dyspnoea); the thorax is less expanded than normally,
especially its upper portions.
As to catheterization and probing, see the remarks under the head of
Morbid Growths.
PATHOLOGY.—The pathological changes in cases of stenosis vary with its
cause. In the great majority of cases of stricture from within,
syphilis—antecedent ulceration followed by cicatrization—has produced
the stenosis; in compression thyroid disease, and next often aneurism,
is the cause. The stenosis is most frequently situated in the lower,
next in the upper, and least in the middle, portion; more often than
the latter alone the whole tube is affected.
PROGNOSIS.—This is rather favorable with timely and proper treatment
unless a continuing active cause be irremovable; without treatment,
however, the cases almost invariably terminate fatally from pneumonia,
tracheal spasm, apnoea as before explained, etc.
TREATMENT.—When the symptoms are urgent and the stenosis is not too
low down, tracheotomy must be performed. Sometimes a very long and
flexible tube may be introduced with success in case of very low
stenosis, but more often tracheotomy is disappointing on account of the
stenosis extending too low down even when its beginning is higher up.
Stricture, especially when the symptoms are not very urgent, may be
relieved by dilatation through the natural passages, with, or if
possible without, previous tracheotomy. The cure of compression implies
removal of the compressing tumor or disease. Soothing inhalations, such
as of hops, benzoin, etc., diminish irritation and give temporary relief.
DILATATION (HERNIA, FISTULE).
Dilatation of the trachea is either confined to the tube (when the
synonym tracheaectasy is applied to it) or is diverticular. In the
former case it may involve only a part or else the whole extent of the
windpipe. Whenever free respiration, especially expiration, is
chronically impeded, some portion of the air-tract below the
obstruction is apt to become dilated; thus, a bottle-shaped dilatation
is sometimes found immediately below an annular contraction. On the
other hand, tracheaectasy may extend upward from bronchiectasy. It has
been observed post-mortem to a slight extent in public criers,
trumpeters, etc., and in old coughers from laryngeal disease, chronic
bronchitis, pulmonary emphysema, etc., but without giving rise to
distinct symptoms during life.
Diverticular dilatation forms an air-containing tumor which either
looks into the oesophagus or is discernible on the outside of the neck.
Though rarely met with, it ought to be thought of in all appropriate
cases, and when pointing externally ought always to be recognized by
the careful practitioner. It is either hernial, glandular, or
fistular—three pathological conditions which have hitherto been
confounded. On account of the construction and position of the trachea
there can be but little protrusion outward without previous
dilatation. Unless there be a deficiency of the cartilaginous rings,
only the posterior wall, which is always unsupported, and to a slight
extent also the intercartilaginous membranous portions, are liable to
tracheal hernia. This is properly called tracheocele; but the various
terms aërial goitre, aërial bronchocele, pneumatocele, tracheal
air-cyst, tracheal retention-cyst, internal tracheal fistule,
subcutaneous or incomplete fistule of the trachea, have been
indiscriminately used as synonyms of tracheocele, and have added all
the more to the confusion, as some of them originated, no doubt, as
correct appellations of the particular cases to which they were
applied. Aside from the occasional occurrence, both congenital and
acquired, of tracheo-cutaneous fistule, complete and incomplete, and
the still more rare occurrence of hernia of entire portions of the
mucous membrane, the cases of diverticular dilatation of the
trachea—or saccular tracheaectasy, as it may be called—are glandular,
as found by Rokitansky more than fifty years ago. Virchow seems to
regard all such glandular dilatations as retention-cysts (see Morbid
Growths), but although retro-tracheal retention-cysts doubtless do
occur (Gruber has reported two unquestionable instances), and although
the tumors now under consideration do in fact sometimes contain a
little mucus in addition to air, they do not constitute cysts or
adenomatous new growths, but are simply distended portions of the
tracheal mucous membrane, respiratory glands, whether the dilatation be
caused, as Rokitansky thought, by traction (Zerrung) and hypertrophy of
the mucous glands, or, as Eppinger suggests—and which is more
likely—mainly by increased intra-tracheal air-pressure. There must,
however, I think, coexist some deficiency or weakness of the
cartilaginous or other tissue, either congenital or acquired.
When the dilatation is retro-tracheal only, the symptoms are very
obscure, and diagnosis during life is at best uncertain. In one such
case under my care, confirmed (death having occurred from another
cause) by post-mortem examination, there was some dysphagia and slight
alteration of the voice. In all other cases the characteristic and
unmistakable sign of the disease is the peculiar intermittent, or, at
all events variable, aërial cervical tumor. It increases and diminishes
with forcible expiration and inspiration, and attains its largest size
during violent coughing, hawking, blowing of the nose, or other
expiratory effort. Occasionally the voice is considerably affected. The
tumor, especially by the manner in which it can be made to temporarily
disappear and reappear, can usually be easily differentiated from
subcutaneous emphysema and goitre, the only two conditions with which
it might be confounded. In the fistular variety the opening into the
trachea can sometimes be seen by means of tracheoscopy.
Aside from the deformity which the tumor may cause, it sometimes
induces laryngeal spasm and dyspnoea; otherwise it is of no gravity.
As to TREATMENT, methodical and continued compression by applications
of astringent collodion or by mechanical means is the only palliative
measure applicable; when suffocatory attacks call for it, tracheotomy
must be performed.
BY GEORGE M. LEFFERTS, A.M., M.D.
The operation of tracheotomy, or the artificial opening of the
air-passage—using the term in its modern acceptation as including all
of the five incisions that are both anatomically and surgically
possible, either singly or in combination, between the lower border of
the thyroid cartilage and the upper edge of the sternum (incisura
jugularis sterni), and reserving the term laryngotomy to denote the
division of the thyroid cartilage alone—fulfils two important and
usually urgent indications: First, in allowing the respiratory current
free access to the lungs in cases where the laryngeal obstruction is of
such a sudden or of so progressive a character as to either immediately
or remotely threaten the life of the patient; and, secondly, in
affording a ready means of direct access to those portions of the
air-tract which lie below the level of the glottis, and thus permit not
only of the direct extraction of such foreign bodies as may
accidentally have found their way within the air-passage, but of
neoplasms here located and of occluding diphtheritic membranes.
Catheterization and aspiration of the trachea are likewise both
rendered not only possible, but easy of execution. Both general
indications mentioned often coexist, and are met by the operation in a
large class of cases; the first alone plays its important life-saving
rôle in many.
The disease or accident which renders the operation necessary varies
greatly, and upon this variation depends not only the surgeon's
decision as to the precise time at which the opening into the air-tube
must be made, but also the precise point at which the operation should
be performed. These general questions I treat of in detail. The special
indications may conveniently, but somewhat arbitrarily, be arranged as
follows, in groups, which I have attempted to make complete, although
some of the conditions, being purely surgical, do not strictly come
within the compass of this essay:
A. Acute inflammatory diseases of the larynx and trachea:
1. Acute oedema of the larynx.
2. Erysipelatous and exanthematous laryngitis.
3. Acute perichondritis, with abscess.
4. Diphtheritic croup.
B. Chronic affections of the larynx and trachea:
1. Syphilitic laryngitis.
2. Phthisical laryngitis.
3. Chorditis vocalis inferior hypertrophica.
4. Carcinoma of the larynx or trachea.
5. Non-malignant growths of the larynx or trachea.
6. Tumors overlying the superior aperture of the larynx.
7. External compression of the trachea by tumors of the neck or chest.
8. Strictures of the larynx or trachea.
C. Neurotic diseases:
1. Paralysis of the abductors of the vocal cords.
2. Spasm of the adductors of the vocal cords.
D. Traumatic conditions:
1. Foreign bodies in the larynx or trachea.
2. Impaction of foreign bodies in the pharynx or oesophagus.
3. Fracture of the larynx. Rupture of the trachea.
4. Scalds and burns of the larynx.
5. Incised and gunshot wounds of the throat.
6. Poisonous bites inflicted by certain insects about the mouth or neck.
7. Suffocation from the passage of blood, fluids, etc. into the
air-passages (tracheotomy, with aspiration of the windpipe and artificial respiration).
8. Suffocation from the acute collection of either mucus or serum in the bronchia (ditto).
9. Suffocation from the inhalation or development of poisonous gases
(tracheotomy, with artificial respiration).
Finally, although it pertains alone to the province of the surgeon, I
may allude to the temporary tracheotomy and "tamponing of the trachea"
which has been recommended—and certainly found efficient—in
preventing the entrance of blood to a dangerous degree into the lower
trachea and lungs during the performance of certain operations in the
neighborhood of or upon the air-passages, such as resection of the
upper jaw, the extirpation of large nasal and naso-pharyngeal polypi,
removal of the tongue, subhyoidean pharyngotomy, laryngotomy, and
extirpation of the larynx.1
1 For the details of this procedure consult Schüller, Die
Tracheotomie, etc., Stuttgart, 1880.
All-important as a preliminary to the operation itself is a thorough
knowledge of the surgical anatomy of the region upon which it is
proposed to operate; and this not alone in the adult, but especially in
the child, where essential differences often exist. Possible anomalies
also are not to be forgotten.2 The assurance of the surgeon depends
upon this knowledge: mere, manual skill will not compensate for its
want; the success, both immediate and remote, of the operation is in
great measure the reward of its possession.
2 See Pilcher, "The Anatomy of the Anterior Median Region of
the Neck," Ann. of Anat. and Surgery, Brooklyn, April, 1881.
It will be remembered that the trachea commences at the inferior border
of the cricoid cartilage, directly opposite to the lower edge of the
fifth cervical vertebra, and reaches thence downward, in the median
line of the neck, until it bifurcates opposite to the third dorsal
vertebra. In its upper part it is nearly subcutaneous, and is
surmounted by the prominent ring of the cricoid cartilage (easily
identified, even in the young child), above which, in turn, lies a
slight depression (the crico-thyroid space) between the cricoid and
thyroid cartilages. As the trachea descends in the neck it recedes
gradually, lying at the episternal notch about one and three-eighths of
an inch from the surface. Throughout the whole of this course it is in
relation with important structures. In its cervical portion it is
covered by the sterno-hyoid and sterno-thyroid muscles, and in the
median space, which is usually distinct between them, by layers of the
deep cervical fascia. It is also crossed by the isthmus of the thyroid
gland, which lies between the second and fourth tracheal rings; by the
arteria-thyroidea ima, when present, and below by the plexus formed of
inferior thyroid veins with their tributary and communicating branches.
In the latter region, but more superficially, are some communicating
branches between the anterior jugular veins. The innominate and left
carotid arteries are also anterior to it in the episternal notch as
they diverge from their origin. Laterally, the trachea is in relation
with the common carotid artery, the lateral lobes of the thyroid body,
the inferior thyroid veins, and the recurrent laryngeal nerves. The
thoracic portion of the trachea is covered by the manubrium sterni,
with the origins of the sterno-hyoid and sterno-thyroid muscles,
by the left innominate vein, and by the commencement of the innominate
and left carotid arteries. Still lower, the transverse portion of the
arch of the aorta crosses, and the deep cardiac plexus of nerves lies
in front of it. Posteriorly, throughout its length, it rests upon the oesophagus.
In performing, then, either the superior or inferior operation of
tracheotomy, after cutting through the skin and superficial cervical
fascia—which is really loose areolar tissue containing fat—the
superficial layer of the deep cervical fascia is reached, and
immediately below it more or less adipose tissue and the two anterior
jugular veins lying in an inferior tracheotomy to either side of the
wound, which is always made in the median line. As a matter of fact,
these various layers are rarely demonstrable, and the surgeon proceeds
irrespective of them until he reaches this point in his operation—viz.
the muscles which overlie the trachea. These may overlap in the median
line, and have to be retracted after having been separated; or, again,
a thin line of connective tissue marks a slight interval between their
inner edges, and is readily seen and dissected through if the operator
has kept his incision vertical and strictly in the median line of the
neck—a matter so important to the success of his operation that I do
not hesitate to again allude to it. The muscles separated and gently
retracted, together with the overlying tissues, toward the sides of the
wound, the upper edge of the isthmus of the thyroid gland overlying the
second and third, perhaps fourth, rings of the trachea, is always seen
in a superior tracheotomy—its lower edge very frequently in the
inferior operation. The isthmus is adherent to the trachea and to the
larynx through the deep layer of the deep cervical fascia, but is
capable of being slightly displaced or pushed upward or downward as the
case may be, and thus kept from obscuring the operative field. This
being done, the deep layer of the deep cervical fascia is seen covering
and strongly adherent to the tracheal wall together with the thyroid
veins. A few touches of the knife, carefully avoiding the
blood-vessels, serve to clear it away, and the tracheal rings are
clearly exposed.
In carrying out this dissection, which has been described as occurring
in an ordinary and uncomplicated adult case, several matters must be
borne in mind; and especially is this true if the operation concerns
infants. In them, for instance, the thymus gland rises half an inch
above the level of the sternum, and is frequently to be found as late
as the sixth or seventh year. In both adults and children the
innominate artery occasionally comes into view in an inferior
tracheotomy, obliquely crossing the lower portion of the right half of
the trachea. It is relatively higher in the child than in the adult.
The left innominate vein is also often observed when the trachea is
opened low down.
Certain abnormalities of the blood-vessels have been alluded to above.
The commonest consists in the existence of a thyroidea ima artery,
which when present usually arises from the innominate trunk, but
sometimes from the right common carotid or the aorta: it passes to the
thyroid body directly in the median line of the neck and close to the
trachea; again, the place of the anterior jugular veins may be taken by
a single central vessel, almost sure to be wounded during the operation
if it exist (Mackenzie).
In performing the operation through the thyro-cricoid membrane
(thyro-cricotomy) or through the cricoid cartilage alone (cricotomy),
the same tissues are met with, and the same dissection is necessary in
the earlier stage of the operation, as have been described in the
operation of superior or inferior tracheotomy; but the parts are more
superficial, adipose and cellular tissue less abundant, blood-vessels
much less numerous, and the operation very much simpler. The thyroid
gland of course does not come into view, and the crico-thyroid
artery, a very small vessel, needs no attention in the dissection.
I have here and elsewhere included under the general term tracheotomy
five distinct operations, having for their object the opening of the
air-passages, which are surgically possible between the lower border of
the thyroid cartilage and the upper edge of the sternum. In this
classification I have followed that of Schüller, and its simplicity,
but exactness, and the avoidance of the old confusion of different
terms which results from the use of one intelligently employed, seem to
me to commend it. These five operations are—1. Thyro-cricotomy, or the
opening made through the crico-thyroid membrane alone. 2. Cricotomy, or
the division of the cricoid cartilage alone. 3. Superior tracheotomy,
the incision being made above the point where the isthmus of the
thyroid gland crosses the trachea and below the cricoid cartilage. 4.
Median tracheotomy, when, the isthmus being displaced or torn through,
the trachea is opened immediately below its site. And 5. Inferior
tracheotomy, the incision being made below the point of crossing of the
isthmus of the thyroid gland, and at varying distances, dependent
mainly upon the age of the patient and size of the parts, above the
sternal notch.
Rarely, I am bound to admit, is the field of all of these operations as
distinctly limited in practice as is here indicated, and one, perhaps
two, are rarely selected. Thyro-cricotomy (old term laryngotomy) is
often indicated, and cricotomy and median tracheotomy are sometimes
performed as here described. Superior tracheotomy is commonly a
combination of at least two of the methods—viz. the division of the
upper rings of the trachea and the cricoid cartilage as well. It may
even, probably frequently does, trench also upon the thyro-cricoid
membrane (thyro-cricotomy) and upon the field of a median tracheotomy,
the isthmus being pushed downward or even cut or torn through. The
latter operation and cricotomy are, I believe, rarely if ever done from
choice. Finally, inferior tracheotomy is a common method. As here
described, it meets a large number of indications, and, despite its
superior difficulties over the higher operations, is therefore
necessarily often chosen; not infrequently, however, does it invade the
median region, the isthmus of the thyroid being pushed upward.
Which of these operations shall be selected in a given case depends
upon the particular conditions which render it necessary, and likewise,
to some extent, upon the age of the patient. Durham summarizes the
question very fairly. Thyro-cricotomy (old term laryngotomy) is by far
the easiest operation to perform, and its execution is attended by
least risk; therefore it is the operation to be preferred in any sudden
emergency when suffocation threatens, and especially where the surgeon
is alone with the patient. Generally, it is not as applicable as the
others, especially in early childhood, on account of the limited
dimensions of the thyro-cricoid space. It cannot be recommended in
cases of acute or extensive diseases or injuries of the larynx, nor is
it likely to be of much service if a foreign body is in the trachea or
bronchus. On the other hand, it is probably the best operation to adopt
in cases in which foreign bodies are impacted in the larynx, in cases
of limited chronic disease or contractions of the superior laryngeal
parts—usually the result of syphilitic ulceration—and in cases in
which respiration is impeded by intra-laryngeal growths which cannot be
removed by the natural passages.
Cricotomy, combined with superior tracheotomy (old term
laryngo-tracheotomy), is not a difficult operation, and may be
advantageously practised, especially in children; in the adult it meets
many indications. Holmes recommends it the more urgently, in preference
to an inferior tracheotomy, the earlier the age of the subject may be.
Inferior tracheotomy is comparatively difficult to perform, and during
its performance dangers may have to be encountered greater and more
numerous
than those met with in either of the other operations.
This is true certainly of children. As regards young children, Holmes
states that after the age of five or thereabouts the surgeon can, if he
prefer it, open the trachea below the isthmus of the thyroid gland. He
himself does not recommend the operation before puberty. In the case,
however, of a foreign body loose in the windpipe of a child, where a
large opening is required, it can hardly be obtained above the thyroid
body and below the cricoid. To cut through the isthmus of the thyroid
(median tracheotomy) is, in early life at least, a doubtful proceeding
when it is of large size, on account of its vascularity, and the
incision must be made below it—in other words, an inferior tracheotomy.
When the operation of tracheotomy shall be performed is a question
which the experience and individual views of the surgeon, based on
experience, must decide in each case. The doubt always arises in the
mind of the inexperienced operator whether the symptoms are
sufficiently urgent to render the operation necessary. To him these
general rules may be given: The immediate indication for the operation
is to be looked for in the thorax. It is the recession of the lower
part of the sternum and contiguous ribs and the retraction of the
intercostal spaces and clavicular fossæ at each act of inspiration. He
must not wait until lividity of the lips and blueness of the
fingernails prove that the blood is being imperfectly oxygenated
(Mackenzie). Let him remember also that, aside from the immediate and
imminent danger of sudden suffocation, a remote one exists and
increases the longer he postpones his operation and allows the struggle
for air to continue—viz. vascular engorgement and oedema of the lungs,
especially in young children; the production of all those conditions
which allow, and even predispose, the lung after the operation to fall
an easy prey to the inflammatory processes.
The instruments necessary for the performance of the operation of
tracheotomy are few and simple, and are such as may ordinarily be found
in any small operating-case. A scalpel, a probe and sharp-pointed
bistoury, dissecting and artery forceps, a tenaculum, a grooved
director, two small retractors, scissors, and a dilator for the
tracheal wound, are necessary. To these may be added the needles and
thread, waxed ligatures, sponges, and tape. The tracheal tube is
elsewhere described. A faradic battery, good suction syringe, and a
large flexible catheter may render good and timely service if at hand.
It is true that many other and more or less complicated instruments
have been devised for the purpose of facilitating the operation; and
other methods, aside from that of the knife, have come of recent years
into vogue; but, still, simplest means, as above given, have in the
experience of most surgeons been proven to be the best. This statement,
undeniably true for all surgical measures, is especially so for the
operation under consideration, which is often necessarily undertaken
without opportunity for elaborate preparation and under the most
adverse and inconvenient circumstances. The more familiar, therefore,
the surgeon is with his instruments, the better and more certain will
be his work.
Holding this view, it is unnecessary for me to more than briefly
mention such instrumental aids as the grooved tenaculum of Chassaignac,
the groove serving to guide the operator's knife into the trachea; the
sharp double hooks of Langenbeck, which, after being caught in the
tracheal walls to either side of the site of the intended incision, are
sprung apart after the latter is made, thus dilating the wound and
rendering the introduction of the tube easy; the tracheotome of
Thompson, a pair of curved cutting forceps, the blades of which are
caused to open by a screw after they have been plunged through the
tracheal walls; that of Garin, a forceps with curved blades—one, the
longest and sharpest-pointed, being made to penetrate the trachea, the
instrument then opened, and both blades cut their way to the desired
extent of
incision; finally, the tracheotome of Maisonneuve, a
curved dilating hook with cutting inner edges. Its point is entered
between the first and second rings of the trachea and brought out again
between the fourth and fifth; the handle is then carried under the
chin, so that the blades are made to cut through the trachea and the
skin between the points of insertion and exit, after which, upon
pushing a spring, the two halves of the hook separate, and the canula
is introduced between them (Thornton). And the trachea-stretcher of
Marshall Hall, by means of which a portion of the trachea is cut out
and the opening kept patent.
None of these instruments have been proven to possess any practical
worth; on the contrary, their use, especially that of the latter forms,
has in more than one instance been attended with disastrous results.
To obviate the danger of serious hemorrhage during the performance of
tracheotomy, both the galvano-cautery knife and the thermo-cautery
instrument of Paquelin have been recommended within the past few years,
and a number of operations placed upon record. The procedure is the
same whichever means be used. The skin and soft parts overlying the
trachea are usually alone cut through by means of the cautery-knife,
the cartilaginous rings of the tube, when reached, being divided with
the ordinary knife. This fact alone speaks against the thoroughness
attainable by means of these methods; but, still more important,
neither has been found reliable in checking hemorrhage, and in several
instances the operator has been obliged in haste to lay aside his
cautery apparatus and turn to the ordinary and better-known means to
complete his operation. The healing of the tracheal wound made by the
cautery is slow: erysipelatous inflammation may attack the wound as the
result of the burn, and extensive sloughing of the edges is not
unknown, while the resulting cicatrix is large, strong, and
contractile, and has caused, in one case at least, a stenosis of the
trachea. In the face of these facts he must indeed be an enthusiastic
advocate who would recommend the procedure. Mackenzie justly remarks
that the use of the thermo-cautery for opening the air-passage merely
introduces an unnecessary complication into the operation.
The choice of a proper tube, one suited to meet the special indications
in a given case and specially adapted to the age of the patient and the
calibre and position of his trachea, is no unimportant matter, and may
do much not only to facilitate the immediate success of the operation,
but likewise prevent the occurrence of those possible unfortunate
results, ulceration, fatal hemorrhage, abscess, pneumonia, and pyæmia,
no lack of which are recorded in our literature.
Although the number and variety of mechanical devices and forms of
tracheal tubes that have from time to time been devised by the
inventive ingenuity of operators is large, the choice practically
centres upon one of two forms. The first, and the one most commonly
used, is but the original canula of Trousseau, modified by Roger, in
that the tracheal portion of the tube is detached from the collar or
neck-piece, and moves freely with the movements of the patient; and by
Obré, by the important device of an inner tube to prevent clogging of
the outer or original tube by mucus. Starting upon this essential
basis, the instrument-maker has perfected the instrument of to-day. It
is a silver tube, double throughout, the inner tube projecting at the
lower or tracheal end beyond the outer—an important point, as it
prevents any possible permanent occlusion by mucus or blood-crusts,
membranes, and the like at this point, removal of the inner tube at
once clearing the end of the outer one. The curve of both tubes should
correspond to the arc of a quadrant, and the outer is fastened to a
transverse collar or shield by means of two small projections or pins
upon its sides which lie under small wire bridges upon the shield after
it has passed through an opening in the transverse neck-collar
large enough to permit of its free movement during the respiratory
movements of the trachea, as well as during the forcible action caused
by cough. The ends of this collar or shield curve slightly backward to
correspond with the curve of the neck, and are perforated by,
preferably, large oval openings, instead of the usual small,
inconvenient slit, through which the tapes are passed which hold the
tube in position by encircling the neck. To this same shield is
fastened, by means of a small turn-screw or a revolving collar, the end
of the inner tube, which is thus prevented from being forced out of the
outer tube by coughing or any motion of the patient. Upon the upper or
convex surface of the outer tube a small ovoid opening is usually made
for the purpose of permitting the expiratory current to pass upward
(the inner tube being removed) into the larynx and render phonation
possible; also, the free opening of the outer tube being closed, to
allow of respiration being carried on through the larynx and natural
passages—often an important matter, as the case progresses toward
recovery, in instances where the operation of tracheotomy has been
performed on account of laryngeal obstruction.
A set of these tubes, which can now be readily obtained, should consist
of four, with the following diameters: No. 1, one centimeter; No. 2,
nine millimeters; No. 3, seven millimeters; No. 4, five millimeters:
their length is of course in relative and fixed proportion to these
measurements. A tube should always be selected less in diameter than
the trachea operated upon: to seek to introduce one of the same calibre
is not only unnecessary, but cannot fail to be dangerous. Tubes
constructed upon the same principles as that just described (Lüer's)
are made of hard rubber instead of silver (Leiter): their lessened cost
is their principal recommendation, added to the one that they are more
easily kept clean and sweet than the silver tubes. The fact that they
are necessarily made much heavier and thicker than the latter is a
disadvantage, the lumen of a hard-rubber tube being smaller than that
of a silver tube of corresponding external diameter. The objection
urged against them, of their great danger of breakage, I have not found
borne out by experience. Tracheal tubes are also constructed of
platinum, and recommend themselves on the score of lightness.
The main objection to any of the forms of tube just described exists in
the nature and shape of their curve, which not infrequently causes the
lower or tracheal end to lie in contact with the anterior tracheal
wall, or its convexity with the posterior, and irritate, even ulcerate,
them. This misfortune is entirely obviated by the canula of Durham, the
second of the two forms to which I have called special attention, and
which is essentially a right-angled tube, made of four sizes, with a
long horizontal portion, varying from 7 to 4 centimeters, and short
vertical portion, of from ½ to ¾ of an inch in length and slanting
slightly backward. The former portion is capable of being lengthened or
shortened in any sized tube by means of a screw arrangement attached to
it as it passes through the usual neck-collar or shield; and the
vertical tube can thus be correctly adapted to the particular depth at
which the trachea naturally lies in a given case from the surface; and
not alone this, but also to the condition of the overlying parts,
whether thin or fat, swollen or otherwise. Once in position, the
vertical portion of the tube remains in the long axis of the trachea,
and does not touch its walls to any injurious degree. Owing to its
right-angled shape, the angular and descending portions of the inner
tube of this canula are necessarily made upon the lobster-tail
principle, with joints—a possible disadvantage, as they can become
clogged with mucus and may become detached. Other modifications and
improvements exist in this Durham canula over the older one first
described, which add to its utility, but need not here be dwelt upon.
Suffice it to say that the tube is an excellent one for its purpose,
and is deservedly highly spoken of and recommended by those who
have had experience in its use. Its cost is an objection.
The other forms of tracheal tube need but passing mention. The bivalve
canula of Fuller is made in two lateral segments, fastened to a collar
and tapering when closed to a point, so that introduction of the
apparatus through the tracheal wound is made easy. Once introduced, an
inner complete canula is slid into its place, thus separating the two
outer halves and rendering the whole round and compact. It has been
criticised unfavorably on account of the danger of hemorrhage that it
is likely to cause through pressure on the tracheal walls by the sharp
edges of the outer canula. In Gendron's canula the same lateral blades
are separated after introduction by means of a screw fastened on a
transverse bar.
Soft-rubber canulas were introduced to the profession not long since by
Morrant Baker for subsequent use after the operation of tracheotomy,
the usual tube having been worn meanwhile for a few days. Being soft
and flexible, they are certainly safe and comfortable for the patient,
but their thickness and the absence of any inner tube are, especially
the latter, serious disadvantages. They are not, I believe, generally
used. Finally, the long, flexible tracheal tube of König was devised by
its author to meet the indications in cases where the trachea is
compressed from without by tumors, and where a long canula that is
flexible, but at the same time rigid enough to resist pressure, becomes
a necessity. It is made in the form of the ordinary tracheal canula,
only larger, some three or more inches of the centre of the descending
portion of the tube being constructed of spirally-twisted silver wire.
It may not be out of place to remind at this point that a tracheotomy
is not infrequently performed, of necessity, very hastily, and in the
absence not only of a tracheal tube, but likewise of other and even
more essential instruments. The lack of the former need never be a
barrier to the prompt performance of the operation, for the ready wit
of the true surgeon will show him various ways out of his temporary
difficulty. A thick goosequill fastened by threads passed through its
outer end makes an efficient improvised canula. A bit of elastic
catheter answers the same purpose. Retractors for the edges of the
tracheal wound, made of wire—silver if it be at hand, a couple of
hairpins if it be not—and connected together by an elastic tape which
passes around the neck, will not only answer a good temporary purpose
in holding the tracheal wound dilated, but have been recommended by
Martin—in a more elegant form, it is true—as a proper method of
treatment after opening the trachea. Finally, one or more stitches
passed through the cartilaginous edges of the wound, and attached to
the soft parts beyond it, will serve to secure its patency, at least
temporarily.
If a patient be doomed to wear a tube constantly in his trachea, the
instrument described above can be removed at a suitable interval after
the operation and its place supplied by a single tube of the same size
and form as has been found adapted in the case. In the convexity of
this permanent tube an ovoid opening should be made to allow of the
passage to the larynx of the respiratory current, in part at least, and
to its mouth a pea-valve may be fitted which shall admit air on
inspiration, and not allow it to escape on expiration, thus doing away
with the necessity of the patient's closing the opening of his tube
with his finger each time that he requires to speak. Several forms of
these valves have been devised, but practically they are of little use,
are annoying to the patients, and, as a rule, not tolerated by them.
How shall the operation of tracheotomy be performed? An answer to this
question necessitates a short description of the operative steps of the
different procedures that is given in the order in which, I believe,
the operations are, as a matter of experience, found to occur in
practice—viz. 1st, superior tracheotomy, combined or not with
cricotomy; 2d, thyro-cricotomy and, 3d, inferior tracheotomy. Certain
preliminaries are common to all.
The patient should be extended upon a table covered with one or two
thicknesses of blanket and of suitable height, which has been placed
sideways in front of a window if the operation is done by daylight. (At
night several candles tied together afford a better and safer light
than a kerosene or oil lamp.) The surgeon stands at the right side of
his patient and facing the window. Of his two assistants—and the value
of trained assistance in this operation is inestimable—one faces him,
without obscuring the light, and is prepared to use the sponges, hand
the instruments, manipulate the retractors, and render such direct
assistance as may be required. The second sits at the head of the table
and holds the head of the patient steadily, the neck being well
extended and thrown backward over a small round pillow (or, better, a
wine-bottle wrapped in a towel) which has been placed beneath it. The
head must be held directly in the median line of the patient's body,
and even in that of the operating-table. The assistant's attention must
never waver from this important duty. In certain cases too great
inclination of the head backward serves to increase the urgent
dyspnoea, or even to check respiratory efforts. This effect he must
watch for, and be prepared to relieve instantly by raising the head.
His duties also include the preliminary administration of an
anæsthetic, and its use during the operation if required. That such use
is safe in this class of operations is now generally admitted, but it
is not always necessary. The operation is not an exceedingly painful
one, and I have often performed it, with the adult patient's consent,
without using any anæsthetic (sometimes freezing the skin over the site
of the incision before making it), he submitting rather than undergo
any addition to the sense of urgent dyspnoea from which he is already
suffering. In children anæsthetics—ether being more commonly employed,
although chloroform is often used—are much more necessary, often
indispensable. Their effects are speedily manifested when asphyxia is
present in any marked degree, and but little of the vapor need be
inhaled. The administration, always to be carefully watched and
profound anæsthesia avoided, renders breathing easier in many
instances, certainly lessens laryngeal spasm, and may be discontinued
early in the operation when the air-tube is or has been nearly reached
by dissection. Any slight risk attending their use is more than
outweighed by the safety and precision which they ensure in the more
difficult and delicate steps of the operation (Sands). If the patient
be already insensible or if death be imminent, their use, of course, is
contraindicated.
The operator having previously decided which operation he will perform,
and after carefully identifying the position of the various parts, the
larynx especially, marking them with ink upon the skin if he chooses,
now steadies the loose skin over the site of his intended incision, and
then makes it, freely, firmly, cleanly, and exactly in the median line.
If it be for a superior tracheotomy, combined or not with cricotomy,
the operation I shall first describe, it must extend from just at the
notch of the thyroid cartilage downward for about four inches. A free
external incision is very desirable in all cases. The subcutaneous
tissue now rapidly dissected through by the careful use of the knife,
the veins as met with either being pushed to one side or, if they cross
the line of incision, cut if small, then twisted or immediately
ligated, or if large doubly ligated and then cut between the ligatures,
the interval between the sterno-hyoid muscles is sought for and found,
then separated by the blade or handle of the knife and held apart by
retractors at the side of the wound. It is important that the faint
whitish line of connective tissue which marks the interval between the
muscles be recognized, otherwise it happens that the operator passes
through the body of one of them, deviates at once from the median line,
and approaches the side of the trachea instead of the front. The
ring of the cricoid cartilage above and the upper edge of the isthmus
of the thyroid gland below can now be either seen or felt by the finger
in the wound between them; and about the latter lies more or less
connective tissue and numerous small veins. As a rule, careful touches
of the point of the knife, or, as some operators prefer at this stage,
its handle or the use of a blunt director, serves to dissect up
piecemeal or tear through and clear this away, the veins again being
pushed out of the way, or if necessary cut and tied, and all parts held
aside by removing and replacing freshly the retractors from time to
time as the dissection proceeds, until the ring of the cricoid and the
upper rings of the trachea come plainly into view; that is, are seen,
not alone felt. During this dissection, especially if the handle of the
scalpel be used, too much pressure must not be made upon the trachea.
More than once I have known it to cause sudden suspension of the
respiration, probably by exciting reflex spasm of the larynx. If the
isthmus of the thyroid gland extend far upward, it must be pressed
downward, its facial attachments to the cricoid and trachea cut or torn
through, and may require to be held downward in the lower angle of the
wound by an additional retractor. The upper rings of the trachea having
been thus well cleared of their overlying parts, the next step of the
operation follows. I am in the habit of now removing the retractors and
allowing the trachea, which may have become displaced by them, to
resume its normal position, the head of the patient being meanwhile
readjusted. All this takes but a few seconds. A tenaculum is then
implanted in the median line, either just below the edge of the thyroid
or the cricoid cartilage, if the latter is not to be severed, and held
firmly by the assistant at the head of the table, thus steadying and
elevating slightly the trachea and rendering the incision into it
certain. The retractors are now reintroduced at the sides of the wound,
and the operative field is clear and steady. A glance having shown that
all bleeding has ceased, another that the tracheal dilator and
tracheotomy-tube lie ready at hand, the operator plunges a
straight-pointed bistoury through the tracheal wall at the level of the
third or fourth ring in the median line, and cuts quickly upward until
the cricoid cartilage is reached, if he proposes, as in the adult can
usually be done, to limit his operation to a superior tracheotomy. If
not, as in the child, and the cricoid cartilage must be cut through to
gain sufficient space for the introduction of the tube, it also is
severed by prolonging the incision upward to the thyro-cricoid
membrane. A hissing of escaping air, with the bubbling of a little
blood and paroxysms of cough, follows the incision and shows that the
trachea has been fairly opened. The tracheal dilator is now introduced,
the lips of the tracheal wound separated, and the canula slipped neatly
into the windpipe (unless in the case of a foreign body), and secured a
moment or two later, when respiration is fairly established, by tapes
passing around the neck. The tenaculum and retractors are removed at
the same moment that the tube is slipped into place.
Many different methods have been recommended for the dilatation of the
tracheal wound and to assist the introduction of the canula. The
dilator (Trousseau) which has been mentioned surely answers all
purposes, and is simple and easily used. An ordinary dressing forceps
will likewise do the work if introduced closed and afterward opened.
More complicated procedures are unnecessary.
Thyro-cricotomy requires that the superficial incision be so made over
the larynx that the thyro-cricoid space shall lie in the centre of one,
about two inches long, made in the median line. Following now the
dissection just described, the thyro-cricoid membrane is easily reached
and quickly seen as soon as the sterno-hyoid muscles are retracted. It
should then be divided transversely close below the lower edge of the
thyroid cartilage, the wound dilated, and the tracheotomy-tube slipped
into place.
Inferior tracheotomy demands that the external incision be free.
In children, and in adults with a short neck, it should extend from the
cricoid cartilage to just above the sternum. The subsequent steps of
the operation are as for superior tracheotomy, with but slight
differences. The anterior jugular veins may come into view, but can
generally be avoided. If they are joined by a transverse branch, this
is necessarily cut through after being doubly ligated. After the
thyro-hyoid muscles are separated, the rings of the trachea are much
less distinctly felt at first than in superior tracheotomy, being
covered by more connective tissue and numerous veins. These inferior
thyroid veins, especially if large, are the great obstacle in the way
of this operation, and much care is necessary in order to avoid them,
which should be done if possible. The lower edge of the isthmus of the
thyroid gland, which presents to a variable extent above in the wound,
does not, as a rule, offer any obstruction. The thymus gland present in
infants is easily pulled downward and out of the way. The trachea at
length fairly exposed and all bleeding controlled, the left fore finger
of the operator is placed in the lower angle of the wound to securely
protect the large blood-vessels here located, and the incision made
through some three tracheal rings from below upward.
It may happen that in either a superior or inferior tracheotomy no time
will be allowed for careful and slow dissection as here described. In
such instances Durham advises that the surgeon grasp the trachea
between the fore finger of his left hand on the left side and the thumb
on the right, and make uniform, steady, deep pressure, thus firmly
securing it and at the same time protecting the large vessels of the
neck. The fingers thus placed are not to be moved until the trachea is
reached, which is accomplished by rapid incisions confidently made. The
pressure of the fingers causes the wound to gape and the trachea to
advance. The latter reached, it is caught by the tenaculum and the
operation completed as before described.
The operation of median tracheotomy may require a word. As has been
stated, that part of the trachea covered by the isthmus of the thyroid
gland is very commonly encroached upon in performing either or both
superior and inferior tracheotomy, the isthmus being slightly displaced
from its site. Other than this the site here mentioned would rarely be
selected as the point for opening the trachea. Certain conditions, it
is true, might render it necessary, but they would be rare. The danger
lies in the hemorrhage which, theoretically at least, is to be expected
when the isthmus of the thyroid gland is either torn or cut through;
but opinions vary very greatly as regards this danger. With a thin,
narrow isthmus in children I have frequently, in performing superior
tracheotomy, cut my way through to a sufficient extent to clear a
suitable space upon the trachea through which to introduce a tube
without difficulty or danger. I should not recommend the procedure,
however, were the isthmus to be seen to be, when reached, thick, wide,
and exceedingly vascular, but at the same time believe that the danger
even here of cutting into it is much overestimated.3 Roser's
recommendation to apply a ligature to the isthmus on either side of the
median line previous to its division is not generally applicable.
Hueter has shown that the fibrous capsule of the thyroid gland
enclosing it and its blood-vessels is firmly attached to the trachea
and sides of the larynx, and that from the isthmus this fascia extends
upward over the larynx (fascia laryngo-thyroidea), and thus prevents,
in a measure, attempts at displacing the gland downward. Bose4
recommends that this fascia be divided transversely over the anterior
convexity of the cricoid cartilage, when a director can be passed
behind the isthmus, to lift it from the trachea and depress it far
enough to expose three or four of the rings: the capsule of the
gland thus remains unbroken and no hemorrhage occurs. The procedure
certainly merits trial; twice it has succeeded well in my hands.
3 See Foulis, "Some Points on Tracheotomy," Glasgow Med.
Journ., vol. xv. No. 2, p. 123.
4 Archiv für klin. Chirurgie, vol. xiv. p. 137.
Cricotomy, the division of the cricoid cartilage alone, is an operation
which, as far as I am aware, is rarely ever performed. The objection
urged against it, however, that in the adult the elasticity of the
cricoid cartilage is so great that a wound through its ring cannot be
made to gape sufficiently to allow of the introduction and retention of
a canula without discomfort and danger of necrosis of the cartilage, is
not borne out by experience. In children the objection cannot of course
be urged.
The description of the operative steps which has been given, and which
comprises the routine in an ordinary and easy cure, should not mislead.
The operation is not always as simple and safe as would appear from
what has been said. At times complicated and difficult, at times
dangerous in practice from the delay involved, it demands in all, but
especially in certain urgent cases, a trained hand and eye, sound
anatomical knowledge, coolness, self-reliance and presence of mind on
the part of the operator. Despite the greatest caution, and even in
apparently favorable cases where time for dissection and deliberation
is allowed, certain mishaps may occur which complicate the operation to
a serious, dangerous, or even fatal degree. Some of these, as will be
seen, are avoidable with care, but others may happen that are not only
unavoidable, but totally unforeseen, and from their very suddenness all
the more embarrassing.
Accidents may occur during the dissection of the soft parts overlying
the larynx and trachea, and the importance of carefully determining by
palpation the location of the various parts prior to making the
preliminary incision, and of studiously preserving their relation and
location during the dissection, cannot be overestimated. Neglect of
this precaution has in more than one instance led to the air-passages
being opened through the thyroid cartilage or thyro-hyoid membrane,
instead of at the intended point. It should not be forgotten also that
the natural laxity of the several layers of connective tissue of the
neck is much increased by their division, and that the trachea, being
naturally freely movable, is thus very easily displaced from its normal
position during the act of dissection; especially will this happen when
unskilful attempts are made to hook aside or retract the divided
structures during the operation. Thus it may easily occur that the
entire trachea is drawn to one side and entirely lost, or, more
commonly, is turned upon its vertical axis, and finally opened at the
side instead of anteriorly in the median line. It may not be opened at
all, either being altogether missed by the surgeon in his dissection,
which is continued past it, even down to the vertebral column, or the
tracheal tube may be passed into the tissues lying in front of the
trachea, under the mistaken idea that the latter has been incised.
Persistence in keeping to the median line during dissection—a golden
rule in the operation of tracheotomy—will render the first accident
impossible; the second may be avoided by hooking up the trachea, as has
been described, before incising it. If the opening into the trachea has
not been made large enough to receive the tube, as often happens to the
young operator, and even to the experienced when he fears to extend his
incision on account of the proximity of the thyroid isthmus, no
resource remains but to carefully enlarge it, pushing the thyroid
isthmus or veins from before the course of the knife. If the opening be
small, and be lost both to touch and sight, a second should at once be
made, especially in urgent cases, and no time lost in searching for the
first. This opening must be made directly in the median line, otherwise
the canula will stand awry in the wound and be easily dislodged from
its position in the trachea. If the first opening made is faulty in
this respect, it is better to at once make a second. It may seem
unnecessary to
warn the surgeon against thrusting his
sharp-pointed bistoury too far inward at the moment of incising the
trachea; but as a matter of fact it has been driven through both
anterior and posterior walls, and even through the oesophagus, until it
has struck the spine. The converse, or a too superficial incision, is
an accident more likely to occur, the point of the knife not being made
to penetrate the mucous membrane of the trachea, which is probably
swollen and thickened. No relief in such cases follows the incision,
and an attempt to introduce a tracheal tube may cause it to pass
between the mucous membrane and tracheal walls into the submucous
tissue, thus stopping up the tube as it progresses. The disastrous
result of such an accident can readily be foreseen unless the
complication be quickly appreciated as to its nature, the tube
withdrawn, and the incision completed. Much more frequently will a
somewhat similar accident occur in the operation of tracheotomy for
croup or diphtheria. The pseudo-membrane overlying the walls of the
air-passage is not penetrated, but pushed before the knife, which has
properly incised the walls of the tube; the introduction of the canula
now crowds this membrane still farther back toward the posterior
tracheal wall, and a complete tracheal stenosis is added to the
pre-existing laryngeal one; sudden and urgent dyspnoea follows, and
prompt relief alone wards off fatal suffocation. Fortunately, in such
instances the forcible efforts at respiration and struggles of the
patient are often sufficient to break through the occluding membrane
and allow the respiratory current to pass. Violent cough often follows,
and more or less of the membrane is forced out through the tube. Should
these events not come instantly to pass, the surgeon must not wait for
the efforts of the patient, he being often cyanosed and unconscious at
this point, but by passing an elastic catheter down through the
tracheal tube break through the occluding membrane forcibly. The
occurrence of such an accident is always denoted by absence of
respiration through the canula and by alarming asphyxia, and its cause
needs but little reflection to be appreciated.
Much the same train of events happens if during the introduction of the
canula large portions of the false membrane are completely detached and
drawn down into the lower trachea by the violent inspiratory efforts of
the patient, or stripped up from the mucous membrane and pushed
downward into the air-tube. No time should be lost in either case in
removing the tracheal tube, dilating the tracheal wound by forceps or
otherwise, and in endeavoring to clear the trachea by seizing the
obstructing membrane with forceps. If this be unavailing, the
suction-syringe must be adapted to the mouth of the canula and the
trachea cleared by aspiration. A large elastic catheter may take the
place of the canula. Sands recommends in such instances as the
foregoing that another opening should be freely made below the first
one in the trachea, when respiration will probably be re-established.
The success of this procedure of course depends upon the depth to which
the false membrane has been drawn in the trachea.
Schüller regards the moment at which the trachea is opened as the most
important and most dangerous of the whole operation. Certain of the
accidents which may occur at this period have been detailed; others
remain to be spoken of, one of which at least—viz.
hemorrhage—requires special mention. Even before the tube is cut into
it may cause an important question to arise for the surgeon's decision.
A bleeding, often copious and persistent, which arises during the
course of the operation from the accidental or unavoidable wounding of
the thyroid veins, especially when they are large and numerous, the
patient unruly, and perhaps with a short fat neck, and the fact that
having wounded one the blood flows so over the parts as to obscure and
increase the chance of wounding others, constitutes one of the
commonest difficulties met with in the operation of tracheotomy.
Hemorrhage arising from a wound of the thyroid isthmus is much rarer,
and neither, as a rule, need be feared if due care and
promptitude be exercised. But should it occur in a case in which the
urgency of the dyspnoea allows of no time in which to employ the
ordinary methods by ligature, torsion, pressure, or otherwise of
checking it, shall the incision be made and the risk boldly incurred of
blood passing to a dangerous degree into the trachea, and this in the
face of the oft-repeated advice—the, in some quarters, absolutely
given rule—that the trachea is never to be opened until all hemorrhage
has ceased? I hold that it unquestionably should be, and that he who
waits in many instances until the former moment will have to wait until
his patient is dead. Durham truly says that it is useless to let the
patient die from suffocation while attempting to prevent death from
loss of blood; and yet this has been done.
In any case, then, where there is great venous congestion, marked
venous bleeding, and little time, the patient being on the point of
suffocation, the surgeon should carefully but boldly proceed and
complete his operation in spite of the hemorrhage, opening the trachea
and introducing the canula even though the entire field of his
operation be obscured by blood. The tracheal opening once made under
such circumstances, the patient, if the blood which enters the windpipe
be not coughed up again, may be turned upon his face, so that the blood
will gravitate toward the tracheal opening and the lips of the latter
compressed about the rigid tube; or the blood may be aspirated from the
trachea by means of the suction-syringe through an elastic catheter in
the wound or the tracheotomy-tube by the operator's mouth, according to
the urgency of the case. These measures answer for the slighter cases,
but where the patient has suffered from urgent impending suffocation
before the opening of the trachea, the entrance of the blood and its
suction downward by the first inspiration may make it complete, and the
danger is great. Still, the choice lies between the two evils, and the
advice given above holds good. To the treatment there recommended will
now have probably to be added artificial respiration and faradization.
Comfort in any case may be taken in the fact that the re-establishment
of respiration through the tracheotomy wound quickly relieves the
pulmonary capillaries and the right heart of their distension, the
venous circulation resumes its natural course, and the venous bleeding,
perhaps alarmingly free, ceases almost immediately or is readily
checked by pressure.
Where time is afforded and despatch in the operation is not a
necessity, the trachea should not be opened until all hemorrhage has
ceased. This, as a rule, is readily controlled by the usual measures,
and in a large percentage of operations is not excessive. A direct
fatal hemorrhage is very rare; likewise an arterial hemorrhage of any
extent, especially if the possible anomalous position of certain
arteries, such as the thyroidea ima, be borne in mind and care in
making the incision exercised. Nothing but gross carelessness on the
part of the surgeon and entire loss of presence of mind can account for
the opening of the carotid or innominate arteries, as has been done.
During the performance of the low operation of tracheotomy the finger
of the operator must more or less frequently be pressed into the lower
angle of the wound, and his anatomical sense constantly on the alert.
The entrance of air into a vein during the operation is a possible
accident, especially when it is much enlarged and imbedded in dense
tissue, as sometimes occurs in malignant disease of the throat or when
large tumors of the parts exist. Should such an unfortunate
complication occur, the proper treatment, according to Erichsen, should
be compression of the wounded vein with the finger and its immediate
ligation if possible; compression of the axillary and femoral arteries
and a recumbent position for the patient to favor cerebral circulation;
and, lastly, artificial respiration.
At the moment of opening the windpipe two conditions may suddenly
supervene, both of which need, as may usually be easily done,
differentiation from the asphyxia produced by the entrance of blood
into the trachea. The first of these is the apnoea which not
unfrequently arises in children suffering from urgent dyspnoea the
moment that a free opening is made and the air-stream rushes unimpeded
into the lungs. The condition lasts but a moment or two, and need
excite no alarm. The second is based upon the fact that the operation
itself not seldom excites an alarming asphyxia, probably by provoking
laryngeal spasm. The introduction of the tube serves to promptly
relieve it.
Finally, I may refer to those rare but unfortunate and unpreventable
cases where the introduction of a tracheotomy-tube after a carefully
conducted operation fails to give relief. Such instances are reported
by several authors, and depend upon the existence of some unascertained
pathological lesion, such as the presence of a stricture of the trachea
below the site of the operation, compression of this tube from without
or a tumor within, stricture of the primary bronchi, or some similar
condition. A careful preliminary examination and study of the case will
in the majority of instances do much to fix the indications for the
operation and perhaps account for the surgeon's failure.
The operation itself having been practically completed with the
introduction of the canula, the after-treatment of the case now becomes
the important consideration. This naturally varies in accordance with
the accident or disease which has rendered the opening of the trachea
necessary. In the instance of a foreign body lodged in either larynx or
trachea the tube may at once be removed as soon as the former is
removed or expelled. Indeed, the introduction of the tube is often
unnecessary, as the offending article flies out through the wound as
soon as the trachea is opened. The only contraindication would be to
this rule when the foreign body is of a sharp and irritating character,
and has been impacted in the larynx, especially of a child, and
consequent inflammation and swelling of the parts may confidently be
looked for. Should the operation have been called for on account of
laryngeal or tracheal obstruction due to syphilis, both constitutional
and local treatment are indicated, the latter varying with the special
conditions presented, and being fully described in the section of this
work treating of that subject. The patient not infrequently is obliged
to wear the tracheal tube permanently. In croup and diphtheria the
first efforts of the surgeon after introduction of the tube should be
directed toward the removal of such shreds of the membrane as present
through the tube or may be reached by forceps introduced through it
into the air-passage. Large quantities may thus often be gotten away,
to the manifest relief of the patient. A pseudo-membrane covering the
vocal cords and causing glottic stenosis has thus also more than once
been removed through the wound. A feather carefully passed through the
tube into the trachea, by exciting cough and through its mechanical
effects, is of assistance in promoting the expulsion of membrane lodged
in the trachea below the wound. The use of an elastic catheter and
aspirating syringe for the same purpose is advised by Roux and Hueter.
In any case, constitutional treatment as well is indicated, and other
measures—viz. the inhalation of steam, direct local applications, and
the like—such as may meet the views of the particular operator.
Granted that the operation has been performed to meet the indication in
cases of sudden and urgent dyspnoea arising from the passage of blood
into the trachea or the accumulation of serous fluids in the lower
air-passages, as well as in cases of dangerous intoxication from the
effects of poisonous gases and narcotics, aspiration of the trachea in
the former instances, followed by artificial respiration in all, and
perhaps the catheterization of the trachea in the latter, as advised by
several recent writers, will tax the surgeon's energies as the primary
consideration after his operation. The catheter may be first used for
the purpose of aspiration in the former cases, if
necessary, then
for the injection of air, it here taking the place of the natural upper
air-passages.
In cases of acute laryngeal oedema, certain chronic inflammatory
processes, neoplasms in the larynx or trachea, and injuries or wounds
of the air-passages, the proper treatment, aside from that of the
necessary tracheotomy, will suggest itself on ordinary surgical
principles, or is elsewhere specially treated of in this work in
connection with the subjects themselves.
Aside from these special indications for after-treatment, which must be
met as they arise, there are certain general rules for the management
of any case after the tracheotomy-tube has once been inserted: they
relate mainly to the care of the patient, the dressing of the wound,
and the care of the canula.
A variable period of intense and exhausting suffering from dyspnoea
having probably preceded the operation, the sooner the patient is
allowed to seek refreshing sleep the better; and this may be allowed if
there be no danger of hemorrhage. Nourishment of a fluid character and
stimulants, if necessary, are to be allowed in quantities and at times
dictated by good judgment. The patient's first attempts at swallowing
must be watched and directed, as the fluids frequently pass in part for
a short time into the larynx, and may appear at the tracheal wound. If
the condition persist, it may be, no other apparent cause existing,
because the tracheal tube is too long and presses on the posterior wall
of the trachea, thus interfering with deglutition. For the first day or
two at least a competent nurse must be in attendance, and the care of
the tube entrusted, after explicit directions, to her. For the first
twenty-four hours the secretions usually need to be constantly cleared
from the mouth of the inner tube as they are coughed up by the patient,
and the tube itself occasionally removed and thoroughly cleaned in
carbolized water (or water to which a little borax or potash has been
added) by means of a bristle brush, such as is used for cleaning pipes.
As the case progresses, the secretions are not as profuse or annoying,
and the patient learns to assist himself, in caring for his tube and to
remove and replace the inner one. Attempts at using the voice are to be
abstained from, and a slate or pencil and paper used until, if the case
progress favorably, the third day, when he may be shown how to produce
it by closing the outer fenestrated tube (the inner being removed) with
the finger. The outer tube does not require usually to be removed,
except in diphtheria, for cleansing until the third or the fourth day,
prior to this it being done by means of a feather. The removal of the
tube should always be done by the surgeon himself, and the occasional
danger of its difficult reintroduction, caused by the swelling of the
parts, not forgotten. At the same date, the wound sutures may be cut
and removed. After its first removal the outer tube is taken out,
cleansed, and replaced at each daily dressing, which consists in the
washing of the wound with carbolized solutions, the application of
adhesive strips, if necessary, across it after the sutures have been
removed, and the insertion between the neck-plate or collar of the
tracheotomy-tube and the skin, upon which it presses, of a layer of
sheet lint covered by a little simple cerate or like dressing. The
tapes attached to the canula for fastening it about the neck need
changing, and care must be taken to regulate each day their degree of
tension about the neck in proportion to the amount of inflammatory
swelling attendant upon the wound through the soft parts overlying the trachea.
The patient, during, especially, the first few days after the opening
into the trachea has been made, should be kept in a well-ventilated
room with a uniform temperature. There is rarely any occasion, except
in cases of croup and diphtheria, when it may be advisable, to envelop
him in steam. Some surgeons place a small wad, two or three layers of
gauze, wrung out frequently in hot water, over the mouth of the tube
for the first day or two. A large, coarse sponge answers the same
purpose; and the precaution seems to me to be a good one, preventing,
as it does, air of a low temperature from entering the lungs, and
rendering it moist and free from adventitious particles. The difficulty
is in keeping it in place.
The question as to the final removal of the canula is a difficult one
to answer here, depending as it does upon the various causes for which
the operation was originally performed. In certain cases, as will be
seen from what has been said, its sojourn in the trachea will only be
from a few moments to a few hours; while, on the other hand, in cases,
for instance, of severe syphilitic disease of the larynx, with
cicatricial stenosis of its cavity, the tube, once introduced, has to
be worn during the lifetime of the patient. Between these extreme
limits the period varies greatly. As a general rule—perhaps from the
fourth or fifth day to the end of the first week—an attempt to cause
the patient to breathe through the natural passages, the outer end of
the outer fenestrated tracheal tube being closed, will partially
succeed. Each day will now make success greater; the voice in part
returns, and a period is soon reached when the outer tube may be closed
with a cork (at first during the daytime only) and respiration carried
on entirely through the larynx. The speedy removal of the tube and the
closure of the tracheal wound then follow as a matter of course. I have
never found it necessary to employ any of the various forms of
after-treatment canulas, and believe them to be unnecessary. The
original tube, preferably a fenestrated one, as heretofore described,
is to be worn until convalescence is established, then permanently
withdrawn.
The tube should be removed at the earliest safe and practicable moment.
Its lengthened sojourn is not devoid of danger, as will be shown; and
an atrophy of the laryngeal muscles, especially the abductors of the
vocal cords, may follow their prolonged disuse, or at least inactivity,
thus giving rise to a narrowing of the glottic opening perhaps
inconsistent with respiration.
The wound, covered by granulation-tissue if the tracheotomy-tube has
been worn for any length of time, quickly closes, when the latter is
removed, and needs to ensure this but a few narrow strips of adhesive
plaster to be passed across it and attached to the side of the neck, to
prevent the air being forced out through it during the first day or two
when the patient coughs or attempts to speak.
In cases where the tube has been worn for a long period, and the edges
of the opening have firmly cicatrized, their freshening by the knife or
scissors is a necessary preliminary to their being brought together by
means of a suture or two.
The wound in the trachea closes not by the formation of a
cartilaginous, but rather of a dense connective tissue, and the
cicatrix is so smooth and small as to be with difficulty discernible.
The cicatrix remaining externally upon the neck need be but slight and
linear, and cause no disfigurement, especially if the wound have been
properly treated and watched during the healing process.
Among the complications and accidents which may occur after a
tracheotomy successfully performed,5 none is commoner, and none,
perhaps, is more to be feared, than the broncho-pneumonia which may
develop at any time within the first three or four days, and especially
in those cases where the operation has been rendered necessary by a
diphtheritic inflammation of the throat or air-passages. Bronchitis is
common when much blood has escaped into the trachea during the
operation. The periodical and careful auscultation of the chest is
therefore desirable, in order that the earliest physical signs of these
morbid conditions may be detected.
5 See Parker, "On Some Complications of Tracheotomy, with
Illustrative Cases," Lancet, Jan. 24, Jan. 31, and Feb. 7, 1885.
Secondary hemorrhage is rare: should it occur, the wound must be
opened, enlarged if necessary, and the bleeding vessel sought for and
secured. A slight hemorrhage may be checked by pressing the parts
firmly about the tracheal tube and the use of styptics locally.
When the pathological condition of the parts has demanded that the
canula be worn for a long time, and in cases where sufficient care has
not been taken to select one suited to the age of the patient or to the
particular form of operation that has been chosen, perhaps to the needs
of the special case, an ulceration of the anterior or posterior wall of
the trachea, the result of the pressure of the lower edge of the tube
or of its upper posterior and convex side, may occur. Usually, it
happens on the anterior wall, rarely on both, and the main trouble to
which they give rise lies in the repeated hemorrhages that proceed from
the laceration of granulation-tissue, in changing the canula, for
instance, and the descent of the blood into the trachea and lungs.
Cases of extensive ulceration, with erosion of the large vessels at the
root of the neck, and fatal hemorrhage, have been reported.
Considerable care should then be exercised in so adapting a canula to a
special case that it will lie as free as possible within the lumen of
the trachea. Ulceration of the tracheal walls, it is claimed, never
occurs with the right-angled canula of Durham. Occasional change of
form in the canula or the use of canulas with rounded extremities
(perforated with numerous slits) is often advisable when the tube is
worn for a length of time.
Another complication following the prolonged sojourn of a tracheal
tube—rare, it is true—is the development of a mass of
granulation-tissue, a veritable tumor, which may occlude the lumen of
the trachea and lead to serious disturbances of respiration. The growth
usually occurs about the inner edges of the tracheal wound, extending
thence inward and upward or downward, as the case may be, and is most
frequently met with, perhaps, after tracheotomies undertaken for
diphtheria, although it may occur as a result of the ulcerations
mentioned above, and develop even from the cicatrix in an old and
perfectly-closed tracheotomy wound. The size of the mass, its location,
and the amount and manner of its interference with the respiratory
current vary much, but the condition must ever be regarded as a
troublesome, even dangerous, one, and may always be suspected when
attempts at the removal of the canula temporarily or permanently are
followed by sudden and urgent dyspnoea.
The exuberant granulation-tissue which forms about the outer edges of
even a recent tracheotomy wound, and occasionally renders the
reintroduction of the tube difficult, as well as closing the wound
while it is out, is a much simpler matter, and is easily remedied by
cutting it away with the scissors or checking its formation by caustic
applications.
A subcutaneous emphysema not infrequently occurs as the result of poor
surgery and delay at the time of introducing the tube into the
windpipe, or may come on later when the tube fits the tracheal wound
incompletely. In either case it need excite no apprehension, and
usually quickly subsides. Cervical cellulitis is a more serious matter,
but is fortunately rare if unconnected with disease of the cartilages
of larynx or trachea. It probably depends upon injury to the tissues
and a too extensive opening up of the intermuscular strata at the time
of the operation. Should the complication arise, the tendency to the
burrowing of pus must be prevented by free drainage and, if necessary,
incisions. The other surgical indications are to be treated on general principles.
When the incision necessary for the introduction of a tracheotomy-tube
has been made through healthy tissue, necrosis of the cartilage in
contact with the tube belongs to the rarest of the complications of the
operation. The simple traumatic perichondritis set up by the operation
shows no tendency to eventuate in death of the parts. Equally
rare is cicatricial contraction of the trachea as the direct result of
the operation. That it may follow the healing of the extensive defects
sometimes left by the syphilitic and other processes can readily be
understood; and the same defects, involving as they occasionally do the
loss of large amounts of tissue and destruction of important parts, may
eventuate in the formation of an aërial fistula during or after the
healing process is completed. The occurrence of such a fistulous
opening as the result of a simple and uncomplicated tracheotomy wound
could only be regarded as the evidence of unskilful surgery and
after-treatment. The various plastic operations undertaken for the
repair of such defects are described in the works on general surgery,
notably in the able monograph of Schüller. Dislodgment of the canula
out of the trachea as the result of an insufficiently long tube, or of
neglect to fasten the tapes which hold it properly about the neck, so
that it slips during coughing or the movements of the patient, is an
accident which may not for the moment attract the attention of an
inexperienced surgeon unless laryngeal dyspnoea is urgent. The patient
breathes quietly, the air passing by the sides of the tube, which
apparently is correctly placed. The simple test of ascertaining whether
air be passing through the canula or not, or of making a trial whether
the patient breathe as well when the finger closes the opening of the
outer tube, as he will do if the tube is out of the trachea, will
decide the question. Should the tube have slipped, it is of course at
once to be replaced.
The breaking off of a portion of the inner canula, and the terminal
piece falling down the trachea—several instances of which have been
reported during recent years—is more apt to happen with the
right-angled canula of Durham, the inner tube of which is necessarily
made up of segments held by small rivets: these become in time loosened
and the piece that they held detached. The outer tube of the
hard-rubber canula also has become detached from its collar and dropped
into the trachea. An occasional inspection of the condition of the tube
is therefore desirable.
BRONCHITIS, ACUTE AND CHRONIC; CATARRHAL; MECHANICAL; CAPILLARY; AND
PSEUDO-MEMBRANOUS.
BY N. S. DAVIS, M.D., LL.D.
DEFINITION.—Inflammation of some part or of the whole of the mucous
membrane lining the bronchial tubes between the bifurcation of the
trachea and the alveoli or air-cells of the lungs. The inflammation may
vary in grade from simple hyperæmia, with increased irritability, to
the most intense engorgement, exudation, and tumefaction of the
membrane, and in activity from the most acute and rapidly-progressive
to the most chronic and protracted in duration.
SYNONYMS.—By the earlier writers the disease was called Peri-pneumonia
notha, Angina bronchialis, and sometimes Erysipelas pulmonis. More
recently it has been called Catarrhus suffocativus, Catarrhus
pituitosus, Catarrhus bronchialis, Bronchial catarrh, and Bronchitis;
Fr. Bronchite; Ger. Bronchialentzundung. Adopting the simple name
of bronchitis, acute and chronic, in the further consideration of the
subject I shall group the cases as they occur in general practice under
the heads of Catarrhal, Mechanical, Capillary, and Pseudo-membranous Bronchitis.
HISTORY.—During all the earlier periods of medical history bronchitis
was generally confounded with inflammation of the membrane lining the
larynx and trachea on the one side, and with pneumonia and pulmonary
phthisis on the other. Among the earliest writers who gave more
accurate descriptions of bronchitis as a distinct disease were Badham,
J. P. Frank, and Broussais, in the latter part of the eighteenth
century. Full and accurate descriptions of the disease, differentiating
it from inflammation of other parts of the respiratory organs, were not
given, however, until the discovery of auscultation by Laennec, and its
practical application aided by percussion to the physical examination
of the chest. This important addition to the previous means for
studying the exact location and extent of all diseases within the
chest, and the largely increased attention given about the same time to
the study of morbid anatomy, soon led to as accurate an appreciation of
the existence and extent of disease in any part of the organs of
respiration and circulation as in any of the structures of the human body.
ETIOLOGY.—The causes of bronchitis, like those of all other acute
diseases, may be divided into two classes—namely, predisposing and
exciting. The first embraces all those influences that are capable of
rendering the mucous membrane of the air-passages more susceptible to
impressions, whether by direct increase of the irritability of the
structure or indirectly by altering the quality of the blood and the
tone of the smaller blood-vessels. The second embraces such influences
only as are capable of exciting a direct increase of irritability of
the lining membrane of the bronchial tubes, with congestion of
blood in its capillaries. Among the most common predisposing causes may
be mentioned age, sex, occupation or modes of life, and climatic
influences. As a general rule, the several grades of bronchitis are
more prevalent during childhood and old age than during the active
period of adult life. The British Registrar-General's Report for 1868
contained 33,258 deaths attributed to bronchitis, being 1344 for every
million of inhabitants. Of the whole number, 10,550 died during the
first three years of life, and 18,485 over forty-five years of age,
leaving only 4223 to occur between the ages of three and forty-five
years. This, however, is very far from indicating correctly the
relative prevalence of the disease at the different periods of life,
for the reason that the disease is far more fatal both in early life
and in old age than in the early and middle periods of adult life.1
During the months of February, March, and April, 1882, in San
Francisco, there were 65 deaths reported from bronchitis, of which 37
were of children under five years of age, 25 adults over forty years,
and only 3 persons between five and forty years. During the same months
there were reported 154 deaths from bronchitis in the city of Chicago,
with about the same ratio in regard to age. In the city of
Philadelphia, during the seven years from 1862 to 1869, the deaths from
bronchitis at all periods of life aggregated 969, of which 495 were of
children under five years of age, 14 over five and under fifteen years,
and 460 of persons over fifteen years of age.2 These and similar
mortuary statistics have led to the very general adoption of the
opinion that early childhood and old age are pre-eminently susceptible
to attacks of bronchitis. Yet my own clinical observations and records
relating to the time and number of acute and subacute cases of
bronchitis coming under my own care lead to a very different
conclusion. By reference to those records I find a larger number of
cases occurring between the ages of ten and thirty years than at any
other period of life. Thus, during the first six months of the present
year (1882) I recorded 59 cases of primary bronchitis; that is, cases
not arising secondarily as complications of other diseases. Of this
number, only 5 were children under ten years of age, 38 between ten and
thirty years, and 16 over forty. It is probable that similar results
will be obtained by all who will take the trouble to record the whole
number of cases, instead of simply the number of deaths. The statistics
of mortality in relation to this disease are deceptive, not only in
regard to relative susceptibility of the human system to attacks at the
different periods of life, but also in regard to the ratio of mortality
of the disease itself. It is generally conceded that the chief
mortality from this disease occurs during infancy or early childhood
and in old age, cases rarely terminating fatally in youth or the more
active period of adult life. Careful examination of cases will show
that this fatality at the extremes of life is owing mainly to the
greater tendency of the inflammation at those periods to extend
directly from the bronchioles into the lobules of the lungs, thereby
complicating the bronchitis with lobular pneumonia; and in more than
half the cases reported under the head of bronchitis the fatal result
was caused by the pneumonia instead of the bronchitis.
1 See Reynolds's System of Medicine, Amer. ed., vol. ii.
p. 318.
2 See A Practical Treatise on the Diseases of Children, by
J. F. Meigs, M.D., and William Pepper, M.D., 4th ed., p. 189.
Neither recorded facts nor my own clinical observations show any
decided difference in the susceptibility of the sexes to attacks of
bronchial inflammation.
Those occupations which confine the parties pursuing them much indoors,
and at a temperature either too warm or too cold, strongly predispose
to attacks of inflammation of the membrane lining the respiratory
passages. Habitual exposure to a warm, confined air invites free
exhalation from both the bronchial and cutaneous surfaces, with
increased susceptibility, and consequently renders the individual
more susceptible to all external impressions. Habitual passive exposure
indoors to a low temperature represses the exhalations and causes the
retention of some of the products of tissue-change which by their
presence in the blood render the individual more liable to attacks of
inflammation on the supervention of any exciting cause. For the same
reasons the habitual wearing of too much warm clothing on the one hand,
or too little on the other, predisposes to attacks of bronchial
disease. Another error of importance is the unequal adjustment of
clothing to different parts of the cutaneous surface. In children
especially we often see an abundance of warm clothing over the whole
body, while the legs and feet and neck have but a single covering, and
sometimes none. And even adult women often go out loaded with warm
clothing, while their feet and ankles are protected only by thin shoes
and stockings. All those occupations that surround the workmen with an
atmosphere filled with irritating gases, floating particles of stone,
metal, or charcoal, or with the dust from grain and many vegetable
substances, increase the liability of such workmen to attacks of all
grades of bronchial inflammation.
It is universally conceded that bronchitis, as well as inflammation of
all other parts of the mucous membrane lining the air-passages,
prevails most in such countries as are characterized by a cold, damp,
and variable climate. This can be well illustrated by comparing the
prevalence of this class of diseases in that belt of our own country
lying north of the fortieth parallel of latitude and east of the Rocky
Mountains with the prevalence of the same class in the belt south of
the thirty-third parallel and bordering upon the Atlantic and Gulf of
Mexico. In the former the summers are comparatively short, with brief
periods of high temperature, the winters cold, and the transition
seasons, spring and autumn, long and exceedingly variable, with a
predominance of cold and dampness. In the latter all the conditions
just mentioned are substantially reversed. Perhaps the earliest
reliable statistics we have bearing upon this subject are those
collected by Samuel Forrey from the several military posts occupied by
the United States Army, and given in a series of articles in the
American Journal of Medical Science, and subsequently in an octavo
volume, on the climate of the United States and its influence over the
prevalence of diseases. The valuable facts presented by Forrey were
added to by Daniel Drake, and given in full in his large work on the
topography and diseases of the great interior valley of this continent.
From these sources we learn that the average annual number of attacks
of inflammation of the mucous membrane of the respiratory passages in
every 1000 soldiers at Fort Snelling, in Minnesota, latitude 44° 53'
N., was 600. At Fort King, fifty miles from the Gulf of Mexico,
latitude 28° 58' N., the annual number of attacks average only 101.2 in
every 1000 persons. Again, at Madison Barracks, near Sackett's Harbor,
New York, the average number of attacks for every 1000 persons was
637.2, while at Key West, Florida, the average number of attacks was
208.9, and at Baton Rouge, Louisiana, only 207.2. Lest it should be
thought that these five posts had been selected for the purpose of
showing the most extreme contrasts, it may be added that Drake, after a
laborious comparison of the statistics at all the military posts in the
great interior valley from Fort Snelling at the north to Fort Jessup in
Louisiana, the most southern, makes the "ratio of decrease in bronchial
inflammations" as we pass from the north to the south as 31.5 for each
degree of latitude.3 A similar comparison of the statistics of all
the posts on the Atlantic Slope from Madison Barracks to Key West gives
nearly the same results. The general inference here drawn concerning
the much greater prevalence of bronchitis in the colder and more
variable climate of the northern belt of our country
than in the
southern is fully corroborated by all the facts to be gathered from
observations in civil life.
3 See A Systematic Treatise on the Principal Diseases of
the Interior Valley of North America, etc., etc., 2d Series, pp. 795,
796.
A study of these same military statistics, representing the mean ratio
of the prevalence of diseases of the respiratory passages for a period
of ten years at nearly all the posts, will justify some other
inferences of interest besides the one just stated. According to this
general inference or rule, which is assented to by all the authors
within my reach, the three important factors in the climates most
favorable for producing bronchial inflammation are cold, variableness,
and dampness, the latter being emphasized by most writers as of
predominating influence. Yet the tables before us show that the highest
ratio of prevalence of inflammatory attacks of the mucous membrane of
the respiratory passages in the northern part of the interior valley
was at Fort Snelling, in the immediate vicinity of St. Paul, Minnesota,
being 600 attacks for every 1000 soldiers, while the lowest ratio was
at Fort Dearborn, on the site now occupied by the city of Chicago,
being only 102 for every 1000 soldiers. Looking at the posts in the
eastern part of the northern belt of country, Madison Barracks, at
Sackett's Harbor, at the eastern end of Lake Ontario, gives a ratio of
637 attacks for every 1000 soldiers, while Fort Niagara, at the mouth
of the Niagara River, near the western end of the same lake, gives a
ratio of only 355. Again turning to the posts in the southern belt of
country, the tables show at Fort Jessup, in the interior of Western
Louisiana, a ratio of 432.8, while at Fort Jackson the ratio was only
47.5 and at Fort King 101.2. As Fort Snelling is on the high rolling
prairie of the interior of Minnesota, noted for its cold and dry air,
and Fort Jessup on the elevated arid plateau between the head-waters of
the Sabine and the Red River, they cannot be noted for a high degree of
atmospheric moisture. On the other hand, Fort Dearborn was located on
the south-west shore of Lake Michigan, on the borders of a low and wet
prairie with a substratum of impervious clay, giving all the conditions
favorable for the prevalence of a high degree of atmospheric moisture.
And Forts Jackson and King are both on low alluvial lands only fifty
miles from the Gulf. Again, Fort Niagara is surrounded by all the
conditions favoring a high degree of atmospheric moisture, certainly
equal to those surrounding Madison Barracks in nearly the same
latitude, and yet the ratio of attacks in the latter was nearly double
those in the former. It is evident, therefore, that there exists some
important factor in the climatic relations of the inflammatory
affections of the respiratory passages besides temperature, humidity,
and changeableness. A glance at the topography of the whole country
will show that each of the posts giving a high ratio of
attacks—namely, Madison Barracks and Forts Snelling and Jessup, to
which may be added Forts Gratiot, Crawford, and Wood—are so located as
to be exposed to the prevalence of unusually severe winds or
atmospheric currents either from the north-east or the north-west and
west, with certain relations either to high mountain-ranges or
ocean-currents. For instance, from Madison Barracks the open valley of
the St. Lawrence River extends in a north-easterly direction to the
Atlantic Ocean, where the cold ocean-current is from the north,
favoring the pressure of cold atmospheric currents directly up the
valley from the north-east, reaching its termination at the eastern end
of Lake Ontario with but little diminution of force. The mountains of
Northern New York, Vermont, and New Hampshire seem to prevent the
deflection of these currents to the south, and help to keep them
directly in the line of the valley. That the high ratio of attacks of
bronchial and catarrhal affections at Madison Barracks is largely due
to the influences here described is corroborated by the fact that the
same class of diseases are much more prevalent in the province of
Quebec, through which the valley of the St. Lawrence extends, than in
the province of Ontario, as shown by the Registrar-General's Report in
reference to the several military posts in the Canadas. Turning
to Forts Snelling and Crawford at the north and Jessup at the south, we
find them so situated in relation to the great mountain-chains to the
west as to be fully exposed to the cold and strong atmospheric currents
that sweep over the Plains from the north-west and west with such force
as to justify the popular title of blizzards. Without consuming more
time in details, it may be said that the force and direction of
atmospheric currents have quite as much to do with the development of
inflammations of the air-passages, including all grades of bronchitis,
as either temperature or humidity.
As might be inferred from what has already been said in relation to the
influence of climatic conditions, season of the year is also found to
exert a marked influence over the prevalence of bronchial affections.
Those parts of the year characterized by a low temperature, high winds,
and frequent thermometric changes are accompanied by the highest ratio
of prevalence of inflammations of the respiratory passages. Thus, the
statistics compiled from the records of all the military posts by Drake
show an average ratio for the four quarters of the calendar year of
119.8 for the first quarter, 72.7 for the second, 48.7 for the third,
and 99.6 for the fourth.4 This corresponds closely with the results
of clinical records kept under my own observation through a series of years.
4 See Drake on the Principal Diseases of the Interior
Valley of North America, p. 792.
That tubercular deposits in the lungs, cancerous growths, emphysema,
and previous attacks of bronchitis, all strongly predispose the patient
to further attacks of the last-named disease, is proved by universal
clinical experience.
EXCITING CAUSES.—Exposure to sudden and extreme changes in atmospheric
temperature from warm to cold is almost universally regarded as the
chief exciting cause of inflammation of the bronchial as of all other
parts of the mucous membrane of the air-passages. More accurate and
detailed observations, however, show that such changes of temperature
are seldom productive of diseases of this class unless accompanied by
coincident high winds and humidity. My own studies concerning the
relations between special meteorological conditions and the prevalence
of particular diseases have led me to the following conclusions in
regard to bronchitis and inflammation of the mucous membrane of the
air-passages generally:
First. Many sporadic cases are caused, at any and all seasons of the
year, by exposure of limited portions of the cutaneous surface to cool
or cold currents of air while the rest of the body is well protected.
Females going out with thin shoes and stockings or sitting before open
windows with low-necked dresses, and children out on cold days with
naked legs from short trousers and defective stockings, afford many and
familiar examples of bronchitis from this cause.
Second. The sudden transition from a protracted period of intense dry
cold to a higher temperature with increased atmospheric humidity.
Almost every winter season, in the northern belt of the United States,
east of the Rocky Mountains, is characterized by several periods of
steady dry, cold air, varying from one to three weeks in duration,
during which the mercury in the thermometer often descends more than
20° C. (8–10° F.) below zero, and which generally ends in a sudden
change in the direction of the winds and a marked elevation of
temperature, constituting what is popularly called a thaw. Such changes
are very uniformly accompanied by a general prevalence of catarrhal
affections of the air-passages, including many cases of bronchitis.
This class of cases occur principally in the months of December,
January, and February.
Third. The occurrence of those cold north-east winds that during the
latter part of autumn and early part of spring so often sweep over the
whole extent of our Atlantic coast and press up the valley of the St.
Lawrence to
the great interior lakes, and the still more severe
currents that come during the same seasons from the north-west and
west, over all the wide plains that intervene between the great
mountain-chains to the west and the upper lakes and Mississippi River
to the east, are also accompanied by a high ratio of prevalence of
bronchial affections, as has been already shown from the records of the
several military posts. Most of these severe storms of wind are
accompanied by either snow or rain and a marked increase of ozone or
active oxidizers. In some of the severe snowstorms from the north-east,
occurring in the latter part of February and in March, I have found an
unusual amount of free ammonia. Whether either the ozone or the ammonia
has had anything to do with the production of the bronchitis cannot be
determined until the observations and records now being made under the
auspices of the American Medical Association have been continued for a
few years, by which adequate data will be furnished for reliable deduction.
Besides ordinary meteorological conditions, bronchitis may be produced
by inhaling irritating substances, such as steam, irritating gases,
steel-dust, or minute particles of other metals or stone in workshops,
and the dust encountered in handling grain, etc. The disease has often
occurred in epidemic form without the presence of an obvious exciting
cause. It also frequently occurs in connection with certain general
fevers, more particularly with typhoid, measles, influenza, and
pertussis. It also sometimes, though more rarely, accompanies
rheumatism, constitutional syphilis, and erysipelas. The presence of
tuberculous and cancerous deposits in the lungs almost always provokes
more or less bronchial inflammation during some part of their progress.
SYMPTOMATOLOGY.—The most common form of acute bronchitis, by many
writers styled catarrhal bronchitis, acute bronchial catarrh, etc.,
presents considerable variety of symptoms, according to the extent of
the membrane involved and the intensity of the inflammatory process. As
a general rule, the disease commences with slight chilliness or unusual
sensitiveness to slight changes of temperature, accompanied by a sense
of soreness and oppression behind the sternum and sometimes across the
whole chest, with a frequent and rather dry, harsh cough. In many cases
there is during the first day or two coincident congestion of the
membrane lining the nostrils, fauces, and larynx, causing sneezing,
with some feeling of soreness in the throat and hoarseness, also a
heavy dull pain in the head, much increased by coughing. By the second
day a moderate general fever has supervened, characterized by dryness
and moderate heat of the skin, flushed face, slight increased frequency
and fulness of the pulse, more sense of oppression and soreness in the
chest, with a continuance of harsh, dry cough, which often causes
soreness in the epigastrium, radiating laterally in the direction of
the attachments of the diaphragm to the inner surface of the ribs. On
the second or third day the inflamed membrane begins to be less dry and
the paroxysms of coughing bring up a scanty expectoration of a
tenacious, somewhat frothy mucus, which gradually increases until about
the fourth or fifth day, when it becomes more opaque, sometimes
yellowish, and much more easily expectorated. At the same time that the
expectoration changes to a more opaque condition, the general febrile
symptoms begin gradually to abate, and the cough is accompanied by less
sore pain both in the chest and head.
In the milder class of cases, the decline in all the general symptoms
is so rapid that by the seventh or ninth day, convalescence is
established. But in the more severe cases the more important symptoms
may continue through two weeks, and convalescence not be complete
until the end of the third week. And in some of the cases the
inflammation does not disappear on the subsidence of the febrile
symptoms, but degenerates into a chronic form, causing a continuance of
cough, with some muco-purulent expectoration and slight soreness in the
chest, through an indefinite period of time. The disease is most likely
to take this course when it occurs in young persons having a scrofulous
diathesis, or in connection with eruptive fevers or pertussis, or in
the aged afflicted with rheumatism.
During the active stage of ordinary cases of bronchitis the urinary
secretion is diminished in quantity, redder than natural, and deficient
in chloride of sodium, and the bowels are inactive. But after the
crisis of the disease is passed, as indicated by the character of the
expectoration, the renal and intestinal discharges soon return to their
normal condition.
The results of auscultation and percussion in ordinary bronchitis,
limited to the membrane lining the larger bronchial tubes, are mostly
negative. In some instances during the first or dry stage, the
respiratory or vesicular murmur may be slightly harsher or more dry
than natural, and after the exudation or secretion of mucus, as
indicated by expectoration, there may be some coarse, moist râles,
which are removed temporarily by coughing, but return again in a little
time. These râles are heard much more in cases occurring either in
infancy or in old age than in youth or the middle period of adult life.
Percussion elicits only the natural degree of resonance throughout the
whole course of the disease, except in those rare cases in which
complete occlusion of the bronchial tube has taken place, causing
exclusion of air from certain lobules of the lungs, and consequently a
shade of dulness on percussion over such lobules.
By mechanical bronchitis is meant those cases in which the inflammation
is caused by the direct action of mechanically irritating substances
floating in the inspired air, as fine particles of steel and other
metals, particles of stone, charcoal, and various vegetable powders and
fungi. Such substances, when inhaled, are liable to impinge on the
surface of the bronchial membrane and produce direct irritation and
inflammation, both acute and chronic.
Cases originating from this class of causes differ from ordinary acute
bronchitis chiefly in the mode of beginning and in the greater tendency
to continue in the chronic form. Instead of slight rigors, coryza, and
early development of moderate general fever, the patient generally
complains first, and for several days, of a sense of tickling or
fulness in the air-tubes, with occasional paroxysms of violent coughing
and little expectoration. Sometimes particles of the foreign substance
that is producing the inflammation may be seen mixed with the mucus or
matter expectorated. In many of these cases there is much soreness in
the chest and considerable dyspnoea, especially during the night,
followed by severe coughing in the morning, and a more free discharge
of mucus occasionally containing little streaks of blood, but which is
never intimately intermixed with the sputa as in pneumonia. If the
patient, by change of occupation or otherwise, ceases to be exposed to
the further action of the exciting cause, the symptoms soon begin to
abate, and a complete recovery may take place in from two to four
weeks. If exposure to the further action of the exciting cause is not
avoided, the disease will necessarily assume a chronic form, and in
many cases produce such changes as to materially shorten the life of
the patient.
By this term is meant inflammation in the smaller bronchial tubes, but
not necessarily involving the true bronchioles as they terminate in the
air-cells. It may arise from all the causes that are capable of
exciting inflammation in the larger and medium-sized tubes. It may
occur at any period of life, but is most frequent in infancy and early
childhood, and next in persons past the middle period of life.
The chief differences in the clinical history of this and ordinary
catarrhal bronchitis arise from the greater obstruction to the ingress
and egress of air through the inflamed tubes. The same degree of
tumefaction of the membrane that occasions but little obstruction in
the larger tubes is capable of completely obstructing many of the
smaller ones, and thereby causing much dyspnoea and sense of
oppression, with frequency of respiration, accompanied at first by an
abundance of dry râles in all parts of the chest, followed later by the
complete intermixture of dry sounds and moist submucous râles, the
latter caused by more or less exudation or secretion of mucus from the
inflamed mucous membrane. The addition of the tenacious mucous
exudation to the previous tumefaction of the membrane, often so far
obstructs the ingress of air to the air-cells of the lungs that the
respirations become short, very frequent and noisy, with blueness of
the lips, coldness of the extremities, drowsiness, and soon death from
suffocation. This result, however, is seldom met with except in quite
young children and in persons enfeebled by age or by previous disease.
In cases which do not thus tend to an early fatal result from the
direct obstruction of the bronchi the respirations continue frequent,
in young children sometimes reaching 50 or 60 respirations per minute,
with much dyspnoea and restlessness; the pulse is quick, but not in
proportion to the respirations; the expression of countenance is
anxious and often slightly bloated, with a leaden hue of the prolabia;
the wings of the nose expand and the chest heaves with each
inspiration, giving a great variety of dry, whistling sounds generally
throughout the whole chest, which after the first two or three days
become mixed with sharply-defined submucous râles, and in the later
stages give place to the latter entirely. The cough is frequent and
inefficient, on account of the difficulty of getting sufficient air to
make it satisfactory. The temperature varies from 38° to 39.5° C.
(101–103° F.), seldom rising above the latter figure unless complicated
with lobular pneumonia. The urine is generally scanty and deficient in
the chlorine salts, and the bowels are inactive. The labored efforts of
breathing in many cases make the upper and anterior part of the chest
appear more prominent than natural, and even more resonant on
percussion on account of temporary emphysema from over-distension of
the air-cells in those parts, while in some parts of the lower and
posterior portions there is less expansion and less resonance than
natural from the occlusion of some of the bronchi and the partial
obstruction of others leading to those parts of the lungs.
Between the third and fifth days usually the mucous exudation, which up
to that time had been scanty and tenacious, becomes more abundant and
more opaque, and in two or three days more assumes a distinct
muco-purulent character and is much more easily expectorated. As that
which comes from the smaller bronchial tubes is less mixed with air,
and consequently less frothy than that which comes from the larger
tubes, the two qualities of matter may often be recognized in the same
mouthful of sputa; and if the whole be placed in water, that from the
smaller tubes will drop lower in the water, or sink to the bottom if
detached from the other, which floats freely upon the surface.
In acute cases, at the same time that the expectoration becomes more
opaque and more easily dislodged by coughing, all the more important
symptoms begin slightly to improve, and by the end of the second
week convalescence is fairly established. Many cases, however, are less
acute, slower in progress, and do not reach convalescence in less than
two or four weeks; and many of this class manifest a strong tendency to
continue indefinitely in a chronic form, more especially in persons
past the middle period of life. In some of the cases that do not
continue in a chronic form, the bronchial membrane is left in a
condition of such susceptibility that the attack is renewed on the
slightest exposure to the exciting causes.
Although many systematic writers on practical medicine make no mention
of this form of bronchitis except as a complication of general
rheumatic fever, yet cases both of acute and chronic inflammation of
the bronchi, of unmistakable rheumatic character, have so often come
under my observation that I am constrained to recognize it as a
distinct form of disease. In regard to the relative frequency of the
occurrence of this class of cases, I find in a brief report concerning
965 cases of chronic pulmonary disease, read in the medical section of
the American Medical Association by F. H. Davis in 1877,5 the
following classification of the cases:
| Chronic catarrhal bronchitis |
403 |
| Chronic rheumatic bronchitis |
283 |
| Chronic bronchitis accompanied by gastric derangement and
spasmodic dyspnoea |
119 |
| Chronic bronchitis, modified by syphilitic disease |
37 |
| Hereditary pulmonary tuberculosis |
56 |
| Inflammatory pulmonary phthisis |
67 |
| Total |
965 |
It will be seen that, of the 842 cases of chronic bronchitis included
in the table, the writer classes 283, or a trifle more than 33 per
cent., as of rheumatic character. That the relative proportion of acute
cases of a distinct rheumatic character is less than those of a chronic
grade I have no doubt, and yet their number is not so small as to be
insignificant or unworthy of careful attention.
5 See Transactions of American Medical Association, vol.
xxviii. p. 269, 1877.
They differ in clinical history from ordinary acute bronchitis chiefly
in the following particulars: Etiologically, a large proportion of them
occur in persons of a rheumatic diathesis, either hereditary or
acquired, and at those seasons of the year characterized by a
predominance of cold and damp air with frequent changes of temperature.
Symptomatically, they are characterized from the beginning by more
continuous dull pain in the chest, often extending to the attachments
of the diaphragm, the shoulders, and the dorsal portion of the spine;
by more persistent dry, harsh cough, often exhibiting a marked
spasmodic character and accompanied by a great aggravation of the pains
in different parts of the chest. When the smaller bronchi are involved
the stage of dry râles is much more protracted, the dyspnoea and
suffocative paroxysms of coughing more uniformly aggravated at night;
and when mucous exudation does take place it remains scanty and viscid,
rarely presenting a distinct muco-purulent character unless the case is
protracted into a chronic form, and sometimes not then. During the
active stage the urine is less in quantity and more decidedly acid in
reaction than natural, and the bowels generally costive.
When not interfered with by appropriate treatment, these cases run a
much more protracted course, and more frequently degenerate into a
chronic form,
than those of an ordinary catarrhal character. When
they are thus allowed to run a protracted course or to continue in a
chronic form, they manifest another tendency of great
importance—namely, to have the inflammation extend by continuity from
the fibrous and muscular structures of the small bronchi into the
connective tissue of the pulmonary lobules, inducing sclerosis of the
latter tissue and consequent compression or obliteration of the alveoli
or air-cells, and permanent contraction of the chest. Much and careful
clinical observation has satisfied me that many of the cases now
classed by writers as fibrous and inflammatory phthisis began as simple
acute or subacute rheumatic bronchitis, which, being renewed at every
return of the cold, damp, and changeable part of the year, not only
ultimately caused permanent thickening of the bronchial structures, but
gradually invaded portions of the connective tissue of the lungs, and
induced similar pathological changes in it, constituting the sclerosis
just mentioned.
Pseudo-membranous Bronchitis.
This affection has been described by different writers under the
additional names of plastic, croupous or croupal, and diphtheritic
bronchitis. The extension of the inflammation and membranous exudation
to the bronchial tubes in cases of diphtheria and pseudo-membranous
tracheitis and laryngitis or croup, is of frequent occurrence. But as a
distinct disease limited to the bronchial membrane it is of
comparatively rare occurrence.
In 1854, T. B. Peacock noticed in the Transactions of the London
Pathological Society 34 cases collected from European sources; Biermer
in 1867 increased the number to 58; Kretschy in 1874 added 10, and
Chevstok 4 more cases—making in all 72 cases in Europe. In 1879, W. C.
Glasgow of St. Louis read to the medical section of the American
Medical Association an interesting report on the subject of plastic
bronchitis, in which he notices 23 cases which had occurred in this
country, accounts of which were obtained from an extensive
correspondence with leading physicians in all parts of the United
States, as well as from reference to our periodical medical
literature.6 These statistics are certainly sufficient to justify the
statement that the disease is of rare occurrence both in this country
and in Europe.
6 See Transactions of the American Medical Association,
vol. xxx. p. 177, 1879.
The statistics thus far collected show a much greater prevalence of the
disease in males than in females, and that the larger number of cases
occur between the ages of fifteen and fifty years, although one case is
reported by T. G. Simons of Charleston, S. C., as quoted by Glasgow, at
four years of age, and Goumoens one at seventy-two. In a large
proportion of the cases reported the disease existed in a chronic form.
When acute, and affecting a large portion of the bronchial membrane, it
is liable to lead to an early fatal termination from obstruction to the
ingress of air to the air-cells of the lungs. But in many cases the
disease has extended to only a limited number of the bronchi, and
recovery has generally taken place in from two to three weeks.
The symptoms differ from those of ordinary bronchitis in only two
important particulars—namely, the more violent and suffocative
character of the cough, and the actual appearance of shreds, patches,
or casts of pseudo-membrane in the matters raised and ejected by
coughing. The latter is the only reliable diagnostic symptom by which
it can be certainly differentiated from all other forms of bronchial
inflammation. When the membranous exudation is discharged in shreds or
small pieces, it may readily escape the attention of the physician, and
even considerable casts when expectorated are in some cases so
surrounded with mucus and collapsed into a slightly yellowish mass in
the central part of the mouthful expectorated, that they might be
regarded as only
a more muco-purulent part of the mucous
secretion. If the whole is thrown into water, however, and agitated a
little, the membranous patches and casts will be quickly unfolded in
such a manner as to be easily recognized. It is distinguished from
mucus by placing it in a solution of acetic acid, which causes it to
swell, while mucus contracts in a similar solution. It has the
appearance of having been formed in concentric layers, and is sometimes
cast-off so complete as to present a continuous representation of one
or both primary and several of the secondary bronchial tubes. Under the
microscope it has the same fibrillated appearance as other
pseudo-membranous formations.
Cases of acute and subacute bronchitis belonging to either of the five
varieties just described may be protracted until they assume a chronic
form, and other cases of each variety are met with which have been
chronic from the beginning. This form of the disease is met with in
aged persons more frequently than at an earlier period of life. In
children it sometimes follows as a sequel of measles and whooping
cough, and in adults is often associated with tuberculosis, emphysema,
and cardiac diseases.
ETIOLOGY.—Chronic bronchitis is capable of originating from any and
all the causes that have been enumerated as capable of producing the
more acute forms of the disease, and consequently prevails most under
the same conditions of topography, climate, and social relations.
SYMPTOMATOLOGY.—The symptoms of ordinary chronic catarrhal bronchitis
differ from those accompanying the acute form of the disease, chiefly
in the absence of general fever and the existence of much less pain or
feeling of soreness and oppression in the chest. The patient generally
complains of a rather harsh, full cough, usually more severe on first
retiring to bed at night and on rising in the morning, but occurring at
intervals through the day, and accompanied by a mucous or muco-purulent
expectoration varying much in its amount and tenacity. In the great
majority of cases occurring in young persons and in the first part of
adult life, the expectoration is simply a whitish or slightly opaque
mucus, more or less frothy from the intermixture of minute bubbles of
air, and easily dislodged, especially in the mornings. In old persons
and in cases which have continued a long time, the expectoration often
becomes more copious and more decidedly purulent, with slight
feverishness at night and some loss of flesh.
In all the cases except those last mentioned the general health of the
patient is but little impaired, the appetite and secretions usually
remaining nearly natural. Those who pursue indoor occupations or are
sedentary in their habits will be prone to constipation and imperfect
digestion—more, however, from the circumstances just mentioned than
from the effects of the bronchial disease. All cases of chronic
bronchitis are subject to temporary aggravation by exposure to a cold
and damp atmosphere, whether indoors or out, and are also very
susceptible to increase from the inhalation of air containing dust or
floating particles of solid matter or of irritating gases.
Cases of ordinary chronic bronchitis rarely prove fatal without the
intercurrence of some other disease, and yet there is no natural limit
to their duration. In many cases the symptoms almost disappear during
the warm months of summer, but return with the first period of cold and
wet weather of autumn. Such patients usually find permanent relief by
changing their residence to a mild and dry climate.
The symptoms of the rheumatic grade of chronic bronchitis differ from
those just described mostly in the more severe paroxysmal character of
the
cough, with either no expectoration or only a scanty quantity
of a glairy, tenacious mucus; in the more soreness or dull pain in the
intercostal muscles and attachments of the diaphragm; and in the more
marked influence of sudden and severe meteorological changes. Perhaps
the most marked and distressing cases of this variety of bronchitis are
those we occasionally meet with in old persons whose joints, especially
those of the extremities, have long been stiffened and sometimes
enlarged from chronic rheumatism, and who are harassed and worn from a
harsh, suffocative cough, the worst paroxysms of which are almost
always during the latter part of the night and the early morning,
accompanied by the expectoration of considerable quantities of a thick,
viscid, and very tenacious mucus, which is dislodged with so much
difficulty that in the midst of the more violent paroxysms of coughing
the action of the stomach is reversed and its contents ejected by
vomiting. This is very liable to happen just after breakfast, and to
occasion the loss of the morning meal. The condition of these patients
is very generally ameliorated during the warm months of summer, but on
the whole they emaciate and grow more helpless from year to year, until
they die either from exhaustion or the supervention of pulmonary
sclerosis (fibroid phthisis), endocarditis, or chronic diarrhoea. There
is one grade of rheumatic irritation which is liable to attack the
fibrous texture of the smaller bronchi and to give rise to a very
persistent form of asthma, which increases with every returning cold
season of the year; but as asthma in all of its forms is treated in
other parts of this work, I only allude to it in this connection.
PATHOLOGY AND MORBID ANATOMY OF
BRONCHITIS.—The special pathology of
inflammation involving the mucous membrane and other structures of the
bronchi does not differ from that of similar grades of inflammation in
any other structures of the body. It consists essentially of an
increase or disturbance of those properties of living organized matter
which regulate the molecular movements constituting nutrition,
disintegration, secretion, and cell-evolution to such a degree as to
cause accumulation of blood in the capillaries, followed by exudation
and increased cell-proliferation, which may organize into plastic
material or pseudo-membrane or degenerate into pus, according to the
coincident circumstances and condition of the patient.
Consequently, the anatomical changes resulting from acute catarrhal
bronchitis are, in the early stage, more or less intense congestion of
blood in the vessels, causing redness and tumefaction of the membrane,
soon followed by an increased flow of mucus, with increase or
proliferation of mucous corpuscles and epithelium-cells, while
leucocytes or white corpuscles are seen permeating the capillary walls
and penetrating the submucous tissue or mingling with the increased
epithelium upon the surface. These several inflammatory products are
seen adhering to the surface of the inflamed membrane and in the
smaller tubes, often so filling their calibre as to greatly interfere
with the ingress and egress of air through them, and of course adding
to the dyspnoea that characterizes the capillary form of bronchitis.
During the latter stage of the disease pus-corpuscles are seen freely
intermingled with the mucus, and, owing to the exfoliation of much of
the epithelium, the surface of the mucous membrane often appears
irregular, abraded, or ulcerated.
When the inflammation has been protracted into a chronic form, the
vessels appear less congested, but the cell-proliferations continue
both in the mucous and submucous structures, causing thickening and
increased density, with a still more purulent quality of secretion. The
bronchial glands are also sometimes found enlarged, and either
softened, colored with pigment, or, more rarely, calcified.
In addition to the foregoing changes, in many cases of the capillary
form of bronchitis some lobules of the lungs are found collapsed from
the complete occlusion of the bronchi leading to them by the
accumulation of tenacious mucus with other inflammatory products. And
in the same cases the air-cells in other parts of the lungs, more
frequently the upper and anterior parts, are enlarged from
over-distension, constituting a degree of emphysema.
In very chronic cases, especially of the rheumatic variety,
considerable hypertrophy of the connective tissue of the bronchi has
been found, and in other cases atrophy of the same tissue, the latter
generally accompanied by more or less dilatation of the tubes.
In pseudo-membranous or croupous bronchitis the bronchial tubes are
found lined, and in some cases filled, with a plastic exudate. Usually,
only a limited number of the bronchi are affected. The tube-casts that
may be expelled are generally in the form of balls, which may be
unrolled, and which will then be found to be fragments or complete
cylindrical casts of the tubes. They are, when expelled, usually
yellowish and often sanious. When washed they are white. There are
frequently points of enlargement along the casts which are caused
either by the presence of air-bubbles within them, or by a more rapid
exudation from that point on the bronchus. The largest casts are
usually solid and laminated in structure; the smaller ones more
frequently are hollow, containing a greater or less number of
air-bubbles; the smallest consist of a single solid thread. Under the
microscope the casts seem to be composed of a structureless or
fibrinous substance holding numerous mucus and pus-cells, more or less
numerous globules of fat, and occasional epithelial cells; seldom red
blood-corpuscles, although these may be numerous on the surface. The
casts are usually moderately compact, firm, and elastic. Toward the end
of the disease, however, they may be less firm. In some cases toward
the close of life epithelial cells are abundant in them, but in other
cases on post-mortem examination the epithelial lining of the bronchi
is found nearly or quite entire. The mucous membrane may be much
reddened, or, on the other hand paler than normal. The submucous
tissues are also sometimes involved in the swelling, and occasionally
infiltrated with serum.7
7 For a representation of one of the most complete specimens
of pseudo-membranous casts from the bronchi the reader is referred to
the paper of Glasgow in the Transactions of the American Medical
Association, already referred to.
DIAGNOSIS.—The principal diseases from which acute inflammation of any
part of the bronchial mucous membrane needs to be differentiated are
pneumonia, pleurisy, laryngitis, tracheitis, and asthma, while it is
still more important to keep a clear line of diagnosis between the
chronic grades of bronchial inflammation and the earlier stages of
pulmonary phthisis and of emphysema. From nearly all the diseases named
it is separated by negative evidence or the absence of symptoms and
physical signs characteristic of those affections. It neither presents
the rusty expectoration or high temperature or fine crepitant râle of
pneumonia, nor the acute pains or short stifled cough or
friction-sounds of pleurisy in the early stage, and still less is there
in the middle and later stages any of the dulness on percussion that
characterizes the corresponding stages of the other two diseases. In
true asthma the active symptoms are distinctly paroxysmal, without
fever or increase of temperature, and the respiration during the
paroxysms is slow, with marked prolongation of the expiratory act;
while in bronchitis, both catarrhal and capillary, the symptoms are
continuous, the temperature increased, and the respirations more
frequent than natural. All grades of bronchitis are easily
distinguished from laryngitis and tracheitis by auscultation, which
enables us
to trace all the morbid sounds to the chest in the
former, and to the front part of the neck in the two latter.
The great advantage of recognizing pulmonary tuberculosis and other
forms of phthisis in the early stage of the disease makes the diagnosis
between it and chronic bronchitis a matter of primary importance. This
can be readily done by all practitioners who have acquired a reasonable
degree of skill in the practice of auscultation and percussion. In all
forms and stages of pulmonary phthisis, whether from primary tubercular
deposits, pneumonic exudation followed by caseous degeneration, or from
interstitial fibroid sclerosis, there is increased vocal fremitus and
diminished resonance on percussion; neither of which is present in any
grade of uncomplicated bronchitis. It is true that in the advanced
stage of some very severe cases of capillary bronchitis there occurs
sufficient pulmonary oedema to increase the vocal fremitus and diminish
the resonance over some parts of the chest; but the accompanying
symptoms and immediately preceding history of such cases are sufficient
to separate them from any stage of phthisis. The same remark is
applicable to those rare cases in which an attack of pseudo-membranous
bronchitis results in the complete occlusion of one or more of the
bronchi and the permanent collapse of the pulmonary lobules to which
the occluded tubes lead. If in addition to the plain difference in the
physical signs already mentioned we remember that in all the forms of
phthisis there is progressive loss of flesh, some increase of
temperature and acceleration of pulse, with a contraction of the upper
and anterior part of the chest, while none of these changes result from
bronchitis alone, there should be no difficulty in keeping the line of
diagnosis clear between these two diseases. And yet there is probably
no more frequent or important error committed in diagnosis than that of
mistaking the early stage of pulmonary phthisis for bronchitis. This
may arise in part from the fact that bronchitis often supervenes and
continues coincidently with phthisis. But the practitioner should
remember that whenever there is increased vocal fremitus and diminished
resonance in any given case there is some altered condition of the
lung-structure, and consequently some form of disease besides
bronchitis, however plain the ordinary symptoms of the latter may be at
the same time.
From pulmonary emphysema, chronic bronchitis is distinguished chiefly
by the abnormally-increased resonance on percussion in the former,
especially over the upper and anterior parts of the chest, and the
peculiar depression of the spaces above the clavicles and between the
ribs at the beginning of the inspiratory act, and their return to
over-fulness near its close; while none of these changes accompany any
grade of simple bronchial inflammation.
PROGNOSIS.—In the ordinary form of acute and chronic bronchitis there
is very little tendency to terminate fatally except when it attacks
infants or persons infirm from age. And even when it occurs at these
extremes of life the fatal terminations are usually caused by the
supervention of lobular pneumonia as a complication, and not from the
bronchial inflammation alone. Severe cases of capillary bronchitis are
more dangerous, and in young children and aged or debilitated persons
often prove fatal before the end of the first week of their progress by
the direct obstruction to the entrance of air into the air-cells of the
lungs. The pseudo-membranous or plastic bronchitis is still more
dangerous. It has been estimated that one out of every five dies. But
the statistics concerning the number and character of cases are not
sufficient to furnish a reliable deduction of the ratio of mortality.
The duration of acute attacks of bronchitis of all varieties from which
recovery takes place is from one to three weeks. Uncomplicated cases of
chronic bronchitis seldom prove fatal, neither is there any self-limit
to their duration. Many cases undergo marked improvement during the
warm
months of summer, but suffer a renewal of all the more
severe symptoms on the return of the cold and wet weather of autumn. In
other cases the symptoms continue nearly the same through all the
seasons of the year and until an advanced period of life.
TREATMENT.—There are certain leading objects to be accomplished in the
treatment of all grades of inflammation affecting the mucous membrane
and connective tissue of the bronchial tubes—namely, (a) to diminish
or overcome the morbid excitability of the inflamed part; (b) to
relieve the vascular hyperæmia or fulness of blood in the vessels, and
thereby limit the amount of exudation or morbid secretion and
consequent dyspnoea; (c) to counteract or relieve secondary
functional disturbances, such as increased heat and dryness of the
skin, diminished renal and intestinal activity, and nervous
restlessness; (d) to hasten the removal of such plastic exudations as
may have caused thickening and induration of the inflamed structures or
formed layers or patches of false membrane on the bronchial surface,
and to lessen the tendency to establish a stage of purulent
degeneration or suppurative action in the inflamed part; (e) to
regulate diet, drinks, exercise, and clothing in such a way as to
sustain healthy nutrition and prevent the further action of
predisposing and exciting causes.
The first three objects to be accomplished belong more particularly to
the early stage of acute and subacute attacks, but are present in some
degree throughout the whole course of the disease; while the last two
belong to the latter stages of the acute and to all stages of the
chronic grades of the inflammation. While the foregoing indications to
be fulfilled or objects to be accomplished are present in all the
various grades and stages of inflammation of the bronchi, the
particular means for accomplishing them will be modified by the age and
previous physical condition of the patient, the nature of the
predisposing and exciting causes, the extent of the disease, and the
stage of its advancement; or, in other words, the nature and extent of
the pathological changes already accomplished. For instance: the same
remedial agents that would be most efficient in relieving the morbid
excitability and the vascular fulness of the first stage of acute
inflammation in a young or middle-aged and previously healthy, vigorous
subject might be positively injurious, or even fatal, if used in the
same stage of inflammation in a subject previously anæmic and feeble or
debilitated from age or from causes capable of impairing the quality of
the blood and favoring a typhoid condition of the system. Consequently,
the practitioner who not only sees clearly the objects most desirable
to accomplish, but who most judiciously selects and adjusts the means
or agents he uses to the special conditions of each patient, will meet
with the highest degree of clinical success.
In the first stage of acute attacks involving the bronchi of both lungs
in vigorous adult persons, and especially if the inflammation extends
into the smaller tubes, causing much dyspnoea and dry râles, there is
no single remedy that will so certainly and speedily check the intense
engorgement of vessels in the bronchial membranes, and thereby gain
time for the action of other remedies, as one prompt and liberal
abstraction of blood by venesection. In cases of a little less
severity, and in children, the application of from two to twelve
leeches to the upper and anterior part of the chest, the number being
regulated by the age of the patient, will be a good substitute for the
venesection. And in case leeches are not at hand extensive dry cupping
over both the anterior and posterior parts of the chest may be applied
with much benefit. Immediately after the venesection, leeching, or
cupping, and without these in cases of only ordinary severity, the
whole chest may be enveloped in an emollient poultice or in folded
napkins wet in warm water and covered with oiled silk. At the same time
the following combination may be given internally:
| No. 1. Rx. |
Liquoris ammonii acetatis, |
(60.0 c.c.) fluidounce ij; |
| |
Tincturæ opii camphoratæ, |
(75.0 c.c.) fluidounce iiss; |
| |
Vini antimonii, |
(15.0 c.c.) fluidounce ss; |
| |
Tincturæ veratri viridis, |
(6.0 c.c.) fluidrachm iss. |
M.—Sig. Give to an adult 4 cubic centimeters or 1 teaspoonful in a
tablespoonful of water every two, three, or four hours, according to
the severity of the case. The same may be given to children, the dose
being properly adjusted to the age of the child.
If the tongue be coated, the bowels inactive, and urine high-colored,
from 6 to 30 centigrams (grs. j–v) of calomel, according to the age of
the patient, may be given, and followed in four or five hours by a
saline laxative sufficient to procure two or three evacuations from the
bowels. Under the influence of these remedies the high fever and great
sense of soreness and oppression in the chest which exist in the first
stage of the more acute cases in previously healthy subjects rapidly
diminish, giving place to more moist râles, easier breathing, and some
expectoration. As soon as such amelioration of symptoms has been
obtained, the mixture containing veratrum viride should be
discontinued, and the following formula substituted in its place:
| No. 2. Rx. |
Syrupi scillæ comp. |
(45.0 c.c.) fluidounce iss; |
| |
Tincturæ sanguinariæ, |
(15.0 c.c.) ounce ss; |
| |
Tincturæ opii camphoratæ, |
(60.0 c.c.) fluidounce ij. |
M.—Sig. Give to an adult 4 cubic centimeters in a little additional
water every three or four hours.
If the patient suffers much from severe sore pain in the head,
aggravated by coughing, or from nervous restlessness, the addition of
bromide of potassium, 16 grams (drachm iv), to the above formula will
render it more efficient in relieving these symptoms and in promoting
rest. Under such quieting and expectorant influences, aided by a mild
laxative when needed, the cough, soreness, and oppression in the chest,
and all other active symptoms, diminish from day to day, and
convalescence ensues in from seven to nine days.
If after the first three or four days the temperature rises in the
evening and the cough becomes more troublesome, interfering with rest
during the first part of the night, followed by some sweating in the
early morning, a single dose composed of sulphate of quinia from 3 to 6
decigrams (gr. v–x), pulverized sanguinaria-root 3 centigrams (gr. ½),
and codeine 16 milligrams (gr. ¼) given between six and eight o'clock
each evening for three or four evenings, will often contribute to the
rest of the patient and hasten the establishment of convalescence.
Cases are sometimes met with, especially in patients debilitated by
previous ill-health or age, in which the fever subsides after the first
three or four days, leaving the patient with a feeling of unusual
weakness, a deep harassing cough, copious muco-purulent expectoration,
and little or no appetite. In such cases tonics and the more
stimulating class of expectorants are indicated. A mixture of equal
parts of the syrup of Prunus virginiana, syrup of senega, and
camphorated tincture of opium, given in doses of 4 cubic centimeters or
one teaspoonful every four or six hours, and 13 centigrams (gr. ij) of
quinia three times a day, will often cause a rapid improvement in all
the symptoms. In some of the cases last described there is added to the
other symptoms a troublesome nausea and disposition to vomit with the
paroxysms of coughing, in which I have found the following formula a
good substitute for the mixture containing the prunus virginiana and senega:
| No. 3. Rx. |
Acidi carbolici, |
(0.50 grams) gr. viij; |
| |
Glycerinæ, |
(30.0 c.c.) fluidounce j; |
| |
Tincturæ opii camphoratæ, |
(60.0 c.c.) fluidounce ij; |
| |
Aquæ, |
(60.0 c.c.) fluidounce ij. |
M.—Sig. Give 4 cubic centimeters (fluidrachm j) or 1 teaspoonful
before each mealtime and at bedtime, giving the quinia a little after
the meals.
If more anodyne influence is required to procure rest at night, 16
milligrams (gr. ¼) of codeine may be added to the teaspoonful of
carbolic acid mixture given at bedtime. If, as sometimes happens in
cases of acute bronchitis, both of the catarrhal and capillary
varieties, the inflammation invades some of the lobules of the lungs,
as indicated by undue rise of temperature, greater expansion of the
wings of the nose during inspiration, with short expiration, and
diminished resonance with fine crepitation over limited portions of the
chest, I have found the most certain and speedy relief to follow the
application of a blister over the seat of the pneumonia and the
internal use of the following formula:
| No. 4. Rx. |
Ammonii chloridi, |
(12.00 grams) drachm iij; |
| |
Antimonii et potassii tartratis, |
(0.13 grams) gr. ij; |
| |
Morphiæ sulphatis, |
(0.20 grams) gr. iij; |
| |
Extract, glycyrrhizæ fluidi, |
(30.0 c.c.) fluidounce j; |
| |
Syrupi, |
(90.0 c.c.) fluidounce iij. |
M.—Sig. Give to adults 4 cubic centimeters (fluidrachm j) or 1
teaspoonful, mixed with a tablespoonful of water, every three or four
hours until some relief is obtained, and then at longer intervals. For
children the doses must be diminished in proportion to the diminution
of age. Quinine and laxatives may be used in these cases under the same
indications as in uncomplicated bronchitis.
In the severe attacks of capillary bronchitis in young children many
writers recommend emetics, and subsequently nauseating doses of
antimony or ipecacuanha. But I have not seen sufficient benefit result
from emetic doses of these agents to compensate for the early
prostration, and sometimes continued gastric irritability, which they
induce. I prefer the proper application of leeches at the very
beginning, followed by emollient applications to the chest, and the
same remedies internally as already mentioned, aided, perhaps, by an
earlier use of quinine and digitalis if the cardiac action becomes weak
and frequent. In all this class of cases, however, much caution should
be exercised in regard to the use of opiates, either alone or in
combination with other remedial agents, lest their narcotizing
influence should diminish the force and frequency of the respiratory
movements too much, and encourage the accumulation of the inflammatory
products in the smaller bronchi to such a degree as to produce apnoea
or death by the exclusion of air from the alveoli or air-cells of the
lungs. And yet just enough of these quieting agents to diminish
excitability and allay excessive restlessness is as desirable in
children as in adults.
In the plastic or pseudo-membranous form of bronchitis it is an object
of much importance, in the first stage, to limit the amount of plastic
exudation, and later to hasten the loosening and disintegration or
discharge of such layers of false membrane as may have formed on the
bronchial mucous surface. For these purposes alterative doses of
calomel may be given alternately with the doses of the formula
containing the liquor ammonii acetatis already given (see Formula No.
1) during the first twenty-four hours, and subsequently pretty full
doses of the iodides of sodium or potassium or of the bicarbonates. In
acute cases in children, when the symptoms indicate that the false
membrane is loosening and the dyspnoea is great, an emetic that will
induce prompt and free vomiting may hasten its expulsion and afford
much relief.
In the cases which have been described as rheumatic bronchitis of the
more acute or active grade I have seen the most prompt and satisfactory
degree of relief follow the administration of the following combination
of remedies in the early stage:
| No. 5. Rx. |
Sodii salicylatis, |
(25.00 grams) drachm vj; |
| |
Glycerinæ, |
(15.00 c.c.) fluidrachm iv; |
| |
Vini colchici radicis, |
(25.00 c.c.) fluidrachm vj; |
| |
Syrupi scillæ compositi, |
(45.00 c.c.) fluidounce iss; |
| |
Tincturæ opii camphoratæ, |
(60.00 c.c.) fluidounce ij. |
M.—Sig. Give 4 cubic centimeters (fluidrachm j) every three or four
hours in a little additional water.
In several cases in which this grade of inflammation was located
chiefly in the smaller bronchi, causing very distressing and persistent
dyspnoea, I have found an equal mixture of the wine of colchicum-root
and the acetated tincture of opium, given in doses of 25 to 30 minims
every three hours at first, to afford more relief than any other
remedies I could use; and after some degree of relief had been
obtained, by lengthening the interval between the doses to four or six
hours and continuing it a few days, all the symptoms were removed. When
the disease occurs in old persons, accompanied by severe paroxysms of
coughing and only a scanty and very viscid mucous expectoration, much
benefit may sometimes be derived from the use of the carbonated
alkalies, such as the carbonate of ammonium or bicarbonate of sodium,
dissolved in an equal mixture of the fluid extract of the Phytolacca
decandra, liquor ammonii acetatis, and camphorated tincture of opium,
in such proportions that the patient will get 3 decigrams (gr. v) of
carbonate of ammonium in each dose of the mixture.
It is proper to remark that there are many mild attacks of bronchitis,
caused by exposure to sudden and severe meteorological changes, which
if seen during the first twenty-four hours can be speedily arrested by
a hot or stimulating foot-bath and a full dose of the compound powder
of opium and ipecacuanha (Dover's powder), taken in the evening, and
followed the next morning by a saline laxative and two or three
moderate doses of quinine during the day. Similar results can also be
obtained in some cases by the use of any agents that will allay
irritability and at the same time produce a free or copious elimination
from the skin and kidneys. An efficient diaphoretic dose of
pilocarpine, or a full warm bath, followed by two or three moderate
doses of quinine, will succeed well if employed in the initial stage of
the disease. Unfortunately, but few cases come under the care of the
physician until after this stage is past.
TREATMENT OF CHRONIC BRONCHITIS.—Most of the cases of chronic
bronchitis are treated satisfactorily by a more moderate use of the
same remedial agents that have been recommended in the acute and
subacute grades of the disease, aided by a judicious regulation of
diet, dress, and exercise. In the great majority of cases of the
ordinary chronic catarrhal variety of bronchitis the formula already
given, numbered 4, or the one numbered 2, if given to adults in doses
of 4 cubic centimeters (fluidrachm j) before each meal and at bedtime,
mixed with a tablespoonful of water, will afford the necessary relief
without confining the patient to the house. If the bowels become
constipated while using either of these prescriptions, the evil may be
obviated by taking one of the following pills every evening:
| No. 6. Rx. |
Extract. hyoscyami, |
(2.00 grams) gr. xxx; |
| |
Ferri sulphatis, |
(2.00 grams) gr. xxx; |
| |
Pulveris aloës, |
(2.00 grams) gr. xxx; |
| |
Pilulæ hydrargyri, |
(2.00 grams) gr. xxx. |
M. et ft. pil. No. XXX. If one pill taken every evening does not prove
sufficient to prompt one natural intestinal evacuation each morning,
another can be taken after breakfast. The patient should adhere to a
plain, nutritious, and easily digestible diet, avoiding the use of all
varieties of alcoholic drinks, wear good warm underclothes of flannel
all the time, and take moderate daily outdoor exercise so long as the
strength will permit.
In addition to the several remedies that have been mentioned as
applicable to the treatment of the different varieties of acute and
subacute bronchitis, there are many others that have been found more or
less beneficial in the treatment of chronic cases. Among the more
important of these are the iodide of potassium and sodium, the
grindelia robusta, eucalyptus globulus, oenothera biennis, cimicifuga
racemosa, asclepias tuberosa, balsams copaiba and tolu, gum benzoin,
turpentine, cod-liver oil, and the hypophosphites of sodium, calcium,
and iron; and a still larger number that have been used for inhalation.
As a general rule, when the cough is harsh and the expectoration
scanty, with the predominance of dry râles, such remedies as the
muriate and iodide of ammonium and the iodides of potassium and sodium,
given in conjunction with small doses of antimony and some mild
anodyne, will produce the best effects. On the other hand, if the
expectoration is abundant and of a muco-purulent character, the
balsamic and terebinthinate remedies, given in connection with such
tonics as the lacto-phosphate of calcium, phosphate of iron, sulphate
of quinia and strychnia with codia, hyoscyamia, or lupulin, at night to
procure rest, will afford the greatest relief. In some of these cases I
have obtained very good effects from a combination of two parts of the
syrup of iodide of calcium with one of the fluid extract of hops, given
in doses of 4 cubic centimeters (fluidrachm j) each morning, noon,
tea-time, and bedtime.
When chronic bronchitis is complicated with pharyngitis and
laryngo-tracheitis, much palliative influence may be obtained by
judiciously-directed inhalations, either in the form of vapor or
atomization. But when the disease is limited to the bronchi alone,
inhalations have much less influence over its progress or in relieving
the more distressing symptoms. And unless the nature of the material
used is judiciously selected with reference to the particular stage and
grade of the disease, the inhalations will be more likely to do harm
than good. There are two conditions of the bronchi met with in
different cases of chronic bronchial inflammation to which local
applications can be made in the form of vapor with much benefit. The
first is indicated by an abundant purulent or muco-purulent
expectoration, sometimes fetid and at other times not. For such the
full deep inhalation of aqueous vapor impregnated with some antiseptic
and anodyne will be of great service. One of the best combinations that
can be used for this purpose is that of carbolic acid with camphorated
tincture of opium in the proportion of 2 grams of the former (gr. xxx)
to 90 cubic centimeters (fluidounce iij) of the latter; 4 cubic centimeters
(fluidrachm j) of this mixture may be put into 250 cubic centimeters
(fluidounce viij) of hot water in an inhaling-bottle and the vapor
inhaled freely, five minutes at a time, two or three times each day.
The second condition alluded to is characterized by a persistent,
harsh, irritating cough, with little or no expectoration, indicating a
sensitive and congested condition of the mucous membrane with
diminished secretion. Such cases may generally be much relieved by
adding to the antiseptic and anodyne mixture just given some one of the
oleo-resin or balsamic preparations, of which perhaps none are more
efficient than that which is known in the shops as oil of Scotch pine.
Four cubic centimeters (fluidrachm j) of this may be added directly to
the quantity of the other ingredients already given, and then used in
the same manner. The combination thus used appears to allay the morbid
sensitiveness and speedily establishes a better secretory action.
There is another important class of cases met with most frequently in
persons of both sexes between twelve and twenty years of age. They
present a narrow, imperfectly-developed chest, with so sensitive a
condition of the bronchial membrane that every trifling exposure to
cold and damp air renews the vascular hyperæmia and cough, until both
become permanent and the morbid process extends into the connective
tissue of the pulmonary lobules, establishing what some call
interstitial pneumonia and others fibroid phthisis. In the earlier
stage of all this class of cases the systematic daily practice of full,
deep inhalations of pure atmospheric air, coupled with a judicious
exercise of the muscles of the chest and arms, will do more to remove
all symptoms of bronchial disease and preserve the general health of
the patient than all the medicines that have been hitherto devised.
There is much evidence in favor of using compressed air for inhalation
in these and some other cases of bronchial inflammation. The late F. H.
Davis of this city, who during his brief professional career gave much
attention to the treatment of diseases of the respiratory organs, and
had good opportunities for clinical observation, says, when speaking of
the same class of young subjects, that "the inhalation of compressed
air for from five to ten minutes once or twice a day produced marked
and rapid improvement in all the cases. The size of the chest on full
inspiration was increased from one-half inch to one inch in the first
month, and a habit of fuller, deeper breathing and a more erect
carriage was established."8 But he adds, with proper emphasis, that
the inhalations to be permanently curative must be continued faithfully
for many months, and be accompanied by a judicious regulation of all
the habits of life.
8 See paper read before the Chicago Society of Physicians
and Surgeons, April, 1877, on "The Respiration of Compressed and
Rarefied Air in Pulmonary Diseases."
Every physician of much practical experience knows, however, that, in
defiance of all the remedies and methods of treatment hitherto devised,
there are many cases of chronic bronchial inflammation which will
continue, and be aggravated at every returning cold season of the year,
so long as the patient lives in a climate characterized by a
predominance of cold and damp air with frequent and extreme
thermometric changes. And yet a large proportion of these, by changing
their residence to a mild and comparatively dry climate, either greatly
improve or entirely recover. Consequently, in all the more severe and
persistent cases such a change is of paramount importance, and should
be made whenever the pecuniary circumstances of the patient will
permit. Probably the best districts in our own country to which the
class of patients under consideration can resort are the southern half
of California, the more moderately elevated places in New Mexico and
the western part of Texas, Mobile in Alabama, Aiken in South Carolina,
and most of the interior parts of Georgia and Florida. My own
observations lead me to the conclusion that the unfortunate invalid,
suffering from any grade of chronic bronchial inflammation, can find in
some of the regions named all the relief that could be gained in the
most celebrated health-resorts on the other side of the Atlantic. But
adherence to strictly temperate and judicious habits of life, with
regular daily outdoor exercise, is essential to the welfare of the
invalid in whatever climate he may choose to reside.
In the foregoing pages I have said nothing concerning the management of
those cases of asthma, emphysema, interstitial pneumonia, etc. which
often occur either as complications during the progress of bronchial
inflammations or as sequelæ, simply because they will all be fully
considered in the articles embracing those topics in other parts of
this work.
SYNONYMS.—Asthma convulsivum (Willis); Spasmus bronchialis (Romberg);
Asthma nervosum; Krampf der bronchien.
DEFINITION.—A violent form of paroxysmal dyspnoea, not dependent upon
structural lesion; characterized by wheezing respiration, with great
prolongation of the expiration, and by the absence of all symptoms of
the disease during the intervals between the attacks.
HISTORY.—Derived from the Greek [Greek: asthmatnô] to gasp for breath,
the term asthma was employed by the older writers to designate a
variety of affections of which embarrassed respiration was the most
prominent symptom, thus including a great number of diseases which a
more extended knowledge of pathology has since distributed among other
nosological groups. By the earlier authors simple embarrassment of
breathing was designated as dyspnoea; if attended with wheezing it was
called asthma; while those forms in which the difficulty in respiration
was so great as to prevent the patient from lying down were
appropriately styled orthopnoea (Celsus). Ignorant to a great extent of
pathological anatomy and unprovided with the improved methods of
physical diagnosis which we now possess, they described as asthma not
only the dyspnoea due to cardiac and pulmonary diseases, but also that
occasioned by affections of the pleura and greater vessels. Covering
such an extensive range of territory, it was found necessary to
subdivide the disease into a number of varieties, each author
classifying them according to his conception of the cause, seat, and
nature of the trouble. Some of these—e.g. a. dyspepticum—still find
a place in medical literature, but the vast majority of them, having
ceased to be of any practical significance, have been discarded, and
are now only interesting as examples of the crude and fanciful notions
which prevailed in an age during which science rather retrograded than
advanced.1 Of the writers of this period, Willis in the seventeenth
century is especially worthy of notice as being the first to describe
the nervous character of asthma. Without discarding the accepted forms
of the disease, he mentions another variety, characterized by spasmodic
action of the muscles of the chest, to which he gave the name asthma convulsivum.
1 "Van Helmont, discarding the ancient doctrine of the four
humors, attributed asthma to an error of the Archeus, which he
conceived to be enthroned in the stomach and to constitute the source
of all diseased as well as of all healthy phenomena. This principle, he
supposed, sent forth from the stomach a peculiar fluid, which, when it
became diseased, gives rise to a morbid state of the parts to which it
was conveyed. He moreover imagined that this fluid sometimes mixed
itself with the male semen, and thus formed a compound which, as one of
its constituents is the means provided by nature for the propagation of
the species, possesses the power of generating a disease of hereditary
character. Thus, when this compound was conveyed to the articulations,
he affirmed it produced gout, and when it took its direction to the
lungs it then occasioned asthma" (Baltimore Med. and Surg. Journ. and
Review, Baltimore, 1833, p. 300).
The improvement in physical diagnosis resulting from the brilliant
discoveries of Auenbrugger and Laennec greatly curtailed the domain of
asthma.
With the aid of auscultation and percussion it was
discovered that most of the cases hitherto regarded as asthma were only
symptoms of some organic disease. Many distinguished authorities,
particularly of the French school, went so far as to declare that there
existed no such disease as asthma, and that in every case the dyspnoea
and other phenomena described under that name were merely symptoms of
some organic affection.
Although very generally received at first, it was not long before this
too-sweeping reform encountered opposition from various quarters. Cases
were observed with marked asthmatic symptoms in which, after death, the
most careful examination failed to reveal the slightest trace of
textural lesion. The discovery by Reisseisen of muscular fibres even in
the minutest bronchi, and the demonstration of their electric
contractility by Longet and Williams, afforded a ready explanation of
these cases, and led to the opinion—which has since been generally
received—that asthma in the modern acceptation of the term is simply a
neurosis. The more recent theories in regard to the nature of asthma
will be more fully discussed in the portion of our article devoted to
the pathology of the disease.
SYMPTOMS AND COURSE.—The following description of an attack of asthma
by Trousseau, who was himself an asthmatic, is perhaps the best that
has ever been written: "An individual in perfect health goes to bed
feeling as well as usual, and drops off quietly to sleep, but after an
hour or two he is suddenly awakened by a most distressing attack of
dyspnoea. He feels as though his chest were constricted or compressed,
and has a sense of considerable distress; he breathes with difficulty,
and his breathing is accompanied by a laryngo-tracheal whistling sound.
The dyspnoea and sense of anxiety increasing, he sits up, rests on his
hands, with his arms put back, while his face is turgid, occasionally
livid, red, or bluish, his eyes prominent, and his skin bedewed with
perspiration. He is soon obliged to jump from his bed, and if the room
in which he sleeps be not very lofty he hastens to throw his window
open in search of air. Fresh air, playing freely about, relieves him.
Yet the fit lasts one or two hours or more, and then terminates. The
face recovers its natural complexion and ceases to be turgid. The
urine, which was at first clear and was passed rather frequently, now
diminishes in quantity, becomes redder, and sometimes deposits a
sediment. At last the patient lies down and falls to sleep."
The next day the patient may feel well enough to pursue his accustomed
avocation, and may remain free from all symptoms of the disease until
another attack comes on; but more frequently he is confined to the
house, if not to bed, the slightest exertion being sufficient to cause
dyspnoea; and during the following night there is a repetition of the paroxysm.
If unchecked by treatment, the disease may continue for days, weeks,
and in some instances even for months, the paroxysms often increasing
in severity until, as in other nervous affections, it ultimately wears
itself out.
There is no regularity in the occurrence of the attacks. In some cases
they recur every few days, while in others there may be an interval of
weeks or months between the seizures. Even in the same case, although
the individual paroxysms of the attack may come on at the same hour,
there is, except in rare instances, no regularity in the recurrence of
the attack itself; and when it does recur at a certain time it is
almost always due to some cause which, as in hay asthma, exerts its
influence only at that particular period.
In the great majority of cases asthma comes on without any warning
whatsoever, but occasionally it is preceded by certain sensations which
to the experienced asthmatic are a sure indication that an attack is
impending. With some it is only a feeling of ill-defined discomfort;
others complain of various disorders of the digestive system—a sense
of dryness of the mouth and pharynx, uncomfortable distension of the
epigastrium with eructation of gases from the stomach, and more
or less obstinate constipation. A troublesome itching of the skin often
precedes the attack. Some experience a feeling of constriction around
the throat; a profuse secretion of clear urine is a symptom of this
stage. Frequent gaping, frontal and occipital headache, are mentioned;
but far more constant than all of these are certain symptoms indicative
of a mild grade of acute catarrh of the respiratory organs—coryza,
with swelling of the Schneiderian membrane and discharge from the
nostrils, sneezing, redness of the conjunctivæ with increased
lachrymation, and later, as the irritation extends downward, more or
less cough.
The attack almost always comes on after midnight, and, as a rule,
between the hours of two and six o'clock in the morning. Salter states
that nineteen out of twenty cases occur between two and four A.M. There
are, however, occasional exceptions to this rule; sometimes the patient
is attacked soon after retiring, and Trousseau cites the case of his
mother, who always had her attacks between eight and ten in the
forenoon, and also that of a tailor, whose paroxysms invariably came on
at three o'clock in the afternoon. Indeed, there is no hour of the
twenty-four during which the seizure may not take place. Various
attempts have been made to explain why it is that the paroxysms of
asthma almost invariably occur during the latter half of the night.
Many attribute it to a stasis of blood in the lungs caused by the
recumbent posture of the patient, while others claim that it is due to
a dulling of reflex impression, the patient during sleep failing to
perceive the necessity of breathing. Germain Sée, who discredits both
theories, inquires why, if the above explanations are correct, does the
attack not come on soon after retiring, as is the case with the
dyspnoea of cardiac diseases.
The paroxysm of asthma develops very rapidly, but not so suddenly as is
claimed by many authors, several minutes to half an hour or more
elapsing before it attains its full height.2
2 Germain Sée in Nouveau Dictionnaire de Médecine et de
Chirurgie, tome iii. p. 617, Paris, 1865.
The patient, experiencing an urgent desire for breath, instinctively
places himself in the position most favorable for the ready admission
of air into the lungs. If in bed he sits up, and, resting on his hands
or grasping his knees with them, he so fixes the body that the muscles
of respiration may work to the greatest advantage. The shoulders are
drawn up and the head thrown back. The expression of the face is one of
great anxiety—pale at first, then red, and as the attack increases in
severity assumes a dusky, bluish tint; the mouth is partially opened,
the nostrils are dilated; the eyes, the conjunctivæ of which are much
injected, are prominent, with a wild, staring look; and the forehead is
moist with perspiration. Others in their desperate struggle for breath
spring from the bed, throw open the window, and, regardless of
everything save what they believe to be impending suffocation,
recklessly gasp in the cold night air. Sometimes the sufferer prefers
to kneel before a table or some other article of furniture, supporting
his head with his hands. Whatever posture he assumes, he is actuated by
the one impulse of placing himself in the position that will enable him
to use to the greatest advantage the muscles of respiration and their
auxiliaries. The sterno-cleido-mastoid muscles are contracted to the
utmost, and, projecting like hard cords, with the aid of other muscles
draw the chest upward. The patient instinctively avoids every
unnecessary exertion as having a tendency to aggravate his dyspnoea; he
speaks but little, and when questioned usually replies with a motion of
the head.
In ordinary respiration the inspiratory movement is twice as long as
the expirium, the latter, except in forced expiration, being a purely
passive act. In asthma this rule is reversed, the expiratory movement
being four or five times as long as the inspirium, and is often so slow
that it fills the whole of the pause which usually intervenes
between the completion of one respiration and the beginning of another.
It is sometimes so slow "that it seems as though the lung would never
empty itself." In the desperate struggle for breath the respiratory
muscles are exerted to the utmost in futile endeavors to expand the
chest; with each inspiration there is an elongation of the thorax, but
no lateral movement. The chest moves up and down, but there is no
expansion; "the muscles tug at the ribs, but the ribs refuse to rise"
(Salter), the walls of the chest remaining immovable.
Notwithstanding the all but tetanic contraction of the diaphragm, there
is during each inspiration a sinking in of the epigastrium, and in
severe cases also of the spaces above and below the clavicles. During
expiration the abdominal muscles, especially the recti, are hard and
tense, the pressure thus exerted being sometimes sufficient to expel
the contents of the lower bowel and bladder.3 The transversus is also
tightly contracted, and a cross furrow above the umbilicus indicates
that the contraction of its upper half is opposed to the contents of
the abdomen forced down by the distended lung (Biermer). Although the
dyspnoea is great, there is no increase in the frequency of the
respirations so long as the patient remains quiet, but, on the
contrary, they are often less frequent than in health. This slowing of
the respiration is also observed in the dyspnoea from laryngeal
stenosis in croup, etc.; but in these cases we do not have the
prolonged expiration which is so characteristic of asthma (Biermer). At
every breath which the patient takes there is a peculiar wheezing sound
which may be heard distinctly all over the room; it is usually heard
only during expiration, but some authors (Biermer) claim that it is
also audible during inspiration.
3 Bamberger's case, as quoted by Riegel, Ziemssen's
Pathologie u. Therapie, Leipzig, 1875, Band iv. 2, S. 282.
On auscultating the chest it will be found that the ordinary vesicular
murmur is either entirely absent, or if heard it is only over very
limited areas. In the place of it we have an endless and ever-changing
variety of dry sounds, such as whistling, cooing, mewing, snoring,
etc., technically styled sibilant or sonorous ronchi. They are usually
equally diffused over both lungs, but are sometimes confined to one.
The sibilant râles afford an index of the degree of spasm, being in
mild cases equally audible during both inspiration and expiration,
while in severe attacks they are louder during expiration (Biermer).
That the vesicular murmur cannot be heard is due not only to its being
masked by the louder ronchi, but also to the absence of the condition
necessary for its production, the spasmodic constriction of the
bronchial tubes or their plugging with tough, viscid mucus preventing
the entrance of sufficient air to produce the sound. Sometimes a
hitherto occluded tube becomes pervious, and we have vesicular
respiration where a moment before only dry sibilant râles were heard.
Usually at the close of the attack, when cough sets in, there are
occasional moist râles. These become more frequent as the expectoration
becomes more abundant. Frequently, however, the paroxysm terminates
much more abruptly, the spasm relaxes, and the air rushing through the
tubes gives rise to puerile respiration.
During the paroxysm there is, even in the early stages of asthma, more
or less distension of the lungs, measurement of the chest showing that
its circumference is four to eight centimeters greater than before the
attack (Beau). This transitory emphysema, which must not be confounded
with that due to structural changes observed in old cases, disappears
with the attack, and the lung returns to its normal condition. This
distension causes the exaggerated resonance obtained by percussion
which is one of the most constant symptoms. At the base of the lung,
especially posteriorly and laterally, there is a peculiar modification
of the percussion sound to which Biermer has applied the name
Schachtelton, from its resemblance to the note produced by striking
an empty pasteboard box. Besides this exaggerated resonance, it
will be found that the line of dulness on the right side, which marks
the upper border of the liver, is fully two inches lower during the
paroxysm than before, and that the area of cardiac dulness is somewhat
diminished by the overlapping of the distended lung-tissue (Riegel).
Another peculiarity elicited by percussion, and to which Bamberger was
the first to direct attention, is that in some rare cases instead of
moving vertically the line of hepatic dulness remains unchanged during
both acts of respiration.
Toward the close of the attack the congested mucous membrane of the
bronchi begins to secrete, and there is more or less cough. The matter
expectorated consists at first of little balls of tough,
semi-transparent mucus not much larger than a pea. It is exceedingly
tenacious, and is raised with great difficulty. Examined under the
microscope, the sputum is found to consist "of a great number of
corpuscles, some of which are polyhedral in form with rounded angles;
they are pale, homogeneous, and slightly granular. At first sight they
resemble pus-corpuscles, but they are much larger, less circular in
form, and have no nucleus. In addition to these corpuscles there are
others which are oval, elongated, fusiform, and sometimes linear in
shape, but all of them appear to be of the same nature and possess the
same refracting power as the corpuscles first mentioned. They are all
of them agglomerated in a sort of viscous matter."4 The expectoration
often contains blood, and in some rare instances profuse hemorrhages
have been known to occur. Sometimes the matter has particles of soot
and coal-dust intermingled with it, the so-called carbonaceous sputum
(Sée). In addition to the cells above described, the sputa contains
small yellowish-green masses or threads in which are imbedded the
peculiar octahedral crystals which Leyden has ingeniously connected
with the etiology of asthma, and to which we shall again have occasion
to refer.5 Ungar has recently also discovered crystals of oxalate of
lime in the sputa.
4 Germain Sée, Nouveau Dictionnaire de Médecine et de
Chirurgie, pp. 612, 613; also, Salter, Asthma, its Pathology and
Treatment, Am. ed., p. 944.
5 Riegel, in Ziemssen's Handbuch d. Pathologie u.
Therapie, vol. iv. 2, pp. 268, 285.
Laryngoscopic examination reveals more or less congestion of the
air-passages. "In ordinary respiration the glottis is widely open
during inspiration, and at each expiration the arytenoid cartilages
approach each other so as to narrow the glottis; but in the labored
respiration of asthma the glottis is fixed in the condition of
expiration; that is, the glottis is narrowed, and the air enters and is
expired through the same narrow space."6
6 Steavenson, Spasmodic Asthma, p. 23.
The embarrassment of respiration and the pressure of the air in the
distended alveolæ by impeding the capillary circulation of the lungs
prevent the left auricle from receiving its full supply of blood; hence
the pulse is small and weak during the paroxysm, but regains its
natural volume as soon as its immediate effects are over. The action of
the heart, like every other phenomenon of asthma, is subject to
constant variation. At one moment it beats tumultuously, while at the
next its action may be so feeble as to cause temporary syncope (Sée).
The venous blood, unable to overcome the obstacles to its passage, is
forced back into the vessels, causing distension of the cervical veins
and the jugular pulse sometimes observed in severe attacks. The bluish
hue of the face in bad cases is due to cyanosis resulting from
insufficient aëration of the blood. The paroxysm is unattended with
fever, the temperature, if altered at all, being rather below than
above the normal. Coldness of the face and hands is quite a common
symptom in protracted cases.
In addition to the nervous sensations described among the premonitory
symptoms, patients have been known to suffer from disturbances of a
more
serious nature during the paroxysm. In some instances there
is complete loss of consciousness, and Riegel7 states that such cases
have been known to have tetanic convulsions of the trunk and extremities.
7 Loc. cit. p. 285.
The course of an attack of asthma is in most cases quite typical, the
paroxysms recurring nightly for an indefinite period, and usually
increasing in severity until, as in epilepsy and other nervous
diseases, it finally exhausts itself. On awaking from the sleep which
usually succeeds the final paroxysm the patient, unless the attack has
been very mild and of short duration, feels weak and exhausted, but
there is no tendency to the recurrence of the dyspnoea; on the
contrary, he may expose himself with perfect impunity to the causes
which at other times would be certain to produce an attack. The chest
feels stiff and sore, the cough and expectoration diminish, and in a
few days disappear, and if the disease has produced no organic lesion
the patient returns to his usual state of health.
DURATION.—The duration of asthma, except in young persons and in those
rare cases in which the cause can be discovered and removed, is very
indefinite, the disease lasting for years, if not for life. As the
patient grows older the attacks become less severe, but are more
frequent. Sometimes a case which has recurred for years and defied the
most energetic treatment will all at once recover of itself.
SEQUELÆ.—Although bronchial asthma is essentially a neurosis, and
therefore purely functional in its character, it is rare for it to
continue for any great length of time without causing some organic
affection of the lungs or heart.
The most common sequel of asthma is emphysema. The bronchial tubes
being more or less completely closed, either by contraction of their
muscular fibres or by plugs of thick, viscid mucus, the air pent up in
the parts beyond the obstruction is subjected to the negative pressure
produced by the exaggerated inspiratory act, becomes rarefied, and, in
obedience to the diminished resistance induced by the partial vacuum in
the thorax, causes distension of the air-cells. This condition
continues until, the tubes having again become pervious, the natural
elasticity of the lung-tissue, aided by the expiratory muscles, forces
out the air and permits them to return to their natural size. This is
the transitory emphysema to which we have already alluded. Germain
Sée8 regards it as analogous to the paralytic emphysema which occurs
the moment the pneumogastric is divided. With repeated attacks the
air-cells lose their elasticity and remain permanently dilated. Owing
to the constant distension, the walls of the alveolæ become more and
more attenuated, until, finally giving way, two or more of them
coalesce, forming one large cell. The symptoms of this condition are
the same as those of ordinary vesicular emphysema.
8 Op. cit., p. 637.
Owing to partial occlusion of the afferent bronchi and the altered
conditions of pressure mentioned, the blood accumulates in the
capillaries during the paroxysm, the lung-cells do not receive their
adequate supply of air, and oxygenation is imperfect. In the early
stages of the disease this congestion is only temporary, and disappears
with the removal of the obstruction, but in those cases in which the
attacks are severe and frequent the vessels lose their contractility
and remain permanently congested.
The state of chronic congestion just mentioned is occasionally attended
with serous exudation into the interalveolar tissue, which by pressing
upon the adjacent air-cells causes their obliteration. This oedema,
with the remains of the compressed air-cells and the viscid mucus
stagnating in the finer tubes, forms the little islets of carnified
tissue known as lobular pneumonia.
The most frequent change observed in the bronchial tubes in old cases
of asthma is hypertrophy of their muscular fibres, causing thickening
of their
walls and diminished calibre. In other cases they are
dilated, but this condition is due more to the concomitant bronchial
catarrh than to the asthma.
Obstructed in its course through the lungs, the venous blood
accumulates in the pulmonary artery, and, pressing back upon the right
ventricle, excites it to increased action, which in the course of time
leads to hypertrophy of its muscular fibres and dilatation of its cavity.
In the early stages of asthma, the face is usually pale during the
intervals between the paroxysms, but when the latter become more
frequent the impeded circulation causes stasis in the peripheral
vessels. The imperfectly-oxygenated blood gives the face a dusky hue,
and in severe cases it may become bluish or even violet-colored. The
eyes are prominent, owing to the enlargement of the orbital veins
(Sée), and the conjunctivæ congested and watery.9
9 For a description of symptoms of the above-mentioned
secondary affections the reader is referred to the articles on
EMPHYSEMA and
HEART DISEASE.
ETIOLOGY.—Predisposing Causes.—Every one is not liable to asthma, and
the fact that out of a large number exposed to its exciting causes only
a few are attacked justifies the assumption that there is an inherent
tendency to the disease. That this tendency is hereditary in its nature
is conceded by every prominent writer on asthma except Lebert, who
believes this to be only occasionally the case. Thus, of 35 cases
collected by Salter, heredity could be traced in 14, of whom 7
inherited the disease from the father, and the remainder from
grandparents and other relations. Ramadge gives an instance in which
the disease appeared in four generations: an asthmatic father had four
children, three of whom inherited the disease; one of the daughters
married, and of her two children one became asthmatic; the other
escaped, but the disease reappeared in one of her children.10
10 Germain Sée, op. cit., p. 668.
The hereditary tendency may skip one generation, as is the case with
Steavenson,11 who inherited asthma from his grandfather, his father's
generation having been entirely free from the disease. In other cases
it may alternate with some other neurosis or with gout or rheumatism;
for instance, the children of an asthmatic father may be epileptic or
gouty and the grandchildren asthmatic, or the asthmatic tendency may
develop in one child of an asthmatic family and the gouty diathesis in
another. It is by no means necessary for the hereditary transmission of
the disease that the father should be asthmatic when the child is
conceived, as there are many cases recorded in which asthma developed
in children whose fathers had completely recovered before they
contracted marriage and never had any subsequent return of the disease.
11 W. E. Steavenson, Spasmodic Asthma, London, 1882, p.
8.
All authorities agree that asthma is much more frequent among males
than females. Of Théry's cases, 60 were females and 80 males. The more
recent statistics of Salter show that the males exceed the females in
the proportion of two to one. This undue frequency of a purely nervous
disease among males appears at first to be at variance with the
generally-received opinion that such affections pertain rather to the
female sex; but on investigating the ages at which the attacks first
come on it will be found that between the fifteenth and thirtieth
years—that is, during the period when sexual function is most
active—the proportion is reversed, females being attacked much oftener
than males.
Asthma occurs more frequently in childhood than at any subsequent
period—a fact which may be explained by the great susceptibility of
young children to catarrhal affections of the air-passages and to the
frequent occurrence at that age of measles and whooping cough (Salter).
Of 225 cases collected by Salter, 71 occurred before the tenth year,
and of these, 10 began during the first year, the youngest of them
being only fourteen days old at the time of the attack. From ten
to twenty it occurs less frequently than at any other period of life,
but from that age to the fortieth year there is a steady increase in
the number of cases. During the next decade, from forty to fifty, the
disease diminishes in frequency, and from that period on the number of
cases continues to grow smaller and smaller with advancing years,
comparatively few commencing after the fiftieth year.
The following tabular statement, compiled by Salter, shows the
comparative frequency of asthma during the various periods of life:
| From |
1 to 10 |
years, |
71 |
cases. |
| " |
10 to 20 |
" |
30 |
" |
| " |
20 to 30 |
" |
39 |
" |
| " |
30 to 40 |
" |
44 |
" |
| " |
40 to 50 |
" |
24 |
" |
| " |
50 to 60 |
" |
12 |
" |
| " |
60 to 70 |
" |
4 |
" |
| " |
70 to 80 |
" |
1 |
" |
These figures demonstrate the fallacy of the popular idea that old
people are especially liable to asthma. Its prevalence during the later
periods of life is due to the fact that while, on the one hand, the
affection rarely causes death, on the other it is scarcely ever curable
except during childhood, and thus the cases contracted at different
ages accumulate and form a large aggregate as life advances.
Those cases occurring in childhood and late in life are likely to be
associated with more or less bronchial catarrh, while those which come
on when the body has attained its fullest development are almost
invariably purely nervous in character.
The period of life at which asthma commences is an important element in
the prognosis of the disease, the cases occurring in early childhood
being likely to end in recovery, while those coming on later in life
are exceedingly protracted in their course and liable to lead to
organic diseases of the heart or lungs.
Asthma does not appear to be influenced by the seasons, some authors
claiming that it is most frequent in summer, while others maintain that
the greatest number of cases occur in winter.
Exciting Causes.—Bronchial asthma being a neurosis of the
pneumogastric nerve, its exciting causes may be divided into those
which act upon the nerve directly, and those which are reflected from
more remote parts or organs.
In the first class the irritant may act upon the nerve at its origin in
the medulla oblongata or upon some part of its continuity. Various
poisons, organic or inorganic, when introduced into the system may so
change the character and composition of the blood as to interfere with
the nutrition of the respiratory centre, and thus cause more or less
embarrassment of respiration; but the attacks of dyspnoea due to these
causes are more continuous than those of ordinary asthma, and are
wanting in many of the symptoms which we have described as
characteristic of that disease. These forms of dyspnoea are usually the
result either of some constitutional disease or of some poison
introduced into the system, both of which act by diminishing the
proportion of red corpuscles in the blood. Of this we have examples in
the dyspnoea sometimes observed in syphilis and malarial fever and in
lead and mercurial poisoning—the so-called a. saturninum and a.
mercuriale. It is true that there have been instances in which the
paroxysms of asthma have come on at regular intervals and have yielded
to quinine, but it is not regarded as proved that such cases were due
to malarial poisoning (Sée).
Enlarged bronchial glands pressing upon the pneumogastric nerve may
cause asthma, and this explains why it is so frequent in children after
attacks of measles and whooping cough (Williams and Biermer). Others
have remarked that asthma is often coincident with hypertrophied
tonsils (Schaeffer). In the great majority of cases the exciting cause
does not act directly upon the pneumogastric nerve, but upon the
skin or some other remote organ, whence it is transmitted to the
nervous centre and reflected back through the nerves of respiration to
the bronchi.
Biermer believes that the irritant in many cases, instead of being
directly transmitted to the medulla oblongata, causes a fluxion to the
exposed mucous membrane. He thinks that the absence of catarrhal
symptoms is more apparent than real, the evidences of congestion being
unappreciable during the early stages of the disease. According to
Riegel,12 the action of the irritant may be explained in one of three
different ways—viz. 1st, both the spasm and the fluxion may be the
common result of the irritant; 2d, the catarrh may cause the spasm; or,
3d, the spasm may secondarily produce catarrh.
12 Op. cit., p. 256.
Although cold may not be so frequent a cause of asthma as was formerly
supposed, low temperature undoubtedly acts as an irritant upon the
terminal branches of the respiratory nerves, especially the
pneumogastric, and in the manner just described may produce spasmodic
contraction of the bronchi. The effect of cold is of course much more
deleterious when it is associated with sudden changes and diminished
barometric pressure, high winds from the east and north being
particularly prejudicial. Aside from its meteorological
characteristics, the locality itself exercises a potent influence in
the production of asthma; and here, again, we have an example of the
capricious character of the disease. A patient who for years has
suffered with asthma may change his residence and find immediate
relief, but of the special factors which engender the disease in one
place and cure it in another we know as yet but little. It is, however,
a generally acknowledged fact that removal from the country to a
crowded city will often diminish the severity and frequency of the
attacks, and English writers mention numbers of cases of asthma which
have been permanently cured by a prolonged residence in the foggy
atmosphere of London. A very slight change is often sufficient to
afford relief, and sometimes removal to another part of the same city
is all that is necessary. The town of Aiken in South Carolina is
divided by a ravine into two sections: the elevation, soil, and
exposure are alike in almost every respect, but persons have been known
to suffer severely with asthma on one side and to enjoy perfect
exemption from it on the other. A gentleman who resides at Bath in the
same neighborhood is perfectly free from asthma at his home, but
invariably has an attack as soon as the train begins to cross the
Savannah River at Augusta, which is only a few miles distant. More
remarkable still is the case mentioned by a French writer of a young
man who was unable to sleep in the front rooms of a house without
having a paroxysm, but who did not experience the slightest
inconvenience when he occupied the back rooms.
Although removal to the city frequently affords relief, there are
exceptions to the rule, and many cases are recorded where a change of
residence to the country has effected a cure. Ozone, of which but
little is as yet known, is supposed by some to be a cause of asthma,
and it is not unlikely that the relief afforded by removal to a large
city may be partly due to the relatively small proportion of this agent
in the atmosphere of crowded localities.
Dust of various kinds, the pollen of plants, certain vapors, gases,
smoke, and the emanations from many species of animals, have all been
known to excite attacks of asthma. Some persons are so sensitive that
the simple act of brushing their clothes is sufficient to bring on a
paroxysm. Others are unable to inhale the perfume of roses, lilies,
heliotropes, and many other flowers without suffering with an attack.
The dust of hay will often cause paroxysms even in those who are not
hay-fever subjects. Since Cullen first published the case of an
apothecary's wife who had asthma whenever ipecac was powdered in her
husband's shop numerous cases of a similar nature have
been
recorded. Ramadge relates the case of an employé in the East India
Company who was compelled to relinquish a lucrative appointment because
the smell of tea always provoked a paroxysm of asthma. Many persons are
unable to come into close proximity with horses, rabbits, cats, and
other animals without suffering, and Austin Flint of New York
experienced great inconvenience when absent from home from sleeping
upon feather pillows. In his case the asthmatic attack was not brought
on by all pillows, but what it was that made one kind more active than
another he was unable to determine.
In persons predisposed to bronchial asthma the eating of any
indigestible substance may of itself be sufficient to cause an attack,
and even an ordinarily full meal, if partaken of late in the day, may
have the same effect. Dyspepsia in its various forms and the presence
of irritating substances in the intestinal canal are such frequent
causes of asthma that they have led to the establishment of several
special varieties of the disease—e.g. a. dyspepticum, a. verminosum.
Asthma is frequently due to uterine and ovarian disorders, the
so-called a. uterinum.
Voltolini of Breslau has described cases which were evidently due to
the presence of naso-pharyngeal polypi, the attacks disappearing with
their removal and reappearing with their renewed growth. These
statements have been confirmed by subsequent cases observed by
Haenisch. Attention has lately been directed to a number of cases in
which the asthmatic paroxysm was found to be associated with catarrh of
the naso-pharyngeal and laryngo-tracheal mucous membrane. In such cases
it is thought that the irritation caused by the pressure of the swollen
mucous membrane upon the adjacent nerves is conveyed through them to
the pneumogastric, and thus provokes the bronchial spasm. Daly, Roe,
Harrison Allen, Hack, and others have traced the paroxysms of hay
asthma to an hypertrophied condition of the mucous membrane over the
turbinate bones and septum of the nose, which renders it peculiarly
susceptible to the action of the irritants which cause that troublesome
affection, and have succeeded in curing many cases by simply removing
the diseased tissue.
Mental emotion, if sufficiently powerful, may sometimes prevent the
occurrence of the asthmatic paroxysm; thus, Steavenson, referring to
his own case, states that although subject to frequent attacks he never
had one on going up for an examination; and the writer is acquainted
with a patient whose attack of hay asthma could frequently be checked
by an exciting game of cards.
Asthma, like other neuroses, is much more frequent among the educated
and refined than among the coarser and more ignorant classes of
society, and those leading luxurious lives are more liable to the
disease than those of simple and frugal habits. Of the various
professions, those which involve much exertion of the voice furnish the
largest contingent; hence it is common among public speakers,
clergymen, and lawyers.
In former days the retrocession of cutaneous eruptions was supposed to
play an important rôle in the production of asthma, but of late years
this theory of causation has found but few advocates among intelligent
physicians, the only author of any prominence who still adheres to it
being Waldenburg, who has proposed to designate such cases as a.
herpeticum.
PATHOLOGY.—We have elsewhere alluded to the various theories with
which the older writers endeavored to explain the phenomena of asthma,
and need not here refer to them again.
The first step toward a truly scientific theory of the pathology of
asthma was the discovery by Reisseisen of the smooth muscular fibres of
the bronchial tubes. These fibres are found not only in the large and
medium-sized bronchi, but even in those of the smallest calibre,
Kölliker having
demonstrated them in bronchioles 0.18 millimeter
in diameter. It was ascertained by Williams that by irritating the lung
he could cause contraction of these fibres, and Longet subsequently
proved that the same effect could be produced by galvanizing the
pneumogastric nerve. Guided by these important discoveries, most modern
pathologists have arrived at the conclusion that bronchial asthma is a
spasmodic contraction of the middle and finer bronchi, dependent upon
some derangement in the function of the pneumogastric nerve. This, the
so-called spasmodic theory, is not entirely new, Willis, as we have
before stated, having described as early as 1682 a variety of asthma
which he believed to be the result of a "spasmodic action of the
muscles and nerves of respiration," and to which he applied the term
"asthma convulsivum." Although revived from time to time, it was not
until some two hundred years later, and after Romberg had definitely
settled the question of the essential character of the disease, that
the spasmodic nature of asthma received general recognition. Bergson
adopted it in his prize essay in 1840, and ten years later it found a
warm supporter in the person of Hyde Salter, whose valuable
contributions have added so much to our knowledge of bronchial asthma.
The theory that asthma is due to spasm of the bronchial muscles met
with but little opposition until 1854, when Wintrich, after a series of
experiments, arrived at conclusions directly opposed to those of
Williams and Longet in regard to the contractility of the muscular
fibres of the bronchi, and refused to accept the spasm theory on the
ground that it afforded no rational explanation of the phenomena of
asthma. He believed that the various symptoms of that disease were due
to tonic spasm either of the diaphragm alone or of the diaphragm and
the other muscles of respiration. These experiments of Wintrich were so
carefully conducted, and his standing as a specialist in respiratory
diseases so high, that his theory found many supporters, and might
perhaps have been generally accepted had it not been for the
distinguished French physiologist, Paul Bert, who in 1870, with
improved methods of scientific research, succeeded in demonstrating
that Williams and Longet were after all correct in their statements as
to the contractility of the bronchial muscles.
One of the most zealous advocates of the spasm theory of asthma, and at
the same time its most learned expositor, is Biermer,13 whose
classical lecture on that disease, which appeared a short time after
the publication of Bert's experiments, is perhaps the most satisfactory
work ever published on the subject. He defines bronchial asthma as a
"neurosis depending upon tonic spasm of the bronchial muscles and
caused by faulty innervation of the pneumogastric nerve." He claims
that this theory is confirmed by clinical experience—that the
suddenness with which the attack comes and disappears, and the long and
forced expiration with the sibilant râles and other evidences of
stenosis which accompany it, admit of no other explanation. In support
of this view he calls attention to the rapidity with which the paroxysm
yields to chloral, all of its symptoms disappearing within from five to
ten minutes after the administration of a moderate dose of that agent.
Wintrich and his supporters, besides denying the contractility of the
bronchial muscles, object to the spasm theory that the distension of
the thorax and descent of the diaphragm, both constant symptoms, are
incompatible with spasmodic closure of the bronchial tubes, and that
constriction from such cause by impeding the entrance of air into the
alveolæ would be more likely to cause diminution in the size of the
thorax than its enlargement, and that the diaphragm, instead of
descending, would be drawn upward. Biermer acknowledges that this to a
certain extent is true, and concedes that constriction of the tubes
would interfere with both acts of respiration, but claims that it does
not do so
to the same extent in the two movements. The spasmodic
constriction acts as a sphincter which is readily overcome during
inspiration, but prevents the escape of air during expiration, the
latter movement being slower and less complete than the former. Were
the expiratory pressure exerted upon the contents of the alveolæ alone,
it would readily overcome the spasmodic constriction of the bronchi,
but it also compresses at the same time the bronchioles. "When the
bronchi are spasmodically contracted, they are subjected during
expiration to the general pressure of that movement plus the pressure
of the spastic contraction of the bronchial muscles. The walls of the
bronchioles being soft and compressible, the expiratory pressure,
instead of overcoming the obstruction and opening them, would tend to
close them all the more tightly." He calls attention to an analogous
condition which obtains in capillary bronchitis, when, owing to
swelling of the mucous membrane and to the accumulation of secretion in
the tubes, the alveolæ are cut off. Here, too, the expiratory pressure
is often sufficiently powerful to overcome the obstruction, but if
under these circumstances it is too feeble, collapse of the lung
ensues. When, on the other hand, the inspiration is strong enough to
overcome this obstacle, air enters the alveolæ, and, being imprisoned
there, causes inflation of the air-cells as in asthma. That collapse of
the lung does not occur in the latter disease is due to the fact that
the inspiratory act is always sufficiently powerful to overcome the
spastic contraction of the bronchioles.
13 A. Biermer, "Ueber Bronchial Asthma," Sammlung
klinischer Vorträge, No. 12, Leipzig, 1870.
The air entering the lung during inspiration is pent up by the spastic
constriction of the bronchi, which, acting as a valve, admits of its
passage in one direction, but impedes its escape during expiration, and
thus causes inflation of the air-cells and insufficient aëration. Owing
to the distension of the alveolæ the thorax is expanded and the
diaphragm forced downward. A tetanic spasm of the diaphragm lasting for
hours, such as that which Wintrich describes, and with which he
endeavors to explain the descent of that muscle as well as the other
symptoms of asthma, is not only improbable, but is contrary to clinical
experience. If the diaphragm were thus spasmodically contracted, it
would remain fixed in one position, but Biermer has demonstrated that
there is more or less rhythmic movement of that muscle even during the
paroxysm; but if no movement of the diaphragm were observed, it would
still be no proof of tonic spasm of that muscle, as its immobility
might be due to other causes. According to Biermer, the inflation of
the lungs and their insufficient ventilation afford a satisfactory
explanation of the most important symptoms of asthma, as Breuer14 has
shown, in his paper on the automatic regulation of respiration through
the pneumogastric nerve, that various embarrassments of respiration
must be corrected by some suitable modification of the act itself;
hence when, as in asthma, the lung is unable to empty itself, the
expiratory act must be strengthened and prolonged to overcome the
obstruction occasioned by the spasmodic constriction of the bronchial
tubes; whereas incomplete filling of the lung would necessitate
increased inspiratory effort. According to Biermer, "expiratory
dyspnoea is as characteristic of obstruction of the finer tubes," be it
from spasm, as in asthma, or from stoppage with viscid mucus or from
swelling of their lining membrane, as in bronchitis, as the same
condition during inspiration is of narrowing of the larger
air-passages—an important point in differential diagnosis to which we
shall again have occasion to refer. He is unable to explain the
relationship between bronchial spasm and catarrhal hyperæmia of the
air-passages, but believes that it may be accounted for as follows:
"Either the bronchial fluxion causes the spasm—that is, that there
exists between them a causal connection—or the hyperæmia and the spasm
are the
joint effect of the exciting (centripetal) nerves; in
other words, both are due to reflex action."15
14 "Die Selbsterneurung der Athmen durch den N. vagus,"
Sitzungsbericht der K. K. Akademie der Wissenschaften zu Wien, Bd.
lviii. Abtheilung ii., Nov., 1868.
15 In presenting Biermer's theory the writer has drawn
freely upon that author's well-known lecture on "Bronchial Asthma," as
published in Volkmann's Sammlung klinischer Vorträge, loc. cit.
Another explanation of the phenomena of asthma is that proposed by
Lebert,16 who, although he concedes that bronchial spasm is an
all-important factor, denies that it of itself is sufficient to account
for the sudden and enormous inflation of the lungs observed in that
disease. He doubts the possibility of a valvular closure of the
bronchi, as claimed by Biermer, but believes that the bronchial spasm,
which he regards as primary, causes secondary spasmodic contractions of
the diaphragm and of the inspiratory muscles of the neck and chest. The
spasm of the diaphragm he believes to be tonic in its character, but
not continuous, thus meeting Biermer's objection to the Wintrich
theory, that tonic spasm of that muscle lasting longer than a few
minutes would inevitably cause fatal asphyxia.
16 Klinik der Brustkrankheiten, 1ster Band, 2te Hälfte, p.
438.
Theodor Weber,17 rejecting the above theories on the ground that
neither bronchial spasm nor tonic contraction of the diaphragm is
capable of explaining why catarrhal secretion should come on at the
close of an attack in which at the commencement there was no catarrh,
attributes the phenomena of asthma to sudden swelling of the bronchial
mucous membrane, the result of dilatation of its blood-vessels produced
through the agency of the vaso-motor nerves; thus reviving the
fluxionary theory of Traube. In support of this theory he cites the
result of Von Loven's18 experiments, which prove that irritation of
the sensory nerves is followed by reflex engorgement of the territory
to which they are distributed. Weber considers that this engorgement of
the bronchial mucous membrane is somewhat similar to the acute swelling
and stoppage of the nostrils to which many persons are subject—a
closure which often does not last longer than a few moments, and which
is attended with increased redness and swelling of the Schneiderian
membrane. The mucous membrane of the nostril and that of the bronchi
being both parts of the respiratory tract, and somewhat similar in
structure, he concludes that the process in the nostrils is analogous
to that which occurs in the bronchi during the asthmatic paroxysm. As
additional proof of the correctness of his hypothesis he cites the fact
that such occlusion of the nostrils is often the precursor of the
asthmatic attack, and in some cases continues throughout the paroxysm.
See investigations of Daly, Roe, Allen, and Hack, further on.
17 "Ueber Asthma Nervosum," Tageblatt der 45 Versammlung
deutscher Naturforscher u. Aertze in Leipzig, etc., 1872, p. 159.
18 Naturforscher u. Aertze in Leipzig, etc., 1872, p.
159.
The idea that asthma is due to swelling and engorgement of the
bronchial mucous membrane appears to have been confirmed by the
tracheoscopic observations of Stoerk.19 On examining the air-passages
with the laryngoscope, he could see the mucous membrane of the trachea
as far as visible (that is, to the bifurcation) grow red with the onset
of the paroxysm, and resume its normal appearance after the termination
of the attack. He opposes the spasm theory, denies the correctness of
Biermer's conclusions, and adopts Weber's explanation of the asthmatic
phenomena. He agrees with Wintrich that spasm of the diaphragm occurs,
but claims that it results from the tension to which it is subjected by
the inflated alveolæ: the diaphragm being forced downward by the
distended lung, its fibres are stretched, and the result is a tonic
spasm of that muscle. His objections, although well stated, are not
sufficiently conclusive to cause us to accept his opinion in preference
to that of Biermer and other supporters of the spasm theory.
19 Mittheilungen über Asthma bronchiale, etc., Stuttgart,
1875.
Max Schaeffer maintains that asthma is due to bronchial fluxion,
as advocated by Weber, but claims that the hyperæmia is followed by
spasm of the bronchial muscles, the former being primary and the latter
secondary. He also, with many other recent writers, believes that
asthmatic attacks are often associated with pathological conditions in
and about the upper air-passages, such as naso-pharyngeal and
laryngo-tracheal catarrh, polypi, hypertrophied tonsils, and enlarged
cervical glands; all of which act as irritants, which, being
transmitted through the neighboring nerves to the vagus, induce the
bronchial spasm.
Among the older and discarded theories is that of Bree, who in a work
published at the commencement of the present century expressed the
opinion that the dyspnoea of asthma was simply an effort on the part of
nature to rid the bronchial tubes of an irritating substance supposed
to have accumulated in them previous to the attack. He believed that
this materia peccans was thrown out with the expectoration which occurs
toward the close of the attack. He regarded the violent efforts made by
the respiratory organs to expel this offending substance from the
bronchial tubes as similar to the tenesmus of dysentery or the painful
contractions of the bladder when irritated by a rough calculus. Bree
was unable to define more clearly the nature of this offending
substance, but of late years another writer, Leyden,20 has discovered
in the sputa of asthmatics certain peculiar crystals to the irritating
effects of which he attributes the various symptoms. These crystals had
been observed previously by Charcot in the blood of leukæmic patients,
and subsequently by Neumann in the medulla of the bones of patients who
had died of that disease. Leyden describes the expectoration in asthma
as tough, grayish-white, and very frothy. Imbedded in a transparent
hyaline mass are a number of small bodies, some thread-like, others in
the form of little plugs or flakes. Under the microscope these little
bodies are found to consist of a mass of brownish cellular detritus
containing large numbers of crystals. These are colorless, octahedral
in form, with sharp points, and vary greatly in size, some of them
visible at once, while others are seen only with the highest powers of
the microscope. Their composition has not been determined, but is
supposed to be a substance resembling mucin. Leyden's idea is that the
sharp points of these octahedral crystals irritate the terminal ends of
the pneumogastric nerve in the mucous membrane of the bronchi, and that
this irritation, being transmitted to the nervous centre, is reflected
back, and thus causes spasm of the bronchial muscles. It seems,
however, that these crystals are not peculiar to bronchial asthma,
having been also found in chronic catarrh and other affections of the
bronchi.21
20 "Zur Kentniss des Bronchial Asthmas," Virchow's Archiv,
Band liv., 1871.
21 Not being able to obtain the original paper, the writer
is indebted for the greater part of what he has written in regard to
the Leyden theory to the treatises on asthma by Knauthe in Eulenburg's
Encyclopædie der gesammten Heilkunde, and by Riegel in the work
already quoted.
Of the different theories of bronchial asthma which have just been
presented, that of Biermer, although unsatisfactory in many respects,
offers the best explanation of the pathology and symptoms of that disease.
PATHOLOGICAL ANATOMY.—Bronchial asthma being a purely functional
neurosis, the organs involved present no anatomical changes specially
characteristic of that affection. It is true that in cases of long
standing, in which, owing to oft-repeated attacks, the air-cells have
become distended and their walls attenuated, we find the lungs in the
condition which will hereafter be described as emphysema, but these, as
well as the evidences of chronic catarrh observed in these cases, are
due to the secondary affections, and not to the primary disease.
As previously stated, a certain amount of hyperæmia of the mucous
membrane of the larynx, trachea, and bronchi may be observed during
life with the aid of the laryngoscope; but whether this condition leads
to permanent tissue-changes observable after death is exceedingly doubtful.
In the pneumogastric nerve pathologists have as yet been unable to
discover, either at its origin or along its course to the lungs, any
alteration in structure capable of explaining the phenomena of
bronchial asthma.
DIAGNOSIS.—The suddenness of the attacks; the occurrence of the
paroxysm usually in the latter half of the night; the slow, labored
expiration, with the whistling, wheezing sounds which accompany it; the
expectoration of catarrhal sputa toward the close of the attack; the
normal respiration and absence of all signs of disease during the
interval between the paroxysms,—are the features by which a case of
simple uncomplicated asthma may be readily recognized. When these
symptoms are present in their integrity in an otherwise healthy
subject, there is no difficulty in arriving at the diagnosis; but,
unfortunately, the picture is not always complete. The asthma may be
complicated with organic disease of the heart or lungs, while primary
disease of these organs, as well as certain affections of the nervous
system, may produce symptoms closely resembling those of bronchial
asthma, and from which it is very essential to distinguish them.
The following are some of the affections which may be mistaken for
bronchial asthma:
1. Bronchial catarrh may be accompanied with more or less difficult
respiration, but even in its worst forms it never causes the severe
attacks of dyspnoea observed in bronchial asthma, and, as Riegel justly
remarks, the severity of the symptoms in the latter disease are out of
all proportion to the insignificance of the physical changes.
The dyspnoea of bronchitis comes on more gradually, the attacks being
dependent upon a variety of accidental circumstances; whereas the
asthmatic paroxysm usually occurs quite suddenly in the night without
any apparent cause. The cough in bronchitis is severer and the
expectoration more abundant than in asthma; the latter is also
different in quality, becoming purulent as the disease advances,
whereas in asthma it seldom loses its mucous character. These points of
difference and the presence of the other symptoms of bronchitis are
sufficient to differentiate that disease.
2. Emphysema is frequently associated with asthma, either as a cause,
as is believed by many, or as an effect of that disease. It is often
exceedingly difficult to determine whether the emphysema when present
is the cause of the dyspnoea (symptomatic asthma), or whether the
inflation of the air-cells and other symptoms are not the result of the
bronchial spasm: a careful inquiry into the history of the case will
often decide the question. The points of difference between the two
diseases are very similar to those to which we have just called
attention as the distinguishing features between the dyspnoea of
bronchitis and the true asthmatic paroxysm. The suddenness with which
the attack comes and goes, the severity of the symptoms compared with
the insignificance of the local lesions, the absence of dyspnoea in the
intervals between the attacks (in uncomplicated cases), are all the
reverse of what is observed in emphysema. In that disease the attacks
develop more gradually; there is always more or less shortness of
breath, and the evidences of changes in the structure of the lung are
quite marked.
3. Dyspnoea resulting from cardiac disease is often very severe, but
may be distinguished from bronchial asthma by the presence of the
various murmurs and other physical signs by means of which that class
of diseases is recognized. The asthmatic paroxysm, as a rule, comes on
when the patient is most quiet, usually during sleep. The attack of
cardiac dyspnoea, on the contrary, is always brought on or aggravated
by physical exertion, mental excitement, or some other apparent cause.
In asthma the respiration during the intervals between the
paroxysms is quite natural; in cardiac dyspnoea there is always more or
less embarrassment. Pain in the region of the heart, in many cases
quite severe and extending down the left arm, may direct attention to
that organ as the source of the dyspnoea.
4. Spasm of the glottis, croup, oedema of the glottis, tracheal
stenosis, are all attended with more or less violent attacks of
dyspnoea. We are indebted to Biermer for having directed attention to
an important symptom by means of which all these affections may be
distinguished from bronchial asthma. In the latter, and in all other
diseases causing narrowing or obstruction of the finer bronchi, the
dyspnoea is during the expiration, but if the impediment be in the
larger air-passages the dyspnoea will be during the inspiration.
"Dyspnoea during expiration is just as characteristic of narrowing of
the finer bronchi as the same condition during inspiration is of croup
and other forms of laryngeal stenosis." In croup the neck is extended
and the head thrown back. Notwithstanding the violent inspiratory
efforts of the patient, the lungs are but partially filled; the air in
them becomes rarefied, causing a yielding of the less-resisting parts
of the thorax—e.g. the supraclavicular space, the lower portion of
the sternum, and adjacent costal cartilages—and a sinking in of the
abdomen. During expiration, which is accomplished quickly and with
comparative ease, the thorax resumes its natural form. In bronchial
asthma, on the contrary, the head is thrown forward, and the shoulders
fixed in such a position as to enable the muscles of expiration to work
to the best advantage. The thorax, instead of sinking in, is expanded
and abnormally round, giving on percussion the peculiar pasteboard-box
sound (Schachtelton) which Biermer has described as characteristic of
inflation of the alveolæ. In croup the sibilant râles are heard during
inspiration, while in asthma they are more pronounced during expiration.
5. Spasm of the diaphragm is another affection from which it may be
necessary to distinguish bronchial asthma. This rare disease, which is
almost always associated with hysteria, is characterized by a short
inspiratory movement, during which all the muscles of inspiration are
brought into action, and we have the same sinking in of the more
yielding portions of the thorax which has just been mentioned as one of
the distinguishing features of laryngeal stenosis. After this the
thorax remains fixed for a few seconds, the muscles of inspiration
remaining in a state of contraction. There then ensues a quick and
powerful expiratory effort, accompanied by a sound not unlike that of
hiccough; then another inspiration, with a repetition of the above
symptom; and so on until the attack is over. It will be seen from this
description that this affection resembles singultus more than asthma,
and that there is but little likelihood of its being mistaken for the
latter disease.
6. Paralysis of the posterior crico-arytenoid muscles, like croup,
spasm of the glottis, and all other affections which produce narrowing
of the larger air-passages, is distinguished by the dyspnoea being
inspiratory, and not expiratory. The function of the posterior
crico-arytenoid muscles being to enlarge the glottis, the result of
their being paralyzed would be to lessen the opening through which the
air passes to reach the lung; and in viewing the cords in such a case
with the laryngoscope it will be found that the opening is reduced to a
narrow chink. Another distinguishing feature is that the dyspnoea is
continuous, and, unlike bronchial asthma, does not come on in paroxysms.
7. An affection which, like asthma, comes on in the night during sleep
is the condition known as nightmare, and, like the former disease, is
characterized by labored breathing. To distinguish it, it is only
necessary to awaken the patient, when the immediate cessation of all
symptoms will at once remove all doubt as to the nature of the affection.
8. Through carelessness or ignorance intercostal neuralgia has been
sometimes mistaken for asthma. Pain along the course of the nerve
and the presence of the points douloureux, which Valleix has described
as characteristic of neuralgic affections, are sufficient to establish
the diagnosis.
9. Embolism of one of the middle or larger branches of the pulmonary
artery is also characterized by great embarrassment of respiration, but
is not likely to be mistaken for asthma by any one at all familiar with
the two affections. The cachectic appearance of the patient, the
intense anxiety depicted on his countenance, the evidence of cardiac
disease or of some affection of the vessels, the weakened cardiac
impulse, the thready and at times irregular pulse, together with
evidences of more or less pulmonary oedema, are sufficient to
distinguish this form of dyspnoea from that of asthma.
PROGNOSIS.—As there is no well-authenticated case of death from
uncomplicated asthma, the prognosis quoad vitam may be regarded as
absolutely favorable. That death never occurs during the severe
paroxysms of asthma may be due to the action of the deficiently aërated
blood upon the respiratory centres, and bronchial spasm, causing
relaxation when the symptoms have become most threatening. The
asthmatic, if his case be incurable, may live for a number of years,
and even attain to extreme old age, but his life will be one of intense
suffering, which becomes more intolerable as he advances in years.
Sooner or later, bronchitis, emphysema, or heart disease is developed,
which in its turn may lead to renal disease and dropsy.
Such is the almost invariable result in middle-aged and elderly
persons; in the young, however, the chances of recovery are much more
favorable. Salter22 states "that in youth the tendency is invariably
toward recovery, whereas in one attacked with it after forty-five the
tendency is generally toward a progressive severity of the disease and
the production and aggravation of those complications by which asthma
kills." The favorable result in childhood he attributes to the
recuperative power of youth: growth and change, being more rapid than
later in life, enable the system to repair during the intervals
whatever damage may have been sustained during the paroxysms.
22 On Asthma, Am. ed., p. 168.
There is another class of cases in which, owing to our being able to
recognize and remove the cause, the prognosis is quite favorable: thus,
if it has been discovered that the disease is due to some local
influence, change will often effect a cure, and the patient will remain
well as long as he remains in the locality which agrees with him, but
generally relapses if he ventures to return to the place where he first
contracted the disease. The same may be said of that form of asthma in
which the disease is due to some trade or pursuit necessitating the
inhalation of irritating dust or gases: the indications are obvious.
Cases in which the paroxysms have been traced to the presence of nasal
polypi or to a tumor pressing upon the course of the pneumogastric
nerve have been promptly cured by the removal of these growths. In all
these cases it is presupposed that there is no organic disease, for the
presence of any one of the serious complications we have mentioned
would dissipate all hope of cure.
In arriving at a prognosis it is all-important to inquire into the
severity and frequency of the attacks, as violent paroxysms at short
intervals soon lead to incurable complications. It is also essential to
ascertain the condition of the patient during the intervals between the
paroxysms: if at that time he feels well and does not suffer with
shortness of breath, we may infer that as yet no organic change has
occurred; if, however, he complains of more or less dyspnoea during the
intervals, we may safely conclude that some organic disease has set in
and that the case is incurable. Salter attaches great importance to the
persistence of expectoration during the intermissions, regarding it as
indicative of bronchitis, and therefore as an unfavorable indication:
to use his own words, "Spitting is one of the worst signs in asthma."
Briefly, those cases may be regarded as favorable in which the
patient is young and has no inherited tendency to the disease, is free
from the many complications of asthma, and in whom the attacks are
light and occur at long intervals. On the other hand, all cases may be
regarded as unfavorable in which the patient has reached or passed the
middle period of life, has inherited a tendency to asthma, if the
attacks are severe with short intervals, or if he has some one or more
of the secondary affections of the disease.
TREATMENT.—The treatment of bronchial asthma consists of measures to
mitigate and relieve the paroxysms and prevent their recurrence.
A. Of the Paroxysm.—A patient suffering with an attack of asthma
will generally instinctively assume the position in which he can use
the muscles of respiration to the greatest advantage, but if found in
the recumbent posture he should be advised to sit up in bed and grasp
the knees with his hands, so as to gain a position which admits of the
more ready entrance of air into the lungs. In severe cases it is better
to have him rise from the bed and support the head with the hands, the
elbows resting on a table in front of him. An ingenious
suspension-apparatus, intended to promote the comfort of persons
suffering with severe dyspnoea, was extensively advertised several
years ago, and may possibly still be furnished by the
instrument-makers. It consists of a cross-piece suspended from the
ceiling, to which straps are attached for supporting the shoulders
without in any way pressing upon the chest; it is also provided with a
band for the support of the head. In severe and protracted cases, when,
notwithstanding the patient's exhaustion, he is unable to rest upon
pillows, such an arrangement might afford great relief. If not
undressed, the clothing should be so arranged as to interfere as little
as possible with the respiratory movements. An abundant supply of fresh
air is essential, and to secure this one or more windows should be
thrown open.
Asthma being the most capricious of diseases, remedies often acting
differently in each individual case, it is well before commencing
treatment to follow Salter's advice and inquire of the patient what
remedy has usually afforded the most prompt relief in previous attacks,
and thus avoid the risk of prolonging suffering by using remedies
which, although apparently indicated, may in his case, owing to
peculiar idiosyncrasies, prove to be useless or even injurious.
We have seen that the disease is often due to some special cause, such
as the inhalation of an atmosphere laden with the perfumes of certain
flowers, with ipecac, dust, etc., the removal of which, if practicable,
should of course precede all attempts at treatment. The condition of
the stomach and bowels should be inquired into, and if found overloaded
they should at once be relieved, the one by an emetic and the other by enema.
In the absence of any hint afforded by the previous experience of the
patient the choice of the remedial agent will depend upon the severity
of the attack. In the majority of cases, when severe, no remedy will
afford such prompt relief as the subcutaneous injection of morphia. To
be effective, the dose should be a full one, a fourth to a third of a
grain, either alone or, if there is likelihood of this occasioning
nausea, combined with one one-hundredth to one-eightieth of a grain of
sulphate of atropia. The writer is aware that the use of opium and
other hypnotics in bronchial asthma is discouraged by one of the most
distinguished authorities on that disease, Salter, who claims that they
are not only worthless, but often injurious. He believes that sleep
tends to promote the paroxysm, reflex action being much more active
then than during the waking hours, and that any agent which induces
such a condition is necessarily contraindicated—that, in his opinion,
in addition to exalting reflex action, it acts prejudicially, as "by
lowering sensibility it prevents that acute and prompt perception of
respiratory arrears which is the normal stimulus to those extraordinary
breathing efforts which are necessary to restore the balance." These
objections, although supported by scientific evidence, are
insufficient to cause the abandonment of an agent which in the hands of
others has proved so prompt and efficacious in relieving the terrible
sufferings of asthma, and Salter himself admits that since writing the
above he has had cases in which it has been of signal service. A
serious objection to its use is that the dose has to be increased as
the patient becomes accustomed to its use. In confirmation of its
marked beneficent effects, I give the following extract from
Steavenson's treatise on asthma. Describing his own experience, he
says:23 "Sedatives and antispasmodics I should consider most
serviceable drugs, but above all in value I should place the hypodermic
injection of morphia. This has never failed to relieve an attack in
myself, and I have never seen it fail in other patients. The objection
to it is that if often used the dose must be increased; but it is
better to increase the dose of morphia than suffer the agonies of
asthma and allow those organic changes in the constitution to take
place which I have described when speaking of the pathology of the
disease. I have now used morphia for five years, but my attacks are so
quickly relieved and so reduced in frequency that I have never yet had
to increase the dose I commenced with—namely, one-sixth of a grain."
23 Op. cit., p. 29.
Having administered the morphia, other measures for the relief of the
patient should be resorted to. The feet and hands should be immersed in
hot water to which a small quantity of mustard has been added. Dry cups
between the shoulder-blades or sinapisms over the chest or epigastrium
often afford marked relief.
If, on account of the existence of an idiosyncrasy on the part of the
patient or from other causes, opium cannot be employed, we have in
chloral hydrate a substitute which is almost as efficacious and perhaps
even more prompt. Next to morphia, it is the most valuable remedy, and
many esteem it superior to that drug, over which it possesses the
advantage of not being followed by the disagreeable effects which so
often succeed the administration of opiates. It should be given in
doses of thirty or forty grains, and repeated if the paroxysm does not yield.
The inhalation of chloroform has long been esteemed as a potent agent
in overcoming the bronchial spasm. One would naturally suppose that the
use of such a powerful sedative as chloroform would be a dangerous
proceeding in a disease which, like asthma, is attended with so much
embarrassment of respiration and circulation; but experience does not
justify this fear, and Salter, who has used it with good effect in 12
out of 13 cases, assures us that he has administered it "in the very
agony of the worst attacks; that, so far from fearing it under such
circumstances, it has been able to relieve the intensest asthma that
nothing else would reach; that he has given it, and that he has never
seen any bad effects from it." He goes on to state that as chloroform
relaxes the bronchial spasm, and thus removes the cause of the
"asphyxial stoppage, the intensity of the apnoea, so far from being a
reason against the administration of chloroform, is the great reason
for its immediate employment." He considers neither muscular weakness
of the heart nor valvular disease as any contraindication to its
administration, provided the circulation is not materially affected.
According to Stokes, the paroxysm is not entirely suppressed by
chloroform, but returns as soon as the patient passes from under its
influence; hence it must be repeated as occasion may require. It should
always, if possible, be given at the commencement of the paroxysm, and
should never be allowed to produce complete insensibility, nor should
so seductive a remedy be left in the hands of the patient. The danger
of the self-administration of chloroform is only too well attested by
the frequent accounts in the journals of persons found dead in their
beds from the effects of that agent, death in such cases being usually
due to the patient's unconsciously leaving the handkerchief over
the mouth and continuing to inhale the chloroform after having become
insensible. When given sufficiently early, a few whiffs may be all that
is necessary to overcome the paroxysm; and this repeated as soon as it
threatens to return, will often enable us to control the symptoms
without resorting to larger quantities.
An old and still very popular treatment—said to have been introduced
by an American, Nicholas Frisi,24 in 1843—consists of the inhalation
of the fumes of burning saltpetre or in smoking cigarettes made of
paper which has been soaked in a saturated solution of that substance.
Inhaled into the bronchi, it is supposed to act as an anæsthetic, and
produces relaxation of the constricted bronchial muscles. In point of
efficiency these inhalations rank quite high, and are probably more
generally used than any other remedy. Aside from the relief which they
undoubtedly afford, this method derives much of its popularity from
being within easy reach of the patient himself. The preparation of the
papers is exceedingly simple: A sheet of bibulous paper is dipped into
a saturated solution of the nitrate of potassa prepared with cold
water; after drying it is divided into strips of the size required.
These papers are burnt before the patient, the windows and doors of the
apartment having been previously closed to prevent the escape of the
fumes. Nitrate of potassa has been prepared in a variety of other ways
for the use of asthmatic patients, one of the most convenient of which
is the Kidder pastilles so extensively used in this country. Another
method is to roll the paper prepared as above into cigarettes, the
smoke of which is inhaled by the patient. The nitre is best used early
in the attack, but is also beneficial when the paroxysm is at its
height. The efficacy of this treatment is attributed by Germain Sée to
the formation of protoxide of nitrogen and carbonic acid gas, which act
as an anæsthetic, and perhaps also to the particles of carbon in the
smoke floating in the air, a smoky atmosphere being beneficial to many asthmatics.
24 Germain Sée, op. cit., p. 709.
The smoking of the Datura metel having been found efficacious in asthma
in India, Anderson of Madras in 1802 sent some of the leaves to Gen.
Gent, an English officer, by whom they were introduced into England.
Simms of Edinburgh, believing that the Datura stramonium might prove
equally good, tested it with such good results that it soon came into
general use, not only in asthma, but in other forms of dyspnoea. This
is the ordinary Jimson or Jamestown weed which is so widely distributed
over the Southern, Middle, and Northern States, and, like nitrate of
potassa, is much used, not only by the profession, but largely as a
household remedy for asthma. The dried leaves are either smoked in a
pipe or in the form of a cigarette. The effects, however, are quite
uncertain, sometimes acting like a charm, while at others it affords no
relief; its physiological action is that of a sedative. Of late years
another species of Datura has been introduced—the Datura tatula. Its
properties and uses are similar to those of stramonium, but it is
supposed to be less narcotic.
Belladonna and its alkaloid, atropia, are often used in the treatment
of asthma, but their action is uncertain and often unsatisfactory. The
three last-mentioned remedies are also used in combination, as in the
well-known Espic cigarettes, the formula for which, according to
Trousseau, is as follows, viz.:
| Rx. |
Fol. belladonnæ, |
gr. vj; |
| |
Fol. hyoscyami, |
gr. iij; |
| |
Fol. stramonii, |
gr. iij; |
| |
Fol. phillandrii aquatic. |
gr. j; |
| |
Ext. opii, |
gr. ¼; |
| |
Aq. lauroceras, |
q. s. |
The leaves, after being cut up, should be thoroughly mixed, after
which they are moistened with the cherry-laurel water, in which the
opium has been previously dissolved. The wrapper of the cigarette is
also soaked in the same solution and dried. One or two of these
cigarettes should be smoked during the attack. Abbott has been very
successful with belladonna applied as a spray (drachm j of the extract
to one ounce of water) when the spasm threatens.
Tobacco is a powerful depressant, and in those who are unaccustomed to
its use is an invaluable remedy in asthma. In the uninitiated it
excites nausea, vertigo, cold sweats, and other symptoms of relaxation
which Salter not inaptly compares to those of sea-sickness. "The moment
this condition can be induced the asthma ceases, as if stopped by a
charm." It may, however, be asked whether the remedy is not worse than
the disease. Those who retain a vivid recollection of the horrible
consequences of their first smoke will hesitate before prescribing
tobacco for one unaccustomed to its use. There are many who, not
wishing to lose the beneficial effect of tobacco in asthma, never smoke
unless a paroxysm threatens.
Lobelia, like the above also a depressant in its action, was formerly
much employed in asthma. It is still used, but its effects are
disagreeable and by no means certain.
The intimate nervous connection which exists between the lungs and
stomach would naturally lead us to anticipate good results from
emetics. In asthma, as in laryngismus stridulus, an emetic often
affords prompt relief and arrests the paroxysm. The nausea which
precedes the act of vomiting, acting as a depressant, causes relaxation
of the spasm, while the emesis by unloading the stomach removes an
important source of irritation. Like tobacco and lobelia, remedies of
this class are only beneficial when pushed far enough to produce the
symptoms of depression and collapse to which we have alluded; these
once established the relief is usually complete. Tartar emetic and
ipecacuanha are the representatives of this class most used in asthma.
Tartar emetic, owing to the excessive and long-continued depression
which it occasions, is now rarely employed, having been almost entirely
superseded by ipecacuanha, which is equally efficacious and more
prompt. Its effects also disappear more rapidly than those of antimony.
Like other remedies intended to cut short the paroxysm, ipecacuanha
should be given as early as possible. It should be taken in full doses
of at least twenty grains.
Bromide of potassium, as is well known, acts upon the vaso-motor
nerves, causing contraction of the arterioles of the brain and spinal
cord, and thus inducing a state of partial anæmia which results in a
lessening of the irritability of these organs, quieting muscular spasm
and inducing sleep. These effects would naturally lead to its
employment in spasmodic asthma. Although occasionally used with success
in shortening the paroxysm, it is better adapted, as suggested by
Riegel, for use during the intervals, when, if given continuously, it
sometimes diminishes the severity of the paroxysms and causes them to
recur less frequently.
Nitrite of amyl, a most valuable addition to our materia medica, has
been extensively used in the treatment of asthma, but the reports of
the results attained are too contradictory to admit of our forming any
just estimate of its merits. The general opinion is that it relieves
the dyspnoea and makes the patient for the time being more comfortable;
and this accords with my own experience. The usual method of
administration is to drop one or more minims upon a handkerchief and to
inhale the vapor. It is also used internally, and, in the single case
that has come under my observation, with benefit. The following case,
reported by Pick and cited by Riegel,25 is instructive as showing the
favorable effects of nitrite of amyl: "The case was that of a medical
student who from his youth onward had suffered with
asthmatic
troubles, which increased as he grew older and had proved rebellious to
all remedies. Nothing except expectorants and narcotics afforded him
the slightest amelioration of his symptoms. On inhaling nitrite of amyl
he experienced immediate relief, which lasted for some time after the
inhalation. He was enabled to breathe deep and with comparative ease.
The relief afforded was but transitory, but, on the other hand, was so
sure that the patient resorted to it whenever the attack came on." The
same writer reports two other cases in which he succeeded by means of
nitrite of amyl in relieving the paroxysms and in increasing the
interval between them.
25 Op. cit., p. 295.
More agreeable to the taste and at the same time more effectual than
the potassium iodide is hydriodic acid. It is best administered in the
form of a syrup, preferably that prepared by Gardener of New York.
Salter, who appears to have had more experience with alcohol than any
other writer, narrates the case of an elderly Scotch lady who, having
exhausted all the known medicines and other agents used in asthma, was
finally relieved by full doses of whiskey. This was invariably
successful, but the dose, of course, had to be increased as the disease
grew older. He also mentions another case in which nothing except
chloroform afforded any relief. This he describes as the severest he
has ever witnessed. "I have never seen or heard of spasms so violent or
that seemed so nearly to put life in peril. His most intense spasms he
calls 'screaming spasms,' from the strangling cries that the want of
breath compels him to make. At the time of which I am speaking he lived
on the same street with myself, and, although his house was half the
length of the street from mine, his nurse has often assured me that if
the doors had been open I could have heard his screams at my house at
night. All remedies except the chloroform had failed, when one day
his nurse advised him to try brandy. It afforded him almost
instantaneous relief. He took enormous quantities of it, the first day
a quart, and in the course of two months as much as twelve gallons. The
spasm invariably stopped as soon as he took it, and for the last five
months that he was under observation he had only what he called a
'thickness, a tight, constricted breathing,' several times during the
night." Salter is particular in stating that the brandy should be given
strong and hot.
Another stimulant highly recommended by Salter is coffee. In stating
his objections to the use of opium it will be remembered that one of
his reasons for not availing himself of that remedy was that it caused
sleep, and that the exaltation of reflex action in that state favored
the asthmatic paroxysm. Coffee, being a strong excitant of the nervous
and vascular system, has the contrary effect and keeps the patient
awake. It should be prepared as a strong infusion without the addition
of either sugar or milk and given some time before the expected
paroxysm. Administered in this manner, he claims that coffee will
relieve two-thirds of all cases of asthma. The relief afforded is,
however, very unequal, being in some cases complete, while in others it
is only slight and transitory.
Quebracho in the form of an extract has been much used of late years in
the treatment of asthma and other affections attended with dyspnoea. It
has been found quite useful in mild cases.
The induced electrical current has been recommended by Schaeffer as a
means of cutting short the paroxysm. His method is to place one pole on
either side of the neck immediately below the angle of the jaw and in
front of the sterno-cleido-mastoid, so as to cover the course of the
pneumogastric and sympathetic nerves. The current should be
sufficiently strong to enable the patient to feel the passage from one
side of the throat to the other. It is applied for fifteen minutes
twice a day for six days, twelve sittings being usually sufficient to
afford relief. When the current is first applied it not
infrequently causes dilatation of the pupils, but this is succeeded by
contraction when the treatment begins to manifest its beneficent effects.
B. During the Intervals between the Paroxysms.—The diet and daily
regimen of the asthmatic should be most carefully regulated, the best
and most skilfully directed treatment being of little avail if these
important matters are neglected.
The asthmatic patient should be encouraged to pass much of his time in
the open air, but the amount of walking he should do will of course
depend upon his strength and freedom from secondary affections of the
heart and lungs. In a case of simple uncomplicated asthma the more the
patient walks the better he will feel; but this is not to be construed
to mean that he is to walk until exhausted; on the contrary, his walks
should at first be quite short, proportioned to his strength and wind,
and then gradually extended, but under no circumstances should he be
allowed to overfatigue himself. With a view to keeping the skin in the
best possible condition the body should every morning be sponged with
water, the temperature of which must be suited to the condition of the
patient. If he be feeble and anæmic, the water should be tepid, but
whenever admissible cold is to be preferred. After the bath it is
essential that the skin be thoroughly rubbed with a coarse towel until
it becomes slightly reddened. The cold bath properly used not only
invigorates the system generally, but by enabling the body to stand the
vicissitudes of temperature diminishes the risk of the patient's taking cold.
The intimate relations existing between the lungs and stomach, and the
fact that asthmatics usually suffer at the same time with dyspepsia,
make the question of diet an all-important one. Their meals should
consist of good, nutritious food, rigidly excluding all heavy,
indigestible substances, such as cheese, nuts, dried fruits, etc. The
meals should be taken at regular hours, and, as asthma almost always
comes on at night, it is important that the principal repast should be
in the morning or early part of the afternoon, and that any food taken
between that and the hour for retiring should be of the lightest
possible description. The more empty the patient's stomach, the better
will be the chances of his passing a good night. Alcoholic drinks,
coffee, and other stimulants should only be allowed when prescribed as
medicines, as they have a tendency to aggravate the hyperæmia of the
air-passages, which is one of the prominent features of the disease.
Constipation should of course be carefully guarded against.
Aside from the apparently well-established fact that asthmatics do
well, and often remain so, in the damp, foggy air of crowded cities, we
have no means of determining beforehand what locality will suit a case
of asthma. Change of climate in such cases is a mere matter of
experiment, but when such change is determined upon the patient should
at first try a place which is in every respect the reverse of the one
he has previously lived in. If his former residence was in a city, he
should remove to the country; if the old place was dry, the new one
should be damp; if he has lived in a flat, low country, let him try the
mountains; and vice versâ. As already stated, removal from the pure air
of the country to the foul, smoky air of a city densely populated often
affords complete relief, but so soon as the patient returns to his old
home the asthma reappears and is as bad as ever.
As regards its capriciousness as to locality, I quote the following
interesting case from Salter's work on asthma: "G. C——, a confirmed
asthmatic, a native of a city in Scotland in which he resided, having
been a sufferer for many years, came to London in 1838 for the sake of
receiving the best medical advice. He took apartments in the centre of
the city of London, somewhere near St. Paul's. His intention was to
wait for an attack, and as soon as one came on to present himself to
his physician, that he might witness it and have a clear idea of the
state he was in. He waited six weeks, much to
his mortification,
not only without experiencing one, but without any difficulty of
breathing whatever. His health altogether improved; he slept well and
gained flesh. Being tired of waiting, he went back to Scotland without
having seen his physician at all, and, to his great disappointment, he
had not been in his native city many days when he was attacked in the
usual way, and continued to suffer just as before his visit to London.
Subsequently, finding it necessary on matters of professional business
frequently to visit London, he experienced the same result on all
occasions as at his first visit—perfect immunity from his disease. To
use his own expression, 'he felt in London like a renewed man.' On his
first arrival in town he was in a miserable state: he could not move
without feeling his shortness of breath distressingly; he got no rest
at night, and was seldom able to lie down in his bed. But in London he
could do anything—eat, drink, sleep. The consequence was he gained
flesh and strength, and went back to Scotland looking quite a different
man. This was the invariable result."
Having once found a place which agrees with him, the asthmatic should
remain there, as change of climate when no good is effected often does harm.
Arsenic has long been a favorite remedy in asthma, and is undoubtedly
of great value in a number of cases. It was used in the form of a vapor
by Dioscorides, and, notwithstanding its poisonous properties, has
always occupied a prominent place in the therapeutics of diseases of
the air-passages. In Styria and other parts of Lower Austria arsenic is
habitually eaten by many of the peasants to enable them to breathe more
readily while climbing over their elevated mountains and to endure the
fatigue incidental to their long pedestrian journeys. The same habit is
said to prevail in China, where, however, it is not taken internally,
but is smoked mixed with tobacco. Its physiological effects are thought
to be due to the increased oxidation of the blood which it promotes, as
is proven by the great increase of urea observed after its
administration. The blood thus oxygenized stimulates the vital centre,
and thus the nerves and muscles of respiration are incited to increased
activity, as a result of which the respirations become freer and more
easy. Those who believe in the herpetic diathesis derive an additional
indication for its administration from the good effects which it
manifests in cutaneous diseases. It is best administered in the form of
liquor potassii arsenitis (Fowler's solution), giving at first only
three drops in a wine-glassful of water after each meal, and increasing
the dose one drop each day until the patient takes thirty drops in
twenty-four hours. Should any toxic symptoms supervene—pain in the
stomach or diarrhoea, puffiness of the lids or redness of the
conjunctiva—the arsenic should be at once suspended, and not resumed
until they shall have subsided. Thus given, it is quite safe. Trousseau
recommends its use in the form of cigarettes, which are prepared as
follows: "Twenty grains of the arsenite of potassium are dissolved in
half an ounce of water, and a sheet of bibulous paper soaked in this
solution until it is all taken up. The paper is then dried and divided
into twenty equal pieces, which therefore contain one grain arsenite of
potassium each. Each paper is then rolled in the form of a cigarette.
In smoking them the patient should endeavor to inhale the smoke into
the bronchi. He should take only four or five whiffs once a day."
Iodide of potassium often affords most satisfactory results in the
treatment of asthma, but in many cases it fails entirely. It is a drug
which must be given for a long period at a time, occasionally for
weeks, before it manifests its effects, and want of perseverance may
account for its failure in many cases. It forms one of the chief
ingredients in Aubrée's antiasthmatic elixir, the formula for which is
somewhat uncertain. According to Trousseau, it is as follows:
| Rx. |
Rad. polygalæ, |
gr. xl; |
| |
Coque c. aqua fervida, |
ounce iv ad ounce ij; |
| |
Filtrat, adde Potass. iodid. |
drachm iv; |
| |
Syrup, opii, |
ounce iv; |
| |
Spts. vin. gallic. |
ounce ij; |
| |
Tr. coccionellæ, q. s. ad coloraud. |
| Filtra. |
|
Of this Trousseau states three tablespoonfuls are taken "in the morning
fasting, at noon, and in the evening, until the asthma disappears."
Each dose contains no less than forty-five grains of the iodide of
potassium and four-fifths grain of extract of opium. Aubrée himself
always insisted that each dose should be followed by a "tablespoonful
of chocolate pastille, which neutralizes the irritating action of the
iodide of potassium."26
26 Trousseau, op. cit., p. 656.
A remedy resembling in its effects the one just mentioned is
nitro-glycerine. It is administered in the form of a one per cent.
alcoholic solution, in doses of half a drop, increased to three should
the smaller dose prove inefficient. Its effects manifest themselves in
from three or four minutes to a quarter of an hour, and disappear
within an hour after its administration. The dose should be increased
with great caution, as a single drop of the above solution has been
known to produce alarming symptoms. The euphorbia pilulifera, much
lauded by Australian physicians for its wonderful effects in bronchial
asthma, promises to rank as an invaluable remedy in the treatment of
that disease. It is best administered in the form of a decoction
prepared by steeping one ounce of the fresh, or half that quantity of
the dried plant, in two quarts of water, and simmering it down to one
quart. The dose of this decoction is three or four wineglassfuls during
the day, the last dose preferably in the evening, after supper.27
27 Boston Medical and Surgical Journal, 1885, p. 66.
Leyden, whose theory has been mentioned elsewhere, has proposed a new
treatment based upon the solubility of the Charcot crystals in chloride
of sodium and carbonate of sodium. A solution of one part of these
salts in one hundred parts of water should be inhaled twice daily in
the form of a spray.
Oxygen has often been used in asthma, but is now seldom administered
except in cases associated with great anæmia.
Sée gives the following statistics of the results of the treatment with
compressed air in asthma and its secondary affections. Bertin used it
in 15 cases of emphysema, all of which he cured, and in 92 cases of
nervous and catarrhal asthma with emphysema, of which 67 were
completely and 22 partially cured, while it was only unsuccessful in 3
cases. Of Sandahl's 77 cases of asthma with emphysema and bronchitis,
57 were much relieved, and of 14 uncomplicated cases, all were
completely relieved. Compressed air may be applied either by placing
the patient in a pneumatic cabinet or by means of the portable
apparatus of Waldenburg. It must be remembered, however, that in the
cabinet the compressed air acts upon the whole body, while in the
portable apparatus only the air-passages and alveolæ are subjected to
pressure; hence if the latter is used the amount of pressure must be
considerably diminished. Notwithstanding the success claimed for this
method of treatment, it should be used with caution, and if the case is
complicated with emphysema it should either be regarded as
contraindicated, or, if employed, the pneumatic cabinet should be used
and not the portable apparatus. In the former, or "air-bath," the
exterior pressure of the compressed air acts as an auxiliary to "the
elasticity of the thorax and to the abdominal gases in" expiration, and
at the same time, by compressing the vessels outside the thorax, aids
the venous circulation. The same force exercised on the inner surface
of the
tubes tends to lessen the hyperæmia of the bronchial
mucous membrane (Moeller).28 When the portable apparatus is used,
expiration in rarefied air causes retraction of the thorax, and thus in
a measure overcomes any tendency to emphysema. A better plan than to
use either singly is to combine the two—to expire into rarefied and
inspire compressed air—which may be readily accomplished with several
of the improved portable apparatuses.
28 Thérapeutique locale des Maladies de l'Appareil
respiratoire, Paris, 1882, p. 283.
The inhalation of sulphuretted hydrogen as practised at Eaux Bonnes,
Cauterets, Aix-la-Chapelle, and other sulphur baths, is said to have
cured some cases, while in many others great benefit is claimed to have
been derived from its use; but allowance must be made for exaggeration
in many of the reports published.
In giving the treatment of asthma no allusion has been made to
Grindelia robusta and other recently-introduced remedies, partly
because the writer has had no experience with them, and again where he
has tried them they have given negative results.
SYNONYMS.—Hay fever; Hay cold; Summer catarrh; Catarrhus æstivus
(Bostock); Freuhsommer katarrh (Phoebus); Autumnal catarrh (Wyman);
Rose cold; June cold; Pollen fever; Pollen catarrh (Blackley). Fr.
Catarrh de foin; Catarrh d'été; Ger. Roggen Asthma.
DEFINITION.—A form of catarrh caused by some irritant floating in the
atmosphere; appearing in the spring, early summer, or autumn; attacking
persons predisposed every year at the same time, the patient being at
other periods free from the disease; characterized by symptoms
resembling those of influenza, the chief of which are sneezing,
redness, swelling, and increased secretion of the conjunctivæ and of
the mucous membrane of the whole respiratory tract from its
commencement in the nostrils down to the finest bronchi; frequently
culminating in more or less severe attacks of asthma.
HISTORY.—Bostock, an English physician, is entitled to the credit of
having been the first to recognize and describe this peculiar
affection, for although, prior to his time, Heberden1 had alluded to
symptoms which are now supposed to be referable to hay asthma, and
Cullen had noted the fact that some persons have asthma oftener in
summer than in winter, neither of these writers recognized the true
nature of the disease.
1 Commentary on the History and Cure of Diseases, 4th ed.,
London, 1816, chap. "Destillatio," p. 113.
Bostock's first description of hay asthma appeared in the form of a
paper, "Case of a Periodical Affection of the Eyes and Chest," which he
read before the Medico-Chirurgical Society in London in 1819.2 This
was a description of his own case. Nine years later he gave the details
of 18 additional cases and mentioned 10 others.3 In the second paper,
having noticed that the disease as known to him, the American rose or
June cold, prevailed only in the late spring and early summer, he
styled it catarrhus æstivus. Rejecting the popular theory, that hay
asthma is due to the emanations from hay, flowers, etc., he maintained
that heat was the real cause of the disease.
2 Medico-Chirurgical Transactions, London, 1819, pp.
161–165.
3 Ibid., London, 1828, pp. 437–446.
It appears singular, in view of its frequency at the present time, that
notwithstanding the attention which had been directed to it only 18
cases should have been collected during the nine years which intervened
between the publication of the first and second articles by Bostock,
and tends to prove that in those days the disease could not have been
as common as at present. That this was indeed the case is rendered all
the more probable by the indisputable fact that, owing to the more
general education of the people and to the requirements of a so-called
advanced civilization, other nervous diseases are certainly much more
frequent than they were formerly. The great prevalence of hay asthma
among the educated is a further proof of the correctness
of this
conclusion. It must, however, be remembered that diagnosis did not then
occupy the position it now does, and it is not unlikely that it was
often overlooked or confounded with other diseases.
During the five years which succeeded the publication of Bostock's
second paper no less than five treatises on hay asthma appeared in
England, some of them by the most prominent medical men of that period.
They are remarkable as showing the great diversity of opinion
entertained at that early date as to the etiology of the disease. Thus,
Macculloch4 (1828) attributed it to the air of hot-houses and
green-houses, while Gordon5 (1829) attributed it to the flowers of
grasses, particularly those of the Anthroxanthum odoratum, and
suggested that grass asthma would be a more appropriate name than hay asthma.
4 An Essay on the Remittent and Intermittent Diseases,
London, 1828, vol. i. pp. 394–397.
5 London Medical Gazette, 1829, vol. iv. pp. 266–269.
Even as late as 1859 the disease appears to have been scarcely known in
Germany, for Phoebus, who has since published a most excellent work on
the subject, on being consulted by a colleague suffering from hay
asthma frankly confessed that he was unacquainted even with the name of
the disease. This incident, and the belief that he had before him a
comparatively unworked field, stimulated him to investigate the
disease. By addressing circulars to the various medical societies and
hospitals, not only in his native country, but also in other parts of
Europe, as well as by personal interviews with patients and by
publishing requests for information in the various medical journals, he
collected a large number of cases and gained much valuable information
concerning the disease. The results of his assiduous and painstaking
labors were published in 1862 in the form of a valuable work,6 which,
although over twenty years old, is still regarded the best authority on
the spring variety of hay fever.
6 P. Phoebus, Der Typische Freuhsommer Katarrh, Geissen,
1862.
Previous to the year 1859, when Phoebus's circulars directed attention
to it, hay asthma seems to have been almost unknown in France, as, with
the exception of a single case by Cazenave of Bordeaux (1837), who
described it as a new disease, we find previous to that date no mention
of it in French literature.
The first case of hay asthma published in America, a typical one of the
autumnal form of the disease, is recorded by Drake in his work, The
Principal Diseases of the Interior Valley of North America, p. 803,
published in 1854.
It will be seen by this brief summary of the history of hay asthma that
the disease was first recognized in England in 1819, where in 1828 it
became generally known, and that at the time of the publication of
Phoebus's work (1862), with the exception of one or two isolated cases
in France and the United States, England was the only country in which
it was generally known and understood. Since the publication of
Phoebus's valuable work numerous additions have been made to the
literature of the disease, but with the limited space at my disposal I
can only refer to a few of the most important that have appeared in the
last two decades.
In no country has the subject of hay asthma attracted more attention
than in the United States, and in no other has its study been rewarded
by the discovery of so many new and interesting facts. To Morrill Wyman
of Cambridge, Mass., we are indebted for the first elaborate American
work on hay asthma, or rather the autumnal variety of that affection,
which Wyman believes to be a distinct disease in no way connected with
rose cold, June cold, and other forms which appear in the late spring
and early summer.7 He had previously described the disease in his
lectures as early as 1854, and also in a paper read before the
Massachusetts Medical Society in 1866. Being himself a sufferer from
it, he naturally devoted much time and attention to its study, and his
work may be justly considered the most valuable contribution to the
literature of the disease which has appeared since that of Phoebus.
Another American work on hay asthma is that of the late Beard of New
York.8 He elaborates the nervous theory of the disease, and
establishes three varieties—the first appearing in the spring, the
second in midsummer, and the third in autumn. In 1877, Elias Marsh of
Paterson, N.J.,9 read an exceedingly valuable paper before the New
Jersey State Medical Society, in which he describes a series of
experiments which led him to believe that hay asthma is caused by the
pollen of plants. In Europe the best treatise on the subject that has
been published of late years is undoubtedly that of Blackley of
Manchester, who by a series of ingenious and carefully-conducted
experiments claims to have found in the pollen of certain plants the
true cause of the disease. To all of these works we shall again have
occasion to refer in the course of this article.
7 Autumnal Catarrh, Cambridge.
8 George M. Beard, M.D., Hay Fever and Summer Catarrh, New
York, 1876.
9 "Hay Fever or Pollen-Poisoning," an essay read before the
New Jersey State Medical Society by Elias Marsh, M.D., Paterson, N.J.,
1877.
ETIOLOGY.—In scarcely any other disease is there such a diversity of
opinion in regard to the cause as in hay asthma. We have seen how
Bostock and his contemporaries differed on this point, he attributing
it to heat, while of the others one claimed that it was caused by the
air of hot-houses and green-houses, and another insisted that it was
neither of these, but the flowers of certain grasses. Since that period
other theories of causation have been advanced, but the same diversity
of opinion as to its origin which marked its early history continues
even at the present day.
In treating of the etiology of hay fever the various causes may be
divided into two classes—viz.:
Predisposing Causes.—The fact that hay asthma is frequently
transmitted from one generation to another, so well established by
Wyman, is now very generally admitted, and will become more apparent in
the future, as in estimating this feature it must be remembered that we
have to deal with an affection which seventy years ago was entirely
unknown and which has only recently become generally recognized. That
the fact of the hereditary transmission of the predisposition is
becoming every year more generally accepted is made apparent by the
replies to two sets of circulars addressed to hay-fever patients in
different years. Thus, Wyman, whose circular was issued at least eight
years ago, received 18 affirmative replies out of 80, a little less
than 25 per cent.; while to the writer's circular, issued in 1882,
there are 25 affirmative replies out of 66. Numerous instances have
been recorded where the disease attacked not only two, but even three,
generations of the same family.
Hay asthma appears to be much more prevalent among males than females,
the proportion being 3 males to 2 females. There is no apparent reason
for this discrepancy other than that males are as a rule more exposed
to the vicissitudes of weather, and that the restless energy with which
many of them carry on their avocations predisposes to the disease.
The causes which produce hay fever act alike upon many thousands, an
infinitesimal percentage of whom are attacked. There must therefore be
some individual peculiarity which predisposes certain persons to the
affection, but, aside from the facts that those attacked are usually of
a nervous temperament, and that the respiratory mucous membrane of many
of them is extremely sensitive, and that the vascular erectile tissue
over the turbinated bones and lower portion of the septum is often
hypertrophied,10 there are no
known peculiarities by which it
can be recognized. What races are subject is a question which thus far
has received but little attention. To the writer's knowledge, the only
well-established fact relative to race susceptibility is that negroes
are exempt from the disease, and that in India (Blackley) it does not
occur among the natives.
10 Roe, The Pathology and Radical Cure of Hay Fever, 1883,
p. 9.
Statistics show that it is much more common in youth and middle age,
and that comparatively few are attacked after forty, as will be seen by
referring to the following table:
| Age when First Attacked. |
Wyman's Cases. |
My Own Cases. |
Total. |
Under 10
10 to 20
20 to 30
30 to 40
40 to 50
After 50 |
11
11
25
8
11
2 |
10
17
13
11
5
1 |
21
28
38
19
16
3 |
Wyman is of the opinion that females are attacked later in life than males.
Without knowing the numerical proportion which the various professions
and occupations bear to each other, it is impossible, even with the aid
of statistics, to determine which of them is most subject to hay
asthma; but the annexed table shows conclusively that those who do
brain-work are much more frequently attacked than those who earn their
living by manual labor:
| |
Wyman. |
My Own. |
Total. |
Statesmen
Clergymen
Jurists and lawyers
Physicians and medical
teachers
Dentists
Pharmacists
School-teachers
Students
Military
officers
Authors, editors, etc.
Mechanical engineers
Bankers
Bank
officers
Merchants
Brokers
Manufacturers
Clerks
Artisans
Farmers and
gardeners
Butchers
Laborers |
1
6
6
8
1
0
3
6
3
0
0
3
2
11
0
12
1
1
4
1
0 |
0
3
2
4
0
1
0
1
0
1
1
1
1
7
1
3
1
1
211
0
1 |
1
9
8
12
1
1
3
7
3
1
1
4
3
18
1
15
2
2
6
1
1 |
It will be seen by the above that of 100 cases, only 12 were engaged in
outdoor pursuits, and that the remaining 88 followed occupations
necessitating confinement within doors and entailing more or less
intellectual effort; which proves conclusively that the earlier writers
on hay asthma were correct in regarding it as a disease of the more
cultured classes of society. The writer agrees with Wyman that the
large increase in the number of hay-fever sufferers may in a great
measure be attributed to the circumstance that many
who were
formerly pursuing agricultural and mechanical pursuits are now engaged
in occupations which require more or less intellectual effort.
11 One of these was an amateur and highly educated.
To determine the value of temperament I have followed Beard's example,
and in my circular of inquiry propounded two questions: 1st, the
temperament of the patient's family; 2d, his own temperament. To the
first query I obtained replies which showed that the nervous
temperament predominated in 28 out of 37 cases; or, in other words, the
family temperament was more or less nervous in two-thirds of the cases.
As regards the patients themselves the temperament was as follows:
| |
My Own. |
Beard. |
Total. |
Sanguine
Nervo-bilious
Nervous
Nervo-sanguine
Nervo-lymphatic
Lymphatic
Sanguino-bilious
Bilious
Sanguino-lymphatic
Bilio-lymphatic |
8
5
23
9
0
3
4
7
0
0 |
18
23
67
27
3
0
5
29
1
1 |
26
28
90
36
3
3
9
36
1
1 |
It thus appears that the nervous element predominates in no less than
157 out of 233 cases.
Other diseases do not appear to predispose to hay asthma, nor, on the
other hand, is that affection a cause of any other disease. The
question whether naso-pharyngeal catarrh is more common among hay-fever
subjects has, after careful investigation, been decided in the negative.
Exciting Causes.—It is generally conceded that the suggestion of a
large number of remedies in the treatment of a disease is good evidence
that no effective curative agent has as yet been discovered. This
observation regarding therapeutics equally applies to etiology, a long
array of causes usually developing the fact that great uncertainty
exists as to the real causative agent. Hay fever affords a most
striking proof of the truth of this remark. The simple enumeration of
the various agents which have been accused of causing the attacks would
cover several pages. An example of the multiplicity of its supposed
causes is afforded by the replies to the question in Beard's circular,
"What is the cause of your attacks?" no less than thirty-three agents
being accused of causing the disease. Of these I propose to confine
myself to a few of the most prominent.
Early in the history of hay asthma heat was considered its chief cause,
Bostock, its first describer, having held that view, as have also many
of his successors. It is now generally conceded that heat of itself is
not a cause, although by promoting vegetable growth and causing dust it
may still be regarded as an indirect factor in its etiology. That heat
of itself is not a cause is proved by the occurrence of the disease not
during the intensely hot weather of midsummer, but in the late spring
and early fall. It, however, undoubtedly produces a temporary
aggravation of many of the symptoms. This appears to be especially the
case in the autumnal variety, as those who have the disease in the
spring seldom complain of any ill effects from heat.
"Strong light, sunshine, especially when it falls upon the face, will
produce a violent paroxysm of sneezing, and the other symptoms then
follow in quick succession; and moving from shade to sunshine, even
when not otherwise annoying, will do the same." This is the opinion of
Wyman, and coincides with that of Phoebus, Abbott Smith, and others,
and is amply confirmed by the experience of the writer. This
applies also, though in a less degree, to artificial light, especially
gas-light.
Dryness of the atmosphere, by promoting dust, may be regarded as an
indirect cause. Hay-fever patients agree almost unanimously that their
symptoms are aggravated on clear, bright, dry days, and that they feel
most comfortable in damp and cloudy weather.
There is no evidence to show that electricity is in any way connected
with the etiology of hay fever.
Ozone is certainly not a cause, as hay-fever patients feel best on the
sea-coast and ocean, where ozone is most abundant.
Long before hay fever was recognized by the medical profession hay was
supposed by the general public to be the cause of the disease. In
England especially, but also in the north of France and in Switzerland,
this opinion prevailed very generally. Some suppose that the dust which
it contains is the real cause, while others attribute it to its
peculiar odor. In those susceptible to its influence it appears to make
but little difference how they come in contact with it, whether in an
open field where it is mowed, by driving behind a wagon loaded with it,
or by entering a stable or loft where it is stowed away. It is not,
however, the cause of the autumnal variety, as it is harvested in the
temperate regions of North America, where this form of disease is most
common, in June or early in July, which is six or eight weeks earlier
than the period at which the attacks commence. That hay is a cause of
the earlier variety of the disease is evident from the experience of
numerous intelligent invalids, who trace it to that agent from the fact
that the outbreak coincides with the blooming or harvesting of hay, and
that removal from the locality in which they are exposed to its
emanations is followed by relief. It must be remembered, however, that
hay does not consist of dried grass alone, but that it contains other
plants and flowers, as well as a large amount of dust.
The flowers of grass, especially those of the Anthroxanthum odoratum,
may be regarded, like hay, as one of the causes of hay fever—a fact
that was early recognized by Gordon and others. Blackley12 cites the
case of an Indian medical officer of high rank, whose statement is as
follows: "I have suffered from hay fever for about thirty-five years; I
have had it both in India and in England. The period at which the
attacks come on is not fixed, the date of the attacks depending more on
the grass ripening late or early than on any other circumstance. They
always begin toward the end of the hay season, when the grass is fully
in flower, and cease slowly and gradually—not directly—on gathering
in the grass."
12 Hay Fever, its Causes, Treatment, etc., p. 47, London,
1880.
Rye, oats, and wheat in bloom may also be ranked among the exciting
causes of hay fever.
Indian corn in bloom often causes symptoms of hay fever, but that it
does so only in certain cases is evident from the fact that the disease
does not exist in some places where large quantities of corn are raised (Wyman).
Geraniums, roses, heliotropes, and other sweet-scented flowers often
bring on attacks. The bean in bloom and elderflowers are also regarded
as causes.
Ragweed, also known as Roman wormwood, Ambrosia artemisiæfolia, a weed
which extends almost over the whole of the United States, is a powerful
cause of the autumnal variety, but, like all the other agents which
have been accused of causing hay fever, is by no means general in its
action, many patients being able to inhale the dust shaken from the
flowers with perfect impunity even during the critical period. On those
susceptible to its influence it will act not only during the hay-fever
season, but also at other periods of the year. Wishing to study the
plant, I procured during the fall several
specimens of it and
placed them between the leaves of a large quarto volume. During the
winter my wife, who is a sufferer with hay fever, accidentally opened
the book, and, seeing the plant, not knowing its nature, picked it up
and smelt it. She immediately began to sneeze, the eyes and nose itched
intensely, there was profuse lachrymation; in short, all the symptoms
of a mild attack of hay fever supervened, the effects of which lasted
until the following morning. The case is interesting from the fact that
in this instance the experiment was made unconsciously, and the effects
could not therefore be attributed to the imagination, the patient being
entirely ignorant of the nature of the plant. The prevalence of
autumnal hay fever appears to coincide with the blooming of the
ragweed, and conforms to the geographical distribution of that plant,
which grows wherever the disease prevails, while in exempted localities
it is seldom found or never seen. In Bethlehem, N.H., a diligent search
was made for it for two days by a botanical friend without his finding
a single specimen, although in the neighboring town of Littleton, which
is within sight of Bethlehem and is not exempt, the plant is quite
abundant. Marsh states that he saw none of it in New Brunswick nor at
Moosehead Lake.
Dust of various kinds is more frequently designated by invalids
themselves as the cause of their disease than any other agent. Thus, in
reply to his question as to the cause of hay fever, Beard received 104
replies assigning dust as the cause, while 540 attributed it to thirty
other agents. All kinds of dust, both in and out of doors, are accused,
but that of railway-cars is supposed to be the most potent.
There is but one case on record in which animal parasites were the
cause of an attack—that of Bastian, who while engaged in the spring
investigating the anatomy of the Ascaris megalocephala, one of the
parasites of the horse, noted that its emanations not only in the fresh
state, but after having been kept in spirits for two years, invariably
caused itching about the eyelids, irritation of the conjunctivæ, with
continuous sneezing and other symptoms resembling hay fever. These
symptoms ceased after two months, and did not return until the
following spring. He finally became so sensitive that the wearing of
the coat in which he had worked during the examinations was sufficient
to bring on the symptoms.13
13 Salisbury in Infusorial Catarrh and Asthma attributes
hay asthma to an animalcular organism, the asthmatos, but his
assertions have not as yet been confirmed by other investigators.
Helmholtz, himself a sufferer from hay fever, discovered that the
secretion of his nasal mucous membrane contained during the attack a
number of vibriones, and, never being able to find them there at other
times of the year, concluded that they were the cause of the disease.
Binz of Bonn having discovered that quinine was inimical to the
vibriones, Helmholtz supposed that that agent would be the proper one
to employ in the treatment. He used it with success, injecting a
saturated solution into the nostrils, the injection each time affording
marked relief.
THE POLLEN THEORY.—Believing from his own experience and that of
others that hay fever was due to the pollen of certain plants, Blackley
of Manchester instituted a series of ingenious and instructive
experiments to prove the correctness of his conclusions. In his first
set of experiments a very small quantity of the pollen of various
plants was applied to the lining membrane of the nostril. That of the
Lolium italicum produced at first a slight feeling of anæsthesia at the
point to which the pollen had been applied, followed "by a feeling of
heat which gradually diffused itself over the whole cavity of the
nostril and was accompanied by a slight itching of the part. After some
three or four minutes a discharge of serum came on and continued at
intervals for a couple of hours." The mucous membrane became so swollen
as to partially occlude the nostrils and impede the entrance of
air. When rye was used the symptoms were much more violent, and were
attended by violent and long-continued fits of sneezing. With wheat and
oats the effect was equally decided. The same experiment was tried with
other orders of plants with varied success, some of them being very
active, while others were found to be quite inert. One grain of the
pollen of Alopecarus pratensis was applied to the fauces, causing
itching and diffused redness. That of the Lolium italicum rubbed into
the abraded skin of the forearm, as in vaccination, produced itching
and swelling.
Marsh,14 who has repeated Blackley's experiments in America, gives
some very interesting facts in regard to the pollen of the Ambrosia
artemisiæfolia. On the 5th of August, 1874, he placed a few sprigs of
the ambrosia in full bud, but without open flowers, in a glass of water
in his office. The next day the flowers were open, and on handling the
plant for the purpose of preparing some microscopic specimens from it,
the pollen was freely scattered around. This caused in him severe
coryza of twenty-four hours' duration, with occlusion of the nostrils
and serous discharge. On August 13th he repeated the experiment, this
time intentionally applying some of the pollen to the nostrils. This
produced such severe symptoms that he had to have recourse to a
hypodermic injection of morphia for their relief. These, however,
continued into his regular attack, which should have been due a few
days later.
14 Op. cit., p. 14.
Having proved that the pollen of certain plants was capable of
producing hay asthma, Blackley next turned his attention to the
determination of the amount of that substance floating in the
atmosphere of different places and at various periods of the year. The
plan which he found best adapted to his purpose was to expose slips of
glass to the open air for a given length of time, so as to allow any
solid matter the air might contain to deposit upon the glass. On each
of these slips a space of one centimeter square was made sticky by
covering it with a mixture of water, proof spirit, and glycerin. These
were exposed to the atmosphere for twenty-four hours, and then placed
under the microscope and the number of pollen-grains adhering to the
moistened square counted. These slides were exposed at the height of
four feet nine inches above the ground, "the average breathing-level,"
and were placed in a grass meadow four miles south-west of Manchester.
The experiment was begun early in April, 1866, and continued until the
1st of August. Only a small quantity of pollen was found during the
first month. On May 30th it appeared in much larger quantities, and
continued to appear on most of the days until August 1st. Barometric
pressure did not influence the deposit of pollen, but whenever the air
was drier the quantity was increased. A fall of rain, especially if
attended with lowering of temperature, had the effect of materially
lessening the number of grains. The largest quantity of pollen was
obtained on June 28th, the day after the highest temperature of the
season, showing that a large deposit of pollen coincides with, or
follows, a marked rise in temperature. Fully 95 per cent. of the pollen
collected belonged to the Graminaceæ, but this would not apply to other
localities and countries, in which that of other plants would naturally
predominate. These experiments were quite successful in demonstrating
that the rise and progress of the disease corresponded with the amount
of pollen present in the atmosphere. A third set of experiments was
made by attaching the glass slides to kites, to determine the amount of
pollen present in the air at different altitudes. These experiments
revealed the fact that grass pollen was much more abundant at
elevations of 500 to 1500 feet than near the surface of the ground.
Marsh also investigated this portion of the subject, only, instead of
attaching the slides to kites, they were placed in the attic windows:
he arrived
at conclusions in regard to the pollen of ambrosia
similar to those which Blackley had reached with reference to the Graminaceæ.
The experiments of Blackley justify the belief that the cause of the
early form of hay fever, which prevails in England, is to be found in
the pollen of a number of plants, especially grasses and grains, which
bloom in the late spring and early summer, while those of Marsh prove
conclusively that the Ambrosia artemisiæfolia, or Roman wormwood, is
certainly one, and probably the chief, cause of the American or
autumnal variety of the disease.
GEOGRAPHICAL DISTRIBUTION.—Both varieties of hay fever prevail in the
United States, but the late variety is much more frequent, and may be
regarded as peculiar to this country. The distribution of the early
form of the disease is much more extensive. It is quite frequent in
Great Britain, and, according to our present knowledge, it extends over
France, Belgium, Holland, Switzerland, Italy, Russia, and in the plains
of India (but only among foreign residents). Further investigations
will probably show that it also extends over the other temperate
regions of Europe. As before stated, the autumnal form is confined to
the United States, where it prevails much more extensively than was
formerly supposed. Commencing in Florida, where it is quite rare, it
extends northward up to Eastport, Maine. Its northern border is defined
by Wyman15 as follows: "From the St. Croix, south of Houlton in
Maine, or about the line of 600 feet elevation above the sea-level, the
line of exclusion turns eastward, following approximately the border of
the elevation just mentioned, excluding the interior lakes of Maine,
which are about 1000 feet above the sea, and, descending toward the
south, strikes the White Mountain region at its northern portion.
Thence, turning toward the St. Lawrence River and running along the
height of land which divides the waters falling into the Atlantic from
those falling into the St. Lawrence, parallel to the St. Lawrence, it
strikes that river north of Lake Champlain." Thence along the southern
border of the Great Lakes to the south of the island of Mackinaw,
between Lakes Huron and Michigan. "It then crosses the lake and runs
north of Lake Winnebago to St. Paul, Minn., leaving the Lake Superior
copper-regions beyond its influence." From this point the line is
undetermined, but there is evidence to show that the disease occurs in
Colorado. The statement of previous authors, that the disease does not
prevail in California, is confirmed by a statement recently made to the
writer by Hatch, secretary of the Board of Health of that State, who
adds that several parties have removed there to avoid the disease.
Southward, the line runs along the Mississippi River to New Orleans,
where the disease prevails. The southern and eastern borders are the
Gulf of Mexico and the Atlantic Ocean.
15 Op. cit., p. 63.
SYMPTOMS AND COURSE.—No better description of an attack of the
autumnal form of hay fever has ever been written than that of Wyman,
who, being himself a sufferer from the disease, has had exceptional
opportunities for studying it in all its details. I therefore extract
the following from his work:16
"All the cases agree in the time of
annual return, about the 20th of August, varying but a few days from
this date in different years. By some individuals it is believed to be
remarkably punctual, being first noticed on precisely the same day of
the month, and, it is even asserted, at the same hour of the day. It is
first perceived as a slight itching in the palate and in all parts
about the roof of the mouth, soon followed by similar sensations,
apparently in the Eustachian tube, extending from the throat into the
ears, and inducing the sufferer to attempt relief by swallowing and by
rubbing his tongue against the back part of the hard palate, and by
pressing and rubbing the external orifice of the ear to give motion to
the parts within. There is often a sense of tension about the forehead,
especially over the eyes in the region of the
frontal sinuses. In
a day or two the nostrils are affected; there is irritation of the
lining membrane, sneezing, and a stuffing and obstruction of the
nostrils. This obstruction is peculiar; it occurs in paroxysms of short
duration, one or both nostrils becoming suddenly obstructed, and in two
or three minutes as suddenly relieved; at other times the obstruction
is more prolonged. But, however complete, it is in many individuals
almost immediately relieved by active exercise, rapid walking, leaping,
or any movement indeed which gives warmth to the extremities.
"At first these attacks occur only in the morning or on first rising;
as the disease advances they occur later in the day, but still in short
paroxysms. At this stage the discharge from the nostrils is limpid and
almost free from mucus; it is often very copious, especially during or
immediately following attacks of sneezing. Holding down the head is
often accompanied by a rapid dropping of the same fluid without
sneezing. With this trouble in the nostrils come watering of the eyes
and itching along the edge of the lids and in the conjunctivæ
generally, but most at the inner corners. This irritation occurs also
in paroxysms of a few minutes' duration. It is so intense that it is
difficult for the sufferer to refrain from rubbing the eyeballs
violently, which soon relieves them, notwithstanding that such
treatment increases the turgidity of the vessels until the whole
conjunctival surface is of a nearly uniform red. The eyelids are
swollen, their edges red and inflamed; the small glands are also
inflamed, and in some cases pustules or styes form and break, leaving
an excoriated surface which heals slowly. The whole face is often red
and swollen, especially in the morning. The senses of taste and smell
are much impaired, in some cases almost abolished; and at times there
is partial deafness, with a sense of obstruction of the internal ear.
The lining membrane of the external tube is sometimes much irritated,
even to the extent of producing a thin discharge, without evidence of
the irritation extending to the tissue beneath. Swallowing is
interfered with, especially when the nostrils are so obstructed as to
prevent the perfect motion of the parts necessary to this act. The
lining membrane of the mouth, tonsils, and pharynx partakes of the
general irritation, and becomes red; and sometimes there is soreness of
the throat. The lips become dry, cracked, and swollen. The skin is
easily irritated and excoriated, and the excoriations are not so
readily healed as in health. Many also suffer from itching of the skin,
especially of the scalp, back, and chest, at times accompanied by a
slight papular eruption. During some portion of this period there is
chilliness, or rather sensitiveness to cold; more or less pain or sense
of oppression in the head; the appetite diminishes; there is lassitude
and weakness, the skin hot and dry, with other signs of a febrile movement.
"Toward the end of the second week to these symptoms are added
irritation of the membrane lining the air-tubes; a frequent and dry
cough, commencing with a sense of tickling in the upper part of the
windpipe, but little relieved by the cough or only after long coughing;
and the expectoration of a small quantity of transparent, glairy mucus.
The severity of these bronchial symptoms depends much upon the
condition of the atmosphere: if dry and dusty, the cough is much worse;
dampness and a rainstorm give relief.
"During the third week the affection of the lungs gradually increases;
the cough, still with very little expectoration, is more troublesome,
especially in the night, sometimes compelling the patient to spend an
hour or two sitting up, and not infrequently is spasmodic in its
character, producing convulsive retching or even vomiting.
"The disease may now be assumed to be at its height. It is in this
stage also that in some cases asthmatic symptoms appear, and, although
they are sometimes severe, are not long continued. At the end of the
third week the catarrhal symptoms diminish, the tickling of the fauces
ceases, the eyes and nose improve; but the cough is apt to
continue longer, and the heart's action is easily accelerated by
exercise, and the pulse is sometimes intermitting. The skin is dry and
warmer than natural.
"During the fourth week in September these symptoms gradually diminish,
and by the end of September or the first frost are nearly gone, leaving
weakness and a more or less altered state of the mucous membrane of the
air-tubes, the effect of the prolonged irritation, from which the
patient, if otherwise in good health generally soon recovers."
16 Op. cit., p. 9.
The spring form of the disease, known as June cold in the United States
and as hay fever in England, differs from the late variety in the time
of its occurrence, the attack coming on, as its name implies, in the
late spring, usually between the 15th of May and the 15th of June,
sometimes much earlier; one of my patients reporting that she commences
to sneeze as early as the middle of April. The attacks in this variety
usually cease during the first or second week in July, although a few
continue on into August—a fact which induced Beard to establish a
third or middle form of the disease. The symptoms are essentially the
same in both varieties, but are much less severe in the early form,
which is also of shorter duration. They differ as to cause, the spring
variety being usually due to newly-mown hay. It occasionally happens
that one person has both forms of the disease, or that a person who has
hitherto had the early form fails to have it in the spring and is
attacked in autumn.
INDIVIDUAL SYMPTOMS.—There is occasionally a stage of incubation,
lasting about a week, during which there is slight feverishness and
undue susceptibility to nervous impressions. The patient often
experiences a feeling of lassitude and weakness; the digestion is
disturbed, as indicated by a coated tongue, want of appetite, and
constipation; he is disposed to be wakeful, and when he does sleep his
rest is often disturbed by unpleasant dreams.
The first effect of exposure to the irritant is itching of the nose,
slight in the beginning, but increasing in severity as the disease
advances, until it at last becomes unbearable. The mucous membrane is
red and swollen, the swelling being often so great that it interferes
with the passage of air; a watery discharge sets in, which, although
slight in the early stages, soon becomes copious, and in severe cases
is so abundant that it actually streams from the nostrils. Sometimes,
when both nostrils are stopped, if the patient changes his position and
lies on the side the uppermost nostril will become free. These symptoms
are attended with sneezing—not the sneezing of an ordinary coryza, but
powerful sternutatory efforts repeated in quick succession and utterly
uncontrollable. In one case which has come under my observation the
sneezing invariably brought on menstruation in advance of the regular
period, and on some occasions caused abortion.
These symptoms just mentioned often appear and disappear with great
rapidity, especially in the early stages of the disease, and are
usually worse in the morning on awakening.
Itching of the eyes begins at the inner canthus and generally extends
over the greater portion of the conjunctiva, slight at first, but
becoming more troublesome as the disease progresses. There is also
redness of the conjunctiva, sometimes of the lids alone, at others
extending over the whole mucous membrane, and giving to the eyes a
bright-red appearance. The lids in severe cases are not infrequently
oedematous, lachrymation is greatly increased, and the tears, trickling
down the face, are liable to cause excoriation of the skin. Pustules
and styes often form on the lids. There is more or less photophobia,
according to the severity of the attack.
Owing to the occlusion of the nostrils the patient is often compelled
to breathe through the mouth, thus causing an uncomfortable drying of
the mucous membrane. There is a peculiar itching of the hard palate,
which
the patient attempts to relieve by rubbing the roof of the
mouth with the point of the tongue. This itching sensation extends over
the pharynx, posterior nares, and upward through the Eustachian tubes
to the ears, causing a disagreeable irritation, which the patient tries
to alleviate by thrusting the tip of the finger into the external
meatus. The mucous membrane of the pharynx is red and swollen. The
dryness observed early in the attack gives place later to increased
secretion, which is sometimes quite abundant. On the anterior surface
of the velum of one of my female patients I observed a hard papule
about the size of a lentil, which she assured me was always coincident
with the attack, and never appeared at any other time.
In addition to headache, which is quite common, patients frequently
complain of a heaviness and fulness, also of a peculiar sensation as
though the head were constricted by a band. This latter symptom I have
found present in about one-half of the cases investigated.
Itching of the skin is quite common, especially of the face, between
the shoulder-blades, and over the sternum, and is frequently
accompanied by a slight vesicular eruption and occasionally by urticaria.
The whole respiratory tract is in a state of catarrh, but there is very
rarely any cough during the first week. This usually commences in the
second week, and at that time is short and dry, and becomes every day
more frequent until the third week, when it changes its type and
becomes paroxysmal. During the first three weeks there is little or no
expectoration, and what there is consists of small transparent
glutinous masses. About the fourth week the irritation reaches the
finer bronchi, and in many cases there is more or less asthma, which,
like ordinary bronchial asthma, usually comes on at night. The asthma
is sometimes quite severe and long-continued. Wyman states that very
few escape cough. This does not accord with the writer's experience, as
in 65 of his cases 15 had no cough.
Hay-fever patients suffer greatly from mental depression, complain of
lassitude, and their capacity for intellectual labor is diminished.
They are often troubled with insomnia, and when such patients do sleep
it is in a fitful way, and their rest is often broken by unpleasant dreams.
NOMENCLATURE AND CLASSIFICATION.—The various terms used to designate
this disease are all misnomers, and up to the present time none has
been devised which conveys any idea of the true character of the
disease. Hay fever is incorrect, because hay is only a cause in a
limited number of cases, and fever is by no means a prominent symptom.
Hay asthma should be discarded, for asthma is far from being a constant
accompaniment of the affection. Autumnal catarrh or early spring
catarrh only serves to designate the time at which the two forms
usually appear, but conveys no idea of the disease in its entirety;
while the term pollen catarrh or pollen fever is objectionable on the
ground that, although the disease is most frequently produced by that
agent, there are causes other than pollen which may excite it.
Hay fever is variously classified by different authors, some, like
Thorowgood and Beard, regarding it as a neurosis, while others
(Bostock, Phoebus, and Wyman) appear to regard catarrh as its
distinguishing feature. Zuelzer has recently classed it among the acute
infectious diseases, but assigns no reason for placing it in that group.
DIAGNOSIS.—To any one at all familiar with the symptoms of the disease
the diagnosis of hay fever is quite easy. Its distinctive features are:
It appears at the same time every year (the early form about the 1st of
June and the later about the 20th of August); the severity of the local
symptoms which usher in the disease—sneezing, stoppage of the
nostrils, the inflamed condition of the eyes, and above all the itching
of the nose, eyes, skin, and mucous membrane of the root of the mouth.
A detailed differential diagnosis is not as important now as it
was formerly, when, as in the days of one of its early describers,
Phoebus, "Man sah sie nicht, wo sie war, und sie sah, wo sie nicht war."
PROGNOSIS.—The number of elderly persons with hay fever, many of whom
have passed the allotted threescore years and ten, and the fact that no
one has ever been known to die from the disease, affords conclusive
evidence that it does not shorten life. On the other hand, when once
affected, except in those cases relieved by operative procedure, the
patient remains subject to it during the remainder of his life. A few
isolated cases are said to have recovered, but such a result is
extremely rare. It is thought by some that a prolonged residence in the
South may mitigate the disease, and eventually cure it, but this
assertion lacks confirmation. It does not, like bronchial asthma, lead
to secondary affections, the interval between the attacks giving the
organs time to recuperate, nor does it predispose to other diseases.
TREATMENT.—Aside from its surgical treatment, to which I shall refer
farther on, the only effectual remedy for hay fever consists in removal
to a region which is exempt from the disease. By going to such a
locality before the attack occurs, and remaining there throughout the
critical period, complete immunity from the disease may be secured. The
time of departure and return must be determined by the previous
experience of the invalid in regard to the date upon which his former
attacks have commenced. As the disease seldom comes on exactly on the
same day every year, but often varies three or four days, he should be
in his place of refuge at least a week before the usual time for the
attack, and should remain until he can return with perfect safety. This
is usually about the middle of July in the early variety, and after the
first frost severe enough to kill vegetation in the autumnal form.
In the milder form which occurs in the spring the seashore affords
considerable relief, except when the wind is from the land. It is
therefore uncertain, and is only indicated when the circumstances of
the patient prevent his visiting one of the exempt localities. On the
eastern coast of the United States there are several places of this
character, such as the Isles of Shoals, a group of rocky islands with
little or no vegetation off the coast of New Hampshire, the climate of
which is very like that of the ocean; and Fire Island, near New York.
Similar to the above, but much more exposed to land influences, are
Mount Desert and Nantucket.
The ocean itself affords complete exemption, and a sea-voyage is the
surest means of avoiding the disease. It is true that persons have been
known to be affected with hay fever even in mid-ocean, but in such
cases it is more than probable that the cause of the attack could have
been traced to the cargo. A case of this character came under the
writer's observation during a voyage from New York to Charleston during
the month of September, and was evidently caused by hay, a number of
bales of which were stowed on the forward deck of the vessel. It makes
comparatively little difference what particular voyage is undertaken,
provided the vessel's course does not bring her too near land; but for
most hay-fever patients a trip to Europe is to be preferred, especially
for those suffering with the autumnal form, as by going to that
country, where this variety does not exist, they avoid the necessity of
remaining nearly two months on the water. A voyage to California is
almost as good, and for the same reasons.
Whether this applies to the so-called June or rose cold, which is quite
common in Great Britain and prevails to some extent on the Continent,
has not as yet been definitely determined, but it is more than
probable. Whether patients who have contracted the disease in Europe
would escape in America is exceedingly doubtful. Two of the cases
reported to the writer, who were first attacked (with the early form)
in Europe—the one in Switzerland and the other at Florence—continued
to have the disease after their return to this country; while, on
the other hand, an English lady who was subject to the disease at home
escaped entirely during her residence of three years in the Southern
States. Of the exempt regions in the United States, the one most
frequently resorted to, and which at the same time affords the surest
relief, is that of the White Mountains of New Hampshire—not the whole
of it, but a certain portion, which is bounded on the west by a line
drawn from Littleton to Lancaster (but not including the former place,
which is only partially exempt), on the north by Canada, on the south
by Franconia, Crawford House, and Jackson, while to the east it extends
as far as Bethel in Maine. Of the various places contained within this
territory, Bethlehem and Jefferson, Whitefield, White Mountain House,
Fabian's, Twin Mountain House, Crawford House, Glen, Gorham, and Mount
Washington, may be regarded as entirely exempt; Franconia Notch almost
equally so; while Dalton, Lancaster, and Bethel must be ranked as
uncertain. Another exempt region extends to the north and east of the
one just described, and comprises the lake region of Maine. Petoskey in
Northern Michigan, at the head of Little Traverse Bay, is said to
afford almost entire relief, and is resorted to by a large number of
patients from the Western and South-western States. There are also
several places in Vermont which offer more or less immunity, such as
Mounts Mansfield and Stow, both of which, however, are inferior to
those first mentioned. Canada, with the exception of a few cases
reported at Toronto, St. Catherine's, and at a few places near its
southern border, appears to be exempt. The same may be said of the
Adirondack Mountains and Pottersville on Schroon Lake and Marquette.
The Catskill Mountains and several places high up on the Alleghanies,
such as Cresson, Pa., Oakland and Deer Park in Maryland, afford relief
in many cases. Colorado is said to be exempt, but several patients who
have gone there failed to obtain relief. California is free from the
disease, and many hay-fever patients have escaped their attacks by
removal to that State. I know of no place in the Southern States which
affords relief except Florida, where the disease is rare; several cases
have been entirely relieved during their residence there. In others,
however, the experiment was unsuccessful.17
17 Two patients in their replies to the writer's circular
claimed to have been entirely exempt—the one (early form) at Beaufort,
and the other (autumnal) at Mount Airy, Habersham county, Ga. Wyman
mentions four cases that were relieved at or near Beaufort.
The relief obtained by resorting to an exempt locality after the attack
has begun is very prompt, all symptoms of the disease disappearing
within a few days after the arrival of the patient. While residing at
Bethlehem, N.H., I was called one evening to see a German who had just
arrived on the train from Fall River. His condition was most pitiable:
his eyes were fiery red, the nose and face were terribly swollen, while
the water streamed from both eyes and nose. The asthma was at its
height, and his struggles for breath were fearful in the extreme. A
quarter of a grain of morphia was injected into the arm, and after
providing other means for his comfort I left him for the night. The
next morning, while preparing to pay him an early visit, the patient
himself appeared at my office, bright and cheerful, and so much changed
that I at first failed to recognize him. A single night had served to
dissipate all traces of his hay fever.
Unfortunately, a journey to the mountains, and a residence there of six
or eight weeks, are not within the reach of every one afflicted with
the disease; and for these unfortunates something must be done to
relieve, or at least mitigate, their sufferings. If unable to visit any
of the exempt localities, a sufferer may secure a certain degree of
comfort by exposing himself as little as possible to the exciting
causes of hay fever. As it is well known that heat and dust aggravate
the symptoms, the windows of the apartment occupied
by the
patient should be so arranged as to exclude the sunlight and every
precaution taken to avoid the presence of dust. He should eat good,
nutritious food, avoiding the use of all stimulants, except perhaps a
little light wine at dinner. Anything which induces dyspepsia must be
carefully guarded against, and care taken to keep the bowels regular.
Blackley18 advises as a surer method of excluding the irritant
(pollen) the hanging of a curtain of thin calico before the door and
fitting into the lower portion of one of the windows a screen made of
two layers of thin black muslin enclosed in a square frame. When in use
both curtain and screen should be moistened with a solution of carbolic
acid, ten grains of the acid to one pint of water. For those who are
compelled to go out he has devised a very ingenious respirator. Having
taken an exact cast of the nasal passages from the margins of the alæ
and septum to the inferior turbinated bones, he constructed with the
aid of these, by means of the galvano-plastic process, cases of silver
fitting exactly all the folds and depressions of the cavity. Several
layers of platinum wire, 0.001" to 0.007", were arranged in the cases.
The sieve thus formed was moistened before using with a
1/10 per cent.
solution of carbolic acid. To prevent the pollen from coming in contact
with the eyes, they were protected with spectacles provided with
accurately-fitting gauze guards. The result of wearing this apparatus
was an almost perfect freedom from unpleasant symptoms.
18 Op. cit., p. 267.
In the absence of any specific, the medicinal treatment of hay fever is
necessarily confined to palliative measures. Debility being one of the
prominent symptoms, tonics are indicated, and in this way quinine, at
times regarded almost as a specific, may be of use. It should be given
in doses of one or two grains three times a day before and during the
attack. Thus administered, it is undoubtedly of great utility in many
cases. Arsenic, whether in the form of Fowler's solution or the iodide
of arsenic, as suggested by Blackley, may also be used with advantage.
Galvanism, which was used successfully by Hutchinson of Rhode Island,
is strongly recommended by the late Beard. He advises that the negative
pole be placed at the epigastrium "and the positive applied a moment
over the forehead and on top of the moistened head, then over the front
and back of the neck, and down the upper and middle of the spine." The
current used should be mild and the sittings short. The writer has had
no personal experience with this method of treatment, nor has it been
generally adopted.
The injection into the nostrils of a saturated solution of quinine by
Helmholtz, although apparently useful in his case, has not met with
like success in the hands of others.
The troublesome itching and burning of the eyes and face are most
readily relieved by bathing the parts at first in tepid and then in
cold water, repeated several times a day, and with mild astringent
collyria, such as a strong infusion of tea or of one or two grains of
sulphate of zinc to an ounce of rosewater. If the lids be much inflamed
and the skin excoriated, the following ointment may be applied:
| Rx. |
Bismuth. subnit. |
drachm ss; |
| |
Ungt. simpl. |
ounce j. |
| M. Ft. ungt. |
|
The pharyngeal symptoms are best controlled by chlorate of potassium as
a gargle, or, better still, in the form of the compressed tablets now
prepared by many of our druggists. The treatment of the asthmatic
symptoms differs in no way from that which we have recommended for the
paroxysms of BRONCHIAL ASTHMA, the details of which were fully
described in the preceding article.
In 1880, Harrison Allen of Philadelphia published an article19
directing
the attention of the profession to the fact that many
cases of chronic nasal catarrh which had resisted the ordinary methods
of treatment could be readily cured by restoring the permeability of
the nasal passages.
19 Am. Journal of Med. Sciences, January, 1880,
Philadelphia.
In April, 1882, William H. Daly of Pittsburgh, Pa., in a paper20 read
before the American Laryngological Association, gave the histories of
three cases of hay fever which he had succeeded in curing by means of
operative procedure. In each of these cases the tissue over the
inferior and middle turbinated bones was hypertrophied, and in one case
it was so extremely sensitive that the slightest touch with the probe
was sufficient to excite a violent paroxysm of sneezing. In these the
diseased tissue was removed with the galvano-cautery or by the
application of glacial acetic acid.
20 "On the Relation of Hay Asthma and Chronic
Naso-pharyngeal Catarrh," Archives of Laryngology, vol. iii. No. 2.
The following year (1883) a much more elaborate article21 on the same
subject was published by John O. Roe of Rochester, N.Y. After
describing the highly vascular and somewhat erectile tissue covering
the inferior turbinated bones and lower portion of the septum, the
turbinated corpora cavernosa of Bigelow, he calls attention to its
great susceptibility to the action of irritants, whether applied
locally or to some remote portion of the body, citing as an example of
the latter the swelling, and sometimes almost complete closure, of the
nostrils supervening after exposure of the body to the action of a
current of cold air. In this situation the tissue is liable to become
hypertrophied, and in that state its susceptibility is greatly
increased. If, when in this condition, it is exposed to the action of
pollen, dust, or any other irritant, the substance produces a local
irritation which is reflected through the sympathetic nerves to other
parts of the respiratory tract; and it is to this reflected irritation
that Roe attributes most of the phenomena of hay fever. He regards it
as analogous to certain forms of laryngeal catarrh which, according to
the recent testimony of many distinguished laryngologists, are clearly
traceable to disease of the nasal cavity. Applying this theory to the
treatment of hay fever, he removed the hypertrophied tissue in five
cases, and in every instance succeeded in preventing a recurrence of
all symptoms of the disease. His operation consists in the removal of
the diseased tissue by means of Jarvis's wire écraseur and the
galvano-cautery, caustics having proved less effective. The wire snare
is best adapted for the removal of the tissue over the posterior
portion of the turbinated bone, where, owing to its being pedunculated,
it is readily caught in the wire loop. Over the anterior portion of the
turbinated bone, as well as over the septum, the growth is more
sessile, and is best destroyed by means of the galvano-cautery. To
avoid inflammatory reaction and to guard against other unpleasant
symptoms it is advisable to remove only a small portion of the growth
at a time. After each operation the part should be sprayed with warmed
vaseline to allay the irritation occasioned by the burning, and this
should be continued until the surface is sufficiently healed over to
admit of a repetition of the operation. The cauterization should be
repeated until every trace of the diseased tissue is removed.
21 The Pathology and Radical Cure of Hay Fever, New York,
1883.
Prior to the publication of Roe's article Harrison Allen had operated
successfully on two cases, the histories of which he has not as yet
published, but has kindly communicated by letter to the writer,
together with a description of his method of operating. This latter
differs but little from that of Roe, except as regards the time at
which the operation should be performed, Roe maintaining that the
operation should never be performed when the patient is suffering from
an attack of hay fever, while Allen considers this immaterial, and does
not hesitate to operate even when the symptoms are at their height. If
symptoms of hay fever recur after the operation, the nares should be
carefully examined, and if, as is usual in such cases, any
remnants of hypertrophied tissue be discovered, these should be at once
removed. The operation is not regarded as a very painful one, and a
patient of Allen's upon whom he had operated during an attack assures
me that he left the doctor's office feeling much better than when he
entered it. This is mentioned because hay-fever patients are
excessively nervous, and timidity on their part has hitherto prevented
many of them from availing themselves of this form of treatment.
It will be seen that, thus far, the operation has been performed in but
ten cases, but the results have been so uniformly successful as to
justify the belief that it is capable of relieving many cases of this
hitherto intractable disease. Whether this hypertrophied condition is
present in every case, as claimed by many, or in even the majority of
cases of hay fever, has not as yet been determined; and until further
observation shall have decided this question it will be impossible to
form an opinion in regard to the general application of this method of treatment.
DEFINITION.—Enlargement of the calibre of a bronchial tube or tubes,
whether confined to a limited portion of one tube, or reaching
throughout a great part of its extent, or involving several or many tubes.
SYNONYM.—Bronchiectasis, from [Greek: bronchos], a bronchial tube, and
[Greek: echtasis], an expansion.
HISTORY.—The change in the physical condition and size of a bronchial
tube, designated as bronchial dilatation, never occurs as a primary
affection, but is always the result of some preceding disease,
especially of chronic bronchitis or fibroid phthisis. The full
consideration of its pathological origin belongs, therefore, to the
natural history of those causative affections.
Later writers have in general followed Laennec's description of the
different varieties of bronchial dilatation; which, indeed, can hardly
be improved upon, for such was the accuracy of that great clinician and
pathologist as an observer that nothing was likely to escape him as
regards physical conditions, though he may sometimes have been in error
as to the theoretical explanation of what he saw. Previously to
Laennec's observations dilatation of the bronchial tubes was, as he
remarked himself, almost entirely overlooked both by pathologists and
practitioners. The reason of this is evident from the considerations
that a smaller tube when dilated would, except to the most careful
examination, closely resemble a larger tube of normal size, and that a
large dilatation might be mistaken by the ear at the bedside and by the
eye at the necropsy for a pulmonary vomica.
Two principal forms of bronchial dilatation are met with. In the first,
or diffused bronchial dilatation, known also as the cylindrical form,
the tube is uniformly enlarged in calibre, so that, whereas in the
normal state it would have admitted only a fine probe, in its enlarged
condition it may be of the size of a goosequill. In this state it may
be readily mistaken, when seen by itself, for a larger tube; but the
alteration is conspicuous when the tube is seen to be larger than the
branch from which it is given off. In the second or circumscribed form,
which is also termed sacculated dilatation, a pouch-like or fusiform
distension occurs in the continuity of a tube. In a third form, which
is far less common, several successive enlargements are met with in the
course of one tube, which thus presents a beaded appearance. It happens
at times that all of these different varieties of dilatation may be
encountered in the bronchial tubes of the same lung. The second, or
sacculated, form is the most common, especially in young persons.
ETIOLOGY.—In both of the more common forms of bronchial dilatation the
previous existence of bronchitis is to be regarded as the chief
causative agency, though other conditions may serve to increase the
dilatation when it has once been established. Laennec's observations
led him to connect the occurrence of bronchitis with the
production of dilatation of the bronchial tubes, though his explanation
of the mechanism of this production was erroneous, inasmuch as he
considered the accumulation of secretion in the affected tubes, and the
forcible inspiratory efforts made in coughing to dislodge this
accumulation, to be the direct causes of the enlargement. The part
played by bronchitis in producing dilatation is, however, less
immediate and mechanical than Laennec held it to be. It may, in a
general way, be considered the direct cause of the cylindrical and the
indirect cause of the saccular form of dilatation.
The long continuance of chronic bronchitis gives rise to weakness and
atony of the bronchial walls, so that they yield to the pressure
brought to bear upon them in the violent or protracted and repeated
respiratory efforts that are made in coughing. In such cases the tubes
which are themselves affected by the inflammatory process may yield
throughout a greater or less extent of their continuity, and thus the
cylindrical form of dilatation may be established. The same mechanism
may be supposed to give rise to the beaded variety of the disease if
the inflammatory action should be greater at several points along the
course of a tube, with intervals of tissue in a healthier or less
atonic state.
In the saccular form, on the other hand, the dilatation does not occur
in the portion of the tube which is chiefly affected with the
inflammatory process, but is the consequence of a local capillary
bronchitis involving the ultimate ramifications of the affected tube
and occasioning collapse of a portion of the lung. This collapse
operates in two ways in causing a pouch-like dilatation of an adjacent
bronchus—partly through the atmospheric pressure within the affected
tube, tending to fill the space created by the collapsed portion, and
partly by the traction of this collapsed lung-tissue outside of the tube.
In addition to the part played by bronchitis and atelectasis of the
lung in occasioning bronchial dilatation, another important factor in
its production is to be found in the condition described by Corrigan in
1838 as cirrhosis of the lung, and since recognized as interstitial
pneumonia or fibroid phthisis. In this affection there is formed around
the blood-vessels and terminal bronchi, as well as around the
air-vesicles, a hyperplasia of the connective tissue, which, as is the
case with connective-tissue formations in other situations, ultimately
contracts, obliterating the air-cells, smaller bronchi, and
blood-vessels, and thus converts the lung-tissue into a tough, fibrous
mass. By the contraction thus produced the bronchial tubes of a larger
size, which have been previously weakened by bronchitis and have lost
their elasticity, are subjected to traction on all sides, and thus
become dilated. Dilatations of all forms may thus be produced,
cylindrical, sacculated, or beaded, according to the amount of lung
involved in the contracting process and to the degree and situation of
the bronchitis which favors the dilating action.
The determining causes, then, of bronchial dilatation are—1st, chronic
bronchitis; 2d, atelectasis; and, 3d, fibroid phthisis or cirrhosis of
the lung.
SYMPTOMATOLOGY.—The general symptoms of bronchial dilatation, as well
as the course and duration of the affection, are such as belong to the
pulmonary diseases favoring its production, especially chronic
bronchitis and fibroid phthisis. The cough and dyspnoea of these
diseases are aggravated by bronchial dilatation; but these symptoms,
together with the impairment of nutrition, are due rather to the
underlying affections than to the mere fact of dilatation. Increased
and fetid expectoration, which often occurs in bronchial dilatation
from retained and altered secretion, is by no means characteristic of
this condition, since it may occur where no sign of dilatation exists.
There is generally some degree of dulness on percussion over a dilated
bronchial tube, due to the condensation of the lung-tissue
surrounding it, and varying in extent and degree with the amount of
that condensation, and also with the amount of secretion retained
within the tube. Sometimes, however, increased resonance of a
tympanitic character is observed, especially if the dilatation be of
the saccular form and near the surface of the lung. Such differences in
the percussion sound are analogous to what occurs over a pulmonary
vomica, which will generally give a dull sound, though, if the cavity
be superficial and thin-walled, it may yield a tympanitic resonance. On
auscultation bronchial respiration may be heard along the course of
tubes affected with cylindrical dilatation when they are free from
secretion; and this is more intense in proportion as the tube is more
dilated and the lung-tissue around it more condensed. Bronchophony and
increased vocal resonance also occur, and if mucus be present in the
dilated tubes coarse moist râles will be heard. In a saccular
dilatation there may be true amphoric breathing, with the gurgling
sounds heard in a vomica. In some cases there is an alteration in the
appearance of the chest-wall, which is retracted by the shrinking of
the condensed lung beneath.
Now, of the auscultatory signs that have been mentioned, the
bronchophony and increased vocal resonance, together with the
percussion dulness, belong also to pneumonia, which, however, at least
in its acute form, can be distinguished from bronchial dilatation by
the previous history, the febrile movement, and the general phenomena
of the case, and by the fact that the tubal breathing of pneumonia,
besides being less persistent, is most frequently met with in the lower
part of the lung, and that of bronchial dilatation in the upper part.
But the diagnosis between a dilated bronchus and pulmonary phthisis is
in some cases a very difficult problem, the signs of the cylindrical
form closely simulating those of the stage of deposit in phthisis,
because involving the same physical condition, and those of the
saccular variety corresponding often with the auscultatory signs of a
cavity. In the former case there may be the same localized dulness on
percussion, the same bronchial or broncho-vesicular breathing, and the
same sinking or contraction of the chest-wall apparent on inspection.
In the latter case there may be equally in saccular dilatation and in a
vomica amphoric breathing, gurgling, and pectoriloquy. In the
establishment of the diagnosis between these two conditions Austin
Flint, Sr.,1 justly attaches importance to the circumstance that
there is in general a greater degree of percussion dulness over a
cavity than over a dilated bronchus, so that a relatively greater
prominence of the auscultatory signs as compared with the degree of
dulness makes the diagnosis of dilatation more probable. But the most
important evidence on the point is to be gotten from the history of the
case. If in a case where the auscultatory signs would leave the
examiner in doubt there were found loss of flesh, fever, night-sweats,
quickened pulse, and the other general phenomena belonging to phthisis,
the existence of this affection would be rendered probable in the
highest degree, and the auscultatory signs should be taken as
corroborating an opinion founded on the general symptoms.
1 Dis. of Resp. Organs, p. 353.
Positive evidence, again, may be furnished by a microscopic examination
of the sputa; the discovery of particles of lung-tissue or the
so-called bacillus tuberculosis pointing clearly to phthisis.
Conversely, the absence of the general symptoms of phthisis would, in a
case presenting the above auscultatory signs, render it probable that
they are due to bronchial dilatation. Long-continued cough and abundant
expectoration are the chief symptoms common in both forms of disease.
There are, however, some cases in which even with the most careful
examination and weighing of evidence the physician will be left in
doubt, inasmuch as in some cases of otherwise
well-marked
phthisis the usual constitutional symptoms are absent or imperfectly
declared. In such exceptional cases the estimate of probabilities is to
be based on the fact that while bronchial dilatation is comparatively
rare, pulmonary phthisis is extremely common.
PATHOLOGY AND MORBID ANATOMY.—Enlargement of the bronchi may be met
with throughout almost the entire extent of a lung; when limited to a
part of the organ the change most frequently occurs, according to
Laennec, Rokitansky, and other observers, in the superior lobe and
toward the anterior border. The tubes of the third or fourth order in
respect to size are most frequently affected, the primary bronchi being
never involved except in association with tracheal dilatation.
In the different forms of dilatation the bronchial walls are found in
various states. In the cylindrical variety they are for the most part
thickened and hypertrophied, both as to the mucous and the fibrous
coats; the mucous membrane being in a catarrhal state, covered often
with muco-purulent discharge, and easily broken down and detached,
while underneath the white fibrous coat is sensibly thickened.
In the sacculated form, on the other hand, the bronchial wall generally
presents a thin and atrophied appearance, the mucous membrane
undergoing but little change, except that the stretching to which it
has been subjected gives it a smooth and shining look. This difference
in the degree of thickening of the bronchial walls in the two forms of
dilatation is in part due to the fact that in the saccular variety the
enlargement in calibre is far greater than it is in the cylindrical
form for a corresponding extent of a tube, so that its wall is much
more stretched and attenuated, and thus the tendency to hypertrophy
which has play in the cylindrical form is more than overcome in the
saccular. But the chief reason of the difference in the state of the
walls in the two forms of dilatation is found in the different modes in
which they are respectively brought about, as already described.
DIAGNOSIS.—It has been shown that the determination of the existence
of bronchial dilatation is at times one of the most difficult problems
in diagnosis, from the fact that the auscultatory signs belonging to it
may be equally met with in other affections, especially in pulmonary
phthisis. The diagnosis is to be established, when this is possible,
only by a careful consideration of the physical signs in connection
with the general symptoms, so that the sources of doubt arising from
the one set of phenomena may be as far as possible corrected by the
other. These signs and symptoms, and the various affections to be
discriminated by them, have been sufficiently set forth under the head
of Symptomatology. While in this way a clear conclusion may be reached
in many cases, yet there are others in which, notwithstanding the
utmost care, there may still be a doubt as to whether the symptoms and
signs indicate a dilated tube or a pulmonary cavity.
PROGNOSIS.—The prognosis of bronchial dilatation is directly connected
with that of the affections which chiefly give rise to it—viz. chronic
bronchitis and fibroid phthisis. When chronic bronchitis has lasted
long enough to cause dilatation, it is seldom if ever cured, and,
though improvement may take place from time to time in its symptoms,
yet the dilated bronchi can hardly undergo diminution in their size.
And in fibroid phthisis, while the progress of the disease is often
very slow, yet it is on a downward grade, and the connective-tissue
contraction giving rise to the dilatation increases with the advance of
the malady.
TREATMENT.—The treatment of cases of bronchial dilatation resolves
itself in great degree into that of the underlying and causal diseases
on which it depends. As regards methods specially directed to the areas
of dilatation, they consist of alterative, astringent, stimulant, and
antiseptic remedies, either administered by the stomach or used by the
process of inhalation. Cough may be allayed with the syrup of
lettuce containing in each dose from
1/8th to ¼th of a
grain of sulphate of codeia or 10 or 12 drops of the spirit of
chloroform. If expectoration is very profuse, sulphate of atropia, in
the dose of
1/100th to
1/80th of a grain, or the extract
or tincture of belladonna, may be used. Turpentine and eucalyptol have
a controlling influence over this symptom, and are specially beneficial
if the bronchial secretion is fetid. They may be given by the mouth in
the dose of minim v–xx in emulsion, and applied also by inhalation of
their vapor or by spray. Inhalations of solutions of carbolic acid,
minim j–x to an ounce of water, are more effective than anything else
in checking fetor of the expectoration and the breath. This agent may
also be administered by the mouth in the dose of fluidrachm j–iv of a 1
per cent. solution.
DEFINITION.—The term emphysema is derived from [Greek: emphysaô], to
inflate, and signifies an increased amount of air in a part or the
whole of one or both lungs. Accordingly as the situation of this excess
of air is (a) in the air-vesicles or (b) in the connective tissue
between the lobules, emphysema is divided into Vesicular emphysema and
Interlobular or extra-vesicular emphysema.
HISTORY.—These two affections are different pathologically and
anatomically, vesicular emphysema being a much more common and
important affection than the interlobular form. The distinction between
the two forms was first drawn by Laennec. Previously to his time the
essential difference between them was unknown; and, as the accurate
diagnosis of the disease can be made only by auscultation, its
existence was no doubt very often entirely overlooked. It has been
remarked by Rokitansky1 that "had Laennec done nothing else for
medical science, his discovery of this diseased condition, and of the
causes giving rise to it, would have sufficed to render his name immortal."
1 Path. Anat., vol. iv. p. 53, Am. ed.
Vesicular emphysema may be defined as an absolute or relative increase
in the amount of air contained in the vesicles of a part or the whole
of one or both lungs. As a substantive disease it occurs in two
principal forms—hypertrophic and atrophic; but besides these it is met
with as a secondary affection due to other diseases and limited to
certain areas of the lungs, sometimes acute and sometimes chronic in
its production and duration. It will therefore be best to consider the
disease under the following different forms:
1st. Acute lobular emphysema;
2d. Chronic lobular emphysema;
3d. Hypertrophic lobar emphysema;
4th. Atrophic lobar emphysema.
1. Acute Lobular Emphysema.
This form of the disease is the result of the rapid distension beyond
their natural size of air-vesicles which had previously been healthy.
It is most frequently met with in children and as the consequence of
bronchitis or
whooping cough. The paroxysms of cough occurring in
these affections, especially in the latter, are attended by deep
inspirations, by which the vesicles are directly distended, and by
violent expiratory efforts, with closure of the glottis, so that the
air is forced into those portions of the lungs where there is least
resistance, particularly at the apex and along the margins. In a large
proportion of cases of acute lobular emphysema, when the distending
cause is removed by the cessation of the cough, the vesicles return to
their normal size through their natural elasticity, which has not been
destroyed. But in some cases, when the cough has been of unusual
violence or of very long duration, the change may be permanent through
loss of this elasticity, and thus a form of chronic lobular emphysema
is produced.
SYMPTOMS AND SIGNS.—Unless emphysema of this form is extensive and
extreme in degree, it is not attended with symptoms additional to those
of the affections giving rise to it. When very great it may occasion
increased percussion resonance.
TREATMENT.—The treatment is only what is required by the causal
affections.
2. Chronic Lobular Emphysema.
In many cases emphysema is confined to a limited number of lobules,
especially at the apices, the anterior borders, or about the base of
the lung; and being gradual in development and permanent in duration,
it is then termed chronic lobular emphysema. This is the form
frequently met with in the different varieties of pulmonary phthisis,
in which its development seems supplementary to the incapacitation of
other portions of the lung. The lobules nearest to the surface of the
lung or immediately beneath the pleura are found to be most distended,
so that they often project beyond the adjacent surface.
Chronic lobular emphysema is chiefly of interest in connection with the
other pulmonary diseases which give rise to it. The mechanism of its
production is like that of acute lobular emphysema, but the diseases
occasioning it being chronic the emphysema to which they give rise is
equally permanent. At the apex of the lung, its most common situation,
it is very often associated with tubercle in a calcareous state. The
changes accompanying this deposit of tubercle favor the loss of
elasticity in the vesicles of the apex, and the violent expiratory
efforts, with closure of the glottis, occurring in the attacks of cough
to which phthisical patients are subject, force the air into this part
especially, and also into other regions of less resistance, and thus
occasion permanent distension of the vesicles.
SYMPTOMS AND SIGNS.—The signs of this form of emphysema are so often
masked by those proper to phthisis that the detection of the former is
difficult or impossible. This, however, is of no practical importance
in respect to treatment. At times the distension of the vesicles at the
apex is so great as to produce bulging in the supra-clavicular region
and to overcome the dulness due to deposit by the resonance it occasions.
TREATMENT.—No special treatment beyond that of the causative
affections is required.
3. Hypertrophic Lobar Emphysema.
This is a substantive affection, and is much the most important form of
the disease, both in its origin and development and in the consequences
to which it leads. Though sometimes limited to one lung, or even to a
single lobe of
one lung, yet it more commonly involves the
greater part of both lungs, which are increased in size, as shown by
the alteration of the contour of the chest during life and by the
appearance of the organs after death. This enlargement of a lobe or of
a whole lung is of course the aggregate of the increase in size of the
individual vesicles, the changes in which form the pathological units
of the disease.
ETIOLOGY.—In no disease is the study of etiology as throwing light on
treatment, both medicinal and hygienic, of more value than in
emphysema, the important question being as to whether it takes its
origin from some immediate mechanical cause acting upon the healthy
cell-walls, and thus distending them, or whether they suffer such
distension only when they have been previously weakened by some
degenerative process in their tissue. The importance of determining
this point correctly with reference to treatment is obvious.
In partial and lobular emphysema the change may have been wrought by
causes mechanical in their nature and directed specially to the
affected parts, such as have been already referred to; but in the
general diffused or lobar form of the disease, in which by degrees the
greater part or the whole of a lung is involved, we are almost
compelled to assume the existence of some degenerative process or
tendency coextensive with the malady and determining its existence.
That any one form of degeneration is present in all cases has never
been proved; indeed, it may be said to have been disproved. Rainey's
view, that the change in the air-cells is essentially dependent on
fatty degeneration of their walls, was based mainly on observations
made upon a single case, and, although favored by the eminent authority
of C. J. B. Williams, it has not been substantiated. The same thing
must be said of Sir William Jenner's teaching, that fibroid
degeneration is the essential lesion. Though both fibroid and fatty
changes are found in not a few cases, yet in others a careful
examination has failed to detect either the one or the other of them,
so that neither can be regarded as the essential condition explaining
all cases. Nevertheless, it is probable in the highest degree that a
degenerative change of some kind, due to imperfect or perverted
nutrition of the cell-walls, always exists in general lobar emphysema,
though its nature may sometimes elude observation.
In cases of well-marked emphysema there may be no discoverable
morphological changes in the walls of the alveoli, though, as remarked
by Hertz,2 "a tissue-relaxation may be present in the lung without
our being able to recognize any corresponding microscopic abnormality."
2 Ziemssen's Cyclop., vol. v. p. 373.
It may be said, then, that while in partial or local emphysema the
alteration in the air-vesicles may be effected by extraordinary efforts
brought to bear upon healthy cell-walls, in general or lobar emphysema,
on the other hand, it may be produced by ordinary efforts acting upon
weakened and diseased cell-walls. The morbid change is probably not in
all cases alike, being sometimes fatty, sometimes fibroid,
degeneration, and in other cases of a kind not ascertained.
In addition to other considerations, the markedly hereditary nature of
emphysema in not a few instances would of itself render the existence
of some constitutional predisposing cause highly probable. On this
point A. T. H. Waters3 quotes the observations of Greenhow and
Jackson. Out of 42 cases collected by Greenhow, 23 showed an hereditary
tendency, and in 28 reported by Jackson, 18 were of emphysematous
parentage. In stating his belief that substantive or general emphysema
is the result of some degenerative process, Waters bases it on the
following considerations: 1st. The high degree of development which the
disease often reaches, without any previous history of violent or
long-standing cough, in connection with either bronchitis, whooping
cough, or any similar affection. 2d. The frequency with which the
disease attacks the whole of both lungs, and the uniform character of
the morbid changes often observed throughout all parts of the lungs.
3d. The hereditary nature of the disease, as shown by observations.
4th. The manner in which the disease is influenced by certain remedial
measures which are known to act beneficially on other diseases attended
with degeneration of tissue.
3 Diseases of the Chest, pp. 122, 123.
As to the nature of the immediate exciting cause of emphysema, whether
in the general or local form, different views have been maintained. The
most important of these are the inspiratory and expiratory theories.
The former of these theories, that in accordance with which the disease
is referred to inspiratory action, was maintained by Laennec, and under
the influence of his authority was at one time generally accepted. In
accordance with this view, the existence of bronchitis is an important
factor in the production of emphysema, as undoubtedly it often is in
the lobular form. The dilatation of the air-vesicles was attributed to
their over-distension by inspiratory efforts allowing the free entrance
of air, the escape of which was impeded by bronchial mucus. Inspiration
was thus regarded as a more powerful act than expiration, which was
considered too feeble to drive the air beyond the accumulated mucus. In
this way the air was supposed to accumulate in gradually increasing
amount within the cells, which thus became distended.
But in opposition to this view it has been shown by Hutchinson's
researches that Laennec was wrong in supposing inspiratory power to be
greater than that of expiration; and it is further opposed by the
researches of Mendelssohn and Traube, and those of Gairdner, which have
shown conclusively that the presence of a pledget of mucus in a
bronchial tube, so far from causing distension of the air-vesicles to
which it leads, must ultimately ensure their collapse. The collapse
thus occasioned, which is most common in the lower parts of the lungs,
may lead, partly perhaps through inspiratory pressure, to vicarious
emphysema in the upper portions, which receive a relatively larger
quantity of air, in accordance with Williams' theory of negative
inspiratory pressure.
It is true, then, as maintained by Laennec, that bronchitis may
occasion emphysema, but the emphysema does not occur in the vesicles to
which the affected tubes directly lead, nor from the force of
inspiration applied to these vesicles, as Laennec taught, but in other
portions of the lungs.
The expiratory theory affords a more satisfactory explanation of
emphysema than does the inspiratory theory, and one more completely in
accordance with the physiology of respiration and the anatomy of the thorax.
In ordinary expiration, in which the lungs are uniformly and equably
compressed by the chest-walls, there is nothing tending to force air
into one part of these organs more than into another, and thus produce
emphysematous dilatation. But in forced expiration, such as occurs in
the act of coughing, it may be plainly seen, if the chest be uncovered,
that the air is driven upward to the top of the lungs, so as to produce
a perceptible bulging in the supra-clavicular region. This bulging is
notably increased in the coughing-spells of emphysematous subjects; and
this fact is urged by Sir William Jenner both as throwing light upon
the expiratory act as a principal factor in the disease, and as
accounting for the special frequency of emphysema in the upper parts of
the lungs. The explanation of this phenomenon is found in the
circumstance that in the strong expiratory efforts of coughing the
abdominal muscles force the diaphragm upward, and thus compress the
lungs from below; at the same time the strong lateral anterior and
posterior thoracic walls resist pressure, while the superior part of
the thorax, covered over with fascia, but not completely
protected by a bony structure, offers least resistance. To this
unprotected part of the lungs and to the free margins and borders,
which contain normally the smallest amount of air, will the strong
currents produced by violent expiratory efforts be driven, so as to
cause distension of their vesicles. Thus, the frequent coughing-spells
of bronchial catarrh, so commonly associated with emphysema, give rise
to the expiratory efforts which are the immediate cause of the emphysema.
While, therefore, it is probable that in some cases and to a certain
degree inspiration may have a share in occasioning emphysema, yet
expiration is to be regarded as a more important and more frequent
factor in its production. This, at least, is probably the case in
partial and lobular emphysema, and in some instances of the lobar form
where the disease gradually spreads throughout a lobe. But in
rapidly-diffused and extensive lobar emphysema such an explanation
cannot always be admitted, because sometimes the disease advances
steadily, so as to involve the greater part of one or both lungs
without the occurrence of any paroxysms of cough which could distend
the air-cells by their violent expiratory efforts. In such cases the
only distending force would seem to be that of ordinary inspiration,
which, while it might have no effect upon healthy lung-tissue, may
easily be supposed to exercise sufficient dilating power upon
air-cells, the walls of which are in a state of degeneration, and, thus
being unnaturally weak, yield to pressure.
SYMPTOMS AND SIGNS.—One of the earliest symptoms of emphysema is
shortness of breath; and, though at first it may not be very marked,
yet as the disease advances it becomes more and more urgent, especially
on going up stairs or walking up hill. Distension of the stomach by a
full meal is likely to induce it, and even a slight degree of bronchial
catarrh may render it extremely distressing. This symptom is due
chiefly to two causes: First, the obliteration of numerous capillaries
in the pulmonary system, occasioned by the thinning and destruction of
the cell-wells in which they ramify, interferes with oxygenation, so
that an increased number of inspiratory acts is required to supply the
deficiency, and thus respiration is hurried; and, secondly, the
impairment of the natural elasticity of the air-vesicles prevents the
expulsion of their contents; the residual air remains, therefore,
unchanged, and cannot supply oxygen to the blood; and thus increased
expiratory efforts are made in order to expel the stagnant air and
obtain a fresh supply. Notwithstanding this increase of both
inspiratory and expiratory action, the movements of the chest are but
slight. As far as bronchial catarrh is a cause of dyspnoea in
emphysematous patients, improvement may take place in the warm dry
weather of summer, when this symptom is often much mitigated.
Cough is a very constant symptom, varying in degree with the extent of
bronchial catarrh. The act of coughing is feeble and expectoration is
effected with difficulty—so much so that sometimes the retained
secretion threatens suffocation.
Asthma occurs in paroxysms, and as a distinct phenomenon from the
dyspnoea which is more or less constant. The asthmatic seizures often
come on in the night after the patient has been asleep; they are
characterized by orthopnoea and constriction in the chest, and
generally subside with free expectoration.
The physical signs of emphysema are highly characteristic and of great
importance. On inspection a peculiar conformation of the chest is
observed when the emphysema has lasted for some time, the departure
from the normal form gradually increasing in the progress of the
disease until, in advanced cases, a degree of deformity is produced
which is strikingly characteristic. In the earlier stages, or if the
emphysema is local and partial, the alteration in the chest-wall
consists only of a prominence corresponding with the dilated
portion of the lung. But when the disease is general and occupies a
considerable portion of both lungs, a rounded, convex, or barrel-like
form of the thorax is produced, most noticeable in the upper part, and
due to increased prominence of the ribs. The thoracic portion of the
spine becomes more curved, and thus throws the shoulders forward,
producing a stooping attitude. The intercostal spaces at the upper part
of the chest are frequently effaced by the pressure of the enlarged
lung, while at the lower part the depression of these spaces may be
increased, especially during inspiration, by the action of the
diaphragm. The enlargement of the thorax as a whole is chiefly due to
the changes in its upper part, the lower part appearing sometimes by
contrast to have lessened in volume. This, however, is in most cases
apparent rather than real; but in some instances the dimensions in the
lower part of the chest are actually lessened.
The respiratory movements in well-marked emphysema are characteristic
and peculiar. The dilatation of the chest which is sought to be
accomplished by muscular action is small and disproportioned to the
amount of effort put forth, notwithstanding that the need for air keeps
the sterno-mastoid and scaleni muscles in constant action. The reason
of this is that, the lungs being distended nearly to their utmost
capacity, there is but little room for further expansion. As there is
only slight enlargement on inspiration, so with expiration the walls of
the thorax contract but little at their upper part.
The result, therefore, of their muscular efforts is that the ribs are
lifted and the sternum carried forward, so that the whole chest rises
and falls in respiration as if its walls formed a solid case. But the
character of respiration is by no means the same in all cases of
emphysema. More than forty years ago Stokes4 called attention to the
different modes of breathing in different cases accordingly as there is
or is not displacement of the diaphragm; and his observations have more
recently been reaffirmed by Waters5 and others. In the one class of
cases the diaphragm retains its normal position and the upper part of
the chest is very prominent, probably because the disease is chiefly in
the upper portion of the lungs. Here there is but little descending
movement of the diaphragm in inspiration and the abdomen remains flat.
In the other class the diaphragm has been displaced and pushed downward
by the enlarged lungs, which have probably been involved in the disease
throughout their whole extent. In these cases the abdomen is protruded
more or less with every inspiration. The difference between the two
types of breathing is important, as in the latter class of cases there
is more advanced and extensive disease than in the former, the symptoms
being more urgent, and especially the dyspnoea greater. Inspection of
the chest shows that the movement of inspiration is more quickly
accomplished than that of expiration, which is prolonged, labored, and
often wheezing in character.
4 Diseases of Chest, 2d ed., p. 173.
5 Diseases of Chest, p. 140.
Percussion and auscultation furnish signs of the utmost importance for
determining the existence of emphysema which are in direct accordance
with the physical conditions giving rise to them.
Increased resonance on percussion is observable over all portions of
the lungs when the disease is general, but it is most marked at the
upper part and along the anterior borders. When the disease is partial,
the increased resonance is limited to the portions of the chest-wall
over the affected areas. This sign is of course due to the greater
amount of air in the distended vesicles. In very marked cases the
resonance sometimes loses the vesicular and approaches the tympanitic
character. There is very little, if any, further increase of the
resonance on full inspiration. This is unlike what occurs in health,
and is due to the fact that the capacity of the distended lungs is not
relatively increased in emphysema, as it is in health, by the act of inspiration.
Over the cardiac region the normal dulness on percussion is
lessened or entirely superseded by resonance from the overlapping of
the heart by the distended lung. In partial emphysema the heart may
escape this encroachment and its area of dulness may not be lessened;
and even in some rare cases where the disease is general and far
advanced the same thing may be observed, from the lung being bound by
pleuritic adhesions, so that it cannot expand in the direction over the
heart. But, as a very general rule, it will be found in hypertrophic
emphysema that the normal præcordial dulness is lessened or absent.
When this is observed the heart is in some cases forced downward, its
beat being felt most distinctly in the epigastrium; and in other cases
it is carried directly backward, so that its impulse can hardly be
detected at all.
Over the posterior wall of the chest percussion gives a clear note at a
lower level than in health, because the dilated lung extends farther
down toward the bottom of the thorax.
The signs afforded by auscultation are highly characteristic of
emphysema, and, like those of percussion, in direct relation with the
physical condition of the lungs. The respiratory sounds are notably
feebler, because the amount of air entering and leaving the lungs at
each act of respiration is less than in health. The distended lungs can
admit only a small amount of air at each inspiration, and from their
diminished elasticity they can expel but a small amount at each
expiration. This feebleness is directly proportioned to the degree of
the disease, or, in other words, to the amount of distension; for the
greater the distension, the less movement of the lungs and the less
play of air. If the disease be unequally advanced on the two sides of
the chest, the respiratory murmur will correspondingly vary, being
feebler on the side where the disease is most advanced.
Besides this change in intensity, there is also an alteration in the
rhythm of the respiratory acts corresponding to what has been referred
to above as observable on inspecting the chest. The ratio of
inspiration and expiration is always changed in well-marked
emphysema—so much so as to be in many instances reversed, the
expiratory occupying more than double the time of the inspiratory act.
Inspiration is short and quick, because the air enters freely and the
limit of the possible expansion of the lungs is speedily reached.
Expiration is prolonged, because there is a loss of their normal
elasticity, and an effort is made by voluntary action of the expiratory
muscles to expel the stagnant residual air. This alteration in rhythm
is eminently characteristic of emphysema when the disease is far
advanced and occupies a considerable portion of the lungs. Feebleness
of respiratory murmur is an earlier sign than alteration in rhythm, and
may be observed before any marked prolongation of the expiratory act
occurs and before there is any very positive increase of resonance on
percussion. Hence it is of great importance if not otherwise
explicable, as it sometimes is by unusual thickness of the chest-walls,
because it indicates, taken by itself, an early stage of emphysema in
which treatment may be most likely to be beneficial. It is sometimes
found in very advanced stages of emphysema that the respiratory sounds
are almost totally inaudible; but in general, while both murmurs are
feeble, expiration is more appreciable than inspiration. If, however,
the disease is associated with bronchitis, either constantly or
intermittingly, the proper auscultatory signs of the accompanying
affection may be observed, though modified by the emphysema. Thus,
moist and dry râles according to the stage of the bronchitis, sibilant
or sonorous, subcrepitant or mucous râles according to the size of the
bronchial tube involved, may be heard, the abnormal sounds being
notably prolonged during expiration.
It can hardly be doubted that the sign referred to by Laennec as
"perfectly pathognomonic of emphysema," and described by him as "the
dry
crepitant râle with large bubbles" (râle crépitant sec à
grosses bulles), is in most cases, if not always, dependent upon
coexistent bronchitis. Certainly, many cases of emphysema are met with
in which, in the absence of bronchitis, no such sound is heard. The
signs or combination of signs which are indeed "perfectly pathognomonic
of emphysema" are increased resonance upon percussion, associated with
marked feebleness of respiration and prolonged expiration. This
association of signs is always indicative of emphysema, because it can
be explained only by the physical conditions involved in this disease.
Auscultation of the cardiac region gives results corresponding with
those afforded by percussion and palpation. When the lung is distended
sufficiently to overlap the heart, the sounds belonging to the latter
organ will be more or less indistinct and distant, and sometimes
scarcely audible. If the heart be pushed to the right or downward
instead of being driven backward, the sounds may still be distinct, but
they are out of place and have their greatest intensity under the
sternum or at the epigastrium. The proper signs of hypertrophy or
dilatation of the heart, which may be revealed on post-mortem
examination, and the mechanism of which will be referred to farther on,
are to a great degree masked during life; for the overlapping lung
prevents the detection of increased cardiac dulness by percussion or
increased impulse by auscultation.
Palpation of the chest serves to confirm the evidence supplied by
inspection. The effacement of the intercostal spaces, the lessened
mobility of the ribs, and the situation of the apex-beat of the heart
are signs of importance of which the sense of touch takes cognizance.
COMPLICATIONS AND SEQUELÆ.—Bronchitis is one of the most frequent of
the affections complicating emphysema. In the partial form of the
malady it often sustains, as has been already seen, a direct causal
relation to the emphysema. When the disease is diffused and general,
bronchitis is sooner or later almost always encountered, and is then of
a congestive rather than an inflammatory type, being often
unaccompanied by fever, and in part due to interference with the
circulation through the smaller bronchial arteries. For, as some
branches of these vessels are distributed in the interlobular areolar
tissue, and others ramify upon the walls of the smallest bronchial
tubes, a constant pressure may be made upon them by the dilated
air-vesicles, and this obstruction of the circulation through them may
occasion passive congestion. The bronchitis accompanying advanced
emphysema is generally attended with free secretion, amounting in some
cases to a bronchorrhoea so profuse as seriously to imperil life by
suffocation, the danger being increased by the difficulty in
expectorating that exists. The discharge from the bronchi is often in
such cases of a muco-purulent character. So urgent is the danger
sometimes arising from this complication that unless it be relieved
death may quickly ensue. The face and other portions of the surface
become livid or leaden, the whole body more or less cool, the pulse
weak and hurried, and copious râles are audible even without applying
the ear to the chest. Life is threatened both by the accumulation in
the respiratory passages obstructing the entrance of air, and by the
tendency to the formation of heart-clots from the embarrassment to the
pulmonary circulation and the consequent malaëration of the blood.
Another very common complication of emphysema is asthma, which, indeed,
is sure to occur in greater or less degree of violence and at longer or
shorter intervals in all cases where the disease has become extensive.
The attacks often come on in the night, arousing the patient from
sleep. The tendency to a nocturnal occurrence of asthma may be due to
the recumbent position favoring passive congestion of the lungs, and to
the diminished activity of the respiratory process during sleep when it
is not aided by
voluntary effort. From both these causes an
irritation may be set up determining reflex spasm of the bronchi.
Moreover, the paroxysmal occurrence of asthmatic attacks is an
illustration of the general law in accordance with which morbid
neurotic conditions frequently occur intermittingly, though the
eccentric cause of them is constantly existing, as witnessed in the
subjects of epilepsy or angina pectoris. The frequent recurrence of
these attacks of spasmodic asthma is in all probability the cause of
the hypertrophic state of the muscular tissue in the bronchial tubes
which is often met with as a part of the morbid anatomy of emphysema.
The structural alterations of the heart that occur in emphysema are the
results, more or less directly, of the mechanical conditions involved
in the disease. Earliest in the sequence of changes affecting this
organ are non-compensative hypertrophy and dilatation of its right
chambers; and by some writers it has been maintained that the
alterations due to emphysema are found only on this side of the organ.
This, however, has been completely disproved by extended observations,
and it has been shown that left hypertrophy and dilatation, while not
such direct consequences of emphysema as the corresponding changes on
the right side, are yet frequently encountered, and are plainly due to
the disease in the lungs.
The hypertrophy and dilatation of the right chambers of the heart are
easily understood when it is considered that the constant pressure of
the enlarged air-vesicles of the emphysematous lungs interferes more
and more with the circulation through the pulmonary capillaries, and
that there is thus a constant impediment to the onward course of the
blood from the pulmonary artery, and a continuous backward pressure
within the right ventricle and auricle. The effort to overcome this
pressure leads to hypertrophy, and ultimately, as this effort is less
and less effective, to dilatation of the right chambers.
It would appear as though the readiness with which the alterations on
the right side of the heart may be explained has led, if not to their
being more frequently observed, yet at any rate to their being more
emphasized, than are the corresponding changes on the left side. Some
writers have referred only to those on the right side, giving the
correct explanation of them, but making no mention of the similar
condition on the other side. Thus, Rokitansky6 refers to the
obstruction to the circulation occasioned by the expansion of the
air-cells in pulmonary emphysema as one of the causes of dilatation of
the right ventricle and auricle, but says nothing of similar changes on
the left side. Other pathologists, however, as Lebert and Gairdner,
have shown that at least in long-standing emphysema the left side is
also not infrequently involved in disease.
6 Path. Anat., vol. iv. p. 130.
What explanation, then, is to be given of those changes in the left
chambers which, if less frequent than hypertrophy and dilatation on the
right side, are yet certainly not uncommon? Evidently, they cannot be
referred to obstruction in the pulmonary circulation; for this, while
producing backward pressure into the right compartments, must, on the
contrary, lessen the amount of blood received by the left chambers,
which therefore have no excessive labor thrown upon them from this
cause, and so cannot become hypertrophied in such a manner.
The explanation is probably to be found partly, as suggested by
Waters,7 in the altered position of the heart occasioned by the
emphysema, and partly in the remora of the venous circulation.
7 Diseases of the Chest, p. 152.
There are thus two factors to be considered, the first of which applies
to the right heart as well as to the left. As to this first, the more
extensive the emphysema the greater is the degree of displacement that
the heart
undergoes; and as the normal position of the ventricles
with reference to the arteries emanating from them offers the easiest
course to the blood-currents, any departure from this position causes
an embarrassment, and consequently increased labor, in the left
chambers as well as the right; hence one explanation of the hypertrophy
on both sides. As to the second factor, the obstruction to the general
capillary circulation necessitates an increased effort of the left
ventricle to overcome it; and so, as far as it is concerned, another
cause of hypertrophy is in operation.
It is frequently observed in advanced emphysema that there is a marked
disproportion between the forcible heart-beat and the feeble radial
pulse, the former being due to the hypertrophy, and the latter to the
small amount of blood received and propelled by the heart.
Besides these changes in the size of the heart and the thickness of its
walls, constituting hypertrophy or dilatation as the case may be, a
displacement of the entire organ is a not uncommon consequence of
emphysema. The direction of this displacement may vary, so that it may
be either directly backward, the heart being overlapped by the
distended lung, or it may be downward or to the right of the sternum. A
much greater degree of displacement of the heart may result from the
pressure of pleural effusion than from emphysema of the lung; but when
due to pleurisy it is generally of shorter duration and admits of
perfect restoration, whereas when caused by emphysema it is usually
permanent. The writer has at present under his care a case of extreme
displacement of the heart to the right, the apex-beat being felt and
seen to the right of the sternum; but in this patient, while extensive
supplementary emphysema of the left lung, due to the almost complete
incapacitation of the right lung, has probably had a share in causing
the displacement, yet a more important cause of it has been contraction
of the right side of the chest, the result of absorption of an old
pleural effusion which has left the lung bound back and adherent. This
case closely resembles one reported by Stokes as presenting "the
singular phenomenon of the displacement of the heart to the right side,
consequent on the removal of an effusion of the right side."8
8 Diseases of the Chest, p. 467.
Dropsy is to be regarded as one of the most notable complications and
consequences of emphysema; for when the disease is of long standing the
loss of balance between the arterial and venous circulation occasioned
by the obstruction to the passage of blood through the lungs gives rise
ultimately to effusion of the serum, which is first seen in the lower
extremities, and may subsequently become general.
In consequence of the disturbances in the circulation and respiration
which have been considered, it is not surprising that the nutritive
function should be impaired, as is found often to be the case in the
subjects of old emphysema, who present a cachectic and anæmic
appearance, partly due to malaëration of the blood, and partly to
imperfect performance of the assimilative functions occasioned by
passive congestion of the alimentary tract. Still another cause may be
found, as suggested by Hertz,9 in the insufficient supply of the
elements received from the lymph through the imperfect emptying of the
thoracic duct into the distended left subclavian vein.
9 Ziemssen's Cyclop., vol. v. p. 382.
There has been much discussion as to the connection between emphysema
and pulmonary phthisis, some pathologists having held that the two
affections are incompatible with each other, and that emphysema may
thus exercise a prophylactic influence against phthisis. Careful and
extensive observations furnish no valid grounds for such a belief. So
far as supplementary emphysema is concerned, it is a common thing to
find emphysematous patches at the bases and along the margins of lungs
the apices of which are tuberculous. In such cases the increased
inspiratory labor thrown upon some portions of the
lungs in
consequence of impaired function of other parts accounts for the
emphysema. But, besides this common condition, cases are met with in
which the emphysematous portions are themselves beset with tubercle.
Such a case is reported by Waters,10 in which an emphysematous lung
was found studded with tuberculous matter, which on microscopic
examination was seen in the air-sacs and ultimate bronchial tubes.
10 Diseases of the Chest, p. 156.
While emphysema ensures no absolute immunity from tuberculous diseases
of the lungs, yet the physical condition involved in it does lessen the
liability to tuberculous deposit, which is favored by active hyperæmia,
and active hyperæmia is not apt to occur in an emphysematous part of a
lung. It likewise lessens the liability to such pulmonary affections as
hæmoptysis, oedema, and perhaps pneumonia. The diminished pulmonary
circulation occasioned by the shrinking and obliteration of the
capillaries explains the infrequency of hæmoptysis. The same cause,
together with the smaller amount of interlobular areolar tissue that
the emphysematous lung contains, lessens the liability to oedema,
because there are both less blood from which the serum can be effused
and less of the tissue in which it can be collected and held. And the
infrequency of pneumonia in an emphysematous lung is owing to the
absence of conditions favoring hyperæmic changes.
DURATION AND TERMINATIONS.—No definite limit can be assigned to the
duration of emphysema, as the progress of the disease varies very much
in different persons according to the underlying cause, and according
also to the care taken in avoiding those influences which promote its
development, such as physical exertion or exposure to cold and damp.
Many persons with extensive emphysema, if they can secure favorable
climatic conditions, and thus escape attacks of bronchial catarrh, will
live on for years in comparative comfort, whereas in others the disease
may advance with rapidity to a fatal issue if their situation in life
necessitates hard work or exposure to causes that induce frequent
attacks of bronchitis. The immediate cause of a fatal termination is
generally either apnoea resulting from extensive bronchitis, or
asthenia from impaired action of the heart, or both of these conditions together.
PATHOLOGY AND MORBID ANATOMY.—From examinations made at various stages
of the disease in those who have died of emphysema it is seen that the
earliest change is a dilatation of the air-sacs, which become gradually
more distended, their walls growing thinner, until they may yield at
some points and perforations occur. As the disease advances the
perforations become larger and more numerous, until the walls are so
far destroyed that several sacs or even lobules are blended together,
forming only one cavity. The alveoli may be dilated to the size of a
mustard-seed, or even a pea, without undergoing rupture, and may thus
become visible by the unaided eye; but when the emphysematous spaces
are as large as a hazelnut or small walnut they consist of numerous
air-sacs, or even of several lobules, fused together by the atrophy and
breaking down of the interalveolar and interlobular tissues. When the
cavities thus produced by the fusion of several sacs or lobules are in
the subpleural portion of the lung, they will sometimes project beyond
the adjacent surface, so as to form appendages of the size of a small
walnut which appear to be connected with the lung by a pedicle. It is
remarked by Waters that perforation of the cell-walls is much more
common in lobar than in lobular emphysema, even though the dilatation
of the sacs may be as great or greater in the latter than in the former
affection; which is due, no doubt, to the fact that the extensive and
diffused changes in the lobar form are dependent upon a degenerative
process, in consequence of which the walls are specially prone to give way.
All the changes just referred to, from the earliest and slightest
degree of distension to extreme attenuation and perforation of the
walls, with final
coalescence of several sacs and the formation
of appendages, may be met with at the same time in different parts of
the same lung. The most advanced changes are found most commonly at the
apices and free margins of the lungs, while in the deeper parts an
earlier stage only may have been reached.
The blood-vessels in the cell-walls are diminished in calibre by the
atrophy of these walls and by the constantly-increasing air-pressure,
so as to admit only the watery part of the blood; and thus is explained
the pigmentary change in the surrounding tissues where the
blood-corpuscles collect. Ultimately, many of the vessels are
obliterated, and the backward pressure thus induced extends to the
pulmonary artery, and thus gives rise to hypertrophy and dilatation of
the right side of the heart, as already explained. It is this pressure
on the vessels in the alveolar walls that causes also passive hyperæmia
of the bronchial mucous membrane, and thus produces a tendency to
bronchitis, which so often occurs as a consequence of emphysema, while,
again, primary bronchitis is frequently a factor in the production of
the disease. The principal change in the bronchial tubes, in addition
to the hyperæmia and softening of their mucous membrane due to
coexisting bronchitis, is a hypertrophic thickening of their muscular
coat, the result probably of repeated spasmodic action in the asthmatic attacks.
DIAGNOSIS.—The chief points by which the diagnosis of emphysema is
determined have already been referred to under the head of Symptoms and
Signs. The most important of these are the auscultatory signs; for,
although the general symptoms and history of the case may point with
probability to the nature of the malady, yet if these alone be regarded
other affections may easily be confounded with it.
The auscultatory signs proper to emphysema are increased resonance upon
percussion, feeble respiratory murmur, and prolonged expiration. Any
one of these physical signs may be met with in other affections than
emphysema, but when they occur conjointly they point only to this
disease. In addition to them the alteration in the form of the
chest-wall, so that it becomes rotund or barrel-shaped, and the
asthmatic character of the breathing, are important indications. The
diseases most likely to be mistaken for emphysema are phthisis,
bronchitis, pneumothorax, and pleural effusion.
In the early stage of phthisis feebleness of respiratory murmur with
prolonged expiration might suggest the existence of emphysema; but,
apart from the fact that these signs at any time when a doubt might be
felt are generally confined to the top of the lung in phthisis, the
diminished percussion resonance, the bronchial or broncho-vesicular
breathing, the bronchophony or bronchial whisper, and increased vocal
resonance and fremitus—all of them proper signs of phthisis and all
wanting in emphysema—would by their presence or absence clearly
establish the differential diagnosis between the two affections. In
more advanced phthisis, when softening has taken place and a cavity
exists, difficulty in discriminating between the two diseases could
hardly arise.
Emphysema is so frequently associated with chronic bronchitis and with
intercurrent attacks of acute bronchitis that it is often important to
determine whether these latter affections exist independently or are
complications of the emphysema. The question is in general settled by
the history of the case and by the conformation of the chest, showing
whether previous dilatation of the air-cells has taken place or not; as
also by the presence or absence of the special signs of emphysema when
those of the bronchial affection are encountered.
Capillary bronchitis, from the urgent dyspnoea attending it and the
vesiculo-tympanitic resonance which it sometimes presents, especially
in the upper and anterior parts of the chest, may possibly be mistaken
for emphysema, from
which, however, it may be distinguished by
the quickened pulse and high temperature that belong to this form of
bronchitis, as also by the rapid diffusion of the subcrepitant râle
over both sides of the chest in capillary bronchitis; whereas this sign
is absent or less marked in emphysema. Moreover, capillary bronchitis
is most common in childhood, when diffused emphysema is less frequently
met with.
Pneumothorax is characterized by distension of the chest and increased
percussion resonance—signs which belong also to emphysema; but the
possibility of error is avoided by the consideration that whereas in
emphysema the respiratory sound is feebler than natural, in
pneumothorax it is strongly exaggerated and amphoric in character; and
there are also the additional signs of metallic tinkling and the
plashing noise or "Hippocratic succussion sound" made by moving the
body backward and forward. Moreover, even as regards the sign in which
the affections would appear to resemble each other, a difference may be
observed on careful examination; for the percussion note of
pneumothorax is purely tympanitic, while in emphysema the increased
resonance has still a vesicular character to some degree. Pneumothorax,
again, is always a unilateral affection, and emphysema is almost as
constant in its occurrence on both sides of the chest.
It might appear that there would be little liability to confuse
emphysema with pleural effusion, in view of the very general presence
of dulness on percussion in the latter affection and of resonance in
the former. But in some cases of fluid effusion in the chest a degree
of tympanitic resonance is met with, more especially in children. J.
Lewis Smith remarks that "as a rule in the pleuritis of children, at a
certain stage of the effusion, percussion produces a sound which is
either decidedly tympanitic or which partakes of the tympanitic
character."11 In both affections, moreover, there may be enlargement
of the chest. The doubt, if it arise, may be settled by the
consideration that in emphysema the altered resonance and the
enlargement are on both sides; whereas in pleurisy these signs are in
general on one side only; and, further, the enlargement is more marked
at the top of the chest in emphysema and at its base in pleural effusion.
11 Diseases of Children, 5th ed., p. 607.
In concluding the account of the diagnosis it may be said that when the
history of a case, the frequent or constant occurrence of dyspnoea, and
the more or less rounded conformation of the chest make the existence
of emphysema probable, this probability may be converted into a
certainty by the discovery of resonance on percussion, feeble
respiratory murmur, and prolonged expiration.
PROGNOSIS.—The circumstances, apart from treatment, which especially
affect the prognosis of emphysema are the form in which the disease
occurs and the ability of the patient to secure immunity from
influences which may increase the malady itself or the attendant
bronchitis, such as hard work, great exertion of the respiratory
organs, and exposure to cold and damp.
Acute supplementary emphysema, even when it affects considerable
portions of both lungs, may entirely disappear and the vesicles be
restored to their integrity on the removal of the underlying cause.
Thus, the vicarious dilatation of air-cells following acute bronchitis
or whooping cough in children may leave no sign of its previous
existence after recovery from these diseases. In general, the shorter
the duration of the causal diseases, the more likely is the emphysema
to disappear; for if it be maintained for a considerable time, the
elasticity of the cells may be so damaged that they may never return to
their natural size.
In hypertrophic lobar emphysema the prognosis in most cases is
unfavorable as regards perfect recovery; while yet the disease may not
materially shorten life, and with proper care may be compatible with a
fair degree of
comfortable existence. And, indeed, even in this
form of the disease, provided it do not affect a great extent of lung
and have not been of very long duration, there is in some cases ground
for hope of ultimate recovery, with restoration of the air-cells to
their normal condition. Modern methods of treatment have rendered the
prognosis in such cases somewhat less unfavorable than it was once held to be.
TREATMENT.—The treatment of emphysema comprises several distinct
objects: 1st, the arrest of the degenerative changes which may be going
on in the walls of the air-vesicles, and which favor their dilatation;
2d, the restoration, as far as is possible, of the integrity of the
lungs, so that they may resume their natural size; 3d, the relief of
bronchitis, asthma, and dropsy, which are associated as secondary
affections with the primary disease.
To meet the first of these indications, the arrest of degenerative
change, iron is among medicinal agents the one most to be relied upon;
for, though neither it nor any other means has power to restore loss of
tissue or to reproduce integrity of structure when several alveoli are
fused into one cavity by the breaking down of their partition-walls,
yet by enriching the blood it may improve the nutrition of these
cell-walls so that the tendency to dilatation and rupture may be
checked. Iron steadily administered in small doses is the best means
for effecting this end, and if the patient object to one form of the
metal after using it for some time, it may be changed for another. The
best preparation of the drug is probably the tincture of the chloride,
and one of the best forms for administering this medicine is the
mixture of acetate of iron and ammonium (Basham's mixture) introduced
into the U. S. Pharmacopoeia of 1880. This is especially valuable, when
any dropsical effusion exists, on account of its gentle diuretic
action. In addition to iron, other agents promotive of nutrition, such
as cod-liver oil and the hypophosphites, may be used with the same
view. Stomachic tonics, such as the simple bitters and pepsin, may be
useful by aiding digestion and nutrition; and at the same time, by
preventing the formation of flatus, they may relieve the dyspnoea
caused by upward pressure on the diaphragm. That real benefit may be
derived from such measures is beyond doubt; and it is to be feared that
some practitioners, in their conviction that no cure can be wrought in
those parts of the lung which have actually undergone wasting and
rupture, have to too great an extent neglected the use of means which
may at least prevent the advance of similar changes in other parts, and
thus tend to stay the progress of the disease.
Deep and hurried respiration will increase the air-pressure within the
yielding vesicles; for this reason active exercise is objectionable,
especially walking up hill, and the use of wind instruments is to be
strictly prohibited. Indeed, as regards this last cause of respiratory
pressure the patient's inability to practise is in general warning
enough, but in the early stages of the affection a caution against it
may be necessary.
The suggestion of the use of strychnia against emphysema is not founded
on a correct knowledge of the mode of action of this drug; for,
although it may stimulate muscular contractility, it has no influence
upon the elasticity of the air-cells and no power to restore them to
their natural size. Whatever benefit may result from it is due solely
to its action on digestion and the improvement in nutrition to which it
may thus contribute.
The second indication of treatment, the restoration of the dilated
air-cells to their natural size, is possible, if at all, only at an
early period of the disease or in portions of the lung which have not
gone beyond a moderate degree of cell-dilatation. An enlarged space
formed by the fusion of several cells cannot be lessened in size by any
means, medical or mechanical, and the loss of respiratory power from
the destruction of the cell-walls in which oxygenation is effected does
not admit of permanent relief. Where, however, such
destruction
has not yet taken place and distension is not extreme, there is reason
to believe that a return of the cells to their natural size may in some
cases be accomplished. The inhalation of condensed air has been
recommended with this view; and no doubt good may result from it, due
chiefly to the retardation of the breathing and of the heart's action
which it occasions, while dyspnoea is relieved by the larger supply of
oxygen taken in at each inspiration. This improvement in respiration
causes more complete tissue-metamorphosis, and thus aids nutrition and
all the functions.
Still greater benefit is to be derived from the exhalation into
rarefied air—a measure which acts upon mechanical principles, and has
been found to give relief not only to the symptoms of emphysema, but to
the organic disease itself; for the retention and stasis of the
residual air, which is far larger in amount in emphysema than it is in
health, serve at once to keep up the dilatation of the cells and to
increase the dyspnoea; and therefore any means which will effect the
withdrawal of this air will favor the return of the cells to their
normal size, and at the same time relieve the dyspnoea. This benefit is
accomplished by the method of expiration into rarefied air, which acts
by suction—or pneumatic aspiration, as it may be termed—drawing out
the air from the distended vesicles, and relieving them of the
continual presence and pressure of this air. Better results would
appear to be gotten from the conjoint use of the two methods—the
inspiration of compressed air and expiration into rarefied air—than
from either one alone.
By the persistent use of these means in cases which have not advanced
so far as to defy all treatment not only may the symptoms of dyspnoea,
cough, asthma, and impaired nutrition be improved, but the size of the
chest may be diminished, as shown by measurement; and this can result
only from the return of the distended air-cells, in some degree at
least, to their normal capacity.
The apparatus best fitted to effect this double purpose is that of
Waldenburg, as modified by Tobold.12 The method of using it is
simple, and can readily be understood by examining the instrument. It
must be said that the most valuable action of this apparatus consists
in the withdrawal of the air from the cells which it effects, for this
tends to produce an organic change for the better—viz. the diminution
of the enlarged cells by a sort of suction; while its other action, the
supply of condensed air, gives relief to symptoms mainly. In emphysema
the expiratory act is relatively more impaired than the inspiratory,
and the apparatus is best adapted to the relief of this greater
deficiency. Henry Saltzer, formerly of Germany and now of Baltimore,
has recently obtained very favorable results from its use in emphysema,
not only as regards the dyspnoea and other symptoms, but also in the
way of lessening the size of the chest as determined by
measurements.13
12 This instrument is made by Messrs. J. Reynders & Co. of
New York.
13 A reference to Saltzer's observations and measurements
may be found in Weil's Handbook of Topographical Percussion, pp. 107,
108, Leipzig, 1880.
The third indication of treatment has reference to the complications of
emphysema. Of these the most common, and one of the most important, is
bronchitis, which is to be treated in the same way as when it occurs as
an independent affection. Expectorants to promote and remove secretion
and agents to allay cough are very important means, because the
retention of secretion and the effort of cough to expel it cause a
strain upon the air-cells, and thus increase the emphysema. The local
use, by inhalation or spray, of opiates, belladonna, hyoscyamus, and
other agents of this class, is often most serviceable by giving relief
to the cough without disturbing digestion. As bronchitis is in many
emphysematous patients a very chronic affection, and is attended with
submucous thickening in the bronchial tubes and consequent diminution
of their calibre, the iodide of potassium is an agent of special
value for its relief. Whether the influence of this remedy is due to a
sorbefacient power or to some other unexplained mode of action, there
is no doubt of its great value in chronic bronchitis, so that for this
complication of emphysema it claims a very high rank among medicines.
The rapidity with which relief is afforded to the cough and dyspnoea of
bronchitis, and to the asthmatic paroxysms attending it, by full doses
of 10 or 15 grains of iodide of potassium at intervals of four hours,
makes it probable that its action is partly neurotic in character. It
is remarked by Austin Flint, Sr., that when the iodide has effected a
marked improvement in the chronic bronchitis he has known the
characteristic deformity caused by the emphysema to be notably
diminished.14
14 Clinical Medicine, p. 131.
A dangerous symptom which sometimes arises in the course of the chronic
bronchitis accompanying emphysema is profuse bronchial catarrh, which
may destroy life by producing apnoea, the surface becoming cold and the
pulse feeble and vanishing as the patient seems to be drowning in his
own secretion. In this condition the writer has in several instances
found prompt and unmistakable benefit from the hypodermic injection of
hydrobromate of quinia, and he would strongly advise the use of this
agent. The solution he has employed is of the strength of 4 grains of
the salt to 20 minims, and of this 15 to 20 minims has been the dose
given. Under the action of this remedy the pulmonary capillaries would
appear to be so toned that further effusion is checked, and the gasping
and cyanotic condition has been speedily succeeded by comfortable
breathing. For the same symptom Waters advises the use of moderately
large doses of turpentine (drachm doses in aromatic water every two
hours) on a plan suggested by Sir D. Corrigan of Dublin.15
15 Diseases of the Chest, p. 172.
As bronchitis has so much power to produce emphysema when the
conditions favorable to its occurrence exist, and to increase it when
already established, everything tending to prevent it is of great
importance. With this view the avoidance of cold and wet, and, when
practicable, recourse to a mild climate in winter, are advisable.
The attacks of asthma to which emphysematous patients are subject are
to be treated in the same way as the purely spasmodic form occurring
independently of discoverable organic disease. If the difficult
breathing has come on suddenly and the patient is not laboring under
advanced dilatation of the heart, prompt relief may be given by a
hypodermic injection of morphia; but if the heart is much dilated, this
might endanger too great depression. Chloral is generally unsafe for
the same reason. The bromides in full doses may be serviceable in the
less severe attacks, and the tincture of lobelia in doses of 10–20
drops every fifteen minutes until slight nausea is felt is often of
great benefit, as is also the smoking of stramonium-leaves.
The dropsy met with in advanced stages of emphysema may be so prominent
a symptom as to require special treatment. Its cause is found in
dilatation and weakness of the right chambers of the heart, which
result from obstruction to the circulation through the lungs when
compensative hypertrophy is no longer efficient, for then these give
rise to passive congestion of the liver and kidneys and remora of the
general venous system, with dropsical leakage, seen first and chiefly
in the lower extremities. Treatment is therefore to be directed chiefly
to increasing the tone of the heart; and for this purpose digitalis is
most useful, as it is in other forms of cardiac dropsy. The chief
indication of its beneficial action is seen in the better action of the
kidneys consequent upon the increased impulsive force given to the
heart. When acting favorably, marked relief both of the dropsy and the
dyspnoea may be obtained from the use of this agent in the dose of 2 to
4 drachms of the infusion or 10 or 15 drops of the tincture every three
or four hours. If
the stomach should not bear the digitalis, as
is sometimes the case, or if it fail to act or lose its power, the
fluid extract of convallaria, recently introduced as synergistic with
foxglove, may be employed as a substitute for it.
Under similar circumstances, if the patient's strength will admit of
it, great benefit will sometimes result from a mercurial purge, by
which passive congestion of the portal system may be relieved and the
upward pressure of an engorged liver in some degree lessened.
4. Atrophic Lobar Emphysema.
This disease differs from the hypertrophic form of emphysema in the
circumstance that the bulk of the affected lungs has undergone
diminution from waste or atrophy of their tissue. Absolutely, the lungs
may contain no more air than they should in health—they may even
contain less—but, relatively, there is an increased amount of air in
them in consequence of the diminished amount of the lung-tissue. Such
relative increase of air in a given area of the lung may be very
considerable from the atrophy and destruction of the cell-walls, the
alveoli coalescing so as to form cavities, while the individual
air-cells are not dilated. The entire lung, however, is shrunken, the
chest-wall correspondingly depressed and contracted, and the thoracic
muscles atrophied. The function of the affected lungs is impaired in
consequence of their loss of size and the diminution of the respiratory
movements. This is of course especially noticeable when exertion is
made, while under other circumstances there may be little or no
embarrassment of breathing unless the disease is far advanced and has
involved a large amount of both lungs. But, in general, this form of
disease causes less distress and is a less formidable affection than
hypertrophic emphysema. In some cases a mingling of the two forms is
found, as when a person the subject of general atrophic emphysema has a
local vesicular dilatation developed at the top and margins of the lungs.
The shrunken state of the lungs in atrophic emphysema prevents the
heart from being overlapped, so that the area of cardiac dulness is not
lessened, as it is in the hypertrophic form; and as the general waste
of the system is attended with a diminution of the amount of blood,
dilatation of the right ventricle, and consequent dropsy, are not apt
to occur, as they are in hypertrophic emphysema.
ETIOLOGY.—Atrophic emphysema is always due to constitutional causes.
It is found chiefly in old persons or in those in whom impaired
nutrition has produced the degenerative changes of old age. Hence it is
described by some writers as senile emphysema or senile atrophy of the lungs.
SYMPTOMS.—Of the general symptoms of atrophic emphysema, apart from
those which belong also to the hypertrophic form, the most marked
are—first, the lessened size of the thorax; and, second, the character
of the dyspnoea, which is not urgent, and is not apt to occur except on
making exertion. The blood is lessened in amount from the general
impairment of nutrition, and is therefore adapted, so to speak, in
quantity to the diminished aërating space. Percussion in general gives
exaggerated resonance, from the relative increase of air in the lung
and the thinness of the thoracic wall, which thus vibrates more
perfectly. In some cases, however, from loss of elasticity in the
cartilages of the ribs, the resonance is even diminished. On
auscultation there are found somewhat prolonged expiration and, in
general, feeble inspiratory murmur—signs which belong also, but in
greater degree, to true hypertrophic emphysema, from which, however,
the atrophic form is to be distinguished by the contraction of the
chest that is seen throughout its entire contour.
In some cases of hypertrophic emphysema there may be, it is true, an
appearance of partial contraction of the chest-wall, since where the
emphysema has produced a marked bulging of the upper portion of
the thorax the part below may seem by contrast to be contracted. But in
the atrophic form of the disease no distension is seen at any part of
the chest-wall, the whole surface being more or less sunken and
contracted. Even in hypertrophic emphysema with distension of the
thorax, when the disease has lasted a long time there may be some
degree of wasting of the lung-tissue; but this condition does not
constitute true atrophic emphysema, which is such from the beginning
without any preceding stage of hypertrophy.
DIAGNOSIS.—The diagnosis of atrophic emphysema is to be made by the
physical signs studied in connection with the conformation of the chest.
PROGNOSIS.—The prognosis of this affection is hopeless as regards a
cure, since the organic change is due to the degeneration of age; yet
the disease may continue for years without materially or at all
affecting the duration of life.
TREATMENT.—The atrophied lungs can never be restored to their
integrity; treatment is therefore limited to the use of tonics and
nutriment in order to hold in check the process of waste; and to the
relief of bronchial catarrh, which is apt to be attended with profuse
purulent secretion. The agents best suited to these two purposes have
already been considered.
II. INTERLOBULAR OR EXTRA-VESICULAR EMPHYSEMA.
Interlobular or extra-vesicular emphysema is, as has been previously
stated, an affection differing anatomically and pathologically from the
form of disease already described. In the vesicular form air is present
where it normally belongs, but in undue amount; in the interlobular
form it is present where it ought not to be—that is, in the meshes of
the connective tissue between the lobules, beneath the pleura, and
around the bronchial tubes and pulmonary vessels. These situations may
be reached by the air through a rupture of the vesicles, and thus in
some cases vesicular may be associated with interlobular emphysema, the
rupture having occurred from violent cough; or the emphysematous
infiltration may be gaseous, as the result of gangrene occurring during
life or of decomposition after death.
DIAGNOSIS.—The presence of air in the connective tissue of the lungs
cannot be determined by any signs or symptoms; if, however, it should
be discovered in the subcutaneous tissue of the neck, face, or chest,
giving rise to puffiness and crackling of the integument, its presence
in the areolar tissue of the lungs may be suspected, especially if
there be coexisting vesicular emphysema, the air having passed into the
mediastinum and thence into the tissue beneath the skin.
The existence of interlobular emphysema is not, in general, of serious
significance, as the air commonly disappears from the subcutaneous
tissue in a few days; whence it may be inferred that it likewise
disappears from the connective tissue of the lung, the opening which
had admitted it there having become closed. If present in large amount
in the lung-substance, it may, however, increase the difficult
breathing of an emphysematous subject by compressing a number of the
air-vesicles. Or, again, if the interstitial emphysema be subpleural,
the bulla may burst, and the air, escaping into the cavity of the
chest, may occasion pneumothorax, or even hydro-pneumothorax, from the
resulting inflammation. Such an occurrence is, however, very uncommon.
Even when the diagnosis of interlobular emphysema is established, no
treatment is needed or practicable.
DEFINITION.—The term atelectasis is derived from [Greek: atelês],
incomplete, and [Greek: echtasis], expansion, and designates a
condition in which the lung has failed to expand or has returned in
part or throughout its whole extent to the state of non-expansion which
is normal in foetal life. In the former case the state is one of
congenital atelectasis, and is of course met with only in the new-born;
in the latter it is acquired atelectasis, or collapse of the lung, a
portion or portions of the organ which have once been expanded having
the air excluded from their alveoli, so that these collapse and return
to the pre-natal state. To this condition of acquired atelectasis the
term apneumatosis, from [Greek: a] negative, and [Greek: pneumatôsis],
filling with air, was applied by Fuchs in 1849, and it has since been
adopted by Graily Hewitt.
HISTORY.—For a long time this affection was regarded as a peculiar
form of pneumonia, for the reason that at post-mortem examinations
patches of collapsed lung-tissue were found which appeared to have
undergone solidification. Inasmuch as the condition was most frequently
met with in young children, and the supposed solidification was often
limited to certain lobules of the lung with intervening healthier
spaces, it was described as the lobular pneumonia of children.
The secondary nature of the affection, and the fact that it is very
generally preceded by bronchitis, and sometimes by catarrhal pneumonia,
were pointed out by Barthez and Rilliet in 1838. Some other important
distinctions between this affection and general or lobar pneumonia had
been referred to by various writers, but it was not until 1844 that its
true nature was satisfactorily elucidated by Bailly and Legendre, who
showed, by blowing air into the lungs after death, that the lobules
supposed to be hepatized were not really solidified by exudation, but
had simply collapsed for want of air.
ETIOLOGY.—The congenital atelectasis of new-born children may be due
to original feebleness, to protraction of labor interfering with the
blood-supply through the cord, or to obstruction of the air-passages by
mucus or other substances. In any case, it is the result of
non-expansion of the chest, so that the lungs are not unfolded. This
constitutes atelectasis in the strict sense.
Acquired atelectasis, apneumatosis or collapse of the lung, is an
affection most frequent in early infancy, though not limited to that
period of life, since bronchitis with defective innervation and great
impairment of strength, the essential factors in the production of the
disease, may occur at any period of life.
It is probably in almost every case secondary to bronchitis, and due to
the occlusion of the smaller bronchi by the presence of mucus allowing
the egress, but impeding the ingress, of air, so that the lobules to
which they lead are gradually evacuated of air, and thus finally collapse.
Obstruction of a bronchial tube by a foreign body or by the pressure of
a
morbid growth within the lung may produce collapse of the
lobules to which such tube leads, a smaller or larger part of the lung
being involved in proportion to the size of the obstructed bronchus.
Such cases are, however, very rare, and they more closely resemble the
condition brought about by the pressure of a pleural effusion giving
rise to the state of carnification, which is, in effect, an atelectasis
involving the greater part or the whole of a lung, and not limited to
certain lobules nor taking place lobule by lobule.
The principal cause of lobular collapse is no doubt bronchial catarrh,
the action of which is aided by impairment of the general strength and
of muscular respiratory power; for the natural elasticity of the
lung-tissue would favor the exit and oppose the entrance of air unless
it were counterbalanced by muscular action in inspiration. If, then,
this inspiratory action is lessened, the requisite amount of air will
not enter the alveoli, and that which they already contain will be in
part driven out, and perhaps in part absorbed into the blood, by the
pressure to which it is subjected. Deficient innervation and lower
vital power are thus important elements in determining collapse, which
is most common in very young infants or in those who, though somewhat
older, have had their nutrition impaired by malhygienic influences or
by other diseases.
The mechanism of the production of lobular collapse by the presence of
mucus in the bronchial tubes has been well explained by the classical
observations and experiments of Gairdner and of Hutchinson. They showed
that the physical result of collapse is in part due to the force of
expiration being greater than that of inspiration, and in part to the
anatomical formation of the bronchial tree. As to the former of these
causes, it was shown by the experiments of Hutchinson, already alluded
to in the article on EMPHYSEMA, that the force of expiration capable of
being applied for the overcoming of obstruction in the bronchial tubes
is greater than that of inspiration—in opposition to the teaching of
Laennec, who regarded the inspiratory as the greater force. Repeated
efforts to clear the bronchial tubes of accumulated secretion by the
forced expiration of coughing must therefore remove air from the
alveoli in greater amount than it can be returned to them by
inspiration, and so they must ultimately be evacuated of their contents
and consequently collapse.
The second mechanical cause to which Gairdner refers is found in the
shape of the bronchial tubes, which taper in size as they advance
toward the air-cells. The mucus contained within a tube may in
consequence of this shape act as a ball-valve, being displaced forward
in the direction of the greater diameter by the expiratory efforts,
thus allowing the exit of air, the entrance of which will be impeded
because inspiratory action will at once close the valve. This
valve-action of a plug of mucus is well illustrated and proved by the
experiments of Mendelssohn and Traube. In one of these a shot was
introduced into the left bronchus of a dog, and in two days the left
lung was found collapsed and the right one in a state of supplementary
emphysema. The collapsed lung was afterward distended by inflation. In
a like manner pledgets of mucus may establish an air-pump action that
will empty the cells to which the obstructed tubes lead and cause them
to collapse. It is, moreover, not improbable that a portion of the
contained air is absorbed by the blood-vessels, as is maintained by Fuchs.
As a predisposing cause age has a remarkable influence in producing
atelectasis, the condition being much more frequent under five or six
years of age than after that time. This is explained by two
considerations: The first is the greater prevalence of catarrhal
affections of the air-passages in young children than in other
subjects; the second is the fact that the chest-walls in a child are
more pliable and less firm and resistant than those of an adult, so
that when the diaphragm descends in inspiration a portion of the
chest-wall
may sink in, and the lung immediately beneath such
portion will not expand to meet the costal wall as it does in older
persons. According to Graily Hewitt, the part at which the chest-wall
is most depressed is "at the junction of the cartilages with the ribs,
and the ribs which more especially exhibit this want of power to resist
the atmospheric pressure are those just above and below the nipple, the
fourth to the seventh inclusive."1
1 Reynolds's Syst. Med., vol. iii. p. 872.
The principal cause of collapse involving an entire lobe or the whole
lung is the presence of liquid in the thorax in the form either of
inflammatory serous effusion, empyema, or hydrothorax. The admission of
air into the cavity of the chest by perforation of the lung or by a
penetrating wound of the thorax may also lead to the same result by
allowing atmospheric pressure on the lung. In such cases the lung may
again expand on the absorption or withdrawal of the liquid or air, but
it sometimes remains permanently compressed and carnified.
SYMPTOMS.—It is probable that atelectasis in very limited degree may
exist without being discovered or suspected, the amount of lung
involved being insufficient to interfere by its loss of function with
respiration or to give rise to appreciable symptoms.
In congenital atelectasis the symptoms are obvious from the moment of
birth, and all point to obstructed or imperfect respiration; but they
vary in degree. Should expansion of the chest not take place at all,
the heart, which at first may be felt feebly beating, will soon stop,
and death will occur. In other cases, in which the atelectasis is not
absolute, but yet expansion is not accomplished sufficiently for
respiration to be kept up, the infant is more or less cyanotic,
especially about the lips and face and at the extremities. The
movements of the thorax are slight in degree, and the cry is weak and
suppressed, and at last inaudible. In such cases death usually occurs
in a few hours, but sometimes life is protracted for several days. The
symptoms then are like those of acquired atelectasis or collapse of the lung.
In this condition—which, as already stated, is generally the result of
bronchitis occurring in debilitated children—the symptoms show
malaëration of the blood. Sometimes they are gradually developed, and
sometimes they occur quite suddenly, according to the rapidity with
which the collapse spreads through the lung and the number of lobules
involved in it.
The signs of bronchitis are present before the occurrence of collapse,
and are more or less mingled with those pointing to the collapsed
state. The hurried respiration so often met with in bronchitis is
increased by the collapse of any considerable numbers of lobules in the
lung. The evidences of imperfect oxygenation of the blood, which in
children are often apparent in bronchitis, are greatly augmented on the
occurrence of collapse, the breathing becoming more rapid and
oppressed, the working of the alæ nasi increased, and the dusky hue of
the surface spreading and becoming deeper. The character of the
respiration is modified in a very remarkable way, as pointed out by
George A. Rees of London, in consequence of the pliable and yielding
condition of the chest-walls in early childhood. When the upper part of
the chest is elevated in inspiration and the diaphragm descends, the
space thus produced cannot be filled by the lungs in consequence of
their partially collapsed state; and for this reason the intercostal
spaces and the lower end of the sternum are sunken by the atmospheric
pressure at each inspiratory act. This character of breathing may also
be observed in older subjects of collapse as regards the depression of
the intercostal spaces, though in less degree than in children, in
consequence of the greater rigidity of the thorax after childhood.
As collapse of the lung in very limited degree may be unattended with
general symptoms, so likewise it may have no positive auscultatory
signs. A
moderately extensive tract of the lungs must be affected
in order to produce these to an appreciable extent. This amount cannot
be stated exactly, but, according to Gerhardt, it is from an eighth to
a sixth of one lung.2
2 Ziemssen's Cyclop., vol. v. p. 332.
Dulness on percussion, varying in degree and extent with the number of
affected lobules and their nearness to each other, is a very constant
sign of collapse; but it must be kept in mind that if the collapsed
lobules are disseminated or central the dulness may be hardly
observable. Sometimes there is difficulty in detecting dulness, because
from the bilateral character of the bronchitis the collapse of lobules
may take place in about equal degree on both sides, so that one side
cannot be contrasted with the other. Ordinarily, however, there is a
difference in the degree of dulness between the two sides, because the
affection is more extensive in one than in the other; and in general
the loss of resonance over the collapsed lobules is determinable
without comparison of the two sides. Not uncommonly, patches of dulness
are found with intervals of comparatively clear resonance.
On auscultation the respiratory sounds are feeble or entirely absent in
an area in which a number of adjacent lobules are involved together in collapse.
When a considerable part of a lobe is affected, bronchial breathing may
sometimes be heard, but this is in general less marked than the degree
of dulness and the amount of condensation would lead the examiner to
expect, because the breathing is too feeble to give rise to the
vibrations necessary for the production of this sign.
An important indication of lobular collapse is the rapidity with which
the signs just described are developed; a part or parts of the lung
which had been clear on percussion and normal in respiratory character
becoming in a day, or sometimes in a few hours, dull and nearly silent
to the ear. This very suddenness with which the physical signs are
developed in a case of bronchitis or catarrhal pneumonia in a child
points very plainly to the occurrence of collapse of the lung.
PATHOLOGY.—The pathological appearances in collapse of the lung vary
according to the extent of tissue involved in the change, and also
according to the cause which has induced it. In the disseminated
lobular form which is due to bronchitis the collapsed portions are
chiefly seen on the surface and at the margins of the lung, and they
extend more deeply into the organ as it becomes more involved in the
atelectatic condition. On the surface or on a section the collapsed
patches are depressed somewhat below the surrounding parts and are of a
darker hue, so that they are readily seen as dark-red or purplish spots
surrounded by the lighter healthy tissue. The contrast is sometimes
enhanced by the fact that the non-collapsed parts are even paler than
natural from the vicarious emphysema that has been established in them.
The consistence of the affected part varies in different cases. If the
change has occurred without previous congestion, the texture may be
somewhat flaccid; but if there has been hyperæmia, the part will be
leathery, non-crepitant, and resisting pressure. If no crepitation can
be detected the part will sink in water from the complete expulsion of
air from the affected lobules. A cut surface is smooth and does not
present the granular appearance of a hepatized lung, nor can
exudation-matter be pressed or scraped from it.
The collapsed lobules may be made to swell up and resume their normal
appearance and rosy color by forcing air with a blowpipe into the
bronchus leading to them. This is so generally true, at least, that it
has been regarded as a certain test by which to discriminate between
atelectasis and pneumonic consolidation when there may be a doubt at a
post-mortem examination as to which condition exists. In general, the
attempt to inflate will succeed when the air is directed into a
collapsed lobule; but the test is of less value than it was once held
to be because it has been shown, on the one hand, that lobules
which have been collapsed for some time will not always expand under
the inflating force, and, on the other, that in recent catarrhal
pneumonia the alveoli may for a time still be inflated with air.
Meigs and Pepper, while stating that in general the results of the
attempt to produce inflation are altogether different in the two
conditions, yet hold, in accordance with Gairdner's teaching, that
"partially pneumonic lung may be inflated when the affection is recent
and combined, as it frequently is, with bronchitic collapse; while in
the latter lesion—i.e. collapse of lobules—in its purest forms
complete inflation is often very difficult or impossible after the
collapsed state has been of some duration."3
3 Diseases of Children, p. 143, 4th ed.
Nevertheless, the test is of value when applied along with others; for,
as stated by J. Lewis Smith, "the inflated pneumonic lung is more solid
and resisting when pressed between the thumb and fingers than is the
collapsed lung."4
4 Diseases of Children, p. 570, 5th ed.
The chief differences between the two conditions are—1st, the color,
which in collapsed lobules is purplish or livid, and in pneumonia
reddish-brown; 2d, the microscopic appearance, showing the alveoli
filled with cell-proliferation in pneumonia and free from change in
collapse; and 3d, the state of the adjacent pleura, which is inflamed
and often covered with lymph in pneumonia, while it is entirely healthy
in non-complicated collapse.
The bronchial tubes present the appearances met with in bronchitis,
being more or less congested, showing a softened state of their lining
membrane, and containing liquid mucous secretion and sometimes firmer
pledgets which have caused the obstruction.
As regards changes in the heart, extensive atelectasis may prevent
closure both of the foramen ovale and of the ductus arteriosus. From
the obstruction to the flow of venous blood offered by the collapsed
portions of the lungs the right ventricle may become so distended that
a portion of its blood may still be forced through the ductus
arteriosus, and another portion backward into the auricle and through
the foramen ovale, so that both of these channels may be kept pervious.
DIAGNOSIS.—Congenital atelectasis, if complete, cannot be mistaken for
any other condition occurring at birth, and is sufficiently denoted by
the signs already described.
Imperfect expansion of the lungs continuing for some days after birth
might suggest patency of the foramen ovale from the purplish hue of the
surface common to both conditions. The expansion of the chest and the
resonance that it yields on percussion in the cardiac affection will be
sufficient to discriminate them except in those cases in which they
exist together.
Acquired atelectasis or collapse of the lung may require to be
distinguished from bronchitis, from pleural effusion, and from
catarrhal pneumonia.
Even uncomplicated bronchitis is in children sometimes accompanied with
so much dyspnoea as to cause apprehension that collapse of lobules has
taken place, but the absence of percussion dulness, either diffused or
in patches, will exclude the supposition.
From pleural effusion collapse of the lung may be distinguished by the
fact that the dulness due to pleurisy is generally on one side only,
that it is more intense and diffused than that of collapse, and that
its line of demarcation may often be made to shift with the position of
the patient.
Catarrhal pneumonia is in general distinguishable from collapse by the
history, course, and symptoms of the disease, especially the sudden
rise of temperature that belongs to pneumonia; as also by the
auscultatory signs. The percussion dulness of pneumonia is more
extensive than that of collapse, and is accompanied with bronchial
breathing; whereas in collapse the respiratory sounds are feeble and
mingled with moist râles.
PROGNOSIS.—In congenital atelectasis, if there be no expansion
of the lungs within the first few minutes after birth, the prognosis is
generally bad. In some apparently hopeless cases, however, the
persistent employment of means tending to arouse the respiratory
function, and especially of those acting through a reflex influence, is
crowned with success. The prognosis varies according to the amount of
unexpanded lung; for even when some respiratory efforts have been made,
if the air enter only a limited extent of the lungs, the infant will
drag on a feeble existence for perhaps a few days, and then perish from
apnoea and exhaustion. When the lungs are once fully inflated the
danger from congenital atelectasis is past.
In acquired collapse of the lung the prognosis is dependent both upon
the number of lobules involved and upon the amount of strength
possessed by the patient. A larger amount of disease may be recovered
from if the nutrition and nervous system be not much depressed, while a
smaller amount may prove fatal in less favorable conditions of the
general system. Much also depends upon the extent and duration of the
coexisting bronchitis, and the degree to which it has affected the
constitutional powers.
TREATMENT.—In the treatment of congenital atelectasis the main
endeavor must be directed to arousing the respiratory function; and
this is best accomplished by means acting reflexively through the
centres of respiration. Sprinkling the chest and back with cold water,
the application of cold water to the spine by a sponge or by affusion,
or the alternate use of cold and hot water in the same way, will often
induce a deep inspiration by which the lungs will be unfolded and
respiration perfectly established. If this be not fully accomplished,
it is of the utmost importance that the child should be carefully
watched as long as the atelectasis continues in any degree, and that
the same means should be again resorted to when the failure of
respiration is threatened. The temperature of the surface should be
maintained by artificial heat and woollen wrappings, as a depression
below the normal standard easily takes place, and serves to lower all
the vital processes and increase the difficulty of keeping up respiration.
In acquired atelectasis treatment must to a great degree be directed to
the superinducing bronchial catarrh. Counter-irritation of the chest
may be practised with Stokes's liniment, which consists of equal parts
of oil of turpentine, acetic acid, and camphor liniment, or with
mustard poultices prepared with special reference to the sensitiveness
of a child's skin by mixing the mustard with a double portion of flour
or Indian-corn meal. With the same view, dry cups may sometimes be
advantageously used.
Expectorants are serviceable by relieving the bronchitis, the best
being the syrup or wine of ipecacuanha in the dose of 5 to 10 drops, or
the muriate of ammonia in the dose of 1 to 3 grains in simple syrup or
syrup of liquorice, every two or three hours.5 These agents may
modify the inflammatory state of the bronchial mucous membrane, and
thus prevent the extension of the collapse. If bronchial secretion be
profuse, the question of the use of emetics becomes very important.
When employed judiciously with reference to the real needs of the case,
they may be eminently beneficial, acting partly by removing the
accumulation in the bronchi which may have occasioned the
collapse and may favor its further extension, and partly perhaps by the
deep inspiration which precedes emesis serving to expand the collapsed
lobules. It must be remembered, however, that there is always a
tendency to failure of the vital powers in acquired atelectasis, and
that this may be dangerously increased by emetics of a depressing
character. The best for the purpose are alum, sulphate of zinc, and
ipecacuanha. The repetition of the emetic must be determined by its
effect on the breathing and on the patient's strength.
5 One of the following formula may be used:
| Rx. |
Syr. ipecac. |
drachm i–ij; |
| |
Syr. prun. virginian. |
drachm vj; |
| |
Ammon. muriat. |
drachm ss; |
| |
Aquæ, |
ounce j. M. |
Dose, teaspoonful for a child of three to six months.
Or,
| Rx. |
Ammon. muriat. |
drachm ss–drachm j; |
| |
Syr. glycyrrhiz.
Aquæ, aa |
ounce j. M. |
Dose, as above.
Tonics and supporting measures are always called for in the treatment
of atelectasis, in view of the fact that the condition is essentially
dependent on failure of constitutional strength. Milk, wine-whey, and
animal broths are appropriate articles of food; alcoholic stimulants
are generally required; and in emergencies, if sudden increase of
prostration occur, the carbonate of ammonia in the dose of 1 or 2
grains may be given.
During the whole course of the malady such tonics as quinia or the
compound tincture of cinchona or one of the soluble salts of iron may
be administered.
Brown Induration of the Lungs.
DEFINITION.—Increased density of certain portions of the lungs, which
are of a reddish color, with brown or yellowish-brown spots scattered
throughout the indurated tissue.
SYNONYMS.—Pigment induration; Congestive carnification.
HISTORY.—This affection is a form of passive congestion of the lungs,
in regard to which it is somewhat uncertain whether the morbid process
is simply one of congestion or whether along with this an inflammatory
element is likewise present. It is beyond question, however, that the
changed condition of the lung is primarily and chiefly congestive, and
that it originates from causes which produce congestion.
ETIOLOGY AND MORBID ANATOMY.—The etiology and morbid anatomy of this
affection are so closely related that they are best considered
together. The most important fact both in the etiology and pathology of
brown induration of the lungs is that it is gradually brought about as
the consequence of obstruction to the pulmonary circulation from
disease of the mitral valve, either constrictive or regurgitant in
character. Interference with the return of the blood to the left side
of the heart is in this way produced, with consequent stasis in greater
or less degree within the pulmonary capillaries.
The most marked changes observed in lungs which have undergone this
form of congestion are that they do not collapse when the chest is
opened, and that they are more compact and less elastic and crepitant
than healthy lungs. On section they present a reddish color
interspersed with spots of yellowish- or reddish-brown, which sometimes
are of a very dark hue.
Microscopic examination shows an increased size of the capillaries of
the lung, which seem to encroach upon the air-cells and thus lessen
their capacity. Whether the walls of the alveoli have themselves
undergone thickening is a question about which different opinions have
been entertained. Rokitansky states that "when stasis has continued for
a longer period the walls of the air-cells and the interstitial tissue
become swollen, so that the former may become perfectly impermeable to
air;"6 and although, in the passage quoted, he is writing of
pulmonary congestion in general, and not of this form in particular,
yet, as he is describing a stasis which has continued for some time,
the observation would seem applicable to the affection under consideration.
6 Path. Anat., vol. iv. p. 59.
Wilson Fox affirms that he has found alveolar thickening in
considerable tracts in this affection, with a distinct increase of
fibrous tissue in the walls of the alveoli; but this change, he
goes on to say, is not uniformly present, and in some places the
alveoli are found filled with epithelial products like those of
catarrhal pneumonia.
The true explanation of the condition is probably this: that, beginning
as a passive congestion, such as might be expected to result from the
mitral disease with which it is almost constantly associated, the
affection afterward assumes an inflammatory condition of a low type
with epithelial proliferation, and in some cases with thickening of the
alveolar walls and the interlobular connective tissue. Passive
hyperæmia is, however, always the basis of the disease. The brownish
spots visible in a section are caused by the leakage of blood from the
congested capillaries into the alveoli or interstitial tissue without
the occurrence of any large extravasation. The blood thus exuded
undergoes pigmentary change, with the production of hæmatoidin, the
shades of color varying accordingly as the exudation has been recent or
of longer duration.
The failure of the lungs to collapse is due to the encroachment of the
dilated capillaries on the air-cells, and perhaps to the thickening of
the cell-walls and the partial occupation of the cells themselves by
epithelial products.
SYMPTOMS.—The general symptoms and the physical signs of this
affection are of the same character as those that occur in other forms
of pulmonary congestion. Dyspnoea is felt, especially on making
exertion; and this may be attributable in part to the associated
cardiac disease as well as to the condition of the lungs. Loss of
resonance on percussion and feebleness of respiratory murmur are
observable; and when the condensation is great bronchial breathing may
be heard.
DIAGNOSIS.—It is evident that there is nothing in these signs
distinctive of this particular form of congestion, which is, in fact,
not diagnosticable with absolute certainty during life. The probability
of its existence may, however, be inferred if along with the above
symptoms and signs a presystolic or regurgitant mitral murmur is heard,
showing constriction or incompetency of the mitral valve.
PROGNOSIS.—The prognosis of this affection is of course always
unfavorable, because the condition depends upon mechanical disease of
the heart of an incurable nature. Temporary improvement may, however,
sometimes take place under proper treatment.
TREATMENT.—Such treatment must be used as serves to support the
weakened heart and hold in check the tendency to dilatation. With this
view digitalis or convallaria may be employed, with tonics and
alcoholic or ammoniacal stimulants as occasion may require.
Counter-irritation over the lungs may be used and expectorants may be
given. If dyspnoea be urgent, the preparations of ether, such as
Hoffman's anodyne, or the carbonate of ammonia, may be administered.
Congestion and oedema of the lungs are often found together, but they
are different morbid conditions, and each may occur independently of
the other. It is best, however, to consider them in connection with
each other.
DEFINITION.—By congestion of the lungs is meant an active or passive
hyperæmia of the pulmonary vessels, which are surcharged with blood.
Oedema of the lungs signifies an effusion of fluid consisting mainly of
the serum of the blood into the air-vesicles and, to some extent, into
the pulmonary connective tissue. Congestion is at times the determining
cause of oedema, but the latter condition may arise from causes not
tending to produce the former.
HISTORY AND ETIOLOGY.—As pulmonary congestion and oedema are almost
always secondary and dependent affections, their etiology is an
essential part of their history, so that these subjects will be best
considered together.
Active congestion of the lungs may result from any cause producing an
increased afflux of blood to these organs, such as hypertrophy or
functional over-action of the heart, or the sudden recession of the
blood from the surface and perhaps from other internal organs, such as
may take place under the influence of cold. Violent exercise, rapid
walking up hill, or even mental excitement, may in some impressible
subjects suffice to produce it.
Why vascular congestion should occur in a greater degree and more
readily in the lungs than elsewhere from the effect of cold is
sufficiently evident when it is considered that the pulmonary
capillaries are not supported by surrounding tissue, as those of other
parts are. And for the same reason the direct action upon them of cold
air or of certain irritant gases, such as ammonia or chlorine, may
suffice to cause an undue afflux of blood to them.
How far a neurotic influence exercised reflexively through the
vaso-motor system may serve to produce active congestion has not yet
been fully determined; but it is probable that the sudden pulmonary
congestions which have been known to follow the drinking of a large
quantity of cold water when the body is heated may be attributed to
such an action.
Passive congestion may be occasioned by a retardation of the blood-flow
from the lungs; as, for example, by a hindrance to its onward passage
through the left chambers of the heart in consequence of obstructive
valvular disease, especially a great degree of mitral or aortic
stenosis. So also mitral or aortic incompetency, by allowing the blood
to be crowded backward in the pulmonary veins, may interfere with its
passage through the lungs, and in this way set up passive hyperæmia.
By some writers mere weakness of the heart is spoken of as a cause of
passive congestion of the lungs; but it can hardly be regarded as
such apart from influences affecting the blood itself or the tonicity
of the pulmonary vessels; for it is to be considered that while
weakness of the left chambers of the heart might impede the onward
course of the blood received from the lungs, yet at the same time the
right chambers, if weakened in a corresponding degree, would send less
blood into those organs, and then the conditions of passive hyperæmia
would not exist. It is well known, moreover, that cardiac weakness
coming on suddenly as in syncope, or gradually as in various asthenic
diseases, may be present without the occurrence of any signs of
pulmonary congestion. Yet it is not impossible that there may be a
disturbance of the balance between the actions of the right and left
sides of the heart, and that thus passive congestion of the lungs may
result from a relatively greater weakness on the left than on the right
side of the heart, so that the left auricle and the pulmonary veins may
be obstructed, and backward pressure produced while the right ventricle
is still sending blood into the lungs.
It is probable, however, that, in addition to the propulsive power
exercised on the blood by the contraction of the heart, another agency
affecting its passage through the lungs is the interchange of gases in
respiration; and therefore any interference with the reception of
oxygen and the elimination of carbonic dioxide may tend to retard the
blood-flow, and thus favor stasis or passive congestion. In this way
the inhalation of impure air, especially air containing an undue amount
of carbonic dioxide, may occasion passive hyperæmia.
Pulmonary oedema is never a primary affection, but is always due to
some preceding disease. In the first place, it may, as already stated,
take its origin directly from congestion of the lungs, the walls of the
obstructed vessels allowing the transudation of serum, which will
collect in the air-cells and connective tissue and also in the mucous
membrane of the terminal bronchi. In an early stage it may be present
in the walls only of the alveoli without being effused into their cavities.
Another cause of pulmonary oedema is obstruction of the circulation of
a part of a lung, such as may take place in pneumonia or miliary
tuberculosis, the vessels of other parts becoming distended by backward
pressure, so that the serum of the blood will exude into the air-cells
or interstitial tissue. When this occurs in pneumonia it may be a most
alarming and dangerous complication.
Still another and very frequent cause of pulmonary oedema is Bright's
disease in its different forms, in which the oedema occurs as a part of
the general dropsy incident to these affections. In acute congestive
nephritis it may come on very rapidly, constituting acute pulmonary
oedema. Hertz remarks that an acute oedema may take place in the course
of an acute nephritis, as has been reported by Lebert, but that such an
occurrence is not frequent.1 The writer of this article has himself
seen several cases of acute pulmonary oedema occurring as a part of the
dropsy of scarlet fever.
1 Ziemssen's Cyclop., v. p. 279.
More frequently it is met with in chronic albuminuria, and varies in
amount from time to time, as dropsical effusions elsewhere do in this condition.
Attacks of asthmatic dyspnoea are not uncommon in the course of
Bright's disease, especially in cases of chronic contracted kidney.
They are described as uræmic asthma, and are referred by some writers
to the action of the depraved blood on the centres of respiration. This
explanation may be correct in some cases, but it seems likely that they
are due in part to dropsical oedema of the bronchial mucous membrane,
the connective tissue, or the air-cells. A weakened condition of the
heart, such as is apt to occur in advanced periods of Bright's
disease, has probably some share in determining the oedema.
In any case of oedema, according to its situation, whether it is in the
connective tissue, the bronchial mucous membrane, or the air-cells, and
according also to the amount in which it is effused, it will interfere
more or less with breathing. If there be interstitial infiltration with
swelling of the bronchial mucous membrane, lessening the calibre of the
tubes, there may be merely some embarrassment of respiration; but if
the effusion invade any considerable number of the air-cells, urgent
dyspnoea will be produced. Oedema is generally most abundant at the
lower part of the lungs, and is not uncommonly associated with pleural
effusion, the two conditions being due to the same cause; and then the
interference with respiration is greater and more perilous.
SYMPTOMS.—It is possible that a slight degree of pulmonary congestion
may exist when the circulation is hurried without the occurrence of any
other symptoms except moderate acceleration of the breathing. Under
such circumstances, however, the existence of congestion cannot be
proved. When it is brought about in greater degree, either by
over-action of the heart or sudden recession of blood from other parts,
the earliest and most prominent symptoms are a sense of oppression in
the chest and quickened, laborious respiration, which may rapidly
increase until the dyspnoea becomes most urgent and distressing. The
heart's action grows more hurried, the pulsations in the carotid and
temporal arteries are strongly felt, and the face is deeply flushed.
Cough is always present, at first dry in character and afterward
accompanied with expectoration of frothy mucus, which may be tinged
with blood or may be even mingled with a considerable amount of
bright-red blood.
The different appearances of the expectoration are probably due to the
fact that in some cases the distended pulmonary capillaries allow the
transudation of blood-corpuscles, and in others they are actually
ruptured by the strain, so that pure blood escapes from them.
If the congestion is due to weakened action of the heart, with remora
of the venous circulation, and is passive in character, the symptoms
may be less acutely developed and less urgent than they are in the
active form; indeed, in some cases in which very considerable portions
of the lung are involved there may be no excessive dyspnoea while the
patient is quiet, in consequence of the organism having become
gradually accustomed to the imperfect respiration.
As the congestion increases, however, and the lungs become more
affected, the signs of malaëration are more conspicuous. Dyspnoea is
more oppressive, the face and surface generally, especially the lips
and extremities, become cyanotic and cold, and the patient perishes
from apnoea and from coma occasioned by oedema of the brain or medulla
or stasis of blood in the cerebral veins, the respiratory centres being
paralyzed. With the occurrence of somnolence the efforts to free the
air-passages from fluid by coughing and expectoration grow less and
less as the sensibility is obtunded.
When the congestion is not very extensive the amount of air in the
lungs is not lessened sufficiently to materially affect the percussion
note, which may remain resonant, though it may have a somewhat
tympanitic quality. The vesicular murmur is still heard, but it is
rather rough in character. When the general symptoms indicate a graver
degree of congestion there will be corresponding changes in the
physical signs; resonance will be lessened, or even replaced by
dulness, in consequence of the filling of the alveoli with serum or
blood; and the respiratory murmur will be completely masked by coarse
and fine mucous râles. If the dulness is very marked, bronchial
breathing and bronchophony may be observed. Elsewhere in parts not
involved in the congestion exaggerated or puerile breathing may
be heard from the supplementary action that takes place there.
The physical signs may vary as to their situation with the patient's
position as the blood in the congested vessels and the serum in the
alveoli and connective tissue gravitate from side to side. But when the
change described as hypostatic pneumonia has taken place, and the
affected portion of the lung has become condensed in texture, position
has little or no influence on the physical signs, which will still
remain even when the affected side is kept uppermost.
When oedema of the lungs is produced by serous effusion invading the
air-cells, there is some degree of dulness on percussion, especially at
the lower part of the chest. Respiratory murmur is feeble or
suppressed, and fine moist râles are heard, with an intermixture at
times of the true crepitant râle. These signs are generally heard on
both sides, but when an area of oedema is due to pneumonia the signs
may be present only on the affected side.
COURSE AND TERMINATIONS.—Acute congestion of the lungs depending on
over-action of the heart or a sudden recession of blood may cause death
in a short time, or may disappear, either spontaneously or under
appropriate treatment, almost as suddenly as it has come on. The
abatement of the symptoms is generally attended with profuse serous
expectoration, and sometimes with hemorrhage, by which the congested
vessels are relieved, so that they return to their natural state.
When acute oedema of the lungs is due to Bright's disease in the acute
or one of the chronic forms, it is often quickly fatal, though if
properly treated it may disappear. When a consequence of chronic renal
disease it is apt sooner or later to return. Chronic passive hyperæmia
and chronic oedema of the lungs admit of only temporary relief, because
they are occasioned by such diseases of the heart or kidneys as are
themselves generally incurable; and they are very sure to recur, even
though they may be relieved for a time. It is not uncommon in cases of
this sort to see the symptoms of chronic oedema suddenly aggravated by
the occurrence of an acute attack, which is the immediate cause of death.
PATHOLOGY AND MORBID ANATOMY.—The pathological appearance of a
congested lung varies according to the form of the congestion and the
manner in which it has been occasioned. Acute congestion may occur very
suddenly from some of the causes that have been mentioned, and may
disappear with equal rapidity, leaving no traces behind. But sometimes,
from the extent of the congestion, respiration is interrupted to such a
degree that life is quickly destroyed. In such cases the affected
portion of the lung is of a dark color from being engorged with blood,
which flows from it if an incision is made. The part is heavier and
crepitates less than normal lung-tissue. The bronchial mucous membrane
is apt to be hyperæmic, as might be expected from the communication
that exists between the pulmonary and bronchial vessels, and the tubes
themselves are filled with mucus and sometimes with frothy and bloody serum.
Where the tonicity of the pulmonary vessels has been impaired by
sickness, age, or other debilitating influences, passive congestion of
the lungs is very likely to ensue if the heart become weakened; and as
the effect of gravity will aid in determining the stasis of the blood,
the resulting congestion is in life most marked in the lower and
posterior regions of the lungs, where the changes are chiefly found
after death. As gravity may thus determine the congestion to one part
of the lungs, so a change in the patient's position may cause it to
disappear from where it was first manifest and to appear in another
part which has become most dependent. The condition thus brought about
is known as hypostatic congestion. One of the consequences of passive
hyperæmia thus induced is a transudation of the serum of the
blood into the air-cells and connective tissue of the lungs; and this
is one way in which pulmonary oedema may be occasioned. When hypostatic
congestion has lasted for some time, it may no longer be affected by
changing the patient's position; and when this is the case it may be
accompanied by exudation of fibrin into the air-cells and by
proliferation of epithelium, thus producing the condition termed
hypostatic pneumonia.
All three of these states may be present in one lung at the same time,
one portion being passively congested, another oedematous, while the
most dependent part may be the seat of hypostatic pneumonia.
The congested parts of the lungs are very dark in color, in some cases
almost black; blood flows freely from a section through them, and serum
exudes from the alveoli and interstitial tissue when oedema exists. If
the altered condition of the lung has lasted for some time, the texture
of the affected part may be so firm as to resemble that of the spleen;
whence this change is sometimes termed splenization. In this condition
dark-red points consisting of extravasated blood may be seen scattered
about. If the state already described as hypostatic pneumonia exists,
the affected part is still more firm and dense in texture, and presents
a granular appearance on section from the exudation of fibrin which has
probably taken place, so that it resembles a portion of a lung that has
been the seat of an inflammatory process from the first.
DIAGNOSIS.—The diagnosis of pulmonary congestion in its different
forms, and of pulmonary oedema, is in general not difficult if the
symptoms of the causative diseases are carefully observed. Acute
pulmonary congestion coming on suddenly, and not preceded by any other
affection, needs to be distinguished from the early congestive stage of
pneumonia, which it somewhat resembles from the slightly impaired
resonance on percussion and the dyspnoea that may occur in both
diseases. The chief points of distinction between the two affections
are the absence in congestion of initial chill, of pain in the side,
and of rise of temperature; all of which are in general present in
pneumonia. As the case advances the divergence between the two
affections will be wider.
The diagnosis of acute oedema and of chronic congestion and oedema is
based upon the physical signs belonging to them, taken in connection
with the symptoms of cardiac and renal disease with which they are associated.
Capillary bronchitis bears some resemblance to pulmonary oedema, since
in both affections there are moist subcrepitant râles; but in capillary
bronchitis there is no such loss of percussion resonance as occurs in
pulmonary oedema, and, moreover, fever is not present in oedema, as it
is in the inflammatory affection. The character of the expectoration is
also different in the two diseases, being thicker and more tenacious in
bronchitis and serous or watery in oedema. From hydrothorax, oedema is
distinguishable by the shifting line of dulness and by the absence of
râles in hydrothorax.
PROGNOSIS.—Acute congestion of the lungs is always a serious
affection, and, as already stated, terminates fatally in some cases in
a short time. In the majority of instances, however, it disappears
spontaneously or under suitable treatment, and the lungs are in general
restored to their integrity. It may result in pulmonary hemorrhage,
from which recovery may take place, or which may give rise to
hemorrhagic infarction, the blood being drawn into the alveoli.
Passive congestion being a secondary affection, its prognosis depends
upon the diseases which occasion it.
In pulmonary oedema the prognosis is always very grave. When occurring
suddenly as a consequence of acute congestive nephritis, it may wholly
disappear under proper treatment, and if the kidney affection is
likewise cured there will be no further return of the pulmonary
complication. When it comes on in the course of chronic renal disease,
it may disappear and recur from time to time, but it is apparently not
often the direct cause of death by itself. Sometimes, however, it is
associated with cerebral oedema and other conditions which together
occasion a fatal termination. When due to pneumonia, oedema adds very
much to the gravity of the affection, and may be the immediate cause of death.
TREATMENT.—The treatment of acute pulmonary congestion consists in the
use of means to check the undue flow of blood into the engorged lungs.
Of these the best, if the patient be seen promptly and the strength of
the pulse admit of it, is general bloodletting, by which the mass of
the blood is lessened and the action of the heart and pressure within
the blood-vessels are lowered, so that both the amount of blood in the
hyperæmic vessels and the force with which it reaches them will be diminished.
This measure may be also useful in the way of preventing or checking
acute pulmonary oedema by lessening the blood-pressure. Should
venesection be thought inadmissible, cups may be applied to the chest
in front or behind, and at the same time the volume of the blood may be
temporarily lessened by placing ligatures around the thighs, so as to
check the flow of blood in the veins near the surface. Revulsion from
the congested vessels of the lungs may also be effected by mustard
foot-baths or the application of mustard poultices to the chest.
Aconite may be serviceable by controlling over-action of the heart, and
may be given in the dose of 1 or 2 drops of the tincture of the root at
intervals of half an hour until some effect on the circulation is produced.
It is of importance to remove any blood or serum that may be present in
the air-cells and smaller bronchi; and for this purpose one of the
quickly-acting and non-depressing emetics may be given, such as
apomorphia hypodermically or the sulphate of zinc or turpeth mineral by
the mouth. Respect must be had to the condition of the patient's
strength in ordering an emetic, since if there be much prostration, or
if the interference with respiration has seriously depressed the heart,
more harm than good might result from its use. Expectorants may
somewhat later supplement the action of emetics, or serve to keep up
the good effects gotten from them by helping to remove the residual
fluids from the air-passages. Among the best of these are the syrup of
senega and the carbonate or hydrochlorate of ammonium.
Passive congestion of the lungs, being dependent upon a weakened
condition of the circulation, requires the use of means to sustain and
reinforce the heart's action. The alcoholic and ammoniacal stimulants
are here of great importance, and digitalis may be of sovereign
efficacy, especially in cases where the congestion is associated with
dilatation and attenuation of the heart. The power possessed by this
drug of increasing arterial pressure, and thus producing diuretic
action, may render it further serviceable when the congestion is
accompanied with oedema, as in this way the serous infiltration may be
absorbed and removed. From 10 to 20 drops of the tincture or from 2 to
4 drachms of the infusion of digitalis may be given every two hours
until some effect on the pulse or the kidneys is noticed. If the
stomach should not bear digitalis well in either of these forms, as is
the case with some patients, the alkaloid digitalin in the dose of
1/60
grain may be given. The convallaria recently introduced as synergistic
with digitalis may be substituted for it, and in the dose of from 20
minims to 1 drachm of the fluid extract it will be found not uncommonly
to be an efficient heart-tonic. Like digitalis, too, it possesses
diuretic power from the increased arterial pressure that it occasions.
Passive pulmonary congestion may assume a chronic form in connection
with chronic cardiac and renal disease, and without presenting urgent
symptoms may cause almost constant embarrassment of respiration
in greater or less degree. Under such circumstances the preparations of
iron are helpful by enriching the blood and increasing the tone of the
heart. One of the best preparations is the mixture of acetate of iron
and ammonium,2 known as Basham's mixture, which combines diuretic
with chalybeate action. This may be given in the dose of from 1 to 4 drachms.
2 U. S. Pharm., 1882.
It is of great importance in all cases of passive congestion and of
hypostatic pneumonia to change the patient's position from time to
time, so as to counteract the influence of gravity and relieve
dependent portions of the lungs.
Pulmonary oedema occurring in an acute form in the course of either
congestive nephritis or chronic renal disease may seriously imperil
life, and therefore it demands prompt and bold treatment. When it
results from acute nephritis, it is more immediately dangerous than
when dependent on chronic disease of the kidneys; yet in this acute
form it may admit of perfect cure if proper remedial measures be at
once instituted. Cups may be applied to the loins with the view of
relieving the engorged kidneys and enabling them to resume their work
of removing fluid from the body. In cases where the strength of the
pulse is sufficient, it may even be good practice to abstract blood by
the lancet to the amount of six to eight ounces. According to
Oppolzer,3 this treatment may be proper even when somnolence
indicates oedema of the brain, provided there be no irregularity of
respiration or intermission in the pulse—signs which contraindicate bloodletting.
3 Ziemssen's Cyclop., v. p. 285.
Active diaphoretics are among the best medicinal agents to be employed,
their good effects being due to their derivative action and to the
large discharge of fluid from the skin which they occasion, thus
promoting the removal of what is effused in the lungs. The fluid
extract of jaborandi in the dose of from 20 minims to a drachm, or the
hypodermic injection of
1/8
to 1/6
grain of nitrate or muriate of
pilocarpine, frequently causes prompt and profuse perspiration. The
writer is confident that he has seen life saved by the use of this drug
when it has been in urgent peril from pulmonary oedema. In the absence
of this agent, or along with it, the hot-air bath, which can almost
always be extemporized in an efficient form, may serve to promote or
increase fluid discharge from the skin. If the patient's strength is
sufficient, one of the hydragogue cathartics may be given, and among
them the most prompt and active is elaterium in the dose of
1/12
to 1/8
grain every four hours. The action of this drug must be carefully
watched and its depressing tendency guarded against by the use of
alcoholic stimulants.
When pulmonary oedema results from weakness of the heart, as in
dilatation of that organ, or from chronic renal disease, all lowering
measures must be avoided. Bloodletting, whether general or local, would
still further depress the heart, and by increasing the hyperæmia of
chronic Bright's disease would favor the further effusion of serum into
the lungs. Dry cupping over the chest before and behind may be
serviceable as a revulsive measure. Stimulants and tonics are called
for, and digitalis or convallaria is directly indicated from the
special power possessed by these agents of improving the cardiac tone
and promoting the action of the kidneys by increasing blood-pressure.
Digitalis has been thought objectionable when there is much
irregularity of respiration, and perhaps it would be safest to postpone
its administration until this symptom is relieved by the use of
alcohol, ammonia, musk, or other prompt diffusible stimulants.
The writer has had repeated opportunities for observing the value of
quinia given hypodermically in checking effusion of serum into the
air-passages, and he would strongly recommend its use in the treatment
of pulmonary oedema in the form of the hypodermic injection of the
solution of hydrobromate of quinia of the strength of 4 grains to
20 minims. Of this solution 10 to 20 minims may be injected at once. If
such a solution cannot be obtained, a full dose of 10 to 15 grains of
the sulphate of quinia may be given by the mouth.
As in the case of passive congestion of the lungs, so in oedema,
advantage may be gained by changing the patient's position from time to
time, so as to prevent the constant gravitation of fluid to the same
portion of the affected organs.
The word means, literally, spitting of blood, from two words, [Greek:
haima], blood, and [Greek: ptyô], I spit.
SYNONYMS.—If we go back far in the history of medicine, we find many
synonyms, such as Hæmoptoe, Emptoe, Emptoica passio, Pneumorrhagia,
Hæmorrhagia pulmonis, Crachement de sang, etc., etc.
DEFINITION.—Bronchial hæmoptysis is the spitting or expectoration of
blood which has been effused into the bronchi or bronchioles from the
bronchial vessels. Pulmonary hæmoptysis is the spitting or
expectoration of blood which has been effused into the air-cells, the
inter-alveolar and interlobular tissues. This distinction is not always
practicable in diagnosis or practice. It may, however, serve for a
grouping of some well-known clinical forms of hæmoptysis.
It is not possible to give indications by which the origin of blood in
the lungs may be positively determined except by a reference to other
symptoms than the hæmoptysis. In general, bronchial hemorrhage is
characterized by a bright-red, fresh color, is aërated, unmixed, and
uncoagulated. In pulmonary or parenchymatous hæmoptysis the blood is
dark, non-aërated, and coagulated to some degree, and often alternates
with a mixed blood and mucus sputum. These distinctions are not
reliable, and must be supplemented by all of our clinical resources in
the case before us. The author maintains that in the hæmoptysis of
phthisis the hemorrhage in the large majority of cases is both
bronchial and pulmonary. The typical parenchymatous hemorrhage is found
in hemorrhagic infarction and pulmonary apoplexy, which, compared with
phthisis, are rare occasions for hæmoptysis. This general statement
will form the basis of what follows in this exposition.
HISTORY.—Historically, there are not many phases in the doctrine of
hæmoptysis. Controversy has been chiefly confined to its relations to
phthisis as cause or effect.
The simplicity and directness of observation of the ancients give a
special interest to their views of hæmoptysis. They believed that it
was oftener cause than effect. They found a warranty of that opinion in
what they thought was a direct conversion of blood into pus, and in the
irritating qualities of the latter. Hippocrates'1 fundamental
statements are, "Ex sanguinis sputo, puris sputum malum;" "Ex sanguinis
vomitione tabes et puris purgatio per superiora purgatio;" "Ex
sanguinis sputo puris sputum et fluor, ubi autem sputum retinetur
moriuntur." Another statement of his is given in translation by
Peter:2 "When some of the veins of the lung are ruptured the
hemorrhage is in proportion to the size of the vessel; a part, on the
contrary, unless the vein be very small, diffuses itself in the lung,
putrefies
there, and after having putrefied forms pus. As a
result, it is at one time true pus, at another pus mixed with blood,
and another time it is pure blood, which is rejected; and if the vein
was very full it is from it that the mass of the blood comes, and thick
pus, mixed with putrefied pituitous secretion, is expectorated."
1 Edition 1696, book 7, p. 1141, Aphorisms 15 and 16, 80 and
81.
2 Clinique médicale, tome 112, p. 243. The precise
locality of this quotation is not given by Peter, but it is from
Hippocrates' Opera, ed. Kuhn, Leipsic, 1825, vol. ii. p. 178.
Thomas Young3 gives the following sentences from Hippocrates'
Predictions and Aphorisms: "The most dangerous consumptives are cured
by a rupture of the great vessel which corrodes the lungs;" "Purulent
expectoration after hæmoptysis is dangerous;" "In some cases
consumption originates from an effusion of blood into the lungs without
hæmoptysis, especially after a strain or accidental injury; a
collection of phlegmatic humors form around it by causing pain and
cough, with purulent and bloody expectoration." All of these quotations
show the Hippocratic doctrine distinctly, that the hæmoptysis where it
appeared in a case was mostly the cause of the subsequent phthisis, and
that phthisis ab hæmoptoe was not only one of the most common, but one
of the most dangerous forms.
3 A Practical Historical Treatise on Consumption Diseases,
London, 1815, p. 111.
The doctrine that blood effused into the lungs became pus, and produced
corroding and ulcerating effects, appears in many other prominent
authors between the Hippocratic writings and the nineteenth century.
Celsus4 (30–40 A.C.) says: "Hæmoptysis is one of the causes of
purulent expectoration." Galen5 (131–201 A.C.) says: "Phthisis is
lung ulceration;" and he thinks "that in the greatest number of cases
it originates in a mechanical way, through tearing of the tissue by
means of an outpouring of blood in consequence of a catarrh or strain."
This extract would imply that he thought the hæmoptysis in many cases
secondary, but that when it did occur it had the effect which
Hippocrates attributed to it, that of producing "purulence of the
lungs." Sylvius6 (1614–1672) says: "Hæmoptysis is one of the causes
of purulent expectoration."
4 Young, op. cit., p. 128.
5 Waldenburg, Die Tuberculose, p. 19.
6 Waldenburg, op. cit., p. 28.
Morton's7 (1689) language partly is: "Decantatum istud medicorum
adagium, quod pus sequitur sanguinem;" and then, translated, he says:
"It (the adage) appears to have originated in the fact that 'purulence'
of the lungs, or phthisis pulmonalis, usually follows hæmoptysis more
quickly and oftener than any other disease." In the sentence
immediately following he suggests this result may be due to a
putrefaction of clots that the hæmoptysis has left behind in the lungs,
or to a copious effusion of humors from the whole body to the tender
lungs, or to an erosion of some vessel.
7 Phthisiological Ed., 1727, lib. 111, chap. v. p. 95.
Another theory appears in Hoffmann's language,8 and was probably
suggested, directly or indirectly, by Sylvius's description of
tubercles: "The blood is easily extravasated into the pulmonary
vesicles, stagnates there and putrefies, corrodes the neighboring
parts, and finally destroys the air-passages or they are converted into
nodes or tubercles." The blood becomes tubercularized, and the phthisis
ab hæmoptoe is established. This idea is found at different periods,
and we find a recent French author arguing against this hypothesis.
8 Peter, loc. cit., p. 244; Young, p. 211, Opera;
Hoffmann, Physico-medica, Geneva, 1740.
The reversal of these ideas is generally acknowledged as the results of
Laennec's energy and genius, yet similar opinions to his had been
expressed by French and English physicians. Bayle does not place
phthisis ab hæmoptoe in his classification. Desault,9 one of
Laennec's countrymen, near a hundred years before him, "insists that
tubercles constitute the essence of consumption, being generally
anterior to hæmoptysis." Mudge10 says that hæmoptysis is often the
consequence of the obstruction produced by tubercles. A
preparation for the positive opinions of Laennec is discernible in
these and other authors. His views on this particular topic were
opposed by Andral. The latter modified his earliest expressions to some extent.
9 Young, p. 220, Desault sur les Maladies venériennes, la
Rage et la Phthisic, Bordeaux, 1733.
10 Young, loc. cit., Radical Cure for a Recent Catarrhic
Cough, London, 1779, 2d ed.
The next important historical epoch in the causative relations of
hæmoptysis and phthisis is in the energetic protests of Niemeyer. They
were in some respects a return to the Hippocratic doctrine, in that he
asserted the predominance of hæmoptysis as cause; but he gave the
doctrine a basis better adjusted to a better pathology, in that he made
the important element of inflammatory lesions the medium between the
effusion of blood and the final purulence or ulceration (ulcus
pulmonum) of the ancients. He energetically advocated the doctrine of
the positive effect of effusion of blood in the bronchi or pulmonary
substance in producing disorganization of the lungs, without reference
to any hereditary or predisposing element or existence of tubercles.
Jaccoud11 calls attention to the fact that Graves had anticipated
Niemeyer in the partial revival of the Hippocratic doctrine and the
teachings of Morton and Hoffmann on phthisis ab hæmoptoe.
11 Clinique médicale, vol. ii. p. 302, Graves.
In a recent work12 there is a general adhesion to the modern
modifications of the Hippocratic doctrine in regard to the pathogenetic
relations of hæmoptysis and phthisis. There is a decided rejection of
the causative influence of tubercle in producing hæmoptysis.13 "The
connection between pulmonary hemorrhage and tubercle stands on no
pathological proof;" "From all the evidence I have been able to obtain
on this point, tubercle seems to have been very unjustly credited with
hemorrhage."14 He differs from others in attributing much more to the
hæmophilic constitution in the production of hæmoptysis. Other phases
of the history of hæmoptysis might be given. We shall allude to two
only: one is the classification of the varieties. Alexander of Tralles
treats of hæmoptysis under three heads: 1, Hæmoptysis by rupture; 2, by
erosion; 3, by dilatation. Bricheteau15 makes four divisions: 1,
constitutional; 2, accidental; 3, succedaneous; 4, critical and
symptomatic. These two classifications show in themselves their origin,
in that the one is representative of a local, and the other of a
constitutional, pathogenesis.
12 On Pulmonary Hemorrhage, Reginald E. Thompson, London,
1879.
13 Page 32, op. cit.
14 Page 33, op. cit.
15 Maladies chroniques de l'Appareil respiratoire, Paris,
1851, p. 523.
The last historical phase is the therapeutic one. We find in the
practice of the present day survivals from the ancient authors. Morton
recommended ligatures around the limbs to arrest hemorrhage, and bark
to prevent hæmoptysis from becoming phthisis.16 Venesection, which to
some extent is a modern remedy, was frequently practised by the older
physicians. Erasistratus17 recommended ligatures, applied to the
limbs in several places, to prevent the return of the blood to the
lungs; Asclepiades thought this practice founded on an erroneous
theory, but experience is in its favor. The head should be kept high,
the face wetted with water, the room cool, and the patient perfectly at
rest. Lietaud (1765) is cautious of employing astringents or
purgatives, but recommended ligatures to the limbs and cold to the
scrotum. A drachm of rhubarb was given by Fernelius in hæmoptysis.
Bryan Robinson18 (1752) relates a case in which an emetic of
ipecacuanha, taken three times a week, kept off hæmoptysis for eight
years, while tar-water constantly brought it on. Marryat (1758, London)
"advises two grains of tartarized antimony, and as much of the sulphate
of copper, in half a spoonful of water." Ipecacuanha was frequently
employed in hæmoptysis by the practitioners of the centuries preceding
the nineteenth.
16 Young, pp. 201, 202.
17 Op. cit., p. 128.
18 Op. cit., p. 156, ed. 1660.
As an important preface to the subjects considered in this article we
introduce an account of the vascular supply of the lungs.
Before entering into a statement of the distribution of the
minute vessels to the lungs it is desirable, in view of the possible
diseased connections between the larger bronchial and vascular trunks,
to recall some points of the topographical anatomy of the latter. "The
root of the left lung passes below the arch of the aorta and in front
of the descending aorta. The bronchus, together with the bronchial
arteries and veins, the lymphatics and lymphatic glands, is placed on a
plane posterior to the great blood-vessels. The pulmonary artery lies
more forward than the bronchus, and to a great extent conceals it,
while the pulmonary veins are placed still farther in advance." The
left bronchus "in passing obliquely beneath the arch of the aorta is
depressed below the level of the pulmonary artery, which is the highest
vessel."19 Practically, the chances of abnormal communications lie in
the relations of the aorta, more especially the different parts of the
arch, to the left bronchus and pulmonary artery, and to the trachea, of
the innominate artery to the trachea, and of the glandular structures
at the root of lung to the pulmonary artery.
19 Quain's Anatomy, vol. ii. pp. 897, 898.
The encroachment of aneurism of the subclavian artery on the lung, and
consequent communication between it and the bronchus, is another form
of accidental or extraneous hæmoptysis.
A recognized classification of the vascular systems of the lungs is
into—1st, functional; 2d, nutritive. To the first belong the pulmonary
arteries and veins, and to the second the bronchial arteries and veins.
Both physiological and pathological experience justifies this division.
Notwithstanding the great attention and labor bestowed upon the
circulation of the lungs, there are still unsettled some important
points. We adopt from Küttner20 some of the anatomical data
applicable to our subject. The branches of the pulmonary artery follow
uninterruptedly the bronchial ramifications. The mutual relations of
the artery and bronchus are such that the larger vessel lying in any
preparation of the lung directly next to the bronchus, and running in
the same direction, can be pronounced to be a branch of the pulmonary
artery. In the lungs of the embryo both lie in the same
connective-tissue sheath that originates at the root of the lung,
enters with them into the root of each lobule, and there spreads out.
In the lobules both run not only closely alongside of each other; there
appear also branches of the pulmonary artery on the bronchus itself,
and press on to the mucosa of the same.
20 "Beiträge zur Kentniss der Kreislaups-verhältnisse der
Saugethierlunge," Virchow's Archiv, vol. lxxiii. p. 476, etc.
With the appearance of the terminal bronchiole this relation is
changed. The bronchial artery, as such, ceases; the pulmonary
artery—or rather its lateral branches—exclusively surround the
alveolar diverticulæ on their external surfaces. At the point where the
terminal bronchiole is developed into the infundibula the corresponding
trunk of the pulmonary artery divides into a number of
branches—"pinselförmig;" each infundibulum receives its stem, which
spreads itself after the manner of a feather on its external surface.
The terminal branches of the pulmonary artery cover the terminal
alveoli. On every lung in which the infundibula and lobules are well
distributed the terminal branches of the pulmonary artery extend beyond
the borders of the infundibula and lobules into the interlobular and
subpleural connective tissue, and here either lose themselves in a
capillary distribution or extend to the periphery of an adjoining
acinus, being lost in its capillaries.
One peculiarity of the pulmonary artery is that from a large trunk
relatively fine lateral branches come. From a vessel of 0.136 mm. come
branches of 0.033, 0.016, 0.011, 0.010 mm. The finest disappear
immediately as vasa vasorum; the larger pass to the perivascular or
peribronchial connective tissue and become capillary, or they
appear on the surface of the immediately adjoining lobules and
disappear in the capillary paths of the alveoli.
The terminal branches of one and the same principal artery behave
differently according as they are distributed to the connective tissue
or to the alveoli. In the first case they form wide meshes and narrow
tubes, and are not different from the capillary terminations of the
body in general. In the other case the meshes are narrow; the vessels
in all of the pulmonary capillaries are wide. If these vessels are
followed from their origin to their final termination, it will be seen
that a considerable part of the pulmonary artery is spread in the
interlobular connective tissue; that it is not exclusively a secretory
vessel; that the capillary network of all the lobuli are in anastomotic connection.
An anatomical investigation shows that between the branches of the
pulmonary artery no anastomoses exist. It is, however, proved that
under certain conditions connections between the larger branches of the
artery may occur. This artificial connection is favored through
peculiarities of terminal branching: wherever two parallel branches of
the pulmonary artery are followed, it will be seen that the terminal
branches lie alongside of each other without anastomosis. One can be
convinced of that, and, further, that the capillaries of only one or
two alveoli separate them. These unusually short capillaries between
two arteries are those in which differences of pressure in one or the
other artery produce wide connections. Küttner agrees so far with those
observers who think that between the larger branches of the pulmonary
artery no wide anastomoses exist already formed. In this sense the
pulmonary artery can be designated a terminal artery; on the other
side, however, it must not be forgotten that such connections can arise
at any time, and the artery there loses the type of a so-called
terminal artery.
He further remarks that the vascular-district supply of the pulmonary
artery is not so limited as Cohnheim and Litten believe; that, more
than that, some branches of it pass from one lobule to the adjoining
one; that others are distributed in the subpleural and interlobular
connective tissue and in the bronchial wall.
If the lung of an animal be injected from the pulmonary artery, there
is produced a complete filling of the vessels of the bronchial wall and
into the subepithelial layer—a fact the more interesting that a
similar event can scarcely be produced by a filling of the bronchial artery.
Pulmonary Vein.—Only at the root of the lung do the bronchus,
pulmonary artery, and pulmonary vein lie close to each other. In the
continuance of the same the artery and the bronchus remain close by
each other, but the vein pursues its own course. The branches of the
same are, from the hilus to their capillary termination, situated in
the interlobular connective-tissue paths. They form on the external
margins of the lobules wide blutbuchten, in which the veins of the
infundibula enter with short stems. The artery lies intralobular—the
vein interlobular. The bronchial veins connect not only with branches
of the azygos and superior cava, but also with those of the pulmonary vein.
Bronchial Vessels.—The variety of origin of the bronchial arteries is
notable. Whatever their origin, they follow with their chief trunk the
bronchus into the parenchyma of the lung, and give off insignificant
lateral branches to the connective-tissue layers. There is still
another kind of artery, which divides independently in the connective
tissue of the lungs, without resting on the bronchial walls; they come
from the oesophageal, mediastinal, and pericardial arteries, branch in
the mediastinal pleura, appear with these at the hilus of the lung, and
form partly an independent mesh of pleural arteries, and partly spread
themselves in the interlobular connective tissue.
All the vessels of the serous membranes of the diaphragm can contribute
in many ways blood to the hilus of the lung: the unusually
fine-branched arteries appear in this way to be in condition to
compensate for obstructions (or lesser). The bronchial arteries in
comparison with the other vessels of the lungs give off sparingly
lateral branches; among the most interesting are the branches which
spring directly from the trunks of the bronchial artery, pass through
the peribronchial connective tissue, appear at the adjoining
infundibula, and lose themselves in capillary terminations.
The capillary districts of the bronchial arteries pass immediately into
those of the pulmonary. It is a fact that besides the pulmonary artery
the bronchial artery provides the infundibula and alveoli with blood.
If the bronchial artery springing from the intercostal and internal
mammary arteries be ligated or cut, leaving open the vessels of the
mediastinal pleura, and the lung be injected from the abdominal aorta,
a mere inspection will show a filling of the parenchyma of the lung;
anastomoses between the pleural arteries and the intra-acinous trunks
of the pulmonary arteries can be recognized. There is an anastomotic
connection between the pleural branches of the pulmonary and bronchial arteries.
The bronchial, as also the pulmonary, artery can be filled by means of
the fine arterial branches from the mediastinal pleura.
The principal branches of the bronchial arteries go to the bronchi; at
the alveolar passage they here stop as such; their capillaries become
continuous with those of the pulmonary artery. The greater part of the
few collateral branches nourish the submucous peribronchial and
perivascular connective tissue, the nerves, the lymphatic vessels; the
smaller part enter the alveoli of other bronchial systems and become capillary.
The branches going to the lung with the mediastinal pleura spread
themselves in the pleura and interlobular connective tissue, nourish
the large subpleural and interlobular lymphatic vessels, but lose
themselves in capillary distribution on the alveoli and infundibula.
The pleural and bronchial arteries anastomose partly with each other
and partly with branches of the pulmonary artery.
With reference to the branches of the pulmonary artery going to the
bronchi, it may be said that they, without giving special branches to
the external layer of the bronchi, press on to the basal membrane and
form a compact capillary network in common with the proportionately few
branches of the bronchial artery.
Amidst differences of opinion, as between Küttner, Lalesque, and
Cohnheim and Litten, there is a concurrence as to the chances of
supplementary function by anastomoses between channels that are
ordinarily separate. Küttner admits a modified form of terminal
arrangement in the pulmonary artery, but at the same time claims an
amount of potential connection that is liable to come into actual
operation and suspend, if not destroy, the terminal type.
The correlation of both functional and nutrient vessels is so intimate
that we believe there is no conclusive argument against the actual
transfer of office from one to the other in certain strained conditions
of disease; Virchow's experiment proves it.
The wonderful delicacy and distensibility of the enormous network of
pulmonary vessels (relation of uncovered space in the alveoli to that
covered by the vessels being 50 out of 200, Kuss); their capacity of
response to great variations of supply and tension; the prompt
supplementary function proven by Litten21 to belong to the
tracheo-oesophageal, pericardial, phrenic, and pleuro-mediastinal
arteries, and their equilibrium under the sensitive changes of the
aortic system; the slower submission of the lesser circulation to the
peripheral impressions, which markedly affect the aortic system; the
facts
verified by Lichtheim22 that on closure of any portion of
the pulmonary artery the same quantity of blood will pass through the
portion remaining open as before; that this is brought about through
increase of pressure in the sections still open, and through the
simultaneous increased rapidity of circulation and distension of the
vessel walls; and that this mechanism is able to compensate for
obstruction of three-fourths of the pulmonary artery,—are important
factors in the anatomical and physiological relations of hæmoptysis.
21 "Ueber den Hämorrhagischen Infarct," Zeitschrift für
klinische Medicin.
22 Die Störungen des Lungenkreislaufs, by L. Lichtheim,
Berlin, 1876, p. 65.
ETIOLOGY.—The natural history of hæmoptysis is practically that of
phthisis: exceptions to this will be noted hereafter. As heredity is
largely a determining influence in the latter, it may be assumed that
it qualifies its principal symptoms. More or less uniformity prevails
in the transmission of normal or abnormal conditions, and we seem to
find an illustration of the latter in the correspondence between the
percentages of hereditary phthisis and those of hæmoptysis in such
cases. Reginald Thompson23 says that "out of 1064 cases of
well-marked inherited phthisis, 426 suffered from hæmoptysis." In his
calculation he omitted all those in which the disease began with
hæmoptysis. Had these then been included, they would have raised the
percentage over that shown by the figures, which is slightly above 40.
The rate would not then be much below that given as an average of cases
of hereditary phthisis. This percentage of cases of hæmoptysis in
hereditary phthisis is a sufficiently uniform transmission to prove the
influence of heredity. Its influence is shown not only in the number of
transmissions, but in the transmission of types; so that, as we have a
family type of phthisis, we may have a family type of hæmoptysis, such
as the cases where all the phthisical members of a family are subject
to hæmoptysis of uniform characteristics, instances where the same
uniformity in type is transmitted, and instances where the phthisical
heredity appears to have its survival in moderate and transient attacks
of hemorrhage.
23 The Causes and Results of Pulmonary Hemorrhage, p.
110.
Atavism is also seen in some family histories. We have in view such an
instance, where the marked hæmoptysical tendencies of one generation
skipped the next to reappear in the third.
A special study of the relation of cases of copious hæmoptysis to
different forms of heredity has been made by Reginald Thompson. His
table is as follows:
| |
Age at which attack commenced. |
| Cases. |
5 |
10 |
15 |
20 |
25 |
30 |
35 |
40 |
45 |
50 |
55 |
60 |
65 |
| Mother |
123 |
... |
... |
27 |
30 |
34 |
18 |
8 |
2 |
3 |
1 |
|
|
|
| Father |
102 |
1 |
4 |
16 |
22 |
24 |
19 |
9 |
4 |
1 |
... |
1 |
1 |
|
| Non-hereditary |
105 |
... |
2 |
14 |
20 |
24 |
16 |
12 |
8 |
5 |
2 |
|
|
|
He claims that this table shows that of the cases of direct heredity,
cross-heredity, and non-heredity, those who were the subjects of
cross-heredity—that is, those from the mother—were more liable to
copious hæmoptysis than either the cases of direct heredity or of
non-heredity; and the numbers of the two latter so closely correspond
as to show that heredity from the father has little influence as
regards hemorrhage. The conclusion he draws from the table is that "an
heredity is drawn from the mother which differs from that derived from
the father, and to this must be attributed the excess of cases of
copious hæmoptysis."
This difference will be seen in the following table, which shows
the number of cases occurring before and after thirty:
| Cases. |
Before age of 30. |
After age of 30. |
| Mother |
123 |
91 |
32 |
| Father |
102 |
65 |
37 |
| Non-hereditary |
105 |
60 |
45 |
He thinks the explanation is to be obtained from the statistics of
hæmophilia, which show a large proportion of transmissions from mothers
to sons, and that we have here a strong argument connecting copious
hæmoptysis, not with tubercle, but with hæmophilia.
His next table is one of 125 cases of double heredity, calculated upon
the same basis as the others, that of 400:
| Cases. |
5 |
10 |
15 |
20 |
25 |
30 |
35 |
40 |
45 |
50 |
55 |
60 |
65 |
| Double heredity |
125 |
... |
3 |
20 |
40 |
23 |
15 |
12 |
9 |
1 |
1 |
1 |
|
|
| Calculated to |
400 |
... |
10 |
74 |
128 |
75 |
48 |
37 |
29 |
3 |
3 |
3 |
|
|
which shows a close approximation to the table of cases of
cross-heredity from the mother, and that the calculated number for 400
cases of double heredity are almost identical with that of the actual
number of 400 cases of cross-heredity between the ages of fifteen and
twenty-five—in the first case being 202, in the second 203—and the
calculated number of cases before thirty amount to 287, not quite equal
to actual number for cases of cross-heredity, which is 294. He
concludes that these cases do not show a greater tendency to hemorrhage
than is shown in cases of direct and non-heredity. We may accept these
figures and calculations as important without endorsing the conclusion
which they are intended to sustain—viz. that such hæmoptyses are
essentially of hæmophilic origin. It may be stated as a general opinion
that hæmophilia does not especially manifest itself in pulmonary
hemorrhages, and that hæmophilic families are not specially liable to phthisis.
The hemorrhagic diathesis, as distinguished from the specific bleeders'
heredity, does not often manifest its activity through the lungs, and,
as correlative, phthisis does not often show hemorrhages in other
organs than the lungs.24 Leudet has met in 244 cases of phthisis 9
times hemorrhages in other organs than the lungs; oftenest by the
intestine, the skin, the nasal mucous membrane; more rarely by the
brain and urinary organs; 10 times between the muscles of the abdominal
walls. These considerations suggest that the phthisical hæmoptysis is
distinct from that of hæmophilia or the hemorrhagic diathesis, and has
an independent origin.
24 "Rémarques sur la Diathese hémorrhagique," Mém. Soc. de
la Biologie, 1859, p. 179.
Some facts in regard to the previous diseases of patients admitted into
the Brompton Hospital with phthisis are given in the second medical
report of that institution, which may have a bearing on the special
features, such as hæmoptysis. Among 1973 patients admitted, 275 were
found to have suffered with well-marked attacks of rheumatism, and 16
had acute symptoms of it while in the hospital, making a larger number
than of any other disease, fevers coming next with 238. The connection
of forms of hemorrhage with so-called rheumatism suggests a
possible influence of that kind in favoring hæmoptyses during the
evolution of phthisis. We know of no facts collected with the view of
studying this relation. If such a conclusion were sustained, it would
tend to confirm the view connecting hæmoptysis with hæmophilia or the
hemorrhagic diathesis.
Williams25 gives a statement qualifying the assumption that the
hemorrhagic variety of consumption specially originates in family
predisposition, for in 72 cases out of 1000 tabulated cases of phthisis
family predisposition was present in only 25 instances. This percentage
is scarcely small enough to exclude a predisposition.
25 Pulmonary Consumption, p. 157.
Considering hæmoptysis in this aspect, as a result of heredity, does
not account for all the cases with which we meet. We are surprised
occasionally by the appearance of pulmonary hemorrhage where heredity
of phthisis cannot be traced. Such persons present the aspect of a
vulnerable state; they yield readily to a phthisical invasion. Some of
the so-called cases of phthisis ab hæmoptoe are found in this class,
yet they may have inherited a phthisical predisposition, brought about
by various degenerating influences acting on their ancestors, such as
antihygienic surroundings, bad air, insufficient food, frequent
childbearing, and excessive nursing. The heredity is not in special
symptoms, but in a predisposition which needs only some exciting cause
for a specific symptomatology that may be carried forward to the next generation.
One individual may himself yield to the same degenerating influences,
and live with more or less of an acquired predisposition until similar
exciting causes reveal his specific weakness. Another may find that he
has a phthisis directly acquired from a single attack of severe illness
without the aid of any element of heredity or of the acquired
predisposition. The gradation would then be inherited predisposition,
acquired predisposition, and acquired phthisis. Hæmoptysis may find its
origin in these several relations of heredity. Combined, they represent
the law of uniformity and the law of variation in hereditary
transmissions. If these general observations be correct, they show that
the ordinarily stated percentage of transmission of hæmoptysis in
inherited phthisis does not express the totality of influence operating
in the production of hæmoptysis. Something must be subtracted from the
so-called non-inherited phthisis and added to the inherited form.
When we attempt to express the relation of acquired or non-inherited
phthisis to hæmoptysis, we find no sufficient data. Thompson's table
above given is assumed by him as showing that the influences
superinducing hæmoptysis in the non-hereditary class are equivalent to
the heredity operating through the father, which is quite subordinate.
R. Thompson26 states that out of 1064 of his cases of well-marked
inherited phthisis, 426 had hæmoptysis; of 1016 when phthisis was not
known to be inherited, 558 had hæmoptysis.
26 Loc. cit., p. 110. In a later work Thompson (Family
Phthisis, London, 1884) states that the general effect of the paternal
inheritance is to reduce the number of cases of copious bleeding for
the total period of life, but an excess is observed for the special
period between twenty and twenty-five; that in the inheritance of the
females from the father the number of cases of bleeding is large, the
number of the copious cases being twice as many as the moderate. The
effect of double heredity upon males was to make the cases of copious
bleeding numerous, and that nearly half the total number of cases were
disposed to bleed. In females there was an increase in the number of
cases of moderate amount. As regards acquired phthisis among males,
that hæmoptysis is a well-marked feature, and nearly three-fourths are
cases of copious bleeding; as to acquired phthisis among females, that
the number of cases is considerably smaller, the reduction being marked
in the cases of copious bleeding.
In a collection of cases of phthisis taken from the Cincinnati
Hospital records, amounting to 1266, there were of
| Cases of |
hæmoptysis |
475, |
or 37.51 |
per cent. |
| " |
phthisis, with family history of same |
332 |
|
|
| " |
hæmoptysis in same |
127, |
or 38.25 |
" |
| " |
acquired or non-inherited phthisis |
934 |
|
|
| " |
hæmoptysis in same |
348, |
or 37.25 |
" |
In 10 cases there was a family history of hæmoptysis; that is, of a
general family peculiarity in that direction. These percentages show no
great difference between the relations of inherited and non-inherited
phthisis to hæmoptysis, the inherited exceeding by 1 per cent. that of
the non-inherited form.
Without here attempting a comprehensive statement of what the
predisposition, transmitted or acquired, is, we may mention two
influences of important force—a tendency to fragility of vessels and
to the catarrhal disposition. It is sufficient to speak of the fact
that in no other disease of the lungs than phthisis have we as a common
feature this vascular fragility. It differentiates the disease and the
symptoms. If it appear in any of them, it should at once excite a
suspicion of the phthisical constitution. That it does appear in some
such cases without ulterior effects does not invalidate the general
statement. It may be put down as a part of the phthisical habit
directly concerned in the liability to hæmoptysis. The proof of this
proposition is more clinical than anatomical.
The attempt to prove that it is hæmophilic rests upon the application
of a few histological examinations of hæmophilic vessels to the
phenomena of phthisical hæmoptysis. The assumption of identity has only
the doubtful force of analogy. Histological examinations of the vessels
in the earliest stages of phthisis and hæmoptysis are too rare to
afford sufficient data. In the latter stages the condition is too
complex, because of positive inflammatory and ulcerative processes.
Although alterations in the vessels in the early stage of simple
inflammation cannot be histologically demonstrated, yet they must exist
in order to allow diapedesis. So with early phthisis: in the
pre-hæmoptoic stage the alterations are not demonstrated, yet that such
disorder of function must have accompanying structural change
underlying the phenomena of the initial hæmoptysis is in accordance
with physiological and pathological doctrines, and has much consistent
clinical force. When we presuppose a delicacy of, or injury to, the
blood-vessels of a part, there is the imminence of not only a rupture,
and consequent hemorrhage, but of those changes which, leading through
stasis and congestion, come to be inflammatory, and which affect still
further the vascular structures and adjoining parenchyma.
Besides these changes initiated in the blood-vessels, there are others
of close relation to the phthisical constitution, which begin in the
vulnerable epithelial elements of the bronchial mucous membrane and of
the air-cells. They are the evidences of the dispositio catarrhalis,
which received its name from the old observers, and the validity of
which has been confirmed by modern pathological and clinical researches.
It is responsible for the great susceptibility to catarrhal affections
of the bronchi and air-cells which lays the foundation for chronic
catarrhal pneumonia.
These two elements, of fragility of vessels and of the catarrhal
tendency, are the tangible instruments of heredity. They are also the
factors of the acquired predisposition.
The Vienna Hospital reports, running through more than fifteen years,
and embracing more than 20,000 cases, give as the ages most liable to
hæmoptysis those between eighteen and twenty-nine years. No statistics
as to sex are given.
Of 1266 cases of phthisis27 taken without selection from the
records of the Cincinnati Hospital, there were
| Between |
10 |
and |
20 |
years |
81; |
in this |
class, |
hæmoptysis |
20 |
| " |
20 |
" |
30 |
" |
459; |
" |
" |
" |
208 |
| " |
30 |
" |
40 |
" |
363; |
" |
" |
" |
143 |
| " |
40 |
" |
50 |
" |
191; |
" |
" |
" |
62 |
| " |
50 |
" |
60 |
" |
110; |
" |
" |
" |
28 |
| " |
60 |
" |
70 |
" |
45; |
" |
" |
" |
9 |
| Over |
70 |
" |
7; |
" |
" |
" |
1 |
| Age not stated |
10; |
" |
" |
" |
4 |
| |
1266 |
|
475 |
27 We desire to acknowledge the services of Walter A. Dun,
then a resident physician at the Cincinnati Hospital, in collecting
these cases from the hospital books.
Ware in Mass. Med. Soc. Proc. gives ages in 317 cases:
| 43 |
up to |
|
|
20 |
| 139 |
between |
20 |
and |
30 |
| 77 |
" |
30 |
" |
40 |
Of Pollock's28 351 cases of profuse hæmoptysis,
| 43 |
were under |
20 |
years of |
age. |
| 168 |
between |
20 |
and |
30 |
" |
" |
| 100 |
" |
30 |
" |
40 |
" |
" |
| 40 |
over |
40 |
" |
" |
These figures from widely-different sources testify to the fact that
the greatest number of cases of hæmoptysis occurs between twenty and
thirty years of age, or at least with a variation of only about a year
from those extremes. The possibility of hæmoptysis, if we may judge by
cases reported, lies anywhere between sixteen days of age and the limit
of life. A case of hæmoptysis in a child sixteen days old is alluded to
in Nouv. Dict. de Méd. et de Chirurg.29 The oldest on the list of
the Vienna Hospital reports is seventy-two. In our Cincinnati Hospital
list we have 7 over seventy years. Others have reported cases beyond
these figures.
28 Prognosis in Consumption, p. 311.
29 Vol. xxix. p. 391.
A case of death from pulmonary aneurism and hæmoptysis in a child aged
two and a half years is reported in London Path. Soc. Trans.;30
also one by Powell31 of a child seven months old from a similar
rupture—illustrations of the remark that children are subject not so
much to initial as to terminal hæmoptysis.
30 Vol. ii. p. 35.
31 Med. Times and Gaz., June, 1874.
As to the relations of sex to the amount of hæmoptysis, we have the
Table XI. from the second medical report of the Brompton Hospital:
| |
Males. |
Females. |
Males. |
Females. |
Total. |
| Below drachm j in quantity. |
843 |
700 |
55 |
83 |
1681 |
| From drachm j to drachm iv. |
616 |
482 |
34 |
69 |
1201 |
| From ½ oz. to 4 oz. |
429 |
268 |
13 |
21 |
731 |
| Above 4 oz. |
343 |
153 |
9 |
7 |
512 |
| Entirely absent. |
588 |
193 |
74 |
65 |
920 |
| |
2819 |
1796 |
185 |
245 |
5045 |
These results correspond with the general one stated by Williams,32
that large hemorrhages occurred in 34.76 per cent. of males, and in
only 17.67 per
cent. of females. In the above table, where
quantities of blood above four ounces were noted, the male figure is
more than double that of the female. As regards exemption, it is stated
that of the cases of decided phthisis which had been free from
hæmoptysis, about five-sevenths were males, and under two-sevenths
females. In general it may be said that females are more liable to
small and males to the larger hemorrhages.
32 Treatise on Consumption, p. 156.
Of 268 females in our Cincinnati Hospital list, 44 had
hæmoptysis—about 13 per cent. Of 998 males, 431 had hæmoptysis, or
about 43 per cent.
In the second Brompton Hospital report33 it is stated that "many of
the most violent attacks of this nature (sudden fatal terminations)
have depended on a sudden rise in the temperature." The peculiar
prevalence of hæmoptysis on the coasts of some warm countries has long
since been noted. Archibald Smith,34 in giving his practical
observations on the diseases of Peru, says: "There appears to be a
general predisposition to this disease, hæmoptysis." An intelligent
individual, himself a sufferer while then a resident on the lower
portion of the North American south-western coast, has given me the
same statement. Pasley35 says at least 10 per cent. of the cases of
phthisis in Trinidad which die in the hospital terminate in a profuse
hæmoptysis; the quantity of blood varies from 15 to 70 or 80 ounces,
and the duration of life from the beginning of the hæmoptysis till the
end five to fifteen minutes. Of Ware's cases,36 83 were in winter,
101 in spring, 69 in summer, 102 in autumn, or 185 in autumn and
winter, 170 in spring and summer. In four months of warm weather, June,
July, August, and September, 97 cases; in October, November, December,
and January, 134; in February, March, April, and May, 124—an average
of 129 for the eight cold months, an excess of 32 cases, or about 33
per cent.; in the transition seasons, spring and autumn, 101 and 102.
The highest numbers were in March and November, 38 and 39; lowest
number in June, 18. These are the only figures obtainable as to our
climate, and they do not agree with those given by R. E. Thompson's
table,37 showing the prevalence of hæmoptysis as to months in 1000
well-marked cases:
| Jan., |
Feb., |
Mar., |
Apr., |
May, |
June, |
July, |
Aug., |
Sept., |
Oct., |
Nov., |
Dec., |
| 67 |
61 |
90 |
95 |
112 |
130 |
128 |
64 |
64 |
55 |
81 |
63 |
The summer months of June and July show the largest numbers, and the
months of December, January, and February lesser numbers. The decrease
in August is explained in great measure by the diminution in
attendance. It is possible that other elements of climate besides
temperature may account for this difference between American and
English figures.
33 Page 17.
34 Edinburgh Med. and Surg. Journ., vol. liv., 1840.
35 Brit. Med. Journ., Jan. 10, 1880, p. 53.
36 Mass. Med. Soc., 1860.
37 On Pulmonary Hemorrhages, p. 114.
A more correct opinion as to the effect of altitude is developing.
Archibald Smith38 more than forty years ago testified to the good
effects of removal from the coast to the high sierras of Peru in cases
of phthisis with hæmoptysis. His own instances of great improvement
following removal to high levels, 5000 to 8000 feet, are conclusive. He
also gives instances where renewals of hemorrhagic attacks followed the
return to the coast. It was the custom for physicians to send their
consumptive patients to the sierras without reference to their
hemorrhagic attacks.
38 Loc. cit.
Similar testimony is accumulating in this country. The Colorado regions
are supplying, through their physicians, much material bearing upon the
effect of altitudes on hæmoptysis. H. K. Steele of Denver, Col.,
writes, June, 1883, that "it is the opinion in the profession
generally, and I endorse it, that this country acts beneficially in the
hæmoptysis of phthisical patients." Jacob
Reed, Jr., says39
that not only does the ascent to this altitude (6000 feet) not
predispose to pneumorrhagia in consumptives, but that "hemorrhagic
cases do well here; in most cases the bleedings becoming less frequent,
in many cases ceasing altogether." By letter May, 1883, he says these
cases number between 500 and 600, and he feels justified in the
positive statement that not only does altitude not precipitate
hæmoptysis, but that "those suffering from this symptom are benefited
here, their bleeding becoming less frequent and less in quantity." He
makes an exception of florid cases in active progress or old cavities
waking up to new action.
39 "Altitude in Reference to Pneumorrhagia," an analysis of
70 cases, read at the eighth annual convention of the Colorado Med.
Soc., 1878, p. 66.
Denison,40 after an analysis of 90 cases of hæmoptysis out of 202 of
phthisis, says: "The advantages of high altitudes are pre-eminently for
hemorrhagic cases in the first stage, while hemorrhagic cases with
excavations, especially if the bleeding has been recent and softening
is in progress, should be interdicted from going to great elevations."
40 Rocky Mountain Health Reports, p. 140.
He also quotes Herman Weber41 as recommending "alpine climates, not
only as a prophylactic measure against hæmoptysis, but also as a means
to promote the cure of the effects of the inflammatory processes
resulting from pulmonary hemorrhage."
41 Hæmoptysis as a Cure of Inflammatory Processes and
Phthisis, with Remarks on Treatment.
These statements are sufficient to show that the view formerly
prevalent, and still more or less so, that high altitudes have the
effect of prolonging or favoring hæmoptysis, is not altogether correct.
It should be understood as applying to the extreme heights of 10,000 or
15,000 feet, and that rapidity of transfer and unusual exertion are
necessary and qualifying considerations. Jourdanet42 places the
region of safety in phthisis about the mid-point between the level of
the sea and the snow-line. The preservative level is lower in Alpine
than in American regions. The line of perpetual snow in Mexico being
about 4500 meters, the preservative zone would be 2250 meters. In
Switzerland, where the line of snow marks 2700 meters, the same zone
would be 1350 meters. No such definite limitations are attainable as
regards hæmoptysis, but a correspondence of zones might be conjectured.
42 Influence de la Pression de l'Air, vol. ii. pp. 183,
184, 213.
The belief that pregnancy in some way favors hæmoptysis is a very old
one. It has been more or less accepted by modern writers. Trousseau43
gives his observations to the effect that there are women who during
pregnancy, and others who during nursing, spit blood. His belief was
that such hæmoptyses were not symptomatic of pulmonary tubercle nor of
cardiac disease, but he classifies them as cases of hemorrhagic
deviation. Peter44 speaks of a gravid pulmonary hyperæmia, proven in
part by his determination of increased local temperatures in the lower
intercostal spaces. Some of his cases do not sustain his theories, and
can properly be referred to puerperal accidents, such as emboli in
phlegmasia alba dolens. Such cases as we have met with in connection
with pregnancy or lactation have had hereditary or acquired tendencies
to phthisis. We have under view a case where hæmoptysis always recurs
during pregnancy and where there is a family history of phthisis. A
brother has pulmonary hemorrhages preceded by inflammatory attacks,
which stand in a relation to him corresponding to the pregnant
hyperæmia of the sister. The well-known effects of pregnancy or
prolonged lactation in developing phthisis are a sufficient explanation
of this class of cases.
43 Clinique Medic. Trans., vol. i. p. 531.
44 Leçons de Clinique médicale, vol. ii. p. 664, 2d ed.
Many exciting causes are assigned by patients in explanation of a
dreaded
event, and some are otherwise misinterpreted. Their mode
of action is not intelligible unless we keep in view the anatomical,
physiological, and pathological data heretofore given. Numerous cases
occur where no exciting causes can be found, such as those coming on in
the quietude of sleep. The insidious agencies of the predisposing
causes must be responsible. A study of many cases will show that the
alleged causes have become operative only after a considerable time has
elapsed, during which a congestive or inflammatory condition has
appeared, the expression of a latent tendency. Dancing in a warm room
or speaking long in the open air, followed in twenty-four hours by
bleeding, are such instances. The physical effort was only so far
instrumental as it gave a chance for the development of a potential
diathetic condition. It was not the direct cause. Falls, frights, blows
on the chest, heavy lifting, playing on wind instruments, and emotional
excitement are sufficient to bring on a hemorrhage by direct influence,
and by so increasing arterial tension as to overcome the resistance of
vessels already weak. It is not intended to maintain the impossibility
of rupture of healthy vessels under some circumstances, but the large
provision made in the great distensibility of the pulmonary vessels and
in the supplementary functions already alluded to make it necessary to
be cautious in such admissions. The fact that hemorrhages from the
direct causes are sometimes not followed by phthisical effects does not
necessarily disprove their diathetic origin.
The effect of blows on the chest in producing hæmoptysis and phthisis
has been the subject of medico-legal examinations in suits for damages.
In all of such cases within our knowledge there has been the element of
fright or great emotional excitement, and hence a complexity of
causation. An hereditary tendency to phthisis was also present—a fact
which diminished the force of the plea that the blow was alone
responsible for the injuries to the health of the parties concerned.
Diseases or injuries of the brain may be mentioned as causes of
pulmonary hemorrhage, which may occasionally be shown by hæmoptysis.
Experimental pathology has recently thrown much light on these cases.
(See PULMONARY APOPLEXY, infra.)
It may be worth while, in view of recent researches, to refer to a form
of hæmoptysis closely associated with a newly-discovered parasite,
named Distoma Ringeri,45 after Ringer of Tamsui, Formosa, who
discovered the parasite, but did not at once recognize its etiological
relation to the endemic hæmoptysis. In a post-mortem of a man dead from
rupture of an aortic aneurism he found the parasite lying on the
lung-tissue, probably escaped from a bronchus. There were some small
deposits of tubercle, no cavities, and slight congestion of the lungs.
Manson found that these parasites were associated with a
frequently-recurring hæmoptysis. Baely of Tokio46 discovered the
parasite, probably before any others. It is quite common in North
Formosa and through Japan. Manson says:47 "Endemic hæmoptysis can be
readily diagnosed. There is a history of irregular, intermitting
hæmoptysis, associated with a slight cough, and in the intervals of
more active bleeding the expectoration once or several times a day of
small pellets of viscid, brownish mucus. Examination of a small portion
of the sputum with the microscope at once settles the diagnosis,
sometimes as many as twenty parasites being found in a single field."
Further examination is necessary to determine the manner in which this
parasite produces the hæmoptysis.
45 The Filaria sanguinis hominis and certain New Forms of
Parasitic Disease in India, China, and Warm Countries, p. 134, by
Patrick Manson, Amoy, China.
46 London Lancet, Oct. 2, 1880.
47 Ibid., p. 143.
The association of bacilli tuberculosis with hæmoptysis is proven by a
number of examinations. These will be referred to in their diagnostic
relations at another page. It is not intended here to imply an
etiological relation, because as yet our knowledge does not point
to the blood-vessels as being the special or usual habitat of bacilli
or the place of their most destructive efforts.
Hydatids of the lung are a cause of hæmoptysis which may come from
congestion accompanying their growth, or from their rupture and
consequent opening of blood-vessels.
Before proceeding farther we shall refer more fully than before to the
conditions prepared by heredity, age and sex, etc. for the action of
the exciting causes. The agencies were stated to be the peculiar
vulnerability of the vascular and epithelial structures of the lungs.
When the morbid imminence is reinforced by an infective element, as in
phthisis, certain results follow which make easy the action of the
incidental causes. Because of the enormous vascularity and great
delicacy of structure of the lungs, and their liability to external
influences, slight external irritants in such constitutions produce
more than what follows in other cases. Instead of a transient hyperæmia
or mild catarrhal inflammation, we may have that fluxionary hyperæmia
of which an early outcome is hæmoptysis. Experimental pathology
explains such occurrences by demonstrating that while a normal vessel,
as in the mesentery, will require a pressure of seventy millimeters of
mercury to produce extravasation of its contents, an inflamed one will
not stand more than twenty-five millimeters. If catarrhal pneumonia
proceed in its phthisical form, it adds its elements of danger.
After its early stage of congestion we have the initiative processes
extending from the epithelial structures of the bronchi and alveoli to
the alveolar wall, which becomes thickened. By means of the double
pressure of abundant epithelial and fibrinous products retained within
the alveolar cells, and of the increased growth in the alveolar walls,
obliterative endarteritis and obstruction of blood-supply follow, the
final result of which may be destructive changes opening the way for
softening and ulceration, and consequent hemorrhage.
The same early hyperæmia accompanies the development and growth of
tubercle, whether it come from the bronchioles, the blood-vessels, or
alveolar walls. Trasbot48 says: "A tubercle is found to be developed
along a small artery, most frequently at the angle formed by a terminal
division of the vessel—some around a capillary, around which it forms
a kind of bead, or in the network of an anastomosis, which envelops it
on every side. Vessels are more numerous in the tissues round the
nodules and in the septa or interstices of the large masses than in the
healthy connective tissue: there the vascularity is often so great as
to be mistaken for inflammation."
48 Quoted by Creighton Bevine, Tuberculosis in Man, p.
133.
Hamilton,49 speaking of the formation of tubercle in the alveolar
wall and cavity, says: "Capillary blood-vessels, filled with
blood-corpuscles, are drawn into it, and in this stage are distinctly
visible. They are all much engorged, and occasionally minute
extravasations are visible, the blood-corpuscles being thrown into the
alveolar cavity." The chance of an earlier obliteration of vessels is
greater under these circumstances than where the process begins in any
other structure. The final result is that combination of catarrhal and
tubercular products characteristic of mixed phthisis.
49 The Pathology of Bronchitis, Catarrhal Pneumonia,
Tubercle, etc., 1883.
As increased vascularity accompanies and surrounds the nascent
tubercle, so vascular neo-formations accompany or are intermixed with
the obliterated zone of vessels, as long since described by Guillot and
recently substantially confirmed by Ewart. The former says:50 "There
result numerous and inextricable anastomoses, which extend incessantly,
and of which the whole forms a mass of vessels proportional in extent
to the age of the tubercles and cavities that they entirely surround."
50 L'Expérience, vol. i. p. 553.
There ensues a connection between this system and that forming on
the false pleural membranes, and a supplementary function of supply for
regions outside of the area of obliterated vessels and for walls of
cavities is established. Considering the want of vitality of new
formations generally, it is quite probable that these become sources of
hemorrhage occasionally. Successive extensions of the diseased regions
reduce the amount of this supply, so that the converse
follows—comparative anæmia of the lung involved and diminished
tendency to hæmoptysis in some of its forms.
These observations, involving considerations of predisposition and its
tangible forms, do not apply to the important class of cardiac
hæmoptysis. The factors here are increased venous tension, pulmonary
hyperæmia of mechanical rather than vital origin, sclerosed or
atheromatous vessels, capillary ectasis, and embolic obstruction of the
pulmonary artery with resultant infarction, etc.
SYMPTOMS.—The definition requires that the blood be pure or unmixed,
yet the coarse physical appearances may vary a good deal. The color is
usually a bright red, but may be dark or venous in hue. There is
sufficient inconstancy in color to prevent its being reliable in
distinguishing the special source of the bleeding, though usually the
bright color is of bronchial and the dark of pulmonary origin. If
bright red at the onset, it loses some if not the whole of its
brightness as the attack progresses or is subsiding, sometimes because
of retention in the air-passages. The mass is more or less frothy, and
varies in density and specific gravity, in diffluence or adhesiveness,
the latter quality increasing in proportion to congestive or
inflammatory conditions, whether in the early or later stages. This is
dependent on the increase of the plastic, fibrinous, or reactive
elements in the blood and adjoining tissues. The mass may lie in a
circumscribed or in a splashy form in the bottom of the vessel,
circumstances of distance and force of ejection, as well as of physical
quality, producing the variations. The quantity varies greatly, both as
to the amount at each act of expectoration and as to the amount during
all of them. The whole amount throughout an average attack of initial
hæmoptysis might be placed at about one and a half to two ounces. Such
would be called moderate but decided hemorrhage. The extremes would
range between a teaspoonful and several pounds, and the time consumed
in the attack may vary between the time taken up by one or two
ejections and several months. The intervals between the successive
ejections will vary from a few minutes to twenty-four hours or more in
a case lasting a week. The manner of ejection is sometimes by a single
effort of hawking or throat-scraping or clearing, sometimes by a slight
hacking cough or by a vigorous effort of expulsion; at other times the
outflow is so rapid through the mouth and nostrils that it resembles
vomiting and may suggest a hemorrhage of the stomach.
The effect which a severe attack may have on the patient is often
notable. He becomes pale out of proportion to the amount of blood that
he has lost; the pulse is full, bounding, and corresponds to what is
called the hemorrhagic pulse. This is sometimes due to the mental
shock, but again it is independent of any excitement on the part of the
patient, or of even any sort of constitutional disturbance, as fever.
We have seen it in full development in connection with a profuse
hæmoptysis and a temperature of 105°. It has been noted also as part of
the phenomena of hemorrhage produced by septic influences upon the
vaso-motor system. Walshe's dictum is no doubt true, that there is a
calm and excited variety quoad cardiac action.51 In the former there
is little vascular or mental excitement or debility, and the patient
does not willingly yield to the necessary restraint.
51 Diseases of the Lungs, p. 330.
Feebleness is an accompaniment, sometimes to a degree disproportionate
to the amount of blood lost, and is an element in the shock which the
patient
feels at so unexpected an event. The early part of the
attack is usually without fever. This comes on later as a part of the
reaction phenomena, and becomes then a very important prognostic
symptom. We have known it, however, to range as high as 105° before the
hemorrhage appeared, and without any reduction by a most obstinate
continuance of the depletion.
Many cases occur without premonition. In a proportion there are
symptoms precedent to the outbreak. The significance of these is often
not perceived until the hæmoptysis appears. Certain subjective symptoms
are common. A sense of burning, which is substernal or unilateral,
corresponding to that lung which is then or shall afterward show itself
affected; soreness within the same bounds; dyspnoea, rarely grossly
objective; slight hacking cough for variable periods, and, more
immediately antecedent, a salty taste in the mouth,—are some of these.
They have their origin in a state of hyperæmia or irritation which has
its outcome in catarrhal processes or hemorrhage. Which it may be will
depend on certain predisposing as well as the immediately operative
causes already mentioned.
Of the objective states, some importance may be attached to
characteristics of the individual, such as the brunette complexion,
dark hair and eyes, or to external correspondences with others of the
family known to have been similarly affected.
More than the usual care is necessary in the physical examination,
particularly in the use of percussion. Palpation and auscultation can
be safely applied, but there might be greater difficulty in getting the
patient into a good position for the actual examination. In the
hæmoptysis of incipient phthisis the physical signs most usually found
are deficient expansion and resonance and vesicular murmur at either
apex. These are evidences of causes that had been in operation before
the hæmoptysis, and indicate important physical changes at the region
where they may be found. Yet they do not necessarily indicate that the
bleeding has its origin at that place. Add moist bubbling râles, and
the presumption becomes almost a certainty that you have found the
locality of the hemorrhage. If these subside as the amount of blood
expectorated gets smaller, the inference is still stronger. Successive
increments of physical signs would indicate that the bleeding had been
correctly located and that the lesion which gave origin to it was
progressing. A proportion of cases occur where no physical sign can be
found even after careful examination, so that it happens sometimes that
at the period of most importance for diagnosis physical signs are not
available, and when they are most distinct in the advanced cases the
diagnosis is already established. They may even become embarrassing by
their abundance. The true significance of the physical signs cannot be
determined until the attack has subsided entirely. The termination of
an attack is usually by disappearance of the congestion of which the
symptoms related were the expression. The soreness and oppression
beneath the sternum, the dyspnoea and fever, are relieved. The
persistence of cough would not necessarily augur badly, because there
is apt to be some catarrhal secretion which necessitates it. The
general result is relief. If the termination is to be unfavorable,
there will be an evident increase of constitutional symptoms,
especially of fever, as in the case alluded to above with the high
temperature. There will be a slower return to the pre-hæmoptic state
and an increase of the physical signs, and you may have apparently a
case of phthisis ab hæmoptoe. The impetus in a large majority of cases
is from the constitutional elements which initiated the symptoms,
rather than from the local cause, blood within the air-passages.
Clinical experience proves that there are cases where serious and rapid
injury to the lungs has followed closely upon an hæmoptysis. It is
admissible to classify such as phthisis ab hæmoptoe only, in the sense
that the effusion of blood in the remote parts of the lungs has brought
about catarrhal pneumonia, which in those predisposed
ends in
phthisis. Sommerbrodt's52 experiments proved that the healthy animals
recovered from the catarrhal pneumonia.
52 Virchow's Archiv, vol. lv. p. 192.
To determine the genuineness of any such special case, we should be
able to include inherited or acquired predisposition; to prove priority
of the hæmoptysis to cough, dyspnoea, and fever, and that these
followed soon after the bleeding; and to show that the age at the time
of the occurrence was not the phthisical age. If a direct or mechanical
cause can be found for the bleeding, the proof would be still stronger.
Most of the cases depended on to prove phthisis ab hæmoptoe or
hemorrhagic phthisis (Powell) do not answer to these requirements. In
the 8 cases reported by Sokolowski53 are summarized these features,
and they give strong support to the conception of a phthisis ab
hæmoptoe. The mode of termination by sudden death is by syncope, and
suffocation cannot be said to be very frequent. There have not been
more than 3 suddenly fatal cases (within a half hour) in the Cincinnati
Hospital records in a period of fifteen years: 22 cases are given in
the second medical report of Brompton Hospital, where the cases of
phthisis are very numerous; Powell's table54 has 15 cases, which
happened at the Brompton Hospital between February, 1868, and November,
1870. The cases which we have collected as occurring since that amount
to about 20. T. Williams55 says that of 198 patients who died, 4 died
of profuse hæmoptysis. Thompson56 says that of 383 deaths occurring
in the hospital (Brompton) during three years, 26 were from fatal
bleeding—a percentage ranging between 2 and 6 in the two series.
53 Berlin. klin. Wochenschrift, 30 Sept., 1878.
54 Vol. xxii., Lond. Path. Soc. Tr.
55 Med.-Chir. Trans., vol. liv.
56 Loc. cit., p. 115.
The symptomatology given above is a general one. Looked at with
reference to the varieties of hæmoptysis, the assignment would be to
the earliest or initial attacks. Assuming five varieties—1, the simple
or idiopathic; 2, the congestive; 3, the ulcerative; 4, the cavernous;
5, the extra-pulmonary—it would belong to the simple or to the
congestive form.
Under the first may be included those cases which occur without any
heredity or traceable cause, are not accompanied by fever, soreness,
dyspnoea, or physical signs, and which further observation shows are
not followed by pulmonary disease. Such cases are rare, yet clinical
records afford them. Time is so important an element in the diagnosis
that the presumption would be against such a classification at the time
of the call for treatment. They have probably developed the hemorrhagic
element of phthisis, and by otherwise vigorous constitutions are
protected from its further evolution.
The congestive form is the one with which we most often meet, and is
essentially the expression of the predisposing element mentioned as one
of the agencies of heredity. Unlike the idiopathic variety, it has its
positive symptoms, so familiar to the practitioner. Special clinical
forms, as the hæmoptysis of pregnancy, the so-called vicarious cases,
the earliest attacks in the hemorrhagic variety of phthisis, the
hæmoptysis of plastic bronchitis (which has a phthisical element in
it), that of hydatids of the lung preliminary to the opening of the
hydatid, and probably others, such as cancer of the lung, may be placed
in this category. Hysterical hæmoptysis is a term of doubtful
propriety, because facts show that the tubercular diathesis has close
affinities with the neuropathic heredity,57 and hence that the
hæmoptysis arises from the tubercular and not the neuropathic element.
From this point of view it has its congestive origin, and can be
properly classified under this head.
57 J. Grasset, Brain, vols. vi. and vii.
The ulcerative form is familiar to us in the second stage of phthisis.
It is more subordinated to the constitutional features, fever, hectic,
and debility, to the purulent expectoration, and to the
easily-determined physical signs. Notwithstanding the apparently
increased chance of profuse hemorrhage, the quantity of blood is often
quite small and apt to be accompanied with a mixed sputum. It is not so
florid as in the congestive form. Some of the most copious hemorrhages
in this stage arise from the presence of the hemorrhagic diathesis or
are found in persons of full and plethoric habit. They will recur at
intervals of once or twice a year for many years, and some of them
finally cease, with a remainder of physical signs. The physical signs
usually indicate nothing more than consolidation of the lung for a long
time. They are dulness, bronchophony, bronchial breathing, and mucus or
crackling sounds over a limited area in the upper part of the chest. In
the slow cases of pulmonary fibrosis there is now and then a small
amount of ulcerative action to produce hæmoptysis. We have seen cases
fatal by a suffocating quantity without discovery of the actual source.
In cavernous hæmoptysis there are striking facts which give this class
a great interest. It includes most of the suddenly fatal cases which
shock families or hospital inmates. It comes from rupture of small
aneurisms in the walls of old cavities. A less dangerous form is that
from small granulations or vessels in the walls of recent cavities or
from small vessels in their trabeculæ. The elucidation of hemorrhage
and death from pulmonary aneurism is of the later acquisitions in our
knowledge.58 A distinction between the ulcerative and pulmonary
aneurism forms is not always practicable. A detection of the aneurism
by auscultation has not been recorded, though it is at times quite
large. In the latter form you may have, as in the former, repeated
attacks of hemorrhage before this fatal one. The most decisive
indication in favor of the aneurismal source of the bleeding, besides
frequent and abundant hemorrhage, would be the proofs of a chronic
cavity. In Powell's59 15 cases of fatal hæmoptysis 3 were without
discoverable source; of the other 12, 3 were immediately fatal; in the
remaining 9 the previous attacks of hæmoptysis occurred at periods
varying from eighteen months to two days. The aneurisms were all in the
left lung except 2: 6 occurred in individuals with family histories of
phthisis; 3 with such histories; 2 are negative or doubtful of fatal hæmoptysis.
58 Williams says that Peacock and Fearn of Derby were the
first to record instances of pulmonary aneurism in England. Stark in
his works edited by J. C. Smyth, 4th Lond. ed., 1788, p. 31 (quoted by
Young, loc. cit., p. 331), relates a case of diseased lungs in which
sudden death took place from the bursting of an aneurism of the
pulmonary artery.
59 Vol. xxii., Path. Soc. Trans., London.
We have a table of cases collected from reports made since Powell's—in
all 21. In 10 the aneurisms were in the left lung, 8 were in the right,
and in 3 the place of the aneurism was not designated; 16 were in
males, 4 in females, and 2 not noted. The relation of heredity to
phthisis was not noted, except in 1, which was affirmative. In 2 there
was no previous attack of hæmoptysis. The longest interval between the
first and fatal attack was four years: 7 were immediately fatal. From
both collections we have 33 aneurisms of the pulmonary artery in
cavities, 20 being in the left lung; 10 were in the right. Most of the
aneurisms were situated in the upper lobes, as might naturally be
expected. Powell's opinion was that there were good grounds for saying
that the more chronic and quiescent the cavity, and the more unilateral
the disease—the more nearly, in short, it approached the type of
fibroid phthisis—the more probable it was that the hemorrhage, if it
occurred in any quantity, proceeded from a pulmonary aneurism. Taking
15 cases from our list the duration of which could be fairly named, the
average was about seventeen months. The average duration of Powell's
cases was about twenty-four months. Most of our cases were bilaterally
affected, and only 2 were positively stated to have been of the fibroid
variety. Yet, practically, the clinical features enumerated by
Powell form the best standard by which to determine the source of the
fatal hemorrhage. Copious hæmoptysis, with great chronicity and
quiescence of phthisis and cavernous physical signs, points to aneurism
of the pulmonary artery within the cavity.
In the class of extra-pulmonary hæmoptysis are included those cases of
ulceration and rupture of aneurisms of the aorta and its branches into
some portion of the air-passages, and the necessary discharge of blood
therefrom. Experience justifies a classification of this kind. Cases
have occurred where the pulmonary symptoms and signs have been so
prominent as to have obscured those of the coexistent and causal aortic
aneurism until the fatal hæmoptysis revealed the mistake. Still others
of simultaneous tubercular disease of the lungs and aortic aneurism are
reported. J. W. Ogle60 reports a case where the patient had had cough
for seven years, at first attended with hæmoptysis, dyspnoea, and
palpitation, and afterward consolidation of the left lung, and where
death was produced by rupture of aortic aneurism into the right
bronchus. Bronchitis and pneumonia have been treated without suspecting
the real cause until a similar event occurred. Janeway and Loomis61
also give instances of aortic aneurism and phthisical deposits with
doubtful diagnoses in the same persons. We have seen an instance where
illness began with cough, frothy and then purulent expectoration, then
loss of flesh and strength and pain in side, fever to 102, dulness
below right clavicle, and then a number of large hemorrhages, and
finally a fatal one, all of the hemorrhages depending on an aneurism of
the internal carotid artery discharging into the mouth. The chances of
these irregular clinical associations must, then, be borne in mind.
Careful examination only will enable us to eliminate the doubtful features.
60 Lond. Path. Soc. Trans., vol. xvii. p. 104.
61 N.Y. Med. Rec., vol. vii. p. 304.
In a collection of 33 aortic aneurisms discharged through the
air-passages, 9 had histories of hæmoptysis previous to the last one.
These discharges were more or less copious, and, considering the
physical signs of phthisis obvious in some, and recollecting that
aneurisms were not recognized, the clinical features were such as to
produce if not justify a diagnosis of intrapulmonary hæmoptysis. Of the
33, 16 opened into the left bronchus, 14 into the trachea, 2 into the
right bronchus, and 1 is given without special designation of the point
of communication. Of 2 aneurisms of the arteria innominata, both opened
into the trachea. Aneurisms of the subclavian have also been known to
have discharged through the apex of the lung. These clinical and
anatomical facts point to a large predominance of symptoms and lesions
connected with the left lung where the pulmonary organs are at all
affected. In our own table, while 18 had marked lesions and symptoms
pertaining to the left, only 6 had them connected with the right lung.
These figures are too limited to be decided, but so far as they go they
tend to prove a greater amount of left-lung lesion in extra-pulmonary
than in cavernous hæmoptysis.
So far we have considered the symptoms and classification of phthisical
hæmoptysis. There remain those other forms of pulmonary hæmoptysis
connected with cardiac disease and hemorrhagic infarction. Practically,
these are reduced to the first variety, as cardiac disease is the
question we have most frequently to consider in this connection. We are
justified in assuming the parenchymatous origin of cardiac hæmoptysis,
because it rarely appears until chronic valvular disease has prepared
the way for its occurrence by its well-known degenerative effects on
the pulmonary circulation whereby thrombosis appears, and because at
those advanced periods emboli are often injected into the pulmonary
artery capable of producing hemorrhagic infarction and consequent
hæmoptysis. This latter is accompanied by aggravation of symptoms
already serious—increase of dyspnoea, cardiac perturbation, and
probably cough. If the hemorrhage be copious, shock may appear, and
varies
according to the size of the obstructed vessel and the
amount of hemorrhage. The patient may have some premonitions, but not
of the kind noted in the initial hæmoptysis of phthisis, such as the
superficial soreness, burning, or pain localized in the substernal
regions. The hæmoptysis, after it has begun, continues more regularly,
at shorter intervals, and for a longer time, with the coarse appearance
of the blood already mentioned, such as dark, non-aërated, coagulated
sputum. The quantity may equal that from the most typical bronchial or
broncho-pulmonary hæmoptysis in phthisis; usually it is not copious.
Fever is not an ordinary accompaniment, but may develop in consequence
of increased structural lesion, as from pneumonic infiltration around a
large infarction. It has not then the typical range of ordinary
pneumonia, seldom going beyond 100 or 101. The physical signs exclusive
of the primary cardiac lesion are those pointing to limited
infiltration of lung-tissue about the middle or lower region of the
lung. We have limited areas where percussion is dull, almost as much so
as over pleuritic effusion, and where the respiration is very feeble or
suppressed, and later a bronchial breathing adjoining as a consequence
of pneumonic complication. There may be several of these areas, varying
in size. Sometimes the localization by physical signs is impossible
because of the hemorrhage or infarction being small and deep-seated.
Pain becomes a localizing symptom when the infarction is superficial
and the pleura becomes involved. The form of valvular disease most
likely to produce hæmoptysis is mitral disease, especially mitral
obstruction disease.
Beside infarctions originating in cardiac disease there are others of
peripheral origin, as in the puerperal condition from phlegmasia
dolens. Hæmoptysis is a rare symptom in such cases, but when it does
appear it has the same basis. It is seldom severe, and soon merges into
an expectoration of pneumonic character, with the clinical forms of
embolic pneumonia, or possibly of abscess or gangrene of the lung.
PATHOLOGY.—Incidentally, the pathological relations of hæmoptysis have
been already indicated as being connected with phthisis and cardiac
disease—principally with the former. If phthisis be an infectious or
specific disease, as a large and growing professional opinion claims,
hæmoptysis has its specific relations with it. Few symptoms have
greater differentiating force than it has. Its occurrence, outside of
well-known cardiac or dyscrasic disease, removes any case of primary
pulmonary disease from the category of simple inflammation. There may
be much more congestion in bronchitis, more catarrhal products in
simple catarrhal pneumonia, and more fibrinous or croupous exudation in
pneumonia, than in the primary stages of phthisis, and yet no
hæmoptysis appear. The mechanical conditions are present in greater
degree, but the infective element is wanting. Its closest affinity is
with apex pneumonia or alveolar catarrh, yet probably most of such
cases occur without it. A blood-dyscrasia contributes an important
element in the pathogenesis of hæmoptysis.
In cardiac hæmoptysis the pathology is more simple. Extreme mechanical
conditions of obstruction and reversal of the circulation are
reinforced by nutritive changes of the vessels and heart, until the
so-called cardiac cachexia is established. There is no infective
element, and such cases are seldom if ever followed by phthisical destruction.
MORBID ANATOMY.—Reference has already been made to anatomical changes
having direct or indirect relation to hæmoptysis, such as those in the
blood-vessels. The anatomical basis of the slight hemorrhages of the
early stage of phthisis is seldom if ever discoverable. The belief in
vascular fragility and congestion with special origin rests much more
upon clinical reasoning than demonstration. The large hemorrhages are
now and then fatal within short periods of time or instantly, and we
then have the opportunity of noting the general appearance of the lungs.
It is notable that cases are not very frequent where the source
of the bleeding has not been found by the most careful search. The
general appearance varies according to the length of time that has
elapsed since the bleeding which preceded death.
In the cases immediately fatal the tubes are filled with fresh blood,
which has stained the mucous membrane and has changed the general
surface of the sections of lung into a dark, mottled, or patchy color.
The greater amount of blood is to be found in the lung from which it
has primarily come, but in the more profuse hemorrhages, and
particularly where there has been time for the struggles of the
threatening suffocation, much blood may either overflow or be inhaled
into the other lung and carried into the extreme portions of the
air-sacs. If the flow be not overwhelming, the patient may survive long
enough to allow other effects from the blood, which has by gravitation
or insufflation been carried into certain parts of the lung. We are
indebted to Reginald E. Thompson62 for the most important study of
the secondary effects of the blood thus remaining. He says that the
relics of blood are to be found in the presence of hard nodules, often
deeply, though not always, pigmented. They are mostly found at the
summit and middle part of the upper lobe, the middle axillary region,
between the third and fifth ribs, close to the pleura, the anterior
inferior border, and the middle part of the base corresponding to the
summit of the arch of the diaphragm. "Absorption, decoloration, and
fibrination go on; the outlying portions of the blood disappear; the
central nodules become hard and white, and alone remain to show what
has taken place." They are in some cases of varying color, slight red
or of an ivory white, mottled with old blood-pigment, around the
bronchioles especially, and in the shape of small black granules.
Microscopically, they consist of "a group of alveola firmly packed with
a semi-opaque, homogeneous fibrinous material, and there is some
thickening of the alveolar tissue and also of the interlobular tissue,
which thickened tissue forms the limiting capsule."
62 Op. cit., p. 46, etc. These researches are an important
epoch in the history of hæmoptysis.
The ultimate fate of these nodules is variable. Sometimes they go on to
formation of cavities, or softening occurs around the periphery or in
the centre, and leads to general liquefaction of the nodule, or they
may separate from the surrounding tissue by traction. Sometimes the
effect of retention of the blood in the air-passages is a catarrhal
pneumonia, with the ordinary anatomical proofs of it referred to in the
paragraph on modes of termination of hæmoptysis.
Accepting the observations, we have the demonstration of a phthisis ab
hæmoptoe.
The morbid anatomy of cases fatal from rupture of aneurisms of the
branches of the pulmonary artery has been made prominent by the
researches of Rokitansky and Rasmussen.63 He describes small sac-like
aneurisms and ectasias situated in the vessels running along the wall
of the cavity. The aneurisms have the shape of a bag and an even
surface. The walls of the unbroken aneurisms are of great thickness,
and those of the broken ones thin. The opening is always found on the
most protruding part of the sac; the edges are thin; their size varies
from a pea to a small orange. Powell64 says a microscopic section
taken from a specimen in an early stage shows new connective-tissue
elements, causing induration affecting the whole thickness of the wall
and obscuring the distinction between the coats. The wall is brittle,
becomes thinner from want of support, and yields to an inciting cause,
with rupture and death as the result.
63 Edinburgh Med. Journal, 1868–69.
64 Trans. London Pathological Society, vol. xxii. pp. 54,
55.
The morbid anatomy of cardiac hæmoptysis is found mostly in two
conditions—that of degenerated, atheromatous, varicose blood-vessels,
brought about by the condition of chronic obstruction and increased
venous tension in valvular disease; and in that of pulmonary infarction.
The first prepares the way for diapedesis or rupture, and consequent
hæmoptysis. The rupture takes place in the parenchyma, or, as the
anatomical details formerly given make probable, from the blood-vessels
of the bronchial mucous membrane also.
Pulmonary infarction is recognized by a dark, dense, pyramidal or
wedge-shaped area of varying size situated at the surface of the lung,
with the base of the pyramid coming to the pleura. It is found oftener
in the lower lobes and in multiple form. It is caused by an embolic
obstruction of a terminal branch of the pulmonary artery; sometimes by
a thrombosis or by both. A venous reflux from the neighboring districts
is supposed to fill the empty vessel, and after a certain time has
elapsed changes are supposed to have occurred in their walls by which
the blood escapes into the air-cells and interstitial tissue.
Litten's65 explanation, sustained by his experiments, is that the
venous reflux, after a closure of the pulmonary artery, is by no means
necessary to the formation of an infarction. The infarction fails if
the pulmonary artery and the bronchial artery, and those arteries lying
outside the lungs, but in circulatory connection with them—the
pleural—are simultaneously shut off. If the whole arterial supply be
thus taken away, but a living connection be maintained by means of the
veins, an infarction does not follow, while it immediately follows if,
at the same time with the open veins and closed pulmonary arteries, the
collateral or supplementary circulation be kept free. A venous reflux
cannot occur so long as a circulation in the capillaries of the lung is
sustained by collateral arterial branches. The explanation is that in
an unobstructed circulation the entire resistance which is offered to
the blood-stream in the capillaries of the lung is overcome by the
pressure existing in the pulmonary artery, which, corresponding to the
greater width of the capillaries, is much less than the pressure in the
corporeal arteries. If the pulmonary artery becomes suddenly
impermeable, the pressure in the collateral arteries, which originates
partly from the bronchial artery, and partly from those outside of, but
in connection with, the lungs, as the pleural, etc., is sufficient to
prevent a venous reflux, but not sufficient to overcome the entire
resistance in the lungs and to drive the blood beyond the capillaries
into the left auricle. Then follows an accumulation and stasis of the
blood in the capillaries and smaller veins, and hence results at first
a hyperæmia and later a diapedesis. Litten makes another important
change in Cohnheim's doctrine: he maintains that the hemorrhage appears
before the integrity of the vessel-walls is impaired.
65 Zeitschrift für klin. Med., vol. i. p. 148, Berlin,
1880.
Other fatal cases find their anatomical basis in the softening and
ulcerating processes, which while forming cavities are liable to open
vessels of greater or less size in their walls or trabeculæ.
The condition of the heart in phthisis is one which has an effect in
influencing the occurrence of hæmoptysis. The general statement by
Peacock, that the weight of the heart in phthisis, though less than in
acute diseases, is greater than that in other chronic diseases, needs
to be modified somewhat, as he did not make a distinction between
different forms of phthisis. The more the case approaches the fibroid
variety the more likelihood of some increase of size, particularly in
the right ventricle. Spatz,66 a later authority, gives as the result
of his examination that phthisis diminishes the size of the left
ventricle—that an absolutely compensatory hypertrophy of the right
ventricle, which is apparent in special cases, does not as a rule
exist, although
the resultant decrease does not throughout stand
in relation to the decreased weight and volume of the whole body in
phthisis. The ratio between the depth of the left ventricle and
circumference of the aorta is diminished; and, as this is not
compensated for by hypertrophy of the walls of the ventricle, arterial
tension diminishes and the pulse becomes soft and small. The chance of
rupture of weak vessels by relatively excessive tension is thus much
weakened in the later stages of phthisis.
66 Deutsches Archiv für klinisch Med., vol. xxx. p. 154.
Another element capable of modifying the hæmoptysical features of
phthisis is claimed by Jaccoud67 as existing in the insufficiency of
the tricuspid valve, which compensates the increased tension in the
field of the pulmonary artery arising from obstruction of a
considerable part of it. The amount of blood passing from the right
ventricle is thus, by a reflux, proportioned to the area of obstruction
in the artery, and the tension is reduced so as to prevent rupture of
the weak vessels. His conclusions are based on 18 cases of measurements
of the tricuspid orifice. They varied from 111 to 130 millimeters. The
evidence obtainable during life was a systolic murmur heard at the
ensiform cartilage and cervical venous reflux.
67 Clinique médicale, vol. ii. p. 346, etc.
DIAGNOSIS is mostly called for with regard to the chances of
hæmatemesis. Inspection of the blood is naturally an early point for
attention. Its bright-red color, frothy look, freedom from extraneous
matter, and its coming up by coughing are strong evidences easily
acquired of its pulmonary origin. Corroborative circumstances are the
family history of phthisis or hæmoptysis, the presence of pulmonary, or
in fewer instances of cardiac, physical signs, the immediately
premonitory symptoms spoken of before. Fever, the age of the patient,
and the continuance of the discharge of blood in its later gradations
of color and mixture of catarrhal elements, inspection of the mouth,
fauces, and larynx, would exclude those possible sources. Each has its
limitations, but together they are conclusive as against hæmatemesis.
Recent and accumulating experience attributes some diagnostic value to
the presence of bacilli tuberculosis in the expectorated blood.
Hiller68 reports 6 cases of hæmoptysis in which the blood showed in
bacilli: 3 were completely initial. The bacilli were easily
demonstrated by preparations and also by inoculation on guinea-pigs.
They have also been found in the blood of cases of acute tuberculosis
by Weichselbaum.69 Resort may be had to the well-known tests for the
presence of the elastic tissue of the lung in sputum.
68 Centralblatt für die med. Wissenschaft, March 24,
1883.
69 Wiener med. Wochenschrift, No. 13, 1884.
As positive data for hæmatemesis we have the dark color of the blood,
its firmer clotting, greater density and want of aëration, acid
reaction, the presence of extraneous matters of food and drink, their
ejection by vomiting, and pain or uneasiness at the epigastrium. As
corroborative we have the less frequent occurrence of hæmatemesis, the
individual history of gastric disease, such as ulcer of the stomach or
presence of hepatic cirrhosis from intemperate habits, and the history
of a blow on the abdominal surface: discharges of blood from the bowels
are more likely to occur in hæmatemesis.
Hæmoptysis may be simulated, as by scratches or cuts on some part of
the internal surface of the throat or mouth. The blood is then likely
to be thinned by secretion from the mouth. Inspection would detect the
imposture. The chance of blood from an epistaxis being swallowed and
afterward ejected by vomiting is to be remembered. Cardiac hæmoptysis
is distinguished in most cases by the presence of symptoms and physical
signs of valvular, usually mitral, disease in a considerable degree of
advancement. These are so pronounced as to exclude phthisical disease.
Other and fewer cases occur where the hæmoptysis is the first evidence
of the cardiac disease, and they require a careful exclusion of all the
features of tubercular disease, so as to be able to
arrive at a
correct conclusion. There are no conclusive considerations pertaining
to the amount and character of the blood. In the severe and copious
hemorrhages there is likely to be present a marked shock.
PROGNOSIS.—Hæmoptysis usually implies phthisis existing or imminent,
and yet it has in general a favorable effect on its course. This
applies more to its first stage than subsequently, and more to the
small than to the large hemorrhages. The gravity of the small ones
increases in proportion to their frequency. The family and personal
equation is of more importance than the mere quantity. We may have a
slight hæmoptysis and a large increase of the morbid condition
following it, and the reverse, the result depending on the individual
tolerance of and susceptibility to reaction. As in the second stage the
reactive elements are more potent, the small hemorrhages then are less
beneficial. They are the index of activity in the destructive lesions,
and yet may relieve the accompanying congestion. The easiest
appreciable symptom of the progress of the disease is the fever. We may
fail to properly interpret physical signs because of want of
familiarity with the individual case before us. If besides more fever
there be more cough, dyspnoea, and debility, the prognosis increases in
gravity. These remarks will apply with more force to the large
hemorrhages than the smaller ones, and are guides for prognosis in all
the clinical forms of hæmoptysis. In the special clinical form, the
hemorrhagic variety of phthisis, bleedings recur often and in large
quantities during years, and some of the cases end with final recovery.
The fever and constitutional irritation give way under seemingly very
unfavorable conditions. The fact that a great part of them have no
history of heredity, and that they come on at a late period of life,
may account for this, because they thus escape the influences which
heredity and age are known to impose upon the other classes of
phthisical subjects. Some interesting conclusions have been drawn from
the history of cases of profuse hemorrhages. Pollock70 thinks that
they shorten the duration of the first stage and lengthen the duration
of the second and third. Out of his 351 cases, 204 occurred in the
first three months of illness: 45 had remained in the first stage when
examined, 142 having undergone softening, while 164 had cavities. Of
286 cases of profuse hæmoptysis classified by Williams,71 the number
of cases in the first stage was 187, and the percentage of deaths was
13.95; 65 cases were in the second stage, and the percentage of deaths
was 24.61; 31 were in the third stage, and the percentage of deaths was
67.74, showing increased effect of hemorrhages upon pulmonary
structures advancing in destructive processes and upon constitutions
being progressively undermined by them. In other clinical varieties the
symptom is so clearly subordinated to the general process that it loses
its prognostic importance in the established disease. There is an
imminence of fatal hemorrhage in many of them, as in fibroid phthisis,
cancer, abscess, gangrene, and hemorrhagic infarction of the lungs. In
extra-pulmonary hæmoptysis or in that from rupture of pulmonary
aneurism there is seldom opportunity for prognosis.
70 Elements of Prognosis in Consumption, p. 139.
71 Pulmonary Consumption, p. 150.
If the condition be recognized, we can but say that the fatal attack is
liable to come at any moment. In cardiac hæmoptysis the hemorrhage is
an event coming toward the close of organic and obstructive changes
which are not much within our control. There are minor degrees, as
shown by expectoration of single small masses of dark coagulated blood
and by the absence of marked aggravation of the symptoms, which do not
prognosticate unfavorably for the immediate, but do show impending
dangers of a future, attack. Morbid anatomy shows traces of a recovery
from a number of premonitory threatenings. The elements of a serious
prognosis are the appearance of a shock, increased dyspnoea, a large
amount of hæmoptysis, increased perturbations in the heart-action, and
increased areas of dulness or râles at certain parts of
the lung
other than the usual sites of consumptive disease. These and other
evidences of constitutional initiation are not as available as in the
other varieties mentioned.
TREATMENT.—In the cases of the mildest form very little more need be
done than to keep the patient quiet. His apprehensions may require
attention. They may be allayed by assuring him that the hemorrhage will
be more of a security than a danger, because it is the expression of a
local congestion that will be relieved by the discharge. We have found
that a large dose of quinine (ten or fifteen grains) will answer the
double purpose of a nervous sedative and of controlling the congestion
and hemorrhage if the latter object be necessary. This suggestion
becomes still more applicable in the severe forms of hæmoptysis. The
dose may be repeated within twenty-four hours if needed. If congestion
be manifested by its symptoms of substernal heat, soreness, oppression,
dyspnoea, and cough to a greater degree, and if the hemorrhage is
becoming copious and the hemorrhagic pulse developed, and the
temperature elevated, the necessity of a more active interference is
evident. Absolute quiet in bed, fresh air, a calm and equable behavior
on the part of the family or friends in attendance so that no
excitement may be reflected to the patient, are essential. The
medicines selected should be such as may control the vascular
excitement, and hæmostatics. Ergot will fulfil such indications. It has
its limitations in its unpleasant taste, but it should be pushed to the
points of tolerance. Of the fluid extract one teaspoonful should be
given every hour or two until some effect is observed in slowing the
pulse or checking the hemorrhage. If the stomach rebel, ergotin pills
may be substituted in doses of three to five grains at the same
interval. Should all the resources of ergot medication be required or
the above mode of use fail or disagree, hypodermic injections may be
added. Two to three grains of the extract of ergotin would form a
proper dose, to be repeated every one or two hours. It has been quite
the exception in our experience to have serious irritation follow the
use of it in this way. Failure in this and other uses of ergot will
follow because we do not administer it with sufficient freedom.72
Another most valuable hæmostatic is turpentine. It should also be given
freely. From ten to thirty drops in an emulsion or in sugar may be
given every two to four hours, according to tolerance and to the
threatening character of the case. The ergot and turpentine are best
alternated at intervals of one to three hours, according to the
requirements of the attack. Some preparation of opium is often required
to quiet cough—morphine or codeine, one-fourth grain of the former and
one-half grain of the latter, repeated at intervals until their effects
are obvious. By adding the use of broken ice and the external
application of cold compresses frequently repeated, and, if time and
strength permit, the inhalation of persulphate of iron spray twenty or
thirty minims in half an ounce of water, we get a plan of treatment
adapted to the urgent cases. Some recent reports have confirmed the
confidence of the ancients in the use of ligatures. They may be applied
to both lower limbs. A dozen dry cups may be applied to the chest.
There is no occasion or time for the use of many medicines, but if a
general plan, such as the above, must be changed, acetate of lead in
doses of two grains every two hours would be an excellent substitute,
due regard being had to the possible toxic effects from too long
continuance of it in such doses; it is usual to add a little opium to
it. Gallic acid is an effectual remedy for the control of different
kinds of hemorrhages. Like ergot, it is usually given in too small
quantities. Twenty to thirty grains must be given every two to four
hours.
It is better borne by the stomach, and can often be
continued longer, than the medicines above mentioned.
72 A medical friend, T. C. Minor of Cincinnati, has in his
own case used three or four drachms of the fluid at a dose, with the
effect of reducing his pulse twenty beats in a few hours.
We have already noted ipecacuanha as one of the survivals of ancient
practice. It has had warm advocates among modern physicians. Graves
places vivisection first and ipecacuanha next in his plan of treatment.
Trousseau strongly recommended it. Peter and the French practitioners
also strongly endorse its use in the severe forms. We have no doubt of
its efficacy. It is important to exclude if possible the existence of a
pulmonary aneurism or any such source of blooding, as there are no
special means by which this can be done. It is a good rule to use the
ipecacuanha in the cases of early or first-stage hæmoptyses. We would
give it as it is given in dysentery. Precede its administration half an
hour with thirty drops of laudanum, then give ten grains in water. If
vomiting comes on, repeat it in an hour, and again, if hemorrhage
continue, in two hours. The usual experience is that tolerance is
established after two or three doses. It has also an application in
small doses of one-quarter to one-half a grain in the milder forms,
with irritative cough and slight fever.
Graves calls attention especially to the excellent effect of opium in
all kinds of passive hemorrhage, hæmoptysis as well, but insists that
it should be given only after vivisection has been performed or when
the hæmoptysis has become rather passive, or in scorbutic and similar
cases. His direction on one occasion to a physician, in a case of
protracted bleeding of the gums, was, "Go home and give two grains of
opium immediately, and then half a grain every hour until the bleeding
stops." A combination applicable to the persistent bleeding recurring
day by day is the sulphate of magnesia made soluble in rose-water by
the free use of dilute sulphuric acid—one teaspoonful of the former,
fifteen drops of the acid, one-half to one ounce of the rose or plain
water. Many other remedies might be mentioned, and among them atropia.
After the bleeding has ceased it is necessary to be assured as to the
condition in which the lung has been left, and to counteract, if
needed, any persistence of irritation. Fever is the most valuable
evidence as to this point. If it exist, the use of quinia and ergot had
better be continued freely. A three-grain ergotin pill about three
times daily, and five grains of quinia morning and evening, can be
tolerated two or three weeks. Local irritation should be applied if
physical signs or pain warrants it.
DEFINITION.—Escape of blood into the pulmonary parenchyma, with
laceration of its substance.
SYNONYMS.—Hemorrhage (pulmonaire) foyer (Jaccoud); Diffuse pulmonary
apoplexy or Diffuse pneumorrhagia (Fleich); Diffuse pulmonary apoplexy
(Loomis); Pneumo-hemorrhagie (Gendrin), etc.
HISTORY.—Latour1 is quoted as being the first to use the words,
"apoplexie du poumon."2 Yet Duguet3 also quotes from Frank that
Dolocus had a long time before employed it. It is known that cases had
been described long before this, as by Corvisart in 1808, Allan Burnes
in 1809, among those of this century, and by Prosper Martiano, Bonet,
Morgagni, Haller, etc., among the more ancient authors.4 Again,
Laennec gives the weight of his authority, and establishes Latour's use
of the name, until, as the synonyms show, modern usage has almost
abandoned it. Among the multitude of those who have treated of
pulmonary apoplexy, we will have filled the requirements of this brief
historical statement by mentioning Virchow and his pathological
investigations into embolism, and also Cohnheim,5 and later
Litten's6 studies on infarction, which have some indirect connection
with pulmonary apoplexy.
1 Histoire philosophique et médicale des Hémorrhagies,
1815, passage misquoted in L'apoplexie pulmonaire by Duguet.
2 Op. cit., pp. 220, 222, and 224.
3 Op. cit., p. 11.
4 Duguet, p. 10, etc.
5 Untersuchungen über die Embolischen processe, 1872.
6 Zeitschrift für klinisch Medicin, Erster Band, 131.
ETIOLOGY.—Predisposing Causes.—The male sex affords predominance of
cases, because of greater liability to accidents, to the various forms
of ulcerative destruction of lung-tissue, and to aneurisms of the aorta
and pulmonary artery.
The adult age is most exposed for similar reasons. Ogston's
statistics7 support in a general way, but not with strictly technical
force, their quotation by Herz.8 Omitting the last 4 of his 20 cases
(2 of which were from poisoning, 1 from fracture of skull by a fall
down stairs, and 1 from drowning), the average for males (12) was 56.4,
and 55.3 for females (4).
7 Brit. and For. Med.-Chir. Rev., vol. xxxvii., 1866, p.
459.
8 Ziemssen's Handbook, vol. v. p. 298. Ogston says (p.
465) it did not appear, however, that any distinct rent of their
substance had taken place—to any extent, at least. "When we consider
that the area of the extravasation was sufficient to involve often one
or two entire lobes, and that death was in most of them very sudden,
the cases may be adopted as showing the action of causes similar in
kind, if not in degree, to those operative in undoubted pulmonary
apoplexy."
As more efficient predisposing causes than either age or sex, may be
mentioned aneurisms of the aorta and pulmonary artery, amyloid
degeneration of bronchial and pulmonary vessels, the influence of
Bright's disease in producing disease of blood-vessels, and
atheromatous diseases of the pulmonary artery.
Exciting Causes.—Penetrating and contused wounds of the chest by their
direct mechanical effect, and diseases and injuries of the brain
through the medium of the nervous system, may produce pulmonary
apoplexy, the result in the latter case being usually an infiltration
or small infarction.
SYMPTOMATOLOGY.—Pulmonary apoplexy is the least common of the two
forms of distinctive pulmonary hemorrhage, the other being pulmonary
infarction, already treated of under HÆMOPTYSIS. A proportion of cases
is associated with mitral disease in its most advanced stages. At that
time we may expect pneumorrhagia, but whether from infarction or
apoplectic laceration even the event can only occasionally determine.
In the latter, if hemorrhage makes its appearance it will be copious
and generally overwhelming; at other times the hemorrhage may not
appear, and the patient dies suddenly with possibly other indications
of the internal flow. The physical signs cannot be relied on, for often
the pulmonary tissue is already changed by the long-continued
obstruction of circulation. Rupture of aneurism, particularly of aorta,
in the great majority of cases takes place into a bronchus, and not
into the parenchyma. In case of wounds of the contused variety a
laceration of parenchyma occurs at times sufficient to produce marked
hæmoptysis. If the blood be not ejected, there are no certain
indications of what has happened. If the case be seen immediately after
the accident, such physical signs as moist bubbling râles on the margin
of an area of feeble or suppressed vesicular murmur, possibly attended
with a dull, high-pitched percussion note over that area, would afford
a strong presumption in favor of ruptured lung and consequent hemorrhage.
The same signs later might be due to a limited traumatic pneumonia. If
the internal hemorrhage, whether traumatic or spontaneous, has made its
way through the pleura, then, if the patient live long enough for
examination, besides such symptoms as great oppression and exhaustion,
the physical signs peculiar to pleural effusion may appear to a limited
degree. This opportunity seldom occurs, as such a rupture produces
almost invariably a fulminant and rapidly fatal result.
COURSE, DURATION, AND TERMINATION.—The course of the lighter cases is
much like that of pulmonary infarction, and that of the severe forms
too brief for observation. As to termination, it is quite possible
there are cases of laceration so limited as to allow complete recovery,
but clinical experience shows that pulmonary apoplexy is usually fatal.
PATHOLOGY AND MORBID ANATOMY.—With branches of the pulmonary vessels
weakened by long-continued heart disease, or with such vessels as are
found with chronic nephritis, a sudden increase of tension in them from
unusual effort or excitement will precipitate a fatal rupture.
Sometimes the progress of the degeneration is so insidious and complete
that a rupture may occur without obvious exciting cause. This is also
the natural history of aortic aneurism. An examination soon after the
laceration will show a mass of blood, usually coagulated, sometimes
partly fluid, lying in an irregular cavity with walls of the lacerated
lung-tissue. After a longer time the lung-tissue beyond the walls of
the hemorrhagic focus becomes oedematous to a certain extent. A
contraction of the cavity, with change of contents, may proceed to the
extent that an encapsuled mass of very small size will remain as the
final result (Rokitansky).
DIAGNOSIS from bronchial hemorrhage by the probable existence of
phthisical conditions and history. The quantity of blood ejected may be
profuse in either case, and therefore be no criterion. From pulmonary
infarction, as the other form of pulmonary hemorrhage, by the larger
amount of hæmoptysis. If there be no hæmoptysis, a presumption would
exist in favor of apoplexy in case of extreme dyspnoea or a fatal
result. The associated diseases or causes being similar, no inference
from the medical history would be reliable except in case of injuries.
PROGNOSIS.—As we meet with it in recognizable form, the result
is almost invariably fatal. A qualification is allowed because of the
experience of such a pathologist as Rokitansky, who describes a process
of cure in a few cases. The prognosis in such would be determined
partly by the severity of the antecedent or accompanying disease, as in
heart lesions, and partly by the increased respiratory distress, pain,
exhaustion, and hemorrhage.
TREATMENT.—As has been before intimated, a case of pulmonary apoplexy
distinctive enough to be diagnosed is usually one that is beyond the
reach of treatment. Remedies that may relieve dyspnoea, exhaustion, and
hemorrhage are those to be relied on. External irritants, as
turpentine-stupe stimulants, ergot, turpentine internally, and such
other remedies as are of known effect in the treatment of the
associated heart troubles and of the incidental pulmonary infarctions.
DEFINITION.—A circumscribed suppuration of the lung, resulting in a cavity.
SYNONYMS.—Abcés du poumon; Lungenabscess.
HISTORY.—The ancients described abscess of the lung, and placed it
among the terminations of the inflammation of that organ. They believed
that if the inflammation did not resolve itself by the fourteenth or
twenty-first day its termination was to be by suppuration. Hippocrates,
Van Swieten, and others are mentioned among those who maintained these
views and consequent frequency of such cases which prevailed until
physical methods and pathological investigation proved their
incorrectness. J. P. Frank, Bayle, and Cayol1 are given credit for a
partial reversal of this opinion. Avenbrugger,2 a pupil of Van
Swieten, in describing vomicæ, divides them into two kinds—the
ichorous and the purulent. By the purulent vomica he means an encysted
abscess of the chest resulting from the conversion of an inflamed spot
into a white, thick, glutinous, fatty matter. When these communicate
with the bronchi and discharge any of their contents by expectoration,
they are called open; otherwise, close or shut. He gives symptoms and
signs belonging to the respective varieties. Corvisart, in his comments
on these propositions, says: "In fact, the purulent vomica is always
the result of an inflammation, more or less acute, of the lung." He
makes distinctions between the various kinds of purulent vomica and the
ichorous vomica. Laennec, as in many other subjects of which he
treated, has the credit of placing this one on its modern basis, at
least so far as the frequent termination of pneumonia in abscess is
concerned. Among English writers Stokes deserves especial mention.
Abscess was the fifth and the last of the stages of pneumonia,
according to his classification. He treated largely of the perforating
abscess. Traube, Trousseau, and Leyden are among those who have
contributed largely to the elucidation of the subject. The latter has
especially claimed for this subject a more prominent place in the
literature of practical medicine, and has strongly enforced his views.
1 Nouv. Dict. de Méd. et de Chirurgie, tome xxix. p. 394;
and Leyden, "Ueber Lungenabscess," Sammlung klinische Vorträge, von
Richard Volkmann, Nos. 114, 115.
2 On Percussion of the Chest, a translation of
Avenbrugger's original treatise by John Forbes, with comment by
Corvisart, 1761–1808, pp. 38, 43, etc.
ETIOLOGY.—Predisposing Causes.—Everything tending to debilitate the
constitution may become a factor in the production of abscess of the
lung. Senile constitutions, Bright's disease, chronic alcoholism,
diabetes mellitus, and insanity are some of the predisposing causes.
Exciting Causes.—These may be divided, as in the case of gangrene,
into the pulmonary, or those originating in the lung or pleura, and the
intra-pulmonary, or those originating outside of the lung or pleura.
Among the former are included pneumonia and empyema, perforating and
discharging into the
lung, or one variety of Stokes's perforating
abscess, pulmonary apoplexy, and suppurating bronchial glands, opening
up a passage through the lung and bronchial tube. Either croupous or
catarrhal pneumonia may be associated with or terminate in pneumonia.
Among the latter, or extra-pulmonary class are included cases of
embolism from the right heart, producing infarction, or from the
systemic veins. These emboli carry with them the productive capacity of
suppuration. Abscess external to thoracic walls, as in deep-seated
mastitis, will at times perforate the walls and enter the lung.
Abscesses of the liver not infrequently perforate the diaphragm, and
are discharged through the lung.
Foreign bodies in the bronchi may ulcerate through them and produce
suppuration of the lung, which may finally open a way externally
through the chest-walls.
SYMPTOMATOLOGY.—The symptoms of abscess of the lung, as may be
inferred from the enumeration of causes, are divisible into two
categories—one including those symptoms with which the abscess may be
associated, but which do not necessarily prognosticate it; and the
other including the symptoms which indicate the abscess as a fact
accomplished. In the simplest and most frequent clinical form, that
following pneumonia, the early symptoms would be those of a severe and
irregular form, as shown by very troublesome and uncontrollable cough
or unusual pain or respiratory embarrassment, high fever, but at that
time fairly typical pneumonic temperature, great prostration, etc.
These may all diminish in due time, and mostly do without suppuration
following. A return of pain, dyspnoea, fever, and general distress
should awaken suspicion, yet they may be the result of an extension of
pneumonia to other portions of the lungs. Rigors and sweats and
increased depression would point to a suppurative process and under
such circumstances to the lung as the locality. We cannot, then,
positively predict an abscess. It is suspected when a more or less
copious eruption of purulent discharge occurs suddenly, and sometimes
the discharge is so abundant and pus-like that any other alternative
than abscess is very remote; at other times the discharge is small in
quantity. The proof of physical cavernous signs is the final step. This
is often difficult. A slightly greater increase of lung-density,
probably at the middle or upper part, with imperfect bronchial
breathing, the appearance of a few moist râles or crepitus, the gradual
increase of these and merging into coarser crepitus, and revelation of
more or less of the cavity signs, is the physical history of many cases
of abscess of the lung. Others have a much more pronounced course, such
as the cases of so-called gangrenous abscess—a sort of connecting link
between gangrene and abscess of the lung. The breaking down of tissue
is ostensibly very sudden, and the cavernous signs are very soon
unmistakable. Other clinical forms are the pyæmia, to be distinguished
by the antecedent history, which will reveal a source for infectious
emboli. The abscesses are usually multiple and small, so that their
precise locality cannot be made out. The proof of infectious
transportation is sudden pneumonic symptoms, as pain, tinged and
finally purulent expectoration. Rupture into pleura may occur and
produce empyema. Rupture of hepatic abscess and discharge through the
lungs is also a clinical form shown by this antecedent event, pointing
to hepatic inflammation. The egress of the pus is sometimes through a
narrow track, and not by a reservoir within the pulmonary tissue; at
other times the lung is really excavated. The discharge of pus is
usually copious and paroxysmal. Leyden recognizes as his third class a
form of chronic abscess, or one coming on during a case of chronic
pneumonia and bearing great resemblance to a variety of phthisis. Its
general symptoms are much the same as in the acute variety,
differentiated by the element of time.
COURSE.—It may be said, in a general way, that the etiology has much
to
do with its course. If the cause be pneumonia, the course will
be such as the detail of symptoms already given shows. In some unknown
way the natural course of the disease is interrupted, and what promises
to be an average case is followed by the characteristic features of
abscess. If pyæmia be the precedent condition, a peculiar form of
pneumonia, embolic in origin, appears, and abscesses again follow.
Greater septicity and rapidity of destruction are probable sequences.
The perforating abscesses are subject to modifying influences of
mechanical effect, such as gravitation and the resistance of tissues,
and have their peculiar course, which is often marked by great chronicity.
TERMINATION.—In the course of seventeen years the reports of the
Cincinnati Hospital show that there have been 6 cases of abscess of the
lung treated there. Of these 4 died and 2 were discharged as improved.
These figures show the infrequency of such cases, and also represent a
greater mortality than probably occurs in the non-hospital class. We
know of no large statistics which show what is the percentage of
recoveries. Our own experience in private practice gives a majority of
recoveries. They were cases following typhoid fever, croupous and
catarrhal pneumonia, and hepatic abscess. A termination in a chronic
cavity now and then happens: perforation of the pleural cavity, with
subsequent pyo-pneumothorax, discharge externally through an
intercostal space, or even extension into the abdominal cavity, are
among the actual events of such abscesses.
DURATION.—The duration of an ordinary case is subject to wide
variations between one and six months. A few cases are recorded of
several years' duration. Previous constitutional condition has much to
do with this element. The degree of infectiousness in the pyæmic class
is important as to time. The abscesses become a subordinate condition
in the fate of the case. In this connection we may also refer to
Leyden's third variety, a so-called chronic abscess.
PATHOLOGY.—A close parallelism, etiologically and otherwise, is
observable up to certain points between gangrene and abscess of the
lung. Both are products of, or associated with, pneumonia. That which
finally determines whether the result shall be gangrene or abscess is
unknown to us. In the article on GANGRENE OF THE LUNG some
investigations are referred to which point to a probable solution in
the existence of specific forms having special pathogenetic force. The
tendency of experimental and clinical investigations is to connect the
suppurative process closely with the product of specific germs. Ogston
in 65 cases of acute abscess found micrococci present in all of them.
Obstruction of blood-vessels in the centre of the pneumonic area or on
the margin of the abscess walls is an important anatomical element in
the production of abscess, and it is claimed that it is often due to
colonies of micrococci within their calibre; so that it is probable
that there are both mechanical and biological or chemical influences at
work. If the view of the zymotic and infectious character of pneumonia
be tenable, the contingency of an abscess developing in its course
would seem not very remote. Yet the proportion of cases of abscess from
pneumonia is not more than 2 per cent. Leyden's high authority supports
the idea of the essential and specific differences in the chemical and
morphological peculiarities of gangrene and abscess of the lung, but
the subject is as yet on a hypothetical basis.
MORBID ANATOMY.—The fresh cavity, generally in the upper lobe, has
rough, ragged, and irregular walls, and may have bridles of the more
resistant structures, as bronchi and vessels, crossing it. Such a
cavity is quite likely to contain portions of undissolved parenchyma or
more or less malodorous pus. The older cavity becomes smoother walled,
and of more regular limits and cleaner contents. A gradation from
granular hepatization through congested to crepitant tissue is almost
uniform in the varieties of abscess, whether simple or pyæmic. In
addition, some peculiarities are observable in the latter. These are
usually several, varying in size from a pea or less to a walnut, some
round and others wedge-shaped; others lying superficially and forming
slight elevations on the pleural surface. In proportion to the curative
progress the cavity will contract and disappear, occasionally leaving
behind a cicatricial mark. A lining pus-secreting membrane will
sometimes form, resulting in such a limitation of morbid action and
such a disappearance of reactionary symptoms as to make the disease
entirely local, but quite chronic.
DIAGNOSIS.—The more or less sudden and copious expectoration of pus,
without a specially offensive odor, in the course of a case having up
to that time the history of a pneumonia, would be considered as due to
the development of an abscess in the lung. Some degree of fetor in
breath and expectoration is observed, but it is far different from that
of gangrene. The detection of the débris of lung-structure in coarse
particles, and the microscopic discovery of elastic lung-tissue, are
important diagnostic points in contradistinction from the solution of
tissue that gangrene usually effects upon the parenchyma of the lung.
According to Leyden's3 very complete investigations, the microscope
reveals fatty crystals, mostly in roundish fragments, of the size of
the epithelium of the lung and of a brilliant structure; pigment-débris
of a yellowish-brown or brownish-red color; hæmatoidin and bilirubin,
which Traube thought were due to hemorrhagic infarction, but which
Leyden has observed in all of his cases; and, lastly, micrococci, in
the well-known form of the round, granular micrococci colonies, which
differ from those in gangrenous fragments in that they show very little
movement and do not give the iodine reaction.
3 "Ueber Lungenabscess," Volkmann's klin. Vorträge, p.
994.
Difficulties of diagnosis arise in the case of an empyema discharging
through the bronchi, or of an encysted empyema discharging through the
third or fourth intercostal space in front; also, between abscess of
the superior portion of the liver and one in the base of the lung, or
between the latter and a pyo-pneumothorax. Very careful study of the
history in each case is of the first importance. Where this is not
attainable the difficulty is often much increased. In the case of the
empyema the discharge is more profuse at each time, the whole amount in
a given period is much greater, and the time of opening is much delayed
beyond that of the pneumonic abscess. Trousseau gives the case of a
child who brought up for more than six months 200 grammes of pus daily.
He makes children an exception to the rule as to the late opening of
the pleural abscesses. In the encysted empyema discharging either
internally or externally the difficulties are greater. A portion of the
lung-tissue may be so near behind the deposit of matter as to make the
physical signs confusing if the pus has opened externally. Some of
these and of the interlobular deposits it is almost impossible to diagnose.
In hepatic abscess opening into the lung and bronchi the discharge is
copious, dirty brown, paroxysmal, and will generally, on careful
observation, show the bile color or its chemical reactions or some
microscopic débris of the liver. In Leyden's third class, or the
chronic abscess arising in the course of chronic pneumonia, the history
is so much like that of some forms of phthisis as scarcely to serve in
diagnosis. He thinks there are some macroscopic and microscopic
appearances which may serve for diagnosis. There are in the
expectoration dark and compact pieces of greenish-black color, not
unlike plugs of pus, and larger, black-pigmented fragments of
parenchyma, from a pin's head to a hempseed in size. Microscopically,
they consist of a close and strongly-pigmented parenchyma, which seldom
reveals alveolar structure. They show fatty degeneration and
cholesterin plates. This class of cases is mostly without fever. The
application of the bacilli-tuberculosis test would seem to offer some
assistance in diagnosis.
PROGNOSIS.—A grave prognosis may be formulated if there be a
history of feeble constitution, and especially if it be further
impaired by habits of intemperance, if the patient belong to either
extreme of age, if there has been a recent debauch, or if there be wide
variation from the typical form of pneumonia. Variations will be shown
in such a complexus of symptoms as follows: fever of low grade, subject
to extremes in range; feeble and frequent pulse, but not so marked as
in gangrene of the lung; dyspnoea, objective and subjective; typhoid
depression; tongue dryish; delirium; copious and fetid or difficult
expectoration; physical signs of extensive lesion, such as a large
cavity with a large outlying pneumonic area. A favorable prognosis
would be conditioned on the appearance of a fewer number of these
symptoms or on their evolution in a milder form.
The capacity of the patient to endure a long-continued suppurative
discharge is principally determined by his natural vigor and his
ability to assimilate food, other elements, such as extent of injury to
the lung, being the same. A well-defined superficial cavity would be
more favorable, because within surgical relief.
In the pyæmic variety the force of the infectious element will
determine largely the result. Chills and sweats are important
prognostic elements in such a case.
In the secondary abscesses of either the empyematous or hepatic variety
prognosis is grave—more so in the latter than in the former, because
surgical procedure would be more promising in the former, and because
of the implication of an organ so liable to destructive inflammation as
the liver. A long and tedious course of suppuration is possible in
either. The dangers in an established abscess arise from liabilities to
septic infection and exhaustion consequent on want of reparative power
and persistent suppuration.
TREATMENT.—The treatment of abscess differs little if at all from that
of gangrene of the lung. The tendencies of the two diseases toward
exhaustion and infection are similar, but are less pronounced in the
former. The same remedies are necessary in both, such as stimulants,
tonics, antiseptics, anodynes, and expectorants internally, inhalations
and drainage externally; brandy and malt liquors as stimulants;
nourishing and concentrated food at frequent intervals; quinine as
tonic and antiseptic; carbolic acid and turpentine as most valuable
antiseptics (the latter being also an excellent stimulant); eucalyptus
in cases of profuse as well as fetid discharge; carbonate of ammonia,
senega, as expectorants; morphine and codeine or anodynes to control
cough; carbolic acid for inhalation; and in cases of definitely
localized cavities a free opening to be made with antiseptic injections.
Successful cases of surgical interference are reported, and such
treatment is now recognized as proper when the system is giving way
under septic poison, evinced in chills, sweats, and great prostration,
where the purulent discharge is fitful and imperfect, and where the
physical signs are clear enough to show the locality of the abscess.
DEFINITION.—Putrid necrosis of the lung-tissue.
SYNONYMS.—Lungenbrand, Gangrene du poumon, Gangræna pulmonum.
HISTORY.—By common consent, Laennec has the credit of first
identifying, naming, and classifying gangrene of the lung as a distinct
disease; yet Lieutaud1 in 1707 describes imperfectly a case of
gangrene of the lung in a child: "the right lung, within and without,
appeared entirely putrid." Bayle2 is considered, in his section on
his fourth variety of phthisis (phthisis ulcereuse), to have described
a rather chronic form of gangrene of the lung. Morgagni, Boerhaave,
Stoll, J. Frank, and Cullen considered gangrene as one of the
terminations of peripneumonia.3 Laennec's development of the subject
has only in a few directions been enlarged. His classification is
universally adopted. His description is adopted generally as the most
complete. There have been, however, controversies on different points,
such as the relation of pneumonia and of the obstruction of the vessels
to gangrene of the lung.
1 Historia Anatomica Medica, 1787, Obs. 329, cited by
Louisa Atkins, 1872.
2 Bayle, G. L., Recherches sur la Phthisis pulmonaire,
1809–10, p. 30.
3 I. Straus, Nouv. Dict. de Méd. et de Chir., p. 403,
etc.
In the pathology and etiology of gangrene Virchow's investigations on
embolism and thrombosis opened up important relations; in diagnosis,
Traube and Leyden and Jaffee; in medical treatment, also Traube; and in
surgical treatment, Haley and Lawson (1879),4 S. C. Smith (1880), E.
Bull (1881), Fengar and Hollister (1881), Mosler and Voght (1882). The
antecedent development of pulmonary surgery, through important work
done by Mosler, Pepper, and others, had prepared the way for special
applications of it to gangrene and abscess of the lung. Spencer Wells
claims to have suggested similar proceedings nearly forty years ago.
4 Lungen Chirurgie, Mosler, xx. p. 67.
ETIOLOGY.—Predisposing Causes.—Constitutional weakness is a common
predisposing influence: it may be a primary condition, but is more
often secondary or dependent on some recently-acting debilitating
cause, as typhoid fever, chronic lung disease, diabetes, etc. Chronic
alcoholism is a cause which, besides its effect on the system at large,
may add a special one on the lungs in producing hyperæmia or drunkard's pneumonia.
Of 46 cases we have collected mostly from the Vienna Hospital report,
the youngest was nineteen years old and the oldest was forty-seven
years. Lebert5 has collected altogether 60 cases, 32 of his own and
28 of others: 19 occurred between twenty and thirty years, and 1
between thirty and forty. Huntington6 gives 32 cases from the
Massachusetts General Hospital Record between 1857 and 1875: 9 were
between twenty and thirty years, and 12 between thirty and forty; the
youngest was ten years old and the oldest sixty-four. It is noticeable
that these figures coincide largely with those
showing the
incidence of phthisis. Louisa Atkins7 gives, as the youngest ages
among all the varieties, one of three months and another of two months.
5 Klinik der Brustkrankheiten, vol. i. p. 827.
6 Boston Med. and Surg. Journal, vol. xcv. p. 486.
7 Gangræna Pulmonum bei Kindern, 1872.
Of the 46 Vienna Hospital cases, 43 were male and 3 female.
Huntington's cases were males 24, females 8. Of Lebert's own 32 cases,
22 were males; of the 32 others summarized by him, in 4 sex was not
mentioned, and of the remainder 17 were males and 11 females. These
figures show the large predominance of males in the liability to attack.
Exciting Causes.—They may be classified as pulmonary and
extra-pulmonary. The influence of the alcoholic habit has been referred
to above among predisposing causes: debauches are a frequent
antecedent, especially in hospital cases, by means of resulting
pulmonary hyperæmia and drunkard's pneumonia. Its association with
croupous pneumonia may be assumed as settled after some warm disputes.
The pneumonia of Bright's disease and putrid bronchitis are
occasionally causative; bronchiectasies result in it not unfrequently.
Extension of diphtheritic inflammation from the tracheal and bronchial
mucous membrane is another form. The catarrhal pneumonia secondary to
measles may produce it in children.
Embolism is the most frequent cause in the class of extra-pulmonary
causes. It may be mechanical or infecting. A bronchial artery may be
plugged so as to produce a gangrenous slough from mechanical cutting
off of nutrition. Embolism of the pulmonary artery branches is more
frequent, and by bringing about infarction and apoplexy may produce
gangrene. Of the infecting variety may be mentioned emboli from the
peripheral veins, as in surgical or uterine phlebitis, or from cerebral
sinuses secondarily involved from otitis. Other causes acting from
without on the lungs are foreign bodies, as particles of food passing
beyond the trachea into the lungs, as in case of the insane or
drunkards, and blows on the walls of the chest. These latter are
capable of producing not only the ordinary phenomena of
contusion-pneumonia8 but gangrene, and without evidence of external
injury or fracture of the ribs.
8 M. Litten, p. 26, vol. v., Zeitschrift für klinische
Medicin.
SYMPTOMATOLOGY.—Gangrene of the lung is the termination of a process
the beginning and progress of which are not declared or cannot be
followed through characteristic symptoms. Even its final occurrence may
remain unknown if a communication be not established with a bronchus,
which event is followed by the true symptoms, the expectoration and its
odor. Whatever symptoms occur previous to that event may occur
independent of it. Adopting Lebert's dictum,9 gangrene of the lung is
not a pathological unit. As its pathogenesis varies, so does its
symptomatology. A feature common to its several varieties is marked
constitutional depression and variations from the typical form of the
disease in which it occurs. If pneumonia, croupous or catarrhal, be the
precedent or associated disease, it will be marked by soft and feeble
and frequent pulse, restlessness, dulness or distress of countenance,
more or less cyanosis, cool and relaxed skin, possibly delirium, dry
tongue, unusual dyspnoea and pleuritic pain, copious prune-juice
expectoration, irregular or non-typical temperatures. Along with these
functional variations occur some in physical signs, as a lesser amount
of dulness or of bronchial breathing, indicative of less structural
density and corresponding exudation. A case with such an evolution may
afford a presumption of an outcome in gangrene, but appearance of the
characteristic expectoration and fetor is necessary to exclude it from
irregular forms of pneumonia, which have no such termination. The same
general remark applies to the cases of gangrene in bronchiectasic
cavities. Perhaps some aggravation of the general condition may excite
apprehension, but the characteristic phenomena of expectoration, odor,
etc. must decide. If the cause be of embolic origin, we
may
expect some suddenness and perhaps shock in the beginning, and later
the evidences of a more limited inflammation of the lung-tissue, such
as circumscribed dulness and modified respiratory sound, which finally
end in those indicating destruction of lung-tissue.
9 Op. cit., p. 803.
The macroscopic characters of the expectoration are those of a putrid
or fetid liquid of varying shades of color, ashy gray, dirty green, or
greenish-yellow, prune-juice, or more or less hemorrhagic. The odor,
which is at first so fetid and penetrating, often disappears after the
expectoration has been standing a while. It is separable, as first
described by Traube,10 into three principal layers. The uppermost,
covered with a layer of foam, consists of, first, dirty green,
crumbling, confluent lumps; second, of larger, homogeneous, green
muco-purulent masses; and, third, of whitish-gray, transparent, mucous
masses. The second layer is formed of a colorless fluid. At the bottom
is a fine yellowish-white sediment. Microscopically are found fat-acid
crystals, many large fat-drops, and finely granular débris, masses of
free, black pigment. It is said elastic tissue is nowhere to be found,
but to this statement there are no doubt exceptions. Other bodies have
been found by Leyden and Jaffee,11 which they named Leptothrix
pulmonalis. Kannenberg,12 besides the above forms, found constantly
infusoria of the family of monads in the sputa of 11 out of 14 cases of
pulmonary gangrene. He considers them peculiar to the processes of
decomposition in the lungs.
10 Gesammte Beiträge zur Pathologie und Physiologie,
Zweiter Band, p. 452, etc.
11 Deutsches Archiv für klin. Med., Band ii. pp. 488,
etc., "Ueber putride Sputa."
12 Virchow's Archiv, Band lxxv.; Zeitschrift für
klinische Med., Band i. p. 228.
PROGNOSIS in general is unfavorable. Individually, the gravity of the
case is determined by the evidence bearing on previous habits and
constitution; by the violence of the onset, as shown in prostration,
severe pain in the chest, dyspnoea, persistent and violent cough,
delirium, feebleness and softness of the pulse; by the variations from
the typical standards of croupous, or especially catarrhal, pneumonia,
such as greater amount of septic or infectious or typhoidal element,
non-typical and low temperatures in the early stages and also in the
stage of disintegration; by the amount of the latter as shown in the
physical signs of extensive lesion and in the amount of gangrenous
sputum; and by the irritant effect of this in producing bronchial
catarrh, and consequent catarrhal secretion, which may of itself become
an element of danger in a system already much prostrated. Favorable
prognosis is allowable when these conditions are being gradually reversed.
PATHOLOGY.—The pathology of gangrene of the lung is scarcely more
settled than it was forty years ago, when Stokes13 published his
eighteen propositions, embodying his experience. Obstruction of vessels
and inflammatory exudations are present as important pathological
conditions, but of themselves are not pathogenetic of gangrene. Other,
as yet unknown, elements of putrefactive agency are present. Leyden and
Jaffee's observations and those of Kannenberg have been mentioned14
as efforts to throw light upon the pathogenesis of gangrene of lung,
but how far the bodies described by them precede, coincide, or follow
the familiar clinical phenomena are undetermined questions.
Filehne,15 in his experiments to determine the reason of the almost
universal absence of elastic fibres in the expectoration of patients
with gangrene of lung, comes to the conclusion that there is a ferment
which, acting under alkaline conditions, destroys the fibres. The
agents of this ferment he does not try to determine. Stokes anticipates
the tendency of modern experimental pathology by announcing as an
alternative proposition that "a process of putrefactive secretion
precedes in many cases the death of lung." The constitutional debility
which is so early a symptom prepares the way for such
an
invasion. In reference to the relation between the septic material and
thrombosis in gangrene, Kohler16 affirms that the septic material
produces the fibrin-ferment, and thereby capillary thrombosis.
Recklinghausen thinks that a special material capable of exciting
coagulation has not yet been found in gangrenous substances, but that
there may be several factors, such as anæmia, changes in the
vessel-wall, imbibition with foreign substances, etc. Other
experiments17 and views point toward the conclusion that there are
substances formed in various diseased conditions which have the power
of ferments and of producing coagulation of blood in the lesser circulation.
13 Dublin Quarterly Journal Med. Science, Feb. 1, 1850.
14 Op. cit.
15 "Sitzungsbericht der Phys. Med. Soc." in Erlangen
Schmidt's Jahrbucher, 1877, No. 7.
16 Recklinghausen's Handbuch der Pathologie, p. 136.
17 Wooldridge, Du Bois-Reymond, Archiv Centralblatt für
med. Wissenschaften, No. 41, vol. xi. 1874, p. 734.
MORBID ANATOMY.—The circumscribed variety, as it usually appears, is a
cavity irregular in outline, with ragged walls, made so by the unequal
invasion of the lung-tissue by the gangrenous process. Sometimes the
cavity itself contains loose fragments of lung-tissue, or the contents
may be of a dirty, greenish, or brownish color, with some of the odor
of the expectorated matters. If the case has been a chronic one, the
walls are smoother, with a more or less formed lining membrane and the
contents of a less characteristic color or odor. The cavity is usually
in the right lung, and in the middle or lower portion. There is much
variety of statement on this point. The tissue immediately adjacent to
the gangrenous walls shows more or less of the products of catarrhal
pneumonia. The vessels terminating in the walls are obstructed by
coagula. If the gangrenous part come to the pleural surface, belonging
to what Fournet calls the superficial variety, it may produce adhesions
there, or it may result in perforation, with the result that we have
the products of pleuritic inflammation united with the contents of the
gangrenous cavity. In multiple foci, some will show the less advanced
stages of disease, such as incomplete softening and local inflammatory
lesions. In the diffused variety the lesions are sometimes described as
being the same except in extent. The demarcations, however, from
surrounding tissue are not as well marked; the tissue is soft, breaking
easily under pressure, sometimes oedematous, dark or dirty black on
surface or on section of lung; at other times the surface is mottled
with lighter-colored patches. A secondary result is the production of
bronchitis by the contact of the irritant expectoration from the
gangrenous cavity.
DIAGNOSIS.—Abscess of the lung is the disease most likely to be
confounded with gangrene of the lung. In the former you do not have the
same amount of profound constitutional depression; the symptoms have a
more frank expression, as it were, because of better precedent
conditions usually; the first eruption of matter from the abscess is
more copious and sudden than the usual manner of expectoration of
gangrenous sputum; the appearance of the contents of the abscess is
that more nearly of healthy pus, though the latter has at times a dark
dirty brown or hemorrhagic look; the separation into layers is not apt
to occur; the odor is usually not so fetid; microscopically, elastic
fibres are much more abundant in abscess than in gangrene of the lung.
The cavernous physical signs are not reliable in either disease. There
are cases in which it is impossible, and in which it is of no practical
importance, to make a diagnosis between gangrenous abscess and
pulmonary gangrene. Gangrene supervening in phthisical cavities is
distinguished by the history of a chronic pulmonary disease in which a
cavity has been previously marked. It is phthisis advanced to the
destruction of tissue plus the unknown gangrenous element which has
found a lodgment in a favorable place. Stagnation of cavity contents,
depression of system, etc. are favoring conditions. The same remarks
apply to bronchiectasic cavities and putrid bronchitis, physical signs
in the latter being additional points of difference.
Our experience proves that the essential SYMPTOMATOLOGY of
gangrene of lung, except the débris of lung-structure in the sputum,
can occur where there was no gangrenous destruction, either
circumscribed or diffuse, no bronchiectasic cavities or bronchial
dilatations, and no phthisical cavity. In the case alluded to the
gangrenous odor and general characters of the sputum and the separation
into layers and the consolidation of tissue were present, but the
post-mortem afforded no explanation of the fetid expectoration. It was
a case of debauch and alcoholic excesses and exposure.
COURSE, DURATION, AND TERMINATION.—The course of this disease is
essentially an acute one. Whatever the early condition be, the
gangrenous element hastens its progress, as in cases beginning with the
phenomena of acute pleuro-pneumonia. A pre-existing phthisical cavity
will take on acute phases, also the septic element will be reinforced,
and, as indicated in the enumeration of symptoms, clinical
irregularities will be introduced. The early prostration is increased,
and the patient dies from exhaustion after a period varying from three
days to six weeks from the time the gangrene became manifest. Various
complications, such as pleuritis and perforation of pleura and
pneumothorax, hemorrhage, or extensive, diffused gangrene may cut short
the patient's life within the average period. Occasionally the
gangrenous cavity becomes chronic and the patient may live for months
in imperfect health. The termination of the circumscribed variety is
usually death. Diffuse gangrene is invariably fatal.
TREATMENT should be directed, first, to the known precedent states of
constitutional weakness, bad habits, etc., which lay a foundation for
unhealthy inflammatory processes, and for the pathogenetic elements
that bring about the gangrenous and septic and exhausting conditions;
second, to the special symptoms, such as severe pain in the side,
harassing cough, dyspnoea, etc. Remedies of the first class are quinia,
turpentine, early alcoholic stimulation, carbonate of ammonium,
antiseptics, as carbolic acid, etc. An anticipation from the beginning
of any irregular form of acute pulmonary disease of its termination in
gangrene is impossible, and hence early treatment is necessarily
general. It would be properly confined to the use of quinia, which
would be useful, either before or after the gangrenous element had
developed, in small doses frequently given, unless high temperature or
the septic process indicate the use of large ones. Turpentine
internally is desirable in proportion to the infectious or typhoidal
character of the attack. Its use by inhalation is beneficial when
gangrenous destruction has already taken place. Brandy or whiskey in
moderate and frequent quantities, one-half to one tablespoonful every
three hours, and carbonate of ammonium, meet the requirements which the
tendencies to debility indicate. Milk, milk-punch, beef and chicken
extracts should be given in the intervals between the administration of
medicines. This general plan is applicable throughout the pre- and
post-gangrenous stages. In the symptomatic treatment pain and a general
respiratory distress often demand attention. Opium is then useful, both
in relieving pain and moderating dyspnoea and cough. As these symptoms
are often urgent in the later stages of gangrene of the lung, the
treatment of the disease harmonizes both in its constitutional and
symptomatic aspects. Prescriptions can also be readily prepared which
contain remedies that have a decided effect in correcting the fetor of
the breath and expectoration, and thus evincing an influence on the
putrefactive process or ferment, which has become the prominent feature
of the disease. The author recommends that carbolic acid, in the dose
of one grain every four hours, be given for that purpose, and also its
use by inhalation. Assistance can sometimes be given by putting the
patient in such a position on the side as to promote the emptying of
the cavity.
Tapping a gangrenous cavity and the introduction of drainage-tubes may
be successfully resorted to. The cases suitable for such surgical
treatment have
been described by Fenger and Hollister18 as
those where, "the presence of a gangrenous or ichorous cavity having
been ascertained, it is found that notwithstanding an outlet through
the bronchi for a portion of the contents of the cavity, it steadily
fills up again; the partial evacuation does not relieve the patient;
the infection of the healthy portions of the lung from the decomposed
contents of the cavity has commenced or is evidently about to take
place; the breath and expectoration continue fetid; absence of
appetite; increasing weakness, with or without fever, etc." For the
steps of the operative procedure reference may be made to the complete
directions given by the same authors or to works on surgery. The double
opening advised by the above authors would be the most efficient plan.
18 Amer. Journ. Med. Sci., Oct., 1881, p. 385.
BY ALFRED L. LOOMIS, M.D.
SYNONYMS.—English and American: Acute sthenic exudative pneumonia;
Primary lobar pneumonia; Vera peripneumonia; and Pneumonitis. Fr.
Fluxion du poitine and Fièvre pneumonique; Ger. Pneumonia lobaris and
Lobäre Lungenentzündung.
DEFINITION.—Croupous pneumonia is an acute general disease with a
characteristic local pulmonary lesion. Anatomically considered, it is
an acute inflammation of the vesicular structure of the lungs,
resulting in infiltration of the alveoli, with inflammatory products,
which renders them impervious to air. This condition is known as hepatization.
HISTORY.—Until the time of Laennec, pneumonia and pleurisy were
described as one disease. Hippocrates said that pleurisy was "a disease
quickly fatal, and characterized by sputa of various colors." Although
these two diseases were undifferentiated, accurate descriptions of the
lesions and objective signs of pneumonia have come to us from the
earliest medical writers.1
1 Thucydides, The Plague at Athens, B.C. 430.
Much of the early history of this disease is interwoven with the
detailed accounts of a great variety of pulmonary symptoms which
occurred in the epidemics and plagues which prevailed in Eastern Europe
in the centuries just preceding the Christian era, and in Western and
Southern Europe during the sixteenth and seventeenth centuries. The
black death has been regarded by some as an epidemic of pneumonia.
While it is probable that in most of these epidemics the lung was early
involved, and that its implication hastened death, yet no proof exists
to sustain the belief that they were other than epidemics of typhus
fever, dysentery, and those (as yet unknown) fevers which collectively
were named plagues. That many of these plagues were complicated by
pneumonia there is scarcely room for doubt.
French investigators were the first to separate the pneumonic process
from all other morbid processes which occur in the thoracic organs.
Valsalva, Morgagni, and Boerhaave gave accurate descriptions of
pneumonia, but they did not sharply distinguish it from pleurisy.
Bichat and Pinel separated collapse of the lung attending pleuritic
effusion from inflammation of the lung-substance.2 Laennec was the
first to draw the line sharply between pneumonia and pleurisy, and to
him, more than to any other observer, is due the credit of describing
pneumonia as a distinct disease. With his labors begins a new era in
the history of pulmonary inflammations.
2 Nos. phil., ii., Pinel.
Grisolle's work3 is especially valuable in statistics relating to the
climatic element in the development of pneumonia and its comparative
frequency among different races. The elaborate treatise on the
geographical distribution of pneumonia by Ziemssen has furnished data
for a more accurate knowledge of its geographical boundaries. Following
in the footsteps of Laennec, Chomel, Stokes, Addison, and many
laborers of our own day have furnished the material from which the
clinical and pathological history of pneumonia is now being constructed.
3 Traité de la Pneumonie.
Recently, Jürgensen has strongly advocated the infection theory of
pneumonia, and has presented strong arguments in support of his
opinions. Sturges of London and Cohnheim4 advocate the use of the
term pneumonic fever, and the former gives a most interesting general
comparison between it and the affections which he regards analogous to
it. Careful pathological experiments have recently been made by
Heidenhain, Sommerbrodt, Schuppel, and Klebs5 with a view to
establish the germ-theory of pneumonia.
4 Leçons de Chir. méd., 1877, p. 17.
5 Arch. für experiment. Pathol., p. 420.
The literature of the past ten years is richer in the development of
facts and experimental investigations than all the centuries that have
preceded; and these recent experiments, combined with modern statistics
and the results of the microscope in pathological histology, have given
to croupous pneumonia a separate and distinct place in the list of
pulmonary diseases.
MORBID ANATOMY.—Anatomically as well as clinically, there are three
recognized stages in croupous pneumonia: 1, Stage of engorgement or
congestion; 2, Stage of red hepatization; 3, Stage of gray
hepatization, resolution, or purulent infiltration (suppuration).
It has been claimed that the stage of engorgement is preceded by a dry
stage, or "stage of arterial injection," in which the lung-tissue is
dry and of a bright-red color. It is evident that congestion of the
minute branches of the pulmonary artery would not give to the
lung-tissue a bright-red color, and if such a condition exists it must
be due to injection of the bronchial vessels. It is by no means proven
that such injection ever precedes pneumonic engorgement. In the stage
of engorgement that portion of the lung which is involved in the
pneumonic process does not collapse when the thoracic cavity is opened.
The affected portion of lung is distended and firmer than normal
lung-tissue, and when pressed upon crepitates less, often remaining
indented after the pressure is removed. The lung is not entirely
airless, for by pressure the air can be forced from one portion of it
to another. Its color is darker than normal, usually being of a
brownish-red or purple. There is an increase not only in its actual
weight, but in its specific gravity. On section a thin, frothy,
blood-stained serum exudes, and sometimes on pressure flows freely from
the cut surface; occasionally this exudation is tenacious. When alcohol
is added to this fluid, it coagulates into a granular, amorphous mass.
The capillaries around the air-cells are distended, and dark blood
oozes from their divided ends. Occasionally, upon close examination,
there may be seen beneath the pleura and between the air-sacs small
points of blood-extravasation. A portion of lung in this stage, when
placed in water, does not float as near the surface as healthy lung-tissue.
When examined with the microscope, the lumen of the alveoli are seen to
be diminished by the encroachment of the varicosed and tortuous
capillary vessels. As a rule, the air-sacs are uniformly dilated; some,
however, may be collapsed—a condition probably due to pressure during
the early period of the pneumonic process. The epithelia of the alveoli
are swollen, and contain a granular protoplasm with free nuclei. The
air-vesicles also contain exfoliated epithelial cells and white and red
blood-corpuscles. The serum which escapes into the alveoli from the
distended capillary vessels is the fluid in which these cell-elements
float. Since the enlarged epithelia often suffer a division of their
protoplasm, embryonic mono-nucleated cells are intermingled with the
other elements. It is still a disputed question whether the bronchial
or the pulmonary capillaries are the chief source of the pneumonic exudation.
Physiology teaches that lung-tissue is nourished by the blood in the
ramifications of the bronchial arteries, and that the pulmonary
capillaries are the passive media for the interchange of gases. Hence
it is claimed that the bronchial capillaries only are implicated in the
inflammatory process. Virchow has shown that the pneumonic process can
be completely established in places where pulmonic capillaries cannot
be traced on account of the plugging of a large branch of the pulmonary
artery;6 yet even he admits that secondarily the pulmonary vessels
have much to do in the inflammatory process.
6 Ges. Abhang., p. 369, Virchow.
On the other hand, it is claimed that in the early stages of the
pneumonic process the parts that are supplied by the bronchial
capillaries are not reddened or injected, as they would be were these
vessels primarily concerned in the inflammatory process. Reasoning from
the above, it would seem that both sets of vessels are involved, but
that usually one set is implicated at the very commencement to a
greater extent than the other.
It is often difficult, and sometimes impossible, to differentiate
between the anatomical appearances produced by pulmonary congestion and
oedema and the first stage of pneumonia. In pulmonary congestion and
oedema the fluid in the alveoli is serum, and contains none of the
pathological cell-elements found in the first stage of pneumonia. The
alveolar capillaries are turgid, and in this respect resemble the
capillaries in pneumonic congestion, but when a stream of water flows
over a portion of lung in the first stage of pneumonia its dark color
remains, while in hyperæmia of a non-inflammatory character this is not
the case.
On account of its color and its resemblance to liver-tissue the name
red hepatization has been given to the second stage of croupous
pneumonia. The lung in this stage has a dark liver or mahogany color,
and is slightly mottled, the mottling becoming more marked the farther
advanced is the hepatization. The color is of a brighter red when the
lung is first removed from the body than after it has been exposed to
the air.
The volume of the lung is increased—at times so as to bear the impress
of the ribs. It is solid and firmer than normal; pressure does not
indent but tears it; it is very friable, and its torn surface presents
a granular appearance. Its specific gravity is increased. It is
airless, and there is an entire loss of crepitation.
Upon section it is seen that the granular appearance of the cut surface
is due to the pneumonic exudation which fills the alveoli. This
granular appearance is not so well shown on the cut as on the torn
surface. The granules can be readily removed from the air-cells by
means of a fine needle. A dirty, red, viscid fluid slowly oozes from
its cut surface, which is more apparent after the lung has been exposed
to the air for twelve or twenty-four hours and has undergone
post-mortem changes. At any time this viscid, rusty-looking material
may be scraped from the cut surface, or it exudes when a portion of the
lung is firmly compressed. A portion of the inflamed lung quickly sinks
in water, and small spots of blood-extravasations may be seen scattered
here and there throughout its substance. When a stream of water is
poured over the cut surface of the implicated lung the color changes
from a maroon to a gray or yellow-gray, the usual color of fibrillated fibrin.
Not infrequently the material in the infundibula and air-cells extends
into the minute bronchi, but these tubes are rarely completely filled
with the pneumonic exudation. When examined under the microscope the
alveoli are found filled with a solid material composed of a network of
fibrillated fibrin, in whose meshes are leucocytes, red blood-globules,
and changed epithelia. These latter are in various forms, usually round
or oval. They may, however, become quadrangular, triangular, or
irregular. They are granular, and may contain a single nucleus, a
nucleolus, or multiple nuclei. These cells finally become granular, and
fat-globules accumulate in them.
They also become discolored from
imbibition of blood-coloring matter, so that in the latter part of the
process there is quite an accumulation of pigment-granules, not only in
the free cells, but in the fixed epithelia. The larger cells discharge
their nuclei into the accumulation of corpuscular elements, and the
whole contents of an alveolus present a more or less round shape. The
alveolar walls remain unchanged, or are slightly thickened by the
capillary turgescence. All of these different cell-elements have been
regarded by different observers as characteristic of pneumonia. The red
globules give the color to the consolidated lung. The pus-cells are
always numerous.
The transition from red to gray hepatization is never well defined. The
mottling gradually becomes more marked, so that the affected portion of
lung assumes a marbled or granite appearance. As the deep-red color of
the second stage fades the density of the pneumonic consolidation
becomes less and less, until it is a mere pulp, breaking down under
slight pressure. The decoloration is due to the pressure on the
blood-vessels, to decoloration of the blood-corpuscles that were
present in the second stage, and to fatty degeneration of the other
cell-elements which occupied the air-sacs.
The weight and density of the affected lung-tissue are diminished, and
toward the end of this stage the lung crepitates. On section a nearly
uniform dirty-gray, bloodless surface is exhibited, from which flows
spontaneously or upon slight pressure a dirty-white or reddish-gray
puruloid fluid. The granular red hepatized look has disappeared or is
very indistinct. The amount of oedema in the affected portion of the
lung varies in different cases. When it is excessive a large quantity
of serum exudes from the cut surface, which then exhibits a smooth,
non-granular, glistening appearance, and it does not so readily break
down when pressed upon as do other forms of gray hepatization. When
examined under the microscope, the alveoli are seen to be filled with
numerous round mono-nucleated cells, the intercellular fibrils that
bound the elements together having disappeared; in other words (the
fibrillated having become granular fibrin), the alveoli are filled with
a fluid or semi-fluid mass in which numbers of discrete oil-globules
and protein granules are freely mingled.
The granular and fatty elements are due to the rapid degenerative
changes that occur in the cell-elements. In this stage leucocytes still
emigrate from the blood-vessels. The masses that occupy the alveoli are
now shrunken, and between them and the alveolar wall is a layer of
fluid, so that in a thin section the contents of the air-sacs are
readily lifted out by a camel's-hair brush. All of the affected portion
of the lung is rarely in the same stage of the inflammatory process,
and to distinguish red from gray hepatization, or the latter from the
beginning of some of the conditions next to be mentioned, is often impossible.
The changes which take place subsequent to the stage of gray
hepatization, and the modifications due to age, remain to be considered.
Croupous pneumonia may terminate—1, in resolution [recovery]; 2, in
suppuration, purulent infiltration; 3, in abscess; 4, in gangrene; 5,
and very rarely, in chronic (fibroid) pneumonia.
1. During resolution the lung is moist, lighter than in the stage of
hepatization, has a yellow or yellowish-green color, and still shows a
marked loss in elasticity. On section, the lung appears to be
non-granular, and a tenacious, puruloid fluid escapes when the section
is pressed upon. Some oedema may still remain. When examined under the
microscope the alveolar capillary vessels are seen to have returned to
their normal calibre; the alveolar epithelium is restored; the cells in
the air-sacs are degenerated, broken down, and resolved into a
detritus. The degeneration of these cells is both fatty and mucoid, and
the coloring matter of the blood gives origin to the granular
pigment which is scattered throughout the disintegrated and liquefied
mass. Some of the pigment is supposed to come from the connective
tissue between the alveoli. In this condition the alveolar contents are
either expelled by expectoration or undergo absorption, the lung being
finally restored to its normal condition.
2. When purulent infiltration or suppuration of the lung occurs, its
surface becomes yellow—more so than in any of the preceding
conditions; it is soft, moist, and friable, and gives somewhat the
sensation of an abscess. It is well described as miry.7
7 Pneumonia, Sturges, 1876, pp. 110, 113.
On section, a diffluent, purulent fluid exudes from a surface whose
yellow color is due both to the large number of cells which are
undergoing fatty degeneration, and to the anæmia which results from
over-distension of the alveoli with these cell-elements.
When examined under the microscope, the cells are found not only
crowding the alveoli, but infiltrating the inter-alveolar tissue. This
corpuscular infiltration of the alveolar walls may so interfere with
their nutrition that they will undergo softening and degeneration.
Whether these cells (in all respects resembling pus-cells) have
emigrated from the blood-vessels or are the result of epithelial
changes is still unsettled. Reason and analogy seem to point to a dual
origin. Now and then these cells are pigmented. Occasionally the
alveolar walls become thinned, indistinct, and finally rupture.
There has been much discussion over the term suppuration of the lung,
but the appearances reported by those who uphold, as well as by those
who protest against, the term are identically the same, all agreeing
that the "lung is filled with pus."
3. Abscess of the lung, as a termination of croupous pneumonia, is
exceedingly rare, and is always preceded by extensive cellular or
interstitial oedema; small abscesses are formed by the rupture of
several of the alveolar septa. It may follow purulent infiltration.
These abscesses vary in size from that of a pea to one which may occupy
the greater part of a lobe. They may have a thick, well-defined,
irregular wall, their interior being crossed by shaggy shreds of
broken-down lung-tissue, or they may form irregular excavations in
softened lung-tissue. They may be single or multiple. Several abscesses
are often found in the same lobe. They increase in size by peripheral
growth or by fusion of several small abscesses.
Abscesses are more common in the upper than in the lower lobes; their
frequency is variously estimated as 1 in 30 or 60 cases. These
pus-cavities, if of small size, may ultimately close by cicatrization,
in which case they may open into a bronchus of sufficient size to allow
of the discharge of their contents. Under such circumstances the
contents of the abscess are expectorated; interstitial inflammation is
set up around their site, which after a time encloses them in a firm
connective-tissue wall; contraction ensues, and finally only a line of
cicatricial tissue marks their former situation. Or if no such
bronchial opening occurs, the abscess becomes encapsulated in firm
cicatricial tissue, and the contents undergo cheesy and calcareous
transformation. Sometimes these abscesses perforate the pleura and
discharge their contents into the pleural cavity, causing
pyo-pneumothorax. External fistulous openings have occurred, but they
are a rare termination of pulmonary abscess.
4. Gangrene is said to be a termination of croupous pneumonia in about
2 per cent. of cases, but this estimate is based on too few statistics
to be wholly reliable. It is met with in bad constitutions where there
is very great vital depression, in chronic alcoholismus, and in cases
of intense septic poisoning. Interference with the blood-supply,
causing the formation of pulmonary or bronchial thrombi, leads to its
development.8 While usually limited to a
small area of
lung-tissue, it may invade large tracts, and be either circumscribed or diffuse.
8 Huss, Pneumonia; Carswell, Ill. El. Forms of Disease.
The gangrenous portion of the lung is changed to a dark, dirty, pulpy
mass, sometimes wanting the fetor of gangrene. When the mass has become
diffluent, a sort of cavity is formed, in which are found fetid fluid
and shreds of gangrenous lung-tissue. Around the gangrenous mass there
is a zone of gray hepatized, friable tissue, which in turn is bounded
by a zone of red hepatized tissue. When the above-named zones are not
present in diffused gangrene, the cavities are large, and shreds of
tissue and vascular bands traverse the cavity, which swarms with
bacteria. Such a gangrenous mass may lead to sloughing of the pleuræ.
It has been denied that a croupous pneumonia can terminate in gangrene,
but modern pathologists all support the opposite view. It may be
mentioned that gangrene in croupous pneumonia of the horse is of
frequent occurrence.
5. Chronic (interstitial fibroid) pneumonia may result when the process
of resolution in croupous pneumonia is delayed and the inflammatory
process does not advance beyond the stage of gray hepatization. In such
cases the walls of the alveoli, and finally the inter-alveolar tissue,
become the site of new connective-tissue developments.
The peculiarly hard and oedematous condition that sometimes marks gray
hepatization is, by some observers, regarded as an intermediate stage
between croupous and interstitial pneumonia. An abundant
cell-production in the second or third stage of croupous pneumonia may
be followed by shrivelling of the alveolar contents, and subsequent
cheesy changes may bring about one form of phthisis. Whether this can
ever occur independent of tubercle is still a mooted question. This is
called (by those who believe in such an origin of phthisis) cheesy
infiltration, and is to be differentiated from tubercular infiltration.
In childhood croupous pneumonia is not of so frequent occurrence as
catarrhal. In its anatomical changes it does not differ from croupous
pneumonia in adults. In old age the pneumonic changes usually begin in
the upper lobes of the lung, and extend downward—the reverse of what
occurs in adult life. In the stage of engorgement crepitation is
usually wholly absent, and when the stage of red hepatization is
reached the color is found much darker than in adults, sometimes being
blue or black; the lung is much more strikingly marbled, and on section
the granules, in those cases where they are present, are much larger
than in adult life. Frequently in senile pneumonia the granular look is
absent. Gangrene is a far more frequent termination of croupous
pneumonia in old age than at any other period. The highly-rarefied
condition of the lungs at this period seems to favor the development of
small abscesses.
Croupous pneumonia involves either the whole lobe or a whole lung. Its
most frequent seat is the lower lobe of the right lung. Its next most
frequent seat is the lower lobe of the left lung, then the upper lobe
of the right, the middle lobe of this lung being least frequently
involved. Double pneumonia has been variously estimated as occurring in
from 5 to 50 per cent. of cases, but in all probability the percentage
rarely, even in epidemics, exceeds 12 or 15 (Huss, Grisolle, Barth,
Ziemssen). In old age the difference in point of frequency of attack
between the two sides is very slight, and some affirm that sthenic is
more frequent on the right and typhoid pneumonia on the left side.
Double pneumonia is more frequent in the senile period than during
adult life.
The average duration of the different stages is as follows: The stage
of engorgement lasts from two to three days; the stage of red
hepatization, from three to five days; and the stage of gray
hepatization, from two to six days. In old age the stages rapidly merge
into each other, and suppuration of the
lung may occur within
thirty-six or forty-eight hours from the onset of the pneumonia, while
it is not at all infrequent for complete red hepatization to occur
within the first six or eight hours.
The changes in the pleura over a pneumonic lung are quite
characteristic. An uneven, thin, downy-looking layer of plastic lymph
is spread over the pleural surface, which presents a fine arborescent
vascularity. At times this plastic layer may partially conceal the
liver-brown color of the pneumonic lung. As the stage of gray
hepatization is reached, pleuritic adhesions are apt to be formed,
which subsequently undergo absorption, and thus the pleuritic changes
follow, to a certain extent, those which are taking place within the
lung. The cell-elements in this fibrinous meshwork are chiefly pus- and
large endothelial-cells. The pleura itself is opaque, congested, and
ecchymotic, and may be so thickened as to give rise to a dull note on
percussion after the pneumonia has undergone resolution. If there are
adhesions from previous pleurisies, or pleuritic changes that have
occurred prior to the lighting up of a pneumonia, they will modify its
course and termination.
The right heart is dilated, and on inspection immediately after death
it is not unusual to find both ventricles filled with pale, firm clots
that insinuate themselves between the columnæ carneæ and sometimes
extend into the vessels. The pulmonary vessels running to the affected
portion of the lung may be the seat of thrombosis. Pericarditis is so
frequently found at the post-mortem of those who die of pneumonia that
its occurrence must be regarded as something more than either accident
or complication.
The blood is hyperinotic in croupous pneumonia, and, while the amount
of fibrin is only slightly increased at the very onset, the amount
obtainable goes on increasing until the eighth or ninth day; i.e. as
the amount of fibrinous exudation within the alveoli augments, so does
the same factor appear in greater quantity in the blood—a circumstance
whose opposite condition we should expect to observe. In infectious
diseases—e.g. variola—as the temperature rises the hyperinosis
increases. In pneumonia, however, the pyrexia and fibrin increase in
the blood and bear no relationship to each other. The amount varies
greatly in every case; it has reached 10.5 in 1000.
Around the zone of pneumonic inflammation it is not infrequent to
discover pulmonary oedema; and in many fatal cases extensive oedema
seems to be the direct mode of death.
Temporary compensatory emphysema may occur in the neighborhood of the
inflamed lobe or lobes. It may be mentioned that when emphysema has
previously existed the pulmonic granules observable in the second stage
are of unusually large size.
The bronchial glands are enlarged and congested, and in rare instances
they may suppurate. The lymphatics of the lung are choked with fibrin
and with red and white blood-corpuscles, and the deeper lymphatics
contain products identical with those in the pulmonary alveoli. In both
lymphatic vessels and in the lymph-glands (bronchial) at the root of
the lung there are always well-marked evidences of inflammation.
The liver and spleen are congested, the latter organ especially
presenting the characteristics which are found in it in cases of death
from fevers.
Finally, gastro-intestinal catarrh is occasionally observed, and in
rare cases it is attended by ulceration and hemorrhage. But there seems
no good reason for believing that there is any connection between
pneumonia and these intestinal changes. Indeed, most of the
observations bearing on this point were made during cholera epidemics.
Still, analogous influences might induce both at the same time.
No change in the brain accompanies pneumonia, except congestion. Pus
and inflammatory products when found in the meshes of the pia-mater are
in
all probability due to coexisting meningitis or cerebro-spinal
meningitis of an epidemic character.
ETIOLOGY.—The specific cause of croupous pneumonia is as yet
undetermined, and the very existence of such a cause is still a matter
of conjecture.
Among the predisposing causes age ranks first. There are three distinct
periods of life in which the liability to pneumonia is greatest—viz.
in early childhood, between the ages of twenty and forty, and after sixty.
Notwithstanding the fact that catarrhal pneumonia is a very common
disease in childhood,9 the statement that croupous pneumonia is rare
at this period cannot be received.10 From a number of statistical
tables it appears that it is five times more frequent during the first
two years of life than in the succeeding eighteen.11 It is met with
most frequently between the ages of twenty and forty, and after a lapse
of twenty years the predisposition to it increases, pneumonia being the
most fatal of all acute diseases after the sixtieth year. Nine-tenths
of the deaths from acute diseases after the age of sixty-five are from
pneumonia. Each year after sixty the liability to it is greatly increased.
9 "Die lobuläre pneumonie ist im Sänglingsalter eine
ausserordenich häufige Krankheit" (Vogel, Kinderkrankheiten, p.
222).
10 "Lobäre pneumonie kommt viel seltener vor" (Vogel, loc.
cit.).
11 Klinik der Kreislaufs u. Athms. org., Breslau, 1856.
In early life, in what may be denominated the first period, anterior to
the second year, males and females are very nearly equally affected.
Between twenty and forty, the time when the condition of males and
females is most diverse, the proportion is 3 males to 1 female, or at
least 2 to 1. After sixty, when the hygienic condition of both sexes
again differs very slightly, this proportion is less striking, and the
disease is pretty evenly divided between old men and old women; still,
the male sex always furnishes more cases than the female. When women
work as men do, or when both sexes are huddled together (as in
prisons), then the difference between them is lost.
The puerperal state does not seem to increase the predisposition, but
pneumonia is more apt to occur at the time of the catamenia.
The general condition of the individual at and before the pneumonic
seizure seems to have some predisposing influence, although opinion is
divided as to whether the strong and robust or the feeble and sickly
are the more predisposed to it. Those who are convalescing from acute
and severe illnesses, those who are habitual alcohol-drinkers, and
those who are under the influence of malarial poison are far more
liable to pneumonia than those who are free from such taints.
Enervating habits, poverty, antihygienic surroundings and dyscrasiæ
(especially cancerous), and chronic nervous diseases act as
predisposing causes. Difficult dentition in children seems to act in a
similar manner. Diphtheria, erysipelas, measles, small-pox, and other
acute infectious diseases must be ranked as causes predisposing to pneumonia.
Chronic and acute uræmia, pyæmia, septicæmia, and all that class of
diseases which depend upon the retention of excrementitious substances
in the blood, are also powerful predisposing causes. It is also of
frequent occurrence in chronic blood diseases, such as chronic
alcoholismus. Suppuration in the abdominal cavity, which opens into the
thorax, may lead to a pneumonia. Long-continued, passive pulmonary
hyperæmia from any cause becomes a predisposing cause to pneumonia. The
pneumonia which frequently occurs during acute articular rheumatism has
been regarded by some as metastatic from the joints; but the more
reasonable explanation is that the blood-changes in rheumatism
predispose to pneumonia.
One attack predisposes to others; as many as twenty-eight attacks have
been noted in the same individual, the time between the attacks and the
number of them being governed by no rule and subject to the
widest variations.
When pneumonia follows a severe blow or injury to the chest or shock
from any traumatic cause, the injury (or the shock) must be regarded as
a predisposing cause. It is noteworthy to observe how often in the aged
fracture of the hip-joint is followed by pneumonia. Within four hours
after this injury croupous pneumonia has been established.
The influence of prolonged exposure to intense cold and sudden chilling
of the surface of the body as a predisposing cause of pneumonia is
still undetermined. Cold does not markedly affect the pneumonia-rate,
except in the very old. Nearly nine-tenths of the cases of senile
pneumonia occur between November and May. The January and February
statistics seldom exhibit the highest pneumonia-rate, as they would
were there any direct relationship between pneumonia and cold. In
elevated regions north-east winds favor the development of pneumonia,
and it is most prevalent in any locality during those periods of the
year when there are the greatest extremes of temperature. A
continuously low or a continuously high temperature has much less
influence in its production than great vicissitudes of temperature. In
New York City early spring and winter seem to be the periods when it is
most prevalent.
A glance at its etiology shows that it is a disease to which all things
predispose that depress the general vitality: this is evidenced by the
fact that children and old people are greatly depressed by the intense
cold of winter and the chilling winds of March and April. Almost
unknown in the polar regions, pneumonia is not an infrequent disease
along the Mediterranean coast; and one peculiarity is to be noted here,
that in cold as well as in warm climates moderate elevation above the
sea-level predisposes to its occurrence.
Rainy seasons or moist districts do not influence the pneumonia-rate to
any appreciable degree. Both these conditions have a direct effect in
increasing the prevalence of bronchial catarrh, but they do not
increase the pneumonia-rate.
The well-established facts that pneumonia occurs oftener among the poor
than the wealthy; in the sailor when on shore oftener than when he is
on shipboard; in soldiers oftener than among civilians at the same
military post,—these are explained on the ground of better hygienic
surroundings, better mode of life, nourishment, etc., of the one class
as compared with the other. And in studying the predisposing causes of
pneumonia one is led more and more to observe that it is the more
liable to occur the less resistance individuals are able to offer to
some (as yet unknown) specific pneumonic influence, and that depressing
influences of whatever kind unquestionably predispose to croupous pneumonia.
The more dense the population in a district, the greater the
pneumonia-rate. Hirsch says: "The amount of the mean fluctuation in the
mortality from pneumonia is in inverse ratio to the density of the
population." When a city has attained a certain size, wind, weather,
seasons, and races have but a slight influence in varying the
pneumonia-rate. Thus, in New York City from 1840 to 1858 (eighteen
years) the mortality from pneumonia was 5.85 per cent., while from 1859
to 1877, inclusive, it was 6.2 per cent.
Before considering the exciting causes of croupous pneumonia, or their
relation to its predisposing causes, the question meets us, Is croupous
pneumonia an acute specific constitutional (infectious) disease or a
local inflammation?12
12 Virchow's Archiv, Bd. lxx., Heidenhain.
That it is not a simple local inflammation appears from the following
facts: the experiments with the inhalation of hot air, moist warm air,
icy-cold air,
vapors of various noxious acids and gases;13 the
tracheal injection of caustic ammonia14 and mercury; and
traumatism,—have all resulted negatively as exciting causes. And these
experiments have all the more weight since they have been conducted not
only at different times, and in countries distant from each other, but
also because they have been repeated by various pathologists, and
always with a similar result—viz. the development of lobular or
catarrhal, and not of croupous, pneumonia. Section of the vagi
certainly produces hepatization of the lungs, but it is not the
hepatization of croupous pneumonia. Its distinctive microscopical
characteristics are always wanting in the part of the lung consolidated
by such experiments. A strong argument of those who adhere to the local
theory of pneumonia is, that cold occupies a prominent place in its
production. As exposure to cold and to draughts is a common experience,
it is easy to ascribe the origin of any disease to cold.
13 Sityl, K. K. Akad. zu Wien, 867, Reitz.
14 Gendrin, Hist. Anat. des Inflam.
"Close rooms and bad air," says Squire, "more predispose than does
outdoor exposure, unless that be prolonged or the individual resistance
weakened by fatigue or intemperance." Both wet and cold invariably
heighten the bronchitis-rate and exacerbate catarrhal processes, but
neither of these can be proven to influence the pneumonia-rate.
Statistics show that croupous pneumonia is more prevalent in our
Southern States than in our Northern States. The epidemics in the West
Indies are as well known as, and have been more devastating than, those
in Iceland and in the Norse countries. The prevalence of pneumonia in
this continent progressively increases from the pole to the equator.
Hirsch's statistics and statement, that "the amount of the mean
fluctuation in the mortality from pneumonia is in inverse ratio to the
density of the population," is a strong argument in favor of the view
that croupous pneumonia is due to some specific pneumonic infection,
for all acute general diseases increase where there is over-crowding.
It is often stated that pneumonia is a far more frequent disease now
than it was twenty years ago. That I might arrive at something definite
on this point, I have carefully examined the death-reports of England
from 1840, also those of New York City, dividing them into two periods
of eighteen years each; and I find that the average mortality from
pneumonia in England from 1840 to 1858 was 5.57 per cent.; from 1859 to
1877, 4.77 per cent., an actual decrease of 14.3 per cent. In New York
City from 1840 to 1858 the average ratio of mortality from pneumonia to
all other diseases was 5.85 per cent., and from 1859 to 1877 it was
6.20 per cent., showing an increase in New York of 15.2 per cent. Thus
it is shown that while in England pneumonia is on the decrease, in New
York City it is on the increase.
Those who advocate cold as a cause of pneumonia base their argument on
the seasons of the year when it is most prevalent. The winter and
spring are pre-eminently the seasons of pneumonia, but cerebro-spinal
meningitis, diphtheria, influenza, measles, and other diseases of
similar general character occur with greatest frequency in the winter
months, yet it is not now claimed that cold causes them. While it is
not to be denied that cold is to a limited extent an exciting cause of
pneumonia, the belief that it is the primary or principal cause must be
held in abeyance if not altogether rejected. Again, the symptomatology
of pneumonia seems to militate against its being a local disorder.
There is no relationship between the amount of lung-tissue involved and
the intensity of the symptoms; high fever, delirium or convulsions, and
rapid heart-failure are often as well marked when a post-mortem reveals
only one lobe to be involved as when a double pneumonia exists. "The
local inflammation in its gradual extension and composite character
offers no sort of
parallelism to the fever which for a while
accompanies it." In local phlegmasiæ there is a direct ratio between
the amount of surface involved and the attendant constitutional disturbances.
Rarely does a second chill occur when there is an extension of the
pneumonic process. "Small consolidations with high fever and severe
constitutional symptoms, and extensive infiltrations with a
comparatively slight fever and general disturbance, are the rule and
not the exception."15
15 Ziemssen's Cyclop. Prac. Med., vol. v. p. 146.
The absence of regular and constant prodromata, the absence of a known
period of incubation, of a typical temperature-range, and of
characteristic surface phenomena, and the fact that it is not
contagious,—these must not be overlooked when we are tempted to regard
croupous pneumonia as an acute infectious disease.
The points of resemblance between croupous pneumonia and the acute
general diseases are the following: It has an initiatory chill, an
orderly pyrexia, and a somewhat typical course, inasmuch as there are
in many cases a day of abrupt crisis and a definite duration. The
symptoms follow in regular sequence.
There is a peculiar countenance, and here we note a resemblance to
typhus and typhoid; there are usually herpetic eruptions; the kidneys
are not infrequently the seat of a nephritis; and catarrhal pyelitis is
a common condition. The cerebral symptoms greatly resemble the
condition that accompanies the exanthems. The peculiarity of its
commencement in the very young and old—convulsions in the former and
coma and collapse in the latter—serves to point to an alliance with
those diseases where a specific morbific agent acts primarily and
principally on the nervous system. Etiologically, it often arises under
precisely similar circumstances as those which give origin to
cerebro-spinal meningitis and diphtheria, to both of which diseases it
is also allied, since the pathological changes are distinct from those
of any other inflammation.
Again, the influence of septic, miasmatic, and atmospheric conditions
is certainly almost universally acknowledged. A good example of this is
the sewer-gas pneumonia so often occurring in New York City, and of
which frequent mention is made by English writers. Again, there have
been frequent epidemics of pneumonia in certain districts in garrisons
and on board ship, where over-crowding, bad ventilation, and general
antihygienic surroundings prevailed.16
16 In the U. S. Sanitary Commission Memoirs, Russel
reports: "The surgeons on duty with the regiments in the barracks
(Benton, Mo., 1864) report that men occupying the same bunks with those
affected were very much more liable to be attacked than those more
remote. Some of the most intelligent surgeons were led to believe that
the disease was actually contagious."
During the winter of 1881–82 I remember three instances where two
individuals in the same house were simultaneously attacked with
croupous pneumonia.
Pythogenic pneumonia is a form which arises under miasmatic influences,
and is contagious.17
17 Dub. Med. Journal, 1874, vol. i., Grimshaw and Moore.
"The epidemic form of croupous pneumonia at certain times bears the
distinct characteristics of a specific infectious disease."18
Miasmatic and zymotic pneumonia are names which have also been given to
this form; and indeed it is now generally acknowledged that croupous
pneumonia does occur as an epidemic disease when it is, seemingly,
dependent upon a specific contagion. Huss thinks that during a typhus
epidemic pneumonia is apt to assume the low typhoid form.
18 Berliner klinische Wochensch., 1879, No. 37, A. Kühn.
Moreover, as in typhoid and cerebro-spinal meningitis, so in pneumonia,
we
have abortive cases, and forms which are distinguished by the
names sthenic, asthenic, malignant typhoid, icteric, etc. Still, a
pneumonia epidemic is different from a typhoid or cholera epidemic: it
does not sweep over large districts and affect all ages and classes indiscriminately.
Every acute general disease has its complications, and the occurrence
in pneumonia of peri- and endocarditis, as well as its cerebral and
renal complications, allies it to other acute general diseases.
Cerebro-spinal fever has its characteristic lesion in the membranes at
the base of the brain and about the cord; typhoid fever, in the
lymph-structures of the intestinal tract; diphtheria commences in and
chiefly involves the epithelia; and pneumonia has its characteristic
local lesions in the vesicular structure of the lungs. Croupous
pneumonia is occasionally met with in intrauterine life, and it is to
be remembered that acute general diseases occur far oftener in the
foetus than local inflammations. Again, the accepted treatment of
pneumonia at the present day is an indication of its specific
character. Thus the weight of evidence leads to the opinion that
pneumonia is an acute specific general disease caused by a specific
poison. The nature and action of the pneumonia-poison may be indicated
by the following facts and experiments: Hyperinosis does not seem
capable of causing croupous pneumonia; the fibrin increases as the
consolidation is completed, and does not antedate either the pyrexia or
the hepatization. Excessive bleeding increases the amount of fibrin
obtainable from the blood; and when, in pneumonia, we find one lung
weighing three pounds more than the other, may not the blood-elements
effused into the alveoli have much to do with the hyperinosis?
Pneumonia resembles quinsy19 in its pyrexia, temperature-curves,
duration, its constitutional as compared with its local symptoms, and
its rapid and abrupt decline. Both have a similar herpetic eruption,
and in both the amount of chlorides in the urine is subnormal, the urea
(in both) being increased.
19 Sturges, Pneumonia, loc. cit.
An analogy has been noted by some observers between pneumonia and acute
rheumatism. Trousseau sees an analogy between erysipelas and
pneumonia.20 But apart from their etiology it is difficult to
recognize any constant resemblances between them. Sturges places
"pneumonia in a middle place between the specific fevers, so called,
and the local inflammations," and adds that it has something in common
with both. Cohnheim classes croupous pneumonia among the miasmatic
contagious diseases.
20 Clinical Lectures, vol. iii. p. 353.
The idea of its being a specific disease dates from the latter part of
the eighteenth century:21 it is not by any means a modern thought,
although it has within the last ten years received a new impulse and
given rise to extended discussions.
21 C. Strackius in Nov. Theo. Morg., 1786.
It seems to me that the resemblance of pneumonia to the acute general
diseases is to be found for the most part in its nervous phenomena, and
that the complications which render pneumonia dangerous are those which
interfere directly with the muscular power of the heart or diminish its
nerve-supply.
In order that the influence exerted by an abnormal nerve-supply upon
the contractility of the cardiac muscles may be more apparent, let us
glance at a few modern physiological facts. When the inhibitory nerve
of the heart, the pneumogastric, is cut, the heart beats wildly. When
the peripheral cut end is stimulated, the heart stops in diastole. But
neither of these phenomena instantly follows the operations, on account
of the intervening cardiac ganglia, the part of the vaso-motor system
which has its centre in the medulla oblongata. Afferent inhibitory
filaments (the depressor branch) of the vaso-motor centre are also in
the vagus. Now, by injecting atropine into the blood we so influence
these cardiac ganglia (which intervene between the conditions of the
vagus and the resulting action upon the heart-beat) that the inhibitory
action is entirely checked. Thus an intimate connection is
apparent between the local heart-mechanisms, the general vaso-motor
system, and some filaments of the vagus. Again, we know that the
natural explosive decompositions of the nerve-cells of the respiratory
centre may be either augmented or enfeebled according to the condition
of the blood supplying this ganglion. Now divide the cervical portion
of the pneumogastric, and there results, after a more or less prolonged
period, an extensive pulmonary consolidation (hepatization), which is
not accompanied by the least sign of heart-failure. It is to be
remembered that such pulmonary consolidation has none of the essential
pathological characteristics of croupous pneumonia.22
22 Michael Foster, Wagner, Goetz, Heidenhain, Du
Bois-Reymond, Ludwig, and Pflüger.
From these experiments the following deductions seem at least
reasonable: The tonic influence normally held by the vaso-motor system
of nerves over the vascular system is either lessened or destroyed by
an altered blood-state or by some morbific agent in the blood
introduced from without. The large quantity of blood which would then
be retained in the arterioles throughout the body, and which could not
be returned to the heart, may cause so great a diminution in the
blood-pressure as in itself to cause heart-failure. But in addition,
and in connection with this, may not the action of a morbific material
in the blood upon the intrinsic cardiac ganglia so interfere with their
function, or so act upon the medullary vaso-motor centre itself, that
the movements of the heart are deranged and its power is more or less
diminished?
It would seem that this materies morbi in the blood may as well act
upon both the medullary centre of the vaso-motor system and the ganglia
in the wall of the heart as upon either alone. The phenomena of
asphyxia are brought about by influences acting solely on the medullary
centre. Again, the large amount of urea excreted, the result of
excessive tissue-change throughout the body, may also be due to
deranged nerve-function.
Klebs23 even claims that he has found the infectious agent—a monas
pulmonale—which can be inoculated, with the result of developing
croupous pneumonia. This has been credited so far as to lead to the
subcutaneous injection of carbolic acid to destroy the pneumonic germ.
Incidentally, it may be remarked that it has been shown that the
contagion of the pleuro-pneumonia of cattle, according to Parkes, "has
been found in the pus- and epithelium-cells of the sputa." The true
nature of the pneumonia poison, if one exists, is as little determined
as that of the other acute contagious general diseases. But, whatever
its nature may be, its primary action seems to be on the nerve-centres.
23 Arch. für exper. Path. u. Pharm., vol. iv., 1875.
SYMPTOMS.—The symptoms of croupous pneumonia may be considered under
two heads—Subjective, or rational symptoms; and Objective, or physical signs.
Subjective Symptoms.—In only a small proportion of cases are there
prodromata. Grisolle found that prodromata occurred in 50 out of 205
adult cases, or in about 25 per cent.; and Fox says that he finds the
proportion to be about 28 per cent. In old age they seem to be more
frequent, the proportion being about 60 per cent.24
24 Durand-Fardel, Mal. des Viellards.
There may be for a day or two, or even for a week, preceding a
pneumonic seizure a feeling of general malaise, accompanied by
anorexia, headache, dull pains in the limbs, back, and lumbar region,
vertigo, epistaxis, or slight diarrhoea. Sometimes the skin assumes a
slightly jaundiced hue, and there may be flashes of heat accompanied
by, or alternating with, slight rigors. Flying pains in the limbs and
chest and epistaxis are common in senile croupous pneumonia. When
prodromes have existed more than three or four days, they will be vague
and undefined.
Rise in temperature as a prodrome is by some thought to be caused
by a deep-seated and undiscoverable hepatization. But let us take one
example from many in support of a contrary view—viz. the case of an
inmate of Bellevue Hospital during the winter of 1880–81. For three
days preceding the first appearance of consolidation the temperature
ranged at 102° and 103° F. During this time there were several slight
rigors followed by flashes of heat.
Wilson Fox25 states that he knows of but one case—the one referred
to by Monthus in his Essai sur la Pneumonie double.
25 Reynolds's System, art. "Pneumonia."
In epidemics febrile symptoms and diarrhoea often precede for some two
or three days the first sign of consolidation.26
26 The Lancet, vol. ii., 1878, p. 701, Couldrey.
In the great majority of cases croupous pneumonia is ushered in by a
distinct chill. Huss and Grisolle found a chill in 80 per cent. of
their cases; Fismer and Louis in about 77 per cent. of theirs; and
Lebert in over 92 per cent. of his. In 84 out of 100 cases admitted to
my ward in Bellevue Hospital, a distinct chill marked the invasion of
the disease.
Generally, the patient retires in his usual health, to be seized with a
severe chill during the night. The chill lasts from half an hour to two
or three hours. Its abruptness and severity are almost characteristic
of the pneumonia.
In children, headache, nausea, vomiting, delirium, and convulsions may
take the place of the chill; its onset then closely resembles that of
the exanthemata, indicating the action of some irritating poison upon
the nerve-centres. When these symptoms are not present there will be
more or less anorexia, thirst, and a tendency to stupor. The child will
awake in the middle of the night with a burning skin, a bounding pulse,
flushed face, and hacking cough. When there are convulsions, followed
by a loss of consciousness, the pneumonia is usually at the apex of the
lung.27
27 Rilliet and Barthez.
If an old person is seized with a severe chill during the night, it is
almost a certain indication that pneumonia is developing. Although the
chill of invasion is of less frequent occurrence, it is more
significant than in adult life. A protracted fit of shivering and pain
in the side are the two diagnostic symptoms of acute sthenic senile
pneumonia. They occur in about 50 per cent. of all cases, and from
statistics taken from the Salpêtrière it seems that in March and April
these two symptoms are almost always present.
In the other half of the cases of senile pneumonia the onset is marked
by a frequent, irregular respiration, slight rise in temperature, short
hacking cough, and signs of great exhaustion. Nausea, vomiting,
diarrhoea, and collapse or a semi-comatose condition may usher in a
senile croupous pneumonia.
Durand and Fardel give the following statistics of the mode of advent
in 35 cases of senile pneumonia: 7 began with distinct rigors; 8 with
rigors and pain in the side; 6 with rigors and vomiting; 8 with pain in
side alone; and 6 with vomiting only. When a chill is the initial
symptom, either in childhood, adult life, or at the senile period, it
is rarely repeated.
In adults, following the chill there is usually pain underneath the
nipple of the affected side; sometimes the earliest symptoms following
the chill are headache, vomiting, and diarrhoea, dyspnoea, a hacking
cough, and pain that simulates that of lumbago. Within twenty-four
hours after the invasion the aspect of the patient becomes
characteristic: there is a rapid rise in temperature, attended with
great prostration; the pain in the side is aggravated by coughing and
deep inspirations; and the respiratory movements are accelerated. The
countenance assumes a dull or anxious expression, with a tendency to
lividity; the pulse is accelerated, full, and soft; there is complete
anorexia and great thirst; speech is difficult, and often there is
great restlessness. The urine becomes scanty and high-colored, the
bowels are constipated, and the tongue is dry and covered with a white coating.
These symptoms either increase in severity or are attended by
exacerbations and remissions until the day of crisis, which usually
occurs between the third and the ninth day; when, if recovery is to
take place, there is a sudden remission of all the pneumonic symptoms;
the temperature falls abruptly; the surface becomes moist; the flush of
the countenance disappears; the pulse and respiration become normal;
and the patient rapidly passes on to complete convalescence.
In some cases the decline in the symptoms is gradual and the disease
terminates by lysis and not by crisis. In unfavorable cases signs of
heart-failure appear within the first few days, and the patient sinks
rapidly into collapse and dies.
With this brief outline of the disease I will pass to an analysis of
its prominent symptoms.
Respiration.—The respirations are more constantly increased in
frequency in croupous pneumonia than in any other acute disease. In
most febrile diseases the respirations increase in frequency with the
pulse-rate. In pneumonia there is no uniform ratio between pulse and
respiration; this is regarded by some as an important diagnostic
sign.28 In some cases the respirations will be 80, and the pulse only
90, per minute. The acceleration in the respiration is not in
proportion to the amount of lung-tissue involved, but seems to be due
to a peculiar condition of the nervous system which existed prior to
the pneumonic seizure or is caused by a poison acting upon the
nerve-centres. Traube29 thinks that it is due to the pain and to the
high temperature. This theory would not explain its occurrence in those
cases where the pleura is not involved—i.e. when no pain is
present—and yet the shallow, panting, rapid breathing is well marked.
28 Dis. of Lungs, Walshe, 1860, p. 366.
29 Annal. de Charité
In other pulmonary diseases, when there is high temperature, as in
acute phthisis, the respirations are not so much accelerated as in
pneumonia. The character of the respiratory acts is also peculiar: they
resemble the panting of a dog. Accelerated breathing may or may not be
accompanied by dyspnoea; in many cases the dyspnoea seems to be
independent of it, for extreme dyspnoea is often present where the
respirations are but slightly increased in frequency.
In children the acceleration of respiration is more marked than in
adults, and the ascent of the chest occurs during expiration, and not,
as normally, with the inspiration. The diaphragm is markedly contracted
with each expiratory act, and the diagnosis will as often be made by
the character of the respiration as by the physical exploration of the
chest, for in children the early physical signs of pneumonia are often unsatisfactory.
The hurried breathing prevents a young child from nursing; it takes the
mother's nipple for an instant, nurses greedily, and then drops back,
gasping for breath.
It is to be remembered that in pneumonia in children the pulse and
respiration discrepancy will not be so well marked as in adults: the
pulse may be 150 to 160 per minute, while the respirations are 80 or
90. In children there will early be noticed the peculiar expansion of
the nostrils which comes on late in adults. In senile pneumonia the
chest enlarges vertically during inspiration. The whole act has a
panting character, and the expiration is prolonged.
In perfectly healthy old people the inspiratory movements are jerky in
character. The lungs become fully expanded only after a succession of
interrupted efforts. An exaggeration of what is physiological in old
age—i.e. catchy breathing—is the most frequent form of abnormal
respiration in senile pneumonia.
Dyspnoea, although frequently accompanying accelerated respiration, is
by
no means a constant attendant of it. When urgent it is not in
proportion to the amount of lung involved, since double pneumonia may
be accompanied by less dyspnoea than when but one lobe is involved. It
can be due only in small degree either to the diminution in the total
breathing capacity, to the pain, or to the rapid and destructive
tissue-metamorphosis; for on the day of crisis it ceases, although the
lung at this time is not relieved of its obstructive exudation. The
most intense dyspnoea usually occurs in those cases where there is
extensive nervous prostration, and must always be regarded as a symptom
of great gravity.
In secondary pneumonias, especially where there is coexistent disease
in any part of the respiratory tract, the dyspnoea is usually more
marked than in primary and uncomplicated pneumonia. It differs from the
labored dyspnoea of general capillary bronchitis. A diagnosis between
these two diseases can often be made by the character of the dyspnoea.
When the summit of the lung is involved, the dyspnoea is always greater
than when the pneumonia is at the base. In pneumonia of the apex in
children the dyspnoea is so great that the nostrils are widely dilated,
the mouth is open, and its corners are drawn downward and outward. In
senile pneumonia, even when the respirations are 70 per minute,
patients do not complain of difficulty in breathing.
When persons over seventy who have been asthmatic or are the subjects
of chronic bronchitis develop a pneumonia, they often suffer less from
dyspnoea than before the pneumonic attack. They feel exhausted, are
unable to move about, and on lying down to rest often suddenly expire.
Immediately after the initial chill pain is present in over 85 per
cent. of the cases. It is of a sharp stabbing character, and is usually
located over the seat of the pneumonia; it is intensified by coughing,
sneezing, and deep inspirations. In some cases there is tenderness on
pressure over the seat of the pain. The pain usually disappears after
the third or fourth day of the disease; if it continues until the
eighth day, it may be regarded as evidence of pleuro-pneumonia. If the
pneumonia is central there will be no pain. In old age, even in a
pleuro-pneumonia, pain is never severe. It is rather a dull, uneasy
sensation referred to the whole chest, or if localized by the aged
patient is referred to the pit of the stomach, the nipple, the loins,
the hypochondrium, or even to the side opposite to the one involved.
Cough is generally present within twenty-four hours after the accession
of croupous pneumonia. At first it is short, ringing, or hacking in
character, and increases the pain in the side. It sometimes entirely
ceases just before a fatal termination. In children a hacking cough is
more constant than in adults. Within a few hours it becomes painful and
urgent, and occasionally assumes a paroxysmal character, resembling
whooping cough.
Old people with pneumonia often have no cough. When present it is
slight, and may escape the notice of the patient as well as of the
physician. When an aged person suffering from chronic bronchitis or
asthma, who has had a chronic cough, develops a pneumonia, the cough
generally becomes less severe, and may entirely cease.
Expectoration.—The sputum in pneumonia is characteristic. During the
first forty-eight hours it is simply frothy mucus; then it becomes
semi-transparent, viscid, gelatinous, and tenacious, but never opaque.
Streaks of blood often appear early, mixed with the sputa. So tenacious
is it that the cup which contains it may be inverted without spilling
the mass. It can be drawn out between the thumb and finger into thin
strings, and its tenacity undoubtedly is one cause of the difficulty in
its expectoration. Its color varies: generally on the second day the
brick-dust or rusty sputa are observed; still, there are numerous
exceptions. The color is due to admixture of blood which extravasates
from the capillaries of the alveoli. The rusty sputa are preceded
in some cases by a transient brighter red expectoration. In other cases
it is of a creamy-yellow color, resembling in this respect ordinary
catarrhal sputa; or, again, it becomes dark and of a prune-juice color.
A severe pneumonia may have none other than a purulent sputum.
Prune-juice sputa of an offensive odor are indicative of a depraved
state, and occur only in grave forms of pneumonia. In alcoholismus and
in those markedly septic forms of pneumonia which are to end fatally,
the prune-juice or burnt-sienna sputum is usually present. In some
instances prune-juice sputa appear before the physical evidences of hepatization.
A watery and blood-stained expectoration indicates pulmonary oedema and
congestion, and is an unfavorable symptom. When a case is tending to a
fatal termination, the sputa become scanty, less tenacious, more
diffluent, and often of a greenish color. But a greenish color may be
present during the stage of resolution, and may temporarily occur in
the middle period of a pneumonia, without being indicative of serious
changes. It is usually present in the so-called bilious pneumonia when
there is jaundice.
Pre-existing or complicating lung diseases may mask or alter the
ordinary rusty pneumonic sputa. On the day of crisis, when resolution
occurs, the sputa usually become abundant and of a creamy-yellow color.
But purulent creamy sputa may occur with a complicating abscess and in
some cases of purulent infiltration. During the whole course of the
disease there may not be a single characteristic sputum, or it may not
be present until the fifth, sixth, or even the twelfth day of the
pneumonia. Again, the sputa may continue of a brick-dust hue until the
ninth or tenth day. There is frequently an entire absence of
expectoration in the pneumonia of acute articular rheumatism and in
pneumonia of the apex.
Lastly, the sputa may be more or less pigmented, or when venesection or
purgation has been extensively practised expectoration may suddenly cease.
In children expectoration is rarely present, but the brick-dust masses
may often be detected in the ejected matter after an attack of
vomiting. In senile pneumonia expectoration is never an early symptom,
and it is liable during any period of the disease to suddenly cease.
Rusty sputa occur in only about 33 per cent. of senile pneumonias. They
are at first scanty, gray, and frothy, then yellow or catarrhal (sputa
cocta). In severe and fatal cases profuse bloody expectoration may be
present at the onset. The reason why the viscid (pathognomonic) sputum
of pneumonia is so often absent in senile pneumonia is that the stages
pass rapidly into each other, and purulent infiltration takes place
very early. The day of crisis is not marked by the same changes in the
expectoration that mark the crisis in pneumonia of adult life.
A chocolate-looking serous expectoration usually accompanies the
so-called typhoid pneumonia.
When examined under the microscope, the sputum is found to contain
swollen epithelia, both spheroidal and columnar, red and white
blood-globules, minute spherules of fat, and the other elements which
were described as filling the alveoli during the stage of red
hepatization. (See Morbid Anatomy.)
Walshe affirms that pus-cells are not found in the brick-dust
expectoration of pneumonia. The mucoid cells will often be stained by
the liberated coloring matter of the blood, and pigment-granules may be
found mingled with the granular débris of its resolving stage. In about
75 per cent. of the cases there will be found in the sputa, when
floated in water, casts of the alveoli and bronchioles.30
30 Diagnost. u. Pathognos. Untersuch., 1845, Remak.
The chemical constituents of the sputa are albumen, mucus, and mucin.
Different observers have found the sputa to contain tyrosin and sugar.
There are two explanations of the acid reaction of pneumonic sputa.31
Verdeil thought it due to the excess of pneumic acid in the
inflamed lung. Bamberger claims that it is due to the deficiency in
alkaline phosphates.32
31 Gaz. méd., 1851, p. 777, Robin et Verdeil; Chem. Anat.
Phys., vol. ii. p. 460 et seq.
32 Wurtzburg Med. Zeitschr., ii., No. 506.
It may be noticed that the following differences exist between
pneumonic and catarrhal sputa: catarrhal sputa contain 10 to 14 per
cent. of alkaline earths; pneumonic sputa contain no alkaline
phosphates. In catarrh the ratio of the soda to the potash is 31 to 20;
in pneumonia the ratio is 15 to 41. There is 3 per cent. of sulphuric
acid in catarrhal and 8 per cent. in pneumonic sputa.
Early in pneumonia there is an increase of the fixed salts, notably
chloride of sodium, in the serum of the blood. It has been thought that
from the rapid and excessive cell-transformation in the lung the
chloride of sodium is attracted to that organ. In one case where no
sodium chloride was found in the urine 10 per cent. of the solid
material of the sputa consisted of that salt. Still, the presence of it
in the sputa and blood, and its absence from the urine, are facts that
still need elucidation.33
33 Beale gives the following analytical table of a case of
acute pneumonia:
| Chloride of Sodium. |
Per cent. of Solids. |
| Urine |
0.00 |
| Blood from heart |
0.68 |
| Hepatized lung |
2.59 |
| Healthy lung |
1.43 |
The expired air in croupous pneumonia is colder than normal, and, as in
many acute general diseases, there is a diminution in the amount of
carbonic acid excreted.
Temperature.—The temperature-range of a typical case of croupous
pneumonia shows it to belong to the remittent or subremittent type of
diseases rather than to the class of febrile disorders marked by a
continuous pyrexia. In rare instances it is intermittent.
As in most acute general diseases which are ushered in by a distinct
chill, the temperature rises rapidly during the chill. In two or three
hours after the chill it may range from 102° to 105° F. After
twenty-four hours it is subject to evening exacerbations and morning
remissions, but the morning temperature is rarely more than 2° F. lower
than the evening. Indeed, the difference in the subremittent type may
amount to only ½° F., and in the remittent type to only 1° F. At
midnight a second exacerbation may occur, but not so marked as that
occurring early in the evening. Occasionally the remissions occur in
the evening and the exacerbations in the morning.
|
FIG. 33.
|
|
|
A Typical Case of Lobar Pneumonia in the Adult: Recovery by Crisis.
|
The temperature is usually highest on the evening of the third day. In
some cases the maximum range may not be reached until a few hours
before the crisis, on the fifth or sixth day.
In fatal cases,
just preceding death, the temperature may reach 107° or even 109° F.
An (average) typical temperature-curve is shown on the preceding page
(Fig. 33).
If after the fourth day of a pneumonia an unusual remission is followed
by a high temperature-range, either an extension of the pneumonia or
the occurrence of some active complication is indicated. If in an
otherwise mild pneumonia the temperature suddenly rises to a high
point, a grave complication is indicated. The sudden fall of
temperature on the fifth or sixth day indicates a crisis and the
beginning of convalescence; it may occur in the morning or after the
evening exacerbation.
In a typical case it is usual to find the temperature on the morning of
the fifth, sixth, or seventh day two or more degrees lower than on the
preceding night, and subsequently it falls until a normal, or not
infrequently a subnormal, temperature is reached. The crisis may occur
by successive and increasing remissions, while the exacerbating
temperature remains constant (Fig. 34); and indeed it is common for the
remissions to be excessive immediately preceding the crisis.
|
FIG. 34.
|
|
|
Lobar Pneumonia, where the Crisis was marked
with Evening Exacerbations, reaching nearly the highest pyrexia of the
second stage: Recovery.
|
Just before the final fall the fever may be greater than at any time
preceding.34 When the decline in temperature is gradual (lysis), the
normal temperature is usually reached by the ninth day, but it may be
delayed until the twelfth or fourteenth day. A very slow or protracted
lowering of the temperature is attended by a coincident slow
disappearance of the physical signs of consolidation. There is no
explanation for this, except that it is met with oftenest in the weak,
debilitated, and dissipated where venesection has been practised or a
depressing plan of treatment has been resorted to.
34 See Fig. 33, where a temperature of nearly 105° F. is
followed on the evening of the fifth day by the final fall.
A high temperature persisting after the tenth day indicates purulent
infiltration (see Fig. 38).
Pneumonia involving the apex of the lung is usually marked by a higher
average range of temperature than when it is confined to the lower
lobes. Statistics show that the fifth and seventh days are the days of
crisis in the majority of uncomplicated pneumonias. Of 867 cases
terminating by crisis, in 677 the crisis occurred before the eighth
day. Neither the height of the temperature-range nor the amount of lung
involved affects the critical day.
In the form of pneumonia sometimes called bilious—a form that prevails
in miasmatic regions—the temperature is markedly paroxysmal.
In children the temperature rises very rapidly, sometimes reaching 106°
F. within the first twelve hours. The highest recorded temperature in
the pneumonia of children, with recovery, is 106°–107° F. The average
temperature
of pneumonia at this period of life is 104° F., the
range being higher than in adult pneumonia.
In children the day of crisis is oftener the seventh than the fifth
day. The fall of temperature during the crisis is somewhat remarkable;
it often falls two and a half degrees below the normal, and this
exceedingly low temperature may be maintained for two or three days,
and yet the child recover.
The accompanying charts show ordinary temperature-curves from children
with pneumonia (see Figs. 35, 36).
|
FIG. 35.
|
|
|
A Typical Case of Lobar Pneumonia in a Child: Recovery.
|
|
FIG. 36.
|
|
|
A Case of Lobar Pneumonia in a Boy ten years
old, in which thermometrical observations were made every four hours:
Crisis on the sixth day.
|
In old age it is often difficult to determine the exact day of the
invasion of pneumonia except by the temperature. The rectal temperature
rises to 103° or 104° F., or even higher, on the first days, and
continues at about the initial point for three or four days, with daily
morning and evening oscillations of a degree or a degree and a half.
The temperature-rise does not begin for several hours after the initial
chill, if a chill occur (see Fig. 37).
|
FIG. 37.
|
|
|
A Typical Case of Senile Lobar Pneumonia: Recovery.
|
Relapse in pneumonia is a rare event; it is quite phenomenal for it to
occur four days after the crisis. The temperature suddenly rises, but
usually returns to normal in three or four days.
Pulse.—The pulse in pneumonia varies with the type and extent, as well
as with the stage, of the disease. In an ordinary mild case the
pulse-rate is usually between 90 and 120 per minute. When the
pulse-rate for any length of time is above 120, the case must be
regarded as an exceedingly grave one.
The pulse at the onset of croupous pneumonia is usually full and
soft. As the disease progresses it becomes small and feeble. In severe
cases, and when the nervous system is markedly implicated, it is rapid,
and may be 130 to 140, or even 160, at the onset of the disease. In
such cases it will also be small and feeble.
A high temperature is usually accompanied by a rapid pulse, and a low
temperature by a moderately frequent, full pulse. At the day of crisis,
when the temperature falls, the pulse will fall; and this occurs in the
severe as well as in the mild cases.
Subsequent to the third or fourth day in severe cases the pulse, in
addition to its frequency and feebleness, may exhibit dicrotism, or it
may be jerky, very compressible, and intermittent. Sometimes just
before death the pulse becomes markedly slow. The feebleness of the
pulse is ascribed by some to cardiac depression, the result of the high
temperature; by others it is claimed that the afflux of blood to the
left ventricle obstructs, and causes a deficiency in, the aortic
circulation. In other words, hepatization is adduced as a cause of the
feeble pulse. In chronic wasting diseases, in feeble, weak individuals,
or in those already suffering from cardiac disease, weakness of the
pulse is a very marked symptom.
I cannot regard a feeble pulse in pneumonia as due to the pulmonary
hepatization, for it is not that pneumonia which is most extensive that
is accompanied by the greatest heart-flagging. Heart-failure may exist
before, or just as, consolidation is beginning. In many pulmonary
affections the obstruction to the pulmonary circulation is greater than
in pneumonia, and yet there is no heart-failure. The pneumonia with the
highest temperature-range is not necessarily the pneumonia in which
heart-failure is most marked
or earliest to develop. There are
many diseases in which there is a much higher range of temperature and
yet no evidence of heart-failure occurs.
If a prolonged high temperature is the cause of feeble heart-power by
the parenchymatous changes which it induces in its muscular fibres,
such a high fever is not met with in pneumonia, and the heart is rarely
found at post-mortem to exhibit such changes. May not the
heart-failure, as indicated by a rapid, feeble, and intermittent pulse
in pneumonia, be due to the presence in the blood of a morbific agent
(as in certain infectious diseases) which so affects the nerve-centres
which supply the heart that its contractile power is diminished and its
rhythm disturbed? The pulse early shows commencing heart-failure by
each cardiac pulsation producing a variable filling of the arteries
with blood; hence the beats first vary in force, then waves occur, then
true intermissions. I have been able to detect this heart-insufficiency
by these variations of the pulse within twenty-four hours after the
onset of a pneumonia, and occasionally during the initiatory chill.
In children the pulse-rate is greatly increased; it may reach 200 in a
minute. It is very small, unequal and irregular, but never intermittent.
In senile pneumonia the pulse is not a reliable indication. The pulse
may be only 50, and yet this would be a rapid pulse for the particular
case in which it occurs.
In old age, both in health and in disease, the pulse has a fictitious
hardness on account of arterial changes. The pulse may not be
intermittent or irregular, yet the heart may be very irregular and
intermittent in its action. Again, the pulse may be feeble and
intermittent and the heart be acting regularly.
Remittence of the pulse is quite common in senile pneumonia independent
of cardiac changes. The action of cold upon the surface in the aged is
very quickly indicated by the radial pulse lessening its volume and
strength, so that if the pulse at the wrist is taken it should be from
the arm which has been covered. To avoid error, the pulse in senile
pneumonia must be counted at the heart.
The surface of the body may be pungently hot and dry until the crisis
is reached, or it may be bathed in perspiration from the onset of the
disease. A moist surface has been regarded as a very favorable sign,
but when in the height of the disease the parched skin becomes moist
and the patient is not relieved, it is an unfavorable rather than a
favorable symptom, and is met with more often in fatal cases than in
those that recover.
In most cases of croupous pneumonia the expression of the countenance
is characteristic. It is one of anxiety, and over the malar bones is a
mahogany flush—not, as in typhus fever, diffused, but well defined and
circumscribed, so that it is sometimes called the pneumonic spot. While
the cheeks exhibit a spot of this dusky hue, the rest of the face may
have an earthy pallor. Bouillard states that the pneumonic flush on the
cheek is most marked when the pneumonia has its seat at the apex of the
lung. Some authorities state that the cheek flushes most or solely on
the affected side, while others35 have shown that the cheek on the
side opposite to that affected is the one that is usually flushed. In
this connection it is interesting to mention the case of Jaccoud, who,
suffering from an attack of pneumonia himself, noticed for twenty-four
hours preceding the pneumonia signs a flush and a burning sensation in
the cheek opposite to the side affected. Usually one cheek is more
flushed than the other, and this is undoubtedly due to disturbance of
the vaso-motor system.
35 Barthez and Rilliet.
When the impediment to the circulation is excessive, or when vaso-motor
disturbance is marked, the lips become cyanosed. At the time of crisis
the face becomes paler.
In about one-half the cases pneumonia is attended by an herpetic
eruption upon the lips, nose, cheeks, or eyelids. It rarely appears
before the second or third day. It may not appear until the crisis is
reached. Herpes occurs with varying frequency in different years, but
is more commonly met in pneumonia than in any other febrile state. One
winter nearly every case of pneumonia in Bellevue Hospital was
accompanied by herpes labialis. When sweating exists and involves the
entire body, it is very frequently accompanied by sudamina, which are
either abundant or sparse, and seem to have a critical significance.
In children, while the surface of the body is hot and dry the
extremities are cool. The pneumonic flush instead of having a mahogany
tint assumes a bluish-white tint. Cyanosis of the extremities is more
frequent than in adults, and herpes labialis more common. All the
cutaneous symptoms are exaggerated in children.
In old age the pneumonic flush is often the first objective sign of
pneumonia. The eyelids alone are cyanotic. If the face is dusky at
first, it subsequently assumes a sallow hue, and the surface-heat,
which is greatest in the morning, is succeeded by a cold, clammy perspiration.
Cerebral Symptoms.—The cerebral symptoms in the early stage of
pneumonia are not very significant. Headache is usually present at the
onset, and may continue throughout the disease. It usually steadily
diminishes after the third day. If it is severe in the evening, there
will be slight delirium at night—so slight as often to escape notice.
Delirium and convulsions rarely occur except in debilitated subjects
and in persons of enervating habits. It is most frequently met with in
alcoholic subjects, and then it assumes the character of delirium
tremens. It is an active, busy, restless delirium: the patient is
constantly talking, but seldom in a coherent manner. Sometimes, in
those who are not alcoholic subjects, the delirium may assume an active
and violent character. Whenever active delirium is present, it is
important to make careful and diligent search into the previous habits
of the patient.
Pneumonia of the apex is more apt to be accompanied by severe cerebral
symptoms than when it has its seat at the base.
Delirium may pass into coma. When delirium and headache are marked
symptoms, muscular tremors (subsultus tendinum) are very apt to occur,
with insomnia and frightful hallucinations. Indeed, these cerebral
symptoms are often so prominent in alcoholic pneumonia, and occur so
early, that the pneumonia may be wholly masked, and will only be
discovered by the temperature-range and by a careful physical
exploration of the chest.
When delirium is present in feeble patients, it assumes a low muttering
typhoid type, and a state of stupor is soon reached.
Among the rare nervous symptoms met with in pneumonia may be mentioned
photophobia, disturbances of vision, and deafness.
In children the cerebral symptoms are more prominent than in adults,
and they do not seem to be influenced by the extent of lung involved.
Stupor and restlessness on the one hand, or headache, delirium, and
convulsions on the other, may usher in pneumonia in children without
any prodromata.
Sometimes children pass rapidly into a semi-comatose condition which
has not been preceded by delirium or convulsions. Convulsions are as
common in children as they are rare in adults, and occur with greatest
frequency and severity during dentition. The convulsions may be general
and resemble those of epilepsy (pneumonie éclamptique of Barthez and
Rilliet), or they may attack single muscles or groups of muscles, the
child occasionally passing into a tetanic or opisthotonic condition.
If convulsions do not occur until late they are quickly followed by a
deep and fatal coma. A very rare occurrence is partial paralysis of the
muscles which were involved during the convulsive period. Such
paralysis is often
permanent. Again, the cerebral symptoms may
closely resemble those which attend cerebro-spinal meningitis—viz.
headache, constipation, great prostration, delirium, convulsions,
opisthotonos, and strabismus. As in meningitis, there is a peculiar
cry, and all the symptoms may point directly to the brain. These
symptoms are most likely to be present in the pneumonia of the apex in
children from five to seven years of age.36
36 This form is the pneumonie méninges of Barthez and
Rilliet.
In senile pneumonia headache may persist throughout the entire attack;
it is usually accompanied by delirium of a mild type, especially when
the apex of the lung is involved. These patients are very loquacious
and have a constant desire to get out of bed.
Alimentary Tract.—The symptoms referable to the digestive apparatus
are neither diagnostic nor important. Nausea and vomiting are not
infrequent, and in about 15 per cent. of all cases are among the
initial symptoms. Gastric symptoms, when severe and persistent, greatly
endanger life. There is no characteristic appearance of the tongue: it
may be normal throughout, or covered with a creamy-white fur, which
becomes dry and brown as the disease advances. In severe cases and
toward the end of the disease the lips and tongue become brown, dry,
and cracked, and sordes collect on the teeth. Anorexia is marked at the
onset, and the thirst is intense. When convalescence commences the
tongue becomes clean and the appetite returns. Occasionally there is a
catarrh of the oral mucous membrane. Diarrhoea may occur as one of the
initial symptoms. It is most apt to be present when there are nausea
and vomiting. As a rule, the bowels are constipated and the stools dry.
In young children nausea and vomiting are more common, and in 50 per
cent. of the cases usher in the disease. They usually cease on the
second day, although they may persist until the crisis occurs.
Excessive and violent diarrhoea may precede a fatal termination.
In senile croupous pneumonia the tongue early becomes dry, shrivelled,
and covered with a thick brown coating, and is protruded with
difficulty. Although these patients do not complain of thirst, they
take with avidity fluids that are placed to their lips. As the period
of crisis is reached critical diarrhoea is of frequent occurrence.
Loss of strength occurs earlier and is more marked in pneumonia than in
any other acute disease except typhus fever. Pneumonia patients become
very weak within the first five days. The recovery of strength during
convalescence is rapid.
Urine.—The urine at the onset of pneumonia is scanty, high-colored,
and of high specific gravity. The amount of urea excreted is twice or
three times more than the normal. The excess of urea increases until
the crisis, and then suddenly diminishes with the fall in temperature,
often below the normal standard.37
37 The daily amount of urea normally excreted is subject to
great variations: it ranges between 355 and 460 grains. Parkes gives
the result of 25 different observations: the lowest estimate was 286.1
gr. and the highest 688.4 gr.
Uric acid is also increased, and follows the same course as that of the
urea. The inorganic salts of the urine, especially the sodium chloride,
are diminished, and during the height of the pneumonia may be wholly
absent. Much has been written concerning this diminution, which is by
no means peculiar to pneumonia, but in no other acute disease is its
diminution so constant and marked a symptom. Sodium chloride is
probably retained in the system, for when the salt has been
administered in large quantities none has appeared in the urine. The
reappearance of the chlorides in the urine marks the approach of
convalescence, and when the crisis occurs they appear in excess,
following an opposite course to the urea and uric acid.
Although these last two ingredients are in very rare cases retained,
the
same as the chlorides, to appear when the crisis occurs,
their retention is usually accompanied by a critical diarrhoea, which
is followed by a prolonged convalescence. The diarrhoea is undoubtedly
due to the irritation caused by the urea.
Parkes38 states that sulphuric acid is increased and phosphoric acid
is diminished, but Huss affirms that both acids are diminished. With
the increase of the urea and uric acid, and diminution of chlorides,
biliary pigment will appear in the urine, and occasionally the biliary acids.
38 On the Urine.
Slight albuminuria is an ordinary phenomenon of pneumonia, and, though
usually met with in the second stage, it may appear at any time. This
symptom is present in 35 per cent. of all cases. Its presence is a
point of resemblance between pneumonia and other acute blood diseases.
The more severe the pneumonia, the more marked is the albuminuria. Some
have ascribed its presence to passive hyperæmia the result of the
pulmonary obstruction. This is questionable, except in those rare cases
where venous engorgement is indicated by cyanosis, enlargement of the
liver, jugular pulsation, etc.
In children the amount of urine corresponds to the quantity of fluid taken.
Critical Phenomena.—At the end of the first week, during which all the
symptoms have increased in severity, the continued fall of temperature
tells us that convalescence is established. As the temperature falls,
profuse (critical) sweating occurs. Both of these phenomena may occur
to such an extent that for hours the condition of the patient is one of collapse.
In rare cases death has occurred in the midst of these symptoms. The
respirations and pulse-rate are diminished in frequency, the pulse
being small and frequently exhibiting dicrotism. The cough becomes
loose, the dyspnoea abates, the flush disappears from the cheek, the
sputum is more copious, and is expectorated with less difficulty; it
loses the rusty color from metamorphosis of its hæmoglobin, diminishes
in viscosity, and no longer adheres to the side of the vessel, but
becomes more opaque, of a creamy consistency, and resembles that of
simple bronchial catarrh. When resolution is retarded, the
creamy-yellow tint may give place to an almost black hue, on account of
the excessive amount of pigment present. As convalescence advances, the
sputa become scantier, more mucous, watery, transparent and colorless.
At the time of crisis the intense thirst diminishes, the appetite
returns, pain in the side subsides, and the patient passes into a
quiet, natural sleep, to waken fully convalescent, suffering only from
extreme exhaustion.
Epistaxis, hæmaturia, and hemorrhage from the bowels sometimes occur at
the critical period, and may be regarded either as accidents or as the
result of the defervescence. After the crisis the amount of urea in the
urine (which during the height of the disease was augmented) falls to
normal or nearly to normal. Sodium chloride appears in the urine as
soon as the crisis occurs.
The critical phenomena in children are the same as in adults, and
frequently the fall in temperature is so great that for hours after the
crisis they lie half unconscious, with a cold surface covered with a
colliquative sweat. With the critical sweat there is often a catarrhal
flow from the nose. When children have been extremely restless or
delirious the crisis is marked by the patient passing into quiet sleep.
In old age, when recovery occurs, it is generally by crisis, and a
critical diarrhoea is much more frequent than a critical sweat.
In adults and in children the recovery of strength and flesh is rapid;
in the aged the period of convalescence is very prolonged, and often
does not begin (when the pneumonia is of the asthenic—typhoid—type)
until the fourteenth or fifteenth day; still, complete recovery may be reached.
Symptoms indicating Danger.—When croupous pneumonia is to terminate
fatally, dyspnoea is greatly increased; the patient suddenly sinks; the
pulse
becomes extremely small, rapid, irregular, intermittent,
and dicrotic. Large moist râles are heard over the larger bronchi and
trachea, while the auscultatory signs of pulmonary oedema become more
and more apparent. The sputa become frothy, liquid, and blood-stained,
or are entirely suppressed. The respirations become more and more
hurried, the face is sunken and livid, the extremities are cold, and
the superficial capillary circulation is more and more interfered with,
as is indicated by the cyanosis. The body is bathed in a profuse cold
perspiration. The fatal issue is usually preceded by coma.
The temperature may steadily rise up to the time of death, or death may
occur in the defervescence. In alcoholic pneumonia death is preceded by
cerebral symptoms, such as somnolence, numbness of the limbs, a sense
of formication, and slight convulsive attacks.
In children death is often preceded by convulsions or coma. If the
disease is protracted, death may be preceded by extreme exhaustion and
collapse. Cyanosis and extreme rapidity of the pulse are usually
present in children just before the fatal issue.
Senile pneumonia may end fatally within a few hours after its onset in
a most unexpected manner. The aged patient walks apathetically about,
totters to the bed, lies down, and dies. If the pneumonia has existed
for a number of days, the signs of a fatal termination are sallowness
of the face, a cold clammy skin, expansion of the alæ nasi, and a
sudden rise or fall of the temperature. The inspirations become mere
gasps, and, following the apathy, the patient gradually lapses into
complete coma.
Symptoms which attend the Termination of Pneumonia in Abscess.—Acute
pneumonia terminates in abscess in from 1 to 2 per cent. of all the
cases. It is therefore a rare termination. It is most frequent in
debilitated, weak subjects and in those who have received a depressing
plan of treatment. The expectoration is exceedingly copious and fetid,
and the sputa are yellowish or yellowish-gray in color, consisting
almost wholly of purulent matter. Pigment is usually found in the
expectorated masses, and when shreds of pulmonary tissue are present
the diagnosis is established. The fever assumes a hectic type and is
accompanied by rigors and sweats.
After these symptoms have continued for a time, the patient grows
weaker and emaciated, and death results from exhaustion, from asphyxia
(when a large bronchus is plugged with pus), or from the discharge of
the abscess into a neighboring cavity.
DaCosta states that "pulmonary pneumonic abscesses are at the base of
the lung;" Fox locates them "at the apex;" Green, "on the upper lobe;"
I have found them in both situations.
The physical evidences of a lung-cavity are the most reliable signs of
pneumonic abscess. Abscess is a very rare termination of croupous
pneumonia in children. In old age the formation of abscesses is never
evinced by any well-marked symptoms. The finding of elastic fibres in
the sputa with the physical signs of a cavity are the only diagnostic signs.
Symptoms which attend the Termination of Pneumonia in
Gangrene.—Gangrene as a termination of pneumonia has been found in
about 14 per cent. of cases.39 This must be regarded as an
exceptionally high percentage. Its occurrence is usually accompanied by
symptoms of sudden collapse. The pulse becomes rapid, feeble, and
intermittent, the face is pale and of a deathly hue, and there is a
profuse expectoration of blackish-green masses containing shreds of
decomposed and decomposing lung-substance of an exceedingly fetid odor.
The breath is fetid and the whole body emits a cadaverous smell. The
rapidly-increasing prostration is sometimes accompanied by hemorrhage.
39 In 28 out of 200 cases (Guy's Hospital Reports, Sec.
vii., 1848).
The sickening and indescribable odor of pulmonary gangrene is most
perceptible after an attack of coughing. Gangrene has its most frequent
site in
the lower lobes of the lung, and it is here that a
careful search must be made for the rather ill-defined physical signs
which attend its development. In old age, when a pneumonia is to
terminate in a gangrene, typhoid symptoms appear very early, and death
occurs with symptoms of the profoundest collapse within five days from
the initial chill.
Symptoms which attend the Termination of Pneumonia in Purulent
Infiltration.—The symptoms of purulent infiltration differ but
slightly from those of the third stage of pneumonia. When resolution
does not take place at the period of crisis, and the temperature
remains high, accompanied by symptoms of prostration and profuse putrid
expectoration, with none of the physical signs of resolution, purulent
infiltration is to be suspected. Death may result from exhaustion, or
recovery take place after a prolonged convalescence (see Fig. 38).
|
FIG. 38.
|
|
|
Croupous Pneumonia in the Adult, terminating in
Purulent Infiltration: Death on fourteenth day.
|
Mild delirium is a frequent symptom during the stage of purulent
infiltration. The sputa contain a large number of cells in various
stages of fatty degeneration. The temperature has regular evening
exacerbations, and often ranges higher than during any preceding period
of the disease. The tongue becomes brown and dry, sordes collect upon
the teeth, and the patient passes into a typhoid state.
Typhoid pneumonia is a term which has been applied to a variety of
croupous pneumonia which is attended by typhoid symptoms. It has also
been called asthenic, low, or nervous pneumonia. There are symptoms of
extreme prostration from its onset. After well-marked pneumonic
symptoms have been present for a few days, the patient passes into a
condition of extreme prostration.
There is little or no expectoration, no dyspnoea, no pain, no cough.
Sordes collect on the teeth and gums; the tongue becomes thickly coated
with black crusts; the pulse becomes small, feeble, and rapid, and
there is a tendency to the formation of bed-sores; and then occur
stupor, somnolence, and a continuous low muttering delirium. This form
of pneumonia is met with most frequently in the aged. In some cases
there is marked disturbance of the special senses.
Tremors and subsultus tendinum frequently coexist. It may be
accompanied by glandular swellings, by sharp and darting muscular
pains, by arthritic symptoms, or by great gastric disturbance. It is
not infrequent in epidemics,
and it may follow or accompany
erysipelas, Bright's disease, alcoholismus, or phlebitis. It is always
a grave condition, but recovery is possible. Convalescence, which is
very tedious, may commence as early as the twelfth or fourteenth day.
Sometimes a modification of typhoid pneumonia accompanies dysentery,
intestinal catarrh, or a phlegmonous gastritis. There are great
sweating, profuse diarrhoea (colliquative), and high fever. The odor of
the sputa resembles that of gangrene of the lungs. Such cases commonly
end fatally.40
40 Cyclo. Pract. Med., iii., art. "Gastritis."
Bilious or Gastric Pneumonia.—Croupous pneumonia occurring in malarial
districts, accompanied by gastro-enteric or hepatic symptoms, is known
as malarial or bilious pneumonia. It has all the characteristic
symptoms of pneumonia of a very severe type, but the fever is
paroxysmal. The tongue is heavily coated; nausea and vomiting are
common, and may persist throughout its entire course; the epigastrium
is distended and tender; the skin is jaundiced; the liver is enlarged,
and there is usually an exhausting diarrhoea, attended by greenish,
black, viscid, and inodorous stools. The hepatic congestion and
jaundice are due to a coincident gastro-duodenal catarrh.
Bilious pneumonia may be of a sthenic or asthenic type. The theory that
the liver becomes inflamed by extension from the lung is untenable.
The symptoms of bilious pneumonia have frequently led to a diagnosis of
typhoid gastric fever or some severe acute affection of the intestinal
tract. But a reference to the physical signs will remove all doubts.
Bilious pneumonia runs a more protracted course and has a much longer
period of convalescence than ordinary croupous pneumonia. In old age
this form is not infrequent. The vomiting is distinctly bilious in
character, and at this period of life somnolence and stupor are quite
common, and are exceedingly unfavorable symptoms.
Latent Pneumonia.—Pneumonia in adults is seldom latent unless it
complicates some disease whose symptoms are so severe, and the
attending prostration is so great, as to obscure the characteristic
signs of the pneumonia. Intercurrent senile pneumonia is always latent,
and Grisolle says that an exploration of the thoracic organs in the
majority of such cases gives negative results. If, then, an
intercurrent senile pneumonia runs its course without expectoration,
without dyspnoea, without the pneumonic flush, and without any of the
physical signs of pneumonia, its diagnosis must rest—first, on the
extreme frequency of pneumonia in old age; secondly, on the fact that
of all the phlegmasiæ of advanced life pneumonia is the one which is
oftenest latent; thirdly, that of all the acute diseases in old age
pneumonia is attended by the highest range of temperature and the
greatest prostration. When an old person has a slight rigor followed by
febrile movement, with great prostration, for which no explanation can
be found, pneumonia may be suspected, even though all its diagnostic
signs are absent.
Intermittent or remittent pneumonia, which is described by some authors
as a distinct type, is a form of acute pneumonia in which a malarial
element is so pronounced that all the pneumonic symptoms, even the
physical signs, undergo distinct intermission, returning each day with
increasing severity. Occasionally, instead of the quotidian it assumes
the tertian type. During the intermission the temperature may fall to
normal. Severe chills and sweating are often present, and the pneumonia
is not infrequently double.
The malarial conditions which give rise to this type of pneumonia occur
more frequently in our Southern and Western States than in any other
part of the world.
PHYSICAL SIGNS.—By studying the physical signs of croupous pneumonia
in connection with the different stages of its morbid anatomy, their
importance as elements in diagnosis and prognosis can best be
appreciated.
Stage of Engorgement.—The physical signs indicative of the first
stage of croupous pneumonia are usually present within twenty-four
hours after its invasion. If the pneumonia is central, their appearance
may be delayed until the third day.
Inspection.—On inspection the movements of the affected side are
noticed to be more or less restricted, while the unaffected side moves
as in health. In double pneumonia the respiratory movements will assume
a costal type, attended by an increase in the abdominal breathing.
Palpation.—On palpation there is more or less increase in the vocal
fremitus on the affected side. The degree of increase corresponds to
the extent of the engorgement. It must always be remembered that
normally the vocal fremitus is more marked on the right side than on
the left.
Percussion.—There is slight dulness over that portion of the
chest-wall which corresponds to the affected portion of lung: its
extent varies with the amount of lung involved. It is never well marked
until the end of the first stage, although the pulmonary capillaries
are engorged with blood from the commencement. Even at the end of this
stage the intensity of the percussion sound, although diminished and
muffled, has a slightly tympanitic quality, due to the fact that the
exudation has not completely displaced the air in the distended
alveoli. Very extensive central pneumonia may fail to give either
increase in vocal fremitus or dulness on percussion until the second
stage is well advanced. Absolute dulness during this stage is of rare occurrence.
Auscultation.—During the dry stage, which according to some41 is
said to precede the exudation stage, there will be noticed a feebleness
and unnatural dryness of the respiratory murmur. Sometimes it is harsh,
at others feeble and loses the peculiar breezy, rustling quality of the
normal respiratory sound. If it is less intense over the affected
portion of the lung, it is exaggerated over the unaffected portion.
These changes are apt to pass unrecognized unless auscultation is
practised frequently and early in the disease. As soon as the
engorgement is well marked and exudation takes place into the
air-cells, fine crackling sounds are heard at the end of inspiration.
These sounds are called crepitant râles, and are regarded as the
characteristic sign of the first stage of pneumonia. They resemble
those produced by throwing salt on live coals or rubbing the hair in
the neighborhood of the ear between the fingers. These râles do not
necessarily depend upon the presence of fluid in the alveoli, but may
arise from the sudden separation of the alveolar walls at the end of
inspiration when they have been agglutinated by a tenacious exudation.
They are as numerous as they are minute, are unaffected by coughing,
and remain audible over a circumscribed space from twelve to
twenty-four hours. Whenever the pneumonic stages follow each other in
rapid succession, the crepitant râle may not be heard. It is rarely
present in a pneumonia which is developed during an attack of acute
articular rheumatism. With the crepitant râle the respiratory murmur is
feeble or assumes a broncho-vesicular character.
41 Stokes.
When, as often happens, pneumonia has been preceded by or complicates
any other thoracic affection, the crepitant râle will be mingled with
the sounds arising from that particular condition. It is said42 that
bronchial breathing is sometimes heard in this stage of pneumonia. The
voice-sounds undergo slight increase in their intensity over the seat
of the pneumonic engorgement.
42 Traube, Annal. der Charité, i. 286.
In children the crepitant râle is frequently absent, and, though it may
be heard at the end of a full inspiration after coughing, it is never
so fine or distinct as in adults. In children there will be no increase
in vocal fremitus if, as often happens, a large bronchus leading to the
inflamed spot is plugged with mucus.
In old age the physical signs of adult pneumonia are modified by
certain physiological changes which occur in the lungs and chest-cavity
of the aged. The more complete bony union of the chest-walls, the
curvature of the spine, the rigidity of the bronchial tubes, the
rounded form of the chest, and the senile rarefaction of the lungs,
give rise to extra resonance on percussion as compared with an adult
chest. On account of the great arching of the sternum and the
deposition of carbonaceous material at the apex of the lung, the
clavicular region near the median line gives a dull percussion sound.
The scapular and supra-scapular regions are less resonant than in the
adult, on account of the tilting of the scapulæ due to curvature of the
spine. There is a loss in the vesicular element of the respiratory
murmur, and it resembles the sound produced by a forceful expulsion of
air from the compressed lips. When the septa or the alveoli are torn
and greatly distended, it has a bronchial character. Its intensity
varies: at one moment it is loud, at another hardly perceptible; the
variation occurs not only in the same individual, but in different
individuals of the same age. The vocal sounds are loud and
bronchophonic in character, and have a vibration closely resembling
oegophony. It is also to be mentioned that it is almost a physiological
condition for old people to have bronchorrhoea; hence mucous râles may
be present during the whole period of advanced life, and if one relies
on the usual crepitating râles of adult pneumonia for a diagnosis he
will be misled.
Inspection and palpation in the first stage of senile pneumonia furnish
little positive information. Percussion will give little dulness until
the lung has reached the stage of red hepatization, and even then it
may be so slight as to pass unnoticed. Very early in the disease the
respiratory murmur is feeble and indistinct over the affected portion,
while the portion of lung that is not involved assumes, for the time,
all the characters of a normal adult respiratory murmur. Again, the
breathing over the pneumonia may be intensely puerile and interrupted.
The crepitant râle is rarely present in the first stage of senile
pneumonia, but subcrepitant râles and large moist râles resembling
those of bronchitis are heard during the whole of this stage. The
explanation of the absence of the crepitant râle is to be found in the
physiological condition of the air-cells just referred to. Sometimes,
on a deep inspiration after violent coughing, fine crepitation is
heard, but upon careful examination it will not be found to differ from
the râles of capillary bronchitis. It may be stated as a general rule
that the feebler and more superficial the respirations the less
distinct will be the adventitious sounds.
The physiological rigidity of the bronchi in old age favors the early
development of bronchial breathing, which is often the first physical
sign of senile pneumonia. One of its peculiarities, when occurring in
the stage of engorgement, is that it is most distinct at the root of
the inflamed lung.
Stage of Red Hepatization.—The physical signs of the second stage of
croupous pneumonia are more diagnostic than those of either of the
other stages.
Inspection shows the expansive movements of the affected side to be
more markedly diminished than in the first stage, while those of the
healthy side are increased. Frequently there is absolute loss of motion
over the inflamed lung.
Palpation.—By palpation the vocal fremitus is usually increased on the
affected side over the consolidated lung-tissue. In some instances it
may be only slightly increased, and in rare instances it will be found
less marked upon the affected side than upon the healthy. Palpation may
also reveal slight displacement of the heart from the pressure of the
distended lung; and in rare cases well-marked pulsation is felt over
the affected lung.43
43 Skoda, Stokes, and Graves regard this as the result of
increased pulsation of the arteries in the inflamed spot; and Walshe
and Fox rather admit it, but Grisolle denies it.
It is evident that the vibrations of the vocal cords can be
transmitted from the trachea through the bronchi and lung to the
chest-wall, and there is no reason why the cardiac impulse may not
likewise be transmitted through a solidified lung to the chest-wall.
If the pneumonia is central, the vocal fremitus may not be increased.
It is diminished when there is an abundant pleuritic exudation over the
pneumonic lung.
Percussion.—On percussion there will be marked dulness over that
portion of the lung which is the seat of the pneumonia, while over the
healthy portion, as well as over the opposite lung, there will be
exaggerated resonance. The nearer the hepatization approaches the
surface of the lung, the more marked will be the dulness. There is a
peculiar sense of resistance on percussion over a completely airless
hepatized lung which is not present in solidification from other
causes. The exact outline of an hepatized lobe can often be traced on
the chest-wall.
The tympanitic quality which is sometimes present during the stage of
engorgement may continue anteriorly during the second stage, and yet
posteriorly the dulness will be complete. A tympanitic percussion sound
is sometimes elicited over that portion of lung which is adjacent to
the consolidated lobe. When an upper lobe is consolidated, forcible
percussion may elicit a tympanitic sound, for the column of air in a
large bronchus will vibrate under forcible percussion. The cracked-pot
sound (bruit de pot fêlé) is occasionally met with over those relaxed
and permeable parts of the lung in the immediate vicinity of the
consolidation. When this sound is present over the consolidated
portion, it is due to the sudden expulsion of air from one of the
larger bronchi. It is most frequent in young persons with thin, elastic
chest-walls. The cracked-pot sound in pneumonia is not increased in
intensity when the patient's mouth is open.
In basic pneumonia the subclavicular percussion note may be distinctly
amphoric in character. Dulness may appear within twelve or twenty-four
hours after the onset of a pneumonia, or it may be delayed until the
fourth day.
Auscultation.—As soon as the air-cells are completely filled by the
pneumonic exudation, the crepitant râle ceases and bronchial
respiration is heard over the affected lung. The bronchial breathing is
due to the fact that the vesicular element of the respiratory sound
disappears on account of the complete consolidation of the vesicular
structure, and the tracheal element of the respiration is conveyed to
the chest-walls through the consolidated lung. It often has a metallic
element, or may sound like the tearing of a piece of linen. Bronchial
respiration is more intense in pneumonia than in any other disease.
Laennec taught that bronchial respiration was due to the superior
conducting power of condensed lung. Skoda combats this view, and says
that bronchial respiration is generated or magnified in caverns and in
the bronchi of condensed lung-substance by the air in these cavities
and in the bronchi vibrating in consonance with that within the
trachea. The condition necessary for this consonance is provided in the
circumstance that the air is pent up in confined spaces whose walls
reflect the sonorous undulations.
The more complete the consolidation, the more intense is the bronchial
respiration. At the commencement of this stage the tubular breathing
only attends expiration, while later it accompanies both acts.
Pleuritic exudation may mask or render this sound very indistinct. It
may in rare instances be absent even when extensive consolidation
exists and the pleura is perfectly normal. This can be accounted for in
most cases by the plugging of a large bronchus. There are cases in
which its absence is inexplicable.
The vocal sounds are increased in intensity and bronchophony is heard
over the consolidated lung. The physical conditions of the lung
which give rise to bronchophony have the same diagnostic significance
as the bronchial respiration, and in all instances its occurrence, its
distinctness, its temporary disappearance, and its reappearance are
dependent upon precisely the same conditions as are the changes in the
bronchial respiration. If the pleural cavity is partially filled with
fluid, bronchophony will be indistinct or absent below the level of the
fluid, while at its level the voice-sounds will be either bronchophonic
or oegophonic.
During this stage the heart-sounds are transmitted to the surface over
the hepatized lung with greater intensity than normal.
In children dulness is especially marked in the infra-scapular region
of the affected side. Some authors44 speak of a feeling of greater
solidity below than above the scapula, which can be detected before the
ear can detect actual dulness on percussion. Vocal fremitus may be
increased, but it is not reliable on account of the changes in the voice.
44 West.
In old age, inspection and palpation give negative results. Dulness on
percussion in old age would be regarded as normal resonance in the
adult; hence the percussion sound in senile pneumonia may be only
relatively dull. The tubular or bronchial breathing in the second stage
of senile pneumonia is more intense than in adult pneumonia. Small
gurgles or mucus râles generally persist throughout this stage.
Bronchophony is not well marked. On causing the aged patient to cough
and expire violently, tubular breathing may be heard where it was
before absent.
Stage of Gray Hepatization.—There is no abrupt transition from the
second to the third stage of pneumonia, so that the physical signs of
the early part of gray hepatization are the same as those of the second stage.
Inspection.—As resolution progresses, expansive motion on the affected
side becomes more and more apparent.
Palpation.—On palpation the vocal fremitus will be found approaching
normal, its intensity diminishing as resolution occurs.
Percussion.—Dulness on percussion becomes less and less marked, but of
all the signs this is the last to disappear. Rare cases are mentioned
where it has disappeared in twenty-four hours after the commencement of
resolution by crisis. As the percussion sound approaches the normal, a
tympanic note is again present in circumscribed spots.
Auscultation.—The bronchial respiration that was present in the second
stage gives place to broncho-vesicular breathing. This soon becomes
blowing, then indeterminate, and finally approximates to, and merges
into, normal vesicular breathing. Bronchophony gives place to
exaggerated vocal resonance in connection with the changes in the
respiratory and vocal sounds. The crepitant râle returns, but is soon
obscured by larger and moister crepitating sounds, "the resolving
subcrepitant râle of pneumonia," called also the râle redux. Large and
small mucus râles, sibilant and sonorous, accompany the subcrepitant
râles, to disappear only when resolution is complete. Not infrequently
the bronchial râles that are developed during the stage of resolution
are of that character called consonant45 or ringing.46
45 Skoda.
46 Traube.
The physical signs of this stage are all retrogressive, and they
disappear in the opposite order to that in which they appeared. In rare
instances resolution is so rapid that the subcrepitant râle is not
heard. In this class of cases dulness on percussion and bronchial
breathing continue for some time after the crisis.
In children, bronchial breathing rarely disappears before the seventh
day. It is often accompanied by the subcrepitant râle. When resolution
takes place, bronchial breathing and the subcrepitant râle will
disappear at the same time.
In old age, inspection, palpation, and percussion give similar
results as in adult pneumonia. On auscultation coarse crepitating
sounds and loud gurgles are often heard at a distance from the site of
the pneumonia. The râle redux is not distinctive of or peculiar to the
third stage of senile pneumonia. The sounds heard during this stage are
called mucous crepitations, by which is meant liquid crepitating râles
produced in tubes intermediate between the bronchioles and the larger bronchi.
If pneumonia terminates in purulent infiltration, the temperature
remains high and symptoms of great prostration are developed. The
bronchial breathing continues, and becomes more intense, dulness on
percussion persists, and sharp, high-pitched râles resembling fine
gurgles are abundant.
The occurrence of abscess or gangrene is indicated by the physical
signs which attend the formation of cavities in consolidated
lung-substance.
No one of the physical signs which is present in the different stages
of pneumonia is sufficient for a diagnosis, but the manner and order of
their occurrence, and their relation to the symptoms which mark the
different stages of the disease, enable one to reach a positive
diagnosis in all typical cases. The only symptom of croupous pneumonia
which can be regarded as diagnosticated is the sputum.
The physical signs of pulmonary abscess in the aged are very generally
wanting. Distinctly localized gurgling and cavernous respiration may,
when taken in connection with the rational signs, suffice for an
approximate diagnosis, but the great rarity of abscess in old age
should make one cautious in its diagnosis. The sputa will greatly aid
in such cases.
The physical signs of senile pneumonia are subject to greater
variations than ever occur in pneumonia in the adult, and often they do
not even follow the course, irregular as it is, which has just been described.
Gray hepatization or abscess may be reached without any distinctive
auscultatory signs, even after repeated and careful examination. The
râle redux of resolution may be absent, dulness and bronchial breathing
being immediately followed by normal (senile) resonance without
crepitation. This occurs most frequently in the typhoid variety.
DIFFERENTIAL DIAGNOSIS.—In typical cases of croupous pneumonia (except
in childhood and old age) the diagnosis is not difficult. The prolonged
chill of invasion, the rapid rise of temperature, the accelerated,
panting respiration, pain, cough, characteristic sputum, increase in
vocal fremitus, dulness on percussion, the crepitant râle, bronchial
breathing, and bronchophony are sufficient to establish the diagnosis.
Croupous pneumonia may be confounded with acute pulmonary congestion
and oedema, capillary bronchitis, pleurisy, hypostatic congestion,
catarrhal pneumonia (in children), pulmonary apoplexy, meningitis, and
typhoid fever.
Pneumonia begins with a chill, while pulmonary oedema has no chill.
Pneumonia is a febrile disease, while in pulmonary oedema there is no
rise in temperature. In pneumonia there is pain in the side; there is
no pain in pulmonary oedema. The sputum in pneumonia is viscid, rusty,
and microscopically pathognomonic; pulmonary oedema is accompanied by a
profuse watery expectoration. Pneumonia is commonly unilateral, and can
occur in any part of the lung, while pulmonary oedema is bilateral, and
usually occurs in the most dependent portion of the lung. In pneumonia
we have the crepitant, dry râle, while in pulmonary oedema we have
subcrepitant râles, larger and more liquid than those in pneumonia.
Bronchial breathing and bronchophony occur in pneumonia, and are absent
in pulmonary oedema. Percussion dulness is more marked in pneumonia
than in pulmonary oedema, and the diseases with which the latter
condition is apt to arise will aid us very much in the diagnosis.
Urinary symptoms are negative in pulmonary oedema, while in pneumonia
the chlorides are diminished or absent.
The stage of resolution in pneumonia is not infrequently mistaken
for general capillary bronchitis, but, though the subcrepitant râle is
present in both, it is heard all over the chest in capillary
bronchitis, while it is confined to a comparatively small space in
pneumonia. The expectoration is muco-purulent in bronchitis, and viscid
and fibrinous in pneumonia. The temperature is lower in bronchitis
(100°–103°) than in pneumonia (104°–106°). Capillary bronchitis is
bilateral, pneumonia usually unilateral. Capillary bronchitis does not
commonly begin with a chill, like that which occurs in pneumonia, but
comes on more insidiously and without pain. Capillary bronchitis gives
an exaggerated percussion note, while there is dulness on percussion in
pneumonia. There is bronchial breathing in pneumonia, and a feeble
vesicular murmur in capillary bronchitis. In capillary bronchitis the
cyanotic appearances are very much more marked than in pneumonia, and
there is no perversion of the pulse-respiration ratio. The breathing is
labored in capillary bronchitis, and panting in pneumonia. In capillary
bronchitis there are several slight attacks of chilliness; in pneumonia
there is usually only one chill, at the onset.
The chief points in making the diagnosis between pneumonia and pleurisy
are the pain, sputum, and percussion note. Pneumonia is ushered in by a
distinct chill, followed by a rise in temperature to 104° to 105°,
while pleurisy begins with chilliness or a number of slight rigors, and
the temperature is lower, rarely above 100°. The dry hacking cough of
pleurisy may be accompanied by slight mucous expectoration, while in
pneumonia the expectoration is characteristic. In pleurisy the
breathing is catching; in pneumonia it is panting. In pleurisy the face
is pale and anxious; in pneumonia the cheek bears a dull
mahogany-colored flush. In pleurisy the pulse is firm, small, tense,
and wiry; in pneumonia it is full and bounding. The amount of chlorides
in the urine is not altered in pleurisy, but in pneumonia they are
diminished or absent. The pulse-respiration ratio is not affected in
pleurisy, while in pneumonia it may fall as low as 2:1. There are no
critical days in pleurisy, while in pneumonia crisis occurs about the
fifth or seventh day. In pleurisy with effusion there may be bulging of
the intercostal spaces, and the heart may be displaced; these phenomena
never occur in pneumonia. The vocal fremitus is feeble or absent in
pleurisy, while in pneumonia it is much increased. In pneumonia there
is dulness on percussion, while percussion over a pleuritic effusion
elicits flatness, which changes with the position of the patient. In
pleurisy the grazing, rubbing, or sticky friction-sound may be heard
with both respiratory acts; in pneumonia we hear the crepitant râle. In
pleurisy the respiratory sounds are feeble or absent, as are the vocal
sounds, while bronchial breathing and bronchophony are marked in
pneumonia. It may be remembered, however, that if adhesions from an old
pleurisy bind the lung to the chest, vocal fremitus may be increased in
pleurisy. Again, bronchophony and bronchial breathing may exist in
pleurisy, but they are always diffuse, never sharp and tubular, as in
pneumonia, and are usually confined to the scapular region.
Hypostatic congestion of the lungs is accompanied by copious, watery,
blood-stained expectoration. In pneumonia the sputa, though bloody, are
rarely watery. Pneumonia occurs anywhere in the lung, and has
well-marked rational symptoms; hypostatic congestion occurs in the most
dependent portion of the lung, disappears when the patient sits up, is
accompanied by no rational symptoms except dyspnoea and expectoration,
and usually can be traced to a long-continued recumbent posture in
those who are suffering from extensive blood-changes.
It is often difficult to decide whether a child has catarrhal or
croupous pneumonia. It is to be remembered that catarrhal pneumonia is
always secondary, while croupous is primary. Catarrhal pneumonia
usually follows
a bronchitis, croupous pneumonia rarely. In
catarrhal pneumonia both lungs are involved; in croupous but one, and
often only a single lobe. Catarrhal pneumonia is accompanied by a
catarrhal sputum, while croupous pneumonia has a viscid, rusty,
fibrinous expectoration. There is no day of crisis in catarrhal
pneumonia, while croupous pneumonia in children almost always ends in
well-marked crisis. In catarrhal pneumonia dulness on percussion is
generally confined to the posterior dorsal region, and does not extend
so far forward as in lobar pneumonia. Again, the extent of the physical
signs and the rapidity of their development in catarrhal pneumonia are
in contrast with those of croupous.
The range of the temperature is a most valuable guide in their
differential diagnosis, since not only the height of the fever is
greater in croupous, but the temperature-curve is different, as seen in
the accompanying tracings:
|
FIG. 39.
|
|
|
Acute Lobar (croupous) Pneumonia in a Child: Recovery.
|
|
FIG. 40.
|
|
|
Acute Lobular (catarrhal) Pneumonia in a Child: Recovery.
|
Pulmonary apoplexy is rarely met with independent of valvular disease
of the heart or pyæmia. It is a non-febrile disease, while pneumonia
has marked pyrexia at the onset. In pulmonary apoplexy dyspnoea is very
intense and comes on abruptly; in pneumonia it comes on slowly and
progressively increases. The expectoration in pulmonary apoplexy
consists of small, black sooty-looking coagula, while in pneumonia the
viscid fibrinous mass contains numerous cell-elements other than
blood-corpuscles. In apoplexy the dulness is distinctly circumscribed,
and around it moist râles are heard, while in pneumonia the area of
dulness is more extended and râles are heard over the seat of the
dulness. The urinary symptoms are negative in pulmonary apoplexy; in
acute pneumonia the chlorides are diminished or absent. There is a
peculiar acid odor to the breath—an odor like that of tincture of
horseradish—in pulmonary apoplexy, never found in pneumonia.47
47 Guéneau de Mussey.
When croupous pneumonia has its seat at the apex of the lung, it may be
confounded with the first stage of phthisis. But the history of a
chill followed by the characteristic pneumonic symptoms will generally
enable one to make the differential diagnosis. Besides, the fever in
phthisis is irregular and is subject to irregular exacerbations and
remissions. If the signs of consolidation persist with little or no
change, if the temperature at no time falls to normal, if there are
night-sweats, if emaciation is progressive,—then the case is to be
regarded as one of phthisis, even though there may have been pneumonic
consolidation complicating it.
In children pneumonia is so frequently accompanied by marked nervous
symptoms that it may be mistaken for meningitis. Meningitis is
developed insidiously; has but slight febrile symptoms (102–103° F.),
which remit with comparatively great regularity; has a pulse which is
often slower than normal; has no thoracic symptoms, no dyspnoea nor
accelerated breathing; the face is pale and anxious; and the physical
signs of pneumonia are absent.
Sometimes a latent pneumonia with typhoid symptoms is mistaken for
typhus fever: especially is this the case when the latter is
prevailing. I frequently saw cases where such a mistake had been made
while in charge of the typhus-fever patients on Blackwell's Island
during a typhus epidemic. In these cases there will be active typhoid
symptoms, such as dry tongue, delirium, high temperature, etc. The
countenance in this pneumonia, although the cheeks may have a purplish
hue, does not exhibit that dull, heavy leaden expression so commonly
seen in typhus fever. Although there may be delirium in both instances,
the delirium in the former disease is of a milder type than in the
latter. The characteristic pneumonic expectoration is often absent in
this class of cases; therefore it cannot be relied upon as a point in
the differential diagnosis. If pulmonary consolidation is a
complication of typhus fever, it will not be developed until after the
sixth day of the fever, the time when the eruption is visible. If no
eruption is present, the pneumonic consolidation may be regarded as the
primary affection, and the symptoms which simulated those of typhus
fever may be regarded as secondary.
Pneumonia with typhoid symptoms is sometimes mistaken for typhoid
fever. It is called typhoid pneumonia. The differential diagnosis is
not difficult if one remembers that the pneumonia which complicates
typhoid fever does not come on until late in the fever, and the regular
history of typhoid fever precedes its development. On the other hand,
when the typhoid symptoms are present from the beginning or come on at
the end of the second stage of pneumonia, the physical signs of
pneumonia will attend or precede the typhoid symptoms. If a patient
over sixty years of age with this type of pneumonia is not seen until
the second or third week of his sickness, although evidences of
lung-consolidation may be found, it will be very difficult to decide
whether the pneumonia is or is not complicating a typhoid fever; and
under such circumstances a differential diagnosis may be impossible.
PROGNOSIS.—The mortality-rate of pneumonia is shown by the following
statistics: Of 12,421 cases treated in the hospitals at Stockholm, 11
per cent. died. In the Vienna hospitals 24 per cent. died. The Basle
hospital's report for thirty-two years gives 23 per cent. of deaths,
Grisolle reports 59 per cent. of deaths in those over sixty years of
age. In the United States medical reports from May 1, 1861, to July,
1866, of 61,202 cases which occurred among the white troops, 14,738
died, or a little more than 24 per cent.; and of 16,133 among the
colored troops (for the same period) 5233 died, or nearly 33 per cent.
The deaths from all other inflammatory diseases of the respiratory
organs for the same period were only one-seventh as many as from
pneumonia. The Confederate hospital reports give the rate of mortality
from pneumonia for twenty-five months of the same period as
331/3 per
cent. Of 255 cases treated in my wards in Bellevue Hospital during a
period of four years, the rate of mortality was 34 per cent.
The statistics given of private practice differ remarkably from
those of hospital reports, and are somewhat contradictory. Of Lebert's
205 cases, 73/10
per cent. died. Ziemssen lost only 31/3 per cent. of
his cases. Bennett (mentioning, however, that no complication existed)
lost none of his 105 cases. Brundes of Copenhagen lost more than 21 per
cent. of his 142 cases. Wilson Fox gives to pneumonia the fifth, and
Walsh the third, place among fatal diseases. The mortality-average from
all the published reports to which I have had access gives 20.1 per
cent. of deaths.
From such facts it must be admitted that a disease in which death
occurs in 1 out of every 5 cases should be classed among the very fatal
diseases. But the death-rate varies very much at different times: it is
to-day the same as when Andral wrote, nearly fifty years ago. He stated
that it varied from 33 to 2 per cent. There can be no doubt but that
treatment somewhat influences the variations in the
mortality-statistics, but not to such an extent as to account for the
great differences in the reports of different observers.
The prognosis depends more upon the age of the patient than upon any
other single element. In infancy the mortality is greater than in early
childhood, in which period statistics give from 4 to 6 per cent. as the
ratio. The period of dentition seems to influence the prognosis in
children. Between the ages of forty and sixty the death-rate is from 10
to 25 per cent.; uncomplicated cases will recover. After sixty the
prognosis is exceedingly grave, and the greater the age of the patient
the less are the chances of recovery.
Statistics do not give pneumonia its proper place among the fatal
diseases of old age. My own experience leads me to believe that it is
the most fatal of all acute diseases at this period of life, for the
large number of autopsies in which it has been found to be the cause of
sudden death in individuals of advanced years, and the frequency with
which red or gray hepatization is found at the autopsy when pulmonary
disease was not suspected during life, must greatly increase the
statistical rate of mortality. Many modern authorities, who have had
large experience in the hospital practice of the aged, state that
nearly nine-tenths of those who die over sixty-five die of pneumonia.
Pneumonia is more fatal in females than in males, in the proportion of
about 3 to 2.
Statistics vary in regard to the influence of seasons on the prognosis
in pneumonia. In some years the proportion of deaths is far greater in
summer than in either the spring or winter. And it must be acknowledged
that certain as yet unknown atmospheric influences are of the utmost
importance in determining the death-rate in different years. Statistics
do not show that the mortality-rate is greatest during cold weather.
The prognosis is greatly influenced by the extent of the pneumonia.
Double pneumonia is not often recovered from, and pneumonia of an
entire lung is more dangerous than when only a single lobe is involved.
In pneumonia at the apex in infancy and old age the prognosis is
unfavorable. The more feeble the patient at the time of the attack, the
less are his chances of recovery. Previous attacks have no influence
over the prognosis.
Most authors make mention of certain diseases that complicate
pneumonia. Few give condensed statements of their influence on the
death-rate. In 255 cases of my own, 87 were fatal and 168 recovered. Of
these 255 cases, 124 were complicated and 131 were uncomplicated. Of
the complicated cases, 75 died; of the uncomplicated, 12. Of these
complications, alcoholism was present in 30 cases, pleurisy in 17,
Bright's disease in 13, pericarditis in 9, hypertrophy and dilatation
of the heart in 3, peritonitis in 2, fibrinous bronchitis in 1, and
rubeola in 1. Lebert in his statistical report on pneumonia states that
he lost only 5½ per cent. of his uncomplicated cases and all of his
complicated cases. Huss of Stockholm lost 6 per cent. of his
uncomplicated
and 20 per cent. of his complicated cases. Wilson
Fox says that, according to the reports of English physicians,
pneumonia complicated by endocarditis is fatal in 75 per cent. of the
cases; complicated by pericarditis, in 54 per cent.; by Bright's
disease, in 50 per cent.; and by alcoholism, in 25 per cent. Brundes of
Copenhagen in 120 uncomplicated cases lost only
62/3 per cent., while
of 22 complicated cases he lost all, or 100 per cent. Thus it is
evident from my own records, as well as from those of others which I
have given, that the rate of mortality in complicated pneumonia is much
greater than in uncomplicated.
By a careful study of these complications it is apparent that they all
exert a direct influence upon the heart, diminishing its power and
crippling its action by obstructing the blood-current from the right
ventricle toward the lungs. It is unnecessary to discuss these
complications in detail; it is sufficient to state that weakening of
the contractile power of the cardiac muscle is an essential feature of
endocarditis, pericarditis, Bright's disease, and alcoholismus. In all
acute infectious diseases such complications are regarded as dangerous,
because they increase the liability of heart-failure when such failure
is especially to be feared.
Other complications in addition to those already mentioned which
increase the mortality-rate in pneumonia are chlorosis, phthisis,
emphysema, laryngitis, oedema glottidis, bronchitis, pleurisy,
parotitis, pregnancy, erysipelas, and rheumatism. Bronchitis,
pleuritis, and jaundice do not seem to increase the mortality-rate very
much, although they certainly influence it; while pregnancy, parotitis,
and affections of the joints are very serious complications. Excepting
small-pox and cholera, abortion is more apt to occur during the course
of pneumonia than in any other acute disease.
A case of pneumonia may be called mild so long as the temperature does
not rise above 104° F.; an elevation of temperature above 106° F. for
two days renders the prognosis unfavorable. Wunderlich48 says that a
gradual rise in temperature after the fourth day is always an
unfavorable symptom. A low temperature is dangerous only when the
respirations are very much accelerated.
48 In Die Eigenwärme in Krankheiten.
When the pulse is 120 or 130 for two or three days, the prognosis is
bad; if the pulse reach 150 per minute, a pneumonia patient rarely
recovers. An irregular and intermittent pulse, and one whose tracing
exhibits dicrotism, has a most unfavorable prognosis. In children the
rapidity of the pulse is not of so much importance, while in old age
the pulse is seldom or never a reliable element in prognosis. A feeble,
irregular, and intermitted pulse is always an unfavorable symptom.
Prune-juice expectoration is also an unfavorable sign, as it indicates
extensive blood-changes or a depraved condition of the patient. If
there is an entire absence of expectoration in the second or third
stage of a pneumonia, or if it becomes scanty and difficult, the
prognosis is unfavorable. Any sudden suppression of the expectoration,
with coincident tracheal râles, in any period of the disease, indicates
impending death.
In adults delirium is an unfavorable symptom, except when it occurs at
the onset of the pneumonia. When delirium occurs late in one who is the
subject of chronic alcoholismus, it generally indicates a fatal
termination. Convulsions in children with great jactitation, and in old
age subsultus tendinum and a tendency to coma, are unfavorable signs.
Great exhaustion and signs of prostration, accompanied by a sunken,
pallid countenance and cold, clammy perspiration, are always attended
with danger. In children bronchial breathing after the seventh day,
numerous subcrepitant râles, copious and persistent diarrhoea, and
swelling of the veins of the hands, are unfavorable.
In old age a sudden rise or fall in temperature, apathy, somnolence,
and a
sallow countenance, are all symptoms indicative of great
danger. Any complication renders the prognosis unfavorable, and the
occurrence of pulmonary oedema or congestion in the unaffected parts of
the lung is to be regarded as a forerunner of death.
Purulent infiltration, the formation of an abscess, and the development
of gangrene are all attended with danger. Recovery from gangrene is
very rare.
Death does not result from heart-clot, for the conditions which favor
the forming of the clot precede its formation. The fibrin factors in
pneumonia are increased—often 400 per cent. more than normal. The
heart is so enfeebled that the right ventricle cannot empty itself; the
columnæ carneæ and the chordæ tendineæ whip up the residual blood
(already prepared for clotting). Heart-clot, it is well known, is the
rule when the death struggle is prolonged and the cardiac contractions
gradually become weaker and weaker. Such heart-failure is always the
beginning of death.
In seeking for the causes of death in pneumonia, observers have taken
the results of their post-mortems as a standard of their observations.
One finds oedema of the lungs at the majority of his autopsies, another
finds a clot in the heart in most of his fatal cases; hence the
conclusion is reached that pulmonary oedema and heart-clot are causes
of death in pneumonia. But it must be remembered that in every disease
there is a great difference between the cause and the mode of death.
If, as a result of the failure of heart-power during the last hours of
life, pulmonary congestion and oedema are developed and clots are found
in the heart-cavities, it ought not to be assumed that these conditions
are the cause of death. Jürgensen states that in fatal cases of
pneumonia oedema of the lungs is always present, and heart-clots are
frequently met with.
Death may occur, then, from heart-insufficiency, from some of the
complicating diseases (cardiac especially), or from asphyxia. In some
cases death seems to come from the overwhelming of the system with a
poison which acts primarily and principally upon the nervous system. In
a few cases fatal collapse has followed an apparently regular,
well-marked crisis.
TREATMENT.—The treatment of croupous pneumonia involves not only many
unsettled questions in modern therapeutics, but it embraces a history
of the therapeutics of inflammation. An heroic, antiphlogistic plan of
one period gave place to the rational plan of another, and that in turn
to the expectant plan of a later period, while to-day an antiseptic
method finds many advocates.
Regarding it as a general disease with characteristic local lesions,
and not a local inflammation with constitutional symptoms, its
treatment must vary with the constitutional condition of the patient
and the type of the disease. When uncomplicated and occurring at
certain periods and in certain conditions of life, it will terminate
spontaneously in recovery. But when certain complications exist and
certain conditions are present, and at certain ages, it is almost
necessarily fatal. Any plan of treatment in such a disease, if resorted
to indiscriminately, must needs be unreliable and unsatisfactory.
Although there is no doubt that a large percentage of cases of croupous
pneumonia will recover without treatment, there is also little doubt
but that well-directed therapeutical efforts can save lives and render
convalescence less tedious. If it is remembered in the treatment of
pneumonia that the pneumonic lung no more requires treatment than do
the intestinal ulcers in typhoid fever, and that we are to be governed
by the patient's general condition, and not by the physical changes in
the lung as indicated by the physical signs, it is evident that all
those measures which have been employed for the arrest of a local
inflammatory process have no place in our therapeutics. It is for this
reason that venesection, which at one time had its stronghold in
the treatment of pneumonia, has now fallen into disuse. A summary of
the arguments against its practice seems to be conclusive, and the
numerous discussions that have so often distracted the most careful and
truthful observers are well expressed in the following terms:49 1st.
That indiscriminate bleeding immensely increases the mortality of the
disease. 2d. That it is specially fatal in old people and in young
children, in patients of exhausted constitutions, and in those
suffering from chronic diseases, and particularly from Bright's
disease. 3d. That it is absolutely unnecessary in the majority of cases
of young adults and also young children. 4th. That in the majority of
cases it has no influence whatever either in cutting short the disease,
in lessening its duration, or in diminishing the pyrexia, but that
occasionally these results appear to follow from its use when practised
early. 5th. That in the majority of cases it hinders the critical fall
of temperature and delays convalescence. 6th. That in the majority of
cases, as shown especially by Bennett's and Didel's data, recovery is
equally if not more rapid when it is not practised as when it is
resorted to. 7th. That in a few cases a moderate venesection may be
necessary in the early stages to avert immediate danger of death from asphyxia.
49 Wilson Fox, Reynolds's System of Medicine.
Not only does indiscriminate bleeding increase the death-rate and have
no influence over the progress, course, or severity of pneumonia, but
it postpones crisis and convalescence, and in the old, young, and
enfeebled is very often nothing less than a fatal procedure. In a
robust, vigorous individual, in spite of the fact that a free bleeding
at the very onset will temporarily relieve the urgency of some
symptoms, it nevertheless diminishes by so much the chances of
recovery, lessens the power to fight against the disease, and makes the
patient far more pregnable to subsequent dangers and complications.
Venesection has no influence upon the temperature. It may sometimes
postpone imminent death from asphyxia; and the fact that there is one
condition in which bleeding may be practised is no contradiction to the
foregoing statements, for venesection is then resorted to on account of
conditions that must be treated independently of the coexistent
pneumonia, such as sudden engorgement of the heart with blood, attended
with all the signs of sudden and extensive pulmonary oedema and
congestion. When the patient is vigorous and the above-mentioned
emergencies exist, free bleeding gives prompt relief. In no case should
more than ten ounces of blood be taken.
A careful study of the pathology of pneumonia not only leads one to the
conviction that venesection must do harm, but it strongly
contraindicates the employment of all those remedial agents which have
been used to arrest a simple pulmonary inflammation. Hence tartar
emetic, veratrum viride, aconite, and all other cardiac sedatives which
at one time were used so extensively have now fallen almost entirely
into disuse, as by their effects they can only add to the burden of a
heart already overtaxed by the venous stasis and the lack of arterial
blood. They may for a time lower the temperature and diminish the
pulse-rate, but they will accomplish this at the expense of
heart-power, and will almost certainly favor the earlier and more
certain development of that heart-insufficiency which must be regarded
as the most powerful death-producing agent in pneumonia. Dangerous
collapse has frequently followed the free use of these drugs.
Veratria is claimed to be a cardiac depressant; and this fact should
make us hesitate before we administer it in pneumonia. It acts promptly
in slowing the pulse, but its effects are only temporary, and when used
for a couple of days the larger doses that are necessary to bring about
the desired results interfere with the nutrition of the patient, often
causing vomiting and diarrhoea. Aconite is also a cardiac sedative, but
my experience with it has
convinced me that it is in all respects
inferior to veratria. Digitalis, which may be regarded as a cardiac
stimulant, is to be preferred to either veratria or aconite. It not
only lowers the temperature, but lessens the frequency of the pulse,
steadies it, and produces in the majority of cases its well-known tonic
action upon the heart. Its use in children is sometimes followed by an
intermittent pulse, but it is a symptom of no dangerous import.
Calomel and antimony have been almost entirely discarded from the
therapeutics of pneumonia: there is no evidence that the former has any
influence either upon the progress of the disease or the absorption of
the pneumonic exudation. Those who advocated its use believed it to be
most advantageous after the patient had been freely bled and large
doses of tartar emetic had been given. The latter was also a part of
the treatment where bleeding was practised. It exercises a depressant
effect upon the heart, and hence, although it may diminish the
frequency of the pulse and lower the temperature temporarily, it is an
exceedingly dangerous relief, as it is obtained at the expense of vital
power. It is absurd, with our present knowledge of the pneumonic
process, to discuss what was once claimed for tartar emetic—namely,
that it had the power of arresting the pneumonic process as well as
preventing pulmonary congestion in the unaffected portion of lung.
These drugs, while they at best afford only temporary relief, require
most careful watching to guard against their dangerous and prostrating effects.
Expectorants have no place in the treatment of pneumonia, as only a
very small portion of the exudative matter in the lung is removed by
expectoration. If mucus or other secretions accumulate in the bronchial
tubes in sufficient quantities to cause inconvenience, it is in
consequence of the exhaustion and a loss of muscular power which attend
the disease, for which expectorants will afford no relief.
Counter-irritation, by blisters or other irritants applied to the
surface of the chest in the earlier stages of pneumonia, is of
questionable utility. Occasionally, blisters may be applied during the
third stage to hasten the process of resolution and promote the
absorption of plastic exudation. The application of leeches, followed
by a linseed poultice or some other soothing fomentation, will often
relieve the pain in the side which is so urgent at the onset of a
pneumonia. If extensive pulmonary oedema occurs, dry cups applied to
the chest will afford relief to the dyspnoea and temporarily remove the oedema.
It has come to be a quite universal practice in this city to encase the
chest in a layer of cotton batting or flannel covered with an oil-silk
jacket. While this procedure has no direct influence on the course of
the pneumonia, it promotes diaphoresis and protects the surface from
sudden changes of temperature, and is always grateful to the patient.
It is especially serviceable in children.
A pneumonic patient should be kept in bed, as nearly as possible in a
horizontal position. Every appliance for promoting rest should be
employed. He should be cautiously moved for the necessary examinations
of the chest, and should be kept as short a time as possible in a
constrained position. If there are evidences of heart-failure, the
sitting posture should be avoided and talking should be prohibited. The
sick-room should be large, cheerful, and well ventilated, and its
temperature should range between 65° and 70° F. In acute febrile
disease there is no danger of catching cold from draughts, and the idea
of the laity that the moment a person is sick or has a fever he must be
put in a dark, close room is one of the superstitions of ignorance.
Pneumonic patients always demand air, and the cooler the more grateful
it is. Pure fresh air has a marked antipyretic power. It is a good rule
to allow adults to regulate the temperature of the sick-room to suit
their feelings.
One of the most important things in the successful treatment of
pneumonia is a carefully-regulated diet. The food should be fluid or
semi-fluid and
highly nutritious, such as milk, eggs, beef-tea,
and concentrated meat-broths. Milk is to be preferred to all other
forms of nutrition. It should be given in small quantities at short intervals.
When not contraindicated wine may always be administered with milk.
Such administration of wine is not a part of the stimulating plan of
treatment hereafter to be considered, but it is a means of increasing
the digestive power of a feeble stomach.
If expectoration becomes difficult, it may be from a loss of muscular
power in the bronchial tubes, when stimulants are indicated; or from
extreme viscidity of the sputa, when alkalies will be of service. Just
here it may be mentioned that alkalies and neutral salines possess a
diuretic and diaphoretic power which often affords relief from the
pungently hot skin, and may aid the elimination of effete material by
the kidneys.
It should be remembered that in the treatment of croupous pneumonia we
have to do with a self-limited, acute febrile disease, which usually
runs a cyclical course.50 Routine treatment is therefore always
harmful.
50 Fernet ("De la Pneumo. franche aigue," etc. Arch. gén.
de Méd., 1881, pp. 5–155) has demonstrated the regular and cyclical
course of pneumonia. The evolution of the malady is represented by the
march of the fever and is figured by the thermometric curve.
The nervous shock which attends the ushering in of a severe croupous
pneumonia is greater than in any other acute disease, unless it may be
peritonitis, and the important question presents itself at its very
onset, What measures shall be employed to overcome or mitigate the
impression made upon the nerve-centres by the morbific agent which is
operating to produce the pneumonia? The experience of the last few
years leads me to the conclusion that during the developing period of
the disease, when the pneumonic blow is first struck, and until the
pneumonic infiltration is completed (usually for the first four days of
the disease), if the patient is brought under the full influence of
opium, and held in a condition of comparative comfort by hypodermic
injections of morphia repeated at regular intervals, he is placed in
the best condition not only for resisting the shock, but also for
combating the activity of the pneumonia. Opium does not, when thus
administered, interfere with a stimulating or antipyretic plan of
treatment which may be demanded, but it does very greatly diminish the
chances of heart-failure, cases often recovering under its use which
from age and condition of life seemed hopeless. Then the great relief
and comfort which it gives to the sufferer in the first four days of
his struggles are sufficient to commend it, especially in those cases
where pain is severe and the restlessness of the patient is exhausting.
After the pneumonic infiltration is completed opium should be
administered with great caution, for paralysis of the bronchi (which it
induces), and the consequent accumulation of secretion in the bronchial
tubes, may greatly increase the already existing difficulty of respiration.
In all severe types of croupous pneumonia there are two prominent
sources of danger: heart-insufficiency and high temperature. There are
consequently two prominent indications for treatment—viz. to sustain
the heart and reduce temperature.
A large proportion of deaths from pneumonia result directly or
indirectly from heart-failure. Alcoholic stimulants, judiciously
employed, are the most efficient means which we possess for sustaining
a flagging heart, but their indiscriminate use is more dangerous than
indiscriminate venesection. It may be that only a few ounces of brandy
will be required to carry a pneumonia patient through a critical
period, or it may be that its free administration will be required to
save life. In the old and feeble, and in those who have been accustomed
to the use of alcohol, stimulants may be indicated from the
commencement of the attack, and their free use required throughout the
whole course of the disease. Each case demands careful study. In no
other disease is so much discretion and judgment required in the
administration of stimulants as in croupous pneumonia. The pulse, being
the indicator of the condition of the heart, must be carefully studied.
A frequent, feeble, irregular, or intermittent pulse always indicates
heart-insufficiency. The quantity of stimulants to be administered in
any case must be determined by their effect upon the pulse. It is
advisable to commence their use in small quantities, and carefully
watch their effects. If the effect is beneficial, a favorable result
will follow within a few hours, and then the quantity to be
administered can be increased according to the necessities of each
case. It is seldom necessary to give more than six or eight ounces of
brandy in twenty-four hours, yet if the necessity of the case demands
it may be given in much larger quantity, twelve or twenty-four ounces
often being required in twenty-four hours. A dicrotic pulse is a
certain indication for the administration of stimulants.
The period immediately following the crisis is the one in which
stimulants are usually most serviceable. Delirium is a symptom which
calls for their administration, whether it is due to asthenia, pyrexia,
or is an expression of blood-poisoning. When muscular tremor and
subsultus tendinum are present, alcohol may usually be freely given. A
critical collapse in the aged and weak, attended by great prostration
and a subnormal temperature, is a condition in which alcohol shows its
best effects, and the amount of asthenia will determine the amount of
stimulation required.
It has been claimed that carbonate of ammonium in large doses
stimulates the heart and prevents the formation of heart-clots by its
action on the blood. The cause of heart-clot is the heart-failure, and
there is no evidence that carbonate of ammonium prevents the
coagulation of the blood when the blood-current is slowed. Besides,
large doses of carbonate of ammonium irritate the stomach, and on this
account interfere with nutrition, and thus diminish the chances of
recovery. As a diffusible stimulant it is inferior to champagne.
Moreover, champagne can be administered for a much longer period
without causing gastric disturbances.
Camphor and musk have been highly recommended as cardiac stimulants,
but they are inferior to alcohol.
Digitalis of late years has been extensively used to counteract
heart-insufficiency, but it is very uncertain in its action in the
heart-insufficiency of pneumonia, and has seemed to me more frequently
to do harm than good. The nervous element of the heart-failure
contraindicates its use.
The second important indication in the treatment of croupous pneumonia
is to lower the temperature. The plan of applying cold compresses to
the chest in pneumonia, though far from being a new one, still has its
strongest advocates in the modern school of therapeutics. It is
proposed to apply thick compresses wet in ice-water over the seat of
the inflammation, changed every five minutes. Some use the Esmarch
ice-bag for the same purpose. Patients who were moribund have, it is
said, been revived by immersion in a cold bath. The advocates of this
treatment claim that the temperature is lowered; that the patient
experiences a feeling of relief during the bath; that the pain,
dyspnoea, pulse-rate, restlessness, and severity of the attack are all
ameliorated; and that the duration of the disease has been cut short by
the continued use of cold baths or cold packs.51
51 Rules for the employment of cold as an antipyretic in
pneumonia:
Cold Bath.—As soon as the axillary temperature in the evening rises
above 103° F., place the patient at full length in a bath with a
temperature of 70° F. or 80° F. Gradually lower the temperature of the
bath by the addition of cold water or ice until the temperature of the
patient begins to fall. It may be necessary to lower the temperature of
the bath to 60° F. before the temperature of the patient is affected.
After the temperature begins to fall, thermometrical observations must
be taken every two or three minutes; the rectal temperature only can be
relied upon. If the temperature falls
rapidly—that is, two or
three degrees in five or six minutes—as soon as the fall reaches 102°
F. the patient should be removed from the bath; if it falls slowly, as
soon as it reaches 101° F. he should be removed and immediately placed
in bed. The patient should never be kept in the bath until the
temperature reaches the normal, for it continues to fall for some time
after his removal from the bath, and he may pass from a condition of
fever into a state of collapse. The duration of the bath should rarely
exceed fifteen minutes. While the patient is in the bath cold should be
applied to the head by means of a sponge or by an ice-bag.
In the young, the feeble, and the aged the duration of the bath should
never exceed five minutes. Once commenced, the baths must be persisted
in until the crisis is reached.
Cold Pack.—This is much less effective than the bath, but if the
patient is too feeble to be moved it may be employed. The patient
should be wrapped in a sheet wrung out of tepid water, and over this a
sheet should be applied wrung out of ice-cold water; the latter may be
removed as often as it becomes warm. Its application and removal may be
continued until the desired fall in temperature shall be obtained.
Cold Compresses.—The method of applying cold compresses in pneumonia
is as follows: A cloth of some thickness is to be wrung from ice-cold
water and applied every five minutes to the affected side, or an
ice-bag is employed instead of the compresses. It is claimed for this
method that it not only relieves the local symptoms, but lowers the
temperature and hastens the day of crisis.
If cold is to be applied to the chest, either moist or dry, all the
disadvantages arising from repeated exposure and frequent changes of
temperature can be avoided by the use of the rubber coil, and it should
always be employed in preference to wet compresses.
The experience of American practitioners, so far as I have learned, is
against this plan of treatment. It is found that under it pneumonia is
more liable to extend; that the shock of the cold to the surface causes
a nervous depression from which the old and feeble do not rally; that
although a reduction of temperature may be effected,
heart-insufficiency is more rapidly reached and is more difficult to
overcome. Besides, the statistical results of this plan of treatment
are decidedly against its use. The above statements do not prohibit
cold sponging of the limbs and face if it is grateful to the patient.
If the high temperature in pneumonia is due to rapid
tissue-metamorphosis, the result of the action of some morbific agent
in the blood, it follows that we must look for an antipyretic which can
check this rapid tissue-change. It is claimed with reason that the
sulphate of quinia is a sedative to the arterial system, and has a
stimulating effect, sui generis, upon the capillary circulation; that
it can arrest cell-development, and also check the amoeboid movements
of the white corpuscles. Theoretically, therefore, it is a remedy par
excellence for the lowering of the temperature in this disease; and
clinically and empirically it has been found to reduce temperature more
permanently and with greater certainty than any other agent. None of
the objections brought against the other antipyretics can be urged
against this one, for it possesses the twofold power of reducing
temperature and sustaining the heart-power from its action on the
nervous system. To act antipyretically, quinia must be given in large
doses. From twenty to forty grains must be given within two hours, or
the whole quantity may be given at a single dose. The greatest
reduction of temperature will be reached in about seven hours after the
quinia is taken.52
52 When quinia is employed as an antipyretic in pneumonia it
must be given in large doses. The administration of two grains every
two hours, or a larger quantity administered in divided doses within a
period of twenty-four hours, will not act as an antipyretic; but from
twenty to forty grains must be administered within a period of two
hours. If the stomach is irritable, ten grains may be given every half
hour until the desired quantity has been administered. Usually in from
four to six hours after the antipyretic dose has been taken the fall of
temperature will begin, and in about twelve hours it will reach its
minimum height; then it will remain stationary from twelve to
twenty-four hours. After the temperature has once been reduced by the
quinia, its administration may be discontinued until the temperature
shall again rise to 105°. As a rule, the temperature does not reach as
high a point as before the quinia was administered. This mode of
administering quinia rarely produces any symptom of cinchonism
other than transient deafness after the first dose. In a large
proportion of cases the temperature by this method can readily be kept
below 103° F.
In Ringer and Gill's experiments with quinia on temperature it took at
least twenty grains to produce a fall of a degree. From fifty to eighty
minutes were required before the fall occurred, and the effects lasted
from forty-five minutes to three hours. Ringer states that in pneumonia
the quinia does not readily pass out with the urine, but is delayed in
the system for a considerable time.
Lately, antipyrine has been brought before the profession as a valuable
and powerful antipyretic. I have used it in both private and hospital
practice, and have found it a prompt and efficient means of reducing
temperature. It has not seemed to me, however, to have any other
beneficial effect either in mitigating the severity or shortening the
course of the disease. In two cases its use was followed by collapse,
which in one case terminated fatally. My experience has seemed to bear
out the belief that this drug is a decided cardiac depressant, and I
should for this reason consider it much less desirable as an
antipyretic than quinia.
During convalescence tonics and restoratives—iron, quinia, the mineral
acids, cod-liver oil, or strychnia—should be administered, and the
highest degree of nutrition should be maintained. If bronchitis
complicates pneumonia, it may be treated with muriate of ammonium,
ipecacuanha, and senega. If severe gastric catarrh occurs, hot
fomentations may be applied to the abdomen, and calomel, followed by a
saline purgative, may be administered.
Diarrhoea is rarely so severe as to require treatment; five grains of
Dover's powder usually suffices to control it.
In the delirium which occurs in alcoholic patients small doses of the
tartrate of antimony and potassium are said to be useful. I have
controlled this form of delirium best with small doses of hydrate of chloral.
By some, camphor, musk, and turpentine are recommended during the stage
of gray hepatization, but it seems to me that the requirements are far
better fulfilled by alcoholic stimulants.
In the first stage of senile pneumonia an emetic, when not specially
contraindicated, is given in the Salpétrière Hospital. The physicians
of the Montpellier General Hospital regard ipecacuanha as an heroic
remedy in senile pneumonia. The English regard nitrate of potassium as
the most efficacious, while the Germans prefer hydrochlorate of
ammonium. Antipyretics are rarely necessary in senile pneumonia; the
most important thing is to sustain the heart by stimulants and
concentrated fluid nutriment combined with iron and quinia. In senile
pneumonia the diarrhoea occurring with the typhoid form must be
promptly checked by vegetable astringents.
In children, as in old age, leeches and blisters should never be used.
The whole chest should be enveloped in a linseed-meal poultice, to
which some anodyne may be added (opium, aconite, or belladonna) if
there is severe pain.
In asthenic pneumonia, in addition to the nutritious diet, burgundy,
port wine, or brandy should be used, and stimulant embrocations should
be applied to the chest. In children the state of the bowels must be
most carefully watched. Stimulating expectorants are more frequently
necessary than at any other period of life.
In conclusion, I would urge that all remedial measures which tend to
paralyze the heart should be excluded from the treatment of pneumonia,
and great care should be exercised not to over-stimulate the heart, for
over-stimulation often results in paralysis. It must always be
remembered that in the milder cases there is necessity for no treatment
except a regulated diet and attention to those general hygienic
measures which have already been referred to.
I shall not attempt to discuss the treatment of the complications which
may occur in the course of a pneumonia, for it is impossible to even
mention every contingency that may arise. The rule is to treat the
pneumonia so long
as it is the controlling disease, and the
complication when it shall have become the most prominent and dangerous
element in any given case. In prolonged convalescence it is of the
utmost advantage that the pneumonic patient shall have a change of
scene and climate.
Antiseptics.—The use of antiseptics in the treatment of pneumonia has
as yet given no definite results. I have employed hypodermically phenic
acid after Declat's method in several well-marked cases of simple
pneumonia, without being able to determine that the temperature or
course of the disease was at all influenced by its use.
F. Schwarz53 states that the very favorable results which he has
obtained in croupous pneumonia can only be due to one thing—i.e. the
specific action of iodine, which renders inert the exciting cause of
the disease, which he regards as an organism, and that its efficacy is
limited exclusively to the very early stage of the pneumonia. He
believes that its action in acute lobar pneumonia is the same as Von
Willebrandt claimed for it in typhus, typhoid, and in malarial fevers.
He even states that he regards iodine as a genuine specific in pure
uncomplicated croupous pneumonia if employed within twenty-four or
thirty-six hours after the ushering-in chill, that hinders its
development and arrests its progress.
53 Deutsche medicinische Wochenschrift, January, 1881, No.
2.
After using benzoate of soda in diphtheria, scarlet and puerperal
fever—drachm ij in the twenty-four hours—E. B. Cady54 states that
when an epidemic of pneumonia visited his town in Wisconsin he had
equally good results from the similar use of this salt in pneumonia,
cases recovering which had a temperature of 106° F. and 107° F.
54 N.Y. Med. Record, 1880, July, 3, "Benzoate of Soda in
Pneumonia."
Orth55 has recently written an interesting account of the treatment
of pneumonia (lobar) with iodine.
55 Allg. med. Centr. Zeitschr., Berlin, 1881, i. p. 181.
T. H. Buckler strongly recommends its treatment with salicylate of
sodium and fresh lemon-juice.56
56 Phila. Med. News, 1882, xl. p. 652.
Phenic acid, boracic acid, and the salicylates are highly recommended
by many as the best drugs in the antiseptic treatment.
BY WILLIAM PEPPER, M.D., LL.D.
SYNONYMS.—Broncho-pneumonia; Lobular pneumonia. Although numerous
other names have been used to designate this affection, it is
undesirable to perpetuate them.
DEFINITION.—Catarrhal pneumonia is an inflammation of the parenchyma
of the lungs, frequently bilateral, and affecting scattered groups of
lobules, which may, however, coalesce, so that considerable areas of
lung-tissue become continuously involved. This anatomical distribution
explains the name lobular as opposed to that of the lobar or croupous
form. As implied by its other titles, it has close associations with
bronchial catarrh, and occurs nearly always either as an extension of
inflammation from the larger tubes or in connection with capillary
bronchitis. In consequence, it is often combined with pulmonary
collapse, with which latter condition it was until recently confounded.
The affected areas show lesions of the bronchioles, together with a
morbid product filling the alveoli, and consisting in varying
proportion of altered epithelial cells from the alveolar walls, of
cells drawn by aspiration from the bronchioles, and of exudation from
the blood-vessels. Catarrhal pneumonia may be circumscribed or diffuse,
and acute, subacute, or chronic. Its course and duration vary greatly:
at times it terminates fatally in a few days, or runs a lingering
chronic course, while recovery rarely occurs in less than fourteen
days. The mortality is always considerable, and it acquires additional
gravity from its tendency to leave behind it organic lesions of the
lungs or even to induce phthisis.
ETIOLOGY.—As catarrhal pneumonia is so closely associated with
bronchitis, and so commonly preceded by it, it may be premised that all
the causes of bronchial catarrh must be considered as liable to induce
this form of pulmonary inflammation, whether they do so by exciting
bronchitis, which subsequently extends to the alveoli, or whether, as
more rarely happens, they affect simultaneously the lining membrane of
the bronchi and of the lobules.
There are, however, several influences which must here be carefully
considered, since they have a special tendency to determine the
production of the more grave form of disease.
The effect of age in predisposing to catarrhal pneumonia is undoubtedly
great, and yet it seems to have been often over-estimated, since by
many this has been regarded almost as a disease peculiar to childhood.
The great frequency with which young children were formerly held to be
affected by this form of pneumonia has, however, been found to be due
in part to the fact that many cases of pulmonary collapse were included
with it; while, on the other hand, there is strong reason to believe
that the frequency with which adults are attacked has been greatly
under-estimated in consequence of the failure on the part of the
profession at large to clearly recognize this affection. It seems in
the highest degree important that more
correct views on this
subject should be generally received. While it is probable that the
more severe and widely-disseminated pneumonias of catarrhal type are
commonly recognized now-a-days, it appears undoubted that in very many
instances of apparently mild sickness, of acute or subacute character,
which are regarded as simple febrile colds or as the result of malaria,
the true condition is one of circumscribed catarrhal pneumonia, which,
while threatening no immediate danger to life, may if neglected leave
lesions of grave significance. Still, it is undoubted that it is during
the early years of childhood, and particularly the first five years,
that catarrhal pneumonia, and more especially its grave and fatal form,
is of frequent occurrence; while the period of next greatest liability
is at the other extreme of life, among aged and debilitated subjects.
Under the head of Pathology we shall have occasion to dwell on the
relations between defective respiratory power, pulmonary collapse, and
catarrhal pneumonia; and it is evident that this connection helps to
explain the relative frequency of the latter in early childhood, when
conditions of debility are so common, and when rickets not rarely is
superadded as an important factor. Another potent cause of the
liability of young children to catarrhal pneumonia is the prevalence at
that period of life of the infectious diseases, which are apt to be
complicated with bronchitis, and which then present a combination of
conditions favoring its development. This is especially true of
measles, of whooping cough, and of diphtheria, while influenza, which
is also frequently complicated with this form of pneumonia, is
operative at all ages. Among predisposing causes which operate chiefly
at a later period of life must be mentioned organic diseases of the
heart and vesicular emphysema. The latter especially has shown itself
important in our experience, both as predisposing to the occurrence of
catarrhal pneumonia and as adding to the gravity of the attack.
Unquestionably, all states of bad nutrition and depressed vitality
render the system much more liable to attacks of catarrhal pneumonia.
The bad air of crowded houses or of ill-ventilated public institutions,
especially if conjoined with the effect of improper food and of other
defects of hygiene, plays an important part in inducing the fatal forms
of this disease which are common among children exposed to such
conditions. It is equally evident that among adults the effect of
overwork, with insufficient sleep and outdoor exercise, is to develop a
peculiar sensitiveness and weakness of system which make the ordinary
causes of bronchitis capable of exciting a deeper and more serious
catarrh. Finally, there are many individuals who possess a catarrhal
diathesis—that is, in whom the epithelial layers are especially
vulnerable, and when attacked are especially prone to take on cellular
proliferation of a deep-seated and obstinate character. Such
constitutions, which are frequently found in the subjects of phthisical
heredity, furnish a ready soil for the development of catarrhal pneumonia.
Nor must the practical lesson be here overlooked that when acute or
subacute bronchitis exists, an additional motive for prompt and
thorough treatment is to be found in the fact that undue fatigue or
exposure may be followed by an extension of the inflammation and by the
onset of catarrhal pneumonia.
PATHOLOGY AND MORBID ANATOMY.—Allusion has already been made to the
relation existing between catarrhal pneumonia and collapse of the lung;
and the present seems to be the proper place to speak more fully of it,
since in order to appreciate the lesions in any case it is necessary to
distinguish between those which are the result of the inflammatory
process and those which can be explained by simple collapse of the
lung-tissue. It is indeed true that in some cases the development of
catarrhal pneumonia takes place in areas already the seat of collapse.
This is only what would
naturally be expected. For the production
of both conditions the existence of preceding bronchial catarrh is, if
not necessary, at least highly favorable. The folds of the swollen
mucous membrane of the smaller tubes come into contact with each other,
or else the diminished lumen of the tubes is occluded by the viscid
mucus formed as the result of the catarrh. The normal activity and
rhythm of respiration is disturbed by the fever and the lowered
innervation. During expiration more and more of the air escapes from
the alveoli of the affected area through these partly-obstructed tubes,
while during inspiration, owing to the less force of that part of the
respiratory act and to the shape of the bronchial tree, air cannot
enter to replace it. Thus, or by the action of a plug of mucus in a
conical bronchial tube, serving as a ball-valve, a condition of
airlessness or of collapse is induced in a more or less extensive area.
It is not, indeed, to be supposed that the mere occurrence of such
collapse serves in any way to excite inflammation of the alveoli. But
at the same time it is evident that there will be a strong likelihood
that the catarrh which has advanced so deeply into the finer tubes will
extend in some spots to the alveoli, and consequently that in a
collapsed area of some extent there will be one or more foci of
pneumonia developed. Moreover, it must be remembered that the collapsed
lung-tissue becomes more or less hyperæmic and disposed to take on
inflammatory action, and that the irritating bronchial secretions, the
suction of which into the alveoli plays an important part in these
affections, would necessarily be less apt to be dislodged by cough and
expectoration from areas which had become collapsed. On the other hand,
it is evident that when areas of catarrhal pneumonia have occurred
directly from extension or establishment of catarrh in air-containing
alveoli, the conditions will exist which favor the development of
collapse in the surrounding zones of lung-tissue. Thus it happens that
while the lesions either of collapse or of catarrhal pneumonia are
found separately, it is common to find more or less evidences of
alveolar inflammation in connection with collapse, especially if it has
lasted any length of time; and still more common to find a considerable
proportion of collapse coexisting with catarrhal pneumonia.
A simple practical rule must therefore be here insisted upon: that in
all post-mortem examinations of the lungs in cases of catarrhal
pneumonia, after careful study of the external appearances, a moderate
inflation by means of a blowpipe must be practised, and the effects of
this upon the consolidated areas be carefully studied before the lung
be incised, in order that any element of collapse may be recognized and eliminated.
The external appearance of the lungs usually presents evident lesions.
There are patches or layers of soft lymph on the pleura over the
affected areas, and when the former are removed the serous membrane is
found roughened, congested, and ecchymosed. On the other hand, while
the pleura over a collapsed patch usually presents small ecchymoses,
there is rarely any evidence of inflammation. More or less evident
signs of vesicular emphysema are also usually present, bearing some
proportion to the extent of the pulmonary collapse. When the areas
affected are small and scattered, the emphysema is limited to their
neighborhood; but when, for instance, both lower lobes are extremely
involved, the upper lobes may present a high degree of emphysematous
distension. In rare instances subpleural emphysema, from separation of
the membrane over a pneumonic focus, may be observed; and even, as in a
case published by me some years ago,1 perforation of the separated
pleura may occur, leading to pneumothorax.
1 Philada. Med. Times, Aug. 15, 1872, p. 425.
After section of the lungs there will always be found lesions of the
bronchial mucous membrane, which presents evidences of catarrh
extending as high as the trachea or larynx in some cases, but
habitually growing more
intense in the finer tubes, where the
membrane is reddened and swollen. Frequently the infiltration extends
throughout the structure of the bronchial walls, so that the tubes
stand out prominently above the surface of the section. Delafield2
has insisted with especial emphasis upon these alterations in the
bronchial walls, and on the view that the inflammation extends from the
bronchi, not to the group of air-vesicles into which they lead, but
directly outward to the peribronchial zones of lung-tissue. In severe
cases of longer standing the bronchial tubes often present in addition
dilatations, either cylindrical or more rarely globular.
2 "The Pathology of Broncho-pneumonia," Medical News, Nov.
15, 1884, p. 534.
The bronchi contain morbid secretions in the form of clear viscid mucus
in the early stage, while later they are filled with creamy pus. In
some cases there are also found small subpleural collections of more or
less inspissated yellowish secretion contained in dilated alveoli or in
small globular dilatations of terminal bronchioles. The most plausible
explanation of their nature is, as suggested by Fauvel, that they are
caused by the suction of particles of bronchial secretion into the
alveoli in the forcible inspiratory effects which follow paroxysms of
cough, and especially such paroxysms as occur when whooping cough is
complicated with catarrhal pneumonia.
The lung-tissue itself exhibits, associated in varying degrees,
congestion, oedema, emphysema, collapse, and pneumonic consolidation.
The patches of simple collapse are to be easily recognized by their
familiar appearance, being depressed below the surrounding tissue,
bluish in color, non-crepitant and solid to the touch, and on section
smooth, airless, firm, and not friable. They sink in water. As already
stated, they can, when recent, be readily inflated, and thus restored
to their normal condition. Such patches are most common at the
postero-inferior parts of the lungs. They are mostly pyramidal in
shape, and vary in size from a few lines to one or two inches in
diameter, though in severe cases an entire lobe, or even an entire
lung, may pass into this state of collapse. On the other hand, the
areas of pneumonic consolidation appear as slightly prominent nodules,
varying in size from that of a pea to that of a hazelnut, which may be
distinctly felt with the finger, if occurring in the midst of a
collapsed patch, by their elevation above the surrounding depressed
tissue. They are usually scattered throughout both lungs, often with
some symmetry of disposition, especially in the postero-inferior
portions. The surrounding zone of tissue is more or less congested and
oedematous, and when the nodules are closely adjacent they may become
confluent, so that large portions of a lobe or an entire lobe may
become infiltrated. Vigorous inflation will usually show in such cases,
however, that the consolidation is not uniform or complete. Section of
the lung will show that the most varied stages of the inflammatory
process are represented in the different nodules; and this is a highly
characteristic feature of the disease. The recent nodules are
brownish-red or grayish-red, faintly granular, smooth, friable, and
yield on scraping a small quantity of thick reddish secretion. Later
they become reddish-gray and yellowish-gray in color, yield a thick,
airless, milky substance, and finally grow more firm and dry: the
inflammatory product undergoes fatty degeneration, is gradually removed
by absorption or by expectoration, and the affected area of lung-tissue
is slowly restored to its normal state. This is the course in favorable
cases, while in those which run into a chronic form or which terminate
fatally at an early period the lesions undergo various modifications.
In some instances the inflammatory product undergoes more acute
degeneration, with destruction of the pulmonary tissue in the affected
area, and the subsequent formation of abscesses, which are not to be
confounded with the minute aspiration-abscesses above described. I have
notes of autopsies in which the lungs have presented every stage of the
process of catarrhal pneumonia, from the nodules of incomplete
consolidation to
circumscribed abscesses. In other cases the
thickening of the walls of the alveoli and of the bronchi, together
with dilatation of the tubes, has become marked, and the interstitial
changes in the zones of peribronchitic pneumonia extend and induce a
slow process of fibroid thickening which results in that form of
chronic pneumonia which has been called cirrhosis of the lung and
fibroid phthisis. In still other cases the morbid products in the
alveoli, with or without an antecedent process of suppuration, undergo
caseation; and the presence of the degenerate cheesy foci, associated
with alveolar and peribronchial thickening, may lead to catarrhal
phthisis with or without true tuberculous formations.
The microscopic examination of the pneumonic nodules shows that the
essential condition consists in a morbid accumulation within the
alveoli, together with changes in the walls of the vesicles, which
become infiltrated with cells in the same way as the bronchial walls.
These changes become more marked after the disease has lasted some
time. The epithelium lining the alveolar walls is the seat of cloudy
swelling, becomes less closely attached, and undergoes proliferation,
with the formation of large epithelial elements. The morbid product
filling the alveoli is composed in varying proportions of these latter
elements, of the richly cellular bronchial secretion which has been
sucked in from the bronchioles, of leucocytes, and much more rarely of
red blood-corpuscles which have escaped from the pulmonary capillaries,
and finally of fibrillated exudation. In contrasting these minute
appearances of catarrhal pneumonia with those of the croupous form it
is to be noted that in the former the fibrinous element is not
constant, or is at most scanty, and that the results of diapedesis,
leucocytes, and especially red corpuscles, are much less prominent. At
a later period of the process fatty infiltration and degeneration of
the alveolar contents usually occur, which is the most favorable
change, since it disposes toward evacuation with restitution of the
lung to its normal state; but at times a larger proportion of pyoid
cells appears, and the alveolar walls become involved and break down,
so that small abscesses are formed, or, again, the contents may become
inspissated and caseous, associated with nuclear growth in the walls of
alveoli and bronchioles.
An account has thus been given of the lesions in fully-developed and
disseminated catarrhal pneumonia; but I would again ask attention to
the existence of a mild and circumscribed form of the disease, which
rarely if ever causes death of itself. In these mild attacks, which
occur frequently in adults, the part affected may be the base of the
lung, but more commonly it is the root, the apex, or the lower anterior
portion of the upper lobe. The anatomical condition is probably one of
congestion, with extension of catarrhal inflammation into the alveoli
without any preceding collapse, and with a varying degree of
implication of the walls of the vesicles and of epithelial accumulation
in the alveoli, though the process may not always go on to the
production of fully-formed pneumonic nodules, such as above described.
Yet it seems to me not only illogical, but eminently unsafe, to regard
such cases otherwise than as catarrhal pneumonia, since while under
proper treatment and in fairly healthy constitutions they uniformly
terminate in resolution, on the other hand, they will, if neglected or
if occurring in highly-vulnerable constitutions, run into a subacute
form, with more extensive implication of the alveolar walls and
peribronchial tissue, and will induce catarrhal phthisis. Allusion will
be made again to these cases when speaking of the symptoms and
diagnosis of catarrhal pneumonia.
In addition to the pulmonary lesions, the bronchial glands are, with
rare exceptions, swollen and congested. In cases of longer standing
foci of suppuration have been occasionally noted in them (Steiner),
though cheesy nodules are more common. Acute miliary tuberculosis is a
comparatively frequent complication. Oedema and congestion of the brain
and meninges occur
frequently, but are to be regarded as
secondary lesions without special significance. It is probable,
however, that more numerous examinations, in cases where death has been
preceded by grave cerebral symptoms, would reveal the occasional
occurrence of circumscribed areas of meningitis, with or without
miliary tubercles. The liver is congested in acute cases, while in
older ones there is apt to be fatty degeneration, which we have seen
occur in irregularly distributed patches, imparting a peculiar mottled
appearance to the organ. The kidneys also may be congested, but serious
changes in the epithelium are rarely met with. Vastly more common are
the lesions of catarrhal inflammation of the mucous membrane of the
stomach and intestine. While in acute cases they may be superficial and
slight, in those which have run a longer course Peyer's patches are
prominent, and the solitary glands are enlarged, and not rarely oval
ulcerations exist which may coalesce, so that I have seen quite
extensive destruction of the mucous membrane of the colon simulating
the effects of dysentery.
SYMPTOMS.—Before entering on a detailed description of the symptoms of
catarrhal pneumonia it must be premised that this disease presents a
far greater range in its degrees of severity than does croupous
pneumonia. In this latter disease, although clinical evidence shows
that its extent and course are less uniform than is often assumed,
there is a remarkable uniformity in the stages through which the
inflammatory exudation passes; but in catarrhal pneumonia, as in all
forms of catarrhal disease, it is a marked characteristic that the
process varies almost infinitely in different cases, both in the
location, the extent, and the degree of development of the lesions. It
is difficult to avoid the conclusion that a corresponding variety is
presented by the symptoms, and that a complete clinical picture of
catarrhal pneumonia must include cases of very mild character and of
short duration, as well as those of a more severe and fully-developed
type. I propose, therefore, to describe a mild form, an acute form of
the ordinary well-developed disease, and also a subacute and chronic form.
The mild form is undoubtedly often overlooked, the attack being
regarded merely as a feverish cold or as an ordinary bronchitis. Yet
certain peculiarities in the symptoms, the course, and the tendencies
of the cases I refer to serve to distinguish them, and enable them to
be recognized as of more serious nature. More commonly the attacks
occur in young adults whose systems are abnormally sensitive either
from original weakness or in consequence of overwork, previous
sickness, or the action of other depressing and exhausting causes.
After some imprudent exposure there is a slight rigor, followed by
headache, flushed, feverish feeling, soreness in the chest, aching in
the limbs, and tight, dry, painful cough. A careful examination soon
after the onset would reveal the familiar signs of a bronchial catarrh,
though even now there might be noted a tendency for the affection to be
less diffused than is usual in ordinary bronchitis.
If the patient is not prudent and solicitous about his health, no
physician is summoned at once, and not rarely in the course of
forty-eight or seventy-two hours the general symptoms have subsided so
considerably that the patient feels able to move about, and may be led
by pressure of business claims to resume his occupation. He finds
himself so weak, however, and the cough is so much aggravated, that
medical advice is sought. Distinct fever of remittent type is found,
the morning temperature not exceeding 100° or 100½°, while in the
evening it rises to 102° or 103°. There is a tendency to perspiration,
especially on exertion, while exposure to a cool wind or draught causes
a chilly feeling; exertion soon fatigues; sleep is restless; appetite
is impaired; the tongue coated; the bowels irregular; and the urine
high-colored. Cough is troublesome and somewhat painful, and the chest
feels sore and weak. Physical examination will reveal, in the first
place, bronchitic
râles, dry and moist (sonorous, sibilant, and
mucous), on both sides of the chest, though not rarely much more
markedly on one side than on the other, or even limited to a portion of
one side.
In addition to this, careful auscultation, especially if conducted not
only during ordinary respiration, but during the strong inspirations
which follow cough, will detect in certain localities subcrepitant
râles, associated with feeble respiratory murmur and slightly prolonged
and blowing expiration. The percussion resonance or the vocal fremitus
or resonance may be only slightly impaired. These signs, which are
connected with an extension of catarrhal inflammation into the alveoli
and the consequent partial occlusion of certain lobules, may be met
with in the subclavicular spaces, at the lower anterior margin of the
upper lobes, at the roots of the lungs, or elsewhere. If the patient be
confined to bed and suitable treatment be employed, the local and
general symptoms will pass away in five to ten days. The cough grows
looser, and the sputa, which were at first very scanty and mucoid, grow
muco-purulent, and then diminish in amount. There follows a greater
degree of anæmia and of weakness than would have been expected from
what is apparently so slight an ailment, and especially there remains a
marked sensitiveness of the throat and chest, so that after any slight
recurrence of catarrh there may be a temporary return of râles at the
affected spot, until gradually the general health and the healthy tone
of the lungs are restored. But if, on the other hand, the patient
persists in keeping about and exposing himself, the febrile process of
remittent type will be prolonged, and though the disturbance of general
health will gradually subside, repeated renewals of catarrhal
irritation will occur, and the local disease will become more deeply
seated, will be attended with increased infiltration of the lobules,
and if the reaction of the system be greatly depressed will end by
becoming chronic. According to my observation, it is in this way—and
this fact confers its great importance upon the mild circumscribed form
of catarrhal pneumonia now under discussion—that very many cases of
pulmonary phthisis begin; and according to the power of resistance of
the tissues, and to the tendency of the system to become infected by
the products of unhealthy inflammation will be the disposition for the
disease to assume this unfavorable development. It is true that the
precise anatomical conditions present in the early stages of such cases
cannot be demonstrated, since death rarely if ever occurs at that
period; but it seems difficult to regard them as differing from those
found in partially developed patches of consolidation in more severe
and typical cases of catarrhal pneumonia. The constitutional symptoms,
the local signs, and the course and results of the affection all
indicate that it is not an ordinary bronchial catarrh, but that it is
properly to be regarded as a mild type of catarrhal pneumonia. Without
pretending to describe minutely all the clinical features of these
interesting cases, it may suffice to have called attention to their
frequent occurrence and great actual importance, and to the fact that
owing to the indifference of the patient or to the hasty examination of
the physician their true nature is often overlooked and the disease is
allowed to pass far beyond its original character of a local catarrhal trouble.
Acute catarrhal pneumonia in its fully-developed form occurs most
commonly in children, especially as a complication of measles or in the
course of capillary bronchitis. It is evident, therefore, that the
passage from the stage of severe bronchial catarrh to that of alveolar
inflammation may be barely perceptible at first. This is especially
true because in such cases the development of the pneumonia is usually
preceded by a considerable amount of pulmonary collapse. The child is
already suffering with fever, rapid shallow breathing accompanied with
movements of the nostrils and possibly with inspiratory retraction of
the thorax, and with frequent painful cough. No rigor, as a rule,
occurs to mark the inception of the pneumonic complication.
The
fever, however, nearly always rises rapidly, and from 102° or 103°,
which has been the maximum during the preceding catarrh, it quickly
reaches 104° or 105°, or even higher. It will be promptly noticed also
that the respirations become even more accelerated, shallow, and
imperfect; in some cases they reach 100 in the minute. The alæ nasi
play violently; the elevation movement of the thorax is marked, while
expansion is but slight; there is retraction of the base of the chest
during inspiration, which is short and quick, while expiration is
prolonged and labored. Severe suffocative paroxysms occur from time to
time. The cough is frequent and painful, so that adults complain
severely of it, while in children it causes moaning or crying. Later,
when the nervous symptoms grow more prominent, the cough grows much
less frequent and severe, or even ceases. Sputa are rarely raised by
children unless with the act of vomiting; they are tenacious, but not
rusty colored, though they may be slightly streaked with blood. The
pulse soon grows very rapid, 160, 180, or even 200 in young children,
and loses force and volume. The appetite is lost, but thirst is
extreme. The tongue becomes brown and parched from deficient secretion
and from mouth-breathing. Diarrhoea is not uncommon, owing to the
frequent presence of intestinal catarrh as a complication. The urine
occasionally contains a small amount of albumen; and it is stated
(Bednär) that the chlorides persist. The nervous symptoms are
prominent. As the dyspnoea increases there is extreme restlessness, the
child tossing about incessantly, with slight delirium. Soon the flush
on the face yields to a distinct cyanotic appearance, with coolness of
the extremities. The restlessness subsides, and there is a tendency to
stupor, alternating with spells of active and restless delirium, and
finally deepening into coma, at times with rolling of the head, so that
there may be a close resemblance to the later stage of tuberculous meningitis.
During the development of these symptoms the physical signs are for the
most part unsatisfactory and require great care to determine and to
interpret them. As already intimated, inspection shows inspiratory
retraction of the base of the chest, increased movement of elevation,
with defective expansion. Percussion does not usually give definite
results, owing to the fact that the lesions may be symmetrical in the
two lungs, and because the pneumonic process is complicated to a very
variable extent with the results of pulmonary collapse. In children
especially the most gentle and careful percussion is requisite to
detect and map out the affected areas. Some assistance may be rendered
by the fact that the dulness dependent on collapse is often found in
the form of symmetrical elongated areas in either intervertebral
groove. The results of palpation are even less satisfactory than those
of percussion. If the patches of consolidation are not extensive and
are scattered, no change will be detected; and it is only when
superficial areas of considerable extent are consolidated that distinct
increase of vocal fremitus can be determined. It may be remarked here
that, on the contrary, there is impairment of fremitus over areas of
pulmonary collapse.
Auscultation usually shows the continuance of the râles due to the
preceding bronchitis. In addition to these coarser dry and moist râles
there is also heard fine moist crackling over the area of pulmonary
consolidation; these fine subcrepitant râles are heard both during
inspiration and expiration. Pure bronchial breathing, such as is heard
in croupous pneumonia, is by no means constantly present. Over large
areas of catarrhal pneumonia, when the small bronchial tubes are
comparatively unobstructed, it may exist; but, on the other hand, there
may merely be weak diffused blowing breathing.
In adults an equally grave type of acute catarrhal pneumonia is not of
such common occurrence. Cases are met with, however, occurring
especially in subjects whose systems are depressed—as, for instance,
by overwork—in old or feeble persons, or in connection with
diphtheria, typhoid fever, or influenza. The
disease may then run
a course closely resembling that described above as found in children,
the rapidly developing interference with aëration of the blood, the
speedy failure of cardiac power, and the appearance of grave nervous
symptoms all being strongly marked. Such cases constitute a notable
proportion of what is commonly styled typhoid pneumonia, especially in
the aged, the disease being often in reality catarrhal instead of
croupous. I have also met with rapidly fatal catarrhal pneumonia
developed during the course of typhoid fever, particularly during the
later stages of cases marked by considerable bronchitis and great
nervous depression. In one instance the patient, a young man of
twenty-six years, who had been much exhausted by mental worry and
anxiety, passed through a well-marked attack of typhoid fever with
moderate pyrexia, but with decided nervous symptoms. Convalescence
seemed established on the twenty-first day, when he was carelessly
allowed to sit up in a chair, and while there was exposed to a draught
of air; he felt chilly, fever reappeared with cough, but no rusty
sputa; centres of catarrhal pneumonia developed in the lower lobe of
the right lung, then in the middle lobe; the fever varied from 101½° or
102° in the mornings to 103½° or 104° in the evenings. On the seventh
day there was a sudden fall to 99°, with a rise in the afternoon to
106°; centres of inflammation appeared in the left lung. For the next
five days there were remarkable fluctuations of temperature, the range
being from 100½° or 101° in the morning to 106° and 106½° in the
evening. The variations in the pulse-rate were not so marked.
Respiration was hurried and imperfect. Nervous symptoms of a typhoid
and ataxic nature developed, and death occurred on the twelfth day.
Considerable daily fluctuations in temperature, though rarely so
regular and extreme as in this case, are often noted in catarrhal
pneumonia, and are of some diagnostic importance. I have many tracings
to show the remittent though atypical course of the pyrexia of this
disease. Such grave cases of acute catarrhal pneumonia are very fatal,
even in adults, scarcely less so indeed than in children; and when
recovery occurs the convalescence is protracted, and often interrupted
by more or less serious renewals of catarrhal inflammation with
constitutional disturbance.
As already remarked, the pulse-rate, which soon becomes rapid, 110 to
124, does not vary as much as the temperature; and even during marked
remissions of the pyrexia the pulse usually continues rapid. The
appetite is greatly diminished or lost; the tongue is coated, often
heavily so; vomiting is not often present spontaneously, but may be
excited by the spasmodic attacks of cough. The respirations are hurried
and superficial, frequently rising to 40, 50, or 60 in the minute in
adults, and this rapidity persists during remissions of the fever just
as does the rapidity of the pulse. As a rule, it is not possible to
observe any marked difference in the movements of the two sides, owing
to the irregular distribution of the foci of disease. The cough is
frequent and may be painful. It is apt to occur in paroxysms, and the
spells may be so severe as to cause alarming interference with
respiration, and also to induce serious exhaustion.
The sputa are at first scanty and consist of tenacious mucus, which may
possibly show fine blood-points, but which are quite different from the
rusty-colored sputa of croupous pneumonia. Later the sputa become more
abundant and less consistent, being much affected by the amount of
bronchitis attendant.
The results of physical examination are much more satisfactory in
adults than in children, owing partly to the less frequency of
pulmonary collapse as a complication, and partly to the assistance
obtained from the more careful study of the vocal fremitus and
resonance possible in the former. Inspection will not show inspiratory
retraction of the base of the chest to anything like the extent seen in
children, owing to the greater rigidity of the thoracic walls.
In
the later stage of the disease, however, when considerable infiltration
and obstruction of the lungs has developed, such retraction and also an
inspiratory depression of the suprasternal space may be noted.
Palpation does not give such clear results as in croupous pneumonia,
yet careful observation will show relative increase of fremitus over
the affected areas. Auscultation of the voice usually gives valuable
results. They are not constant, however, nor is it common, even when a
considerable area is consolidated, to meet with such bronchophony as in
the second stage of croupous pneumonia. Still, it is nearly always
possible to detect some alteration of the vocal resonance by comparing
corresponding portions of the two sides; and this, as contrasted with
the negative results in bronchitis, possesses high value. The
respiratory murmur is usually feeble and blowing over the patches of
catarrhal infiltration. In some cases it is as intensely bronchial as
in the croupous form; but more commonly the greater or less obstruction
of the bronchioles renders it weaker and more distant and diffused. I
have observed considerable areas of consolidation due to catarrhal
pneumonia, over which the respiratory murmur was so feeble as to
suggest the presence of moderate pleuritic exudation. Râles are apt to
be present at all stages of the disease. Usually they are fine
subcrepitant or fine dry crackling râles, audible in both inspiration
and expiration; and even over consolidated areas these may be audible,
being doubtless transmitted from the fine bronchioles.
As the case progresses toward resolution the râles become larger and
looser. It often happens that the râles are variable, changing in
character, extent, and position from day to day vastly more than occurs
in croupous pneumonia.
Percussion gives valuable data if practised with care over symmetrical
areas of the two lungs. From such comparative study alone can
satisfactory results be obtained, since in many cases the areas of
disease are too small or not sufficiently superficial to yield more
than relative dulness. But it must happen rarely that spots are not
found where resonance is at least relatively impaired, while of course
in some cases actual dulness is readily detected. It has been stated
that collapse of the lung is a comparatively rare complication in
adults, yet careful study of the physical signs from day to day will
occasionally show its existence in a marked degree. It may occur in a
striking manner in the subacute catarrhal pneumonia of emphysematous
subjects; but in acute cases also considerable areas of the affected
lung may quickly pass into a state of collapse. In a fatal case of the
acute form in a young man I observed the abrupt development of the
signs of pulmonary collapse over the whole lower lobe of the right
lung, requiring care to avoid the error of supposing a considerable
pleuritic exudation to have supervened, but passing away in the course
of thirty-six hours with renewed expansion of the lobe and restoration
of the previously existing physical signs.
It is not necessary to give any detailed discussion of the other
symptoms of acute catarrhal pneumonia as occurring in adults—the
atypical remittent type of fever; the rapid pulse and breathing; the
digestive symptoms, anorexia, thirst, occasional nausea, and a
comparatively frequent tendency to diarrhoea; the nervous restlessness
and depression, with delirium supervening, at first slight, later more
active, and toward the close of fatal cases of such violence as to
require restraint, alternately with deepening stupor from exhaustion
and defective aëration of the blood. Albuminuria may be present in a
slight degree toward the close of severe cases. When death occurs in
these acute cases it usually does so from the tenth to the sixteenth
day. In children it may occur suddenly during or after a violent
paroxysm of cough, or an attack of convulsions may be the immediate
cause of death. More commonly death is preceded by evidences of
increasing intensity of interference with the aëration of the blood,
and with deepening stupor and nervous
disturbances such as have
been described. The degree of cardiac failure present is to be ascribed
rather to nervous exhaustion than, as in many cases of croupous
pneumonia, to the action of hyperpyrexia on the muscle of the heart.
The extreme interference with respiration in catarrhal pneumonia is
readily accounted for, not only by the extent of lung-tissue actually
involved in the process, but by the associated bronchitis with swelling
of the mucous membrane, by the accumulated bronchial secretions, and by
the frequent complication with collapse. When recovery is to follow,
the disease declines gradually and irregularly, slight recurrences of
fever and renewed catarrhal irritation being observed from time to
time. These exacerbations may not rarely be traced to atmospheric
influences or to trifling indiscretions on the part of the patient. The
pain declines gradually; and the pulse-rate also falls, but even after
the temperature has become normal some degree of rapidity of the pulse
is apt to remain for a considerable time. The physical signs gradually
disappear: the respirations, like the pulse, remain somewhat rapid, or
at least are for some time readily accelerated; and there is apt to be
some cough remaining, with gradually decreasing muco-purulent
expectoration. The digestive functions are also apt to be left in an
enfeebled condition, and the recovery of full nutrition and health is
often slow. A peculiar sensitiveness of the general system is
frequently noted after this disease, so that morbid processes,
especially of catarrhal type, are readily excited.
As would be expected, catarrhal pneumonia frequently presents much less
violent symptoms and runs a much less acute course than above
described, so that it may be said to assume a subacute or chronic form.
In children this may occur as the result of an acute attack, the severe
symptoms gradually subsiding, and passing into a less violent but
persistent type. In other cases the disease assumes this form from the
beginning, and such instances are more commonly noted after ordinary
bronchitis of moderate severity or after whooping cough. In adults this
form also is less common than in children. It is met with as an
intercurrent affection in certain cases of phthisis; and not rarely the
exacerbations of that disease are due to the development of centres of
catarrhal pneumonia which too often become later the seat of an
extension of the tuberculous process. It occurs in this form also in
the old and cachectic, and doubtless proves the undetected source of
death in many cases where the end is preceded by irregular pains and by
some signs of hypostatic infiltration of the lungs. In a feeble and
exhausted state of the system at all ages it is liable to be induced.
At times this is brought about by a series of recurring slight
catarrhal attacks, gradually deepening into a subacute process of
catarrhal pneumonia; while in other cases a more powerful disturbing
cause will in such states of system directly induce this type of the
disease. It develops insidiously. There is little or no pain. The fever
is highly irregular; the maxima usually occur in the evening and reach
102° or 103°, but there may be such marked remissions as to make the
case closely simulate one of intermittent malarial fever complicated
with bronchitis, and I have known such an error to be made in repeated
instances. In some cases, especially in the old and feeble, there may
be very little fever, at least until the disease is more fully
developed. The dyspnoea is not urgent; the pulse is not extremely
rapid; and cough may actually seem diminished if the disease has
originated in the course of severe bronchitis. The physical signs
develop slowly, but may eventually appear over considerable areas of
lung-tissue. In this way with an irregular fluctuating pyrexia,
presenting from time to time marked exacerbations, with an equally
varying amount of cough and muco-purulent expectoration, and with
marked and progressive debility and emaciation, these forms of
catarrhal pneumonia pursue a course extending over many weeks or
months. Complete recovery is still possible, after a tedious
convalescence. Commonly,
however, some permanent lesion of the
lungs, as emphysema, dilatation of the bronchial tubes, or
circumscribed induration of the lung, will remain as sequels. In a
large proportion of cases a fatal result finally follows, more commonly
from the passage of the morbid process into pulmonary phthisis usually
associated with true tuberculosis; while in some cases acute miliary
tuberculosis supervenes and proves rapidly fatal. Undoubtedly, however,
cases of chronic catarrhal pneumonia may continue purely as such, with
recurring exacerbations at irregular intervals from the development of
new centres of disease, until death is finally induced by exhaustion.
COMPLICATIONS AND SEQUELS.—It is needless to repeat what has been said
as to the essential connection between catarrhal pneumonia and
bronchitis, so that the latter is to be regarded as an invariable
symptom and attendant rather than as a complication. As might be
expected also, catarrhal laryngitis of varying degrees of severity is
of comparatively common occurrence. Especially in cases occurring in
connection with measles, where the upper respiratory tract is already
inflamed, the increased intensity of the laryngitis may induce so much
swelling as to cause some mechanical obstruction to respiration which
will arouse fears of pseudo-membranous formation, and which, during the
spasms of cough and dyspnoea which are apt to occur occasionally, will
closely simulate true croup. Pleurisy rarely appears in such a high
degree as to constitute a serious complication. When the areas affected
are superficial, there is apt to be circumscribed plastic exudation on
the corresponding portions of the pleura. Less frequently quite
extensive plastic pleurisy occurs, with layers of exudation
sufficiently thick to modify the physical signs; and in still more rare
instances does fibro-serous effusion occur. I have noted the occurrence
of purulent pleurisy, as has Jürgensen; and in two cases it was found
to be associated with subpleural purulent foci, one at least of which
had ruptured. In the other cases the purulent character of the pleurisy
was presumably due to the constitutional dyscrasia. Allusion has
already been made to the occurrence of emphysema and bronchiectasis in
connection with catarrhal pneumonia, especially of the subacute and
chronic varieties. The observations of Delafield on the tendency of the
catarrhal inflammatory process to extend laterally through the
bronchial wall into the peribronchial zones of lung-tissue are of
special interest in their bearing on the liability to dilatation of the
bronchial tubes and to deep-seated circumscribed indurations of
lung-tissue as sequels of catarrhal pneumonia.
Gangrene of the lung I have known to occur as a complication in one
case of extraordinary severity, but in which recovery ultimately
followed a very tedious process of reparation. It was attended with
recurring attacks of hæmoptysis. The case occurred in a young man of
twenty-four years of age: the lesions existed chiefly over the right
back, though there were smaller centres elsewhere; and the spot of
gangrene and from which the hemorrhages occurred was near the right
root. He was four months in bed; his convalescence extended over a
year; evidences of induration at the above spot lasted five years; and
now, eight years after the attack, he is in vigorous health, though
still with slight cough.
Pneumothorax may occur as a sequel in protracted cases in consequence
of the rupture of a subpleural abscess. I have elsewhere reported cases
of this, and Steffen has also reported two instances.
Tuberculosis occurs in various ways in connection with catarrhal
pneumonia. There may be a development of acute general miliary
tuberculosis, owing to the depressing and irritating effect of the
disease upon a constitution strongly predisposed to tuberculosis. Or
tuberculous pulmonary phthisis may ensue, either directly as a
complication or as a sequel to ulcerative changes of inflammatory
nature in the lung. Finally, those who have passed through
an
attack of catarrhal pneumonia are usually left with such vulnerability
of system that any predisposition to phthisis or to tuberculosis is
very apt to be readily called into activity. It seems highly important
to note this close and complicated connection between catarrhal
pneumonia, in its various types and even in its mild and circumscribed
form, and subsequent organic disease.
Further evidence of the profound disturbance of nutrition often
effected by an attack of this disease may be found in the occasional
development of marked rachitis, and in the much more frequent
establishment of subsequent anæmia and debility, which prove obstinate
and are associated with a high degree of susceptibility of the system
to morbid influences, and which are doubtless, in some instances at
least, dependent upon impaired primary assimilation due to lesions of
the intestinal canal, which existed as complications of the original
attack of catarrhal pneumonia. It has been mentioned that
gastro-intestinal irritation is often present, both in the acute and in
the more chronic forms, and this may reach such a high degree as to
justify the name of a complication. It has seemed to be especially in
these cases, or in those where, owing to the subsequent vulnerability
of the system, gastro-intestinal catarrh occurs as a sequel, that the
serious impairment of nutrition above mentioned is most likely to ensue.
Lastly, allusion must be made to the frequency with which severe
nervous symptoms appear, especially during the later stage of the
attack. As has been seen, convulsions are not rare in children, while
at all ages active delirium and extreme restlessness, often requiring
restraint, are of frequent occurrence. These cannot be attributed, as a
rule, to uræmic intoxication, but are to be referred to the high
systemic irritation, the great nervous exhaustion, and the marked
interference with respiration and aëration of the blood. It is probable
also that circumscribed areas of lepto-meningitis, or even of
tuberculous meningitis, are of occasional occurrence in these cases.
DIAGNOSIS.—The direct recognition of catarrhal pneumonia in its acute
stage is not always free from difficulty, while both in the acute and
chronic forms there are certain conditions with which care must be used
not to confound it.
In the first place, it is important to recognize at the earliest moment
the development of the pneumonic process during acute bronchitis of the
finer tubes. In all cases of the latter, especially in children and in
patients of debilitated system, this occurrence must be constantly
apprehended. Its occurrence may be strongly suspected if sudden rise in
the fever and in the rate of respiration and pulse is noted, though if
the areas affected are small, scattered, or deeply seated it may not at
first be possible to demonstrate it. It must be remembered also that in
the capillary bronchitis of children the fever and disturbance of pulse
and respiration may be aggravated quite abruptly from extensions of the
disease, so that actually it must be recognized that in such cases the
presence of small pneumonic centres can only be assumed, but can
neither be proved nor disproved. The course of the pyrexia may afford
some assistance, since I believe more marked diurnal variations,
amounting at times to distinct remissions, will be noted in cases of
catarrhal pneumonia than in those of severe bronchitis not so
complicated. In adults less hesitation need be felt in admitting the
development of pneumonic foci under such circumstances, even though the
physical signs are negative. Usually, however, carefully repeated
examination will soon reveal the signs of infiltration in irregularly
disposed areas; and I suspect it must be infrequent that the close
study of the relative physical signs afforded by examination of the
corresponding areas on the two sides of the chest will not afford
substantial ground for diagnosis.
It must always be remembered that areas of consolidation arising in the
course of severe bronchitis of the finer tubes may be from
collapse, and not from pneumonia. This is especially apt to be the case
in children, but occurs not rarely in feeble adults. The diagnosis of
catarrhal pneumonia from mere collapse must therefore be carefully
considered. The occurrence of collapse, though it may be marked by
sudden and severe increase of dyspnoea, pulse-rate, and distress, is
not accompanied by a corresponding rise of temperature; and this is a
point of capital importance. Again, the development of the physical
signs is usually much more abrupt than where catarrhal pneumonia is
occurring. Considerable areas of dulness on percussion appear in the
course of twelve or twenty-four hours, between the successive visits of
the physician, without corresponding increase of fever; and these areas
may subsequently present marked peculiarities, at times disappearing
almost as abruptly, to be succeeded by similar areas in other portions
of the lungs, though at times also they persist and pass through the
changes already described. The physical signs furnish further
assistance. Retraction of the base of the chest during inspiration is
much more common in collapse, especially when the areas are at all
extensive and when they occur in the lower lobes, since there is
necessarily a reduction in the volume of the lungs; and this, added to
the inability to inflate the affected lobules, induces this important
sign, which should always be carefully looked for. The dulness over
collapsed lung-tissue is rarely as marked as over extensive areas of
catarrhal pneumonia; the vocal resonance and fremitus are diminished;
râles are wanting or are feeble and transmitted; and again, it must be
mentioned that the physical signs present remarkable variations within
short periods of time. It is, however, necessary to suspect the
existence of pneumonic areas in cases of severe bronchitis where
portions of lung become collapsed, and continue so, while the general
symptoms indicate persistence of inflammatory action. The differential
diagnosis is therefore in many instances rather as to the relative
proportion of these factors than as to the total absence of either.
Catarrhal may be confounded with croupous pneumonia. This error may
most readily be made if the case be not seen until a consolidated area
of considerable extent is present, since, as we have seen, in some
instances the foci of catarrhal pneumonia may chiefly occupy one lung
and may coalesce. Even then, however, the dulness of percussion rarely
corresponds with the outline of the lobe, and is rarely as complete as
in croupous pneumonia, nor are the bronchial respiration, the
bronchophony, and the exaggerated vocal fremitus as pronounced, for the
simple reason that the consolidation is not so uniform, and that many
of the smaller bronchial tubes are more or less obstructed by swelling
of the mucous membrane or by the accumulation of viscid secretions. It
will rarely happen, moreover, that strong efforts at
respiration—induced, if necessary, by having the patient cough during
the auscultation, so as to ensure a full inspiration—will fail to
develop subcrepitant râles at some point of the catarrhal
consolidation. To this must be added the information drawn from the
history of the case; the character of the cough and sputa; and, above
all, the atypical course of the pyrexia, and the fact that
carefully-repeated examinations will show frequent and abrupt
variations in the physical signs around the margins of the affected
area. If the case is observed during its development, there will be
less difficulty in making a correct diagnosis. The process is very
rarely unilateral throughout its development; and the evident
bronchitis, the development of irregularly scattered foci of partial
consolidation in both lungs, and the frequent coexistence of collapse,
combined with the absence of the characteristic symptoms and course of
the croupous form, make the nature of the case apparent.
The diagnosis of ordinary pleurisy with effusion from catarrhal
pneumonia presents no difficulty. But, on the other hand, it is not
easy to recognize the
occurrence of a moderate pleuritic effusion
complicating a catarrhal pneumonia. The fact that the lower lobes of
both lungs are apt to be involved in the pneumonic process interferes
with the displacement of the heart, and the enfeebling of the
respiratory and vocal phenomena may be attributed to bronchial
obstruction or to collapse. A careful study of the outline of the dull
area, and of the effect upon it of changes in the position of the
patient's body, has proved of service. After all, this is a rare
complication; but not so rare is the coexistence of plastic pleurisy
with catarrhal pneumonia, and this also may give rise to doubt in the
diagnosis. An area of dulness appearing near the base and extending
with moderate rapidity, attended with bronchial irritation, with
irregular fever of slight or of moderate degree, and with some
evidences of engorgement of the lower part of the opposite lung, and
presenting over the affected area, in addition to marked percussion
dulness, bronchial respiration not of intense concentrated type,
distant bronchophony, no increase of vocal fremitus, and crackling
râles irregularly scattered over the affected area, represent a
clinical condition, occasionally met with in adults, which requires
care to ensure its proper interpretation. I have observed crackling
râles in particular in such cases, which might have been regarded
either as intrapleural or as developed in the finest bronchioles. It
will be observed, however, that the degree of dulness is excessive for
a mere plastic pleurisy; that the respiratory and vocal signs, while
not typical of croupous consolidation, are yet far more developed than
would be consistent with the presence of a quantity of plastic pleural
exudation sufficient to cause such dulness; that any such grade of
plastic pleurisy is very rare; and that the general symptoms and the
course of the disease are indicative of much more gravity than would
attach to such a pleuritic process if it were to exist. It is
altogether probable that there has been here a coexistence of catarrhal
pneumonia with a moderate degree of plastic exudation on the
corresponding part of the pleura.
Again, it is essential to distinguish catarrhal pneumonia from acute
miliary tuberculosis with special localization in the lungs and
meninges. This diagnosis may present marked difficulties both in
children and in adults, but of course chiefly in the former, and
especially at a late period of the case, when cerebral symptoms,
closely simulating those characteristic of tubercular meningitis, may
have appeared. The irregular fever, the marked disturbance of pulse and
respiration, with evidence of diffuse bronchial irritation, but out of
proportion to the physical signs of consolidation, the occasional
vomiting in the early stage, and the appearance of nervous symptoms,
are present in both conditions. But in tuberculosis there may be high
fever before any marked evidences even of bronchial irritation appear;
there is not so much bronchitis to aid in explaining the dyspnoea;
there is not so much tendency to pulmonary collapse, and the physical
signs present are more persistent; the pulse presents the
characteristic successive stages of alteration; vomiting is apt to be
more frequent, while the diarrhoea which is often present in catarrhal
pneumonia is replaced by constipation; the Cheyne-Stokes respiration is
more apt to appear; and, finally, an ophthalmoscopic examination may
reveal retinal tubercles. It remains true, however, that in some cases
it must evidently be wellnigh impossible to decide whether the case is
one of acute tuberculosis, with a high grade of bronchitis, and very
probably with some centres of pneumonic infiltration associated, or one
of catarrhal pneumonia developing out of a severe bronchitis. It must
be remembered, moreover, that even when the case has begun as one of
catarrhal pneumonia there is a tendency to the development of
tuberculosis, both pulmonary and general; so that it may be found after
death that the nervous symptoms, which were reasonably ascribed to
congestion, to high temperature, to prolonged and exhausting nervous
irritation, and to the effect of imperfectly aërated blood, are in
reality connected with the
presence of miliary tubercles in the
meninges, while at the same time these have also been developing around
the pneumonic foci in the lungs.
It is no less important to bear in mind the necessity for close study
in distinguishing between chronic catarrhal pneumonia and phthisis.
There are not a few cases of the former where the protracted irregular
fever of hectic type, the progressive debility and emaciation, the
moist râles, the areas of altered percussion resonance, possibly the
signs of a dilated bronchus, and the purulent sputa, may closely
simulate true phthisis, but yet which microscopic examination of the
sputa for bacilli and elastic fibre, and the effect of treatment and
climatic change, prove to be merely inflammatory. On the other hand, it
appears undoubted, from the standpoint of clinical observation, that in
many cases, especially where a predisposition exists, catarrhal
pneumonia terminates in phthisis.
DURATION, TERMINATIONS, PROGNOSIS.—The duration of this disease is
highly irregular, and care must be taken not to confound the subsidence
of the marked general symptoms with a full restoration of the affected
areas. A considerable period is required for this latter process to be
effected, and during this interval the lung-tissue continues in a
highly sensitive and vulnerable state. Speaking with reference to the
obvious symptoms, however, it may be said that mild acute cases may
terminate in seven to ten days; fully-developed acute cases, in fifteen
to twenty-five days; while the subacute and chronic forms may last
several or many months.
Death may occur in from two to four days, especially in weak young
children, while more commonly the fatal result occurs from the seventh
to the tenth day. Of course in the chronic form death may occur after
many weeks or months.
The various terminations are in complete recovery; in apparent
recovery, but with vulnerable lungs or general system; in partial
recovery, but with residual lesions, such as bronchial dilatation or
emphysema; or the disease may pass into the chronic form, associated
with chronic bronchitis, or it may lead to the development of acute
tuberculosis or of chronic phthisis.
The rate of mortality of catarrhal is much higher than that of croupous
pneumonia. Excluding the mild circumscribed form, if such is admitted
to exist, as I believe it does, the mortality varies from 30 to 60 per
cent. It is apparently less fatal when occurring in the course of
measles than in connection with some other diseases, as diphtheria or
whooping cough. The nature and tendencies of this disease make it
evident that debility and frailty of the patient would render catarrhal
pneumonia much more fatal. So it is found that in infants within the
year death almost constantly follows, and in older children of bad
constitution, especially in those who are scrofulous or rachitic and
subjected to malhygienic influences, it is almost equally fatal. After
puberty the mortality is chiefly influenced by the constitutional state
of the subject and by the extent of the pneumonic process.
The greater tendency to pulmonary collapse and to severe capillary
bronchitis in young children justifies Jürgensen's generalization, that
before the age of puberty the danger from catarrhal pneumonia grows
greater in proportion to the youth of the individual. Partly because
the disease is more apt to assume the subacute form in feeble and
sickly individuals, partly because in this form the pneumonic process
is more apt to run into destructive lesions of the lung-tissue or to
induce tuberculosis, it is found that the mortality from the subacute
is even greater than from the ordinary acute form.
It is needless to detail the special symptoms of unfavorable
significance. The most important considerations to guide us in
prognosis are, therefore, the age, constitution, and vital resistance
of the individual; the extent of the pneumonia and of the associated
pulmonary collapse and capillary bronchitis; the degree of
gastro-intestinal irritation; the vigor of the circulation
and
respiration, and the manner in which aëration of the blood is
maintained; and, finally, the grade of the fever and the character of
the nervous symptoms.
TREATMENT.—It is difficult to lay down definite rules for the
treatment of catarrhal pneumonia, as the indications are extremely
variable and complicated.
In the first place, it is scarcely necessary to call attention to the
importance of guarding against the development of this disease in all
cases of bronchitis occurring in children or in delicate adults. This
care is essential not only in idiopathic bronchitis, but in those
general diseases, such as measles and whooping cough, in which
bronchitis is constantly present. As children of bad constitution and
those exposed to depressing hygienic conditions, such as over-crowding,
bad air, and the like, are most liable to become attacked with this
form of pneumonia during the course of a bronchitis, it is especially
in such cases that our precautions must be most stringent. They should
include a strict attention to the condition of the sick-room, which
should be well ventilated, but free from drafts, the temperature not
being allowed to rise above 68° or 70°, and the air being kept moist by
the generation of steam. The diet must be carefully regulated, so that
the child's strength shall be as far as possible maintained, and
stimulants must be used if indicated by weakness of the pulse or by a
tendency to failure of respiratory power. Stimulating applications
should be made to the chest, both to serve as counter-irritants and
because they stimulate respiration. It would be manifestly unsuitable
to enter here into the details of the treatment of such cases of
bronchitis, and the above remarks have been made chiefly for the
purpose of calling attention in an emphatic manner to the great
importance and value of strict and thorough treatment of all severe
cases of bronchitis, especially in children, not only with a view to
the prompt cure of the primary disease, but because thus also will the
development of the more serious conditions of pulmonary collapse and of
pneumonia most surely be prevented.
So soon, however, as the coexistence of catarrhal pneumonia is
established the gravity of the disease should be promptly recognized,
and the closest attention should be paid to every detail of treatment.
The condition of the sick-room as to temperature, ventilation, the
absence of drafts, and the suitable moisture of the air must be even
more carefully watched. The clothing of the child and the bed-covers
must be adapted to the season, the weather, and the patient's habit and
strength. It is certainly true that aggravations of the disease are
often induced by apparently slight indiscretions in the above respects.
It is rarely desirable to employ poultices. Unless skilfully made and
dexterously applied, they fatigue by their weight; dangerous exposure
is incurred in the frequent changing necessary; and, especially in the
case of children, they do not keep their position well. A layer of
cotton batting stitched inside of a merino shirt of suitable weight,
upon the outside of which oiled silk may be stitched, forms an equally
efficient and vastly more comfortable and convenient protection. This
should be directed when the bronchitis assumes a severe type, or
certainly as soon as pneumonia is suspected. It will not be necessary
to change this for a week or ten days, unless copious sweating calls
for its more frequent renewal. Among the advantages of this application
must be reckoned the fact that it allows us to employ at any part of
the chest, and as often as desired, local stimulants or
counter-irritants, such as turpentine liniment, mustard plasters, or,
what is one of the most valuable, the repeated application of tincture
of iodine of suitable strength so as not to cause too severe irritation.
The next most important part of the treatment relates to the
restoration and maintenance of the digestive function, which is so
commonly disturbed in this disease. No one factor contributes more
powerfully to produce vital
debility, which in turn rapidly
increases the gravity of the lung disease by the failure of respiration
and the development of collapse, than does gastro-intestinal disorder.
Not only the diet, but the entire medication, must therefore be
rendered subordinate to the conditions of the digestive tract. It has
been seen that, at the onset of the attack, vomiting and diarrhoea are
not rare symptoms, and that throughout the course of the disease the
condition of the tongue, of the appetite, and of digestion often shows
that a catarrhal process exists in the gastro-intestinal as well as in
the bronchial mucous membrane. It is therefore frequently advisable for
a day or two to avoid all remedies directed to the condition of the
lung, and to address the treatment, dietetic and medicinal, solely to
the state of the alimentary canal. Thus it will often be of service to
employ minute doses of calomel and bicarbonate of soda or of Dover's
powder, as in the following formulas, adapted for children of five
years of age:
| Rx. |
Hydrargyri chloridi mitis, |
gr. j; |
| |
Sodii bicarb. |
gr. xxiv; |
| |
M. et div. in Chart No. xij or No. xvj. |
S. One every two or three hours until the bowels are moved once or twice.
| Or, Rx. |
Hydrargyri chloridi mitis, |
gr. j; |
| |
Pulv. ipecac. composit. |
gr. x; |
| |
M. et div. in Chart No. xij or No. xvj. |
S. One every three or four hours.
During this early stage of cases attended with marked gastro-intestinal
irritation it may be desirable to use remedies to allay high fever, for
which purpose fractional doses of tincture of aconite by the mouth and
quinia by enema or suppository are efficient, while avoiding all risk
of injuring the stomach. The diet at first should be carefully
restricted: it is not at this time that prostration is to be feared,
while by a thorough allaying of gastric irritation and by the
establishment of fair digestion an ally of immense value for the later
and more dangerous stages is secured. But at all periods of this
disease the occurrence of vomiting or of diarrhoea should be the signal
for instant revision of the diet and for the omission of any remedy, no
matter how strongly indicated on other grounds, which could be regarded
as the cause of the disturbance.
Milk, skimmed or whole; gruel, light broths, or beef-tea; junket,
arrowroot, or similar light yet nourishing articles, are most suitable.
Stimulants are frequently indicated on account of the tendency to
failure of the respiration and heart, and owing to the typhoid nervous
symptoms. They are required at all ages, especially by young children
and by the aged. Children in particular bear relatively large amounts,
and respond to their use well and promptly. The form and strength of
the stimulant must be adapted to the state of the stomach. Wine-whey
and weak milk-punch are often serviceable. Many children will take
brandy or whiskey in water, but will refuse the former preparations.
Dry champagne has proved highly valuable in many serious cases,
especially in older persons, for young children will rarely take it.
Other important indications are to favor expectoration and to stimulate
the respiratory forces. These are closely associated, and are of prime
importance, since in catarrhal pneumonia the principal danger to life
undoubtedly comes from the progressive diminution of the pulmonary area
open to respiration, and from the increasing failure of the respiratory
muscles to overcome the obstruction to full inflation. It is through
this agency that pulmonary collapse extends, that heart failure
subsequently occurs, and that carbonic acid poisoning, with its
attendant nervous symptoms, is finally developed.
The preparations of ammonia seem to be the most valuable remedies to
meet these indications. In adults, where the disease is attended with
high fever, the following may be ordered:
| Rx. |
Ammonii chloridi, |
gr. lxxx; |
| |
Syr. scillæ vel syr. senegæ, |
fluidrachm iij; |
| |
Liq. ammoniæ acetatis, q. s. ad |
fluidounce iv. |
Ft. sol. S. A dessertspoonful in water every three hours. To this may
be added one or two drops of tincture of aconite in each dose, watching
carefully for the appearance of its effects; or small doses of morphia
or of deodorized tincture of opium may be added, according to the
severity of cough or of nervous restlessness. But to children in nearly
all cases, and frequently to adults, it is best to give carbonate of
ammonia at once, as follows:
| Rx. |
Ammoniæ carbonatis, |
gr. xlviij; |
| |
Pulv. acaciæ et sacchari, |
aa q. s. |
| |
Sp. lavandulæ comp. |
fluidrachm ij; |
| |
Aquæ, q. s. ad |
fluidounce iv. |
Ft. mist. S. One teaspoonful in water every two or three hours for a
child five years old.
It may occasionally be necessary, owing to the abundance and the
viscidity of the bronchial secretions, to administer an emetic, but
this should be avoided if possible. If required, choice should be made
of one which will act promptly and decisively without subsequent nausea
or relaxation. Such is a combination of alum and ipecacuanha, or of
sulphate of zinc and ipecacuanha, which have proved very satisfactory
in my hands. Jürgensen recommends apomorphine, administered
hypodermically, as the agent which he has found most efficient. The
dose of this substance is about gr.
1/12
for an adult, whilst for a
child of five years it should not be more than gr.
1/30 or gr.
1/25.
The dose may be repeated in 15 or 30 minutes if no emetic action is secured.
I attach great importance to the use of strychnia in catarrhal
pneumonia after symptoms of respiratory failure appear. Its value as a
stimulus to the muscles of respiration, and possibly directly to the
respiratory nervous centre, is established. It may be given alternating
with the ammonia mixture, thus:
| Rx. |
Quiniæ sulph. |
gr. xxiv; |
| |
Strychniæ, |
gr. ¼; |
| |
Acid. muriatici diluti, |
gtt. xvj; |
| |
Glycerinæ, |
fluidrachm iij; |
| |
Liq. pepsinæ, q. s. ad |
fluidounce iv. |
Ft. sol. S. Teaspoonful in water every three or four hours, for a child
of five years of age.
But when urgent symptoms arise it may be given in much larger doses and
hypodermically, so as to ensure its full absorption and effect. I have
thus given in many severe cases, and at times with unquestionably good
results, as much to an adult as gr.
1/24 every four hours, day and
night, for seventy-two or ninety-six hours.
The fever in catarrhal pneumonia does not demand special treatment
nearly so often as in the croupous form. Though the evening maxima may
be quite high, yet the occurrence of the morning remissions brings some
relief and obviates the necessity for vigorous antipyretic treatment.
The nervous system and the heart do not therefore suffer severely and
constantly from this cause in this disease. Still, there are not a few
cases when hyperpyrexia occurs and demands prompt treatment. If the
nervous symptoms are not threatening, and if the respirations are still
fairly well performed, it will be proper to try the effect of a few
full doses of quinia, or, if that fails, of antipyrine. But if, despite
these remedies, or in the event of the stomach rejecting them, or,
finally, if more urgent symptoms of nervous and respiratory failure are
impending, recourse should be had to cold effusion, particularly if the
highly laudatory statements of Bartels, Ziemssen, and Jürgensen be
confirmed by further observation. I have not found it necessary, or may
have failed to
appreciate the necessity, to resort to the
external use of cold in catarrhal pneumonia; but the remarks of
Jürgensen as to the remarkable influence of cold water dashed upon the
surface of the chest or directed against the cervical spine in
stimulating deep respirations accord with general observation, and
suggest this mode of treatment, especially in cases of sustained high
temperature with rapid, shallow, imperfect respirations and defective
aëration of the blood.
The nervous symptoms frequently are so severe as to require the
administration of sedatives. Remedies of this class must, however, be
used cautiously and sparingly. It were unwise to give those which
depress the heart and respiration, or, on the other hand, to administer
opium in such doses as would blunt perception and lessen cough to an
injurious degree. By the use of small doses of opium from the beginning
of the attack, however, combined with strict attention to the other
details of treatment, it is often possible to prevent the development
of severe nervous symptoms which would require powerful sedatives. In
cases of extreme restlessness and sleeplessness benefit may be found
from the use of such a suppository as the following:
| Rx. |
Pulv. assafoetidæ, |
drachm j; |
| |
Quiniæ sulph. |
gr. xxx; |
| |
Ol. theobromæ, |
q. s. |
To be made into twelve suppositories of small size, suitable for a
child of five years of age, one of which may be used and repeated in
three or four hours.
Enemas of chloral hydrate, from five grains for a child of five years
to twenty grains for an adult, may be used without fear of depressing
the heart or checking the secretions, and with great relief to the
nervous symptoms, especially if tending toward convulsions. In cases of
extremely active and restless delirium, where prompt sedative action is
demanded, and yet where the use of opiates is forbidden, the hypodermic
use of hyoscyamia in doses of gr.
1/80 to
1/100 for an adult may give
gratifying results.
In cases which pass into a subacute form a continuance is demanded of
every precaution as to the diet, the hygiene of the sick-room, and the
use of general tonic remedies. Advantage may then be found from the use
of oil of turpentine, which has seemed to me the most valuable
alterative and stimulating expectorant under such circumstances.
As the case progresses into the chronic form it becomes necessary to
gradually substitute for the more strict and special method of
treatment previously employed one in which the maintenance of the
general health shall be the prime object. The regulation of the diet,
care in dress, the cautious resumption of gentle exercise, and the use
of carefully-regulated pulmonary gymnastics so as to favor the full
inflation of the lungs and the invigoration of the respiratory muscles,
are to be closely attended to.
The condition of the skin demands careful attention also, and dry
friction, inunction, and suitable stimulating sponge-baths followed by
friction, according to the constitutional condition of each patient,
may be cautiously directed with great advantage.
The remedies suitable for the more acute stages may now be replaced by
cod-liver oil, arsenic, or iodide of iron. Occasionally alterative
expectorants, such as copaiba or yerba santa, with or without an
alkali, as muriate of ammonia, will still be found desirable.
Most signal benefit will also be obtained from suitable change of
climate, associated with a continuance of careful regimen and
treatment; and, indeed, we may be gratified by witnessing a complete
restoration to health, with the exception of unimportant residual lung
lesions, of cases in which the general symptoms and the physical signs
strongly indicated hopelessly incurable organic disease. Not only in
the acute, but in the most tedious chronic, cases of catarrhal
pneumonia must our efforts be continued to the very close.
BY BEVERLEY ROBINSON, M.D.
DEFINITION.—Pulmonary embolism signifies the transport during life of
clots, or of other solid substances appearing within the right heart or
systemic veins, from these parts to the trunk or divisions of the
pulmonary artery.
SYNONYMS.—Fr. Embolie pulmonaire; Ger. Embolie der Lungenarterie;
It. Embolia pulmonare.
CLASSIFICATION.—A rigorous classification of the different kinds of
pulmonary emboli or a clear separation of them into distinct orders is
very difficult on account of the rôle in producing them, partly
mechanical, partly dyscrasic, of some of the affections in which they
are likely to occur. This is particularly true of the puerperal state,
uterine affections, and fractures.1 Bertin, however, has made of them
four divisions, according as the cause is mechanical, dyscrasic, mixed,
or undetermined; but these are objected to by Luzzato on the ground of
their inadequacy, and he deems it preferable to regard them from the
point of view of their medical, surgical, or obstetrical origin. From
this latter point of view we also consider it best to consider them
until a more satisfactory separation shall be established.
HISTORY.—Latterly, the subject of pulmonary embolism, or the
obstruction of this artery by means of a clot which has had its origin
in the right heart or one of the systemic veins, has been very
carefully studied. Many cases of sudden death are properly and readily
explained in this manner, where formerly they would have been doubtful
or inexplicable. Sometimes the previous existence of a fibrinous
coagulum in the right heart or in the crural vein has been recognized
previous to the symptoms indicating plugging of the pulmonary artery;
occasionally these coagula have been wholly overlooked, and the sudden
cry with intense dyspnoea, pointing to obstruction of the blood-supply
to the lungs, is a matter of dread surprise to the beholder. According
to Trousseau,2 our knowledge of embolism is due mainly to Legroux.
This is not, however, the view of Ball3 nor of Walshe, who attribute
the clearest insight into this process to the clinical and experimental
observations of Van Swieten, who, half a century before Legroux's time,
had injected different coagulating materials into the veins of animals
and produced the characteristic symptoms of pulmonary embolism. To
Virchow's4 exhaustive researches, however, we are principally
indebted for a great deal of what is actually known upon this subject
to-day. True it is that contemporaneous writers have added many new
facts to those he so well elaborated, but the greater part of credit in
this line of study should be awarded to him. After Van Swieten's time
the doctrine of pulmonary embolism fell somewhat into disrepute, owing
to the lukewarmness of Hunter and
Morgagni. Cruveilhier (1842)
recognized their existence, but was so much impressed by his doctrine
of phlebitis that he believed the majority of pulmonary coagula were
autochthonous (formed on the spot), and not the consequence of
transport or migration in the venous current. This opinion was strongly
combated by Virchow, who held that pulmonary coagula formed some time
before death were not the result of an inflammation of this arterial
vein (Galien), but always had for origin a migratory clot which came
from some part of the venous system.5 This doctrine of Virchow's is
certainly too exclusive, and although primary or secondary inflammation
of the pulmonary artery is certainly rare, it is certainly not unknown,
and when it exists will sufficiently explain the formation of a
fibrinous clot. Facts of this kind have been reported by Bumann,
Bouillaud, Andral, and more recently still by Lancereaux, who has shown
to the Anatomical Society of Paris6 distinct new formations in the
pulmonary artery. Until further investigations are made on this point
it seems wise to abstain from having an opinion too categoric on one
side or the other. Virchow's first studies on pulmonary embolism were
published in 1846, and were based upon 11 cases of this disease. All
these cases were caused by migratory clots from the heart or one of the
systemic veins. In this first publication, and later on (1854–56),
Virchow gave the results of numerous experiments in which he had
injected bits of fibrin of diverse origin, particles of flesh, and
fragments of rubber into the jugular veins, and showed in an admirable
description the immediate effects of embolic plugs upon the blood, the
arterial coats, and the surrounding pulmonary tissues.7
1 Étude critique de l'Embolie, Paris, 1869.
2 Clinical Lectures, Sydenham Society's ed., vol. iii. p.
414.
3 Des Embolies pulmonaire, Thèse de Paris, 1862.
4 Froniep's Neue Notizen, 1846, p. 910.
5 Bucquoy, Des Concrétions sanguines, Paris, 1863, p.
138.
6 Bullétin, 1861, p. 377.
7 Dict. de Médecine et de Chirurgie, vol. xxix. p. 334.
In 1852, Senhouse Kirkes8 also studied very carefully different cases
of embolism, and showed how they were connected with organic disease.
Most of these cases, however, showed rather the effects on the brain
and the production of right or left hemiplegia than the asphyxic
sequelæ of obstruction of the trunk or divisions of the pulmonary
artery. In France the doctrine of embolism was at first received
doubtingly, and was the subject of animated discussions at the Medical
Society of the Hospitals in 1857. In this year Charcot and Ball
published the first case of pulmonary embolism which had been observed
in that country. Five years later (1862) pulmonary embolisms formed the
subject of a remarkable inaugural thesis by Ball, and articles of
considerable value were also written in regard to it by Velpeau,
Lancereaux, Lemarchand, Trousseau, etc. Spontaneous coagulation of the
blood in the right heart and pulmonary artery was considered by Meigs
in 1855 to be a frequent cause of death in the puerperal state.
Analogous cases, although none of them occurred after childbirth, had
five years previously been carefully studied by Paget.9 The cases of
sudden death subsequent to confinement are now generally considered to
be due to pulmonary embolism.10 Amongst the later sources of
information on the subject of pulmonary embolism or its consequences we
would direct special attention to the work of Luzzato11 and the
theses of Duguet12 and Levrat.13 These and numerous other writers
have made researches as to the different varieties of pulmonary
embolism, such as the fatty (Flournoy), atmospheric, specific, those
following confinement, or traumatism.
8 Med.-Chir. Trans., vol. xxxv.
9 Ibid., vol. xxvii. p. 162, and vol. xxviii. p. 352.
10 Playfair, A Treatise on the Science and Practice of
Midwifery, Philada., 1882.
11 "Embolia dell' Arteria pulmonale," Annali Univers. di
Med. e Chir., Milano, 1877–79.
12 De l'Apoplexie pulmonaire, Paris, 1872.
13 Des Embolies veineuses d'Origine traumatique, Paris,
1880.
ETIOLOGY.—The great majority of emboli which are found in the
pulmonary artery after death come from the systemic veins. They may
also be
transferred from the right heart. According to
Hayden,14 in fact, the migratory clot is usually derived from cardiac
thrombosis of the right heart. This opinion, however, is not generally
accepted as correct. Of all the veins of the economy, those of the
lower extremities give the largest number of emboli. This statement is
notably true of the femoral and internal saphena veins. According to
Lancereaux,15 the reason why coagula form in the veins of the lower
limbs high up and in the cerebral sinuses is the fact that in these
locations the action of the vis-a-tergo and thoracic aspiration is
scarcely or at all felt. Besides, we know that coagula of these veins
are very frequently found in cachectic conditions (tubercle, cancer)
and in the puerperal state (phlegmasia alba dolens). As we shall have
reason to remark further on, embolism of the pulmonary artery is often
due to fragments of cancer, of pus, of a valve, etc., which have made
their way into the return blood-current, or indeed have formed there in
the first place. The direct cause of the separation of a portion of
thrombus is either some mechanical cause or the influence of regressive
changes affecting the clot. We are called upon, however, to consider
briefly—1, the causes in a general way which predispose to the
formation of thrombi; 2, the diseases, dyscrasic and local, in which
emboli occur most frequently. Virchow, Richardson, and others have
shown conclusively that the blood is prone to coagulate in the
vessels—1, whenever it stagnates or is arrested in its course; 2, if
there be, by reason of morbid alteration of vascular wall or presence
of an embolus, a mechanical obstacle present; 3, if the blood be
modified by septic conditions or increase of fibrin. Now, then, in the
veins of the lower extremities we have a considerable tendency to
stasis—greater indeed than exists elsewhere in the economy—because
these veins have to contend against the weight of the blood in the
iliac veins, the venæ cavæ, and the right heart. Further, they are
often obliged to resist the effects of accidental pressure in the
abdominal cavity, or that which takes place in lungs altered by some
chronic diseases16 (emphysema, pneumonia, bronchitis). Usually in
these veins, as elsewhere, when a thrombus exists there is local
inflammation at its level of the walls of the vein. This inflammatory
condition itself is dependent upon mechanical injury, change of the
blood (gout),17 or the introduction of septic material. At times
septic material is introduced into the blood and absorbs from
disintegration of a clot. Hence arise typhoid or pyæmic symptoms.
14 Dis. of the Heart and Aorta, Part ii. p. 1029.
15 Gaz. hébdom., 1862, quoted by Bucquoy.
16 Hayden, Diseases of the Heart and Aorta, Part ii. p.
1023.
17 Tuckwell, St. Bartholomew's Hosp. Reports, vol. x.,
1874.
I. Amongst the medical causes which frequently occasion pulmonary
embolism we should mention diseases of the heart,18 of the lungs, the
stomach, the kidneys, and the uterus. Mitral affections which have
reached their ultimate period are a fruitful source of pulmonary
embolism on account of the effect produced on the right heart. The
slowing of the circulation in this condition by digitalis has been
wrongly accused by some writers of favoring the production of emboli.
Evidently, digitalis does not promote this formation when given with
circumspection, as it increases the force of the heart-beats. Sometimes
constitutional disease precedes the formation of emboli. This is
particularly true of leucocythæmia, which is an efficient cause of it,
at times, when sudden death has followed plugging of the trunk and both
branches of the pulmonary artery.19 In the convalescence of typhoid
fever pulmonary embolism is quite frequent, and follows upon the
formation of thrombi in the veins. Such a specimen was presented by
Fagge at the meeting of the London Pathological Society on Nov. 16,
1876. The patient died suddenly in the fourth week of an attack of
typhoid fever following an attempt to get
out of bed. The marked
symptom of the case was intense dyspnoea.20 It would appear that
emboli are more apt to take place in acute than chronic disorders,
because in the former they grow more rapidly, are less intimately
attached to the vascular walls, and in consequence are prone to become
detached and carried in the current of the circulation.21 Chlorosis
has been invoked as a cause of venous thrombosis of the lower
extremities,22 but rarely under these circumstances has pulmonary
embolism been due to its existence. Hayden23 reports a case of
similar formation in advanced pulmonary phthisis. In this instance
death occurred, but no symptoms of pulmonary embolism were at any time
present. At the autopsy a firm, decolorized clot was discovered in
either femoral vein. Although phthisis is a frequent cause of
phlegmasia alba dolens, owing to the compression of enlarged lymphatic
ganglia or the blood-dyscrasia, it is not often the source of pulmonary
embolism (9 cases out of 160 of all kinds, according to Luzzato). A
probable explanation of this fact is that the fibrinous coagulum does
not form in the veins until a late period of the disease, and death
results before it has had time to soften and disintegrate.24
18 Am. Journ. Med. Sci., Oct., 1876.
19 Hayden, Case 124, p. 1030.
20 Lancet, Nov. 24, 1876.
21 At times septic material is introduced into the blood and
absorbed from disintegration of a clot. Hence arise typhoid or pyæmic
symptoms.
22 Reports of Pathol. Soc. of London, vol. xvi.
23 Op. cit., p. 1024.
24 Dict. de Méd. et de Chirurgie, vol. xxix. pp. 336,
337.
II. Surgical affections are frequently the efficient cause of pulmonary
embolism. Thus, out of 160 cases of the latter disease collated by
Luzzato, 66 owed their origin to conditions embraced in this division.
Wounds, contusions, compressions, diseases of, and all surgical
operations upon, the veins are specially liable to be followed by
pulmonary embolism. Sometimes the thrombus formed originally in the
implicated vein takes place there spontaneously; sometimes it is the
direct consequence of a localized phlebitis. Several times the
injection of tincture of iron into varicose veins of the inferior
extremity25 or into a nævus26 has been the occasion of symptoms
indicating sudden obstruction of the pulmonary artery; again, it is an
accident, more frequent than is generally admitted, of the operation of
transfusion (Vulpian). According to Le Dentu,27 the varicose veins
tend to cause stasis of the blood, and thus to favor coagulation. They
are, therefore, a predisposing cause of the formation of thrombi, and
hence of pulmonary embolism. Extensive burns and frostbite are also
efficient causes of venous thrombus, and after this manner predispose
to pulmonary embolism. The separation of the placenta after delivery
leaves an open condition of the uterine sinuses which is a real
traumatism, and which occasions the formation of sanguineous coagula.
The irritation of the sinuses may extend to the large extra-uterine
veins (iliacs), and lead to further deposits of fibrin which may give
rise to pulmonary embolism. In these latter cases the inflammation of
the veins, if it occurs, is apt to follow the formation of the
coagulum. Cases of pulmonary embolism have sometimes been occasioned by
the compression of the lower extremities with Esmarch's elastic
bandage.28 Massari indeed cautions his readers against the use of
elastic bandages for varicose subjects. Even if their use be deemed
advisable, never should the limbs be permitted to remain bandaged
during several consecutive hours, for fear lest fibrinous clots be
formed. Azam cites a case of cyst into which an injection of iodine was
made, and quickly followed by obliteration of the pulmonary artery.
Hélie (1837), Gütterbock, and Marjolin (1837) have each related a case
of pulmonary embolism following a sprain. The most frequent cause, in
this division, of pulmonary embolism is
without question
fractures. The first case reported is probably one by Virchow in 1846
of an extra-capsular fracture of the thigh which led to a fatal
termination by a pulmonary embolism.29 Sixteen years later (1862) a
second fact of pulmonary embolism following upon a fracture was
communicated to the Institute by Velpeau.30 In 1864, Azam31 read
two memoirs—the first before the French Academy of Medicine, the
second before the Congress of Bordeaux—in which not only the relation
of fractures, but all kinds of traumatisms, to pulmonary embolism was
fully considered. In these two articles several illustrative cases were
recorded as being seen by Gosselin, Richet, and Labat. In the following
years several articles of value appeared on the subject of emboli and
of their relations with contusions and fractures. Among authors we
should cite the names of Bertin (1868), Durodié (1874), and Besson
(1878) as workers in this direction. It has been noted not only that
the fractures amongst traumatisms cause a large proportion of cases of
pulmonary embolism (16 times in 30 cases), but also that the number of
instances of fracture of the leg largely predominate (11 cases).32
The explanation given to the latter circumstance is in part the near
proximity of the bones with large veins (Verneuil), and second the
dilatation of the veins themselves (Le Dentu). Occasionally the
embolism of the pulmonary artery has consisted mainly of fat: in one
instance there was fracture of the thigh consequent upon a fall;33 in
the other the patient was suffering from a gunshot wound of the left
knee.34 In both specimens examined after death under the microscope
fatty matter was found in the capillaries and pulmonary arteries. It
was probable that the fat had been transported by the veins—in part
from the lacerated marrow, in part from the subcutaneous adipose tissue.
25 Soc. Méd. Bordeaux, 15 Nov., 1867.
26 Annales d'Oculistique, 1864.
27 Discussion à la Soc. de Chirurgie, 14 Avril, 1875.
28 Annali Universali di Medicina, Milano, May, 1877;
Wiener Med. Woch., 1875, No. 48, quoted from Dr. Dobell's report on
Diseases of the Chest, vols. ii. and iii.
29 Traube's Beiträge sur experimentalen Path. und Phys.,
1846, Heft 551, quoted by Levrat.
30 Comptes rend. de l'Académie des Sci., 7 et 14 Avril,
1862.
31 Gaz. hébd. de Méd. et Chirurg., 1864.
32 Levrat, Des Embolies veineuses d'Origine traumatique,
p. 54, Paris, 1880.
33 Hesch, Anzeiger d. K. K. Gesellschaft der Aerzte in
Wien, 1876, No. 3, quoted in Dobell's Reports, vol. cxi., 1877.
34 Dorpater Medicin. Zeitschrift, Bd. vi., Heft iii. and
iv., 1877, pp. 326–338, cited by Dobell.
III. The puerperal state has been considered by Behier, Dubreuilh, and
others with some degree of reason as one closely resembling a condition
of traumatism. In fact, the raw surface with widely-open uterine veins
and sinuses which exists so soon as the placenta is fairly separated is
analogous to that of a limb which has just been amputated. The
differences which present themselves are those which arise from the
special state of the patient herself. During gestation, and
particularly toward its terminal period, the relative quantity of
fibrin to the mass of the blood is greatly augmented. According to
Andral and Gavarret, this excess of fibrin may become so great as to
reach a third more than the normal quantity. After delivery of the
foetus and placenta involution of the uterus begins. This process lasts
several weeks, and during this period the blood is filled with effete
material. Besides these favoring causes of thrombosis which are special
to the puerperal state and mark its blood-dyscrasia, we have the fact
of loss of blood, both during and after confinement, as an efficient
and well-known cause of this accident. According to Leishman,35 who
cites Merriam, this is doubtless the reason why after placenta prævia
cases of phlegmasia alba dolens are so frequently observed. Not only
does Richardson consider the loss of blood as predisposing toward
pulmonary thrombosis, but also syncope or exhaustion in other depressed
states of the system. In some such instances, however, we must not
ignore possible disease of the myocardium or compression from an
abscess of the broad ligament (Charcot and Ball). The coagula formed in
the femoral or saphena veins may
sometimes extend into the
iliacs, venæ cavæ, and become a frequent source of pulmonary embolism.
Owing to the rapid softening of clots formed in the uterine veins
during septic endometritis, we have a special cause of pulmonary
embolism accompanied by toxic phenomena (Virchow). Several of the
operations necessary in certain complications of this condition, such
as application of the forceps, detachment of the placenta, etc., have
been followed by pulmonary embolism (Massari). It is not remarkable
that with so many predisposing causes of thrombosis blood-clot should
be of frequent formation in the puerperal state.
35 System of Obstetrics, p. 710.
Phlegmasia and pulmonary embolism have been well studied on account of
their gravity; the other situations of fibrinous deposit are very
imperfectly known. Playfair36 believes that clots may form in the
right heart and pulmonary artery, just as they may be produced in other
portions of the venous system and under the influence of the same
causes. This conviction is opposed to that of Virchow and Bertin,37
who hold that an embolus must be the starting-point of a blood-clot,
and that without its presence it cannot form. Virchow, indeed,
considers stagnation of the blood as the most essential condition of
the formation of a coagulum. It would seem, however, that the action of
the heart is so feeble in certain debilitated persons, or in diseases
in which there is strong tendency to adynamia, that this objection is
at least partially met. Certainly, as Humphrey38 has shown, the
pulmonary artery, owing to its numerous divisions and the prominent
angles it offers, is favorable to coagulation by its anatomical
formation. Moreover, if coagulation may form around an embolus, why
cannot similar causes which bring this about also occasion a
spontaneous deposit of fibrin? The greater number of cases of pulmonary
embolism in the puerperal state occur in young women not many days
after confinement (Hennig, Luzzato). Occasionally a case is seen as
late as the fifth week. Cases also occur, though exceptionally, during
pregnancy. Playfair39 has endeavored to show, partly by post-mortem
appearances, partly by the date of the accidents, the distinctions to
be drawn between pulmonary embolism and pulmonary thrombosis. After the
nineteenth day from the date of delivery the accidents are usually due
to embolism, before this date to thrombosis. This would appear to be
rationally explained when we consider that the degenerative changes
which alter the vascular clot sufficiently to permit its transport from
the place of its formation to a distant organ take a certain time to
become effected. The causes of the pulmonary thrombosis are those which
produce coagulation elsewhere in the vascular circuit during the
puerperal state. Pulmonary embolisms are more frequent with women than
men on account of affections of the uterus and the puerperal condition
(80 to 66, Luzzato). In children pulmonary embolisms generally come
from clots first formed in some one of the peripheral veins (renal,
umbilical, diploe, etc.). Autochthonous clots in the pulmonary artery
may be due to direct pressure from enlarged ganglia of the neck. The
great number of pulmonary embolisms form in the vessels of the lower
extremities. Thus far, thrombi have not been shown in the larger
lymphatic trunks of the body.
36 "The Puerperal State," being Part V. from a Treatise on
Midwifery, p. 50, Philada., 1882.
37 Des Embolies.
38 On the Coagulation of the Blood in the Venous System
during Life, quoted by Playfair.
39 Lancet, 1867.
SYMPTOMATOLOGY.—The symptoms thus far observed of pulmonary embolism
are not usually very full or accurate. Many of the cases occur so
suddenly and fill the beholders with such dismay that clinical
observations are imperfect. Opposed to this statement we note the fact
that what pertains to pathology and morbid anatomy of pulmonary
embolism is particularly complete. Nevertheless, for the sake of
clearness and in view of accidents really
observed, we may divide
the cases into—1st, sudden, fatal form; 2d, grave form; 3d, benign form.
1st. Sudden, Fatal Form.—In this category should be placed those
instances in which the main trunk or both primary divisions of the
pulmonary artery have become wholly obstructed in a sudden, almost
instantaneous, manner. Immediately the patient is a prey to the most
intense dyspnoea and anxiety; the chest-walls rise and fall in an
exaggerated degree and with great rapidity; the heart-pulsations are
tumultuous and irregular; there is intense pallor of the face; a groan
or cry is heard; there is a vain and brief struggle for breath; and
death may occur before aid can be offered, with symptoms resembling
those of asphyxia. These rapidly fatal accidents are always deeply
impressive, but never so appalling as when they take place in
convalescence, when everything appears to be going on well, and there
is no reason to apprehend such an occurrence had not numerous recorded
facts affirmed their verity. Such cases have been observed40
particularly after fractures of the lower extremities and during
recovery after confinement.41 The accidents are not always asphyxic
in character, even though they be equally sudden and destructive.
According to Trousseau,42 this is true where the embolus is arrested
in the right ventricle and is of sufficient size to cause stoppage of
cardiac contractions and an attack of fatal syncope. In instances which
are not mortal in a few moments, and where the gasping and struggling
for breath continue during half an hour, an hour, or more, the
excessive pallor gives way to a deeply cyanosed tint of the face. When
the face assumes a livid purple hue it has been considered as proof of
a condition of spontaneous thrombosis rather than embolism.43
40 Azam, 1re Mémoire, Gaz. hébd. de Méd. et Chirurgie,
1864; Observ. II., reported by Levrat.
41 British Medical Journal, March 27, 1869.
42 Clinique méd., t. iii. p. 715.
43 Such a case is reported by Playfair in Part V. of his
Treatise on Midwifery, and is also recorded in Obst. Trans., vol.
xii. p. 194.
Although the heart-beats are vigorous at first, they soon become weak,
intermittent, and irregular. Similar characters may be noted in the
pulse, which is very soon compressible, thready, and at times almost
imperceptible. These latter conditions of the cardiac movements may
exist from the beginning of the accidents, and may be accompanied by
coldness of the extremities and chilly sensations (Cohn). Frequently we
observe convulsive movements and foam at the mouth just before death.
When these symptoms have been remarked, the question has been raised as
to whether the patient was suffering from an epileptic seizure.44 The
first impressive effects of pulmonary embolism undoubtedly attach
themselves to the respiration and circulation. The nervous system is
not always so visibly affected. Frequently the patients preserve
complete mastery of their intelligence to the end, and cry out in no
doubtful accents, "I am stifling! I am dying!" Occasionally they even
point with their fingers to the exact seat of the sudden obstruction in
the chest. In a case of Vidal45 the peculiar and painful sensations
indicated by the patient in the precise location of the embolus had
considerable diagnostic importance. This indication, however, is not
always valuable, and may be misleading, as in the case reported by
Ormerod, when the patient, a young girl, paraplegic, was attacked
suddenly with intense feelings of suffocation and pointed to the throat
as being the seat of the obstruction.46 Frequently these suddenly
fatal cases occur in the course of an acute or chronic disorder, and
usually the terrible phenomena manifest themselves after some movement
or effort, as one makes in sitting up in bed or reaching for a desired
object. Under these latter circumstances sudden pallor may overspread
the features, the heart
cease to beat, and the patient expire in
a true syncopal attack, without any of the asphyxic appearance
previously referred to. Usually, however, the need of air is most
acutely felt, the muscles of the neck and thorax are violently
contracted, whilst the patient suffers from intense anxiety and
oppression. Meanwhile, air enters the lungs freely with each successive
inspiration. Percussion and auscultation of the chest do not reveal any
notable change in the pulmonary structure, and the peculiar asphyxia
which is present results rather from the want of blood to be oxygenated
than from the lack of air or sanguineous stagnation. Indeed, Lancereaux
affirms that death in all cases of fatal pulmonary embolism follows
upon these progressive asphyxic features. Never, according to him, does
it occur from a real attack of syncope.47
44 Picot, Les grands Processus morbides, 1876.
45 Ball, Des Embolies pulmonaires, Observ. xxvii., Thèse,
Paris, 1862.
46 London Med. Gazette, vol. ix. p. 788, quoted by Hayden,
p. 1029.
47 "Comptes rendus de la Société de Biologie," 1861, Dict.
de Méd. et de Chirurgie, vol. xxix. p. 365.
The immediate cause of death in these cases is differently regarded by
eminent authorities. Virchow48 holds that the heart-beats suddenly
stop and death is caused by syncope. Picot and Panum claim that
inasmuch as the left heart does not receive any blood from the lungs,
the brain cannot be supplied, and thus anæmia of the brain becomes the
immediate source of a fatal termination. True it is that owing to the
complete obstruction of the pulmonary trunk or its bifurcation no blood
can reach the brain, but for a similar reason the coronary arteries
cannot be supplied, and indeed the whole arterial system remains empty,
whilst the surface of the body becomes livid, owing to marked venous
distension. Paget holds to a conservative view, believing that death
results at times from anæmia and on other occasions from syncope. It is
the belief of the writer that most of the phenomena preceding death are
in the majority of cases those of asphyxia, and he recognizes with
Bertin49 and Lancereaux that deficient oxygenation of blood is, after
all, the essential cause of death. In all cases of very rapid death,
Lancereaux believes that the embolic clot must have originated in, and
been transported from, one of the large veins of the lower extremities
or the pelvis, and that the prolongation of clots formed elsewhere in
the venous system, when broken off and carried in the blood-current,
are insufficient by reason of their small size to block up completely
the pulmonary artery.50
48 Gesamm., Abhandl., 1862, p. 316, quoted by Playfair.
49 Étude critique de l'Embolie, Paris, 1869.
50 Bucquoy, Des Concrétions sanguines, Paris, 1863, p.
147.
2d. Grave Form.—In this form neither the pulmonary trunk nor one or
both of its primary divisions had become obstructed. The embolic clot
or clots have been carried farther into the pulmonary structure and
filled up one or more of the secondary bronchial divisions.
Nevertheless, the accidents declare themselves with the same remarkable
suddenness, and are accompanied by chilly feelings and pallor of the
face, just as we have for a brief period after all great shocks to the
system (Levrat). In spite of the rapid occurrence of the accidents,
they last a considerable time, and hence we are able to study more
carefully the respiratory and circulatory symptoms proceeding from the
pulmonary obstruction. The pallor of the face soon passes away, and we
have in its place cyanosis of the features and a livid hue of the
extremities, and in fact of the entire surface. Sometimes, owing to
tricuspid regurgitation, we have a venous pulse rapidly produced in the
veins of the neck. The patient constantly suffers from oppression and
anxiety, and sighs and utters complaints, whilst he makes powerful and
ineffectual efforts to diminish his uneasy sensations by deep and rapid
inspirations. Occasionally partial convulsions are noted. At times,
also, the patient complains of cephalalgia and vertigo, but rarely
shows signs of delirium. After a time the accidents narrated become
less, and there is relative ease. Soon, however, there is a
recrudescence of the attack, and the anxiety and oppression are even
greater than before. A succession of such occurrences may take
place, and are attributable to a change of location of the clots. If we
examine the chest by our physical means of exploration, the result is
little better than negative. Percussion shows no abnormal dulness.
There are no abnormal râles, and at most there is only a certain rough
timbre of the respiratory murmur. After a short time the heart-beats
become irregular and feeble, the temperature falls one or two degrees
(Cohn), the body is covered with abundant clammy perspiration, and the
patient succumbs. Sometimes death is due, where the accidents are
prolonged, as much to the secondary effects in the lungs of the embolus
as to the embolic plug itself. The accidents commence, indeed, by
intense dyspnoea and oppression, but are soon followed by sanguinolent
sputa. Luzzato has mentioned one case where the hæmoptysis was an
initial symptom of pulmonary embolism, but it is very probably
explained by concomitant chronic cardiac disorder. Whenever we find the
local signs of an infarctus, the general condition is apt to become
more and more serious, new clots reach the lungs, and death occurs in a
few days from asphyxia. Frequently albuminuria and oedema of the
extremities are observed. In those instances where the patient recovers
the mucous râles and localized dulness caused by the infarctus remain
for a while, but the sanguinolent sputa diminish, and little by little
respiration becomes more vesicular. The patient is now only exposed to
dangers due to ulterior transformations of the infarctus. Occasionally
new infarctions may form several times and produce accidents similar to
those referred to. If there is no hæmoptysis, an infarctus can only be
suspected, and often after death this condition is discovered when
during life it was wholly overlooked. Sometimes the pulmonary
embolisms, although quite numerous, affect vessels of very small
calibre, and remain latent during life or occasion no characteristic
symptoms. In those examples in which some of the secondary divisions of
the pulmonary artery are filled with embolic plugs there is of course a
diminished supply of oxygenated blood sent by the left heart to the
brain, and there is likewise an accumulation of carbonic acid in the
nerve-centres. The lack of oxygen is not enough to cause rapid death,
and the accumulation of carbonic acid produces, no doubt, the symptoms
of temporary excitability and the local convulsions which are so often
present under these and analogous conditions. Whenever after this
period of excitement symptoms of slow asphyxia become apparent, they
are due either to an excessive afflux of blood into the free arteries
of the lung and the passage of the plasma through their walls into the
pulmonary vesicles, or they are caused by a succession of emboli
blocking up the remaining vascular twigs. Upon the mechanism of death
resulting from pulmonary embolism Jacquemet51 has made a careful
study, showing the cases of death attributable to syncope and those
solely explained by asphyxia. The only physical sign observed in the
region of the chest in fatal cases which would appear without question
to be caused by a pulmonary clot is a prolonged basic murmur extending
itself to the right and left of the sternum in the direction of the
primary divisions of the pulmonary artery. "This sign," says
Walshe,52 "I most certainly heard in an old gentleman whose life was
brought to a sudden close in the course of an acute affection by
coagulation in the pulmonary artery."
51 Congrès médicale de France, 2ème session, Lyon, 1864,
quoted by Levrat.
52 Diseases of the Heart, 4th ed., 1873.
Whilst authors have usually insisted with much emphasis upon the
habitual fatal termination of pulmonary embolism, especially where the
plug fills one or both of the large divisions of the pulmonary artery,
they have not referred as a rule to the possibility of the patient's
recovery. Now, if the arteries be only partially filled by the plugs,
and a current of blood can pass around them, the lungs may be
sufficiently supplied with oxygenated blood to sustain
life for a
while and until the clot can be reabsorbed. That this clot can be
reabsorbed in the pulmonary artery is shown by what has been frequently
observed in regard to clots which have been contained in other vessels
of the body.53 Not infrequently, simultaneous with or following
upon54 obstructed pulmonary circulation, the phenomena due to
peripheral thrombosis have been observed (phlegmasia dolens). In a
somewhat analogous manner, after anxious respiration had occurred,
obviously due to pulmonary embolism, a peripheral thrombus previously
present has been known to have disappeared.
53 Humphrey, Med.-Chir. Trans., vol. xxvii. p. 14.
54 Case reported by Playfair in Treatise on Midwifery,
Part V., amongst those illustrative of recovery after symptoms of
pulmonary obstruction.
3d. Benign Form.—This form occurs frequently after the traumatisms as
described by Besson.55 Habitually we have few or no symptoms which
are at all characteristic. The embolisms are capillary and remain
latent. Now and then there may be a sudden attack of difficulty of
breathing, accompanied by constriction of the thorax which shall
probably be explained in this manner. Sometimes the sputa are slightly
covered with blood, and this fact lends additional authority to the
diagnosis. According to Ball, the physical evidences of the embolisms
in the chest are wholly disappointing. Besson, however, finds distinct
evidences of their presence in crepitant and subcrepitant râles and
dulness on percussion. Levrat56 believes we may have probable signs
of the existence of capillary emboli, and cites as an example a case of
traumatism in which there might be present a thrombus, and where there
would be sudden hæmoptysis followed by sanguinolent sputa, and yet the
examination of the chest remained negative. There are cases reported by
Paget, Colin, and Feltz in which fatal terminations, caused by a
succession of asphyxic paroxysms, took place just as they do after
sudden plugging of the large pulmonary divisions. This is true only
when the capillary embolisms are very numerous.
55 Paris, 1878.
56 Thèse, Paris, 1880.
It has been noted that secondary changes of capillary embolisms are not
apt to occur in the anæmic and cachectic; in the plethoric and those
affected with chronic cardiac disorders the contrary is true. According
to the condition of the nervous system, to its greater or less tendency
to react, there will be more or fewer chances of the capillary
embolisms making their existence known by an attack of suffocation (Luzzato).
PATHOLOGY AND MORBID ANATOMY.—Pulmonary embolism gives rise to
different morbid lesions. The nature of these and their extent depend
in great measure upon the size, situation, and character of the plug
which fills the main trunk of the pulmonary artery or one or more of
its divisions. The changes of tissue which take place are of course in
close relationship with the length of time which has elapsed since the
embolus first migrated. They are also influenced greatly by accidents
or complications which have arisen. It shall be our effort first to
narrate the important considerations which pertain to simple embolus,
and whether it affect a large artery or only a small vessel. After
speaking of the simple variety we will refer briefly to septic and
fatty emboli and also to those of other nature.
The pulmonary artery may be blocked up by a clot formed in situ. This
fact has been shown to be true by many writers—i.e. Lancereaux,
Duguet, etc. When a thrombus is present it may be occasioned by an
inflammatory condition of the artery (rare), or by a dyscrasic
blood-condition, or again by localized compression in the vicinity of
the coagulum, as from a tumor. We may find arterial thrombosis during
pulmonary phthisis, in pneumonia, in pleurisy, and in cases of cardiac
dilatation or degeneration.57 Endocarditis of the pulmonary valve and
compression of the neck by enlarged ganglia have been mentioned as
causes of these thrombi.
57 Here it is due to relative stasis of the blood.
Ordinarily, a pulmonary embolus is fixed at the point of division
of the main vascular trunk. It more or less completely blocks up the
calibre of the artery, and is usually situated in the midst of a soft
new clot, which also covers it in front and behind. The embolus often
manifests its origin from a clot contained in one of the large veins of
the lower extremities. One end is rough and excavated, and fits into
the coagulum we find lodged there. It is often twisted like a
corkscrew, or has on its surface the mark of the valves of the vein
from which it has migrated. It is white or yellow in color. If we
examine the interior of an ordinary autochthonous clot, we find it
softer relatively than the clot of an embolus, and, moreover, no
prolongations proceed from it which fail to correspond with any
vascular division. The suddenness of the accidents and the
disappearance of a previous peripheric clot are strong reasons in favor
of the existence of the embolus.
More emboli are carried into the right lung than into the left, on
account of the larger size of the artery. The median and lower lobes
are also the ones most usually affected. When the right lung is
diseased the emboli are then more frequently transported on the left
side. After a time an embolus goes through certain transformations. It
softens at its centre, owing to degeneration of the white
blood-corpuscles. The hematies disappear soon, and the fibrin also
changes in structure, becoming soft and granular. This softening at the
centre of the embolus must not be confounded with a purulent change
which affects certain thrombi which come from or are carried to a focus
of suppuration. Whenever an embolus has been a long while in the
artery, a neo-membrane forms between it and the arterial wall. This
neo-membrane is mainly constituted by fibrillous tissue and here and
there some developed vascular twigs. As a whole, it forms a sort of cap
or covering for the embolus, and finally it takes up by absorption the
granular detritus which forms in the interior of the clot. We perceive
from the foregoing statement that a pulmonary embolism may heal, and
that the process of its cure differs in no respect from what occurs in
the case of a coagulum which disappears by absorption from some other
portion of the vascular system, or indeed from the surface of the
serous membrane. When the embolic plug comes from a focus of
suppuration or gangrene the vascular walls will probably be affected
with similar alterations.
In consequence of the obstruction of the main trunk, or of the
important branches of the pulmonary artery by embolic plugs, certain
effects are directly produced. These are—1st, mechanical; 2d,
nutritive; 3d, irritative.
Perhaps, however, before describing these effects in detail it would be
well to mention certain anatomical facts with respect of the
circulation of the lung which have considerable importance in view of
certain morbid lesions to which we shall refer presently. It has now
been proven experimentally, by the researches of Cohnheim, Litten, and
Küttner, that there are no vascular communications between the
pulmonary and bronchial arteries, and, further, that there are no
branches coming off from the small divisions of the pulmonary artery by
which a collateral circulation can be carried on when the arteries of
the third order are obstructed by embolic plugs. It is also further
corroborated by the investigations of the authors named that the
pulmonary artery is mainly instrumental in keeping up the function of
the lungs, whilst the bronchial artery is the artery of nutrition. If
the latter were obstructed in any manner, gangrene of the pulmonary
structure must surely follow; if the latter be ever so thoroughly
closed, no death of tissue will ever result.
The mechanical effects caused by the obstruction of the main artery or
of a primary division of it are much less considerable than when a
smaller artery is plugged. In the first case the only observable
condition is that of anæmia of pulmonary tissue. Occasionally
Lancereaux has noticed atelectasis of certain lobules. The pathogeny of
this condition is difficult to
explain, as air enters the bronchi
freely, and it should not be produced without effusion taking place. If
life lasts a few hours hyperæmia and oedema of lung-tissue may be
caused. The latter conditions are aided if there be existing organic
disease of the heart. If, now, the smaller arteries be obstructed by
embolic plugs, there is a strong tendency to the formation of
hemorrhagic effusions, to which the name infarctus has been very
properly given by Virchow. These infarctions vary in size from that of
a small nut to that of a pullet's egg, just as they implicate one or
more pulmonary lobules. They are situated at the periphery of the lung
underneath the pleura. They are conoid in shape, with the apex turned
toward the root of the lung. They seem like hard nuts under the surface
of the lung when felt with the fingers. Their color is dark-brown or
black; their cut surface is granular, even more so than the surface of
a lobule solidified by broncho-pneumonia. The capillaries in and around
these masses are filled with red blood-corpuscles. The same is true
also of the alveoli, in which we find degenerated epithelial cells in
large numbers containing granules of pigment. The connective tissue
about the alveoli becomes thickened, the alveolar cavities contract,
and finally the infarctions are changed into a real fibrous cicatrix,
in the same way as they are transformed in other viscera of the body.
Prior to this stage, however, we notice that the color of the
infarction has gradually changed, and that it has become pale and
yellow. This is due to the fatty degeneration of the fibrin contained
in the alveoli, and the same affection of the enclosed cells. May any
infarctions be restored to a condition of perfect integrity? It is more
than doubtful, even if the obstructing plug of the pulmonary artery
disappeared very soon, because the pulmonary parenchyma beyond the clot
has suffered so much from fatty changes and hemorrhage that the vessels
are unequal to their function. At times, owing to the stoppage of the
nutritive action of the bronchial artery, the infarction may become a
cheesy mass, which soon softens and is expectorated. This leaves a
cavernous opening in the lungs. Sometimes the infarction becomes
infiltrated with calcareous salts. It cannot be confounded readily with
other lesions, especially pulmonary apoplexy, on account of its
distinct limitations. Sometimes a lobule affected with
broncho-pneumonia and hemorrhage may simulate it closely. The pathogeny
or mode of production of the hemorrhage in a more or less limited area
of the lung which is concomitant with an embolic plug in one of the
branches of the pulmonary artery is difficult to present. This fact may
be explained by the different solutions afforded by various authors as
to the manner in which the apoplectic condition and the embolus are
correlated. Certain writers have affirmed that the embolus itself is
but a secondary phenomenon, and the surrounding hyperæmic state is the
real cause of its production (Laennec). Later authorities have
established that this statement is rarely true, and that the embolus
always occurs first and the localized congestion follows closely afterward.
Precisely the way in which the congestion or hemorrhage was occasioned
has not been elucidated in a similar manner by all. Virchow years ago
(1856) recognized that one or other was due to vascular stasis and
reflux of venous blood from neighboring vessels; in other words, the
explanation here given was the same as for infarctus of the kidney or
spleen. Jürgensen regards infarctus as being similar in structure to
lobular pneumonia. It has been also affirmed that owing to incomplete
obstruction tissue supplied by the artery was at first anæmiated, and
later, by reason of excess of backward pressure from venous trunks, it
became congested or hemorrhage was effected. Duguet states that the
arterial walls beyond the embolic plug become inflamed, and thus act as
a cause of hemorrhage. The first effect, then, of an embolic clot being
arrested in the lung is that of anæmia. Soon this state is followed by
hemorrhage occasioned in the way I have mentioned. In the lung the
hemorrhage means of necessity rupture of a vessel; in the spleen
and brain this is not so invariable. Whilst the smaller bronchi are
sometimes congested, they are rarely infiltrated with blood. For this
reason gangrene is not a frequent sequela of pulmonary infarctus. It is
not admissible that hemorrhage should occur without rupture of the
vessel in many instances, for the reason that the sanguineous effusion
is not always limited to the area supplied by a given vascular division
obstructed, nor is it in the centre of the lung conoid in shape. The
catarrhal changes in the lungs are very constant, although usually
superficial in character and only affecting the epithelium. As
Cohnheim58 has pointed out, there is a proneness to degeneration
rather than to inflammatory action.
58 Untersuchungen über die Embolischen Processe, Berlin,
1872.
Due consideration being given to the changes of tissue effected by an
arrested embolus, we can more fully understand the clinical phenomena
connected with them. True it is, however, that the troubles of
innervation and respiration thus brought on may pass unperceived, and
for the simple reason that the pathological lesion follows, as a rule,
only the transport of an embolus into a small arterial division. In a
similar way the intensity of the venous reflux is in direct
relationship with the functions of the heart and lungs, and if either
the diseased hemorrhagic effusion is rendered more certain.
It is probable that a simple embolus cannot be followed by a gangrenous
focus in the lung. This result is recognized frequently when the
embolus originates in a purulent deposit, whether it be the consequence
of an abscess, of puerperal fever,59 of a compound fracture, etc. The
gangrenous cavity finally softens, its contents are expectorated, and
the pulmonary tissue becomes indurated and cicatrizes around the excavation.
59 Dublin Journ. of Med. Science, May, 1875.
Pulmonary embolism may at times be the occasion of a pneumonic
consolidation limited to the area of distribution of an obstructed
pulmonary division. Sometimes the consolidation extends beyond this
limit, and is seemingly the immediate effect of neighboring irritation.
When the consolidation exists near the surface of the lung, it may
extend to the pleura, producing considerable effusion and
pseudo-membranous deposit upon the visceral layer. Both sides of the
chest may occasionally be thus affected.
Capillary emboli of simple nature have long been described. Unless they
obstruct a great many vessels simultaneously, they rarely cause death
(Feltz). They do not, moreover, produce hemorrhages or infarctus,
inasmuch as a collateral circulation is so easily established. The
principal sources of these emboli exist outside of the vascular system,
and in this variety we find emboli of air, fat, of the débris of new
growths, etc.
Since 1866, the period at which Zenker first directed attention to
fatty emboli in the pulmonary capillaries as a complication of an
accident in which a patient was crushed between two wagons, many
observers have noted accidents due to these obstructing bodies. Fatty
emboli may follow numerous causes (contusions, suppurations,
osteomyelitis, etc.), but are more frequent and fatal after comminuted
fractures of the limbs than from any other single cause (Flournoy).
Occasionally the patient will have recovered from the shock following
the fracture, when he is suddenly attacked with intense dyspnoea and
expires within a few hours. The only effectual remedy would seem to be
immediate amputation of the limb above the seat of the fracture. When
the vessels of the lungs have been examined in these instances, they
have been found to contain elongated masses, several millimeters in
length, possessing a particular brilliancy, "disappearing under the
action of ether, and becoming a deep, black color with osmic acid."60
60 Déjerine, Le Progrès médical; Med. Record, Jan. 15,
1879.
Specific emboli may be followed by the mechanical effects of
simple emboli, but they are also accompanied by specific phenomena
which are in relation with the particular focus in which they took
origin—i.e. purulent or septic focus, gangrenous cavity, cancerous
tumor, etc.
In the region where the embolus is arrested, local alterations of
tissue become developed which correspond with the nature of the changes
which exist in the spot from which the embolus was derived. Very often
these morbid effects are produced without any mechanical results of
emboli being occasioned.
Septic emboli are observed in infectious diseases, such as pyæmia and
puerperal fever, and are prone to occasion not merely mechanical
effects, but equally the suppuration, liquefaction, and finally the
absolute destruction of tissue. Cruveilhier has seen pulmonary embolism
followed by metastatic abscesses. The formation of these was attributed
by him to suppurative phlebitis affecting the capillaries.61
61 Dict. de Méd. et de Chirurgie pratique, vol. xxix. p.
360.
It is admitted to-day that infectious germs causing metastatic
abscesses may be transported in the pulmonary vessels without being
accompanied by pulmonary emboli. It is equally true, however, that the
usual means of transport for these infectious bacteria or micrococci is
an embolic plug (Jeannel).
The effects produced by the septic emboli are pneumonic consolidations
involving the lobules and going on rapidly to suppuration, and
sometimes to gangrene. The coloration of the lobules is red, gray,
tending toward yellow as the tissue shows signs of softening. The
contents of the abscess are yellow or brown and contain particles of
the pulmonary structure. The tissue in the vicinity is gray and
infiltrated with pus.
The number of metastatic abscesses is often very considerable. Their
size is usually smaller than the infarctus due to simple emboli. The
smaller abscesses are found usually near the surface of the lung. When
several abscesses unite into one they may attain the size of the fist.
Whenever there exists a gangrenous lesion in some portion of the body,
sphacelated débris may be carried from this focus into the venous
system, and finally into the lungs. Arrested in some spot of the
pulmonary tissue, the embolus will give rise to gangrenous changes
similar to those of the region from which it started.62 The infarctus
thus produced will assume a dark color, then become gray toward the
centre, where it shows signs of softening. Later, under the form of a
thick semi-fluid mixture of extreme fetid odor and dark-brownish color,
it is expectorated by degrees, and leaves behind a gangrenous cavity.
The process of change in this case is due to the proliferation of
infectious germs. It may be, however, that the gangrenous particles
transported into the lungs have the power in themselves to decompose
the tissues by chemical action into more simple elements.63 According
to the later researches of Doleris, septic bacteria have been found by
him in these putrid infarctions.64
62 This process was first pointed out by Cruveilhier in his
work on Phlebitis. It remained, however, for Virchow in his Cellular
Pathology (p. 235, ed. Strauss), and later for Billroth in his
Surgical Pathology, 1868, p. 395, to give greater development to this
belief.
63 Lancereaux, Traité d'Anatomie pathologique, vol. i.,
1875–77, p. 14 et seq.
64 Quoted by Levrat, p. 78.
The infecting power of cancer is certainly not equal to that of
gangrene. Nevertheless, Lancereaux has shown that cancerous nodules may
be produced by metastasis. This belief in the possibility of a simple
embolus taking on a cancerous change, and carrying this disease to
far-removed parts, has been strongly combated by Cohn. Neither
experimental nor human pathology has thus far decided the subject in an
absolute manner. Certain it is,
however, that the power of emboli
from cancerous foci to carry similar disease elsewhere depends partly
upon the vitality of the cancerous particles, partly upon the power of
receptivity as shown by certain constitutions for developing special
diseases, and which relates, after all, to the general question of
dyscrasia. Langenbeck has shown that certain animals will die within a
few hours after the injection of cancerous juice. On the other hand, it
is known that the infective power of the juice only lasts a very brief
period. Weber, Luzzato, and others have reported numerous examples of
secondary tumors of similar nature developed in the lungs when
epithelioma, enchondroma, sarcoma, or carcinoma existed somewhere in
the body. Finally, it would appear that emboli containing hydatids in
embryo have been the means of transporting these parasites into the
pulmonary structure.
DIAGNOSIS.—The sudden commencement of the accidents, especially when a
peripheral thrombus has existed previously in one of the large veins of
the extremities, renders the diagnosis almost certain. If the patient
has been suffering from the effects of a traumatism (contusion,
fractures, operation on the veins of the limbs or rectum, etc.), and is
almost instantaneously attacked with intense dyspnoea and a feeling of
anguish which he refers to the thoracic region, we shall be able
usually to eliminate other intercurrent affections and to diagnosticate
the existence of pulmonary embolism.
This accident is often confounded with cardiac thrombosis. It may
usually be separated from it by the following differential symptoms:
Cardiac obstruction from a clot usually comes on insidiously, by
degrees; the heart-beats are irregular, tumultuous, muffled, and
distant; there may be a murmur from one or other of the cardiac
orifices; there is no initial chill; peripheral thrombosis is not
present as a rule; there is no sensation of localized obstruction in
the chest.
In pulmonary embolism the début may be instantaneous and death follow
in a few seconds; or, again, the beginning may be rapid, ushered in by
stifling in the chest, a chill, cyanosed face, followed soon by
excessive pallor, a distinct sensation of obstacle to breathing in a
particular region. Percussion and auscultation may remain negative. The
patient may have a succession of similar accidents, and yet finally
recover. According to Ball, pulmonary embolism and pulmonary thrombosis
cannot be distinguished during life. In one case which he reports where
pulmonary embolism should have been present without question the
autopsy showed the presence of a thrombus in the pulmonary artery. A
succession of chills, general malaise, febrile excitement, the
localized phenomena of pneumonia or gangrene of the lung, point
indubitably to the existence of septic emboli.
The differential diagnosis between pulmonary embolism and other
affections, such as angina pectoris, a foreign body in the
air-passages, pneumothorax, etc., may usually be reached without much
difficulty. Sometimes the paroxysmal dyspnoea with sensations of great
oppression which accompanies mitral stenosis may be mistaken for
pulmonary embolism. In these instances the absence of a discoverable
cause of the attack in pre-existing emboli, and the presystolic murmur
with marked general anæmia, may surely lead to an accurate diagnosis.
It must, however, always be remembered that in mitral stenosis it is
not infrequent to have cardiac coagula formed in the right auricle,
which may become detached and give rise to pulmonary emboli. Under
these circumstances a severe localized pain in the side of the chest
has considerable diagnostic importance as pointing to the presence of a
pulmonary embolus (Cohn).
When there is pre-existing cardiac disease of organic nature a syncopal
attack may sometimes occasion doubt with respect of a correct
diagnosis. The sudden loss of consciousness, excessive pallor, and
absence of pulse will ordinarily, however, confirm the diagnosis of
syncope. Rupture of the heart
is accompanied with symptoms of
syncope rather than those of suffocation (Balzer). Emboli of the
bronchial arteries are not accompanied by any characteristic symptoms
which will enable us to make a differential diagnosis. There is the
same sudden dyspnoea, the initial chill and hæmoptysis, as in pulmonary
embolism (Penzold).
PROGNOSIS.—As will be readily understood, the prognosis is sometimes
difficult to estimate and varies with many circumstances. Certain
emboli, even among those which have occasioned severe symptoms, have
never been recognized. Other pulmonary emboli always remain
comparatively latent. In this connection we should mention those which
take place in the lungs of tuberculous patients. Again, the size and
seat of the embolus will always have great importance in regard to the
prognosis. If the trunk or primary divisions of the pulmonary artery be
suddenly and completely obstructed by emboli, sudden death will surely
follow. If secondary divisions of the pulmonary artery are filled up,
more or less grave symptoms will usually follow. When emboli are
carried into the tertiary or still smaller branches of the artery, they
may not occasion any appreciable phenomena other than a moderate and
passing dyspnoea. If, however, there be a large number of small emboli
carried into both lungs at the same time, it is possible that rapid
death may follow their presence. It is true, however, according to
certain authors, that even a large embolus blocking up the main trunk
of the pulmonary artery may be followed by recovery. Such a case is
that of Jacquemier, reported by Ball. Even in this case, whilst the
presence of the embolus cannot perhaps be doubted, still the exact size
and location may be called in question. And here we may add that in all
cases of reported cure of this nature there will naturally and
inevitably exist an atmosphere of legitimate doubt about the correct
observations and diagnosis of the narrated facts.
What precedes relates exclusively to the existence of simple emboli. Of
course if the embolus be of septic origin, it will be followed by the
appearance in the lungs of foci of purulent pneumonia or of gangrenous
changes of tissue which will finally produce such structural
destruction as almost certainly to terminate in death.
TREATMENT.—The majority of those who have studied this subject have
recognized how vain are our efforts of treatment in many instances.
Pulmonary embolism is one of those accidents which we should always be
prepared to admit, however, when its characteristic symptoms show
themselves, and should endeavor rationally to combat by the therapeutic
means in our power. Even before we have any signs present which
indicate obstruction of the pulmonary circulation, we may have those
which point in a very certain manner to the existence of a peripheral
thrombus. This thrombus may block up completely one of the large veins
of the lower extremities, and may, owing to its possible detachment and
transport, be a constant menace to life. At times these peripheral
thrombi are accompanied by local inflammatory symptoms which belong to
phlebitis. This condition of things is not uncommon after fractures or
other traumatisms. Frequently there is no evidence of any inflammatory
state, and we recognize the thrombus solely by the signs which result
directly from obstructed venous circulation and by the existence of a
hard, indurated cord which fills the vein at a given level. Now, what
are the means we have at our command to prevent the transport of this
coagulum, or indeed to dissolve it, or absorb it in its place?
First, if inflammatory signs are present we should endeavor to subdue
these by local applications of an emollient character, for the reason
that excessive inflammation is apt to produce such changes as cause the
disaggregation of the clot, and hence its detachment. In either case,
whether there be or be not any local inflammatory condition, we should
insist upon absolute repose and quiet. We should not permit the limb to
be moved: we should be
extremely careful in all our manipulations
of it, and only employ those which are absolutely essential. The
patient should not be permitted to raise himself in bed, nor even eat
or drink without assistance. These counsels are very important, since
we know how frequently a very slight movement or exertion has been
followed immediately by the transport of the clot, pulmonary embolism,
and sudden death. In cases of fractures or severe wounds where such a
peripheral clot is discovered the surgeon should be particularly
careful in applying bandages and retentive apparatus. The risk of
displacement of the clot is greater after several days from the time of
the fracture or wound than it is at first, and it is at this period
that the most careful attention should be exercised. Instances are on
record in which so late as the fifty-seventh day after a fracture of
the lower extremity a peripheral thrombus was transported from its
original site and caused a fatal termination (Bouchard).
Some eminent writers have thought by employing a suitable medication we
might hasten the solution of the peripheral thrombi and thus prevent
their migration. With this view Legroux has given the acetate of lead
internally and applied it in solution over the seat of the thrombus.
Richardson has vaunted the use of the carbonate of ammonium in large
and frequently-repeated doses as a solvent of the fibrin. By its means
he believes he prevents the fibrin from precipitating from the blood,
and further helps it to resorb when it has already become solid.
Prevost, Dumas, and Schutzenberger recommend specially the bicarbonate
of sodium, taken internally, with a view of rendering the blood more
fluid and also hastening the retrogressive changes in the clot by its
oxidizing power. According to Boyer, the very object which is thus
sought if it were accomplished would result injuriously to the patient,
since it would favor the detachment of the clot. Further, the continued
use of large and frequent doses of ammonia or soda is prone to lower
the general system very much, and in this manner to act to the
prejudice of the patient. According to Azam, it would appear that what
we most desire to effect is the organization and adhesion of the
thrombus to the walls of the vessel. This can best be accomplished by
fortifying the patient in every possible way and raising his nutrition
to the highest attainable point. Iron, cinchona, the most nutritious
food, should be freely given. Further, the greatest attention should be
paid to the hygienic surroundings. The air should be purified, and if
by chance the patient is suffering from a wound close attention should
be given to the renewal of the dressings and the employment of a
disinfectant locally applied. One of the reasons for this last counsel
is because if the thrombus were detached it is important that it should
be free of any septic taint and not lead to specific accidents
(purulent pneumonia, gangrenous abscess). In the above enumeration we
include the means usually to be employed as preventive measures against
the migration of clots.
Is there any other method which can be adopted with any chance of
success? Of the surgical attempts we should mention favorably in
certain cases, and especially in those where the affected vein is
superficial, the adoption of persistent compression between the clot
and the heart. This means has been alluded to by J. Hunter65 as far
back as 1773. Ligature and section of the vein have also been supported
by some writers as suitable operations to bring into use with a like
intent. Unfortunately, we are obliged to make a second traumatism in
order to carry out this object, and, further, we make by the ligature
at least a second coagulation, which may be the origin of the very
accident we seek to avoid. Nevertheless, J. Teissier66 of Lyons
reports a case
observed by himself in the service of Noël Guéneau
de Mussey, in which a ligature was instrumental in arresting the onward
progress of the clot, which otherwise would have given rise to the
accidents of pulmonary embolism.
65 Observations of the Inflammation of the Internal Coats
of the Veins, quoted in thesis of Levrat, p. 108.
66 Nouveaux Éléments de Pathologie et de Clinique
médicale, t. ii. p. 931, quoted by Balzer.
In the event of pulmonary embolism taking place in spite of all
preventive means employed, what shall we do in order to combat this
terrible accident? According to Ball,67 there are three indications
to be observed: 1. To establish collateral circulation in the lungs; 2.
To diminish local congestions; 3. To favor the resorption of the obstacle.
67 Thèse quoted, Paris, 1862.
The first indication cannot be effectually responded to, by reason of
the fact that there is no way in which a collateral circulation can be
promoted in the lung, owing to its anatomical structure.
The second indication is best observed by the application to the
chest-walls of dry cups in large number, mustard poultices, turpentine,
blisters. In this place we must consider the propriety of bleeding. As
a result of the embolism there is arterial anæmia and venous plethora.
This latter condition can be temporarily relieved by venesection. In
this method, indeed, we have an immediate help for the distended and
burdened heart, and we give time to the system to recuperate somewhat.
We should, however, remember that bloodletting establishes a greater
tendency in the system to the formation of emboli, and is therefore to
be avoided. Moreover, sometimes it is decidedly objectionable on
account of cardiac degeneration, anæmia, or great weakness.
When this method is contraindicated we should not hesitate to recur to
the use of drastic purgatives (Jaccoud). Digitalis has been
recommended, so as to regulate the cardiac action and to increase its
power. Bertin has gone so far as to praise emetics and the use of the
faradic current over the thoracic parietes. It seems as if these were
dangerous methods to employ, since if a portion of the clot is still
undetached the efforts caused by these agents would be apt to separate
whatever portion remained in its original site. In order that a
quantity of oxygen should be inhaled in a given time sufficient to
supply the needs of the economy until a greater power of oxygenating
the blood is established, the inhalation of compressed air has been
vaunted. The objection to this means is merely the one which arises as
we reflect how improbable it is that this agent would be at hand in a
serviceable form when the sudden accidents of pulmonary embolism take place.
The third indication, to favor the resorption of the obstacle, must be
virtually attended to by giving the alkalies in large doses internally.
The advantages and objections to this sort of treatment we have already
referred to.
After this exposition of the different means to be employed, both as
preventive and curative agents of pulmonary embolism, we are obliged to
recognize that very frequently they remain ineffectual. Usually the
accident takes place in a very sudden manner and when we are least
suspecting its advent. When the phenomena do occur which are caused by
its presence, they take place so suddenly, and terminate fatally in
such a brief period, that we scarcely have the time to employ the
remedial agents referred to. Finally, we must admit that in presence of
this complication, especially when there is complete obstruction of the
trunk or primary divisions of the pulmonary artery, all our therapeutic
means are without avail, and we are indeed almost powerless.
DEFINITION.—Pulmonary phthisis is a chronic disease, characterized in
its common form, anatomically, by a morbid product within the
air-cells, in a large majority of cases progressively increasing and
extending, having a tendency to cheesy degeneration and liquefaction
forming collections of puriform liquid which, evacuating by ulceration
into the bronchial tubes, are followed by cavities, these pathological
conditions accompanied by more or less induration from interstitial
morbid growth and by small granules called miliary tubercles. A
comparatively rare form of the disease is characterized by the great
predominance of interstitial growth, leading to notable diminution of
the volume of lung by atrophy and to dilatation of the bronchial tubes.
The latter form is now commonly distinguished as fibroid phthisis. This
will claim separate consideration after having considered the form
generally understood by the name pulmonary or pneumonic phthisis.
SYNONYMS.—Classification.—Much confusion, as regards nomenclature and
classification, followed the adoption by many of the theory of Virchow
that the sole characteristic of tuberculous disease is the presence of
the so-called miliary tubercles. According to this theory, the morbid
product which constitutes the most marked anatomical feature of the
common form of phthisis is simply an inflammatory exudation.
Heretofore, pulmonary phthisis and pulmonary tuberculosis were
considered as convertible terms, but, adopting Virchow's theory, in a
certain proportion of cases pulmonary phthisis is not a tuberculous
disease. Hence arose a variety of names denoting non-tuberculous
phthisis, such as chronic broncho-pneumonia, chronic lobular pneumonia,
catarrhal pneumonia, cheesy pneumonia, etc. These names have shared the
fate of the theory from which they originated, the latter, at the
present time, having but few supporters in any country. It is
convenient to distinguish the morbid product which is characteristic of
pulmonary phthisis as a tuberculous product, and it will be so
distinguished in this article.
The name acute pulmonary tuberculosis denotes an affection which may be
sharply separated from the chronic forms of pulmonary phthisis. The
acute affection is characterized by the presence, exclusively or in
great abundance, of miliary tubercles. It runs a rapid course and the
symptoms are those of an acute disease. The name phthisis implies a
chronic affection. In a small proportion of the cases of pulmonary
phthisis miliary tubercles become developed in great abundance. In
these cases acute pulmonary tuberculosis supervenes upon chronic
phthisis. These cases, by those who regarded phthisis in its ordinary
form as a non-tuberculous affection, were designated cases of
tuberculous phthisis. The fact that in cases
of phthisis there is
a liability to the supervention of miliary tubercles as abundantly as
in cases of acute tuberculosis, is to be borne in mind, but it does not
seem necessary to make a distinct variety of the disease on the basis
of this fact. In some cases of pulmonary phthisis the tuberculous
product is notably large at the outset, and destructive changes in the
lungs go on continuously with unusual rapidity. To these cases the
names phthisis florida and galloping consumption have been applied.
In view of what has been stated, the classification in this article
will not extend beyond a division into the common form of pulmonary
phthisis and the form distinguished as fibroid phthisis. The latter
form has been designated chronic interstitial pneumonia, chronic
pneumonia, and cirrhosis of lung. It is to be understood that reference
is had to the common form of pulmonary phthisis, except in that portion
of this article which has for its heading Fibroid Phthisis.
HISTORY.—Pulmonary phthisis, in typical cases, is developed so
imperceptibly that it might with propriety be included among the
so-called insidious diseases. A slight dry cough is the first local
symptom. This increases, and after a variable period is accompanied by
the expectoration of a small quantity of mucus. The latter becomes
gradually more abundant, and has the characters of the sputa in cases
of bronchitis. So slow is the increase of those symptoms before they
are regarded as of sufficient importance to require attention that not
infrequently the patient is unable to state precisely how long they
have existed. They are generally attributed to a slight cold which will
take care of itself or call for only popular remedies, and the
existence of a grave disease may not have been suspected until a
physical examination of the chest discloses the fact that the
phthisical affection has already made considerable progress. Coincident
with or preceding the commencement of cough is often some obvious
impairment of the general health, as indicated by diminished muscular
strength and endurance, decrease in weight, pallor of the complexion,
and lessened appetite. The impairment, however, may not interfere with
customary occupations, and may be evident to others when the patient
takes no cognizance of it.
In not a few instances hæmoptysis is the event which first awakens
suspicion of an important disease. The hemorrhage generally takes place
without any apparent causation, and often in the night. It may be
either slight or profuse. It may occur but once, or there may be
recurrences after intervals of hours, days, or weeks. The cough in some
cases dates from the occurrence of hæmoptysis. In other cases the
hemorrhage or hemorrhages antedate the cough for a variable period.
From the time when the symptoms and physical signs render the diagnosis
of the disease positive the history in different cases presents notable
variations. Comparatively, the course of the disease is continuously
progressive and rapid in cases of so-called galloping consumption. The
characteristics of the disease in these cases are—an unusual degree of
cough with abundant expectoration, rapid breathing, frequency of the
pulse, persistent pyrexia, chills or chilly sensations followed by
exacerbations of fever, profuse perspirations, anorexia, rapid
emaciation with decreasing muscular strength, and a fatal termination
after a few months. The physical signs in these cases show a large and
progressively increasing amount of solidification from the morbid
product, followed quickly by destructive changes.
The disease pursues a rapid course, and ends fatally whenever acute
tuberculosis supervenes. This may occur in the early part of the
chronic phthisical affection or at any period during its course. The
supervention of the acute disease sometimes follows a profuse
hæmoptysis. The characteristics are high fever, frequency of the pulse,
cyanosis, prostration, and death within a few weeks or even a few days.
The physical signs which denote a large
extent of solidification
of lung and the consequent destructive changes are wanting in these cases.
A small proportion only of cases of pulmonary phthisis fall in the
category either of galloping consumption or of the supervention of
acute tuberculosis. In by far the larger proportion the disease is
chronic from the beginning to the end, and a fatal termination takes
place after a period averaging from two to three years, the period
sometimes extending to many years.
An important distinction, as regards the history of the disease, is
expressed by the terms progressive and non-progressive. The disease is
progressive when the local and the general symptoms denote more or less
activity in the tuberculous process, the physical signs generally
showing progressive extension of the pulmonary affection. It is
non-progressive when symptoms and signs having the significance just
stated are wanting. The disease may become non-progressive early or
late, and at any period during its continuance. A stationary condition
may continue indefinitely. The symptoms and signs may show processes of
restoration—namely, disappearance of the tuberculous product,
diminution in size, and the cicatrization of cavities. The disease is
then said to be regressive. A regressive course is not extremely
infrequent. It is more or less slow and may or may not end in recovery.
A stationary condition, regression having taken place to a greater or
less extent, is not infrequently observed. This condition may remain
because the pulmonary lesions are too great to admit of restoration. In
most cases the disease is not steadily progressive. It ceases from time
to time to progress, the periods of non-progression varying much in
duration. With each renewal of progress the physical signs generally
show an addition to the tuberculous product. As a rule, this product
does not increase continuously, but, as it were, by successive
eruptions after intervals of time which may be either short or long.
Pulmonary phthisis in some cases ceases to progress, and regression
continues, recovery taking place from an intrinsic tendency—that is,
irrespective of any measures of treatment. This highly important fact
has not hitherto been distinctly recognized by medical writers and
practitioners. I have established it by having recorded a series of
cases in which recovery took place without medicinal or other treatment
and without any material change in habits of life.1 In these cases
the disease may be said with propriety to be self-limited.2 The
weight of this fact in its bearing on prognosis and treatment is
obvious. That non-progression and regression ending in recovery may be
brought about by judicious measures of management cannot be doubted; in
other words, the disease may be arrested in a certain proportion of
cases when non-progression and recovery would not have resulted from an
intrinsic tendency or self-limitation.
1 Phthisis, in a Series of Clinical Studies, by Austin
Flint, M.D., 1875.
2 Vide "Self-limitation in Cases of Phthisis," by Austin
Flint, M.D., N.Y., Archives of Medicine, June, 1879.
Pulmonary phthisis proves fatal by undermining more or less slowly the
powers of life. The appetite and digestion fail. There is progressive
loss of weight and of muscular strength. A greater or less degree of
pyrexia is persistent, with diurnal exacerbations and night
perspirations, forming what is known as hectic fever. Muco-purulent
matter is expectorated in abundance, with fatiguing cough. The
respirations are accelerated, and there is often suffering from
dyspnoea. The pulse becomes more and more frequent and weak. Oedema of
the lower limbs is of frequent occurrence. The patient dies by slow
asthenia, the mental faculties usually remaining intact and the patient
hopeful of recovery to the last.
The history of the disease in many cases embraces tuberculous
affections elsewhere than in the lungs, and other complications. The
duration is often
shortened by some of these. The more important
are tuberculosis of the intestines, tuberculous peritonitis,
perforation of lung giving rise to pneumo-hydrothorax, pneumorrhagia,
pulmonary gangrene, tuberculous meningitis, and chronic laryngitis
affecting deglutition. The less important affections are pleurisy with
effusion, thrombosis of the femoral or the iliac vein, a circumscribed
non-tuberculous acute pneumonia, chronic laryngitis not affecting
deglutition, intercostal neuralgia, and perineal fistula. Profuse
hæmoptysis is sometimes a grave event, and may prove the immediate
cause of death.
It is impossible to divide the course of pulmonary phthisis into
sharply-defined stages based on anatomical changes. Often after death
the lungs present in different situations all the changes which
intervene between a fresh tuberculous product and cavities. The
division into a stage of crudity of the product and a stage of
softening is of no practical utility. There are no symptoms nor signs
which are reliable for determining when softening has taken place. The
existence of cavities can generally be determined by means of the
cavernous physical signs, and the disease may be considered as advanced
phthisis when cavities are discovered. The term incipient phthisis is
used to designate an early period of the disease. Having passed the
incipient or early period, and before reaching the advanced stage or
stage of excavation, cases may be conveniently grouped according to the
amount of the tuberculous affection. In different cases and at
different periods in the same case the affection is either small,
moderate, considerable, or large. Exact chronological divisions are impracticable.
ETIOLOGY.—Pulmonary phthisis, as a rule, is developed irrespective of
any antecedent affection of the lungs. The researches of Louis
established the fact that the phthisical affection is very rarely
preceded by bronchitis, either acute or chronic.3 My clinical studies
have led to the same result.4 That a neglected cold may eventuate in
phthisis is a traditional popular error, unfortunately held also by
some medical writers and practitioners. The error is to be regretted
because it often interferes with hygienic management in cases of
phthisis. The name chronic catarrhal phthisis proposed by Niemeyer was
based upon this etiological error. It is a matter of common clinical
observation that persistent bronchial inflammation leading to pulmonary
emphysema, and often accompanied by asthma, involves no liability to
phthisis. The long-continued inhalation of coal- and stone-dust, of the
oxide of iron, and particles of other substances gives rise to
bronchitis and interstitial pneumonia (pneumonokoniosis, anthracosis,
siderosis, etc.), but is rarely followed by the common form of
pulmonary phthisis. It is common for phthisical patients to suppose, as
a matter of course, that their disease originated in a cold. In giving
the previous history they often say that they took cold at a certain
time. The analysis of carefully-recorded cases shows that very rarely
does the disease follow directly upon an attack of bronchitis,
notwithstanding that the frequency of the latter, from the law of
chances, would involve an accidental concurrence in a certain
proportion of cases. Acute lobar pneumonia or pneumonic fever has
little or no tendency to eventuate in phthisis. This statement is
sustained by the researches of Louis and by my clinical studies. In the
rare instances in which phthisis follows either acute pneumonia or
bronchitis, the latter diseases act only as auxiliary causes of the
phthisical affection if the sequence be more than an accidental
connection. This statement applies also to pleurisy with effusion. In
certain of the few instances of phthisis apparently having been
preceded by pleurisy it is probable that the former was the antecedent
disease, occurring early in the history of the phthisical affection and
retarding or arresting the progress of the latter. It may be added that
there is no ground for supposing that phthisis is ever produced solely
by traumatic causes acting upon the chest.
3 Recherches sur la Phthisie, 1825.
4 Phthisis, in a Series of Clinical Studies.
It is an old doctrine that bronchial hemorrhage may be causative
of phthisis. This doctrine has been recently revived by Niemeyer and
some others. It is disproved by the following clinical facts: in
two-thirds of the cases in which hæmoptysis antedates phthisis the
development of the latter is after the lapse of a considerable
period—weeks, months, or years. The instances are few in which
phthisis immediately follows the hemorrhage. The occurrence of
hæmoptysis during the course of phthisis, as a rule, is not followed by
any increase of the phthisical affection. On the contrary, the local
symptoms are not infrequently relieved by the hemorrhage. It is,
however, to be remarked that hæmoptysis as a forerunner of phthisis is
of much significance. In the larger proportion of cases phthisis
follows its occurrence sooner or later. It is to be added, in view of
the recent discovery by Koch, that bronchial hemorrhage may proceed
from the same local cause which afterward leads to the development of
phthisis—namely, the presence of a special micro-organism.
The etiology of pulmonary phthisis not involving any antecedent
affections of the lungs nor any appreciable local causes, it would seem
to follow that the disease involves either a predisposing or a
causative agency elsewhere within the organism; and as, with our
present knowledge, the source of this intrinsic agency cannot be
localized, it is customary to say that the disease has a constitutional
origin. This use of the term constitutional here, as in other
instances, expresses an important fact—namely, that the disease is not
purely local; that is, attributable solely to extrinsic or any
appreciable causes acting on the affected part. At the same time, the
term is a confession of the imperfection of our knowledge, inasmuch as
it does not specify the nature of the causative or predisposing agency,
nor its origin, beyond the statement that it is not local. That the
constitutional agency has a special character is a logical inference
from the fact that the disease may be said to have such a character.
The term vulnerability does not fully express the special character of
the constitutional agency. The condition of the constitution which
stands in a causative relation to the disease is something more than an
undue susceptibility to morbific influences of any kind—a
susceptibility giving rise to diseases the nature and seat of which are
accidental. The condition is one which has relation both to the
character and the situation of the pulmonary affection. Such a
condition is expressed by the term cachexia.
It remains to inquire whence arises this phthisical or tuberculous
cachexia.
A congenital predisposition or diathesis exists in a certain proportion
of cases. This is to be inferred from the number of instances in which
several or many members of a household, brothers and sisters, become
affected with phthisis. There may or may not be evidence that this
predisposition is inherited. An inherited predisposition is to be
inferred from the number of the cases in which parents or grandparents
were phthisical. While statistical facts show undoubtedly heredity as
involving a causative agency, making due allowance for the law of
chances, it is important for the physician to bear in mind that a
tuberculous parentage involves only a certain measure of liability to
phthisis in the offspring. The progenitors of many healthy men and
women have been phthisical. There are instances of large families of
children in which many have died with phthisis, leaving, however, some
who escape this disease and are in all respects healthy.5 The
question arises whether in cases of phthisis where there is lack of
evidence of a congenital predisposition the diathesis may not be
innate. The affirmative answer seems probable in view of the inability
oftentimes to find any rational explanation on the supposition that the
diathesis has been acquired. Positive data bearing on this question are
of course not available.
5 For data on which these statements are based, vide
Phthisis, in a Series of Clinical Studies, by the author.
Age has a decided influence on the development of phthisis. Cases
in which the ages of patients are between twenty and thirty years
greatly preponderate over the number in any other decade of life. Next
in order as to the number of cases are the ages between thirty and
forty years. The form of tuberculous disease under present
consideration is rare under ten years and also in advanced life. All
that can be said with our present knowledge in explanation of the
influence of age is, that either an existing diathetic condition tends
intrinsically to the development of the disease or that the diathesis
is likely to be acquired at certain periods of life more than at other
periods. Of these two explanations the former is the more rational.
Statistics show that occupations which involve sedentary habits,
confinement within doors, especially in small, illy-ventilated rooms,
poor or insufficient food, and prolonged mental depression, increase
the liability to phthisis. The disease is developed either during or
shortly after gestation in a sufficient number of cases to show that
pregnancy has a causative agency. Facts appear to show a less degree of
prevalence of the disease in most cold and tropical climates than
within the temperate zone. It is, however, true, as stated by Ruehle,
that "there are regions in all zones which are free from the disease,
and, on the other hand, there is no zone in which it is not very
prevalent." The prevalence is less in high than in low altitudes.
Humidity of the soil has been shown by Bowditch, Buchanan, and others
to enter into the etiology. In order to determine how far purely
climatic agencies exert an influence either for or against the
prevalence of the disease, it is necessary to take into account other
associated agencies, together with an innate predisposition; and the
latter especially does not admit an exact estimation.
Certain general diseases seem to involve a liability to phthisis as a
sequel. This is true of rubeola and pertussis. In cases of diabetes
mellitus, phthisis is considered as occurring sufficiently often to
show a causative connection. In my own clinical experience, however,
phthisis has not been of frequent occurrence in that disease. Typhoid
fever in some cases appears to favor the development of phthisis. Some,
however, have contended for the reverse of this statement. Certain
affections are apparently antagonistic in their influence. In this
category are pulmonary emphysema and obstructive or regurgitant
valvular lesions at the mitral orifice of the heart. The disease is
rarely developed in chlorotic patients. Facts go to show that
alcoholism opposes its development. In opposition to current belief, my
clinical studies lead me to conclude that they who have had scrofulous
disease of the cervical glands in early life are not likely to become
phthisical in after years. Contraction of the chest from deformity
diminishes the liability to the disease.
The communicability of phthisis is a doctrine dating as far backward as
the history of medicine extends. Distinguished physicians in every age
have held that the disease may be communicated under circumstances
which involve close proximity, as from husband to wife or vice versâ,
and from patients to nurses or attendants. The contagion is supposed to
be contained in the expired breath. The clinical evidence in behalf of
this doctrine is the number of instances which seem to be striking
examples of communicability. It is easy to collect a considerable
number of such examples. But in order to constitute clinical proof of
the doctrine of communicability the number must be so large as not to
be accounted for on the ground of mere coincidence. A collection of
isolated instances gathered from medical literature or reports from
different physicians does not establish the doctrine. Owing to the
great frequency of phthisis, mere coincidence suffices to account for a
certain number of instances. Moreover, long-continued proximity to
cases of phthisis generally involves causative agencies other than a
contagium—namely, confinement within doors and mental anxiety. In my
collection of 670 recorded cases of phthisis, the number of instances
in which there was
room for the suspicion of the disease having
been communicated either from the husband to the wife or from the wife
to the husband amounted only to 5. In one of these instances, a wife,
who became phthisical after her husband, had lost two sisters, one of
whom was a twin sister, by the disease. It must be admitted that the
analysis of these cases, without disproving the doctrine of
communicability, fails to lend to it support, for the reason that in
such a large collection of cases the number of examples of apparent
communicability are so few.
A new and strong impetus was given to the discussion of the doctrine by
the discovery of the inoculability of tuberculous disease. Villemin in
1865 demonstrated the fact that this disease could be communicated to
rabbits and guinea-pigs by inserting beneath the skin portions of the
tuberculous product. The experiments of Villemin and many others have
shown conclusively that the insertion of fresh undecomposed tuberculous
matter beneath the skin or within the pleural and the peritoneal
cavity, or in the anterior chamber of the eye, is followed by an
eruption of tubercles in these animals within two or three weeks. If
tuberculous matter taken from an animal in which the disease has been
produced by inoculation be inserted in another animal, the disease is
transmitted to the latter. These results of inoculation, which have
been abundantly confirmed in all countries, prove indisputably the
communicability, by that mode, of tuberculous disease in certain
animals which have a peculiar susceptibility thereto. The fact that the
disease is not readily communicated to dogs, cats, and other animals
shows a peculiar susceptibility to be an important factor in the
successful results of inoculation. The conclusion drawn by Villemin and
others from these experiments is that the disease is communicated by
means of a specific virus, a term implying the existence of a contagium.
Opposed to this conclusion are experiments which appear to prove that
tubercles may be produced in rabbits by inoculating them with various
kinds of non-tuberculous matter. By those who adopt the doctrine of a
specific virus it is contended either that true tubercles are not
produced in these experiments, or that, if followed by the development
of true tubercles, the production of the latter is attributable to the
derivation of the virus from the laboratories in which tuberculous
animals had been confined or to a contagium received directly from
these animals. The introduction of non-tuberculous matter was found by
Cohnheim and Fraenkel never to be followed by tuberculous disease when
the experiments were repeated in places where tuberculous animals had
not been confined and the animals on whom the experiments were made
were isolated from those affected with tuberculosis. Cohnheim states
that inoculation with portions of indurated lung, or of the nodules
resulting from peribronchitis, or of the contents of bronchiectasic
cavities, will not give rise to true tubercles, for the reason that,
although taken from phthisical lungs, they do not contain the
tuberculous virus. This distinguished pathologist, at first an opponent
of the doctrine of a specific virus, afterward became a strong advocate
therefor. He was led to regard a successful inoculation as affording
the only criterion and reliable test of tuberculous disease; that the
etiology of tuberculous disease invariably involves the presence in the
system of this virus; that it exists in a latent form whenever there is
an innate predisposition to phthisis; and that it may enter the system
in different directions—namely, with the inspired air into the lungs,
and even within the skull through the foramen of the ethmoid bone, into
the small intestine by deglutition, and into the uterus with the semen.
Becoming developed in any situation, the virus may remain localized, or
it may be disseminated more or less extensively by means of the lymph
and blood. The behavior of the tuberculous virus, according to
Cohnheim, corresponds closely to that of syphilis.
Experiments made by Gerlach, Bollinger, Aufrecht, Chaveau, Leisering,
Harms, Gunthern and others, have shown that the disease may be
communicated by incorporating tuberculous matter with food. Rabbits,
guinea-pigs, dogs, calves, swine, sheep, and goats have been rendered
tuberculous by these experiments. Klebs, Tappeiner, Parrot, and Puech
claim to have communicated the disease by combining with the food the
matter of expectoration from phthisical patients. Gerlach and Klebs
have seen the disease in animals fed with milk from cows affected with
the so-called pearl disease (perlsucht), which is considered to be
identical with phthisis. Finally, the disease appears to have been
produced by exposing animals to an atmosphere impregnated with fine
particles of tuberculous matter by means of an atomizer, and by blowing
into the trachea this matter reduced to a fine powder.6
6 For a summary of the experiments relating to the
communicability of tuberculous disease by inoculation, by the ingestion
of tuberculous matter, and by its inhalation, and for reference, the
reader is referred to an article by Wm. P. Whitney in the Boston
Medical and Surgical Journal, July 28, 1881; to the article on
"Tuberculosis" by Frederick C. Shattuck in supplement to Ziemssen's
Cyclopædia of the Practice of Medicine, 1881; to the "Cartwright
Lectures," by William T. Belfield, M.D., published in the New York
Medical Record in February and March, 1883; and to an article by
Surgeon George M. Stemberg, U. S. Army, in the American Journal of
Medical Sciences, January, 1885.
It is noteworthy that tuberculous disease may be produced by
inoculating with the infiltrated product, with matter from miliary
tubercles, or from scrofulous glands in the neck. The identity of these
morbid products is thus made evident, assuming that the fact of
communicability involves the existence of a specific virus.
The practical importance of the facts already ascertained respecting
the communicability of phthisis is obvious. They constitute the
foundation for a reasonable supposition that the disease may be
communicated to man by means of the meat of tuberculous animals, by
milk, and by breathing an atmosphere charged with particles of
tubercle. That the instances in which the disease is communicated,
however, are rare seems to be a rational inference from the difficulty
of obtaining clinical proof of communicability. That susceptibility is
an essential factor is made evident by the well-known predisposition
pertaining to certain periods of life. It is to be considered that
while the communicability of the disease to certain animals is
abundantly shown by the experiments to which reference has been made,
the existence of a special virus or a contagium is not as certainly
established by these experiments. They leave to be settled, by further
investigation, the question whether or not the communicability of the
disease involves only the agency of a septic matter devoid of the
special character expressed by the terms virus and contagium. Without
waiting for data sufficient to settle this important question, prudence
would dictate the propriety of all practicable precautionary measures.
Still more recently, and since the foregoing remarks on the
communicability of phthisis were written, have appeared the remarkable
experimental researches of Koch of Berlin. Koch claims to have
demonstrated the constant presence in tuberculous products of a
specific organism which he calls the bacillus tuberculosis, and that it
is not found in non-tuberculous products. This parasite he has
isolated, and by cultivation carried through several successive
generations. By its introduction, after, as well as before,
cultivation, into the pleural cavity, the peritoneal cavity, the
anterior chamber of the eye, and in other situations, he produced
tuberculous disease, not only in rabbits and guinea-pigs, but in dogs
and rats, the latter animals being less susceptible than the former to
tuberculous infection. In his experimental observations, animals not
inoculated, placed under the same external conditions as those
inoculated, did not become tuberculous. The same parasite, alike
capable of infecting healthy animals, he found in miliary tubercles, in
the cheesy tuberculous deposit, in scrofulous glands, and in the sputa
from
tuberculous patients. The parasite was found not to have
lost its vitality in dried sputa.7
7 For the details of Koch's researches vide his report in
the Berliner klinische Wochenschrift, April 10, 1882; vide, also,
Verhandlungen des Congresses für Innere Medicin, Erster Congress
gehalten zu Weisbaden, 20–22 April, 1882.
The researches of Koch had been continued for two years before the
publication of the results in March, 1882. Moreover, his ability as a
skilled experimental observer in the study of micro-organisms, and his
sincerity as a truth-seeker, are universally admitted. Naturally, the
publication of the results of his researches excited at once great
interest in all countries. At the present moment (April, 1885)
questions connected with the bacillus tuberculosis are more considered
than any others relating to medical pathology and etiology. Thus far,
the observations of competent medical mycologists are confirmatory of
the results of the researches by Koch. It seems to be established that
the so-called bacillus tuberculosis is uniformly present in tuberculous
products, and as uniformly absent in other morbid products; that it is
generally present in the sputa of phthisical patients, and never
present in the sputa of non-phthisical patients; and that tuberculous
disease in animals may be produced by inoculation with this organism
after cultivation has been sufficiently continued to eliminate all else
pertaining to the tuberculous product. On these data are based the
conclusions that phthisis is an infectious disease—in other words,
that it involves in its causation a specific agent capable of
self-multiplication; that it is a communicable disease, and that the
agent of the communication is the bacillus tuberculosis—that is, this
agent is the contagium. The supposition that the presence of the
bacillus is secondary to the tuberculous affection is not tenable in
view of the fact that the affection is produced by the introduction of
this organism after it has passed through several generations by
culture out of the body.
As has been already seen, clinical experience fails to furnish positive
proof of the communicability of phthisis. There are many striking
instances which, taken by themselves, render it probable that the
disease was communicated; but, on the other hand, there are so many
cases of its development under circumstances not pointing to contagion,
and of the number of persons in close proximity to tuberculous patients
the proportion of those who become affected is so small, that it has
seemed impossible to establish the doctrine of contagion by clinical evidence.
The insufficiency of clinical proof, however, cannot invalidate the
demonstration by inoculation. Assuming it to be demonstrated that the
disease involves a specific agent, and that this agent is proven to be
a contagium by its capability of producing the disease when introduced
into a healthy body, the conclusion as to communicability is not to be
shaken by the lack of corroborative clinical evidence or by inability
to explain certain facts which seem to be inconsistent with that
conclusion. Having accepted a demonstrated truth, the endeavor should
be to reconcile therewith facts which do not sustain it and which may
appear to be opposed to it. It remains to inquire in what way the
communicability of phthisis by means of a contagium vivum is to be
reconciled with facts furnished by clinical experience.
If we accept the conclusion that a particular parasitical organism is
the primary and efficient causative agent in the production of
phthisis, the development and multiplication of this organism must
require certain local conditions. Without these the parasite is
innocuous. The conditions are to its development and multiplication
what the peculiarities of soil are to the production of different
vegetables. Of the nature of these conditions we are at present
ignorant. When they exist the bacillus develops and multiplies; when
they are wanting the parasite is incapable of development and
multiplication. This dependence of specific morbific agents upon
particular
conditions is exemplified in other infectious
diseases. For example, the contagium of the eruptive fevers, received
into the system ever so abundantly, is inoperative in some persons,
and, as a rule with rare exceptions, it is never operative after the
disease which it occasions has been once experienced. In these
instances it is not the contagium itself which has lost the capability
of producing the disease, but the conditions for its activity are
wanting. Of the nature of these conditions we know as little as of
those which are essential to the development and multiplication of the
bacillus tuberculosis. The inoculation of animals with tuberculous
matter shows that the disease is produced in some species of animals
much more readily than in other species, and some animals of the same
species much more than others are susceptible to this contagium. These
facts are to be explained by variations in different species of
animals, and in different animals of the same species, as regards the
conditions required for the efficiency of the morbific agent.
The facts in the clinical history of phthisis which denote a
constitutional predisposition thereto or a tuberculous cachexia are
explicable by reference to the conditions requisite for the development
and multiplication of the parasite. A predisposition which may be
innate, inherited, or acquired involves the existence of these
conditions. The latter may be greater or less in degree. The causative
agencies of confinement within doors, humidity of soil, pregnancy, etc.
operate by either giving rise to or increasing these conditions. If
this view be correct, it is evident that the curative influence of
climatic changes, alteration of the habits of life, and other hygienic
agencies must be by means of an effect exerted upon these conditions;
and probably it is in this way chiefly that remedies are useful. Of the
essential nature of these conditions we know neither more nor less than
of what consists the tuberculous cachexia. We are, of course, as
ignorant of the one as of the other if it be assumed that they are
identical—that, in other words, the different expressions have the
same meaning. The only difference is this: If phthisis be an infectious
and a communicable disease, a contagium enters into its etiology;
whereas if the existence of a contagium be denied, it follows that the
cachexia is itself sufficient for the causation of the disease.
In connection with the etiology of phthisis a theory which of late
years has found favor with many should be referred to. It is, that this
disease may be a result of the absorption of caseated non-tuberculous
morbid products in different parts of the body. This theory of
autochthonous infection derives but little support from clinical
observation. In much the larger proportion of the cases of phthisis it
is impossible to discover anywhere caseated morbid products which may
be supposed to have a causative connection with the disease. To assume
that, when not discovered, foci of infection nevertheless are concealed
somewhere within the organism is evidently begging the question. On the
other hand, how often do suppurations, necroses, and degenerated morbid
products occur in different situations without being followed by phthisis!
SYMPTOMATOLOGY AND COMPLICATIONS.—Giving under this head a fuller
account of the symptomatology and complications than has been already
given in sketching the history of the disease, it will be a convenient
arrangement to consider these topics in their relations to the
different anatomical systems of the body—namely, the respiratory,
circulatory (including temperature), hæmatopoietic, digestive, nervous,
and genito-urinary systems.
Symptoms, etc. referable to the Respiratory System.—The dry cough
which is the earliest pulmonary symptom in typical cases is to be
regarded as an effect of the local irritation caused by the presence of
the tuberculous product. This product, increasing and extending, gives
rise to circumscribed bronchitis which causes increase of cough with
expectoration. The expectoration represents this secondary bronchitis
prior to the occurrence of
ulceration, the escape of liquefied
tuberculous product, and the existence of cavities. The quantity and
the characters of the matter expectorated depend on the degree and the
extent of the bronchial inflammation, the latter depending on the
extent of the phthisical affection. Different cases present wide
variations in these respects. The frequency and severity of the cough
depend in a great measure on the quantity of the matter of
expectoration and its adhesiveness. The matter expectorated, at first
semi-transparent mucus, becomes muco-purulent, the characters
pertaining to mucus and pus being combined in varying proportions, as
in cases of chronic bronchitis. Nummular sputa—so called from the
resemblance in form to a coin when lying on a flat surface, the edges
often serrated—are considered as casts of small cavities formed by
dilated bronchi. A microscopical examination of the sputa may show
elastic yellow fibres. The presence of these is almost pathognomonic of
phthisis, and denotes either the process of ulceration or exfoliation
of tissue from within cavities.8 Liquefied tuberculous product
appears in the matter of expectoration as a puriform fluid. It
sometimes contains small semi-solid tuberculous masses. The lining
membrane of tuberculous cavities furnishes a veritable purulent matter
of expectoration. It is stated by Buhl that the presence of alveolar
epithelium in the sputa is distinctive of phthisis; hence the name
proposed by him, desquamative pneumonia. It is, however, stated by
Frischl that the alveolar epithelium is found in the matter
expectorated in cases of oedema and congestion of the lungs.9 There
is sometimes notable fetor of the matter of expectoration, due to
putrescent decomposition of the purulent contents of cavities or to
small sloughing portions of pulmonary tissue. The varieties of sputa
which have been mentioned may be accompanied by a serous liquid in more
or less abundance. Calcareous masses varying in size from a pin's head
to a pea are expectorated in some cases. I have known several hundred
to be expectorated in a single case. In the instances which have fallen
under my observation these pulmonary calculi have been expectorated
when the symptoms have denoted arrest and regression of the disease;
and it is consistent with this fact to regard them as obsolete
tubercles. They are not to be confounded with the small solid bodies
sometimes formed in the follicles of the tonsils, the latter consisting
of a sebaceous-like product, which is crushed, without crumbling, by
pressure, and emits a fetid odor. Since the discovery of the bacillus
tuberculosis by Koch microscopical examinations of sputa in a large
number of cases by different observers have shown that this parasite is
generally, but not invariably, present. Its abundance in the sputa
appears to correspond to the rapidity with which the tuberculous
affection is progressing, and examinations with reference to its
presence and its abundance are of much practical utility in diagnosis
and prognosis.
8 In order to discover the elastic fibres readily, Fenwick
advises as follows: "Prepare a solution of caustic soda, about twenty
grains to an ounce of distilled water. Collect all the patient has
expectorated in twelve or twenty-four hours, from ten at night to ten
the next morning being the best period. Pour this, previously mixed and
well shaken with an equal quantity of the soda solution, into a glass
beaker, and boil it over a gas or spirit-lamp, stirring it occasionally
with a glass rod. A test-tube does not warm as well as a beaker. As
soon as it boils pour it into a conical glass, and add four or five
times the amount of cold distilled water. If the mucus is still
gelatinous after boiling, you have either added too little soda or not
boiled it sufficiently. The cold water carries down to the bottom of
the glass any lung-tissues that may be present, where they form a
slight deposit in about a quarter of an hour; if no deposit is visible,
put the glass aside for two or three hours. Remove the deposit with a
dipping-tube, place it in a glass cell, cover it with a piece of thin
glass, and examine with a one-inch object-glass. The lung-structures
will be often found clinging to hairs and other foreign bodies present
in the sputa" (Guide to Medical Diagnosis).
9 Vide Niemeyer by Seitz, tenth ed.
Hæmoptysis occurs in a large proportion of the cases of pulmonary
phthisis.
It occurs much oftener in the early than in a later
period of the disease. As regards the number of attacks, their
duration, the intervals between them, and the amount of hemorrhage,
there are wide variations. Prior to the formation of cavities the
hemorrhage is from the bronchial tubes (bronchorrhagia). After cavities
are formed the blood comes from the interior of these. As a rule,
bronchial hemorrhage is not followed by the evidence of any increase of
the phthisical affection. Not infrequently a sense of relief follows.
The analytical study of a large collection of cases shows that the
occurrence of bronchial hemorrhage does not diminish, but apparently
increases, the chances of arrest and of tolerance of the disease. This
statement holds true with regard to cases in which the hemorrhage is
often repeated and profuse, as well as to those in which it is slight
and infrequent.10
10 Vide Phthisis, in a Series of Clinical Studies, by the
author.
Cavernous hemorrhage may be due to rupture or ulceration of
parenchymatous bands which traverse cavities, but often it is caused by
the bursting of small aneurisms in their walls. It may be so profuse as
to prove fatal. Cavities sometimes become filled with coagulated blood,
which, if life continue, becomes decomposed and gives rise to a
grumous, fetid matter of expectoration. Bronchial hemorrhage is
supposed to be caused by a circumscribed hyperæmia at the situation
where the blood escapes. In a case under my observation in which death
took place shortly after a profuse hæmoptysis, there was congestion
limited to the middle lobe of the right lung, and the bronchial tubes
in this situation contained bloody mucus, none being found elsewhere. A
circumscribed hyperæmia, however, must depend upon some local cause.
Probably in most instances this anterior local cause is the tuberculous
product. That the escape of blood involves a change in the coats of the
vessels from which it escapes is probable.
A rare event occurring in connection with hæmoptysis is the coagulation
within the bronchial tubes of fibrin which may be expectorated in the
form of casts of the tubes, analogous to those which characterize
fibrinous or plastic bronchitis. I have met with an instance, and also
with a case in which after death the bronchial tubes of an entire lobe
were found to be filled with solidified fibrin. The death in this
instance followed quickly a profuse hæmoptysis. There is not the danger
connected with the gradual disintegration and expectoration of the
coagulated fibrin which was surmised by Niemeyer.
The presence of the tuberculous product in the lungs and the processes
to which it gives rise, inclusive of the secondary bronchitis, occasion
no pain. Patients often strike the chest with violence, as affording to
them evidence that the organs are sound. But in most cases, from time
to time during the course of the disease, sharp stitch-like pains
occur. They are sometimes slight or moderately severe, but they may be
sufficiently intense to confine to the house or even to the bed. They
last, usually, but a few days, and recur at variable intervals. They
are referred generally to the upper part of the chest, often beneath
the scapula. Patients are apt to imagine that the pains are rheumatic.
They are symptomatic of successive, circumscribed, dry pleurisies,
which are very rarely wanting in cases of phthisis, leading to the
pleuritic adhesions constantly found after death. These pleurisies are
secondary to the phthisical affection, and recur at epochs when new
developments of the latter take place. There is no reason to suppose
that they contribute in any way to the increase of the phthisical
affection. On the other hand, they protect against one important event
at least—namely, perforation of lung, and, as consequent thereon,
pneumo-hydrothorax. In this point of view they are conservative. These
pleuritic pains are to be discriminated from those of intercostal
neuralgia. The neuralgic pains generally are situated lower, and the
diagnostic criterion of intercostal neuralgia is
available—namely, the tenderness on pressure in the intercostal spaces
near the median line in front, the axillary line, and the spinal column.
The respirations are more or less frequent in different cases and at
different periods in the same case according to the impairment of the
function of hæmatosis by the pulmonary affection and the increased
frequency of the heart's action. A sense of the want of breath as
implied in the term dyspnoea is, however, seldom sufficient to occasion
much suffering. Even when the respirations are considerably increased
in number it is rare for the patient to complain of the want of breath
when at rest. A degree of muscular weakness which prevents the patient
from freeing the bronchial tubes and cavities of morbid products may
give rise to distressing dyspnoea. A sudden increase in the frequency
of the respirations, with dyspnoea and cyanosis, when not attributable
to filling of the bronchial tubes nor to pneumothorax nor pleuritic
effusion, points to the development of miliary tubercles in
abundance—in other words, to the supervention of acute tuberculosis.
Important complications referable to the respiratory system are
laryngitis, non-tuberculous pneumonia, pleurisy with effusion,
perforation of lung with pneumo-hydrothorax, pneumorrhagia, and
pulmonary gangrene.
Dysphonia and aphonia, the voice being husky or hoarse and the whisper
stridulous, denote laryngitis. These diagnostic symptoms are never
wanting, and the laryngeal complication may be excluded if they be
absent; but the extent to which the larynx is affected is of course
determinable by means of the laryngoscope. The affection in some cases
extending to the epiglottis, paroxysms of cough and spasm of the
glottis are produced by the act of swallowing food and drinks. The
interference with deglutition may be so great as to restrict seriously
alimentation, and in this way may hasten a fatal termination of the
disease. In the majority of cases, however, deglutition is not
interfered with. There is very rarely laryngeal obstruction to
respiration. The affection involves little if any liability to the
supervention of acute laryngitis or oedema of the glottis.
In most cases the laryngitis occurs at a considerable period after the
commencement of the pulmonary affection, this period, in a proportion
of more than one-third, being from two to four years. In some instances
it seems to occur coincidently with, and in some to precede, the
pulmonary affection. In the latter instances it is probable that latent
tuberculous disease of the lungs preceded the laryngitis. The diversity
as regards the interval of time between the date of the pulmonary
affection and of the occurrence of the laryngitis, the apparent
coincidence in the occurrence of both in some instances, and the want
of any uniformity in different cases as regards the amount of pulmonary
disease and the stage of its progress when the laryngitis occurs,
render it a rational conclusion that laryngitis is not dependent on the
disease of the lungs, but that it proceeds from the same cause which
determines the latter.
Excluding the instances in which the laryngitis involves the epiglottis
and interferes with alimentation, clinical experience teaches that this
complication does not diminish the chances of arrest or recovery from
the pulmonary affection, and that it has no untoward influence on the
duration of the disease in the cases which sooner or later end
fatally.11 As a rule, in cases which recover the voice remains
permanently more or less affected.
11 Vide Phthisis, in a Series of Clinical Studies, by the
author.
Acute lobar pneumonia or pneumonic fever is sometimes an intercurrent
affection in cases of phthisis. The cases are so rare as to show
absence of any predisposition to that disease derived from the
phthisical affection. The pneumonia ends in recovery in a proportion of
cases sufficiently large to show that, as a rule, the prognosis is not
unfavorably influenced by phthisis, and, as a rule also, the course of
the latter is not influenced unfavorably by the
pneumonia. A
circumscribed pneumonia is an occasional complication of phthisis. Its
non-tuberculous character is shown by the rapidity and completeness of
the absorption of the intra-vesicular product. This circumscribed
pneumonia gives rise to physical signs which appear to denote a rapid
and considerable increase of the phthisical affection. The
disappearance within a short period of the added dulness on percussion,
bronchial respiration, and bronchophony, is the evidence that these
signs represent a circumscribed pneumonia occurring as a complication.
Pleurisy with serous effusion is not an infrequent complication at an
early period in the course of the disease. There is very little if any
liability to its occurrence at an advanced period, except as associated
with pneumothorax from perforation of lung. It is probably secondary in
certain of the cases in which the phthisical affection appears to
follow the pleurisy. The pleuritic effusion appears to retard the
progress of the phthisical affection. Clinical experience shows that
this complication, if it be unilateral, is not an untoward event. A
double pleurisy with effusion is evidence of the existence of phthisis.
Perforation of lung, giving rise to pleurisy with effusion and
pneumothorax, is an event which belongs, with some exceptions, to an
advanced period of the disease. The perforation is caused by rupture of
the wall of a cavity superficially situated where pleuritic adhesion
from circumscribed dry pleurisy had not taken place. In most instances
the occurrence of the perforation is quickly followed by acute pain and
orthopnoea, with notable disturbance of the circulation, fever, and
prostration, these symptoms being due to the sudden entrance of air
into the pleural sac, the development of acute inflammation, and rapid
serous effusion. The recognition of the pneumo-hydrothorax by means of
physical signs is easy. The suffering of the patient becomes less after
twenty-four or forty-eight hours. In the great majority of cases death
takes place within a short period; that is, within a few days or weeks.
The duration of life depends on the amount of phthisical disease,
together with the condition of the patient as regards strength, etc. In
some instances, the perforation taking place when the phthisical
affection is small and accompanied by favorable symptoms, the
pneumo-hydrothorax is tolerated for a long period. The accumulation of
liquid within the pleural sac sometimes causes the air to disappear,
and the pneumo-hydrothorax is converted into simple pleurisy with large effusion.
Pneumorrhagia and pulmonary gangrene are very rare complications of
pulmonary phthisis. The analytical study of nearly 700 recorded cases
furnished but a single example of each of these complications.
Symptoms and Complications referable to the Circulatory System,
including Temperature.—More or less acceleration of the pulse and
elevation of the temperature of the body belong to the clinical history
of pulmonary phthisis. It may be stated that the pulse and temperature
are never normal if the disease be progressive. A persistent normal
pulse and no elevation of temperature therefore denote arrest or
non-progression of the disease. It may also be stated that the
acceleration of the pulse and the increase of temperature form a good
criterion of the rapidity or otherwise of the progress of the
tuberculous disease, provided inflammatory complications be excluded.
The disease is progressing rapidly in proportion to the frequency of
the pulse and the increase of temperature.
If the disease be progressive daily exacerbations of fever take place.
They occur in the afternoon usually, and continue into the evening or
the nighttime, ending in perspiration which is more or less profuse.
The exacerbations are often, but not always, preceded by chilly
sensations, and sometimes by a well-pronounced chill which may be
accompanied by rigors. During the febrile exacerbations the cheeks
frequently present a circumscribed flush
and the eyes have a
glistening appearance. The term hectic fever has long been applied to
the febrile exacerbations which characterize progressive phthisis.
The febrile exacerbations sometimes occurring prior to the development
of marked pulmonary symptoms may be supposed to be malarial
manifestations. Recurring daily at or near the same hour, they may
simulate closely the paroxysms of intermittent fever. A differential
point is the existence of more or less fever between the exacerbations
in cases of phthisis, whereas after a paroxysm of intermittent fever
there is apyrexia. Another point is, the occurrence of exacerbations in
cases of phthisis is generally after mid-day, whereas in the majority
of cases of intermittent fever the paroxysms occur earlier. But of
course the existence of phthisis is to be ascertained by means of the
diagnostic symptoms and the physical signs. It is, however, to be borne
in mind that phthisis and intermittent fever may be associated.
The profuse night-sweating which is a source of great discomfort in
cases of phthisis has no fixed relation to the intensity of the fever
which precedes it. The fever may be high and very little perspiration
follow, and vice versâ.
Acceleration of the pulse and elevation of temperature may arise from
an inflammatory complication, such as pleurisy, pneumonia, or
peritonitis, and from the supervention of acute miliary tuberculosis.
To endeavor to explain the rationale of the acceleration of the pulse
and the rise of temperature would require the consideration of the
general pathology of the febrile state. The absorption of septic matter
is probably a factor, but is hardly sufficient for a full explanation,
and it would not be easy, with our existing knowledge, to explain the
modus operandi of this morbific agent. The difficulty here, however, is
not greater than in explaining the phenomena of fever when occurring in
other pathological conditions. Here, as in other instances, there is no
uniformity in the relative degree of acceleration of the pulse and the
increase of temperature. The latter may be high without a proportionate
disturbance of the circulation, and the reverse. Clinical experience
shows a connection between a persistent high temperature and the waste
of the body, and in proportion as the vital powers decrease the action
of the heart is enfeebled, and a notably small and weak pulse denotes
that death by asthenia is not far distant.
Thrombosis of the iliac vein on one side or on both sides is an
occasional event in cases of advanced phthisis (marantic thrombosis).
The effect is a considerable oedema of the lower limb or limbs. Oedema
of both lower limbs, however, occurs as an effect of feebleness of the
systemic circulation. If, as is sometimes observed, there be general
dropsy, it denotes a renal complication, which is generally the waxy
variety of chronic Bright's disease. Under these circumstances the
urine is found to be albuminous.
Symptoms and Complications referable to the Hæmatopoietic
System.—Pallor of the face is generally more or less marked from an
early period in the history of phthisis, and it becomes, as a rule,
more and more marked as the disease progresses. There is considerable
variation in this respect in different cases. Impoverishment of the
blood is in a great measure to be explained by the diminished ability
to ingest and assimilate food. It is not, however, in all cases
proportionate to defective alimentation, and therefore it is a fair
inference that the disease in some other unknown way interferes with
the blood-forming processes. Exceptionally, in some cases in which the
disease is progressing, pallor is wanting. The complexion sometimes
retains for a long time a rosy color. This is probably due to the
condition of the vessels, and is not evidence of a normal condition of
the blood. It is a noteworthy fact that notwithstanding the appearances
denoting anæmia in cases of phthisis the venous hum in the cervical
veins is, as a rule, wanting.
That the impoverishment of the blood is an effect of the disease, and
that
it does not contribute to the progress of the tuberculous
affection, may be inferred from the fact that anæmic patients are not
likely to become phthisical. This fact, which has already been stated,
is established by clinical observation. Nor do the diseases relating to
the hæmatopoietic system, anæmia being a prominent feature in
all—namely, leucocythæmia, Hodgkin's disease, pernicious anæmia, and
Addison's disease—involve any special liability to phthisis. Other
intercurrent affections occasion death in these diseases when it is not
due exclusively to the latter.
Symptoms and Complications referable to the Digestive System.—The
opinion has been held that the development of phthisis is preceded and
accompanied by appreciable disorder of the digestive system. This
opinion is not sustained by the analysis of carefully-recorded cases.
In many, and perhaps the majority of, cases at the time of the
commencement of the phthisical affection the appetite is not notably
impaired and the digestive functions appear to be well performed.
Sooner or later, however, the appetite fails. This symptom may be
marked when the food which can be taken does not occasion evidence of
indigestion. Different cases differ very much as regards the degree of
anorexia. It is marked in the cases in which there is notable increase
of temperature and acceleration of the pulse. It is often invincible;
that is, not only is the desire for food wanting, but there is a degree
of repugnance which renders it impossible for the patient to take it.
It is intelligible that in these cases emaciation and exhaustion must
be progressive. It is not more easy to give a pathological explanation
of anorexia as an effect of phthisis than when the symptom occurs in
connection with other diseases not involving either inflammation or any
ascertained structural affection of the digestive organs. The symptom
is probably connected with morbid changes within the gastro-intestinal
or peptic glands.
Vomiting is a rare symptom in cases of phthisis, except it be produced
sympathetically in paroxysms of coughing. As thus produced it is not
rare. It is of importance from its interference with alimentation.
Diarrhoea is a frequent symptom. It may be due either to intestinal
indigestion or to a subacute enteritis or colo-enteritis thereby
induced. A waxy or fatty affection of the liver may conduce to
diarrhoea by interference with the digestion of certain alimentary
principles. If, however, the diarrhoea be persistent, it points to
intestinal ulcerations. These are usually seated in the Peyerian and
solitary glands within the small intestine, but not infrequently they
are found after death in the large intestine, and in the small
intestine above the portion in which the Peyerian glands are situated.
The number and extent of the intestinal ulcers found after death do not
always correspond to the prominence of diarrhoea as a symptom. They
cannot be excluded by the fact that this symptom is not prominent. The
presence of pus and blood in the dejections is evidence of ulcerations.
If the ulcers be situated high up in the intestinal tract, the pus and
blood may have undergone changes which render them unrecognizable by
the naked eye, and the microscope is necessary to demonstrate their
presence. The diarrhoea is often accompanied by griping or colic-like
pains. In proportion as diarrhoea is prominent it contributes to
emaciation and exhaustion. These effects are expressed by the term
colliquative, which has long been applied by medical writers to
exhausting diarrhoea and perspirations occurring in cases of phthisis.
Peritonitis occurs in phthisis as an acute and as a chronic affection.
When acute, it is caused by intestinal perforation incident to
ulcerations; this is a rare accident. It is to be inferred whenever the
symptoms denote rapidly-developed acute peritoneal inflammation. The
peritoneal sac contains intestinal gas. Perforation is excluded if
percussion shows dulness or flatness over the site of the liver. The
normal hepatic dulness or flatness on percussion is always abolished if
the peritoneal cavity contains gas. A tympanitic resonance
over
the liver, on the other hand, is not evidence of the presence of gas
within the peritoneal cavity, inasmuch as this resonance may be
conducted from the transverse colon distended with gas. Peritonitis
from perforation is speedily fatal. In a chronic form the peritonitis
may be preceded by an eruption of miliary tubercles in this situation,
or the inflammation may have proceeded from intestinal ulcerations,
perforation not having taken place. The local symptoms of chronic
peritonitis are often not marked. The diagnosis is to be based on pain,
tenderness, muscular rigidity, and the signs denoting liquid within the
peritoneal sac. A chronic peritonitis may be associated with a small
pulmonary affection which may not actively progress, and under these
circumstances the peritoneal complication may be tolerated for a
considerable period.
Peritoneal fistula may be reckoned among the complications referable to
the digestive system. It occurs sufficiently often in cases of phthisis
to show some pathological connection. Analysis of cases in which it
occurs affords no evidence of its having an untoward influence on the
course of the phthisical disease. On the other hand, there is ground
for the opinion generally held that it either occasions or betokens
slowness in the progress of the pulmonary affection. It follows that it
is unwise to attempt to effect a cure by surgical interference. The
characteristic bacilli have been found in the matter derived from
peritoneal fistula, showing that this affection is tuberculous in character.
Symptoms and Complications referable to the Nervous System.—The
symptoms referable to the nervous system relate to the mind. The mental
faculties in most respects remain intact, except that in proportion to
the general feebleness there is diminished ability to continue their
exercise. The integrity of the intellect, with one exception, often
remains up to the last moment of life. A marked characteristic of the
disease, however, is a delusion in respect to improvement and recovery.
In spite of the progressive emaciation and debility, which are obvious
to every one, patients are apt to believe that their condition is
becoming more and more favorable and to feel confident of restoration
to health. Even medical men affected with phthisis manifest the same
delusive ideas. So strong is the determination in some cases to keep up
the delusion that the statements of patients in regard to their
symptoms cannot be relied upon. They are sometimes offended if the
physician feels it to be his duty to intimate danger. On the other
hand, when patients are convinced of the nature of the disease, and
that they have not long to live, as a rule they become quickly and
completely reconciled thereto. Perhaps there is no other chronic
disease in which the near approach of death is generally regarded with
greater complacency.
Cephalalgia, delirium, and coma are symptoms which are developed in a
few cases. They denote tuberculous meningitis. This is a very rare
complication in the adult. When it has given rise to the symptoms just
mentioned a speedy fatal termination is to be expected.
Symptoms and Complications referable to the Genito-urinary
System.—Tuberculous disease of the kidneys, testicles, ureters and the
prostate gland is sometimes secondary to pulmonary phthisis. The local
symptoms will depend on the situation and amount of the tuberculous
product, together with the destructive changes to which it gives rise.
The consideration of the anatomical conditions and the symptomatology
falls properly under the head of diseases of the genito-urinary system.
As already stated, the variety of chronic Bright's disease known as the
amyloid or waxy is an occasional complication in cases of phthisis. The
other varieties may coexist, but the coexistence is rare. There is no
tendency in phthisis to these affections, and, on the other hand, they
do not involve any predisposition to phthisis.
As regards functional disorders of the genito-urinary system,
there is nothing noteworthy which pertains to the urine. From the
readiness with which often phthisical patients of either sex enter into
the marital relation it may be inferred that the disease does not for a
considerable period extinguish the sexual instinct. By interrogating a
considerable number of patients Louis was led to conclude that in men
the disease has an erotic influence.12 Phthisical women do not
readily conceive, but pregnancy is not extremely infrequent. They may
give birth to healthy children. During the course of phthisis the
menses, as a rule, cease, but they continue in some cases up to a late
period in the history of the disease. When suspended early they may
return if the disease become non-progressive. That the cessation of the
menses has an unfavorable influence on the tuberculous affection is a
popular error. Nothing is gained by efforts to bring about their
return. Their cessation, however, is not a good omen, and their return
has a favorable significance.
12 Recherches sur la Phthisie.
MORBID ANATOMY AND PATHOLOGY.—In the definition of the common form of
pulmonary phthisis were embraced the leading anatomical characteristics
of the disease. For a full account of these, together with the changes
referable to peribronchitis, periarteritis, endoarteritis, secondary
pleuritis, and bronchitis, as well as for histological appearances, the
reader is referred to treatises on morbid anatomy. The practical
objects of this article will be fulfilled by stating the abnormal
physical conditions incident to the morbid changes in different cases
and at different periods in the same case, and by a statement of the
anatomical points involved in the general pathology. Knowledge of the
abnormal physical conditions is essential with reference to physical
signs and the diagnosis. It has also an important bearing on the
prognosis, and is not without importance in its relations to the treatment.
Certain anatomical facts may be premised, as follows: The pulmonary
affection begins at or near the apex of one lung in the vast majority
of cases; exceptionally it begins at the base of one lung. The
affection extends from the apex downward. The extension is not
continuous in respect of time, but a series of tuberculous deposits or
eruptions takes place at different epochs after variable intervals.
Hence it is that different sections of one lung may show all the
changes which intervene between a fresh deposit and tuberculous
cavities. As a rule, not long after the affection begins in one lung
the other lung is affected. This rule is so constant that, although
both lungs are not affected simultaneously, the affection may be said
with propriety to be bilateral. The constant occurrence of secondary
circumscribed pleurisies and bronchitis has been stated under the head
of Pulmonary Complications.
At an early period of the disease the marked changes appreciable by
physical signs usually consist of a few hardened patches or nodules
varying in size from that of a pea to that of a filbert, situated at or
near the apex of one lung. The physical signs are those of slight
solidification—namely, some dulness on percussion, increase of vocal
resonance, and broncho-vesicular respiration. The presence of the
morbid deposit causes circumscribed bronchitis affecting the smaller
tubes, and this complication may give rise to subcrepitant râles within
the area of the tuberculous affection. The disease may end with no
further increase or extension of the local affection, this termination
resulting either from self-limitation or from the agency of treatment.
Of this fact I have proof from cases not only studied during life, but
in which appearances were noted after death. The ending of the disease
and recovery after a small tuberculous deposit occur oftener than is
generally supposed.
An increase and an extension of the phthisical affection occasion
larger
areas and also a greater degree of solidification. As the
amount of increase and extension within a given period varies very much
in different cases, it follows that there is nothing like uniformity in
these respects. Generally, the solidified portions of the lung form
islands between which the tuberculous deposit is wanting. Between these
islands the lung not infrequently becomes emphysematous. This vicarious
emphysema explains the existence of a vesiculo-tympanitic resonance in
some cases notwithstanding the solidification. Exclusive of that sign,
as thus accounted for, the solidification causes a dulness on
percussion proportional in degree and extent to the solidified portion
of lung. The auscultatory signs of solidification are generally
present—namely, either bronchial or broncho-vesicular respiration, and
bronchophony or increased vocal resonance, according to the degree of
solidification. The existence of bronchitis over a larger extent is
represented by more abundant and coarser moist bronchial or bubbling
râles. These râles do not, as has been supposed, necessarily denote
that softening of the tuberculous deposit has taken place. Dry
circumscribed pleurisies occurring from time to time, even from the
very commencement of the phthisical affection, may give rise to a
pleuritic friction murmur. The escape of the liquefied tuberculous
deposit into the bronchial tubes by ulceration, added to the products
of the bronchial inflammation, occasions an increase of the bubbling
râles. Moreover, the liquefied tuberculous deposit is better suited for
the production of bubbling sounds than the products of bronchial
inflammation. Hence the abundance of the bubbling râles, taken in
connection with the characters of the matter of expectoration, is
evidence of the escape of liquefied tuberculous deposit.
If phthisis be progressive, the physical conditions already
enumerated—namely, solidification, liquid in the bronchial tubes,
pleuritic exudation—continue. They are present in both lungs.
Associated with these conditions are cavities. The cavities formed in
different cases differ greatly in size and number. They differ also as
regards the number and the size of the openings by which they
communicate with the bronchial tubes. The latter conditions are of
importance with reference to the free discharge of the contents of
cavities and the production of certain physical signs. Enumerating here
the cavernous signs, they are—tympanitic resonance within a
circumscribed space, frequently with amphoric or cracked-metal
intonation, cavernous and sometimes amphoric respiration, increased
vocal resonance, cavernous whisper, pectoriloquy in some instances,
and, as a rare sign, metallic tinkling. An accumulation of liquid
within a cavity which has free communication with the bronchial tubes
gives rise to the cavernous sign called gurgling. I have met with an
instance in which a loud splashing sound was produced within a cavity
synchronous with the impulse of the heart, and due to the agitation of
the cavity by the cardiac movements. Owing to the association of
cavities with solidified portions of lung, the latter varying greatly
in different cases in the extent and the degree of solidification, with
the cavernous signs are combined those which represent varying degrees
of solidification—namely, either dulness or flatness on percussion,
either bronchial or broncho-vesicular respiration, and either
bronchophony or increased vocal resonance.
In the physical conditions incident to pulmonary complications of
phthisis—namely, pleurisy with effusion, perforation of lung with
pneumo-hydrothorax—the reader is referred to the article on DISEASES
OF THE PLEURÆ.
With reference to the general pathology of phthisis, points relating to
the morbid anatomy are to be considered. There are two distinct
varieties of morbid product in cases of phthisis—namely, the miliary
granulations and the infiltrated deposit formerly distinguished as
crude tubercle. Laennec taught that these are only varieties of
essentially the same morbid product, the former being preliminary in
their occurrence to the latter. Following
Virchow, some late
writers have restricted the application of the term tubercle to the
miliary granulations, regarding the infiltrated deposit as a
non-tuberculous inflammatory product. Histological investigations have
failed to establish an essential distinction between the two varieties.
The fact that they are so constantly associated shows some close
pathological connection. Both varieties undergo the same degenerative
changes. Each is found by inoculation to produce tuberculous disease in
certain animals. Moreover, according to the late researches of Koch and
others, each contains the characteristic parasite, the bacillus
tuberculosis. In view of these considerations, the doctrine of Virchow,
advocated by Niemeyer and others, is not tenable, and, as already
stated under the head of the Definition and Classification of pulmonary
phthisis, the term tuberculous is properly applied to both varieties.
There is no such affection as a non-tuberculous pulmonary phthisis. The
terms pulmonary phthisis and pulmonary tuberculosis are now, as
heretofore, to be regarded as synonymous.
That the pathology of pulmonary phthisis involves a predisposition or a
tuberculous diathesis has been already shown by facts pertaining to the
etiology. It does not in the least invalidate this logical conclusion
that in the present state of our knowledge pathologists are unable to
explain this diathetic condition; that is to say, in what it consists.
Its recognition is not merely a matter of speculative or theoretical
interest; it has an important bearing upon a rational prophylaxis and
on the treatment of phthisis.
Up to a very recent date the opinion has generally been held by
pathologists that the local phthisical affection may be determined
entirely by a tuberculous cachexia—that the latter, in other words,
may produce the affection exclusive of any local extrinsic cause; and
the question has been much discussed whether or not at the outset the
phthisical affection is an inflammation. But if the parasitic doctrine
be accepted, a local causative agent derived from without—namely, the
bacillus tuberculosis—is essential, the predisposition or the cachexia
consisting of certain unknown conditions which are required for the
development and the multiplication of the parasite. According to this
doctrine, the extension of the local affection is due to invasions
successively of different portions of the lungs, and the development of
tuberculous disease in other situations is due to the migrations of
this parasite. Without the presence of the bacillus, no matter in how
great degree the required conditions may exist, phthisis will not occur.
Inflammatory processes, however, accompany and follow the development
of the tuberculous affection. Bronchitis, peribronchitis,
periarteritis, endoarteritis, interstitial pneumonia, and pleurisy are
terms which denote inflammation. To these are to be added ulceration
and suppuration within cavities. The infiltrated tuberculous deposit is
to be regarded as an inflammatory exudation. There is an intrinsic
propriety, therefore, in calling it a pneumonia. But the behavior of
this deposit differs widely from that of the exudation in lobar
pneumonia. In the latter affection it is readily absorbed and
disappears, leaving the pulmonary structure intact, whereas in phthisis
it is absorbed with difficulty, and in most cases leads to more or less
destruction of the pulmonary structure. For these reasons, irrespective
of histological points of difference, the term tuberculous should be
used to distinguish the exudative pneumonia which is characteristic of
phthisis. The term desquamative pneumonia was proposed by Buhl. The
so-called cheesy degeneration of the tuberculous products—a necrotic,
not an inflammatory, process—was considered by Laennec as a
distinctive mark of the products. This doctrine has been disproved.
Other morbid exudations and growths may undergo similar degenerative changes.
DIAGNOSIS.—It is evidently very desirable to recognize the existence
of phthisis at as early a period as possible with reference to the
adoption of
measures with a view to prevent the further
development and progress of the disease. It is also very desirable, if
practicable, to determine that phthisis does not exist; that is, by the
absence of diagnostic points to exclude it. Difficulty of diagnosis
relates almost exclusively to an early period when the phthisical
affection is small. The diagnostic points pertaining to the symptoms
and the physical signs in the incipiency of the disease therefore
especially claim attention.
A cough of more or less duration, which was at first slight and dry,
gradually increasing and accompanied by the expectoration of mucus,
should always excite a suspicion of phthisis, especially if the
patient's age be between twenty and thirty years. This is not the
history of a chronic primary bronchitis. A cough as just described
should never be considered as nervous or sympathetic without due
investigation. It should not be attributed to pharyngitis, although the
latter affection is found to exist. Want of breath on exercise is a
symptom pointing to something more than a bronchial or pharyngeal
affection. The import of these symptoms is still greater if, after the
commencement of the cough or from an earlier date, there has been
decrease in weight and strength. Their significance is much increased
by the occurrence of hæmoptysis. Hæmoptysis followed by a persistent
cough, and still more if cough preceded its occurrence, is always
presumptive evidence of a phthisical affection. Occurring without
having been preceded by cough, and when cough does not immediately
follow, it should suggest the probability of phthisis. In the larger
proportion of cases under these circumstances it is a forerunner of the
diagnostic symptoms and signs of the disease. In connection with the
cough a persistent increase of the temperature of the body is an
important diagnostic symptom. Chilly sensations and flashes of heat are
symptoms of some importance. Especially significant are pleuritic
stitch-pains referable to the upper part of the chest or beneath the
scapula, these being symptomatic of the circumscribed dry pleurisies
which may occur at an early period of the disease. Impaired appetite,
pallor of the face, and a tendency to perspire during sleep have much
significance taken in connection with the pulmonary and other symptoms.
A positive diagnosis must rest on physical signs, together with more or
less of the foregoing symptoms. The physical conditions which furnish
the diagnostic signs are solidification of a small portion or of small
portions of lung, usually at or near the apex, the presence of mucus in
the small-sized bronchial tubes, and perhaps fibrinous exudation on the
pleural surface within a circumscribed area corresponding to the
solidified portion or portions of lung. The signs furnished by these
conditions are slight dulness on percussion, a broncho-vesicular
(formerly called rude or harsh) respiration, some increase of vocal
resonance and of the whispered voice, subcrepitant râles, and perhaps a
grazing friction murmur. It may be important to consider the physical
signs of phthisis with some detail. Aside from their importance, a
reason for this is that terms by which some signs are designated are
not used in precisely the same sense by all medical writers.
A small phthisical affection gives rise to slight or moderate dulness
on percussion. In order to appreciate this sign if the dulness be
slight, attention should be paid to the pitch of the resonance as well
as to the lessened intensity of resonance. The pitch is always raised.
By attention to the latter character, in conjunction with the
diminution of intensity, a degree of dulness may be sometimes
appreciated which, without attention to the pitch, might not be
determinable.13 In determining abnormal dulness in the
infra-clavicular region on one side, the normal disparity between the
two sides of the chest
in this region must be taken into account.
The resonance at the right summit, as compared with that of the left
summit, is, normally, somewhat dull. Hence it is not as easy to make
out an abnormal dulness at the right as at the left summit. If the
relative abnormal dulness at the right summit be but slight, the
question is whether there be more than a normal disparity. This
question is rendered difficult by the fact that the degree of normal
disparity varies somewhat in different healthy persons. In cases of
doubt little reliance is to be placed on this sign alone, but it is to
be taken in connection with auscultatory signs.
13 The author was the first to indicate the fact that
dulness is always associated with elevation of pitch. Vide "Prize Essay
on Variations of Pitch in the Sounds obtained by Percussion and
Auscultation," Transactions of the American Medical Association,
1852.
With reference to the auscultatory signs in cases of phthisis, it is to
be premised that often, owing to the importance of studying the sounds
derived from a limited area and of localizing morbid conditions, the
use of the stethoscope is indispensable. It is impossible to meet all
the requirements of physical diagnosis by immediate auscultation. After
an experience of more than a quarter of a century the writer would
advise the binaural stethoscope in preference to any other. For the
benefit of those who are not practically familiar with this instrument,
it should be added that in order to appreciate its advantages, the
instrument, in the first place, must be properly constructed, and, in
the second place, some practice is necessary. A sound produced within
the instrument is at first an obstacle, but it is speedily overcome by
use.14
14 The dissatisfaction with the binaural stethoscope so
often comes from defects in its construction that it seems proper to
refer to Tiemann & Co., and to Ford & Co., of New York as reliable
makers of this instrument.
A small tuberculous solidification is represented by a
broncho-vesicular respiration. This sign was named and described by me
in 1856. The name takes the place of the terms rudeness, harshness, and
hardness—terms which are not only inadequate, but convey an erroneous
idea. Quoting from another work, the characters of the
broncho-vesicular respiration and its comprehensive signification are
as follows: "The sign represents the different degrees of
solidification of lung between an amount so slight as to occasion only
the smallest appreciable modification of the respiratory sounds, and an
amount so great as to approximate closely to the degree giving rise to
bronchial or tubular respiration. In other words, all the gradations of
respiratory modifications caused by incomplete or an inconsiderable
solidification are embraced under the name broncho-vesicular. The
gradations correspond to the amount of solidification; that is, they
show the solidification to be either very slight, moderate, or nearly
sufficient to be regarded as considerable or complete. The sign is
therefore important as evidence, first, of the existence of
solidification, and, second, of the degree of solidification. Analyzing
this sign, the most distinctive feature is the combination of the
vesicular and the tubular quality in the inspiratory sound. These two
qualities may be combined in variable proportions. The pitch of the
sound is raised in proportion as the tubular predominates over the
vesicular quality. The expiratory sound is more or less prolonged,
tubular in quality, and the pitch raised. The prolongation of this
sound, its tubular quality, and the raised pitch are proportionate to
the predominance of the tubular over the vesicular quality in the
inspiratory sound. If the solidification be slight, the characters of
the normal vesicular respiration predominate; that is, the inspiratory
sound has but a small proportion of the tubular quality, and is but
little raised in pitch, the expiratory sound being not much prolonged,
its tubularity not marked, the pitch not high. If, on the other hand,
the solidification be almost enough to give a bronchial respiration,
the inspiratory sound has only a little vesicular quality, the tubular
quality predominating, the pitch proportionately raised, and the
expiratory sound is prolonged, high, and tubular, nearly to the same
extent as in bronchial respiration. The less the solidification the
more the characters
of the normal vesicular respiration
predominate over those of the bronchial respiration; and, per contra,
the greater the solidification the more the characters of the bronchial
predominate over those of the normal vesicular respiration."15 By
means of the broncho-vesicular respiration a slight morbid
solidification may be recognized in one of the infra-clavicular regions
or over the scapula. Here, however, as with regard to percussion, an
allowance is to made on the right side for a normal disparity. The
respiratory sounds on the right side at the summit, as compared with
those at the left, have normally the characters more or less marked of
a broncho-vesicular respiration. These characters are more marked as
the stethoscope is brought toward the sternum. Hence a small
solidification of lung is more easily ascertained by auscultation at
the left than at the right summit.
15 Vide Manual of Auscultation and Percussion, by the
author; also, paper contained in the Transactions of the International
Medical Congress, London, 1882. The broncho-vesicular respiration was
called by Skoda indeterminate (unbestimmt), and this term is still used
by German writers. These sounds are not indeterminate if the characters
derived from pitch and quality be analytically studied; they are sounds
intermediate between the normal respiratory murmur and bronchial
respiration.
Not infrequently in cases of incipient phthisis the respiratory sounds
at the summit on the affected side are so weakened that their
characters cannot be studied. Weakness of the respiratory murmur in
these cases becomes a diagnostic sign taken in connection with other signs.
A small tuberculous deposit may increase the vocal resonance. But,
again, a normal disparity between the two sides must be allowed for.
The normal vocal resonance is always greater on the right side. If,
therefore, it be a question as to the existence of a small tuberculous
affection at the right summit, it is to be decided whether the
disparity be greater than normal. A small tuberculous deposit at the
apex of the left lung, on the other hand, may not increase the
resonance to an equality with that at the right summit.
Attention should be paid to the whispered voice, and, still again, the
two sides show a normal disparity. The sound heard with the whispered
voice, which may be distinguished as the normal bronchial whisper, is
louder on the right than on the left side, and somewhat higher in pitch
on the left side, at the summit of the chest. If at the right summit it
exceed the normal disparity, and the pitch be higher than at the left
summit, the sign may be distinguished as increased bronchial whisper,
and it denotes solidification. If, on the other hand, the sound at the
left summit be louder than that of the right summit, there is increased
bronchial whisper, representing the solidification at the apex of the
left lung.16
16 The different abnormal modifications of sounds produced
by the whispered voice were first named and described by the author.
Vide Manual of Auscultation and Percussion.
The normal points of disparity at the summit of the chest render the
diagnosis of incipient phthisis by means of alterations in the
resonance on percussion, the respiratory sounds, the vocal resonance,
and the whispered voice a problem in some cases of not a little
difficulty. In these cases an examination of the sputa for the presence
of the tuberculous parasite may furnish proof of the existence of the
disease. This proof may in some instances be obtained when the physical
signs, together with the symptoms, do not render the diagnosis
positive, and it may be sought for in order to corroborate the evidence
derived from other sources. The author can testify from considerable
experience to the value of an examination of sputa for bacilli in cases
in which the diagnosis is not rendered positive by other signs and by
symptoms. It must, however, be borne in mind that the absence of
bacilli in the sputa is not sufficient to exclude phthisis, especially
if but a single examination be made. In doubtful cases, if an
examination of the sputa be negative, the examination should be
repeated. The weight of evidence against the
existence of
phthisis is, of course, greater in proportion to the number of
examinations with negative results.17
17 The following method of staining the bacilli tuberculosis
in the sputum is essentially that recommended by Ehrlich in the
Deutsche medicinische Wochenschrift, Mai 6, 1882:
It is important that the sputum to be examined should be derived from
the lungs, and should not be solely that from the upper air-passages. A
small opaque particle from the sputum is to be pressed between two
cover-glasses, so that when these are drawn apart a thin film will
remain upon each. Each cover-glass, as soon as the film is dry, is to
be passed, with the preparation upward, rather rapidly three times
through the flame of a Bunsen's burner or of an alcohol lamp. The
preparation is now ready for staining.
A small quantity of water in a test-tube or flask is now shaken with an
excess of aniline oil (which need be only in small amount), and after a
few moments is filtered through moistened filter-paper. To the clear
filtrate thus obtained is to be added, drop by drop, a saturated
alcoholic solution of fuchsin (gentian-violet, methyl-violet, and
several other aniline colors may be substituted) until the fluid begins
to be opalescent, showing that it is saturated with the coloring agent.
In this manner an alkaline-aniline staining solution is prepared.
Into this staining solution the cover-glasses, having the dried films
of sputum prepared as above described, are dropped, preferably so that
they will float with the preparation downward. Here they remain from a
half hour to twenty-four hours. If taken out in a short time, the
fluid, at least for a time during the staining process, should be
heated moderately over a water-bath, and in any case the process of
staining is accelerated and rendered more certain by heating.
After removal from the staining fluid the cover-glass is washed for a
few moments in water, and is then dipped into a mixture of one part of
pure nitric acid (it should contain no nitrous acid) to about three or
four parts of water. Here it remains only a few moments, when it will
be found that the preparation has lost its color, although a part will
be restored by the subsequent washing in water, which should be done at
once. If the preparation has not been sufficiently decolorized, it may
be placed again in nitric acid, but it is not necessary or desirable
that it should remain there many minutes. The object of the nitric acid
is to extract the color from all but the tubercle bacilli.
The preparation may now be at once examined either in glycerin or
(after drying or after treatment with alcohol and oil of cloves) in
balsam. Ehrlich recommends, previous to this, a staining of the
background with some color other than that of the bacilli; thus, with
methyline blue if the organisms are stained red with fuchsin. This
staining of the background, however, is not necessary. While the ideal
method of studying the stained bacilli is by means of Leis's
oil-immersion lenses and Abbé's illuminating apparatus, they can
usually be seen readily enough with the high powers in ordinary use,
such as the one-fifth or one-sixth inch objectives of our American
microscope. After staining with fuchsin the bacilli appear as short
rods of a red color, frequently curved or bent.
The adventitious sounds which have been mentioned—namely, the
subcrepitant râle and the pleural friction murmur—sometimes afford
valuable aid in the diagnosis. Taken in connection with the direct
signs obtained by auscultation and percussion, these accessory signs
when present make the diagnosis positive: they are by no means
uniformly present, and therefore their absence is not proof against the
existence of a phthisical affection. To these accessory signs another
sign may be added—namely, an abnormal transmission of the heart-sounds
within one of the infra-clavicular regions. In the middle of this
region there is nearly an equal transmission of these sounds normally.
Comparing the two sides as regards the two sounds respectively, the
first sound is a little louder on the left, and the second sound a
little louder on the right side. Now, with a little solidification the
sounds may be better transmitted, so that they are abnormally loud on
the affected side.
A decision that there is no physical proof of phthisis must rest on the
absence of all the foregoing signs after repeated examinations of the chest.
It is not to be concluded that for a positive diagnosis of incipient
phthisis all or most of the foregoing diagnostic signs must be
recognized. They are not all present in all cases. Two or three of
these signs, and even a single one if well marked and associated with
diagnostic points pertaining to the symptoms and history, may suffice
for a positive diagnosis.
It is an interesting question how small a portion of solidification may
furnish signs sufficient for a diagnosis. I have the records of two
cases bearing
on this question. A patient came under my
observation at Bellevue Hospital in 1867. In the right infra-clavicular
region the respiration was abnormally broncho-vesicular, the vocal
resonance was increased, and there was increase of the bronchial
whisper within a small circumscribed space. On these signs was based
the diagnosis of a small tuberculous deposit. The case served to
illustrate the signs just named to classes for practical instruction in
auscultation and percussion. The patient, who was employed as a helper
in the apothecary's shop, died suddenly from taking by mistake an
overdose of the fluid extract of aconite. The autopsy showed at the
apex of the right lung a nodule of the size of a filbert, no
tuberculous deposit being elsewhere found.
A recent medical graduate, twenty-two years of age, had cough and two
attacks of hæmoptysis. His father and a sister had died with phthisis.
There was slight dulness on percussion on the summit of the chest on
the left side, with crepitation at both summits. These were the only
signs noted. This case was included among the cases of recovery
reported in my work on phthisis published in 1875. He enjoyed excellent
health and was notably vigorous for twenty-eight years. Death took
place in 1880 from disease of the heart and kidneys. The autopsy showed
at the apex of each lung a small indurated portion somewhat larger on
the left than on the right side. Elsewhere there was no appearance
denoting present or past pulmonary disease.
It is in only a small proportion of cases that, when patients first
come under medical observation, the phthisical affection is so small as
to render the diagnosis difficult. The tuberculous solidification is
generally sufficient to give rise to well-marked signs. The shrinkage
of the lung at the apex from interstitial growth and diminished
capability of expansion may have caused a small infra-clavicular
depression and restricted respiratory movements in this region. The
dulness on percussion is readily recognized. The characters of the
broncho-vesicular respiration are easily determined. The increase of
vocal resonance and increased bronchial whisper admit of no doubt. With
these signs, oftener than at an earlier period, are associated
accessory signs—namely, subcrepitant râles and bubbling in larger
tubes, pleuritic friction murmur, and undue transmission of the
heart-sounds.
At a somewhat later period, and sometimes even when cases are first
observed, the physical signs denote a still greater degree of
solidification. Infra-clavicular depression and restricted movements on
one side are marked. The respiration is bronchial and the voice
bronchophonic. There may be pectoriloquy with the bronchophonic
characters, showing that the speech is transmitted through solidified
lung.18
18 Bronchophony is to be understood as a sign distinct from
increased vocal resonance. In bronchophony the resonance may or may not
be increased. Intensity is not a character of this sign. Its
distinctive characters are concentration of the voice sound, nearness
to the ear, and elevation of pitch. The terms concentration and
nearness to the ear properly express what was intended by Laennec in
the words "la transmission évidente de la voix à travers le
stethoscope." Pectoriloquy is to be distinguished from bronchophony.
These two terms are sometimes confounded. Bronchophony is transmission
of the voice, pectoriloquy the transmission of speech—that is,
articulate words.
Exceptional cases are to be referred to in which over lung containing
solidified portions from tuberculous deposit dulness on percussion is
wanting. Not only is dulness wanting, but the resonance is greater than
normal. The resonance is altered in character. With an increase of
intensity the quality is in part tympanitic and the pitch is raised.
This is the sign described by me many years ago under the name
vesiculo-tympanitic resonance. The distinctive characters are those
just mentioned—namely, increase of intensity, the quality a
combination of the vesicular and the tympanitic, and more or less
elevation of pitch. The name vesiculo-tympanitic expresses these
characters. It is the sign of pulmonary emphysema. It denotes that
portions of
lung situated between islands of solidification have
become emphysematous. The emphysema is vicarious; that is,
supplementary to the shrinkage of the portions solidified, and, added
thereto, probably collapsed lobules. Were one to be governed by
percussion alone in the physical diagnosis, this sign would in some
cases mislead. The liability to error is avoided by taking due
cognizance of the associated signs furnished by auscultation.
In cases of advanced phthisis cavities are added to tuberculous
solidification. It is desirable to recognize the existence of these. In
most instances the signs which may be distinguished as cavernous
suffice for the recognition of cavities. The cavernous signs are
furnished by percussion and by auscultation of the respiration and of
the voice.
A purely tympanitic resonance within a circumscribed space points to a
cavity, but a tympanitic resonance with either an amphoric or a
cracked-metal intonation is more especially a cavernous sign. An
amphoric or a cracked-metal resonance over a cavity may often be
obtained by observing certain rules in percussion—namely, percussing
with a single and rather forcible blow, the mouth of the patient being
open and brought close to the ear. These signs may be rendered still
more distinct by means of the binaural stethoscope, the pectoral
extremity being close to the patient's opened mouth, an assistant
making the percussion. These cavernous signs are not present when
cavities contain much liquid or when communication with the bronchial
tubes is temporarily obstructed; hence the signs are sometimes present
and sometimes absent.
There is a distinctive cavernous respiratory sign. This assertion is
called for by the fact that the existence of the sign is not as yet
recognized by all medical writers. According to Laennec, the
respiratory sounds derived from cavities resemble the bronchial
respiration. From his description it would be impossible to distinguish
the former from the latter. Skoda considered the cavernous and the
bronchial respiration as absolutely identical; and this view is held by
German writers at the present time. Walshe indicated an essential
differential point pertaining to the inspiratory sound in cavernous
respiration—namely, its low pitch. The fact that in purely cavernous
respiration the pitch of the expiratory is lower than that of the
inspiratory sound was stated by me in 1852.19 The distinctive
characters of the cavernous respiratory sign as then indicated were as
follows: An inspiratory sound low in pitch and non-tubular in quality,
followed by an expiratory sound still lower in pitch and non-tubular.
The quality of the sound in inspiration and in expiration may be said
to be blowing, after the term soufflante used by Laennec, but applied
by him to a sound either bronchial or from a cavity, when the air seems
to be drawn from the ear of the auscultator.
19 Vide "Prize Essay."
Appreciating clearly the characters which are distinctive of cavernous
respiration, it is impossible to confound this sign with bronchial
respiration, both the inspiratory and the expiratory sound in the
latter sign being high in pitch and tubular in quality. This cavernous
sign approaches much nearer to the normal vesicular respiration. The
only distinction between these two signs is the presence of the
vesicular quality in the latter and its absence in the former. Hence,
the only liability to error is in confounding the two. This error can
only be committed when the respiratory murmur is so feeble that the
vesicular quality is not readily appreciable. In order to avoid the
error, the respiration should not be pronounced cavernous when the
sounds are quite weak, except there be present other correlative
cavernous signs.
Cavities are often situated in close proximity to lung solidified by
tuberculous deposit or interstitial pneumonia: cavernous respiration
and bronchial respiration are then in juxtaposition, and their
differential characters are
rendered very distinct by contrast.
Under these circumstances, however, the cavernous respiration is
sometimes modified by combination with the characters of the bronchial
respiration. Not infrequently a cavernous inspiration is joined to a
bronchial expiration, the more intense expiratory sound representing
adjacent solidification extending over the site of the cavity and
drowning the weaker cavernous expiration. In another mode of
combination the inspiratory sound is bronchial at the beginning and
cavernous at the end. Here the cavernous sound occurs a little later
than the bronchial, and the latter is supplanted by the former. This
variety of broncho-cavernous respiration has been recently described by
Seitz under the name metamorphosing respiratory murmur
(metamorphosirendes athmungs geräusch). In like manner, the characters
of the cavernous and of the normal vesicular respiration may be
combined. This combination may be expressed by the term
vesiculo-cavernous respiration.
The effect of a cavity upon vocal resonance is to increase its
intensity without giving rise to the characters distinctive of
bronchophony—namely, nearness to the ear, concentration, and elevation
of pitch. Increased vocal resonance, and not bronchophony, is therefore
a cavernous sign. If bronchophony be present over a cavity, it denotes
adjacent solidification of lung. With the vocal resonance more or less
increased the vocal fremitus appreciable on auscultation is often intensified.
A cavernous whisper has the characters of the expiratory sound in the
cavernous respiration; that is, it is low in pitch and blowing or
non-tubular in quality, being in contrast, as regards these characters,
with a high-pitched tubular sound in whispering bronchophony. The
latter sign is often found near a cavity, showing the proximity of
solidified lung.
Amphoric respiration, amphoric voice, and amphoric whisper are
pathognomonic signs of a cavity, provided pneumothorax be excluded. The
same is to be said of metallic tinkling, a very rare cavernous sign.
Gurgling within a circumscribed space is a cavernous sign of some
value. Pectoriloquy—that is, the transmission of articulated words—is
not, per se, a cavernous sign; that is to say, the speech may be
transmitted by solidified lung as well as through a cavity. This is
true alike of words spoken with the loud and with the whispered voice.
It is, however, easy to determine whether pectoriloquy be or be not due
to a cavity. If with the loud voice the transmitted speech be
unaccompanied by the characters of bronchophony, it denotes a cavity.
So, if transmitted whispered words be unaccompanied by the characters
of the bronchophonic whisper, they denote a cavity. On the other hand,
the transmission is by solidified lung if bronchophony and pectoriloquy
be conjoined in either the loud or the whispered voice.
The shrinkage of lung incident to the formation of tuberculous cavities
increases the depression apparent on inspection in the infra-clavicular
region. The site of a cavity is sometimes indicated by a circumscribed
bulging of intercostal spaces, within a localized area, on forced
expiration or an act of coughing. A sharply-defined circumscribed
depression corresponding to the area of a cavity is visible in some
cases. Another effect of shrinkage of lung is to uncover the aorta in
the second intercostal space on the right side, or the pulmonary artery
in a corresponding situation on the left side. The pulsation of these
arteries may then be perceived by the touch, and perhaps, also, by the
eye. This effect should not lead to the error of inferring the
existence of aneurism. Shrinkage of the upper lobe of the left lung may
cause considerable elevation of the heart, also enlarging considerably
the space within which is felt the cardiac impulse.
With a practical knowledge of the physical signs of which a concise
account has been given, it is practicable to determine, first, the
existence of phthisis in its incipiency when the tuberculous affection
is small; second, during the
progress of the disease to ascertain
the degree and the extent of the tuberculous solidification; and,
third, to recognize the existence of, and to localize, cavities.
Recapitulating the signs belonging to the foregoing phases of the
disease, in incipient phthisis they are slight dulness on percussion,
broncho-vesicular respiration approximating to the normal vesicular or
a respiratory murmur too weak for its characters to be studied, some
increase of vocal resonance, increased bronchial whisper, and, as
occasional accompanying signs, subcrepitant râles, pleuritic friction
murmur, and abnormal transmission of the heart-sounds, more or less of
these signs being limited to the summit of the chest on one side. After
further progress of the phthisical affection the signs are, dulness on
percussion more or less marked, either a broncho-vesicular respiration
approximating to the bronchial or a purely bronchial respiration,
either notable increase of vocal resonance or bronchophony, either
increase of the bronchial whisper or whispering bronchophony, and moist
bronchial or bubbling râles which may be either coarse or fine, or both
may be combined. After the affection has advanced to the formation of
cavities the cavernous signs are added to those of
solidification—namely, circumscribed tympanitic resonance on
percussion, cracked-metal and amphoric resonance, cavernous
respiration, cavernous whisper, increased vocal resonance and gurgling.
Pectoriloquy may be present before and after the formation of cavities;
in the former instance the transmission of speech being by solidified
lung, and in the latter through a cavity, the two modes of transmission
being easily differentiated by means of the characters associated with
the pectoriloquy.
An intercurrent pneumonia, not tuberculous, may lead to the error of
supposing the tuberculous affection to be much greater than it is.
Especially is there liability to this error if the patient have not
been under observation prior to the intercurrent pneumonia. The latter
may give rise to bronchial respiration and bronchophony, with notable
dulness on percussion over a considerable space. If the patient have
been under observation, the rapidity with which the solidification
denoted by these signs has been developed is a diagnostic point. A
notable diminution of the solidification within a few weeks or days is
evidence that it was due to an intercurrent pneumonia. The tuberculous
deposit is never absorbed with such rapidity. The following case may
serve as an illustration of this complication: A man aged thirty had
had for some time slight cough and want of breath on active exercise,
but he had kept about, actively engaged in business, until within a few
days of the date of my visit. He was then up and dressed, his chief
complaint being want of breath on any exertion. The physical signs gave
evidence of considerable solidification of the upper lobe of the right
lung. The question was, whether the solidification was due exclusively
to phthisis, or whether with this disease was associated an
intercurrent pneumonia. The question was settled definitively by an
examination of the chest six weeks afterward. At the time of this
examination the solidification had in a great measure disappeared;
there was only slight dulness on percussion, with increase of vocal
resonance and feeble respiratory murmur. Meanwhile, the symptoms had
denoted progressive improvement; the cough was now slight; he no longer
suffered from want of breath on exertion, and he had improved as
regards appetite, strength, etc. This patient consulted me seven years
and four months afterward. In the mean time he had considered himself
in fair health, but he had been subject to cough, and for the preceding
six months the cough had been persistent. There was now dulness at the
summit of the chest on the right side, with feeble broncho-vesicular
respiration, increase of vocal resonance, abnormal transmission of the
heart-sounds, and subcrepitant râles. He had held his weight and
strength, and his appetite and digestion were good.
An occasional event in cases of phthisis is obstruction of a
primary bronchus from the pressure of an enlarged bronchial gland. This
event may explain a degree of embarrassment of respiration out of
proportion to the changes which have taken place in the lungs. The
bronchial obstruction is shown by notable feebleness or by suppression
of the respiratory murmur on the side of the obstruction, and an
increase of the murmur on the other side of the chest. Obstruction of a
primary bronchus may prevent the appreciation of morbid respiratory
signs on the obstructed side.
During the progress of phthisis the symptoms concur with the physical
signs in showing the progressive inroads of the disease upon the
pulmonary organs. They show, more than the physical signs, the inroad
upon the powers of life. They also afford evidence, in conjunction with
the physical signs, of arrest of the disease. More reliance is to be
placed on the symptoms than on the signs in judging of the rapidity on
the one hand, or on the other hand of the slowness, of the progress of
the disease. In these several points of view the consideration of
symptoms comes more properly under the head of the prognosis.
The symptoms pertaining to complications of phthisis may be the first
to lead patients to consult a physician. Not infrequently advice is
sought for harshness or hoarseness of the voice, arising from chronic
laryngitis, the cough and other symptoms which preceded this affection
not having been regarded as of sufficient consequence to require
medical aid. It is to be borne in mind that chronic laryngitis, when
not of syphilitic origin, is generally secondary to phthisis. The chest
is therefore to be examined carefully with reference to the signs of
the latter.
Pleurisy with effusion may be a complication which the physician is
called upon to treat. A lung compressed by liquid which fills the
affected side of the chest cannot be interrogated by means of physical
signs. Under these circumstances subcrepitant râles may denote a
phthisical affection on the summit of the chest on the opposite side.
The existence of cough and expectoration prior to the pleurisy is
strong evidence of an antecedent phthisical affection. The occurrence
of hæmoptysis adds greatly to the evidence.
A tuberculous patient who has not been under any treatment may apply to
a surgeon to be relieved of the inconvenience of a perineal fistula.
Operative interference for this affection should never be resorted to
without a careful examination of the chest.
PROGNOSIS.—Whether pulmonary phthisis is ever a curable disease has
hitherto been a mooted question. Prior to the time of Laennec instances
of apparent cure were open to doubt on the score of diagnosis. Laennec
did not admit the probability of a cure before the formation of
cavities, but he gave the histories in a number of cases in which the
cicatrization of cavities had taken place.20 If by the term
curability be meant a complete restoration of the portions of lung
affected by tuberculous disease to the normal condition which existed
prior to the disease, the doctrine of Laennec is probably true. A
moderate or even a small phthisical affection leads to changes which
are permanent. There remains more or less impairment of the integrity
of the pulmonary organs. But if by the term be meant that all pulmonary
symptoms cease, that the patient has good general health, and that the
damage to the lungs is not sufficient to prevent an adequate
exercise of their functions, a cure may take place before as well as
after the formation of cavities. Accepting the latter sense of the term
curability, no one at the present time will deny the statement just
made—a fact which is due, at least in a measure, to the different
views in regard to the treatment of phthisis now as compared with the
time of Laennec.
20 "Les observations contenues dans l'ouvrage de M. Bayle, ainsi
que ce que nous avons dit nous-mêmes ci-dessus du dévelloppement des
tubercles, prouvent suffisamment que l'idée de la possibilité de guérir
la phthisie au prémier degré est une illusion. Les tubercles crus
tendent essentiellement à grossir et à se ramollir. Il est peut être au
pouvoir de l'art de ralentir leur dévelloppement, d'en suspendre la
marche rapide, mais non pas de lui faire un pas rétrograde. Mais s'il
est impossible de guérir la phthisie au premier degré, un assez grand
nombre de faits mont prouvé que dans quelques cas un malade peut guérir
après avoir eu dans les poumons des tubercles qui se sont ramollis et
ont formé une cavité ulcéreuse" (Traité de l'Auscultation médiate).
The appearances found after death in cases which may be considered as
exemplifying, practically, recovery from phthisis vary according to the
extent of the tuberculous affection and the stage to which it had
advanced. In a case referred to in connection with the diagnosis (vide
p. 407) an examination after death, nearly thirty years having elapsed
from the date of recovery, showed within small circumscribed spaces at
the apex of both lungs a condensed pulmonary tissue. In the following
case there was a similar condition within larger spaces: The patient, a
man aged about forty, was attacked with hæmoptysis in April, 1846. Soon
afterward the symptoms and signs of tuberculous disease became
manifest, and death took place in the following June. On examination
after death the lungs were found to contain infiltrated tuberculous
deposits, some of which had undergone softening, and miliary tubercles
in abundance. In addition to these appearances, at the apex of each
lung was a solid mass nearly as large as a hen's egg, that on the right
side being somewhat larger than that on the left. The surface over
these masses presented a marked depression and a puckered appearance.
On dividing the masses they appeared to consist of condensed
parenchyma: they were of a reddish color, friable, and contained an
abundance of minute calcareous particles. They were surrounded by a
thick, firm wall isolating them from the adjacent pulmonary structure.
Eighteen years before his death this patient had cough and other
symptoms which were regarded at the time as denoting pulmonary
phthisis. He recovered, and had good health up to the fatal illness.
The only exception to this statement of his previous good health was
the occurrence of a perineal fistula, which was nearly cured by
division of the gut nine months before the hæmoptysis.
No one can doubt that tuberculous cavities may completely cicatrize.
Instances in abundance have been observed since the publication of
Laennec's treatise. The gradual contraction and final closure of a
cavity may be observed during life, the cavernous signs becoming less
marked, and at length disappearing. At the present time I see
frequently two persons who have recovered from phthisis, recovery in
one taking place nearly twenty, and in the other nearly ten, years ago.
In these cases the cavernous respiration was well marked in situations
in which now there is a feeble vesicular murmur. In both cases there is
a circumscribed depression of the chest in these situations.
Recovery may be said to take place when cavities do not cicatrize, but
remain, being lined by a membraniform structure and free from morbid
products. Under these circumstances cavities are innocuous. There is an
approximation to recovery when cavities furnish more or less matter of
expectoration, the lungs elsewhere being free from tubercles or
tuberculous products.
Recovery with calcification of tubercles is illustrated by the
following case: A farmer from Illinois, aged forty, consulted me in
June, 1843. Within the preceding four months he had from time to time
expectorated calculi, some of which were of the size of a small pea, in
great numbers. A hacking cough had existed for several months before he
began to expectorate the calculi. At the time of the expectoration of
these the cough was severe and he raised some bloody mucus. In the
intervals the cough was slight and without expectoration. The
examination of the chest was negative as regards any signs of disease.
Thirteen years afterward this patient came to report his condition of
health. The expectoration of calculi had continued for some
time
after his former visit; then his cough ceased, and meanwhile he had
been perfectly well.
It is a question whether the tuberculous product is ever absorbed. The
fact that in some instances the physical signs in life and the
appearances after death give no evidence of either tuberculous deposit
or cavities, and the fact that tuberculous solidification is observed
to diminish or disappear when apparently the deposit has not been
expectorated, render it probable that under some circumstances
absorption does take place to a greater or less extent. It is doubtless
true that, as a rule, the deposit is not absorbed; the tuberculous
affection in this respect affords a striking contrast to
non-tuberculous pneumonia.
Cases of recovery from phthisis are cited by medical writers as proving
the curability of the disease. The term curability implies that
recovery is due to remedial agencies. It does not therefore embrace a
truth of great importance in its bearing on the prognosis and the
treatment—namely, the disease in certain cases ends in recovery purely
from an intrinsic tendency. My clinical studies have furnished facts
which conclusively establish this important truth. Out of a large
number of cases (640) recorded during a period of thirty-four years,
recovery took place in 44. In 23 of these 44 cases there were no
measures of treatment to which the recovery could be attributed. The
disease ended favorably in these 23 cases from self-limitation. This
assertion does not express a conjecture or a theory, but a logical
conclusion. Self-limitation, therefore, is a highly important element
in prognosis; it is a highly important factor in the treatment. The
claim in behalf of phthisis of self-limitation, based on the analysis
of cases of recovery, was made by me nearly a quarter of a century
ago.21 It has not as yet received that recognition in medical
literature which it is desirable that it should receive in view of the
importance of its practical bearings. It will enter here into
considerations connected with treatment and prognosis.
21 Vide American Journal of the Medical Sciences, January,
1858.
Recovery from phthisis involves, of course, cessation of the progress
of the disease. This cessation of progress may be due either to an
intrinsic tendency or to arrest by measures of management, or to both
combined. Recovery may or may not follow the cessation of progress.
Owing to the disposition and the extent of the tuberculous affection,
reparation of the lesions does not take place. It is a useful grouping
of cases into—first, those which become non-progressive and end in
recovery; and, second, those in which the cessation of progress is not
followed by complete recovery. It is also useful to consider as forming
a third group cases in which the progress of the disease is extremely
slow. The cases in the latter group are the opposite to those in which
the progress of the disease is continuous and rapid, giving rise to the
name galloping consumption.
There is much significance in the fact that in cases of progressive
phthisis the disease does not, as a rule, advance by a steady increase,
but by a series of invasions. Successive eruptions of the tuberculous
affection occur. In these eruptions the affection may be either small
or moderate or considerable in amount. The intervals between them may
be brief or long. The disease may end with a single eruption. This may
be small or even slight, and followed quickly by recovery. There is
reason to believe that instances of this kind are not infrequent. The
phthisical affection may have been overlooked, or it is inferred from
the recovery that there was an error in diagnosis. In the great
majority of cases a series of eruptions occurs, and it is in this way
that the disease is generally progressive. These clinical facts,
regarded from the standpoint of the parasitic origin of phthisis, are
to be explained by supposing that bacterial colonies invade at
successive epochs different portions of the lungs, but that in a
certain number of instances there is neither invasion nor migration of
the parasite.
The occurrence of successive eruptions is made
manifest by the symptoms and the physical signs. After the occurrence
of a single eruption or a series, if there be no recurrence the
recovery will depend, cæteris paribus, on the amount of the tuberculous affection.
The prognosis in individual cases involves clinical points which
pertain to the symptoms and signs of the pulmonary affection, and to
the symptomatic phenomena referable to other of the anatomical systems
of the body. The latter are of importance as representing the
constitutional condition or the cachexia, and as indicating either, on
the one hand, self-limitation, or, on the other hand, a progressive
tendency of the disease.
Other things being equal, the smaller the pulmonary affection the
better the prognosis. But assuming that the first tuberculous eruption
is small, it does not follow that other eruptions may not occur more or
less speedily, and, assuming a considerable or a large eruption,
another may not occur. The prognosis in the latter case is of course
much the more favorable. In forming a judgment in respect of the
prognosis, the amount of the pulmonary affection is less to be
considered than the symptoms which relate to the progressive tendency
of the disease and to its tolerance by the system. An unfavorable
prognosis, however, is to be based on the existence of an amount of the
pulmonary affection sufficient to compromise the respiratory function,
as shown by notable increase of the frequency of the respirations and
by dyspnoea. Hæmoptysis, as has been seen, if unaccompanied by other
symptoms which are untoward, even if the hemorrhage be profuse, is not
an unfavorable event. Microscopical examinations of the sputa afford
important information bearing on the prognosis. Examinations, thus far,
made by different observers, show that in proportion to the abundance
of the parasite in the sputa the disease may be considered as actively progressing.
Important prognostics derived elsewhere than from symptoms referable to
the pulmonary organs relate especially to the circulatory system,
inclusive of the temperature of the body, to the digestive system, to
the hæmatopoietic system, and to nutrition. Acceleration of the pulse
is an unfavorable symptom. In proportion to the degree of acceleration,
either activity of the progress or a want of tolerance of the
tuberculous affection, or of both combined, is to be inferred. It is of
course important, if practicable, to know the patient's normal pulse as
the standard for comparison in individual cases, inasmuch as the
frequency in health varies considerably in different persons. A febrile
temperature is especially significant as a symptom of progressive
phthisis. It is the best criterion of the activity of progress. There
is no constant proportionate relation between the amount of the
pulmonary affection, as shown by the local symptoms and the signs, and
the elevation of temperature. Nor does the degree of fever correspond
always with the acceleration of the pulse. Diurnal exacerbations of
fever, with more or less profuse sweating, are evidences that the
disease is progressive. Both fever and the rapid action of the heart
not only have symptomatic significance, but they contribute to
progressive exhaustion.
Impaired power of digestion and anorexia are bad prognostics.
Especially bad is a degree of anorexia in which not only no desire for
food is felt, but it is so loathed as to render adequate alimentation
impossible. Diarrhoea, although not dependent on tuberculous disease of
the intestine, is a bad prognostic, as denoting impairment of the
digestive processes. Notable pallor, whether an effect of deficient
alimentation or referable to the hæmatopoietic system, weighs heavily
against the expectation of improvement. A considerable emaciation has
even greater weight. Whenever in the progress of the disease the
patient becomes notably pale and emaciated, there is little ground for
hope, especially if there be conjoined muscular debility, a rapid
pulse, and a high temperature. It is unnecessary to attempt a clinical
picture of the
disease as it is presented toward the close of
life. The reality is unhappily too familiar to every observer.
The picture just referred to has another side. The disease is not
always progressive. There is reason to believe that its progress is
sometimes arrested. It ceases to progress in some cases from
self-limitation. In a certain proportion of cases recovery takes place.
What, then, is the basis for a favorable prognosis? In general terms,
it is the absence of the unfavorable prognostics which have been
mentioned. The prognosis is favorable in proportion as the action of
the heart is but little disturbed, the temperature of the body
non-febrile, the appetite and digestion but little affected, the
complexion not much changed, and the nutrition of the body fairly
maintained. The inference under these circumstances is that the disease
does not tend to progress, and that the existing pulmonary affection is
well tolerated. The ground for encouragement is greater the less in
amount the pulmonary affection; but even if the symptoms and signs show
the latter to be considerable or even large, encouragement is
warrantable so long as there is evidence of non-progression and
tolerance. It is not, however, to be forgotten that there is always
more or less danger of a renewed tuberculous eruption.
The suspension of menstruation belongs among the unfavorable events,
but alone it has not great significance. Its occurrence as respects the
previous duration of the disease varies much in different cases. In
some cases menstruation continues nearly to the close of life. The
return of menstruation after its suspension for a greater or less
period is a favorable prognostic.
The occurrence of certain complications is of marked importance with
reference to the prognosis. Perforation of lung followed by pleurisy
and pneumothorax is in most instances speedily fatal. On the other
hand, simple pleurisy with effusion, in some instances at least, seems
to have a favorable effect upon the pulmonary affection. Tuberculous
ulcerations of the intestine preclude the expectation of improvement
and hasten the fatal termination. Tuberculous peritonitis is a fatal
prognostic. Chronic laryngitis, if it interfere with alimentation, is a
serious complication, but if that effect be wanting it is not
unfavorable as regards its significance in prognosis. Perineal fistula
is not unfavorable, to say the least. Renal disease, and any accidental
complication sufficient in itself to tell more or less against the
powers of life, must be regarded as telling proportionately upon the prognosis.
What influence has the evidence of a congenital tendency and heredity
upon the prognosis? It is commonly believed that the chances of arrest
and recovery are less in proportion to this evidence. There is
doubtless truth in this belief, but it has sometimes too much weight in
the minds of both patients and physicians in individual cases. The
disease is by no means always progressive even when the antecedents of
the patient afford the strongest evidence of an innate predisposition.
The following instance is given by way of illustration: In 1861 a young
woman, eighteen years of age, affected with phthisis, came under my
care. The disease had existed for two years, and she had tried various
climates—namely, Cuba, Florida, Minnesota, Kentucky, and Ohio. The
case ended fatally in 1863. The mother of this patient and two sisters
had died of tuberculous disease. The father was tuberculous at the time
of her death, and he died soon afterward with an intestinal
complication. There remained two sisters and two brothers. The elder of
the brothers, aged seventeen, was attacked in 1861 and died in 1863.
The climate of Minnesota was resorted to in this case with no benefit.
The younger brother, aged sixteen, in 1861 had a dry cough, which after
a short time ceased, and he became apparently well and robust. The
physical signs at that time showed a small tuberculous affection at the
summit of the left lung. In the winter of 1863 the cough returned, and
the signs now showed a tuberculous affection of the summit of the right
lung. He was immediately
sent to Europe, and he passed the winter
and spring at Nice. He returned and went to South America in 1864. He
passed the winter of 1865–66 in New Orleans and France, making the
voyage in sailing ships. He passed the winter of 1866–67 in St. Paul,
and died in the following spring. Of the two remaining sisters, the
previous history in the case of the elder, aged thirty, seemed to
warrant a retrospective diagnosis of a small phthisical affection which
had ceased to progress and from which she had recovered. There were
slight dulness of the summit of the chest on the left side and
broncho-vesicular respiration. This one of the sisters has been well
for the twenty-three years which have elapsed since the date of the
supposed phthisical affection. The younger of the two sisters at the
age of twenty-two had a cough with small expectoration and a moderate
bronchial hemorrhage in the winter of 1862. There was abnormal dulness
on percussion at the summit of the chest on the right side, with
weakened respiratory murmur, some crepitation, and increase of vocal
resonance. After a few weeks the pulmonary symptoms ceased. In this
case there was no treatment, medicinal nor hygienic; she had passed the
winters in the city and summers at attractive places of resort,
entering with zest into social enjoyments, and she has been in all
respects well up to the time when I last saw her, in the spring of
1881, twenty years after the phthisical disease.22
22 Since that date a recurrence of the affection has taken
place, but without being progressive.
The last two cases are instances of recovery from phthisis irrespective
of any medicinal or hygienic agencies; that is, a recovery by
self-limitation. Considering the evidence of a family predisposition, a
favorable prognosis at the outset would hardly have been justifiable.
From my records of cases other instances might be selected illustrative
of the caution not to allow too much weight in the prognosis, in
individual cases, to the evidence of an innate predisposition.
It might be supposed, from the greater liability to phthisis between
the ages of twenty and thirty years, that its occurrence at this period
of life affects unfavorably the prognosis. Facts, however, do not
appear to sustain this supposition. So far as the ratio of recoveries
bears upon the point, the study of a limited number of cases shows it
to be not larger after than before the age of thirty.23
23 Vide Phthisis, in a Series of Clinical Studies.
The liability to a recurrence of the disease after recovery is
important to be considered in connection with the prognosis. Of 44
cases of recovery among those which I have recorded and analyzed,
recurrence had taken place in 6 up to the time of the analysis. In one
of these 6 cases the disease had recurred twice. The patient recovered
from the second recurrence, and is now well, more than ten years having
elapsed. In all the other cases the recurrence proved fatal. The
recurrence took place after periods ranging from one and a half to over
six years from the date of the recovery. So far as these cases warrant
a conclusion, it is that in cases of recurrent phthisis the prognosis
is very unfavorable. This conclusion might be materially modified by
the study of a large number of cases. The fact that after recovery
there is considerable liability to a recurrence of the disease has an
obvious bearing upon the prophylactic management.
Facts pertaining to the duration of phthisis come properly under the
head of prognosis. Of 44 cases of recovery which I have recorded and
studied, the duration varied from six months to ten years. In more than
one-half of these cases the pulmonary affection was small; in 4 cases
it was moderate in amount; in 10 cases it was considerable; and in 1
case it was large and advanced.24 These facts show that the prospect
of recovery is much better
when the tuberculous affection is
small or moderate, but that a considerable and large affection does not
preclude recovery.
24 Vide Phthisis, in a Series of Clinical Studies, for
abstracts of the histories of these cases. Absence of all pulmonary
symptoms was known to have existed in the different cases for periods
between six months and twenty-seven years. Throwing out two cases in
which the period was six months, and one case in which it was eight
months, the average period was six years.
Next to recovery, the course of the disease is favorable when it ceases
to be progressive and life with fair health is continued for a long
period. Out of the cases which I have analyzed, there were 28 in which
the disease was known to have existed for periods ranging from one year
and three months to twenty-five years. The duration was reckoned up to
the time of the analysis or of the last information obtained. The
number of years noted does not express the duration of life. The
average period during which the disease was known to have been
non-progressive is a fraction over eight years. The histories in these
cases exemplify the fact that phthisis, when it ceases to be
progressive, although recovery does not take place, is not incompatible
with fair and even good general health and long life. That recovery
does not take place is owing to the persistence of pulmonary lesions,
such as cavities which do not cicatrize or an interstitial pneumonia
with dilatation of bronchial tubes. The tuberculous disease no longer
continues, but the local effects of the disease remain. Slowness of
progress and prolonged tolerance are to be hoped for when the disease
neither ends in recovery nor becomes non-progressive. In some cases the
disease ends fatally, having existed for many years where at no time
could it be said that its progress had ceased. The prolongation of life
under these circumstances depends on the slowness with which the
disease progresses and the ability of the system to tolerate it.
The extremes of the duration of the disease in a large collection of
fatal cases are so far apart that the average period is of little
practical value as bearing on the prognosis in individual cases. In the
collection of recorded cases which I have studied analytically, there
were 112 the duration of which from the commencement of the disease to
its fatal termination was ascertained. The mean duration was about
twenty-three months. Laennec found the average duration twenty-four
months; Louis and Bayle, twenty-three months; Andral, twenty-four
months; Sir James Clark, thirty-six months; and Williams of London,
forty-eight months.
TREATMENT.—The author premises the consideration of the treatment by
stating that this article was written before sufficient time had
elapsed after the publication of the researches by Koch for their
confirmation by other competent observers. At the present time (May,
1885) the doctrine that phthisis depends on the presence of a special
micro-organism is to be considered as probably established. The grounds
for this statement have been presented under the head of the Etiology,
and reference to the practical bearings of the doctrine have been
introduced in connection with the Diagnosis and Prognosis. It is
evident that the doctrine is likely to have important bearings on the
treatment. If it be true that the origin, the extension, and the
diffusion of the disease within the body require the presence and the
multiplication of a particular parasite, it is evidently a rational
object of treatment to effect its destruction. For this object an
efficient parasiticide is to be sought after, to be administered either
by inhalation or by its introduction into the blood-vessels. Already,
within the short time which has elapsed since Koch's discovery,
extended observations have been made with various substances which are
destructive to bacteria outside of the body, but thus far without
success. A difficulty as regards inhalation is in the way of a
destructive agent in the form of either an impalpable powder or a vapor
or a gas reaching the colonies of bacilli in sufficient quantity to
effect the object, without doing injury to the tissues or inducing
toxæmia. As regards the introduction of
parasiticides into the
blood, it seems hardly probable that a toxic agent can be safely
introduced in sufficient quantity to effect the object. It remains to
be determined by clinical observation whether or not these difficulties
are insuperable.
Efforts to destroy the parasite in another direction promise to be more
effectual—namely, by the removal of the co-operating conditions on
which their multiplication depends. It is to be borne in mind that the
development and continuance of phthisis involves two factors, one which
is the presence of the parasite, and the other the existence of those
unknown conditions constituting the tuberculous predisposition or
cachexia. The removal of the latter may effect the destruction of the
parasite indirectly, but not less certainly than by bringing into
direct contact with it a destructive agent. It is in this indirect way
that the measures of treatment which experience has shown to be more or
less effective may be supposed to operate. And it is to be added that
those measures of treatment the usefulness of which rests on clinical
observation are in no wise disproved or modified by the parasitic
doctrine. At the present time the treatment of the disease is to be
governed by principles which, based on reason and experience, are
independent of that doctrine.
The intrinsic tendency of phthisis to be either progressive or
non-progressive underlies the treatment. In a certain proportion of
cases the disease tends to advance steadily and actively, as shown by
the symptoms and the physical signs. In these cases treatment cannot be
expected to do more than to palliate symptoms, and perhaps prolong the
duration of life. These are cases of so-called galloping consumption.
In a larger proportion of cases the disease does not steadily or
actively advance. Remissions occur. The pulmonary affection increases,
and extends by successive tuberculous invasions or eruptions after
intervals variable in duration. These cases offer more encouragement
for treatment. There is room to hope after each invasion that another
will not take place, and that the affection which exists may be
tolerated indefinitely if the cases do not end in recovery. In a
minority of cases when a certain amount of pulmonary affection has
taken place there is no further increase or extension. In this respect
the disease ceases to progress. In some of these cases after the lapse
of weeks or months all pulmonary symptoms disappear, and the patient
may be said to have recovered. The probabilities of the recovery and
the time required therefor vary, other things being equal, according to
the amount of the pulmonary affection. In other cases recovery does not
take place. More or less of pulmonary symptoms remain. The existing
lesions which these symptoms represent, however, may be well tolerated,
and their existence may not interfere with fair or even good general
health and long life.
Whenever the disease ceases to be progressive, with or without
recovery, an intrinsic tendency has more or less agency in the
cessation of progress. In some instances it is certain that this result
is wholly due to self-limitation. Expressing the fact in other language
than that of personification, the disease may become non-progressive
because the unknown, special, constitutional morbid conditions which it
is customary to embrace under the name tuberculous cachexia no longer
exist; or, assuming that a particular parasite is essential to the
progress of the disease, this organism may cease to multiply in
consequence of the non-continuance of conditions which are necessary
for its multiplication. Whatever be the explanation of the tendency of
the disease—to be, on the one hand, progressive, or, on the other
hand, non-progressive—it must be taken into account in estimating the
influence of measures of treatment. How largely an intrinsic tendency
to be non-progressive is accountable for apparent success in treatment
cannot be determined with precision. The evidence of its agency can
only be derived from the accumulation of cases of non-progressive
phthisis in which no active measures of treatment were pursued.
Reference has been made to a few such cases
among those which I
recorded during a period of thirty-four years. Some cases in addition
have come under my observation since the analysis of my cases recorded
up to 1875. It is evident that a large collection of such cases cannot
be made by a single observer.
From what has been stated, it follows that the treatment in case of
phthisis has reference especially to the constitutional conditions
which stand in a proximate causative relation to the pulmonary
affection. The chief objects are to arrest the disease and to keep the
cachexia in abeyance. In the present state of our knowledge measures of
treatment addressed directly to the pulmonary affection, albeit
important, are of secondary importance when compared with those which
either co-operate with or oppose the underlying intrinsic tendency of
the disease as manifested in individual cases.
Proceeding to consider the treatment in cases of phthisis, a convenient
division of topics is into those relating to the climatic treatment,
the dietetic and regiminal treatment, and the medicinal treatment.
Climatic Treatment.—It would be impossible within the limits of this
article to enter into a discussion of the various questions connected
with climatic influences or to consider the relative advantages of
different climates. Nor, were it possible, would this be desirable as
regarded from a practical standpoint. I shall confine myself to the
general considerations which bear upon the climatic treatment.25
25 For an account of the characteristics of different places
of resort in different countries, and a full consideration of the
subject of climate in relation to phthisis and other diseases, the
reader is referred to the article entitled "Klimatstherapie" by H.
Weber of London in Handbuch der Allgemeinen Therapie, von H. v.
Ziemssen, Zweiter Band, Leipzig, 1880.
In the analytical study of the cases of phthisis I had recorded up to
the year 1875, I endeavored to draw some conclusions respecting
climatic treatment from the facts contained in the histories. Temporary
changes of climate entered into the treatment in 74 cases. The
histories were interrogated with reference to the number of cases in
which recovery took place, the number in which the disease ceased to be
progressive without recovery, and the number in which the disease
progressed slowly, with reference to the apparent influence exerted by
climate. The changes of climate in the 74 cases were various. In a
considerable number the patients traveled in Europe, visiting different
places. The foreign resorts in which they sojourned for greater or less
periods were Nice, Algiers, Mentone, Egypt, Nassau, Lima, Rio Janeiro,
Cuba, and the West India islands. In this country the different resorts
were in Minnesota, California, New Mexico, Florida, Georgia, South
Carolina, Louisiana, Virginia, Kentucky, the District of Columbia,
Michigan, and the Adirondacks. Colorado as a place of resort had not
excited much attention prior to my making abstracts of my histories for
analytical study, and for this reason it does not appear in the
foregoing list. I have notes of not a few cases in which the latter
climate was resorted to. It is at once evident that 74 cases
distributed over so many places of resort cannot furnish adequate data
for judging of the relative advantages of different climates.
Nevertheless, the analysis of these cases led to an important
conclusion as respects, in general, the usefulness of a temporary
change of climate. Of the 74 cases, 9 ended in recovery, 13 were in the
list of cases of arrested or non-progressive phthisis, and 5 were in
the list of cases in which the disease was slowly progressive. In 33
cases the disease ended fatally, and in 14 cases neither the duration
nor the termination of the disease appears in the histories. Moreover,
of the 33 fatal cases, in 23 the histories afforded evidence of more or
less benefit from the changes of climate.26 From these facts it
seemed warrantable to deduce, as a positive conclusion, that in a
considerable proportion of cases a
change of climate has a
favorable influence on phthisis. It follows also, as a corollary, that
a favorable influence is exerted by a variety of climates. Indeed, it
would seem, judging from these facts, that the favorable influence
pertains to the change rather than to the particular climate selected.
If this be true, it follows that the agencies by which a favorable
influence is exerted relate to accessory or incidental circumstances
more than to purely climatic conditions.
26 For further details vide Phthisis, in a Series of
Clinical Studies.
It is an absurd supposition that any climate exerts a specific
influence in arresting phthisis. This statement is not in the least
inconsistent with the fact that certain climatic conditions are much
more favorable than others for an arrest of the disease. Dryness,
equability, and purity of the atmosphere are essential elements of a
favorable climate. Within late years a high altitude (4000 to 8000 feet
above the ocean-level) has been deemed by many of much importance.
Aside from the purity of the air incident thereto, the rarefaction is
supposed to have a salutary effect by increasing the expansion of the
lungs.27 Few at the present time regard a tropical temperature as
advantageous. The choice is usually regarded as lying between a cold
and a warm climate, each having favorable elements aside from
temperature. There is abundant testimony in behalf of each.
Circumstances pertaining to cases individually must determine which to
choose. A patient who in health has found cold weather more favorable
to vigor and well-being than warm weather will be likely to find a cold
climate more beneficial than a warm climate, and vice versâ. In order
to derive benefit from a cold climate a patient must have preserved
sufficient vigor to endure out-of-door life in such a climate.
Confinement much of the time within doors must deprive patients of the
benefit to be hoped for from a cold climate. For obvious reasons a cold
climate is better suited to men than to women. With reference to the
superior excellence of particular health-resorts, caution is to be
exercised in weighing not only testimony either for or against their
superiority, but the value of reported cases. Putting aside the chances
of error in diagnosis, it is to be considered that among those who
elect a particular place of resort an arrest of the disease or
improvement to a greater or less extent would probably have taken place
had any one of many places been selected, and perhaps if no change had
been made. On the other hand, in a certain proportion of cases the
disease will be progressive anywhere. A limited number of cases must
not be relied upon to establish the relative advantages of particular
places, especially if there be not data enough to judge of the
condition of the patient in each case as regards the amount of the
pulmonary affection, the temperature, pulse, and other symptoms. A few
cases which have been selected to illustrate either the favorable or
unfavorable influence of a particular climate are not entitled to any
weight in the formation of an opinion. To gather clinical facts
sufficient to determine by analytical study the actual advantage
severally of different climates is a work attended by so many
difficulties that it must be long before it can be accomplished.
Meanwhile, in discriminating between different places of resort the
physician is to be governed by rational considerations. In reality,
custom and fashion have much to do in this matter. Places which were
formerly in vogue as health-resorts have now fallen into disrepute. It
is almost inevitable that sooner or
later this will be the fate
of any place which becomes so popular as to attract very largely
phthisical patients, owing to the aggregation of the instances in which
no benefit could have been expected from climatic treatment.
27 On this topic the reader is referred to an article by C.
Theodore Williams, entitled "The Treatment of Phthisis by Residence at
High Altitudes," in the Transactions of the International Medical
Congress, London, 1881; also to a work entitled Rocky Mountain
Health-Resorts, an Analytical Study of High Altitudes in Relation to
the Arrest of Chronic Pulmonary Disease, by Charles Denison, M.D., 2d
ed., 1880.
There is much reason in the suggestion that the immunity from phthisis
in situations which are sparsely settled may be due not so much to
climatic influences as to the fact that these situations are free from
non-climatic causes contributing to the prevalence of the
disease—namely, in-door occupations, overcrowded dwellings, etc.
There is reason to believe that the benefit derived from climatic
treatment is often in a great measure due to accessory circumstances.
As already intimated, this seems to be a fair inference from the number
of instances of arrest of the disease, of cessation of its progress,
and of notable improvement in a collection of cases in which many and
varied climates had been resorted to. Under the name accessory are
embraced a variety of circumstances—in fact, everything not pertaining
purely to climatic agencies. The opportunity of living in the open air
and freedom from the cares of business, together with relaxation and
mental diversion, are in the category of accessory circumstances. These
contribute largely in some cases to the benefit derived from change of
climate. Patients at a health-resort are apt to carry out hygienic
regulations more faithfully than when at home. In contrast to the
accessory circumstances which are favorable there are those which have
an unfavorable effect, such as home-sickness, ennui from lack of usual
occupations, anxiety lest affairs should suffer for want of personal
supervision, interruption of fixed habits, and the want of home
comforts. These in some cases may go far toward counteracting the
benefit from climatic influences.
All these accessory circumstances, as bearing upon individual cases,
are to be taken into account in deciding the question as to the
importance of climatic treatment. Of course a change of climate is
important, other things being equal, in proportion as the climate in
which the patient resides is humid, variable, and the atmosphere
impure. So far as purely climatic influences are concerned, it may be
important only that the patient escape the more trying seasons of the
year—namely, the spring and the hot summer months. A malarial climate
should certainly be exchanged, if practicable, for another during the
season when there is danger of being infected with the malarial miasm.
To avoid this cause of disease, as well as the changes of temperature,
etc. incident to the spring and summer months, it may not be necessary
to go very far from home. It is probably better not to go to a distant
climate for a few weeks, in order that the double acclimatation caused
by going and returning within such a brief period may be avoided.
It is of essential importance to take fully into account the condition
of the patient as regards the pulmonary affection and the general
symptoms before advising or sanctioning a change of climate which
involves long journeys and separation at a distance from home and
friends. There is more reason to expect benefit from a change the
stronger the evidence against an intrinsic tendency of the disease to
progress actively. Whenever the temperature and circulation denote
activity of progress the propriety of a change is doubtful. Whenever
there is great emaciation with muscular feebleness there is little
ground to expect material benefit from any climate. The experiment is
allowable at an advanced period of the disease only with a view to
satisfy the wishes of the patient and the friends, having a full
understanding with the latter in respect of the danger of dying away
from home. It should be added that sometimes in cases which offer no
ground for the expectation of any essential benefit journeys or voyages
are well borne, and life is apparently prolonged by a change from an
inclement to a genial climate.
Distance is a point to be considered in the selection of places of
resort. It is often an objection to crossing the ocean that
communication with relatives or friends is attended with delay and
difficulty. The voyages, as a rule, are not objectionable. Our own
country embraces almost every possible variety of climate, and
therefore, so far as purely climatic influences are concerned, it is
not necessary to resort to foreign countries. The latter, however, have
for many the advantage of being made more attractive by novelty and
historical associations. Moreover, there are often better
arrangements for comfort and enjoyment. The accessory advantages are
always to be considered with reference to the particular tastes and
needs in individual cases. Good food in abundance and well cooked,
large and well-ventilated rooms, facilities for walking, riding, and
driving, opportunities for hunting, fishing, and other out-of-door
sports, ample provisions for in-door exercise in bowling, etc.,
agreeable society,—these are among the accessory advantages without
which often the best climatic influences will prove inoperative. To
these is to be added available judicious medical advice.28
28 For details concerning the health-resorts of the Riviera,
Hyères, Cannes, Nice, Mentone, and others which are much esteemed in
Europe, the reader is referred to a work entitled The Riviera, by
Edward I. Sparks, London, 1879.
A mistake often made by those who find benefit from a change of climate
is to continue the change for too short a period. The benefit speedily
obtained may be speedily lost when the patient is again placed under
the climatic and other circumstances attending the development of the
disease. It is to be borne in mind that the benefit from a change of
climate does not depend on any special remedial agency, but on a
combination of favorable circumstances, and that the salutary
influences connected with climate are exerted not so much directly upon
the lungs as upon the general system. It follows that the beneficial
effect may be manifested more by increase of appetite, better
digestion, greater endurance of muscular exercise, and especially gain
in weight, than by immediate improvement in the pulmonary symptoms.
Many patients cannot afford the loss of time and the expense of
lengthened absence, and therefore are unable to make trial of change of
climate. These may be consoled by the fact that not a few cases of
phthisis do well without any climatic treatment. In some of the most
striking of the instances of arrest of the disease which have come
under my observation change of climate did not enter into the
treatment. Important as is this fact, it does not conflict with the
belief that additional chances of arrest and the prospect of more or
less improvement are often secured by climatic treatment. It is a wise
precaution for patients to reside permanently in a climate in which an
arrest of the disease has taken place. Of course this is not always
practicable. Its importance is attested by reason and experience, and
it is the duty of the physician, according to his discretion, to
suggest it. The many obstacles which are often in the way of its
adoption are sufficiently obvious.
Sanitaria for phthisical patients at health-resorts are doubtless
serviceable in many cases, because hygienic measures are enforced which
would not under other circumstances be thoroughly carried out. An
offset to this advantage is the depressing effect upon some minds of
association with other patients. Owing to this moral effect it is
sometimes judicious to advise patients not to go to places which, for
the nonce, are especially popular, in order that they may not have
before their eyes cases exemplifying all the phases of the disease, and
be led to talk over symptoms with other patients affected with
phthisis. As regards sanitaria, those in which the chief object is to
enforce measures of hygiene are perhaps most likely to be serviceable.
If these measures be secondary to some system of medication, there is
room for distrust.
It is hardly necessary to say that the treatment of patients in such
institutions should be under the charge of competent physicians who
have not originated or adopted any peculiar notions respecting the
pathology and therapeutics of the disease. As a matter of course, there
cannot and should not be any restriction in either originating or
adopting ideas and methods of practice, however much they may be at
variance with commonly-received opinions; but a physician who
appreciates his obligation to his patients will hardly feel willing
that they should be made subjects for testing pathological and
therapeutical novelties in behalf of which his own belief is not committed.
Dietetic and Regiminal Treatment.—The dietetic treatment
resolves itself into a few simple principles. It may be assumed that as
much assimilation of aliment as is possible is desirable. No one
probably will contend for the propriety of any restriction of diet with
a view to limiting the amount of the nutritive constituents of the
blood. The difficulty in this part of the treatment lies in the
impairment or loss of appetite and in lack of digestive or assimilative
ability. It is useless to consider whether such or such articles of
food are suitable or not for phthisical patients. All wholesome
articles which can be taken with any relish and digested are suitable.
Nothing could be more ill advised than to direct kinds of nutriment
which a patient does not like, and to enjoin avoidance of those which
the patient's appetite would dictate. Pains should be taken to
ascertain the articles of diet most acceptable or against which there
is the least repugnance, and to excite the appetite by variety and
culinary attractions. It is important not to judge too hastily of the
ability to digest the food which can be ingested. The evidences of
indigestion are nausea, vomiting, flatulence, acidity, and diarrhoea:
whenever these symptoms are wanting it is fair to assume digestive
ability. Nor should evidence of indigestion deter at once from
continuing articles which appear to have occasioned it. The processes
of digestion are so apt to be disturbed by extrinsic accidental
circumstances that a meal which will occasion indigestion to-day may
not do so to-morrow. In short, so far as regulation of the diet is
concerned the patient is to be encouraged to take all kinds of
wholesome food according to appetite and taste, giving to each and all
a fair trial as regards digestibility. Fully aware that these views may
not commend themselves to the approval of many who think that the diet
should be regulated on scientific principles rather than by the
instincts of the patient, I do not any the less adhere to them,
believing that they are based on experience and common sense. As
regards the liability, where the instincts are followed, to the
over-ingestion of food and to the ingestion of food indigestible from
its quality or modes of preparation, it is far better to incur whatever
inconvenience may therefrom arise than the evils of inadequate
nourishment. In short, the dietetic instructions to a phthisical
patient may be summed up as follows: Eat of wholesome articles of food
whatever the appetite may dictate; endeavor to maintain and develop
appetite and relish for food by the excitement of variety in kind and
in preparation; eat whenever hungry; satisfy the appetite; eat without
any expectation of harm; do not hastily attribute an indigestion to any
particular articles of diet; incur the risk of over-feeding rather than
of the greater evil of under-feeding.
Anorexia in a degree which I have characterized as invincible—that is,
an almost complete inability to take food—is one of the most
discouraging of symptoms in cases of phthisis. Of course if the symptom
continue the duration of life is simply a question of time and
tolerance. Milk is an invaluable form of food when appetite is
completely lost. The advantage sometimes of substituting for simple
cow's milk buttermilk, koumiss, or milk made sour by fermentation with
yeast is due wholly to these being taken more readily and more easily
digested. The same is true of the substitution for the milk of the cow
that of other animals—the goat, the ass, and the mare. Eggs may be
given in a liquid form with milk or other fluids. Very little reliance
is to be placed on the various meat-extracts (Liebig's, Valentine's,
and others) as representing any considerable amount of nutriment. Meats
artificially digested—that is, in the form of peptones, as in Leube's
meat solution—form a valuable addition to beef-tea. Rectal
alimentation may be resorted to. A. H. Smith has reported marked
benefit from defibrinated blood as a form of rectal diet.29 A French
writer, Debove, has lately reported notable benefit from forced
alimentation, food being injected through a tube introduced into
the stomach.30 If in any way food can be introduced, in spite of the
anorexia, and assimilated, there may be room to hope that a return of
appetite will be among the beneficial effects. Cod-liver oil and
alcoholics will be considered in connection with the medicinal treatment.
29 Vide N.Y. Med. Record, 1881, No. xix.
30 Vide Bullétin générale Report, Paris, 1881. Another
French writer more recently in the same journal, Desnos, has pointed
out a source of danger in forced alimentation—namely, the occurrence
of violent acts of vomiting, during which portions of food ejected from
the stomach are inhaled. The danger is from asphyxia and pneumonic
inflammation excited by the presence of particles of food within the
smaller bronchi. In order to avoid this source of danger, food should
be introduced slowly and not in too large a quantity at a time.
Intolerance of the presence of the tube within the stomach is an
obstacle which may be overcome by use, but in some cases it is
insuperable (vide article in Philadelphia Med. Times, March, 1882).
The regiminal treatment embraces changes relating to out-of-door life,
exercise, occupation, clothing, etc.
Of all the changes in this category, those relating to out-of-door life
and exercise are of greatest importance. In-door life and sedentary
habits, if not factors in an acquired cachexia, undoubtedly favor it.
This is shown by the place which these hold in the etiology and by
their agency in the arrest of the disease. With respect to the latter
point, the result of my analysis of recorded cases has much
significance. In 44 cases change of habits from those more or less
sedentary and confining within doors to those involving out-of-door
life and activity entered into the treatment. In all but 4 of these
cases the hygienic treatment consisted chiefly or exclusively of the
change of habits mentioned. Of the 4 excepted cases, in 1 the patient
passed several months in Europe; in 1 the patient passed a summer in
Minnesota; in 1 the patient made several voyages to Europe; and in 1
the patient travelled in Europe. Of these 44 cases, 15 are in the list
of cases of unknown duration and termination. Deducting these, the
remaining number is 29. Now, of these 29 cases, 11 are in the list of
cases ending in recovery; 7 are in the list of cases in which the
disease was arrested or became non-progressive; and 3 are in the list
of cases of slowly-progressive phthisis. Thus, only 8 out of the 29
cases were not included among those in which the course of the disease
was favorable in the three aspects just named, and in more than
one-third of the cases recovery took place. Of the 8 fatal cases, in
all save 1 case the change of habits appeared to be beneficial. The
benefit was marked in 2 of the cases, there being in 1 of them no
evidence of progress of the disease for several months.31 Moreover,
the majority of the histories of the 15 cases of uncertain duration and
termination show more or less improvement. In 7 of the 11 cases ending
in recovery the change in habits constituted all the treatment. Making
the fullest allowances for an intrinsic tendency in the disease to end
in recovery, and in some instances purely from self-limitation, the
foregoing facts afford ample proof that changes of habits from those
more or less sedentary and confining within doors to those involving
out-of-door life and activity have considerable agency in the arrest of
phthisis and exert a favorable influence upon the disease when it is
not arrested. There is reason to believe that the favorable influence
is greater than any other class of hygienic measures, and it is
probable that to this source much of the benefit derived from change of
climate is to be referred.
31 For details of the changes of habits in these cases vide
Phthisis, in a Series of Clinical Studies.
The particular changes to be made in order to secure as much
out-of-door life as practicable with a certain amount of exercise must
of course vary in different cases. Clerks, school-teachers, mechanics
whose business requires in-door life, etc., should, if possible, adopt
some other occupation securing the desired objects. Students,
clergymen, and men of leisure should systematically devote a fair
proportion of time to exercise in the open air, and as far as
practicable the exercise should involve recreation. It is needless to
say that the importance of change is as applicable to women as to men.
Caution is sometimes necessary not to carry muscular exercise to an
injurious extreme. If carried to the extent of producing great fatigue
or exhaustion, it is debilitating instead of invigorating. Exercise
within doors, although much less useful than when taken in the open
air, is nevertheless useful. Gymnastic exercises may be recommended
when other measures which are to be preferred are not available. They
are inferior to rowing, horseback riding, hunting, etc. An increased
expansion of the chest is apparently a desirable effect of exercise.
Forced efforts of expiration to overcome a mechanical resistance, the
lungs being fully inflated, constituted a method of treatment formerly
in vogue, and I have met with instances in which it seemed to have been
useful. In taking exercise patients are apt to imagine that in order to
avoid catching cold they should go out of doors only when the weather
is in all respects favorable. Precautions in this regard are often
carried so far as to interfere materially with the amount of life in
the open air which is desirable. It should be understood that
phthisical patients are no more—and perhaps less—liable to catch cold
than persons in health, and that a cold, as a rule, does not affect the
progress of the tuberculous disease. These excessive precautions have
arisen from the error of considering phthisis as a sequel of
bronchitis. There is no ground for the great scrupulousness with which
phthisical patients avoid the night air, although out-of-door life in
the daytime is to be preferred.
Every practitioner has known of cases in which some remarkable changes
of habits as regards out-of-door life and exercise have led to
recovery, such as performing long journeys on horseback or on foot,
accompanying expeditions which involved camping in the open air with
hardships, etc. Several instances of this kind have come within my
knowledge. In one of these the patient, a young physician who consulted
me, on being told that he had incipient phthisis gave up his practice
and joined a tribe of Indians in the Far West. He remained with them
for more than a year, adopting all their customs, and returned in
vigorous health. But in order to rough it a patient need not go to a
distance from home and friends. This fact is lost sight of when
physicians sanction the exposures and hardships of travel without the
limits of civilization, but enjoin upon patients great care in taking
exercise out-of-doors so long as they remain in their places of residence.
All who have had the opportunity of observing the effect of sea-voyages
in cases of phthisis are agreed as to their utility. A long sea-voyage
or a series of voyages entered prominently into the treatment of 20 of
the cases which I have analyzed. In a large proportion of these cases
the favorable influence was marked. This is an accessory circumstance
which contributes to the benefit in many cases derived from a change of
climate. It is evident that a certain proportion only of phthisical
patients can avail themselves of this measure. It is to be advised
especially for those who can leave home and business without anxiety,
who are fond of ocean-life, and who as a matter of course are good sailors.
The supposed liability to, and danger of, catching cold often leads
phthisical patients to wear an overplus of clothing. When they strip
for an examination of the chest not infrequently they remove two or
three undershirts, a woollen or fur chest-protector, and sometimes in
addition an oiled-silk jacket. The body is kept in constant
perspiration by these articles. They occasion not only discomfort, but
debility. A single word expresses the governing principle in
clothing—namely, comfort. Articles of dress should be so adapted to
the seasons and to changes of temperature as to secure comfort. This
maxim applies to persons affected with phthisis as well as to those in
health. In some instances, from an erroneous theoretical notion,
patients
make themselves uncomfortable in an opposite way. They
dispense with woollen or silk underwear throughout cold seasons with
the idea that the system is thereby hardened. A good non-conductor of
heat next to the surface protects against changes of temperature and
promotes the functions of the skin. Attention to the sense of comfort
will enable the patient to avoid error in this direction as well as an
overplus of clothing.
Other regiminal observances relate to ventilation and the sponge bath.
The apartment in which the patient is expected to pass at least
one-third of the twenty-four hours should be sufficiently large and
well ventilated. Fresh, cool air in abundance is not deleterious, as it
would seem to be regarded when the utmost care is taken to exclude it.
It is essential to healthful sleep and invigoration. Here, again, the
supposed danger of catching cold antagonizes hygienic treatment. Air
should have free access to sleeping apartments in cases of disease as
in health. As a measure for invigoration the sponge bath is often
useful in cases of phthisis. The water used may be cool or tepid
according to the sensations of the patient and the effect. It should be
followed by a glow with a feeling of invigoration. The water may with
advantage be made stimulating by the addition of salt or of alcohol.
Medicinal Treatment.—The medicinal treatment in cases of phthisis
embraces no known remedies having a special influence over the disease;
in other words, no drug has as yet been found to be an antidote to the
tuberculous cachexia. Nevertheless, medicines in many cases form an
important part of the treatment. They have for their objects
improvement of appetite, digestion, assimilation, and nutrition, relief
from complications or associated affections, and the palliation of symptoms.
Cod-liver oil is considered in this article, as is customary, in
connection with the medicinal treatment. It has, however, little or no
claim to be regarded as a medicine. It is a nutrient. It is a form of
fat which patients often digest readily, and which evidently increases
the weight of the body. That it does more than simply increase the
amount of fat in the body is shown by the fact that frequently under
its use the appetite, the digestion, the condition of the blood, and
the nutrition of the tissues manifest improvement. These effects are
not inconsistent with the statement that it is simply an article of
diet. Although the claims in its behalf as a special remedy which were
made forty years ago have long since been disproved, clinical
experience has continued to furnish proof of its usefulness in the
treatment of cases of phthisis. It should enter into the treatment
wherever it is well tolerated and digested. If it occasion nausea or
diminish the appetite or give rise to eructations, its use should not
be persisted in. In the choice among the different varieties of the oil
experience in each case is to be the guide. Some patients find the
brown varieties more acceptable than the pale, and vice versâ. I have
known in several instances the unrefined, coarse oil obtained at the
fish-markets to be preferred. Patients should not give up this part of
the treatment until the different varieties have been tried. The
popular preparations in which the oil is combined with salts of lime or
with some flavoring extract are sometimes tolerated by those who are,
or who fancy that they are, unable to tolerate the pure oil. They have
probably no advantage for those who are able or who are willing to take
the pure oil. The oil should never be given in doses larger than are
readily digested, and, following this rule, the doses will rarely
exceed half an ounce. They are best given shortly after meals. It is a
popular notion that the oil should not be continued in hot weather. The
weather should have no influence on its continuance, provided it be
well tolerated and digested. The addition of fifteen minims of ether to
a half-ounce dose of the oil has been found to promote its digestion,
and by means of this addition persons with whom the oil disagrees may
be able to take it without difficulty. The ether is to be given
half an hour after the oil has been taken.32 Salad oil, cream,
butter, and the extracts of malt may be made to supply, in a measure,
the place of the cod-liver oil in the cases in which the latter is not tolerated.
32 Vide report by Dr. Andrew H. Smith, chairman of Committee
on Restoratives of the New York Therapeutical Society in the N.Y.
Medical Journal, April 20, 1879.
Embracing the varieties of spirits, wine, and malt liquors under the
name alcoholics, these are to be regarded as alimentary, but also as
medicines. That they are useful in certain cases of phthisis is as well
established on the basis of clinical experience as any fact in
practical medicine. Their usefulness in this disease, as well as in
other diseases, is to be considered irrespective of questions relating
to their use and abuse in health. But as bearing on the very important
subject of intemperance it may be stated that, administered purely as
remedies in cases of phthisis, patients do not become so addicted to
them as to make it difficult to relinquish their use whenever this is
advisable. This statement is based on a large experience.
Alcoholics are useful in some and not so in other cases. The question
as to their usefulness is to be decided in each case by trial. If they
produce a sense of comfort without any excitation of the circulation or
of the nervous system, they are likely to be useful. If in lieu of a
cordial effect they occasion flushing, weariness, or indisposition to
exertion or discomfort of any kind, they are not likely to be useful.
The quantity to be given is to be regulated by the immediate effects.
There is sometimes a notably increased tolerance of alcohol. This is to
be ascertained by experimental observation. The quantity of alcohol
given should never occasion the least approach to alcoholic
intoxication. It should be given at or near the times of taking food,
or in combination with food, as in milk-punch or egg-nog.
As to the choice of an alcoholic, this is to be determined by the past
and present experience in each case. Each of the many varieties of
spirits, malt liquors, and wines is best suited to some cases and not
to other cases. There is no rule of choice applicable to all patients.
Changes in the form of alcoholics from time to time are often advisable
in the same case. In the majority of cases some forms of spirits will
be found best to agree. Malt liquors, either the strong or mild
varieties, agree best in some cases. Of wine, some patients take with
most comfort the light and some the stronger varieties. The effect upon
the pulse, respiration, and other symptoms should be observed with
reference to the employment of any of the alcoholics, and of the
particular ones best suited in individual cases, but much reliance must
be placed on the subjective symptoms. It has been proposed to
substitute pure alcohol for any and all the alcoholics used as
beverages, in order to give to the treatment more distinctly a
medicinal character and to avoid risk of the formation of a habit which
may lead to intemperance. Since, however, of the many varieties of
alcoholics, some agree in certain cases and not in other cases, it is
doubtful whether alcohol is able to take the place of all. This is a
point to be decided by clinical observation.
Phosphorus in the form of the hypophosphite of soda and of lime was
recommended about forty years ago on the theoretical ground that it
favored cell-formation and retarded the rapid waste of the tissues.
More recently it has been supposed to have a specific influence over
tuberculous disease. It has been employed pretty largely in different
countries, but without effects sustaining the claim of having a
specific action. It seems to be useful, and many physicians attach
considerable importance to its use.
The preparations of iodine, from their evident utility in certain
scrofulous affections, and in view of the identity of scrofula and
tuberculous affections, have heretofore entered largely into the
treatment of cases of phthisis. From the fact that they are now but
little employed in phthisical cases it may be
inferred that in
this instance, as in many other instances, theoretical considerations
have failed to find support from clinical experience.
Of arsenic it can be said that many able observers have borne testimony
to its great usefulness in some cases, as manifested by improvement in
appetite, nutrition, and in the powers of life generally, together with
the cough and expectoration. Here, as in other instances in which it is
desirable to continue the remedy for a considerable period, the doses
should be small and not increased. Noël Guéneau de Mussey testifies to
a remarkable efficiency in some cases of the mineral water of Bourbole,
either exported or taken at the spring.
Sulphur, especially as contained in the Sulphur Springs water, has long
been considered a useful remedy in phthisis as in other chronic
diseases. The Sulphur Springs of our country, however, although much
resorted to for other diseases, have not in phthisical cases with us
the celebrity which those in Europe (of which Des Eaux Bonnes are a
famous type) have with European physicians.
The symptomatic indications for medicinal treatment in cases of
phthisis are many and varied. Among the most important are those
relating to appetite and digestion. For the improvement of these
functions the preparations of cinchona, salicin, gentian, quassia, and
other of the vegetable bitter tonics, including nux vomica, may be
selected, according to the choice of the physician, or given in
succession. They have more or less efficiency in conjunction with the
more potential hygienic measures considered in connection with the
climatic, the dietetic, and the regiminal treatment. Pepsin and dilute
hydrochloric acid, taken after a meal, promote its digestion, their
medicinal action being, however, limited to the meal in connection with
which they are administered. The tincture of the hydrochlorate of iron
and other ferruginous tonics which are much used in cases of dyspepsia
and indigestion are useful in cases of phthisis. The anæmia which
exists so constantly in phthisical cases is an indication for their
use, and there does not seem to be ground for the conjecture which has
been entertained that they promote the occurrence of bronchial
hemorrhage. If they had this effect it would not disprove their utility.
Pulmonary symptoms which may furnish therapeutic indications are cough
and expectoration, hæmoptysis, pain in the chest, and dyspnoea. Cough
is of course necessary for the removal of the morbid products within
the bronchial tubes and cavities. If the act of coughing be accompanied
by expectoration, palliation is not required. But often there is what
may be called a superfluous cough—that is, not accompanied by
expectoration. This superfluous cough may be frequent, and occur in
violent paroxysms which occasion fatigue and exhaustion. Frequently the
cough prevents sleep. Palliative remedies are then indicated. It is
desirable, if possible, to palliate cough with remedies which do not
contain an opiate, owing to the impairment of appetite and digestion
caused by the latter. Simple remedies, such as the balsam of tolu, the
syrup of wild-cherry bark, Turlington's balsam, etc., may suffice. If
not, other narcotics than opium should be tried—namely, hyoscyamus,
lactucarium, and belladonna. Fothergill recommends hydrobromic acid and
the spirits of chloroform. The addition, however, of some form of
opiate is often required. The paregoric elixir is the simplest form,
and therefore the best if it suffice. Of other forms, perhaps codeia is
in general to be preferred. Patients should be enjoined not to prolong
voluntarily ineffectual coughing efforts. The disposition to cough may
in a considerable degree be controlled by the will until the morbid
products are in a situation to be readily expectorated. The stimulant
expectorants and those which act by causing nausea are not indicated in
cases of phthisis, and are objectionable in so far as they impair
appetite and digestion. Stimulating medicinal
inhalations are of
doubtful propriety, but a superfluous cough is sometimes relieved by
breathing some vapor, a little laudanum or paregoric elixir having been
added to the water vaporized. The continuous breathing of an atmosphere
charged with carbolic acid, either by diffusing it in an apartment or
the use of a respirator, is advisable if there be fetor of the expectoration.
It has been seen that bronchial hemorrhage is not, as a rule, an
unfavorable event in cases of phthisis. It does not follow from this
fact that the loss of blood is desirable, and therefore that the
hemorrhage should not be arrested. Moreover, the loss of blood in some
instances involves immediate danger. A first attack of hæmoptysis
occasions great alarm and anxiety. The prostration which appears is a
moral effect rather than the exhaustion caused by the loss of blood. In
repeated instances after attacks of hæmoptysis have several times
recurred, I have known patients to keep about as usual during an
attack, giving little or no heed to it.
The internal remedies which may be employed for the arrest of
hemorrhage are: Ergot or ergotin, acetate of lead, tannic or gallic
acid, and the astringent preparations of iron. Ergotin has been given
with good effect by subcutaneous injection, from five to ten grains in
water, with or without glycerin, being injected and repeated pro re
nata. Opium in some form should be conjoined in order to allay nervous
excitement. A teaspoonful of table-salt taken into the mouth and
repeated after intervals of a few moments is a well-known remedy during
the hemorrhage. The hemorrhage is sometimes so profuse and rapid that
much blood is swallowed, and may be afterward vomited. Under these
circumstances, and whenever the persistence of the hæmoptysis calls for
more prompt measures, cold may be applied to the part of the chest
which corresponds to the seat of the hemorrhage. This may be found by
means of a localized subcrepitant râle. Another measure is the
inhalation of a vaporized solution of the liquid persulphate of iron.
Still another and more potential measure is the temporary ligation of
one or more of the members of the body, the pressure being sufficient
to interrupt the flow of blood in the veins and not in the arteries.
This measure must be resorted to and continued only when the physician
is present. The effect is sometimes almost magical. The measure is a
substitute for venesection, which was formerly employed for the arrest
of bronchial hemorrhage. Cavernous hemorrhage, occurring usually late
in the disease, if profuse calls for prompt measures, and the topical
employment of cold will be likely to be the most promptly effective.
Pain in the chest denotes either pleurisy or intercostal neuralgia.
Mild counter-irritant applications by sinapisms or stimulating
liniments, with anodynes graduated to the degree of pain, are
indicated. Dyspnoea, if not caused by restrained movements of the chest
from pain, or by pleuritic effusion, or by an intercurrent pneumonia,
may denote either rapidity and extent of the tuberculous deposit or an
accumulation of morbid products within the bronchial tubes: if the
latter be the explanation, acts of expectoration are to be promoted.
This is not easily done if the difficulty of expectoration proceed from
great general debility. The ethereal stimulants, Hoffmann's anodyne,
chloric ether, and the compound spirits of lavender are advisable under
these circumstances as palliatives.
Pyrexia and increased frequency of the heart's action are symptoms
indicative of an active tuberculous cachexia. How far these are purely
symptomatic, and how far they may conduce to the progress of the
disease, cannot be determined with our present knowledge. It may be
assumed that they represent something more than is represented
generally by the fever which is secondary to a local inflammation. That
the febrile temperature is itself causative of changes in the tissues,
as well as in the functions of the body, is probable; and the muscular
power of the heart must be weakened by the
persistent frequency
of its action. A rational object in therapeutics is either the removal
or the neutralization of the morbid conditions on which the pyrexia and
the increased frequency of the heart's action depend. The means of
effecting this object are to be determined in the future, when more is
known of the morbid conditions giving rise to pyrexia; meanwhile, there
are certain medicines which, as experience shows, diminish the
temperature, and febrile temperature can be reduced by external means
which abstract heat from the body.
At the present time data are wanting for determining the importance of
antipyretic treatment in cases of phthisis. Hyperpyrexia, however, may
be considered as furnishing an indication for a trial of antipyretic
medication, and the most reliable of the drugs employed for that
purpose is quinia. It should be given for this object in full doses, as
in other instances in which it is given for an antipyretic effect.
These doses should not be continued long enough to disorder the
stomach. Diurnal exacerbations of fever, especially if ushered in by a
chill, may sometimes be arrested, or, if not arrested, materially
modified, by full doses of quinia, although there may be no ground for
the suspicion of malaria.
When the skin is hot and dry, with a high axillary temperature,
sponging the body may be employed and continued until the pyrexia is
diminished. I am not prepared to say whether the cold bath or the wet
sheet is admissible or allowable. As having some antipyretic effect,
and as diminishing the frequency of the heart's action, digitalis might
be expected to prove a valuable remedy to fulfil the symptomatic
indications under consideration. This drug was formerly much employed
in cases of phthisis. The fact that it has in a great measure fallen
into disuse may be taken as evidence that the theoretical
recommendations are not sustained by clinical experience. The liability
to disturbance of the stomach from its use is perhaps a sufficient
reason for considering it inapplicable.
The profuse night-sweating which so often occurs in the course of
phthisis claims treatment. Belladonna or atropia, the oxide or sulphate
of zinc, gallic acid, the acetate of lead, and aromatic sulphuric acid
are internal remedies for the palliation of this symptom. Sponging the
surface before bedtime with diluted alcohol, diluted acetic acid, or
with spirit in which alum is dissolved should be tried. Hot vinegar
largely charged with capsicum has been found to be an efficient
application. The covering at night should be as light as is consistent
with comfort. Brunton has found strychnine and nux vomica, given at
bedtime, useful. Another remedy, recommended by Murrell, is picrotoxin.
This is given in the form of a solution (1 part to 240 parts water),
the doses of from one to four minims daily, the last dose given late at
night.33 Agaricus, or the common toadstool, is recommended as an
efficient remedy by Wolfenden of London and J. M. Young of Glasgow.
From ten to twenty grains may be given in the form of an electuary with
honey, or it may be given in the form of a tincture. In both these
modes it is apt to cause nausea. This objection does not apply to the
isolated medicinal principle, a crystallized substance which it is
proposed to designate agaracine. Of this one-twelfth of a grain is a
dose, which may be repeated if required. Young is of the opinion that
it is not less effective than atropia as an antihydrotic remedy, and
not open to the same degree of danger from an overdose as the latter.
He has found it to act also as a soporific remedy, to relieve cough,
and to diminish the temperature of the body.34 A popular remedy is
cold sage tea taken at bedtime.
33 Vide Supplement to Ziemssen's Cyclopædia, 1881, p.
325.
34 Glasgow Medical Journal, March, 1882.
Of complications and associated diseases, one of the most frequent is
disease of the intestine. Of diarrhoea not thus connected the treatment
is that
of indigestion. As incident to tuberculous ulcerations
opium and astringents are indicated. Full doses of the carbonate of
bismuth, with a salt of morphia, will often prove an efficient
palliative. Peritonitis, acute and chronic, pleurisy with effusion,
chronic laryngitis, pneumo-hydrothorax, and cerebral meningitis are to
be treated according to indications which are considered in the
articles treating of these affections, making of course proper
allowances for their occurrence as secondary to the phthisical disease.
Intermittent fever associated with phthisis should be arrested as
promptly as possible. There is no foundation for the opinion which some
have held that malaria retards the progress of tuberculous disease.
Clinical facts show directly the reverse. If a perineal fistula occurs
in a phthisical patient, the safest policy is not to interfere with it
except so far as to make it as endurable as practicable. The idea that
a fistula has a salutary effect by way of revulsion has been one of the
reasons for making artificially an issue in the arm or elsewhere. This
was formerly much in vogue, but it has mostly, and probably deservedly,
fallen into disuse.
Medical opinion is sometimes asked concerning the propriety of marriage
with a phthisical man or woman. As an abstract question there need be
no hesitation as to the answer. If men went about deliberately
selecting wives, or vice versâ—as, for example, horses are
selected—there could be no doubt that phthisis should be considered a
disqualification. Husbands and wives, however, are not mated in such a
way. A marriage engagement has been entered into, and afterward one of
the parties becomes phthisical. The friends of the non-phthisical
party, not the parties themselves, come for advice, and the adviser is
sometimes placed in an awkward situation. With respect to the effect of
marriage on the tuberculous party, my analysis of 17 cases, 2 only
being women, did not show that it was unfavorable. Were it unfavorable,
considerations of sentiment and sense of duty generally outweigh all
others. A more important point relates to offspring. A hereditary
tendency is entailed in some, but not in all cases. The risk incurred
in this point of view having been fairly stated, the responsibility of
the medical adviser is ended.
After recovery from phthisis measures for the prevention of a relapse
should receive due attention. The hygienic influences which were
brought to bear on the disease, and which, as it is fair to conclude,
had more or less agency in effecting the recovery, are as far as
practicable to remain in operation. This important injunction applies
alike to cases in which an arrest of the disease has taken place, so
long as it ceases to be progressive. To prevent a renewal of its
progress is an object having a similar importance as the prevention of
a relapse after recovery.
In concluding the consideration of the treatment of pulmonary phthisis
reference is to be made to a measure to which one of our countrymen has
recently given much attention—namely, the injection of tuberculous
cavities. More than thirty years ago the late Brainerd of Chicago
related to me a case in which he made an opening through the chest-wall
into a tuberculous cavity. He had the idea that cavities might in this
way be treated by local applications with advantage. Of the result in
that case it is only recollected that no bad consequences followed.
Probably Brainerd did not prosecute further experimental observations,
as I am not aware of any publication by him on the subject. In 1873,
Mosler of Germany advocated making a free opening in tuberculous
cavities with a view to drainage and topical treatment. He reported 3
cases in which a drainage-tube was introduced and kept in the cavity.
The practicability of the operation and the absence of any evil result
were shown by his cases. The operation had been advocated and performed
prior to Mosler's publication, but without exciting consideration. To
William Pepper belongs the credit of injecting medicated liquids by
means
of a small syringe and hollow needles. Pepper has reported
12 cases in which cavities were thus injected. In these 12 cases two
hundred and ten injections were made. In no instance did any harm
result therefrom. The injected liquid in most of the cases was a very
weak solution of iodine. In some instances a weak solution of carbolic
acid was used. The objects are "the disinfection of the cavities, the
relief of cough, the diminution of secretion, and the modification of
the morbid action of the lining surface of the cavity, so as to favor
cicatrization and contraction and the prevention of infection of the
constitution." The results of the treatment in the cases reported by
Pepper go to show that it may contribute to these objects. His
observations have opened up a new and important department in the
therapeutics of pulmonary phthisis.35
35 For reports of Pepper's cases and other details vide
article in the Transactions of the American Medical Association, vol.
xxxi., 1880; also article in the American Journal of Medical
Sciences, October, 1874.
Fibroid Phthisis, Chronic Interstitial Pneumonia, Cirrhosis of Lung.
The characteristic anatomical feature of this variety of phthisis is
the predominant growth of the pulmonary connective tissue. If, as is
generally held, this hyperplasia be due to a chronic inflammatory
process, the name chronic interstitial pneumonia is not inappropriate.
From an analogy to the structural affection of the liver characterized
by an abnormal development of Glisson's capsule, the affection was
called by Corrigan cirrhosis of the lung. The propriety of regarding it
as a distinct form of pulmonary phthisis is based on points pertaining
to the morbid anatomy and to the clinical history.
An abnormal interstitial growth enters more or less largely as an
element into the morbid anatomy in cases of the ordinary form of
phthisis. It is the chief element in typical cases of fibroid phthisis.
The affected lung-structure is condensed and indurated, owing to
obliteration of alveoli and bronchial tubes. The affection leads to
notable diminution in volume. Resulting therefrom is a compensatory
dilatation of bronchial tubes. Sacculated dilatations may reach the
size of an English walnut or even a hen's egg. These are known as
bronchiectasic cavities. The pleura is thickened and the opposed
surfaces closely adherent to each other. With these distinctive changes
are usually found small cheesy tuberculous deposits or true tuberculous
cavities and miliary tubercles. The latter anatomical points show
relationship to the ordinary form of phthisis. Exceptional cases are
those in which the interstitial pneumonia is the result purely of the
local action of inhaled irritating particles (vide PNEUMONOKONIOSIS).
In these cases the tuberculous characteristics may be wanting. In cases
of fibroid phthisis both lungs are often affected. But the affection is
apt to be confined to, or much more extensive in, one lung, so that
during life it either is, or appears to be, unilateral. Exceptionally,
both lungs are extensively affected. It may originate in and be limited
to a lower lobe. It is stated by Trojanowsky that when the affection is
unilateral it oftener begins in the upper lobe, and when bilateral the
lower lobes are first affected. A series of bronchiectasic dilatations
may be so closely situated as to resemble an anfractuous cavity
resulting from the discharge of liquefied tuberculous deposits.
It is customary to consider this affection as occurring consecutively
to acute lobar and broncho-pneumonia, to chronic bronchitis, and to
pleurisy. Taking into view, however, the slow, insidious development of
the affection, the infrequency of its occurrence, and the frequency of
the diseases just named, a more rational conclusion perhaps is that
when these diseases are associated
with the phthisical affection
they are secondary to it. The affection occurs oftener after than
during the decade in which the ordinary form of phthisis is most apt to
occur—that is, after thirty years of age.
The course of the affection as regards activity of progress is
strikingly different from that of ordinary phthisis in a large
proportion of cases. Commencing imperceptibly, after it has advanced to
a certain extent it may remain apparently stationary, or it progresses
very slowly during a long period. Its duration may extend over many
years. In a case for a long time under my observation it existed
probably for forty years. If the lesions be not extensive enough to
interfere notably with the respiratory function, it may be tolerated
indefinitely. The appetite, digestion, and nutrition may be well
maintained. The muscular strength may not be much impaired. The
circulation, temperature of the body, and other functions may be but
little disturbed. A fatal termination, if not caused by some
intercurrent disease, takes place after a very gradually progressive
general debility and exhaustion.
As regards the different anatomical systems of the body other than the
respiratory system, it is not important to add to the foregoing sketch
details of symptomatology. The important symptoms referable to the
respiratory system relate to cough, expectoration, and disturbance of
respiration. The cough varies according to the quantity and character
of the matter to be expectorated, the difficulty of its expulsion, and
the susceptibility of the patient to the reflex influences on which
cough depends. The matter expectorated is muco-purulent, and in many
instances it is at times extremely fetid. This is due to the
putrescency of morbid products detained within the bronchiectasic
cavities and bronchial tubes, owing to difficulty in effecting their
expulsion. The fetor may be suggestive of gangrene. The matter
expectorated, however, if examined microscopically, will not be found
to contain the débris of pulmonary structure. There may be sloughing of
small portions of mucous membrane, but this is probably rare. The
expectoration after certain intervals of putrid sputa in considerable
or great abundance, the expectorated matter during the intervals having
the characters of muco-pus without fetor, is almost pathognomonic of
this variety of phthisis. The repeated occurrence of the putrid sputa,
the clinical history, and the physical signs render it easy to exclude
abscess of the lung. The detention of morbid products within
bronchiectasic cavities, and the consequent putrescent decomposition,
depend of course on the difficulty with which the contents of the
cavity are expelled. This difficulty is greater if the cavities be in
the lower than in the upper lobe. In a case which came under my
observation the affection had been known by the attending physician to
have existed for fifteen years. There was more or less habitual
expectoration of ordinary muco-purulent matter, but after intervals of
several days a considerable quantity of intolerably fetid matter was
expelled. In this case the physical signs showed the affection to be
limited to the lower lobe of the left lung. There was notable
retraction of the lower and lateral portions of the chest on this side;
solidification of lung was denoted by bronchial respiration and
bronchophony over the posterior aspect; and the cavernous respiration
was perceived over a circumscribed area in the latero-posterior aspect.
This patient's general condition of health was fair; he had not a
morbid aspect, and he was able to perform the duties of a clerkship in
one of the municipal departments.
The respirations are more or less increased in frequency, the increase,
other things being equal, being in proportion to the amount of damage
of the pulmonary organs, or, in other words, the extent to which the
respiratory function is compromised by the lesions. These may be
sufficient to give rise to much suffering from dyspnoea. This was true
of a case under my observation in which both lungs were extensively
affected, while the muscular
strength and the functions generally
of the body were not greatly impaired. The embarrassment of breathing
is increased by an accumulation of muco-pus within the bronchial tubes,
and notable relief follows expectoration of the accumulated products.
Hæmoptysis occurs in some cases, but much less frequently than in the
ordinary form of phthisis. The hemorrhage is sometimes profuse. It
proceeds from erosion of the walls of vessels or the bursting of small
aneurisms within bronchiectasic cavities.
Cyanosis is marked in some cases. This symptom is not always in
proportion to the dyspnoea; that is, the cyanotic appearance of the
prolabia and face may be present when the patient does not manifest
suffering from a sense of the want of breath. The cyanosis is
symptomatic of distension of the cavities of the right side of the
heart, this being an effect of the obstruction of the pulmonary
circulation. The obstruction may lead at length to dilatation of the
right ventricle and auricle. Thence arises the general dropsy which may
take place at an advanced period of the history of fibroid phthisis. A
tricuspid regurgitant murmur may be perceived with or before the
occurrence of dropsy; also visible pulsation of the cervical veins. A
frequent physical sign under these circumstances is bulbous enlargement
of the ends of the fingers and sometimes of the toes. The clubbed
fingers, as they are called, are symptomatic of disturbance of the
circulation. They are observed in some cases of disease of the heart,
phthisis not existing.
The physical conditions giving rise to physical signs are as follows:
Notable shrinkage of lung; solidification, which, if the lung be much
diminished in volume, may be considerable or complete in degree and
extensive; dilated tubes and bronchiectasic cavities varying in size,
number, and relative situations; the presence of muco-pus in more or
less abundance, the quantity variable at different times within the
bronchial tubes and cavities. Vicarious emphysema is more frequent than
in the ordinary form of phthisis.
In typical cases of extensive and advanced unilateral fibroid phthisis
the affected side is much contracted. The appearance is like that
presented in some cases after recovery from chronic pleurisy. The range
of respiratory movements is much diminished, the two sides presenting a
marked contrast in this regard. With this one-sided contraction of the
chest there may be lateral curvature of the spine, the concavity
looking toward the affected side. The supposition that the contraction
is in reality a sequel of chronic pleurisy is at once disproved by
finding the evidence of a degree of solidification notably greater than
would be incident to the mere diminution of the volume of the lung. If
the affection be limited to a lobe, either the upper or lower, there
may be contraction more or less marked over the portion of the chest
corresponding to the affected lobe. If the two lungs be much affected,
the evidence of contraction is apparent to the eye on both sides. It is
rarely if ever that the two lungs are equally affected.
The signs furnished by percussion and auscultation which represent
solidification of lung, the presence of air in dilated tubes or
bronchiectasic cavities and emphysematous lobules, are present either
separately or in various degrees of combination. Solidification from
induration without dilatation, sacculated or otherwise, of tubes, or if
these be filled with morbid products and without vicarious emphysema of
adjacent lobules, will give dulness on percussion more or less marked
and over an area corresponding to the degree and the extent of the
solidification. There may be flatness over the greater part or the
whole of an entire lobe. Often, however, dulness is found in some
situation, and either tympanitic or vesiculo-tympanitic resonance in
other situations. Over bronchiectasic dilatations a tympanitic
resonance may have the amphoric or the cracked-metal intonation. On
auscultation the respiration over a space more or less extensive or
within separate spaces of variable extent is either bronchial or
broncho-vesicular. With these respiratory signs
representing
solidification of lung are associated either bronchophony or increased
vocal resonance, and the corresponding whispering signs—namely,
whispering bronchophony and increased bronchial whisper. Over
bronchiectasic cavities, may be heard the cavernous respiration and
whisper. These signs of cavity may be combined with those of adjacent
solidification of lung, giving rise to the several varieties of
broncho-cavernous respiration. Coarse mucous or bubbling râles are of
frequent occurrence, and the accumulation of muco-pus within the
cavities may be represented by gurgling.
By means of the foregoing signs furnished by percussion and
auscultation the character of the lesions, their situation, their
extent, and the physical conditions as regards the presence of morbid
products within the air-cavities, are determinable. These lesions are
sometimes in striking contrast to the symptoms which represent the
general conditions of the patient—the pulse, temperature, emaciation,
etc. The symptoms and the physical signs may seem to conflict with each
other, owing to the remarkable tolerance of the disease in some cases.
To the physical changes which have been stated is to be added removal
of the heart from its normal situation. If the seat of the affection be
the left lung, its shrinkage may be such that the heart rises into the
infra-clavicular region, and the space within which it is in contact
with the chest-wall is larger than when the organ is in its normal
situation. The latter circumstance is to be borne in mind with
reference to the error of inferring therefrom enlargement of the heart.
Not only is the area of notable dulness on percussion over the heart
greater than in health, but the movements of the organ are remarkably
apparent to the eye and touch. If the right lung be affected, the heart
may be removed to the right of the sternum, the heart-sounds being
heard here with their maximum of intensity. In this abnormal situation
the presence of the heart may give rise to a notable dulness on
percussion, and its impulses may be both seen and felt.
The differentiation of fibroid phthisis from the ordinary forms of the
disease cannot be made with positiveness so long as the anatomical
changes are small or moderate in degree and extent. The chief
differential point is a greater degree of depression at the summit of
the chest than would be likely to occur at an early period if the
affection were of the ordinary form. If the affection begin at the base
of the chest, it is more likely to be the fibroid variety. In typical
cases, when the affection is unilateral and has led to notable
shrinkage of the entire lung, taking the physical signs in connection
with the evidence of tolerance afforded by the symptoms, it may be
differentiated with confidence. Age is to be taken into account in the
diagnosis; patients are rarely under forty. The expectoration from time
to time of fetid mucus has considerable diagnostic significance.
With reference to the diagnosis, it is to be considered that between
the ordinary form of phthisis and typical cases of fibroid phthisis
there is every degree of gradation as regards the combination of the
anatomical characters of both. There is no sharp line of demarcation
between the two varieties. In these intermediate cases to determine by
means of the symptoms and physical signs the relative proportion of
each variety is not practicable, nor is this a matter of much practical
importance. It may be added that the coexistence of chronic laryngitis
and of tuberculous disease of the intestine is proof against fibroid
phthisis. There is no possibility of the restoration of a lung affected
with fibroid phthisis to its normal condition; but the prognosis as
regards tolerance, arrest of progress or slowness of progress, and
consequently duration of life, is much better than in the ordinary form
of phthisis. On this account the diagnosis is of importance. The
prognosis is better the nearer the approach to the affection in typical
cases. Per contra, the prognosis is less favorable in proportion as the
changes characteristic of the disease in its ordinary form are
associated with those characterizing fibroid phthisis. If the affection
be
confined to a lower lobe, it may not extend beyond this limit,
and the persistence of solidification of the affected lobe may not be
incompatible with good general health. Of these facts the following
case is an illustration: Phoebe, aged five years, came under my
observation in 1864. There was at that time notable dulness on
percussion over the lower lobe of the left lung, with bronchial
respiration and bronchophony. She had cough and expectoration, but had
not been confined to the bed or house, and her general condition of
health was then fair. The treatment consisted of tonic remedies and
out-of-door life. I saw her repeatedly during the next two or three
years, the physical signs remaining the same, and the general health
fair. In 1869 she had chorea and was treated with Fowler's solution. I
did not see her again until October, 1871; she had then, and had never
been free from, some cough and expectoration, but her general health
had been maintained. The signs of the solidification of the lower lobe
of the left lung were then present, the upper lobe remaining
unaffected. In November, 1874, I noted that I had again seen her and
examined the chest. The dulness on percussion over the lower lobe of
the left lung continued; there was at this time absence of respiratory
sound over this lobe, but the vocal resonance was greater than on the
opposite side. The left side was considerably contracted. She had still
some cough and expectoration, and there was some deficiency of breath
on active exercise. Her aspect was healthful, and she was well
developed for her age (fifteen years). Menstruation was irregular. She
consulted me for this irregularity, not regarding herself as ill in
other respects. About six years afterward I met her in the street, and
she accosted me. Her appearance was healthful.36
36 This patient remains in fair health at the present time,
May, 1883, nearly twenty years after she first came under my
observation.
The treatment in cases of fibroid phthisis differs in no essential
points from that in cases of the ordinary form of the disease. The
slowness of progress and the long duration show less activity of the
tuberculous cachexia. Nevertheless, the cachexia either exists or has
existed, and the measures relating thereto which have been considered
as belonging to the dietetic and regiminal treatment are alike
applicable to both varieties of phthisis. The circumstances which
render changes of climate admissible, if not advisable, are much
oftener present in the fibroid variety, and there is greater
probability of the disease being either arrested or retarded. Medicinal
treatment is to be employed with reference to therapeutic indications
alike in both varieties of the disease.
The treatment by inhalations to prevent putrefactive changes in the
contents of bronchial tubes and in cavities is oftener indicated by
fetid sputa in cases of fibroid phthisis. The continuous breathing of
the atmosphere of a room containing an antiseptic vapor requires the
patient to remain within doors. A more effective method is to make use
of a respirator inhaler. A portable and convenient instrument, worn
over the mouth like an ordinary respirator, has been devised by W.
Roberts and improved upon by H. Curschmann. In this instrument the air
which is breathed passes through layers of tow moistened with the
antiseptic liquid. The disinfecting agents which have been found
efficient are carbolic acid, creasote, oil of turpentine, a mixture of
the tincture of iodine and the compound tincture of benzoin and
thymol.37
37 Vide article by William Pepper in Transactions of the
American Medical Association, vol. xxxi., 1880.
The number of deaths throughout the globe which are caused by pulmonary
phthisis vastly exceeds the number caused by any other disease.
The etiology of pulmonary phthisis embraces largely causes which can be
removed. Hence the disease is to a great extent preventable. Are any
comments on these simple statements needed in order that the prevention
of phthisis may be regarded as among the most important of the subjects
belonging to preventive medicine?
It has been assumed that phthisis involves a predisposition which is in
most, and perhaps in all, cases innate. Putting aside all questions
relating to an acquired tuberculous diathesis, it may be assumed that
the development of the phthisical affection depends in many or perhaps
in most cases, more or less, and probably often in a great measure,
upon causes which promote the diathetic condition. Now, many of these
causes are removable, and if removed phthisis is prevented, and the
prevention of a disease which may properly be called a scourge of the
human family will be diminished.
Of removable causes may be mentioned humidity of the soil in places of
residence; living in small unventilated dwellings; confinement within
doors; breathing in close workshops or factories, and in overcrowded
rooms at night, an atmosphere deficient in oxygen and contaminated with
pulmonary and cutaneous emanations; working underground in mines from
which light as well as pure air is excluded; a deficiency of food
sufficiently wholesome and varied; impairment of the cutaneous
functions from uncleanliness; and want of a proper adaptation of
clothing to the climate or season. These are obvious violations of the
hygienic requirements for health. It is unnecessary to cite facts to
show to what extent these violations prevail in different countries.
They are causes which admit of removal, however difficult may be the
task. Connected with their removal are other considerations than the
prevention of phthisis. But confining the attention exclusively to the
latter object, how incalculable would be the saving of life and health
were these causes to be removed! Much has been done within the last
half century toward diminishing the mortality from phthisis by
advancement in pathological and therapeutical knowledge; how much more
remains to be done by preventive measures!
The prophylaxis against phthisis must date from birth. An infant should
not nurse a mother who is consumptive or whose milk is of poor quality.
Care is to be observed in the selection of wet-nurses. All the various
articles which are sold under the name of infants' food should be
discarded. Many of these are fraudulent; that is, they are not what
they purport to be. But admitting that, if properly prepared, they are
safe substitutes for milk and the simple farinaceous foods, there can
be no guarantee for their proper preparation; and the risk is too great
to rely upon articles which cannot be readily tested and for the
genuineness of which dependence must be placed on irresponsible
dealers.38 There is need of much caution respecting the purity of
milk, especially in cities. Much harm is not infrequently done by
over-care in children's diet—that is, by denying articles which they
crave, and restricting them to those which they do not like. In this
matter the instincts are not to be set aside, especially in early life,
when perversions of appetite and taste have not been acquired. Not
infrequently from undue caution the quantity of food is restricted, and
children suffer from insufficient alimentation; this is more likely to
occur in our country among the wealthy than among the poorer classes.
Other prophylactic provisions pertaining to exercise, out-of-door life,
clothing, etc. need not here be considered.
38 Vide "Address by A. Jacobi on Infant Diet," Transactions
of the New York State Medical Society, 1882.
In order to combat the various causes which have been named, knowledge
of hygienic laws must be diffused among all classes. There is a
lamentable lack of information and of interest as regards matters of
hygiene among the more intelligent classes. But it is not sufficient to
enlighten these: the
knowledge must be extended, as far as
practicable, to those who, in this point of view, are lower in the
scale. Many persons of wealth fall in this category. The causes which
are purely personal can be reached only by information diffused by
means of publications, lectures, and intercourse with medical men and
others. Here is a rich field for missionary labors. To overcome certain
of the causes, however, the intervention of legislative authority is
necessary. With reference thereto health boards, properly constituted
and invested with adequate powers, should be organized in States,
counties, and cities. In this way it is practicable by the prevention
of phthisis to lessen greatly the rate of mortality.
Protection against the communication of the disease requires to be
specially noticed. Occupying the same bed with phthisical patients and
sleeping in the same room, if the latter be not enjoined by the
dictates of humanity, are objectionable. They are to be objected to on
the score of unhygienic influences, physical and moral, irrespective of
the doctrine of a tuberculous contagium, and of course still more in
view of the probabilities in favor of this doctrine. Care should be
taken to exclude from the table the meat of tuberculous animals. In
addition to the purity of milk in other regards, it should be
ascertained that the supply is not from cows affected with tuberculous
disease. Obviously, this is especially of importance with reference to
infants who are bottle-fed and in childhood, when generally milk forms
a much larger proportion of the diet than in after years. The
ventilation of apartments occupied by phthisical patients should be
attended to with reference to the possibility of the disease being
communicated by the inhalation of particles of tubercle; and it may not
be a needless precaution to introduce a disinfectant into the vessels
which receive the matter expectorated.
DEFINITION.—Lesions of the lungs with a syphilitic impress include
catarrhal inflammation of the bronchial mucous membranes, chronic
inflammatory new formations, which affect especially the connective
tissue, producing sclerosis or else gummatous growths.
HISTORY.—From the early part of the eighteenth century attempts have
been made to create a word-portraiture representing the peculiar
features of syphilitic pulmonary disease as a separate entity. It has
been defined histologically and clinically from simple and from fibroid
phthisis, or from cases of syphilis in which a damaged state of the
general health has fostered the development of phthisis. But the
question, Is there a peculiar microscopic and macroscopic anatomy, or a
special symptomatology by the aid of which the cause, seat, and
dissemination of pulmonary syphilis can be recognized? remains even now
but partially removed from the field of debate and conjecture, although
unquestionably the syphilitic poison bears intimate relation with
various pulmonary processes.
ETIOLOGY.—Predisposing and Exciting Causes.—Syphilis of the lungs is
a rare disease as compared with the forms of specific laryngitis, but
even here Leman asserts that there is an early simple catarrh of the
larynx indistinguishable from the specific catarrhs. Whistler, in
recording his observations upon 88 cases of the lesions found in
syphilis of the larynx, observes that catarrhal congestions in early
laryngeal syphilis simulate the same lesions from ordinary causes.
Schnitzler lays particular stress on the association of pulmonary
syphilis with affections of the larynx and a specific bronchitis which
may occur in the first two months after inoculation. Many other writers
on this subject assert that laryngeal and bronchial catarrh attend the
period of early skin eruptions, disappearing in consequence of an
antisyphilitic treatment.
The rarity of pulmonary syphilis has been further attested by the
observations of Greenfield, who states that out of 22 cases of visceral
syphilis, only 1 occurred in the lung and 4 in the larynx and trachea:
in these cases, while the dura mater and cerebral vessels were
extensively diseased, no trace of skin affection could be found.
Goodhart has collected from the post-mortem records in Guy's Hospital
during twenty-two years 189 cases of visceral syphilis, but in only 38
of these chronic lung disease occurred. Phthisis associated with
syphilis is usually a late secondary or tertiary process, which appears
from two to five years after the infection; in rare cases ten—even
twenty—years have been said to elapse before the supervention of
pulmonary trouble. Cases of phthisis associated with syphilis have,
however, been described as occurring within the first twelve months
after infection. Further investigation may establish these cases of
early pulmonary syphilis as attributable to violent systemic infection,
or their etiology may be involved in the deterioration of the general
health which sometimes occurs. Moreover, one
must remember that
simple phthisis may more readily be developed in the scrofulous
syphilitic, owing to the predisposition of such persons to catarrhal
forms of inflammation. In the progress of syphilis there is also a
tendency to catarrhal processes through anæmia and damaged general
health, which may predispose certain cases to an ordinary type of
phthisis. The origin of the new formation in both tubercular and
syphilitic phthisis is similar—viz. the arterial, lymphatic, and the
peribronchial sheaths, spreading thence to the interlobular connective
tissues. It is therefore not surprising that it has been difficult to
differentiate the tubercular from the specific forms of phthisis, and
Goodhart asserts that there is no histological difference between
syphilitic and tubercular phthisis, except that the former is more vascular.
We may assume that true pulmonary tuberculosis may be associated with
syphilis, but preserves its own pathological characters; that, although
we are ignorant of the exact differential histological changes, there
is sufficient evidence to show that there is a distinct association
between syphilis and pulmonary disease; and that syphilitic phthisis is
commonly interstitial. Whether the relation be one of cause and effect,
or whether the process is simply a modification of ordinary tubercular
phthisis, it is impossible at present to determine. The final
adjustment of the theories concerning the specific etiology of
tubercular phthisis may throw further light upon the etiology of
syphilitic phthisis. That gummata may be found in the lungs is a
well-established fact, and by some authorities is not considered rare.
The discussion of the etiology has already indicated the relation of
the predisposing and exciting causes to pulmonary processes in
connection with syphilis. In certain cases of syphilis the antecedent
of pulmonary changes is a laryngeal or bronchial catarrh. The relation
which an active virus in the blood sustains to the process is still
subject to debate. Hutchinson writes as follows: "If the infected blood
were the cause of the local phenomena, it is almost certain that such
phenomena will be symmetrical, because the blood is equally supplied to
both sides; such is the case during the secondary stage. If, however,
the symptoms result from tissue-conditions, and the blood is at the
time of the outbreak free, then there is a considerable probability
that local influences may take a large share in evoking them, and they
will be asymmetrical—evoked by some local cause."
The existence of gummata, then, does not necessarily show that there is
any active virus in the blood, because their formation is sometimes
symmetrical, sometimes asymmetrical.
PATHOLOGY AND CLASSIFICATION.—The lesions of pulmonary syphilis may be
divided into four classes: (a) early phthisis, associated with
principal interlobular proliferation; (b) advanced syphilis, in which
gummatous or allied formation exists; (c) simple phthisis, developing
in consequence of impaired general health induced by syphilis; (d)
inherited or congenital syphilis, occurring in infants.
(a) The pathological process in the majority of cases in the adult is
interstitial new formation, very often evoked by antecedent catarrhal
inflammation. At first small spindle-shaped and round cells appear and
develop into connective tissue, among the fibres of which blood-vessels
are freely produced; the septa of the alveoli are thickened and the
alveoli themselves compressed. In any morbid process in the lungs, such
as tubercle, sarcoma, or cancer, the alveoli act as the
inter-fascicular spaces of the connective tissue. In the same manner in
syphilis the alveoli of the lungs are always in the later stages, and
sometimes primarily, more or less filled with small cells, which,
surrounded by the newly-formed connective-tissue fibrous framework,
gives the appearance of some of the forms of simple phthisis. The
smaller bronchi become narrowed, and perhaps occluded, by the pressure
of the new growth which develops along their lumen. Occlusion of the
bronchi may also be caused
by enlargement of the bronchial
glands, which is one of the incidents of the syphilitic pulmonary process.
If we endeavor to nucleate the peculiar impress attributed to early
syphilitic pulmonary processes, we find much that is vague. The
vascularity and advanced grade of organization of the new growth are
considered by Greenfield and Goodhart to be characteristic when
compared with tubercular consumption, in which the original growth is
bloodless and the tendency is to retrograde metamorphosis. Green and
Virchow suggest that the origin of syphilitic diseases of the lungs is
distinctive in this respect, that while in the ordinary forms of
phthisis the fibroid is secondary or coequal in its development with
changes in the alveoli and alveolar wall, in syphilis there are
primarily interstitial changes. In chronic bronchitis the fibroid
thickening proceeds from the bronchi. Wagner, however, maintains that
implication of the alveolar wall is as common in syphilis as in
ordinary phthisis.
In the general pathology of syphilis the change in the intima of the
blood-vessels is characteristic: this has not yet been demonstrated in
the lung, but merely the general thickening of the external coat of the
vessels. When entire vesicular consolidation and breaking down occurs,
the process is similar to ordinary phthisis, and indistinguishable from it.
(b) In the gummatous stage the same formation of cellular and
connective tissue is found as in the diffused form, with which gummata
are often associated. Gummata may originate anywhere in the
intervesicular tissue, usually near the visceral pleura. Sometimes they
are formed near the roots of the lungs, intimately connected with the
blood-vessels and bronchial sheaths. They may also be formed in the
deeper layers of the costal pleura or upon the periosteum of the ribs.
Owing to the peculiar anatomical formation of gummata, their subsequent
history is one of combined caseous and fatty degeneration. These
centres of softening may communicate with a bronchus, more or less
rapid evacuation of the mass may occur, and a cavity be formed which
often enlarges as the gummata break down. Contraction may ensue,
leaving a small fibrous scar with cheesy cretaceous deposit, or the
gummata may point externally, with or without the appearance of
inflammation in the adjacent tissues, or they may remain stationary for
an indefinite period. In some cases the pulmonary new formation may be
a combined interstitial, gummatous, and catarrhal process; but, as a
rule, the fibroid process of syphilis in the earlier stages is not
accompanied by the filling of the alveoli with catarrhal cells. Gummata
developed in or near the pleural sac may increase in size, and by
compressing the lung simulate pleural effusions.
(c) The morbid anatomy of cases in which simple phthisis develops in
consequence of the vulnerability of the pulmonary tissues to the
exciting causes of bronchial inflammation requires no special consideration.
(d) Interstitial inflammation, gummata, and enlargement of the
bronchial glands have been found in the syphilitic foetus and in very
young children. It is also claimed that syphilitic disease of the lung
may be one of the forms of tertiary disease which develop in children
between the second dentition and maturity. Virchow and Lebert have
described pulmonary gummata in children suffering from inherited
syphilis. Depaul gives the cases of two children with pemphigus who had
soft puriform nodules or collections scattered through the lungs. In
the infant lung the highly cellular character and ready reversion to
the embryonic type of structure would naturally lead to exuberant
growth and rapid diffusion of the morbid process, which could not occur
in the more fibrous, less cellular lung of the adult. Hence the slower
growth in the latter establishes the more fibrous and limited extent of
disease: in other respects the origin and distribution of the growth
are identical in both cases. In the infant enlargement of the bronchial
glands
and bronchitis leading to broncho-pneumonia, or an unusual
proliferation of epithelium in the alveoli, is more frequent than in
the adult.
MORBID ANATOMY.—In the earlier stages of pulmonary syphilis the
macroscopic appearance of the lung is firmer at the seat of deposit
than elsewhere. It is also heavier and has a smoother surface. The
infiltrated parts are grayish-red or grayish-yellow, smooth, and
homogeneous. Sometimes the appearance resembles pale-whitish patches
invading districts of the lung. The hyperplastic material becomes
converted into a tough, contracting, fibrous tissue, which radiates
through the lung, drawing together the bronchial tubes and flattening
them, possibly even to obliteration. The entire lung may be involved,
but the changes most frequently proceed from the hilus of the organ
into the interior, following the track of the bronchial radicles and
the bronchial and pulmonary arteries. The lesions frequently develop
near the visceral pleura, where there is more connective tissue. This
accounts for the depressed puckered scars which are found on the
pleural surface.
The macroscopic appearances in specific pulmonary disease differ,
according to Goodhart, "both from a chronic pneumonia and from that
solidification ensuing after contraction of the lung from old pleurisy,
in that it is less evenly distributed, and generally less widely spread
over the lobe, than they. It is nodular, rather diffused, and more
symmetrical than unilateral. From miners' phthisis the appearance
differs in the absence of the extreme dilatation of the bronchial tubes
and more solidity from greater growth. The tissues involved are more
tough and less granular than red or gray hepatization." It is possible
to differentiate other forms of fibroid phthisis by noting, in addition
to the above points, the presence of the syphilitic process in other
viscera, and by comparing the clinical records with the post-mortem examination.
Syphilitic lesions may be found in any part of one or both lungs, but
their localization at definite points in the lungs, leaving the balance
free even when the lesion has proceeded to formation of cavities, may
be characteristic. There is, however, a wide division of professional
opinion upon the subject of the localization of the process in
syphilitic pulmonary disease; some claiming the middle lobe, some a
symmetrical lesion at the apices, others lesions at a definite point
elsewhere than at the apices. If the pulmonary lesions are introduced
by an attack of pleurisy, the process in the lungs is usually located
at one or both bases. Some, however, locate the disease at the base,
without mentioning an antecedent pleurisy.
Gummata are more frequently situated in the middle or lower lobes of
one or both lungs, and are defined by a boundary layer of fibrous
tissue. Fibroid development may ensure their adhesion to the visceral
and costal pleura. They are gray or yellowish-gray, hard, well-defined
nodules, of varying size and number, occurring as single large masses
surrounded by normal or compressed lung. In the centre is found a
diffluent material, not unlike the centre of a scirrhous nodule,
similarly enclosed in a limiting fibrous investment from an inch to
many inches thick. In the condition of the neighboring pulmonary
substance a difference may be observed between gummatous and
tuberculous nodules: the latter occur in more numerous masses, usually
small, and the entire lung is more or less diseased; while in syphilis
extended districts of non-affected lung occur in the neighborhood of
gummata. Whenever gummatous lesions in the lungs exist a history of
pustular eruptions, laryngitis, arterial lesions—in fine, some
indication of general systemic syphilitic poisoning—can always be
found. Fournier thinks there are five anatomical points of distinction
between syphilitic gummata and tubercle: "1. Tubercle involves the
upper part of both lungs; gummata one lung, and may be limited to a
portion. 2. Gummata are few as a rule, solitary; tubercles sooner or
later become confluent. 3. Gummata are larger than tubercles, never
miliary in form. 4. Gummata are always yellow or white, never
transparent like miliary tubercle. 5. Until softening takes place
gummata are of more equal consistence than tubercles, and if they
soften do not break down, wholly owing to the capsule. Histologically,
there is no difference in structure." Gummatous formations may be found
on the pericardium and heart and in the thoracic and abdominal walls.
Clinically, the most important pathological feature is that large
districts of healthy lung are interposed between the affected
districts; this is not so in ordinary phthisis.
Bronchial Lesions.—The syphilitic like the scrofulous are predisposed
to catarrhal inflammation, and this may spread down the bronchial
tubes, giving rise to a general bronchitis; a coexistent laryngitis may
or may not exist. Enlargement of the bronchial glands is frequently
combined with the syphilitic pulmonary process. When the glands are
enlarged they present a firm pigmented character, varying in size from
a hazelnut to an egg, and the connective tissue surrounding them is
usually infiltrated. Subsequently, owing to the pressure of the
mediastinal growths, the bronchi are narrowed and more or less
occluded; the same effects are occasioned in the smaller bronchi by the
pressure of the new growth which develops along their lumen. The
effects of bronchial narrowing or occlusion produce serious mischief in
the lungs proportioned to the degree of obstruction. By the retention
of the bronchial secretions the air-supply to the vesicles is
interfered with; emphysema with or without asthmatic symptoms or
atelectasis may ensue. Further, the results of bronchial narrowing
affect the circulation through the lungs, and in combination with
atelectasis very intractable local bronchitis may be developed; and,
with or without atheroma, hemorrhagic infarctions may occur, with a
form of pneumonia which has been described by Fuchs as apneumatosis.
The narrowing of the bronchial tubes in specific fibroid phthisis
affords a means of differentiating this disease from non-syphilitic
fibroid phthisis, in which the tubes are widened. Cases have been
reported of nodules of syphilitic new formations in the mucous membrane
of the superior and inferior extremities of the trachea and larger
bronchi. The nodules ulcerate, and in healing cicatricial bands of
fibrous tissue are formed which cause contraction of the tracheal tube
transversely or diminish its length. These lesions resemble tuberculous
ulceration, but they differ in the nature of the initial neoplasm by
the formation of cicatricial tissue and by the tendency to stenosis of
the tracheal tube. The cutaneous syphilides, mucous patches, the
exostoses of the bones of the cranium help to demonstrate the
connection of the marked cachexia with syphilis rather than scrofula.
SYMPTOMATOLOGY.—As the pathology of syphilitic pulmonary processes is
intertwined with the pathology of many other forms of phthisis
pulmonalis, so the symptoms must be common to those obtaining in other
forms of pulmonary disease. They are insidious and gradual in their
development, and may be classified as the subjective, the physical
signs, and the objective phenomena. The subjective symptoms may be
present without noticeable departure from an appearance of health.
There may be difficult respiration with more or less dyspnoea,
especially in the mornings and evenings, besides a sense of heaviness
and oppression in the chest, with a feeling of inability to inflate the
lungs. These symptoms may be increased on exertion, respiration
becoming wheezing, with imperfectly-developed asthmatic attacks.
Hoarseness, with varying degrees of aphonia, more or less dysphagia or
unequal pupils, may be present. Nearly all of these symptoms may be
accounted for as indicative of mediastinal pressure or irritation of
the pneumogastric nerve by the enlargement of the bronchial glands. The
catalogue of phenomena may be present in whole or in part, and the
intensity of their manifestations may vary from time to time in the
history of a single case. If the bronchial glands are much enlarged, a
sense of discomfort, oppression, and uneasiness
at the root of
the neck may be experienced, which increases until actual pain is felt,
located in the back between the scapulæ, but sometimes radiating
through the intercostal nerves around the chest. Cough, as a rule, is
an early symptom, usually dry, paroxysmal, and associated with
dyspnoea, or there may be bronchial catarrh, with a relative amount of
expectoration. Syphilitic disease of the larynx may occur coequal with
the pulmonary trouble, and some of the above symptoms may be thus
explained and many others added. Rheumatic and nervous symptoms,
including sleeplessness and deterioration of the blood-crasis, may
testify to the syphilitic infection of the blood.
When a physical examination of the chest is instituted, thickening of
the head of the periosteum of one or both clavicles, substernal
tenderness, thickening of the tibial periosteum, are usually detected.
Prominent among the physical signs are the evidences of enlargement of
the bronchial glands. According to Guéneau de Mussey, percussion over
the spinous processes of the cervical vertebræ in the course of the
trachea reveals in a healthy subject a distinct tubular sound down to
the point of bifurcation of the trachea at the level of the fourth
dorsal vertebra. Opposite the fifth and downward we get the
lower-pitched pulmonary resonance. When the tracheal and bronchial
glands are enlarged, the tubular sound over the upper dorsal vertebra
is replaced by dulness, which may contrast sharply above with the
tracheal and below with the vesicular resonance.
The respiratory murmur will be feeble in volume and limited to
inspiration, especially over the interscapular region. Over one or the
other bronchus the respiratory murmur may be more high pitched than in
health, and slightly exaggerated on one side or at the base of the
chest. The rhythm is often jerky and paroxysmal; the paroxysms are more
or less constant, but are liable at times to increase.
The additional physical signs in syphilitic phthisis, unassociated with
gummata, are those shared by other forms of fibroid phthisis, and do
not require particular description here, as increasing dulness, varying
degrees of bronchial breathing, and bronchophony. A peculiar alveolar
rustle, resembling the sound produced by the rumpling of wall-paper,
has been alluded to as characteristic.
Inspection or palpation sometimes reveals changes in the contour of the
chest, with displacement of the movable thoracic viscera, as in fibroid
phthisis. When cavities occur, the physical signs necessarily
correspond to those of other varieties of phthisis at this stage.
When a gumma is large enough to be recognized by physical examination,
one finds dulness or flatness on percussion, confined to a section of
the chest, and not occupying its semi-circumference, as in pleural
effusions. The vocal fremitus is suppressed in proportion to the size
of the gumma. The respiratory murmur is abruptly cut off over the area
of flatness, but it may be only distant bronchial breathing. The vocal
resonance is absent or is distant bronchophony. Around the gumma the
respiratory murmur is usually very feeble or scarcely audible,
generally without râles unless they are due to neighboring congestion.
The percussion resonance is good or exaggerated. Proportionate
vicarious functional activity prevails in the opposite lung. If the
gumma be large, the heart's impulse may be displaced to the left or
right, and dyspnoea may occur as in case of pleural effusions. In this
stage, owing to irritation of the bronchial mucous membrane, there may
be expectoration of a tough, glairy mucus, or as a gumma softens the
expectoration may become purulent.
The objective phenomena vary: the chest is often well developed, the
body fairly nourished, and constitutional symptoms of a severe
character may be wanting. The patient may be capable of hard physical
labor, even though a
considerable part of the lung be affected.
Moxon relates a case of a man "employed in carrying sacks of grain who
was suddenly killed, and who had fibroid infiltration of a great part
of the left lung and part of the right, and besides scars in his liver
and testes." But in some cases the complexion is pallid and waxy,
indicative of cachexia associated with digestive disorders, with
night-sweats, and a variable but low thermometrical record. Usually,
the progress of the disease is slower in syphilitic than in tubercular
phthisis, but when the systemic poisoning is grave and many other
organs are coincidently involved, the progress is more rapid; but the
process peculiar to syphilis is often past, and the patient suffers
from simple catarrhal phthisis with formation of cavities and softening
gummata. Diarrhoea and night-sweats are said to be less frequent than
in ordinary phthisis, and the pulse is slower. Hæmoptysis occurs
infrequently, because the process in the lungs is chiefly fibroid; but
it is possible through the rupture of newly-developed blood-vessels in
the new formation in the lung or hemorrhagic infarction through the
rupture of atheromatous vessels.
DIAGNOSIS.—This depends mainly on the history of the cases, the prior
or coexisting syphilitic lesions, especially laryngeal processes,
cutaneous syphilides, exostoses, perforation of the palate, substernal
tenderness, and the thickening of the tibial periosteum or that of the
head of one or both clavicles. Family immunity from phthisical
tendency, recovery from lesions usually incurable if they have any
other than a specific origin, are suggestive of pulmonary syphilis. If
a patient retains flesh and strength beyond the natural expectation
considering the serious lesions of the lungs, the fact is of relative
importance when considered in connection with the other diagnostic
features. The distribution of specific lesions is variously located by
different authors. Grandidier found induration affecting the middle
lobe of the right lung in 27 out of 30 cases believed by him to be
specific phthisis; the surrounding lung contained large areas free from
disease. This tendency to localization in portions of the lungs,
leaving large areas free from disease, is of value in diagnosis.
PROGNOSIS.—The prognosis is involved in the discovery of syphilis as
the cause of the disease and on the subsequent appropriate treatment.
Grave and important specific lesions, according to some authors, have
yielded to the resources of art. Fournier has recorded a case where
"dulness at the summit of the left lung was extensive and signs of a
cavity distinct. After six weeks of antisyphilitic treatment recovery
was almost complete. In this case the presence of a phagedenic ulcer of
the foot was the only sign that suggested syphilis, the symptoms of the
pulmonary affection being identical with those of tubercular phthisis."
The principles presiding over the prognosis of the various stages of
pulmonary diseases in general are applicable to syphilitic pulmonary processes.
TREATMENT.—When a case of pulmonary lesion presents itself, unless the
existence of tuberculosis be demonstrated, we must ascertain if the
symptoms can possibly be due to syphilis, and the line of treatment
indicated in any single case must be based upon an estimate of the
prominence of the specific process. The ravages of syphilis, however,
often produce such loss of substance in the lung that the lesions are
irreparable, and therefore we cannot always accomplish the brilliant
results which usually attend an antisyphilitic treatment. If there is
evidence of enlarged bronchial glands, in addition to other measures
local counter-irritation is useful by means of the biniodide of mercury
ointment, 16 grains to the ounce, and applied for a continued period,
or a preparation of iodine with croton oil may be tried. In the main,
the general principles of treatment correspond with those recognized in
similar forms of pulmonary disease of a non-specific etiology.
DEFINITION.—A generic term applied to pulmonary diseases due to the
inhalation of particles of irritating dust.
SYNONYMS AND CLASSIFICATION.—The synonyms and classification of
pneumonokoniosis have been based upon the character of the dust
inhaled, using such terms as anthracosis ([Greek: anthrax], coal),
disease due to coal-dust; siderosis ([Greek: sidêros], iron), due to
metallic dust; chalicosis ([Greek: chalix], gravel or pebbles), due to
mineral dust; tabacosis, due to tobacco-dust; and byssinosis ([Greek:
byssos], cotton), due to cotton fibre and dust. A more imperfect
classification has been derived from the avocations of the sufferers;
for example, miners' phthisis, Sheffield grinders' rot, potters'
consumption and asthma, freestone-hewers', masons', or millers' lung.
HISTORY.—From the early experiments of Cruveilhier, who injected
mercury into the system and subsequently noted the pulmonary changes,
down to the experiments of the present day, evidence has accumulated to
show that inorganic irritant materials are capable of exciting
inflammatory new formation in the lungs. The difference between the
changes produced in the lungs by experimental processes and those
occurring after the inhalation by artisans of inorganic materials
consists in degree rather than in essential character. In
pneumonokoniosis the pulmonary processes are gradually developed, and
consequently the ensuing changes in the tissues represent those usually
associated with the more chronic forms of pulmonary lesions, and may
not only occasion phthisis, but during years of life may cripple the
sufferer by engendering chronic catarrhal processes in the mucous
membranes, complicated by emphysema or asthma.
ETIOLOGY.—Predisposing Influences.—Atmospheric dust is composed of
organic and inorganic matter, and both have been demonstrated by many
admirable experiments to be very widely diffused in the air we breathe.
In most instances the injurious action of inorganic dust is augmented
by the conditions of imperfect ventilation under which it is inhaled,
because the amount of dust deposited in the lungs is thereby increased.
Illustrations of this fact can be found in various avocations,
particularly among miners. The injurious action of dust inhaled when
there is imperfect ventilation is increased in proportion as there is
deprivation of sunlight, both conditions tending to lower the vitality
of the artisan. Again, the rigor of confinement of parents engenders a
sickly or scrofulous constitution which is transmitted to their
offspring, causing great mortality among the children of artisans,
especially where they, in turn, are subjected to unfavorable environment.
When work is performed in constrained or stooping positions, or when
proper inflation of the chest is not secured, the liability to
pulmonary disease is increased.
The foregoing conditions having been considered, the injurious action
of dust upon the lungs is in proportion to the quantity deposited in
them. The
entrance of dust is, however, physiologically opposed
by the action of the pulmonary cilia, although the resistance is
frequently ineffectual. This inefficiency may be owing to the quantity
of dust inspired or to deficient tissue-integrity in general upon which
the ciliary action depends in inverse ratio.
Exciting Causes.—These vary materially in different avocations. The
most injurious industries are those in which the various forms of
grindstones are used, or those trades which necessitate labor in an
atmosphere loaded with particles of steel, iron, or flint. In London,
where millstones are made from French burr, a peculiarly hard flint
quarried on the Marne to the east of Paris, and more liable to chip
from its hardness and dryness than flint quarried in other places, the
mortality among the artisans is said to be very much increased.
Peacock, who has investigated this subject, asserts that in certain
manufactories of this class the average age of those engaged is very
low: of 23 apprentices the average age was twenty-four, and the longest
period during which the occupation could be followed was thirteen
years. The same author has also demonstrated the presence of silicious
particles in the lung-tissues. In the pottery districts of England the
death-rate from pulmonary diseases is greater among those who work at
that avocation than among the other inhabitants.
The study of the effect upon the lungs of the inhalation of coal-dust
is very important. In the coal-mining region of Cornwall the deaths
from chest diseases among miners is double that of males in the
community at large; the mortality of those working in lead-mines is
also very great.
The black spit of pitmen, examined under the microscope, is seen to
consist of mucus enclosing finely-divided particles of coal, frequently
presenting the special bands of the particular coal in which the
subject of the disease may have worked. The fact that coal-dust may
enter the lungs in the act of breathing is corroborated by Rindfleisch,
who, reporting for Traube a post-mortem made in 1860, found in the
fluid expressed from the parenchyma of the lung "one of the dotted
cells of coniferous wood entirely carbonized, in which he was able to
count seven pores close together. This particle of charcoal-dust
equalled half the diameter of an alveolus." Inhaled particles of dust
first penetrate the bronchial tubes and infundibula, and, entering the
alveolar parenchyma, mix with the general current of extravascular
fluid, together with which they ultimately tend to reach the lymphatic
vessels. On their way they must occasionally meet with corpuscular
elements which have the power of permanently adopting small solid
particles into their protoplasm: foremost among such elements are the
stellate corpuscles of the connective tissue, next the migratory
amoeboid cells, which are found in the connective tissue of the lungs
as well as elsewhere, and which carry the black pigment with them
wherever they go. The residual portion which escapes, being arrested by
cells on its way through the lymphatic system, is carried to the root
of the lung and enters the lymphatic glands of the mediastinum; here
the granules meet an obstacle to their further progress, for the
countless lymph-corpuscles with which the glands are stored are ready
to take up as many of the charcoal particles as can by any possibility
be accommodated in their protoplasm. We may conclude that the influence
of inhalations of coal-dust varies in different cases, but may be
considered as prominent among the exciting causes of pneumonokoniosis.
The charcoal-grinders and carriers, chimney-sweeps, moulders, iron and
glass polishers, and the workers in mother-of-pearl, all suffer more or
less from destruction of lung-function. Deposits of oxide of iron have
been found in the lungs of operators who have for years used this
substance as a polishing pigment. Merkel reports the case of a man who
was employed to clean the surface of oxidized iron by scrubbing it with
sand: his expectoration was grayish-black, and was found to contain
small grains of magnetic
oxide of iron; the lungs were found to be indurated with cavities at the apices.
Many other instances of dusty avocations may be mentioned as exciting
causes. The polishing of brass is sometimes effected by rollers made of
canton flannel which revolve with great velocity, filling the air with
fibres of cotton which are capable of acting as mechanical irritants.
In the sizing process in some cotton manufactories the material is
often adulterated with clays or some sort of salt to lessen the
glutinous qualities of the flour or tallow, and although the process is
carried on in damp rooms to lessen the brittleness of the size, dust
prevails, causing irritation of the nose, eyes, and throat. Some
interesting observations have been made on this subject by James Y.
Simpson, who has especially investigated the hygiene of woollen
manufactories. He suggests that these artisans are comparatively
healthy because of the oil absorbed while running the machines. In the
manufacture of cotton it has been found that in mills where cotton
containing dust and dirt is used, as the East India varieties employed
in England during the American War, the respiration was affected, and
the expectoration of numbers of operatives contained slaty-colored
matters, found, on microscopic examination, to contain cotton fibres.
Bakers who have to deal with highly-dried biscuit flour suffer more
than those using ordinary brands of flour. But when all has been said,
when we consider how many persons live permanently in an atmosphere
specially surcharged with dust without showing a symptom of a morbid
state of the respiratory organs, and since the epithelial cells of the
lungs can contain particles of coal, it demonstrates that foreign
bodies may penetrate the lungs without always inducing serious changes.
Mineral matter has been found by Riegel in the form of silica in the
lungs of a boy aged four, constituting 2 per cent. of the ash left
after incineration. In those of a day-laborer aged forty-seven it
amounted to 13 per cent., and in those of a woman cook sixty-nine years
old it reached 16 per cent. Accepting these figures as accurate, they
show a progressive accumulation in proportion to age among individuals
breathing dusty atmosphere. Traube thinks that the changes in the lungs
of coal-miners may not be produced by the accumulated particles of
coal, but by the chemicals contained in coal, and not found in
charcoal. In a discussion of this question in London in 1869, Wilson
Fox thought it remarkable that in proportion to the number of persons
exposed to the inhalation of irritating substances the cases of
phthisis were comparatively few, and suggested that a diathetic
condition might underlie the entire pathology.
In summing up the evidence bearing on the predisposing and exciting
causes of pneumonokoniosis we cannot overlook the recent discoveries of
Koch and his collaborators, but may conclude that although there is
increasing evidence tending to show that the bacillus tuberculosis is
always present in tuberculous pulmonary processes, yet its exact
etiological relation cannot be considered as established. We may still
hold that when large amounts of inorganic materials are taken into the
lungs, particularly if the ventilation or hygienic conditions under
which the dust is inhaled are imperfect, certain diverse pulmonary
processes are apt to ensue. That phthisis can be thus produced is
undoubted, but the nature of the irritant has less to do with the type
of the resulting disease than has an inferior or scrofulous
constitution, inherited or acquired, or the indulgence in habits
directly damaging to the health; since an unvarying specific cause
would be more destructive than has been proven, large numbers of
individuals escaping any serious effects when equally exposed.
PATHOLOGY AND MORBID ANATOMY.—Whatever be the dust inhaled, the
pathological processes set up by it partake of the same essential
character, though differing in intensity and in the division of
pulmonary tissue
principally involved, while the combined
inhalation of organic particles may essentially modify the results
produced. Examination of the lungs has revealed deposits of various
inorganic materials which have been inhaled, such as oxide of iron,
indigo, snuff, silica, coal, carbon, etc. A black discoloration of the
pulmonary tissue, with or without induration, enlargement, and
blackening of the bronchial glands, may, however, have its origin in
morbid changes independent of inhaled matter, such as defective
elimination of carbon and carbonic acid, with a sort of precipitation
of carbon within the tissues.
The black coloration of the lungs, especially in miners, is also partly
due to the deposition of a true hæmatoidin pigment in granular form,
caused by the irritating particles inhaled setting up changes in the
bronchial or pulmonary tissues, resulting in the escape of the coloring
matter of the blood either by rupture of capillaries or from
transudation of serum. Similar discoloration is often found in cases of
chronic bronchial processes independent of a dusty etiology. The most
penetrating form of dust is the silicious, on account of its hard,
vitreous character. German authors comment on the difference in the
power of penetration of mineral coal-dust as compared with
charcoal-dust, because the spiculæ of the former are elongated,
sharpened splinters. The coloration of the lung from clay-dust does not
diffuse itself so readily as coal-dust, yet it possesses more
irritating properties and creates more damage.
The morbid anatomy of pneumonokoniosis includes nearly all the
pathological processes incident to the pulmonary tissues. The bronchial
lesions are those of chronic bronchitis, with thickening of the
bronchial mucous membrane, associated with possible ulceration and
bronchial dilatations, forming bronchiectasic cavities. These cavities
are caused by combined softening of the bronchial tissues with traction
from without by the newly-formed fibrous tissue. The bronchial glands
may be enlarged to the size of walnuts, and are often perfectly black
and gritty on section. These enlarged glands may occasion, through
pressure, many changes in the pulmonary tissues. The effect of this
pressure is especially manifest in the lymphatic system. The
lymph-circulation is further crippled by the accumulation in the
lymph-channels of the inhaled inorganic materials. These interferences
with the lymph-circulation may be followed by exudation or lobular and
interlobular formation of tissue; secondary to these changes the
pressure upon the vesicles may cause local congestions, exudations, and
even hæmoptysis. By one or all of these processes the expansile power
and elasticity of the lung are slowly depreciated, emphysema develops,
intertwined with the lesions of acute, subacute, or chronic bronchitis,
fibroid phthisis, and atrophic emphysema. Nodules of cretaceous matter
can be recognized through the lungs, which are black in anthracosis or
gray in silicosis. These nodules occur from the size of a pin's head to
that of a pea, and are especially found in the lungs of glass-cutters,
sandstone-workers, and grinders. In these cases they consist in part of
iron and in part of stone. In sandstone-workers they are composed of
silica; the organ feels nodulated, very fibrous, and in some cases
actually gritty. The predominant form of pulmonary change is fibroid;
hardened districts of advanced cirrhosis occur measuring two inches and
upward in length and width, and in depth and thickness nearly as much.
These may be rounded, but are not separable from the adjacent
structures, the condensation of the tissues lessening without a
defining line. On section they appear tough and leathery, most
pronounced along the anterior edges of the lungs, and are apt to be
covered in by thickened pleura. If the nodules previously alluded to
are encysted, fibrous prolongations extend from these cysts into the
substance of the lung, the thickening of the lung being greatest in the
septa, on the pleural surfaces, and along the course of the bronchial
tubes. Sometimes subacute or chronic pleural processes coexist. The
caseous masses found in tubercular fibroid phthisis are infrequent in
pneumonokoniosis, but in the latter process the
pathological
changes may be identical with the ordinary forms of phthisis,
especially in those individuals who are predisposed to pulmonary
affections and those in whom the pathological processes are rapid.
In anthracosis the lung is large and increased in weight; the surface
of the pleura has a bluish-black color, contrasting with the coal-black
color of the lungs, which are universally pigmented and contain nodules
of pigment. When only small quantities of pigment are present, it
presents the appearance of dark lines running between the lobules; on
section these are very hard and distinct, being about the size of a
millet-seed. They are universally distributed throughout the lung, and
in some places appear like small masses of charcoal. Upon squeezing the
organ a blackish fluid exudes which stains the hands, but the discharge
which is found lying in the bronchial tubes is often yellow and
muco-purulent, although the sputa during life is more or less
discolored. When the distribution of the discoloration of anthracosis
is investigated, it is found to closely correspond with the lymphatic
distribution of the lung, and the conclusion is probably well founded
that all other irritating particles pursue the same course through the
pulmonary tissues. When particles of coal or pigment enter the bronchi
with the air, they cannot pass through its mucous membrane, because the
basement membrane and fibrous coat underlying it present an obstacle to
their lodgment, whilst the cilia of the epithelium tend to prevent
their retention in the bronchi; they therefore enter the vesicles, and
may be found sticking to the walls. In this way the exemption of the
bronchi from pigmentation, even down to the smallest ramifications, can
be explained. The interlobular septa ate also the seat of great
pigmentation. The germinating epithelium elevates the cells slightly
above the surface, and in the interspaces between them the pigment
insinuates itself, and thus enters the underlying plasmatic or
lymphatic spaces; or the pigment may be incorporated into the
epithelial cells, which transfer it to the underlying lymph-space. Once
the pigment has found entrance to these lymphatic channels, it is
carried by them through the lymphatic vessels in the sheath surrounding
the bronchial tubes and the small branches of the pulmonary artery, and
in the interlobular septa to the bronchial glands. In this manner the
special distribution of the coloring matter in these situations is
explained. The special deposit around the small branches of the
pulmonary artery is owing to the double set of lymphatics, the
peribronchial and the perivascular, which form an anastomosis. The
perivascular set is the larger; consequently the pigment passes into
them more readily, forming the nodules. Pigment is also found in small
quantities around the bronchi, which can be accounted for by the
anastomosis of the lymphatics. The bluish-black appearance of the
pleura and the distribution of the pigment only in the deeper layers of
the visceral pleura are susceptible of a similar explanation, because
the deeper layers of the pleura contain lymphatic vessels which are
directly continuous by means of the lobular septa with the large
perivascular branches of the lymphatic system.
The consequences of the obstruction to the lymphatic and
pulmonary-artery circulation may be very serious. In grave cases the
lung breaks down, forming a gangrenous-like cavity, which differs from
an ordinary cavity in not being rounded; it is more like a gangrene or
slough. In a few cases the pathological appearances indicate phthisis,
chiefly interstitial, with formation of cavities; sometimes traces of
cavities are found which have cicatrized. More commonly oedema is
developed in the lung and the bronchial passages. As a consequence of
combined bronchial irritation from continuous inhalation of inorganic
particles, and the consequent oedema, a continuous germination and
shedding of the bronchial epithelium—a chronic bronchitis—associated
with emphysema, is maintained. The mechanical cause of this
bronchitis—more or less impediment to the vascular and lymphatic
circulations by the
pigment deposit—is capable of explaining the
persistence of various forms of bronchial processes in anthracosis and
in other forms of pneumonokoniosis after the patient has ceased working
in a dusty atmosphere.
SYMPTOMATOLOGY.—Pneumonokoniosis does not present a special
symptomatology. The course of the various morbid processes is insidious
and slowly progressive: the development of any of the forms of
pulmonary disease depends largely upon the degree of exposure to the
exciting causes, or the inherited tendencies, or the susceptibility to
influences liable to diminish general vitality or affect the personal hygiene.
The earliest objective symptom of pulmonary lesion is cough, especially
recurrent in winter, accompanied by expectoration, which is whitish,
frothy, or stringy in character. Gradually the physical signs, taken
together with the symptoms, indicate the various forms of bronchitis,
acute, subacute, or chronic, sometimes associated with emphysema,
bronchorrhoea, or bronchial dilatation. In other cases the
symptomatology is that of asthma, either purely spasmodic or secondary
to emphysema or cardiac degeneration. In true anthracosis dyspnoea is a
marked symptom, and perhaps the accumulation of pigment may interfere
with the oxygenation of the blood, or dyspnoea may be due only to an
emphysematous pulmonary tissue. The sputa will be black so long as the
subject is working in an atmosphere loaded with pigment.
Fibroid phthisis is frequently associated with atrophic emphysema, and
the clinical history corresponds with that which is commonly observed
in these diseases. Hæmoptysis is rare, but if it occurs it suggests the
addition of some tubercular element; a purulent nummular sputa is a
suspicious sign of similar import. The symptoms and physical signs of
dry pleurisy are to be expected whenever any form of the phthisical
process supervenes. The cavities in the lungs are usually
bronchiectasic, unless tubercular phthisis occurs as a complication,
and the physical signs need no comment. Subacute and chronic laryngitis
with ulceration complicate certain cases, particularly those which have
inherited or acquired a tubercular tendency.
DIAGNOSIS.—The diagnosis involves a comparative examination of the
etiology and the physical signs.
PROGNOSIS.—The prognosis depends very largely upon the withdrawal of
the sufferer from an unhealthy environment. In each single case the
inherited tendencies, the personal constitution and habits, must be the
basis for an opinion upon the gravity of the pulmonary processes and
the possibilities of restoration to health. The progress of the disease
may be materially retarded or arrested by withdrawal from the
occupation involving the inspiration of dust, and restoration to
comparative health after years of invalidism is possible for these
victims of dusty avocations, even after serious damage has taken place
in the lung, if suitable hygienic conditions can be obtained.
TREATMENT.—The treatment of pneumonokoniosis divides itself into the
prophylactive and the curative. In works devoted to the hygiene of
occupation careful directions are given in reference to methods
designed to prevent the dust from entering the respiratory passages.
This is partly accomplished by the use of masks or respirators, which
possess the obvious disadvantages of clumsiness and interference with
respiration. Various devices may be employed in different avocations to
prevent the generation of dust, but the most practical plans consist in
thoroughly ventilating the atmosphere, and thus preventing the dust
from reaching the artisan. Aside from these, the management of the
various pathological conditions must be based upon the general
principles which govern the treatment of pulmonary processes.
DEFINITION.—A malignant disease affecting the pulmonary tissues. (Vide
also MEDIASTINAL DISEASE.)
SYNONYMS.—Fr. Carcinome du poumon; Ger. Lungenkrebs.
ETIOLOGY.—Carcinomatous disease affecting the lung-tissue is
exceedingly rare as a primary process, and exhibits only a feeble
inclination to inoculate other portions of the body. In the majority of
cases the mediastinal glands are first affected, or it appears in the
lungs as secondary to disease elsewhere in the system. Metastasis is
probably effected by means of particles of living cellular material
which are transferred through the blood-vessels or lymphatics.
Cancer of the lung often reverses the rule that carcinoma occurs most
frequently in the female, Hasse, Kohler, and Cockle giving a majority
of cases among males. It has been met with in childhood and in extreme
old age, but is more common in the middle periods of life, from twenty
to sixty years.
PREDISPOSING AND EXCITING CAUSES.—The predisposing and exciting causes
of malignant pulmonary disease are involved in the obscurity that
surrounds the development of all neoplasms.
PATHOLOGICAL ANATOMY.—Clinically speaking, cancer in the pulmonary
tissues includes the scirrhous or encephaloid neoplasms. The colloid,
enchondromatous, or fibromatous growths have been recorded as possible
tumors, but possess only a pathological interest.
Malignant disease may commence in, or ultimately implicate, one or all
of the pulmonary tissues; secondary neoplasms have been experimentally
produced by lodgment in the lung of living cellular particles which
grew centrally by virtue of inherent cell-proliferation, independently
of changes produced in the surrounding tissues. Cancer of the lungs,
whether primary or secondary, usually originates near the roots of the
lungs, implicating the mucous and submucous membranes of the bronchi,
sometimes commencing in its small mucous follicles. The bronchial
passages and the lymph-channels become the viaducts along which the
growth proceeds in its march of invasion, involving most frequently the
posterior portion of the middle lobe. The apices of the lungs may be
implicated, but not primarily, as in tuberculosis. The mediastinal
lymphatics are originally involved in an unestimated number of cases,
or enlargement of these glands is coexistent with the development of
pulmonary cancer. The enlargement of the mediastinal glands is
sometimes moderate, but an enormous mass may be formed. (Vide
MEDIASTINAL TUMORS.)
Carcinoma is found in masses varying in size from a hempseed to an
orange or larger, and since its distribution follows the lymph-channels
in their circuitous route through the lung, we can account for the wide
distribution of the nodular masses of secondary cancer. The isolated
nodules present an
ovoid outline, sometimes situated near the
pleural surface, in contrast with the larger formations which affect
the roots of the lungs.
The primary malignant formation presents a single large mass of
infiltration, possibly associated with a few small nodules scattered
throughout the lungs; the right lung is conceded to be the most
frequently affected, but secondary cancer usually implicates both organs.
Cancer in the parenchyma of the lung may diminish or occlude the lumen
of the bronchial tubes, or they may be filled with cancerous matter and
their walls perforated. The development of cancer along the
distribution of the bronchial passages shows us how readily chronic
bronchitis may occur as a complication and form a confusing element in
the diagnosis. The remaining pulmonary tissues may escape anatomical
change, or from pressure atrophic or hypertrophic emphysema or collapse
may ensue. These changes, together with the similarity to a fibroid
phthisical process which many cases suggest, must be borne in mind in
making a diagnosis. Pulmonary apoplexy, or even gangrene, is an
incident in some of the clinical pictures of this disease, and embolism
or thrombosis in other parts of the system may occur. The terminations
of intra-thoracic cancer vary in accordance with the history of these
growths elsewhere. Infiltration with blood or melanic deposition has
been noticed; evacuation of the new growth through the bronchi may
induce the development of cavities in the lungs, preceded or
accompanied by suppuration, ulceration, or gangrene. In addition,
hydro- or pyo-pneumothorax may occur by perforation or invasion of the
pulmonary pleura.
Carcinoma of the pleura is usually secondary to its development in the
lung, but it may be communicated from a similar process in the mammary
gland by infection through the pectoral and intercostal muscles to the
parietal pleura. Carcinomatous formations on the pleura are small and
hard in scirrhous, but are larger in encephaloid, cancer. The minute
spots of early formation are found scattered over the pleura like drops
of wax. The thickened tissues, when they coalesce, undergo
degeneration, and may form plaques of cartilaginous hardness. Large
pleural growths may compress or nearly efface the lung, but are among
the curiosities of medical literature.
Neuralgia may be occasioned when nodules impinge upon the intercostal
nerves. Similar pressure is the cause of the pain in pulmonary cancer,
except that induced by the pressure of mediastinal enlargement. Chronic
pleural inflammation may be frequently developed by the new growth, and
the diseased lung may become adherent to the inner surface of the
sternum and ribs. The lung in other cases may be compressed or
retracted, uncovering the heart and rendering the chest-walls smaller.
The chest may be enlarged, especially if there is pleural effusion;
usually the contour is unchanged.
Pleural effusions are frequent in the history of this disease: they may
be passive, resulting from pressure on the azygos or hemiazygos veins,
preventing the return of the blood from the pleural veins, or from
mediastinal pressure. An inflammatory hydrothorax may be excited by the
deposit of cancerous material in the pleura; and it is possible for
these effusions to undergo purulent transformation or to become
hemorrhagic. A hemorrhagic effusion when grouped with other symptoms
may be considered an important evidence of malignant formation. The
further history of pleural effusions in this association is usually an
increase of such an amount as to necessitate removal by thoracentesis,
but reabsorption is possible.
SYMPTOMATOLOGY.—The interest of the clinical observer nucleates itself
around the symptomatology and diagnosis. The frequent negative results
of physical examination indubitably prove that its teachings alone are
insufficient for the purposes of diagnosis, so that any study of a case
would be partial which did not unite the evidence yielded by physical
signs with the general symptoms. The clinical evidences are more
definite when the
neoplasms are multiple and associated with some
mediastinal process than when single or absolutely primary growths. The
development of the disease is insidious. Gradually the facies and
general surface of a patient indicate the true nature of the malady by
the characteristic cachexia. Cough is an early symptom, unimportant
save that it cannot be assigned to any definite cause. It may be dry
and hard, attended only by expectoration of glairy mucus, or the sputa
may be purulent. Usually the amount is in ratio with the degree of
coexistent bronchitis. In the latter stages of the disease the sputa
may contain blood, resembling prune-juice or black-currant jelly, due
to erosion of some of the blood-vessels. In this stage of softening
cells characteristic of the new growth, with portions of the pulmonary
structure, may be found on microscopic examination of the sputa; the
appearance of the expectoration sometimes suggests fibrinous bronchitis.
When there is elevation of temperature it may present a hectic type,
with night-sweats, which are stated by Walsh to be sometimes confined
to the affected side. The presence of an abnormal temperature-curve is
indicative of associated inflammation of the bronchial mucous membrane,
the development of a pleural process or of phthisis, especially the
fibroid form. The pulse becomes accelerated in ratio to the degree of
these inflammations and the failure of the sufferer's strength.
The new growth determines some mechanical symptoms cognate to all
intra-thoracic tumors, especially those which involve the mediastinum.
Lancinating pain would presumably be a constant symptom, but is, in
fact, infrequent, unless the growth or growths enlarge so as to cause
pressure on the nerve-trunks, in which event pain may become a
distressing symptom. Characteristic pains complicate those cases in
which the pleural tissues are involved in the morbid process. Dyspnoea
is a pressure-symptom of considerable import if other conditions
capable of producing it, especially uncomplicated emphysema, are
rigidly excluded. When the new formation is infiltrated throughout the
lungs, the growth may, as in miliary tubercle, impair the aërating
power of the lungs by diminishing their elasticity and increasing their
density. When, however, the process is local and restricted, the
dyspnoea may be due to irritation of the terminal filaments of the
vagus; this being a mixed nerve composed of accelerator and inhibitory
filaments, the balance of innervating power may be readily destroyed
and partial or incomplete respiratory effort follow. Dyspnoea may also
result from pleural adhesions or effusions, or may be secondary to
direct cardial or pericardial involvement in the cancerous process.
Palpitation or increased pulse-rate may be referred to irritation of
the vagi, or to some of the foregoing pathological processes.
Kindred to these symptoms are the changes in the voice, which sometimes
undergoes frequent variations due to irritation or pressure on the
trachea or on the branches of the pneumogastric nerve, especially when
mediastinal disease is present. Aphonia, huskiness, a bass voice, or
high treble, one or all, may be constant or alternating harbingers of
the concealed mischief. The laryngoscope will inform one whether there
is direct involvement of the larynx with morbid growth. Dysphagia is to
be expected if the new formation involves the regions through which the
oesophagus passes, and a sacculated pouch may be formed above the
compressed spot. Changes of posture may increase or diminish the
pressure, and thus the dysphagia or dyspnoea may at times be more
pronounced than at others. Dysphagia may also be due to swelling of the
oesophagus near the location of pressure. Reflex irritation of the
sympathetic ganglia may induce pupillary contractions in one or both
eyes: this symptom is chiefly present when the mediastinum is involved.
The physical signs contingent on pulmonary cancer include those
ordinarily indicative of bronchitis with or without atrophic emphysema,
simple pleural effusion, or chronic pleurisy with retraction. By
inspection a study
should be made of the contour of the thorax,
the respiratory movement, and displacements of the intra-thoracic
viscera. The thorax may appear enlarged, either from the new formation
or from associated pleural effusions. It is often retracted, owing to
the atrophic changes, and collapse brought about by the new formation
or induced by pleural adhesions. The movements of the chest, unless
there is a pleural complication, possess no distinctive character in
this disease. Displacements of the heart or trachea may be expected on
mechanical principles if there is mediastinal disease. General
inspection may detect in the clubbed fingers evidences of venous
obstruction, and sometimes an asphyxial hue of the upper portion of the
body. Nearly always a general emaciation with anxious expression
exists, and a tawny or lemon-hued skin indicative of the cancerous cachexia.
By palpation of the substernal or supra-clavicular spaces one may reach
masses of painless, movable, glandular enlargement, but these may be
easily overlooked unless a careful study be pursued. Circumscribed
swellings of the thoracic walls may be detected, though not often, and
the glands of the axillæ and neck may enlarge. Palpation may also
reveal an inequality in volume between the radial pulses, but not so
commonly as in purely mediastinal tumors or in aneurisms. Percussion
and auscultation are negative or yield an area of dulness or flatness
with restricted or absent respiratory murmur. When there is a single
large growth the boundaries of these signs are local. If the tumors are
diffused the respiratory murmur varies. In tiers of lung it is feeble
or absent; elsewhere it is harsh, puerile, or bronchial. Chiefly
remarkable is the fact that the character of the respiratory murmur
cannot be harmonized with any other pulmonary states when the entire
clinical evidence is taken. Vocal resonance corresponds with the
respiratory murmur according to accepted laws. When there is pressure
on the principal bronchus on one or both sides, one can detect either a
snoring, increased bronchial respiration, or else, if the pressure
decidedly narrows the calibre of the bronchus, the breathing becomes
feeble or wheezing. Expiration may be prolonged and sonorous in
character, with or without râles. The pressure is rarely equal on the
two sides. The vocal resonance in these cases is ringing and brazen.
Mensuration corroborates inspection. Pleural effusion from whatever
cause is revealed by the ordinary signs. Enlargement of the bronchial
glands, either primary or coexistent with the development of cancer in
the lung, reveals itself by pressure-symptoms proportionate in their
severity to the degree of bronchial enlargement. Pain, laryngeal
irritation, differences in the radical pulses, tumor if the enlargement
is anterior, one or all, may be present. The aorta itself may be
compressed by the enlarged glands; and by the narrowing of its lumen
thrill, and even systolic, murmur can appear, making a differential
diagnosis from aortic aneurism very difficult. (Vide MEDIASTINAL
TUMORS.) Embolism and thrombosis, with the ordinary symptoms, may
complicate the course of pulmonary cancer and obscure the diagnosis.
The duration of cancer of the lung is fixed by Walsh at 13.2 months,
mean average, maximum, at 27 months; minimum, at 3.5 months; but this
is based on a confessedly small contingent of cases. The first
symptoms, dry cough, pain in the chest, difficulty of breathing, may
last for some years without alarming the patient. After the more
dangerous phenomena appear the course is often more rapid. The history
of cancer in the lung in the main corresponds with cases of similar
types of cancer elsewhere. The grave symptoms appear earlier in cases
of mediastinal cancer than in cancer of the lungs proper. Death may
result from asphyxia; from bronchial obstruction; from pulmonary oedema
occurring suddenly, as in chronic alcoholism; from embolism of the
pulmonary artery; or from pleural effusion. Life may gradually ebb away
through general asthenia with malnutrition; in some
remarkable
cases the same result is accompanied by hectic fever and the typhoid
phenomena, with evidences of tissue-disintegration.
COMPLICATIONS.—The complications of pulmonary cancer have been already
outlined. They are chiefly the bronchial, pleural, and mediastinal
processes. Primary cancer of the lungs possesses a feeble tendency to metastasis.
DIAGNOSIS.—The most valuable assistance is derived from a close study
of the personal and hereditary history. Whenever a new growth has been
extirpated, the possibility of its reappearance in the lungs should
always be remembered. The most disciplined comparative analysis of
physical signs may be fruitless. The origin of a primary growth from
the roots of the lungs may help to interpret the physical signs, and
examination of the sputa should never be omitted. In secondary cancer
the history of the case may include the removal or development of
morbid growths from other parts of the body. Any pulmonary symptoms in
these cases become more suspicious than they would in persons in whom
no signs of cancerous diathesis have ever made their appearance. This
rule must not be pressed too far, for forms of pleurisy, bronchitis,
and pneumonia or phthisis may be the explanation of the symptoms.
In the differential diagnosis it is a matter of universal experience
that some form of chronic pleurisy is the most frequent source of doubt
to the clinician. It has been said by Wintrich that vocal fremitus in
cancer is more often present than absent. If there is much pleural
effusion, paracentesis will be helpful in two ways. When the fluid is
turbid, highly albuminous, with a large proportion of coagulable
fibrin, it is an evidence of its inflammatory origin; but if it is
clear and limpid, and upon standing gives but a delicate veil of
pseudo-fibrin, it indicates a passive or mechanical cause. If the fluid
evacuated should contain any considerable amount of blood, such a
peculiarity in association with the other symptoms already indicated is
to be regarded as probable evidence of the existence of cancer of the
pleura. If the external veins of the thorax are enlarged, they indicate
a deep-seated cause of pressure. In malignant disease with retraction
there may be less deepening and narrowing of the intercostal spaces on
full respiratory movement than is associated with chronic pleurisy:
there is usually greater volume and nearness of the respiratory murmur,
although this is more noticeable on the left than on the right side,
since the liver is present in the latter. The greater severity of the
local symptoms and the increase in gravity of the disease must be
contrasted with the features of a disease in the decline, as is the
case in chronic pleurisy. Walsh considers that "the normal position of
shoulder, spine, and scapulæ distinguishes cancer from the results of
simple pleurisy." In addition, we have the shorter duration of cancer,
which is never over two and a half years, often less. The lemon-hued
cachexia is so frequently absent that the inference from general
inspection of the features is marred. From fibroid forms of pulmonary
disease we have the pressure-signs, giving evidences of mediastinal new
formation; also the possible prune-juice expectoration of cancer. The
retraction and displacements of the intra-thoracic organs, chiefly the
heart, are greater in fibroid disease than in either pleurisy or cancer.
In addition, the history of phthisis includes a higher thermometrical
record, frequent hæmoptysis, and abundant sputa. Physical diagnosis in
cases of phthisis reveals a destructive process involving extensive
areas of pulmonary tissue in a comparatively regular sequence. The
cancerous process is more local or involves the tissues in an irregular
order. Moreover, the asphyxial hue and the pressure-symptoms
preponderate in malignant disease. To distinguish the cancerous process
from simple forms of bronchitis we may observe the frequency with which
the symptoms of bronchitis recur in cancer
without exposure to an
adequate cause; by the absence of marked tendency to hypertrophic
emphysema; by the resistance to treatment; by the persistence of
dyspnoea as a prominent symptom; and by the gradual development of
patches of hypostatic congestion. To differentiate from aneurism we
should consider the occupation of the patient, the absence of syphilis
or other causes of arterial disease, the history, the location of the
tumor, and the absence of the murmur. Hydatid cysts may simulate
cancer, but this disease is rare in America. (Vide PULMONARY HYDATIDS.)
In cancer of the liver, as that organ enlarges pulmonary symptoms may
occur from irritation, and congestion or oedema be produced. We must be
content to mention the possibility of error, and decide in each case
after a crucial analysis of the abdominal or thoracic symptoms.
PROGNOSIS; TREATMENT.—The prognosis is fatal; the treatment purely
palliative. It is quite justifiable to relieve pain by the hypodermic
use of morphia, cough by chloral or the usual narcotics, and fetor of
the breath may be palliated by inhalation of carbolic acid or other
disinfectants. Dyspnoea may be alleviated by the use of strychnia as a
respiratory stimulant—by inhalation of nitrate of amyl or small
allowances of chloroform or digitalis. Paracentesis thoracis must often
be resorted to in cases of pleural effusion, even although the relief
it affords be temporary.
DEFINITION.—A disease in the lungs consequent upon the entrance into
the human system of the eggs of a small tape-worm, whose usual habitat
is the upper half of the small intestine of the dog.
SYNONYMS.—Tænia echinococcus; Acephalocyst. Fr. Kystes hydatiques du
poumon; Ger. Lungenechinococcus.
HISTORY.—Unmistakable references to this disease are found in the
writings of Hippocrates, Aretæus, Galen, and other early writers. For a
long time, however, the animal character of the hydatid cyst was not
recognized, but confounded with slowly-developed local dropsies of
various orders and with lymphatic dilatations. Their animal nature was
suspected by Hartman in 1685, but their origin was not separated from
the cysticercus. In 1766, Pallas clearly distinguished the two species,
and this author was followed in a more positive way by Groeze in 1782.
Laennec in 1804 carefully studied the hydatid cyst as found in the
sheep, recognizing even the mode of reproduction, but he erroneously
described the same parasite, when existing in man, as a distinct
animal, which he termed acephalocyst. Since 1821, Bremsen, Davaine,
Küchenmeister, and others have definitely settled the true mode of the
entrance of the Tænia echinococcus into the human system, and the
subsequent development of the hydatid cysts. The development of the
parasite resembles that of the cysticercus. Like the latter, the larvæ
infest the bowels of certain animals, and take their further
development in a different animal or species, forming vesicles which
are distributed in the parenchyma of the different organs, and in this
way more or less seriously compromising the functional life of the part
in which they occur.
ETIOLOGY. (See article on INTESTINAL WORMS, by Leidy.)—Hydatids have
been found in the human subject in all countries, but especially in
France, Germany, and in the north of Europe. They are rarely found in
North America, and the fact that the majority of cases seen here have
occurred in foreigners favors the probability of the hydatid disease
having been imported. But there are two countries where it may be said
to be endemic—Iceland and Australia. Finsen found 1 out of every 43
inhabitants affected with this disease in the district of Ofjord in
Iceland. Hydatids are communicated to the human race through the system
of the dog, and in Iceland the proportion of these animals to the
population is probably more than 1 to 3, a recent census recording
20,000 dogs to 70,000 inhabitants. Hydatids usually enter the system
through the digestive and respiratory organs. The Icelanders are
excessively uncleanly and careless of the laws of ventilation. In the
winter season both men and women are confined to the house in company
with their dogs, and in consequence the air is impregnated, and
oftentimes the drinking-water contaminated, through their dejecta,
which contain thousands of the eggs of the echinococci. The largest
number of cases occur in the agricultural districts, since the
dogs are more required there than on the sea-coast.
In Australia large numbers of dogs are maintained to guard the sheep.
The droppings of these animals, dried by the hot winds, are inhaled as
dust. It is curious to note that in Australia, where the high winds
prevail, the proportion of pulmonary hydatids is very large, while in
Iceland, where the drinking-water is the principal medium of
communication, the lungs are less often affected than other viscera.
Finsen's records in the latter country show 255 cases; of these, 176
occurred in the liver, and only 7 in the lungs. In both Iceland and
Australia women are more subject to echinococci than men. This is
possibly accounted for by the facts that the women take care of the
dogs and wash the vessels from which they eat, and are also less
protected by hair about the mouth and nose than men.
The disease occurs most often between the ages of twenty and thirty
years, but it has been found in children of four years of age. Before
ten and after sixty the proportion of cases in both sexes is equal. The
malady is not hereditary, but uniformity of environment accounts for
the propagation in communities. Pulmonary hydatids occur as primary
formations in the lungs, but may be secondary to similar growths
elsewhere, especially in the liver. There is, however, scarcely a
tissue in the body in which hydatids have not been found.
MORBID ANATOMY.—Hydatid cysts consist of sacs of various sizes, from
that of a pea to an orange or even an adult head. They are usually
globular in shape, and attached by a vascular membrane to the organ in
which they are situated. The walls of the cysts are composed of a few
laminæ of indeterminate membrane of varying thicknesses, commonly
depending on the age of the cyst. In young cysts they occur in direct
contact with the lung, but as they grow larger a thicker investment is
formed, and large old cysts which have generally undergone spontaneous
rupture often have a dense leathery sac. Walsh asserts that the parent
cyst lies in direct contact with the lung-tissue, and, unlike that of
the liver, is rarely surrounded with a thick shell or cyst-wall of
pseudo-areolar tissue. The interior of the pouch is smooth and of the
aspect of serous membrane without epithelial covering. The parent cyst
contains daughter cysts which are single or multiple, and a liquid the
proportion of which is variable. This liquid is nearly limpid, and
non-coagulable by heat or acids; it deposits by evaporation crystals of
chloride of sodium.
Commonly, only one hydatid tumor is found in the human lungs, although
in animals multiplicity of cysts is the rule. They are usually located
in the base of the lungs, and are thought to be more common on the
right side, but they may occupy any portion of one or both lungs. They
have been found in the pleura, the bronchi, the pericardium, and the
thyroid gland. In the pleural cavity they may be attached to both the
costal and the visceral pleura; in the latter case they may form an
outgrowth from the lung into the pleural cavity. Authorities differ as
to the condition of the neighboring lung-tissue, some stating that the
cysts are rarely surrounded by healthy lung-substance, while others
assert the contrary. Since the growth of the cysts is often very slow,
the accommodating power of the lung is remarkable when no
constitutional mischief exists. In some instances the rapid enlargement
of a cyst has been accompanied by certain forms of pneumonia, secondary
inflammatory lesions, congestion of the neighboring tissue,
splenification, or even gangrene.
Hydatids situated either in the lung or pleura may rupture into the
bronchial tubes, and thence be discharged by cough and expectoration,
or they may open externally like a pleural empyema, or even rupture
through the diaphragm into the intestines or peritoneum. None of the
above accidents are necessarily fatal, not even the latter, unless the
fluid be puriform.
Empyema with pneumothorax usually follows
rupture into the pleura. Finsen observes that a general urticaria may
follow the rupture of a cyst into a serous cavity. In old cases, after
rupture of cysts, pulmonary changes may almost always be found. The
ruptured cyst may become a suppurating cavity, suggesting the possible
development of phthisis. In some cases hydatid formations have been
described with coexisting catarrhal or tubercular disease, or these
processes may occur as a complication without rupture of the cyst.
SYMPTOMS.—The symptoms of hydatid cysts are obscure, and the physical
signs difficult to analyze when the cysts are small. They are more
suggestive when the cyst becomes large enough to contain a pint or more
of fluid. The outline of the cyst is usually globular, and is imbedded
in healthy or nearly healthy lung-tissue. According to Bird, the
physical signs correspond with those familiar to us in pleural
effusions: absolute dulness or flatness on percussion, with absence of
respiratory murmur over a space of the chest-wall not smaller than the
palm of the hand; vocal fremitus and resonance are also abolished. The
expansion of the chest is more or less deficient upon the affected
side, but seldom with any change on mensuration.
The area of the above physical signs usually presents a rounded
outline, limited by a line of demarcation so exact that it can be
mapped out with pen and ink, but is unaltered by position. Their
location is generally in the lateral or infra-clavicular regions;
beyond the boundary-line percussion is vesiculo-tympanitic resonant or
normal, and the respiratory sounds begin at the very margin of the
pen-and-ink line, and, though probably harsh and puerile in character,
are indicative of healthy lung-tissue.
Pulmonary hydatids can seldom be examined by palpation, but all authors
allude to a frémissement or peripheral fluctuation which may sometimes,
but not invariably, be detected by palpation over the intercostal
spaces. Davaine directs palpation as one would palpate an abdominal
cyst. The sensation of fluctuation is as though the fluid were
gelatinous; when the quantity of liquid is excessive this movement is
not perceptible. It is most recognizable when there is but a single
hydatid in the parent cyst (Jobert). The frémissement cannot be felt
when the sac has undergone atheromatous degeneration, because there is
then no liquid, and the cysts are withered, agglutinated to one
another, and the tumor is inelastic and hard. By auscultating the tumor
while practising percussion one may hear more or less positive
vibrations resembling those produced by a bass string (Briançon).
The general symptoms of pulmonary hydatids are of mechanical origin:
pain, dyspnoea, cough, with duskiness of the surface, all of which are
more or less marked according to the size and location of the tumor and
its rapidity of growth. A phthisical appearance is possible, with
deterioration of the blood-crasis and progressive loss of flesh. Marked
clubbing of the finger-ends and incurvation of the nails have been
noticed, all of which symptoms have disappeared after the hydatid cyst
has been tapped or expectorated. Cough nearly always accompanies this
disease, as it does a large pleural effusion. The expectoration is a
glairy mucus, sometimes stained with blood; when local bronchitis
occurs as a complication, it may become muco-purulent. There is much
diversity of opinion as to the frequency of hæmoptysis, many authors
looking on it as a rare symptom. According to Bird, there is seldom or
never profuse hæmoptysis, though several ounces have been expectorated
at a time in an aggravated case where tapping had been long delayed.
The cause of hæmoptysis is usually pressure of the growing cyst upon
the pulmonary veins, leading to extravasations of blood.
If dyspnoea with deficient aëration of the blood, wasting, clubbed
fingers, and expectoration persist after the expulsion or death of the
hydatid, the probability is in favor of some associated pulmonary
inflammation. When
a hydatid cyst ruptures into the bronchial
passages, there is serious likelihood that the patient may choke or
suffocative dyspnoea supervene. The quantity of entozoal substance
voided at any one time varies from a few microscopical fragments up to
a pint or more of unbroken acephalocysts. The expectoration of
acephalocysts may continue several months. Serious general pulmonary
symptoms precede and follow this accident. When rupture has taken place
into a bronchial tube, there are the usual physical signs of a
pulmonary abscess or large vomica. The sac usually suppurates, and
there is a constant expectoration of blood, pus, and half-putrid
acephalocysts of excessive fetor, and often portions of gangrenous
lung-tissue. With these symptoms the temperature is sometimes of a low,
remittent type, with hectic and sweats. The symptoms resemble those of
empyema or advanced phthisis, and may continue for months, until the
patient, in most cases, sinks from exhaustion, unless relieved by the
evacuation of the sac and its contents. When hydatids develop in the
pleural cavity the signs are identical with a localized pleural effusion.
Nothing has been said to differentiate pulmonary-hydatid expectoration
from cases where an hepatic hydatid cyst has burst into the lungs, and
the diagnosis may be very difficult. The physical signs of enlarged
liver are present, also the antecedent symptoms of disordered hepatic
action, especially intestinal indigestion and the staining of the sputa
with bile. If the cyst has undergone suppuration, the symptoms may be
allied to those of hepatic abscess.
The nucleation of testimony favors the view that a latent or slow
growth is by far the most common history of hydatids. Their duration is
very variable: patients may harbor them for a long time unconsciously,
even over a period of sixty years. This is corroborated by Finsen, who
reports cases in which the disease lasted sixteen, eighteen, and
fifty-two years, proving this by stating that these individuals had
left the country where the disease was endemic, and were residing
during these periods where the malady was rare.
TERMINATIONS.—30 or 40 per cent. of cases terminate in recovery if the
cysts spontaneously burst, death being caused in others by suppuration
and exhaustion. There is, in addition, the risk of sudden death from
the rupture of a large cyst in the lung, and consequent filling up of
the air-passages by its contents. The cysts may sometimes undergo
atheromatous changes in which the hydatids resemble crushed
grape-seeds. Microscopically, one finds a puriform fluid, plates of
cholesterin, crystals of hæmatoidin, hooklets of echinococci, and
débris of membranes. Again, the cysts may resemble a caseous or
cretaceous tubercle without special characteristics. This may be looked
on as a species of spontaneous cure. The growth of hydatid cysts may
bring about by pressure such a state of chronic pulmonary engorgement
that it affords a predisposing condition favoring the development of
tubercular phthisis.
DIAGNOSIS.—The differential diagnosis is necessarily difficult. The
nationality of the subject and the presence of a predisposing
environment should always be remembered. If the disease progresses
rapidly without interference, the diagnosis may be complicated by the
development of patches of bronchitis or pneumonia with rusty sputa. The
bronchitis is, however, local, which, taken with the physical signs of
a cyst, may be suggestive. The only absolute evidence of the existence
of hydatids in the lungs, whether primary or secondary, is the
appearance in the sputa of the characteristic cysts or portions of
them, such as fragments of the hooklets of the echinococci. This,
unfortunately, occurs as a late accident in their history. If the
boundaries of the cyst can be recognized, it is justifiable to resort
to paracentesis, and thereby withdraw some fluid for examination. The
physical signs of local serous effusion, globular in shape, not evenly
distributed around the circumference of the chest, is one of the
best differential evidences between hydatids and pleural effusion.
Moreover, there is no fever in hydatids unless after rupture, or with
extensive phthisical complication, while there is a history of fever in
some stage of most cases of pleurisy. Hydrothorax is differentiated
through its being bilateral and by its etiology. From local encysted
pleurisy the only resort is exploratory puncture and the question of
the probabilities in each case. In the same way paracentesis removes
doubt whether there be mediastinal tumor, solid tumor of the lung, or
circumscribed pneumonic abscess; in the latter the general history of
each case is helpful. From phthisis we must have recourse to the
physical diagnosis already mentioned as belonging to hydatids. An
unbroken cyst in the liver, high up and far back on its convex surface,
may not be distinguishable from one in the base of the lung immediately
over the liver or one in the cavity of the pleura.
PROGNOSIS.—According to Reynaud, this depends on—1, whether the
hydatid is single or multiple; 2, whether the pressure is exercised on
blood-vessels or bronchi; 3, if hydatids are discovered elsewhere; 4,
size of cyst; 5, alterations in the walls of cysts; 6, whether
complicated with any other disease or independent.
If there is a tendency to pulmonary phthisis, inherited or acquired, or
if this disease exists as a complication, it forms an unfavorable
element in the prognosis. Persons once affected with hydatids are more
susceptible to a second invasion of the parasite. The practicability of
treatment by tapping is also an element in the prognosis.
TREATMENT.—Naturally, the preventive treatment rationally deduced from
the now distinctly-understood causes should be practised. The
water-supply should be protected from sources of contamination, and in
addition the inhabitants of countries where the disease is prevalent
should, as far as practicable, use boiled or stone-filtered water and
refrain from eating water-cresses or plants of like character wherever
these are liable to be contaminated.
Many drugs have been administered, among them the bromide and iodide of
potassium; solutions of salt are also said to be deleterious to the
life of the echinococcus; Laennec even prescribed salt baths. Tincture
of kamela has been recommended by Hjaltelin, a physician in the employ
of the Danish government in Iceland. He administered it in doses of
thirty drops daily to adults, continuing its use during a month or
more. It has a distinctly irritating and destructive effect on the
acephalocyst (Bird). Turpentine, from its well-known anthelmintic
powers and ready diffusibility, has naturally suggested itself as a
remedy, and according to some has proved of great service in many
instances, while in others it has signally failed.
Paracentesis is generally regarded as the most efficacious treatment,
and may be carried out upon the principles usually applied in the
treatment of hydrothorax. Bird recommends that the trocar should be not
less than six inches long and of the smallest diameter that is made,
always providing that it is strong enough to bear the strain of a firm
pressure. Cysts can be tapped in this manner even when they are
separated from the chest-wall by quite a deep layer of lung-substance.
This treatment should be practised at the earliest possible period in
the life of the cyst. Speaking of the aspirator, he says that cases
always do so well if tapped early enough with the simple trocar and
canula that aspiration is not required. The gradual expansion of the
lung as the cyst is emptied is sufficient to expel all the fluid,
especially if aided by the effects of coughing. In exceptional cases of
old standing, where there is a thick adventitious external wall to the
cyst, which is generally closely adherent to the ribs, or again in
cysts of the pleura, a free antecedent incision of the external tissues
is sometimes required. It has been suggested by different authors that
tincture of iodine should be injected after
aspiration to secure
the obliteration of the cyst by inflammation. The injection of carbolic
or salicylic acid under the same conditions has been practised with
success by Mosler and others.
The treatment of old suppurating cysts is rather different. The centre
of the sac, as nearly as can be judged, is fixed upon, and an incision
is then made through the skin and muscles, and the largest-sized trocar
and canula that will pass between the ribs is introduced into the sac.
This gives exit to a quantity of pus, even chalky substances and
fragments of cysts of different sizes. The opening must be free and
kept patulous for some weeks, and the sac should be daily washed out
with some disinfecting solution through the drainage-tube. Some delay
is always necessary to allow of the separation of the parent cyst from
its nidus and the gradual expansion of the lung. Immediate attempts at
its removal by forceps are generally unsuccessful, and portions are
very apt to be left behind. Several complications may interfere with
the success of the operation. One is the unavoidable piercing of a
small bronchus by the trocar. After the operation the wound of the
bronchus may remain patulous and a violent paroxysmal cough comes on,
with subsequent possible evacuation of the cyst through this channel.
The bronchial tubes, however, have been opened in operative treatment
of pulmonary cavities without serious result. When the parent cyst has
progressed to maturity quite unhindered, and is stuffed full of
daughter cysts, it has been recommended in such cases to introduce the
stylet and endeavor with its sharp point to stir up and break down the
smaller cysts as much as possible. The thermo-cautery has recently been
used successfully by Mosler to afford a means of penetrating the cyst
in the treatment of pulmonary hydatids. The tissues of the thoracic
wall must be first divided down to the pleura, as recommended in the
opening of pulmonary vomica by the thermo-cautery. Resection of the
ribs should be practised in case sufficient drainage cannot be
accomplished through an interspace.
Before applying to these operative measures it is desirable that
adhesions should have occurred between the visceral and the parietal
pleura. Fenger and Hollister recommend the introduction of a needle as
a means of diagnosis: if there be adhesions, it is unaffected by
respiration; if no adhesions exist, it is moved synchronously with the
breathing. There are, however, no absolutely reliable signs by which
this adhesion can be determined. Paracentesis of suppurating sacs has
been performed in cases in which the pleural surfaces have not been
adherent. In some instances the lung has been stitched to the opening
in the pleura, and after partial adhesion has occurred the purulent
collection has been punctured. In certain other cases, when pleural
adhesions have been absent, paracentesis has not been followed by
serious pneumothorax, possibly because the apposition of the pleural
surfaces is maintained by the tendency to cohesion which exists, and
after operative interference these surfaces are united by adhesive
inflammation.
Acute miliary tuberculosis may be defined to be an acute disease
characterized by an eruption in one or all of the organs of the body of
small nodular or granular masses called tubercles, attended with fever
and various other functional disturbances.
The fact which Villemin and Klebs were the first to show,1 and which
hundreds of others have since verified, that tuberculosis can be
conveyed by inoculation to certain animals, and the additional fact
that Koch and his followers seem to have identified the infective
material in the micro-organism which he has named bacillus
tuberculosis, would seem to justify our placing tuberculosis, along
with variola, measles, etc., among the acute contagious infectious
diseases. But since some able pathologists still deny the correctness
of Koch's conclusions; since in certain animals indifferent irritants
have excited a disease which could not be distinguished from
tuberculosis by the ablest pathologists of Europe and America; since to
some species of animals even more nearly allied to man by their
organism than rabbits and guinea-pigs the disease cannot be conveyed at
all, and that even to some of the latter inoculation fails to transmit
it; and, above all, since there is, as far as we know, not one single
case on record in which the disease has been clearly and unmistakably
traced from man to man in the order of infection,—we do not think that
as yet we are justified in defining it as a contagious infectious
disease purely and only. Everybody will take small-pox if not protected
by vaccination or inoculation, and this disease may be transmitted in a
modified form to many of the lower animals. The same may be said of
measles, scarlatina, and nearly all other diseases known to be
contagious and infectious. Since, then, so few persons take
tuberculosis that the evidence of its contagiousness rests upon a vague
popular belief, and since even some animals of a species known to be
peculiarly susceptible to the disease fail to take it even by
inoculation, we think that we are justified in assuming that there must
be something else besides a contagium required to produce the disease.
This is evidently a predisposition which depends upon some peculiar
diathesis, cachexia, or dyscrasia, congenital or acquired. It has been
assumed that scrofula constitutes the particular diathetic condition
which predisposes to tuberculosis, and it is common for scrofulosis and
tuberculosis to be spoken of as convertible terms. In the article on
SCROFULA in this work we have already given our reasons for dissent
from this view, and to that article the reader is referred. Farther on
we shall give our views as to what constitutes the tubercular diathesis
when we shall speak of the mode of formation of tubercle.
1 But Buhl had long before advanced the doctrine that
tuberculosis was a resorption disease.
While, then, we cannot as yet admit that acute miliary tuberculosis is
always and only set up by a contagium, it is unquestionably true that
it is in a large majority of instances caused by an infective material,
which, however,
does not come from without, but is produced
within the system. This material is the purulent detritus resulting
from the softening and breaking down of the inflammatory and other
cellular hyperplasias which have undergone the caseous degeneration. It
seems to make little difference whether the caseous product was derived
from scrofulous glandular hyperplasia, catarrho-pneumonia, inflammation
of serous membranes with a cellular exudation, or ordinary cellular
inflammation; the only essential prerequisites being that there shall
exist a cellular exudation or proliferation, and that these cells shall
undergo the caseous degeneration.
The inoculation of this material into certain species of the lower
animals or its absorption into the blood of a human being predisposed
to tuberculosis will, as a rule, produce tuberculosis. Koch and his
disciples add to the foregoing another prerequisite—viz. that the
caseous matter must contain the bacillus tuberculosis. But as the
bacillus is generally found in all the cheesy inflammatory products we
have mentioned, they have (ignoring Virchow's definition of tubercle)
declared that all these are tubercle, thus very much enlarging the
hitherto accepted doctrine upon this subject. But if any of the cheesy
products are found not to contain the bacillus, then such product is
not tubercle, whatever may be the apparent identity or dissimilarity in
their etiology, microscopical appearances, or clinical history. This
seems to us to be a begging of the whole question of the relation of
the bacillus to tubercle, and in the absence of fuller experimentation
and investigation involves an assumption which cannot yet be admitted.
While the absorption of caseous pus is undoubtedly by far the most
frequent cause of miliary tuberculosis, it cannot be inferred that all
who may happen to have foci of caseous degenerations will necessarily
be attacked by tuberculosis. On the contrary, a vast majority escape,
and it is almost surprising how few of those who suffer from scrofulous
inflammation of glands, joints, etc. become the subjects of miliary
tuberculosis. Many cases of pulmonary phthisis also, originating as a
cheesy pneumonia, run their course without any distinct tubercular
complication. We can only explain these exemptions from the tubercular
process by supposing that in such cases the predisposition to
tuberculosis does not exist—they do not have the tubercular
diathesis—or that such persons possess a peculiar means of resistance
to the entrance of the infecting material into their blood.
Other diseases are supposed to favor the tubercular process, either by
directly exciting or increasing the predisposition to it. Among others,
measles, whooping cough, and typhoid fever have been regarded as
specially liable to be followed by tuberculosis. Bad air, poor or
insufficient food, onanism or other forms of sexual excess, severe
study with insufficient exercise, and, in short, anything which impairs
the strength or lowers the vitality, have been heretofore considered as
excitants or predisposers of the disease. Admitting all these causes as
effective in either exciting it or increasing the predisposition to it,
there still remains quite a large residuum of cases in which the
disease can be traced to none of these causes, and which, for the want
of more accurate knowledge, we are compelled to call idiopathic or
spontaneous. Such are those cases of tubercular meningitis occurring in
young children heretofore in apparent good health, and in whom no
traces of caseous degeneration can anywhere be found. It is true that
it may be asserted that these children may have been infected through
kissing by persons suffering from pulmonary consumption; but if this
were so the disease ought to be far more frequent than it is, since the
habit of kissing babies is universal and consumption the most
prevailing of all diseases. In the absence of any proof to the
contrary, we think that we are justified in believing that these are
cases of spontaneous tuberculosis, occurring in consequence of
intensity of the diathesis, either inherited or acquired.
Miliary tubercles are found in the form of small roundish nodules
ranging in size from 1/500
to 1/250 inch (submiliary tubercles), up to
the size of a millet-seed or even of a pea. When of the latter size
they are always made up of a number of submiliary tubercles. Much
larger masses are found usually in the lungs and in the mesentery, but
these will generally be found to consist not of miliary or submiliary
tubercles alone, but of cellular new formations derived from
endothelial or lymphatic proliferations excited by the presence of
tubercles, and therefore mixed with them. When first formed they are
grayish in color, somewhat translucent, and tolerably firm to the touch
(gray granulations). They soon, however, undergo partial fatty
degeneration (this degeneration usually commencing in the centre of the
mass), and subsequently are converted into a dry, yellowish-white, and
somewhat crumbly mass which from its resemblance to cheese is called
caseous. This sooner or later softens (the softening process beginning
also in the centre), and the mass breaks down into a fluid
detritus—tubercular pus. In some situations they never reach the
caseous and purulent stage (notably in the cerebral meninges), because
the interference with the organs or nerve-centres of animal life
excited by their presence destroys the patient before there is time for
the accomplishment of these changes. The subsequent history of tubercle
depends upon the condition of the patient, his powers of resistance,
the intensity of the tubercular diathesis, the injury inflicted by the
first eruption, and the appearance of secondary eruptions. If all
conditions are favorable, the patient placed under proper hygienic
conditions and properly treated, the first eruption will also be the
last, and the tubercle dries up into an earthy mass (calcareous
degeneration), or it may remain for months, and even years, in its
caseous stage without undergoing the softening process.
If we examine a fresh tubercle under the microscope, we find, according
to Woodward2 and Zeigler,3 that it is usually made up of three
different kinds of cells: first and most abundantly, lymphoid cells
(Woodward) or white blood-cells (Zeigler); second, endothelioid cells;
and third, embryonic cells. In addition to these there is often found
(but not always) a few so-called giant-cells, generally occupying the
centre or circumference of the tubercle, and sometimes both. These
cells, which usually contain two or more nuclei and are much larger
than the ordinary lymphoid cell, were thought at one time to constitute
an essential histological feature of tubercle, and have been named
tubercular cells. But the frequent absence of these cells in genuine
tubercle has led to the conclusion that they do not possess any special
significance and are purely accidental. Each submiliary tubercle is
usually surrounded by a proliferating zone in which multinuclear
(giant) cells and fibro-plastic or spindle-form elements can be
distinguished (Cornil and Ranvier4). According to Rindfleisch,5
Woodward,6 and Zeigler,7 the cellular elements of tubercle are
always found included in a trabeculum of fine fibrillar (connective)
tissue, while Cornil and Ranvier deny the existence of any such
trabeculum, maintaining that its appearance is due to the action of
hardening agents used for preparing it for microscopic examination.
Virchow and Woodward believed that tubercle always takes its origin in
a lymphatic vessel, while Rindfleisch, partially agreeing with this
view, maintains that they most generally occur in the lymphatic sheaths
of the blood-vessels and follow the course of the latter, and that the
cells which compose the tubercle are formed by proliferation of the
endothelia of the lymphatics.
2 Medical and Surgical History of the War of the
Rebellion, Part 2, Medical Volume, p. 593.
3 General Pathological Anatomy, London, 1883, p. 171.
4 Pathological Histology, Philadelphia, p. 116.
5 Textbook of Pathological Histology, Philadelphia, 1872,
p. 125.
6 Op. cit.
7 Op. cit., p. 168.
Zeigler has not been able to demonstrate this relation of the
tubercle to a blood-vessel—that is, to an artery—but leaves us to
infer that they always arise from a capillary vessel, since he
maintains that the tubercle is primarily and principally made up of
emigrated leucocytes.
Such is a brief résumé of our knowledge as to the histology and mode of
formation of tubercle, and such are the opinions—in some particulars
agreeing, in others discordant—of those whose investigations and
observations the world regards as most complete and accurate. This
résumé is doubtless unnecessary and out of place in this article, since
this question (the histology and mode of formation of tubercle) has
been already discussed in the first volume of this work; but, as in the
explanation which is to follow of our views as to what constitutes the
tubercular diathesis and what is the mode of formation of tubercle we
shall have to frequently refer to the facts above stated, we have
thought it best, in order to save repetition and too frequent reference
to authorities, to give the above résumé of the present state of the
views of pathologists upon the histology of tubercle.
A careful consideration of the foregoing facts ought, it seems to us,
to enable us to arrive at a rational and probably correct conclusion as
to the mode of formation, as well as the principal etiological factors
concerned in the causation, of the miliary tubercle; and we venture to
offer the following explanation of the subject as more in consonance
with the facts above related than any view which we have seen upon this
question:
1. Miliary tubercles always occupy a lymph-space surrounding a
capillary blood-vessel. When found, as they quite often are, occupying
the wall of a larger vessel, artery or vein, it is still in the
lymph-sheath of a capillary of the vasa vasorum that they primarily
originated. And it may be said that this is the most dangerous site a
tubercle can occupy, because when softening takes place it is so apt to
burst into the lumen of the vessel and so produce a general infection.
2. The tubercular process consists at first of an undue or excessive
emigration of leucocytes through the walls of a capillary which runs
through a lymph-space, and where, of course, the walls of the vessel
are less firmly supported. Those cells whose vitality is lowered by the
causes which have preceded and excited the process can neither undergo
any process of differentiation nor wander on through the lymphatics;
they remain in the lymph-space, which they crowd and block up, and
finally by their pressure occlude, the capillary vessel from which they
emigrated. Until this event occurs they still retain a feeble vitality,
and even abortive attempts at proliferation are seen, which, however,
only reach the stage of division of the nucleus, the body of the cell
meanwhile swelling up by imbibition and thus forming the so-called
giant-cell. As soon as the capillary vessel becomes occluded further
addition to the incipient tubercle from this source ceases; nutrition
is now entirely cut off, and the cells, dying, become a foreign
substance, and soon undergo the caseous degeneration. But by their
presence they now excite a quasi-inflammatory process in the endothelia
lining the lymph-space, and hence we have a secondary addition to the
tubercle derived from the proliferating endothelia. Lastly, the
inflammatory process extends to the connective-tissue cells around the
lymph-space, and embryonic cells (the only cells capable of resulting
from connective-tissue inflammation) are added to the mass. This
constitutes the proliferating zone, consisting of many nucleated cells
and fibro-plastic and spindle-form elements, described by Cornil and
Ranvier.8
8 Loc. cit.
As soon as one capillary vessel becomes entirely occluded, the
neighboring ones become distended by a collateral hyperæmia, and the
same process of cell-exudation or emigration begins; and thus the
process goes on until all the capillaries supplied by a single arterial
twig take part in the process, and
one of the larger tubercles is
thus formed by an almost innumerable number of smaller (submiliary)
ones. It would seem to be quite probable that the trabeculum which
Rindfleisch, Woodward, and Zeigler described, and which Cornil and
Ranvier denied, consists of the remains of the connective-tissue fibres
which originally existed between the capillaries successively attacked
by the tubercular process.
In the lungs this process is usually complicated by a true
catarrho-pneumonic inflammation. The tubercle deposited beneath the
lining membrane of the air-sacs sets up inflammation in that membrane,
giving rise to abundant proliferation of the endothelia as well as
emigration of leucocytes, so that the air-sac becomes packed with cells
which may finally undergo caseation, and then cannot be distinguished
from the original tubercle which started the process. If the eruption
of tubercles should be very abundant, life may be destroyed by the
pneumonic process before caseation has even begun in the inflammatory
products. We have quite recently observed a case of this kind. A man
came to the city hospital (Baltimore, Md.) who presented all the
rational and physical signs of tuberculosis of the lungs. After about
three weeks, during which there was only moderate fever, no notable
dulness, and only a few scattered crepitant râles, the temperature
suddenly rose to 104° F.; dulness appeared first over the lower third
of the right lung, which rapidly extended over that side, and
subsequently to the left side, and the man speedily died, comatose and
cyanotic. The autopsy showed the most extensive miliary tuberculosis we
had ever seen in the human lung; but in addition to the tubercles,
which were found in almost every lobule of the right lung, the air-sacs
were almost universally filled with a soft, purulent-like matter which
oozed from the cut surface, and which could be squeezed out in enormous
quantities; myriads of Koch's bacilli were found. It was interesting to
note that the apparent starting-point of this tuberculosis was two
small cavities in the apex of the left lung surrounded by
firmly-indurated walls. Neither of these cavities was larger than the
kernel of an ordinary-sized almond, and, as the induration surrounding
them did not extend to the surface of the lung, their existence was not
recognized before death. The man gave a history of cough and fever,
which had lasted several weeks, about three years before his admission
to the hospital.
More frequently, however, the reverse of the process above described
takes place. That is, a catarrho-pneumonia terminating in caseation and
softening sets up tuberculosis through absorption of the caseous pus.
Indeed, in the case above related the order of pathological processes
was, first, a catarrho-pneumonia of limited extent, a cavity or rather
cavities; second, general tuberculosis; and lastly, a secondary
catarrho-pneumonia caused by the tubercles. We believe, therefore, that
Niemeyer's remark, that "the greatest danger for the majority of
consumptives is that they are apt to become tuberculous," is not so
absurd as a distinguished American author would have us believe.
The formation, then, of tubercle we believe to be an inflammatory
process, in which we have—1st, an exudation of lymphoid cells
(leucocytes) into the lymph-spaces, and occlusion by pressure of the
capillary vessel from which the cells have escaped; 2d, inflammation
and proliferation of the endothelium lining the lymph-space; and 3d,
inflammation of the tissues nearest adjacent to the space. If this is
simple areolar connective tissue, we have a "proliferating zone
consisting of many-nucleated cells and fibro-plastic and spindle-form
elements;" if a mucous or serous membrane, the usual products of
inflammation of such membrane in other and ordinary cases.
But behind these processes there must exist something else which stands
in the relation to them of predisposing and exciting causes. This we
believe to be some anatomical and histological peculiarity, congenital
or acquired, which gives to the individual that defective organization
which is denominated the
tubercular diathesis. It seems probable
that this diathesis comprises two factors—viz.: 1st, an unusual
thinness, and consequently weakness, of the walls of the capillary
blood-vessels, which permits and favors a too facile emigration of the
leucocytes; and 2d, a diminished or lowered vitality of the leucocytes themselves.
Both of these factors may exist at the birth of the individual as an
inheritance from his progenitors, or both may be produced by causes
which impair the general nutrition during either intra-uterine life or
during the earlier infancy of the subject. Or one of them may exist
without the other, and the animal thus escape for a long time, though
exposed to the exciting causes of the disease. Sternburg's guinea-pigs
(animals peculiarly susceptible to tuberculosis) remained healthy while
enjoying the freedom of grassy fields, although inoculated with Koch's
bacilli, which were found in their blood and tissues when killed, while
those that were confined in cages under bad hygienic conditions
speedily succumbed after a similar inoculation.9 If the first of
these factors exist, any exhausting disease producing a dyscrasia,
habits or hygienic conditions which tend to impair the nutritive
functions, even psychological and emotional influences which take away
the appetite for food or impair the functions of digestion—anything,
in fact, which tends to degrade the quality of the blood and diminish
the functional activity of the white blood-cell—may furnish the second
factor constituting the tubercular diathesis. Both factors being
present, it only requires an uncertain increase of the blood-pressure,
causing a dilatation of the capillaries, to ensure that increased
leucopedesis which constitutes the first step in the tubercular
process.10 A protracted fever, therefore, of any kind, may furnish
both the second factor in the tubercular diathesis and the exciting
cause of the tubercular process itself; while any fever or any irritant
capable of exciting fever or reaction against its presence occurring in
man or other animal that happens to have the complete tubercular
diathesis may excite tuberculosis. Koch's bacillus will undoubtedly
excite tuberculosis in animals (and probably also in man) that have the
tubercular diathesis complete; but it does so only by exciting that
inflammatory and febrile reaction against its presence in the blood
which other and perhaps indifferent irritants may also excite. In
rabbits and guinea-pigs confined in cages, and therefore under
unnatural and unhygienic conditions, it suffices to excite the disease
only to introduce the bacillus into any part of their tissues: that it
will not do so in guinea-pigs that are healthy and kept under natural
conditions and surroundings Sternburg's experiments, alluded to above,
clearly prove. It is true that other animals that are regarded as
ordinarily non-tuberculous can also be inoculated with the bacillus
with affirmative results, provided the bacillus is introduced into the
eye or other serous membranes; but we must not forget that the pain and
injury of such an operation will almost inevitably produce that
deterioration of the health and impairment of cell-vitality which we
maintain constitutes so essential a part of the tubercular diathesis.
That the bacillus tuberculosis is always found in tubercle is
undoubtedly true; but it is there because tubercle furnishes the most
favorable and congenial breeding-place for it. Some special microbe is
found in almost every special inflammatory product—vibriones in the
pus of abscess, gonococcus in urethral inflammation, micrococcus in
diphtheria, etc.—but no one, we believe, now holds that these various
microbes are the causes of these diseases, since inoculation with pure
cultures have given entirely negative results. While we believe,
therefore, that the bacillus of Koch can excite tuberculosis in man or
animal having the tubercular diathesis, we
also believe that it
does so because of its property of exciting that amount of irritation
and reaction necessary to initiate the tubercular process—a property,
however, possessed by many other irritants; and while it is probable
that a few cases may be thus produced in man, a vast majority of the
cases arise independently of its presence. And hence we maintain that
tuberculosis is not a specific contagious disease in the sense that it
is only produced by a special contagion, as small-pox and other similar
diseases are.
9 Journal of the American Medical Association, vol. iv.
No. 12, p. 314.
10 We hold that leucopedesis is a normal physiological
process that is always going on during the period of active growth of
the individual, as well as during the process of repair.
Primary acute miliary tuberculosis occurs only in the young or early
adult period of life, for the reason, perhaps, that persons of the
tubercular diathesis can hardly long escape the exciting causes of the
disease, and so are attacked early. Persons possessing what may be
called the incomplete or partial diathesis may be attacked by a
secondary miliary tuberculosis at any, even the most advanced, age; but
it will be found that in all such cases of late tubercularization there
has occurred a direct infection of the blood by absorption of caseous
detritus from a softening cheesy pneumonia or cavity. "In 28 out of 52
cases collected by Litten, it was associated with pulmonary phthisis,
and this accords with general experience" (Roberts11).
11 Practice of Medicine, 5th ed., p. 301.
Acute primary general miliary tuberculosis—that is, in which all or
nearly all the vascular tissues are attacked at once—must be one of
the rarest diseases. Such cases can only occur when the tubercular
diathesis is strongly marked and exciting causes of the most active
character have been applied. As a rule, tubercular eruptions occur in
successive crops, attacking the more vascular organs, as the lungs,
cerebral meninges, spleen, liver, serous and mucous membranes, and
bones, first and usually in the order given. Laennec's law, that if
tubercle is found in any other organ it will also be found in the lung,
is undoubtedly true, with the single exception perhaps of tubercular
meningitis. If our explanation of the causes and mode of formation of
tubercle is correct, we must a priori expect to find that a tissue so
soft and spongy as the lung, and which is so vascular and subject to
such great and sudden alterations of pressure and relaxation, would
naturally be the site of the first formation of tubercle.
SYMPTOMS AND COURSE.—It is impossible to give a clear or lucid
description of acute miliary tuberculosis, since there cannot be said
to be any constant or pathognomonic symptoms produced by the disease
per se. The symptoms present in any given case depend upon the organs
involved, and may be said to consist merely of those furnished by such
organs when invaded by inflammation. Fever is present in all cases. The
grade or height of this fever will depend upon the number and extent of
tubercular formations, and to some extent upon the organs involved. It
will generally be highest in tubercle of the serous membranes, and of
the lungs next. In general miliary tuberculosis the fever is highest,
and can be distinguished with difficulty from enteric fever. If the
intestinal mucous membranes are involved, and diarrhoea consequently
exist, the differential diagnosis will be almost impossible. The fever,
following the law of nearly all inflammatory and symptomatic fevers, is
usually remittent, and the remissions and exacerbations correspond to
the normal diurnal variations of temperature—lowest in the morning,
highest in the evening. The remissions are also usually attended with
perspiration, sometimes profuse, at others moderate. The patient early
falls into that condition of prostration and general exhaustion which
speedily comes on in all fevers of high temperature and protracted
duration expressed by the term typhoidal state. Even the pains
ordinarily complained of in inflammation of various organs are not
felt, or if felt at all are seldom mentioned; which perhaps helps to
render the diagnosis more difficult. Almost the only exception to this
is when the cerebral meninges are early affected, in which case
unusually severe headache may be complained of. Cough may be present,
but is not more troublesome than in many cases of enteric fever,
and is quite out of proportion to the lesions found in the lungs and
pulmonary mucous and serous membranes. The expectoration varies, and is
sometimes entirely absent. Generally, it is moderate and consists of
frothy serum, occasionally streaked with blood. Hæmoptysis is said to
be occasionally present, but must be extremely rare. Respiration is
notably frequent early in the disease, and in the absence of pronounced
physical signs of pulmonary lesions is perhaps one of the most reliable
and pathognomonic signs present. Respirations are often as frequent as
60, seldom less than 30, per minute. The pulse is usually rapid,
generally hard at first, but soon becoming soft and weak. The rate
varies between 110 to 120 to 160 or more late in the disease.
The disease runs a rapid and invariably fatal course, often ending
within the first fortnight, seldom lasting as long as two months.
Tubercles, miliary and submiliary, are found after death in almost all
the vascular organs, varying much, however, in number in various
organs, and often presenting different stages of development. In some,
and especially in the lungs, tubercles will be found already in a state
of incipient softening, others still firm and yellow (caseous), and
others still grayish and semi-translucent, showing, we think, a
different period of eruption, and demonstrating the correctness of our
observation that miliary tubercles are always formed in successive crops.
If the tuberculosis is associated with inflammatory phthisis, and, as
is the case in a majority of instances, has been caused by absorption
of caseous detritus, large masses of caseous matter may be found in the
lung, either in a softening condition, or cavities will be met with
empty or partially filled with pus, and surrounded by indurated walls
the result of interstitial pneumonia. These caseous masses and cavities
are, in our view, the result of precedent catarrhs or croupous
pneumonias, and not a result of the tubercular process.
Partial or local miliary tuberculosis is a much more frequent
occurrence than the general disease above described. It occurs most
frequently in persons under twenty-five years of age, and in a very
large majority of cases between the ages of two and twenty. It occurs
also most generally in the lungs first in point of frequency, in the
mesentery next, and last in the cerebral meninges. Of course a
secondary general tuberculosis may result in any of these cases from
resorption, except in the meningeal variety, which generally destroys
life before there is time for secondary infection.
Acute miliary tuberculosis may occur in the young as a consequence of
measles and other exanthematous fevers, whooping cough, typhoid fever,
and various other affections which seriously impair nutrition.
According to our own observation, it is most likely to attack boys and
girls soon after puberty who are pursuing too severe a course of study
in school with insufficient exercise in the open air, and perhaps also
those evil practices unfortunately too common in both sexes. Tubercular
meningitis as an idiopathic affection (that is, without the previous or
concurrent deposit of tubercles elsewhere) is almost exclusively met
with in children between two and seven years, but secondary
tuberculosis of the meninges may occur at any age. We have seen two
cases of pulmonary phthisis, one of three and one of three and a half
years' duration, and who bid fair to live for a long time, suddenly
carried off by tubercular meningitis. Both of these persons were past
thirty years of age.
Tuberculosis of the mesentery, peritoneum, and liver (for they are
sometimes found in all three of these organs) is invariably either
coincident with a general tuberculosis or the secondary consequence of
scrofulous inflammation of the intestinal glands. Quite often here the
tubercular process is associated with the scrofulous process, and large
masses of caseous material will be found in the mesenteric system of glands.
As in general miliary tuberculosis there are no symptoms by which
the disease can be positively recognized, so too in the partial or
local disease there are absolutely no pathognomonic signs. We may say
in general terms that if a person who is known to have had a pneumonia
which has ended in a permanent consolidation of any considerable
portion of one or both lungs, and who has for some time presented the
symptoms, however slight, of chronic pulmonary phthisis, is suddenly
attacked with fever and night-sweats; or, if fever has already existed,
the temperature rises considerably above the previous average, with
increase of cough; or if an uncontrollable diarrhoea sets in; or if
headache and delirium should suddenly occur—delirium out of proportion
to the fever,—then we are justified in believing that tuberculosis of
the lungs, mucous membrane of the bowels, or arachnoid has occurred. Or
if a young person of either sex, such as above described, should, after
becoming pale and anæmic, begin to have slight fever with a dry,
hacking cough, at first without expectoration or with a frothy
muco-serous expectoration, which for an unusual length of time
continues to retain this characteristic, and this fever and cough
cannot be otherwise accounted for, then the existence of pulmonary
tuberculosis is rendered extremely probable, although there is neither
history nor evidence of preceding pneumonia or scrofulous glandular
degeneration. If a few scattered and slight crepitant râles can be
heard over one or both lungs without alteration of pulmonary resonance,
and the respiratory rate is much too frequent for the temperature and
pulse, then the diagnosis becomes almost absolutely certain.
Unfortunately, this scattered or diffuse crepitant râle is often
absent, and there are absolutely no physical signs whatever of the
deadly mischief going on in the lungs.
Prolonged expiratory movement is spoken of by some as one of the
reliable signs of tuberculosis, but as this sign is usually present in
almost all forms of chronic pulmonary disease, its significance cannot
be relied upon. Or if a child over two and under ten years of age,
after showing evidences of malnutrition, should suddenly be attacked
with fever of moderate temperature, become restless and fretful, should
frequently vomit and retch even when the stomach is empty, and begin to
have convulsions, with squinting and trismus, and if old enough
complain of severe pain in the head, have a rapid, frequent, but
irregular or slow and intermitting pulse,—if these symptoms become
exaggerated at night and somewhat mitigated in the daytime, the
diagnosis of tubercular meningitis may be made with tolerable certainty.
It would take more space than is allotted to this article to describe
all the phases of tuberculosis: we shall therefore summarize the
symptoms of this disease by saying again that the signs and symptoms of
tuberculosis are simply those of inflammation with fever and such
derangements of function and other local disorders as would be
furnished by inflammation of any given organ under other circumstances,
except that the pain produced by tubercular inflammation is not usually
so severe as in other inflammations, and hence diagnosis is not always
so easy as in the latter. For it is a remarkable fact that in tubercle
of the peritoneum—an organ which in a state of inflammation usually
gives such excruciating pain—this symptom is often not complained of,
and the existence of tuberculosis not suspected until after a
post-mortem. The same may be said of tubercle of the meninges. Pain is
often not complained of, and is never so severe as in ordinary meningitis.
TREATMENT.—In acute general tuberculosis no treatment will be of any
avail. All that can be done is to moderate the fever and support
nutrition by appropriate food. For the first, quinia in large doses is
undoubtedly the best remedy. It should be given in one or at most two
doses daily. Twenty grains should be given early in the morning, and
this dose repeated at 1 o'clock P.M., or thirty to forty grains may be
given in a single dose about 8 or 9 o'clock A.M. Antipyrine should
prove a valuable antipyretic in these
cases, and, being probably
equally effective, produces less disorder of the nervous system and
digestive functions than the salt of cinchona. Judging from what we
have seen of its effects in other fevers and inflammations, fifteen to
twenty grains repeated about four times in the twenty-four hours should
keep the temperature very near normal.
For the second indication milk and raw eggs constitute the best diet.
Brandy or whiskey in the form of eggnog or milk-punch is useful, and in
the latter stages indispensable. It should not be forgotten that
according to the latest observations muriatic acid disappears from the
gastric juice of fever patients, and that its power to digest animal
food is therefore very much impaired. This should be supplied,
therefore, by giving after every ingestion of milk, eggs, or other
animal food ten to fifteen drops of dilute hydrochloric acid in a
sufficient quantity of water. Peptone will also aid in the proper
digestion of protein substances, and should therefore be added to the
acid. Some of the liquid peptone sold by manufacturing chemists
contains hydrochloric acid, and would therefore meet both these indications.
By these means we may doubtless prolong the life of the patient and
promote his comfort or at least diminish his suffering, and if a cure
is possible secure it. Tuberculosis of the mesentery and peritoneum, as
well as tuberculosis of the cerebral meninges, will generally prove
fatal, the one by impairing the chylo- and hæmatopoietic functions, the
other by injury to the central nervous system, though Hartshorne of
Philadelphia reports one case of the latter in which temporary recovery
lasting one month took place, and quotes two cases by Guersant in the
Dictionnaire de Médecine (1839) in which also partial recovery,
lasting five weeks and two months respectively, occurred. "May we not
imagine, however," says Hartshorne, "that if such convalescence could
last two months, it might in a case affected with nearly similar
lesions be prolonged indefinitely?"12 I am informed that a case of
permanent recovery has been reported in England, but I have not been
able to obtain the reference. To these I have to add a case of my own
in which recovery has been maintained for a little more than nine
months. In this case, a boy of twenty-six months, the convulsions were
controlled for many days by hypodermic injections of morphia, while
quinia was given by the mouth when possible, and otherwise by the
rectum; and, though he had left hemiplegia and was for a time both
blind and deaf, he recovered entirely in about six weeks, and has
remained well.
12 Reynolds's System of Medicine, Am. ed., Philadelphia,
1880, vol. i. pp. 826, 827.
In pulmonary miliary tuberculosis the treatment is by no means so
hopeless if the disease is promptly recognized and actively treated.
The thing to be accomplished in this case is to prevent secondary
eruptions and the softening of the tubercles already formed. We know
that this last can be done in caseous deposits resulting from
catarrho-pneumonia, and we also know that tubercle can be maintained in
a quiet state or be made to dry up by calcareous impregnation or
degeneration for an indefinite time, since post-mortems often show old
tubercles in one or the other of these conditions. We know of one man
who carried a caseous lung for nineteen years, coughing more or less
during all that time, but in a sufficiently good state of health and
strength to follow his occupation of ship-carpenter, but who died at
last from phthisis; while another, a farmer living in one of the
Southern States, has lived in fair health, with his left lung indurated
from top to bottom, for twenty-four years. There cannot be a doubt,
therefore, that if secondary crops of tubercles are prevented, and a
perfect state of health and general nutrition maintained, the tubercles
may remain quiescent in their cheesy condition or may undergo
calcareous degeneration and dry up into inert and innocuous masses
incapable of further harm.
The first and most important indication, therefore, in the treatment of
tuberculosis is to suppress the fever; for as long as this
continues new tubercles will continue to form, since the fever is both
a predisposing and exciting cause. Quinia, therefore, or antipyrine,
should be given as directed in general tuberculosis. The patient should
be put to bed and not permitted to go about until the arrest of fever
seems permanent. Nutrition should be supported and promoted also by the
same means already indicated. As soon as the fever is permanently
arrested (but not before) the patient should be permitted to take
gentle exercise in the open air, and should be encouraged to spend as
much time as possible out of doors, and if able to do so should be sent
during the winter to that climate or place where, on account of its
warmth and dryness, the most time can be spent in the open air.
Hypophosphites of lime and soda should be given constantly, and
cod-liver oil also if the stomach can tolerate it. Large doses of the
oil are useless, and often hurtful, a dessert-spoonful being quite as
much as most stomachs can bear without exciting unpleasant eructations
and nausea. The appetite and digestion are best excited by tincture or
extract of cinchona and nux vomica. Iron we have found to be of little
use, and often hurtful. We much prefer small doses of arsenic (two to
five drops of Fowler's solution), and if there is much bronchitis this
will be found especially useful. Some persons, however, cannot tolerate
arsenic in any dose. The patient should carry a clinical thermometer,
and as soon as the slightest fever is detected he should go to bed and
active antipyretic treatment should be instituted, the tonics and
alteratives being meanwhile suspended. If cough is troublesome (but not
otherwise), one to two grains of codeia should be given two or three
times a day or as often as may be found necessary. This is much
preferable to morphia or other preparations of opium, which constipate
the bowels, dry the mouth, impair the appetite, and so stupefy the
patient that all inclination or even ability to take exercise in the
open air is destroyed. Codeia is amenable to none of these objections.
Guided by these principles, we think we have successfully treated many
cases of primary pulmonary tuberculosis—many in which the hereditary
predisposition was strongly marked and the diagnosis unquestionable. It
is true that many of these cases have relapsed and died after a
variable period, but others have remained well for several years, and
still others permanently.
DEFINITION.—Inflammation, partial or general, of one or both pleuræ.
SYNONYMS. Pleuritis ([Greek: pleuritis]) morbus lateralis; Morbus
pleuriticus (Celsus); Pneumona pleuritis (Cullen). Fr. Pleurésie;
Ger. Seitenstich.
HISTORY.—Pleurisy derives its name from the accompanying pain in the
side, usually its most prominent symptom. In the sense in which
Hippocrates used the word [Greek: pleuritis], it meant all kinds of
pain in the side, especially such as are of a violent character.
Pleurisy was mentioned by Celsus, and was still better defined by
Galen. Æctæus, however, was the first to describe it with precision and
to speak of its treatment. These ancient authors viewed the disease as
seated in the layer of the pleura lining the ribs or external parietes
of the chest. More modern writers contended that the disease was more
frequently in the expansion of the pleura over the lungs and other
parts. Boerhaave and Van Swieten contended for the separate and
distinct affection of the pleura. Sydenham, Hoffman, and Morgagni
believed that the pleura and the substance of the lung were generally
both implicated. Pinel was the first to definitely establish the
difference between pleurisy and pneumonia from the anatomical lesions.
Laennec laid the foundation of our present knowledge. He was followed
by Andral, Chomel, Louis, and Cruveilhier in Paris, and by Forbes and
Williams of London and Stokes of Dublin. They demonstrated, by the
physical signs and general symptoms during life and by the post-mortem
lesions, that inflammation may commence in and be limited to the pleura
in some cases, and in others that it may extend to and involve the
lungs. Again, they showed that in some instances the lung may be
inflamed without involving the pleura generally, yet that in the large
proportion of cases the disease may originate in one organ and extend
in a greater or less degree to the other, thus implicating both of
them. Previous to Laennec the incomplete anatomical knowledge of the
nature of the serous membrane, the pleura, as a capsule of the lungs,
and the thoracic organs and walls, as well as the theoretical views of
the nature of inflammation as a morbid process, led to erroneous views.
Their diagnoses were made from general symptoms only. Pleurisy was
considered the more common disease. Avenbrugger, Corvisart, and
Laennec, by their discoveries of the accurate physical modes of
exploration of chest diseases, gave far more reliable data for
differential diagnosis. Now we have, in addition to the general
symptoms, the modern refinements in auscultation and percussion, the
delicate measurements of Woillez's cyrtometer, Ransome's stethometer,
and Pravaz's and Alex. Wood's hypodermic exploring-needles to enable us
to attain great accuracy in the diagnosis.
CLASSIFICATION.—Pleurisy is one of the most common diseases of the
respiratory apparatus. Though apparently simple, careful study
shows it to be extremely complex. It occurs in very different forms and
in a great many modifications, according to the producing causes and
the numerous lesions which follow its course. We might classify the
forms of pleurisy, according to their causes, as primary or secondary,
tubercular, traumatic, etc.; or we could designate them according to
their anatomical lesions, as dry pleurisy, pleurisy with effusion,
general or parietal pleurisy, encysted, multilocular, purulent,
hemorrhagic, etc. A methodical classification of all these forms is
difficult if we attempt to base it upon the prominent characteristics
or the lesions. We prefer a classification which enables us to study
separately the clinical varieties which are most frequently met with,
and therefore the most important. The symptomatology shows that the
inflammatory process in pleurisy is of different degrees of intensity.
We propose for our study to divide them into two main groups, according
to the nature of the exudation:
| Fibro-serous pleurisy, |
Acute,
Chronic. |
| Purulent pleurisy, |
Acute,
Chronic. |
They may be local or general. When they result from disease of
neighboring parts, they are generally local. Each of these groups
comprehends primary and secondary varieties.
In the first, we have an exudation resembling the plasma of the blood.
The effusion is not serous, for the fluid is spontaneously coagulable,
whereas serum is not. It is not properly termed fibrinous, for it
contains more albumen than fibrin. Fibro-serous is the most accurate
term by which to designate it. The watery portion gravitates to the
lowest part of the cavity, while the plastic deposit is thrown out over
the two surfaces of the pleura. In the most acute forms the general
symptoms, especially the pain and fever, are well marked. The exudation
is at first largely fibrinous, but it is afterward more fluid in its
character. In milder cases, the latent variety of the older authors,
frequently designated as the subacute form, the subjective symptoms are
so slight that the individual is not aware of his condition until the
exudation, which is largely sero-fibrinous, mechanically interferes
with his respiration. When first recognized these cases are really
often chronic. They frequently remain sero-fibrinous in their character
for a long time. Sometimes they become sero-purulent (the intermediary
variety), and later purulent. Purulent pleurisies (empyema) are those
where pus is the product of the inflammatory action. They may be acute
(empyema d'emblée) or the result of transformation of acute or chronic
fibro-serous pleurisies.
By this division we shall be able to take into consideration the
fundamental causes of all the forms of pleurisy. Starting from the
simple primary form, we shall be able to study special varieties of
secondary pleurisies, such as tubercular and rheumatic.
Next, we shall examine separately the hemorrhagic variety as distinct
from hæmothorax. The localized forms, such as the interlobular,
diaphragmatic, and mediastinal, will be studied as varieties caused by
their development in different localities.
The simplest plan to elucidate the whole subject of pleurisy is to
analyze carefully, in the first place, the unquestionably acute
disease, primary pleurisy, and afterward to connect with it the study
of the several forms and varieties. Acute primary pleurisy has a
sero-fibrinous exudation, and is the most common form of the disease.
In it are best defined the usual characteristics of this inflammation.
We consider this the principal type of this class, and with it shall
study the development and character common to all the varieties of
inflammation of the serous membrane of the thoracic cavity.
PATHOLOGICAL ANATOMY OF FIBRO-SEROUS
PLEURISY.—The anatomical
changes in all forms of pleurisy begin by hyperæmia of the vessels of
the serous membrane and of the subserous connective tissue. This is
followed by an exudation of a liquid, a pseudo-membranous deposit. In
acute primary cases this is first noticed on the costal pleura. The
pleura itself shows, by puffiness and oedema with red points and small
ecchymosed spots, that the inflammatory process has affected it. In a
few hours, in acute cases, there is found a thin deposit of fibrinous
lymph of a reddish-yellow tinge, with more ecchymosed spots, resulting
from the rupture of fine capillary vessels. The pleura is somewhat
thickened and loses its transparency, and is studded with very fine
granulations. Under the microscope it is shown that the epithelial
cells are swollen, that their number has been largely increased by
proliferation, and that they have been detached in great quantities.
The granulations are scattered over the pleural surfaces, and separate
the pleura from the fibrinous deposit. The connective tissue is loaded
with liquid, in which are found in increased quantity leucocytes which
have migrated through the walls of the blood-vessels.
Over the surface of the pleura there is a tissue of granulations
composed of embryonic cells, which are derived from the proliferation
of the elements of the connective tissue. In this tissue of new
formation we find new blood-vessels coming from those belonging to the
subserous tissue, which advances through small points, even to the free
surface of the granulations. These vessels are very thin and brittle.
They sometimes rupture and cause ecchymoses of the pleura and of the
false fibrinous membranes—sometimes effusions of blood, which,
becoming mixed with the serum in the pleural cavity, cause hemorrhagic
pleurisies. This new tissue is susceptible of organization, and of
transformation progressively into a tissue analogous to that of a
cicatrix. Under the plastic exudation we find abundance of embryonic
cells, which become elongated and spindle-shaped in the formation of
new connective tissue. This is at first tender, but may become dense
and fine over circumscribed points, so as to produce bands which
enclose and touch the effusion. This is the origin of the organized
neo-membranes which are found on the surface of the pleura. It is,
moreover, this tissue of granulations which constitutes the bands which
unite the parietal to the visceral pleura, the adhesions being produced
by the contact and the union of vegetations or neo-membranes developed
on the two opposed layers of the pleura. The membranes form the
filamentous thin bands which draw obliquely together portions of the
pleural sac. These lesions are very often slight and rudimentary in
simple acute pleurisy, but are found well developed in purulent
pleurisy, especially when it is chronic. These are hyperplastic
parenchymatous lesions of the pleura. Acute inflammation of the pleura
gives rise to two distinct forms of exudation—the plastic, deposited
on the free surface of the serous layers or formed in flakes in the
fluid; and the serous, which falls into the dependent portions of the
cavity. The plastic may exceptionally exist alone. Their formation
together is the rule. Anstie questions whether the serous effusion ever
occurs without the fibrinous. The plastic exudation takes the form of
granulations more or less prominent, constituting a bed of very
irregular rough points. So long as the period of inflammation
continues, new plastic deposits are formed over the old ones. They thus
increase in thickness. The neo-membranes which play such an important
rôle in the natural history of pleurisies increase very rapidly. Little
by little, they are transformed into firm, very resisting tissues. They
may become fibrous, cartilaginous, or even calcareous in their
structure. These false membranes develop more freely at first when the
opposing surfaces are kept apart by the effused liquids. The rubbing of
the two pleuræ together seems to impede the process of organization.
According to Wagner, the lymphatics are dilated and contain a liquid
poor in corpuscles. The newly-organized and vascular
tissues
often become the starting-points of fresh inflammatory processes and of
new products.
Exudations are of two kinds—liquid and pseudo-membranous. When the
inflammation extends over a limited surface, the fibro-plastic
exudation may be the only one; in which case the disease soon
terminates with local adhesions. This is dry pleurisy, which is rarely
primary in its origin. Ordinarily, the principal lesion of acute
pleurisy consists in a sero-fibrinous effusion which collects in the
cavity of the pleura; almost always the liquid effusion exists in
decided quantity. In it there are suspended fibrinous flocculi, and on
the surface of the pleura are found false membranes. The nature of the
effused liquids has been thoroughly studied, ample opportunities having
been furnished since thoracentesis has been so extensively used. The
quantity of liquid is very variable, from a few grammes up to several
liters. The terms small, moderate, and abundant are used to designate
the quantity—one-half of a liter is considered a small quantity;
moderate, one to one and a half liters; abundant effusion, two to two
and a half liters; very abundant, when the effusion goes beyond three
liters. The liquid is transparent and of yellowish-amber color. It is
darker when the fluid has been some time in the chest, and resembles
that of bouillon. Sometimes it has a rose tint when the liquid contains
a sufficient quantity of red globules, or it may be somewhat opaque
when it encloses a large proportion of leucocytes.
The presence of a few red globules does not constitute a hemorrhagic
pleurisy, nor does the presence of a small quantity of leucocytes make
a purulent pleurisy. It is only when they are very abundant that they
severally give those characters to the effused fluid. Dieulafoy
states,1 after frequent examinations of aspirated serous fluid of
acute pleurisy, simple and frank, that it contains the smallest
quantity, from 500 to 600 red globules to the cubic millimeter, while
the white globules were from fifteen to twenty times more numerous. In
some instances he counted 1500, 2000, and even 3000, red globules to
the cubic millimeter without the coloration of the liquid being
sensibly modified. He adds that the liquid from the pleura has not a
perceptible rose tint unless it contains from 5000 to 6000 red globules
to the cubic millimeter. He concludes that there is no tendency to
transformation into purulent pleurisy unless the number of red globules
reaches 4000 or 5000 to the cubic millimeter. Rindfleisch (ed. 1869,
Leipzig) states also that upon their number and that of the
proliferated epithelial cells, with the floating flocculi, depends the
convertibility of the serous into purulent effusions.
1 De la Thoracentèse par Aspiration dans la Pleurisie
aigue, p. 42, Paris, 1878.
Chemical Character of Effused Fluid.—Mehu2 gives the composition of
the fluid as closely resembling that of the serum of the blood. He
found in it the same elements—water, albumen, fibrinogenous matter,
salts, red globules, and leucocytes. The proportion of these principal
constituents of the blood was greatly modified in the pleuritic liquid.
The quantity of water was always increased. On the other hand, the
quantity of substances in solution was greatly diminished. The
exudation was really blood-plasma, more or less diluted, in which the
relative proportion of the constituent elements varied according to the
intensity of the inflammation. It has the same alkaline reaction, and
it is spontaneously coagulable, owing to the presence of the fibrin
which is in solution in the serum, the proportion of fibrin making it
coagulate more or less rapidly. Mehu found the quantity of fibrin to
vary from 09.073 to 19.276 to the kilogramme. The same mineral
substances were found, but in less quantity, than in plasma of blood.
The intensity of the inflammation causes alterations in the composition
of the exudations. The more acute the inflammation, the greater is the
quantity of albumen and of fibrinogen. The fibrinogenous matter
contained in the
exudation is coagulated only by contact with the
air. One portion of it becomes concrete in the interior of the body in
the form of fibrinous flocculi, which float in the fluid, and in the
false membranes, which are deposited in successive layers on the
surface of the inflamed pleuræ. This coagulation takes place in a
manner analogous to that of the coagulation of the fibrin in a drop of
blood. These false membranes are almost always found in acute
pleurisies, but their development is very variable. Sometimes they are
very thin, friable, and readily disappear; again, when the inflammation
is intense, they last a long time and cover thickly both pleuræ.
Occasionally they envelop the effusion and produce veritable cysts and
localized pleurisies. Their color is opaline or semi-transparent when
recently formed, but opaque when old. Their consistence varies
according to the duration of the disease. At first they are soft,
impregnated with fluid, easy to tear or break; later on they become
resistant and almost dry. The microscope shows these false membranes to
be formed of crossed fibrillæ, with intervals containing white
blood-corpuscles, with voluminous, swollen epithelial cells of serous
membrane, proliferated and detached.
2 Arch. général de Méd., 1872.
When the pleural inflammation subsides, the exudation is destined to
disappear. Usually the cure is produced by the reabsorption of the
effused products. The liquid part of the exudation, the serosity, is
absorbed by the lymphatics, which are found frequently dilated, and
some of them are filled with fibrinous coagulations and the leucocytes.
The solid parts, the false membranes, concrete fibrin, and cells
disappear with more difficulty. They undergo granulo-fatty
metamorphosis, and are then taken up by the lymphatics.
These fibrinous false membranes are not, as was formerly supposed,
susceptible of organization. It is only the neo-membranes, formed by
the proliferation of the elements of the pleura, which are organized or
organizable. It is these that form bridles or ligaments which attach
the lung to the thoracic wall, and are susceptible of transformation
into cartilage or even into bone. In chronic cases these new membranes
bind the lung down, impair its expansive powers, and inflict great
damage upon the respiratory force.
Care must be taken to distinguish between the neo-membranes and the
plastic and liquid exudations. These last contain transitory-formed
elements entangled in the fibrinous layers. They are principally
lymph-corpuscles, containing solitary nuclei, together with a few
epithelial cells, almost always in process of disintegration, and
isolated blood-corpuscles (Fraentzel).
Distribution of Fluid.—The situation and form in which the effusions
are found in the pleural cavity furnish important data for study as
applicable especially to diagnosis. At the commencement of the disease
the effused plastic products form a thin covering to the pleural
surface—a slight cushion interposed between the lung and the thoracic
wall. Later, the fluid products gravitate by their weight to the lowest
portion of the cavity of the pleura; then, as they increase in
quantity, they gradually rise or are drawn to the superior portion of
the thorax. Once formed, these effusions are but slightly movable and
but little displaced by the varying positions of the patient, unless
the quantity be very great and no adhesions or bands have been made. If
the effusions be of viscid consistence, or if false membranes exist,
they are mechanically prevented from moving. The serous transudations
of hydrothorax always occupy the most dependent portion of the cavity,
but observation shows how frequently the pleuritic effusions are
immovable, being maintained and suspended between the diaphragm and the
lungs, and imprisoned in the situation where they form by the false membranes.
Previous to 1843 the authorities universally taught that the effused
fluids in the pleural cavity obeyed, as they would in an open vessel or
in a vacuum, the law of gravity. They never appeared to question but
that the fluid
would necessarily assume its hydrostatic level,
and consequently that it would reach a horizontal line in all parts of
the chest. The distribution and the form which the effusions take were
first studied by Damoiseau.3 Fernet and D'Heilly4 maintain that
Damoiseau perfectly established the form and disposition which the
effusions take in pleurisy. To study them well we must bear in mind,
they say, three facts: the irregularly conical form of the pleural
cavity; the effect of gravity; and the habitual position of the patient
when lying down. Damoiseau and these authors utterly ignored the
retractile force of the lung, as well as that of the diaphragm, and the
resiliency of the thoracic walls, as effecting the position of the
fluids in the pleural sac. If we observe that the patient at the
commencement lies ordinarily on his back, the thorax being raised and
more or less inclined to the horizontal position, we easily appreciate
that the effusion ought to accumulate, at first, behind, in the most
dependent portion of the costo-vertebral gutter, below the inferior
angle of the scapula; then, as it increases in quantity, it rises and
obliquely strikes the conoidal cavity, which encloses it, and makes on
its surface curves resembling those of an oblique conic section
(Damoiseau). As Damoiseau described the pleuritic line of flatness as a
parabola, it was highest in the axillary region, where it first
appears; thence, as its summit rises, its branches advance downward and
outward to the sternum and the vertebral column.
3 Thèse de Paris, 1845.
4 Nouveau Dict. de Méd. et Chir., Paris, tome xxviii.,
1880.
Since Damoiseau's first paper5 it has been generally acknowledged
that the line of flatness over the upper surface of a moderate effusion
is not horizontal when the patient is in the sitting or erect posture.
There has been considerable difference of opinion among the English6
and continental writers as to the exact disposition of the fluid: some
partially assent to Damoiseau's views; others, again, very materially
modify them. Wintrich,7 who was one of the first among the Germans to
emphasize the percussion line of demarcation between a pleuritic
effusion and a contracted lung, says: "As the exudation gradually
increases, the level of the fluid does not present a line which is
horizontal or parallel to the ground, but one which descends toward the
ground at a more or less acute angle." Fraentzel says that the line is
never horizontal. Leichtenstein and Ferber8 maintain that the line
depends upon the position of the patient early in the disease. Gee9
holds very much to this opinion. He states that the upper limit of the
surface of liquid, when it reaches as high as two inches above the
nipple, is horizontal. When lower than this, the dulness forms
irregular parabolic curves, which become smaller and smaller as they
descend. Austin Flint10 says, in his more recent edition: "The upper
limit of the dulness or flatness, the position of the body being
vertical, is not in a continuous horizontal line extending over the
posterior, lateral, and anterior aspects of the chest." Flint,
Wintrich, and Fraentzel speak of the line being highest behind. Calvin
Ellis of Boston in two very suggestive papers11 described a
curve-line made by the upper line of the effused fluid, which radically
differed from any one previously mentioned. "This curve begins, with
medium effusions, relatively low down on the back, passes outward from
the vertebral column, and soon turns upward and proceeds obliquely
across the back to the axillary region, where it reaches its highest
point. Thence it advances in a straight line, but with a slight
descent, to the sternum." Powell, however, does not find
that the
curve invariably commences at a lower level behind. G. M. Garland,12
in consequence of the resemblance of this curve to the italic letter
S, has named it, very appropriately, the letter S curve. He adds
that, according to his experience, "this curve, as described first by
Ellis, may be traced, by proper percussion, in any case of free,
uncomplicated pleurisy when the patient's body is erect and the amount
of fluid present is not excessive. As any effusion increases in amount,
the curve of its distribution gradually rises and tends to flatten out,
so that it no longer presents its characteristic S feature after it
reaches the second rib. At this point, when the fluid occupies nearly
the entire side, the curve comes quite near to the horizontal, but if
some of the fluid be withdrawn by aspiration or absorption the letter
S curve will reappear and retreat downward in the inverse order of
its advance, until with entire absorption it becomes merged into the
normal boundary of the lung."13 Garland quotes from two recent German
authorities—Heitler of Vienna and Rosenbach of Breslau—to the effect
that the line of flatness of the effusion extends lower on the back
than it does on the side, and that there is a triangle bounded by the
vertebral column, the upper curve from the bottom, and a line drawn
from the summit of the curve, where there is impaired resonance over
the lung from adhesions and oedema of the lung, but where there is no
fluid and no flatness. Garland had previously called attention to this
space, and had named it the dull triangle. He had warned all who sought
to trace the true line of pleuritic flatness to be careful not to
overlook this region. Heitler had likened it to a monk's hood cut
longitudinally through the centre and hanging apex down. Rosenbach made
this dull space, clearing up in exercise and deep breathing, as
distinctive between pleurisy and pneumonia. We must expect impaired
resonance on the posterior wall above the fluid, for the fibrinous
deposits from exudation collect there when the patient is in the
recumbent position. Garland14 calls attention to the confused views
caused by confounding the two physical signs of dulness (or impaired
resonance) and flatness (absence of resonance), the latter only
indicating the presence of fluid. If the differential diagnosis between
the dulness on percussion over the dull triangle and the flatness over
the fluid be not carefully made by delicate, light percussion, the two
may easily be confounded and the fluid be thought to have arisen to a
much higher level than it has. In some cases, owing to greater
thickness in the walls and coverings of the chest and adhesions, it may
be more difficult to draw nice distinctions in percussion sounds. This
distinction can, however, be made if the percussion-stroke is used with
proper delicacy and lightness, and a comparison made between the two
signs, and not between them and vesicular resonance. If the percussion
be strong, the vibrations are communicated from the resonant lung above
the fluid, and deceive the examiner. The most effective manner of
percussing is at right angles to the general direction of the curve,
which is transverse across the chest. Thus examining, we have had ample
opportunities of confirming the statement of Ellis and Garland that the
curve line is never highest behind, even with the largest effusion.
Wintrich and his German followers hold a different view. In moderate
effusions it is highest in the axilla, from which point it turns
downward posteriorly to touch the vertebral column at the interscapular
region. In front it extends downward toward the sternum. R. Douglass
Powell15 reports cases with drawings, showing that in typical cases
the fluid does not take a water-level, "but a curve, having its
convexity upward in the lateral region." When the effusion becomes
excessive and fills the whole cavity, there is flatness on percussion
everywhere. As the fluid subsides, however, from absorption or from
mechanical removal, the distribution again resumes, to a greater or
less degree, its previous shape.
In moderate effusions there is,
ordinarily, the dull triangle posteriorly, and Skodaic resonance under
the clavicle in front in the anterior triangle. On the left side the
lower limit of the effusion can be recognized by the flatness being in
the shape of the arch of the diaphragm. In cases complicated by
adhesions or by pathological changes in the lung itself the curve is
changed, and in some the Ellis curve is straighter than in others.
Adhesions form sometimes early in the disease. They mechanically
interfere with the usual distribution of the fluid, as do catarrhal,
tubercular, or pneumonic consolidations, and, indeed, emphysematous
conditions. All these physical alterations of structure modify the
elastic force of the lungs. According to Mohr's statistics, adhesions
were wanting in 47 per cent. of the cases analyzed by himself.
Garland's experiment of injecting glue and plaster of Paris, and
subsequently cocoa-butter, into the pleura of living and dead dogs, and
by moulds testing the curves formed, showed that if the dogs were
suspended by the head the curve of flatness on percussion was very
similar to the Ellis curve. On removing the casts after they had
solidified, he found they closely corresponded to the shape and
position indicated by the physical signs elicited before opening the chest.
5 Archives générale de Méd., 1843.
6 See Hyde Salter, Lancet, 1865; Powell, Trans. Roy. Med.
and Chir. Soc., vol. lix.; W. N. Stone, Lancet, 1877; Le Gros
Clarke, Roy. Soc. Med. and Chir., 1872.
7 Quoted by Garland, N.Y. Med. Journal, 1879.
8 Ibid.
9 Auscultation and Percussion, 1877.
10 Practice of Medicine, 1880, p. 130.
11 Boston Med. and Surg. Journ., 1874 and 1876.
12 Pneumono-Dynamics, New York, 1878.
13 N.Y. Med. Journal, Nov., 1879.
14 Pneumono-Dynamics.
15 Med. Times and Gazette, Oct., 1882.
Ellis's observations, and those of Garland with his experiments, have
given us the most accurate views as regards the form of the curved line
of flatness.
Nearly all modern authorities, including Peter, Gerhardt, and Paul
Niemeyer, admit that fluids in the pleural sac assume more or less
irregular curves, and not a hydrostatic, horizontal level. Whatever may
be the nature and consistence of the effusion, fibro-serous,
sero-purulent, or purulent, it does not behave in its distribution as
if it were in an open vessel. But few writers, however, have troubled
themselves to ascertain the causes of this apparently abnormal
condition. They appear to have completely overlooked the facts that had
been discovered in regard to the mechanics of the chest in connection
with respiration and the circulation. Physiology had shown, especially
by Marry's researches, the negative force of the lungs in aspirating
the blood from the large venous trunks into the right side of the
heart, and thus assisting the whole venous circulation. John
Hutchinson16 drew attention to the antagonism existing between the
expansion of the chest by muscular action and that of the lungs and the
chest-walls. Hyde Salter17 showed that at the commencement of
inspiration thoracic elasticity was favorable to inspiration, but as it
advanced it became an expiratory force with lung-tension against
further expansion. R. Douglass Powell18 drew further attention to
these facts in connection with respiration and its modification by
disease. Le Gros Clarke19 showed that atmospheric pressure over the
abdomen kept the diaphragm in a condition of arched passive tension. He
claimed that this negative force resisted the elasticity of the lung,
and was the means of retaining the supplemental air in the lung and
limiting the encroachment of abdominal organs.
16 Trans. Med. and Clin. Soc., 1846.
17 Lancet, Aug., 1865.
18 Trans. Clin. Soc., 1870.
19 Trans. Roy. Soc., 1872.
Douglass Powell in March, 1876,20 in an elaborate and very suggestive
paper on "Some Effects of Lung Elasticity," gives the practical bearing
of these physiological facts in clinical medicine, as indicating a
better insight as to the true mechanism and relative value in diagnosis
of some signs of chest diseases, especially as to the importance of
thoracic resilience as a force in respiration.
20 Trans. Roy. Med. and Clin. Soc., vol. lix.
W. H. Stone early in 187721 reported his experiments on sheep as to
the amount of negative pressure exerted by the lungs, and concluded
that it was equal to four to five inches of water. He moreover showed
that even when the effusion was considerable in the pleural cavity, the
lung still had contractile force sufficient to support two inches of
water, so that to evacuate the
fluid it was necessary to use
external suction sufficient to overcome this lung-traction. In
December, 1877, G. M. Garland22 gave to the public the results of his
observations and experiments in regard to the form of the curve of
distribution assumed by the pleural fluid, and its causes. He
demonstrated that "the lung, by virtue of the strength of its
contractility, takes the effusion along with it in its retraction, and
that thereby assumes a pneumono-dynamic instead of a hydrostatic
level," and that the Ellis curve was the true line of the upper level
of the fluid in free, uncomplicated pleuritic effusion. Thus the
physical cause of this condition was the retractile force of the lung
lifting up the fluid. This is aided by the elastic resistance of
thoracic walls and the negative pressure exercised by the effused
liquid. The normal line on right side of demarcation between lung and
liver is the letter S curve drawn out, the summit being high and the
anterior branch correspondingly depressed. The modifications of this
normal line in pleuritic effusions represent the effect of the negative
pressure of the fluid. The decline in the Ellis curve toward the
sternum shows that the elastic energy of the anterior part of the lung
is feeble compared with that in the axillary region. "The layer of
fluid is of less thickness above than at the base of the lung against
the diaphragm. The upper surface takes its shape from the lung, which
lifts it up by its retractility, and the effusion by its weight exerts
a negative pressure upon the lung. The mass of the fluid is held when
in moderate quantity in the supplemental space between the lower border
of the lung and the diaphragm" (Garland). The atmospheric pressure from
the interior of the lungs and from the exterior of the chest-wall keeps
the costal and parietal surfaces of pleura together. Skoda, Powell,
Stone, Homolle, and Quincke have shown the retractile energy of the
lung, but the credit of drawing especial public attention to it, and of
afterward elucidating the subject in its practical application to the
study of pleurisy and in putting the whole subject upon a scientific
basis, is unquestionably due to G. M. Garland of Boston.
21 London Lancet.
22 Pneumono-Dynamics, Boston, 1878.
ETIOLOGY OF FIBRO-SEROUS PLEURISY.—The etiology of acute primary
pleurisy is frequently obscure. It may be hæmatic in origin, or it may
be secondary, arising from pathological causes or antecedent disease.
It is difficult to state with certainty whether it occurs in perfectly
healthy persons, because there may be occult pathological conditions
which cannot be appreciated. However, individuals are attacked with
acute pleurisy who to all appearance, both to themselves and to those
around them, are healthy. Authors differ very widely as to the disease
being ever caused in healthy persons by exposure to cold. The older
writers bring many proofs that such is the case. Ziemssen states that
he could not trace the disease to exposure to cold in a single instance
in 54 cases. Anstie holds the same view. Loomis states that in all
instances where it (pleuritis) has followed upon exposure he has been
able to find some predisposing cause. It is undeniable that pleuritis
very frequently indicates the existence of some constitutional
cachexia. Vital statistics show that it is more frequent in winter and
spring than at other seasons. The vicissitudes of the weather, of
temperature, and other atmospheric conditions have unquestionably a
marked influence on the prevalence of the disease. Drafts of air
passing over the chest or over other parts of the body, particularly
when the subject is surrounded in-doors with a warmer atmosphere, wet
clothing, intensely cold or a raw, damp atmosphere inhaled by persons
coming out of a comparatively high temperature, especially if they are
improperly protected by clothing, appear to be direct causes of primary
pleuritis. If individuals thus exposed are debilitated by fasting, by
such medicines as mercury, iodine, iodide of potassium, by
over-exertion, by free perspiration, or by previous disease, they will
be still more liable to contract the disease. Overheated apartments,
especially at night during the
sleeping hours, frequently are the
direct cause of acute pleurisies or of croupal pneumonias. These cases
are of such frequency that we are obliged to differ from the high
authorities who consider the pleura as free from acute idiopathic
inflammations as is the peritoneum.
There are numerous predisposing causes which, when examined, are found
to lessen the power of resistance of the organism. Senility is an
important one; so is childhood. Formerly it was supposed that pleurisy
rarely attacked children. This view was prevalent because the disease
often escaped detection. Of all chest diseases in children, mistakes in
diagnosis are most frequently made with pleuritis.
We might suppose that this disease would be frequently met with in
children, because they are oftentimes ill protected against the
vicissitudes of the weather; besides, their feebleness predisposes them
to feel keenly such shocks to their powers of endurance. The disease
may occur at any age, and is more common under two years than was
formerly supposed (Eustace Smith). Empyema is the form most frequently
found in children, the effusion soon becoming purulent in them.
Ziemssen tabulates the ages of 54 children whom he treated for primary
pleuritis: first year of life, 3; second, 1; third, 7; fourth, 4; the
remaining 39 between the ages of five and sixteen years.
Pleurisies are more frequent in males than in females, in the
proportion of 5 to 3, owing to the greater exposure of the former to
the exciting causes, and notwithstanding their stronger organisms.
Among the predisposing causes we must not fail to give due importance
to the malhygienic conditions which so powerfully impair the forces of
the body. Prominent among these are sedentary occupations, imperfect
alimentation, city lives, overwork of mind and body, deficient
sunlight, overcrowded houses, and dampness of soil. These and many
others interfere with the formative forces and lessen the power of
resistance to exciting causes of pleurisy.
Traumatic pleurisies are caused by injuries or other mechanical causes.
Injuries to the walls of the chest, contusions, burns, scalds, and
lacerations which are superficial, frequently give rise to primary
traumatic pleurisies. If the ribs are fractured, or blood, air, or pus
gets into the pleural cavity, we have what has been termed secondary
traumatic pleurisies.
Secondary Pleurisies.—The exciting causes of secondary pleurisies are
numerous. They are pathological, and more readily appreciated than the
causes of primary pleurisies. Owing to the anatomical connection
between the lungs and the pleura, diseases, acute and chronic, of the
former frequently give rise to pleurisies.
Among acute affections of the lungs, the several forms of pneumonia are
the most frequent causes of pleurisies. Fraentzel states that we always
find fibroid pneumonia associated with pleurisy as pleuro-pneumonia,
even when the inflammation of the lung-tissue itself does not reach the
pulmonary pleura. There is an intimate connection also between caseous
pneumonia and pleurisy. This is sometimes quite circumscribed, and
leads to adhesion of the pleural layers at the affected spot; sometimes
it is diffused over a great part of the pleura, and it is then not
infrequently associated with a considerable outpouring of different
kinds of effusions. Catarrhal pneumonia rarely occurs without secondary
pleuritis (Fraentzel). Pleurisies may also be caused by violent
bronchial catarrhs or by hemorrhagic infarctions.
There are cases where, from the presence of tubercles under the
parietal pleura, inflammatory action is set up and pleuritis ensues.
Vomicæ bursting into the pleural cavity or tubercular perforation in
pulmonary phthisis gives rise to pleurisies. Inflammation of the liver,
cellular abscesses, and pericarditis may cause secondary pleurisies.
Diffuse peritonitis is often complicated with pleurisy, the
inflammatory process extending from the
peritoneum to the pleura,
through the diaphragm, by means of the serous canaliculi. This
frequently occurs in puerperal peritonitis, and is almost invariably
fatal (Fraentzel). The author had a case of fatal peritonitis in a man
sixty-five years of age, which originated from an empyema. There was no
rupture nor perforation of the diaphragm, so that the inflammatory
process must have extended from the pleura to the peritoneum by means
of these canals. Malignant diseases of the mammæ, oesophagus, lungs,
and hydatids produce secondary pleurisies. Eruptive fevers, especially
scarlatina, variola, typhoid fevers, are among the most frequent
pathological causes of secondary pleurisies. It is doubtful whether
their germs pass through the circulation or through the lymph-canals,
and produce local inflammation of the same nature as their own, or
whether they render the pleura more sensitive to shocks of various
kinds. Rheumatism, gout, and nephritic diseases are frequently followed
by pleurisies. As we have rheumatic endocarditis and pericarditis, in
like manner there are rheumatic and uræmic pleurisies. Alcoholism and
pyæmia, septicæmia and the puerperal state, especially during the first
month after parturition, are powerful predisposing causes of
pleurisies, as are also any morbid conditions of the skin, kidneys, or
intestinal canal which interfere with their eliminating or depurating
functions. This includes all forms of blood-poisoning. Hutchinson says
that children suffering from congenital syphilis are especially liable
to serous inflammations, and that pleurisy is in them a not uncommon
cause of death. Niemeyer denounces the impropriety of giving the name
of secondary pleurisy to all cases of pleurisy occurring in subjects
with broken-down constitutions or weakened by other diseases. We often
meet with such cases when Bright's disease exists. Niemeyer holds that
it is not dependent upon renal disease, but upon the increased
predisposition for all kinds of inflammatory disease. A trifling cause
will sometimes excite a pleurisy when the resistance of the organism is
materially lessened by previous disease.
SYMPTOMATOLOGY.—Rational Symptoms.—These vary according to the
severity of the disease. Ordinarily, attacks of acute pleurisy come on
suddenly, and it rarely happens that there is any appreciable feeling
of malaise. Usually the first symptom is an acute pain in the side,
which alarms the patient. The significance of this severe stitch is
generally appreciated, as the subject at once calls attention to his
sufferings. The pain is sharp, cutting, stabbing, that causes him to
hold his breath as long as possible. When he is forced to breathe, it
is by the action of the superficial intercostal muscles. He endeavors
to fix his diaphragm and hold it rigid in order to prevent the surfaces
from coming in contact and thus increasing his agony. This causes him,
necessarily, to breathe frequently in order to get sufficient air. The
greater the intensity of the pain, the more frequent and shorter are
the respiratory acts. The dyspnoea and the effort to lessen the pain
give the patient an expression of great suffering. Usually, the pain is
felt over a circumscribed spot under the nipple of the affected side.
Sometimes it is experienced as low as the sixth or seventh intercostal
space, but rarely posteriorly below or under the scapula or in the
axilla. In children the seat of pain is not always in the chest. Their
lower intercostal nerves are often affected, and the sensation being
referred to the ends of these nerves where they ramify on the abdominal
wall, the pain is often seated in the abdomen. Such being the case in
children, care must be taken not to confound pleurisies in them with
epigastric or hypochondriac irritations. In adults, the pain is rarely
located in the abdomen when it is caused by pleuritis in the lower
portion of the pleural surface or in that part covering the diaphragm.
In children there is also much tenderness on pressure. In what has been
termed subacute or latent pleurisy the stitch may be entirely absent.
Valleix found pain in 40 cases out of 46. Sometimes it is absent
in ordinary breathing, but is brought on by sneezing or violent
coughing or strong percussion. In severe cases, the effusion coming on
rapidly, the pain may subside by the second day. If the effusion comes
on slowly, the pain may keep up for six or eight days. The continuance
of the pain always shows that the inflammatory process in the pleura is
continuing, although the pulse and the temperature may be normal. The
renewal of the sensation of pain after the pleurisy has passed away
justifies us in the conclusion that there is a return of the
inflammation. When the pain is agonizing, with signs of collapse, it is
indicative of a secondary pleuritis arising in the course of a chronic
caseous pneumonia. Tubercular and purulent exudations are distinguished
from the sero-fibrinous by the longer duration and the greater
intensity of the pain—two circumstances which afford a reliable basis
for the diagnosis of such cases. The severe pain in pleuritis is
probably caused by the inflammation extending to the sheaths of the
nerves and to the nerve-texture itself (neuritis), as well as by
inflammation of the pleura itself.
Severe attacks of acute exudative pleurisy may commence with a severe
initiatory chill, followed by high fever, but ordinarily there are in
pleurisy slight rigors, initial in their character. Some authors
question whether they are not caused by the limited points of pneumonia
connected with the pleuritis. If the rigors occur at regular intervals
for days, we have reason to suspect tubercular trouble or empyema. The
temperature does not run any regular course in pleurisy, nor does it
bear any fixed relation to the pulse and the respiration. It usually
varies from 100° to 102° F. In violent, acute cases it may reach 105° F.
Careful observations with the thermometer give us important indications
by which to diagnose the nature of the pleurisies. In those of a
tubercular nature the temperature continues high, from 100° to 104° F.,
for weeks. When the effusion becomes purulent the temperature becomes
like that of hectic fever—in the morning normal, and in the evening
rising to 102°, or even 103½° or 104° F. Sometimes the temperature is
one or two degrees higher on the diseased side than it is on the
healthy side.
As in other inflammations, the pulse in this disease varies
considerably. The researches of H. Newell Martin show that there is
ordinarily a constant ratio between the pulse-rate and the temperature.
If the temperature be high (over 102° F.), we must expect the pulse to
be as frequent as 115 or even 120 per minute. In mild cases, where the
temperature does not go beyond 99.5° or 100° F., the pulse will not
exceed 90 to 96. In slight cases, where the fibrinous exudation is very
limited, the pulse may not exceed 80. In tubercular and purulent
pleurisies the pulse may vary between 100 and 120. When there is a
relapse the pulse advances as the temperature rises. Anstie has called
attention to the quality of the pulse, which follows a uniform course
on the whole, regard being had to the general vital condition of the
patient. In the first stage of acute pains, with more or less tendency
to shivering, the pulse, as tested with the sphygmograph, presents the
algid form—i.e. the pulse-waves are very small and nearly devoid of
secondary markings. As soon, however, as flushing of the face occurs,
and a general sense of burning heat of the skin, the pulse passes to
the true pyrexial type; the waves become large and dicrotic. The
sphygmograph uniformly shows that the large and somewhat bounding pulse
is always less resistant than that of health.
Jaffé-Duval23 states that he found the temperature of the diseased
side raised above that of the healthy chest. Subsequently, Peter,24
after a long series of researches, reported some very important results
as to the localized parietal temperature in cases of pleuritic
effusions: (1) He found that the
parietal temperature, as tested
by the thermometer, is always higher on the side of the pleurisy than
that of the body as tested in the axilla; (2) that the elevation of the
temperature increases as the effusion augments, the highest local
temperature corresponding to the period of secretory activity of the
inflamed pleura; (3) the rise affects both sides, but is greater over
the diseased pleura; (4) the temperature falls by degrees as the
effusion is reabsorbed—less on morbid side; (5) the absolute elevation
of local temperature is greatest in the sixth intercostal space; (6)
after paracentesis the parietal temperature is increased: this falls in
a few hours where the effusion is not re-formed, but when such is the
case it continues for some days. This local rise of temperature, he
considers, is from hyperæmia and cell-production, caused by the
traumatism from the needle added to the already-existing hyperæmia.
This excessive congestion, caused by the accumulation of blood
occurring when a large quantity of fluid is rapidly withdrawn, produces
the syncope, pulmonary congestion, consecutive albuminous
expectoration, the pain, and the oppression amounting sometimes to
suffocation, and occasionally ending in death.
23 Thèse de Paris, 1875.
24 La France médicale, 4th May, 1878.
At the commencement in acute cases the respiratory acts become very
frequent, even going to 40 or 50 per minute. They are short,
interrupted, and superficial. Their frequency makes up for their
incompleteness in furnishing sufficient air. The painfulness of each
act forces the individual not to expand the walls of his chest more
than he can avoid. Moreover, the high fever in itself produces frequent
respiration. As the temperature falls the respiration becomes less
abnormal. If the effusion forms rapidly, the patient may become
oppressed, even when the quantity is not large. If it is thrown out
gradually, the breathing is not so much interfered with until a large
quantity forms, the organism becoming accustomed to the interference
with the play of the lungs. The strength of the individual and the
activity of his nutritive functions are materially lowered. Sometimes
he breathes with difficulty, especially when he takes active exercise.
The dyspnoea is very painful and alarming. The aëration of the blood is
so materially interfered with that there results a large quantity of
carbonic acid, which irritates excessively the respiratory nerve-centres.
During the acute stage the patient sometimes lies on his back, but more
frequently on the well side, and exceptionally on the diseased side. He
avoids lying on the side where the inflammation exists, because the
weight of his body increases the pain. I have, however, seen patients
who would persist in lying on the painful side and supporting it with
their hand. It sometimes happens that a patient lies on the affected
side, and will not move, because the movement gives him such acute
pain. Ordinarily, he prefers to lie on the healthy side, even after the
fluid has been poured out to a moderate degree, because his pain is
less. When, however, the effusion has become great enough to deprive
him of the use of the diseased side, he instinctively turns on that
side, so as to avoid the weight of the fluid pressing upon the lung on
the sound side. Moreover, he wishes to expand as much as possible the
side whose respiratory force now needs to do double work. This change
of position in patients has an unmistakable significance. It shows that
the sufferer is aware that he is more comfortable lying on the diseased
side. His physician's attention is drawn to the condition of the chest
as influenced by the increased quantity of fluid pressing the air out
of the lung.
Cough is not a constant symptom in pleurisy, but ordinarily it occurs
at some stage of the disease. It is short, dry, and suppressed in
character. It is painful, and therefore is avoided when possible,
especially previous to the effusion. It disappears generally about the
fourth or fifth day, when the effusion has attained a considerable
amount. The cause of the cough has been generally supposed to be the
exalted sensibility of the inflamed
pleura, but Nothnägel
maintains that such is not the case. Fraentzel holds that the cough is
caused by the strain on the lung-tissue and the finer bronchi when
there is a slight effusion. Cough brought on by change of position is
one of the characteristic symptoms of large effusions into the pleura.
If the lung is completely compressed by the pleuritic effusion, then no
actual strain on the alveoli or the bronchi can exist. In such cases
there is no cough, but it returns when the effusion decreases in
quantity, and quite violently, if this occurs suddenly, as, for
instance, in puncture of the chest (Fraentzel). In the latter case the
cough is probably caused by the rush of blood and the sudden expansion
of the chest.
Slight frothy expectoration may exist, but ordinarily there is none
whatever, unless from bronchial catarrhal complications. In that case
sero-mucous fluid is expectorated in small quantity. If it becomes
viscid and tinged with blood, it is caused by pulmonic involvement.
In empyema, if the expectoration becomes purulent, we ought at once to
suspect the presence of some circumscribed spots of necrosis of the
pleuritic covering of the lung, which have allowed the pus from the
pleural cavity to filter through the lung-tissue. By careful physical
examination of the chest we can ascertain whether there has been any
diminution in the quantity of fluid. When, as sometimes occurs, there
is actual perforation of the lung, the pus from an empyema comes in
quantity, through the bronchial tubes, out of the mouth. Patients may
sink from exhaustion following this discharge, or if the discharge be
excessive it may fill up the bronchial tubes too rapidly for its
removal by expectoration, thus causing suffocation. This danger is
increased if the discharge takes place during sleep.
Cyanosis is a symptom which should cause serious alarm, for it shows
that the effusion is so great as to interfere very materially with the
due arterialization of the blood. When the cyanosis is accompanied by
pallor, coming on suddenly in the course of a pleurisy, we may infer
with considerable probability that there is a hemorrhagic exudation.
But if the paleness comes on slowly during weeks or months, it may also
be dependent on a simple sero-fibrinous effusion (Fraentzel).
Protracted cases of effusion, especially if purulent, are associated
with emaciation and loss of strength. There may exist more or less
oedema of the lower extremities and of parts of the body where the
patient lies down, as we have in the chronic diseases of the chest.
When this oedema is limited to the affected side of the chest, whether
it be extensively developed and spread over the entire half of the
chest or confined to certain spots, it almost invariably justifies the
diagnosis that the effusion is purulent. The effusion may, however, be
purulent without the presence of this localized oedema. Occasionally,
cases are met with of effusion in the left pleura where there are
visible and palpable systolic pulsations in the intercostal spaces
arising from the impulse of the heart or of the larger blood-vessels
passing through the fluid.
Physical Signs.—Perhaps in no other disease of the chest are physical
signs so important for purposes of diagnosis as they are in pleurisy.
Even at the very beginning of the attack they give us valuable
information. In later stages, when the effusion is in the pleural sac,
they furnish, as we shall hereafter show, trustworthy data for
diagnosis, prognosis, and also very valuable indications for treatment.
There is no other disease of the chest where the physical changes made
by the inflammatory process are so pronounced and so accessible to the
senses of hearing, sight, and touch. The physical signs are so marked
that, almost by themselves, they give us the pathological condition.
They have been so carefully studied, and their correlative value
insisted upon, that they are readily interpreted. One is often tempted
to rely too much upon them to the exclusion of the proper consideration
of the general symptoms.
As the physical condition of the pleuræ varies much in the
several stages of the disease, the physical signs must necessarily vary
accordingly.
At the very beginning of the attack the sensibility of the pleuræ is
augmented by the inflammation. Consequently, on inspection, it will be
observed that the patient is careful to avoid the pain caused by the
inflamed pleuræ rubbing together. He not only tries to avoid using the
ordinary muscles (especially the intercostals) for enlarging the
capacity of the lower portion of the chest, where the disease is
generally found, but he retracts his chest and keeps the pleuritic side
almost motionless. The well side has double work to do, and is seen to
expand more fully. The patient will frequently press the lower ribs in,
on the affected side, with his hand, or he will lie on that side, so as
to control the expansion of the chest, or he will lie on the healthy
side and bend his body over.
The respiratory movements are marked by an irregular and jerking
rhythm, and are quickly made. The pain felt on inspiration is of a
catching or stabbing character, and produces dyspnoea, the subject
struggling for air. The diaphragm is held as fixed as possible, so as
to prevent the movement of the inflamed surfaces over each other. The
patient restrains as far as possible the respiratory movements,
especially those of expansion and retraction. This is the condition not
only at the initiation of the disease, but at the next stage, that of
effusion. We meet with the same painful respiration also in dry
tubercular pleurisy. Mensuration shows that the sound side of the
thoracic cavity is slightly enlarged by the extra work it has to
perform in the first stage. The elevation movement is noticed to be
restrained when the effusion has increased to the extent of overcoming
the retractility of the lung, for the diaphragm is no longer drawn up
by the lung, and the effusion rises and separates the parietal and
pulmonary pleuræ. The diaphragm bags from the quantity of fluid, and
contracts but feebly. This condition forces the liver and the spleen
down in the abdominal cavity. Gradually the jerking rhythm ceases as
the effusion advances, and the characteristic stitch in the side
disappears. If the effusion increases until it reaches as high as the
second rib, the respiratory movements are scarcely perceptible to the
eye. When it reaches its maximum, the clavicle, they appear to be
arrested, but the vertical diameter is slightly altered by the action
of the intercostal muscles as they endeavor to elevate the ribs, and of
the diaphragm as it feebly contracts and relaxes. The pleural cavity,
which in health is lubricated by about two drachms of moist serous
secretion, is frequently filled to the extent of seventy, eighty, or
more—even to one hundred and twenty—ounces. We cannot wonder that it
should be changed in shape and diameter. All available space is filled
with the fluid, and yet the serous membranes continue to throw out the
secretions. The lung must lose in size by its retractile force, and
when that is overcome the fluid must press in all directions. The fluid
gradually rises from the surface of the pleura over the diaphragm, and
the lung, by negative pressure, draws it and the fluid upward. As long
as the diaphragm is arched, although the lung recedes before the
effusion, it is not really compressed. When, however, the diaphragm
yields and falls from the large quantity of fluid, then the fluid
conquers the lung. Ordinarily, the fluid, when in excessive quantities,
presses upon the lung and the bronchi until it forcibly expels the air;
the lung is compressed against the vertebral column, occupying a very
small space corresponding to the surface under the scapula, often not
larger than from three and a half to four inches square. Inspection
shows that the spaces between the ribs become flattened out, that the
ribs are more widely separated, and that the spaces themselves
frequently bulge. The first observable indication of great distension
of the pleural cavity, sufficient to cause intra-thoracic pressure, is
the depression of the diaphragm, and next the flattening of the spaces
between
the ribs. This last is followed by increased pressure,
which causes more general and marked enlargement. "This levelling of
the intercostal spaces is due partly to paralysis of the intercostal
muscles from serous inflammatory infiltration, and partly to the
limited range of movement now possessed by the lung, which is reduced
in volume by the effusion, and is no longer in contact with the
thoracic parietes" (Guttman). This is especially noticed in children
and young persons before the ribs become firm and resisting, the
negative pressure exerted by the lung being in part annulled by the
presence of the fluid. The diaphragm is notably depressed, and pushes
the liver, the spleen, and the stomach below their usual point. So
great is this centrifugal force that the heart's impulse may be felt in
the epigastrium. The heart, when the effusion is on the left side, is
frequently found over to the right of the sternum, and, in extreme
cases, even in the right axilla. When the effusion is on the right
side, the mediastinum is drawn over with it, and the heart is forced to
the left until the apex-beat is perceived as far as one and a half
inches to the left of the line drawn through the nipple, or, in some
cases, to the left axilla. This rarely occurs unless we have fluid
intra-thoracic pressure on the diseased side in addition to
lung-traction of the healthy side. Even the costal pleura, projecting
above the clavicle, may yield to pressure. Inspection reveals to the
observer these striking physical alterations. Hippocrates did not fail
to notice them.
1st. Mensuration shows that the semicircular, antero-posterior, and
vertical measurements of the side are generally increased. According to
Douglass Powell, the total circumference of the chest is always
increased in effusion. 2d. Except in children, the bulging of the
intercostal spaces does not occur until after the adjacent organs have
been displaced by the fluid. When the effusion is large, it becomes
evident, by inspection and by pressing the hand over the sides of the
chest below the armpits, that there is almost immobility of the
diseased side. We insist upon the importance of daily and repeated
comparative measurements of the two sides as aids to diagnosis and
prognosis in pleurisy. A full inspiration or a prolonged expiration
will sometimes show a marked difference by measurement when it is not
discovered during ordinary breathing. Woillez's cyrtometer, as
perfected by Samuel Gee, is the best instrument for testing the
circumference of the chest, and a pair of callipers for the diameter.
The cyrtometer tracings give us the altered shape as well as
circumference. It is especially valuable in the diagnosis of local
empyema from basic pulmonary cavities. Care should be taken not to
confound congenital deformities in the shape of the chest, such as the
alar, flat or pigeon-breasted, or rachitic, with alterations produced
by internal disease. It must also be borne in mind that the
semi-circumference of the right side is normally greater by one-quarter
to half an inch than that of the left side. By inspection of cases
where large effusions have remained for long periods of time slowly
absorbing—often, perhaps, not recognized—we discover marked
unilateral retraction of the chest-walls, with torsion of the spine and
shoulders. The adhesions preventing the lung from expanding, the
alveoli become obliterated, and we have, in fact, atelectasis of the
lungs. This is particularly the case in children, where the disease
prevents the proper development of the side, the healthy side becoming,
from supplementary work, more enlarged. Care must be taken not to
confound with these the anatomical depressions met with sometimes in
the anterior wall of the chest, especially at the lower portion of the
sternum. The amplification of the chest takes place, to a greater or
less degree, at its lower portion as soon as an appreciable quantity of
liquid collects, long before it is possible to have any intra-thoracic
pressure. The lung by its elasticity collapses, and the fluid is drawn
upward in contact with the lung. The thoracic wall, consequently, has
not, at that point, the retractile force of the lung to
counteract its excentric resilience. It is not then drawn in in
expiration by the lungs, while it is continually being drawn outward in
inspiration. The lung-traction of the parietes of the chest is feeble
from the diminished size of the lung. The greater the amount of fluid,
the less lung-tension; consequently, the greater the enlargement of the
chest, as shown by the cyrtometer. If the lung is contracted to its
utmost limit (one-third of its size, according to Powell; one-eighth,
according to Rokitansky), then there could be no suction force
exercised by it upon the parietes of the chest, for, being disabled in
its elasticity, it literally has no power. The whole parietes of the
chest on the diseased side have nothing to antagonize their elasticity,
so it is kept enlarged. In addition, at this stage the fluid of itself
presses against the walls of the chest in all directions.
The elastic pulmonary tissue is always, to a certain extent, on the
stretch. It is striving to pull asunder the pulmonary from the parietal
pleura; but this it cannot do, because the air can have no access to
the pleural cavity. The five mm. of mercury elasticity of the lungs can
be increased by a distension of the chest from a forcible inspiration
to thirty mm. of mercury. Anything which lessens this elasticity of the
lungs takes off so much from the force which interferes with the
rebound of the thoracic resilience, and consequently increases the
circumference of the chest. Such is the case in emphysema, oedema of
the lungs, pulmonary congestion, and, curious to relate, at the outset
during the pyrexial stage of acute diseases, such as pneumonia,
variola, bronchitis. The enlargement of the thoracic circumference is
appreciable. It, however, gradually decreases and becomes normal. This
yielding of the thoracic walls is attributable to temporary engorgement
of the lungs, lessening their retractile force.
At the very commencement immediate results of percussion are negative,
but by delicate taps over a pleximeter there is a sound at the margins,
owing to the deficient expansion, of impaired resonance and of higher
pitch, and the vibrations are less full. There is also a sense of pain,
owing to the increased sensibility of the costal pleuræ. As the
fibrinous coatings form, the sound becomes less and less full and the
normal vibrations of sound are less diffused, more circumscribed,
giving to the finger, used as a pleximeter, a sense of resistance from
the diminished elasticity of the lung. This is especially the case at
the base over the attachment of the diaphragm. As the effusion rises
from the base, the sound on percussion becomes flat. The fluid being a
non-resonant body, the vibrations of the percussion taps do not extend.
The sound is of high pitch, but not resonant. It has been properly
designated by Skoda an empty sound, for it conveys to the ear the
condition beneath, which is one of perfect airlessness. It is not
simply a dull sound or one where there is not the normal resonance, but
it is destitute of all resonance: it is absolutely flat. The confusion
of dulness with flatness has in the past led to erroneous conclusions
as to the line showing the level of the fluid in pleurisy. As high an
authority as Woillez, in reference to fluid flatness, speaks of dulness
as complete, absolute, or very incomplete sub-dulness! The muscular
coverings of the walls of the chest or unusual amount of adipose tissue
or pleuritic coatings or bands produce impairment of resonance, and
sometimes marked dulness on percussion. But when the percussion wave
penetrates to the lungs, there is more or less resonance. When the lung
is solid from pneumonia or tubercular deposits, the sound is often very
dull, but rarely flat, because it seldom happens that all of the
alveoli are filled up, and even when they are the vibrations are
communicated to the bronchial tubes which contain air, and in this way
there is some resonance. We call particular attention to the importance
of these distinctions and to the necessity of light and delicate
percussion in order to test the resonance or non-resonance of the
thoracic cavities. If the percussion be strong, the vibrations are
conveyed
by the thoracic walls to the portions where there is no
fluid, and thus we have impaired air-resonance, and not flatness. We
have frequently seen errors of diagnosis in cases of pleurisy owing to
the physician percussing with too much force. To secure accuracy,
Garland25 lays down the simple rule of percussing with great care and
always in straight lines, and of percussing each line to its terminus
before taking up another. Powell26 compares the peculiar flat
percussion sound of pleuritic effusion to that elicited on striking
against a brick wall. The flatness is characteristic and more marked
than the dulness of lung-consolidation. If we are not careful to make
the distinction between impaired resonance and non-resonance, we may
easily draw erroneous conclusions as to the rise and extent of the
fluid in the chest. We have shown elsewhere (Pathological Anatomy of
Pleurisy—Distribution of Fluid) that, as the fluid collects in the
cavity, the lung contracts before it. The border above the level of the
liquid contains less air, the capillary circulation is less active, and
frequently there is more or less oedema, owing to its being the most
dependent portion. These physical conditions impair, to a greater or
less extent, the pulmonary resonance. Thus at the base above the fluid
we might, on reflection, naturally expect some dulness on percussion,
lessening as we recede from the fluid. Several observers have called
attention to the impaired resonance over the lowest portion of lung
posteriorly when the person is standing. Garland27 termed it the dull
triangle. Heitler28 of Vienna observed this same condition in that
locality, and likened it to a monk's hood cut longitudinally through
the centre and hanging apex down. Rosenbach29 of Breslau noticed that
this non-resonant triangle in pleurisy would often clear up on exercise
or by breathing; this fact he considered distinctive between pleurisy
and pneumonia.
25 Loc. cit.
26 Med. Times and Gazette.
27 Ziemssen's Supplement.
28 Wien. med. Wochenschr., 1878, quoted by Garland.
29 "Ein Beitrag zur phy. Diag. der Pleur.," Berlin klin.
Wochenschrift, 1878, No. xii.
Although the fluid first collects over the posterior portion of the
diaphragm, flatness on percussion is first observed over the axillary
portion of the diaphragm, because, as explained by Calvin Ellis, the
conditions there are more favorable for percussion. As the effusion
increases the line of flatness, when the patient is in the upright
position, advances, not directly up the back and horizontally across
the chest, as was formerly supposed, but across the back in a curve
reaching its highest point in the axilla, from which it descends toward
the sternum.30 R. Douglass Powell31 says the upper margin of the
effusion in typical cases is not a water-level, but presents a curve
having its convexity upward and in the lateral region. Since the
attention of the author was first called to a careful examination of
the curve of flatness as ascertained by light and delicate percussion
(in the erect position), he has found it to be more or less of an Ellis
curve at an early stage of the effusion. The line is sometimes better
defined than at others. All observers, however, must acknowledge that
at the stage of the disease when cases of chronic fibro-serous pleurisy
are first seen the letter S curve is not well marked. Mason states
that although in some of his 200 cases this peculiarity was observed,
in others the line was horizontal. When fluid fills the chest to excess
and overcomes the elasticity of the lung, it gives flatness on
percussion high up, even to the clavicle, and behind to the
supra-spinous fossa. The fluid filling the cavity, the line of flatness
becomes nearly horizontal. Then it is that percussion reveals the
displacement of the diaphragm and abdominal organs. On removing the
excess of fluid by aspiration or by absorption, this curved line
reappears, and continues as previously.
30 See section on Pathological Anatomy of Pleurisy,
distribution line.
31 London Med. Times and Gazette, Oct., 1882.
Contrary to the general belief, when the fluid is moderate in
quantity change of position of the patient modifies but little the area
of flatness, owing to its being retained between the lung and
diaphragm. Woillez32 noticed slight mobility (never more than to the
extent of one intercostal space) only in 5 of his 82 cases. He
concluded that the conditions were very different from what they were
in ordinary vessels outside the body. Woillez does not attempt to
explain what these conditions are. Skoda acknowledged that in the
majority of cases the fluid does not change its position as the patient
moves. Skoda and Wintrich attribute the non-movement of fluid to
adhesions. Garland, and subsequently W. H. Stone and Douglass Powell,
showed that the effusions were immovable when in moderate amounts,
because they were kept so by the retractility of the lung, and that the
large amounts were movable because the retractility had been overcome
by them. When in large quantities the fluid accumulates in depending
positions of the chest. Later on in the disease, adhesions and bands
mechanically interfere with the line of flatness; or if there be any
disease of the lung interfering with its retractive force, the fluid
may not take its usual line. These peripheral adhesions frequently
occur at the upper margin, and are sometimes wavy and irregular. They
often occur early in the disease, and prevent in a marked degree the
fluid from yielding to the negative lung-traction.
32 Mal. Aigues des Org. Resp., Paris, 1872.
By these bands the pleuritic fluids become sacculated in different
parts of the thorax—between the lungs and the walls of the chest,
between the diaphragm and lungs and the pericardium, the mediastinum,
the vertebral column, and actually between the lobes of the lung.
Fraentzel holds that the percussion sound is dull over the thorax
whenever the effusion attains the depth of from one inch and a half to
two inches between the lung and the chest wall. Garland by his
experiments on dogs shows that the fluid does not thus rise between the
lung and parietes, except a very thin layer, by capillary attraction,
not sufficient to cause flatness on percussion or to interfere with the
expansion of the lung unless the amount is very excessive, and not
until the lifting power of the lung is completely overpowered. When the
effusion is very large, it fills up the posterior portion of the
thorax, compressing the lung against the uppermost portion of the spine
or the mediastinum. The percussion sound is absolutely flat, provided
the force of the blow be not too great; in that case the ribs are
thrown into vibration or the vibrations extend to the sound lung. This
materially impairs the dulness and may lead to error of diagnosis.
The lung may be prevented from contracting by reason of various kinds
of adhesions or by means of widespread infiltrations, by emphysema, and
by laryngeal stenosis. In such cases, as the effusion increases, it
quickly rises in the thinner layers without displacing the organs.
Fraentzel warns us that sometimes, in left-sided effusions, the lung
having become adherent to the heart, the heart is drawn back with the
lung away from the wall of the chest, and then it cannot be felt
anywhere: the absence of the apex-beat and the feebleness of the
heart-sounds may lead us to assume, incorrectly, that there is effusion
in the pericardium. If the fluid collects between the external layer of
the pericardium and the mediastinum, the heart is surrounded and
pressed by the pleuritic effusion.
The Skodaic resonance is a remarkable tubular quality of resonance
heard on percussion when the effusion extends up to the fourth rib or
beyond it, nearly filling the pleural cavity. It is a high-pitched,
long vibration, semi-tympanitic sound, rarely absent when, from an
effusion, the lung is retracted to a very small size, but still
contains some air. It is most frequently found anteriorly under the
clavicle, near the sternum, because to that point the lung withdraws as
long as it has any retractility left. If the air be forced
out of
the lung by pressure, this sound is no longer heard. Flint called this
peculiar tympanitic sound, heard above the level of the fluid in
pleurisy, by the descriptive name vesiculo-tympanitic resonance. The
vesicular, though feeble, is combined with the tympanitic quality, and
the intensity of the resonance is abnormally increased. This
subclavicular tympanitic sound is not peculiar to pleurisy. It exists
in pneumonia preceding hepatization, and was noticed by Hudson, Graves,
and Williams before Skoda called attention to it in pleurisy. Skoda's
explanation of this phenomenon is now generally accepted—namely, that
it comes from diminished tension of the lung-tissue, caused by
diminution in the quantity of air, and consequently relaxation of
lung-tension. The residuary air in the alveoli does not mix properly
with the tidal column: it is indeed pent up by the narrowed diameter of
the minute bronchi. Thus it becomes surcharged with carbonic-acid gas;
this relaxes the air-sacs and lessens their tension. In fact, the
percussion sounds are invariably tympanitic when the parietes of the
organ which contains air are not stretched. When they are firmly
stretched, the sound elicited by percussion becomes less and less
tympanitic, and finally dull: such, we know, is the case in striking a
drumhead. The chief characteristic of the sign relates to the quality
of the sound; the resonance is nearly devoid of vesicular quality. A
resonance absolutely non-vesicular is always tympanitic (Flint). This
tympanitic sound is so constant under the clavicle that although it may
be from other causes, its appearance would lead us to suspect effusion,
especially in children. It is not only at the apex, but wherever the
lung shrinks from pleuritic exudation and loses in tension, the
percussion sound has the tympanitic quality. We find it occasionally
near the sternum, and sometimes in sacculated effusions we observe it
in different parts of the thorax. Traube, and subsequently Fraentzel
(Ziemssen's Cyc.), called attention to the fact that sometimes a long
expiration would cause a temporary abolition of this tympanitic sound
at the apex. Their explanation is that the sound is heard over the
compressed lung. Garland urges that this explanation cannot be a
satisfactory one, for a certain amount of pulmonary expansion is
essential to the production of tympanitic resonance.
This exaggerated resonance elicited by percussion has received its name
from the eminent German who wrote so much about it; but it did not
escape the accurate ear of the discoverer of percussion, Avenbrugger,
who clearly defined the subclavicular tympanitic resonance in
pleurisy.33 Skoda's sign, however, is not unique, for observation
proves, when the lung is contracted with fluid below, that there are
several varieties of resonance. Notta,34 who was not aware of Skoda's
ideas, describes the sound as hydroaérique where the lung is above the
level of the fluid. Roger,35 who called especial attention to Skoda's
views, admitted that there were several varieties of tympanitic
resonance heard above the fluid. He compares them to those heard on
percussing over the stomach of the cadaver. Woillez36 describes five
varieties or types of sonorousness, according to their intensity, their
tone, and their quality. He noticed these under the clavicle at
different points above the liquid—ordinarily on the level of the
second or the third rib. (1) The most common and the best defined was a
short sound, dry and superficial; the tone of this was acute, with
exaggeration of intensity. Williams37 in 1841 called attention to
these peculiarities. With this variety we frequently have a
reverberation, pointed out by Stokes in 1837—a cracked-jar sound more
or less marked. Woillez noticed this variety in 11 of his 82 cases; of
this number 9 were in pleurisy of left side. (2) There was exaggeration
of intensity or tympanism with a grave tone: 7 of Woillez's cases
showed
this variety, of which 6 were on left side. (3) A
subclavicular resonance, unnaturally acute, but with exaggerated
intensity. (4) Exaggeration of intensity, with equal tone on both
sides; only 2 patients out of 82 showed this variety. (5) Exaggerated
abnormal resonance, more acute than healthy side, and with normal
fulness of sound. These are all modifications of percussion sounds
elicited in pleurisy and other pathological physical conditions
resembling it, where there are variations of tension together with
other modification of the structure of the lung. The bruit de pôt fêlé
is sometimes clearly marked, as it is also in hepatization of lung.
33 Avenbrugger, Ouv., ed. de Corvisart, 1808, Paris.
34 Arch. gén. de Méd., 1850, t. xxii.
35 Ibid., 1852, t. xxix.
36 Mal. Aig. des Org. Resp., Paris, 1872.
37 The Path. and Diagnosis of Dis. of the Resp. Organs,
1841.
Traube's Semi-lunar Space.—There is a point on the left side where we
find normally a vesiculo-tympanitic sound, first pointed out by Traube
and enforced by Fraentzel. It is situated at the anterior base of the
left side, and is of a half-moon shape. It is bounded inferiorly by the
margin of the thorax, and superiorly by a curved line whose concavity
is turned downward. It begins in front, below the fifth or sixth costal
cartilage, and extends backward along the margin of the chest as far as
the top of the ninth or tenth rib. Its greatest breadth is from four to
four and a half inches. This tympanitic sound is caused by the air in
the stomach, which lies well up against the diaphragm. When the stomach
is pushed down by the falling of the diaphragm, from excessive fluid,
the tympanitic sound disappears. The value of this semi-lunar space in
the diagnosis of pleuritic effusions has been variously estimated.
Fraentzel considers it of great significance in the differential
diagnosis between pleurisy and pneumonia; Ferber and Garland do not.
Weil suggests that the area of this space may be diminished by filling
the stomach and colon with solid or fluid food. Garland shows that as
the diaphragm's depression depends upon the excess of fluid overcoming
the lifting force of the lung, we may have, with a vigorous, unimpaired
lung, a large amount of effusion in the pleural cavity, yet the
resonance of the semi-lunar space may remain tympanitic. The condition
of this semi-lunar space is of most diagnostic value in extensive
left-sided effusions. The more the diaphragm is pressed down by the
effusion, the smaller becomes the space of tympanitic resonance. It may
gradually disappear altogether.
Auscultatory percussion may sometimes be advantageously employed to
detect fluid in the pleura, especially in the younger subjects, for
intercostal fluctuation may frequently be appreciated when we press
carefully with the palm or surface of the finger between the ribs while
the percussion shock is applied to another part of the same side. If we
auscultate with a stethoscope, the chest extremity of which is made to
fit in between the ribs, while another person percusses the chest, we
can sometimes detect the fluctuation within the cavity of the chest.
We thus see that in the diagnosis of pleuritic effusions percussion is
very valuable, perhaps the most valuable of the physical signs. We must
not, however, forget that its significance may deceive us if the fluid
is prevented from gravitating by pre-existing adhesions, or if it is
encapsuled between the diaphragm and lung or between the lobes. Cases
occasionally occur where, from fibrinous bands, the fluid is kept in
the posterior part of the thorax, consequently there is pronounced
clearness and fulness in front. Percussion does not enable us to
diagnose the consistence of the contents of the pleura, or its nature,
whether it be fibro-serous or purulent. To do this we must resort to
Bacelli's method, or, still better, to exploratory punctures by the
hypodermic syringe.
Palpation.—The sense of touch gives valuable physical signs in
pleurisy. At the commencement, before there is any effusion of fluid,
even of fibrinous deposit, we notice by palpation the decreased
movement of the walls of the chest, and also the sensitiveness of the
walls. When the eye cannot
notice modifications of the expansion
and elevation movements or movements of the ribs, correct views may be
formed by palpation, especially in regard to the amount of local
expansion in the upper part of the chest. In the lower part, by
inserting a finger in the intercostal space we notice the modification
of local expansion, also the convergence of the ribs taking place
coincidently with the continuance of the elevation movement. We are
thus furnished with additional presumptive proofs of the impermeability
of the pulmonary tissue. When fibrinous effusion exists, the hand,
early in the disease, recognizes the pleuritic friction or grazing.
Later on, palpation perceives the rubbing when the muscles have
recovered from their temporary paresis.
As soon as the effusion begins to form we detect a lessening of the
delicate vibrations of the voice as communicated to our hands, always
guarding ourselves against error by remembering that the normal sound
is greater in the infra-clavicular region of the right side, and that
it is always weaker in children and women, unless they have shrill,
weak voices, in which case it may be entirely absent. It, indeed,
requires a certain sonority of voice to be felt through the walls of
the chest. When we find that both sides convey the vocal vibrations to
our touch, we may be sure there is no effusion of fluid. Errors are
often made by applying palpation over too extensive a surface, thus
reaching beyond the fluid. It is important to use light, delicate
palpation, employing the finger-tips instead of the whole hand, in
order to exclude the vibrations from above as we approach the confines
of the effusion. This vocal fremitus is entirely lost from the base up
to the point to which the fluid reaches, and later on when it separates
the two pleural surfaces. This absence of vocal fremitus is one of the
most valuable physical signs of pleuritic effusion. It enables us to
diagnose it from nearly all cases of lung-consolidation except when
caused by malignant disease. When there are considerable pleuritic
adhesive bands, they interfere with the complete absence of fremitus;
but in children this sign is not so reliable. With them vocal fremitus
is often scarcely perceptible in health. In dry tubercular pleurisy
palpation gives us the characteristic friction. Palpation detects also
the rubbing of the two lymph-covered surfaces after the absorption of
the fluid. When there are thick fibrinous bands extending between the
parietal and pulmonary pleuræ, there may be a vocal fremitus
notwithstanding the presence of a quantity of fluid in the pleural cavity.
Displacement of Adjacent Organs.—The displacement of the heart as a
physical sign indicating the presence of fluid in pleurisy is one of
great significance. It is indeed a cardinal sign, second only in value
to percussion flatness. It is almost invariably met with. Stokes38
stated that it was observed at an early period, and was one of the very
first signs of effusion; "that it may exist even before the upper
portions of the chest have become dull, and is a circumstance of
constant occurrence long before any yielding of the muscular portions
of the thoracic walls." The heart is displaced at the very commencement
of the effusion, and its dislocation increases pari passu with the
effusion. The absence of the displacement, unless it can be explained
by some special circumstance which rarely occurs, such as the retention
of the pericardium by old adhesions or consolidation of the opposite
lung, would negative the diagnosis of unilateral effusion. In this
condition there is a marked contrast with the displacement and
depression of the diaphragm and the resulting alterations of position
of liver, spleen, and stomach. These only occur when the effusion is in
great excess—not until from the large quantity of fluid the
retractility of the lung is overcome, and it is consequently unable to
lift up the fluid and the diaphragm. This altered position of the
diaphragm drags the heart
downward by means of the ligamentous
attachment of the pericardial sac to its tendinous portion. The
deviations from the normal positions of the heart in slight effusions
can always be noticed if the exact point of the apex-beat is sought for
by palpation and listened for with the stethoscope. Careful percussion
will show the shifting area of flatness.
38 Dis. of Heart and Aorta, 1854, Dublin.
Powell calls attention to a fallacy with reference to cardiac
displacements in the earlier stages of effusion—that, as the base of
the lung retracts, the left or the right margin of the heart, as the
case may be, becomes uncovered. This may lead to an apparent delay in
the displacement of the organ, the more extreme left or right boundary
being now within reach of palpation. The axis of the heart is not
greatly changed by an ordinary degree of effusion. It becomes a little
more vertical, and in extreme cases it may become slightly twisted.
Only in rare and extreme cases does the axis of the heart become
altered in direction beyond the vertical line. Powell39 found at a
post-mortem a heart that had become so twisted as to present itself
obliquely edgeways in front. Sibson had previously pointed out this
disposition of the heart to turn over and to present its posterior
surface forward in cases of effusion.
39 Consumption and Dis. of Lung, London, 1878.
In examining into the cause and significance of the displacement of the
heart in pleurisy we find that until within a few years, it was, and
indeed very generally now it is, believed that the sole cause was from
direct pressure of the fluid actually pushing the heart away from its
normal position. Skoda, Traube, Stokes, Powell, and Garland were, we
believe, the first authors to show that such was not the case,
certainly in moderate effusions. The displacements take place when the
amount is very small—too small to exert any positive pressure. It is
true that nature places the heart in such a position that it can yield
readily to slight forces. It hangs in the pericardial sac, which is
suspended by the aorta, and which is bound by ligaments to the body of
the third dorsal vertebra. Every change of position of the body causes
certain anatomical alterations of the heart's position. Wintrich,
Skoda, and Braune think that the heart swings like a pendulum from its
base, and that its apex is therefore elevated with every deviation to
the right or left. Lebert says the heart is first depressed by the
sinking of the diaphragm, and then elevated by being pushed to the
right. Fraentzel says that in displacements to the right the heart is
simply pushed over, and is never elevated as Wintrich describes it. The
mediastinum offers but slight resistance, and is very easily pushed to
the right side, where there is no compact organ to resist, and where
the cavity is larger; whereas it is with more difficulty pushed to the
left, where the heart occupies so large a space.
It has been satisfactorily demonstrated that until the pleura is about
two-thirds full of fluid no positive pressure is exercised upon the
lungs or heart. According to Rokitansky, the lung cannot be compressed
until seven-eighths of the pleural cavity is occupied by fluid. The
fluid cannot be drawn off by a canula unless air enters to replace the
fluid. Unless the pressure on the fluid from within the cavity is
greater than that of the atmosphere we cannot draw off a large
quantity: if the pressure balances that of the atmospheric air, only a
few drops of fluid are discharged externally, except by forced
expirations and coughs. This is the case even when the quantity reached
several liters. The feebler the expiratory force the less fluid
escaped. Yet the heart is displaced as soon as the effusion appears.
The significance of the displacement is that it shows the presence of
fluid, but does not show the measure of intra-thoracic pressure (Powell).
Garland's explanation is that the heart, with the sac and its
connections, "is placed between two highly elastic bodies (the lungs)
which are striving to retract in opposite directions. The heart,
therefore, being acted upon on
either side by opposing forces,
occupies a position where these forces just balance each other; and
this is the status of physiological repose in the vertical position of
the body. Now, when an effusion is poured into either chest, the lung
of that side contracts, and thereby exhausts a certain amount of its
retractile energy. The opposing lung, however, still remaining normal,
immediately begins to draw the heart toward itself, and the degree of
displacement thereby induced will be proportional to the diminution of
energy in the compromised lung." Stokes divided displacements of the
heart into excentric and concentric. The former he considered due to
direct pressure of the fluid, and the latter, when from any cause there
was diminution in volume of one lung, the other lung, by its increased
volume, forced it over. The concentric displacements, he thought, were
generally the result of some chronic disease producing atrophy of lung.
Thus we see that displacements of the heart occur at three distinct
periods in the course of pleurisy, and from different causes in each
case: (1st) As soon as fluid forms in the pleural sac. At this period
the displacement is caused by the presence of the fluid which occupies
part of the pleural cavity. The lung by its elasticity retracts. It is,
consequently, of less volume and exerts less negative force upon the
mediastinum and its contents than the healthy lung. The two lungs
having by their equal tractile energy previously kept the heart in
situ, the healthy lung draws the mediastinum out of its position in a
transverse direction. Necessarily, the displacement of the heart from
this cause is in proportion to the amount of fluid effused. This is the
most frequent mode of displacement of the heart. It can be said to be
almost always present. (2d) When the quantity of fluid is great enough
to overcome the retractility of the lung and exert intra-thoracic
pressure, it forcibly expels the air from the alveoli of the lung and
by direct positive pressure pushes the heart aside. The displacement of
the heart in this case can only be produced when the pleural sac is
two-thirds or more filled by fluid. When this condition is met with,
the displacement is very great, because the heart has been already
displaced by lung-traction. Previous to the researches of Garland,
Stone, and Powell, this was supposed to be the only manner of
explaining the displacement of the heart from pleurisy. (3) Where, as
illustrated by Stokes',40 Hunt's,41 and Chew's42 cases, the heart
is displaced toward the diseased side. This occurs more as a sequel of
pleurisy in the course of the absorption of chronic or suppurative
pleurisy, where by non-expansion of lung a partial vacuum is produced.
The external atmosphere presses in the thoracic walls of the diseased
side, and the internal atmospheric pressure from the healthy side is
exerted against the mediastinum and presses the heart in that
direction. Marked displacements from this cause are rare; slight
displacements are more frequent. Cicatrices from healing of large
cavities would have this effect. Mere consolidation of lung could not
cause it.
40 Dis. of Resp. Organs.
41 J. W. Hunt, Dub. Med. Journ., loc. cit.
42 S. C. Chew, case reported to Med. and Chi. Soc. of Md.,
1883.
Displacement of Lung.—The lung in cases of effusion is drawn up by its
own retractile energy. It has been demonstrated that this force is
considerable. As the effusion advances the lung recedes to a certain
point, when the fluid, having overcome the retractility of the lung and
having a fixed point below, actually exerts positive pressure upon the
lung (Garland), and compresses the air out of the alveoli and the
compressible bronchi. This compression cannot take place until the
diaphragm is no longer elevated into the thorax, but is bagged down by
the excessive weight of the fluid. There can be no compression of lung
until its elasticity has been exhausted. The gradual effect of the
continued contraction of the lung is to straighten out the letter S
curve. The force of lung necessarily diminishes gradually as it
contracts in volume. On the other hand, the immediate effect of
compression is to
obliterate that curve. So long, therefore, as
we are able to trace a well-marked letter S on the chest, we may be
certain that the lung is well out of reach of compression (Garland).
Peyrot43 showed by plaster-of-Paris injections into the chests of
cadavers, and then making cross-sections, that deformities of the chest
are not due to a development of one side, the other remaining normal,
but that they consist of a mutual adjustment of all parts. The
simultaneous movement of the sternum toward the left in left-sided
effusions makes the displacement of the heart appear greater than it
actually is.
43 Arch. gén., Juill., 1876.
The Diaphragm and Intercostal Spaces.—The diaphragm is not depressed
below the edges of the ribs, nor do the intercostal spaces bulge until
the weight of the fluid exceeds the lifting force of the lung. The
admission of air into the pleural sac produces the same result. The
depression of the diaphragm is due in part to the weight of the fluid,
but chiefly to the diminished contractile energy of the retracted and
diminished lung. The displacement of the mediastinum depends upon
similar conditions. Since the traction of the lungs always affects both
sides of the thorax, the movable mediastinum must follow the lung,
which is still capable of contracting, and therefore with right-sided
exudations the left lung will draw the parts over to itself. Only with
excessive effusions in the pleural cavity does the pressure of the
fluid come into activity.
The liver and spleen may be pushed below their normal position by
excessive effusion after the diaphragm yields to the weight of the
fluid. Woillez found the liver displaced downward in the abdominal
cavity in one-fourth of the right pleurisies and only once in left-side
pleurisies. The extent on the right side was from two or three
centimeters to three fingers' breadth, even as far as the umbilicus.
The stomach, when the diaphragm sinks, may be pushed downward; thus the
so-called semi-lunar space of Traube may be obliterated. Ferber noticed
a peculiar displacement of the stomach in two cases where he had
produced an artificial hydrothorax of the left side. The fundus was
pushed to the right, and the stomach was folded over on itself to a
certain extent. A second and marked folding-in of the greater curvature
occurred near the pylorus. This condition of stomach, with left-sided
pleural exudations, has been hitherto entirely neglected by authors.
May not the vomiting which is often observed with excessive effusion,
and which has been attributed to violent acts of coughing, be due to
this doubling over of the stomach?
Auscultation.—At the commencement of acute pleurisy, when hyperæmia
exists with dryness of the pleural surfaces, auscultation shows a
respiratory murmur lessened in intensity and duration. There is also a
jerking unevenness in the rhythm of respiration, and weakness or
indistinctness of the vesicular murmur consequent upon the imperfect
and irregular expansion of the lung. On the healthy side the
respiratory murmur is hypervesicular, and becomes puerile and noisy in
character. In from twelve to eighteen hours the plastic fibrinous
deposit on one or both pleuræ causes us sometimes to hear, over
circumscribed spots, at the end of inspiration and the beginning of
expiration, a fine friction sound, which varies in intensity over the
points of contact of the surfaces. This is especially the case in the
infra-mammary, infra-axillary, and infra-scapula regions. Woillez heard
friction sounds in 52 of his 82 cases. The pain in respiration makes it
very jerking and irregular. The contact of the surfaces pushes aside
the lymph, and thus we hear the sound at a given point at one
inspiration and not at another. It is heard more distinctly during
inspiration than expiration. The reason of our not hearing the friction
sound at the early stage of pleurisy continuously, but with
interruptions in inspiration and expiration, is because the opposed
rough pleural surfaces do not continuously rub against one
another, but remain adherent for a few moments, until a deeper
inspiration tears them asunder. The effusive stage comes on so rapidly
in acute pleurisy that often when patients are examined the friction
sound of the first stage has disappeared. It has been generally taught
that the cause of the disappearance of the friction sound, and its
subsequent reappearance as convalescence commences, are owing to the
fluid separating the surfaces and its reabsorption. We have seen, from
Garland's experiments and from careful clinical percussion
explorations, that the fluid does not come between the two surfaces
unless in very great effusion, but that it occupies the cavity between
the lung and diaphragm. Stokes long since showed that there was
temporary paresis of respiratory muscles, and consequently loss of
movement of the surfaces over each other, which movement was necessary
to produce friction sound. The reappearance of friction sounds
indicates recovery of this muscular power. When heard, the friction is
of the grazing variety—the most delicate form. Walshe designates it as
the attrition species, and says it is audible over a limited extent of
surface, occurring with occasional respirations, dry, and limited
strictly to inspiration. As the effusion appears, we find, beginning
with the lower border, that the respiratory murmur disappears, becoming
less distinct as the effusion advances in the pleural cavity.
Ordinarily, we hear no breath sounds. The absence, however, of breath
sounds as a sign of pleuritic effusion is by no means a constant one.
When the fluid contains many fibrinous bands, binding the lung down to
the costal pleura, or when the effusion is very large and forces the
air nearly out of the pulmonary tissue, pressing it into a firm mass
against the vertebral column (at a point corresponding to the spine of
the scapula), or when the lung is solid simply from the residual air
being pressed out of it, diffused bronchial tubular breathing is heard.
The tubular sound is conveyed, not ordinarily through the fluid, but by
the parietes of the chest and by the solid plastic linings and
adhesions. The fluid, if in large quantity and filled with fibrinous
bands, may also feebly conduct the sound, which, being produced on
solid surfaces, is best conducted by solids. We hear, in fact, a
respiratory sound of low pitch, but tubular in quality. It is
bronchial, but it differs widely from the familiar bronchial
respiration observed when the lung is consolidated in pneumonia. It is
a diffused distant tubular sound unaccompanied by moist sounds, soft in
its quality and muffled. It has not the brazen, harsh character of
pneumonic bronchial respiration. In pneumonia this sound is immediately
under the ear, the lung being in contact with the inner surface of the
ribs, and rendered a good conductor by its solidity, and the sound
rendered louder by the increased consonating properties of the walls of
the bronchi; whereas, in pleurisy, the lung is contracted above the
level of the fluid, or, when the effusion is excessive, is removed from
the walls by an indifferent conductor of its sounds, and the sounds are
conveyed from the compressed lungs at their base by the walls of the
chest, and, in a degree, by the deposits on the pleural surfaces. The
bronchial breath sound which we hear over the lung, compressed by
fluid, near the vertebra continues sometimes a long time after the
absorption of the fluid, because the lung, deprived of air, expands
slowly. If the effusion be small, we do not hear bronchial respiration,
because there is sufficient air in the alveoli to prevent the
conduction of the sound, the air not being compressed out by the
effusion, but the whole lung being lessened in volume. If, again, the
mass of fluid be very large, it prevents the free transmission of the
waves of sound, and we do not hear them.
The auscultatory phenomena necessarily vary according to the amount of
fluid in the cavity, the extent of the adhesions, the retraction, and
the compression of the lung-parenchyma. If the compression be
sufficient to prevent the air from passing down the bronchi, we do not
hear bronchial respiration,
because where, as in health, it is
not communicated to the ear (owing to its non-conduction by the
lung-tissue), it cannot be produced. Douglass Powell44 calls
attention to another unusual pressure effect—altered quality of voice
and cough, a husky voice, and a laryngeal quality of cough
undistinguishable from that so often heard in cases of mediastinal
tumor or aneurism. These disappear after paracentesis.
44 Consumption and Dis. of Lungs and Pleura, 1878.
Above the level of the fluid, and again as absorption of fluid takes
place, we have a return of the characteristic friction sound as the
muscles of the chest recover their normal power. With care this sound
will not be confounded with intra-pulmonary râles, which are moist
sounds removed or modified by cough or expectoration. These convey to
the ear the sound of bubbles of air as they pass through the mucus and
the secretions of the bronchi; whereas the friction sounds are
superficial noises from rough surfaces moving over each other. The
mucous râles which are sometimes heard are not from the pleurisy, but
from bronchial catarrh. The friction sounds heard in the stage of
absorption are ordinarily coarser and more abrupt. They are unequally
jerking in character, and in quality resemble osseous crepitation. In
chronic pleurisy, and for a long time after the fluid is gone in acute
pleurisies, we have pleuritic rubbing sounds when the walls of the
chest are drawn out in full respiration. At the absorption stage we
ordinarily hear the lung gradually expanding. The respiratory sounds
are feeble, and frequently moist subcrepitant râles are heard in the
bronchial tubes. If the effusion has been of long duration, we find the
pleural surfaces so thoroughly coated with fibrinous deposit, and the
lung so separated by bands from the costal pleura, that the expansion
of the lung is very much impaired and the percussion dulness does not
subside. Leaming and Camman of New York give numerous cases where there
might well be difference of opinion as to whether the signs heard were
intra-pulmonary or pleuritic. In cases where the intra-pulmonary
adventitious râles resemble the extra-pulmonary frictions, the
diagnosis is assisted by considering the length of the sound. The
character and intensity of the friction murmur varies very much. It may
be a slight grazing sound or a coarse, sharp creaking-of-leather noise.
Walshe gives no less than six modifications of the friction sound,
ranging from a feeble, scarcely audible noise to one of extreme
loudness. Friction sound is mostly an isolated phenomenon—that is, it
is not accompanied by any unnatural quality of respiratory or vocal
sound. Advanced type friction consists of a series of jerking sounds,
rarely exceeding three or four in number.
We must remember that sometimes, notwithstanding a considerable
quantity of fluid, the lung expands, and, pushing the fluid aside,
causes the rubbing of the pleural surfaces together. When unmistakable,
these respiratory friction phenomena are pathognomonic of the results
of pleurisy. Thus they are properly considered of great value in the diagnosis.
Pneumo-pericardial Friction Sounds.—On the left side the uneven
pleural surfaces are sometimes forced together by the impulse of the
heart; of course, the resulting friction sounds are cardiac in their
rhythm. Then, again, fibrinous deposits on the outer surface of the
pericardium are forced against those of the covering pleural layers,
both by respiratory and heart impulses. Close attention to the rhythm
and the positions where these sounds are heard will prevent their being
considered pericardial in their nature.
The fluid may be nearly removed and yet the condensation of the
superficial strata be sufficient to produce extensive and marked
dulness. Under such circumstances the production of friction phenomena
is inevitable. The retention of some portion of the lung surface in
tolerably close proximity to the costal pleura by means of adhesions
also renders the production of
friction sound possible, although
a considerable quantity of fluid be present in the pleura. It is common
to find effusion signs in the back and friction signs in front. We most
frequently have friction at the base when there is absolute flatness.
If the walls be separated by fluid, there can be no friction from
contact. But it rarely happens that the fluid rises between the
surfaces. To produce friction sounds we must have motion of rough
surfaces which are in contact.
If the patient talks while we are listening in cases of small effusion
we hear over the scapula, toward the spine, and between the scapula and
the spine, bronchophony, as we do also when the lung is nearly deprived
of air, in which case the sound sometimes has the bleating, nasal
resonance designated by Laennec ægophony. In his opinion this was of
constant occurrence and of great diagnostic value, but now it has been
demonstrated that this sound can be heard when there is no fluid
whatever, but consolidated lung. Anstie calls it one of the fancy signs
of pleurisy. Ægophony is an unimportant variety of bronchophony, and
not a characteristic phenomenon of pleuritic effusions. Of itself, it
is not diagnostic of effusion, yet it is none the less true that it is
a modification of bronchophony, and is commonly met with in cases of
moderate pleuritic effusion, usually toward the upper margin of the
fluid. It is difficult to state definitely the amount of fluid which
usually produces it. Guttman thinks it is probably produced by the
vibration of the walls of the flattened, compressed bronchi; this
vibration is excited by the voice and transmitted to the thin layer of
fluid which, at the upper part of the exudation, lies between the lung
and the chest-wall. This tremulous movement of the sides of the bronchi
gives the voice sounds a quavering, interrupted character; and, as they
have to pass through a fluid medium to reach the surface, they lose in
clearness and precision and acquire a nasal twang.
When the effusion is large, and we have full dilatation of the chest,
all vocal resonance ceases, because the vocal vibrations go through
media of such different kinds that they are lost before they reach the
ear. During absorption, before the lung recovers its normal volume, we
again hear bronchophony. Pleural adhesions and thickening cause the
sound to be heard through the effusion when we least expect it. It is
not unusual to find ægophony and bronchophony in the same lung. They
are also found in some cases of pneumonia, and in some individuals,
especially in children, we have between the scapula a normal resonance
of the voice, with an ægophonic resonance.
Bacelli's Sign (Pectoriloquie aphonique).—This, the reverberation of
the whispered voice through the fluid, is a sign of considerable value.
If well marked it indicates fibro-serous fluid; its absence, however,
does not show that the fluid is not of this character. (See Purulent Pleurisy.)
Auscultation is of great value as indicating with definiteness the
position occupied by the effusion as it is being reabsorbed.
Heart Murmur.—From excessive accumulation of fluid in the pleural sac
a systolic murmur over the base of the heart is very often heard. That
it is produced by pressure or twisting of the aorta is evident from the
fact that it ceases when the fluid is withdrawn.
Phonometry we have found of but little value in the diagnosis of pleurisy.
COURSE AND DURATION. Acute pleurisy is essentially a unilateral
disease. It does not pursue a regularly-defined course, nor have we any
critical stages, as in pneumonia. In mild cases of acute primary
pleuritis the disease advances slowly and recovery is tardy. The
febrile movement may be four or five days in reaching its height. It
remains at this point for several days—from four to seven days; in
rare instances as long as ten days.
The effusion sometimes comes on very rapidly, but ordinarily is one or
two days in forming. When it appears it may be divided into (1) the
stage of
progress, (2) stationary period, and (3) resolution. For
the examination of both of these we must employ percussion, and
mensuration by means of the cyrtometer, which give us exact results.
Woillez in a large number of observations found that the first period
lasted from eleven to twenty-four days, most frequently from fifteen to
twenty days. The stationary period he found varied from twenty-four
hours to several days. Frequently the reabsorption commences suddenly
without any interval. Resolution is initiated from the eleventh to the
twenty-fifth day, and lasts over fifteen days.
As the effusion advances the acute symptoms—rapid pulse, the elevated
temperature, acute pain, and superficial dyspnoea—are materially
lessened. If, however, the effusion be very great, we shall have at
first painful dyspnoea, especially when the patient makes unusual
exertions. This dyspnoea is ordinarily in proportion to the amount of
the effusion. If there is much displacement of heart or distortion of
larger blood-vessels, there is imminent danger to life. After the first
few days we are often surprised at the tolerance of the whole system of
the excessive amount of fluid. Absorption, after the effusion has been
thrown out, is at first rapid, then it occurs more gradually; part of
the liquid portion disappears, and the fibrinous portion undergoes
fatty degeneration previous to absorption. The physical signs of
flatness, vocal fremitus, together with the return of the displaced
organs, the heart, liver, and diaphragm, to their normal positions,
give us accurate means of judging of the progress toward cure. The
general health shows unmistakable signs of improvement. The appetite is
better, as are also the color and strength. If the effusion remains
undiminished in quantity, or if it becomes purulent in character, the
general appearance will show evidences of weakness and lowered vitality.
The average duration of acute primary pleurisies varies, when the
effusion has not reached any considerable height, from two to four
weeks. It may continue thirty or thirty-eight days—minimum duration
twenty days. The absorption requires many weeks if the effusion is
large or if it becomes chronic. Two months may elapse before the fluid
entirely disappears. In some cases it continues, unless thoracentesis
be performed, for many months. We have given the symptoms manifested
when there is any renewal of the inflammatory process. In pleuritis
acutissimus death may occur in ten days or two weeks from syncope, or
from thrombosis caused by pressure upon the large venous trunks and
consequent twisting, especially of the ascending cava, where it
perforates the central tendon of the diaphragm to reach the
pericardium, or by torsion of the aorta. When the effusion remains for
a long time, the lung may be permanently prevented from expanding by
pleuritic thickenings resulting from inflammatory products. In acute
primary pleurisy the tendency is toward resolution. Louis went so far
as to state that pleurisies never caused death. Trousseau, Lacaze, and
others give cases where sudden deaths were produced by the quantity of
fluid pressing upon the heart and blood-vessels. In subacute pleurisy
(latent pleurisy of the older writers) the course of the disease is so
gradual, so unattended by pain or even discomfort to the patient, that
he goes perhaps weeks with considerable fluid in the cavity without
being aware of it. He has probably been able to continue his occupation
without intermission. It is only when he begins to feel weak and to
lose flesh, and finds that his respiratory force is impaired, that he
consults a physician. The rational symptoms scarcely point to pleurisy,
but the physical signs of the presence of fluid are very distinctive.
In this form the effusion is ordinarily greater in quantity than in the
acute variety, and unless some of the fluid be taken away by
aspiration, absorption is very sluggish. In these cases, if the fluid
remains long in the cavity, the lung may become permanently disabled by
the long continuance of the compression.
In chronic pleurisy the effusions from the acute or subacute
pleurisies remain unabsorbed. They ordinarily are purulent in
character, but sometimes they remain sero-fibrinous many months.
Purulent pleurisies may be primary as well as secondary. (See Purulent
Pleurisy.)
TERMINATIONS.—Pleurisy of a fibro-serous nature terminates in (1)
convalescence, (2) becomes chronic, or (3) ends fatally. Among those
who are cured there are some instances where the disease is of short
duration and the recovery prompt and complete. With others the disease
itself is of a severer type and lasts longer. If the attack of pleurisy
be secondary to another disease, especially if the latter be of a
nature to profoundly affect the nutrition, convalescence is very tedious.
Acute pleurisies which are primary but rarely become chronic, but when
secondary they frequently are chronic from the beginning. Heyfelder
states that chronic pleurisies are three times more frequent on the
left side than on the right side.
Trousseau, Bowditch, Lacaze, Behier, and others have reported sudden
and unexpected deaths in cases of fibro-serous pleurisies. Not only has
this resulted in cases where the fluid was excessive in quantity, but
also in cases where the amount was moderate. Wilson Fox (Brit. Med.
Journ., Dec., 1877) gathered from medical literature between 50 and 60
sudden deaths from effusions of all kinds. Syncope has been the usually
assigned cause of death. Négrié45 collected 12 cases of unexpected
deaths from pleurisy, and there were but 2 of them where syncope could
be assigned as the cause of the fatal termination. Of the remaining 10
cases, 3 were caused by what is invariably a grave complication,
pericarditis, and 7 by clots formed in the heart or pulmonary artery.
In the cases where pericarditis existed the deaths occurred as early as
the eleventh or twelfth day. In the other cases death occurred as late
as from the twentieth to the forty-fifth day. Woillez46 reports 2
cases where death was produced by supervening congestion of healthy lung.
45 Thèse de Paris, 1864.
46 Loc. cit.
COMPLICATIONS AND SEQUELÆ.—The inflammation may extend by contiguity
to the lung-parenchyma, pneumonia supervening after a few days, or it
may appear to come on simultaneously. It is, however, a rare
complication. Lacaze47 reported one case, and that followed
thoracentesis; Lugrol reported a similar case.
47 Loc. cit.
Pneumonia does not appear to commence after the effusion has reached
the point of compressing the lung. The inflammations frequently are
peribronchitic and broncho-pneumonic. The mediastinum may become
involved. Fraentzel states that it can never be clearly proved that
simple croupous pneumonia exists as a complication of primary pleuritis
on the side affected; on the sound side it occurs occasionally. Laennec
taught that the compression by the fluid always tended to prevent the
occurrence of pneumonia. Anstie's opinion was that when the lung is
compressed to carnification it is incapable of inflammation. The most
formidable way in which pneumonia may complicate pleurisy is where,
considerable effusion existing in one pleura, inflammation attacks the
opposite lung. It may be doubted whether this ever occurs in truly
primary pleurisies: kidney disease, specific fevers, pyæmia, etc.
nearly always precede it. Hyperæmia or congestion of the opposite lung,
without its amounting to pneumonia, does occur, and is a very grave
complication. The same may be said of double pleurisy and peritonitis
as resulting from blood-poisoning. It rarely happens in primary acute
pleurisy that both pleuræ become involved. When such is the case,
however, it is generally tubercular in its nature, and necessarily a
very grave if not a fatal complication. Walshe reports having seen 4
cases of idiopathic bilateral pleurisy in persons thoroughly healthy
and perfectly free from constitutional taint of
any kind. In all
the pericardium was involved, and in 1 the peritoneum. They were all
fatal. Acute pericarditis from extension of the inflammatory process is
a frequently-occurring complication. When the inflammation extends to
the pericardium, the effusion is of the same character as that of the
pleurisy, whether it be sero-fibrinous, purulent, or hemorrhagic. It is
a complication of great gravity and is sometimes the cause of a fatal
termination of the pleurisy. We have never met with endocarditis as a
complication, but Fraentzel speaks of having seen it in acute pleurisy
in children. Before complete carnification occurs oedema of the lungs
may be produced on the diseased side or in the healthy lung. This
pulmonary oedema, when it attacks the sound side, is acute, being
produced by rapid pulmonary congestion, which causes free, albuminoid,
and frothy expectoration, often ending in asphyxia. The serum and
albumen of the blood by transudation pass into the bronchi and the
alveoli, and fill them more rapidly than they can be expectorated: the
subject dies by suffocation. Auscultation reveals fine vesicular râles,
characteristic of oedema of the lungs, closely resembling the fine
crepitation of pneumonia. Traube has named this oedema pneumonia
serosa. Engorgement it certainly is, but it can scarcely be designated
a pneumonia. It closely resembles the oedema we meet with after
thoracentesis, which has been named by Hérard expectoration albumineuse.
Bronchial catarrhs, when complicating pleurisies, cause dyspnoea, add
much to the discomfort, and protract the duration of the disease.
Barth48 speaks of dilatation of bronchi as a complication of
pleurisy. Woillez49 calls attention to a complication which has been
generally overlooked by the authorities—a persistent pain which some
patients suffer in the side of the chest a long time after the disease
has been cured. The most dangerous complications are syncope, formation
of clots, venous emboli, and exaggerated distension of the thoracic
walls by the effusion.
48 Mém. de la Soc. Méd. d'Obs., Paris, 1856.
49 Article "Pleurisy," Mal. Aigu. Resp., 1872.
Sequelæ.—The connection of pleurisies, especially chronic, with
subsequent tuberculosis, is very generally admitted. Bartholow says:
"The importance of pleuritis as a cause of phthisis is hardly
sufficiently recognized in inducing tubercular deposit, and by adhesion
limiting the movements of the organs, and thus inducing diseases."
Anstie says: "It is now well established not merely that pleurisy often
occurs in phthisical lung disease, but that pleurisy itself is capable
of setting up true tuberculosis even in previously healthy persons.
This is specially apt to occur where purulent effusion has been allowed
to remain too long in the pleura, or where paracentesis has been
performed repeatedly for empyema, the wound being closed in the
interval." Modern authors thus consider that a productive field is
offered for the bacillus tuberculosis.
Flint states that "in an analysis of 47 cases, in 3 the subsequent
development of phthisis was probable, although not demonstrated, and in
1 case only the occurrence of this disease as a sequel was certain." Of
53 cases reported by Blakiston, not one became phthisical during
several years after recovery from the pleurisy. Flint says the effect
of chronic pleurisy with effusion in a person already phthisical is to
arrest or retard for a time the progress of phthisis. We have mentioned
the retraction of the chest-walls with deformity of shoulders and
spine, and the permanent dislocation of the heart and larger
blood-vessels, as serious results, as also the orifices produced by the
bursting of the empyemas outwardly. These may all in time, with
judicious care and treatment, be very materially lessened, and even
cured. Empyema sometimes causes destruction of the periosteum of the
ribs and subsequent necrosis. It is questionable whether there are any
cases of pleurisy which do not leave more or less extensive adhesions
between the two pleural surfaces. In many cases they do not, it
is true, seem to injure seriously the general health, yet they must
impair the full functions of the lungs. How frequently this is the case
is shown at autopsies of persons dying of other diseases, where we find
extensive adhesions when we had no reason during life to suspect that
such would be the case. Adhesive bands may interfere with the expansion
of the lungs and cause chronic bronchial catarrhs, ending in death.
Caseous pneumonias are among the sequelæ of pleurisy. When the false
membranes are thick and numerous, the lung remains impervious to air
and useless. This condition sometimes produces bronchiectasis. While it
is true that the lungs, when the effusion is not great enough to
actually compress them, sometimes retain their expansibility for three,
six, or even eight months, yet there are cases where they do not expand
after being bound down for months, and then we have depression of the
walls of the chest. Woillez met with 6 such cases.
DIAGNOSIS AND PROGNOSIS.—The diagnosis of the several varieties of
pleurisy ought easily to be made by the due appreciation of the general
symptoms and physical signs we have enumerated. Cases occur where the
differential diagnosis is not free from difficulties, even to the most
careful of observers. Pleurisies on the left side are more easily
diagnosed than those on the right side. Most of the signs are much more
frequently observed on the left than on the opposite side: some of them
are rarely met with except on the left. Before the discovery of the
science of auscultation and percussion pleurisy and pneumonia were
frequently confounded. By their aid the two diseases may ordinarily be
diagnosed with precision. In both there are chilliness, fever, cough,
and dyspnoea. At the initiation of acute pleurisies, we expect for
several days more or less of chilliness, but in pneumonia one, or at
most two, decided rigors. The temperature in primary pleurisy rarely
goes beyond 100° F. in the first twenty-four hours, whereas in croupous
pneumonia, in the same length of time, it not unfrequently rises to
103° F. or 104° F. In consequence of this high temperature in pneumonia
the skin becomes hot and dry, with frequently a bright spot on the
cheek corresponding to the side of the diseased lung. This is not the
case in pleurisies, where, on the contrary, we have a pale, anxious
expression of face. The comparatively mild fever of pleurisy is
continuous. We have not, as in pneumonia, the marked changes, often of
two or three degrees, between the morning and evening temperatures, nor
have we critical days (between the fifth and eleventh) where the fever
breaks with rapid defervescence.
Pleurisy is a more prolonged disease, and is not self-limited. The
cough of pleurisy is short and quick, with no expectoration, unless it
is thin, frothy mucus. In pneumonia the cough is longer, and is
accompanied by a tenacious expectoration, more or less free, and
generally (not always) tinged with blood. The rusty-colored sputa is
almost characteristic of pneumonia. At first there is a marked
difference in the dyspnoea in the two diseases. In pleurisy it is
superficial, because the lungs are not freely expanded in consequence
of the accompanying pain. In pneumonia it is deeper and the oppression
is greater. The struggle for breath in the first stage of pneumonia is
frequently alarming to witness. The relative frequency of pulse and
respiration is more modified in pneumonia. The stitch-like, cutting
pain in pleurisy is characteristic and very circumscribed, whereas in
pneumonia, unless the pleura is involved, there is little or nothing
beyond a dull soreness. We have in pleurisy the restrained movement of
the side affected, and corresponding increase of movement of the
healthy side. Not so in pneumonia. At the beginning of croupous
pneumonia we generally have the crepitant râle heard in inspiration,
but not observed in pleurisy. The friction sound, if present, heard in
inspiration and expiration, is equally characteristic of pleurisy. If,
as sometimes happens, we do not hear either
the crepitant râle or
the friction sound, we must be cautious in our diagnosis until we have
the more definite symptoms of the next stage.
Later on in the clinical course of the diseases, in their second
stage—consolidation in pneumonia and effusion in pleurisy—the
physical signs enable us to make the differential diagnosis. We expect
dulness in both diseases, but it is more absolute in pleuritic
effusions, and to the finger, as a pleximeter, the resistance is
greater. In pneumonia there is very seldom complete dulness over the
whole side of the chest, for there are frequently lobules not
consolidated, or spots where the solid deposit has been partially
absorbed. Moreover, the area of dulness is not bounded by that peculiar
curved line, with its concavity at the base behind, facing the
vertebra, gradually becoming convex as it turns upward and forward
toward the axilla, again descending toward the sternum, as is the case
in pleuritic effusions. Changes of position of the patient may cause
the fluid, when in large quantity, in pleurisy, unless prevented by
fibrinous adhesions of the two surfaces, to gravitate to a greater or
less degree, and thus alter the points where we have flatness on
percussion. The enlargement of the thorax, the bulging of the
intercostal spaces, the marked displacement of the organs, and the
frequently complete obliteration of the semi-lunar space, are
characteristic of excessive pleuritic effusions. The displacement of
the neighboring organs, especially of the heart, is a very valuable
diagnostic sign of pleurisy.
There are, however, other conditions besides the presence of fluid,
such as new growths and pneumothorax, which, by increasing the contents
of the chest, may produce the same result. We may also meet with cases
of congenital malposition of heart or instances where infantile
disease, or constrained position, necessitated by occupation, have
caused malformation of the contents of the chest.
The most characteristic percussion sign of effusion in pleurisy is the
semi-tympanitic (Skodaic) or amphoric resonance high up in front. In
rare cases it is found in pneumonia, but it is most pronounced over the
consolidated lung, whereas in pleurisy it is above the level of the
fluid. The vesicular murmur is not heard below the level of the fluid,
unless very feebly at its upper surface, nor indeed is the passage of
the tidal column of air up and down the bronchial tubes. In pneumonia
bronchial respiration and increased resonance of voice rapidly
supervene; whereas in pleurisy the voice is obliterated. In pneumonia
we find the characteristic loud, high-pitched, brazen bronchial
respiration over the whole of the consolidated portion. When a tubular
quality is given to the inspiratory murmur in pleurisy, it is a
diffused, distant, and low-pitched sound from the compressed lung.
There is a marked contrast between the increased vocal fremitus of
pneumonia and its entire absence in pleurisy. In pneumonia there is
strong bronchophony with a jarring thrill to the ear, but there is not
the displacement of the adjacent organs, the increased volume of the
affected side, nor the widening and bulging of the intercostal spaces,
with sometimes fluctuations, perceived on auscultatory percussion, as
in pleurisy.
Although both diseases are ordinarily unilateral, yet we more
frequently meet with double pneumonia than with double pleurisy. It
must be borne in mind that we may discover the coexistence of pneumonia
and pleurisy. When this does occur special care must be taken in the
diagnosis. In cases of pleurisy on the left side, sometimes the impulse
of the heart forces the two surfaces of the pleura together, and causes
us to hear a pleural, cardiac friction sound. It has the rhythm of the
heart, and is heard when respiratory movements have been suspended.
This sound is limited to the left border of the heart. Care is needed
to prevent the error of diagnosing pericarditis.
The diagnosis of pleurisy from hydrothorax, or passive transudation of
fluid into the cavity of the pleura from mechanical causes or
blood-poisoning, depends upon the recognition of the fact that
ordinarily the latter is not
ushered in by fever—that it is
bilateral, and is frequently accompanied with dropsy in other parts of
the body. Transudations being slowly developed, the lung gradually
contracts, and the presence of the fluid is tolerated for a
considerable time; indeed, it is not until it is excessive that it
compresses the lung. Thus, dyspnoea is not ordinarily produced until
the accumulation is very great.
Sometimes the diagnosis between pleurisy and intercostal myalgia, or
pleurodynia, is confused and uncertain. The pain may be as intense and
the respiration as jerky where there is no pleurisy, if there is great
soreness of the muscles between the ribs. The pain is, moreover,
accompanied by more or less rise of temperature. Oftentimes the
respiration is as painful as in pleurisy, for the individual
instinctively refrains from causing the muscles to contract. Usually
there is greater tenderness on pressure over the walls of the chest,
less fever, and the area of pain is larger in this form of muscular
rheumatism. The friction sound, if present, makes the diagnosis clear.
We sometimes remain in doubt for twenty-four hours.
Intercostal neuralgia less closely resembles pleurisy. It occurs
without fever, generally in anæmic subjects or in those debilitated by
chronic general diseases, especially uterine. The tenderness is limited
to several points along the course of a nerve, at the exit of the nerve
from the spinal cord, in the axillary region, and near the sternum.
Pericardial effusions and aneurisms can ordinarily be readily diagnosed
from pleurisies. Their positions in the cavity are so well defined, and
the accompanying physical signs are so characteristic, that they ought
not to be confounded with pleuritic effusions.
Solid tumors and cysts occupying a considerable portion of the pleura
or bulging into it from the mediastinum may deceive us into thinking
that there is an effusion. They displace organs, press upon the lungs,
or intervene between the lung-texture and the walls of the chest, thus
preventing us from hearing the entrance and exit of air and the
vibrations of the voice. Not containing air, we have flatness on
percussion. Being solid conductors, we have with them increased vocal
fremitus, whereas in pleuritic effusions it is not perceived.
Ordinarily, tumors are found at the superior or central portion of the
chest, and cause an irregular bulging of the walls instead of the
general enlargement caused by liquid effusions. Before the discovery of
the present modes of physical diagnosis intra-thoracic growths,
especially cancerous ones, were frequently confounded with pleurisies
by even the most careful observers. Now such errors are only
occasionally committed. The history of the case, the general symptoms,
absence of fever, etc. will assist us in making the differential
diagnosis. A careful examination by physical exploration will give us
valuable aids. The bulging produced by malignant growths is not so
marked nor is it so uniform. The dulness on percussion is not so
pronounced. It does not vary from changes of position of patient. The
displacement of heart and other organs is not so marked. Hunt50 calls
attention to the considerable blood-stained expectoration from cancer.
He calls it currant-jelly expectoration. We must look also for the
characteristic signs of cancerous cachexia and enlargement of glands in
the axilla and in the supra-clavicular fossa. The exploring
aspirator-needle will generally enable us to arrive at an accurate
diagnosis, with the assistance of a microscope to examine the fluid or
solid matter withdrawn. The fluid thus obtained from cancer is
generally blood-stained.
50 Loc. cit.
Inflammations of the pleuræ are sometimes caused by the presence of
intra-thoracic tumors. Abscesses of the liver and echinococci cysts may
ascend, and, pushing the diaphragm before them, occupy the pleural
sacs, and thus simulate pleuritic effusions.
Pulmonary atelectasis, caseous inflammation of the tissue of the
lung, aneurisms of the large thoracic blood-vessels, may, without care,
be mistaken for pleurisies. It is very important to ascertain the
nature of the fluid effused into the pleural cavity, whether or not it
is serous, sero-fibrinous, purulent, or hemorrhagic. Generally this can
be done by careful study of the accompanying general symptoms and the
clinical history of the case. If there are repeated irregular rigors
from the beginning, followed by high fever and free perspirations,
there is every reason to fear that the fluid is purulent. If symptoms
of blood-poisoning develop, we are still more confident that there is
pus. Its hemorrhagic character may be inferred when great pallor,
weakness, and lowered temperature suddenly appear during an acute attack.
Bacelli's physical sign known as pectoriloquie aphonique, or the
passage through the effused fluid of the whispered voice, has
considerable significance as a means of testing the nature and
character of the fluid. His conclusion was that, when heard, it showed
the fluid was fibro-serous; when not heard, it revealed to us that the
effusion was purulent or sero-purulent. Laennec had noticed that in
voiceless consumptives the whispers would sometimes resound as if the
patient shouted in the ear of the auscultator. R. Douglass Powell
reported51 10 cases bearing upon the value of this sign. In 6 of
these, in which the fluid was clear, 5 yielded the sign, the sixth did
not. In 2 acute cases, when the effusion was purulent, the sign was
heard. He adds that he has heard the sign to perfection in fetid
sero-purulent effusion. Mercadie52 claims that when pectoriloquie
aphonique is heard in purulent effusions it is only at the uppermost
part of the fluid near its limit, where it has become very thin from
the weightier portion, the flocculi, and the leucocytes falling to the
dependent portion of the sac. Care must be taken in listening for this
sign. The patient must be ordered to speak each syllable slowly and in
a whisper, distinctly counting up to twenty or thirty. If it be present
we ought to be able to perceive that the syllables sound, to the ear,
clearly articulated along the height of the effusion. The sound is
caused by the transmission of the whisper without any buzzing and
without continuous murmur. The maximum of intensity of this sound is
heard along the vertebral gutters and along the posterior base of the
pleural cavity. It becomes feeble in its distinctive character as we
approach the axillary region and also immediately under the angle of
the scapula. The theoretical objection has been made to this sign that
its production is contrary to well-known physical laws of the
conduction of sound-waves. It is said because the sound originates in
the air it must be indifferently conducted by fluid; moreover, that its
transmission ought to be in proportion to the density of the fluid,
whereas this sound is best conducted by a thin fluid. Walshe's
explanation of the greatly-increased sound-conducting power of a
consolidated lung in croupous pneumonia was that it was owing to its
homogeneity of structure. Bacelli avails himself of this principle to
account for our hearing through a fibro-serous fluid the whispered
sonorous waves, and our not hearing them when the fluid was
sero-purulent or purulent. In the latter case the fluid is excessively
heterogeneous, containing leucocytes in abundance, besides layers of
membranes, flocculi, and blood-discs. The sound-waves are lost as they
pass through these media of different density. We have found it to be a
physical sign of value in the differential diagnosis of the nature of
the fluid, yet its presence is not pathognomonic of serous effusions.
In thin fluids it is generally heard, and ordinarily it is not found in
purulent pleurisies. If well marked, it indicates a fibro-serous
effusion. Its absence does not necessarily show purulent pleurisy. Its
greatest value is as indicating the purulent transformation of a
fibro-serous effusion.
51 Trans. Int. Med. Cong., 1881, vol. ii.
52 Thèse de Paris, 1876.
Thanks to modern investigations, we have in the very fine needle of the
aspirator, or that of the hypodermic syringe, a delicate and sure
means of accurate diagnosis, not only as to the nature of the fluids,
but as to that of tumors and growths which may be confounded with them.
We would not use for exploration a trocar and canula. We consider it
best to employ a short needle in aspiration, for fear that a delicate
hypodermic needle might break. Flint states that he has known several
instances of this accident. Aspiration can be performed with perfect
safety, and, indeed, without any fears of unpleasant results even if we
perforate an aneurism. The orifice made is so small that the tissues
close the moment the needle is withdrawn after making the exploratory
puncture. If care be taken to cleanse the instrument and to use
Listerism that no deleterious germ be introduced, the operation is
harmless. (See Purulent Pleurisy.)
Blunders in diagnosis, however, will rarely occur if an examination is
conducted with great accuracy, and if we follow the course of the
disease with care.
PROGNOSIS.—The prognosis of simple primary pleurisy is generally
favorable, unless it is complicated with other diseases or occurs in
enfeebled persons. The intrinsic tendency of the disease is to
recovery. Laennec considered that the prognosis in acute pleurisy was
always favorable. Pleurisy with scanty sero-fibrinous effusion is not
in itself serious. Dry pleurisy is free from danger. Subacute pleurisy
with large effusions, where the course of the disease is insidious and
slow, is more apt to be followed by tuberculosis than the more acute
cases. Louis's law, deduced from 150 cases, that patients never died
from the effusion in acute pleurisies, was long since disproved by
Trousseau. Lacaze du Thiers published in 1873, in his thesis, a number
of cases of sudden death from large accumulation of fluid. These deaths
were caused by a large amount of effusion being thrown out rapidly, and
suddenly compressing the lung before the system had time to accommodate
itself to the presence of the effusion. These cases, termed foudroyant,
should be very carefully watched. There is danger of death from
orthopnoea when the pleural cavity is completely filled, especially in
latent pleurisies, where the patient, unaware of the risk, makes,
perhaps, unusual physical exertions. Some deaths have been caused by
oedema of the lungs and some by syncope; others, again, from thrombosis
of the pulmonary artery. We must bear in mind the grave prognostic
value of attacks of orthopnoea and severe dyspnoea, because they, more
than the mere quantity of the fluid, show the want of tolerance in the
organism. These cases demand prompt mechanical interference with the
aspirator. The very rapid accumulation of the effused liquid, even if
unattended by dyspnoea, is an unfavorable sign, for observation has
proved that in such a case its absorption is attended with more
difficulty. Bilateral pleurisies attended with considerable effusion
are commonly fatal.
If there are complications with other acute diseases, such as
pericarditis or pneumonia, the prognosis may be far from favorable,
more particularly if pleurisies supervene when the organism has been
exhausted by a long continuance of the primary disease.
If absorption begins soon after the acute symptoms subside (and we
expect it to do so where the general health and strength are good), and
goes on vigorously, we can with confidence predict a favorable result,
especially if there be no contraction of the walls. The earlier the
reabsorption takes place the more favorable the prognosis. If, however,
four or five weeks pass without any perceptible diminution in the
extent of the effusion, there is cause for uneasiness. Especially is it
dangerous if, in addition, we have those ugly symptoms, emaciation,
weakness, and hectic fever, which point to the conversion of the fluid
into pus. There is the prospect of protracted formation of pus with its
dangerous sequelæ, including tuberculosis from infective absorption.
That these dangers can in a great measure be obviated by prompt
thoracentesis ought now to be universally admitted. Anstie predicts
that the experience of the next twenty years will enable us to ensure
an absolute immunity from fatal results from either of these serious
complications. Symptoms of oedema of the lungs or of cyanosis are bad
prognostic signs; so is diminution in the amount of urine secreted,
which indicates that the arteries are incompletely filled. Still worse
are the symptoms of over-distension of the veins, dropsy, and the
appearance of albumen, casts, and blood in the urine.
The prognosis in secondary pleurisies is much more serious. In cases
where the effusion is purulent at their commencement, the prognosis is
graver than when it becomes purulent after remaining some time in the
cavity. This is because they are often pyæmic in their origin.
With modern treatment, however, the percentage of recovery is greater
than it formerly was. When we have to contend with chronic purulent
cases occurring in cachectic constitutions or in those debilitated by
other illnesses, especially tubercular, the prognosis is necessarily
unfavorable. The most fatal of all secondary pleurisies are those
supervening in the course of pyæmia or puerperal infection. Here death
is the rule, recovery the rare exception.
Pleurisies supervening on Bright's disease or nephritis, following
scarlatina and idiopathic fevers, have a high rate of mortality. The
modern employment of the thermometer is of the greatest assistance to
us in forming our prognosis. Marked variations of temperature, whether
they be below the normal or constantly high or advancingly high, have
grave significance. Anstie's valuable results from the use of the
sphygmograph, as giving us the favorable and the unfavorable pyrexial
pulse-forms, cannot be over-estimated. We fully concur with him, "that
in the dangerous secondary pleurisies the combined use, for prognostic
purposes, of the thermometer and the sphygmograph is more valuable than
all the other modes of observation put together." It is so because they
give us accurate physical data by which we can estimate the exact
condition of the patients.
Relapses, with a rapid increase in the amount of fluid after
reabsorption has been active and convalescence apparent, are frequently
attended with danger, because they often denote a tubercular or
hemorrhagic development. A very unfavorable sign is the rapid increase
in the effusion after spontaneous or artificial discharges, especially
if the fluid has become fetid in its character and has the dark
appearance of unhealthy, purulent matter.
TREATMENT.—The study of the natural history of acute fibrino-genic
pleurisy teaches us that there is always in it a tendency toward
recovery unless there is some constitutional weakness behind the
disease or a large fibro-serous effusion resulting from it. We have all
met with cases where patients have recovered in the course of a month
or six weeks spontaneously, without any treatment. Of A. L. Mason's 200
cases, 132 recovered without having to resort to thoracentesis. It is
often a harmless disease when left, as far as medical treatment is
concerned, entirely to itself. Of course the body-temperature and the
physical evidence of the effusion ought always to be carefully
observed. The hygienic treatment ought never to be neglected. We should
insist upon rest in bed in the most comfortable position to the
patient. The temperature of the room should be from 65° F. to 68° F.,
the approximate in-door winter degree for healthy adults.53 The body,
especially the chest, should be kept quiet; all unnecessary movement
should be avoided. The food ought to be nourishing in quality, easy of
digestion, and in quantity sufficient to keep up healthy nutrition.
Stimulants are unnecessary, but it is a mistake to withdraw water,
which contributes so much to the comfort of the patient and
cannot injure him in the first stage. We should take care that the
patient has enough sleep. If necessary, mild hypnotics should be used.
The effusion results from the inflammatory process, and not from simple
transudation. If the pain is very severe, we must resort to the
administration of opium by mouth or to hypodermics of from one-eighth
to one-sixth of a grain of morphia; this, however, should be avoided
when possible, as preparations of opium impair the appetite and depress
the patient. The pain ordinarily passes off in 48 hours, and can often
be relieved by application of hot-water bags, turpentine stupes, or
anodyne liniments. Bloodletting, general or local, is rarely necessary.
Leeches will give relief to the acute pain, but opium does that more
effectively. Depletory remedies are hurtful and retard convalescence,
and do not control the amount of the effusion, which in itself is
depletory. If the patient is seen at the initiation of the disease, a
large dose of quinia (from ten to fifteen grains), especially if the
temperature goes to 101° F., often has a marked effect in controlling
the temperature and also the tendency to effusion. Smaller doses may be
repeated every few hours. Liq. ammonii acetatis, in fluidrachm j to
fluidrachm ij doses every two hours, and Apollinaris or other alkaline
drinks, relieve vascular tension and promote the action of the skin and
kidneys. During the pyrexia, with the effusion increasing, we endeavor
to lower arterial pressure within the pleural vessels by aconite,
diaphoretics, mild salines, diuretics, with complete rest of the body.
Hot applications (not heavy poultices, however) may sometimes be used
at short intervals, with a view of dilating the superficial vessels and
thus relieving those of the interior.
53 Boston City Hosp. Reports, 3d Series, 1882.
Under this simple treatment many patients are sufficiently well in a
few weeks' time to sit up. They ought not to be permitted to move about
unless there is a very small amount of effusion. Roberts54 of
University College Hospital applies adhesive strips over the chest in
all cases from the beginning. Mason prefers Martin's india-rubber
bandage, three or four inches wide, extending from the lower border of
the ribs to the axilla, as it adapts itself better to the chest-walls
and supplies an easily-regulated elastic pressure. He considers it also
useful in promoting absorption after tapping. Generally in three or
four weeks, in favorable cases, the effusion has been absorbed and the
patient is able to resume his ordinary duties. The writer cordially
endorses Anstie and Bartholow's protests against the employment of
mercury for any supposed aplastic properties. It really exhausts the
recuperative forces of the organism, and probably injures instead of
benefiting in pleurisy.
54 Quain's Medical Dictionary.
If the exudation be in considerable quantity, three or four weeks may
be required for its absorption. If this process is sluggish, can we by
medicines promote it? Mercury has lost its old reputation as a remedy
for this purpose. Iodine externally, and iodide of potassium in decided
doses, still retain, to a limited extent, the confidence of
practitioners. Preparations of iron, especially the muriatic tincture,
have had better effects in the hands of the writer than any other
remedy. Large blisters cause great discomfort, and their utility is
very questionable. Alkalies possess the power of dissolving exudation,
and of these the most efficient is ammonia, especially carbonate of
ammonium in doses of from five to ten grains. Saline laxatives, by
producing watery stools, have some power in reducing the amount of
fluid. Some authors recommend highly the acetate and citrate of
potassium dissolved in a decoction of scoparium. J. W. Hunt55 places
most reliance upon pilocarpus pinnatus, which has given him most marked
and successful results, even where other remedies have failed. He
pushes it to the extent of producing extreme diaphoresis. He commences
with thirty minims of the fluid extract four times daily, rapidly
increasing
the quantity and the frequency of the doses to the
extent of fluidrachm j every two hours. The one-eighth of a grain of
its alkaloid, pilocarpine, given hypodermically, acts very promptly. He
admits that the vital forces are so exhausted by this treatment as to
require at once the administration of tonics, especially of iron with
strong food. Grasset56 reported 5 cases of effusion treated by
jaborandi. They were cases of pleurisy without fever or sign of
inflammation—cases which ordinarily require several blisters to
produce an effect.
55 Dublin Journal Med. Sci., Dec., 1882.
56 Journal de Thérapeutique, Avril, 1876.
Ernest Wernaere57 reported 7 cases of acute pleurisy where there was
considerable febrile reaction. Jaborandi was effectual in every case,
and the effusion rapidly disappeared after two doses of the infusion.
The fever at the same time was diminished, and there was no return of
it, as frequently occurs in non-inflammatory cases. It has less effect
upon children than upon adults. In a case of Wernaere's only one dose
was given.
57 Thèse de Paris, 1876.
The value of counter-irritants has been frequently questioned of late
years. Fly blisters give relief in limited dry pleurisy. Many
practitioners have great confidence in large blisters used over the
chest after the febrile stage has subsided. Woillez, in tabulating the
results of the various means of promoting absorption, puts purgatives
first in utility, and blisters last. Blisters, he claims, had no effect
in 90 per cent. of cases. The iodide of iron, in pills, or the compound
syrup of the iodide of iron and manganese, with improved digestive
powers, are the best means of promoting absorption. At this period of
the disease it is an advantage to lessen, within certain limits, the
amount of fluid taken into the stomach, forcing the blood to abstract
water by absorption from the chest. Jaborandi has the same effect by
withdrawing water from the blood.
There are cases of excessive quantity of fluid, and others which resist
all drugs given to promote absorption. Among these are some acute
cases, but many of a subacute and chronic nature, where the effusion
remains stationary, injuring respiration and often mechanically
endangering life. This occurred in nearly one-third of Mason's cases.
Thoracentesis.—In studying the history of this operation we have seen
how frequently, since the time of Hippocrates, it has been in favor
with practitioners, and then has fallen into discredit. During the past
thirty years, thanks especially to Bowditch and Trousseau, its
unquestionable value has been established, and is now universally
recognized. Improved knowledge of pathology, safe and easily-applied
instruments, together with the discovery, by Lister, of the means of
securing the operation from septic dangers, have perfected this
surgical treatment. Observation in hundreds of cases has proved that,
properly used, it is almost without risk. As a means of diagnosis it is
the most accurate we possess; as a treatment for affording positive
relief it is a boon to suffering humanity; as a method of cure it has
been most successful.
Such being the estimate of its value, let us study, 1st, the
indications for its use; 2d, the manner of operating; 3d, and finally,
the objections founded upon the accidents that have followed its application.
The indications are met with in two conditions—that of excessive
accumulation of fluid, and where there is non-absorption of the effused
liquid. In going over the symptoms we have seen the effects of large
collections of fluid in the pleura—how the heart is pushed out of its
normal position, and how the large blood-vessels are distorted. We have
called attention to the retraction and compression of the lung until in
many cases it is airless, and thus not able to perform its functions.
We have shown that all the adjoining organs and cavities are sometimes
forcibly thrown out of the position nature placed them in. The liver is
pressed forward into the abdominal cavity, and
the diaphragm is
unable, from mechanical pressure, to ascend and contract. The
mediastinum, with its contents, is materially interfered with.
Observation has shown that such a state is a very dangerous one. Not
only does it cause great dyspnoea, pain, and oppression, but the risk
to life is imminent. In a number of instances it has caused death.
Trousseau tells us of 3 deaths; Lacaze reports others. Bowditch, having
seen several fatal cases produced by the quantity of fluid, worked with
energy and perseverance until he was furnished by Wyman with his
ingenious aspirator, of which he promptly availed himself,
notwithstanding the objections he met with from others. "Ridicule," he
says, "was pointed at me by some high in surgery: at first the whole
medical profession was against me." He could not stand still and see
men die whose lives could be saved. Chew had a patient die suddenly
from this cause. Many authors mention cases of death from the large
amount of fluid. Wilson Fox summed up from the records between 50 and
60 deaths from effusion in the pleural sac. Moreover, many patients
have died where the disease was not recognized. The condition of the
circulatory apparatus is such that we can readily understand that
emboli would form in the heart, in the large blood-vessels, and in the
parenchyma of the lung itself. These clots produce grave results. If
they form in the pulmonary veins or in the left heart, they determine
an embolic obstruction of the central artery, with all its
consequences—apoplexy, hemiplegia, etc. If it forms in the right heart
or in the pulmonary artery, it may produce rapid aphasia and death
(Paget). Louis was certainly wrong when from his 150 cases of pleurisy
he deduced the law that none died of this disease per se. It is thus a
matter of the utmost importance that we should be able to recognize
that there is a quantity of fluid capable of producing such serious
results. The call for relief and diminution of the amount of fluid by
thoracentesis is urgent. What amount is dangerous to life, and how can
we arrive at an accurate estimate? To what extent can we judge by the
subjective symptoms, especially by the dyspnoea? Andral and Trousseau
both speak of it as a very fallacious and uncertain symptom, and by
itself may be unimportant as an indication. In the beginning of the
disease we find suffocating dyspnoea for a time when there is very
little fluid. Diffusible stimulants and anodynes give relief. On the
other hand, there are patients who with large amounts of fluid, even
two quarts, walk about with but little difficulty in breathing, and
attend to their pursuits unconscious of being in danger of sudden
death. Bowditch58 speaks of several fatal cases in simple pleurisy
from excessive amounts, "from sudden failure of the power of the heart,
with or without more or less dyspnoea." This is especially the case
where the fluid forms insidiously, without marked general symptoms.
When, however, we meet with dyspnoea, together with other and more
reliable symptoms, it is very significant of danger, and ought to force
us to resort to thoracentesis to afford mechanical relief. If we rely
upon general symptoms, we may be deceived as to the amount of fluid,
and serious results may follow. However, we must bear in mind that the
most imperative reasons for thoracentesis are the signs of threatened
failure of cardiac power. Bowditch lays down the rule that "if the
dyspnoea is excessive, so as to amount to permanent orthopnoea, or if I
learn that within a few hours previous to my visit there has been even
one attack of momentary orthopnoea during which the patient felt as if
the breath would be wholly lost, I tap immediately, provided I am sure
that there is even a small quantity of fluid in the pleural cavity, and
that it is apparently the chief or perhaps only cause of the
orthopnoea. I fear," he says, "death may occur before my next visit."
This eminent American authority on this subject lays down as the result
of his vast experience the rule that "when a patient comes under
notice in whom a large quantity of fluid has been long effused, I
advise thoracentesis as the first remedy." The author ventures to
assert that where the amount is excessive there is imminent danger to
life from the mechanical results of the presence of the fluid, even
during the febrile stages; consequently thoracentesis is urgently
necessary. I am confirmed in this view by Dieulafoy, Fernet, Clifford
Allbutt, Marshall, and Cross. Barnes59 says in all cases where the
effusion is large and where dyspnoea is urgent it is better to operate
at once. "It is my practice to operate at once when the chest is two
parts filled with water, without waiting for urgent dyspnoea."
Dieulafoy, in discussing these questions, states,60 after consulting
all the authorities accessible to him, that death has never been caused
by less than two liters (equivalent to 62½ fluidounces), except in one
instance reported by Blackey, where after death there was found 1500
grammes (47 fluidounces). In adults with well-formed chests he
considers 1800 or 2000 grammes as the amount demanding surgical
interference. He candidly acknowledges that he cannot make this an
absolute rule, because the capacity of the pleural sacs must
necessarily vary in different individuals according to their height,
breadth, development of thoracic muscles, sex, etc.; consequently, the
inconveniences and functional disturbances produced by a given quantity
of fluid in the chest must be different in different persons. But how
can we arrive at an accurate estimate of the amount in the chest?
Dieulafoy,61 in calculating the quantity, states that if it amounts
to 1200 grammes when it reaches the sixth intercostal space, it ought
to be valued at 2000 grammes when it is found at the third intercostal
space. This is only approximative and unreliable. The height of liquid
is not always proportional to quantity. It varies with size of chest,
resistance of organs and walls, and condition of lungs. Potain insisted
upon the difficulties that the pulmonary hyperæmia caused in the
diagnosis, the abundance of fluid, the variable degree of yielding of
the lung, and the adhesions which have drawn the walls to the lung. The
true way of judging of the necessity for the operation is from the
grave functional disturbances and by the definite positive physical
signs which give us unmistakable indications which we dare not neglect.
We can calculate the amount of the effusion by the level of the
flatness on percussion, by mensuration with the cyrtometer, and of the
impaired thoracic movements by the stethometer. Physical examination
reveals the extent of the displacement of the heart and other viscera.
The displacement of the abdominal viscera, the liver, the spleen, and
the stomach shows that there must be excessive amount of effused fluid
in pleura—enough to produce serious intra-thoracic pressure. This is a
condition demanding surgical interference. The Skodaic resonance under
the clavicle, the complete flatness being horizontal instead of giving
us the Ellis curve, impaired resonance over the posterior triangle
becoming absolute dulness, the presence of cavernous or amphoric
respiration near the sternal-clavicular articulation, and, in rare
instances, subclavian murmur from pressure upon the subclavian
artery,—all these signs give unmistakable evidences that the pleural
cavity is full of fluid. It is important, in considering the treatment,
to form a correct estimate of the degree of intra-thoracic pressure,
for Erichson has shown that the mere collapse of a lung affects but
little the facility of the circulation through it; its compression or
forcible collapse necessarily retards the circulation and throws extra
work upon the already overburdened heart. The more precise our physical
diagnosis, the more appropriate will be our treatment. Douglass Powell
found the intra-thoracic pressure to vary from a – pressure to ½ and
1½ inches of mercury at the commencement, and from –1/8 to –½, and even
–1, inch mercury at the termination of paracentesis, there being in all
cases a more or less considerable amount of fluid still remaining in
the pleura. He states,
as the result of his own observations,
that in recent cases the period of effusion at which the intra-thoracic
pressure is converted from a – pressure or zero to a positive pressure
upon the lung and heart is marked clinically (1) by the flatness
mounting up above the third cartilage (patient in sitting position),
and (2) by the Skodaic resonance becoming changed from the full note to
a more tubular quality. The extent of Skodaic resonance is a very
valuable indication of the amount of fluid, and consequently of the
propriety of operating. If this tympanitic resonance be down to the
third rib, and the cyrtometer shows no decided enlargement, we had
better not interfere. On the other hand, if the Skodaic sign is not
heard, and instead there is flatness, we will be sure to find decided
increased measurements and tubular breathing behind. Under such
circumstances we may feel confident of positive intra-thoracic pressure
of from one inch to one inch and a half of mercury—an amount
sufficient to compress the lung and interfere with the heart's action.
There is some danger of syncope, even if the patient remains motionless
in bed, but if he moves about he is in imminent danger. The subject is
annoyed by a straining retching cough with frothy, viscid sputa with
perhaps some discolored points. The heart and the lung of the healthy
side give warning of the danger, which ought never to pass unheeded. A
murmur may be heard over the displaced heart, and over the lung on the
unaffected side we may hear a fine crepitant râle, showing pulmonary
hyperæmia and resulting oedema. The syphon or aspirator will afford, by
withdrawing perhaps a quart, the necessary relief. Nature will do the
rest in a large proportion of cases.
58 Unpublished MSS.
59 Brit. Med. Journal, Dec., 1877.
60 Nouveau Dict. Méd., vol. xxviii., art.
"Thoracentesis."
61 Loc. cit.
We cannot always estimate accurately the quantity of fluid by the
displacement of the heart and other organs. The retractile energy of
the lung is a very important factor in producing this result. A very
large effusion, associated with a very powerful lung, will produce but
slight displacements, while small effusions, when the lung of the
affected side has lost its elasticity, will cause relatively great
displacements (Garland). If there be no adhesions present, the letter
S curve of flatness becomes a sign of the greatest value. It marks
accurately the height of the effusion. Knowing this, as well as the
position of the heart and diaphragm, and the capacity of the chest, we
can estimate the quantity of fluid in the pleural cavity. If in left
pleurisies the heart be so pressed out of position that its apex beats
to the right of sternum it is very diagnostic. With these signs,
whether accompanied by dyspnoea or not, we must regard thoracentesis as
imperatively called for. The presence of the febrile movement is not a
counter-indication under these circumstances. The presence of a basic
murmur, caused by the heart or aorta displacement, is an urgent
indication for surgical interference.
There are attacks of fainting and syncope, suffocative paroxysms, with
irregular and painful palpitations of the heart, with sometimes
alarming threatenings of asphyxia—especially in pleurisy of the left
side. These symptoms are probably due to the twisting of the inferior
cava as it passes through the quadrilateral foramen of the diaphragm.
The danger is necessarily increased by long continuance of the
effusion. Prompt surgical treatment is indicated when we detect
evidences of embarrassed circulation in the opposite lung, with a
blowing quality of respiration and subcrepitant and oedemic râles.
In all cases of double pleurisy, where the total amount is sufficient
to fill one whole cavity, we ought not to postpone operating. Even when
the effusion is not very large, if there are other diseases of the
respiratory or circulatory systems to cause grave complications, and
danger of increased impairment of their functions, thoracentesis is
rendered necessary. That these conditions justify thoracentesis we
believe no one who has any practical experience will question. But two
conditions exist where there is considerable
difference of
opinion in regard to the propriety of operating: 1st, during the
febrile stage, and, 2d, where moderate effusion remains unabsorbed.
In regard to the first of these, many authorities, even among the most
enthusiastic advocates of the operation, have contended that unless
there is imminent danger to life from the excessive collection of
fluid, it should not be withdrawn, as it would at once re-form, and
additional inflammatory action might be excited by surgical treatment.
Castiaux,62 however, strongly advocates the view that the operation
by aspiration will hasten the cure of acute pleurisy and prevent the
formation of the fibrinous deposits and bands which to a greater or
less degree, even in moderate effusions, impair the expansion of the
lungs. He relates 37 cases, almost all of which were operated upon by
himself. He was successful in all of them, and the patients suffered no
inconvenience or discomfort in consequence. In most of his cases the
pulse and body-temperature fell (perhaps the same day, certainly the
next morning), and even became normal after the operation, and the
patients improved rapidly. He aspirated as soon as he detected the
presence of fluid by exploratory punctures, believing that from the
moment we have at our disposition sure means of relief which are
harmless, it is useless to leave to nature the duty of removal—useless
to leave to untrustworthy medication the relief which we can promptly
give. He operated at the height of the first or inflammatory stage of
the disease. He assigned as reasons for operating that he thereby
relieved the lung of the compression which impairs expansion; that he
removed a liquid rich in fibrin and capable of increasing the thickness
of the neo-membranes; that by restoring the power to dilate he further
prevented the lung from being compressed by the false membranes. These
membranes cannot become organized unless they are separated by fluid.
He states that he removed the fluid as completely as possible. As soon
as the cavity was emptied respiration was made easy and the patient was
relieved. Auscultation showed, by the vesicular murmur, that the lung
had resumed its place without difficulty from top to bottom. The
effusion returned, only in a few cases, with high temperature and
frequent pulse, but another operation effectually arrested them. The
pleurisy was cut short and puncture was considered the means of
aborting the disease. The duration of the disease treated by this means
was much shorter. Thus the patients were not forced to retain for
months the liquid and false membranes in their chest. He states
emphatically that there never supervened any accident, and especially
that he never witnessed as a result the transformation of the serosity
into pus, although it might appear theoretically likely to occur, as
the serous membranes, already inflamed, ought to be more sensitive to injury.
62 Thèse de Paris, 1873.
This testimony is very strong. Moutard-Martin operated upon 12 patients
with fibro-serous effusions where they had existed less than ten days,
and where there was more or less of fever. Out of this number, 8 had no
reproduction whatever of fluid, and in 4 there was only a slight
re-formation, and there was no degeneration into purulent fluid in any
of them. In the other cases operated upon, where the effusions dated
from twenty to sixty days, the fluid was almost always reproduced,
though ordinarily to a moderate extent. He urges the prompt withdrawal
of the fluid as the most successful method, especially if there is
reason to suspect the formation of false membranes.
Wedal's63 results confirm this view of the harmlessness of punctures
during the febrile stage; and, more than this, they show that they
hasten the cure. He operated on 17 patients from the second to the
fifth day, and three times from the eighth to the tenth day. In cases
of acute disease, where the patients were exempt from pulmonary or
bronchial complications, the cure was not protracted beyond the twelfth
day. Some were cured by the sixth day. His patients were, for the most
part, vigorous men, young
soldiers—very favorable subjects.
Ordinarily, however, as shown by J. L. Mason's64 report of 132 cases
where the operation was not performed, the duration of the attacks was
weeks, and in some cases months. He considers the operation more apt to
be successful if performed early in the disease, and that the existence
of fever is no contraindication. The author has always pursued a more
conservative course, and abstained from operating in the febrile stage
unless, as in three instances, the effusion was so rapid in its
formation that there was danger of serious consequences from the amount
of the fluid. In these three instances the result was successful and
without unpleasant sequelæ. Moutard-Martin65 states that aspiration
made during the febrile stage is in no way prejudicial to the patient.
Dieulafoy66 advises us to wait until the fever falls.
63 Étude clin. des épanchments pleurit., 1877.
64 Boston City Hospital Reports, 3d Series, 1882.
65 Loc. cit.
66 De la Thoracéntèse dans la Pleur. Aigue, 1878.
To remove the effusion during the inflammatory stage does not appear to
be rational treatment unless the quantity is so excessive as to
endanger the life of the patient. The fluid remains limpid unless
exposed to air or contact with foreign substance. When, after a time,
there is some coagulation, it is only of a thin layer which covers and
protects the roughened surface of the pleura. A certain amount of
effusion is useful; it separates and bathes in a bland fluid the tender
and inflamed surfaces, and keeps at rest the affected portion of the
lung. The lung in health exercises a constant traction upon the pleural
sac, the vessels of which have therefore to sustain a negative or
aspiratory pressure: this being so, it is physiological that if these
vessels become temporarily weakened and congested by the inflammatory
process, increased exudation proceeds from them. The effect of this
exudation is to neutralize lung-traction, and therefore to lessen the
afflux of blood to the weakened vessels. "Fluid effusion being thus
both natural and salutary, in acute pleurisy we must be watchful, but
not meddlesome" (Powell). We must not hurry, but we must try if nature
will not by spontaneous absorption cause it to subside. We can
ordinarily do this up to the end of two or even three weeks before
resorting to artificial means.
The defervescence in pleurisy, we have seen, has no fixed period, as in
pneumonia. In favorable acute cases the absorption begins as soon as
the temperature begins to fall. Moreover, the liquid may be absorbed,
notwithstanding the continuance of fever, and the effusion may continue
notwithstanding the defervescence. In the subacute form the febrile
period passes by unnoticed, although the effusion is often in large quantity.
When not urgent, how long should we wait for absorption of fluid? This
is a question much discussed, and not yet settled. What becomes of the
effusion in the acute pleurisies?
In the first days of its formation the liquid portions of the effusion
are reabsorbed by the normal vessels of the serous membranes at the
points left intact and the recent vessels of the neo-membranes, but the
organization of these last demands, to be complete, from two to three
weeks; it is not until the end of that time that they will be most
favorable to reabsorption. Dybkowsky points to the anatomical fact that
the lymph-vessels are found only in those parts of the costal pleura
which cover the intercostal muscles, while the portions which are
reflected over the ribs are destitute of such vessels.
On the other hand, the eccentric pressure made by a considerable
effusion on the pleuræ may retard their vascularization and lengthen
out the work of absorption. Moreover, during the time necessary for
that organization a certain quantity of coagulable fibrin is deposited
on the surface of the serous membranes. The pseudo-membranous bridles
are not slow in forming, and cause the adhesions which press the lung
against the costal wall, the
vertebral gutter, and the superior
parts of the thoracic cage, toward which the effusion tends to force them.
In very favorable cases the effusion may disappear by the twentieth day
of the disease. In many cases, however, it lasts with the false
membranes for several weeks, and not infrequently for many months.
Cases are recorded by Powell and others where the effusion remained of
a sero-fibrinous character for eighteen months and two years. Flint
mentions two cases where the effusion was permanent, having lasted for
years. Wilson Fox67 thinks that there is but slight danger of the
fluid becoming purulent from mere lapse of time unless the patient
should have another fresh inflammatory attack. It must be noted,
however, that such is not the case in children. Voyet68 says that
simple pleurisy in infants is transformed into purulent pleurisy with
facility and extreme rapidity—so much so that when with these a serous
effusion is slowly absorbed there is great danger of suppuration taking
place. M. Vertiac69 states that chronic serous pleurisy may not exist
among children. In 13,000 sick children in eleven years Barthez did not
have a single case. Pathological anatomy has demonstrated to us that
this fluid in separating these neo-membranes on the parietal and
pulmonary pleuræ increases their development. The plastic rugosities
collect the fibrils of fibrin on their surface, in the same manner as
they are found on the twigs in whipping the blood, and as the
atheromatous deposits on the interior of blood-vessels favor the
formation of emboli. These false membranes may cause a number of
complications by surrounding the lung with a thick, inelastic shell.
The collapse of one part of the lung diminishes necessarily the field
of hæmatosis, and consequently causes a compensatory congestion of that
lung, and even of the lung of the other side. This occurring in an
individual predisposed to tuberculosis or in a condition to develop and
cultivate the bacillus tuberculosis may start the disease. Formad70
maintains that pleurisy is a very frequent cause of pulmonary
tuberculosis. These imperfectly organized embryonic membranes cause
deformities of the thorax; they are good ground for the growth of
pathological products, such as cancer or tubercle; their fragile
capillary vessels are the principal cause of a most troublesome form of
hemorrhagic pleurisy. (See HEMORRHAGIC PLEURISY.) If the lung be
compressed but a short time, it does not undergo irreparable injury,
but if for a considerable time, the thickened organized membrane, with
the effusion, causes a more or less considerable atelectasis, binding
down the lung and preventing its expansion. The author holds that the
effusion, after the fever has subsided, is, in itself, a foreign and
troublesome element; for even with a medium effusion we are not exempt
from unpleasant results.
67 Brit. Med. Journ., Dec., 1877.
68 Thèse de Paris, 1870.
69 Ibid., 1865.
70 Paper read before the Baltimore Clinical Society,
February, 1883.
Although, in moderate effusions, there is no compression of the lung,
yet there is necessarily collapse of it pari passu with the amount of
fluid. This interferes with its retractive power—the aspiration force,
as it has been called—by which the venous blood is drawn into the
right side of the heart. T. B. Curtis of Boston calls attention to this
very important fact, and shows that the result must be disturbance of
circulation, with imperfect blood-supply to the heart, interrupted
cardiac action, feeble arterial tension, together with venous repletion
and stagnation. In consequence of this condition there is a diminution
of the quantity of urine, and, as generally occurs where there is
venous congestion, a small quantity of albumen, cyanosis, etc.
Fraentzel, Traube, and Lichtheim attribute the venous stagnation, etc.
to obstruction in the pulmonary circulation resulting from pressure
exercised by the effusion. Curtis and Garland hold that these bad
symptoms are not caused by pressure, but by the diminished pulmonic
retractility which exercises the negative pressure of emptying the
large venous trunks.
Such being the ill-effects of the retracted lungs, is it well to
allow even a moderate amount of fluid to remain in the pleural sac
after Nature has failed to remove it? Besides, the presence of liquid
alone displaces the organs, especially the heart and lungs; adhesions
form and keep them in an abnormal condition. The retracted lung, bound
down by bands, becomes enfeebled, loses its suppleness, and is rendered
rigid, seriously impairing respiration. There exist three
factors—false membranes, adhesions,71 and interstitial
pneumonia—which tend to seriously disable the lung and even to produce
complete atelectasis pulmonum. We must bear in mind that there is some
danger of the fluid becoming purulent, especially if a fresh
inflammatory attack should occur. The less time a pleurisitic effusion
lasts, the sooner the patient will be placed beyond the probability of
these serious injuries to the process of hæmatosis. It is but right to
give Nature an opportunity, assisted by iron, salines, diuretics,
iodine, and even blisters, in cases of moderate effusion. The rapidity
of Nature's work in many cases in removing large quantities of fluid
here and elsewhere is wonderful. But if she does not act, we ought not
to let our patient become feeble and depressed in his nutrition, or
perhaps maimed for life, by not withdrawing the fluid. Sometimes the
absorbents only half do their work of removing the fluid, and leave a
quantity in the chest. Under these circumstances tonics, good diet, and
change of air will complete the absorption.
71 According to Wilson Fox, the density of the adhesions and
false membranes is determined within the first fortnight of the
effusion.
The question arises, How long shall we wait for absorption? Test first,
by exploratory puncture, the nature of the fluid: if it is fibro-serous
day after day, try by the cyrtometer the size of chest and by
percussion the exact amount of flatness. If there is no evidence of any
decline of the effusion in two weeks, slowly withdraw some of the
fluid. This will start the absorbents into activity, for the natural
absorbing power of the pleura is diminished when it has been unduly
stretched for some time. The layer of lymphatics subjacent to the
pleura and communicating by stomata with the pulmonary lymphatics,
together with the other absorbent vessels, appear to be unable to
remove the fluid. We maintain that the pressure on the orifices of the
lymphatics is often too great for absorption to take place, and that by
removing the pressure we can start the absorbents into activity.
Aspiration under these circumstances shortens the duration by several
weeks and hastens convalescence. J. W. Hunt72 advises that we should
wait two or three weeks before operating. Loomis73 says if the fluid
remains stationary for one week, or is increasing when the cavity is
half filled, we must operate. Barnes74 would only wait a few days if
the chest is half full, to see if absorption will begin to remove it.
When the chest is two-thirds full, he advises immediate surgical
interference. Oxley75 advises a delay of three or four weeks before
operating. Anstie's76 rule is to postpone operating for one month. T.
Clifford Allbutt's77 general rule is, if an effusion rises above the
angle of the scapula, and abides in that quantity or increases for two
or three weeks in spite of adequate treatment, it must be drawn off,
whether the patient be embarrassed by it or not. Bowditch78 says: "If
the effusion does not subside under the medical treatment, and the
symptoms have not lessened after two or at the utmost four weeks, I
have, after long experience, been led to the following general rules
for my own guidance: 1st. I never allow any time to elapse before
performing thoracentesis after a decided and prominent dyspnoea
appears, or if a sudden and very threatening orthopnoea occur, or if I
find the chest has become full or more than half full of fluid in a
perfectly latent manner
during a month of illness. 2d. After
there is dulness to the angle of the scapula, with the other rational
and physical signs of pleuritic effusions, I tap within four weeks,
even if the patient seems quite comfortable, if the line of dulness
does not get lower and seem to subside under the treatment. I think
fatal mistakes are made by delaying too long before tapping." The
author prefers ordinarily to wait for the subsidence of the fever in
acute cases, unless the effusion is in dangerous quantity. The
practitioner must continually use the thermometer as well as observe
physical phenomena and general symptoms. Cyrtometric tracings give very
valuable indications as to the activity or non-activity of the
absorbent vessels. After the fever subsides the fluid may be regarded
as a foreign body doing harm to the two principal organic functions
upon which the nutrition of the animal frame is dependent—respiration
and circulation. It is from this standpoint that Dieulafoy79 advises,
if absorption is slow or difficult after two or three days, that the
fluid should be aspirated. The greatest success has been obtained in
cases where the fluid has been present but a short time. The number of
fatal cases is increased by delay of operation. Toussaint's cases show this:
| 4 |
deaths in |
176 |
cases |
operated |
upon |
between |
1st |
and |
20th |
day. |
| 6 |
" |
80 |
" |
" |
" |
" |
20th |
and |
60th |
" |
| 1 |
" |
7 |
" |
" |
" |
" |
60th |
and |
120th |
" |
In the quiet kind of pleurisy, formerly designated the subacute or
latent, thoracentesis is especially applicable. Ordinarily, when the
practitioner is consulted, there is considerable fluid, without any
febrile movement. Here we are in duty bound to assist nature. Iron in
the form of the tincture of the chloride and the syrup of the iodide
are our best remedies. We cannot give the patients the tonic influence
of outdoor air with exercise, because there is danger in their moving
about; but they should have an abundant supply of nourishing food, with
light wines. Absorption is very inactive and sluggish. Even with
moderate effusion to the extent of one-third of the pleural cavity, we
cannot let the fluid remain too long. Pidoux designated this form of
pleurisy as the thoracentesis variety.
72 Loc. cit.
73 Dis. Resp. Org., etc., 1875.
74 Loc. cit.
75 N.Y. Med. Ex., Sept., 1882.
76 Syst. Med.
77 Quain's Dict. Med.
78 Unpublished MSS.
79 La Thoracent. par Asp. dans les Pleur. Aigues, 1878.
Conclusions.—1st. The author wishes to be distinctly understood as not
advocating aspiration simply because there is an effusion, as a mere
matter of routine, for its indiscriminate employment is undoubtedly
attended with risk. He does claim that its performance is imperatively
called for when the pleural cavity is full or nearly so; when there is
much displacement of the heart or other viscera; when the patient is
suffering from serious dyspnoea and danger of syncope, and when there
are complications of disease of any kind of the other side or of the
heart; finally, when there is double pleurisy. Bowditch states that he
has seen thoracentesis give great relief in effusions following
Bright's disease and cardiac diseases.
2d. He thinks that in acute cases, after the subsidence of the fever,
if the pleura is one-third full of fibro-serous fluid, Nature will
probably do her work of removal promptly. If she shows no sign of doing
so, we should come to her assistance in about ten days or two weeks,
and draw off a portion of the fluid—enough to relieve pressure and to
encourage the absorption of what is left in the sac.
3d. In the subacute or chronic fibro-serous effusions it is not well to
wait over three weeks before operating. As he shall show in the study
of the dangers and objections, he considers the operation a perfectly
safe one if the simple rules now generally observed by operators are
faithfully carried out.
In studying the advisability of operating where there are not urgent
indications we must ever bear in mind that while it takes a large
quantity of
fluid to compress the lung, the retracted lung may,
by neo-membranes, be kept to its diminished volume. As long as the lung
is able to lift up the fluid and the diaphragm it is in no danger of
atelectasis. It is in a state of physiological rest. In a subject of
bad constitution interstitial changes may indicate an earlier
operation, but, if an effusion exists on the side on which there is
already lung disease of a phthisical nature, we should be loath to
interfere; for "experience has shown that an effusion checks, and
sometimes arrests, the tubercular process" (Powell).
Contraindications.—These are principally in connection with the
general condition of the patient. If it is such that there is no hope
of his rallying, if he is very old, or if he has intervening croupal
pneumonia, the operation is not justifiable. If the quantity of fluid
is not large and does not interfere with organic functions, we can wait
for some time.
Mode of Operating.—The old trocar method of operation is now
abandoned. It was not always an easy one, was painful, and there was
more or less danger of cutting the intercostal artery, of introducing
air, and of establishing, by the size of the puncture, a fistulous
orifice. If, perchance, the lung was perforated by the trocar,
pneumothorax was established. In some cases of sacculated and limited
effusions, and in chronic cases where the membranes were thick, it was
not effectual, and if the fluid was not reached, the operator hesitated
to introduce the trocar elsewhere. When the fluid flowed through the
trocar, it came frequently in jets with painful coughs. The above
operation was quite a formidable one. Now thoracentesis is always
performed with very fine perforated needles attached to aspirators of
some modern pattern, and guarded by Fitch's dome-trocar or Castiaux's
protected point. We employ Dieulafoy's Potain's bottle-aspirator,
Castiaux's of Paris, or Raumussen's of Copenhagen. Flint recommends the
use of Davison's syringe. We fear it would be found too rough an
instrument for so delicate an operation. The points of attachment of
the bulb with the tubing are not sufficiently air-tight. The valves are
very imperfect, and easily get out of order. In our efforts to pump out
the fluid we might throw air in, and with it particles of organic matter.
The operator has his choice among no less than thirty-odd instruments
similar to Dieulafoy's. They all work upon the same principle—the
close operation, the withdrawal of the fluid by aspiration. The needle
or trocar must be capillary: the smallest that is effective is the
best—say a half millimeter in diameter—in order to make the orifice
as minute as possible.
If we prefer the syphon, we must use a larger canula than we employ for
aspiration—one of four millimeters in diameter. It should have two
outlets—one straight, for the trocar, and one at an angle, for the
attachment of the tubing. It should also be guarded by an air-tight
collar. Into the syphon tubing a T-tube may be inserted for the purpose
of attaching a side tube to be connected with a mercurial manometer, by
means of which the exact intra-thoracic pressure may be observed during
the operation. The syphon tube should be long enough to provide a fall
of one, two, or three feet, as may be necessary. A fall of twelve to
eighteen inches is usually enough, as we wish to remove the fluid
slowly. We can easily increase the force by lengthening the tube. If
the canula should become obstructed, lowering the basin suddenly will
probably remove the piece of lymph. The trocar can be pushed again
through the canula if necessary. In case the aspirator should be
needed, the end should have a metallic joint affixed to it. In all the
instruments used, absolute cleanliness should be observed. The tubing
previous to operation should be filled with a solution of carbolic acid (1:40).
In cases of rapid effusion, especially during the febrile stage and
when the intra-thoracic pressure of fluid is great, some prefer using
the feeblest form of aspiration. Southey's capillary trocar, with
drainage-tubes attached, is used as a syphon for this purpose. The
fluid is drained off
through a narrow india-rubber tubing which
is placed under water to prevent air being drawn into it. Ordinarily,
the use of the fine aspirating-needle without much force, and slowly
drawing off the fluid, answers the same purpose. The fear some have
expressed, of the danger of injuring the lung by the force of the
rarefied space, is more theoretical than real. Even with a canula of
the size that Southey employs there is some danger of leaving a
fistulous orifice, for it has to be kept in for hours. If the smallest
tube is used, from which the fluid simply comes in drops, the operation
consumes five or even ten hours. Southey speaks of cases where the flow
was kept up for twenty-four hours. Unless aspiration is resorted to,
flocculi may easily stop up the canula, and then we are compelled to
reintroduce the trocar, and afterward to reattach the tubing. Oxley,
who thinks that the best results are obtained by the use of these
tubes, acknowledges that so much time was consumed that he inserts four
canulas, drawing off 44 fluidounces of fluid in one hour and ten
minutes, thus defeating the object of using this method, which was to
draw off the fluid very slowly, so as to enable the lung to expand
gradually and healthfully.
There are cases where, to withdraw the fluid, more suction force than
is usually employed with the syphon has to be used in order to
antagonize the negative force exercised by the traction of the lung and
the passive tension of the diaphragm. The author recently had a case
where, notwithstanding the presence within the right pleural sac of a
quantity of fluid large enough to obliterate the Skodaic resonance
under the clavicle, not a drop could be drawn out by a syphon attached
to a canula of 2 mm. in diameter. Having no additional tubing to
increase the force of the syphon at hand, he used Dieulafoy's rack
aspirator, ½ mm. in diameter, and drew off a quart of fluid—enough to
relieve the symptoms of oppression. Stone reports a case of the kind
where, although there were two quarts of fluid in the pleural sac, no
fluid could be drawn out with a syphon exerting a force of 1½ pounds to
the square inch, or one-tenth of an atmosphere. In the same case there
was actually, in inspiration, a negative pressure exercised by the lung
of two inches of water. Stone mentions another case where a boy fifteen
years of age died from the quantity of fluid, which would not flow out
when tapped. If he had had an instrument by which he could have used
aspiration he would have saved the life.
The value of this syphon method has within a few years grown much in
favor. It is simple and inexpensive. It allows the fluid to be drawn
out with a uniform and feeble aspiratory force. The flow is very slow,
which gives the lung time to expand gently, and the displaced organs to
return gradually to their normal position. With the manometer attached
we can judge accurately as to the intra-thoracic pressure. The size of
the canula has to be larger than when we employ the aspirator—4
mm.—whereas with the latter we use ½ mm. or 1 mm. in diameter. If by
any accident the lung should be perforated, the larger orifice would
not be as harmless and insignificant as the smaller one. It must be
borne in mind, especially in cases of long standing, that the
neo-membranes are very vascular, and that with a 4 mm. perforator we
may rupture the blood-vessels and complicate matters by the escape of
blood into the pleural cavity. It is claimed that when the canula and
syphon tubes have been introduced the patient can be left in charge of
the nurse. This, the author thinks, should never be done, for nurses
are rarely competent to judge whether a sufficient amount has been
withdrawn, nor are they fit to assume the responsibility of acting in
cases where promptness of treatment may be of the utmost importance.
The operator or a competent substitute must remain until the operation
is over. The withdrawal of fluid must, moreover, be slow, for slowness
contributes in a great degree to lessen the dangers. Fraentzel
recommends testing the force of the
aspirator in the palm of the
hand. Garland80 employs needles which are 1–2 mm. in diameter and
remove only 50 to 100 grammes per minute. The thoracic pressure must be
relieved by the withdrawal of only enough fluid to effect that purpose.
It has been objected that the negative force of the aspirator is
uncertain. It is a well-founded objection, yet we can employ with it a
feeble force by exhausting only a portion of the air from the cylinder
or bottle, and thus remove the fluid cautiously and very deliberately.
It is admitted that if there is no intra-thoracic pressure the fluid
will not flow out unless we introduce air or negative force. We claim
that the syphon and the aspirator with capillary needles, employed with
the precautions dictated by modern experience, are both safe and
effective. Ordinarily, we prefer the bottle aspirator of Potain, or
Dieulafoy's instrument with the manometer attachment.
80 "Dis. of Pleura," in Ziemmsen's Appendix.
Modern aspirators, if in perfectly good order, completely prevent the
possibility of septic contamination by admission of air. Unclean
needles and canulæ can—and we fear formerly often did—convert
sero-fibrinous into purulent pleurisies. A case came under Powell's
observation in which carelessness in this respect apparently led to
decomposition of the fluid, suppurative pleurisy, and ultimately to the
death of the patient. Before operating we ought always to test the
instrument, and see that it works well by passing carbolized water
through it. The points should be put in the flame of a spirit-lamp, and
then dipped in carbolized water and glycerin—not in oil, which may be
rancid. The hands and clothes of the operator should not be overlooked
in this regard. The atmosphere of the room should previously be
completely cleansed by ventilation, and afterward purified by
atomization of disinfectants. We must not, in a word, incur the
slightest risk of converting a simple inflammatory effusion of
fibro-serous fluid, a mild disease, into a suppurative inflammation, a
very troublesome, dangerous one.
A needle of not larger diameter than 1 millimeter (No. 2) should be
connected with the end of the tubing. Next turn the stopcocks which
shut off the barrel from the tubing on both sides, producing a vacuum
in the receiver. The patient should then be placed in the recumbent
position in bed, with his head and chest raised. We prefer this
position, as the easiest for the patient at the time of operation and
less apt to produce syncope or faintness. He can, without being moved,
lie down in the horizontal position, which he should maintain for at
least two hours. Bowditch has, without any accident, had his patients
to sit during operation sidewise in a chair, with one arm resting upon
a pillow placed upon the top of the back. The operation is accompanied
with so little pain that it is not necessary to use either general or
local anæsthesia. Some surgeons advise before operating the
administration of a small dose of morphia hypodermically, or a
stimulating drink of whiskey. We are not in the habit of using either.
We have generally allowed patients to take a good meal of
easily-digested food (milk if they consent) about two hours previous to
the operation. Whiskey and ammonia we have ready in case of need. If we
find it necessary to use a 4-mm. canula for syphon, it may be best to
spare the pain of its introduction by local anæsthesia by ether, or by
rhigoline in Richardson's spray, or by applying a piece of ice
surrounded by salt, as suggested by Powell.
The point of puncture should vary according to the quantity of fluid.
If the fluid is excessive, we can operate as high up as the fifth
intercostal space on the right side and the seventh on the left. We can
choose a lower intercostal, but as it is not proposed to draw off all
the fluid, the higher operation is preferable. If the chest is
two-thirds full, we can take the seventh or sixth intercostal space on
the right side and eighth on the left. If only one-third of the cavity
is occupied by fluid, we can go as low as the eighth intercostal
on right and left sides, on a level with the angle of the scapula in
the axillary line. If the quantity of liquid is so great as to force
the abdominal viscera, especially the liver and the spleen, below their
normal position, we may be safe in puncturing below the seventh
intercostal space. But if such is not the case, the diaphragm may
easily be touched on a level with even the seventh intercostal space.
Aran plunged a trocar into the liver when operating through the seventh
intercostal space. Ch. Bernard impinged upon the peritoneum at the same
point. Woillez and Paul Barbille recommend the fifth intercostal space.
Cruveilhier advises the third or fourth as being the point of the
spontaneous openings. The author usually inserts the needle in the
sixth intercostal space in the mid-axillary line: it is out of reach of
the diaphragm and is accessible when the patient lies in the position
in which he prefers placing him. The space is sufficiently wide and the
parietes thin. Before operating the point must be examined carefully by
percussion, auscultation, and palpation, so as to be accurate in the
diagnosis that there is fluid at that point, and that nothing can be
injured—lung, heart, or diaphragm.
Before inserting the needle the skin should be wiped over with an
antiseptic solution. The skin being drawn up, the nail of the left
index finger serving as a director, the point, having been first made
aseptic, is introduced along the upper margin of the lower rib, taking
care not to injure the periosteum—not by a boring motion, but by a
sharp push, giving it a downward direction instead of a perfectly
straight one, so as to avoid striking the lung. When the fluid is
reached the stopcock is turned, so as to convert the needle into an
aspirator. The index tells us whether we have struck the fluid, and its
nature is shown. In chronic cases, where the bands are thick and
partitions are firm, we may not find the fluid the first time. In such
cases the needle is withdrawn and another point selected. The author
had a case where he made no less than eight punctures before getting
the fluid. At the last insertion of the needle he found it, and drew
off a large quantity. The patient feels relieved in a very short time.
As the fluid flows out the aspirating force should be only sufficient
to draw it out slowly and gently. It is well to stop for a few minutes
after aspirating about 4 fluidounces to watch the effects. The fluid
running in a very small stream, we give the lung time to accommodate
itself to its altered condition. The lung by this process is led,
rather than forced, to resume its normal position. It is a difficult
matter to fix the quantity that ought to be drawn off at one time. This
must vary according to the circumstances of each case. Our rule has
been to draw off more when the pleurisy is acute than when it is
chronic. The long continuance of the fluid in the cavity has so
impaired the lung's capability of expansion by the adhesive bands or
compresses that the sudden withdrawal of a large quantity is attended
with risk. If the patient bears the operation well, we may remove much
more than if the contrary is the case. The amount withdrawn at the
first operation should vary from 8 fluidounces to 16 fluidounces in a
child, and 12 fluidounces to 24 fluidounces for an adult. We must bear
in mind, as to the quantity to be removed, that ordinarily there is
more or less danger of producing fresh engorgement of the capillaries
and hyperæmia of the lung in removing a large quantity; and, moreover,
it is unnecessary. We wish to remove the intra-thoracic pressure upon
the lung and to promote the absorption of the fluid. The manometer will
tell us accurately whether it is necessary to take out one, two, or
three pints. If nature does not in due time remove what is left, the
operation can be again resorted to. Slowness in the withdrawal of the
fluid, as well as the small quantity drawn, lessens the probability of
any unpleasant effects. Bowditch says: "I always draw with great
deliberation. I pull so lightly upon the handle of the piston that it
seems as if the fluid itself were pressing out from the chest and
pushed the piston upward, my hand simply following that impulse. The
instant that the patient becomes
restless, especially if he have
any constriction or sharp pain in the chest, I withdraw the tube, even
if a large quantity of fluid remains. If I do this, I find the patient
is soon relieved, and in most cases nature appears stimulated even by
the withdrawal of a very small part of the effusion. The absorbents
begin to act well, and the fluid that is left is speedily removed."
One point is of the utmost importance: the needle should be instantly
withdrawn at the onset of dyspnoea, constriction, much cough, or any
tendency to syncope. These symptoms are warnings we should never
neglect. This is the time to administer stimulants, and ordinarily the
patient soon recovers from these effects. We must not, especially in
cases of long duration, expect to find much expansion of the lung until
next day. The greatest success has followed cases treated by early
operation and partial removals, repeated, if necessary, every day or
two until absorption is commenced.
The needle should be taken out suddenly, the operator having previously
turned the stopcock, and the skin allowed at once to fall over the
orifice, which is so small that no air can enter. It is indeed
obliterated at once. It may be well, however, to put some collodion
over it, with a small compress. The patient ought not to be permitted
to move for twenty-four hours after the operation. He should lie
quietly in bed and partake of simple nourishment. The removal of fluid
causes the return of friction sounds and of pleuritic pain. Nature
slowly does her work of absorbing the fibrinous bands. The
breath-sounds in some cases are not heard for weeks, or even months,
after the operation. Complete recovery being slow, and the shock to the
organism very serious, the patient should thoroughly re-establish his
health and strength before reassuming his active duties. A protracted
rest in an invigorating climate or a sea-voyage should be advised. If
the lung is slow to expand, the patient should frequently practise
long, deep inspirations.
Dangers of and Objections to the Operation.—Thoracentesis as a means
of relieving suffering humanity has from time to time been praised and
proscribed, even in this century. Boyer operated several times, and
never saved a single case. Dupuytren had only 2 successful cases in 50.
He said he preferred that his patients should die by the hand of God
rather than by the hand of man. Sir Astley Cooper had only 1 successful
case, Gendrin not 1 out of 20 cases. Davis saved two-thirds of his
cases. The eminent W. W. Gerhard of Philadelphia looked upon the
operation as nearly always attended by fatal results. What a contrast
to modern views and clinical results! Since Bowditch and Trousseau
popularized the operation, and Dieulafoy improved the aspirating
instruments, there is now no difference of opinion as to the imperative
necessity of operating in cases where there is, from the quantity of
fluid, imminent danger to life. Up to Nov., 1882, Bowditch81 had
operated 386 times in 245 cases, without a single fatal result, and
with only 1 case in which alarming symptoms supervened. Dieulafoy's82
cases in 1878 amounted to 150, without the shadow of an accident. My
colleague, S. C. Chew, has never met with any unpleasant result from
his operations. The author has had 84 cases, with 138 operations,
without any unpleasant result beyond temporary cough and slight
dyspnoea. Fraentzel83 had 85 different cases, with 164 operations. A.
L. Mason84 performed 122 operations in 70 cases, with no unfavorable
result which could be attributed to the operation in any instance, but
usually with great and permanent relief. In 42 of his cases 1 operation
was all that was necessary. So common is the operation that cases are
not reported unless there is something to attract attention to them. As
illustrative of the great interest taken in the operation see the
number of writers on the subject and the numberless articles in medical
journals, and the modifications of instruments of all kinds connected
with aspiration
and drainage. Such being the case, we ought not
to be surprised that some operators may have used the aspirator-needle
when they ought not to have done so—that some should have neglected
the simple rules now insisted upon as the result of experience.
81 Unpublished MSS.
82 Tho. Pleu. Aig., 1878.
83 Ziemssen's Cyc., vol. iv.
84 Loc. cit.
Although thoracentesis by aspiration is always a harmless operation in
itself, there are dangers and accidents which may follow. They may be
slight, serious, and sometimes even fatal. The number of deaths which
have been the result of the operation, however, is small compared to
that of persons dying from the effusion whose lives might have been
saved by the withdrawal of fluid. Thoracentesis was frequently made use
of without accident, and was considered a perfectly safe operation
until Terrillon85 called attention to an accident which occurred
sometimes after operating, a complication which Pinault86 had
mentioned in 1853—the albuminoid expectoration. Terrillon reported 2
cases of sudden and rapid death with that symptom. Several similar
cases, resulting in death, had been previously reported. Dieulafoy has
collected from different sources reports of 6 deaths with albuminous
expectoration, caused by acute oedema of the lungs brought on
apparently by the operation of thoracentesis in twenty-four to
thirty-six hours. In one of these cases (Gérard's) death occurred in
ten minutes; in another (Gombault's) in fifteen minutes; in another
(Bouveret's) in two hours; in Behier's in four hours. Terrillon's
cases, where there was this frothy, albuminoid, and sometimes bloody
expectoration, numbered 16, of which 6 were fatal. The patient is
attacked with cough and oppression, with the characteristic
expectoration. Auscultation shows the fine subcrepitant râles of oedema
of the lungs, mingled with tubular quality and ægophony. Gradually, in
favorable cases, the cough subsides, respiration is re-established, and
in one hour the danger has passed. In fatal cases the cough becomes
irregular and jerky, the agony increases, and the patient throws up the
yellowish and albuminous expectoration in quantity varying from 50
grammes to (in one case reported by Moutard-Martin) 1 liter. The
intensity of the dyspnoea and its duration vary very much—from twelve
to twenty-four hours.
85 Thèse de Paris, 1872.
86 Ibid., 1853.
There has been considerable discussion among different authors as to
what produce this serious condition. The view sustained by Hérard87
is the one generally admitted to be correct—viz. that it is from rapid
congestion and acute oedema of the lung, and not from the passage of
serous effusions of the pleura through the bronchi. Foucart88 relates
a similar case of albuminous expectoration occurring in heart disease.
This condition could not be produced by perforation of the lung, for
the pre-existing vacuum renders the aspirator-needles the safest to
introduce, because if there is fluid present it at once flows out and
warns the operator not to push the implement farther in. In no autopsy
has the orifice made by the needle been found, nor has it ever been
known to produce pneumothorax. The quantity of albuminous sputa is out
of all proportion to the orifice made. In several cases of reported
perforation these symptoms did not occur. After the lung has been a
long time compressed by an effusion, and when, in consequence of the
expulsion of the liquid, it retakes its normal proportions, there
occurs a rush of serum which is expelled by the bronchi. Hérard has
seen patients in whom he could not find more than traces of liquid
after the puncture, and who at the end of a half hour or an hour
expectorated 500 to 1000 grammes of fluid which did not come from the
pleura. That oedema of the lungs, or serous exudation from the
capillaries into the walls and on the free surface of the alveoli, is a
result of hyperæmia and pulmonary congestion is admitted by Robin,
Bernard, Niemeyer, Jaccoud, and others. We have first congestion of the
lung, then oedema resulting from it, ending in free albuminous
expectoration,
which comes not only sometimes from the diseased
side, but from the healthy side, owing to pressure against the
mediastinum and the other lung. This is an accident the possibility of
which should be always before us in operating. No precaution ought to
be neglected which will ward it off. It is instructive to analyze
Terrillon's cases as to the cause of the oedema. As he considers that
the aspirator, by draining out the lung, is likely to produce this
unfortunate result, it is satisfactory to find that of the 16 cases
where this unpleasant symptom was found, 12 were where the old trocar
(Reybard's) was used without aspiration, and 4 where aspirators were
used. Of the 6 fatal cases collected by Terrillon, 3 were with the
trocar and 3 with the aspirator. Five out of the 6 fatal cases are
found to have been not simple pleurisies, but pleurisies with
complications, such as heart disease, bronchitis, tuberculosis,
numerous adhesions, double pleurisy. The same may be said of the benign
cases. In addition to these complications, large quantities of fluid
had been drawn out at one time. Dieulafoy challenges his confrères to
produce an instance of death from this cause when the fluid removed did
not exceed 1200 grammes. His rule now is never to withdraw more than
1000 grammes of liquid at one time, and in large effusions to empty the
sac by several operations. The older and more complicated the effusion,
the more rigorous should be the rule, because there is great danger in
thoracentesis when the fluid has existed long enough to have compressed
the lung to a serious extent by bands. All careful operators now follow
this rule. It is dangerous, and withal unnecessary, to draw off large
quantities at a time. The gradual removal of fluid diminishes the risk
of syncope where a sudden withdrawal may be serious in its effects. The
effect is to suddenly deprive the lung of pressure which has for weeks
perhaps made it anæmic. The blood rushes into the empty vessels, the
air into the alveoli, and violent congestion and consequent oedema
result. If, on the contrary, we draw out moderate quantities at
different times with the capillary needle, which is so small that its
introduction is harmless, the lung resumes progressively the functions
it has lost, and the circulation gradually enters. Thus there is no
risk of congestion.
87 Acad. Méd., 30 Juillet, 1872.
88 Thèse de Paris, 1875.
In examining the fatal cases reported by different authors, Foucart,
Dieulafoy, Mercier, Lerebenthel, and Gagnet, we find other modes of
death in addition to those by oedema of the lung, such as asphyxia and
pulmonary emboli, and, as connected with the heart, syncope and cardiac
thrombosis. In most of the cases these accidents resulted indirectly
from the operation in twenty-four hours or a longer time. In a case
reported by Guyot it occurred three days afterward. Congestion by
itself may cause sudden and rapid death by determining asphyxia.
There are other lung causes which produce sudden death following
thoracentesis, such as atelectasis, consecutive to effusion; secondary
pneumonia, caseous or not; pulmonary tubercles. Besnier reports a case
of gangrene of the lung following paracentesis. Of the 8 cases
collected by Dieulafoy which may be put into this category, we find
death from pericarditis, cardiac clot, and from thrombosis of the
pulmonary artery. Death from the heart may be due to old lesions, to
syncope, or to the presence of clots in the heart or small circulation.
Stokes has given fatty degeneration of the heart as a cause of death in
simple pleurisy without operation. Syncope, with death after operation,
is caused by the sudden return of the heart to its normal position. The
heart being pushed out of position, the larger blood-vessels are
distorted, and the course of the circulation is severely interfered
with. A very slight cause will arrest the circulation. By aspiration
the mechanical cause is removed, but a small embolus, may, by the
increased force of blood, be carried into the pulmonary circulation.
Death by emboli in the capillaries of the lungs is very similar to
death
from clots in the right side of the heart and at the origin
of the pulmonary artery. These clots may be formed in the pulmonary
vessels, or may be transported in the small circulation to points more
or less distant. Potain in 1861, and Vallin in 1869, reported sudden
deaths from effusion in the pleural sac, causing embolism of the
cerebral artery. How far aspiration is responsible for accidents of
this kind it is difficult to decide. Were they caused by thoracentesis
or notwithstanding the operation? They are unquestionably the cause of
death without the operation in excessive effusions. The conditions
which produce these results ought to be well considered previous to
operation. We notice that in most of these cases large quantities of
fluid were withdrawn—2000 grammes (Legroux), 3 liters (Vallin), 3500
grammes (Guyot), 1500 grammes (Chaillon and Goquel). The withdrawal in
cases of long standing of such large quantities had, beyond a doubt,
considerable influence in producing the fatal result. Bowditch89
addressed letters to 60 physicians, living in 31 of the States and 2 in
Canada—representative men—asking if they had ever seen or heard of
fatal results following thoracentesis by aspiration. Of this number, 53
replied in the negative, and 7 in the affirmative. "Upon an analysis,
however," he states,89 "of the circumstances under which death
occurred in these last, I found nothing to shake my confidence in the
operation, provided it be performed with proper precautions during and
subsequent to the tapping. In no one of these cases had the operation
been the sole cause of the fatal result." "In 4 there was extra motion
on the part of the patient after operation, and in the other 3 the
disease had been allowed to continue without aid from a surgeon long
after the operation was needed. In 1 the operation was a forlorn hope.
One patient died on the table from anæsthetics." Bowditch adds: "These
cases should not lessen our confidence in the operation, but simply
teach us caution on three points—namely: do not delay too long; be
very careful to direct the patient not to move, if possible, for
twenty-four hours after operation; be cautious of using anæsthetics."
Bowditch, from 29 fatal cases collected from Otto Leichtenstein,90
from his own knowledge, and from European literature, tabulates the
causes of death in American and European practice: 7 of these cases
were caused by extra-exertion after operation; 3 from cyanosis and
coma; 4 from spray injections; only 1 from syncope; and 2 from
albuminoid sputa. He quotes the final remark of Leichtenstein: "Death
or any serious symptoms are so rare that they ought not to have the
least influence upon our estimate of this most benign and blessed
operation." Bowditch states that there were only 7 deaths in this
country (as far as he could ascertain), and 29, or four times as many,
in Europe, although the operation has been done much more frequently
here and for a much longer time. Does not this show that in this
country, in following Bowditch's precepts of great care and
deliberation, the operation has been more successful? He never ceased
in his lectures and writings to caution us to suspend the withdrawal of
fluid the moment the patient begins to suffer in breathing, even in the
slightest degree. Of course there may have been other cases occurring
in American practice of fatal results, of which no reports were made to Bowditch.
89 Unpublished MSS., 1882.
90 Deutsches Arch. für klin. Med., vol. xxv., 1880.
The author has carefully gone over Leichtenstein's collected cases, and
he finds a number of deaths mentioned by other European authors which
are not included in his list. (The reader is referred to the theses of
Terrillon,91 Foucart,92 Foster,93 Dieulafoy,94 Mercier,95
Pinault,96 Wilson Fox,97 and others.) Terrillon alone reports 6
deaths with symptoms of oedema of the lungs following thoracentesis.
Leichtenstein does not mention any deaths from embolism,
such as
are quoted by Goquel, Chaillon, and Woillez. In his collection he gives
only 1 death by syncope, whereas Dieulafoy comments upon 4 as found
recorded by Trousseau and other French authorities. Toussaint's98
statistical tables of 300 cases, collected from other sources, give 14
deaths. Wilson Fox collected between 30 and 40 deaths connected with
thoracentesis. Besnier stated in 1876 that the mortality from pleurisy
in the French hospitals had greatly increased since the practice of
thoracentesis had been largely followed. It is difficult to account for
this in the face of the statements made by so many of its innocuousness
when properly guarded: it may be explained by the fact that suppurative
pleurisies are often confounded with those of a fibro-serous nature and
treated by simple aspiration. Many fatal cases of empyema are
complicated with phthisis; formerly these were added to the mortality
for phthisis; where paracentesis was performed upon them they were
added to the pleurisy column. Bearing in mind that chronic pleurisies,
serous and purulent, are frequently consecutive to diabetes, Bright's
disease, chronic alcoholism, cirrhosis of the liver, and other organic
diseases, patients die of the primary lesions, though they have been
relieved of the secondary ones. These statistics may record the deaths
as resulting from pleurisy, for which there was operative interference,
instead of from the organic diseases.
91 Loc. cit.
92 Loc. cit.
93 Clin. Obs.
94 Loc. cit.
95 Thèse de Paris, 1876.
96 Ibid., 1855.
97 Brit. Med. Journ., Dec., 1877.
98 Thèse de Paris, 1878.
Formerly, when trocars and canulas of considerable diameters were used,
only extreme necessity from peril to life made surgeons consent to
operate. We claim that by capillary needles, gentle force, and
protected points all the old objections are obviated. As Anstie says,
there is no opposition to the modern operation by men who have fairly
tried Bowditch's practice. Only theorists who are afraid of its
imaginary results and men too timid to act hesitate to make use of it.
We have discussed elsewhere (Purulent Pleurisy) the danger of admitting
air into the pleural cavity, but we insist that in the close method,
with capillary needles, there is no danger whatever of air entering.
The puncture is so very small that it closes at once by the elasticity
of the structure of the chest, just as the knuckle of the intestine in
hernia closes after the needle has drawn gases and fluid out of it.
Another objection urged against puncture of the pleura in such cases is
the possibility of perforating the lung by fine needles, thus letting
air into the cavity and causing cough.99 Marotte read a memoir on the
subject to the Academy in 1872. He reported 4 cases, in all of which
there were only temporary effects, no serious ones. Dieulafoy100
says: "I have been witness to the puncturing of the lung several times,
and I have never seen any accident supervene under any circumstances. I
have thoroughly convinced myself that punctures performed with a No. 1
needle, diameter half a millimeter, are harmless, and experiments on
animals have given me the same results." He even suggests aspirating a
few grammes of blood from a congested lung in the first stage of
pneumonia, and thus practising local bloodletting. The author has 3
times pricked the lung in aspirating—twice with a No. 2 needle,
diameter 1 millimeter, where a few drops of blood were drawn into the
instrument, and they did not even produce a cough or the slightest
inconvenience. The third time was with a No. 4 needle (2 millimeters).
From this puncture some air escaped into the pleura, and for a few days
there was evidence of pneumothorax. It then disappeared entirely, the
air being absorbed. The case was a circumscribed empyema, which
entirely recovered.
99 Allbutt, Quain's Dict. Med., 1883.
100 Treatise on Pneumatic Aspiration, Eng. trans., p.
256.
It will be noted that throughout the discussion of this important
subject liberal use has been made of a valuable communication specially
prepared by Henry I. Bowditch for this purpose, and embodying the
mature results of his study and experience of thoracentesis. It seems
not only to establish conclusively the claim that to him, in
conjunction with Wyman, is due the
great credit of introducing
the principle of aspiration, but also to how great an extent it was
through his persevering and skilful advocacy and performance of the
operation that it became so firmly established in America upon a true
scientific basis.
DEFINITION.—Purulent pleurisy is that disease in which the pleura
secretes pus instead of fibro-serous fluid, as in simple pleurisy.
SYNONYMS.—Pyothorax; Empyema; Suppurative pleurisy.
HISTORY.—The term empyema was applied originally to any internal
collection of pus—[Greek: en] and [Greek: pyon]. It is now restricted
to pus in the pleural sac. The ancients, from the time of Hippocrates,
diagnosed and treated empyema by thoracentesis and pleurotomy. They
were familiar with the fact that it would sometimes discharge through
the bronchi and make an orifice through the walls of the chest, and
discharge outwardly. Their views of its pathology and its connection
with other forms of pleurisy were necessarily crude and indefinite. Of
late years, owing to the aids given by exploratory punctures, purulent
pleurisies have been thoroughly investigated. Townsend101 divided the
disease into four varieties, all of which are from degenerations of
acute serous pleurisies, from increase of intensity of the inflammatory
phenomena, or from modification of the secretion of the serous
membrane. More modern researches have shown that frequently such is the
case, and that purulent pleurisies often succeed serous pleurisies. The
liquid when first thrown out is serous and limpid in character, and
afterward becomes cloudy, opaline, then more and more opaque and
purulent, owing to the pus being freely secreted and mixing with the
fibro-serous effusion. In a certain number of cases, however, the
effused liquid has from the first the appearance and anatomical
composition of purulent fluid—d'emblée purulente. This has been shown
by autopsies in cases of women who died in childbed from suppurating
pleurisies, and in persons attacked with pyogenic fever, not simply
from deposits of pus, but where an inflammatory period, of longer or
shorter duration, preceded the deposit.102 Dieulafoy103 showed that
in all effused liquids in the pleural sac there were present red
globules and leucocytes.104 Laboulbène105 has established the fact
that the exuded fluid in all pleurisies, even those apparently serous,
contained, from the time of their formation, purulent globules. All
cases, then, are historically purulent; but clinically serous and
purulent pleurisies are distinct in their progress, termination, and
treatment. Purulence is not always the sign of chronicity of pleural
inflammation. It may, and does, show itself in many instances from the
very commencement of the attack. Wilson Fox106 shows there is but
little natural tendency in serous effusions to undergo purulent
transformations. He thinks in the vast majority of cases suppurative
pleurisies are so at early periods of disease. He states the proportion
of primary suppurative pleurisies as from 14 to 20 per cent. It is when
the number of leucocytes, from the intensity of the inflammation or
modification of the process, discolors the fluid and gives to it its
distinctive properties, that we use the name of purulent pleurisy.
Verliac107 states that all chronic cases in infants become purulent.
101 Article "Empyema," Cyc. Prac. Med., vol. ii.
102 Pleurisie purulente, (Moutard-Martin), Paris, 1872.
103 "De l'Examen histologique des Liquides, etc.," Soc.
Méd. des Hôp., 1878.
105 Traité d'Anatomie path., Paris, 1872.
106 Brit. Med. Journ., Dec., 1877.
107 Thèse de Paris, 1865.
ETIOLOGY.—The causes of purulent pleurisies are divided into local or
traumatic, which are well ascertained and defined; and the general, the
action of which is uncertain. Among the first are wounds of the
chest, fractures or caries of the ribs, phlegmonous abscesses of the
walls of the chest, effusions of blood, pathological liquids, pulmonary
gangrene, rupture of tubercular cavities, and other injuries from
adjacent organs, especially of those where pus is discharged into the
cavity, for the presence of pus engenders pus. Thoracentesis has been
accused of converting serous into purulent pleurisies by the admission
of air into the pleural cavity. If the atmosphere admitted is
contaminated by germs, we must acknowledge that such a result is
possible. By the older methods, previous to the adoption of Reybard's
protected canula, such a result may have been produced. We can thus, in
a measure at least, account for the great mortality in cases operated
upon. But since the adoption of the protected orifices of the small
aspirating trocar of Wyman and the capillary perforating needles of
Dieulafoy, we question whether, with such an insignificant puncture and
the complete exclusion of air, thoracentesis can be justly accused of
producing such serious mischief. Trousseau108 earnestly denied such a
deleterious effect of the operation in his day. We have now not only
the results obtained by Demarquay, Leconte, and Manotte of injecting
air into the pleural cavities of inferior animals, but we have the bold
experiments of Matice, who, convinced that air could not have any bad
influence, actually had the audacity to perform the operation a number
of times, allowing the air to enter freely through the canula. From
numerous observations there resulted the fact, unsuspected by many,
that air, penetrating freely to replace the liquid extracted, never
gave rise to purulence in pleurisy; that, owing to its rapid
absorption, it did not in the least interfere with the expansion of the
lungs; in short, that it produced no accident whatever. While admitting
the force of Matice's conclusions, we think it preferable to avoid the
possibility of doing harm.
108 Loc. cit.
GENERAL CAUSES.—We have shown that secondary pleurisies frequently
occur in the course of convalescence from eruptive diseases, measles,
small-pox, and especially scarlet fever, and that they are purulent in
their nature. The puerperal condition predisposes to suppurative
inflammations of the serous membranes, and pleurisies in lying-in women
are almost always purulent. In rheumatism, gout, and delirium tremens,
and albuminuria as a rule, the pleuritic effusion is serous. It is
purulent in persons suffering from severe injuries and among men
exhausted by over-work or by alcoholic excesses, or protracted obscure
diseases, such as typhoid fever and pyæmia. Analyses of the cases in
which purulent transformation has occurred show that tubercles of the
lung have only a minor influence in its production—only 34 per cent.
of the whole number. Attimont's109 observations were founded upon 130
cases, 80 of which recovered; of the remaining 50 that died, he found
tubercle in only 9 cases. Sometimes malhygienic conditions and
insufficient alimentation may account for them. Men are more subject to
this disease than women in the proportion of 8 to 1,110 and young
children oftener suffer from purulent pleurisy than adults. It is not
easy to explain the transformation of serum into pus in pleuritic
effusions that have existed for some time where there have been no
grave symptoms. Imprudent exposure, affecting the general health, may
thus produce disastrous results. This occurs so frequently that
purulent pleurisies are generally called chronic pleurisies. There are
cases where neither local nor general conditions explain the
transformation of serous into purulent effusions in the chest.
109 Thèse de Paris, 1869.
110 E. Moutard-Martin.
PATHOLOGICAL ANATOMY.—This is shown by an examination of the effused
liquid, the different solid detritus that it contains, the false
membranes, the pleura, the lung, and the thoracic wall itself. The
liquid effused is purulent in character. It contains a greater or less
number of leucocytes,
some red globules, and voluminous granular
cells, besides crystals of the fatty acids and plates of cholesterin.
The pus is mixed with the serosity in varying quantities. The liquid
may be slightly opaline or greenish-yellow, and sometimes gray. It may
be thin or thick, with heavy flocculi, so as to pass with difficulty
through a canula. The liquid is, ordinarily, inodorous, but it may be
strong, and even fetid, where it has been in contact with air. In very
few cases of old standing can the pus be regarded as active, the
corpuscles being, as a rule, dead or having undergone fatty
degeneration. Active suppuration is also more readily set up in a
pleura which has already yielded pus.
Purulent effusions, independent of contact with air, may become in a
short time the seat of putrid transformations. False membranes undergo
alterations which produce fetid gases. The air, with its germs, its
humidity, and heat, the three grand factors in putrefaction, is thrown
in contact with substances of a putrescible composition. Marshall111
holds that sero-fibrinous effusions appear to have a greater tendency
to quick decomposition when air is admitted into the pleural sac than
the sero-purulent or purulent products. Pus, he considers, is more
stable and less inclined to rapid putrefaction than sero-albuminous
fluid. In quantity it varies from a very small number of grammes to
five or even six liters. By examining the fluid first drawn out we can
predict, by the number of leucocytes present, whether the pleurisy will
continue to be serous or will become purulent. If subjected to the
influence of ammonia, it will become thready, just as happens when pus
is suspended in water, if the fluid contains many of these
pus-elements. The purulent fluid may fill the whole or occupy but a
small part of the cavity, or again the interlobular spaces only may
contain the fluid, the cavity itself being empty. False membranes are
almost constantly present and adherent to the parietal or pulmonary
pleura; we find them also floating in the liquid. These false membranes
may be more or less voluminous. The flocculi, which may be as large as
an egg, undergo transformation when air is admitted, and become
horribly fetid. They may give rise to septicæmic symptoms. When we see
these enormous masses in the cavity, and are unable to get rid of them
by suction, we do not wonder that their presence should poison the
patient and the case become incurable. Pleurotomy is the only effective
mode of getting rid of these dangerous masses, with sometimes
gangrenous portions of pleural or lung-tissue. These false membranes
frequently form pouches and divisions for isolated quantities of fluid.
The false membranes are partly adherent and partly free, especially in
cases where there are pulmonary or thoracic fistula. These false
membranes differ in acute purulent pleurisies from those found in
pleurisies of long standing. They are but feebly adherent to the
pleura, and have a slight rose coloration. In old pleurisies the false
membranes are of greater density, sometimes from 6 to 8 mm. in
thickness. They are more adherent, and cannot be separated, and have a
grayish color. The physical state and position of the lung and
disposition of the adjoining structures are very similar to what they
are in serous effusions. In but few cases do the false membranes
envelop the whole of the lung. They pass over one part, and on to the
costal pleura. The pulmonary tissue is condensed, sometimes absolutely
impermeable to air, so that it will actually sink when dropped in
water, being in a state of atelectasis. In cases of shorter duration it
is found crepitant throughout its structure. Brouardet112 called
attention to the inflammation in the under-pleural cellular tissue, as
well as in the interlobular connective tissue, forming interstitial
pneumonia, which determines condensation of this tissue and its
retraction after the manner of cicatrices, and afterward its
inextensibility. These explain the retraction of the thoracic walls and
the narrowing of the chest.
111 Loc. cit.
112 "Interstitielle Pneumonie," Soc. Méd. des Hôp.
Bullétin, 1872.
The most serious complication of this disease is the
pleuro-bronchial fistula113 by which the fluid escapes through the
lung. The firm adhesions between the lungs and walls, forming enclosed
pockets, contribute in no small degree to the incurability of purulent
pleurisy. These pockets cannot be emptied thoroughly, nor can the
washings be made to penetrate them. The purulent secretion exercises a
destructive action over the tissues surrounding it, as well as upon the
viscera and walls of the chest: the soft parts become inflamed and
abscesses form; the intercostal muscles suffer atrophy and undergo
fatty degeneration, external openings occurring from ulceration. The
latter are found less frequently than pleuro-bronchial fistula. This
external perforation is habitually in front, in the upper intercostal
spaces, which, near the sternum, are very wide and not protected by
external intercostal muscles. The fifth intercostal is the most
frequent locality. There may be one or several openings. They may be
caused by the pus ulcerating through the parietal walls, or abscesses
may be produced in the walls and burst externally. Exceptionally, the
emptying of the liquid is by ulceration of the diaphragm into the
abdomen, causing fatal peritonitis. Some years since the author saw, in
consultation, a patient where the autopsy proved this condition. Rare
cases have been reported where the fluid escaped into the pericardium,
into the mediastinum, and into the opposite pleural cavity
(Fernet114). Bouveret115 relates a number of cases in which the
discharge of pus took place through such unusual channels as the
oesophagus, the stomach, the intestines, and the pelvis of kidneys;
also where the pus perforated the posterior cul-de-sac of the pleura
and appeared in the posterior walls of the abdomen. In the last cases,
he states, it may point in the groin, the lumbar region, the buttocks,
or even in the thigh.
114 Loc. cit.
115 Journal de Méd., Dec. 16, 1882; N.Y. Med. Rec.,
March, 1883.
SYMPTOMS.—In a large number of cases of purulent pleurisy the general
symptoms do not differ materially from those of fibro-serous
pleurisies. Sometimes, however, they do. This is according to whether
they are acute purulent or chronic purulent pleurisies.
In acute purulent pleurisy the disease commences in the same way as the
ordinary acute fibro-serous pleurisy. Indeed, the first effusion is
ordinarily serous in appearance, and afterward it becomes purulent. We
have the initial chilliness more or less marked, accompanied by the
characteristic pain in the side and dry cough, the fever keeping up,
even as high as 103° to 104° F.; and soon the signs of an effusion
supervene. In a few days, ordinarily, in acute fibro-serous pleurisies,
the febrile exacerbation disappears. Graves116 states that the extent
of a pleurisy is not augmented after twenty-four hours. In acute
purulent pleurisy the fever persists in spite of treatment; the
effusion increases, sometimes less rapidly than in the serous variety,
but in a continuous manner. If thoracentesis is performed about the
eighth or tenth day, we notice that the fluid is opaline and contains a
large quantity of pus. After this the fluid is reproduced, and as it
forms the fever continues; the skin is hot and dry, the appetite
impaired, and sweats appear during the night. In examining carefully
the thoracic walls we find oedema of the diseased side. Later on there
will probably be oedema of the lower extremities.
116 Clin. Méd., edited by Neligan.
Chronic purulent pleurisy is marked by symptoms somewhat different. It
commences in a similar manner to that of acute pleurisy, with fever,
but in a few days the fever disappears. In the evenings there may be
some febrile action with slight chills. It is remarkable that
frequently vast collections of purulent fluid do not give rise to
chills. The fluid augments progressively, but sometimes very slowly,
and often it appears to remain stationary for a long time. This
condition continues sometimes for many months. The
patients are
pale and feeble, although they may get up and walk until the quantity
is increased to such an extent as to impair their breathing capacity.
Then the forces of the body by degrees diminish, and the appetite is
impaired to a serious extent. The face becomes pale and the lips
discolored. From time to time diarrhoea supervenes and oedema of the
chest-walls is noticed, and general anasarca comes on without albumen
in the urine. If nature does not open an orifice through the parietes
of the chest or through the bronchi for the discharge, the patients
finally succumb in the last degree of wasting with profuse sweats and
fetid colliquative diarrhoea.
PHYSICAL SIGNS.—These, with some modifications, are very similar to
those of ordinary sero-fibrinous pleurisy. We have the same dilatation
of the chest, but it is more frequently localized. The oedema of the
thoracic walls is almost characteristic of the presence of pus in the
pleural cavity. We may, however, meet with it in fibro-serous pleurisy
and in cachectic subjects on the side of decubitus. Then, again, there
are cases of purulent pleurisy where it does not occur. It must be
looked for with care, especially at the lateral portion beneath the armpit.
Mensuration and percussion afford especial evidences of purulent
pleurisy, and frequently they discover encysted points.
The tubular quality of respiratory sounds is more pronounced, as are
also the amphoric characters at the apex, caused by long-continued
pressure of the compressed lung around the large bronchi. Ægophony is
less frequently heard, the bronchophony is distant and less distinct,
and vocal fremitus is more completely abolished. The non-transmission
to the ear of the whispered voice through the walls of the chest
(Bacelli's sound) in purulent pleurisy is a sign of considerable
significance in tracing the transformation from serous fluid into pus.
We must, however, bear in mind that when the sero-fibrinous effusion
contains fibrinous flocculi, it has the same effect as a purulent fluid
in interfering with the passage of the voice. (See article ACUTE
PLEURISY.)
DIFFERENTIAL DIAGNOSIS can be but indifferently reached by considering
the points mentioned. An exploratory puncture enables us to decide with
certainty as to the nature of the fluid. Without this the diagnosis is
often very difficult. In acute purulent pleurisy the diagnosis is most
difficult, especially at an early period, because the general symptoms
and the local signs resemble closely those of ordinary pleurisy. When,
however, the disease is further advanced, and we have the earthy aspect
of countenance with oedema of the thoracic walls, we can be nearly
positive in our opinion. Moutard-Martin117 speaks of this localized
oedema at the level of the fluid as a certain indication of the
purulent character of the fluid. But this oedema, as he admits, does
not always exist. It is wanting in many cases, and it may be found in
cases of sero-fibrinous effusion where the patient has been lying on
the side, and in other cases of advanced cachectic disease. Formerly,
there were many more errors of diagnosis, which were only discovered at
autopsies, but now, thanks to aspiratory punctures, the diagnosis is
much more accurate, and indicates to us the rational treatment. In both
varieties of purulent pleurisy there is a tendency to discharge by
making orifices through the walls of the chest or through the lung.
This is nature's mode of spontaneous cure. The most common is the
pleuro-bronchial fistula, and the period of the disease at which this
accident may occur is very variable. Woillez118 cites a case where it
occurred as early as the twenty-eighth day; ordinarily it occurs at a
much later period, sometimes as late as the eightieth day. It comes on
early in purulent pleurisy. In infants the perforations take place as
early as in fifteen or twenty days, and are favorable to the cure in
one-half of the cases. Saussier in 29
perforations of this kind
counted 15 cures. The symptoms of this accident are easy of
recognition. They vary according as the pleuritic effusion is diffused
through the whole pleural cavity or is limited, encysted, or
interlobular. In the first variety, where we have the physical
evidences of the presence of pus, suddenly, during a paroxysm of
coughing, the pus is forced up through the bronchi, and the patient in
a very short time expectorates a considerable quantity, varying from a
few grammes to a liter or more. The quantity thus thrown off depends
upon the diameter of the fistula. It may be excessive, as in a case
recently observed by the author where suffocation was produced, causing
syncope, asphyxia, and death, the flow being so rapid as to fill up the
bronchi to such an extent that the patient could not get rid of it. In
many cases the pus is brought up more gradually, with successive coughs
or with changes of position. Frequently vomiting is produced by the
flow from the vomica. After the first instantaneous evacuation of pus
(ordinarily continuous, sometimes intermitting) purulent expectoration
takes place. The patient may pass hours without any discharge, when
suddenly a severe cough brings up a quantity of pus, and again may
spend days without further expectoration. Pleuro-bronchial fistulæ may
have a valvular character, so that air may or may not be admitted into
the pleural sac as the pus is discharged. With or without the formation
of pneumothorax there is a tendency to cause putridity of pus. In cases
of children, who swallow their expectoration, it often produces a very
troublesome diarrhoea. The course of the disease and its prognosis are
necessarily altered according to conditions met with. When the air does
not penetrate, we observe that the diseased side becomes depressed and
the swelling, previously noticed, disappears. The flatness on
percussion diminishes or disappears entirely. On auscultation we have
coarse râles, sometimes just inside the fistulous orifices, sometimes
at a considerable distance. The general symptoms, as well as the
physical signs, improve, and the case advances slowly toward cure.
Ordinarily, the pus expectorated from the pleura, when free from
contact with the air, is odorless, but it is rarely as unpleasant as in
bronchial dilatations, unless it is long retained in the cavity, when
putrefaction ensues. When the air enters from the bronchi, it
frequently acquires a disgusting odor. If the air enters the pleura and
takes the place of the pus, the chest remains enlarged. Indeed, it
sometimes increases in size to such an extent as to cause suffocation
unless the pus and gas are withdrawn. The valve made by the false
membrane allowing the air to enter the cavity, but not to escape from
it, causes the fluid to accumulate rapidly, and we have pneumothorax to
a very painful degree. The diaphragm is pushed down, and, if the
disease is on the right side, the liver is forced down, and descends to
a level with the umbilicus.
117 Purulent Pleurisy, 1872.
118 Traité Clin. des Mal. Aigues des Organes Resp., 1872.
The collection of gas and fluid may be in such excess as to produce a
concavity of the upper surface of the liver, while the organ is forced
down into the abdomen. E. Moutard-Martin119 explains this extreme
condition by the fact that the fistulous orifice being at the superior
portion of the lung, the air having equalized the interior pressure
with the exterior pressure, the liquid obeys the laws of gravity, and
depresses the diaphragm. The fluid thus does not reach the level of the
pulmonary fistula. Under these circumstances the expectoration may
cease altogether unless the patient, by change of position, allows it
to flow outward through the orifice.
119 Loc. cit.
The physical signs of this condition of pyo-pneumothorax are very
marked and characteristic. Above the level of the fluid there is
ordinarily a great exaggeration of resonance on percussion, especially
at first. At the end of a few days, however, this resonance is
sometimes materially modified, and we have obscurity of the percussion
vibrations. Percussion, by itself, may lead
us into error of
diagnosis which the other modes of physical exploration will correct.
On auscultation we hear the amphoric murmur, which is sometimes of
great intensity, and at others so feeble and distant as to require
great attention on the part of the auscultator. These varieties of the
amphoric respiratory sound appear to depend more upon the position of
the pleuro-bronchial fistula, and upon the greater or less free
circulation of air through the fistula, than upon the extent of the
cavity (E. Moutard-Martin). This sound and the amphoric voice are the
two principal auscultatory phenomena. There is also the vibrating
metallic tinkling produced always in expiration. Although the physical
cause may exist, this latter is by no means a constant sign. It may
disappear for hours, and even days together, and then be heard for a
short time. Sometimes it is only heard when the patient coughs suddenly
and violently. When heard it is a very valuable indication of the
presence of a pleuro-bronchial fistula. Auscultatory percussion gives
us a still more valuable diagnostic phenomenon—the metallic amphoric
reverberation—especially if we percuss with a metallic percussor over
a metallic pleximeter. The Hippocratian splashing caused by succussion
is a more characteristic sign of pyo-pneumothorax than any other we
have mentioned. Other signs may fail, and often this is the only sign
present. Almost all the symptoms and signs that have been considered
characteristic of the presence of pus may coexist with a perfectly
limpid sero-fibrinous effusion. We may even have in serous effusions a
high, fluctuating temperature, profuse sweats, and quick pulse lasting
several weeks. On the other hand, purulent effusions may be associated
with symptoms of so mild a character as to lull suspicion. Previous to
the application of exploratory punctures for purposes of accurate
diagnosis, purulent pleurisies were confounded with the milder disease
until so far advanced as to be too late for effective treatment. Now we
can without risk discover purulent pleurisies at their very
commencement, and before they reach the point of great danger to the
subject we can relieve them by thoracentesis, and afterward pursue the
treatment for a radical cure.
Limited, circumscribed pleurisies, such as are found at the base of the
surface of the diaphragm and in the interlobular fissures, as well as
those involving the pleural cavity itself, may empty their contents
through the bronchi. As we have shown, the diagnosis of these forms is
often very obscure and difficult. The fine capillary exploring-needle
is a safe, and often a reliable, means of diagnosis. It may happen that
we can only guess at the nature of the disease until, after a
protracted cough, there is ejected by the mouth a quantity of pus, and
the diagnosis is made clear. We may perhaps discover a point of
flatness at the base or about the centre of the lung, but often this
flatness is very incomplete, because the collection of pus does not
always reach the thoracic wall. It may, indeed, be separated from it by
healthy lung-texture. Auscultation may discover coarse râles or even
gurgling with cavernous respiration. The voice sometimes has the
character of pectoriloquy, at other times of bronchophony: the cavity
is rarely large enough or the walls sufficiently firm to give the
amphoric tone. Under these circumstances there is neither metallic
tinkling nor Hippocratian succussion. The diagnosis of bronchial
fistulas caused by encysted pleurisies may be confounded with
tubercular cavities or with dilated bronchi. The exact position,
however, of the lesion, the rapid manner of the first purulent
expectoration, and the nature of the pus expectorated, will enable us
always to arrive at an accurate diagnosis. We must remember that in
bronchial dilatation the disease is developed by degrees, and the
patients do not expectorate suddenly a notable quantity of pus;
tubercular caverns are ordinarily at the summit. The mode of
expectoration is different, and the matter expectorated does not
present the same purulent and homogeneous characters.
The general
health is very different where encysted pleurisies exist from what it
is in patients suffering from tubercular cavities. In the former case
it is comparatively good; there are no profuse night-sweats, diarrhoea,
etc. Perforation through the thoracic walls may take place at a period
more or less remote from the commencement of the disease. The first
indication of this result is, ordinarily, a pain over a limited point
of one or two of the intercostal spaces, followed, in a few days or a
week, by a raised sensitive point on the surface, without change of
color of the covering skin. This may remain a long time in an unchanged
condition, but generally it increases gradually until it becomes soft
and fluctuating, reducible by pressure, but increased in size by
efforts to cough or by forcible expectorations. The skin over the
raised point becomes thin with a purplish tinge; suddenly, from some
effort to cough or unusual exertion requiring suspension of breath, it
bursts and gives exit to a quantity of pus far out of proportion to the
size of the small tumor. Sometimes there are several such points in the
same subject, appearing simultaneously or consecutively, especially if
the discharge is not free through the first one. Ordinarily, there is
but one which appears on the anterior portion of the chest about the
fifth intercostal space or in the intra-mamillary line. These orifices
sometimes close and then reopen. Of 18 cases of empyema necessitatis
collected by John Marshall,120 1 occurred in the sixth intercostal
space and 17 in the fifth, and 6 of his own cases in the fifth, beneath
the nipple. This is, as he states, the weak point of the chest,
relatively unprotected by the adjacent muscles. The internal
intercostal muscle, the weakest portion of the great pectoral, and the
thin fascia, are the only coverings at that point. There is valid
reason why special bulging and spontaneous perforation should occur
there. The spot also corresponds nearly with the middle of the pleural
cavity when distended. The fifth intercostal space is wider than those
below, and its limiting ribs, held to the sternum, give firmness to its
borders—conditions which help the thinness of the walls in determining
the place of perforation. In children perforation often takes place in
the very wide second intercostal space. The perforation, although it
may contract in size, persists and remains a fistulous canal,
permitting air to enter and to escape. The fluid rarely becomes fetid
unless there is a pleuro-bronchitic fistula or air is otherwise freely
admitted. Sometimes when the orifice is oblique, the air does not enter
at all. When the purulent effusion escapes through the thoracic walls,
the patient experiences at once manifest relief. The respiration
becomes better, the fever decreases, the sweats disappear, the appetite
improves, and the general condition is decidedly ameliorated. This
improvement persists as long as there is free discharge, but if from
any cause it ceases, we have a return of serious symptoms. If no air
enters, percussion and auscultation show the gradual disappearance of
the evidences of disease; but if air enters we have the signs of
pyo-pneumothorax, amphoric breathing, metallic and succussion sounds.
The diagnosis of parietal openings is comparatively easy: the quantity
of pus, its odor, with the physical signs, show its nature. With care
this form of pleural opening is distinguishable from a fistula made by
caries of the ribs or by vertebral abscesses, and not communicating
with the pleura. The existence of a thoracic fistula does not prevent
the formation of pleuro-pulmonary fistula, and reciprocally a parietal
fistula can be found where the other has been previously formed. The
abscesses following purulent pleurisies and empyema have been long
recognized. Hippocrates mentioned them as contributing to a favorable
prognosis in empyema.
120 London Lancet, March, 1882.
Pulsating empyema is where the lesion is situated in the neighborhood
of the heart or of the aorta, which transmit their impulse. They are
also sometimes called pulsating tumors, rising and falling with
alternate movements of
inspiration and expiration (Stokes,
Graves, and Aran). These cases strongly simulate aneurisms. According
to Fraentzel, the fluid is always purulent. In 1 case reported by him,
and in 2 cases seen by Traube, pericarditis with effusion was present.
Douglass Powell mentions two well-marked cases of pulsation in the left
supra-mammary region where the diagnosis between effusion and aneurism
was very difficult, but where paracentesis removed a large quantity of
fluid and the signs of pulsation ceased. In these cases there was
present neither pus nor pericarditis.
TERMINATIONS.—If allowed to take its natural course, pulsating empyema
almost always ends in death from exhaustion or syncope, or by
discharging through the lungs or through the intercostal spaces.
Formerly, it was oftener fatal than now, but it is still justly
considered the gravest form of pleurisy. We have seen that
exceptionally it is cured by becoming encysted. It may be cured by
spontaneous openings into the lungs, and more rarely by fistulous
orifices121 through the walls of the chest. Is it possible for the
disease to be cured by the absorption of the pus? The bearing of this
inquiry upon the treatment cannot be over-estimated. If absorption can
remove the pus, we may safely leave it in the pleural cavity. If the
pus cannot be taken up by the absorbent vessels, we ought promptly to
make use of radical measures and evacuate it. The literature on this
point gives us few reliable cases. Spontaneous cure can rarely be
produced by absorption. Douglass Powell122 writes that "the
spontaneous disappearance of such effusions is too uncommon to be
expected, and the process of reabsorption is one too full of peril to
be anticipated with anything but dread. It is indeed an attempt at such
absorption that occasions the most characteristic hectic symptoms."
Surgical intervention is the rule. The writers previous to the
introduction of exploratory punctures speak of cases where purulent
pleurisies were diagnosed and the effusions were absorbed. We have
shown that the differential diagnosis between serous and purulent
effusions is very uncertain when made from the general symptoms and
physical signs. Even Trousseau, with all his skill and vast experience,
made the mistake of diagnosis, and performed the operation of
pleurotomy in a case of serous effusion, and his patient died. There
are well-authenticated cases where, after thoracentesis, small
quantities of pus left behind have been absorbed, especially in
children. That purulent pleurisies have been effectively cured by the
pus becoming encapsuled has been demonstrated by autopsies of persons
dying from other causes. E. Moutard-Martin reports a case where, after
withdrawing with an exploratory trocar a few drops of pus, and thereby
establishing the diagnosis of purulent pleurisy, he was unavoidably
prevented from opening the chest. Two months afterward he found the
effusion had entirely disappeared. He states that this was the only
case he had ever seen of a spontaneous cure without evacuation.
Douglass Powell has seen one case which has satisfied him as to the
possibility of a local empyema becoming absorbed. Wilson Fox reports
another similar case. Chronic pleurisies in childhood are almost
invariably suppurative, yet Barthez and Rilliet report 7 out of 13
recovered. It must be, and generally is, admitted that cure by pus
undergoing retrogressive fatty degeneration, and then being absorbed,
is possible, but it rarely occurs. Should the more fluid portion be
absorbed, the inspissated pus remaining on the pleural surface may at
some future time, upon softening, give rise to secondary tubercular or
purulent collections. It is also true that cure is quite often effected
by spontaneous evacuation through the lungs and through the walls of
the chest. This is especially the case
in interlobular effusions
and in cases sacculated by adhesions. Such cure is explained by the
fact that adhesive inflammation, assisted by the elasticity of the lung
on both sides, glues together the walls, isolates the fluid, and
prevents air from entering, thus preventing the pus from putrefying.
121 In Andral's 8 cases of bronchial perforation there were
only 3 deaths—a mortality less than by artificial opening previous to
the application of Listerism.
122 Dis. of the Lungs and Pleura, London, 1878.
In cases of pulmonary perforations the probabilities of a favorable
termination by absorption of gas, evacuation of fluid and the contents
of the chest, are greater where air does not enter the cavity. The
presence of air, especially if stagnant, in contact with the pus, makes
a serious complication, causing putrefaction of the pus and consequent
septicæmia, with all its dangers. The discharge of the purulent
collection, through the parietes of the chest, after the manner of an
ordinary abscess, is ordinarily made through the anterior part of the
thorax, but it may take place in any part. At first this mode of
evacuation, empyema necessitatis, is a great relief, but cures rarely
result from it. Most frequently, owing to the imperfect evacuation
through the tortuous canal and the entrance of air mingling with the
pus, death supervenes unless the surgeon enlarges the orifice or
produces a new one, and thoroughly empties the sac and persistently
washes it out. From statistics collected by Wilson Fox, the mortality
is not so great from spontaneous parietal openings as was formerly
supposed. Of Andral's cases there were 2 deaths in 25. Goodhart had 11
cases, all of which recovered. Ewald lost 3 of his 6 cases. Cases of
empyema necessitatis should be treated as artificial openings with
every possible antiseptic precaution. The mortality would thus be
decreased. The chances of cure by absorption are so small that when
nature shows no tendency to either of the two spontaneous modes of
cure, there is great danger of a fatal termination through hectic
fever. The time for this result varies from a few weeks to months. When
in empyema we have fistulous orifices they sometimes remain open for
years. Near them are local points of depression, caused by external
atmospheric pressure. When acute purulent pleurisy follows a low fever,
such as typhoid or scarlet, a fatal termination may result in a short
time; in other cases it is many months before the patient dies from exhaustion.
We cannot forbear to urge the importance of promptly and definitely
settling the diagnosis by exploratory aspiratory punctures. Properly
guarded, no evil can result, whereas a positive diagnosis enables us to
act promptly with effective mechanical means of relief. It is
undeniable that purulent effusions in the pleural cavity are very
serious in their results, and are followed by death unless Nature or
the surgeon evacuate them. Even when Nature does so, it is often
imperfectly done, and the termination may be death unless we assist her
to get entirely rid of the fluid.
PROGNOSIS.—Formerly the prognosis in every case was of extreme
gravity. The condition was looked upon as of necessity fatal. Surgeons
despaired of a successful result in operating. Now, thanks to thorough
drainage and Listerism, unless the case is an old chronic empyema, we
are hopeful of cure and a favorable prognosis may be given. We may look
for good results where the disease is early recognized and promptly
treated. J. G. Blake123 cured 16 in a total of 19 cases. Since 1869
he cured 9 out of 10 cases. Homer124 saved 26 out of 52. Feidler125
treated 112 patients, only 25 of whom died (all advanced tubercular
cases); 21 were restored to good health; 66 (tubercular) were cured so
far as return of effusion was concerned. Israel126 had 10 recoveries
out of 11 cases. A. T. Cabot127 reports 11 recoveries out of 14
cases. Of the fatal cases, 2 died of phthisis; the third had existed four years.
123 Med. and Surg. Rep. Boston City Hospital, 2d Series.
124 Quoted from Med. Times, Philada., Aug., 1883.
125 Ibid.
126 Quoted from Dabney, Amer. Journ. Med. Sciences, Jan.,
1883.
127 Bos. Med.-Surg. Journ., Aug. 16, 1883.
When purulent pleurisy follows fibro-serous effusions, and when
it occurs in vigorous children, the prognosis is more hopeful than when
it is preceded by scarlet fever or occurs in subjects debilitated by
diseases which have exhausted the recuperative forces of the body.
Empyema of tubercular origin has necessarily a grave prognosis. In
persons in advanced life the prognosis is very unfavorable. If hectic
fever or septicæmia occur, the prospects of cure are comparatively
slight. In cases of empyema necessitatis much depends upon the power of
resistance of the patient, and upon whether the matter is discharged
before it has produced caries of the ribs, sternum, or spine, or has
prostrated the vital powers. If these sequelæ have been produced, the
condition of the body is most unfavorable to the restoration of health.
If the pus in pyothorax has been discharged through the bronchi, though
it may give temporary relief, it is attended with great danger, and if
the discharge continues it will gradually wear out the patient's strength.
TREATMENT.—The diagnosis being established, we at once realize the
great responsibility of treating a disease of such gravity. In many
other diseases of serious import we trust Nature to do her part toward
cure; here, as we have shown, we find her unable to come to our
assistance. One of the large serous cavities, connected as it is with
the lungs, is not only disabled, but contains a deleterious fluid which
cannot remain in a closed cavity without sooner or later affecting the
processes of nutrition. We can do little by medical treatment save to
sustain the organism by tonics and reparatory agents; we can give wine,
quinine, arseniate of soda, and cod-liver oil; we can administer a
sustaining diet and place the patient in the best hygienic and sanitary
condition. We cannot conscientiously hold out to the patient a prospect
of cure by medicines.
There is danger in resorting to the expectant plan of treatment. We
lose valuable time, and finally we shall be forced to resort to
surgical operations, which in fact constitute the modern treatment of
purulent pleurisy. By them only are we able to promote the primary
objects of our treatment, which are to get rid of the purulent matter
and to stop the suppurative inflammation. We thus endeavor to
obliterate the pleural cavity and promote the expansion of the lungs.
Surgical Treatment.—This has been the treatment which has been most
effectively used from the time of Hippocrates to modern times. There
has been, and still is, great diversity of opinion as to the best modes
of withdrawing the pus contained in the pleural cavity, but it is
settled that when the diagnosis is certain the fluid must be
removed—if not by spontaneous openings, by artificial means. We must
except to this rule cases of suppurative pleurisy of phthisical origin.
Bowditch years ago stated that in this class of cases it was advisable
not to make permanent openings into the chest. In these the suppuration
does not stop, and the operation appears to hasten the fatal issue of
the disease. Wilson Fox demonstrates from statistics that the mortality
in phthisical cases is increased by operations.
There is no room for discussion as to the indications, as in cases of
simple sero-fibrinous pleurisy. There is only one thing necessary to be
ascertained—the certainty of pus in the cavity. This is shown by the
pointing or by pus abstracted by exploratory puncture. The more
promptly we act, the greater the prospect of cure. As Powell128
emphatically says, "The prognosis is practically hopeless without
surgical help. We must adopt some surgical measures or take upon
ourselves responsibility for a large mortality." Bowditch, Trousseau,
Hamilton Roe, Anstie, Parker, Marshall, and Moutard-Martin all concur
as to the necessity of surgical interference. Clifford Allbutt129
says: "If pus or septic material be present in the body, we must not
rest until it is removed. I therefore dislike and reprobate all
tampering with an empyema."
128 Loc. cit.
129 Brit. Med. Journ., Dec., 1877.
We propose to mention, as briefly as we can in justice to the subject,
the several modes of operating, together with our conclusions and the
results obtained by us and by others of much larger experience.
Modes of Operating.—These are numerous, but they may be divided into
three classes: First, the simple immediate evacuation of the fluid by
subcutaneous thoracentesis with the ordinary trocar or with an
aspirator of some kind, without allowing the flow to be continuous:
this is the closed method; secondly, the open method—the operation by
incision with a bistoury, and the introduction of permanent canulæ or
of drainage-tubes of metal, of hard rubber, or of soft tubing; thirdly,
the more radical treatment by free incision (pleurotomy) with or
without washings or injections by the aid of syphons. With all these
modes of operating the strictest antiseptic precautions should be taken.
Thoracentesis.—For this operation we have a choice between the
ordinary hydrocele trocar, the trocar protected by a soft valve at the
orifice (Reybard's instrument), Jules Guérin's or Wyman's aspirating
pumps, Dieulafoy's previous-vacuum aspirator with capillary needles,
and numerous modifications by others of Dieulafoy's, including
Potain's, and Reynard's modification of Potain's, or we can have
recourse to Potain's, Southey's, or Williams's syphon. If we select the
trocar (Reybard's), we prepare the instrument by cleansing it
thoroughly and Listerizing it. Reynard130 recommends a hypodermic of
morphia previous to operation, to prevent the painful cough. The
simplest method is to pass the aspirator needle through the flame of a
spirit-lamp, and subsequently to plunge it in carbolic-acid solution.
We spray with a carbolized solution the point of puncture, which should
be at the sixth intercostal space, when possible, in the axillary line.
Powell prefers a lower opening, in the seventh or eighth intercostal
space and in the posterior axillary line. He wishes to completely empty
the pleural cavity of pus and promote the obliteration of the
abscess-sac by the descent of the lung as it re-expands, and by the
return of the heart to its normal position: these processes converge
toward the lower and postero-lateral position. We ordinarily prefer
local anæsthesia by sprays of ether or rhigoline or by cocaine
hypodermics to anæsthesia by inhalation. After drawing up the skin, so
as to be able to close the orifice by the flap after the operation, we
direct the trocar by the nail of the left index finger; we, with a
quick movement, insert the trocar to the extent of three or four
centimeters. By this quick insertion we do not run the risk of stopping
the canula with the thick membranes. We allow the fluid to flow out
slowly, but as completely as possible. In fibro-serous effusions we
only draw off sufficient to remove intra-thoracic pressure, to avert
the dangers caused by that pressure, and promote the process of
absorption. In suppurative pleurisy, while we aim at relief from
pressure, we wish to get rid of a fluid which is itself deleterious.
Consequently, our object is to prevent absorption and to ward off the
formation of fistulous outlets through the lungs or the parietes of the
chest. Therefore we endeavor to completely evacuate the pus, and, as
far as possible, to prevent its re-formation. While we desire to remove
all the fluid if we can, we must not run any risk by doing so. If the
cough annoys the patient, and the elasticity of the walls and the
pressure from the displaced organs do not continue to force out the
fluid, we had better stop the flow temporarily or renew the operation
next day. We must desist if the cough becomes very persistent. We
prefer Dieulafoy's aspirator or Potain's modification for the simple
evacuation of the fluid, unless we wish to wash out the pleura; then we
employ Potain's or Williams's (of Boston) syphon, because either can be
applied
with greater effect. It is best not to take needles of
too small a diameter, for the flocculi may easily choke them. We prefer
No. 2 (1 millimeter) or No. 3 (1 millimeter and a half). By using the
small-sized dome-trocar we avoid the possibility of injuring the lung.
Care must be taken in removing the canula to withdraw the aspiratory
force by turning the stopcock; otherwise we may draw the pus into the
texture of the walls and establish fistulous openings. In using the
common trocar fistulæ have frequently been made, causing a serious complication.
130 Brit. Med. Journal, Sept., 1881.
Thoracentesis thus performed has often cured empyemas, especially in
children. We find instances mentioned by Lacase, Duthiers, Dieulafoy,
Lebert, Hamilton Roe, and others. It has been demonstrated that the
operation is sometimes effective without resorting to injections and
washings of the pleural cavity. Bouchet131 reports a case in a child
following typhoid fever, where he aspirated thirty-three times and
cured the patient; another case, a child four years of age, after two
operations; another child, seven years of age, after six aspirations.
Guérin132 reported several cases. M. Fouson133 reported 19 cases of
children treated by aspiration with success. The younger the child, the
greater are the chances of success. He advised complete emptying of the
cavity. Lewis Smith134 prefers the use of an aspirator in operating
upon children. He does not think it necessary to remove all the pus
present. Cordet Gassicourt135 reports cases of three infants, each of
whom was cured by one aspiration. C. Gerhardt of Würtzburg136
recommends in children complete evacuation of purulent fluid, through
incisions and washings, avoiding entrance of air. Adolph Bajincke of
Berlin137 states that aspiration with antiseptic treatment is often
successful in children. He advises, if after two or three aspirations
the fever returns and the fluid increases, that free incisions be made,
with injections of salicylic acid (3 per cent.), with antiseptic
dressings. He recommends the removal of only a portion of the fluid. A.
Jacobi138 mentioned having in a single year 3 cases of empyema in
young children, each of which required but a single aspiration; the
quantity of pus in 1 case amounted to 300 or 400 grammes. The
flexibility of the young ribs causes sufficient sinking in of the
thorax to promote recovery. F. Richardson139 advises two aspirations
before incisions. R. W. Parker,140 London, takes Richardson's view.
He strongly advocates antiseptic precautions and injections of quinine
(5 grs. to ounce j) and injection of filtered and carbolized air into
the pleural cavity. Austin Flint141 advises that aspiration should be
used first, but if not successful, then incisions should be made at the
base of the thorax and a tent introduced to keep the orifice open.
Anstie142 gives similar directions. According to Bowditch,143
"whenever the pus is pure there is no immediate call for thoracotomy,
for patients at times get well after simple aspirations. Youth and
recent uncomplicated disease favor this. Heretofore, after three
aspirations the author has resorted to thoracotomy." Dabney144 says
that aspiration occasionally gives good results, even in adults. S. C.
Chew reported the case of an adult (twenty-five years of age) cured of
empyema by one aspiration of sixteen ounces, and also a case of a child
three years of age after three aspirations. Barnes145 reports a case
of a patient nineteen years of age who recovered after four aspirations
of large quantities of pus. J. G. Blake146 reports a case (boy ten
years of age) where one aspiration of ten ounces accomplished a cure.
He adds that in children repeated withdrawals of pus by aspiration are
justifiable, but in adults after
one unsuccessful operation he
advises permanent opening. Dupuytren147 cured a case after
seventy-three aspirations. The author has had 3 cases perfectly cured
by aspiration: a child eleven months old, after three operations; a
child of five years, after five operations; a boy sixteen years of age,
after two operations.
131 London Lancet, 1860.
132 De la Thoracentèse par asp. dans la Pleu. Pur., 1871.
133 Thèse de Paris, 1877.
134 Diseases of Children.
135 Soc. de Thér., 26 April, 1882.
136 Trans. Int. Med. Con., vol. iv.
137 Ibid.
138 Ibid.
139 Ibid.
140 Ibid.
141 Clinical Medicine.
142 Reynolds's Sys., vol. ii.
143 Unpublished MSS.
144 Amer. Journ. Med. Sci., Oct., 1882.
145 Brit. Med. Journal, Dec., 1877.
146 Med. and Surgical Reports Boston City Hospital, 2d
Ser., 1877.
147 Altimont, loc. cit.
Such being the record, we are in duty bound to try simple aspirations
before making use of the more radical modes of treatment. The character
of the fluid as drawn off by the exploring-needle furnishes valuable
indications. Should it be found laudable and inodorous, we had better
aspirate once or twice before resorting to the free incision. It can do
no injury, and we thus enable the lung to expand, diminish the size of
the cavity, and prepare for the more radical operation. In children we
ought to try this mode repeatedly unless we have symptoms of emaciation
and hectic approaching; in adults only two or three times. The
operation is simple, painless, without danger, and occasionally
perfectly effective. If the fluid re-forms quickly—and it sometimes
does with astonishing rapidity—or there are evidences of depression
from fever, sweats, and diarrhoea, we must promptly have recourse to
one of the effective surgical methods producing free drainage. It is
undeniable that the treatment by thoracentesis is frequently
unsuccessful, notwithstanding repeated operations.
In sero-fibrinous effusions the close method is the most successful,
but in purulent effusion this is not ordinarily the case, and we are
forced to employ the open method to produce free, continuous
discharges, as the purulent fluid re-forms rapidly.
Open Methods.—Of these we have—(1) drainage through a single orifice
by the introduction of a permanent canula or soft india-rubber tube;
(2) drainage through two openings; (3) use of syphon; (4) pleurotomy;
(5) drainage by resection of ribs. Each of these modes has its
advocates. They have all been frequently used with varying results.
Each has its advantages and disadvantages.
The first point to be noted about these modes of operation is, that we
cannot prevent the introduction of a greater or less amount of air to
replace the fluid, and therefore it is of primary importance that we
should always render the air aseptic. The incision must be made after
thoroughly cleansing the point to be opened. The bistoury, the canula,
the dressings, the receptacles of the pus, the sponges, and everything
connected with the operation, should be purified to prevent the
possibility of the contamination of the pleural cavity and its
contents. At each subsequent dressing all these precautions should be
renewed. Antiseptic gauze of six or eight layers in thickness, with
finely-combed oakum or salicylated cotton, ought to be placed over and
around the orifice for an area of twelve inches. In this way what
little air enters after the operation may be rendered thoroughly aseptic.
Lister148 recommends that the coverings of gauze should be in eight
folds if the drainage be excessive—that these be charged with a
disinfectant composed of one part of carbolic acid to four parts of
resin and pure paraffin. The dressings, he directs, should be kept in
place by elastic bandages. This treatment stops suppuration promptly,
and converts the discharge into one of a serous nature. His views have
been amply confirmed. A. T. Cabot149 recommends that the dressings be
covered with a piece of mackintosh large enough to project in every
direction. In his cases he found it acted as a valvular fold, forcing
the air and pus out and preventing air from entering.
148 "Lectures on Clin. Surgery, etc.," London Lancet,
Dec., 1879.
149 Loc. cit.
Drainage by Canula through a Single Orifice.—The patient, having had
about three hours previously a good substantial meal of easily-digested
food, is placed in a semi-recumbent position, leaning over toward the
healthy side.
Before selecting the point of puncture, the side
ought to be first washed with soap and water, so as thoroughly to
remove all dirt and epithelium débris, and then bathed in a 1:20
solution of carbolic acid. As there is to be but one opening through
which the fluid is to pass, it is desirable to have it low down. The
eighth intercostal space, somewhat behind the posterior axillary line,
is ordinarily the best point for the puncture. Lower than that we may
encounter the diaphragm, and, as we must use a trocar of considerable
size, we may inflict serious injury. As we desire to completely empty
the pleural cavity, a higher point would not be as effective. After
having satisfied ourselves of the presence of fluid at the point
selected by the physical exploration, we ought always to insert, as a
crucial test, a new exploratory hypodermic needle which has been
rendered aseptic. Ordinarily, it is not necessary or expedient to
resort to etherization, unless in case of a child, for local anæsthesia
by cocaine hypodermically, by rhigoline or the ether spray, or by the
application of a small piece of ice covered with salt (as suggested by
Powell), will render the incision painless. It is needless to add that
a weakened heart, a sluggish capillary circulation causing a cyanotic
appearance, and marked dyspnoea contraindicate the employment of
etherization. We prefer cutting through the integument with a bistoury,
and then inserting the trocar, which must be pushed with a thrust
through to the pleura. All of the pus should be allowed to escape,
unless cough, oppression, or threatening syncope should be noticed, in
which case it is better to insert the tube and arrest the flow by a
cork. The outward flow should be rendered slow by covering the orifice
with the dressings and allowing the fluid to soak into them. The tube
should only be long enough to go well through the parietes into the
pleural sac; otherwise it acts as an irritant, and interferes with the
adhesion of the two pleural surfaces, which is necessary for the
obliteration of the pus-secreting cavity and the expansion of the lung.
The tube should be kept in position by a hard-rubber shield attachment,
with bandages previously soaked in disinfectants applied around the
body, and several layers of carbolized gauze. The firm canulæ, metallic
or hard rubber, straight or curved, as proposed by Woillez and
Dieulafoy, are now generally abandoned. These admit air either by the
sides of the opening or through their canals, and they sometimes
produce, at their extremities, local ulceration through the lung or
even through the diaphragm, and cause peritonitis. Their only advantage
consists in the facilities they offer for washing out the cavity. With
canulæ made of soft india-rubber there is no danger of injuring the
lung, etc. They are not painful to the patient, and they can be
protected by valvular strips of gold-beater's skin or some soft
substance at their orifices. Through these india-rubber tubes we can
inject all fluids and washes, except those containing iodine. It has
been proved by Dujardin-Beaumetz150 that iodine hardens india-rubber,
renders it extremely brittle, and destroys its elasticity in a short
time, even after a contact of forty-eight hours. In a case of
Bucquoy's151 the tube underwent such alterations that it could only
be extracted by a long and painful operation. If these tubes are in use
when iodized fluid is to be injected, they must be temporarily removed,
and a metallic one, with arrangements for a double current, substituted
during the process of washing. If the canulæ are to be kept in
permanently, they must be of large size, so as to allow free flow
outward of fluid.
150 Quoted by Dieulafoy, Pneum. Asp., English ed.
151 Ibid.
After the operation the patient should always remain in bed in an easy,
comfortable position, with the orifice covered by the dressings. His
diet should be of an easily-digested and nutritious character. His
temperature, pulse, and the condition of his secretions should be
carefully watched. Ordinarily, it is not well to reopen the
discharge-tube for three days. The same antiseptic precautions should
be used then as at the operation,
and a fresh tube inserted. The
pus secreted ought, if the case be one of recent origin, to be small in
quantity and without odor. After a few days it is best to allow the
fluid to flow out on the dressings as it forms, which is done by
turning the patient well over on his side. An occasional cough assists
the discharge. Should the odor become putrid or gangrenous, or hectic
symptoms show that the secretion is profuse and has no free exit, it
becomes necessary at once to use washings and injections of simple warm
water or warm water feebly alcoholized—1:45 or 1:80—or feebly iodized
solutions. The greatest care should be taken with these washings that
very gentle force be employed. (See Pleurotomy.) This mode of operating
is most effective in recent cases, for it gives the best opportunity to
the lung to expand. It is the easiest to perform, and, subsequently,
the least troublesome. If it be found ineffective, an additional
orifice can be made and a fenestrated tube inserted, or the orifice can
be enlarged by a free incision. There have been many successful cases
of this mode of operating, but, as the author has sometimes found, it
is difficult to establish free drainage, which is most important for
the success of the treatment. The result of his experience has been
that, in chronic cases especially, the two-opening drainage or free
incision without tubes (pleurotomy) has finally to be employed. Powell
recommends, after removing intra-thoracic pressure by aspiration or
syphon, in a day or two to completely evacuate the fluid under the
antiseptic spray and insert a tube for a few days only; then to allow
the wound to heal, and await results, trusting nature to secrete a
fibro-serous fluid which can be easily absorbed.
Drainage by two openings, as first effectively employed by Chassaignac,
is made by the introduction, through a large covered canula, of a tube
of india-rubber, perforated with holes, drawn out at another orifice.
The tube has its two extremities on the outside, and one posterior, in
the eighth or ninth intercostal space, and the other in front, in the
seventh intercostal space, after the withdrawal of the canula. The
anterior orifice is first made, and a long curved probe with a bulb at
the end is passed through backward and downward until it strikes the
posterior lowest intercostal space. The operator cuts down on the
probe, which points outward. To this end the fenestrated drainage-tube
is securely fastened, and is then drawn out through the first orifice.
Both ends are retained out of their orifices, by a shield firmly fixed
on the tube, for at least an inch. The pus flows out little by little,
but continuously, through one or other orifice, according to the
position of the patient. This is the most effective method to prevent
accumulation. Unfortunately, false membranes and flocculi sometimes
stop up the orifices in its walls, the pus does not flow out as it is
formed, and there are all the evils of air and fluid mixed and retained
in the serous cavity. It is, however, generally admitted that by this
system of drainage a number of cases have been cured; but it is not
often employed as a primary operation, as we wish to avoid, if
possible, the irritation which may result from the presence of so much
tubing in the chest. Moreover, it is not the best operation if there is
any hope of the lung expanding again. In old chronic cases we cannot
hope for more than very limited expansion.
Gross152 speaks of drainage-tubes as harsh and dangerous. Flint,
Sr.,153 prefers free incisions, with introduction of tents, to
drainage-tubes. Dabney154 considers continuous drainage in some form
vastly preferable in the majority of cases. Israel155 had 10 cases
recover out of 11 treated by thorough and continuous drainage. Cheadle
believes that a large collection will certainly require a free opening
in the end, and the sooner the pus is let out the better.
152 System of Surgery, vol. ii.
153 Clin. Med.
154 Amer. Journ. Med. Sci., Oct., 1882.
155 Quoted by Dabney.
Chassaignac's method of drainage will answer well unless, as frequently
happens, the purulent pleurisies contain large fibrinous masses,
hydatid pouches, or pieces of sphacelous débris.
Syphons, as used in purulent pleurisies, have some very decided
advantages. Potain's ingenious instrument, based upon the syphon
principle, enables us alternately to empty the pleural cavity into a
basin of water, and, by reversing the instrument, to inject the water
into the pleural cavity, thus washing out as often as necessary and
with ease the purulent collection and cleansing the cavity. Potain's
syphon is composed of an india-rubber tube 30 centimeters in length, to
be introduced and remain in the pleural cavity. This tube is introduced
through the canula, after the withdrawal of the trocar, to the depth of
at least 20 centimeters, in order that its extremity should reach the
posterior wall, the tube having been previously filled with water. The
outer extremity is put into a basin containing water. The part of the
tube at the outside of the orifice is closed by a serre-fine just
beyond the shield, as is also the extremity in the water. Another tube
is connected with the chest portion. This can be used for introducing
water to wash out the pleura. The syphon of Potain has very decided
advantages over the metallic and hard-rubber drainage-tubes. It
prevents the introduction of air and enables us completely to empty the
cavity; it permits us to wash out the cavity as frequently as is
necessary without fatigue to the patient, without pain, and without
change of position, and thus prevents attacks of coughing. All this is
done slowly, and the flow can be arrested at any moment by means of the
stopcocks. Where repeated washings are required the patient himself can
perform them with ease. With the other modes the washings are practised
with difficulty. The improved syphon by F. H. Williams of Boston is
simple in construction, of small size, and inexpensive. Revilloid of
Geneva (1882) reports 10 cases thus treated, of which 6 were cured.
Bénard156 reports 8 cases treated by syphon, of which 4 were cured.
Goodhart's157 statistics are not favorable to the use of the syphon.
Of his 28 cases thus treated, 10 died; in only 6 did the syphon method
alone effect the cure. Powell158 objects to the syphon method,
because by it the chest cannot be drained unless the lung expands
completely or air is freely allowed to enter the pleura. These
conditions are impossible in such cases with a single opening and a
single tube. Moutard-Martin, while speaking of the advantages of
Potain's syphon, admits that in chronic cases where there are pieces of
false membrane and flocculi floating in the fluid the tube may be
clogged up, just as occurs in the metallic tubes and the
drainage-tubes. The patient may thus die by retention of pus and by
putrid absorption, unless pleurotomy is employed. It must be borne in
mind that the syphon is a weak aspirating instrument. It ought to be 10
meters long to possess an aspirating force equal to that of a pneumatic
pump (water being taken as the standard), and its long arm should
measure from 7 to 8 meters, in order that its aspiratory force should
equal that of a good pneumatic aspirator. Thus we see how weak is the
aspirating power of a syphon which only measures the space which
separates the bed of the patient from the floor. The ordinary aspirator
can be easily changed into a syphon. The descending arm of the tube
must be emptied by a stroke of the piston; the current is then
established and the stream becomes continuous (Dieulafoy159).
156 Thèse de Paris, 1871.
157 Guy's Hospital Reports, 1877.
158 Loc. cit.
159 Trea. Pneum. Aspiration, Eng. trans., 1873.
While all prominent modern authorities admit the value in some cases of
double metallic tubes, of those of hard rubber, of drainage-tubes, and
of syphons, with thorough and complete antiseptic treatment, yet
observation has taught us that there are many disadvantages and
uncertainties. The drainage-tube may give rise to considerable
irritation and prevent the closing of the sac—a very important aid to
the cure. If the flow is retarded, the
fluid may decompose.
Therefore it is well to remove the tube frequently, to wash, cleanse,
and renew it. The admission of air and stopping up of tubes, the feeble
force employed, the putrid pseudo-membranes, and sometimes sphacelous
débris, cause, in many instances, fatal results. It frequently happens
that at first, when trying the simple aspirations, we find a whitish
laudable pus which subsequently becomes thick and fetid. We use
drainage-tubes and Williams's syphon, with strict adhesions to
Listerism, and yet there may ensue continuous fever, emaciation,
sweats, drawn face, and general oedema. We resort to detergent washes,
with salicylate of sodium, of tincture of iodine, very diluted, yet the
patients get worse and the tubes become obstructed. There is not
sufficient free flow of the contents of the chest.
Pleurotomy.—We naturally shrink from freely opening the chest. It is
right to try the simpler methods—aspiration, tubes to remain in the
chest, drainage, use of syphons—but we are forced in many cases of
chronic empyema to use pleurotomy, the thoracotomy of Bowditch, the
operation of l'empyème of the ancients. It consists of a wide opening
into the thorax between two ribs, permitting the escape of the effused
liquids. If the orifice is large enough, we can remove from the cavity
of the pleura not only the pus, but the large fibrous masses,
gangrenous débris, hydatids, and putrefying material which produce
septicæmia and death. The literature of this subject shows that bad
results have ensued from this operation, and again and again it has
been abandoned, but now that we can, by means of large openings, freely
wash out the cavities, and can apply injections of antiseptic and
alterative medicines to the suppurating surfaces, many lives are saved.
Hippocrates' dogma as to the danger of free and rapid evacuation of pus
had often a dangerous influence in preventing a thorough emptying of
the sac. The object of this radical operation must be kept in view—to
evacuate the pus by a free current, to permit the discharge of plastic
products and organic débris, and to allow easy and frequent washings
with healing and purifying injections. By these means we arrest
suppuration, obliterate the sac, and allow the lung to expand. For this
purpose wide orifices should be boldly made. They should be made where
the chest bulges most, but not always at the most dependent portion.
Ordinarily, the eighth intercostal space, somewhat behind the posterior
axillary line, has been the one selected, because it has been supposed
that thereby the cavity could be most effectually drained. The author
has usually punctured higher, in the seventh intercostal space on the
left and in the sixth on the right side, for the fifth and sixth ribs
being more fixed, there is less danger of subsequent approximation. We
cannot always determine the exact position of the diaphragm. The lung
may be bound down by old adhesions to the diaphragm, and thus the
latter may be injured by too low an incision; we can, moreover, better
adapt the position of the patient to enable the matter to flow out from
a higher orifice. Cases have occurred where the liver has been
perforated on the right side by low punctures. In health the uppermost
point of the diaphragm may be as high as the fifth space on the left
side or the fourth space on the right. The cure does not depend upon
the exact position of the puncture, because we expect to insert a
mouth-tube to keep the orifice open, and probably resort to washings.
It is not by its weight only that we expect the fluid to escape;
incessant movements of the thorax assist in forcing the fluid through
the tubes. Marshall160 urges the fifth space on the right side, and
as near the weak point of the chest under the nipple as possible. On
the left the pericardium must be carefully avoided. He advises that the
operation should never be lower than the sixth or seventh intercostal
interval. Douglass Powell prefers a lower puncture, in the seventh or
eighth space in the posterior
axillary line. In the punctures
lower down the tube as it ascends rubs upon the diaphragm and protracts
the healing, and the orifice closes too early. The emptying of the sac
and the washings can be thoroughly attended to higher in the chest. The
weak point selected by nature for empyema necessitatis ought always to
be examined to see if there be any thinning of the wall, for if that be
the case, the puncture should be made there. The incision should be
made on a plane somewhat below that of the aponeurotic and muscular
portions of the chest, to prevent the liquids from infiltrating into
the subcutaneous cellular tissue. If we ascertain first by exploratory
puncture that there is pus lower down, it is safe to operate at that
point. The exterior orifice should be wider and larger than the
interior, and not parallel with it, in order to avoid the gaseous
infiltration in the tissues by the respiratory movements. Care must be
taken that the bistoury should pass close to the upper border of the
inferior rib, to avoid the intercostal artery. In making the
incision—about 6 centimeters in length—should the artery be cut, it
can easily be remedied by torsion. We raise the skin, and thus make a
flap over the orifice. The bistoury should not be introduced with one
cut through the soft textures, as recommended by Woillez, but layer by
layer should be cut through. This secures avoiding the intercostal
artery, and gives a larger exterior than interior cut, thus preventing
danger of liquid infiltration. We can be guided by the index finger,
and feel the textures as we cut down upon them. Under a continuous
spray to thoroughly purify the air that may enter, a free opening
should be made large enough to allow the finger to be introduced. As
air enters the fluid contents escape through the orifice, protected by
antiseptic dressings of gauze, oakum, and salicylated cotton. At first
it is well to remove the dressings containing the pus twice daily;
later, once daily will be sufficient. The orifice must be kept patent
by a short, wide tube with a fine wire around it. We can thus, by
changing the position of the patient, get rid of the contents of the
chest cavity. If there should be fetidity, it is desirable to use
washes of warm water first, and afterward of feebly-alcoholized
water—a solution of salicylate of soda, chlorinated soda, or
permanganate of soda. Cabot161 had most success in the use of sol.
chlorinated soda, one part to twelve or fifteen of water, for purposes
of injection. The average time that the tubes remained in, with his
cases, was only twenty-four days. His favorable results he imputed to
the mechanical action of the india-rubber covering over the antiseptic dressings.
160 Loc. cit.
161 Loc. cit.
Resection of Ribs.—The ancient operation of resection of ribs, dating
back to Celsus, is strongly advocated by Pietavy, Thomas of Birmingham,
Lane, and other modern writers as affording the best means of
thoroughly evacuating the pleural cavity of its purulent contents and
of keeping up constant drainage. John Marshall162 reports 4 cases
where he resected the ribs to make permanent openings. In all of these
cases the walls became gradually firm and new bone was formed. He
concluded that the removal of a portion of one rib was not sufficient,
but that a large space through four ribs is the proper size for the
opening, that the sixth rib is the essential one to deal with, and that
from one and a half to two inches of bone should be taken away. In one
case he performed a subcutaneous division of costal cartilage with a
view to weakening the thoracic walls and allowing them to fold in. A
number of cases are reported of resection of ribs, with varying
success, by Ewald,163 Taylor, House,164 and Thomas.165
Taylor166 advises the removal of the periosteum to prevent the rapid
re-formation of bone. If after the puncture the rigidity of the ribs
seems to keep up the discharge, and the lung does not expand to meet
the rib, a resection of a considerable portion of two or three ribs may
be
made for relief. If, again, in the progress of the case the
adjoining ribs have fallen in and have approximated, and thus become a
source of pain in retaining a permanent drainage-tube, a portion of rib
may be resected. The principal object of resection of ribs is to favor
their falling in, for a sufficient orifice can thus be made between the
ribs for the discharge. The upper two-thirds of the breadth of a rib
may be trephined in order to give more room for exploration,
evacuation, ablution, and prolonged drainage. This is the operation of
Esthander,167 who thus treated successfully 5 of his 6 cases operated
upon. Fenger of Chicago168 operated in this manner on fourth, fifth,
and sixth ribs.
162 London Lancet, March, 1882.
163 "Med. Soc. Berlin," Lon. Med. Rec., 1876.
164 London Med. Record, Aug., 1876.
165 Trans. Clin. Soc., vol. xiii.
166 Brit. Med. Journ., Feb., 1881.
167 "Resection du Côltes de Emp.," Revue Mens. de Méd. et
Surg., 1879, vol. B.
168 Med. News, Philada., Sept., 1882.
Jacobi169 says that resections ought not to be practised upon
children. W. A. Lane,170 from the observation of 5 cases of empyema
in children, strongly recommends that a portion of rib or ribs be
removed at first, and the cavity thoroughly drained from the beginning.
It assists, he argues, the cure by promoting the falling in of the
ribs, the expansion of the lungs, and the ascent of the diaphragm. In
children the difficulty in securing free drainage is that the spaces
between the ribs are small, and after the cavity is opened they become
much more contracted; soft tubes thus become compressed, and hard tubes
cause much local irritation. Resection of ribs enables the operator to
keep the orifice open and have perfect drainage. The opening should be
large enough to allow the introduction of the finger and of an
india-rubber tube of sufficient diameter to give free passage to the
contents of the chest, without the tube being displaced by movement of
the ribs. In only one of Lane's cases was trouble caused by rapid
increase of bone. He operated as low as the ninth intercostal space in
the axillary line, taking care always, by the hypodermic syringe, to
ascertain that there was pus at that point. He divided the periosteum
longitudinally, and removed with cutting forceps about three-quarters
of an inch of rib. After he had thoroughly cleared out the cavity he
introduced a short india-rubber tube, so that its inner end should not
project into the cavity. Wire sutures were passed deeply through the
intercostal tissues and tube, and, to render the position of the tube
more secure, soft pins were fixed through the wall of the tube, and
attached to them were pieces of elastic surrounding the chest.
169 N.Y. Med. Record, Jan., 1881.
170 Guy's Hospital Reports, vol. xli., 1882.
If necessary in order to have uninterrupted free drainage, children as
well as adults should have their ribs resected. The important point in
operating is to secure free exit to the fluid and purification of the
cavity by the necessary washings by the open method. Pleurotomy by
resection of ribs is almost universally acknowledged to be the most
effective treatment, for it promotes most rapidly the agglutination of
the pleural surfaces and the expansion of the lung.171
171 Lawson Tait strongly advocates this same method of
treatment in peritonitis. He has performed laparotomy successfully in
20 cases, using washings and drainage-tubes (Bost. Med. and Surg.
Journal, Aug. 16, 1883).
Good drainage is the essential consideration after the operation. We
must prevent putrefaction or fetid decomposition in the pleural
contents. So long as pus is retained within the sac, it does not
putrefy, but putrefaction follows contact with the putrefactive
agencies which abound in ordinary air, as shown by Pasteur and Tyndal.
These are solid particles floating in the atmosphere. Although air must
be admitted, it should be rendered aseptic. The drainage-tube, which
should be just long enough to go thoroughly into the cavity, by itself
is in many cases insufficient. The upper part of the cavity may retain
on its surface pus and flocculi which may prove dangerous. By the
syphon we can fill the cavity slowly with medicated tepid water without
shock and
without risk of tearing away the neo-membranes.
Woillez172 advises that pleurotomy should be promptly used whenever
pus is found. Béhier advocates the same treatment. E.
Moutard-Martin,173 whose authority is high from his great experience
and conservatism, advises us always to commence the treatment with
thoracentesis by aspiration. He says, if the fever persists and the
general condition grows worse, he does not hesitate to resort to
pleurotomy. The author's more limited experience coincides with his. I.
Marshall174 states as his opinion that purulent pleurisies require
the immediate or early adoption of the open method. In fibro-serous
pleurisy we wish to restore the physiological condition of the pleura,
whereas in purulent cases the object is to obliterate the sac by
adhesions throughout the surfaces, just as abscesses are cured. It is
necessary that the costal and pulmonary pleura and that of the
diaphragm should be brought closely in contact. This is produced
simultaneously by the dilatation of the lung and the diminution in
every way of the pleural cavity. The dilatation is produced by the
disappearance of the intra-pleural pressure and the pressure in the
opposite direction from the bronchial surfaces. This last depends upon
the condition of the lung and of the visceral pleura. If the lung has
been long compressed, it is almost carnified and reduced to a state of
foetal atelectasis. It rarely happens that the bands which bind the
lung down do not in time undergo granular fatty degeneration and
disappear. This enables the lung to expand, if not to its original
size, yet sufficiently to occupy the cavity, reduced in size by the
approach of the walls. The heart, which previous to the operation was
thrown more or less out of its normal position, comes back from the
empty side, and often passes the position that it normally occupied.
The lung follows the heart. The whole mediastinum finds itself altered
in its position and in its contents. The depressed diaphragm rises
promptly to its old position in the pleural cavity. The liver, spleen,
and the rib-wall undergo striking modifications. We do not expect the
lung to dilate to its full extent, as after aspirations in simple
pleurisies. The lung, indeed, is already impaired in its movement. We
admit air in order to secure treatment to these surfaces. When air is
admitted into the normal chest, the lung is retracted to about one-half
its size. In serous effusions we fear free admissions of air, because
it assists in compressing the lungs, and may contain germs which
promote suppuration. We must bear in mind that we may have double
pleurisy from the pus producing pleural necrosis at the point of
contact of the pleural sacs about the middle of the sternum opposite
the middle of the third rib. Elsewhere there is no such danger, for the
pleural surfaces remain a long distance from each other.
172 Bul. Soc. Méd. des Hôp., 26 April, 1872.
173 Pleurisie purulente, 1872.
174 Loc. cit.
Why should we postpone pleurotomy, with or without resection of ribs,
until we have used the drainage-tube, canula, etc.? The impression is
that this operation is attended with danger, whereas ordinarily, with
care, such is not the case. In pleurotomy there is not the same danger
of serious accidents as in thoracentesis, especially as performed by
canulas and trocars. Pleurotomy never causes acute oedema of the lung.
The forcible unfolding of the lung, with rush of blood to vessels that
have been almost emptied by compression, does not occur under these
circumstances. After the large openings of the chest the causes of the
forced expansion of the lung do not exist. The diminution of the
pressure on the mediastinum, the re-establishment of the thoracic
aspiration, and consequently the more free access of venous blood into
the right heart, favorably influence the general circulation. The pulse
increases in force, the cyanosis is dissipated, frequently within a few
hours, and the anasarca disappears in a few days.
Theory and observation show beyond a doubt that in all cases where
there exists a decided intra-pleural tension pleurotomy of the
thorax modifies efficiently the circulatory and respiratory functions.
Instead of causing suffocation, it diminishes almost always, and that
instantly and remarkably, the dyspnoea. In 1868, Maisonneuve175 made
the startling announcement, which he claimed was nevertheless rigidly
true, that of 100 patients who die after surgical operations, 95 are
poisoned by organic substances absorbed. He claimed that the liquids
exuded from the surface of wounds become corrupt when exposed to the
external air, and that subsequently they undergo morbific changes and
become formidable poisons. If, he said, we can prevent the dead liquids
from putrefying, the gravest operations could be performed without
danger. No one who studies the results of empyema in the past can
question that the greatest danger is from the blood-poisoning known as
septicæmia, caused by the absorption of the septic infection by the
lymphatics.176 No matter what may be the nature of septicæmia, it is
sufficient that the vast surfaces of the pleura produce certain
prurient secretions, which, when absorbed and carried into the
circulation, cause hectic fever with its results. We claim that there
is less danger from putrid absorption when free incisions are made than
from those only large enough to introduce a drainage-tube. Rome177
collected 49 cases, but of these 10 contained fetid pus; 9 of the
number had been treated by one or many, even up to fifteen,
aspirations. He concludes that the surgical interventions, other than
pleurotomy, provoked in the purulent liquid of the pleura putrid
fermentations in one-fifth of the cases. The products of this
fermentation irritate actively the serous membrane, and cause an
abundant suppuration intractable in its nature, and there is imminent
danger of rapid exhaustion and hectic fever. One-third of Rome's cases
contained solid pieces which could not be removed in any other way than
by making free incisions. Although subserous cavities are not perfectly
analogous to phlegmonous abscesses, yet they closely resemble each
other. Histologically, the inflammatory process and its phases are the
same, but there is this difference—absorption of the deleterious
products is more active. Why allow a warm abscess to be transformed
into a cold abscess, which will open later spontaneously after having
caused grave disorders? We have seen how frequently large collections
of pus sooner or later open either through the lung or through the
chest-walls. If an opening has to be made, the more promptly the
better. In the first stage, especially in acute purulent pleurisy, the
slight neo-membranes and fibrinous deposits, barely solid, readily
undergo granular fatty degeneration, and are absorbed if relieved of
the pus. In this stage the two folds of the pleura are in their best
condition for becoming adherent to each other, and by obliteration of
the pleural cavity to end the disease. If acute empyema be treated
early and gently before the lung is compressed or injured, with free
opening and constant drainage, the patient being in a recumbent
position on face or side, the pleura needs no washings. The orifices
made spontaneously are frequently insufficient to completely empty and
to keep up the current of pus as it forms. In bronchial fistula, unless
the air is prevented from coming from the lung into the pleura by a
valvular opening, we have frequently to resort to pleurotomy. If in
empyema necessitatis the orifice partly closes or is not free enough,
we must not hesitate to enlarge it or make a counter-opening to enable
the matter to flow out. In tubercular pyo-pneumothorax, where the
purulent fluid has been the primary lesion and has perforated the lung,
the operation is not indicated. E. Moutard-Martin's treatise was
founded upon 17 subjects, 5 of whom died and 12 were cured. Of the 12
cured, 2 had bronchial fistula in pneumothorax without any sign of
tubercle; 5 had permanent fistulous openings and discharged
occasionally a few drops of pus; 7 were cured without fistula.
Blake178 reported 19 cases treated by permanent openings, with 15
"cured and much relieved." He operated by making incisions from one to
two inches long, parallel with the ribs, between the seventh and eighth
ribs, a little inside of the scapula. His practice was to keep the
orifice open. He used either a spiral wire covered with gutta-percha or
a gum-elastic catheter fastened to a shield and kept in position by
adhesive plasters. Martin Oxley179 by pressing open the incision with
a pair of dressing forceps introduced a silver or india-rubber
tracheotomy-tube to keep the orifice open. He related several instances
where pieces of tubing fell into the cavity and remained there without
injury for months, and in one case as long as several years.
Dabney180 urges with force the importance of our having a continuous
discharge of pus as far preferable to its daily removal, "not only
because it seems less liable to become fetid, but because, as the two
surfaces of the pleura have to come together and heal by granulations,
the retention of pus would delay this process by keeping the costal and
pulmonary surfaces apart." Thorough drainage by two orifices or a wide
incision kept open by two tubes is more effective than a simple
drainage-tube. Antiseptic precautions are essential to ensure success
at every stage of the operation.
175 London Prac., 1868.
176 Ranney, Annals of Anat. and Surgery, 1881.
177 Thèse de Paris, 1882.
178 Boston City Hospital Reports, 2d series.
179 Liverpool Medico-Chirurg. Journal, January, 1882;
N.Y. Medical Abstract.
180 American Journal Med. Sciences, Oct., 1882.
Value of Injections and Washings.—The object of injections is to
enable us thoroughly to wash out the cavity and to promote adhesions
between the pleural surfaces. The chief danger being from septicæmia,
it is of the greatest importance that the pus should not be allowed to
remain in the cavity longer than can be avoided. The body-temperature,
taken twice daily, is one of the best means of ascertaining the extent
of the re-formation of pus. Stagnant pus, mingled with air, will
undergo fermentation and cause putridity; hence the great value of
incessant drainage through unobstructed tubes. When the pus is free
from unpleasant odor and runs freely, it is not necessary to use
washings or injections of any kind, for the cavity will purify itself.
Washings and injections have sometimes been found very injurious and
irritating, and sudden deaths have been attributed to them. If flocculi
form, washings of tepid water with a very small percentage of alcohol
or of salicylic acid (1 per cent.), used without force for fear of
rupturing some of the recently-formed capillaries, are useful. When
modifying injections are used, the patient ought to lie on the opposite
side. In this way all the diseased parts are reached by the fluid. An
ordinary syringe should not be used, but a Thudicum bottle or a
fountain syringe: either of these can be raised sufficiently high to
allow a gentle flow into the cavity. If the discharge becomes fetid,
injections of solution of permanganate of potash (1 or 2 grains to
ounce j) or of tinct. of iodine (1:4) in water ought to be used. The
author has never seen any results of poisoning from the use of carbolic
acid, but he has always used a feeble solution, 2 or 3 per cent. Dabney
had symptoms of carbolic-acid poisoning in one of his cases where he
used a 2 per cent. solution, notwithstanding the fact that he had taken
every precaution to ensure its prompt return. A. T. Cabot181 mentions
a case of carbolic poisoning in a boy four years of age produced by a
feeble solution of one part to thirty of water used only to cleanse the
instruments, tubes, and hand of the operator. Kuster's182 experiments
show that anæmia and septic and pyæmic fevers predispose the system to
carbolic-acid poisoning. He recommends an 8 per cent. solution of
chloride of zinc. Chlorate of potassium drachm j to pint j has been
used with benefit. The medical journals contain so many reports of the
serious, and even fatal, results from absorption of carbolic acid when
thrown into abscesses
that we are compelled to abandon it in
favor of other injections. B. W. Richardson long since showed the great
value of iodine as a disinfectant. It not only corrects the fetor of
decomposed pus, but at the same time lessens the secretion from the
walls. The first injections should be weak, gr. 4 or 5 of iodine and
iodide of potassium to a pint of water. Liq. iodinii com., ounce ss to
ounce iv, ought not to be used until the surfaces have become
accustomed to the action of iodine. Injections of medicated fluid ought
not to be used unless they are absolutely necessary, because in some
instances they have produced fainting attacks and epileptiform seizures
with alarming convulsions. These results have followed injections of
different fluids—borax, carbolic acid, iodine, permanganate of
potassium, and even warm water. Similar phenomena have followed the
injection of the bladder, the uterus, and even from passing a catheter.
The shock may have been too sudden or the injection too forcible or the
fluid too cold. A. L. Mason183 suggests that it is probably owing to
sudden irritation of the lymphatics through the great splanchnic nerve,
with anæmia of the brain. Paralysis of the limbs after convulsions
makes the theory of embolic origin probable. These accidents must not
make us underrate the great value of frequent washings with injections
when rendered necessary by the approach of putrid infection. The number
of these washings should depend upon the urgency of the symptoms, and
antiseptic injections should not be employed unless we find evidences
of fetor, because of one great objection: they do not favor the
expansion of the lung.
181 Loc. cit.
182 Quoted by Dabney, loc. cit.
183 Boston City Hospital Reports, 2d Series.
Cases of long-standing compression of the lung could hardly result in
complete re-expansion, but the general health will be recovered and the
chest, contracted by approximation of the pleural surfaces from the
walls being pressed in or ribs resected, will cease to secrete pus. If
fever persists, with diarrhoea, sweats, emaciation, and fetid
suppuration, it shows that the washings are not sufficient in number.
They can be repeated as often as every three or four hours, to be
decreased in frequency as the patient improves. Under frequent washings
Feyrot184 reports favorable results in almost hopeless cases. Time is
very precious when these symptoms of exhaustion or septicæmia set in,
as it is of the utmost importance that we should endeavor to prevent
promptly the absorption of the putrid products, the inevitable effects
of which are to produce, before long, fatty and amyloid degeneration of
the principal viscera. The most effective way of using detergent fluids
is by syphons through two tubes perforated at their extremities and
fastened with shields. A Thudicum douche-bottle or a fountain syringe
can easily be used by patients themselves as often as is required. The
orifice and the tubes should be protected by thorough and rigid
antisepticism. As the case improves the cavity gradually gets smaller,
the two pleuræ become adherent, and the quantity of fluid lessens until
only a small amount flows out. Every eight or ten days we carefully
draw out the tubes by degrees, until we have only a little canal
beneath the walls. We can thus let the orifice heal slowly, for the sac
is obliterated and the patient cured.
184 Thèse de Paris, 1876.
In the hands of Boyer, Delpech, Dupuytren, and Sir Astley Cooper the
bistoury gave bad results, but as now used, with all modern appliances
and antiseptic precautions, it affords infinite relief and many cures.
We claim that by early pleurotomy, with Listerism scrupulously used at
every stage of the operation, and if necessary with detergent washings,
the mortality from this extremely grave disease can be very materially lessened.
Pleurisy may occur on both sides at the same time. Double pleurisies
are secondary, not primary, and result from rheumatism, or still more
frequently,
according to Louis, from tuberculosis. In 150 cases
of pleurisy quoted by him, there were no bilateral cases which were not
produced by rheumatism, gangrene, or tuberculosis. A double pleurisy in
a previously healthy person creates a strong suspicion of tubercular
origin. There is generally an interval of some days before the attack
of one side is followed by that of the other. When effusion takes place
the dyspnoea is very great. Death is imminent unless the fluid is
withdrawn by aspiration. Maintenon185 states that the inflammation
may be so intense and the fever so high as to destroy life before the
effusion is thrown out. The physical signs are the same as in
unilateral cases. The effusion is never so great on one side as on the
other. The progress of disease is rapid, and the result is almost
always fatal.
185 Thèse de Paris, 1873.
The serous lining of the upper surface of the diaphragm may be involved
in an ordinary pleurisy, or inflammation may be limited to it without
involving either the pulmonary or the parietal membrane. In this latter
case we have modifications of the characteristic symptoms and physical
signs. Functional disturbances and special symptoms enable us to
diagnose it. There is a febrile movement with occasional delirium, and
some of the prominent symptoms, but without the physical signs to
indicate the exact locality. The pain is intense, and dyspnoea exists
even to the extent of orthopnoea and respiratory anguish, the
respiration jerky and convulsive. The pain comes on suddenly in one of
the hypochondriac regions, extending up to the attachments of the
diaphragm to the costal surfaces. The pain is intense, and increased by
full inspirations, by physical efforts, by vomiting, and even by the
eructations of wind. The position of the patient attracts attention: as
he sits with the trunk inclined forward, he has an anxious and
distressed expression of countenance, sometimes accompanied by nausea
and vomiting with singultus. Pressure elicits a characteristic
tenderness; if applied under the false ribs, it causes suffering. The
phrenic nerve is painful on pressure practised over the accessible
points of its course, between the two inferior bands of the
sterno-cleido-mastoid at the base of the neck. There are also painful
irradiations in the cervical plexus above the clavicle and in the
scapular region. Pressure over a circumscribed spot of the epigastric
region causes a sharp agony of pain. This point is at the intersection
of two lines—one, the external border of the sternum; the other, at
the osseous portion of the second rib. Guéneau de Mussey186 has named
this the diaphragmatic bottom. This pain extends sometimes to the
vertebra and upward to the first intercostal space. Auscultation and
percussion at the base of the lung give us some results: impaired
expansion of the lung at the base and dulness on percussion; the
diaphragm is in a great degree immobile, owing partly to the pressure
upon it, and partly to a paresis from inflammation of its upper serous
covering (Stokes187). When the inflammation is on the right side, we
may find an icteroid tint, with vomiting, delirium, etc., with the
liver pushed below its normal position in the abdomen. The inflammation
of the pleural covering of the diaphragm may be caused by
sero-hepatitis extending through the diaphragm (Copeland188).
186 Archiv. de Méd., 1879, vol. ii.
187 Dis. of Chest, 1837.
188 Dict. Med., vol. iii., edited by Lee.
If the effusion is confined to the space between the lung and
diaphragm, the diagnosis is obscure. There may indeed be cases where we
have but few of the symptoms already mentioned. If the fluid is not
confined to this portion, but flows into the pleural cavity, it gives
great relief, and the result is favorable. Diaphragmatic pleurisy may,
however, end in death, either by its discharge into the peritoneal
cavity or by constitutional disturbances.
Interlobular and Mediastinal Pleurisies.
The effusion is sometimes confined by adhesions between two lobes. The
mediastinal variety is situated between the pleural boundary of the
mediastinum and the adjacent portion of the pulmonary serous membrane.
It is but rarely met with, and may be diagnosed by local symptoms. The
flatness on percussion in the interlobular variety is very
circumscribed. Both forms cause local pains, but in the mediastinal
variety the pain is very deep and perceptible at the middle of the
sternum, and is increased by the respiratory movements. In both
varieties there is more or less fever. If either variety exist on the
left side, the condition of the pericardium must be carefully examined,
as pericarditis may be confounded with it. These limited collections of
fluid may burst into a bronchus and be expectorated.
Multilocular Areolar Pleurisies.
Multilocular encysted collections of fluid in the pleural cavity are
due to the partitions made by pseudo-membranes which divide the pleura
into subcavities. These occur generally in subjects who have had
previously dry or adhesive pleurisies. They are more serious than
ordinary pleurisies. We meet with them in aspirating, when, after
draining off the fluid from the base of the pleural cavity, we find the
lung expanding, but above that point there is absence of respiratory
murmur and of other physical signs indicating the presence of fluid.
Reybard189 divides multilocular pleurisy into three varieties, with
varying symptoms and physical signs, according to whether it exists at
the upper, middle, or lower portion, right or left side. Owing to the
thickness and distribution of neo-membranes, it is frequently difficult
to localize the points of collections of fluid. Aspiration is the most
accurate means of ascertaining the exact point and extension of the effusion.
189 Bullétin Acad. Méd., 1879.
HISTORY.—The recognition of the fact that we can have local
manifestations of rheumatism in the texture of the lung itself, of the
bronchi, and of the pleura is of comparatively recent date. There had
been indefinite, loose statements, or rather suggestions, in some of
the writers in the early part of the century, such as Chomel and
Andral, as to the possibility of rheumatism appearing in the pulmonary
textures; but we believe that the first definite description of the
disease was made by T. H. Buckler of Baltimore in 1865.190 He claimed
that the white fibrous tissue of the bronchi could be the seat of
rheumatism, as well as similar textures about the joints. He
illustrated his views by cases observed and reported by himself. He
showed how, as a result, there were symptomatic engorgements, more or
less solid, of the pulmonary parenchyma or rheumatic pneumonia. In
1854, Black191 found crystalline particles of uric acid and of urate
of soda deeply imbedded in the thin white fibrous tissue of bronchi.
Buckler showed the metastatic character of rheumatic inflammation in
the bronchi and lungs as elsewhere. Buckler's subsequent papers192
published in connection with this subject, show remarkable success in
treatment of fibro-bronchitis and rheumatic pneumonia based upon his
views of their pathology.
190 Fibro-Bronchitis and Rheumatic Pneumonia.
191 Edin. Med. Journal, 1854.
192 Boston Med. Journal, 1882, and Amer. Med. Journal,
Oct., 1882.
SYMPTOMS.—We find rheumatic pleurisy coming on in the course of
rheumatic fever with the characteristic mobility of the points of
inflammatory action. Laseque193 gives the symptom with accurate
details—the acute pain in the side of the chest without cough or
expectoration. He describes the pain as differing from that of ordinary
pleurisy, in that the extent of pain is greater and not so limited, due
to the fact that the rheumatism invades the aponeurotic tissue which
forms the covering to the intercostal muscles. It persists longer and
is wider spread. The dyspnoea is caused by the inability to move the
respiratory muscles and by the disease invading the aponeurotic centre
of the diaphragm.
193 "Pleurésie rheumatismale," Arch. Gén. de Méd., 1873.
The rapidity of the inflammation causes the sudden pain and the
accompanying effusion in even a few hours. In a well-defined case
recently seen by the writer in a lady forty-seven years of age the
rheumatism literally jumped from a large joint to the pleura, giving
rise to a severe pain, without cough or expectoration, with an increase
of 2° of temperature and 20 beats of pulse. There was a moderate
effusion. In forty-eight hours, under the influence of an initiatory
dose of quinine (20 grains), followed by free doses of salicylate of
sodium, the attack subsided and the friction sound at the base of the
lung disappeared. This case did not follow the rule mentioned by
Senx,194 that the disease, upon leaving the pleura of one side,
appears in the same manner on the other. It sometimes goes to the
pericardium and endocardium from the pleura. Chomel195 insisted upon
the frequent examination of the heart to ascertain whether this had occurred.
194 De la Pleurésie rheumatismale, Paris, 1878.
195 Art. Pleurésie Dict., in 30 vols., 1842.
Rheumatism of the pleura does not always appear and disappear suddenly.
It sometimes is gradual in progress and slow in recovery. It usually
occurs when we have manifestations elsewhere, but the pleura may be the
point first attacked, as is more frequently the case in pericarditis.
DIAGNOSIS.—The diagnostic signs are hereditary or personal tendency to
the disease, the character of the local pain, the mobility of the
disease, violence of pain and its rapid disappearance, and the
existence of profuse sweats. Suppuration rarely occurs.
PROGNOSIS is in its nature serious, not from the intensity of the
disease, but from its being a visceral rheumatic affection. It is,
moreover, frequently double, and may recur often in the same subject.
TREATMENT is that of rheumatism elsewhere—salicylic acid and its
salts, alkalies with opiates. Thoracentesis is rarely indicated,
because mechanically the effusion does not seriously impede
respiration: if the pericardium be involved, it may be necessary in
order to relieve the pleura or the pericardium.
DEFINITION.—Pleurisy complicated by hemorrhage. Hemorrhagic pleurisy
is the union of an ordinarily slight hemorrhage in the pleura with
inflammation of that membrane (Laennec).
ETIOLOGY AND PATHOLOGY.—These must be studied together, because the
pathology of the disease explains its etiology. While hæmothorax
designates hemorrhage into the pleural cavity without inflammation,
hemorrhagic pleuritis involves necessarily the idea of inflammation
accompanied by effusion of blood, whether this occurs before, during,
or subsequently to the inflammation. We cannot assign the name
hemorrhagic pleurisy simply because there may be slight red coloration
of the effusion. Microscopic researches have shown that all effusions,
even the simplest, contain more or less white and red blood-corpuscles.
The presence of a certain number of the red discs no more justifies us
in calling the pleurisy hemorrhagic than the presence of
the
leucocytes would entitle us to call it purulent pleurisy.
Dieulafoy196 states that there can be from 500 to 4000 red globules
to the cubic millimeter without producing any coloration. They must
reach 5000 before they will really attract attention. He says, however,
that when the number of red corpuscles reaches 2000 the effusion is
"histologically hemorrhagic," because the presence of blood is
analogous to the state of engorgement or congestion of the first stage
of pneumonia or other phlegmasia, and constitutes a particular phase of
pleurisy which must produce purulent matter. The name hemorrhagic
pleurisy ought to be used when the number of red blood-corpuscles is
sufficient to enable us, by the unaided vision, to detect the presence
of blood. We may, however, find a fluid in the pleural sac which is red
and yet does not contain blood-discs, but their coloring principle, the
dissolved hæmatin. Jaccoud197 designates this condition
pseudo-hemorrhagic pleurisy. Vulpian and Charcot explain the slight
discoloration by the presence of hæmatin crystals, which, having been
imbedded in the false membranes, escape into the flow of the chest.
Nolais198 included both of these discolored effusions among the
varieties of hemorrhagic pleurisies: "Hemorrhagic pleurisies include
all those of which the liquid borrows the red coloring matter of the
blood." Moutard-Martin (R.)199 divides hemorrhagic pleurisy into
three varieties: simple, as produced in simple, acute, or subacute
pleurisy; tubercular; and cancerous. Trousseau200 considered all
hemorrhagic pleurisies as caused by cancer. Beigel201 states
positively that in cancerous pleurisy the effusion is limpid with a
yellowish tinge. Walshe202 held the same views. Nolais,
Moutard-Martin (R.), and Fernet satisfactorily demonstrated that such
is not the case, but that the hemorrhagic effusion may be simple and
independent of any organic disease. It may be produced by acute
inflammations of the pleura as well as by cancer of the lung or pleura.
It may be connected with pleuro-pneumonia or miliary tubercle. It
comes, although more rarely, from fevers, such as measles, and from
certain dyscrasiæ due to renal, hepatic, or even splenic lesions. When
hemorrhagic pleurisy follows hæmothorax, the blood, after remaining
liquid at least one or two hours, initiates the inflammatory action
which has, according to Ch. Nélaton,203 for its object the encystment
of the clot. Cornil and Ranvier204 claim that the cyst is caused by
the retracted clot, and that after absorption of the serosity this cyst
may become organized. The presence of air causes fetidity of the blood
and purulent pleurisy.
196 De la Thoracentèse par Aspiration dans la Pleurésie
aigue.
197 "De l'Humorisme ancien comparé à l'Humorisme moderne,"
Thèse de Concours, 1863; Gazette Méd., 1860, quoted by Nolais.
198 Thèse de Paris.
199 Thèse de Paris, 1878.
200 Clin. Méd.
201 Reynolds's Syst. of Med., 1871.
202 Dis. of the Chest.
203 Thèse de Paris, 1880.
204 Path. Anatomy.
We may have hemorrhagic effusions occurring simultaneously with acute
pleurisy, with pulmonary congestions, pneumonias, and apoplexy of the
lung. They are caused by the violence of the inflammation with local
plethora, producing a sanguinary stasis—a mechanical result of intense
congestion. Moutard-Martin (R.) states that in these cases the red
globules come through the walls of the blood-vessels, as do the
leucocytes, by diapedesis. Jaccoud205 admits that the blood-vessels
are altered by the inflammation, perhaps also by the derangement in the
vaso-motor innervation. The tissue of the pleura is penetrated by both
red and white blood-corpuscles, and the blood-vessels and lymphatics
are dilated, red corpuscles being found in lymphatics. By far the
greatest number of hemorrhagic pleurisies are secondary to pleural
inflammations, either resulting from acute causes or from cancerous or
tubercular disease, or from diseases causing a dyscrasia of the blood,
such as nephritic diseases, hepatic, cardiac, scorbutic affections, or
alcoholic excesses. The secondary result of these pleurisies is the
formation of neo-membranes, fibrous
in their nature, which
pathological anatomy shows contain, as they become organized, abundant
blood-vessels with thin and brittle walls. A slight exciting cause is
all that is necessary to produce their rupture. The primary cause is
the false membrane, and, in some cases, vascular granulations, which
have rapidly formed, perhaps in twenty-four hours—conditions eminently
favorable to the production of hemorrhage. In cancerous, tubercular,
and dyscrasial conditions of the blood, the blood-vessels are
especially weak and easily give way, owing to the defective nutritive
properties of the blood itself, just as, in typhoid fever, we have
nasal and intestinal hemorrhage, and in typhus, petechiæ. In 200 cases
collected by Moutard-Martin206 there was found intra-pleural effusion
in three-eighths of the cases. Only one-third of that number were
hemorrhagic. In 42 cancers observed between 1872 and 1876, 35 were
without pleural effusion, 1 only was hemorrhagic. M. Moutard-Martin
reports 34 observations of hemorrhagic pleurisy produced by cancer, 19
by tubercle, and 31 following simple pleurisy. Of these last there were
7 cases of effusion complicated with a pneumonia, 3 with a cirrhosis, 6
with a cardiac affection: all except 12 of these cases had some
complication. Most of these (12) recovered, so he had not the autopsies
to verify his diagnosis. Rayer207 cites 4 cases of bloody effusion in
the pleura occurring in the course of a nephritis. Poutin208 reports
1 in renal sclerosis. M. Natalis-Guyon209 reports an epidemic of
measles where many infants died of hemorrhagic pleurisy. Marguerite
cites 13 cases complicating pneumonia, granulations, chronic pleurisy, small-pox, etc.
205 Clin. Méd.
206 Loc. cit.
207 Traité des Mal. des Reins.
208 Soc. Clin. de Paris, 1879.
209 Soc. Méd. des Hôpitaux.
Rilliet and Barthez210 say that it is common to find in infants
considerable discoloration of effused serum in variolic and other
organic poisons. It seems fair to conclude that hemorrhagic pleurisy
may occur in a large number of cases where the blood has undergone
alterations, but to produce it, it is necessary that the pleura should
have been rendered vulnerable by pre-existing causes, because it
ordinarily resists, better than many other membranes, the hemorrhagic
tendency. If we admit the existence of tubercular or cancerous
hemorrhagic pleurisies, we ought not to consider those as simple which
are produced under the influence of the other causes that we have
mentioned. The tubercular granulations are deposited either on the
pleural surface or in the parenchyma of the lung near the surface, the
most frequent locality being in the thickest parts of the organized
false membranes. The rupture of their blood-vessels causes the escape
of blood into the pleural cavity. The effusion, more or less
discolored, rarely exceeds a liter in quantity. Effused blood from
cancerous origin may either come from rupture of the vessels in the
growths themselves by ulceration, or from the neo-membranes in their vicinity.
210 Traité des Mal. des Enfants, t. iii.
The primitive seat of the cancer is rarely in the pleura, but most
frequently in the lung, the cancer being of secondary formation arising
primarily from ganglions of the mediastinum. Hemorrhagic pleurisy may
be caused by laceration of the newly-formed blood-vessels in the
neoplasms by aspiration or by the lung expanding too suddenly. We
conclude that hemorrhagic pleurisy is generally owing, directly or
indirectly, to vascular neo-membranes which are produced in simple, in
tubercular, and cancerous pleurisies.
SYMPTOMS.—The symptomatology of this form of pleurisy does not differ
materially from that of other varieties. We cannot attach much
importance to the initiatory symptoms nor to the march of the disease.
If the quantity of blood be great, we must expect general weakness,
pallor, and even fainting. We may have oedema of the walls, as in
purulent pleurisy, and exceptionally in serous pleurisy. Ordinarily,
however, hemorrhagic pleurisy is more extensive, and limited to the
inferior part of the chest, owing to the interference with the venous
circulation. If cancerous in its origin, we shall have dyspnoea
and violent intercostal neuralgia from pressure of the tumor. When the
effusion is formed in the pleural sac, the physical signs already
enumerated indicate its presence. Some authors, especially Fernet,
Moutard-Martin, Alcoud, and Guéneau de Mussey, attach considerable
significance to Bacelli's whisper-pectoriloquy as showing that the
effusion is not serous in character. Nolais questions this view, and
says that this sound ought to be heard whenever there is blood, whereas
they state it is heard only at the base or summit of fluid. When
hemorrhagic pleurisy results from tuberculosis, it is never from the
ordinary ulceration form, but always from the acute miliary,
non-ulcerating variety. We must not, therefore, expect to be aided in
our diagnosis by the progress and symptoms of pulmonary phthisis. We
may, however, detect uncertain, indefinite symptoms which are hard to
interpret as indicative of tuberculosis. The effusion is rarely
excessive in this variety, whereas when resulting from cancer it is
often very abundant and is rapidly reproduced.
DIAGNOSIS.—We may suspect the presence of hemorrhagic effusions, but
only by exploratory punctures can we arrive at certainty of diagnosis.
We must bear in mind that we may withdraw with the aspirator-needle
some drops of blood at its insertion and at the close of the
exploration from the highly vascular neo-membranes or from the lung
itself. Having ascertained the nature of the fluid, the differential
diagnosis must be made as to the cause, simple, tuberculous, or
cancerous. We must study the manner of access of the disease, and
especially ascertain if its invasion was violent, with a quantity of
blood (d'emblée), or whether it came from the neo-membranes. In the
simple variety there are the ordinary acute or subacute symptoms of
pleurisy, without any preceding symptoms. In cases of tubercular origin
we have to aid us a small quantity of fluid effused and the insidious
character of symptoms. In cancerous cases we must expect to find traces
of hereditary or of personal taint which may have affected the general
health. We must look for cancer elsewhere, and examine carefully to see
if there be any tumor of the mediastinum or intra-thoracic pressure, or
any infiltration of the lymphatic glands, especially above the
clavicle. The fluid drawn in the exploration ought to be examined
microscopically, for we may detect evidences of cancer. Walshe211
cites a case where encephaloid débris was thus discovered. Other
authors also give similar cases.
211 Diseases of the Chest.
PROGNOSIS.—This depends upon the nature of the disease producing it.
When caused by the newly-formed membranes connected with simple serous
pleurisy it is ordinarily not serious, for the mere presence of blood
in the pleura has no bad influence over the restoration of health. It
is more the intensity of inflammation, with the quantity of blood
effused, that indicates gravity of prognosis. Dieulafoy212 considers
the prognosis as unfavorable in the hémorrhagie d'emblée form, drawing
the distinction between this and the histologically hemorrhagic. He
thinks that every purulent pleurisy was at first hemorrhagic, and the
presence of pus shows greater intensity of inflammation. Homolle213
also states that the pleurisies rich in red globules are ordinarily
very acute, and, in consequence of that fact, predisposed to purulence.
Purulency is not the sole cause of danger. We fear compression of the
lungs, and still more septicæmia. In the tubercular and cancerous forms
the prognosis must be very serious. When the hemorrhagic pleurisies
arise in the course of organic diseases of the heart, kidney, and
liver, they are of grave import.
212 Loc. cit.
213 Rev. des Sci. Méd., 1880.
TREATMENT.—If the quantity is excessive, local applications and ergot
ought to be employed to arrest the flow. If the dyspnoea and oppression
are great, it is best to draw off at least some of the fluid. If the
quantity be not large enough to embarrass respiration, we must expect
nature to absorb
it, or by local inflammation to encyst it.
Lacaze214 reports a case where a fistula was established, and the
case was cured. Dieulafoy gives another case where six punctures were
made, and no less than 6 liters, in all, were withdrawn. He injected
afterward a solution of 4 grammes of sulphate of zinc to 400 grammes of
water, and the patient was cured. In the first stage of the disease we
use palliatives—morphia hypodermically, bromides, and chloral—if
indicated. During febrile symptoms of acute cases we refrain from
withdrawal of fluid unless it is excessive. The question of
thoracentesis has been discussed in regard to simple pleurisies. The
same rules apply, a fortiori, when the nature of the fluid is
hemorrhagic. Ordinarily, the abundance of fluid, and the dyspnoea which
results therefrom, indicate the operation. We prefer not to draw off
the fluid completely—only enough to relieve the embarrassment of
respiration—because we destroy the equilibrium of pressure on one side
against the neo-membranes and the compressed lungs on the other.
Congestion of the lung may thus be produced with albuminoid
expectoration. Moutard-Martin (R.) coincides with Dieulafoy in limiting
the amount to be withdrawn to one liter. Of course the fluid is slowly
aspirated. After part of the fluid is withdrawn, what remains is
absorbed, remains stationary, or increases in quantity. We repeat the
operation, and slowly draw off greater quantities of fluid if it
returns; especially in cancerous cases, where the effusion is often
very large, the operation gives great relief. It is rarely large enough
in tubercular cases to justify thoracentesis.
214 Thèse de Paris, 1851.
Tubercular pleurisy may be acute or chronic. It may occur during the
course of ordinary tubercular disease of the lung, by extension of the
disease from the lung to its serous covering, or it may proceed from
tubercular deposit on the pleura independently of any previous disease
of the lung. Acute tubercular pleurisy may be dry and situated at the
summit of the chest, or may be what is called accidental pleurisy. Dry
pleurisy is almost constant in tuberculosis of the lung. Its existence
is, in itself, a powerful presumption of pulmonary phthisis, especially
when it is situated at the apex. In tuberculosis pleuritic inflammation
is lighted up by slight and scarcely appreciable causes. Its
commencement is insidious, with little or no pain or fever: indeed, it
is with subacute symptoms that the disease slowly advances. The first
intimation the patient has of the disease is the impairment of his
breathing-power by the presence of fluid. The fluid is not generally in
large quantities, and is serous or sero-fibrinous, and sometimes
sero-purulent. Latent pleurisy of the older writers was frequently
tuberculous in its origin. This form of tuberculosis may precede or
follow the deposit of tubercles in the lung-tissue. The tubercles may
be deposited to a slight extent in the tissue of the lung, and their
presence is shown by an irritating cough only when the pleurisy
approaches insidiously. The tubercular granulations over the visceral
pleura are extended to the parietal surface also, and notably to the
circumference of the fibrous leaflet of the diaphragm—an especial
point of elevation for the secondary products.
This disposition of tubercular lesions of the pleura is one of the most
striking examples of what is called infection from contiguity, and is a
powerful proof of the infective property of tubercular products which
from an initial nucleus is propagated from point to point. Acute
tuberculosis of the pleura is one of the most common manifestations of
acute phthisis. It more frequently causes acute than subacute pleurisy.
Chronic tuberculosis almost always produces purulent pleural effusions.
It is much
more common in infants than in adults, and is
sometimes met with in children from three to ten years of age (Barthez
et Rilliet215). Tubercles may be developed in the intra- or
extra-serous membrane. Among old people the tubercle sometimes appears
first in the recent false membranes produced by pleuritis (as
associated with caseous pneumonia, or genuine tuberculous processes in
the lungs), or in connection with tubercles of other organs
(Fraentzel216). The advance of this disease is habitually slow, or at
least not accelerated by the development of other tubercular diseases.
The diagnosis is often accompanied with great difficulties, for the
disease may be confounded with chronic or with purulent pleurisy,
especially if these are developed in a tuberculous subject. In both
cases we have hectic, night-sweats, emaciation, etc. Thoracentesis
alone can give definite results when the effusion is in considerable
quantity. When suppurative pleurisy supervenes in tuberculous subjects,
the prognosis is very grave. Should the pus be sufficient in quantity
to embarrass respiration, it can be drawn off cautiously by aspiration.
The open method of drainage and free incisions should not be used, for
experience has shown that they injure instead of benefiting the patients.
215 Mal. des Enfants.
216 Ziemssen's Cyc., vol. iv.
From [Greek: hydôr], water, and [Greek: thôrax], the chest.
DEFINITION.—Dropsy of the chest. The accumulated fluid in the pleural
cavity which resembles the serum of the blood is not the product of
inflammation, but is caused by mechanical obstruction to the
circulation or by blood-poisoning. Hydrothorax is never idiopathic, but
invariably secondary, resulting from disease, not of the pleura, but of
the circulatory system or of the blood itself.
HISTORY.—Before pathological anatomy had been accurately studied,
effusions resulting from inflammatory processes in the pleura were
confounded with simple hydrothorax, which is not a variety of pleurisy.
Royer217 and Laennec218 divided hydrothorax into idiopathic and
symptomatic; Darwell219 adopted in a great measure their views. They
did not draw the distinction between the passive transudation of serum,
constituting the condition known as hydrothorax, and exudations
resulting from idiopathic pleurisy. Before physical modes of exploring
the chest were used there was great uncertainty in the diagnosis of
collections of fluid in the pleural cavity.
217 Dict. de Méd., 1832.
218 Dis. of Chest, Forbes's edition.
219 Cyc. Pract. Med.
ETIOLOGY.—Dropsical effusion in the thorax is produced by the same
causes which give rise to collections of watery fluid in other serous
cavities and in the connective tissue, constituting general anasarca.
Primary among the causes is obstruction of the venous circulation in
the walls of the chest or in the lungs. Mitral disease, especially
insufficiency with dilatation, deranges the normal circulation in the
lung and its serous coverings, producing hyperæmia, oedema of the lung,
and finally serous effusions into the pleural sac. General dropsy
results. According to Fernet,220 in dropsies resulting from mitral
disease oedema of the lungs and hydrothorax always precede all other
oedemas. Fraentzel,221 on the contrary, states that it does not occur
until there is no longer any room for the transuded fluid in the deeper
portions of the subcutaneous tissues. Other diseases of the heart
produce hydrothorax. Whenever there is abnormally high venous pressure,
which invariably follows dilatation of the right side after
compensatory hypertrophy has reached its limit, and the heart literally
yields to the backed current of blood, we must expect dropsical
results. Intra-thoracic tumors, aneurisms, emphysema, and sclerosis of
the
lung cause hydrothorax by pressing upon the venous trunks and
upon the thoracic duct without producing general dropsy. Chronic
diseases, such as cancerous disease, chronic malaria, etc., produce
great exhaustion and give rise to general hydræmia. Especially is this
the case in chronic disease of the kidneys, such as the several
varieties of nephritis and amyloid degeneration, where there has been a
loss of albumen for a long time and the blood-serum has been rendered
poorer in solid constituents. Hydrothorax is not a disease, but a
symptom resulting from a variety of causes which produce physical
exosmosis of the serum of the blood.
220 Nouveau Dict. Méd., vol. xxviii.
221 Ziemssen's Cyc., Amer. trans., vol. iv.
PATHOLOGICAL ANATOMY.—Hydrothorax being merely dropsy of the thoracic
cavity, there is no lesion of the pleura. There is a collection varying
from 100 grammes to many liters of fluid in the cavity. It differs from
the effusion in subacute pleurisy in its small quantity of fibrin, in
having far less of albuminoid material, and no white blood-corpuscles.
The water collects almost always in both sides of the chest, more on
the side on which the patient lies in bed. In the recumbent position
the fluid gravitates posteriorly more than the effusions of pleurisy.
In the upright position it will follow Ellis's curved line more
regularly than in effusions resulting from pleurisy, for there are no
adhesion-bands interfering with its doing so. The fluid is limpid, of a
light-yellow or citron color. Its composition resembles that of the
plasma of the blood, but it contains more water and less of the
constituent elements. Alex. James222 found that the amount of mineral
matter was the same in dropsical fluids in all parts of the body, and
that the organic albuminoid substances were larger in quantity in the
pleura than in any other cavity. The amount of organic substances
varied directly in accordance to the degree of pressure on the
different capillary vessels. The anatomical changes in the pleura and
the subpleural connective tissue are similar to those found in other
collections of dropsical fluid. They are swollen and thickened by
maceration with water. They become opalescent and less firm of texture.
The lungs retract as the fluid increases in quantity. As the filtrates
collect in both pleural sacs, the lungs do not forcibly collapse. The
patient would sink at once were this the case. The arch-tension of the
diaphragm is but rarely overcome, and consequently we must not expect
to find the liver and spleen pushed down, especially when there is
fluid in the peritoneal cavity. The position of the heart, unless there
is a marked difference in the collections of the two sides, is but
little altered, the retractive force of both lungs being impaired.
222 Med. Times and Gazette, Jan., 1880.
SYMPTOMS.—The general accumulation of watery fluid is not attended by
any pronounced symptom until it has reached the point of interfering
mechanically with the normal play of the lungs. At first dyspnoea is
only perceptible on increased physical exercise. When the quantity is
excessive, the individual suffers when perfectly quiet. The patient,
until the fluid is excessive, lies on his back as the most comfortable
position, but as the quantity increases he is often obliged to sit up
in bed.
The dyspnoea is ordinarily much more oppressive than in pleuritic
effusions, because both lungs are compressed. There is no rise of
temperature, no pain in the side, no tenderness on pressure, no
acceleration of the pulse, and but rarely any cough, as there is in
pleurisy. The dyspnoea often becomes very painful, and may even produce
orthopnoea, being accompanied by short and frequent acts of breathing.
Where there are very large amounts of fluid the mechanical interference
with the breathing is so great that cold sweats, cyanosis, and asphyxia
follow, the pulse becoming smaller and more feeble until the patient dies.
The physical signs are, in general, the same as those of pleuritic
effusions, especially the subacute form, with some slight variation.
Inspection
and mensuration do not aid us as in pleurisy, for in
hydrothorax the accumulation of fluid is bilateral instead of
unilateral. The tension is not sufficient to dilate the walls of the
chest. Palpation shows absence of vocal resonance, but not invariably,
for we are unable to compare the two sides. We must remember that we
have oedema of the walls of the chest, which would partially prevent
the thoracic vibrations from being felt. Percussion flatness is not as
absolute as it is in pleurisy, unless the fluid is in excessive
quantity, for the tension of the fluid is feebler and the lung contains
more air. The lung is never completely compressed, as in pleurisy,
there being no fibrinous bands to constrict it. The percussion
vibrations, unless very lightly made, are communicated to the lung; and
so there is dulness instead of flatness. The absence of fibrinous bands
permits the fluid to change its position with the varying postures of
the patient. This rarely occurs in pleuritic effusions after the first
few days. Finally, Skodaic tympanic resonance at the apex is but seldom
met with in simple hydrothorax.
Auscultation.—The presence of fluid between the lung and parietes
prevents us from hearing the vesicular murmur. The distant bronchial
respiration is rarely heard in hydrothorax, as it is in pleurisy,
because the lungs are not completely deprived of air, and when present
is less intense. Ægophony is frequently heard over the upper limit of
the fluid, the whispering voice being transmitted through the fluid.
Owing to pulmonary oedema there are subcrepitant râles, but never
pleuritical friction sounds.
DIAGNOSIS.—Ordinarily, the diagnosis ought to be made without
difficulty. The only disease with which there can be any danger of
confounding it is subacute pleurisy. The principal points of
differential diagnosis have been enumerated above. In subacute pleurisy
(latent pleurisy) we have, in less intensity, the ordinary pleuritic
symptoms. The pleuritic friction murmur is present, and a fluid
containing the products of inflammation. Very exceptionally is subacute
pleurisy double, whereas hydrothorax is almost invariably so.
The history of the case enables us to arrive at an accurate diagnosis.
The withdrawal of a small quantity of fluid with a fine perforated
needle, and its chemical and microscopical examination, will complete
the diagnosis in doubtful cases.
Oedema of the lung can scarcely be confounded with hydrothorax. The
absence of the physical evidences of water in the cavity, and the
crackling sound heard in auscultation, are distinctive of oedema.
PROGNOSIS.—The prognosis is always serious, but it depends upon the
nature of the disease producing the dropsy. If this can be removed, the
collection of water may disappear. But, unfortunately, the circulatory
diseases which produce it are generally chronic and incurable. The
fluid can, by general treatment and mechanical means, be reduced, and
the life of the patient prolonged and made comparatively comfortable.
Sooner or later a large number of cases must succumb.
TREATMENT.—The treatment should first be directed to the primary
disease causing the dropsy. If heart disease be the promoting cause, we
must, by means of digitalis, endeavor to promote compensating
hypertrophy, and by arsenic and iron improve the quality of the blood.
If Bright's disease be the cause, the skimmed-milk diet, with iron and
manganese, must be given with remedies which lessen the hydræmic
condition of the blood. Digitalis, diuretics, jaborandi, and drastic
purgatives give decided results. Of all purgatives, elaterium in
decided doses (¼ grain), guarded by conium or hyoscyamus, causes most
relief by producing free watery stools. Mechanical means must be
resorted to without hesitation. It is best first to remove the fluid
from the lower extremities by the insertion of Southey's capillary
canula with caoutchouc tubing attached. Large quantities of water may
thus be drawn off without local irritation, erysipelatous in its
nature, being produced. Thoracentesis by aspiration averts death very
often, and gives the greatest possible relief when the effusion is
large enough to produce dyspnoea. In a case under the author's care
life was prolonged many months and large quantities of fluid were
removed. Altogether, there were twenty-two operations and 1563½ ounces
of water removed. As often as every week one or other side had to be
emptied, the quantity removed each time varying from 49 ounces to 112
ounces. For two months previous to death filtrates collected in the
abdominal cavity also, and had to be frequently withdrawn.
DEFINITION.—A collection of atmospheric air or of gas in the pleural
cavity. Pneumothorax ([Greek: pneuma] and [Greek: thôrax]).
In ancient times gaseous collections were frequently noticed in serous
cavities, especially on opening the chest for empyema and at
post-mortem examinations. The presence of air resulting from laceration
of the lungs by fractured ribs was known and designated as emphysema
thoracis. Air in the pleura was considered as an accidental
complication which occurred with empyema or as formed after death.
Morgagni and others mentioned the presence of gas as formed in the
pleural cavity. Itard223 was the first to speak of it as a disease
and to name it pneumothorax. Owing to the imperfect knowledge of
pathology at that period, he attributed the production of the air to
the decay of the lung from chronic suppuration, and to the
decomposition of the long-retained pus. Laennec was the first to give
an accurate anatomical and clinical account of the disease.
223 Thèse de Paris, 1803.
HISTORY.—Pure pneumothorax—that is, pneumothorax caused by the
presence of air alone in the pleura—is but rarely met with, except for
a short time, when it has been introduced from without by traumatic
injuries. The irritating effects of gas, unless it comes in small
quantities through the ribs from wounds in the chest-walls, are very
frequently followed in a short time by the production of a quantity of
serosity or of pus. If air is introduced into the pleural cavity from
perforation of the lung, there is also liquid matter from the lungs of
such a character as at once to provoke inflammatory action. Such a
condition is then denominated hydro-pneumothorax or pyo-pneumothorax.
The latter was, in fact, recognized by Hippocrates by the sign of
succussion, though not so designated.
ETIOLOGY.—Laennec divided pneumothorax into three distinct varieties:
1st, essential pneumothorax, resulting from the spontaneous formation
of gas in the pleural cavity; 2d, pneumothorax from putrid
decomposition of liquids effused into the pleura; 3d, pneumothorax by
perforation, due to rupture into the pleura or to an accidental opening
by which atmospheric air or gas from the lungs is introduced into the
pleural cavity. This division, having Laennec's high authority, was for
a long time generally received. It has now been established that the
pleuræ cannot secrete air.
Proust224 collected 25 cases of so-called spontaneous pneumothorax,
and showed that they could all be otherwise satisfactorily explained.
In some cases errors of diagnosis had been made by mistaking tympanitic
sonority at the anterior-superior portion of the chest, or the
existence of the amphoric breathing found in pleurisy, for
pneumothorax. Some were cases of pneumonia in which tympanitic
percussion resonance deceived observers. Then, again, there was found,
among the cases cited, pneumothorax resulting from rupture of a
tubercular cavity or of a hydatid. In tubercular cases Proust found
that the orifices made were so small—no larger, as Gairdner of
Edinburgh had stated, than a pin's point—that they could not be
detected, or that they had cicatrized before the post-mortem
examination, or perhaps closed by adhesive false membranes. Other
investigations by Ewald225 and Jaccoud226 have confirmed Proust's
views that essential pneumothorax does not occur. Researches in
pathological physiology disprove the possibility of a serous membrane
producing a secretion of gas or of its passing from the blood through
the capillary walls. We therefore conclude that pneumothorax from
secretion of air within the pleura is contrary to physiological facts
generally accepted, and is disproved by pathological investigations.
224 Ibid., 1862.
225 Quoted by Fraentzel, Ziemssen, vol. iv.
226 Gaz. hébd., 2ème serie, 1864.
The second variety in Laennec's division—namely, where the gas results
from decomposition of fluid in the pleural cavity—has been supported
by such high authorities as Hughes Bennett, Townsend, Wunderlich, and
Jaccoud. Yet it is difficult to understand how it could occur. The
contact of air appears to be necessary for the decomposition of serum
and pus in the pleural cavity. While shut up in a cavity coated with
neo-membrane, a fluid may certainly remain undecomposed for a long
time, and undergo decomposition as soon as taken out of the cavity.
Recent researches in regard to putrid fermentations appear to confirm
the view that the presence of air is absolutely necessary to produce
that effect.
We believe, therefore, that perforation, with rupture of the visceral
or parietal layer of the serous membrane, causing the introduction of
air into the pleural cavity, is the invariable cause of pneumothorax
and of hydro-pneumothorax. The causes of the rupture are in the lung,
in the pleura, or in the adjoining organs. They may be traumatic or
non-traumatic: the latter may be perfectly designated pathological
causes, because the pneumothorax is always secondary, following upon a
pre-existing pathological condition.
Traumatic pneumothorax may take place in consequence of an injury to
the thoracic walls, of an exterior injury, or of a penetrating wound.
The parts may be so bruised that pleural necrosis gives rise to sloughs
and resulting openings. Fracture of ribs may tear the lungs, and allow
air to enter the connective tissue and produce local emphysema. Violent
contusions, as in a case recently observed by the author, produce
laceration of the lung without the rib or costal pleura being injured.
Non-traumatic or Pathological Causes.—Laennec taught that pulmonary
tuberculosis was the most frequent cause of pneumothorax; and further
observation has demonstrated the correctness of this view. Walshe
states that such is the case in 90 per cent. of the cases of
perforation of the lung. In 131 observations reported by Saussier,227
81 were from pulmonary phthisis, principally from caseous pneumonia.
Fraentzel228 says, from his own observation, that 90 out of 96 cases
of pneumothorax are produced by vomicæ on the surface of the lungs in
the course of caseous pneumonia. Grisolle states that nine-tenths of
the cases result from rupture of a lung-cavity. Fuller229 reports 22
cases, in 18 of which the disease was produced by tubercular
ulceration. Chambers,230 at St. George's Hospital, reports that 21
out of 23 were tubercular. Fernet231 states that pneumothorax results
in nine-tenths of the cases from some of the forms of pulmonary phthisis.
227 Thèse de Paris, 1841.
228 Ziem. Cyc., vol. iv.
229 Dis. of the Chest, p. 226.
230 Dec. Pathologicum, cap. v. sec. v.
231 Nouveau Dict., vol. xxviii.
Ordinarily, pneumothorax is unilateral; only exceptionally is it met
with on both sides. In tubercular cases it is twice as common on the
left side as on the right (Condrin232). In the total of 146 cases
reported by Louis, Walshe, and Powell, 94 were on the left side;
whereas when it is consecutive to a pleuritic effusion it is almost
always on the right side—17 out of 18 (Saussier233).
232 Thèse de Paris, 1882.
233 Ibid., 1841.
In tubercular cases perforation of the lung may occur at any
period of the disease; the most frequent time, however, is that of the
softening or while excavations are being formed, where adhesions have
not yet protected the two sides by binding them together with
neo-membranes. It may come from a small cavity. Andral met with cases
where only a few tubercles existed. Townsend reported a case where one
tubercle burst immediately under the pleura. The superior lobe of the
lung is where the perforation generally occurs, because it is there
that the tubercular lesion ordinarily commences and is most advanced
(Louis). It is least frequent in chronic fibroid phthisis and most
often met with in acute pneumonic phthisis. Douglass Powell234
reports cases where sinuses extended from cavities, and finally burst
into the pleura. Sometimes the rupture occurs at the base of the
superior lobe, about the third or fourth rib; it may happen, however,
at any point of the lung; it has even occurred at the base of the lung
lying on the diaphragm (Houghton235).
234 Med. Times and Gaz., Jan. and Feb., 1869.
235 Cyc. Pract. Med., vol. iii.
Saussier236 shows by the following table the relative frequency of
the principal causes of pneumothorax in 131 cases:
| Pneumothorax |
with |
phthisis |
81 |
| " |
" |
empyema |
29 |
| " |
" |
gangrene |
7 |
| " |
" |
pulmonary emphysema |
5 |
| " |
" |
apoplexy |
3 |
| " |
" |
hepatic fistula |
2 |
| " |
" |
hydatids |
1 |
| " |
" |
hæmothorax |
1 |
236 Thèse de Paris, 1841.
Empyema ranks second as a producing cause of pneumothorax. Ordinarily,
by direct necrosis of the parietal pleura, an orifice is made through
which the pus is evacuated through the bronchi, and air in inspiration
enters the pleural cavity by the bronchial fistula. Pyothorax is
converted into pyo-pneumothorax. The valvular opening may, however, be
closed by inspiration so that air cannot enter, or adhesions may limit
a portion of the pleura, and then we have a circumscribed pneumothorax.
Empyema, by producing ulceration of the thoracic walls and pointing
exteriorly (emphysema necessitatis), leaves fistulæ through which air
enters the pleural cavity.
Gangrene of the lung by sloughs allows air to penetrate. Bronchiectasic
cavities sometimes become the seat of putrefactive changes and
ulcerations through the lungs into the pleura. Infective emboli being
arrested in the smaller peripheral branches of pulmonary arteries, air
enters the cavity; it is thus that pneumothorax arises in various kinds
of surgical diseases when infective emboli pass into the circulation
(Fraentzel). Flint237 reports a well-marked case of pneumothorax,
lasting less than one month, where there was every reason to suppose
that it had been caused by rupture from interstitial emphysema. W. T.
Gardner had previously reported a similar case. Saussier found
emphysema was a cause in only 5 out of 131 cases. Fraentzel speaks of
emphysema as rarely being a cause. Perforation of the oesophagus,
ulcerative, cancerous, or traumatic from the use of bougies, produces
pneumothorax. Suppurating bronchial glands—a case of which was met
with by the author—bursting into the cavity produce pneumothorax.
Hydatids of the lungs, abscesses of the abdomen, sometimes coming even
from the cæcum and from the liver, burst into the pleural cavity and
introduce air. Echinococcus cysts of the liver are occasionally emptied
into the pleural cavity.
237 Practice of Medicine, ed. 1881; Series of Amer. Clin.
Lectures, article "Pneumothorax," 1875.
Pneumothorax is more than four times as frequent in men as in
women. One-third of the whole number of cases occurs in persons between
the ages of twenty and thirty years; one-tenth between the ages of ten
and twenty; one-twelfth between thirty and forty (Saussier238).
Although pneumothorax has a number of exciting causes, yet they are all
comparatively rare except pulmonary tuberculosis and purulent pleurisy.
238 Thèse de Paris, 1841.
PATHOLOGICAL ANATOMY.—In traumatic pneumothorax and simple cases, such
as from the bursting of emphysematous alveoli, the presence of air is
the only pathological product. If the pleura and adjoining organs are
not diseased, the rupture or tearing cicatrizes rapidly, and the air
disappears in a few days by absorption. If a quantity of air be
admitted, the pneumothorax may last for months; yet if the pleura is
healthy, the air itself will not produce local changes. If blood or
morbid products flow in with the air, then inflammatory changes occur,
and we have deleterious products effused. Demarquay and Leconte239
demonstrated the innocuousness of introducing air into healthy pleural
sacs of dogs, having injected it repeatedly into the same dogs without
any unpleasant result. These observers analyzed the air after it had
remained in the chest, and confirm Davy's240 researches as to the
changes in its condition. The oxygen diminished gradually, and finally
disappeared, while carbonic acid replaced it to nearly the same amount.
This air from the pleura approximated in composition to the air of
expiration. When blood and bronchial secretions with pus are thrown
into the pleura, they promptly produce more serious results, especially
intense suppurative pleurisy. Duncan241 found in a case of
pyo-pneumothorax a fetid gas to contain 26 parts of sulphuretted
hydrogen and carbonic acid and 74 parts of nitrogen. Secondarily,
lesions are produced—hydro-pneumothorax and pyo-pneumothorax. In other
cases, the pleura having been previously the seat of chronic disease
with purulent effusion, this latter undergoes fetid changes and
septicæmia results. Under these circumstances the pathological changes
are similar to those we have described as found in empyema. We find
like increase of tissue-formation, of pus, and of the development of
the gases, sulphuretted hydrogen and sulphydrate of ammonia, which give
rise to a horrible fetidity. The quantity of air varies very much, as
does the amount of fluid: there may be a small quantity of air and much
fluid, or the reverse.
239 Gaz. Méd., 1864.
240 Phil. Trans., 1823.
241 Edin. Med. and Surg. Journal, 1827.
The opening into the pleural cavity may be direct or oblique: if
direct, it remains open; if oblique, it is generally more or less
valvular. The symptoms, prognosis, and treatment vary accordingly.
Through a patent orifice the air enters in inspiration, and goes out
with the expired air from the lungs. As it cannot accumulate, there can
be no positive air-pressure within the pleura. If, however, the orifice
be valvular, although the air enters it does not escape, for it presses
upon the valve and closes it. If the valvular fold be perfect, the air
soon becomes excessive in quantity, and exerts dangerous pressure upon
the lung and adjacent organs. By means of a trocar, attached by tubing
to a water-pressure gauge, Douglass Powell242 ascertained post-mortem
the degree of intra-pleural pressure present in 16 cases of
pneumothorax. In 4 out of these cases the pressure was nil. In 12 there
was more or less intra-pleural pressure present, varying in degree from
1¾ to 7 inches of water.
242 Medico-Chir. Trans., 1876.
Unless the lung be mechanically prevented, the entrance of air into the
pleural cavity at once produces a retraction of the lung, owing to its
elasticity. There is no compression of the lung unless the air is
increased in quantity by each inspiration, and, having no exit,
accumulates; then the lung may be forced against the spinal column and
the residual air actually
forced out of the alveoli. Powell243
questions whether the intra-thoracic pressure excited in pneumothorax
is ever equal to what is sometimes the case in pleurisy: the highest he
had ever met with in pneumothorax was 7 inches of water. Garland,244
in repeating Damoiseau's experiments in testing the effects of the
introduction of air into the pleural cavity, found that the air did not
penetrate between the lung and the lateral chest-walls until the lower
border of the lung had retracted upward the distance of several ribs.
243 Loc. cit.
244 Loc. cit.
One of the most pronounced effects constantly observed in pneumothorax
is the immediate displacement of the heart to a greater extent than in
pleurisy. Gaidy,245 as far back as 1828, described displacement of
the heart as an important sign of pneumothorax. He related a case
where, at the moment of the perforation, the woman was conscious of the
heart's beat having been transferred to the right of the sternum.
Powell246 out of 17 cases found the heart displaced in 16: in the
seventeenth the unruptured lung was so consolidated that it could not
collapse. In pneumothorax of the right side a careful examination is
sometimes required to detect the displacement of the heart. The apex
can be discovered at a considerable distance to the left of the nipple,
with the right ventricle drawn to the left edge of the sternum. It has
been generally believed that the cause of this displacement was the
intra-pleural pressure of the air, but this does not satisfactorily
explain it, for there can be no pressure until the elasticity of the
lung has been overcome. In 13 of Powell's cases there was great
displacement of the heart with different degrees of intra-pleural
pressure. In 3 cases there was great displacement of the heart with no
intra-pleural pressure. The same author247 showed, experimentally,
that the elastic tension of one lung, when unopposed by that of the
other, was sufficient to draw aside the mediastinum, and with it the
heart. He thus demonstrated that these displacements are by no means
necessarily a sign of intra-pleural pressure, since they may occur to
the right of the sternum without there being any pressure. Clinically,
we know that the admission of air into the pleural cavity immediately
and constantly displaces the heart, unless the opposite lung be
consolidated or otherwise injured in its resiliency. This occurs even
when the patent orifice of the perforation prevents the accumulation of
any quantity of air. There is not enough air to produce direct
pressure, but there is enough to impair the elastic traction of the
lung, and thus to destroy the equilibrium of traction which keeps the
heart in its normal position. The healthy lung by its unimpaired
tractile force immediately draws over the heart. Skoda248 maintains
that "air does not enter the pleural cavity simply at the cost of the
torn and retracted lung, but the sound lung also retracts to such a
degree as to move the mediastinum." Garland's experiments249
conclusively demonstrate that the air in pneumothorax is powerless to
exert an appreciable lateral displacing force until the lung has
completely collapsed; and this does not ordinarily occur. There can be,
he says, but one cause of constant and early displacement of the
heart—the elastic force of the opposing lung, which draws it over to
itself. He adds that "the explanation of the greater displacement of
the heart in pneumothorax is that the air, having practically no
weight, cannot exert upon the heart the negative pressure which an
effusion evidently would."
245 Arch. Gén. de Méd., tome xvii., 1828.
246 Medico-Chirurg. Trans., vol. lix.
247 British Med. Journal and Med. Times and Gazette,
July, 1869.
248 Auscultation and Percussion, Eng. trans.
249 Loc. cit.
The fluid in hydro-pneumothorax is very rarely of a serous character.
Saussier found but 1 such example in 169 cases. It is almost always
purulent pneumothorax, and frequently it has a very offensive fetid
odor from putrid decomposition. Mixed with pus there are sometimes
found masses of
pseudo-membranes, débris of lung, and gangrenous
patches, as in purulent pleurisies. The fistulous orifice through which
the air has entered is not always easily found, being often hid away
among false membranes. It is small and tortuous, and can only be
discovered by placing the lung under water and blowing air through the
bronchial tubes. Sometimes the orifices close and the air becomes
encysted, interlobular, or diaphragmatic. There is sometimes only one
opening; again, there may be several. Nolais reports a case where there
were six openings. Orifices with lacerated edges are met with, varying
in length from one to ten or twelve centimeters. It must be borne in
mind that perforation can take place without producing pneumothorax.
Saussier found this occurred in 2 out of 74 cases, and in 8 out of 29
resulting from pleurisy. Fériol and Guéneau de Mussey give similar cases.
SYMPTOMS.—The initiatory symptoms of pneumothorax vary according to
the cause which produces it. When the effusion of air into the pleural
cavity is from perforation of a diseased lung (most frequently
tuberculous, more rarely gangrenous or from an abscess), the first
symptom is a sudden agonizing pain in the side, accompanied with
dyspnoea amounting almost to suffocation. In rare instances, where
strong old adhesions limit the pneumothorax, there may be only slight
pain, without dyspnoea. The rush of a moderate quantity of air into the
cavity causes the lung to collapse; but should the amount of air be
excessive, it will render the symptoms of oppression most intense, for
it will compress the lung and heart and obstruct the capillary
circulation in the lung. Such must be the case, for there is no
aspiration of blood from the large veins, and no aëration of blood in
the lung. The patient often feels as if the chest were being torn away,
and the expression of his countenance betrays distress and alarm. If
the orifice be large and valvular, preventing the escape of the air,
the air accumulates rapidly and completely forces the air out of the
lungs, and death shortly follows, sometimes in a few hours. There is no
rise of temperature or fever. On the contrary, the temperature very
frequently falls one or two degrees below the normal in consequence of
the sudden collapse, the pulse from exhaustion being very frequent and
feeble, accompanied by cold sweats. The voice becomes exceedingly
feeble and whispering. In many cases the patient does not sink at once
from the shock of the perforation, but becomes less oppressed, although
he suffers considerably, being unable to lie flat in his bed.
Respiration is not only frequent (sometimes 60 per minute), but the
dyspnoea is oppressive and distressing to witness. Fever follows
invariably, and sometimes with great rapidity, caused by pleuritis.
When this occurs, the patient again suffers from dyspnoea as the
purulent fluid accumulates in the pleura and gradually dropsy comes on.
These cause dyspnoea and cyanosis. The position of the patient, leaning
forward, supporting his elbows on his knees, indicates his agony and
difficulty in breathing; the pain appears to go through and produce
local hyperæsthesia, and the patient dies from the empyema with hectic
and oedema of the lungs. The pleurisy excited may be simply serous in
its products, even when it is tuberculous in origin. Usually, however,
it is purulent, and we must then expect to find the grave symptoms we
have enumerated in speaking of empyema with hectic and septicæmia.
PHYSICAL SIGNS.—These are well distinguished and marked, and lead
easily to its diagnosis. Inspection shows the side to be immovable and
the dilatation permanent; the spaces between the ribs are obliterated
and the shoulder raised. There is no rhythmical expansion and
contraction of the walls of the chest, the diaphragm is not elevated,
and the liver and stomach are kept down. Air continues to enter the
cavity, until the quantity is so great that its tension is equal to the
atmospheric pressure. The contrast between this condition and that of
the healthy side is very great. In the former the breathing is labored,
with painful muscular contraction in the walls and whole side.
Percussion over the chest gives a hyper-resonant sound, with a
graver-pitched tympanitic resonance. There is but little sense of
resistance to the finger, owing to the elasticity of the contained air.
When fluid is secreted in the second stage we have absolute flatness at
the base over a horizontal level, and tympanitic resonance above. The
pitch of this last sound varies according to the tension of the gas
contained in the chest and the correlative tension of the thoracic
walls. If this tension be feeble, the pitch is higher; if it be
extreme, the tone will be drum-like, muffled, acute, and the tympanitic
character will be less easily perceptible. It may happen that the pitch
will be so high that we may be misled and think there is flatness. It
is not true flatness, but a clean and high-pitched sound, very
different from the tympanitic sound usually found; it is sometimes
remarkably metallic in character. With auscultatory percussion, using a
solid pleximeter, we have the prolonged metallic resonance which
Trousseau appropriately named the bruit d'airain.
The area of hyper-resonance and flatness on percussion is changed with
the altered position of the patient. The fluid, obeying the law of
gravitation, takes its hydrostatic level, and when the patient's chest
is upright is horizontal. Hyper-resonance is often pronounced over the
sternum, and sometimes infringes upon the healthy side. When the
disease is on the left side it obliterates the normal dulness over the
cardiac area.
Palpation.—Thoracic vibrations of the voice are not felt over the
portion of the chest containing air, nor over that containing fluid.
This absence of vocal fremitus is very characteristic. The hand detects
that the heart has been displaced toward the sound side and that the
abdominal viscera are pushed down.
Auscultation.—The auscultatory phenomena vary according to the cause
of the pneumothorax and the size and direction of the orifice. In
tubercular cases, where perforation has produced a large, free opening,
as the air passes in and out of this large pleural cavity with firm
walls (the lung having collapsed perhaps to one-third or less of its
normal size), we have the physical conditions which give marked
amphoric and metallic respiratory sounds, with absence of respiratory
murmur. The amphoric breathing is of greatest intensity near the point
of perforation, which ordinarily is at the mammary or upper scapular
region, and is found in both inspiration and expiration. The cough and
the whispered voice give the characteristic metallic quality. There is
also metallic tinkling produced by droppings of fluid in the cavity, by
the shaking of the body, or by vocalization. Even when the orifice in
the lung is closed we may have amphoric echo, from sounds produced in
the bronchi, and passing through a cavity filled with air. The
intensity of these sounds varies in different cases. Sometimes they are
very loud; in other cases they are feeble and seem distant from the
ear. The fine metallic tinkling may be heard at one moment and
disappear at the next. These amphoric and metallic sounds, heard at
different points, are characteristic of pneumothorax with free
openings. When, however, the orifice from tubercular perforation is
small, oblique, or valvular, the respiratory murmur is inaudible,
except perhaps at the very apex of the lung, and we cannot perceive any
adventitious auscultatory phenomena beyond a faint, distant, hollow sound.
There is, in both kinds of orifices, the well-known splashing
Hippocratian succussion sound on shaking the chest. The latter is
pathognomonic of hydro-pneumothorax, and is sometimes heard when no
other sign is present. The hands applied over the surface of the chest
feel the fluctuations of the fluid striking against the interior walls.
When pneumothorax follows purulent pleurisy we do not find immediately
the pronounced symptoms nor the physical phenomena heretofore described
as occurring when it is produced by rupture from the lung into the
pleural cavity. The condition
of the parts is very different. Pus
is present in considerable quantity in the cavity, and the ulceration
of the costal pleura and the soft walls of the chest allows the fluid
to flow outward and air to enter the cavity. Or there may be necrosis
of parietal pleura into a bronchus and consequent discharge of pus
through the mouth. The lung is already disabled. The violent pain in
the side and the dyspnoea are no longer found. Indeed, the exact time
of the rupture and commencement of the discharge is frequently unknown
to the patient himself. The symptoms of entrance of air into the
pleural cavity may not occur for some time. The patient who has had
empyema is made more uncomfortable; the discharge through the mouth is
offensive, and its quantity and its character call attention to the
chest, in which percussion shows the presence of air; auscultation
gives amphoric breathing, and succussion demonstrates the presence of
air and fluid in the pleural cavity. Very soon, however, the presence
of air produces putridity of the secretion, with loss of appetite,
fever, diarrhoea, and the other alarming symptoms of pyo-pneumothorax.
In some instances the pleura discharges its contents and heals over.
There is another variety of pneumothorax, which is ordinarily attended
with only temporary inconvenience, and which may soon disappear,
leaving the patient no worse than before the attack. This variety of
pyo-pneumothorax may be produced by the sudden rupture of emphysematous
vesicles, by coughing, or even without any unusual force in the
expiratory effort, the alveoli having become extremely thin and brittle
by degeneration of their walls. For the minute the pain is violent and
the dyspnoea great, but it soon subsides, and in a few days the gas may
be all absorbed, unless it is in large quantity. If the pleura is
healthy and the lung not otherwise diseased, the rupture may not cause
any inflammatory action, fever, or effusion. The rupture may heal over
entirely, or if some inflammatory effusion is produced it will probably
be rapidly absorbed. In exceptional cases pleurisy may be excited and
the case become prolonged. While the air remains in the pleura we have
the physical signs characteristic of pneumothorax—displaced heart, as
shown by palpation and auscultation, tympanitic percussion resonance,
amphoric breathing, and succussion.
DIAGNOSIS.—Ordinarily, there should be no difficulty in diagnosing
pneumothorax, no matter how it is produced. We have simply to consider
well the already-mentioned modes of the commencement of the disease,
and give due value to the characteristic physical signs, especially
displacement of the heart, hyper-resonance on percussion, absence of
vocal fremitus, amphoric respiration, succussion, and decided shifting
of flatness and resonance on change of position. When all these signs
are present, each being in itself almost characteristic, there can be
but little question. Obstruction of a large bronchus would be followed
by absence of health sounds and intense dyspnoea, but we should not
have the other physical signs of pneumothorax. Extensive emphysema
would produce some of the signs—exaggerated resonance on percussion
and enlargement of the side. Emphysema, however, is bilateral, and the
resonance over an emphysematous lung has not the same pronounced
tympanitic quality as in pneumothorax. The enlargement in emphysema is
more under the clavicle; the breathing not amphoric; the normal murmur,
although enfeebled, is never completely annulled; and the heart is not
displaced. Large superficial pulmonary cavities with firm but thin
walls give us several of the physical signs of localized pneumothorax,
such as amphoric respiration and metallic tinkling; but the succussion
sound is never heard over them. The tympanitic percussion is rarely so
pronounced in a cavity as in pneumothorax, and in the latter there is
never the cracked-jar sound. In phthisical cavities of large size there
probably would be depression instead of enlargement of the chest. The
situation will ordinarily enable us to make the differential diagnosis,
for localized pneumothorax is almost always low
down in the
thorax, and the pulmonary cavities but rarely below its middle third.
The progress of the case and clinical history would clear up the
diagnosis. If a circumscribed pneumothorax was present with phthisis,
the diagnosis might be difficult. Powell calls attention to the
similarity of some of the signs of acute congestion rapidly supervening
at the base of a comparatively sound lung to those of pneumothorax. But
in the former the resonance, although high-pitched, is not truly
tympanitic, and the heart is not displaced. There is no other disease
of the chest where we find in such close proximity the two extremes of
percussion sounds—flatness from the secondary effused fluid, and the
tympanitic resonance above. If delicate, slight percussion is used, the
line of demarcation can be clearly defined; if, however, the force of
the percussion stroke be even of moderate intensity, the flatness is
mingled with the tympanitic quality, as it is in percussing from the
left lobe of the liver to the stomach.
PROGNOSIS.—The prognosis is unfavorable and always uncertain. During
the first few days after the rupture of the pleura it is especially
bad, though it becomes less so as time goes by. There are cases where
the perforation and its results appear to prolong life. "If the
opposite lung be healthy, we may hope that arrest of the pulmonary
disease may convert the case into one of chronic empyema" (Powell).
But, unfortunately, the rupture often occurs when the patient is
emaciated and dying of chronic lung ulceration. Cases of
pyo-pneumothorax produced in advanced phthisis or by gangrene of the
lung are almost invariably fatal. The most unpromising cases at first
sometimes prove the least serious, and, again, those that appear at the
commencement slight, contrary to expectation, die. Much depends upon
the condition of the other lung and the position of the perforation. If
the other lung be healthy and the perforation low down, the chances of
recovery are better. The progress is most favorable in the cases where
the rupture occurs from emphysema. When from purulent pleurisy the
discharge passes through a bronchus, the orifice may heal and in due
time plastic material be thrown over it, and the air and fluid be left
in the pleura. Cases are reported where the orifice remains open and
pneumothorax lasts for a long time. Laennec reported one case where the
patient lived six years. Fuller250 reports another where the orifice
was open at the end of eleven months, another nineteen months, and
another twenty-seven months. We have mentioned Demarquay and Marotte's
experiments of the innocuousness of air injected into the pleura. Air
is harmless, as they have shown, in the pleura, unless sulphuretted
hydrogen or sulphite of ammonia be developed. Fuller says the prognosis
is very unfavorable when the effusion is large, with great displacement
of the organs. Flint considers pneumothorax occurring as a complication
of phthisis as almost hopeless. It is important to ascertain promptly
the nature and direction of the opening, whether it be free or valvular.
250 Diseases of Chest.
TREATMENT.—This is in a great measure palliative. Hypodermics of
morphia or opiates relieve the agony and lessen the shock caused by the
perforation. Alcoholic and diffusible stimulants may sustain the heart
in its struggle against the effects of dislocation and impaired
circulation. Care must be taken not to depress the powers of reaction
by too much morphia. Hot water in india-rubber bags applied to the
chest gives great relief. Alcoholic stimulants must be given to prevent
sinking from exhaustion. When the distension from air is excessive,
paracentesis gives marked relief, the lives of patients having been
prolonged for days by it. If the opening is valvular, to prevent the
air from accumulating in excessive quantity Reybard's protected
gold-beater's skin trocar may be used and kept in the chest. Otherwise
fine aspirators may be employed, which would seem to be harmless, and
the
operation be repeated whenever necessary. Larger points and
the trocar should never be used, as there is danger of making a
permanent fistulous orifice, as well as of injuring some blood-vessels
or the lung itself. After the excess of air has been removed by
aspiration the affected side should be strapped to control the
inspiratory movements on renewal of positive pressure. Anstie251
recommends drachm ss doses of ether every three or four hours.
Fernet252 recommends inhalation of oxygen. If fluid should compress
the chest, some of it must be removed by aspiration, but care must be
exercised, for the presence of fluid is conservative in its effects.
Its pressure stops up the orifice and promotes its healing. If it
becomes fetid, pleurotomy, with detersive washes, ought to be resorted
to. Food should be frequently administered, with quinine and cod-liver
oil, and good hygienic surroundings prescribed.
251 Reynolds's System of Medicine, vol. iv.
252 Nouveau Dict. Méd., vol. xxviii.
DEFINITION.—Accumulation of blood in the thoracic cavity unconnected
with inflammation of the pleuræ.
ETIOLOGY.—Hæmothorax may be caused by traumatic injuries, by the
bursting of an aneurism, from ulceration through the walls of the aorta
of the vena cava, or from the veins of the pleura. It may be caused by
laceration of the intercostal arteries in penetrating wounds. In very
rare cases a profuse bleeding takes place in caseous pneumonia or in
gangrene of the lungs, and bursts into the pleural cavity (Fraentzel).
Cancer of the lung or pleura may, by pressure, produce absorption and
destruction of the walls of the blood-vessels, and cause discharge of
their contents into the pleural cavity. Sir Thomas Watson253 reports
a case where enormous hæmothorax caused enlargement of the left side,
pushing the heart to the right of the sternum from caries of two ribs
with ulceration through an intercostal artery. The blood never escapes
from the lung into the pleura when there is considerable pulmonary apoplexy.
253 Practice of Medicine, vol. ii.
PATHOLOGICAL ANATOMY.—Blood is found coagulated to a greater or less
degree in the pleural cavity, and the lesion producing the hæmothorax
can generally be found; the remains of blood may be found even after it
has been some time effused. If the hemorrhage does not prove fatal, it
may all be absorbed, or it may by its presence cause local inflammation
of the pleural membrane.
SYMPTOMS.—The symptoms are those of perforation into the chest—sudden
intense pain on the diseased side, with internal hemorrhage, great
pallor, feeble circulation, cold extremities, and syncope. Patients
often die in a few minutes. If the hemorrhage is moderate in quantity,
they revive and the circulation returns, but they complain of feelings
of suffocation and oppression. Slowly the general strength returns and
the patient recovers.
SEQUELÆ.—Most modern surgeons admit that serious hemorrhages into the
pleura come from the thoracic walls, or from the blood-vessels in the
neighborhood of the hilum, or from those which accompany the bronchial
diseases of the second or third order. Hæmothorax is always consecutive
to some primary lesion. Where it is caused by penetrating wounds or by
the bursting of blood-vessels in the lungs, air enters the cavity and
becomes mixed with the blood, producing a complication in the form of
hæmato-pneumothorax. This frequently gives rise to pyo-pneumothorax
with a collection of purulent and ichorous fluid.
DIAGNOSIS.—The previous history of the case, together with the
characteristic symptoms we have mentioned, enables us to diagnose
hæmothorax from
pneumothorax, which commences in a similar way.
The only other condition likely to be confounded with it is effusion in
pleurisy, the physical signs of which are somewhat the same. If the
blood remains uncoagulated we shall have absence of vesicular murmur,
with dulness on percussion, absence of fremitus, and no friction sound.
The introduction of a fine hypodermic needle enables us to be certain
of the nature of the fluid.
The PROGNOSIS is always serious. If the cause of the hemorrhage is the
bursting of an aneurism, death supervenes in a short time. Hæmothorax,
when caused by penetrating wounds, unless they produce hemorrhage, is
not necessarily serious. The blood may entirely disappear in a few
weeks. Entrance of air with the blood renders the prognosis more
serious. Secondary pleurisy is not ordinarily severe unless pus forms.
TREATMENT.—If time is allowed, every effort must be made by local and
general treatment to arrest the hemorrhage—ice-bags and hot-water bags
ought alternately to be applied to the chest and between the scapula;
the patient to be kept in the horizontal position and made to rest
quietly; ice taken by mouth; small doses of morphia and large doses of
ergotin must be given promptly hypodermically, as the stomach is in no
condition to absorb remedies readily. If the accumulation be excessive
and continues to embarrass the respiration very much, we recommend free
incisions to take out sufficient blood to relieve the pressure and
great dyspnoea. Unless danger is imminent, this is a hazardous
experiment, as letting in atmospheric air among blood-clots may
seriously complicate the condition. Should pleuritis or other
complications occur, they must be rationally treated.
Growths in the Pleural Cavity.
Some authors mention various tumors which are rarely met with in the
pleural cavity, and which are not peculiar to the serous membrane of
the pleura. Among them may be placed sarcomas, fibro-sarcomas, and
epithelioma. Their presence in other organs may assist in the
diagnosis. Other varieties exist more or less connected with chronic
pleurisies. Among these are fibromas, cartilaginous and osseous
formations. Rokitansky speaks of lipomas as deposited on the costal
pleura. The only varieties which we think it necessary to call
attention to are cancer and hydatids.
CANCER OF THE PLEURA.—Cancer of the pleura is not a very rare disease,
but ordinarily it is a secondary formation, coming from cancerous
disease of the mediastinum, of the lung, or of some abdominal organ.
Some authors doubt whether it is primary even in the lungs and
mediastinum. It certainly is not often met with as a primary disease of
those organs. Lebert254 had only seen 6 observations, in 447 cases of
cancer, involving the mediastinum, the pleura, and the lungs.
Walshe255 reported 29 cases of primitive cancer of the respiratory
organs; in 18 cases one lung was diseased with its pleura, and in 13
the right lung. Lépine256 in 1869 communicated a very curious case of
primary cancer of the pleura in a child ten years of age. The right
pleural cavity was filled by a white scirrhous tumor. Darolles257
(1874) reported another example of primary cancer of the pleura, which
afterward spread to the lung. Andral, Vidal, and Lebert reported cases
where the tumors appeared to develop simultaneously in the pleura and
other organs. Primary cancer of the pleura may exceptionally occur, but
ordinarily the disease results from its extension step by step, or else
distant propagation, from lungs, breast, mediastinum, or the abdominal
organs. Most frequently the secondary
cancer appears more or less
independently of the primitive tumor, and is seen in the form of
disseminated points on the surface of one or both folds of the pleura.
This propagation of cancer is now generally admitted to be through the
intermediary of the lymphatic system; in fact, the lymphatics are
themselves attacked by the degeneration, and they are seen,
particularly on the surface of the pleura, in the form of white small
cords. Some modern pathologists consider that the serous cavities are
lymphatic cavities, which can, just as the vessels themselves, serve as
ways of generalizing the disease (Cornil and Ranvier, Charcot, Lépine,
and Virchow).
254 Traité Prac. Mal. des Cancereuses, Paris, 1851.
255 Nature and Treatment of Cancer, London, 1846.
256 Bull. de la Soc. Anat., 1869.
257 Quoted by Fernet, Nouveau Dict. Méd., vol. xxviii.
PATHOLOGICAL ANATOMY.—Primary cancer of the pleura is ordinarily
encephaloid and multiple. Extended infiltration is very rarely found.
Lebert reports one case in an infant of seven months. The multiple
masses are ordinarily soft and pulpy, varying in volume from the size
of a grain of millet-seed to that of a small nut. The aspect is
yellowish-white. The juice is rarely pressed out of them. Under the
microscope we see large cells and multiple cells with their nuclei. The
small granulations or the lenticular masses are flat, resembling drops
of wax. We may have solid bodies possessing all the characters of
scirrhous, encephaloid, and colloid, grayish, or gelatinous structure.
These cancerous productions are generally vascular, especially in the
encephaloid variety. Their rupture frequently produces hæmothorax and
hemorrhagic pleurisies. The bronchial glands, and finally the cervical
glands, often become involved.
SYMPTOMS.—The symptoms of pleural cancer, especially of the smaller
and secondary deposits, are often obscure and indefinite. They are not
sufficiently definite to attract attention during life. If the masses
are scirrhous and large, they press upon the lungs, impede respiration,
and give rise to dyspnoea. If the disease is propagated from the lungs
or breast, we may suspect cancer where we have a dull pain with some
cough. Pain, indeed, is constant, but not violent, unless the nodules
excite local inflammation. When scirrhous tumors press upon the
intercostal nerves, the pain is very persistent. External pressure over
the points gives rise to pain. The dyspnoea increases as the size of
the tumor increases. The expectoration is occasionally bloody. The
physical signs are sometimes characteristic—dulness on percussion,
absence of respiratory murmurs, friction sounds, no vocal fremitus.
DIAGNOSIS.—Generally very difficult. The progress of the disease is
ordinarily slow, and follows its development in other portions of the
body. Cancerous cachexia, degeneration of the glands above the
clavicle, hæmothorax, and hemorrhagic pleurisy, together with dry cough
and persistent intercostal neuralgia, are, when present, valuable aids
to diagnosis. Extensive caseous pneumonia and pleuritic effusions may
be confounded with cancer of the pleura. These tumors may not be at the
base, but in the middle of the thorax; dulness may not exist at the
base as is invariably the case in pleurisy. The position of the body
does not affect the limit of dulness in cancer.
The PROGNOSIS is always very serious, the disease being invariably
fatal. In Walshe's cases the duration of the disease was from three and
one-half months to twenty-seven months; average duration, thirteen and
one-fifth months. One-fourth of his cases occurred between the ages of
fifty and sixty years.
The TREATMENT is palliative—opium and other narcotics, and locally
chloroform and aconite for the intercostal pains. When effusion results
from cancerous inflammation the aspirator may be used to relieve the
great oppression caused by the quantity of fluid.
Trousseau258 considered hydatids of the pleura a comparatively rare
disease. He believed that when found in the cavity it was frequently
caused by cysts of the lung which had fallen into the pleural cavity.
Vigla259 mentions 3 cases. Davaine260 met with 25 cases of
hydatids, only 1 of which he believed originated in the pleural cavity.
The acknowledged greater frequency of these hydatids in the right
inferior lobe of the lung, gives probability to Dolbeau's261 view
that "they frequently proceed from cysts on the convex surface of the
liver." Hearn262 reports 75 cases collected from various observers as
intra-thoracic, 15 of which were in the pleura, in the subserous
tissue, between the parietal pleura and thoracic wall.
258 Clin. Med., vol. i., Philada. ed.
259 "Des Hydàtides intrathor.," Arch. gén., 1855.
260 Traité des Entozoaires, etc., Paris, 1860.
261 Thèse de Paris, 1856.
262 Thèse de Paris, 1875.
PATHOLOGICAL ANATOMY.—In the greater number of cases, as examined at
autopsies in Hearn's reports, the tumor was formed by a voluminous
pocket occupying a large part or the whole of the cavity of the pleura.
The walls of the envelope were formed of a transparent or slightly
opaline and whitish membrane composed of numerous thin layers,
containing on its interior surface the echinococci. In the interior of
the cyst there was a limpid hyaline liquid with living parasites.
Nothing different was noticed in cysts from those found elsewhere,
except the absence of the usual adventitious membrane—a fact
previously noticed by Davaine. When the cysts are very large they press
upon the lung and adjoining organs just as is the case with large
effusions in the pleural cavity. The heart, moreover, is pushed to one
side, out of its normal position; the lung is compressed and diaphragm depressed.
SYMPTOMS.—The first appearance of cysts of the pleura causes but
little disturbance of the functions of the lung. It is scarcely
appreciable until it interferes with the play of the other organs. The
three prominent symptoms are the pain, the dyspnoea, and the cough. The
pain occupies the exact point where the tumor is situated, and radiates
from that point. Once developed, it persists with tenacity throughout
the duration of the disease. This persistence of the pain is indeed an
important characteristic of the disease, and is a sign of value in the
diagnosis between hydatids and pleuritic effusions. The dyspnoea
increases progressively with the volume of the tumor. The cough is not
heard as frequently as when the cysts occur in the lungs. It is dry,
and does not cause hæmoptysis.
DIAGNOSIS.—Physical signs must be marked to enable us to distinguish
fluid cysts of the pleura from cysts in the lung or effusions in the
pleural cavity. When the hydatid tumor has attained sufficient size to
cause pain and dyspnoea it generally presses outward the walls of the
chest after the lung has been compressed. It does not occupy the base
of the cavity, as the effusions do, and the dilatation has a globular
form. Trousseau263 has given several examples in which this shape
determined the diagnosis. With this arching of the chest the immobility
of the chest is an important sign. Vocal fremitus is diminished or
totally abolished, and percussion elicits absolute flatness. These two
physical signs assist us in making the diagnosis between hydatids and
pleurisy. The auscultatory phenomena, from similar physical conditions,
closely resemble those of pleuritic effusions. It must be borne in mind
that sometimes hydatid cysts are complicated by pleuritic
inflammations, caused by their presence. The diagnosis is
unquestionably complicated by difficulties that are not removed unless
the cysts burst through a bronchial tube and discharge a transparent
and clear fluid in which the microscope shows the presence of
echinococci. Such hydatid expectoration is a pathognomonic
sign
of the existence of an intra-thoracic cyst. Hydatids of the liver may
press the diaphragm far up into the pleural cavity without bursting
through it. Trousseau maintained that without bursting they may make a
passage for themselves through the distended, attenuated fibres of the
muscular portion of the diaphragm, for the progress of these cysts is
necessarily slow. We must not hesitate to make an exploratory
aspiration to determine with certainty the nature of the fluid.
263 Loc. cit.
PROGNOSIS.—The prognosis is certainly very serious, but not so bad as
when cysts of the same nature are situated in the lungs. Their
spontaneous cure may be effected by bursting through a bronchus or even
through the walls of the chest. The patient may, however, die from
asphyxia during the discharge through the lungs. When not evacuated
they may produce death by compression of the lungs.
TREATMENT.—If the disease is recognized previous to its making an
opening through a bronchus, it can be treated safely and effectively by
aspiration. Bird264 reports a number of cures by this operation in
Australia. Trousseau advises extreme caution, even in regard to
exploratory punctures, unless adhesions have taken place between the
tumor and the walls of the chest, for he fears the escape of fluid into
the cavity of the chest and consequent purulent pleurisy. It is well to
remember that this great practitioner was not aware of the
innocuousness of capillary punctures and aspiration. If the bronchus
has been perforated, we must hope for spontaneous cure. If empyema be
caused by the tumor pleurotomy must be used as recommended by
Moutard-Martin265 and Vigla,266 and constant washing of the pleuræ
must be used. This treatment gives us reasonable assurance of success.
264 Quoted by Hearn.
265 Purulent Pleurisy.
266 Loc. cit.
History of Thoracentesis.
Thoracentesis ([Greek: thôrax], chest, and [Greek: chentein], to
pierce) is the operation for the evacuation of collections of fluid,
serum, pus, or blood from the pleural cavity.
Among the ancients, dating back to the time of Hippocrates, it was
practised, and was known as the operatio empyematis. Hippocrates uses
the word [Greek: empyon], signifying, literally, an internal collection
of pus just above the cavity of the peritoneum, above the diaphragm.
Subsequently he speaks of empyema of blood, empyema of serum, empyema
of gas, but not of pus, applying the term to the operation, which he
employed principally for empyema necessitatis. Subsequently the name
empyema was used, as now, to designate a purulent collection in the
pleural cavity.
If we may credit the story which has descended from mythological times,
the operation for empyema had its origin in an accident. It is related
that a certain Phalereus, who was attacked with what was denominated an
ulcer on the lungs, was pronounced by all his physicians to have an
incurable disease. In his despair he exposed himself in battle so that
he might be slain; the enemy's weapon, however, pierced his side,
making an opening through which the pus escaped, and he recovered.267
267 Cicero, De Naturâ Deorum, lib. iii. cap. 28.
It is certain that from the most remote periods the chest was opened
when collections of pus were formed. Galen states that the ancients
employed actual cautery for that purpose. He reports that Euryphon de
Cinde by this means saved the life of Cinesias, son of Evagoras.268
The details into which Hippocrates and his school entered in regard to
the operation show that it was frequently performed in their day. It is
very remarkable that many of the more important precautions in the
operation were observed by
Hippocrates. We find from the
Aphorisms that the operation was considered the only means of
cure,269 and that when these precautions were observed, and the fluid
was white and of good quality, the patients recovered.270 The
principal precautions were not to delay the operation after the
existence of pus was recognized, and to draw off the liquid. He further
states that if the serous fluid in dropsy of the chest or pus in
empyema should be drawn off too rapidly the patient would die. So
impressed were the disciples of Hippocrates by this view that they
adopted the operation of perforating a rib instead of cutting through
the intercostal space, because they could with more ease stop up the
orifice and regulate the outward flow of the fluid. The later
Hippocratians preferred cutting instruments to actual cautery.
Hippocrates, if unable to discover the locality of the fluid in the
thorax by succussion, applied over the walls of the chest a linen
compress which he soaked in earth of Eretria and warm water, and
concluded that the collection existed at the points where the earth
commenced to dry!
268 Comm. in Aphor. Hipp., lib. vii.
269 Aphorisms, lib. vii., Aph. 44.
270 Ibid., lib. vi., Aph. 27.
When these signs failed, he cut through the most prominent rib at the
base of the chest and toward the back. He made a large incision through
the rib, but only a small one the size of a thumb-nail through the
tissue beneath the rib. After allowing a small quantity of pus to
escape, he introduced a tent of undressed flax, with a piece of thread
attached to it. This he withdrew twice daily, to allow the pus to flow.
At the end of two days he permitted the remaining pus to be discharged,
and inserted a tent of linen. To prevent the lung, habituated to the
presence of fluid, from drying too rapidly he injected wine and oil
through a canula. When the excavated fluid was thin (serous?) he
replaced the tent by a tube of tin, and when it ceased to secrete fluid
he shortened each day the length of the tube, so that the cicatrization
of the wound extended from the inner end of the orifice.271 The
genius of Hippocrates cannot but excite our admiration, as it did
Laennec's, who selected as the subject of his thesis "The Doctrines of
Hippocrates as applicable to the Practice of Medicine." Can it have
been Hippocrates's modes of physical explanation that suggested to
Laennec the idea that led to his great discovery of auscultation?
271 De Morbis, lib. i. p. 448.
Hippocrates's operations were made by boring through the rib or with a
red-hot iron or a bistoury cutting through the intercostal space. Galen
(A.D. 150) had his pyulcon with which to draw out the fluid. Galen and
Roger of Parma bored through the sternum. Many of the ancient surgeons,
such as Eumphon of Cnidos, Paul of Ægina, Celsus, Solinger, divided the
soft parts by caustics and the knife after laying bare the pleura.
Blunt instruments were sometimes used, such as sounds. Celsus in his
latter years lost confidence in the operation, and it fell into
discredit among the Greeks and the Romans, by whom it seems to have
been nearly abandoned. In the Middle Ages the question was discussed
whether it was better to open the chest by steel or by fire in
traumatic pleurisies. Trousseau states that about the sixteenth century
the operation of trepanning the ribs was revived. About the same time
the detersive injections which had been recommended by Galen were again
advocated, especially by Fabrice d'Aquapendente. The operation was
unpopular among the greatest surgeons, and but seldom resorted to
except in extreme cases. Notwithstanding the servile obedience to
tradition in those days, some important points were advocated in regard
to the propriety of allowing the openings for empyema to remain
unclosed for an indefinite period. From the seventeenth to the
eighteenth century the operation of paracentesis was the topic of many
surgical treatises.
Early in the seventeenth century practitioners became less distrustful
of
puncturing the chest, and were led to believe in the
harmlessness of the operation (Trousseau). As a consequence of this
tendency, physicians began to study the question of puncturing the
chest in hydrothorax. In 1624, Gérome Goulée alleged that he succeeded
more frequently in hydrothorax than in abdominal paracentesis. Twenty
years later, Zacutus Lucitanus asserted that paracentesis was as
necessary in cases of serous effusion into the chest as incision in
empyema. In 1663, Robin and Duval recommended thoracentesis as the best
treatment for hydrothorax. Some time afterward this practice was put in
force by Willis. Lower also mentions a case, and subsequent authors
quoted these cases as an encouragement to the performance of
paracentesis of the chest for the removal of serous effusions. Jean de
Vigo brought out again the pyulcon. Druin about the year 1665 proposed
the use of the trocar as a substitute for the actual cautery in opening
the chest.
In 1658, Bontius for the first time took up in a precise manner the
subject of the introduction of air into the pleural cavity. He declared
there was no danger from it. Bartholin maintained the opposite opinion.
The indications for the operation were laid down, but they were
necessarily very imperfect. In proportion as attention was directed to
the question of the admission of air, the manner of operating was
modified. In 1669, Scultetus discussed thoracentesis in his work
Armamentarium Chirurgicum. He made use of a trocar, with a bladder at
the external orifice, principally to prevent the introduction of air,
as Reybard later used a piece of cat's intestine and a bladder of
gold-beater's skin. Scultetus used the sypho, a common syringe, for
injecting the chest, and also the [Greek: pyoulchon] ([Greek: pyon],
pus; [Greek: elchô], to draw out), or pyulcon, for drawing out matter,
as its name indicates. This was practically the syphon. Scultetus
describes the operation by incision with his gladeolo salicet longo,
and by puncture with the canula et acus, both figured in his plates; so
also his drainage-tubes, with directions for shortening them as the
cavity heals, and the long tubes, which probably acted by gravitation
after the manner of the syphon. Aspiration was made by the mouth, by
cups, and by syringes affixed to a canula or catheter.272
272 These facts were kindly furnished me by Morrill Wyman,
who carefully examined Scultetus' work (edition 1672) in the Harvard
Library.
It is thus evident that more than two hundred years ago aspiration was
used to evacuate fluid from the pleural cavity. Trousseau says that "at
that period aspiration and suction were used for this purpose—timidly
pursued, in accordance with Scultetus' example; and that it became
afterward in vogue with the masters of surgical art."
Palfin preferred the trocar to incision for treatment of hydrothorax.
In 1707, Anel wrote a book on the art of sucking wounds without using
the mouth. Bourdelin (1742) rejected the trocar for fear of injuring
the lung. That Scultetus' practice was continued is evident from the
work of Laurence Heister (1742), who described puncture of the chest,
with drawings of exhausting syringes for the removal of pus or serum.
In 1765, one hundred years after Druin's use of the trocar, when
perforation by actual cautery was abandoned, Lurde timidly advocated it
on account of his fear of wounding the lung. He advised the operator to
close the canula with the finger at each inspiration, leaving it open
during expiration, so as to prevent the entrance of air. Chopart and
Desault opposed the use of the trocar as a coarse mode of operation,
involving the risk of wounding the intercostal artery and lung
(Trousseau). Van Swieten at the end of the last century questioned the
advisability of using the trocar. Later, in 1796, Benj. Bell,273 in
cases of thoracentesis, used india-rubber bottles fitted to the opening
for the same purpose, first compressing them and then allowing them to
expand by their elasticity. He strongly recommended paracentesis
of the pericardium when the amount was so excessive as to cause death.
He gives exact directions how and where to operate.
273 Vol. v.
Isbrand de Diéonerbrock274 plunged a bistoury between the fifth and
sixth ribs, and introduced into the wound a silver canula large enough
to fit the orifice, and stopped the canula with a tent which he
withdrew each day. Jean Scultetus275 recommended several different
canulas, some of silver, some of gold. He also invented syringes,
straight and curved, to absorb the pus or make injections into the
chest. Scultetus operated in the sixth intercostal space; he raised a
piece of skin, so that it might lap over the orifice after the
operation. He used a tent until the eleventh day, when he inserted a
canula. After Scultetus, Lamzweerden276 used suction, and contended
that it was very successful. Paul Barbette277 considered
thoracentesis as indispensable in empyema and hydrothorax. He
maintained that it was less dangerous than the puncture for ascites. F.
Hoffmann at the commencement of the eighteenth century278 gave his
full and complete approbation to the operation performed according to
the accepted rules. Dominique Anel279 was an avowed partisan of the
suction of the effused fluids in the chest. He had seen soldiers very
successfully suck, with the mouth, wounds of the chest. He invented
different syringes and other machines to pump out the effused fluids,
some of which were very large, with canulæ whose orifices were very
wide and of different shapes.
274 Medic. Morb. Pectoris Hist., 2.
275 Armam. Chir., Paris, vol. i. p. 20, quoted by
Sprengel.
276 Appendix ad Sculpt. Armen, 1671, quoted by Sprengel.
277 Chirurgia, lib. iii. cap. 2, Geneva, 1688, quoted by
Sprengel.
278 Medicina consultatoma, vol. i., 1721.
279 L'art de Sucer les plaies sans se servir de la bouche
d'un Homme, Amst., 1707.
Laurence Heister280 (1742) acknowledged that Anel's syringes were
valuable in pumping out the fluid from the middle or lower part of the
chest, but not when paracentesis was performed in the higher portions
between the second and third ribs. Heister gives281 drawings of
exhausting syringes for the removal of pus or serum. C. G. Ludwig
published282 a new apparatus invented by a surgeon named Bucer to
pump out the fluids contained in the chest. This machine was composed
of canulæ, to which was adapted a bowl to receive the liquid as it was
withdrawn. Ludwig claimed that the especial advantage of this
instrument was that it pumped all the fluid out at one time, without
the operator being annoyed by any disagreeable odor. Leber283
proposed a similar instrument which was easier of application. A. T.
Richter demonstrated the inutility of all these inventions; the blood,
he said, would be drawn out with the fluid and by coagula stop up the
canula. Valentin (1772) objected to the use of these pumps as applied
to chest fluids.
280 Chirurgie, Th. i. Buch. i. Kap. 10, p. 89.
281 Ibid., p. 72.
282 Diss. de Vul. Pectoris, Leip., 1768.
283 Quoted by Sprengel, p. 60, vol. ix.
In the latter part of the eighteenth century there were numerous
English and continental writers on the subject of paracentesis. Among
them were J. W. Belquer, Sharp Mohrenheim, Richter, Ponteau, Callisen,
Pierre Cooper, Allemoth, Zellar, and Audouard. Some of these preferred
the trocar to the bistoury. Some were in favor of prompt action, and
others objected to the operation unless there were threatening
symptoms. Valentin urged that the presence, on the surface of the
chest, of oedema and ecchymosed spots was a certain indication of fluid effusion.
During the first twelve years of this century the operation seems to
have fallen into disuse. In 1808, Audouard objected to the Hippocratian
method, which had been practised for centuries, of drawing out small
quantities at a time, for fear that the sudden withdrawal of a large
quantity would produce a vacuum in the chest. He maintained, and
proved, that sudden and
complete evacuation had no such result.
In 1811, Corvisart284 drew attention to thoracentesis. In 1812,
Larrey discussed its merits. Charles Bell285 preferred the trocar to
the other methods in hydrothorax when he could be positive of the
presence of fluid, but he stated that he preferred first to introduce
the bistoury. He operated in the sixth intercostal space, but in
empyema he preferred to make the puncture higher up. Samuel Cooper286
recommended as small an orifice as possible for the evacuation of
serum, but larger and wider ones for pus and blood.
284 Maladies du Coeur, 1811.
285 System of Operative Surgery, vol. ii. p. 194.
286 Dictionary of Surgery, p. 749.
In tracing the history of this important operation we have shown that
it has been performed from the time of Hippocrates, and that it has
been held in different degrees of estimation by the numerous authors
who have discussed it—that sometimes it has been popular, and again
regarded unfavorably.
Récamier operated, but unsuccessfully. Up to the period we have now
reached (1816) great difficulty of accurate diagnosis existed, and
crude notions of physiology prevailed. Errors of diagnosis as to the
character of the fluid when present, and still more as to its existence
in the chest, frequently led to unpleasant results. Laennec's genius so
completely cleared up the differential diagnosis of all diseases of the
chest, including pleurisy, that men grew less timid. Laennec287
himself was a strong advocate of the operation; he advised it in acute
pleurisy where dyspnoea, threatening life, supervened, and in chronic
cases where other remedies failed. He proposed to apply a piston
cupping-glass over the wound after the discharge of liquid, and to
produce a vacuum in the chest more or less quickly, continuously, and
completely according to effects.
287 Traité d'Auscultation mediate, 1818.
As Bowditch288 states, "We should be groping in the same dark way,
and perhaps getting into the chest by caustic pastes or by actual
cautery, had not Laennec discovered for us auscultation, with all its
admirable powers of diagnosis of thoracic affections."
288 Unpublished communication to the writer, 1882.
In 1815, Blondel practised puncture of the chest with a bistoury.
Gendrin performed the same operation in acute pleurisy in 1831, but
with only bad results. Townsend289 (1833) acknowledged that the
operation had fallen into disuse, as much from uncertainty of diagnosis
as from any experience of its general danger. He gives the results of
Thomas Davies's operations—8 out of 10 successful cases in empyema,
with 9 fatal cases in pneumothorax with effusion (probably tubercular),
and 3 fatal cases in hydrothorax. Davies used a grooved needle to
determine the presence of the liquid, its quality, and the thickness of
the walls. After the operation his practice was to inject a weak
solution of chloride of lime, which he found to have the effect of
diminishing the discharge and correcting its character. Crompton290
(1834) had 3 successful cases out of 10.
289 Cyc. Prac. Med., vol. ii. p. 43.
290 Ibid., vol. iii. p. 400.
Robert Law291 pronounced paracentesis more successful in chronic than
in acute pleurisy. Townsend doubts whether the admission of air was
hurtful; he quotes Nysten and Spies's experiment, showing that air
introduced into healthy pleuræ was invariably absorbed in a few days.
291 Ibid., 1834.
Townsend292 and Law, as well as C. I. B. Williams,293 speak of the
different kinds of syringes that have been proposed to draw off the
fluids.294 Dupuytren proposed (1814) the introduction of a small
canula with a very flexible substance at its outward extremity, such as
the bladder of some domestic animal, which would allow fluid to escape,
and at the same time would oppose the entrance of air into the chest.
Becker (1834) published a work in which he investigated the nature of
the false membranes in pleurisy, and showed that the
access of
air did not produce unpleasant results. He reported 2 successful cases
out of 3 of operation.
292 Ibid.
293 Library of Pract. Med., 1841.
294 Boyson, Thèse de Paris, 1814.
R. Townsend295 wrote an elaborate paper in 1833 on empyema, in which
he applied the principles of physical diagnosis. He cites numerous
cases of thoracentesis, and speaks of the operation as easy of
execution, productive of little pain to the patient, generally followed
by immediate relief, and as having been in numerous instances crowned
with complete success. Robert Law296 (1834) speaks discouragingly of
the operation in consequence of the "unavoidable admission of air into
the inflamed cavity." He considered the operation of tapping the chest
more likely to be successful in chronic than in acute pleurisy.
295 Cyclop. Prac. Med., vol. ii., 1833, London.
296 Ibid., vol. iii., 1834.
In 1835, Faure297 read his paper on thoracentesis before the Academy
of Medicine of Paris, which attracted a great deal of attention.
Contradictory opinions were given by prominent members as to the value
of the operation. The debate was prolonged, and no definite conclusion
was reached. Laennec, although he had recommended the operation in
excessive effusions and in chronic cases, was yet timid, and his advice
had not the overwhelming influence that it should have had. Becker of
Berlin in 1834 wrote his paper on chronic pleurisy, in which he also
laid down the principles of diagnosis by means of auscultation and
percussion. He detailed 5 cases which he had operated upon. To Thomas
Davies is due the credit of having in 1835 recommended the use of the
exploring-groove needle to ascertain the nature of the pleuritic
effusions, but Powell claims that Sir Benj. Brodie first suggested it.
Ringer first recommended the use of the hypodermic syringe for that
purpose. Stokes298 insisted upon the evils attending paracentesis,
among which he mentions the converting of serous into purulent effusions.
297 Bullétin de l'Académie de Médecine, 1838, tome i. p.
62.
298 Dis. of Chest, Dublin.
Watson's lectures on practice, delivered in 1836–37, show that while he
was much interested in the operation, the necessity of which he
discusses with his characteristic ability, yet his conservatism led him
to put prominently forward the dangers and evils connected with it.
According to these two prominent English practitioners, only imminent
peril to life justified the operation. Guérin299 in 1841 applied his
subcutaneous method of operation to empyema. He drew fluids from the
chest by a suction-pump applied to a canula, using a curved trocar and
canula to prevent injury to the lung.300
299 Essai sur la Méthode Sous-cutanée, Paris, 1841.
300 Drawings of the trocar and canula, with the aspirators,
are shown in Jacob and Bongeré, Med. operatoire.
Reybard in 1837 took up Dupuytren's suggestion, and used gold-beater's
skin as a valvular means of excluding air at the mouth of the canula;
this is now known as Reybard's canula apparatus, and was the one used
and highly recommended by Trousseau. Stanski in 1839 invented an
apparatus for drawing off air from the chest, working on the principle
of aspiration. Bowditch states301 that while in Paris from 1832 to
1835 he never saw a case of pleurisy in Louis's, Chomel's, Andral's, or
Trousseau's wards where thoracotomy was performed or even suggested.
Medical opinion was either indifferent or in actual opposition at that
time. H. I. Bowditch of Boston relates302 that he saw 2 cases of
effusion in the pleural cavity in 1839, in which he proposed
thoracentesis, but the surgeons would not operate: both of these
patients died. He was convinced at the time that their lives might have
been saved. Schuh of Vienna published his work on the Influence of
Auscultation and Percussion on Practical Surgery, in which he boldly
maintained that paracentesis was a radical cure in cases of chronic
thoracic effusion, no matter how originating. This work had a great
influence in advancing
the popularity of the operation of
thoracentesis. Subsequently, Schuh and Skoda, both professors at
Vienna, published303 a monograph on the treatment of pleurisies,
especially by surgical means, which, as Trousseau acknowledged, has
become a classical work in Germany, and occupies a distinguished place
in the history of paracentesis of the chest. They admitted that when
the effusion is not excessive in quantity, and there are no
complications, recovery generally takes place. When the effusion is
excessive even, it may in time disappear, but it may prove a matter of
months or years. They advised that the operation should be performed
when there was no marked improvement for three weeks. These authors
refuted the arguments urged against the operation, and gave details as
to the mode of operating. The Germans were the first to consider the
puncture as a means of radical cure in pleuritic effusions: Becker,
Schuh, and Skoda gave it a decided impulse. Hope's304 paper
endeavored to prove that pleuritic effusions did not require surgical
interference, but would yield to general treatment.
301 Unpublished MS., 1883.
302 American Journal Med. Sciences, April, 1852.
303 Medicinische Jahrbücher der K. K. Oesterreich Staates,
1841.
304 "Notes on the Treatment of Chronic Pleurisy," in
Medico-Chir. Review, London, 1841.
Thus we see that up to 1841 these unsettled controversies over the
dangers and advantages of the operation were still going on. Fred.
Bird's results in 1843 proved the possibility of its successful
employment, doubted up to that time in England. Trousseau's attention
was strongly drawn to the necessity of the operation of thoracentesis
as early as 1832, when he attended a case at the Hôtel Dieu that died
from excessive pleuritic serous effusion. Louis, from the observation
of 150 cases of simple pleurisies that had recovered, had enunciated
the law that pleurisy is never the immediate cause of death. This fact,
together with Récamier's want of success, had so prejudiced the minds
of French practitioners against the operation that it was loudly
condemned in acute cases of effusion and in all cases of hydrothorax.
Having no fears of fatal termination in pleurisy, they saw naturally no
necessity for surgical interference. Trousseau states that it was not
until after he had witnessed three patients die from acute pleurisy
that he ventured to operate (Sept. 11, 1843). He did not summon a
consultation, for fear of being thwarted. It was so successful that he
was emboldened to operate without hesitation. After his third operation
he read his memoir to the Academy of Medicine in 1843. Trousseau in
these memoirs maintained the proposition which extensive observation
has now after forty years fully sustained, that dyspnoea and orthopnoea
may occur when the effusion is in moderate quantity, and that they may
be absent when the effusion is considerable, especially if it has
formed slowly. Furthermore, that the signs that constantly indicate the
gravity and imminent danger of effusions, and which consequently demand
the operation, are the displacement of the heart (whence results
syncope), displacement of the mediastinum, depression of the spleen and
of the liver, acceleration and feebleness of the pulse, and an anxious countenance.
The next year (1844) Trousseau read another memoir on the same subject.
He used the trocar with Reybard's gold-beater's skin at the orifice.
While he was popularizing the operation and laying down the indications
which called for its performance, several English observers305 were
turning their attention in the same direction. The paper by Hughes and
Cock306 showed that they had been operating in Guy's Hospital for
four or five years, and with great success, using a simple trocar and
canula of the diameter of one-twelfth of an inch. They imputed their
success to the small size of the instrument used, which allowed the
fluid to flow slowly and never permitted air to enter the chest during
respiration. They gave a tabular account of 20 operations. Hamilton
Roe307 at that time was operating successfully with the trocar.
Roe's paper was replete with information and with practical
suggestions. He tabulated 39 cases where syncope (one great objection
which had been urged against the operation) did not occur even once. He
disproved another popular objection, that there was great danger of the
admission of air into the pleural sac. Owing to the size of his trocar,
a considerable quantity of air entered the pleura during his
operations, and in some of them so freely as to produce all the
physical signs of pneumothorax, but in none of them did it produce any
permanently evil effects. In one instance only was even temporary
inconvenience caused. When the fluid was ascertained by the
exploring-needle to be purulent, he advised the immediate performance
of the operation. In acute cases he recommended a delay of three weeks
as the time for testing nature's powers of absorbing the fluid. He
advised the closing of the orifice after operation. This author gave an
account of his 24 cases. He concluded by stating that the operation is
not more dangerous than any other which is performed upon the human
body, and that the evil consequences supposed to attend it are
imaginary rather than real, inasmuch as it was only fatal in 1 out of
24 cases, and does not produce even temporary inconvenience. Thompson
in the same year justly condemns the practice of leaving the canula in
the orifice—a proceeding he considers as capable of converting a
serous into a purulent fluid. In 1848,308 at the request of H. I.
Bowditch of Boston, J. M. Warren operated by the usual method
recommended in the works on surgery. Partial relief was obtained, but
the amount of suffering undergone by the patient during the operation,
and the fact that an aperture was usually left open by this method,
decided Bowditch that he would never recommend it unless under very
urgent circumstances. Soon after this, Stone operated with the common
trocar and canula, by the advice, in consultation, of Bowditch. In
1849, Bowditch saw another death resulting from effusion where he had
advised the operation, but the consulting surgeon would not consent.
305 London Medical Gazette, 1847.
306 Guy's Hospital Reports, vol. ii., 1844.
307 London Lancet, 1844, copied into Amer. Journal Med.
Sciences, Oct., 1845.
308 Bowditch, Amer. Journal Med. Sciences, April, 1852.
To illustrate the opposition Bowditch found in the United States, he
quotes309 a remark of W. W. Gerhard, the distinguished auscultator of
Philadelphia, "that he should be as willing to have a bullet shot
through his chest as to have paracentesis performed on one of his patients."
309 Unpublished MS., 1882.
About 1850,310 Bowditch saw the paper published by Hughes and Cock,
and it determined him in future to try the trocar they had used or
something like it.311 "Fortunately, a few weeks before (April 10,
1850) M. Wyman had a sudden and severe case with large effusion and
intense orthopnoea. Death was threatening, yet Wyman felt called upon
by public opinion, medical and lay, to summon a prominent practitioner
from Boston. They both agreed that the patient was in extreme danger,
and Wyman urged tapping with an exploring-trocar. It was decided to
postpone surgical interference until next day, when another meeting
would be held, the consulting physician returning to Boston to advise
with the ablest men of the faculty and render their decision the
following forenoon. That was done, and it was found that no prominent
practitioner in Boston would consent to the idea of tapping.
Nevertheless, the oppression was so severe, and death so imminent
unless the patient could be relieved by some means, that the country
physician agreed to Wyman's proposal that an exploring-trocar should be
introduced. The fluid flowed out imperfectly, but some relief and no
harm resulted" (Bowditch). Two days after this, Wyman operated again
with the exploring-trocar and a suction-pump. Wyman312 demonstrated
to John Homans on the 23d of February, 1850, that the chest could be
safely punctured with his instrument and the serum evacuated in acute pleurisy.
310 Ibid.
311 Ibid.
312 Private letter to author, 1883.
Although suction, as we have shown, was used as far back, probably, as
Galen (second century), by Scultetus in 1662, and was in use in 1707,
as
shown in Anel's work, in 1742 in Laurence Heister's work, by
Ludwig and Lehren in 1768, again in 1796 (Benj. Bell), yet it had been
abandoned and lost sight of, with the exception of Laennec's suggestion
of its application in the form of a cupping-glass over the orifice of
puncture, until Guérin (1841) used it. The author followed Trousseau's
clinics in 1849 and 1850, and saw him repeatedly operate with Reybard's
canula guarded by gold-beater's skin, but never with Guérin's suction
apparatus. The French seemed to have lost sight of it until 1865, when
Guérin, at the French Academy, recalled attention to it, showing how he
aspirated liquids, instead of allowing them to flow outward after the
puncture. His apparatus consisted of a curved trocar, the end of which
was made tapering and sharp enough to puncture the thorax through the
skin and the muscles; of a pump, the piston of which was perfectly
adjusted to produce a vacuum; and of an adjuster at the extremity of
the pump, consisting of a stopcock which enabled the operator
alternately, without removing the instrument, to aspirate the fluid and
evacuate it into a basin. Wyman's pump, invented in 1850, was arranged
very much in the same way, only it contained valves which were opened
and closed by the movement of the barrel, to enable the operator to
suck out the fluid and then force it out of the pump. After the
operation the skin, being drawn over and closing the orifice, acted as
a valve which prevented at the same time the entrance of air and the
escape of fluid. Dieulafoy, in November, 1869, invented his aspirator,
which is based upon the same principles as those used by Guérin (1841)
and by Wyman and Bowditch (1850)—namely, pneumatic aspiration, which
the vacuum of the air-pump supplies. Guérin's instrument was large and
costly. Wyman's trocar was of a very small diameter, being only
one-twenty-fourth of an inch, and the canula but little larger. This
was attached, at first, directly to the aspirating syringe, afterward
by means of a flexible tube. With this apparatus Wyman demonstrated
that tissues could be safely punctured and cavities evacuated without
the admission of atmospheric air, that the wound, causing but a drop or
two of blood, was followed by no inflammation, and that no dressing was
required. The smallest trocar used previously to Wyman's was that of
Roe, which was one-twelfth of an inch in diameter. From 1850, Bowditch
appreciated the great value of Wyman's invention, as shown in one of
the first operations on a patient of his. He adopted and practised it.
His position as professor of diseases of the chest, and his great
reputation in that branch, gave him an extensive practice and brought
him many cases of pleurisy. He met with great opposition from the
surgeons and prominent practitioners of the country, but his results
were so favorable that he forced an unwilling and an unbelieving
profession to accept, as he expresses it, "the beautiful thought of
Wyman of thoracentesis or aspiration with a fine needle." "I considered
the operation so simple, and yet so effectual, and never harmful, that
I deemed it my duty to print cases illustrative of its value." Bowditch
had been for eight or ten years endeavoring to get some effective plan
of opening the chest without risk. He readily caught at Wyman's plan,
and he operated so frequently and successfully as to demonstrate its
value to the medical public both of this country and of Europe. As he
states,313 it was, in fact, what he had been for years longing
for—viz. a simple and painless, or almost painless, operation for
removing fluids from the thorax—one that could be done without danger
and leave no open wound. Bowditch relates314 that when he visited
Europe, nine years after his first publication of cases, he showed the
instrument in England, Scotland, France, and Germany, and that he met
with very indifferent recognition of its value. Only W. T. Gardner of
Edinburgh and Budd of London seemed to appreciate the plan. They had
instruments made after the American pattern. All others had no faith in
the operation. In Paris his old master, Louis, smiled
incredulously at his enthusiasm for it and doubted its necessity. At
Vienna Skoda turned with apparent scorn and left the room as Bowditch
was demonstrating its employment. The Parisian authors, Woillez, Peter,
Moutard-Martin, Peyrot, and others, do not even mention Bowditch, but
give Trousseau alone the credit of popularizing thoracentesis.
313 Unpublished MSS., 1883.
314 Ibid.
Trousseau's first publication was in 1843, and yet in 1859 there was no
general adoption of the operation, nor was there until 1869, when
Dieulafoy rediscovered Wyman's wonderful improvement of the application
of negative force to draw out fluids from the chest.
In estimating the value of the substitution of aspiration for the
trocar-and-canula method, we must bear in mind that with the latter
there was danger of the introduction of air into the thoracic cavity,
of the production of fistulous orifices, and the too rapid, and
therefore dangerous, evacuation of the fluid. Moreover, there are cases
where the trocar and canula is not effectual, although the quantity
effused be considerable—where, indeed, the fluid cannot flow out,
although the canula be pushed in actual contact with the fluid. The
explanation of this is now understood. The fluid is kept in the pleural
sac by a negative pressure of from 4 to 5 inches of water (Stone), 6
millimeters mercury (Donders), 5 millimeters mercury (M. Foster),
exercised by the lung in its elastic contraction, and by the passive
tension of the arched diaphragm. The fluid has no tendency to flow out,
and this suctional pulmonary force must be antagonized by an external
suctional force, that of aspiration, before the fluid can be withdrawn.
The invention can best be appreciated from the standpoint reached by
modern investigations of the physics of the living mechanism of the
chest. The principle of applying suctional force in pleurisy is in
imitation of nature's gentle methods in connection with respiration. We
have shown that most of the dangers connected with aspiration are
caused by not taking into consideration the adjustment of lung-tension
with thoracic resilience, and consequently of using too great negative
force and withdrawing the fluid too rapidly and in too great quantity.
Thoracentesis by aspiration, with greater or less force as may be
necessary, is now placed upon a scientific basis. We claim that this
modern method is an American invention—that Morrill Wyman was the
discoverer and H. I. Bowditch the utilizer of the discovery. As such
they may be regarded as benefactors of the human race.
It is extraordinary that Trousseau never alluded to Bowditch's
operations, and that Dieulafoy should never have heard of them.
Fraentzel acknowledges that Bowditch was the first to introduce
aspiration into practice. The Germans have been very slow in
appreciating its value. Fraentzel states that he did not use it until
1871, and that it was not until 1879 that it had in Germany any ardent
supporters. Bowditch315 has now operated 387 times upon 246 patients
without any unpleasant result.316 The distinctive points in
Dieulafoy's ingenious modification of the aspirator are that the
needles are very fine, even one-half of a millimeter in diameter; that
the barrel of the exhausting pump is of glass; that there is a
pre-existing vacuum; that we are not compelled to jar the side of the
patient by the process of pumping, and moreover by turning the cock we
produce at once a vacuum in the needle itself, and know with certainty
the moment the fluid is reached, and can see it flow through the glass
index in the tubing, even if it be in drops. We can judge of the nature
of the fluid, whether it be serum, pus, or blood. The minuteness of the
needle is a great cause of safety, because it allows the fluid to flow
so gradually that the lung has time to expand slowly. We can in an
instant arrest the flow of the fluid by turning the stopcock, and if
necessary by drawing out the needle. By giving the needle a downward
direction after it
enters the cavity, we prevent the point from
pricking the lung. So small an orifice is made that even if the needle
does touch the lung, there is no danger, for the orifice closes over at
once. As Dieulafoy claims, "the fineness of the needle guarantees the
harmlessness of the puncture." Castraux's concealed point (invented in
1873), and Fitch's (of Nova Scotia) protected canula (invented in
1873), are valuable additions to the aspirator-needle. These
dome-trocars, as they are called, prevent the possibility of injuring
the lung, for the sharp-pointed needle, after it has penetrated the
pleural cavity, is at once, by a slight movement, converted into a
blunt-pointed needle with an orifice near the end. With these very fine
needles the force is sufficient to draw up the thickest fluids. We are
compelled to admit that Dieulafoy's instrument is a great advance on
any other that has been invented. Its simplicity, its easy application,
its safety, have rendered paracentesis a harmless operation and one of
great value in serous effusions. While Guérin and Wyman may both claim
priority of invention, all must admit that Dieulafoy has improved upon
their ideas and given us a beautiful and effective instrument. There
have been proposed, since Dieulafoy showed his instrument in 1869, no
less than forty other aspirators, modifications in form or dimensions
of his apparatus. Of these, to us the most valuable is Potain's bottle
aspirator, with which aspiration can be so easily and effectually
employed. It is simple and cheap. An india-rubber cork accurately
fitting a strong bottle is perforated for two tubes each having a
stopcock. One of the tubes fits on the end at the exit in the basin,
and the other is adapted to an aspirating syringe.
315 London Lancet, vol. ii., 1879.
316 Letter to author, 1883.
One of the most important of the improvements to the aspirator-canula
is the addition—first suggested in 1858 by Charles Thompson,317 and
afterward adopted by Potain, Powell, and Fraentzel—of a lateral tube
for the outflow connected with the main canula through which the trocar
passes. By this improvement, in case the canula is clogged up, the
trocar can be pushed down to remove the obstruction without danger.
317 Med. Times and Gazette, 1858.
The principle of aspiration is now well established, and the
indications for its use are becoming more defined and more accurate.
New applications as a means of diagnosis, as well as of treatment,
daily render it more valuable.
To guard against the dangers shown by modern experience to be sometimes
attendant upon the operation of aspirating the pleura (see Dangers of
Thoracentesis), it is now generally admitted that the removal of the
contents of the chest should be slow and gradual; and that, ordinarily,
it is safest at one operation to remove only a portion of the effused
liquid. Our object should be to remove pressure and allow nature by
absorption to take away the remainder, for positive pressure is an
urgent indication for thoracentesis. It is therefore of primary
importance to properly estimate the quantity present, and thus to test
the intra-thoracic pressure. Great care and caution must be used,
because if we extract too much the operation may be followed by serious
results.318 Large-sized canulæ should never be used, for fear of too
rapid withdrawal of fluid. It has been demonstrated that even with a
capillary perforated needle we can exercise more negative pressure than
is safe, especially toward the close of the operation, when there
supervenes a negative pressure exerted by the fluid remaining in the
pleural cavity. It is from these well-known facts that we recognize the
great value of Potain's ingenious addition to the aspirator of a
manometer of extreme simplicity, a kind of barometer or cuvette, which
is placed along the tube which withdraws the fluid. If we are not
satisfied with this new safety improvement of the aspirator, we may
adopt Douglass Powell's suggestion (On Consumption, etc.)
of
fitting into the bottle a pressure-gauge, so as to know at any moment
what degree of aspiration is being used.
318 Trans. de l'Assoc. pour l'Adv. des Sciences, 6th
Session, 1877.
The syphon method has been of late years very extensively used,
especially by Southey, W. H. Stone, and Garland, A. T. H. Waters,
Wilks, Oxley, and habitually by Douglass Powell. It is a feeble
aspirating force, which has very decided advantages. It is effective,
and acts slowly and uninterruptedly with a gentle and uniform negative
pressure. Its action allows the lung gradually to expand and the
displaced organs slowly to resume their normal position. It thus in
many cases furnishes us with a safe means of thoracentesis. (See
Surgical Treatment, in Pleurisy.)
.